It combines scraping and heat.
A lesion is scraped with a curette and treated electrically.
Electrodesiccation and Curettage: A small, low-risk skin cancer is scraped out with a sharp loop, and the base is then burned. It takes one visit and needs no stitches. It leaves a round pale scar, and the edges are never checked under a microscope.
Mohs Surgery: Skin cancer is removed one thin layer at a time, and each layer is checked under a microscope during the appointment before the next one is taken. It has the highest cure rate and removes the least normal skin, and it takes most of a day.

Choose for a small, low-risk skin cancer on the body when one quick visit with no stitches matters more than margin checking.
Choose for skin cancer on the face or other high-risk sites, where the highest cure rate and smallest scar matter most.
Can you have both?
Both treat basal and squamous cell carcinomas. ED&C suits small, low-risk cancers on the body; Mohs suits the face and higher-risk cancers.
A lesion is scraped with a curette and treated electrically.
It can treat carefully selected low-risk skin cancers.
It lacks the margin assessment of excision or Mohs surgery.
Type, site, size and depth determine suitability.
Each layer is mapped and examined under the microscope.
Further tissue is removed only where cancer remains.
Type, size, site and recurrence determine suitability.
The final defect may exceed the visible lesion.
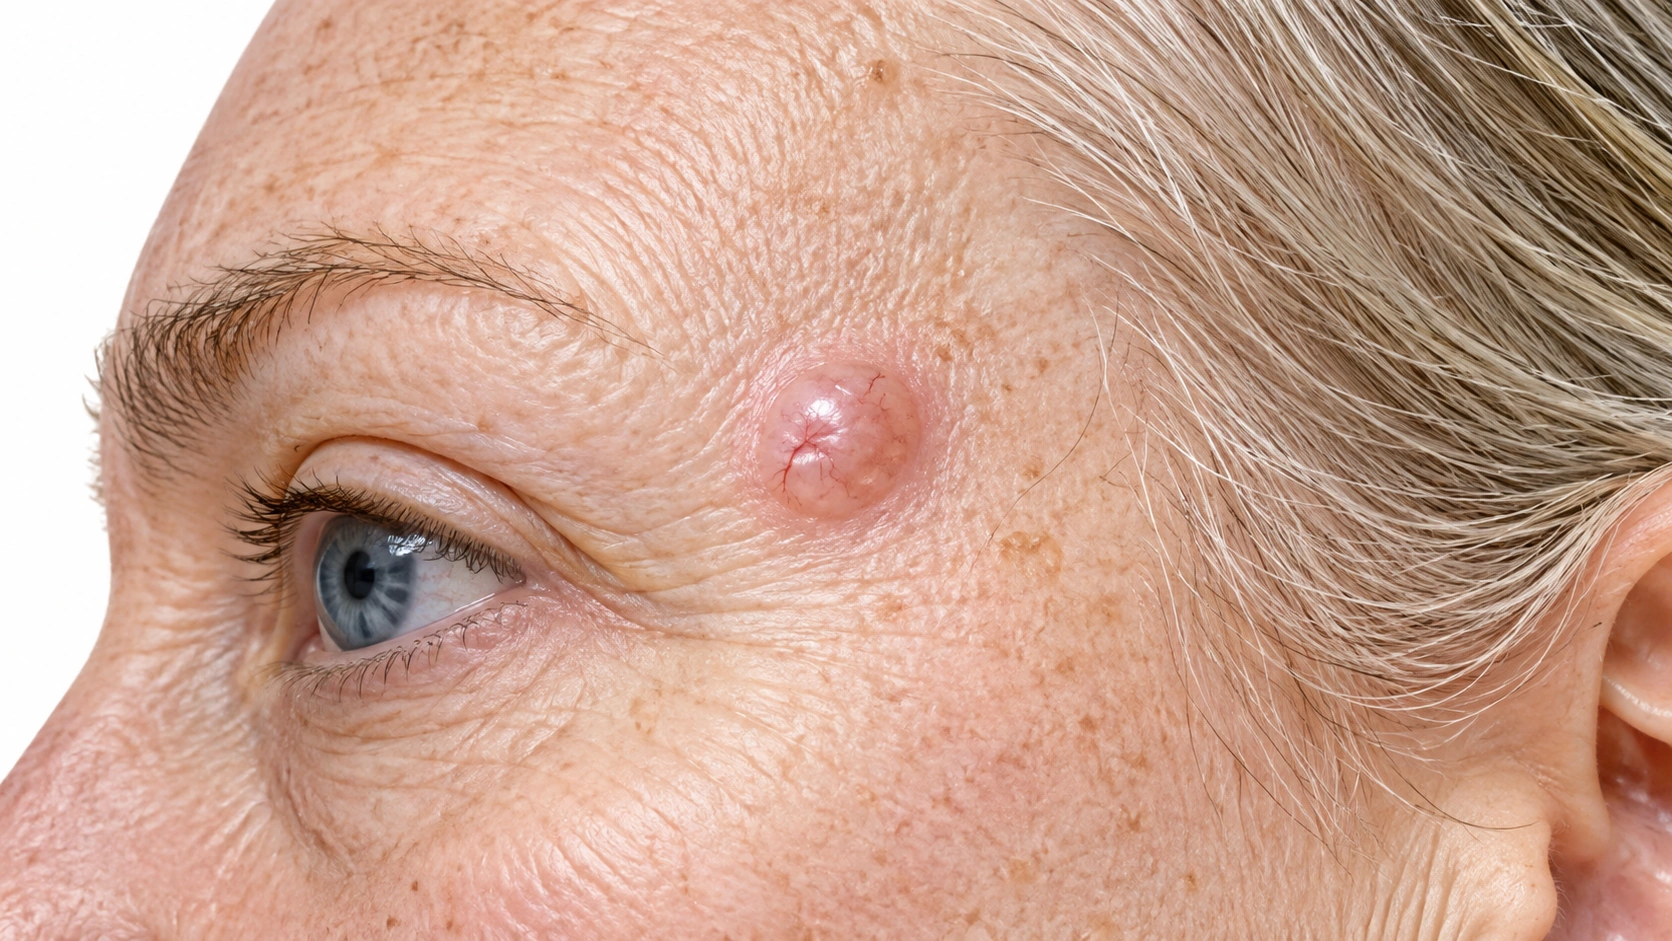
High cure rates for small tumors.
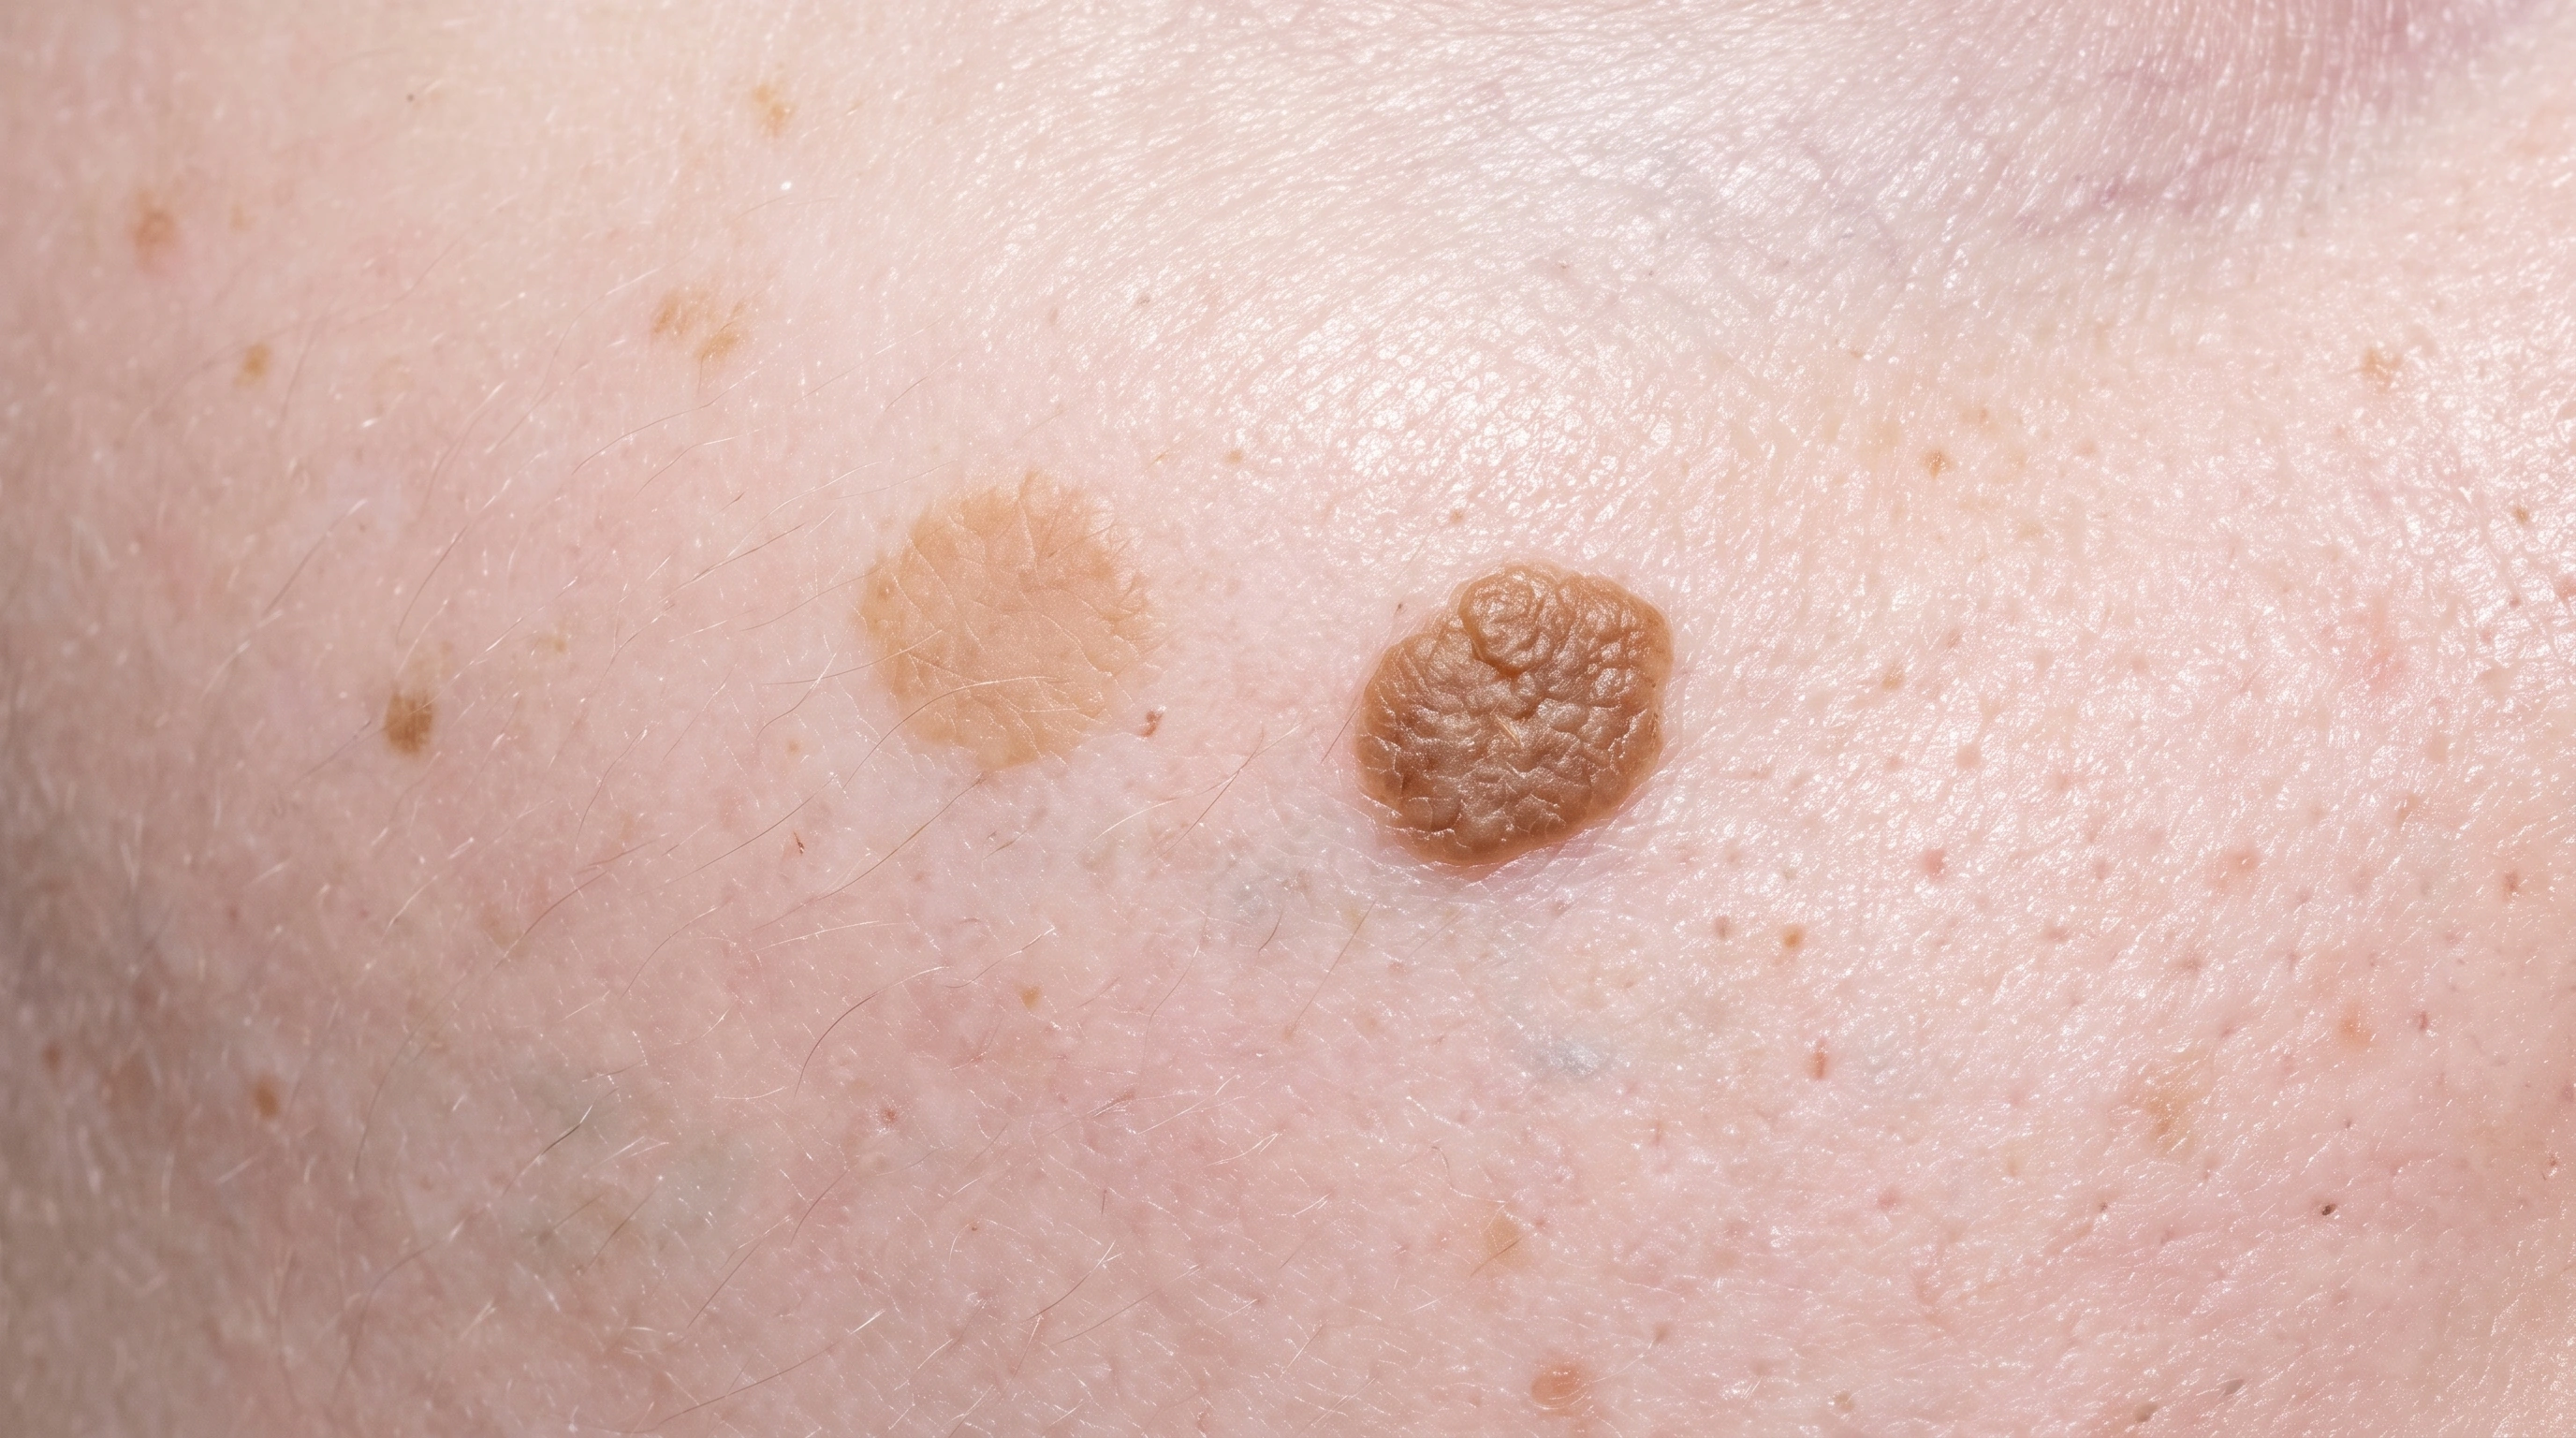
Removes growths quickly.
About 99% cure rate for first tumors.
Precise removal on the face.
For small, low-risk tumors.
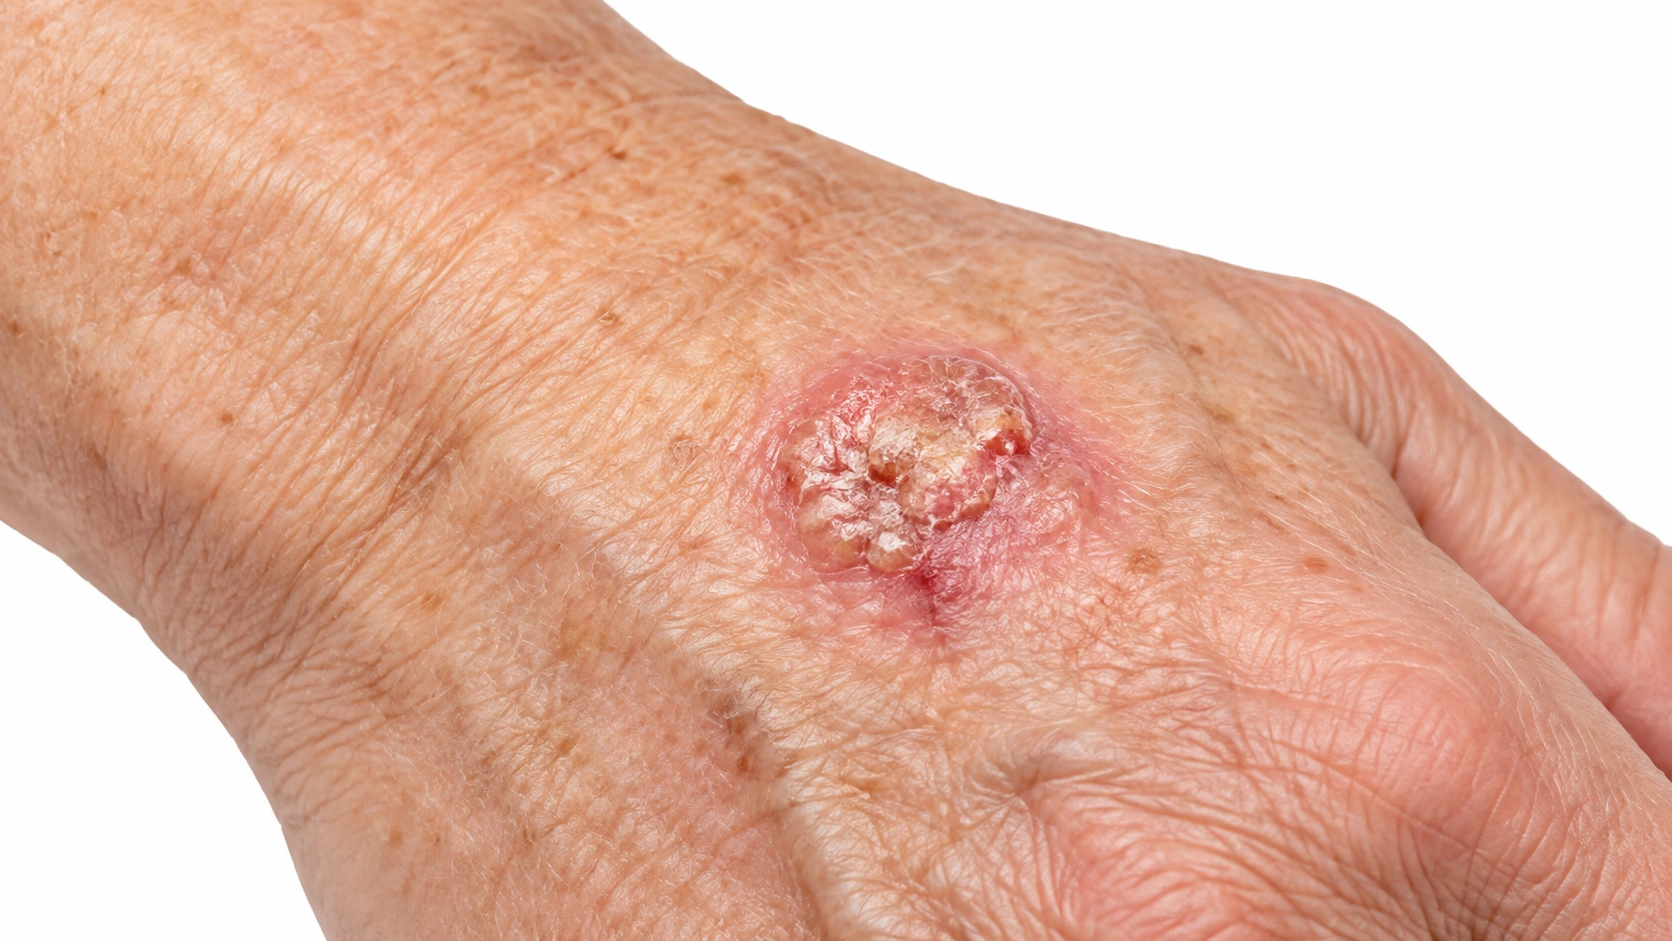
Needs excision with margins.
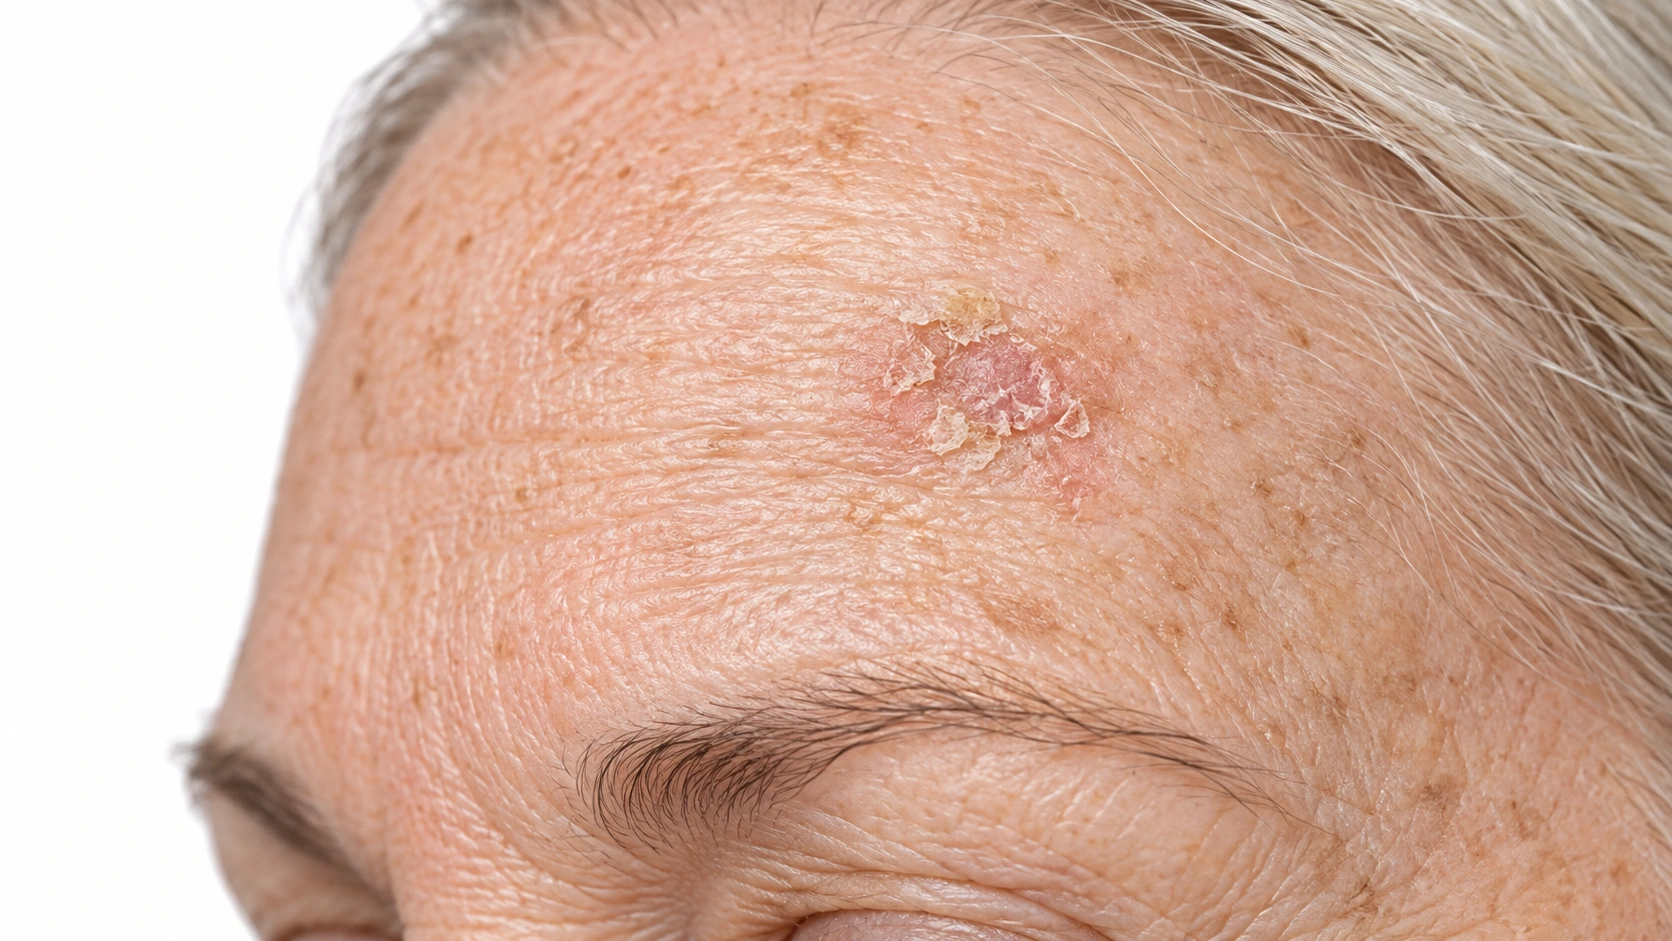
Too much for precancers.
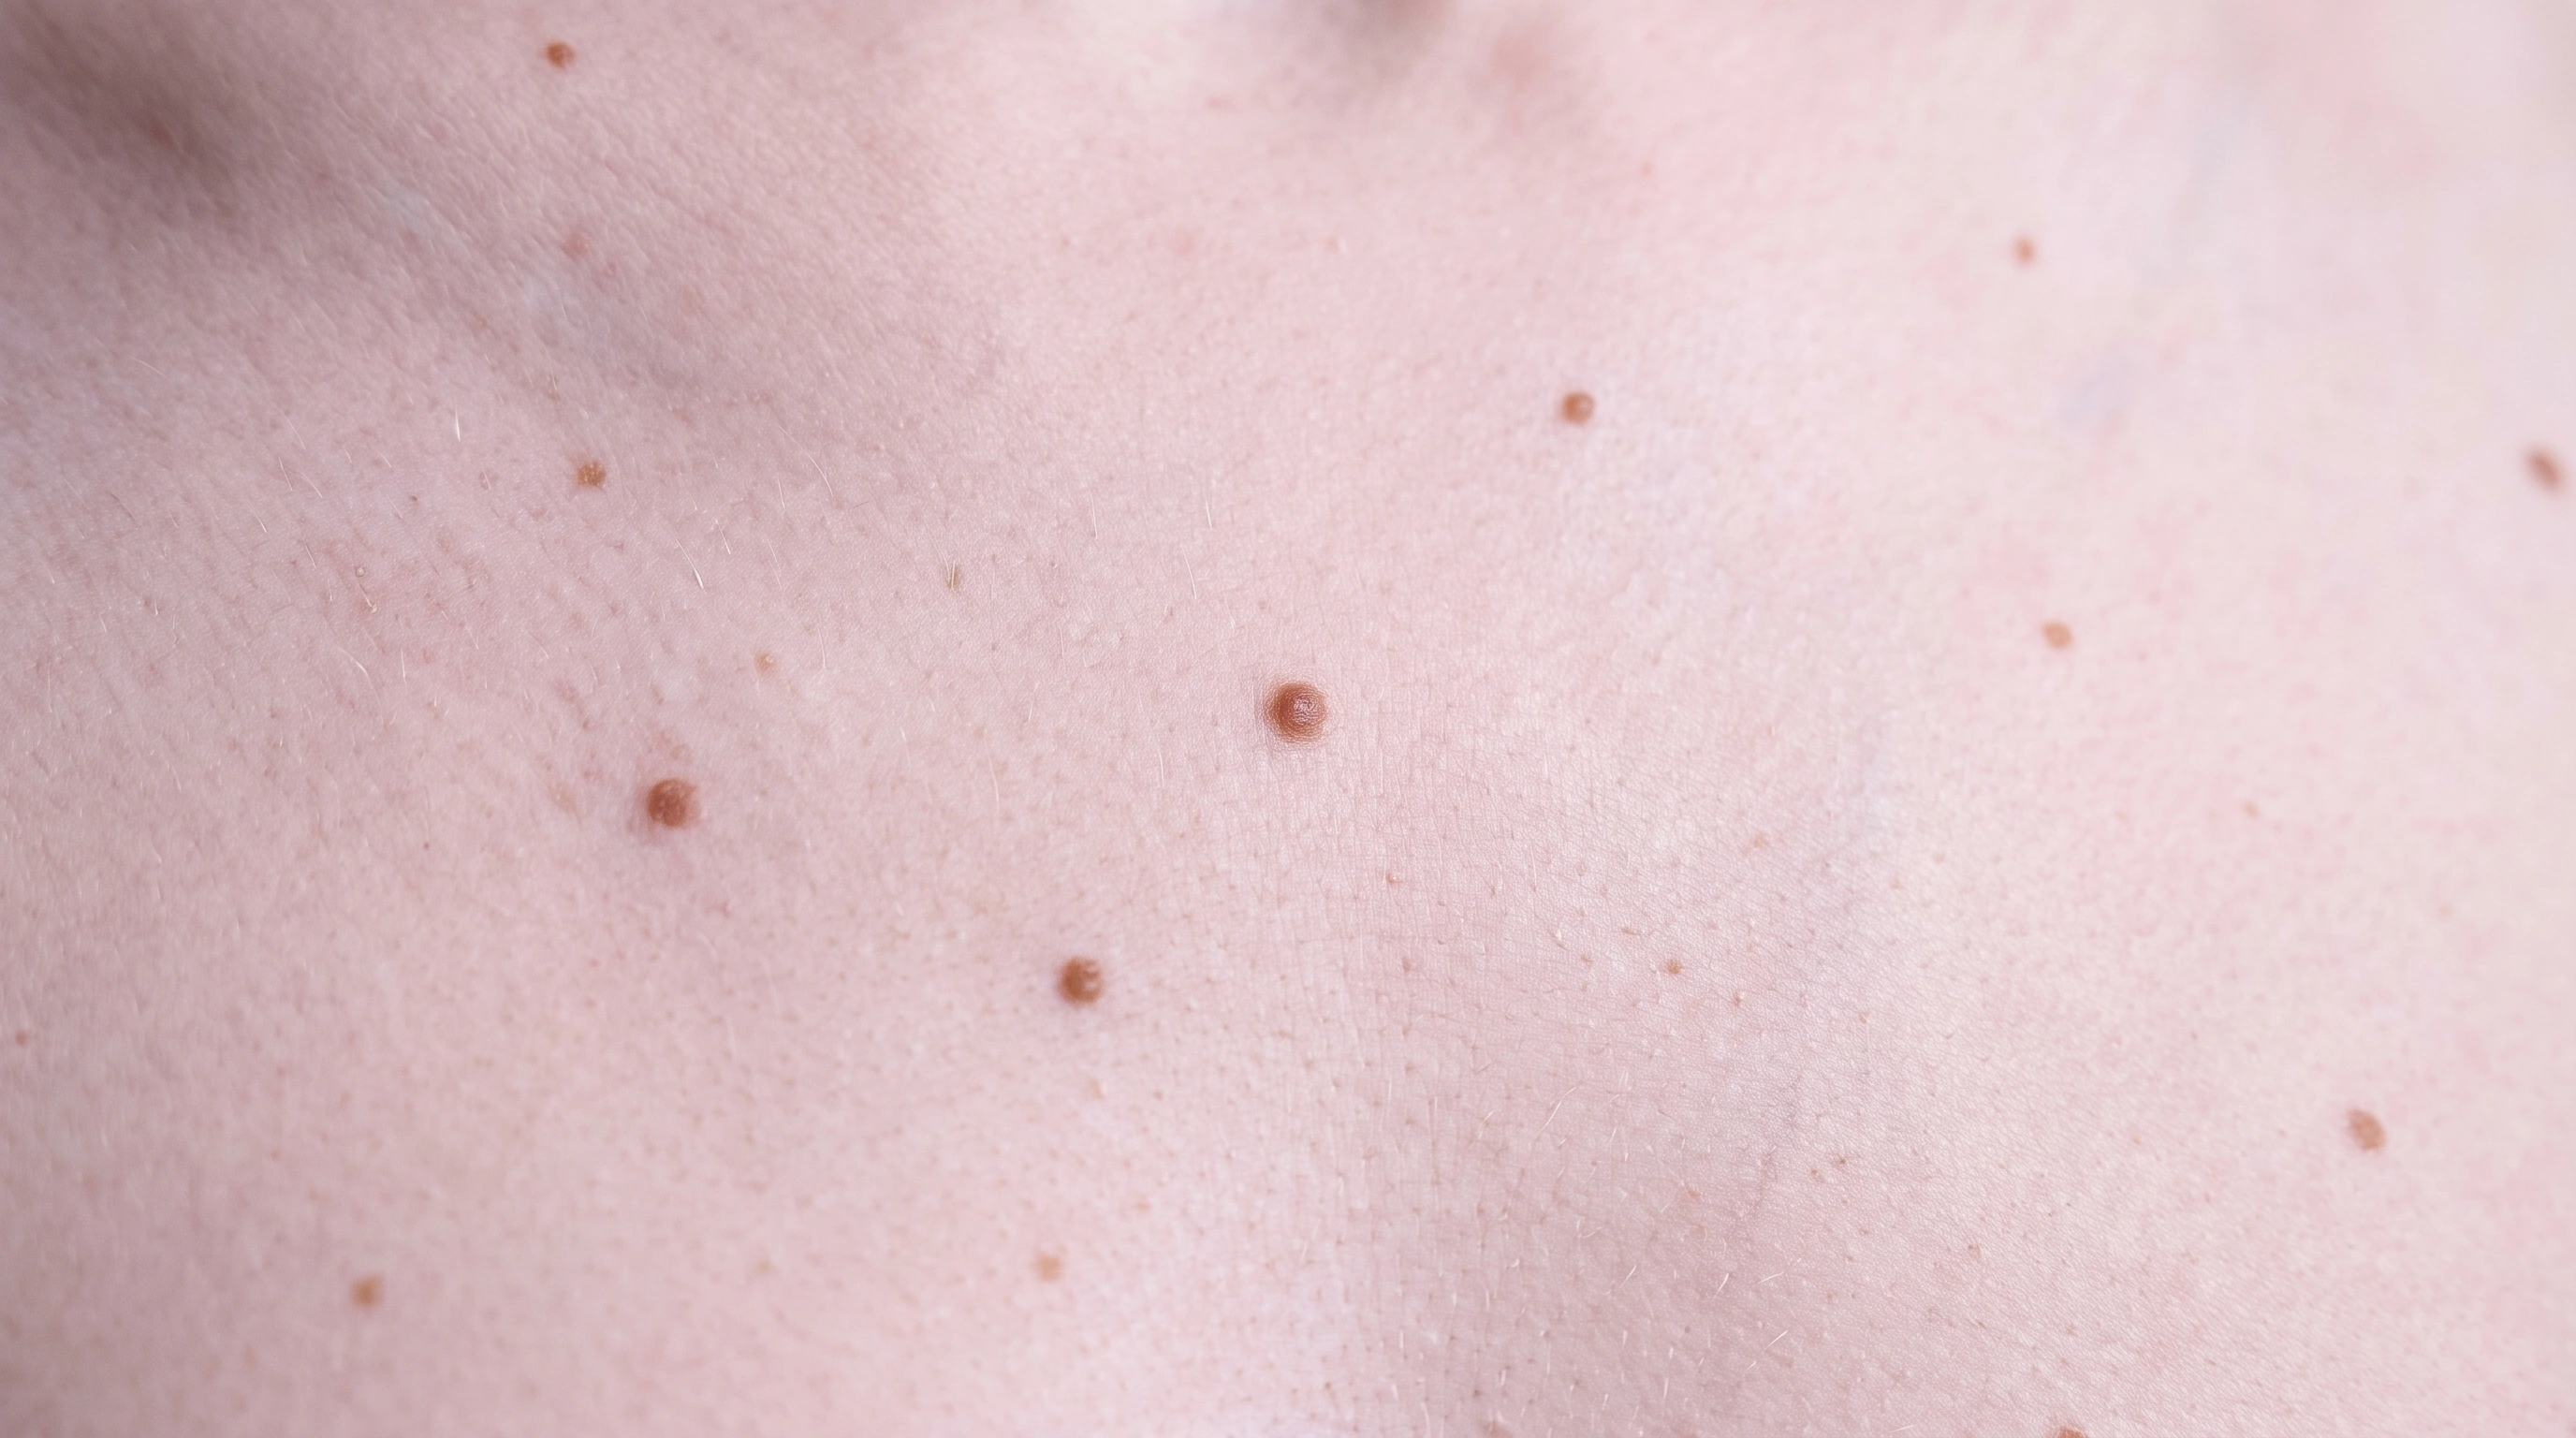
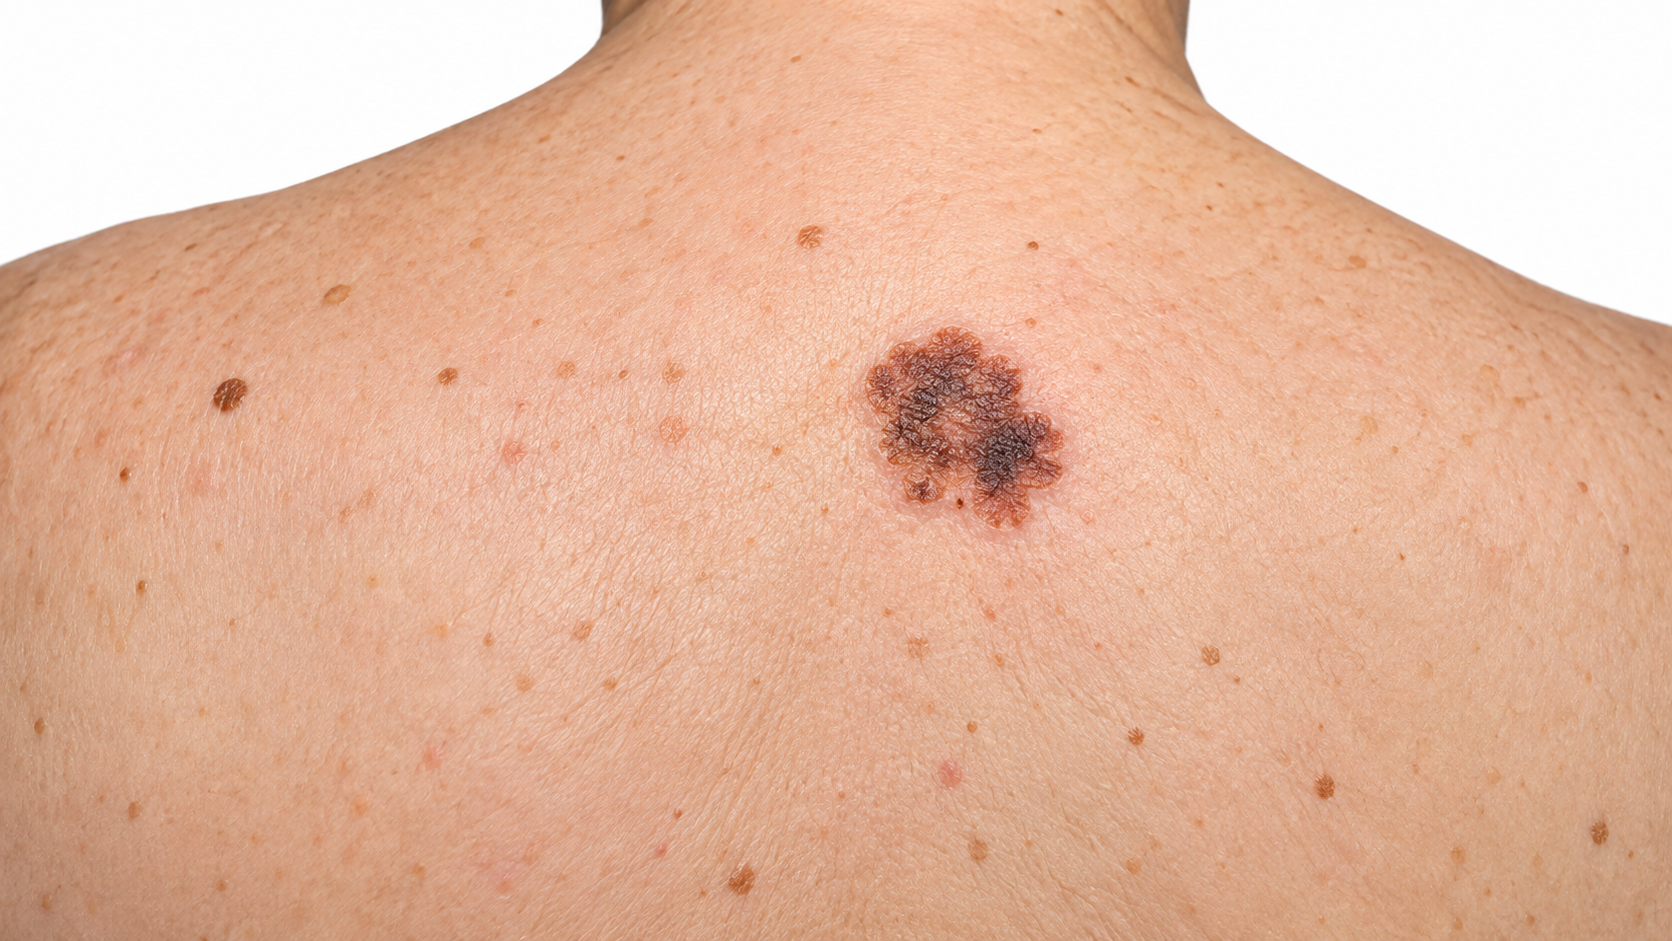
Not for benign moles.
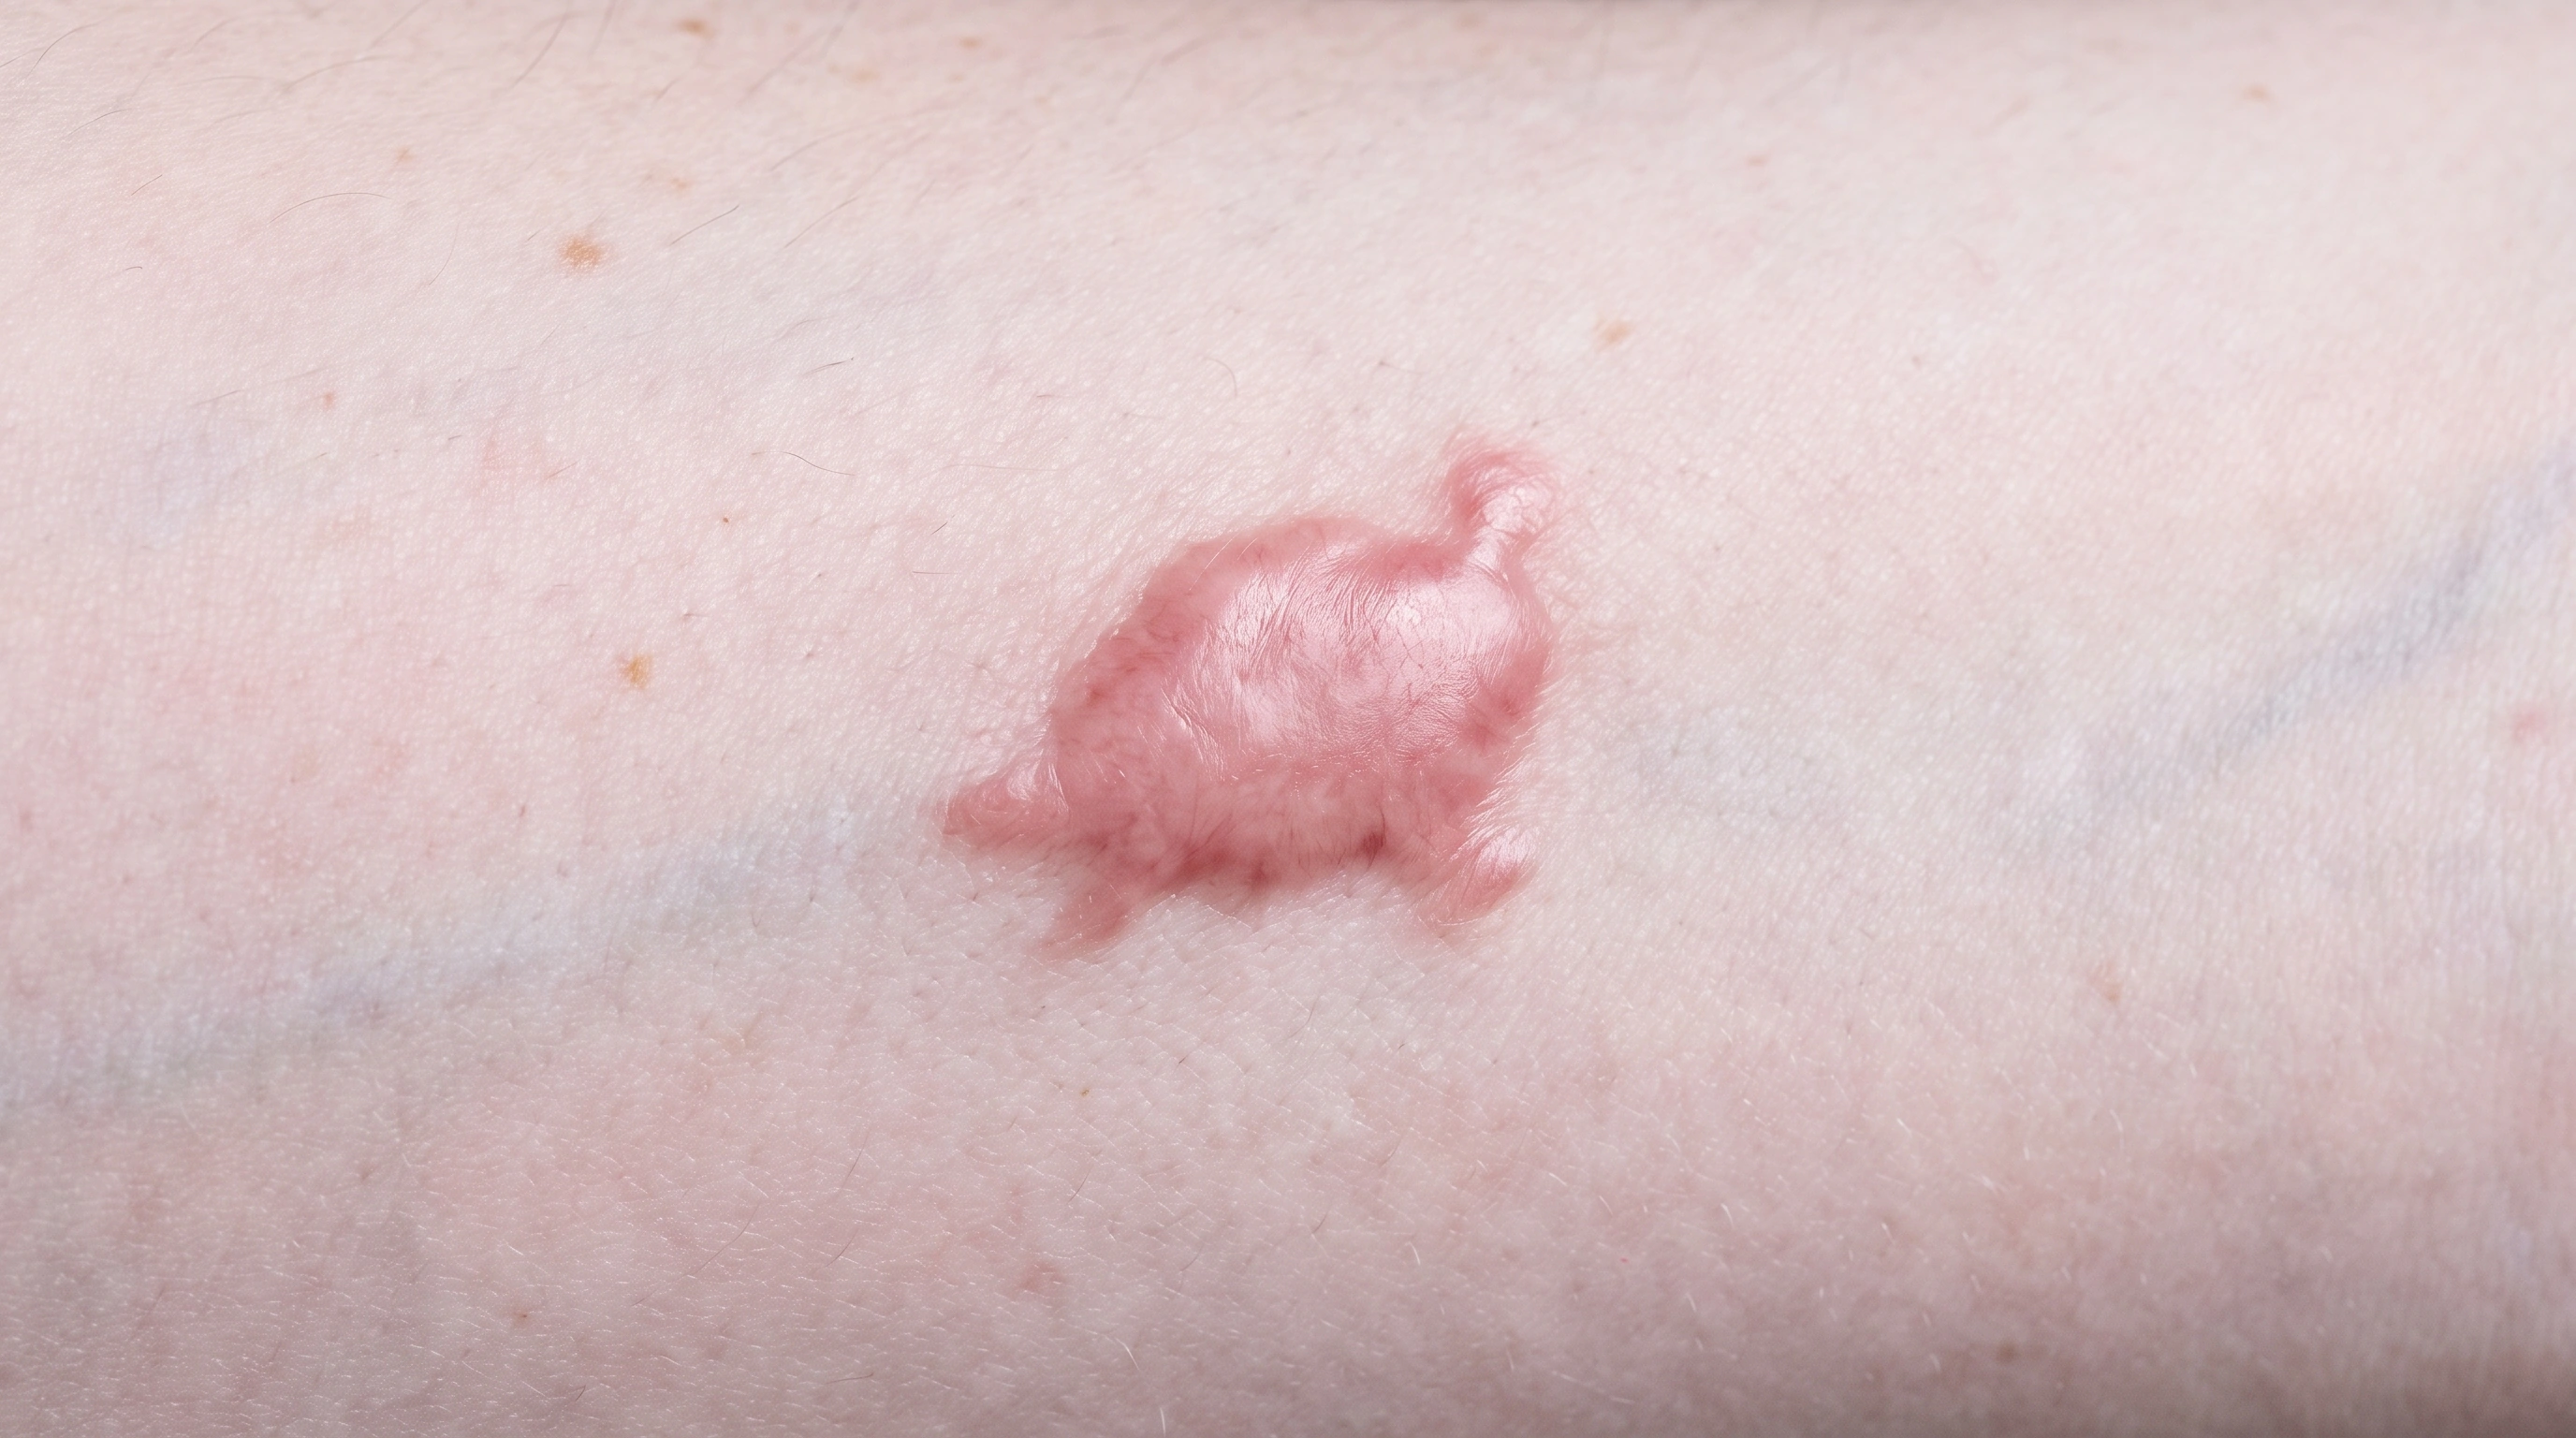
Can trigger new keloids.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.


A curette removes tissue: A clinician scrapes away the selected lesion. Electrical treatment treats the base: Energy dries or coagulates tissue in the treatment bed. The wound heals: The open area repairs with scar tissue; follow-up remains important.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
A thin tissue layer is removed: The surgeon removes visible cancer and a surrounding layer. Margins are mapped and examined: The tissue edges are checked under a microscope. Only involved areas are treated again: Stages continue as needed before planning wound repair.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Do not stop: Blood thinners: Aspirin, clopidogrel, warfarin, apixaban, rivaroxaban and similar are usually continued — extra oozing is easier to manage than a clot or a stroke.
Ointment and dressings: Buy plain petrolatum ointment and non-stick dressings beforehand, not on the way home.
Supplements and alcohol: Blood-thinning supplements you do not need, such as fish oil, vitamin E and ginkgo, are commonly stopped about a week before, and alcohol the night before.
Smoking and vaping: Stop from at least a week before through the first two weeks after if you can.
What to wear and eat: Wear something you do not mind getting blood on.
Eat, dress and plan: Eat a normal breakfast and take your usual morning medicines unless told otherwise.
The lesion is matched against the biopsy report, photographed, and consent signed.
The site is confirmed against the biopsy report and photographed, and you will be asked to point to the spot yourself.
The doctor scrapes with the curette, which feels like pressure and tugging, not pain.
The electric probe follows, with a faint buzz and a smell of burning. The pair is repeated two or three times; one lesion takes about 10 to 20 minutes. Nothing should feel sharp once you are numb, so say so if it does.
The surgery: The tumor and a narrow margin come out in minutes.
The surgery: You then wait 45 minutes or more while the tissue is frozen, sectioned and read. If tumor remains at a mapped edge, another layer is taken there only; most finish in one to three stages. The wound is then closed with stitches, a flap or a graft, or left to heal, in 30 to 90 minutes. The injections sting; nothing else does.
A round, shallow, raw crater slightly larger than the growth, under ointment and a dressing.
A firm pressure dressing stays on 24 to 48 hours, with written wound-care instructions and a suture removal appointment.
Day 1 to 7: The wound weeps and the base looks yellow.
First 24 to 48 hours: Keep the dressing dry and in place, your head elevated including overnight, and ice over the dressing in short spells.
Days 2 to 14: Bruising and swelling are worst around day two and can spread around the eyes.
Weeks 2 to 6: The crater shrinks and the base turns pink.
Week 2 to Month 12: The scar becomes a hard, raised, pink ridge.
Month 2 to 12: The scar starts pink and firm, then flattens and pales over roughly a year.
Immediately
Same day
90–95% cure for suitable cancers
About 99% cure for first basal cell cancers
This is the least expensive way to treat a skin cancer surgically.
Mohs is the most expensive of the standard skin cancer treatments, and the day shows why: a surgeon who is also reading the pathology, a laboratory and technician in the building, and hours of appointment time.
In the US it is billed as a destruction procedure, priced by lesion size and body site, and generally covered when it treats a diagnosed skin cancer.
It is generally covered by health insurance when the tumor meets accepted criteria for Mohs, which is why the location, size and subtype are documented before it is booked.
The numbing injection stings for under a minute. After that you feel pressure and tugging, not pain. Afterward the site is sore rather than painful, and acetaminophen is enough.
There is no intact specimen to check — the tumor is scraped away in fragments and the base burned. The method relies on the operator feeling soft tumor against firm normal tissue, which is reliable for shallow, clearly bordered tumors and unreliable for others.
A round, flat disc, usually slightly wider than the original spot and lighter than the skin around it. Some are a little sunken, some raised. Pink at first, paling over about a year. It is permanent.
About 3 to 6 weeks on the face, trunk and arms. On the lower leg it is slower, sometimes two to three months, particularly in older adults or with diabetes or poor circulation.
Sometimes, for a small superficial tumor on the cheek or forehead. Generally not for the nose, eyelids, ears, lips or the creases around them, where recurrence is higher and there is less spare skin. Ask why one is recommended over the other for your tumor.
For a well-selected, small, low-risk tumor, cure at 5 years is commonly quoted around 95 percent. That falls when the method is used on tumors it was not meant for — aggressive subtypes, recurrent tumors, unclear borders, high-risk facial sites.
Mostly waiting. Removing a layer takes minutes; freezing, slicing, staining and reading it under a microscope takes 45 minutes to well over an hour, and that happens once for every stage. One to three stages plus a repair fills most of a day.
No — Mohs is done under local anesthetic while you are awake. You will be numb but able to talk, eat between stages and walk to the waiting room. General anesthesia is used only in unusual cases.
Not knowable in advance, which is uncomfortable and honest. The wound ends up as large as the tumor's roots turn out to be. Mohs removes less normal skin than any other method, so the wound is usually smaller than an excision would have produced for the same tumor, and a tumor that looked like a small spot on the surface can still be considerably wider underneath.
Not unless the doctor who prescribed it tells you to. Blood thinners are usually continued through Mohs. Extra bleeding during surgery is manageable; a stroke or a clot is not.
Location, mainly. On the face there is little spare skin and recurrence rates are higher, so removing the least tissue with the highest certainty is worth the time and the cost. On the back a straightforward excision achieves the same result more simply. Size, an aggressive subtype under the microscope, unclear borders and a tumor that has come back before all push toward Mohs anywhere on the body.
Almost certainly, and follow-up still matters. Cure at 5 years for a previously untreated basal cell carcinoma is commonly quoted around 99 percent. The bigger reason to keep coming back is that having had one skin cancer makes a new one elsewhere substantially more likely.