Hydrocortisone
The mildest topical steroid, and the only one sold without a prescription. It is the usual starting point for the face, for skin folds and for young children.

Key facts
Hydrocortisone at a glance.
Used for
Mild eczema or selected itchy rashes
Results
1–2 weeks
Treatment commitment
Short course; reassess if persistent
Key precautions
Can worsen infections and some facial rashes
What is it?
Top things to know about Hydrocortisone
- It is a mild corticosteroid. Hydrocortisone reduces local inflammation and itch.
- This page covers skin use. Oral, injected and ear-drop forms have different uses.
- OTC cream is for short-term use. The 1% cream is for temporary relief of minor irritation.
- Persistent symptoms need review. Recurring rashes or sensitive sites may need assessment.
Often used for
What Hydrocortisone is used for

Eczema
Calms mild flares.
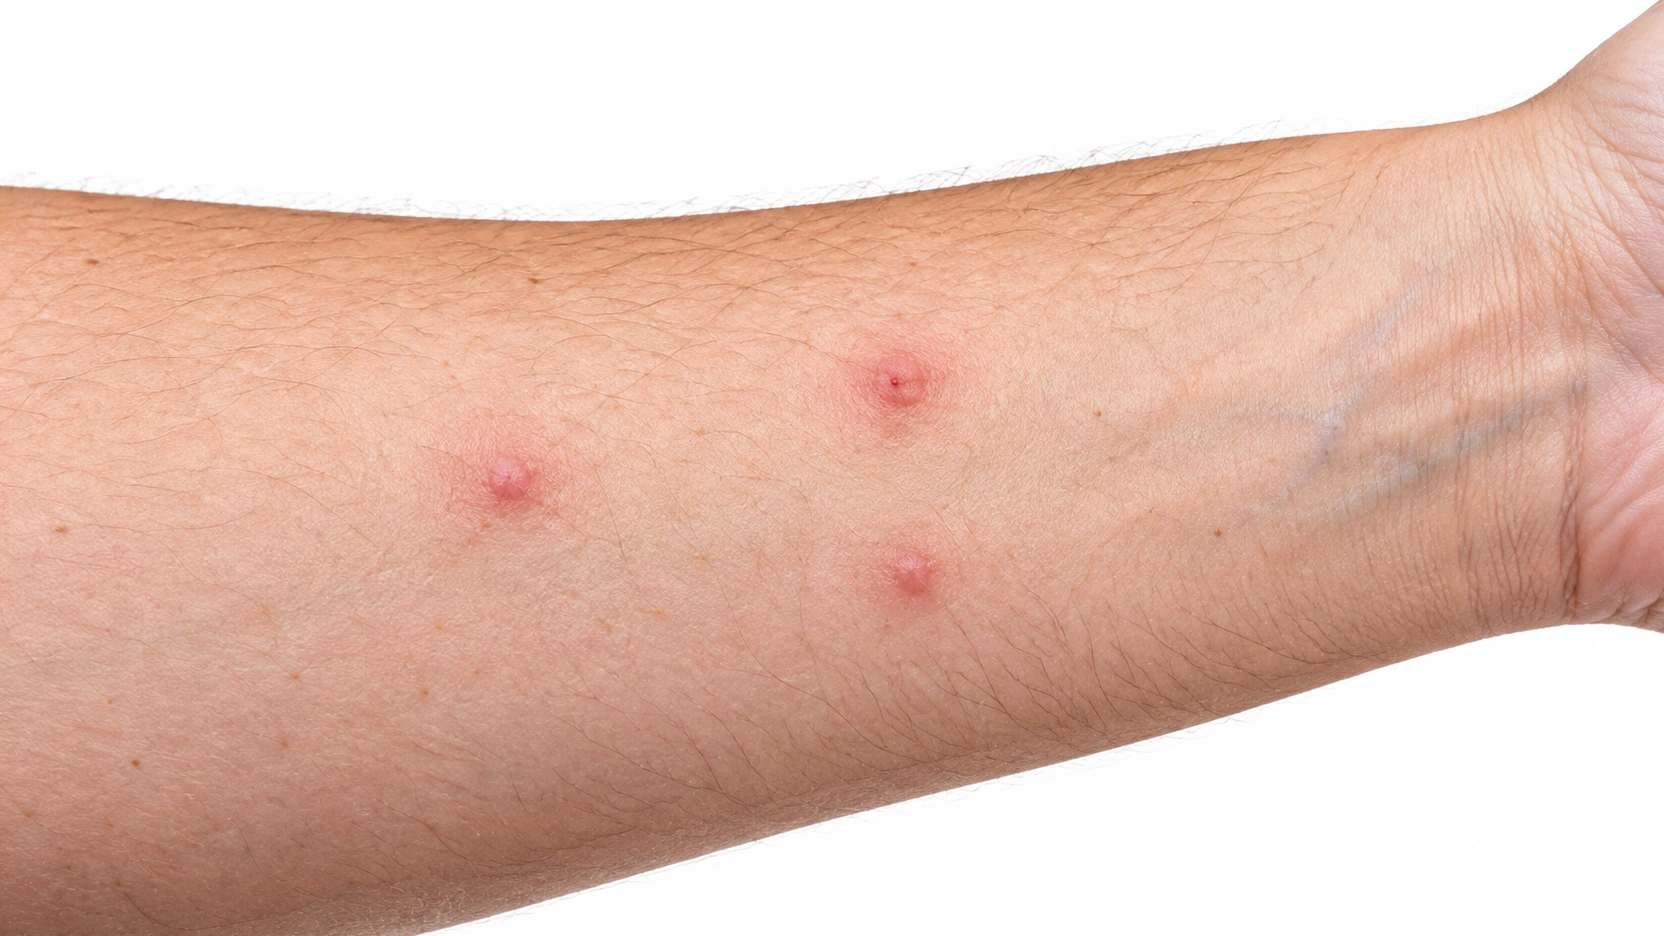
Insect Bites
Reduces itch and swelling.
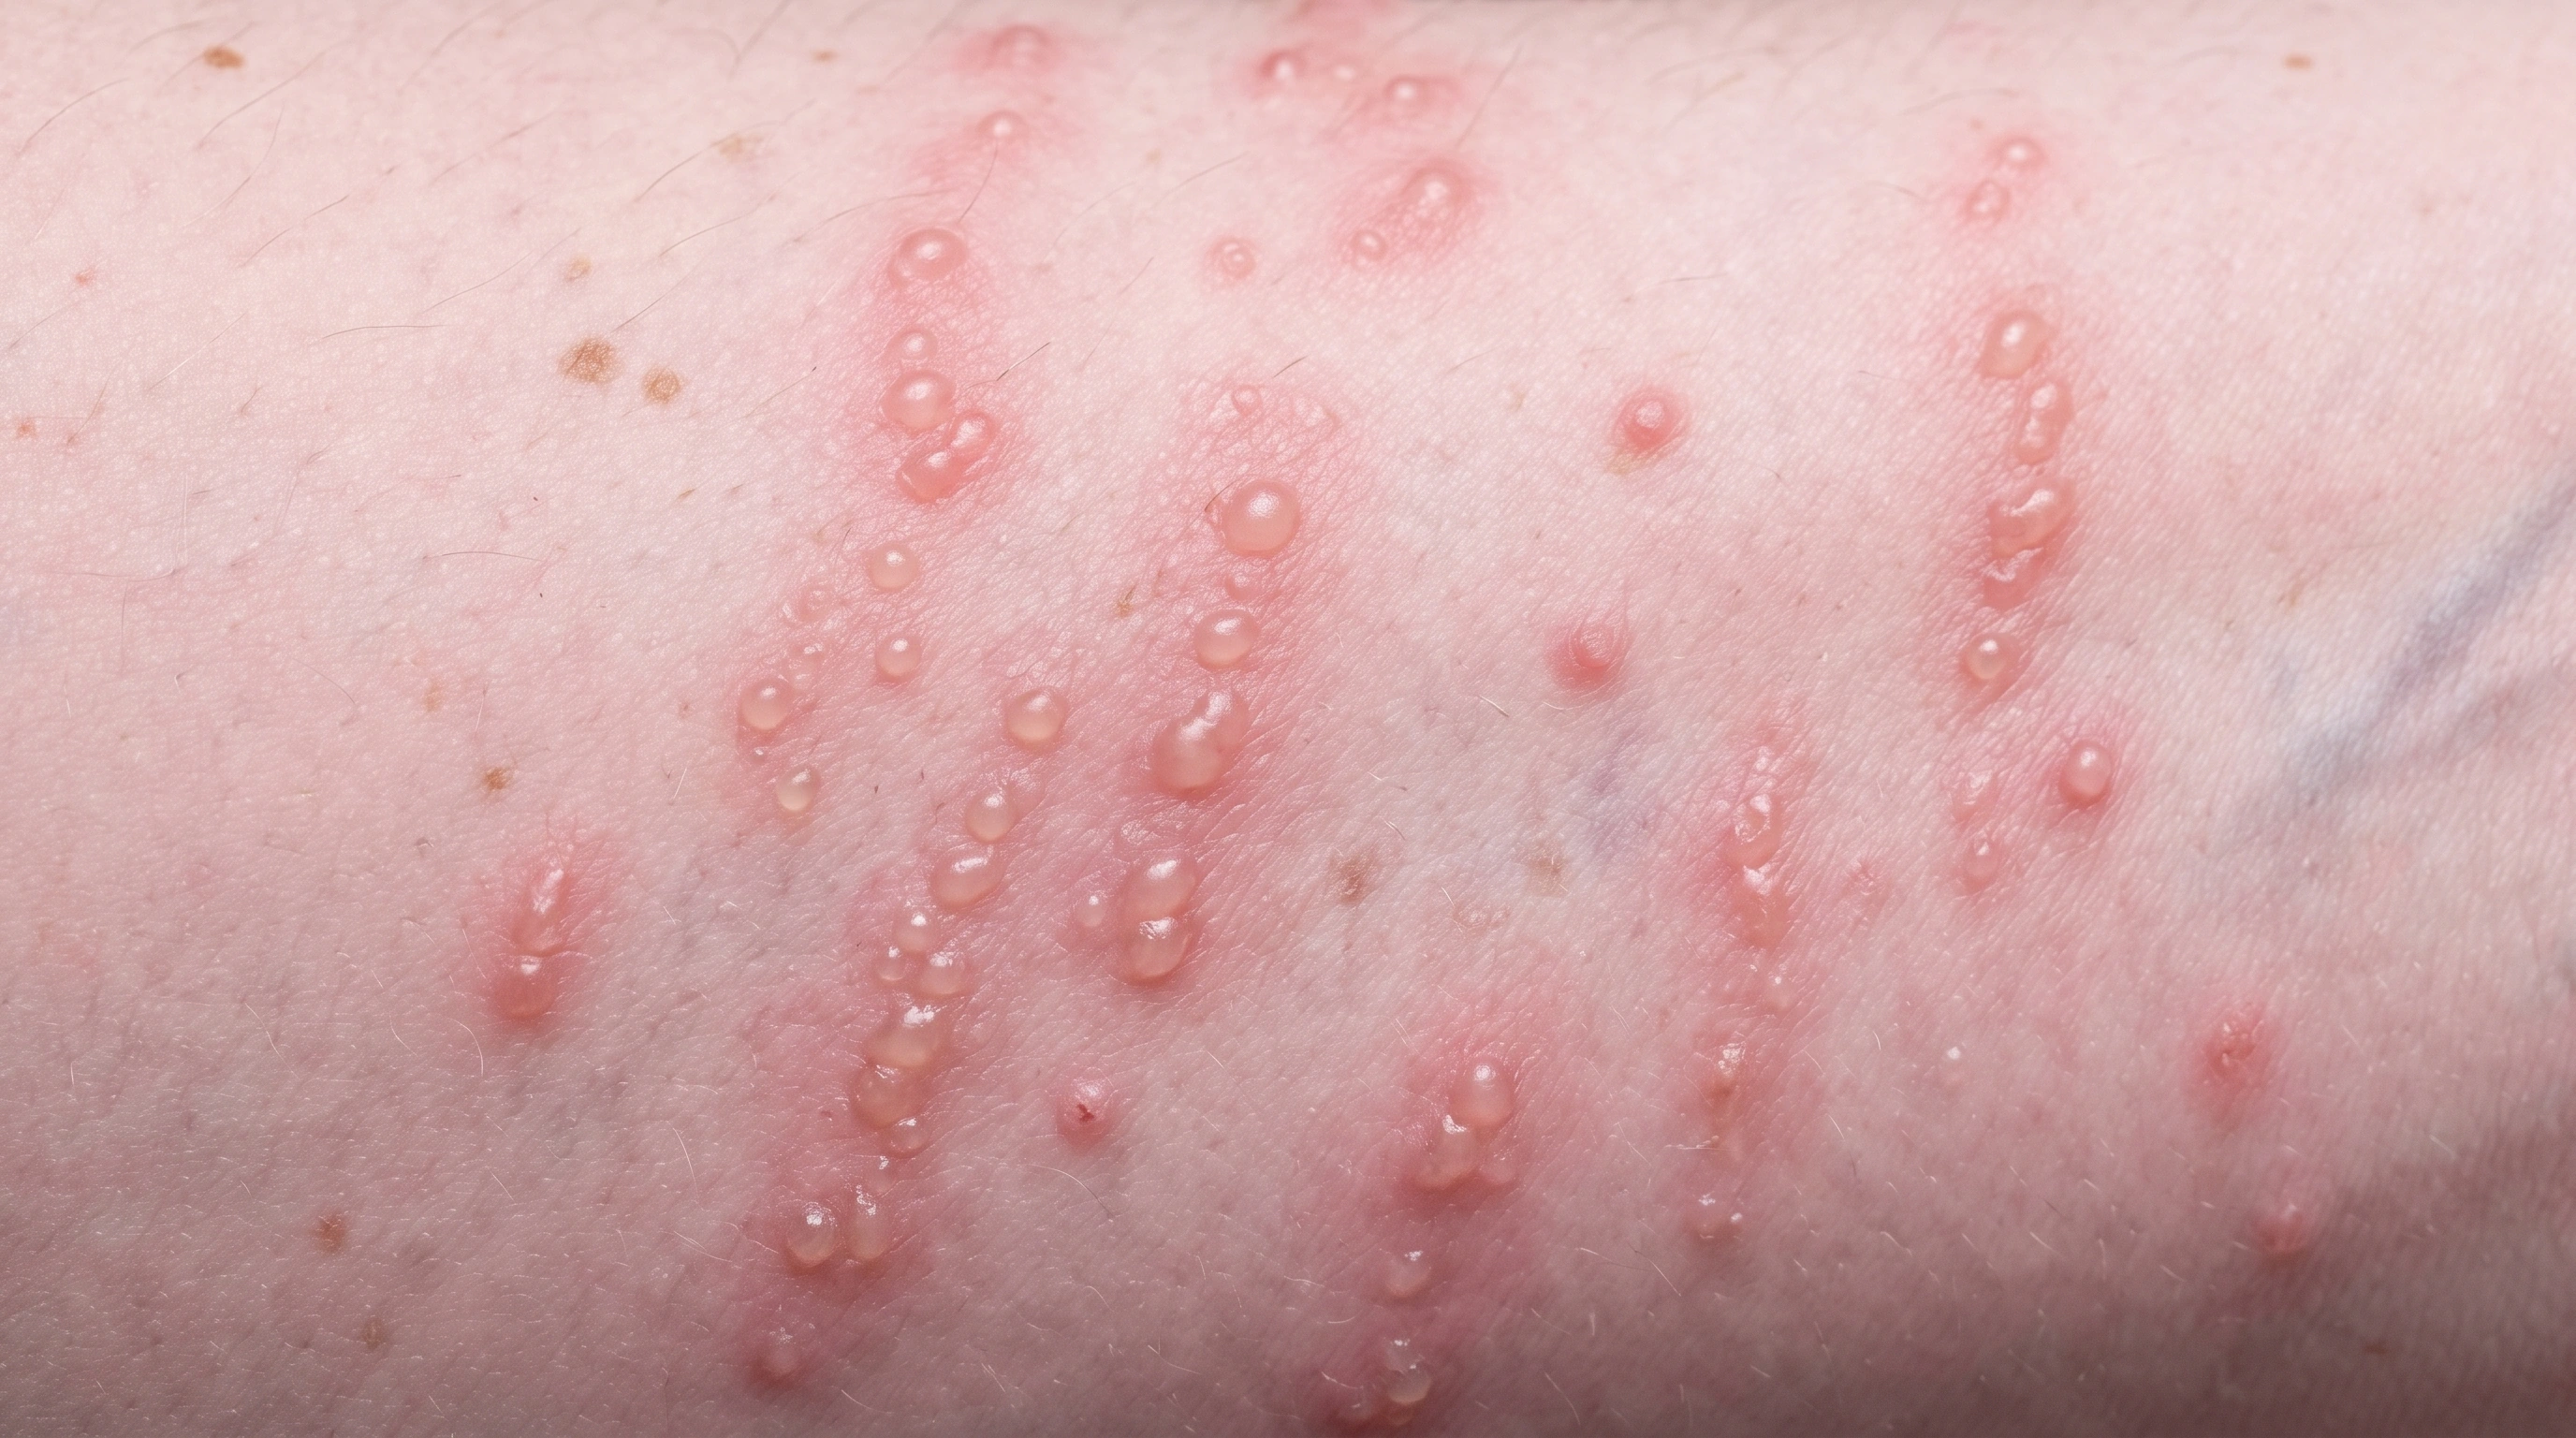
Contact Dermatitis
Calms mild rashes.
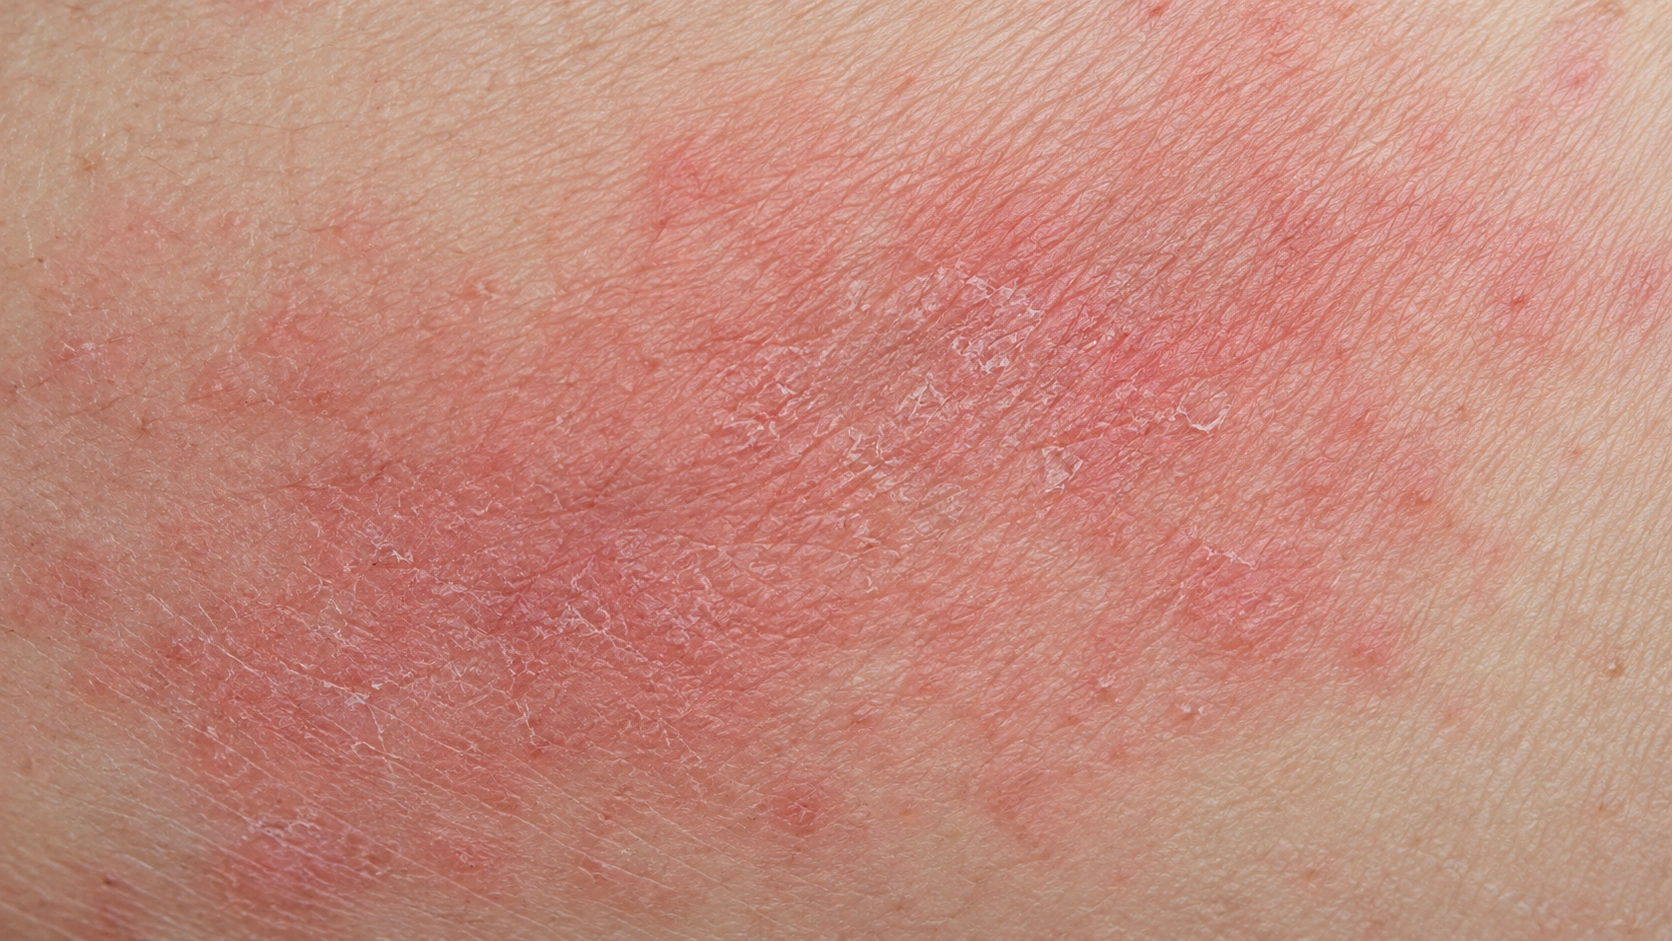
Diaper Rash
Short use for inflamed rashes.

Psoriasis
Too mild for plaques.
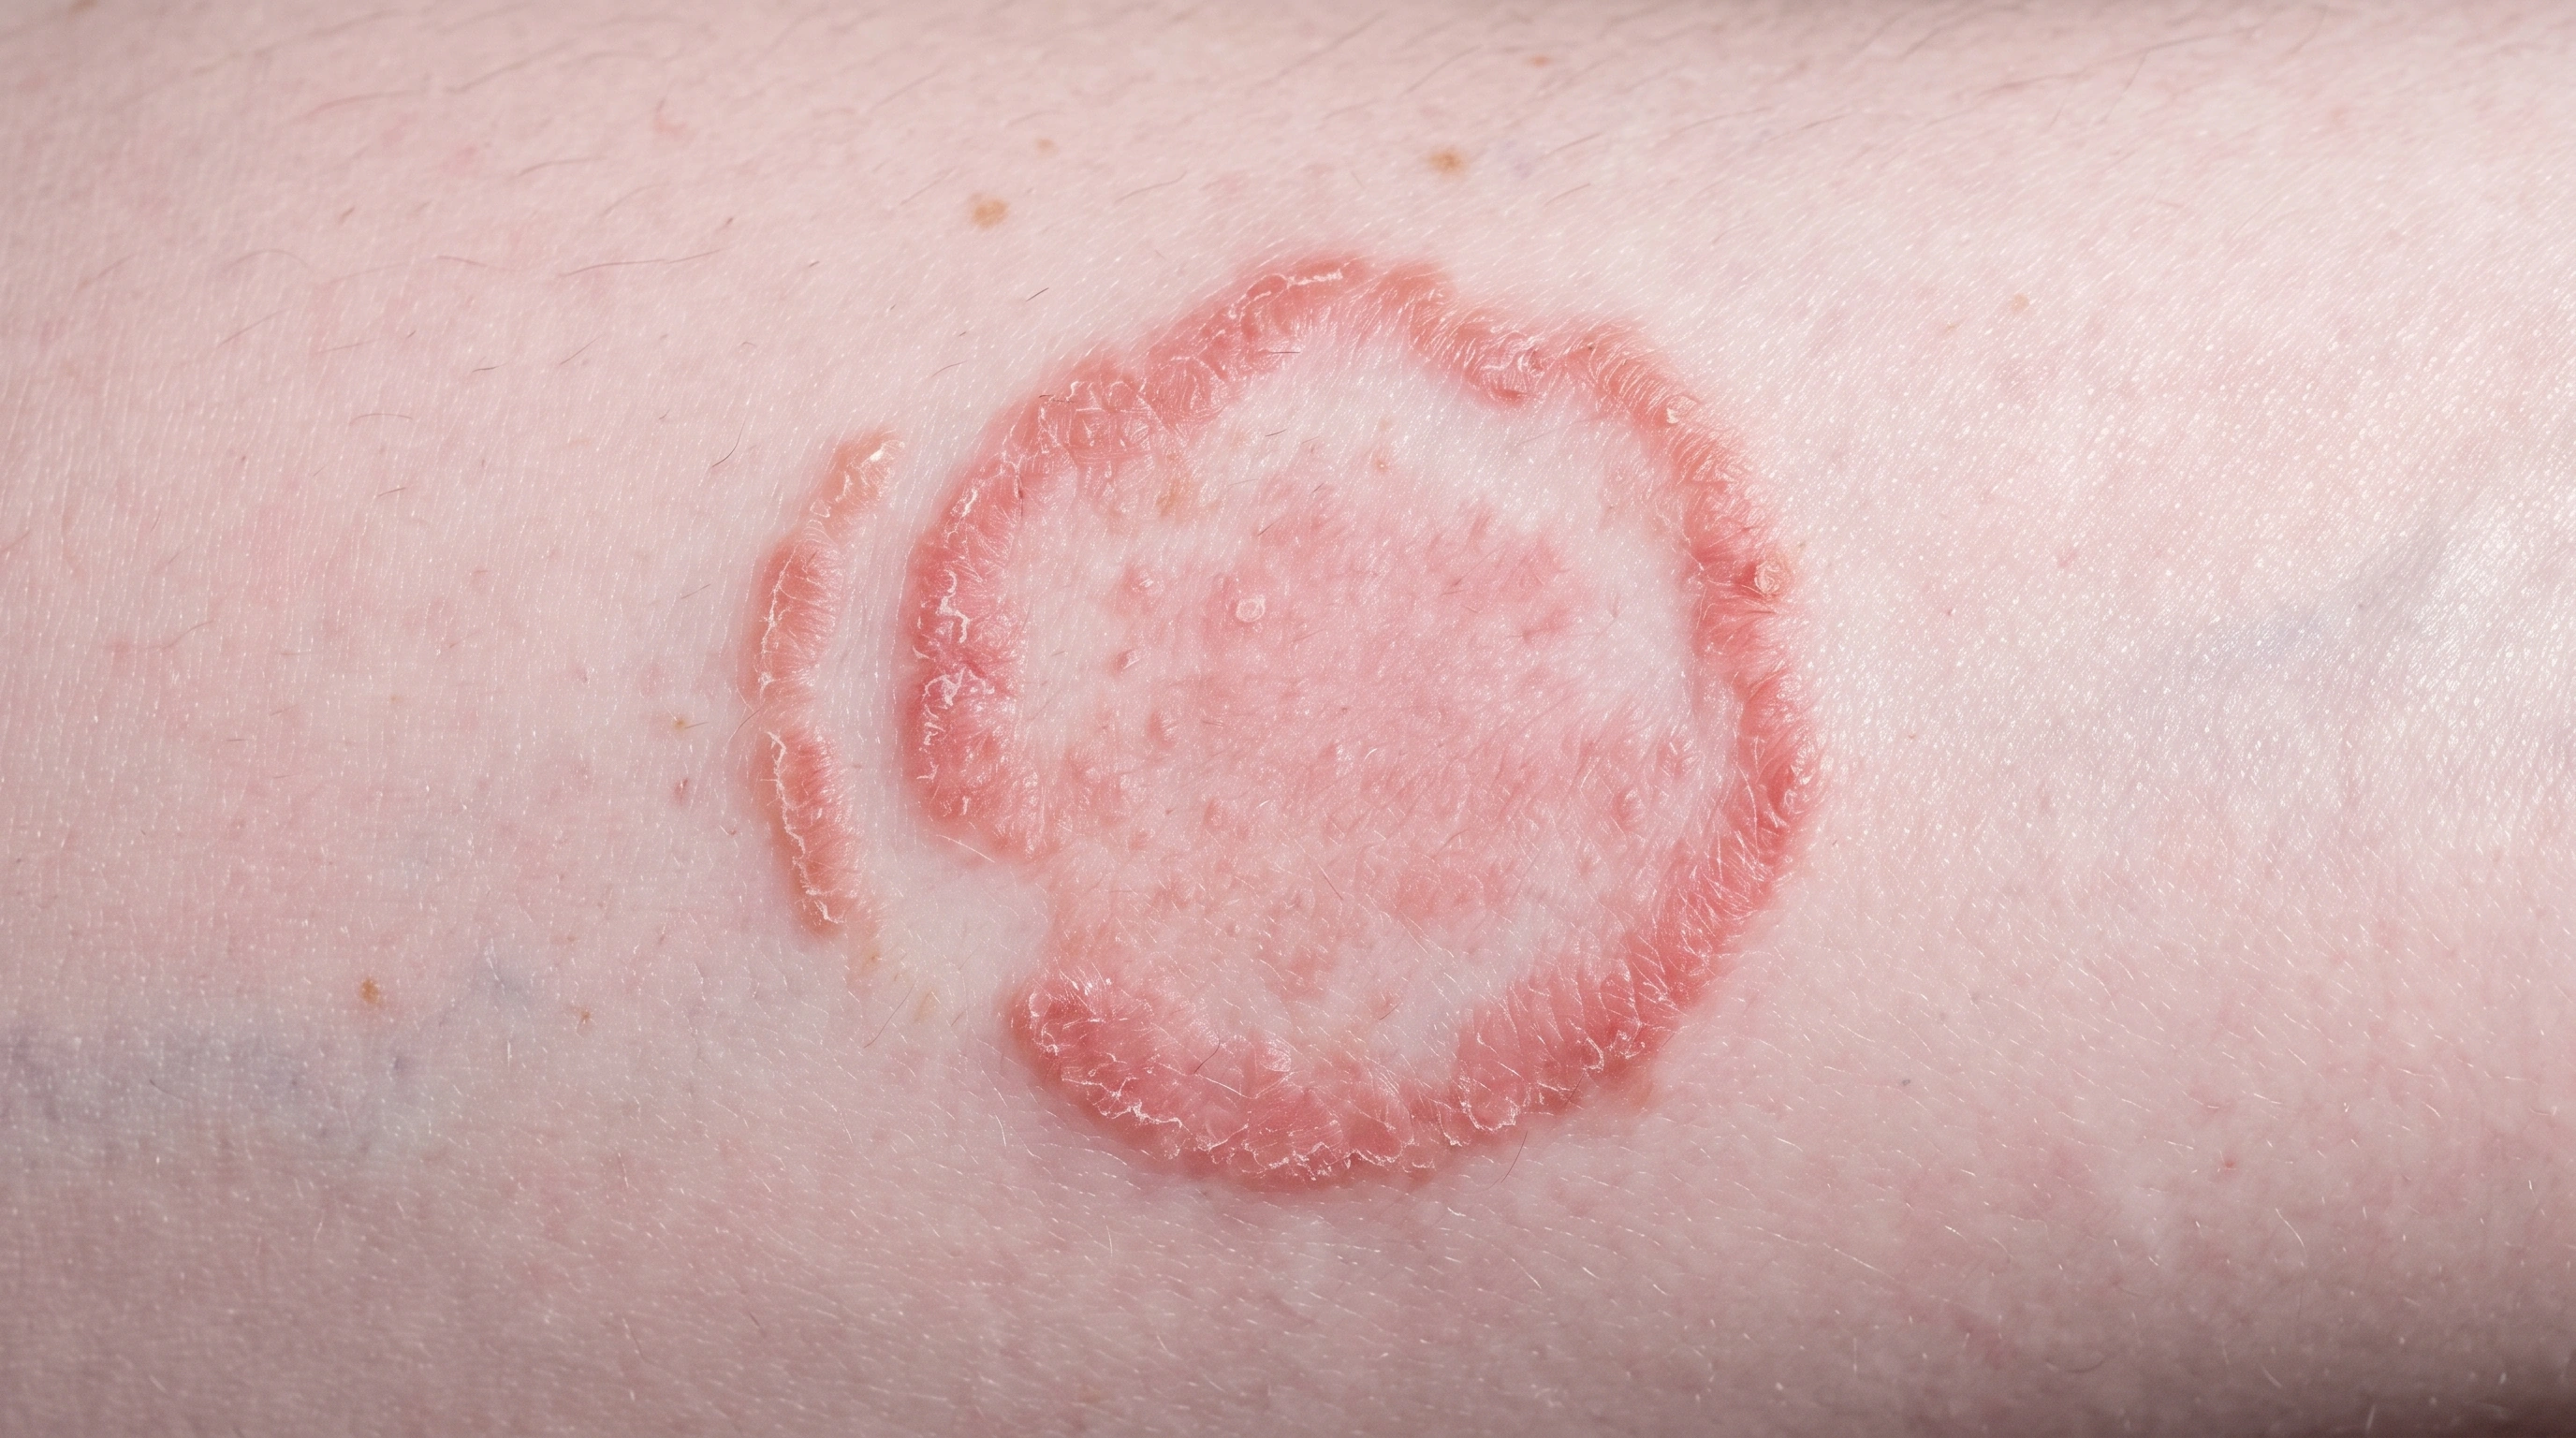
Ringworm
Steroids let fungus spread.
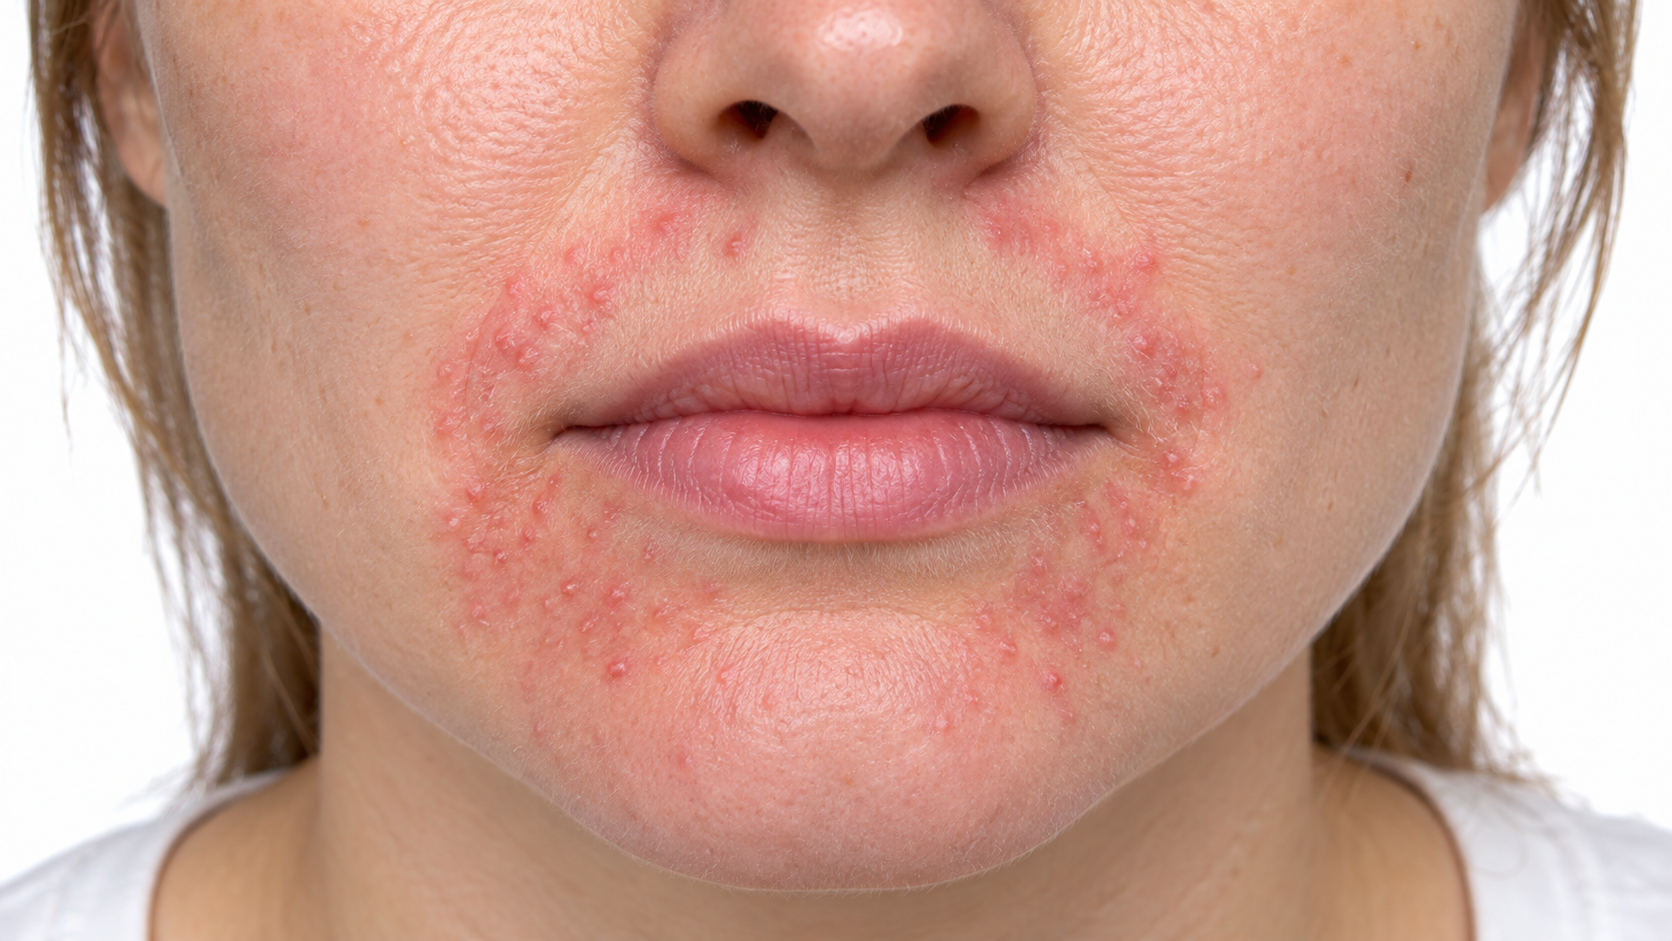
Perioral Dermatitis
Steroids worsen it.
HOW IT WORKS
How Hydrocortisone works
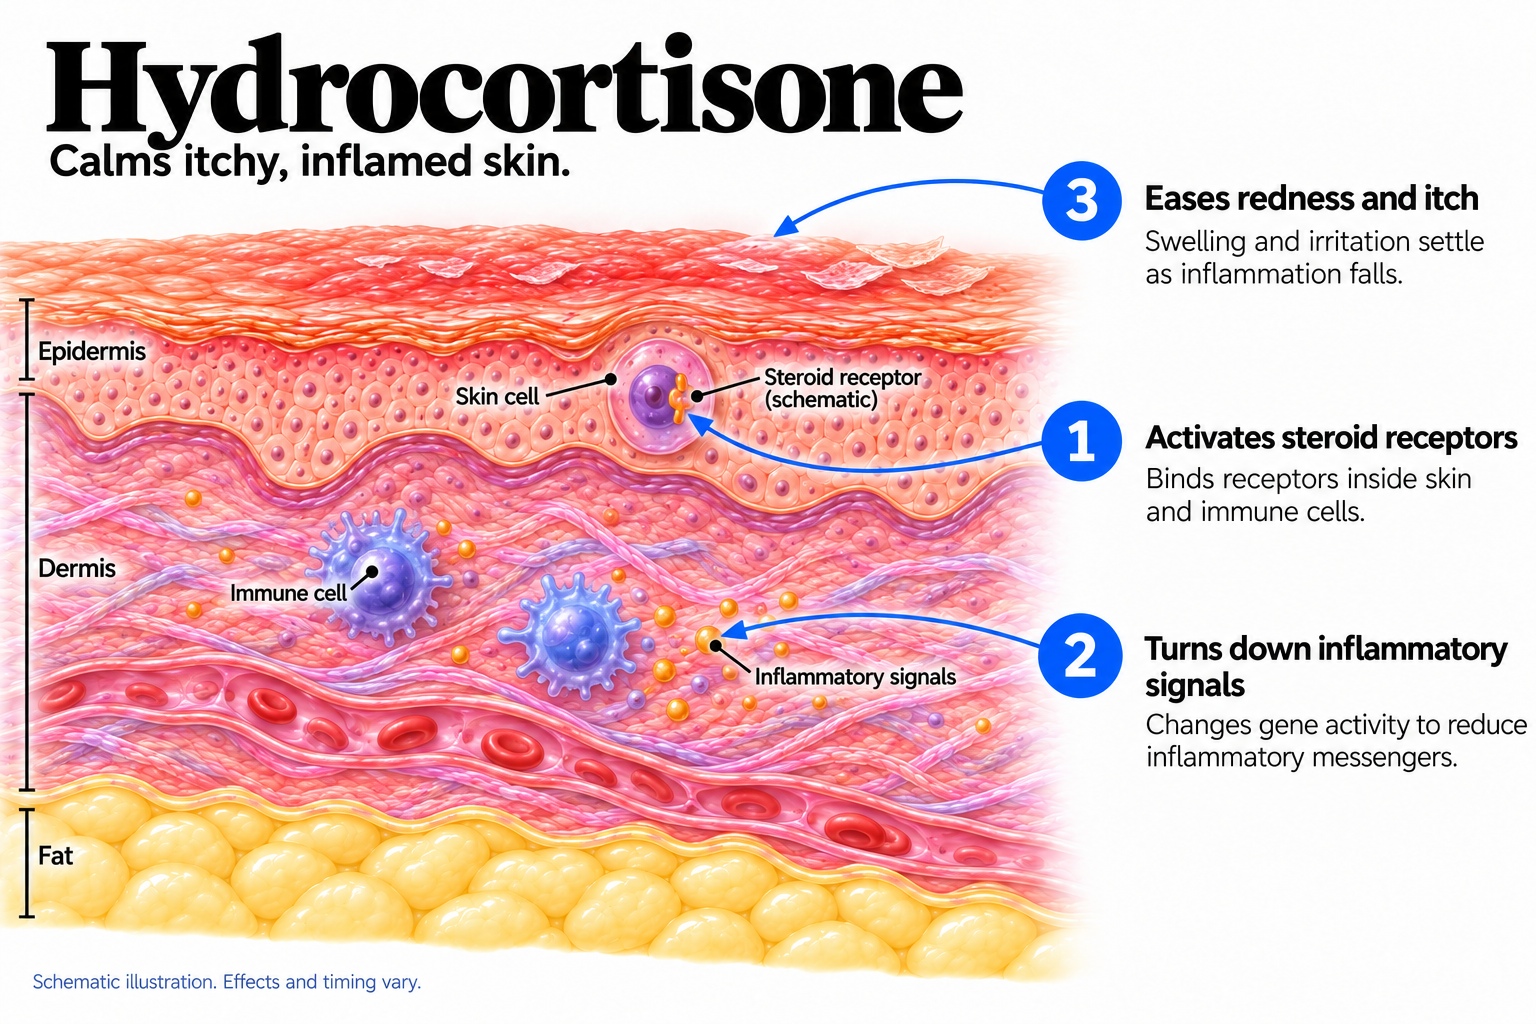
Diagram explanation and sources
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
Strengths
Hydrocortisone strengths
In the U.S., 0.5% and 1% hydrocortisone products are sold over the counter; 2.5% is a prescription concentration. These percentages cannot be used to rank hydrocortisone against different steroid molecules.
0.5%
1%
2.5%
A lower labeled concentration for temporary relief of minor irritation. Follow the product’s age and duration limits.
Available in several bases. OTC labeling is not permission for prolonged use on an undiagnosed rash.
A clinician-directed concentration. Cream, ointment and lotion can differ in feel and appropriate use.
Forms
Hydrocortisone forms

Cream
Richer and more moisturizing; often suits dry skin. The full formula still affects comfort.

Ointment
A greasy, protective base that helps hold moisture in. Often comfortable on very dry skin, but can feel heavy or sticky.

Lotion
Thinner than a cream and easy to spread over larger or hair-bearing areas. May feel less rich on dry skin.
How to use it
Your treatment, step by step.
How to apply it
- 01
When to Apply
Twice a day, on the rash only, on clean dry skin. A thin film that makes the skin look shiny is enough. One fingertip unit, the amount along the last joint of an adult index finger, covers about two adult palms. Moisturizer can go on a few minutes before or after.
- 02
How to Start
Twice daily from day one, until the rash is flat rather than merely better. Usually three to seven days. Two weeks is the outer limit for one stretch without seeing a clinician, less on the face.
- 03
If It Irritates
Stinging on application is usually the base, not the steroid, and is more likely on broken skin or from an alcohol-containing gel or spray. An ointment often settles it. Itch or redness that worsens over days can mean an allergy to something in the product, which does happen with steroids.
- 04
If It Is Not Working
Stop after about a week and reassess. A rash that does not respond to hydrocortisone is often not eczema. Ringworm, a yeast rash in a fold and psoriasis all look plausible and all need something different.
Monitoring & follow-up
No blood tests are needed for ordinary short courses in a healthy adult. Monitoring means looking at the skin: did the rash clear, has the skin gone thin or shiny, have small blood vessels appeared, are stretch marks forming in the folds.
Children absorb proportionally more because they have more skin surface for their size, so a doctor watches how much is used and over how large an area. Anyone applying a steroid to large areas most days for months should be under review rather than repeating over-the-counter purchases.
Hydrocortisone is not a drug to stay on continuously. Where a condition needs ongoing control, the plan is short bursts for flares, emollients doing the daily work, or a switch to a treatment designed for maintenance.
What to expect
How things change over time.
Applying it
A thin layer on the affected skin. The mildest steroid strength, which is why it is sold over the counter.
Itch first
Itching and stinging ease before the rash looks different, the earliest sign it is working. Insect bites and minor irritation settle in a day or two, and that is the whole course.
Clearing
Redness fades and the skin flattens. A mild eczema flare settles here; cracked skin takes longer than skin that was only red. Weeping or crusting should be settling, not spreading.
Judge it here
A mild rash should be gone or nearly gone. Contact dermatitis clears steadily once the trigger is gone.
Mild seborrheic dermatitis
Redness and flaking around the nose and brows improve.
Marks stay behind
Brown or gray patches where the rash was are pigment change, not scarring. They fade over weeks to months.
- First few minutes
- Days 1 to 2
- Days 3 to 7
- Weeks 1 to 2
- Weeks 2 to 4
- After stopping
When you stop
Short courses are stopped outright. No taper, no withdrawal from a week of hydrocortisone.
What does happen is relapse. Eczema, seborrheic dermatitis and psoriasis are ongoing conditions, so the rash returns if nothing is holding it. That is the condition coming back, not the cream causing it, which is why a maintenance plan matters more than the steroid's strength.
Topical steroid withdrawal is a separate, much less common problem, seen after months or years of near-daily use on the face or genital skin. It looks like burning, stinging and bright redness spreading beyond where the cream went, flaring badly on stopping. It is not a reason to avoid a week of treatment for a rash that needs it. If you have used a steroid daily for months, plan stopping with a clinician rather than quitting abruptly.
What it Pairs with
Hydrocortisone + your routine
| Product or situation | With Hydrocortisone | What to know |
|---|---|---|
| Moisturizer | Can pair | Moisturizer can go on a few minutes before or after. |
| Using it on a rash nobody has looked at | Avoid | Steroids blur ringworm and yeast rashes and let them spread. That is how a simple problem becomes stubborn. |
| Covering it unless you were told to | Avoid | Plastic wrap, a tight bandage or a diaper all count. Occlusion pushes far more drug in and turns a mild steroid strong. |
| Weeks of daily use on thin skin | Avoid | The face, eyelids, groin and armpits are thinnest and absorb most. Short courses are fine there. Months are not. |
| Using it as a moisturizer | Avoid | A steroid does not repair the skin barrier. A plain emollient does, and that is the daily job. |
| Using someone else's prescription tube | Avoid | Potency is not obvious from the label, and someone else's strong steroid used on the face is how the worst thinning happens. |
| Acne, rosacea and perioral dermatitis | Avoid | A steroid settles all three for a few days, then makes them worse. |
| If you are pregnant or breastfeeding | Use care | Ask the doctor managing your pregnancy before starting or continuing, including where on the body. If breastfeeding, keep it off the nipple area before a feed. |
| If the rash has not improved | Use care | After about a week, it may not be eczema. Ringworm and yeast rashes get worse with a steroid. |
| If the skin is weeping or crusted | Use care | Weeping, crusting, a golden-yellow color or spreading warmth suggests infection, which needs treating first. |
| If you are treating a child | Use care | Especially under two. Children absorb more for their size, and diaper areas are effectively occluded. |
| If you need it for more than a week or two | Use care | The face, eyelids and genital skin need a plan, not repeat purchases. |
| If the skin becomes thin or shiny | Use care | Easy bruising or small blood vessels appearing mean the same. Stop and get it looked at. |
| If pale patches appear on treated skin | Use care | Steroids can lighten skin, and it shows more on deeper skin tones. It usually recovers slowly, but get it assessed. |
| If you get swelling, hives or wheezing | Use care | Any change in breathing needs emergency care. |
Getting it and cost
Getting Hydrocortisone.
Cost & access
Hydrocortisone is cheap. Store-brand 1% cream is the same drug at the same strength as the branded tube, usually for much less. Anti-itch versions with added ingredients cost more without treating the inflammation any better.
What affects the cost
Prescription 2.5% is generic and also cheap, though the visit costs more than the tube. Ointments and creams are the cheapest vehicles. Foams and sprays cost more.
Alternatives
Other options to consider.

Desonide 0.05%
One step up in potency and still mild enough for the face and for children. Prescription only, so it is the usual next move when hydrocortisone is not enough.

Triamcinolone acetonide 0.1%
Mid-potency, and much more effective on body eczema and thicker rashes. Not a face or skin-fold treatment for more than a very short course.

Emollients and moisturizers
They do not clear a flare, but they reduce how often flares happen and how much steroid is needed overall. The two are partners, not alternatives.

Tacrolimus and pimecrolimus
These calm the same kind of inflammation without causing thinning, which makes them useful on eyelids and folds for long-term control. They burn or sting for the first week or two and cost more.

Crisaborole
A non-steroid option for mild to moderate eczema. Gentler on thin skin, commonly stings on application, and more expensive.

Antifungal creams
For the rashes they treat, which is the point. If the problem is ringworm or a yeast rash in a fold, a steroid is the wrong drug and an antifungal is the right one.
Questions
Questions you might be asking.
How long can I use hydrocortisone?
About a week at a time on the body for an over-the-counter tube, less on the face. A rash that needs it longer than two weeks is a reason to be seen, not to buy more.
Can I use it on my face?
For a few days, yes, and it is the mildest option there. Facial skin is thin and absorbs well, so weeks of daily use causes thinning, redness and small bumps around the mouth.
Is 1% strong?
No. It is the bottom of the potency ladder. If a week of it has not worked, question the diagnosis.
Will it thin my skin?
A short course on the body will not. Thinning comes from stronger steroids over long periods, especially on the face, eyelids, groin and armpits. Early changes usually recover over months. Stretch marks are permanent.
Can it lighten my skin?
It can. Pale patches on treated skin show up more on deeper skin tones, and usually fade slowly after stopping. Untreated inflammation also leaves light and dark marks, so avoiding treatment is not a way around it.
Can I use it on a fungal rash or on my child's diaper rash?
Not on its own. A steroid makes ringworm and yeast harder to recognize while they keep spreading. Diaper areas are covered, so absorption is higher, worth having a child's rash there looked at.
Related
Keep exploring.
Eczema
Ringworm
Contact Dermatitis
Psoriasis
Perioral Dermatitis
Eucrisa
Eucrisa vs Hydrocortisone

Clobetasol vs Hydrocortisone

Cyclosporine vs Hydrocortisone
Desonide vs Hydrocortisone
Dupixent vs Hydrocortisone
