Psoriasis
An overactive immune system tells skin cells to grow many times faster than normal — building raised, scaly plaques that come and go.


Key facts
Psoriasis at a glance.
Typical signs
Scaly, raised plaques
Common locations
Elbows, knees, scalp, lower back
Expected course
Lifelong, with flares
Treatment options
Creams, light therapy or medicines
What is it?
Top things to know about Psoriasis
- It is an immune-driven disease. Immune signals speed up the production of skin cells.
- Cells build into plaques. They accumulate into well-defined, scaly patches instead of shedding normally.
- It is more than surface scale. Scrubbing off scale does not treat the underlying process.
- It can affect nails and joints. Nail changes and joint swelling or morning stiffness warrant assessment.
What it looks like
What Psoriasis looks like
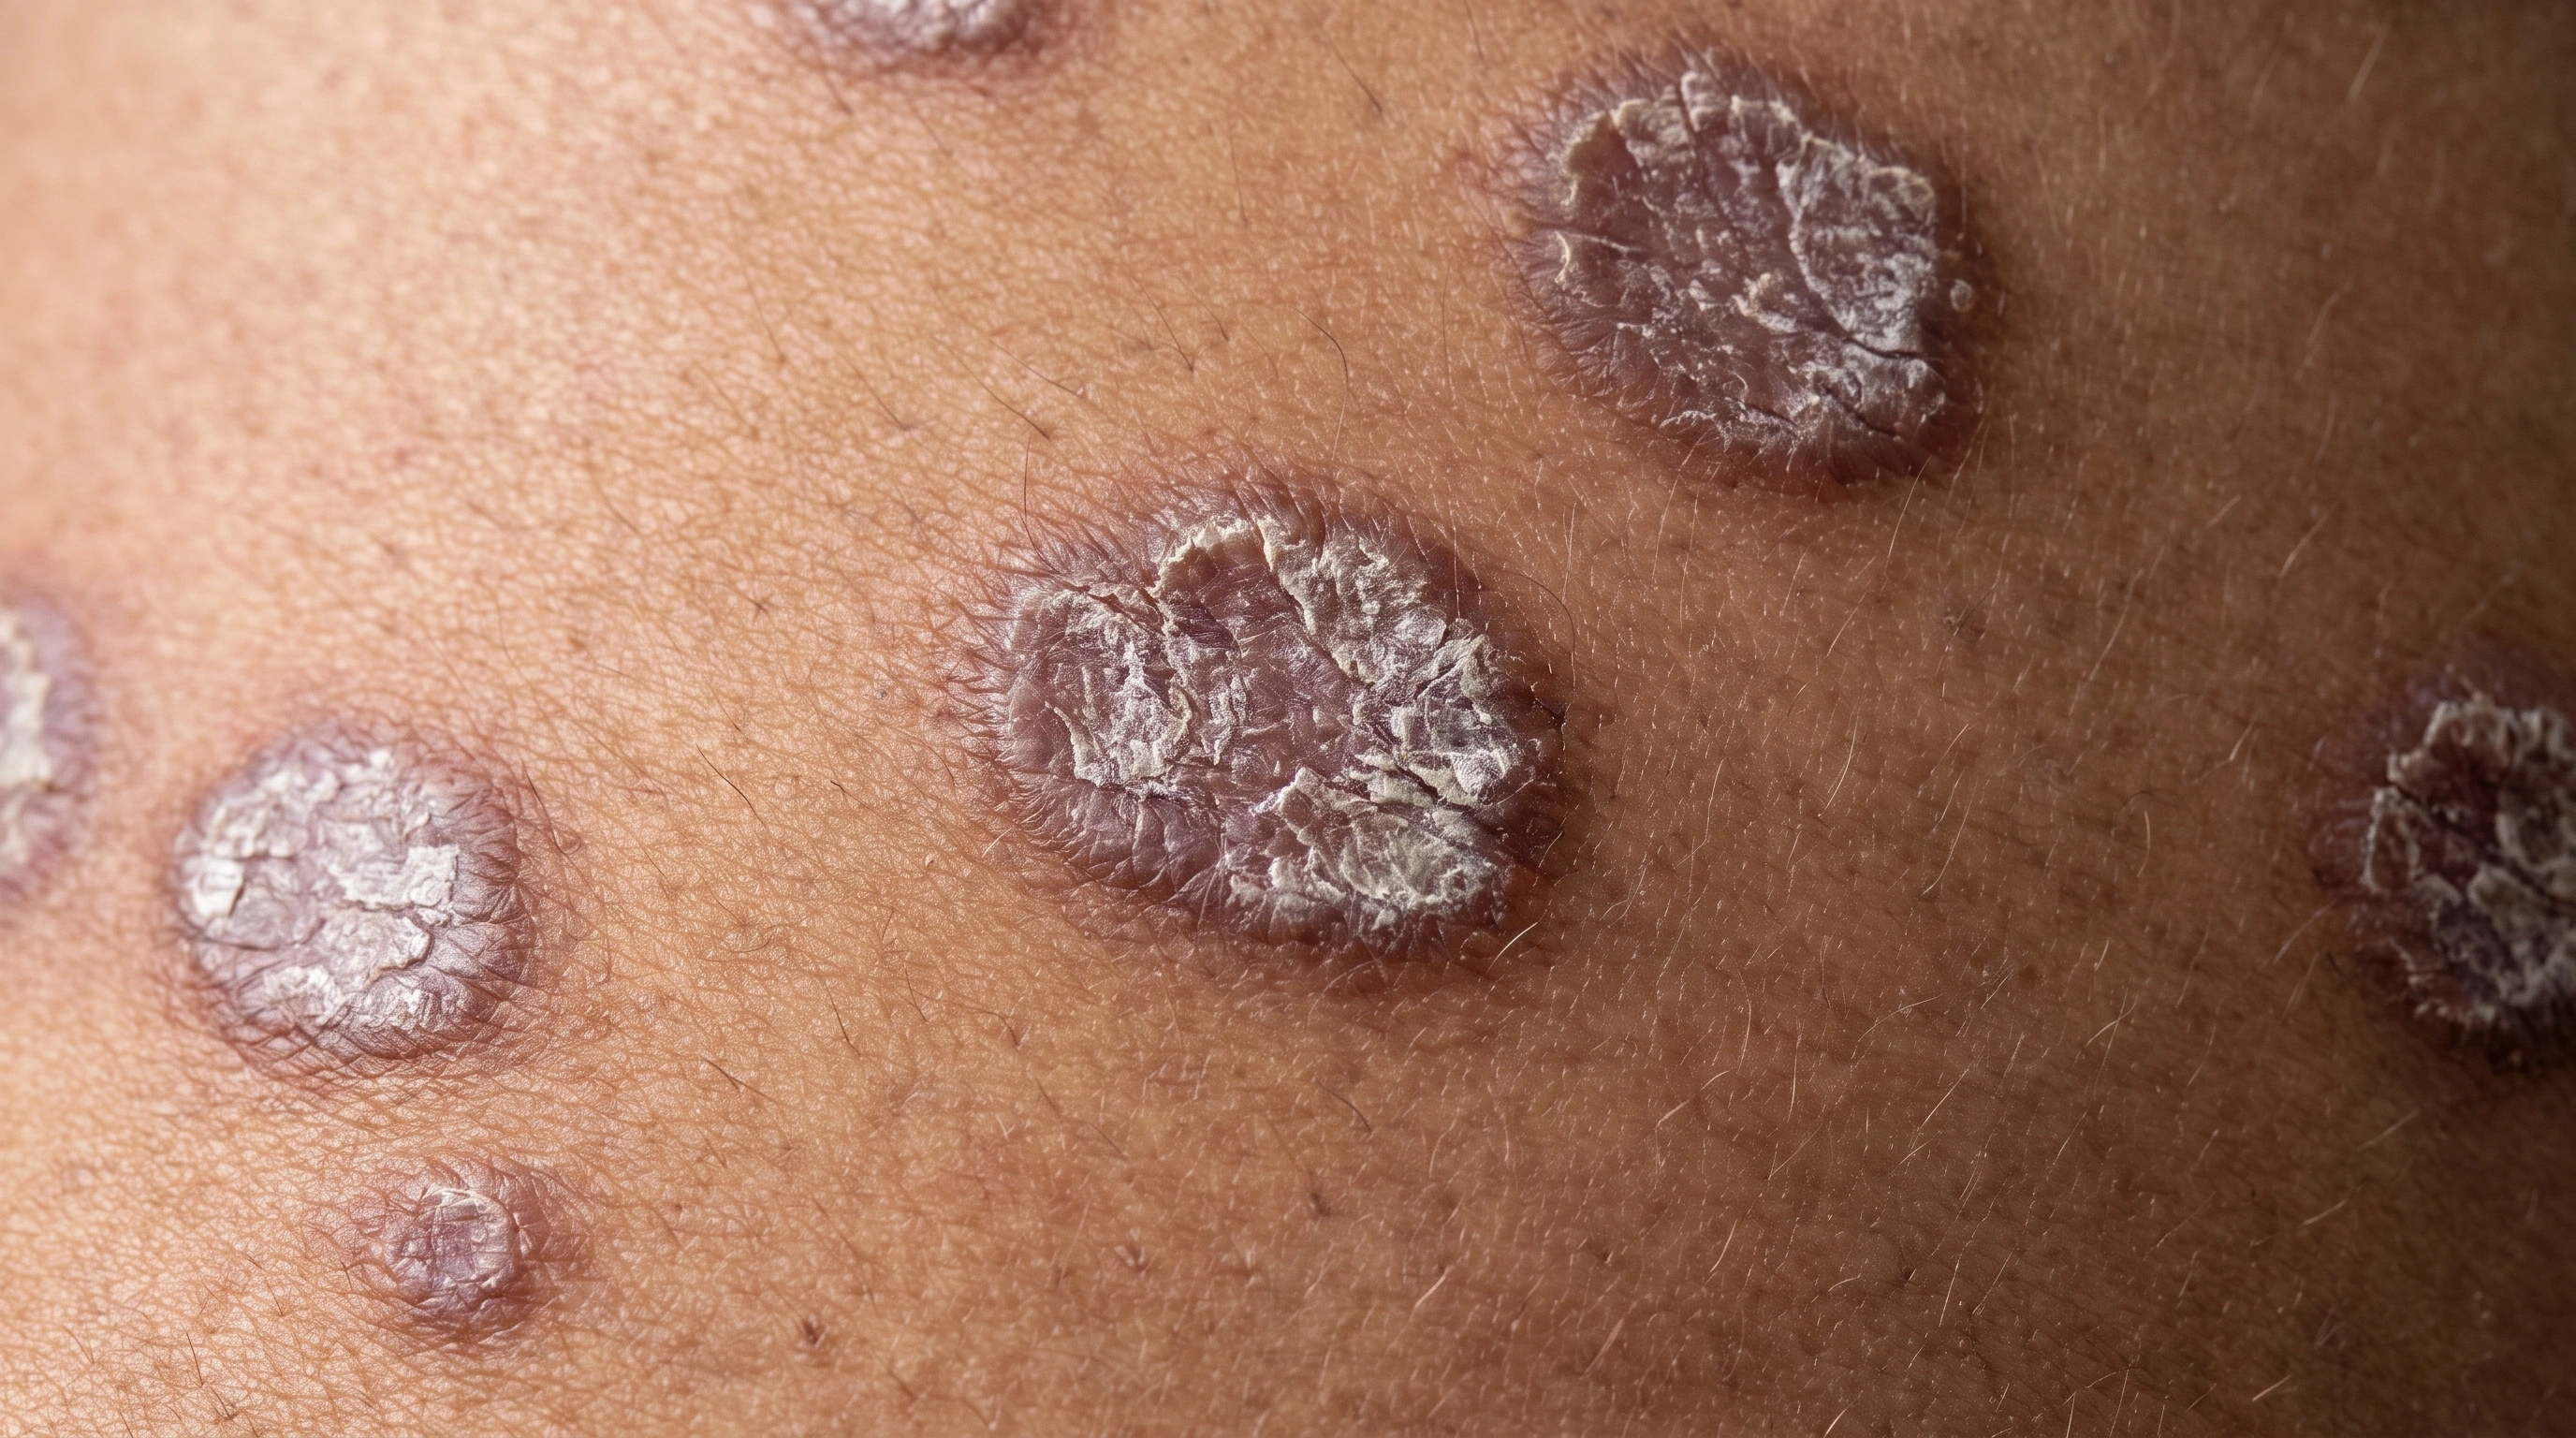
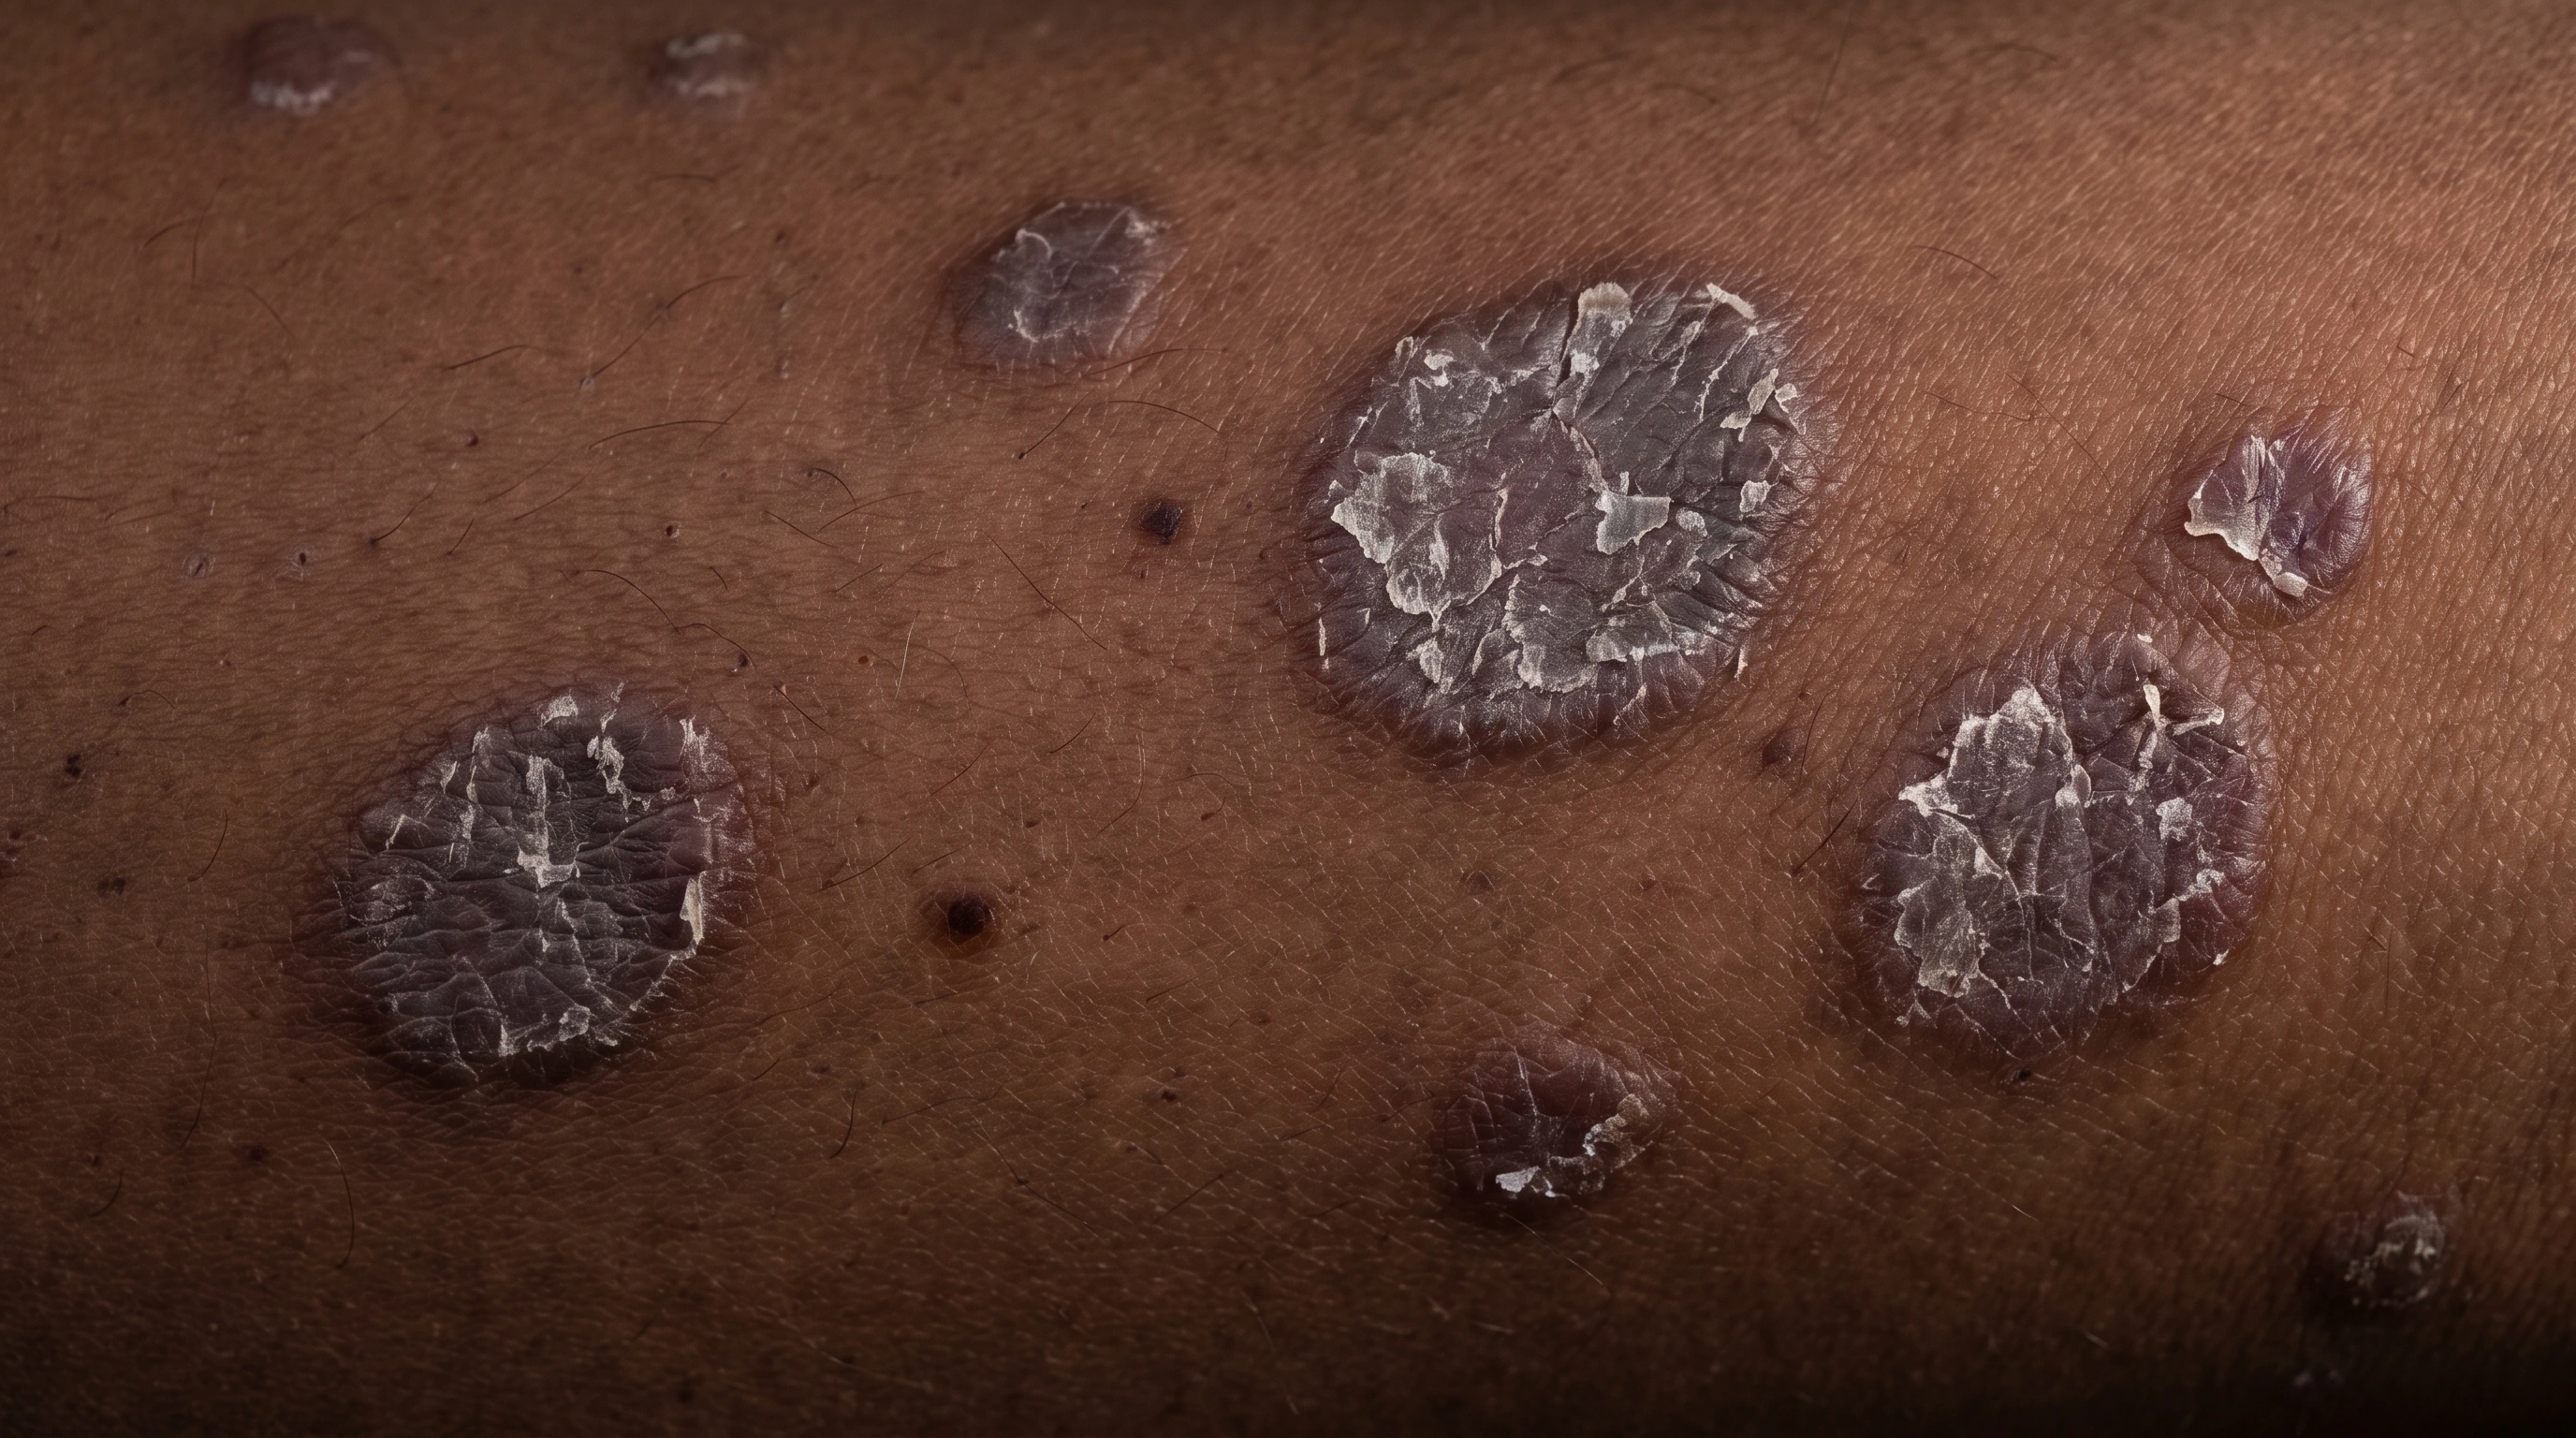
Psoriasis usually appears as raised, well-defined patches called plaques, covered in dry silvery-white scale. The patches tend to show up symmetrically on the elbows, knees, scalp and lower back, and they can itch, burn or crack. Scratching or injuring the skin can trigger new plaques in the same spot, a reaction known as the Koebner phenomenon. Up to half of people with psoriasis also have nail changes.
Psoriasis comes in several forms, and some people have more than one at once. Plaque psoriasis is by far the most common. The other types differ in where they appear and how the skin looks, from small drop-like spots after an infection to smooth patches in skin folds. Erythrodermic and widespread pustular psoriasis are rare but serious, and they need prompt medical care.
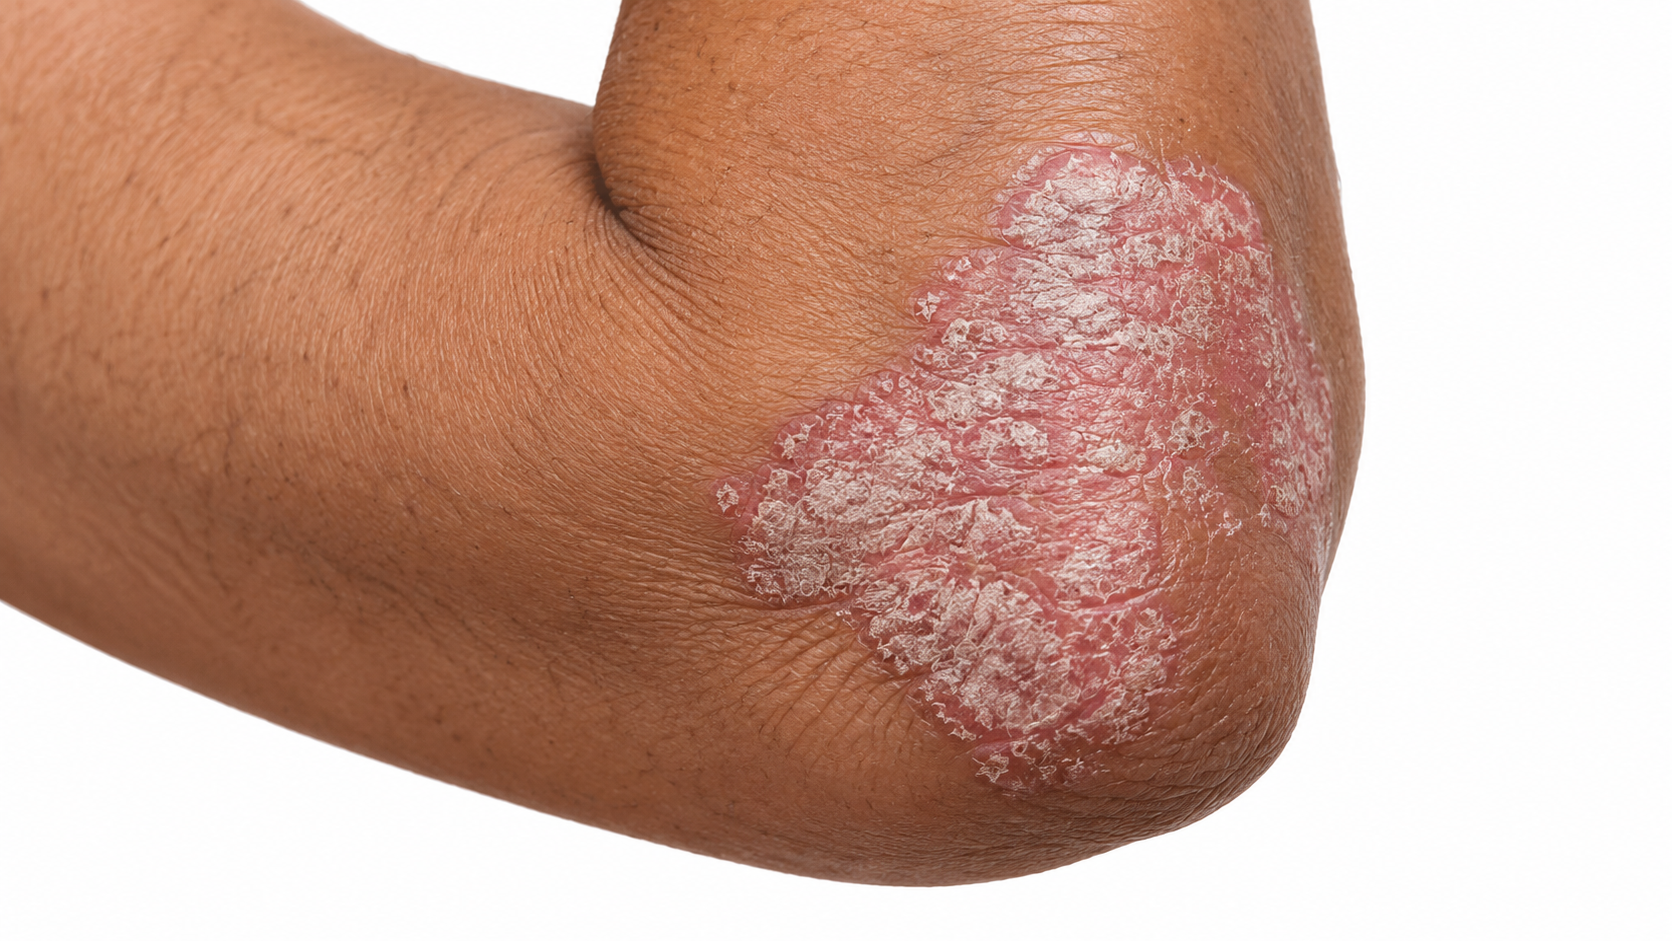
Plaque psoriasis
The most common type, about 80–90% of cases.

Silvery scale
Silvery-white scale covers the plaque surface.
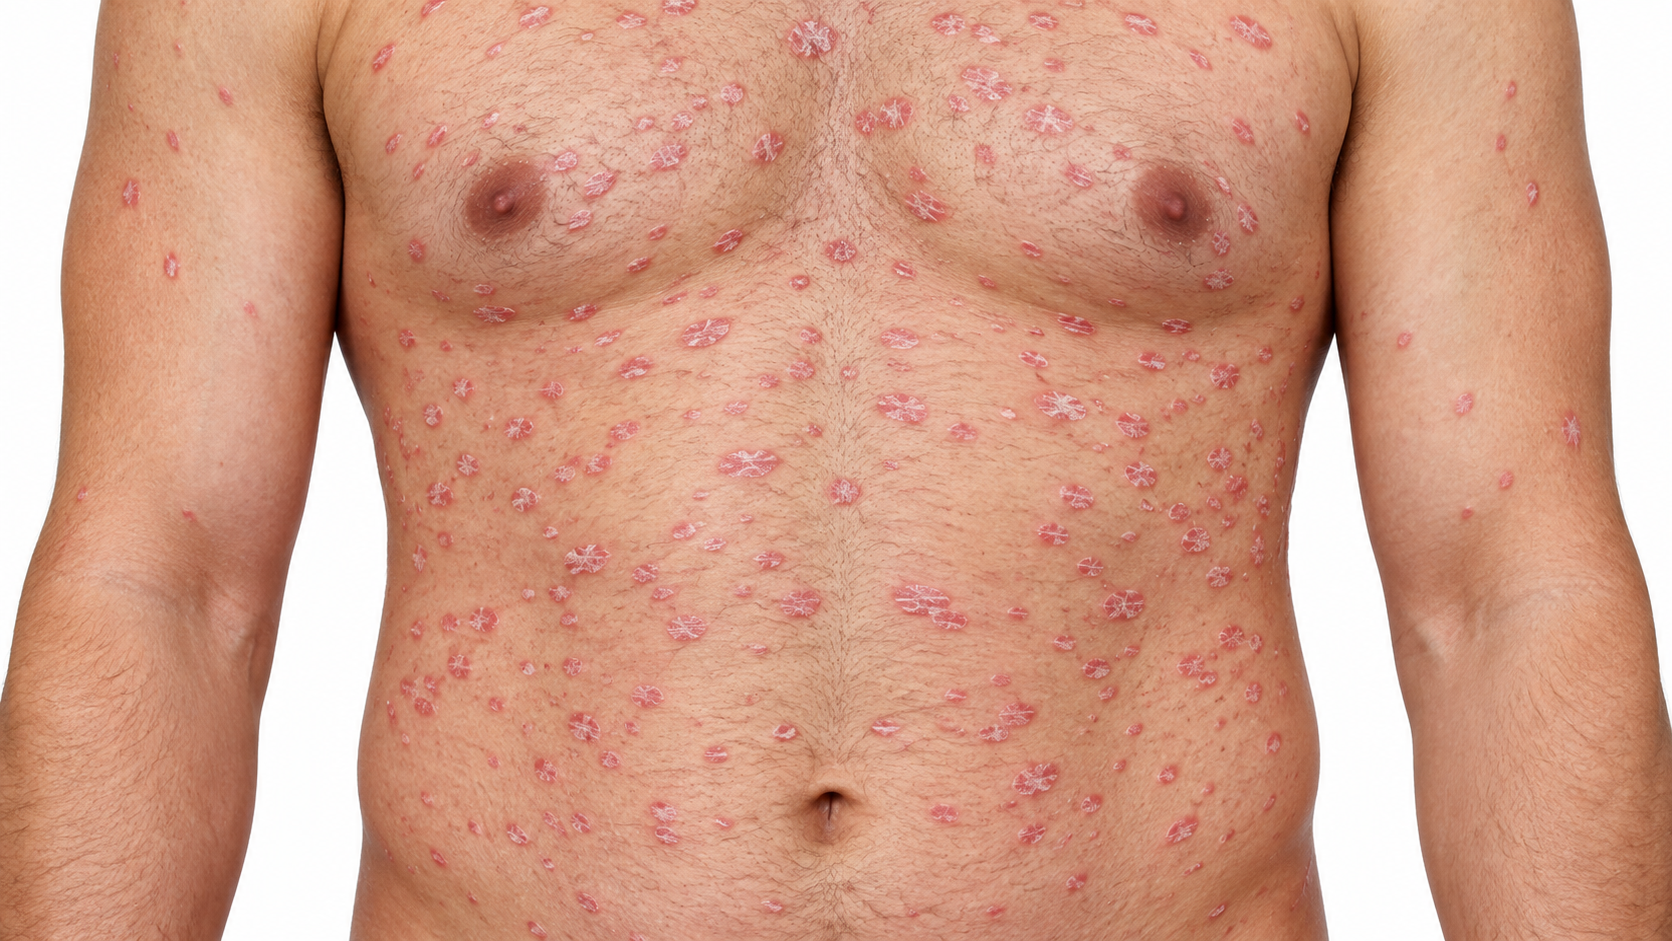
Guttate psoriasis
Small drop-shaped spots, often after strep throat.
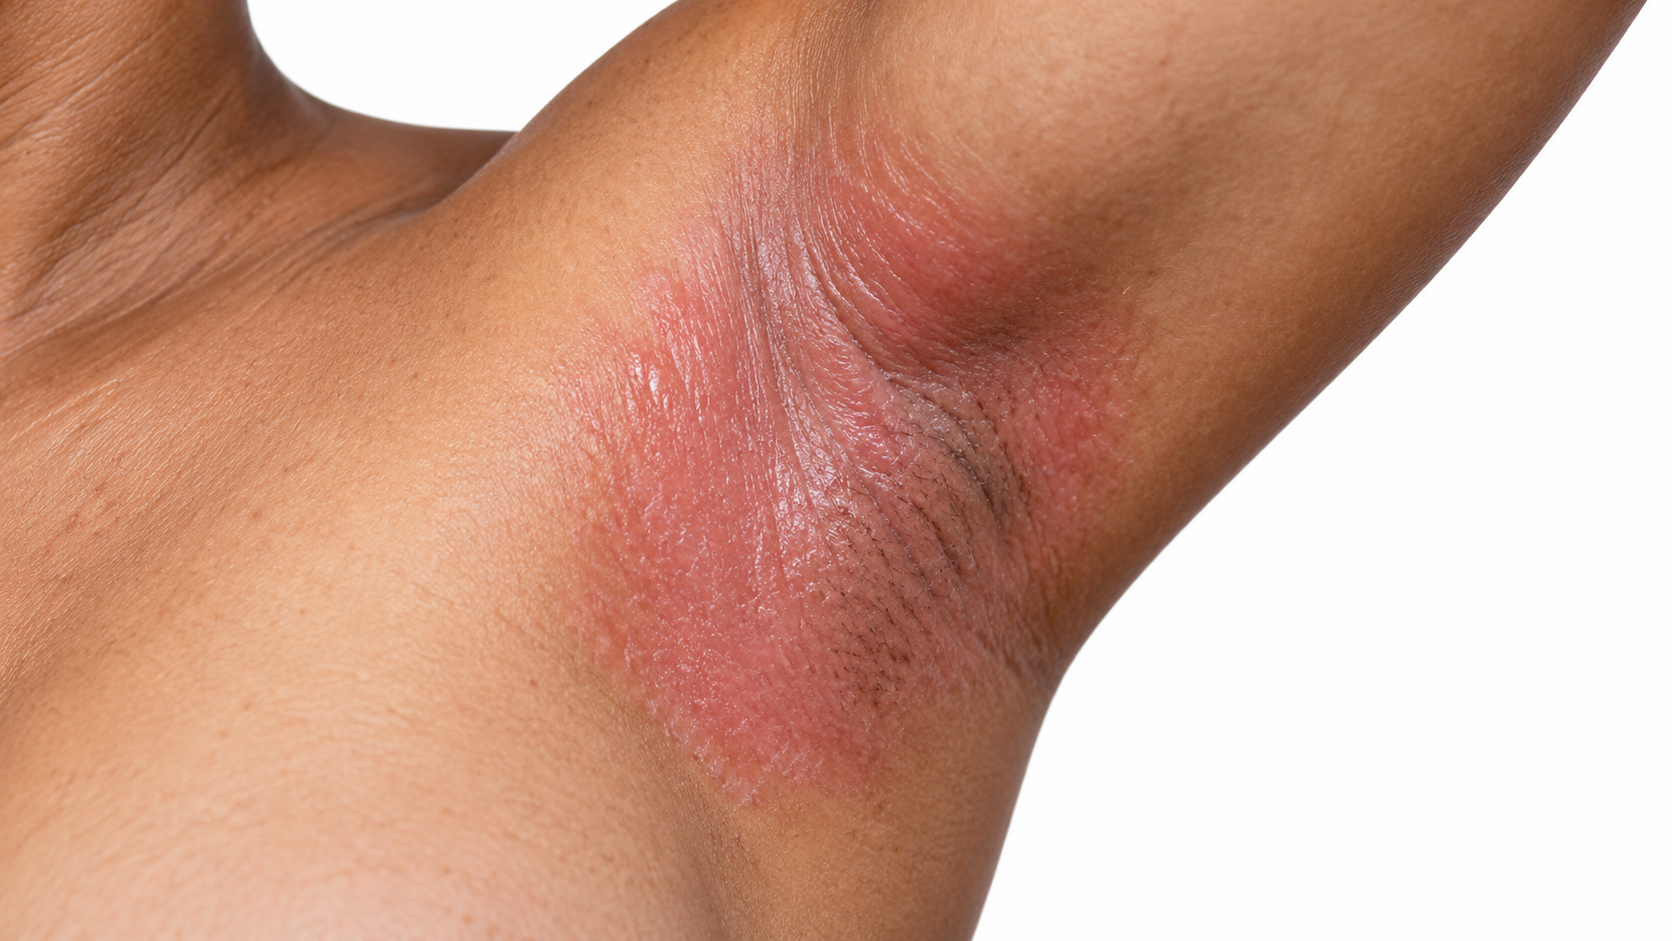
Inverse psoriasis
Smooth red patches in skin folds, without scale.
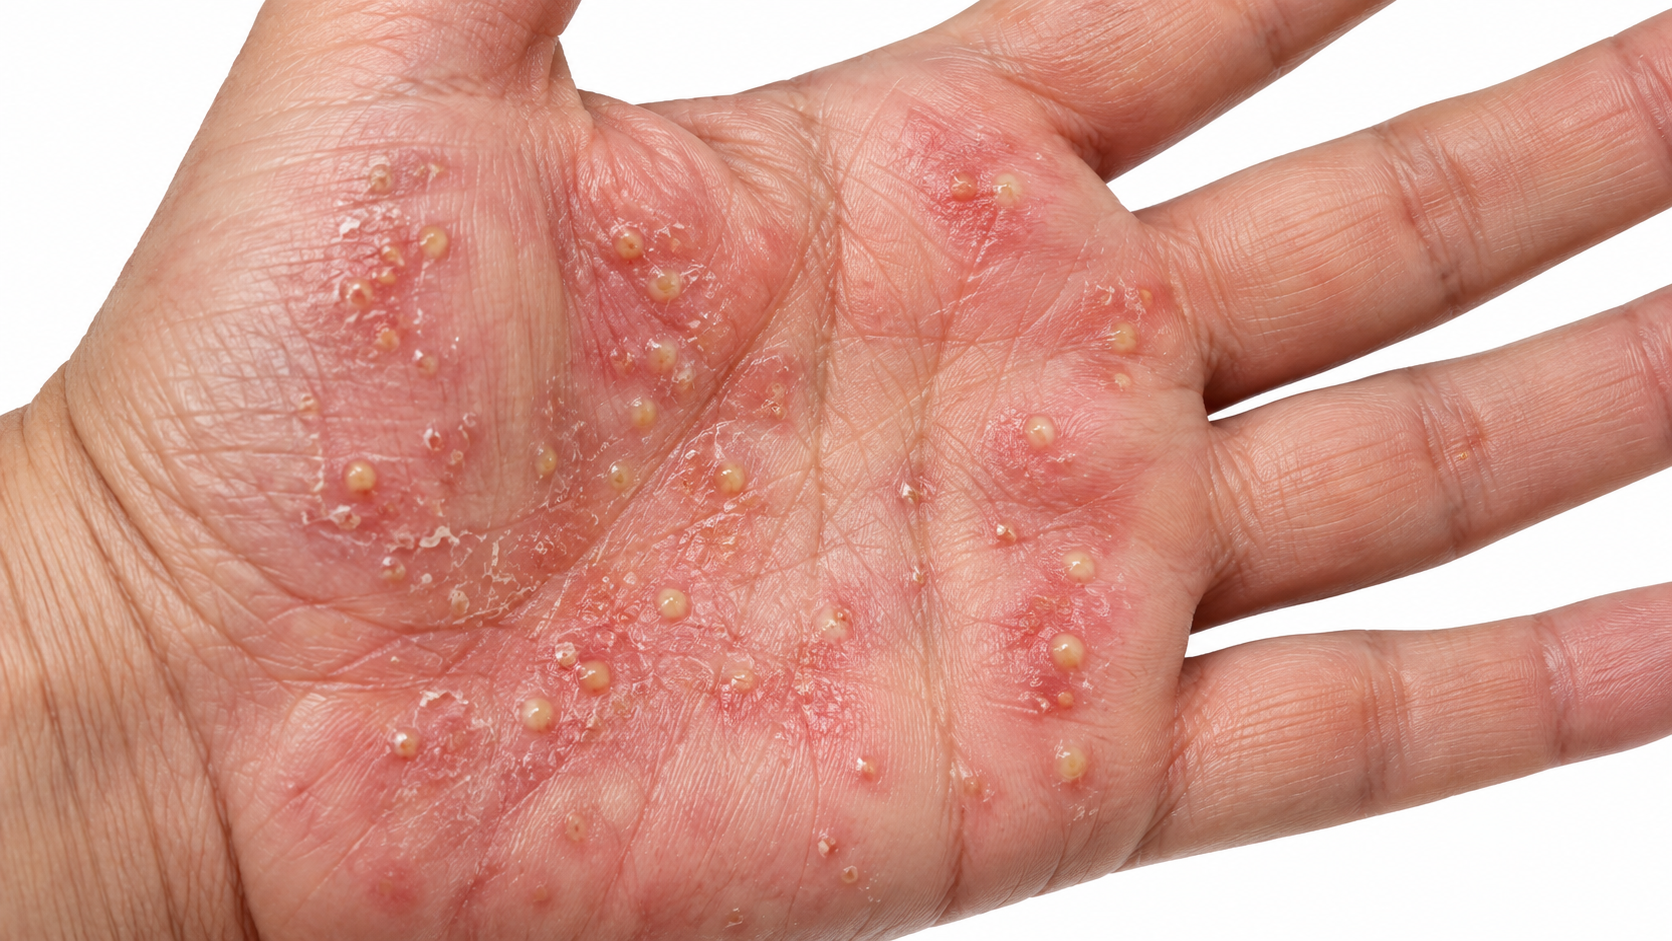
Pustular psoriasis
Pus-filled bumps on red skin, often hands and feet.
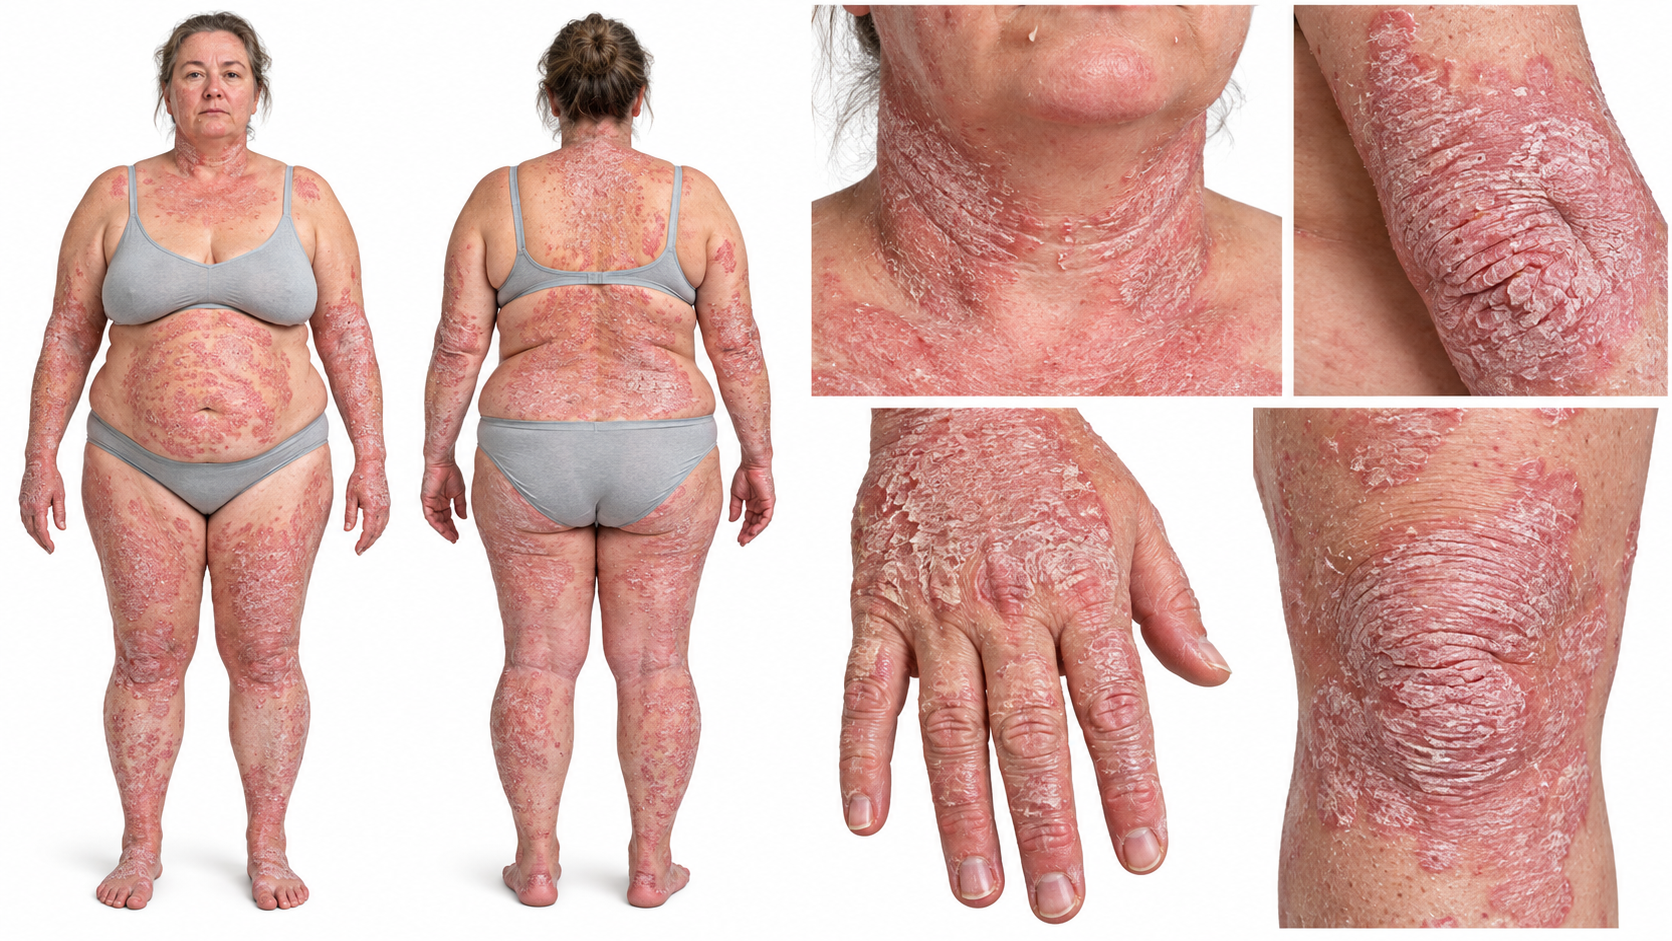
Erythrodermic psoriasis
Rare, widespread redness that needs urgent care.
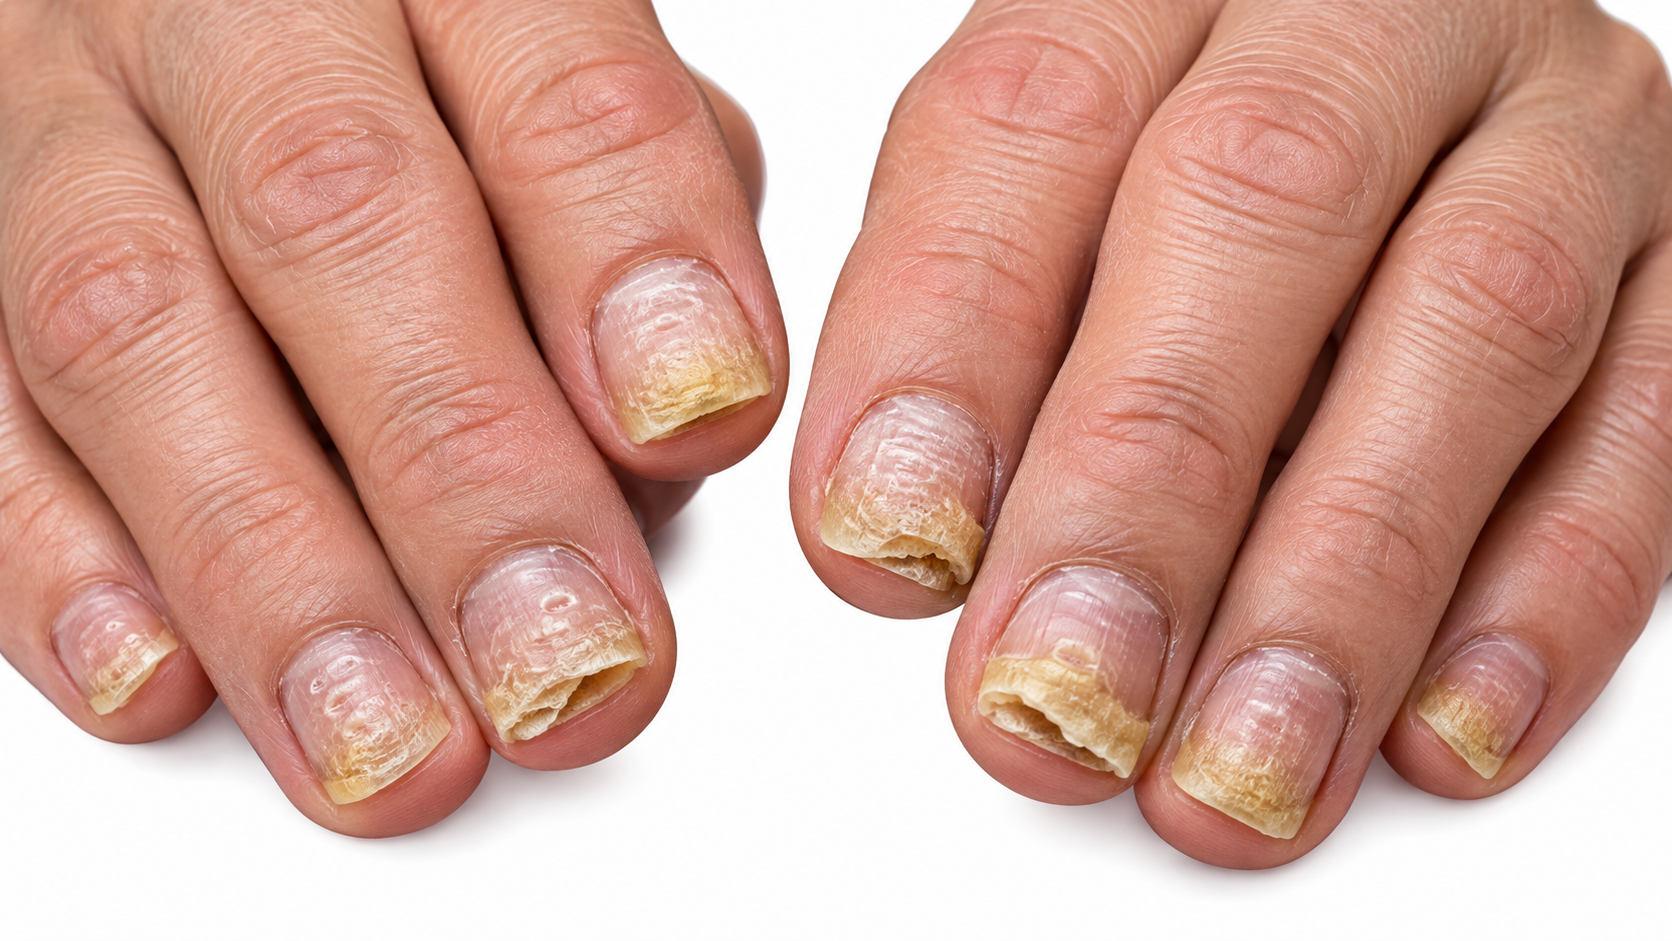
Nail psoriasis
Pitting, thickening and lifting of the nails.
Where it shows up
Adult: Outer joints and lower back
A classic plaque pattern affects the outside of the elbows, fronts of the knees, scalp and lower back. Nail and skin-fold involvement are not shown here.
Child: Scalp and outer joints
Children can have plaques on the scalp, elbows and knees. Facial and skin-fold involvement can also occur; this map shows one example pattern.
Baby: Diaper area and skin folds
Infant psoriasis can involve the diaper area, including folds. The dashed outline marks the covered area; scalp involvement is shown separately.
Hairline, behind the ears and nape
Scalp psoriasis can extend beyond the hairline. The rear view shows example sites on the back of the scalp, behind the ears and at the nape.
On different skin tones
Psoriasis on different skin tones
Most textbook photos show psoriasis on light skin, where it looks pink or red. On brown and Black skin, plaques are often violet, dark brown or gray, and the scale can be more noticeable than the redness. This can delay diagnosis. After a plaque clears, darker skin often keeps dark or light marks for months. These marks are not scars and usually fade on their own.
What happens in Psoriasis?
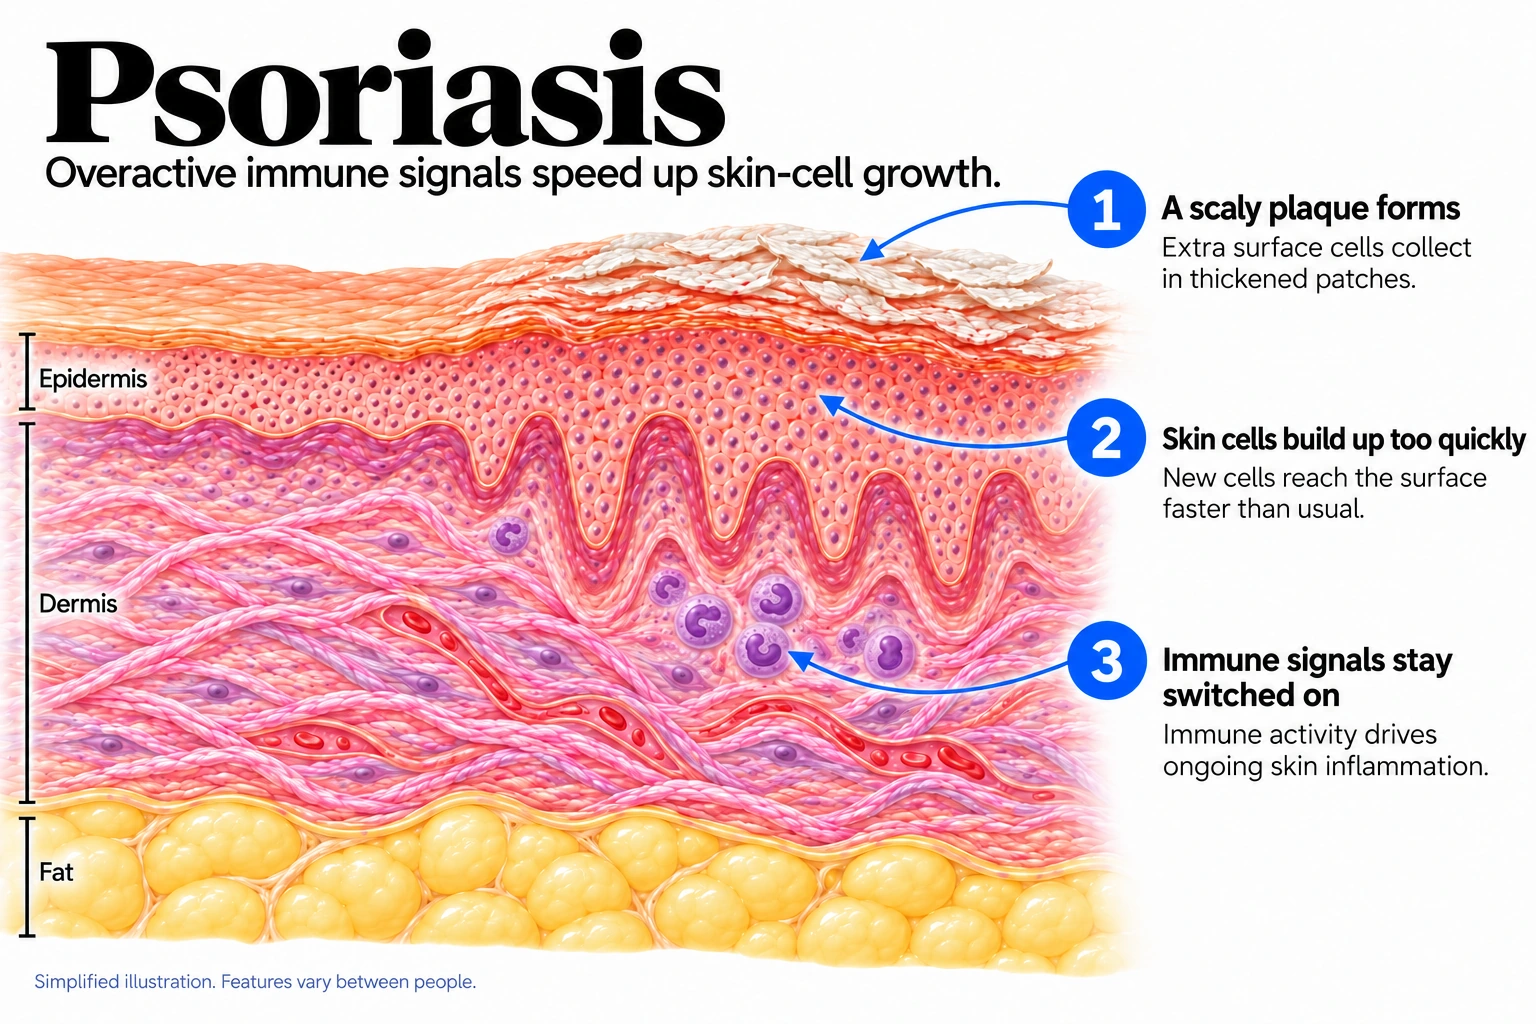
Overactive immune signals make skin cells multiply faster than they can shed normally. The extra cells build into thick, scaly plaques over inflamed skin.
- A scaly plaque forms: Extra surface cells collect in thickened patches.
- Skin cells build up too quickly: New cells reach the surface faster than usual.
- Immune signals stay switched on: Immune activity drives ongoing skin inflammation.
Causes and triggers
What causes Psoriasis
Causes
Why it happens
Psoriasis happens when the immune system overreacts and speeds up skin growth. Genes set up the tendency, risk factors raise the odds, and triggers set off each flare.
About 1 in 3 people have a close relative with psoriasis. HLA-C*06:02 is the best-known gene, but many genes play a small part.
Risk factors
Raise the odds
- Obesity
- Smoking
- Heavy drinking
- HIV
Triggers
Bring it on or make it worse
- Stress (Well established)
- Strep throat (Well established)
- Skin injury (Well established)
- Some medicines (Strong link)
- Stopping steroids (Strong link)
- Cold, dry weather (Possible)
When it usually starts
When it usually starts
Psoriasis
Can begin at any age; onset commonly occurs in younger adults or later adult life.
Daily care
Small habits, calmer skin.
A gentle routine supports your skin alongside your treatment plan.
Leave scale alone
Avoid picking or rubbing irritated skin.
Make time to unwind
Build a manageable stress break into your day.
Notice your patterns
Keep brief notes on flares and possible triggers.
Moisturizing
Help with dryness and discomfort.
Treatments
Find the right level of treatment.
Explore the options your dermatologist may discuss, from skin treatments to light therapy and medicines.













Phototherapy
Narrowband UVB is a prescribed ultraviolet light treatment for psoriasis.

Outlook
Lifelong, but very manageable.
Psoriasis tends to come and go. Treatment can help control symptoms, with a plan that changes as your needs change.
- 1
Diagnosis
Your dermatologist examines your skin, scalp, and nails and discusses your symptoms.
- 2
Starting treatment
Give your plan time to work. How soon you see changes depends on the treatment.
- 3
Checking progress
Review your response and any side effects. Adjust the plan together if needed.
- 4
Long term
Maintain control and plan for flares, with follow-ups tailored to you.
Complications
More than skin deep.
Psoriasis is associated with other health conditions. These are possibilities to be aware of, not things everyone will develop.
Psoriatic arthritis
Joint pain, stiffness, or swelling can be signs. Tell your doctor about new joint symptoms.
Heart disease
Cardiovascular risk is higher, especially with severe psoriasis. Discuss your overall heart health.
Metabolic syndrome
High blood pressure, blood sugar, and cholesterol are among the related health concerns.
Depression & anxiety
The emotional effects deserve care too. Tell your care team how psoriasis affects your life.
Inflammatory bowel disease
Crohn’s disease and ulcerative colitis are associated conditions.
Eye inflammation
Uveitis can occur. A painful red eye or changes in vision need prompt medical attention.
When to get help
When to get help
When to seek care
Seek assessment for persistent plaques, nail changes or joint pain and stiffness. Widespread painful redness, fever or rapidly spreading pustules need urgent care.
Lookalikes
What else could it be?

Eczema
Psoriasis usually has sharper edges than eczema, so it is easier to see where the rash starts and stops. Eczema’s edges tend to fade into nearby skin.
Seborrheic Dermatitis
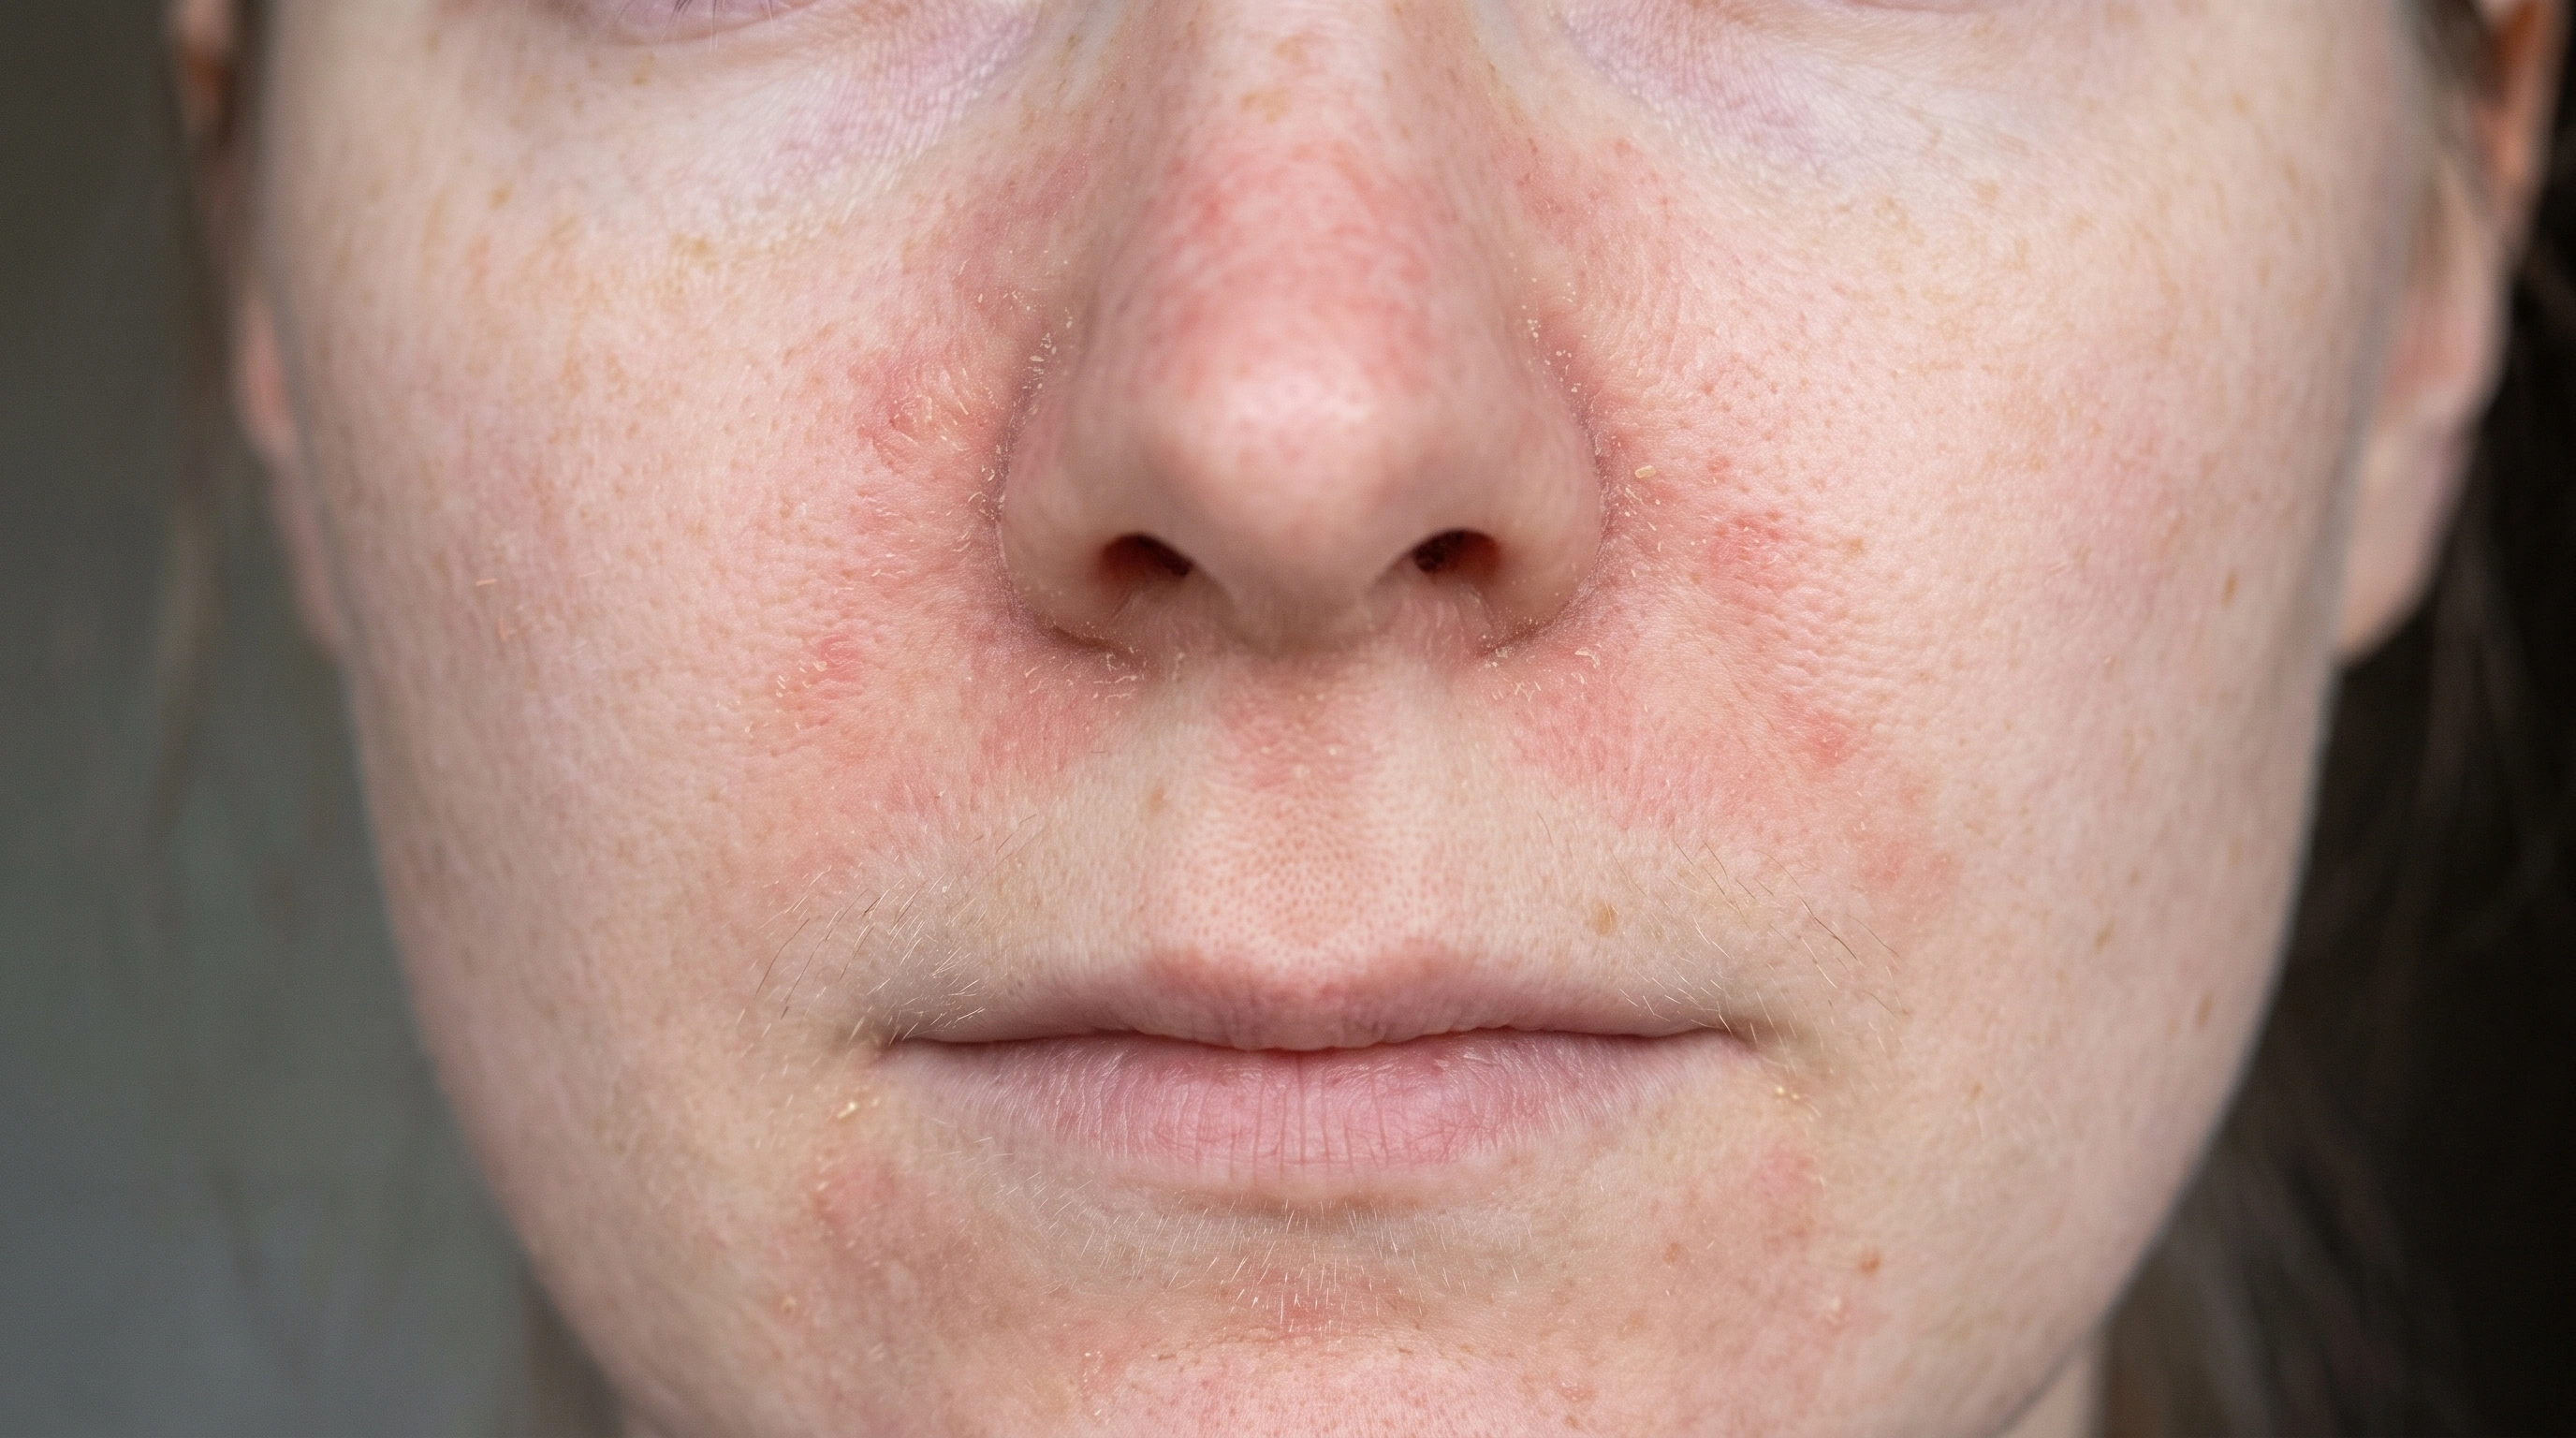
Seborrheic dermatitis usually has greasier, yellowish scale and softer edges. Psoriasis tends to be thicker and drier, with a clearer border that may cross the hairline.
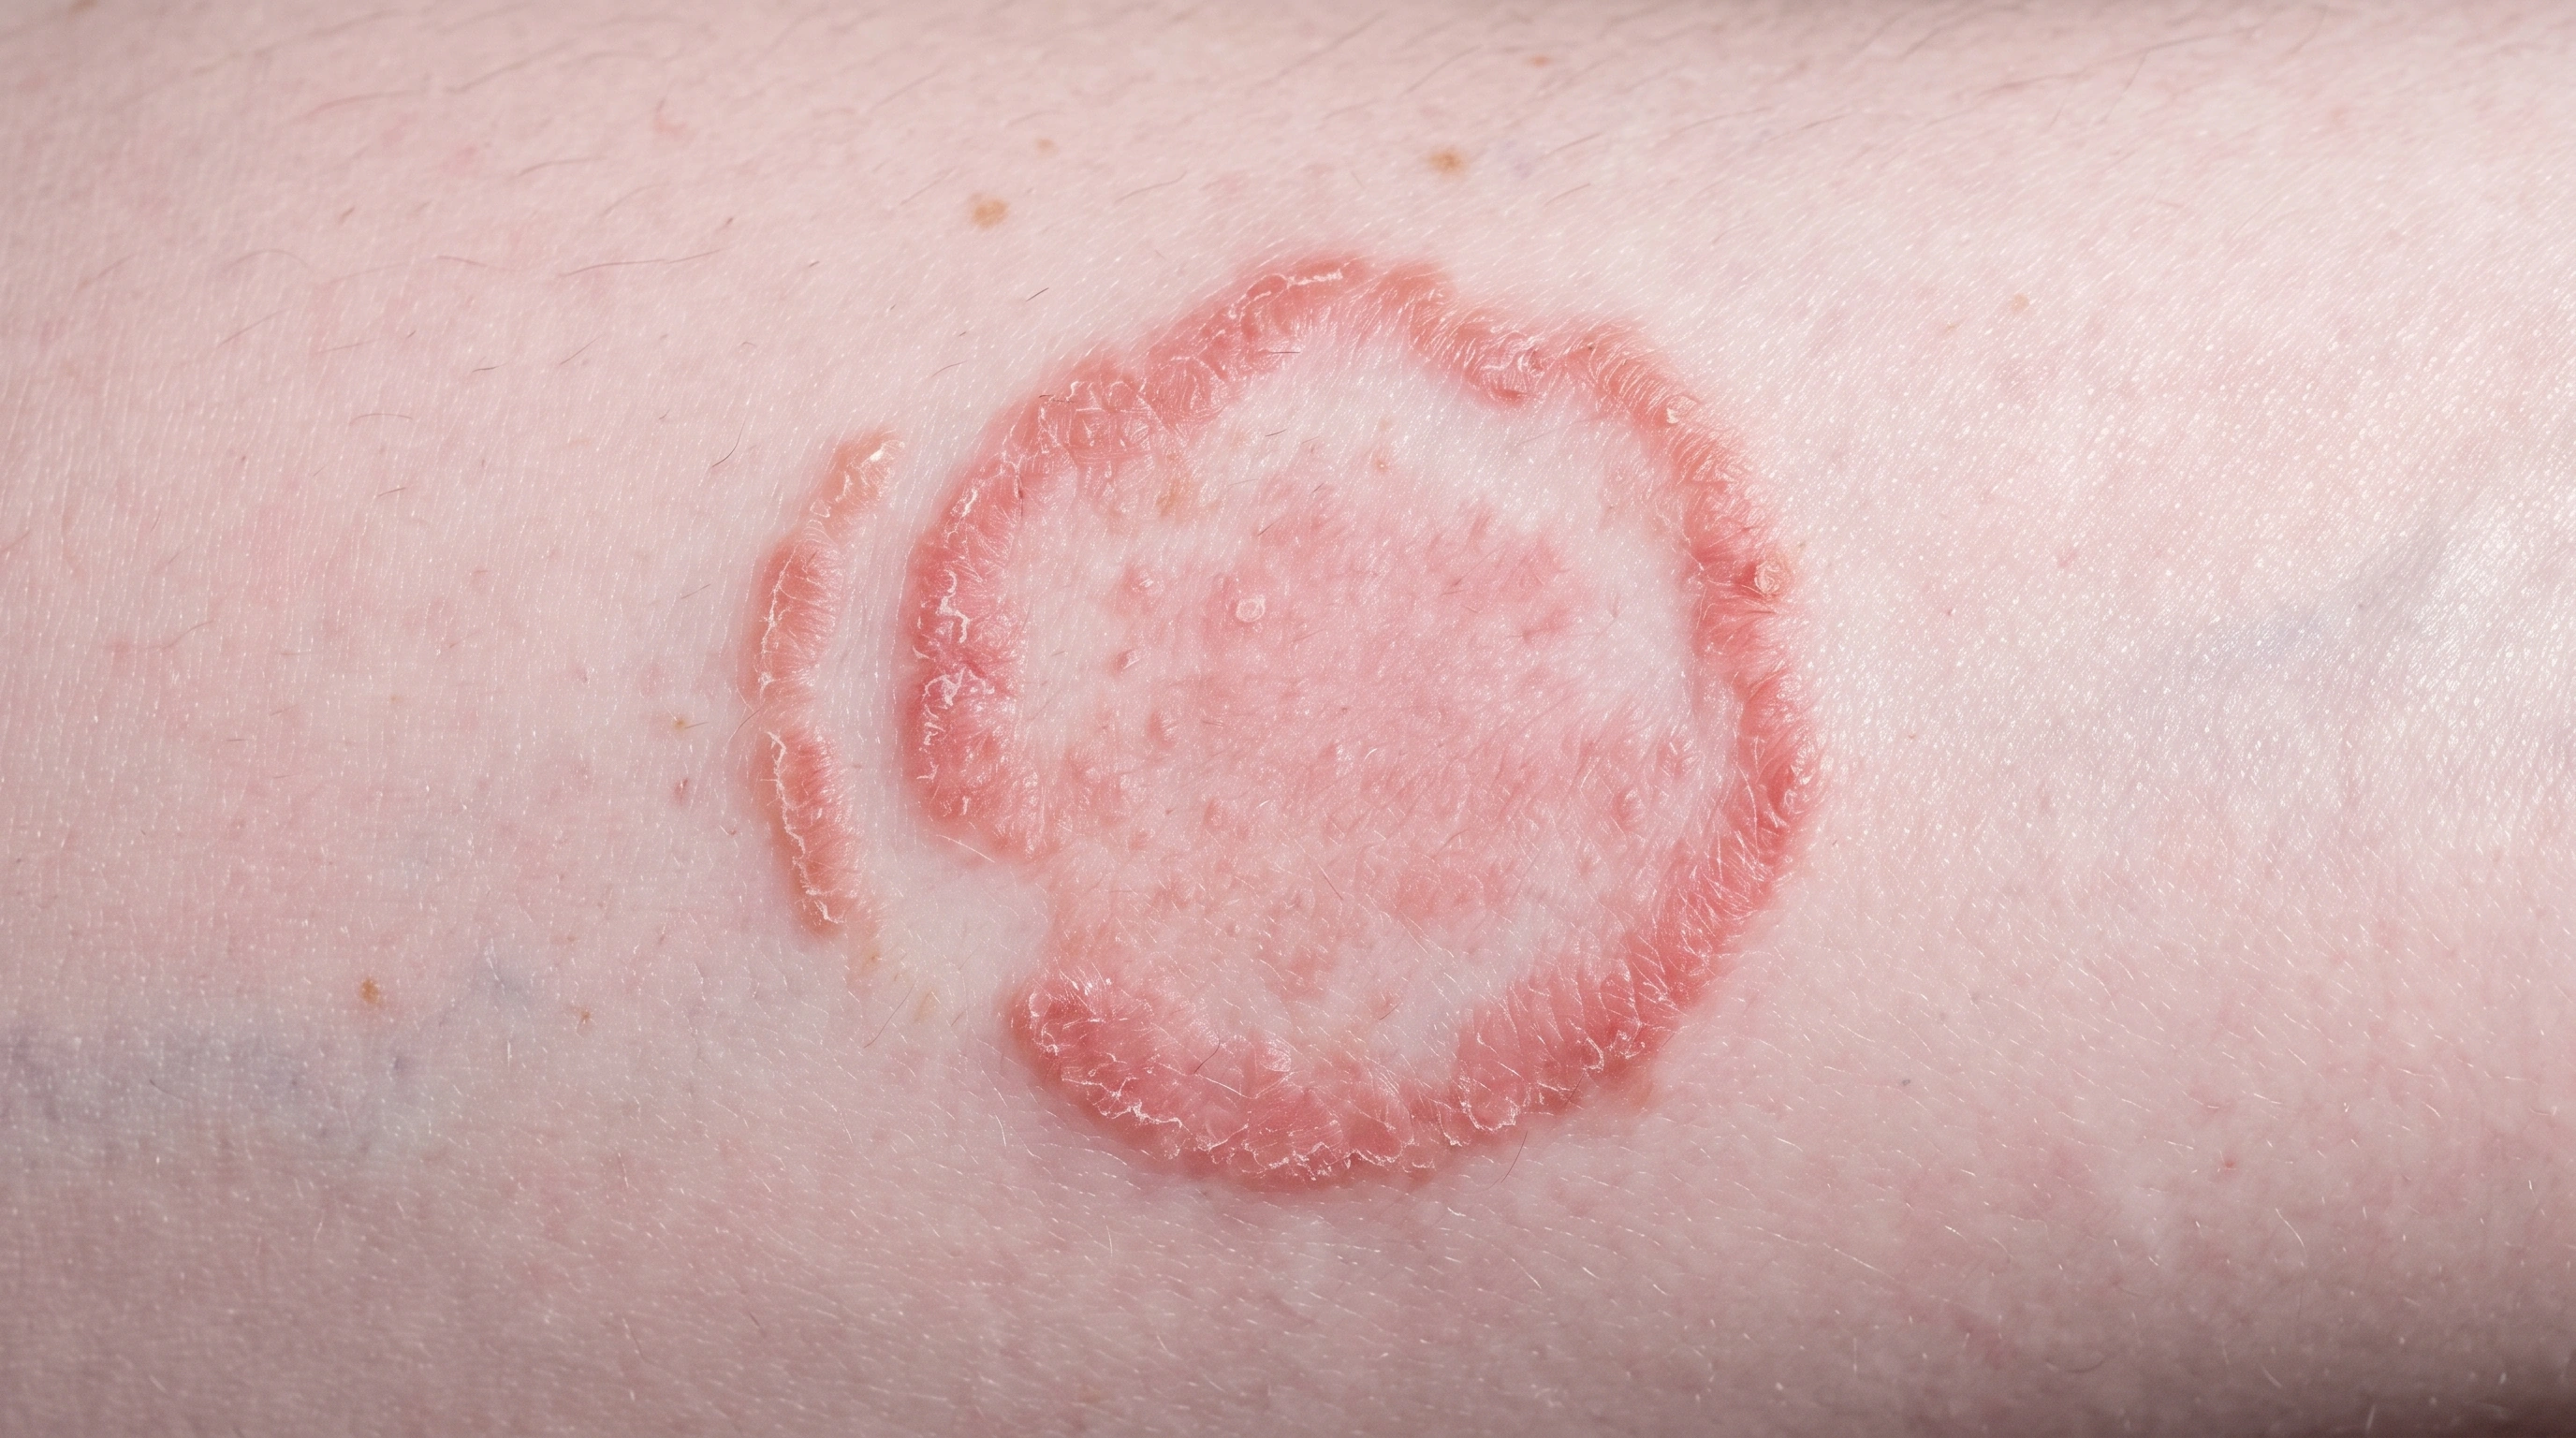
Ringworm
Ringworm often has a clearer center and a scaly rim spreading outward. Psoriasis usually forms a more evenly filled patch; a scraping can help distinguish them.
Questions
Questions you might be asking.
Is psoriasis curable?
No, but that is less discouraging than it used to be. It is lifelong and comes and goes, and nothing removes it permanently. What has changed is control — with modern treatment, a large share of people with moderate to severe psoriasis reach clear or nearly clear skin and keep it there for years.
Is it contagious?
Not at all. You cannot pass psoriasis to anyone by touch, by sharing a towel or a bed, or in a pool. It is your own immune system acting on your skin. The misunderstanding is often harder to live with than the plaques.
Will I get psoriatic arthritis?
Around one in three people with psoriasis does, usually years after the skin is affected, occasionally before. There is no way to predict it, so know the symptoms — joint pain and swelling, a whole finger or toe swelling up, heel or lower back pain, and morning stiffness over thirty minutes. Report those early; joint damage cannot be undone.
Are biologics safe?
Well studied and, for most people, well tolerated. They block one specific immune signal rather than suppressing the immune system broadly, which is why they work so well. There is a real but modest increase in some infections. Tuberculosis and hepatitis screening comes first, and monitoring continues. Decide from a conversation about your own risks, not a general verdict.
Does diet matter?
Less than the internet suggests, more than not at all. What has decent support is losing weight if you carry extra — that improves psoriasis on its own and makes some treatments work better — and cutting back on alcohol. Gluten-free eating helps only the small group with celiac disease too. No diet clears psoriasis.
Can I stop treatment when my skin is clear?
Usually not, and this is the commonest reason people end up back where they started. Clear skin means the treatment is doing its job, and most plaques return within weeks to months of stopping. Treatment can often be stepped down instead — a decision for your dermatologist, not you alone.
Sources
