It combines scraping and heat.
A lesion is scraped with a curette and treated electrically.
Electrodesiccation and Curettage: A small, low-risk skin cancer is scraped out with a sharp loop, and the base is then burned. It takes one visit and needs no stitches. It leaves a round pale scar, and the edges are never checked under a microscope.
Skin Tag Removal: A quick office procedure to snip, freeze or burn off a skin tag. It takes seconds and there is little downtime. Anything pigmented, growing or changing is not treated as a skin tag until a clinician has looked at it.


Choose for a small, low-risk skin cancer on the body when one quick visit with no stitches matters more than margin checking.
Choose to remove skin tags that catch or bother you in a quick visit — anything pigmented or changing is checked first.
Can you have both?
Light electrocautery is one way to remove small skin tags. One method is chosen per tag.
A lesion is scraped with a curette and treated electrically.
It can treat carefully selected low-risk skin cancers.
It lacks the margin assessment of excision or Mohs surgery.
Type, site, size and depth determine suitability.
Skin tags are usually benign and need no treatment.
Removal helps tags that catch, bleed or irritate.
Other growths can be mistaken for skin tags.
Cutting or tying off an uncertain growth is unsafe.
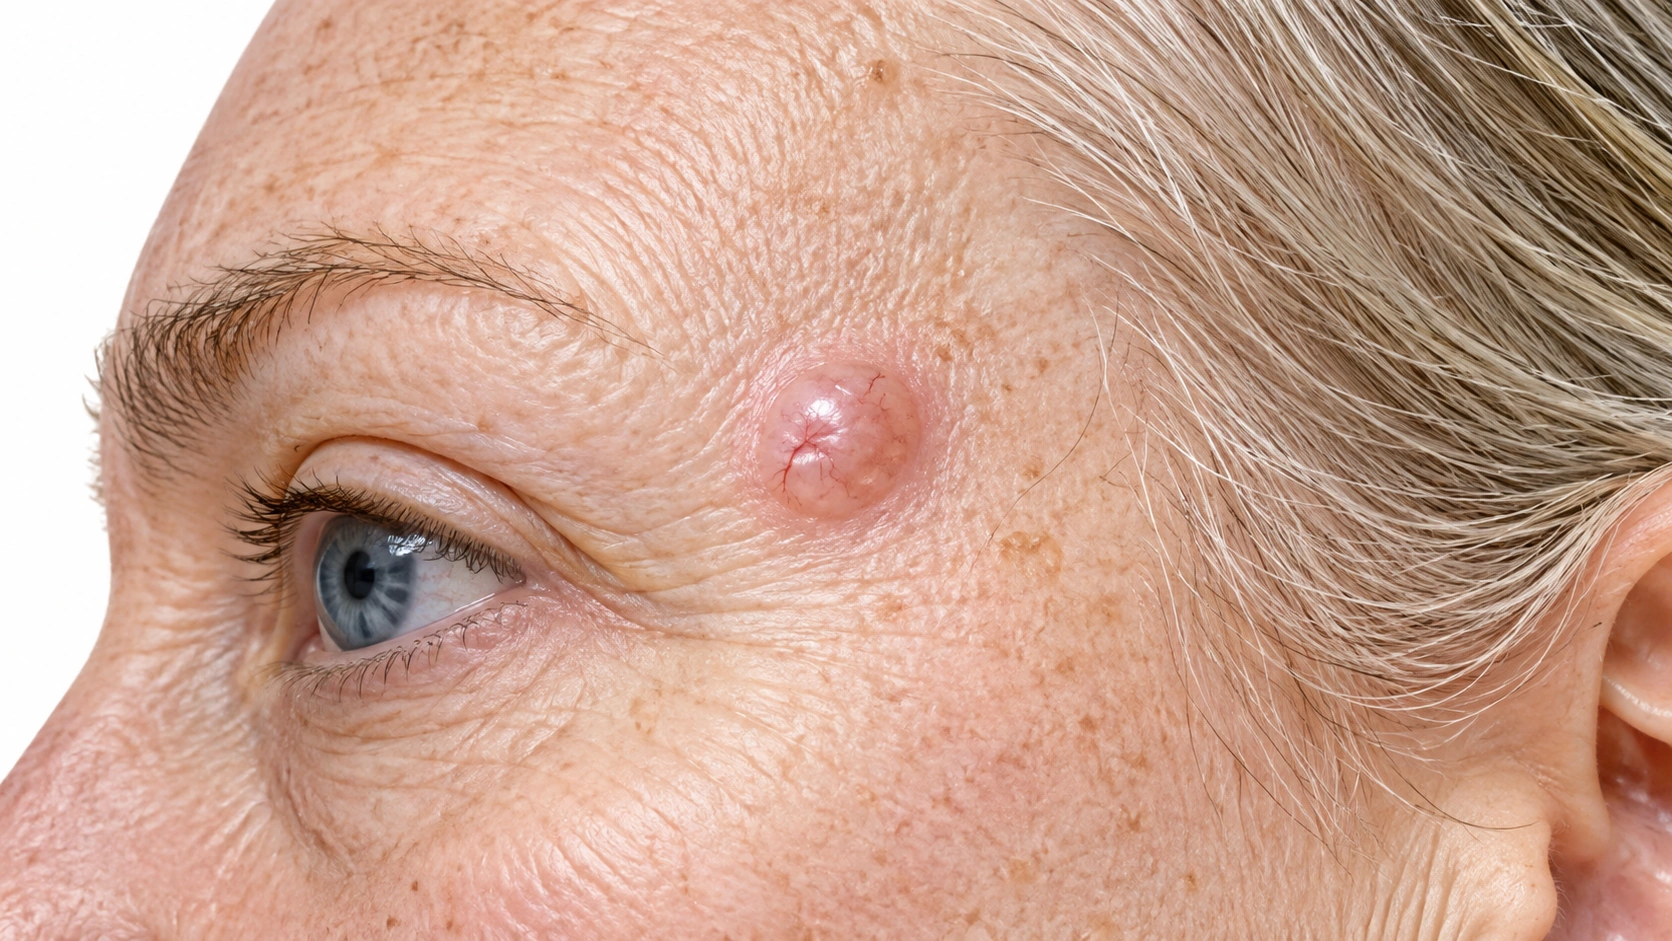
High cure rates for small tumors.
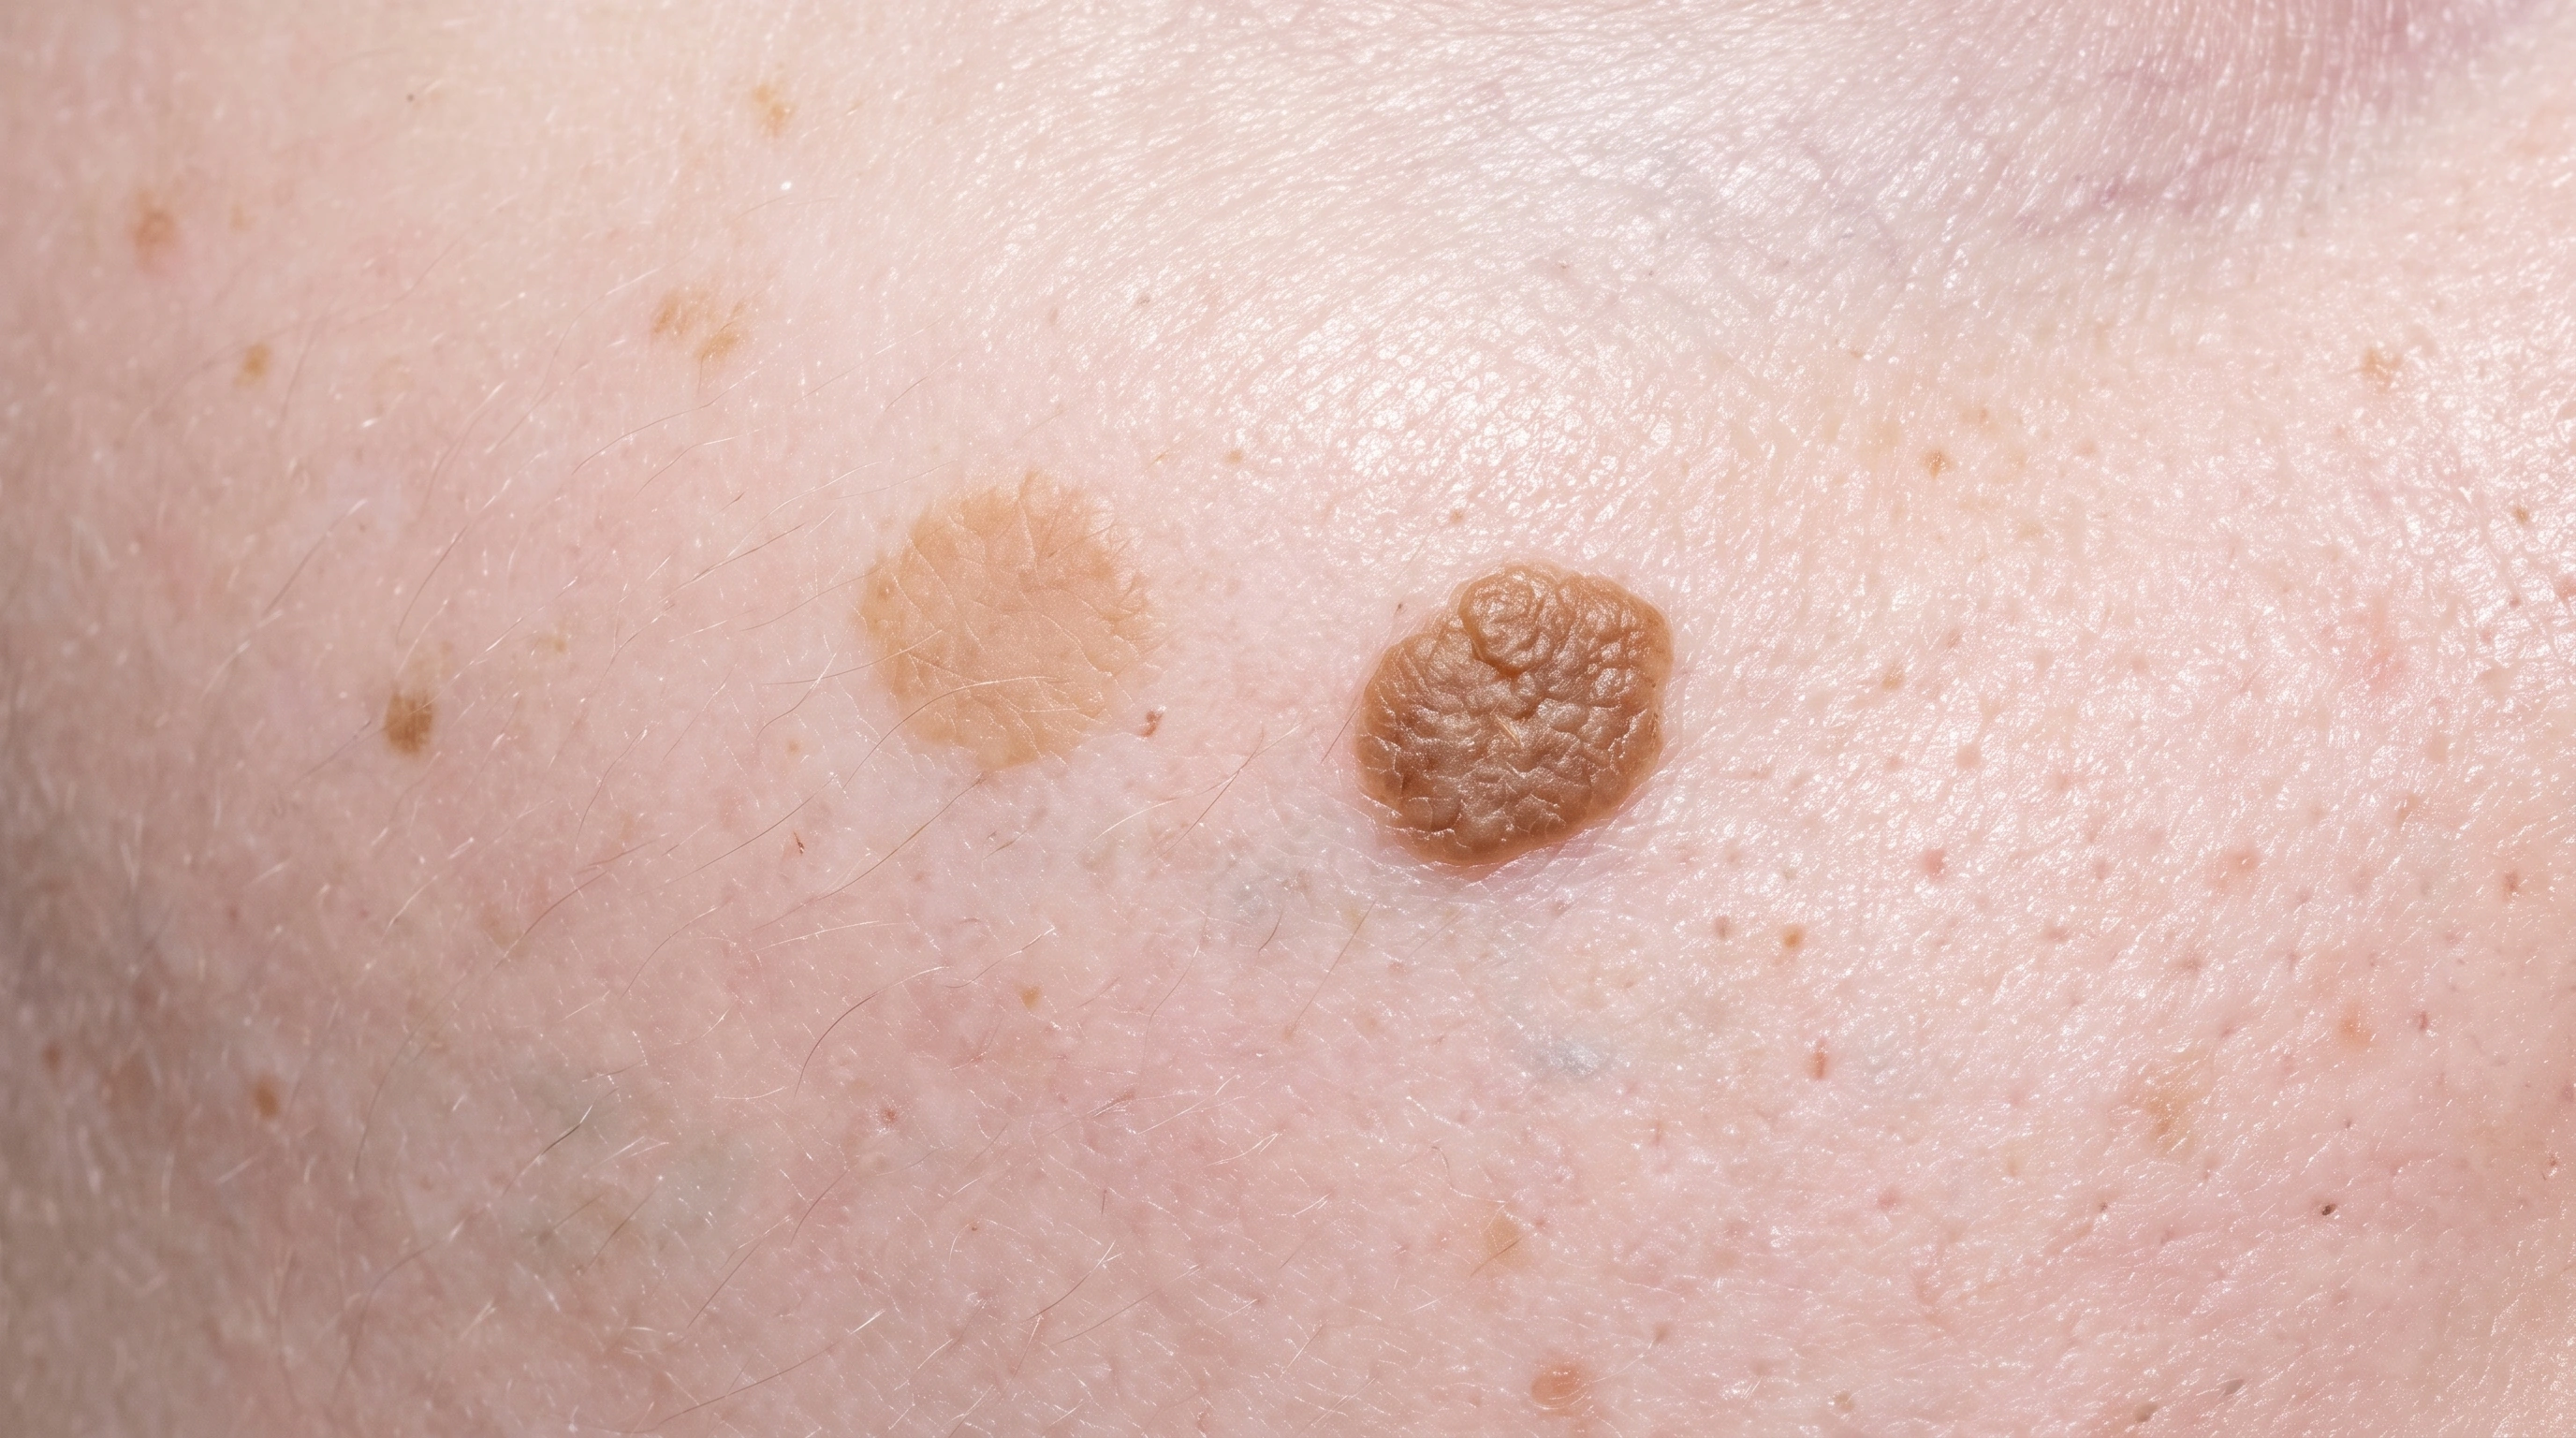
Removes growths quickly.
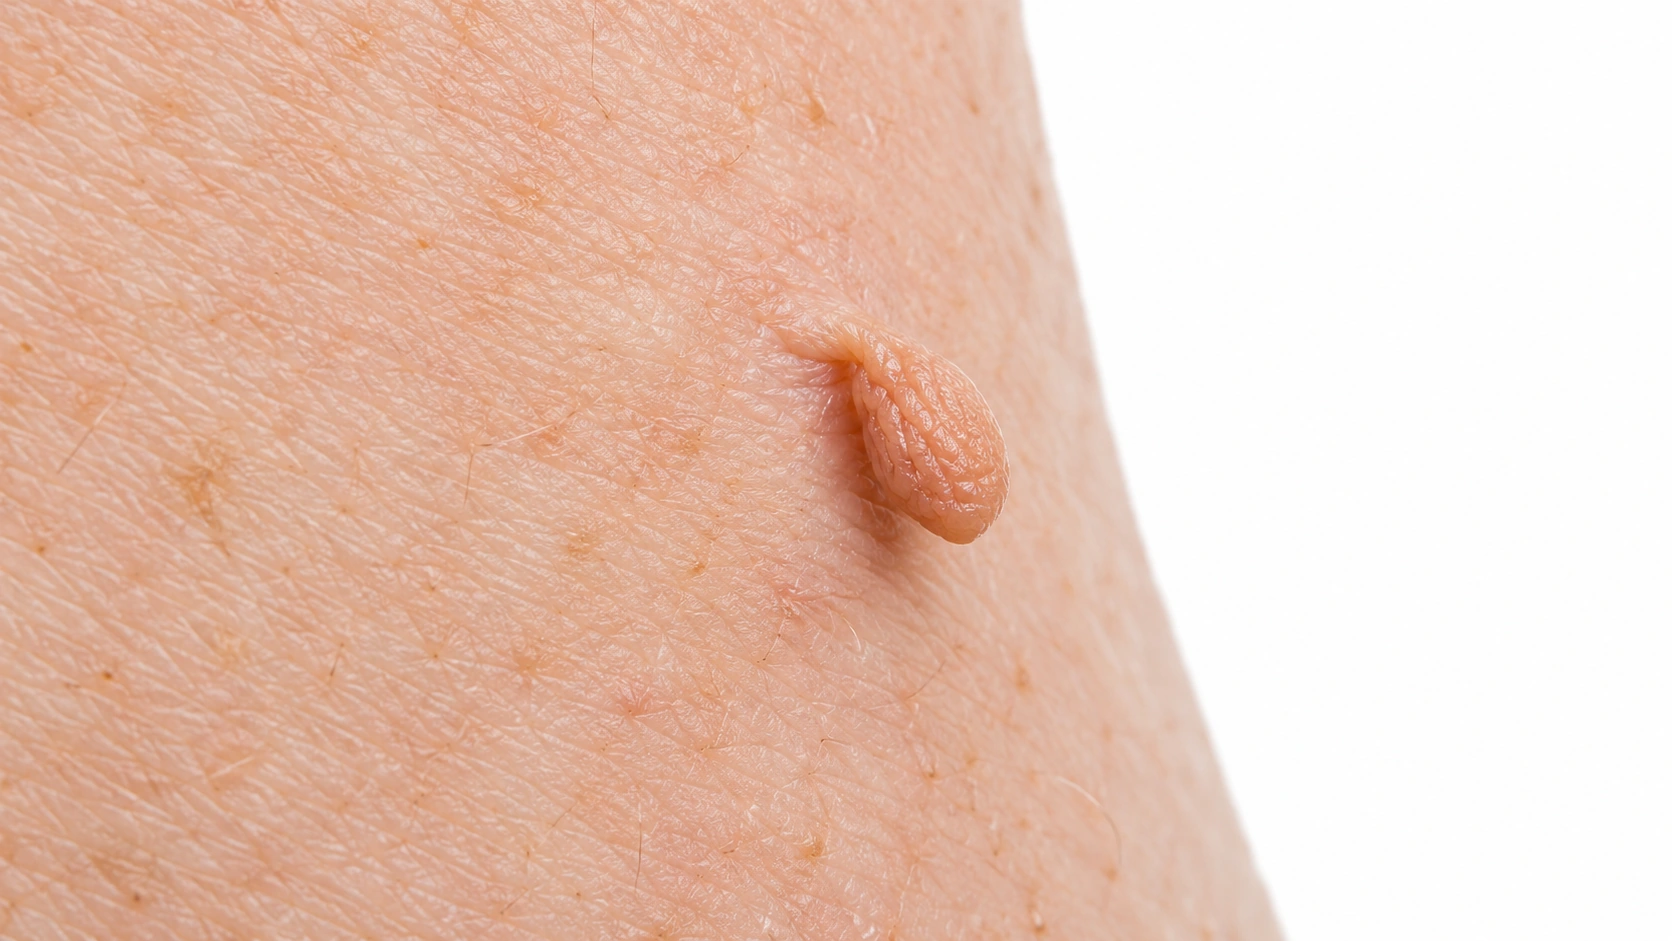
Removed in one visit.
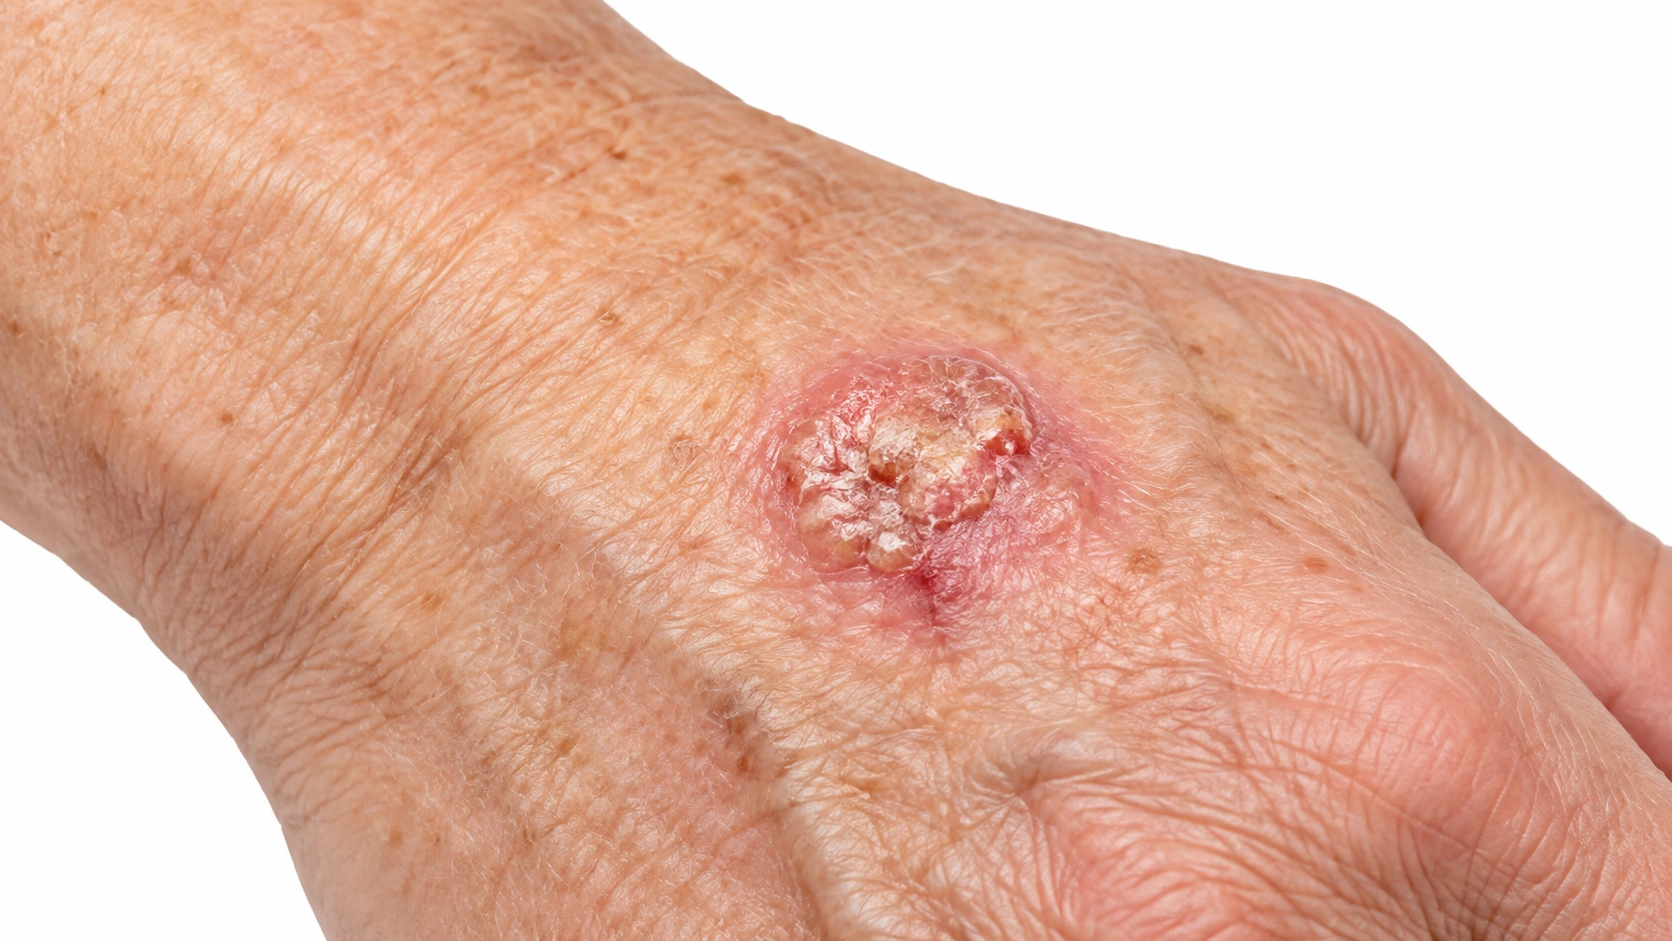
For small, low-risk tumors.
Similar methods remove them.
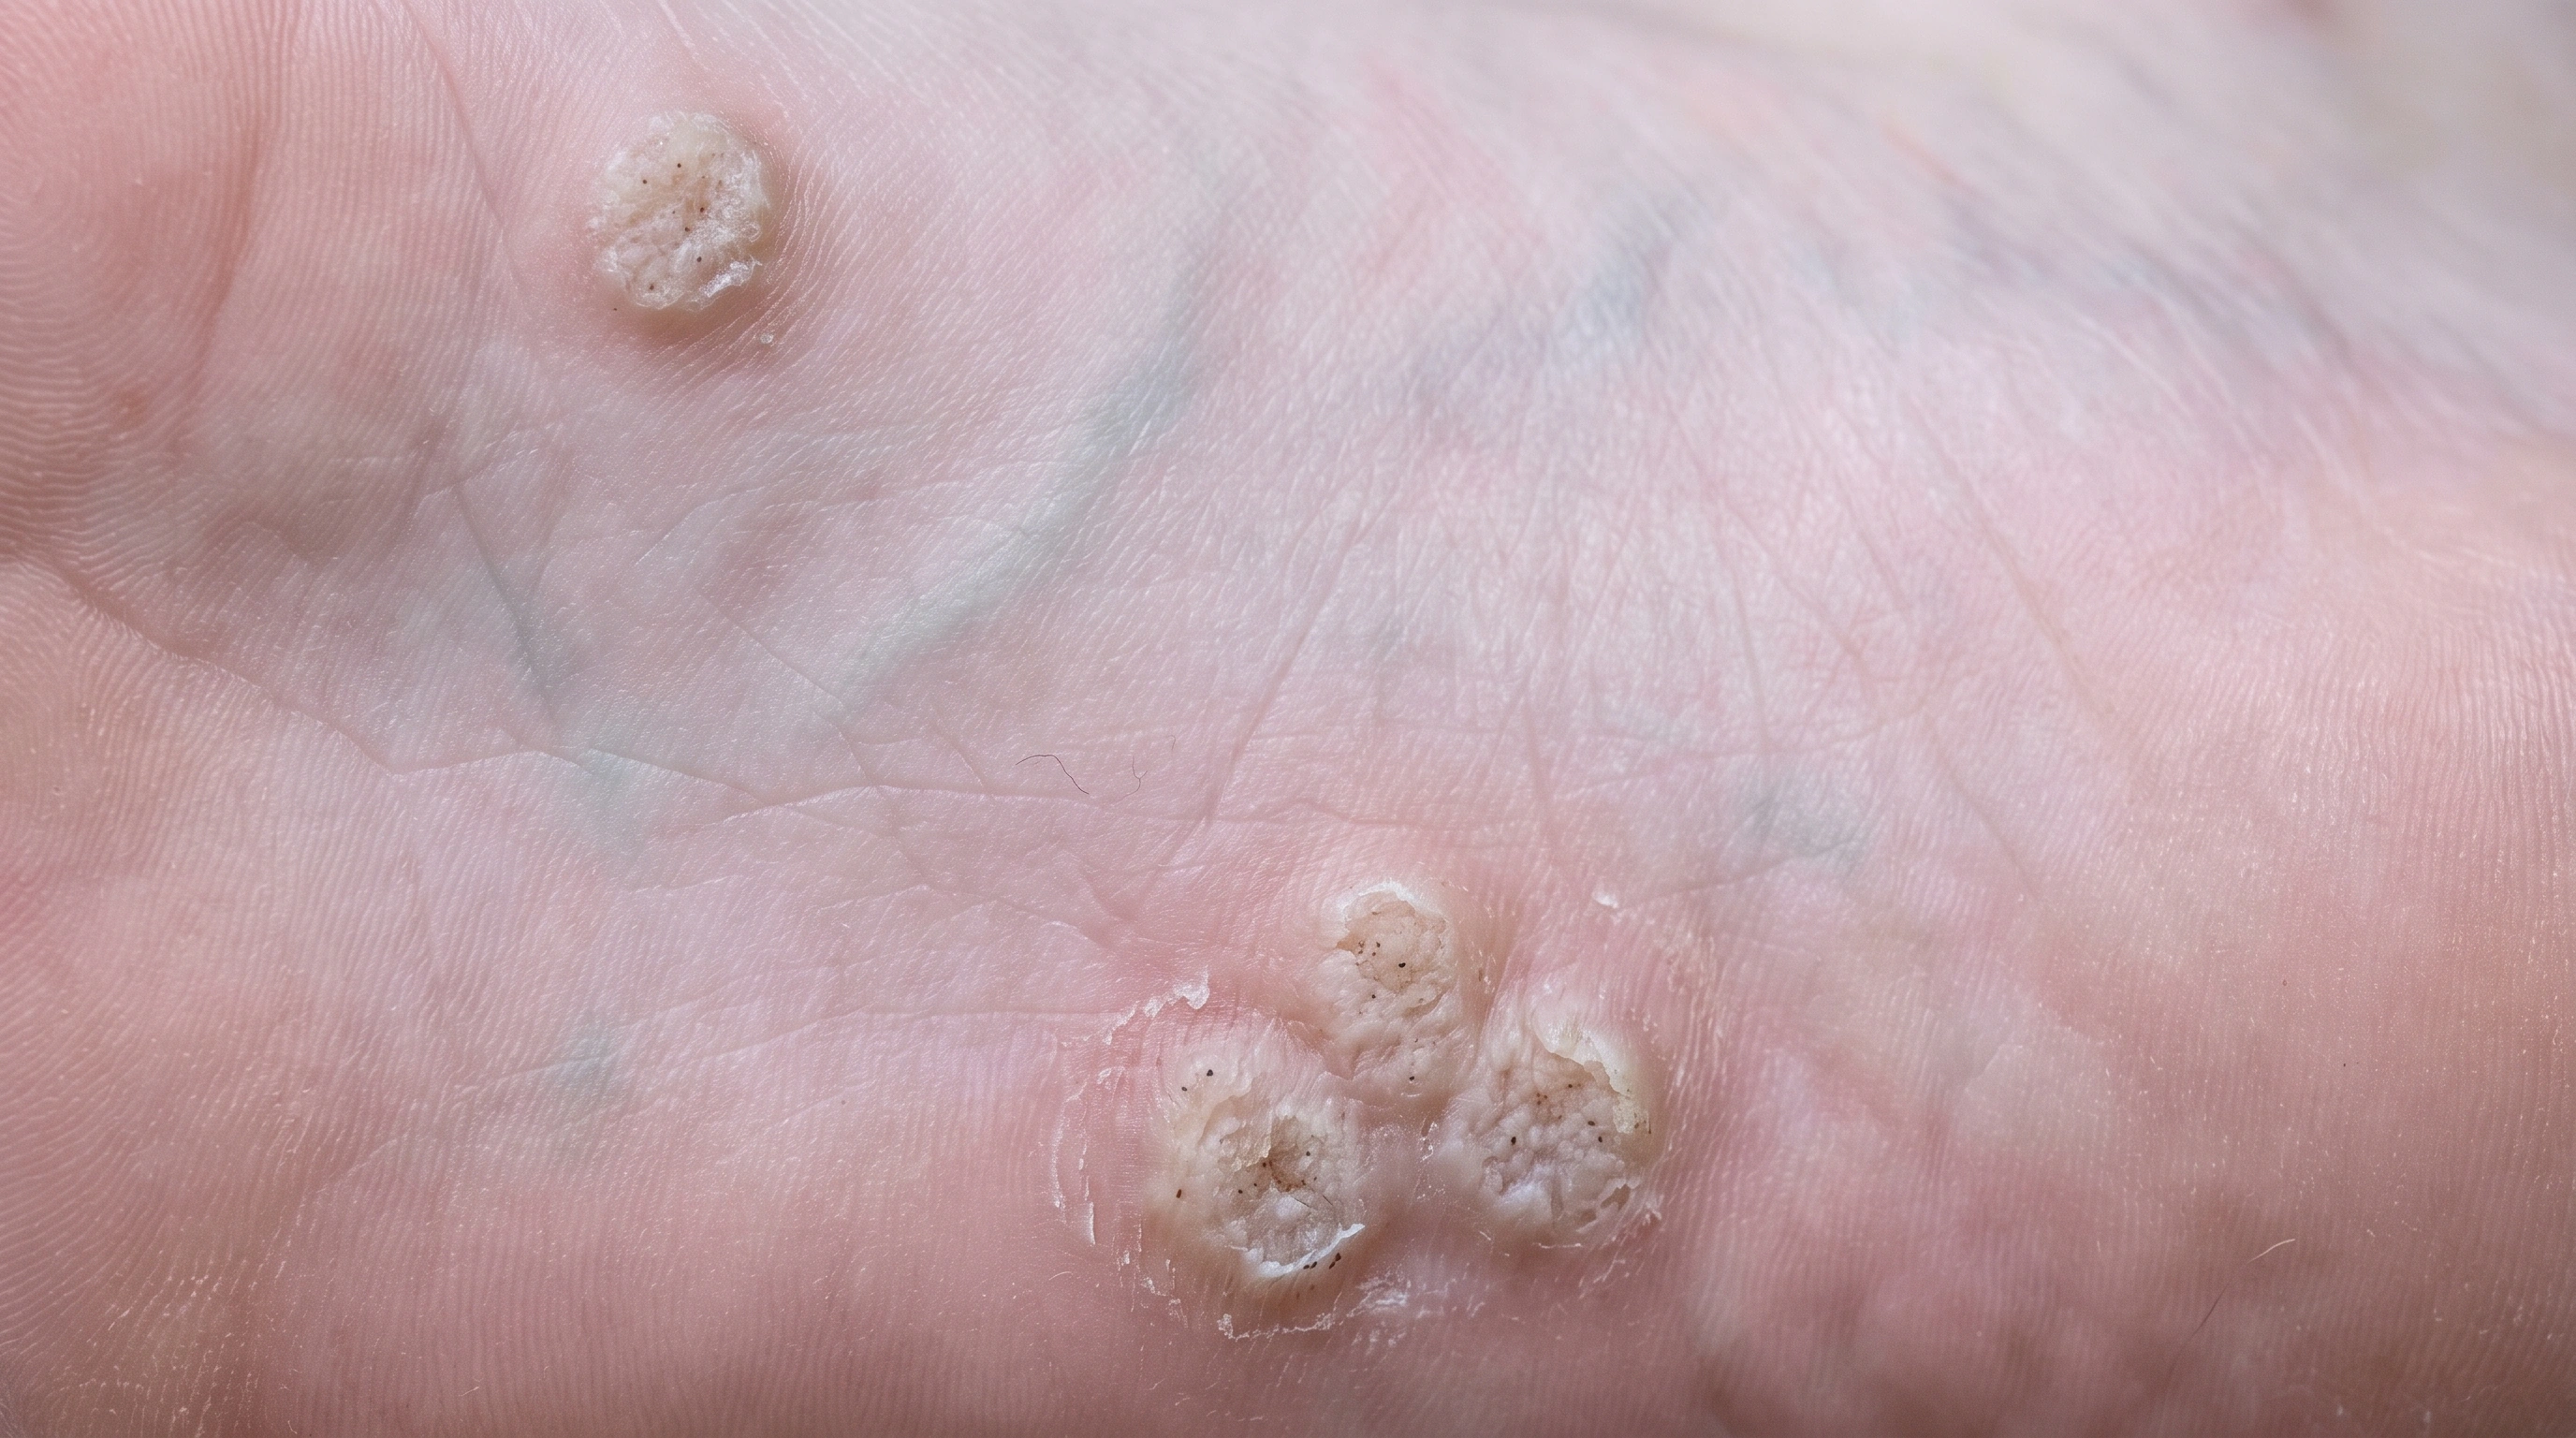
Usually treated differently.
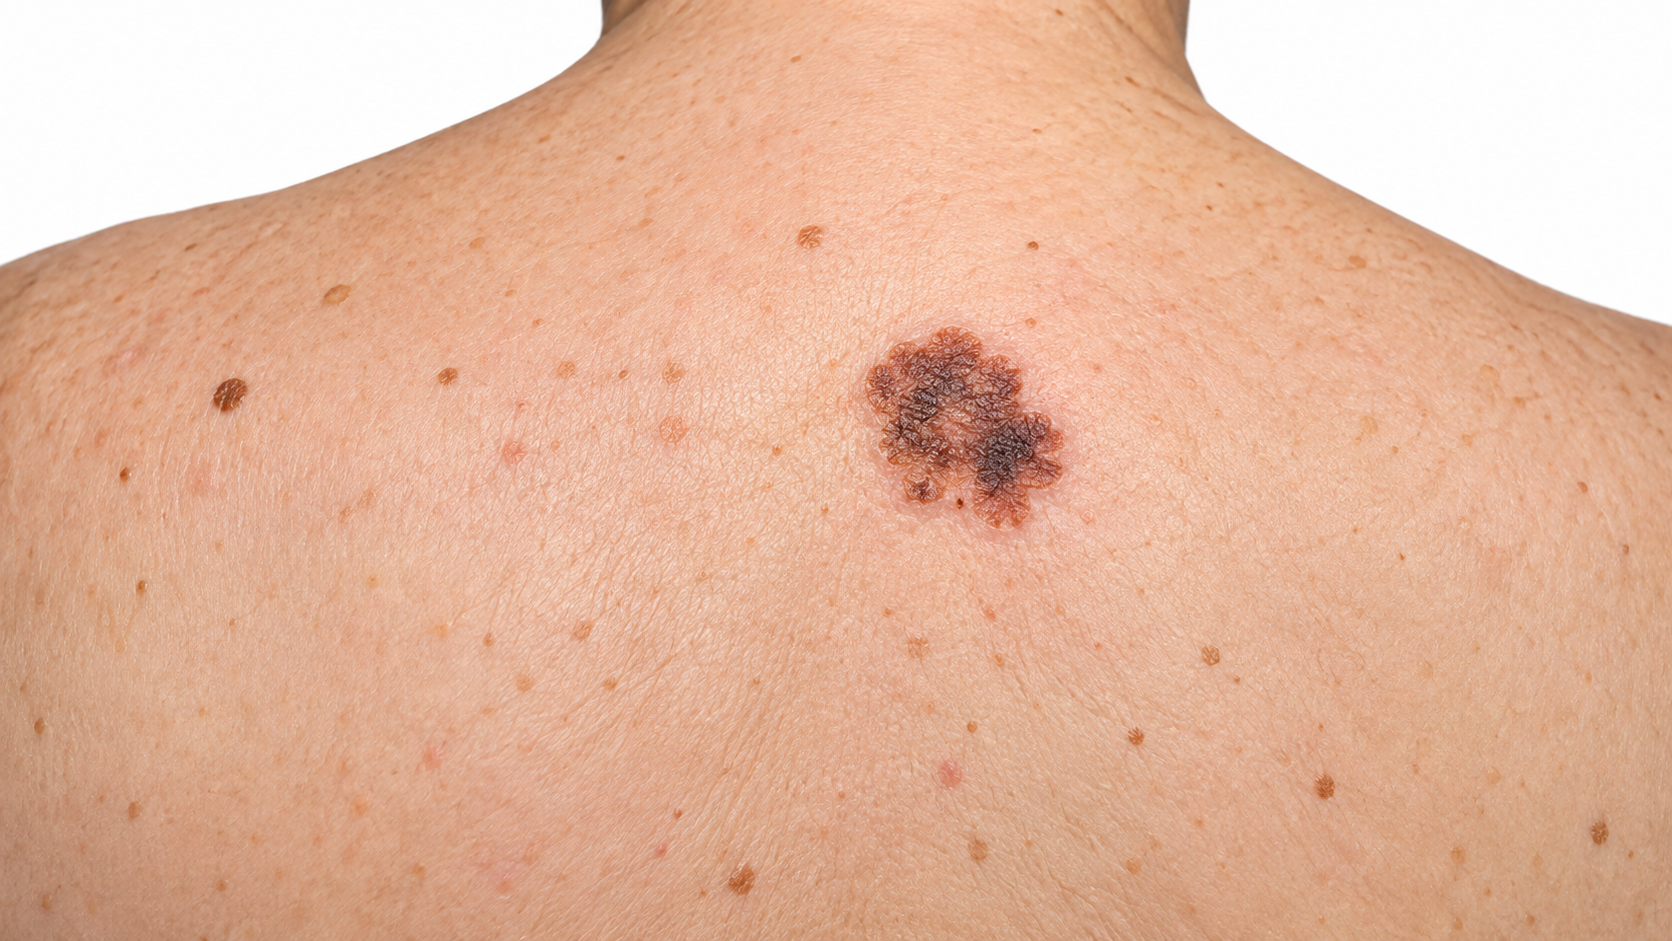
Needs excision with margins.
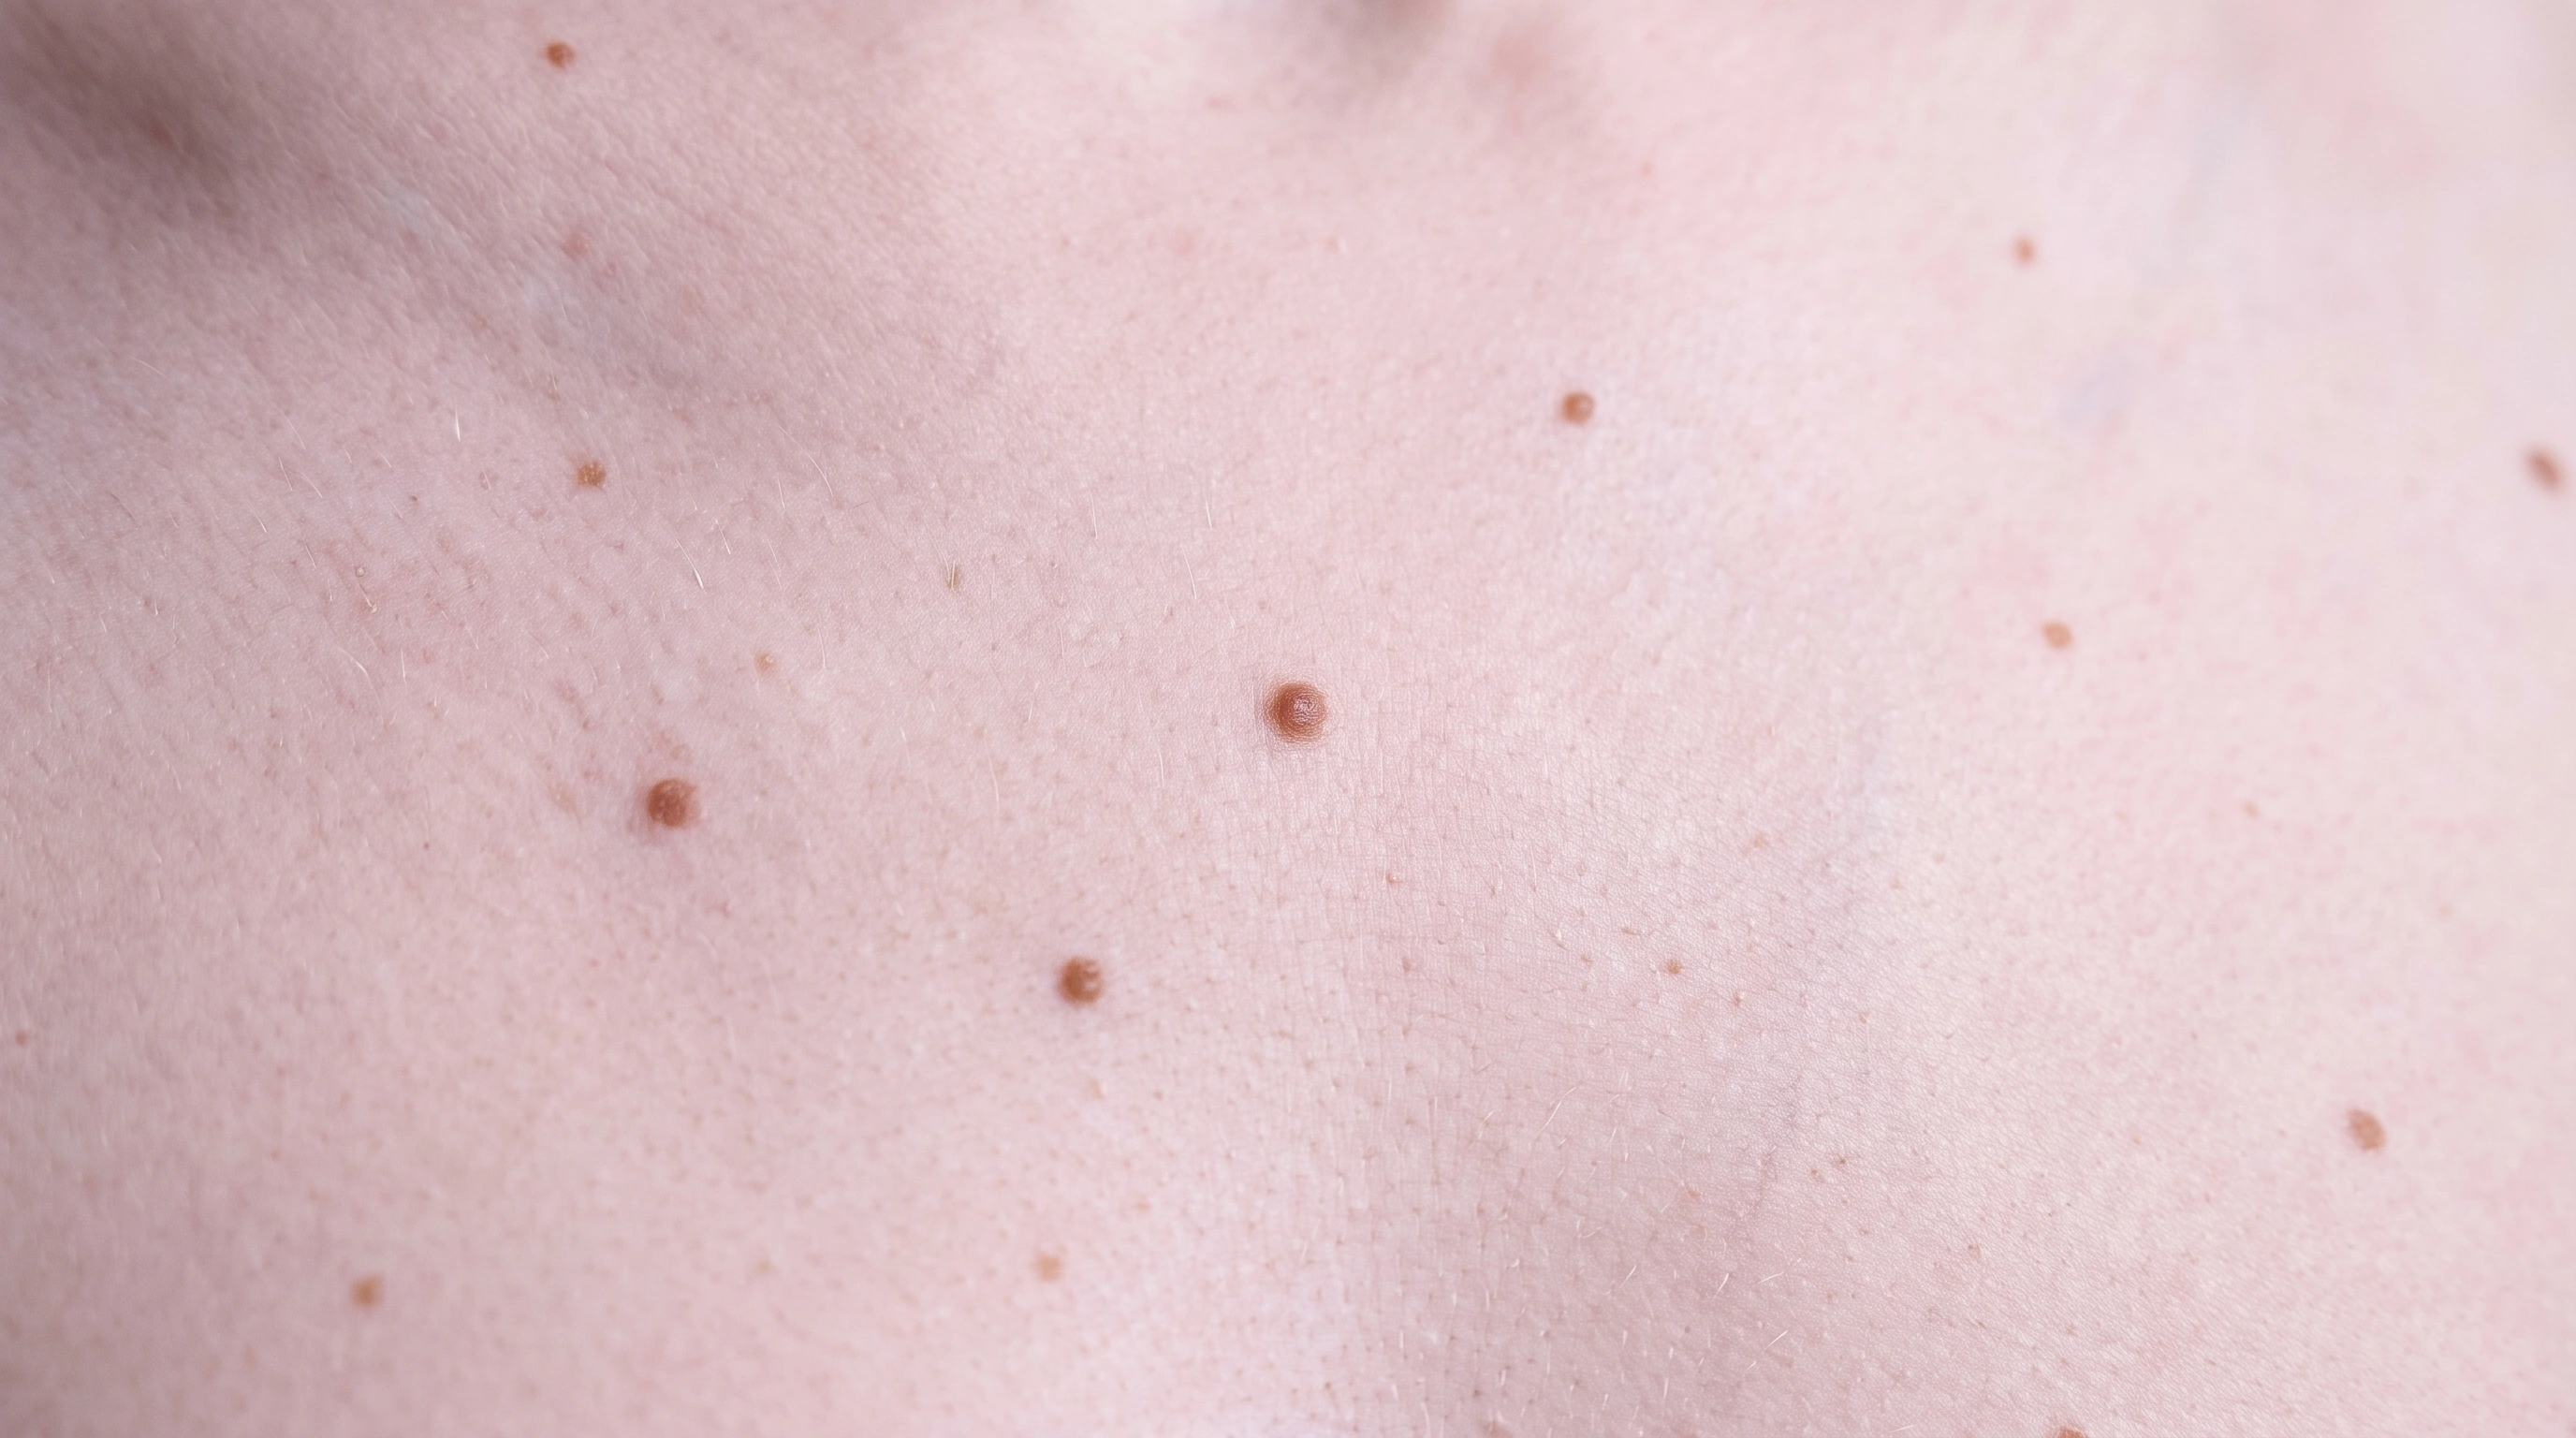
Moles need a different method and lab check.
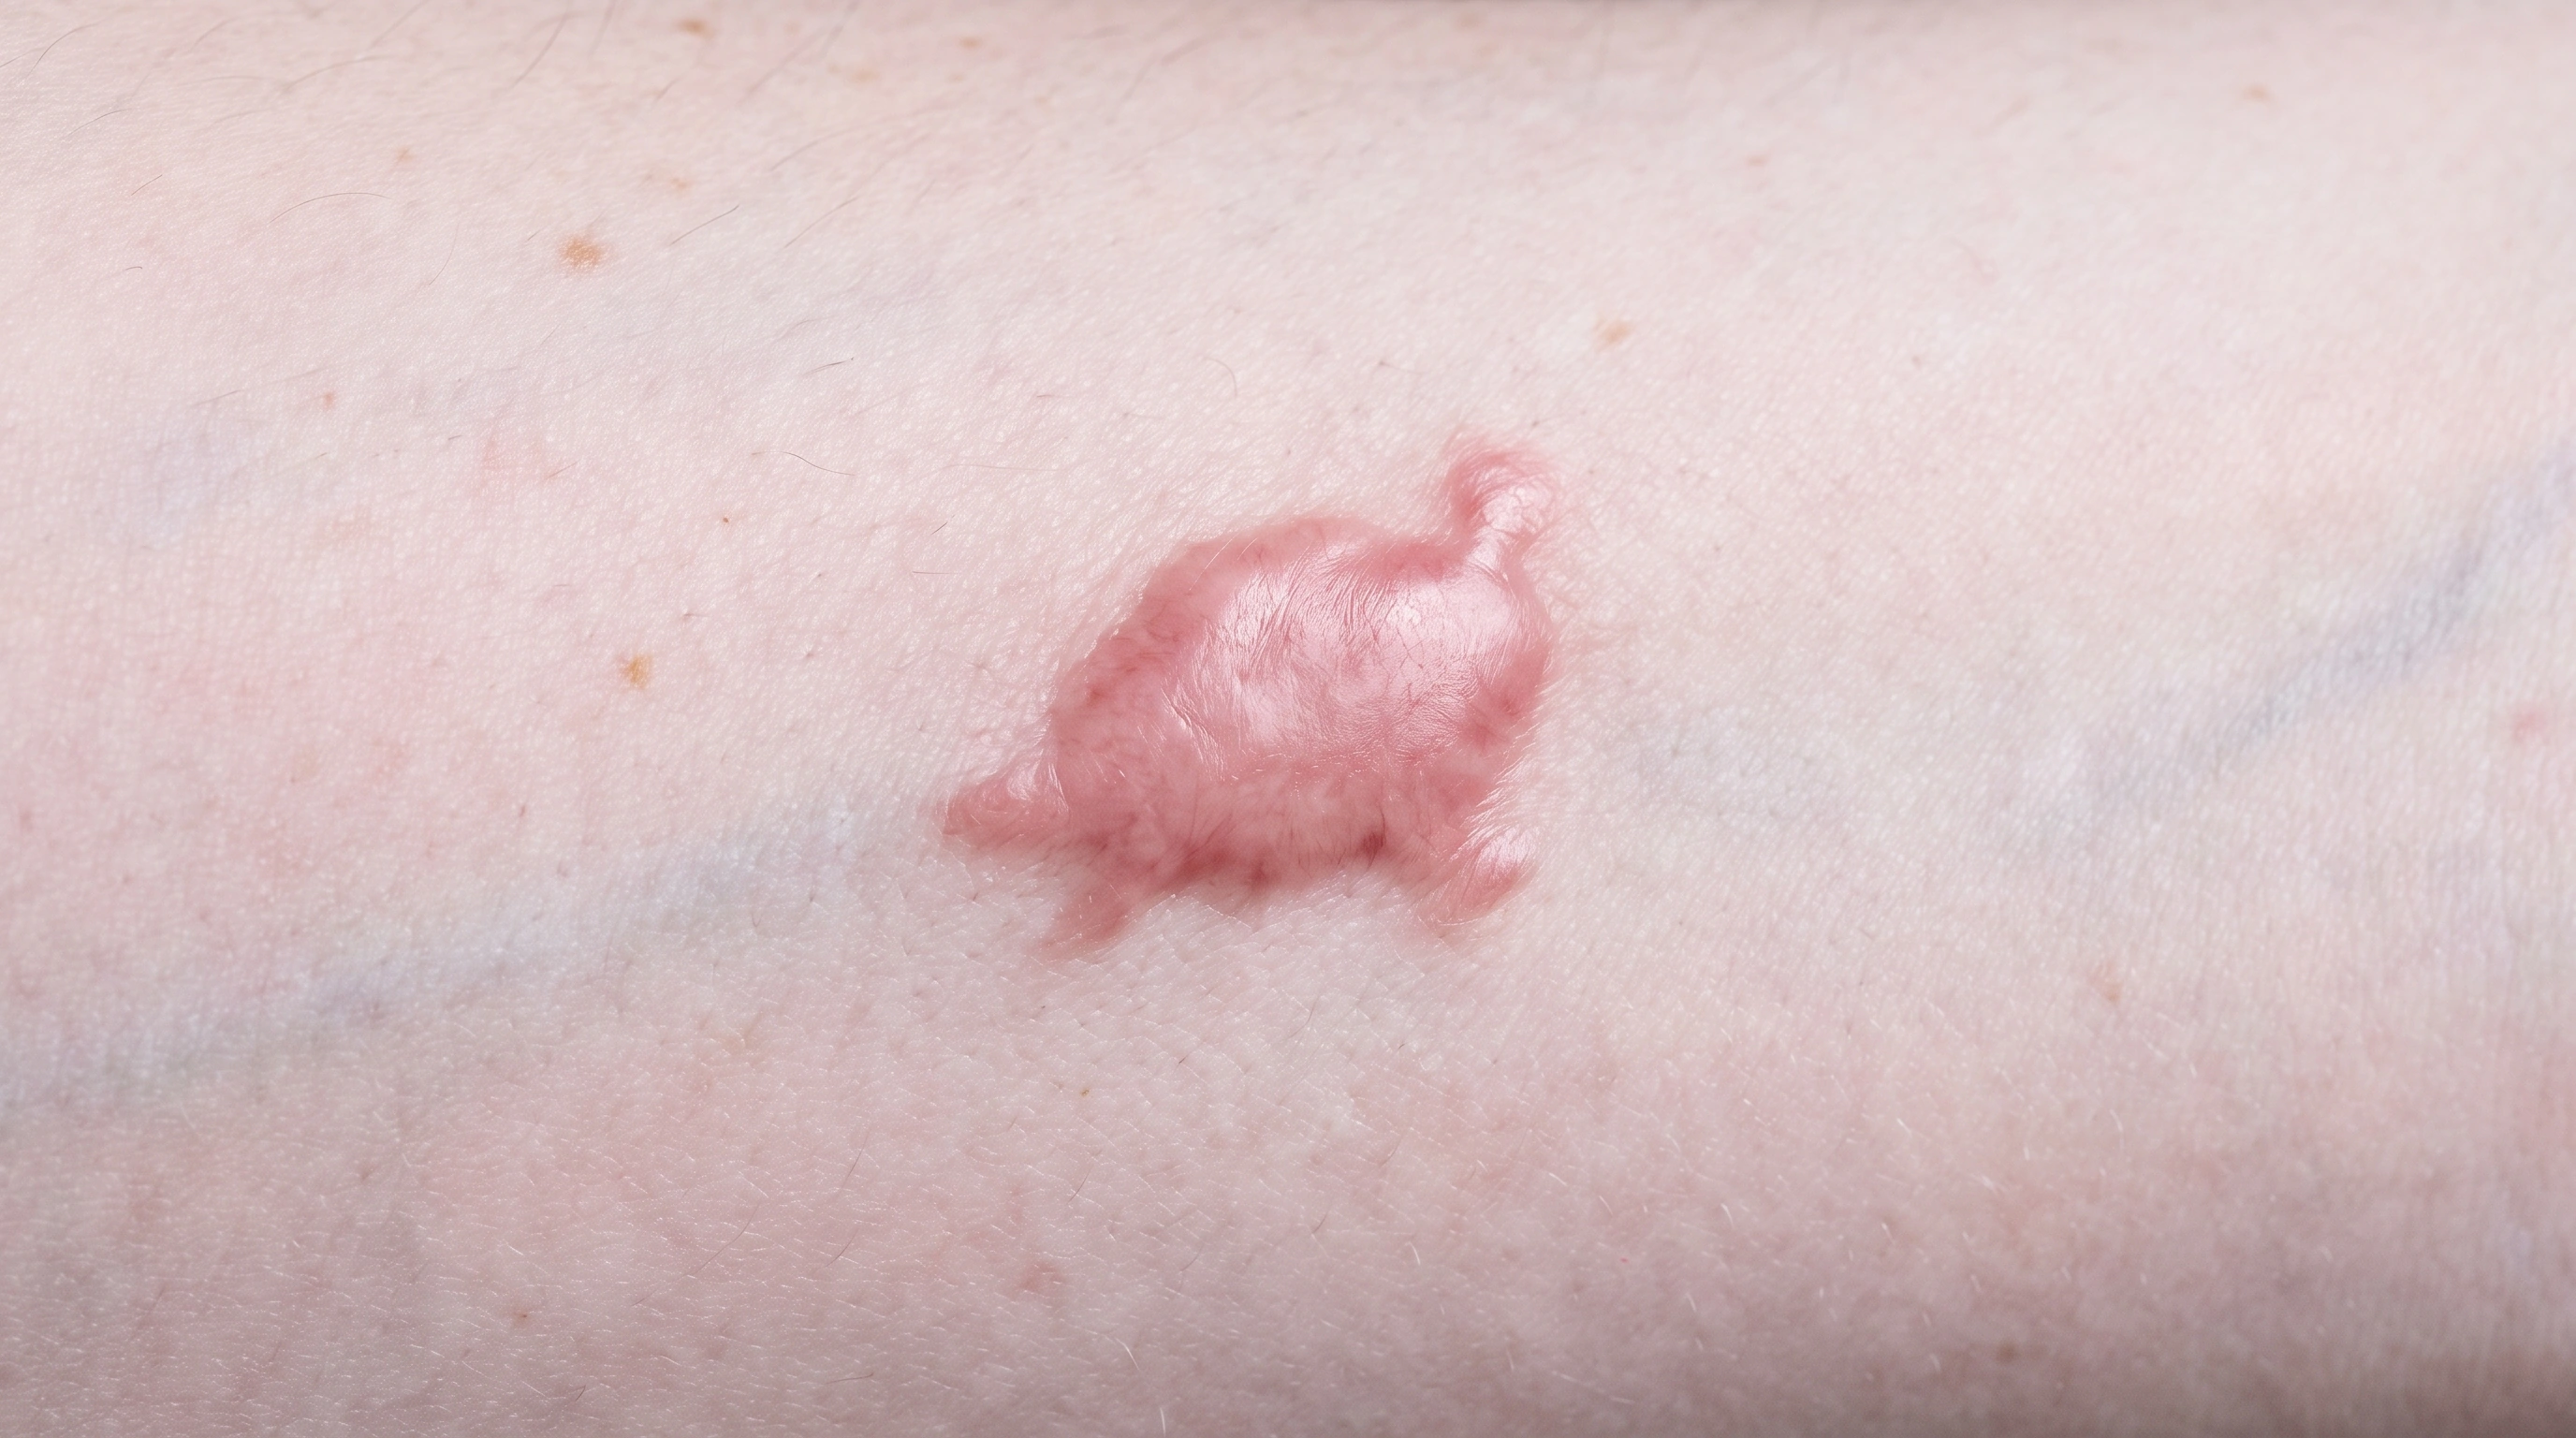
Can trigger new keloids.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Neck and underarms; groin tags are also described in the guide but are beneath the clothing in this illustration.


A curette removes tissue: A clinician scrapes away the selected lesion. Electrical treatment treats the base: Energy dries or coagulates tissue in the treatment bed. The wound heals: The open area repairs with scar tissue; follow-up remains important.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
The growth is checked: A clinician confirms the diagnosis and chooses a method. The attachment is treated: A tag may be snipped, frozen, or treated electrically. A small wound heals: The treated spot repairs; other tags can develop later.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Do not stop: Blood thinners: Aspirin, clopidogrel, warfarin, apixaban, rivaroxaban and similar are usually continued — extra oozing is easier to manage than a clot or a stroke.
Ointment and dressings: Buy plain petrolatum ointment and non-stick dressings beforehand, not on the way home.
What to wear and eat: Wear something you do not mind getting blood on.
Hair removal and clothes: No shaving, waxing or hair removal cream on the area that day.
20 to 30 min before: Numbing cream: If you were given numbing cream, apply it 20 to 30 minutes before under a small dressing, or arrive early and have it applied in the office.
The lesion is matched against the biopsy report, photographed, and consent signed.
Your provider looks at each lesion, often with a dermatoscope — a lit magnifier held against the skin — confirms which are skin tags, marks what is coming off, and says which method they are using.
The doctor scrapes with the curette, which feels like pressure and tugging, not pain.
The electric probe follows, with a faint buzz and a smell of burning. The pair is repeated two or three times; one lesion takes about 10 to 20 minutes. Nothing should feel sharp once you are numb, so say so if it does.
For snipping, the tag is lifted with forceps, cut at the stalk with fine scissors, and the pinpoint sealed with pressure, a bleeding solution or cautery.
Freezing is liquid nitrogen sprayed for a few seconds. Cautery touches a fine tip to the base, with a faint burning smell. A dozen tags run 10 to 20 minutes. Expect a sharp pinch per tag; freezing stings for a minute.
A round, shallow, raw crater slightly larger than the growth, under ointment and a dressing.
Tiny dots of blood or small scabs, sometimes a dressing on the larger ones.
Day 1 to 7: The wound weeps and the base looks yellow.
Days 1 to 3: Small scabs form on snipped and cauterized sites.
Days 5 to 14: Scabs lift off by themselves, and frozen tags darken, dry and drop off in this window.
Weeks 2 to 6: The crater shrinks and the base turns pink.
Weeks 2 to 12: A pink, pale or darker spot is left where each tag was, and most fade over weeks to months.
Month 2 to 12: The scar starts pink and firm, then flattens and pales over roughly a year.
Immediately
Immediately
90–95% cure for suitable cancers
Permanent; new tags can form
This is the least expensive way to treat a skin cancer surgically.
Offices commonly charge a set visit fee covering several tags, or a per-lesion price with a minimum, and the per-tag cost drops as the number goes up.
In the US it is billed as a destruction procedure, priced by lesion size and body site, and generally covered when it treats a diagnosed skin cancer.
In the US, skin tag removal is usually self-pay because it counts as cosmetic.
The numbing injection stings for under a minute. After that you feel pressure and tugging, not pain. Afterward the site is sore rather than painful, and acetaminophen is enough.
There is no intact specimen to check — the tumor is scraped away in fragments and the base burned. The method relies on the operator feeling soft tumor against firm normal tissue, which is reliable for shallow, clearly bordered tumors and unreliable for others.
A round, flat disc, usually slightly wider than the original spot and lighter than the skin around it. Some are a little sunken, some raised. Pink at first, paling over about a year. It is permanent.
About 3 to 6 weeks on the face, trunk and arms. On the lower leg it is slower, sometimes two to three months, particularly in older adults or with diabetes or poor circulation.
Sometimes, for a small superficial tumor on the cheek or forehead. Generally not for the nose, eyelids, ears, lips or the creases around them, where recurrence is higher and there is less spare skin. Ask why one is recommended over the other for your tumor.
For a well-selected, small, low-risk tumor, cure at 5 years is commonly quoted around 95 percent. That falls when the method is used on tumors it was not meant for — aggressive subtypes, recurrent tumors, unclear borders, high-risk facial sites.
No — they are harmless growths of ordinary skin. What makes them worth showing to someone is that other things can look like them, so a lesion that is dark, firm, growing, bleeding or changing should be examined rather than assumed.
Often you cannot, and that is the honest answer. Skin tags are soft, skin-colored and hang on a narrow stalk in areas that rub, but moles, warts and seborrheic keratoses can be raised in the same places. A clinician with a dermatoscope can usually tell in seconds.
No. There is no evidence that removal encourages new ones. New tags appear because the tendency continues, and they show up in the same friction areas over the years.
Each tag is a brief sharp pinch, and larger ones are numbed first. A small pink, pale or darker spot at each site is normal and usually fades over weeks to months. Freezing is most likely to leave a lasting pale dot, particularly on deeper skin tones.
You can buy kits, and the honest advice is not to. Nothing at home examines the lesion first, freezing kits are too weak and blister normal skin, acid pastes and cauterizing pens burn a permanent mark, and floss ligation half-works often enough to be miserable. In an office it takes seconds and someone checks what it is.
Usually not, because removal for appearance is cosmetic. It is sometimes covered when tags repeatedly bleed, get inflamed or catch on clothing, and that needs documenting. Ask the office to check beforehand.