Vitiligo
Vitiligo is a condition where the immune system destroys the cells that give skin its color, leaving smooth white patches. It is not painful, not contagious and not caused by anything you did, and treatment can bring color back to many patches if it is given long enough.


Key facts
Vitiligo at a glance.
Typical signs
Smooth, depigmented patches
Common locations
Face, hands, folds
Expected course
Unpredictable; repigmentation possible
Treatment options
Topicals, light therapy or camouflage
What is it?
Top things to know about Vitiligo
- It causes loss of pigment. Defined white patches form when melanocytes are lost or stop working.
- It is often autoimmune. Nonsegmental vitiligo commonly involves autoimmune mechanisms.
- Hair can turn white. White hairs may grow within a patch.
- Its impact is real. The emotional effect can be significant regardless of how much skin is involved.
What it looks like
What Vitiligo looks like
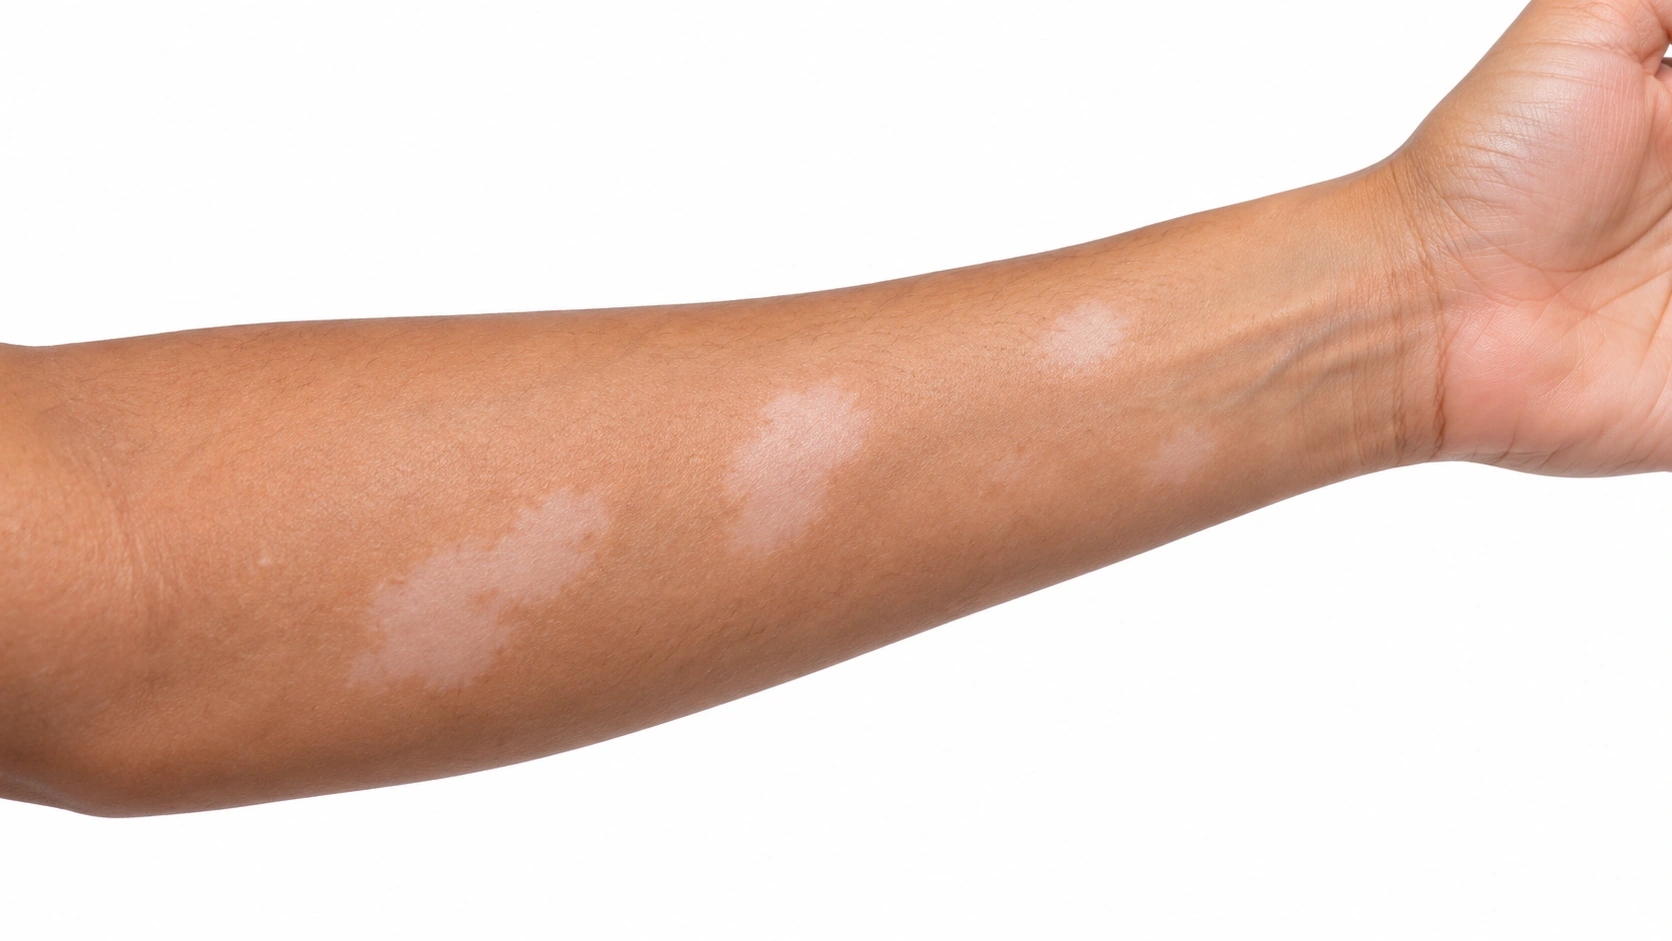
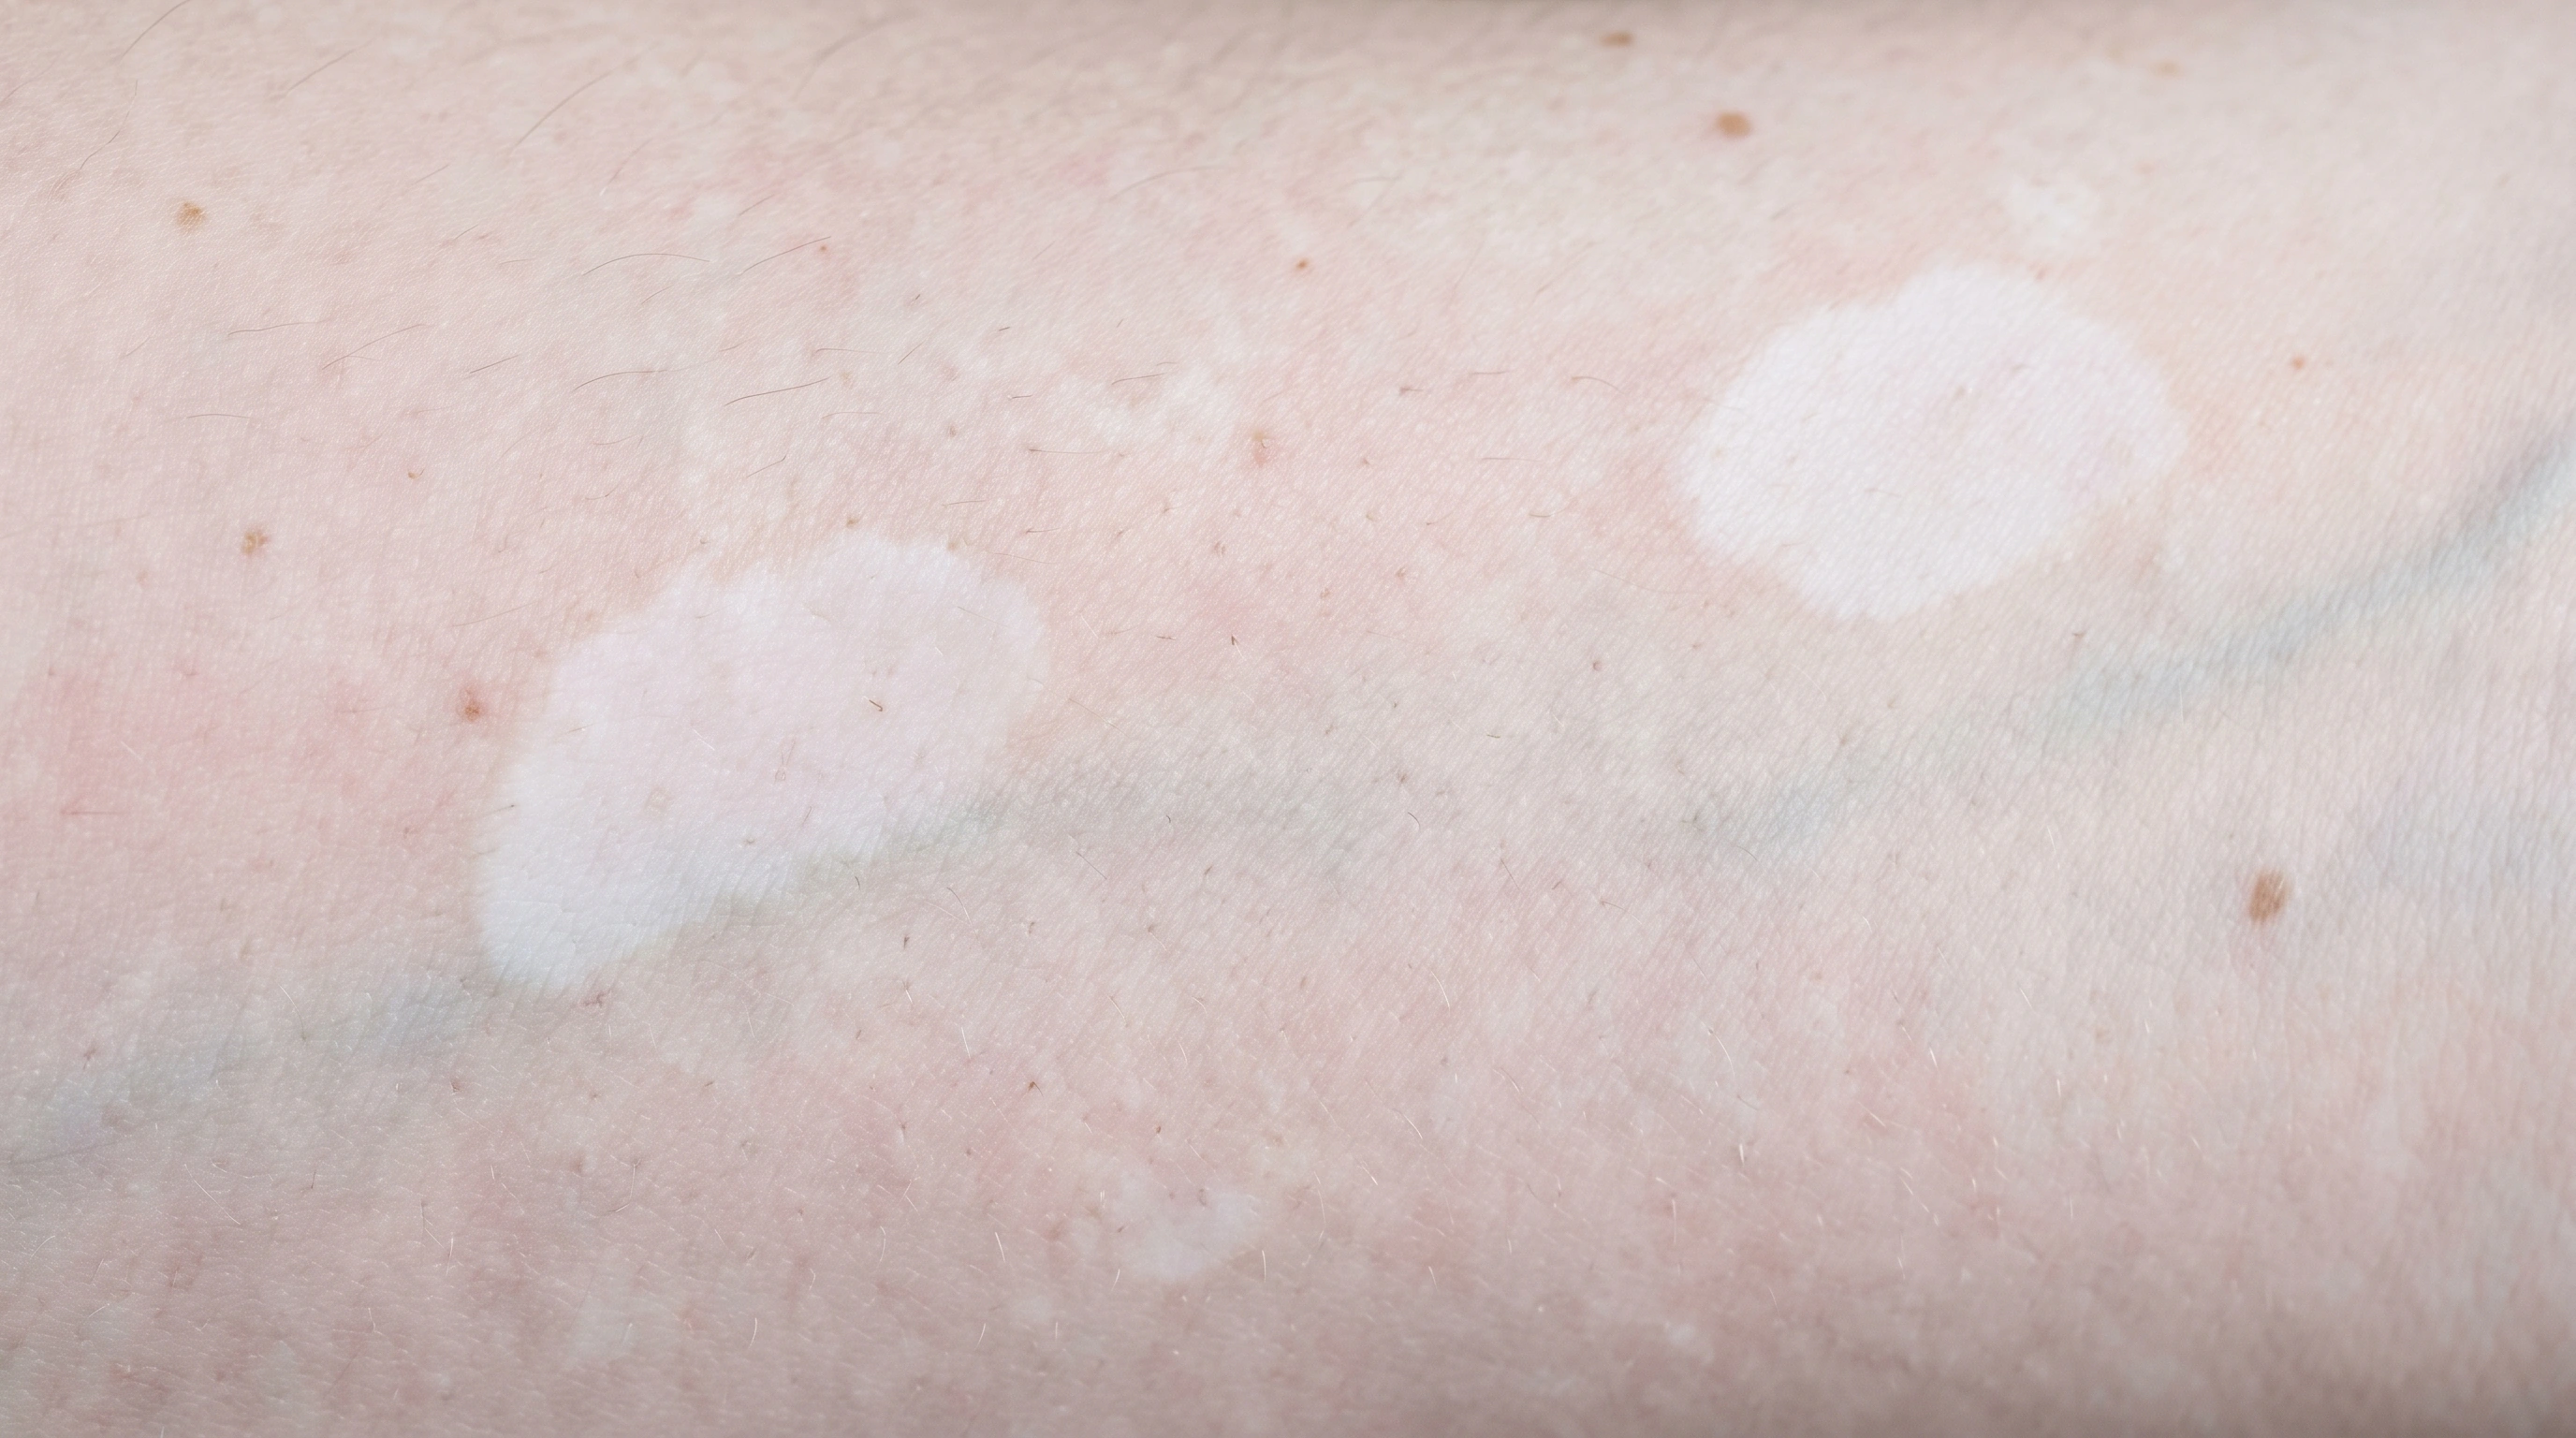
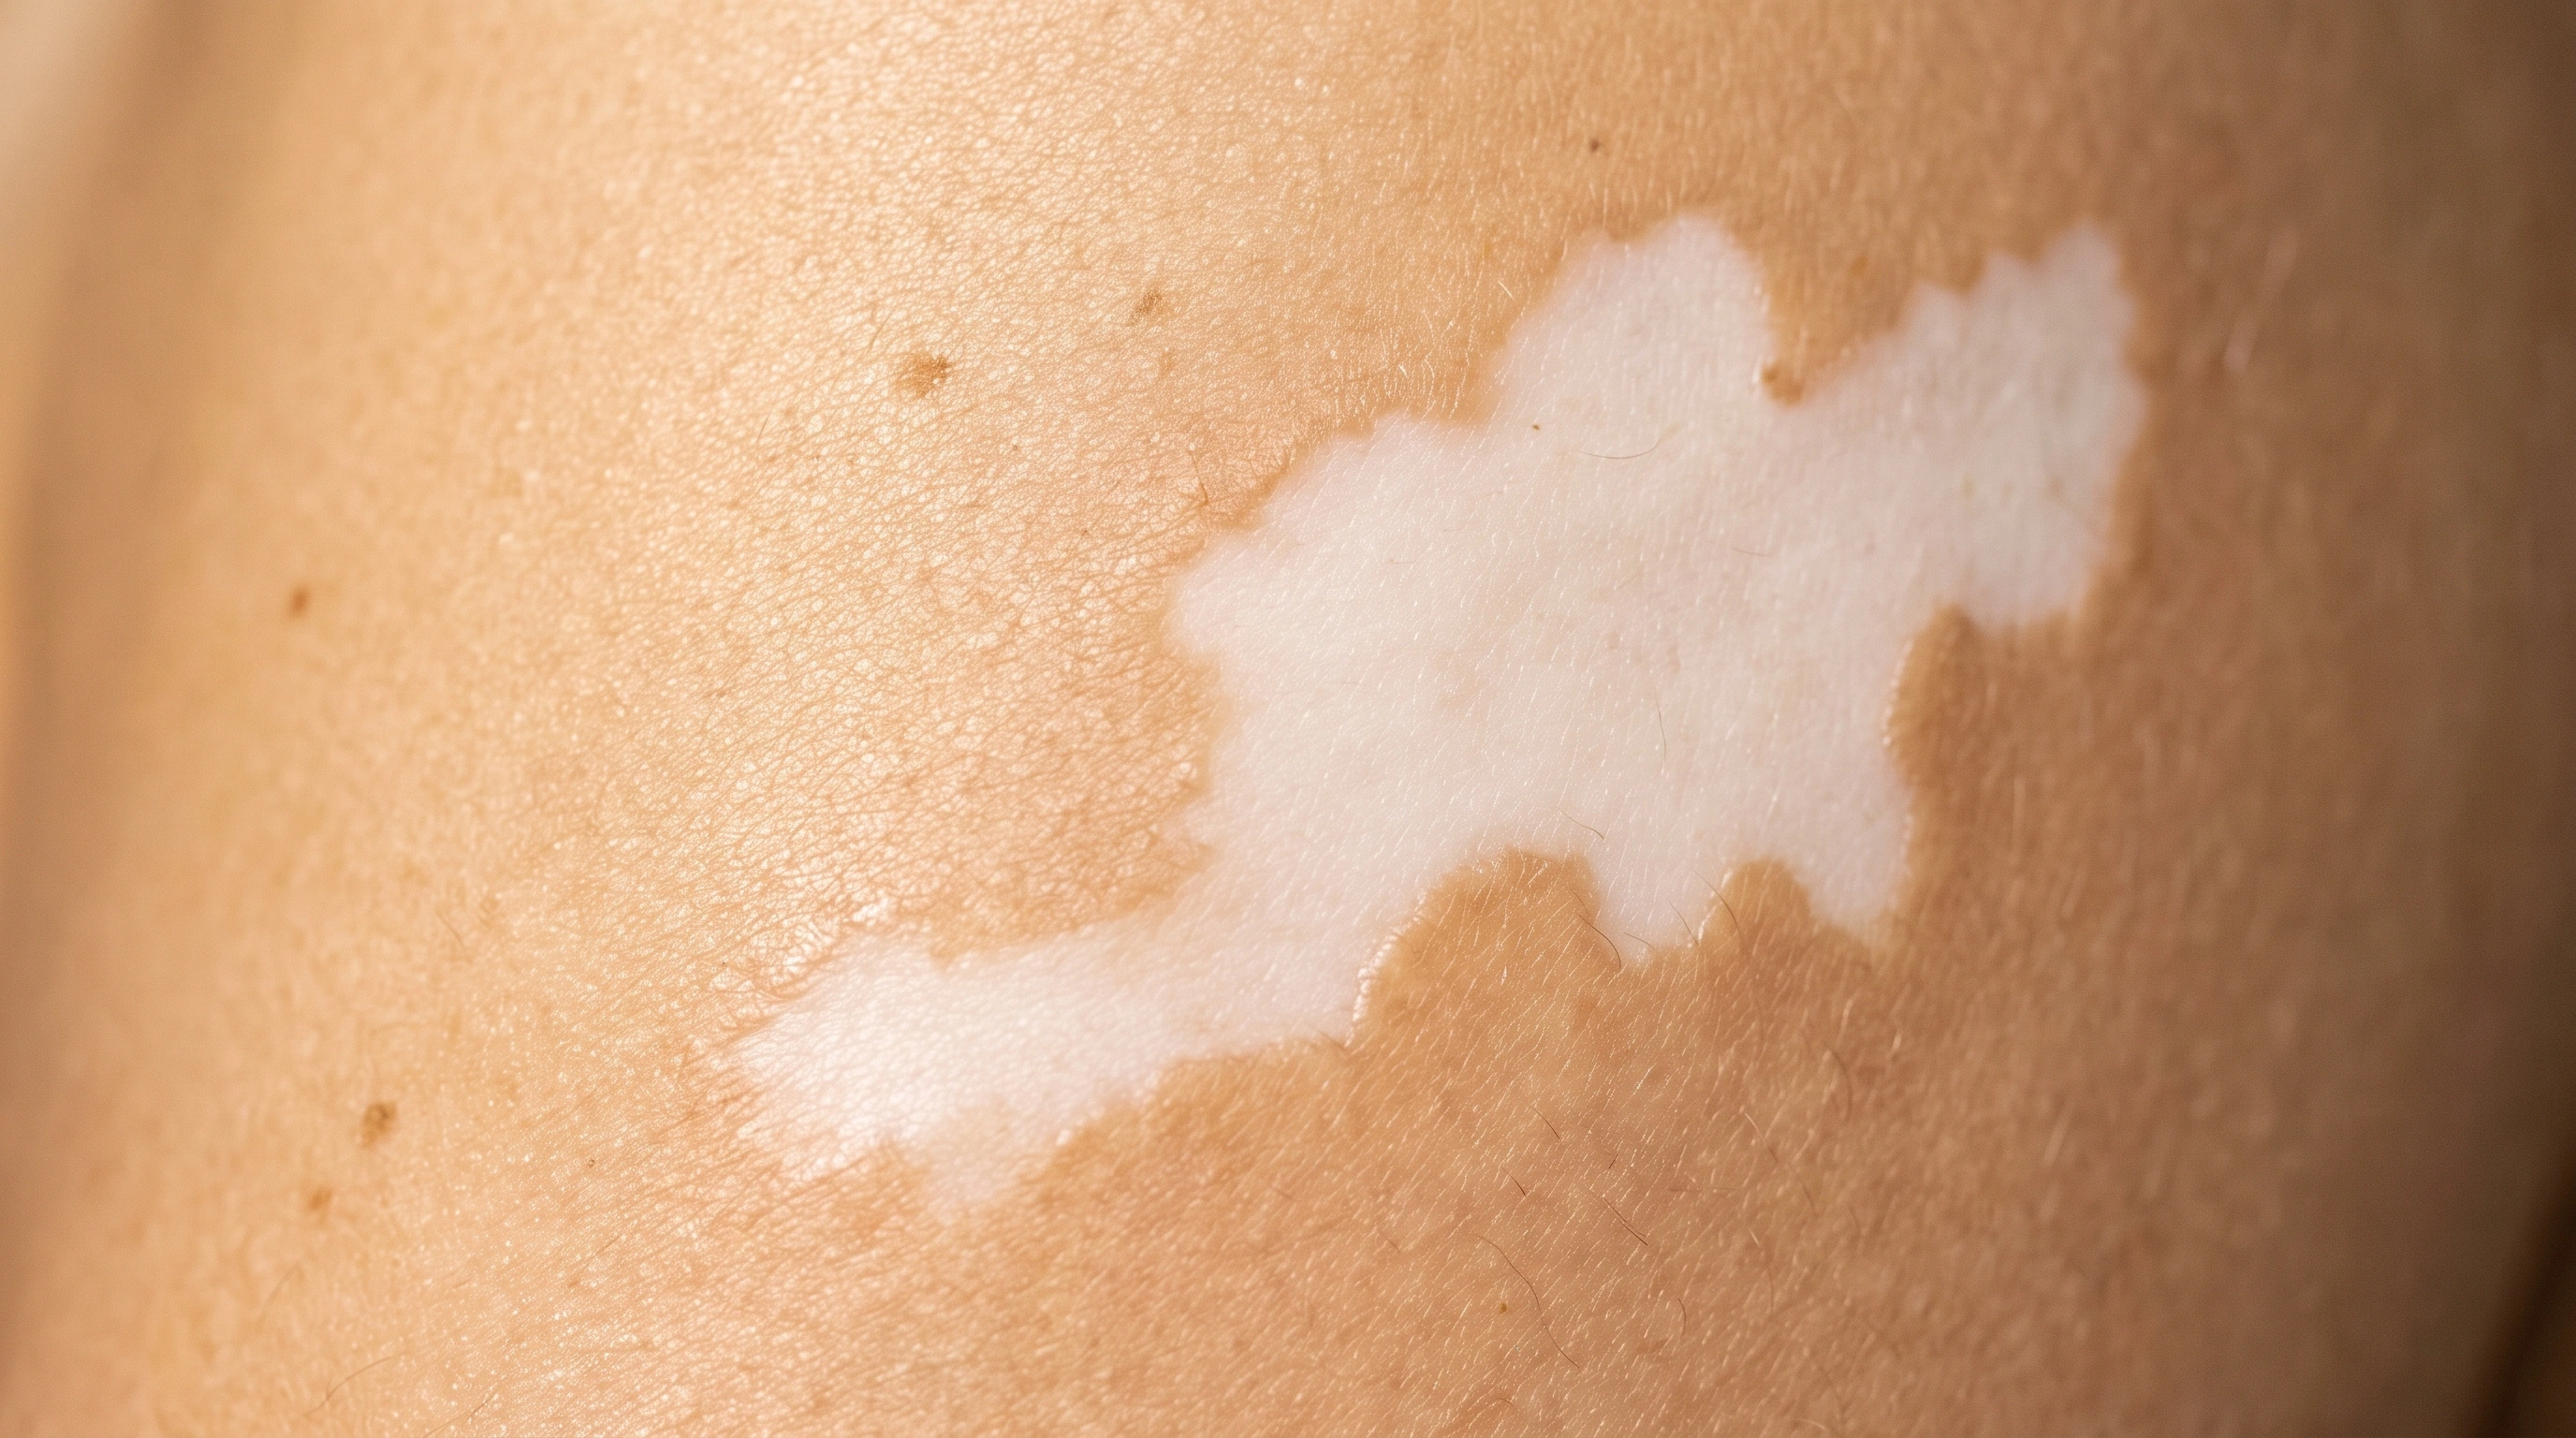
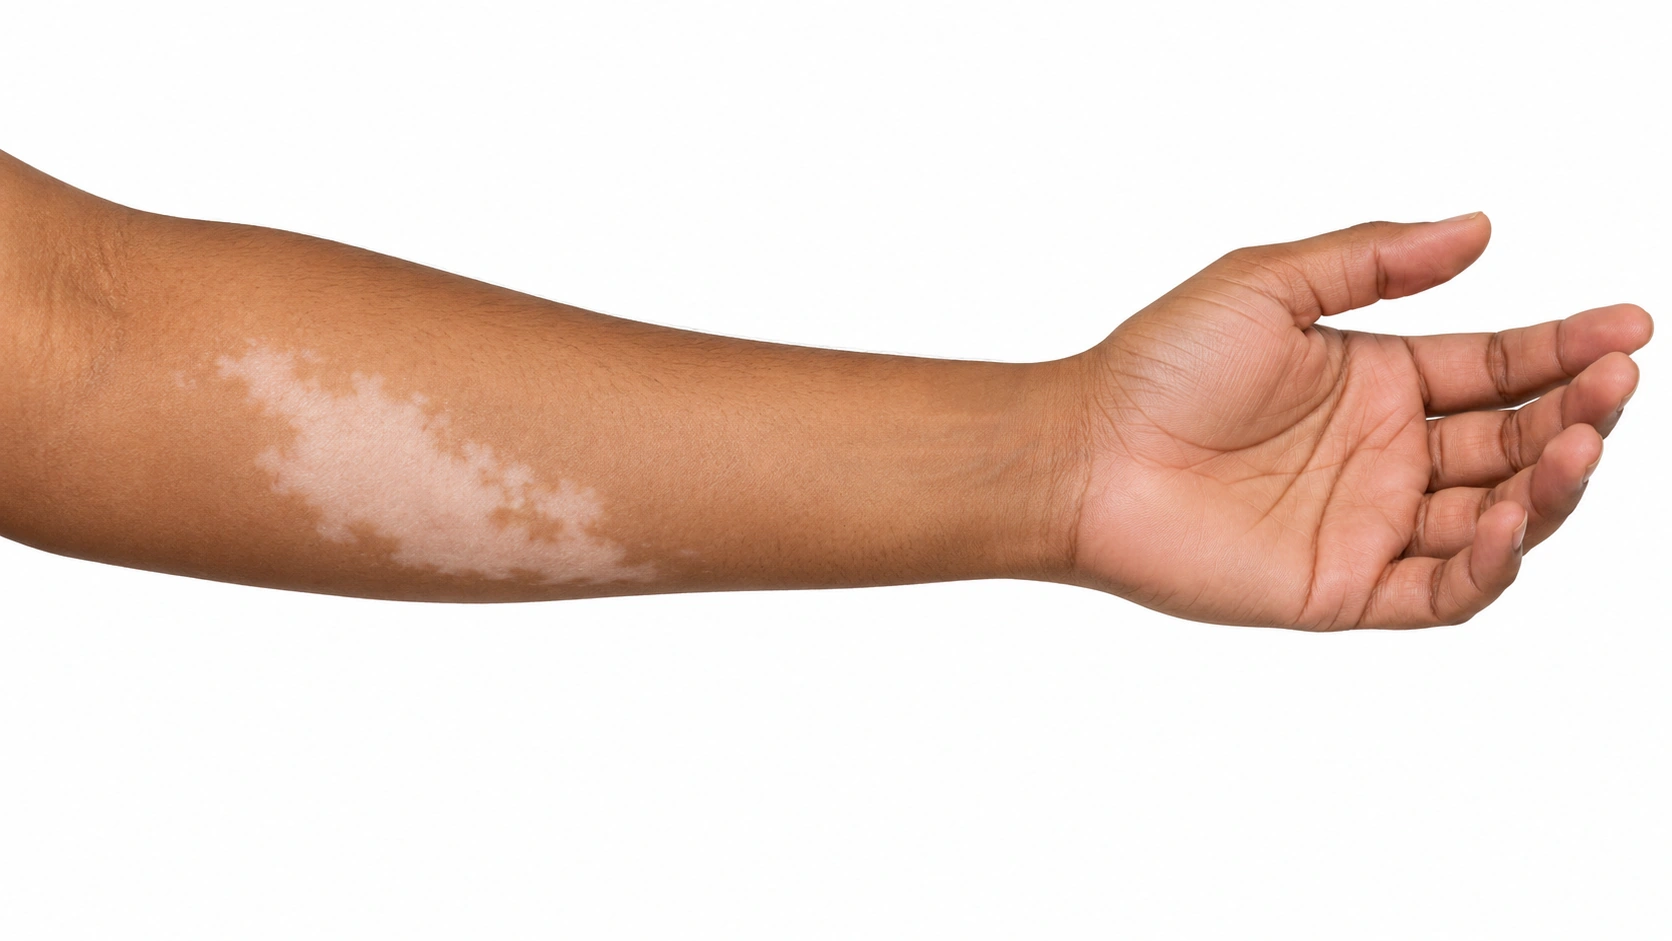
Vitiligo causes patches of skin to lose their color completely, becoming milky white. The patches have clear borders and are often found on both sides of the body. Common sites include the face around the eyes and mouth, hands, feet, elbows, knees and genitals. Hair in affected areas may turn white. The skin feels normal and doesn't itch or hurt.
Vitiligo is grouped by its pattern on the body. The type helps predict how it may spread and respond to treatment.

Non-segmental vitiligo
Patches on both sides; most common.
Segmental vitiligo
One side or one area only.

Focal vitiligo
A few patches in one area.
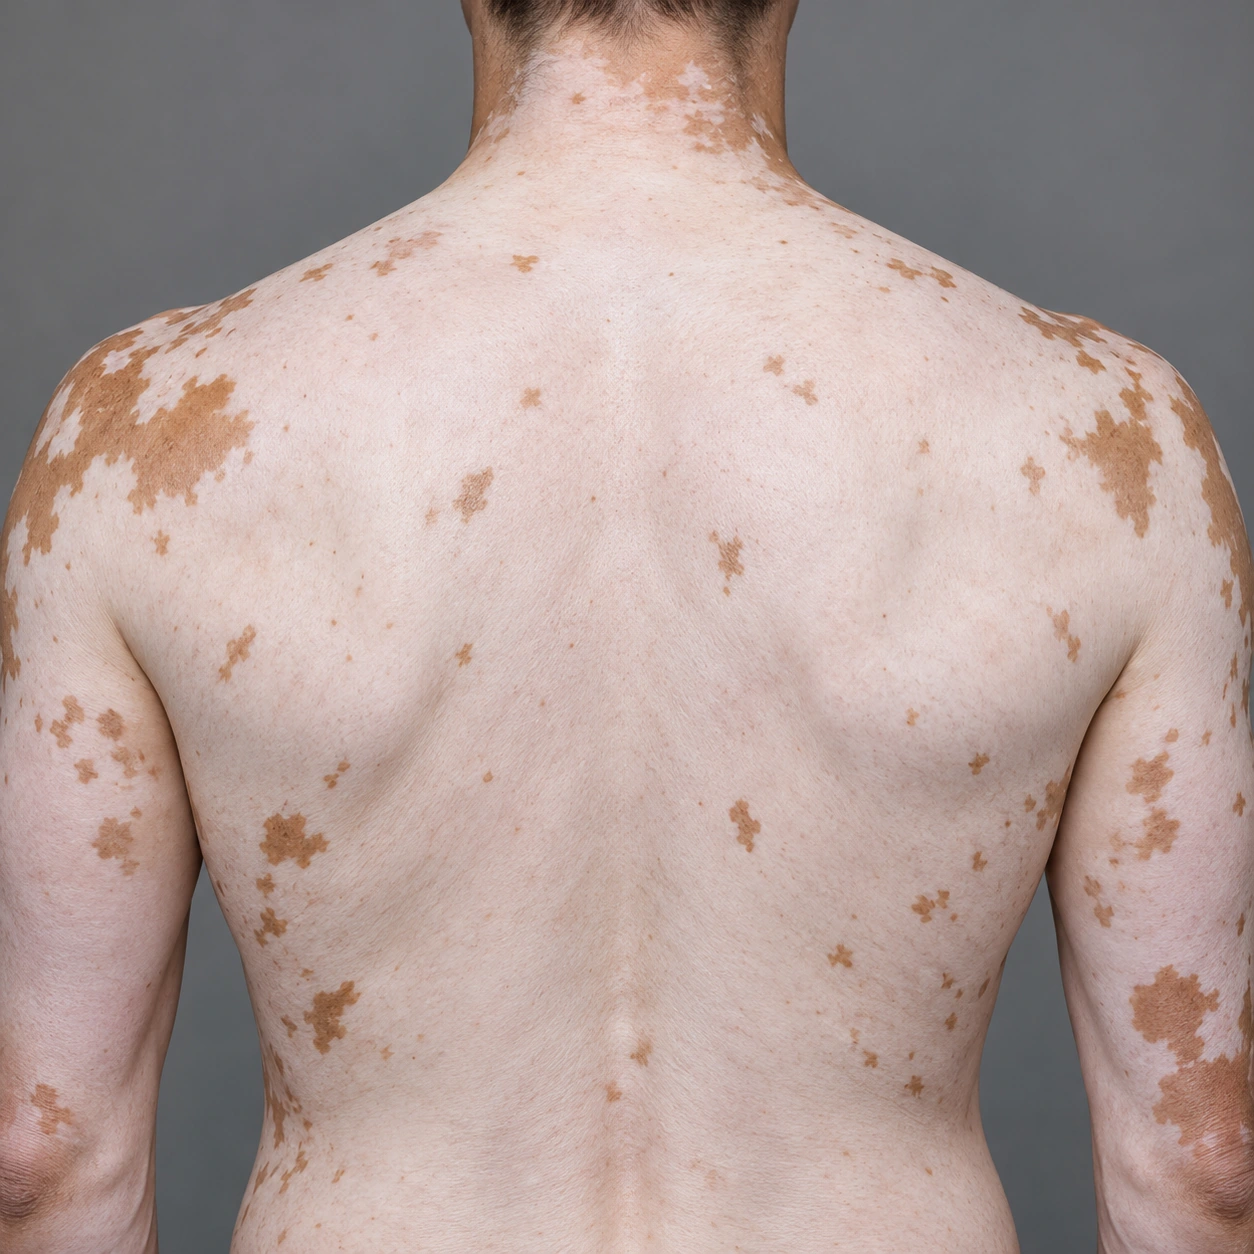
Universal vitiligo
Generated illustration. Most of the body.
Where it shows up
Location varies
Vitiligo may affect the face, hands, folds and other areas. The distribution varies with the subtype and individual.
On different skin tones
Vitiligo on different skin tones
Vitiligo affects all skin tones equally, but it is much more visible on brown and Black skin, where the white patches stand out sharply. On very light skin, patches may only be noticed after a tan. Sunscreen protects the white patches, which burn easily.
What happens in Vitiligo?
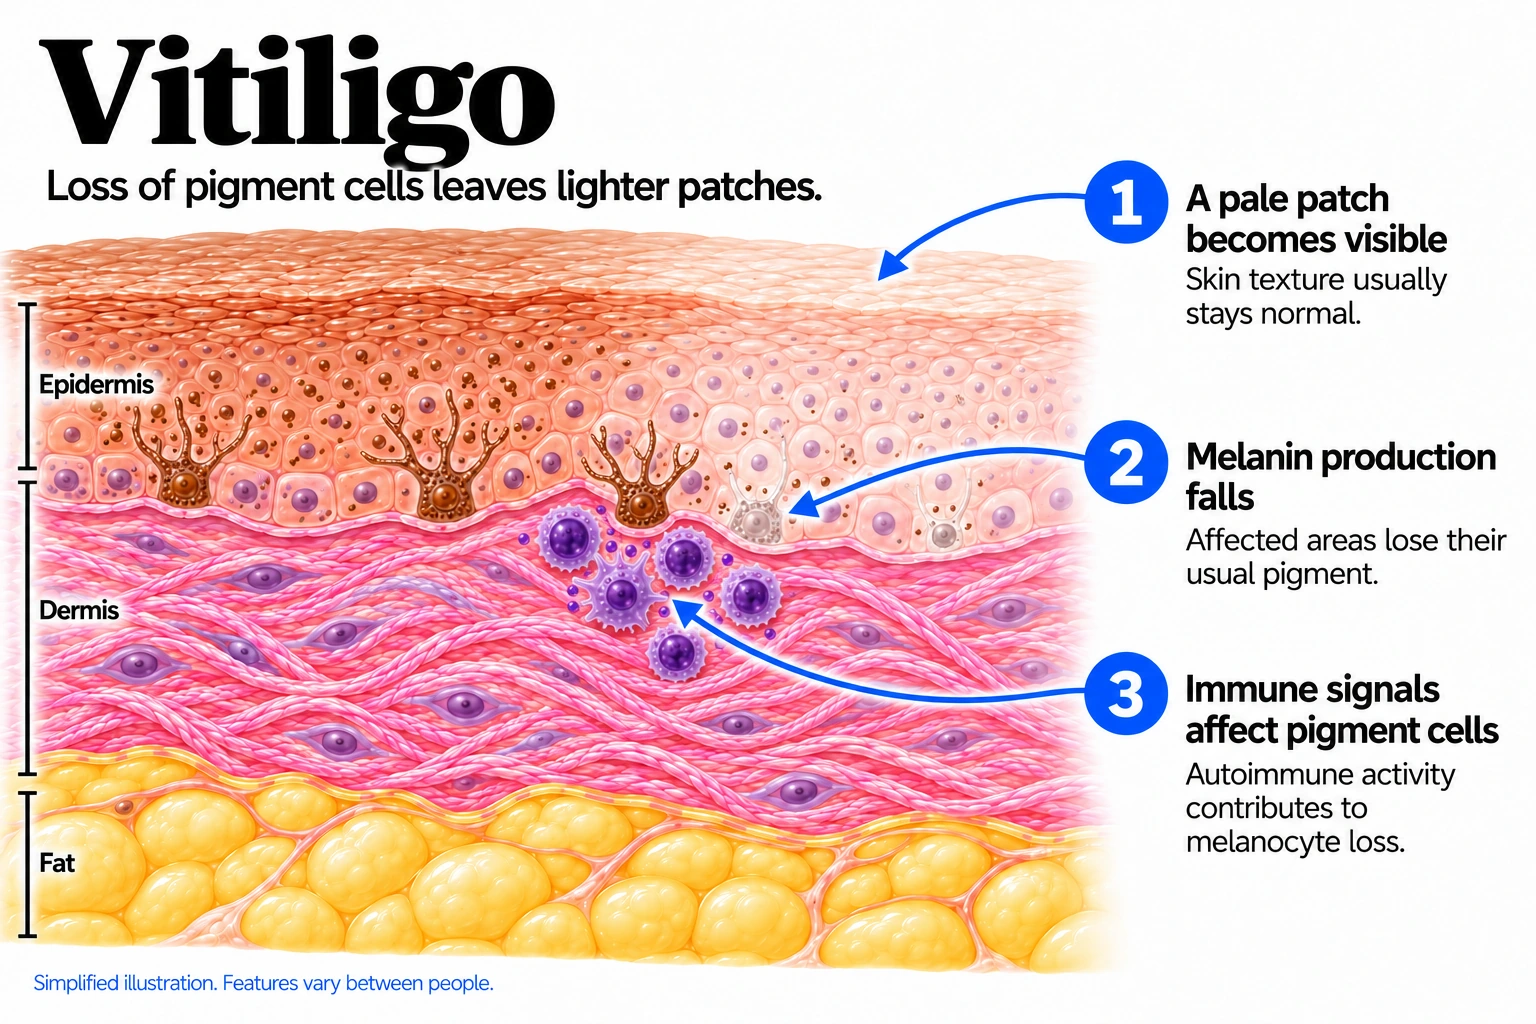
Immune activity contributes to the loss of pigment-producing cells in affected skin. With less melanin, pale patches become visible while the skin's texture usually remains normal.
- A pale patch becomes visible: Skin texture usually stays normal.
- Melanin production falls: Affected areas lose their usual pigment.
- Immune signals affect pigment cells: Autoimmune activity contributes to melanocyte loss.
Causes and triggers
What causes Vitiligo
Causes
Why it happens
Vitiligo is an autoimmune condition. The immune system attacks the pigment cells in patches of skin, leaving them white.
About 1 in 5 people with vitiligo have a relative with it.
Risk factors
Raise the odds
- Family history
- Thyroid disease
- Other autoimmune conditions
Triggers
Bring it on or make it worse
- Skin injury (Strong link)
- Severe sunburn (Possible)
- Stress (Possible)
- Chemicals like some hair dyes (Possible)
When it usually starts
When it usually starts
Vitiligo
Can begin at any age, commonly before early adulthood.
Daily care
Daily care for Vitiligo
Daily sunscreen on exposed patches
Prevents triggering burns and limits the contrast.
Camouflage and self-tanner
Changes nothing underneath, but makes daily life easier meanwhile.
Topical calcineurin inhibitors
Tacrolimus and pimecrolimus calm the same attack without thinning skin.
Ruxolitinib cream
A prescription JAK inhibitor cream approved to restore pigment, used for months.
Narrowband UVB light therapy
The mainstay for widespread vitiligo, two or three sessions a week.
Combining light therapy with a cream
Repigments more skin than either alone.
Checking the thyroid
Thyroid disease is common alongside vitiligo and often silent.
Avoid: Injuring the skin
Cuts, burns, tight straps, surgery and tattoos bring out new patches at that exact spot.
Avoid: Sunburn
An injury and a chemical stress at once, and depigmented skin burns faster.
Avoid: Constant friction and pressure
Belt lines, bra straps, watch bands, rubbing shoes.
Avoid: Certain chemicals
Some phenol and catechol compounds destroy pigment cells directly, including in some lightening creams.
Avoid: Physical or emotional stress
It does not cause vitiligo, but it can make an existing tendency act up.
Avoid: Stopping treatment when color returns
Without maintenance, many repigmented patches lose color again.
Avoid: Waiting to be seen
Patches white for years respond much less well than fresh ones.
Treatments
Treatments for Vitiligo

Antioxidant supplements
Ginkgo biloba and polypodium leucotomos extract are the two most often asked about. Small studies suggest they may slow spread a little or add slightly to light therapy, but the trials are small and the results are inconsistent. They are not a treatment on their own, and no supplement has been shown to bring color back.

Camouflage makeup and self-tanner
Cover creams made for skin conditions, and self-tanning lotions containing dihydroxyacetone, color the surface of a white patch for a few days at a time. They change nothing underneath and they do not interfere with treatment. For many people they make daily life easier during the year or more that repigmentation takes.
Opzelura
A JAK inhibitor cream approved specifically to restore pigment in vitiligo, applied twice a day. In trials about a third of people had most of the color back on the face by six months, and results keep improving past a year. It is slow, it is expensive, and color can be lost again if it is stopped, so it is usually continued about twice a week afterwards.
Protopic
The usual choice for vitiligo on the face, eyelids, neck and skin folds, because it quiets the immune attack without thinning the skin, so it can be used in those places for months. It stings or feels warm for the first week or two in some people. It works best on the face and much less well on hands and feet.

Clobetasol
Clobetasol Propionate. A strong steroid cream, the standard first treatment for a small number of patches on the body. It is used in courses with breaks, often a few weeks on and a few weeks off, because continuous use thins the skin and leaves stretch marks. It is not used on the face or eyelids, where tacrolimus is chosen instead.

Elidel
A gentler relative of tacrolimus, used on the same delicate areas and often preferred for children or for people who find tacrolimus too stinging. It works the same way on the immune attack. It is generally a little less effective than tacrolimus for vitiligo.

Calcipotriene
A vitamin D cream sometimes added to a steroid or to light therapy, on the idea that it helps pigment cells return. On its own it does very little for vitiligo. Its value is as a partner treatment, and the evidence for even that is mixed.

"Bleaching" cream
Monobenzone cream removes the pigment that is left, so the skin ends up one even color. It is only considered when vitiligo already covers most of the body and repigmenting is not realistic. The change is permanent and cannot be reversed, and the skin afterwards has no protection from the sun at all, so it is a decision taken slowly and never as a first step.
Oral JAK inhibitors
Tablets in the same family as ruxolitinib cream. Trials show real repigmentation, particularly when they are combined with light therapy, and they are the most active area of vitiligo research right now. They are not yet standard treatment for vitiligo, and they carry more risk than a cream, so they are used through a specialist or a trial.

Prednisone
Prednisone in short pulses. Low-dose steroid tablets taken on two days a week for a few months are used for one purpose in vitiligo: to stop pigment loss that is spreading quickly. It is a brake, not a way to bring color back, so it is paired with a cream or light therapy. Blood sugar, blood pressure and mood are watched while it is running.

Phototherapy
Narrowband UVB, two or three sessions a week in a cabinet at the clinic, is the mainstay for vitiligo that covers more than a few small patches. It calms the immune attack and coaxes pigment cells out of the hair openings. Expect three to six months before the face shows change and a year or more for a full course, and better results when it is combined with a cream.

Excimer Laser
The same wavelength as narrowband UVB delivered through a handpiece, so it treats one patch and leaves the skin around it alone. It suits a small number of patches, especially on the face, and it is the practical option for children who cannot stand still in a cabinet. Sessions are usually twice a week, and it is not used for widespread vitiligo.
Surgical pigment grafting
Pigment cells are taken from normal skin and moved into a white patch, either as tiny grafts or as a cell suspension. It is the best option for segmental vitiligo and for patches that have been completely stable for a year or more, including patches where the hair has gone white. It is never done while vitiligo is spreading, because the graft is attacked in turn.
Outlook
What to expect with Vitiligo
Vitiligo is unpredictable, which is one of the hardest things about it. Non-segmental vitiligo, the common type, moves in waves — an active spell, a long still period, then another. Segmental vitiligo spreads within one area on one side over roughly six months to two years, then stops for good.
- 1
Active spread · Weeks to months
Look for blurred rather than sharp edges, tiny confetti-like white spots, and new patches where skin was recently injured. Treatment does the most good now, so be seen rather than wait and see.
- 2
Still phase · Can last several years
A person may hold still for years before the next active spell. A minority repigment on their own, usually not completely, and nobody can predict who.
- 3
During treatment · Results vary by site
Face, neck and trunk do best. Elbows, knees, hands, fingers, feet and lips do worst, and patches where the hair has turned white often do not refill at all, because the reservoir of pigment cells in the hair openings is gone.
- 4
After color returns · Long term
A treatment cream twice a week on a repigmented area substantially reduces the chance the patch returns. Vitiligo does not shorten life or damage organs, so long-term decisions are about how visible it is and how much it bothers you.
Complications
Complications to know about
Sunburn inside the patches
Skin inside a vitiligo patch has no melanin at all, so it burns quickly and can burn badly while the skin around it is fine. A burn is also an injury, and injuries can bring out new patches, so a bad burn can make things worse in two ways at once. Daily broad-spectrum sunscreen on exposed patches prevents it, and it counts as treatment rather than an extra.
Thyroid and other autoimmune disease
The same immune tendency that causes vitiligo makes other autoimmune conditions more likely, and thyroid disease is the common one. It is often silent for a long time, which is why a thyroid blood test is standard at the first visit and is sometimes repeated later. Type 1 diabetes, pernicious anemia and alopecia areata also appear more often than average.
The weight of being looked at
Vitiligo does not make you unwell, but it is visible, and being looked at all day is tiring. Anxiety, low mood and avoiding ordinary things are common, and they are worse where the contrast is greater or the patches are on the face and hands. This counts as a medical reason to treat, not a cosmetic one, and it is worth saying out loud at the appointment.
When to get help
When to get help
When to seek care
Seek assessment of new white patches or spreading pigment loss. Discuss associated symptoms, sun protection and whether targeted autoimmune screening is appropriate.
Questions
Questions you might be asking.
Will my color ever come back?
Often, at least partly. Face, neck and trunk repigment well for a substantial proportion of people. Hands, fingers, feet and lips do poorly, and patches where the hair has gone white usually do not refill, because the pigment cells that restock a patch live in the hair openings. Nobody can promise a result, which is why photographs at the start are worth taking.
How long does treatment take?
Longer than almost anyone expects. The first visible change on the face usually takes about three to six months, and a full course often runs a year or more. Judging a treatment at week six is judging it before it has done anything.
Is vitiligo dangerous?
Not to your body. It does not shorten life, damage organs or turn into anything else. Two points matter: depigmented skin burns easily, and autoimmune conditions such as thyroid disease are more common alongside it, which is why blood tests are usually done.
Will it spread over my whole body?
Most likely not. Vitiligo moves in waves, and losing pigment over almost the entire body is uncommon. Nothing predicts the course from the first patch, which is why active spread is treated promptly.
Can my children get it?
Higher than average, but still low. Vitiligo runs in families through a group of immune genes rather than one, so most children of a parent with vitiligo never develop it.
Does stress cause vitiligo?
No — the underlying immune tendency is genetic. But major stress, illness or surgery frequently lines up with the start of an active spell. Managing stress is worth doing for its own sake, and it is not a substitute for treatment.
Sources
Sources and further reading
Related
Keep exploring.
Elidel
Protopic
Tinea Versicolor
Calcipotriene
Opzelura
Excimer Laser
Phototherapy
Clobetasol
Prednisone
Vitiligo vs Tinea Versicolor
Vitiligo vs Pityriasis Alba