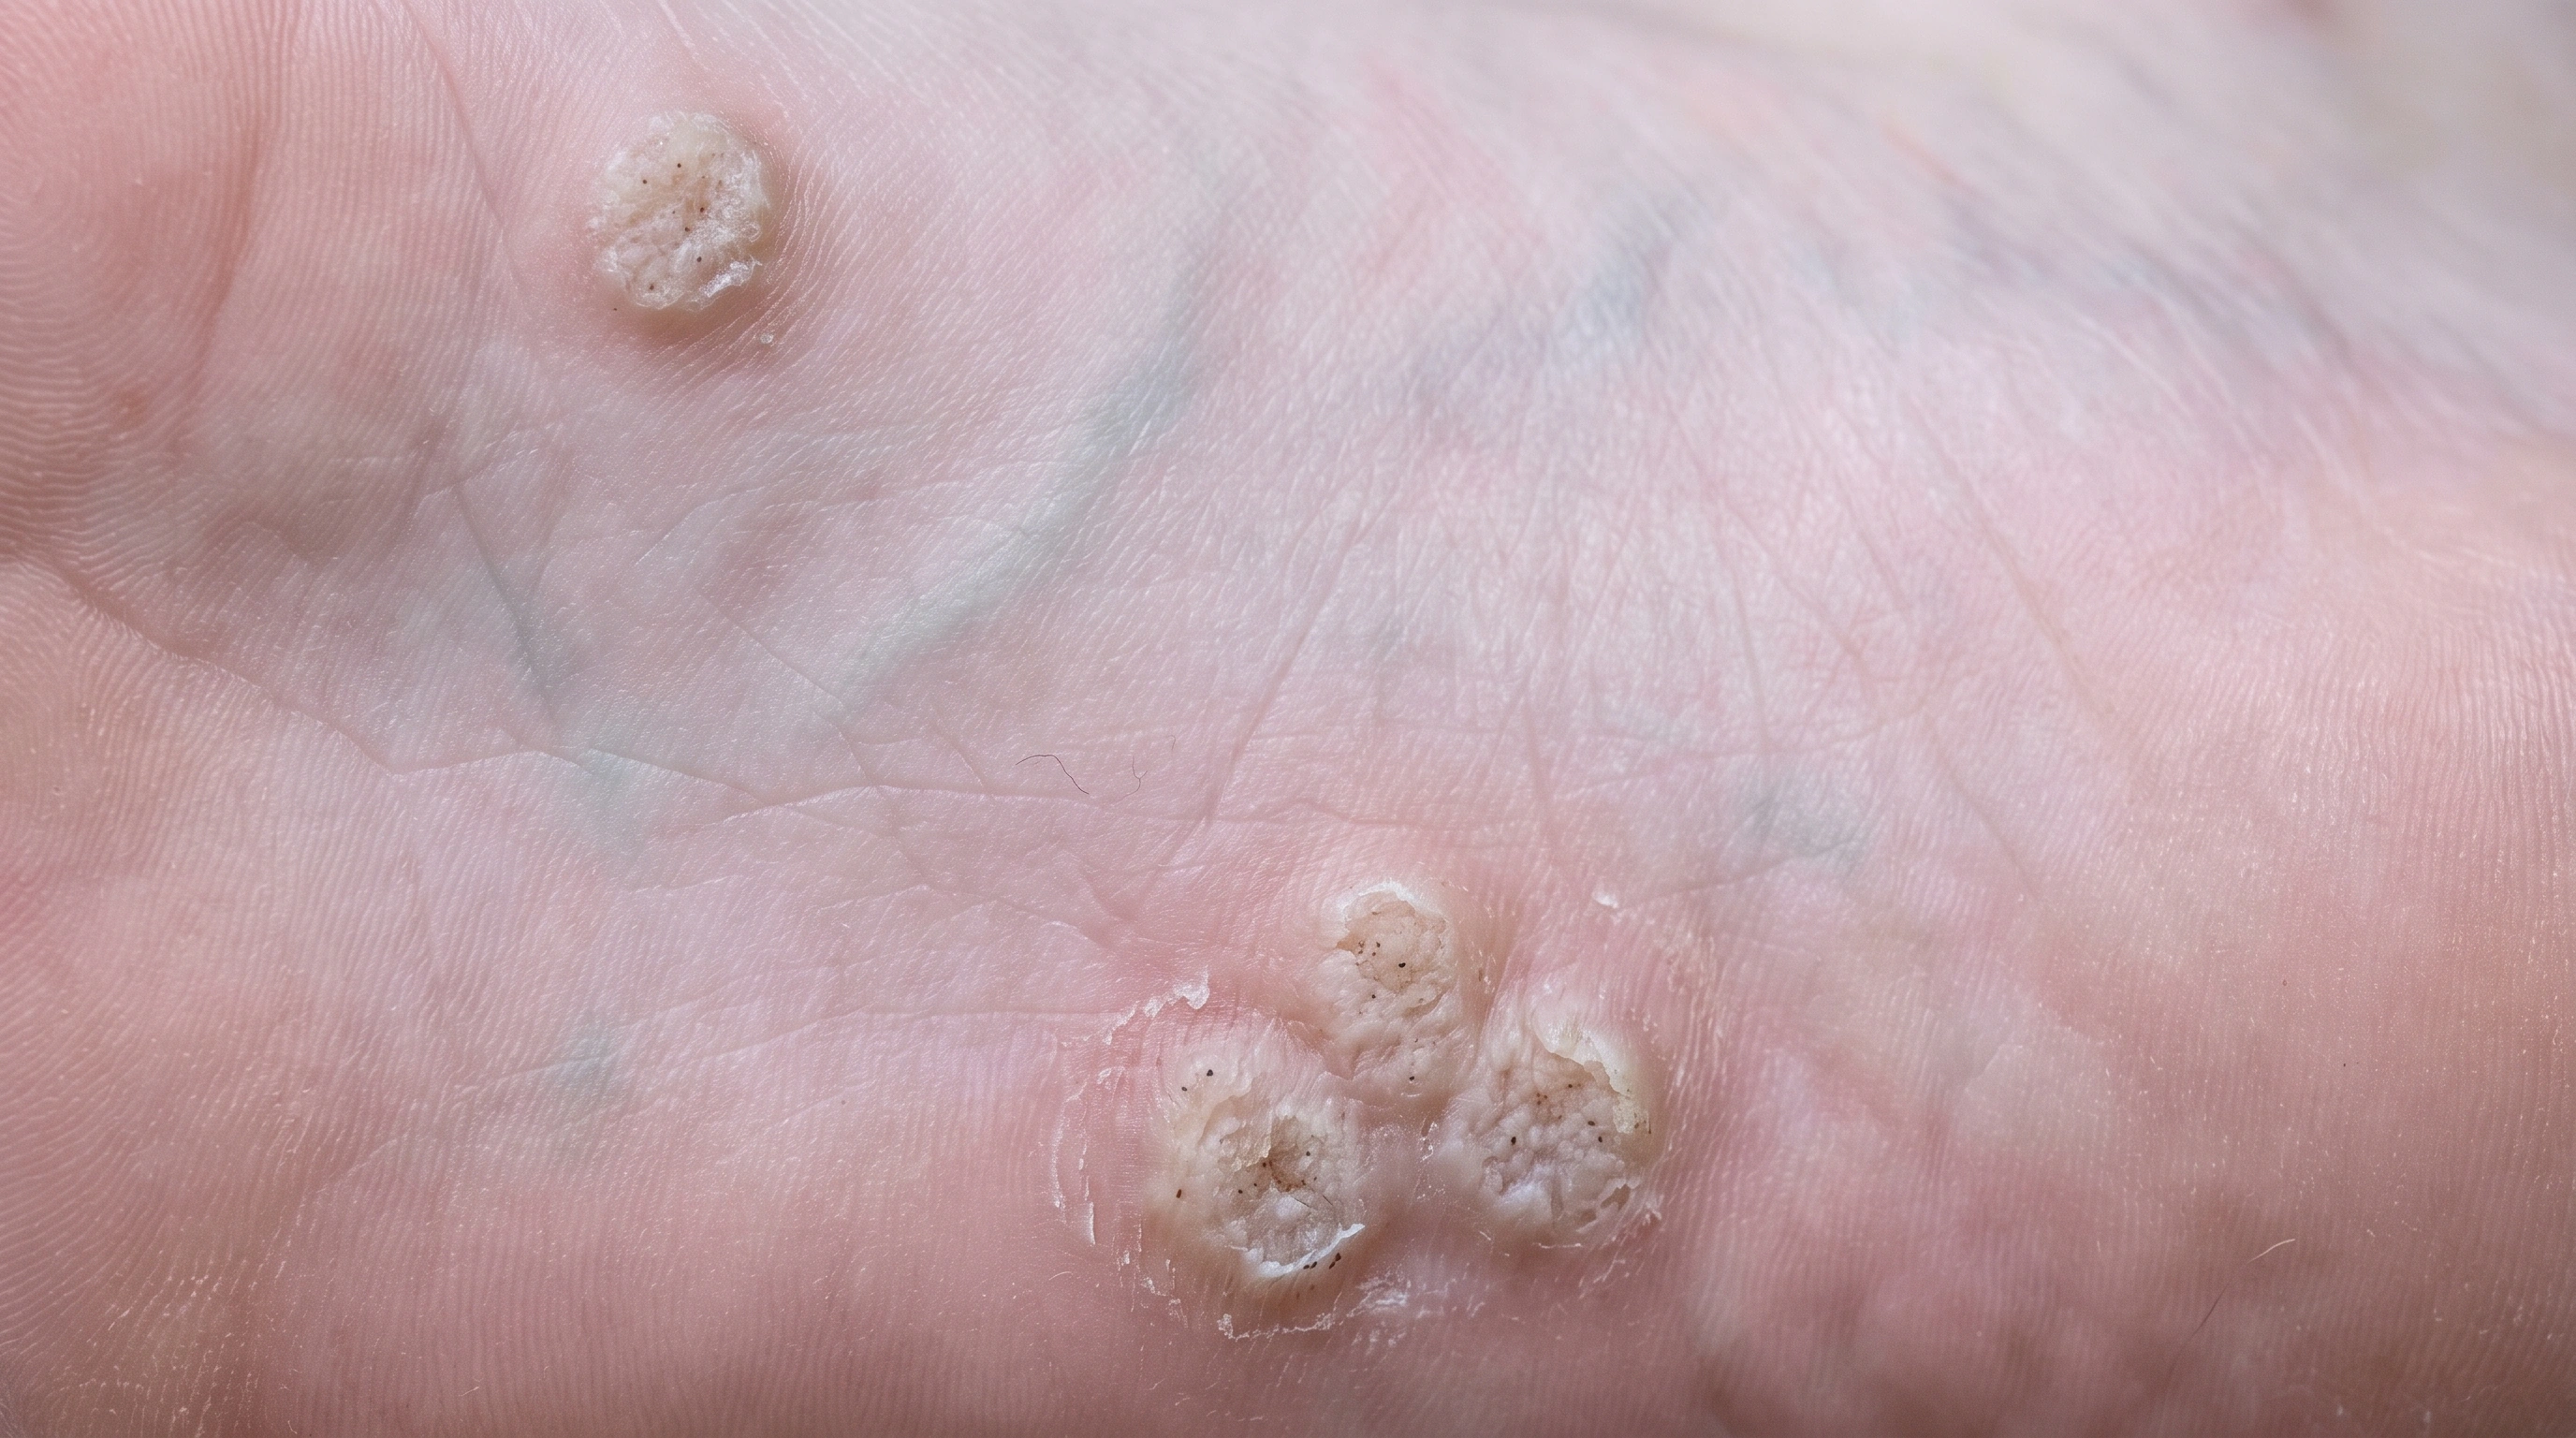
Squamous Cell Carcinoma
Squamous cell carcinoma is the second most common skin cancer. It usually appears as a rough, scaly or crusted bump on skin that has had years of sun, and it often looks like a sore that will not heal. Found early it is removed and cured. Left alone it grows deeper, and a small share spread.
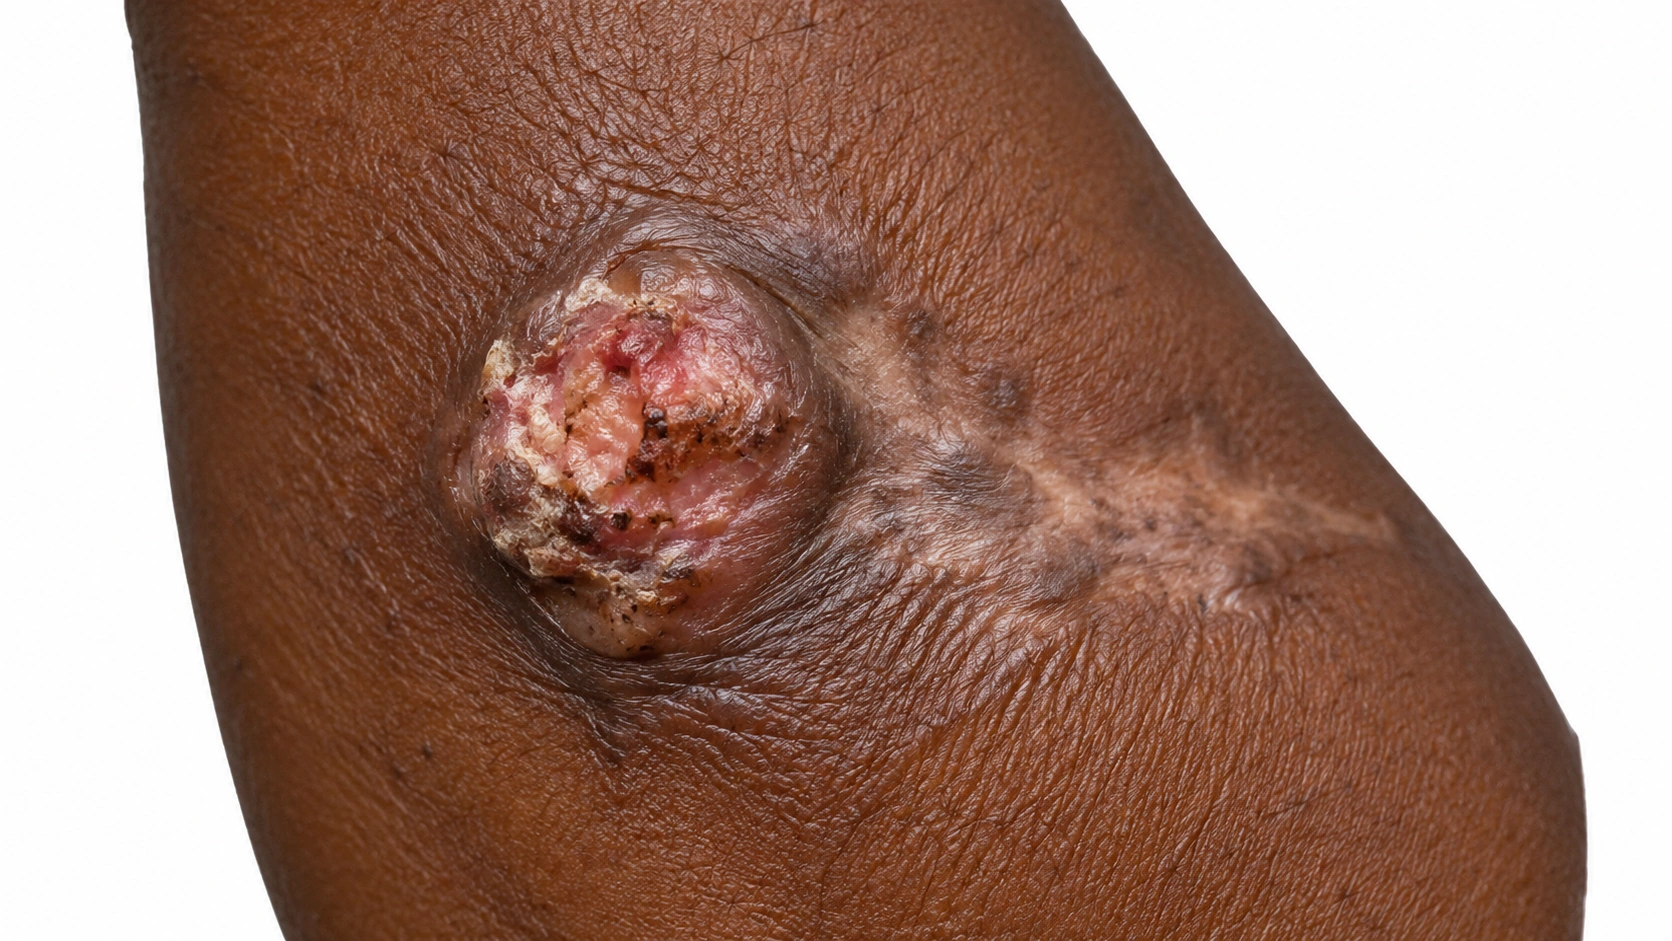
Key facts
Squamous Cell Carcinoma at a glance.
Typical signs
Persistent scaly growth or sore
Common locations
Face, ears, scalp, hands
Expected course
Often curable when treated early
Treatment options
Excision or Mohs surgery
What is it?
Top things to know about Squamous Cell Carcinoma
- It is a skin cancer of keratinocytes. It arises from the main cells of the outer skin.
- It often looks crusted or ulcerated. It may be a growing scaly lump, persistent sore or tender patch.
- Most are treated successfully. Some can invade deeply or spread to lymph nodes.
- Risk is assessed individually. Size, depth, site and immune status guide care.
What it looks like
What Squamous Cell Carcinoma looks like
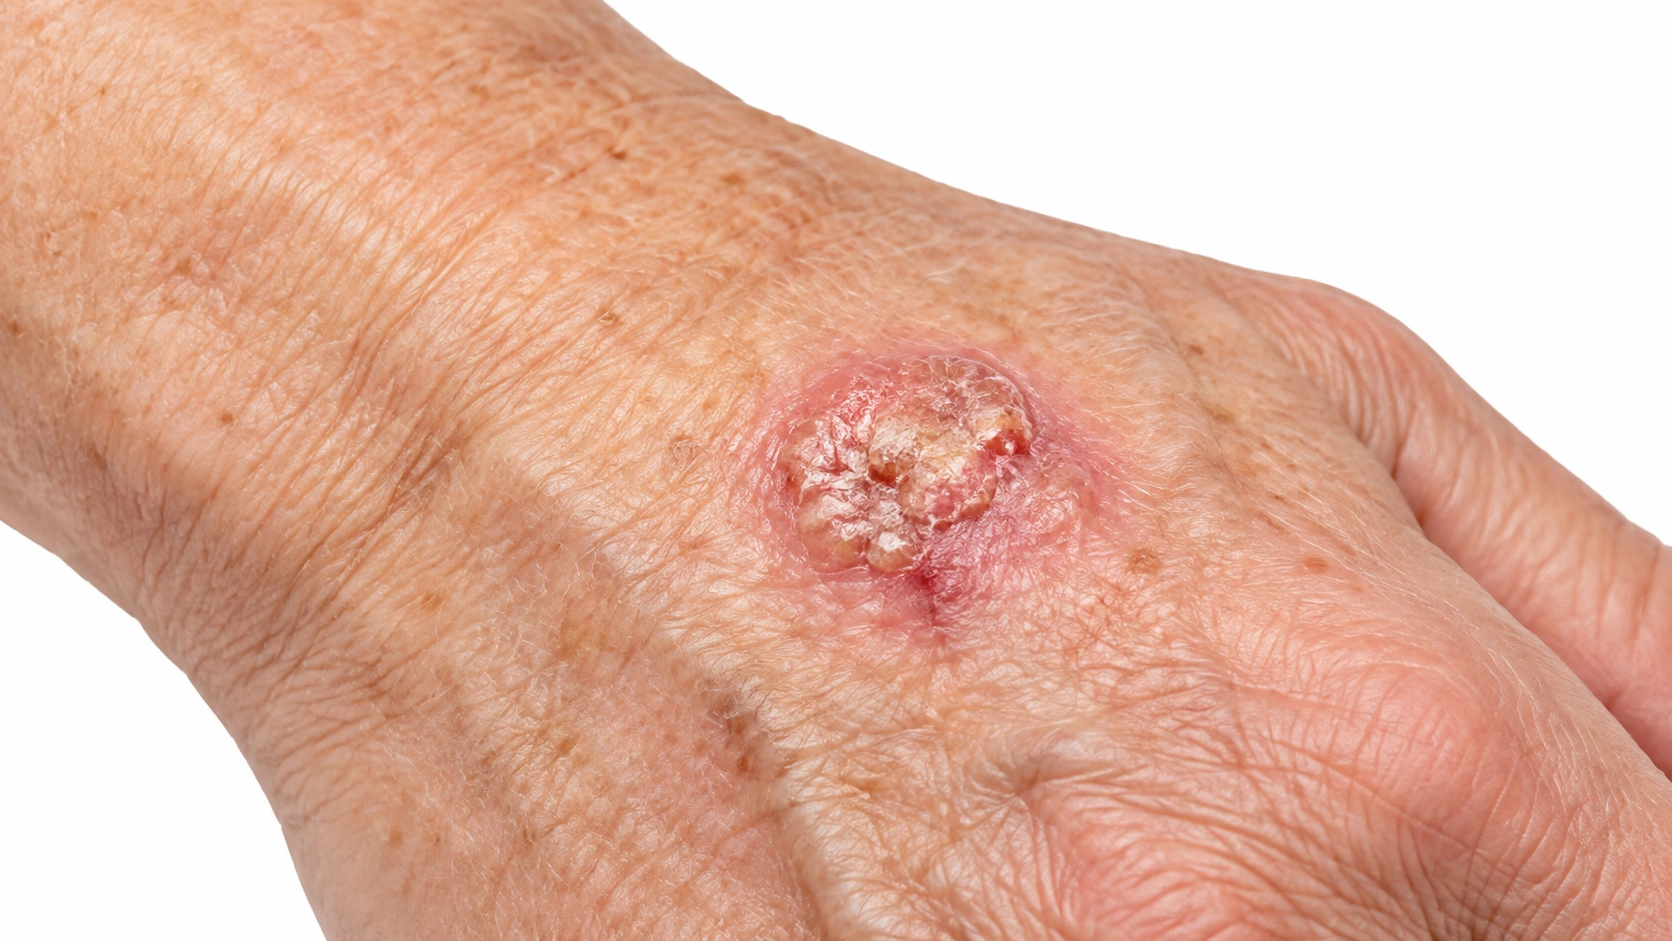
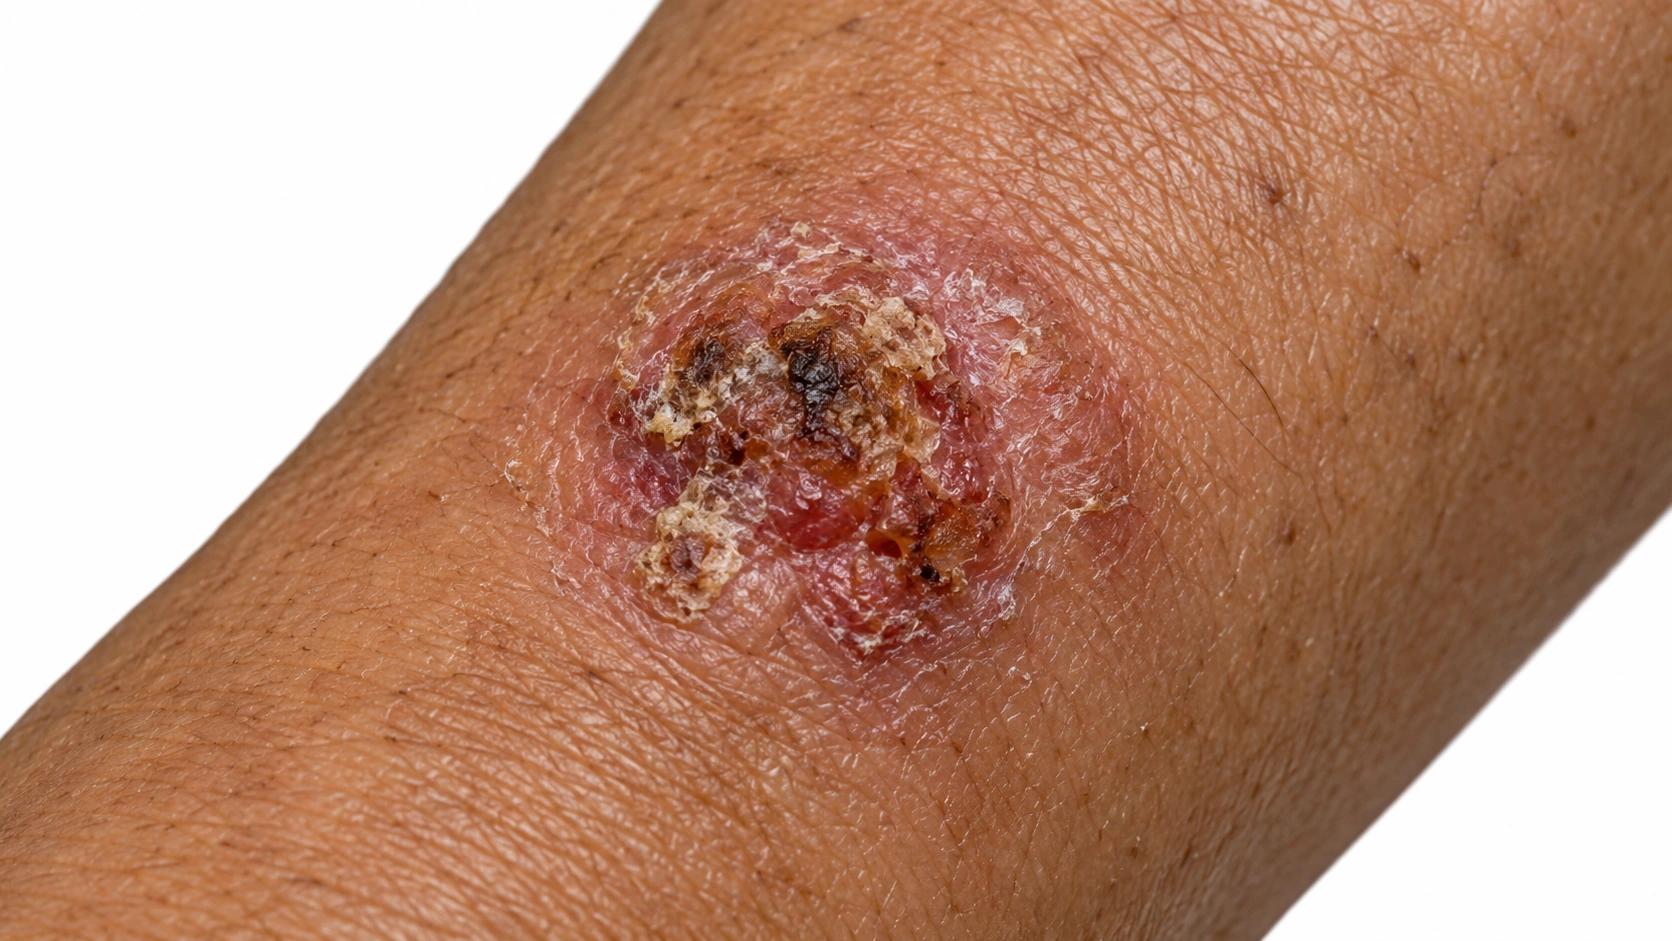
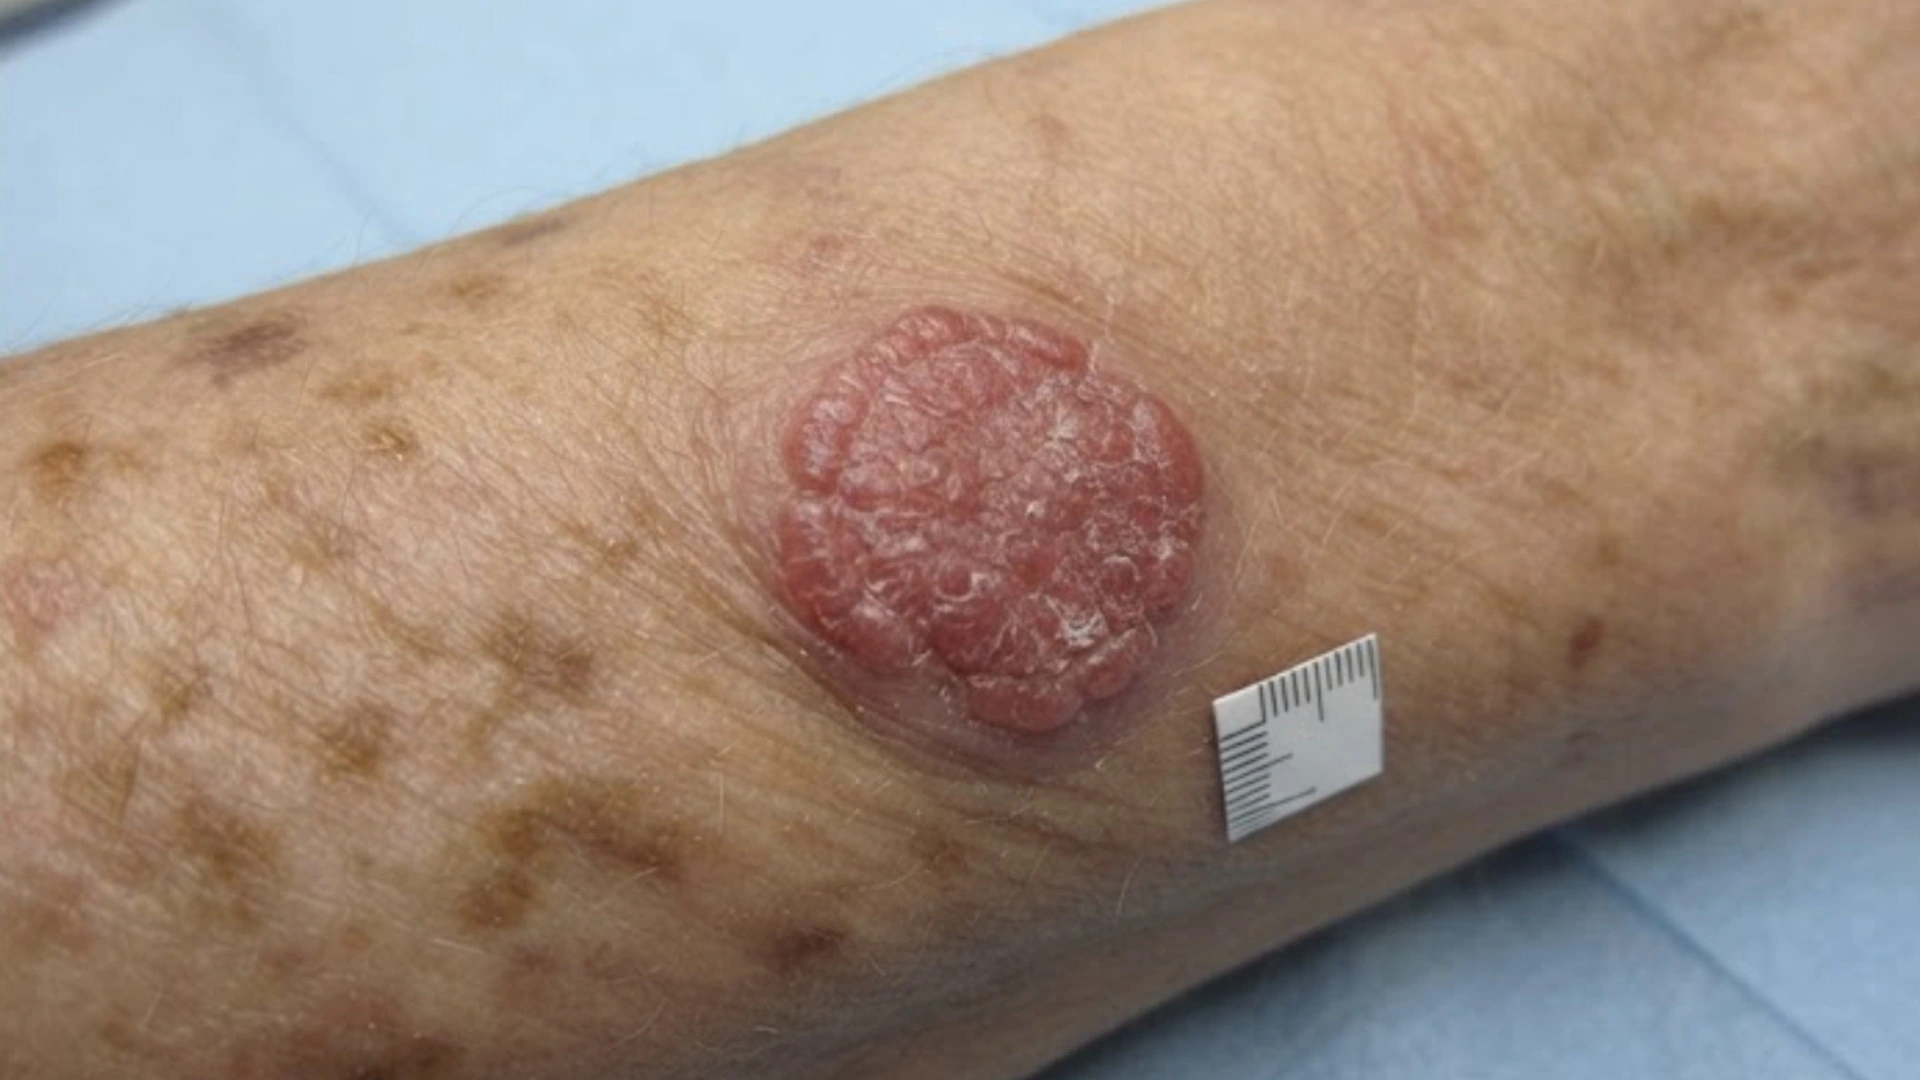
Squamous cell carcinoma is the second most common skin cancer. It usually appears as a firm, scaly or crusted red bump, a flat sore that bleeds, or a wart-like growth that keeps getting bigger. It develops most often on sun-exposed skin, such as the face, ears, lips, scalp, backs of the hands and forearms. It can also form in old scars or chronic wounds. Any sore that doesn't heal in a few weeks should be checked.
Squamous cell carcinoma ranges from early surface forms to deeper invasive types.
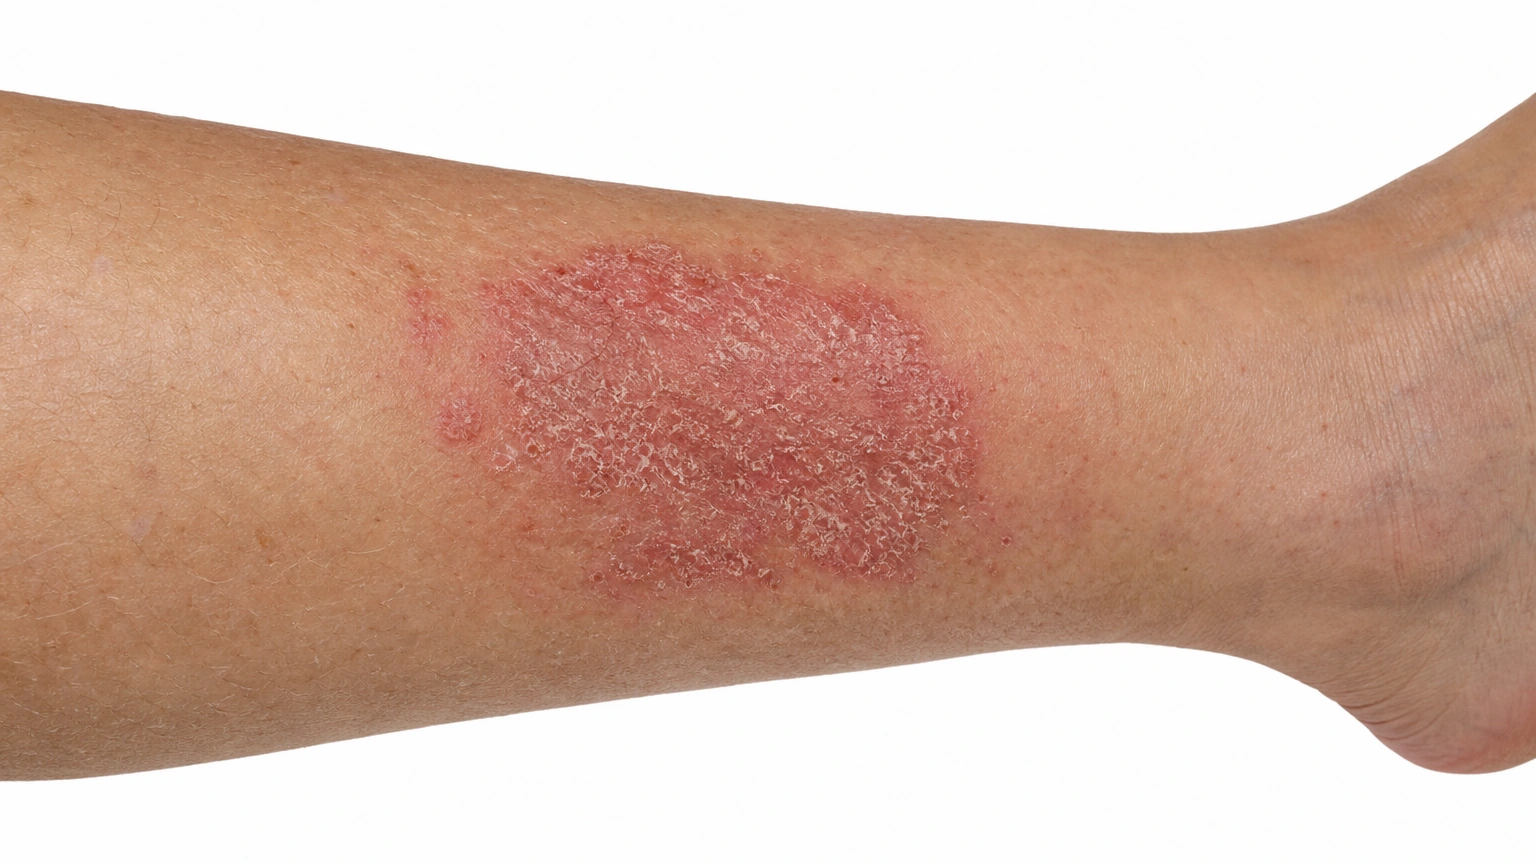
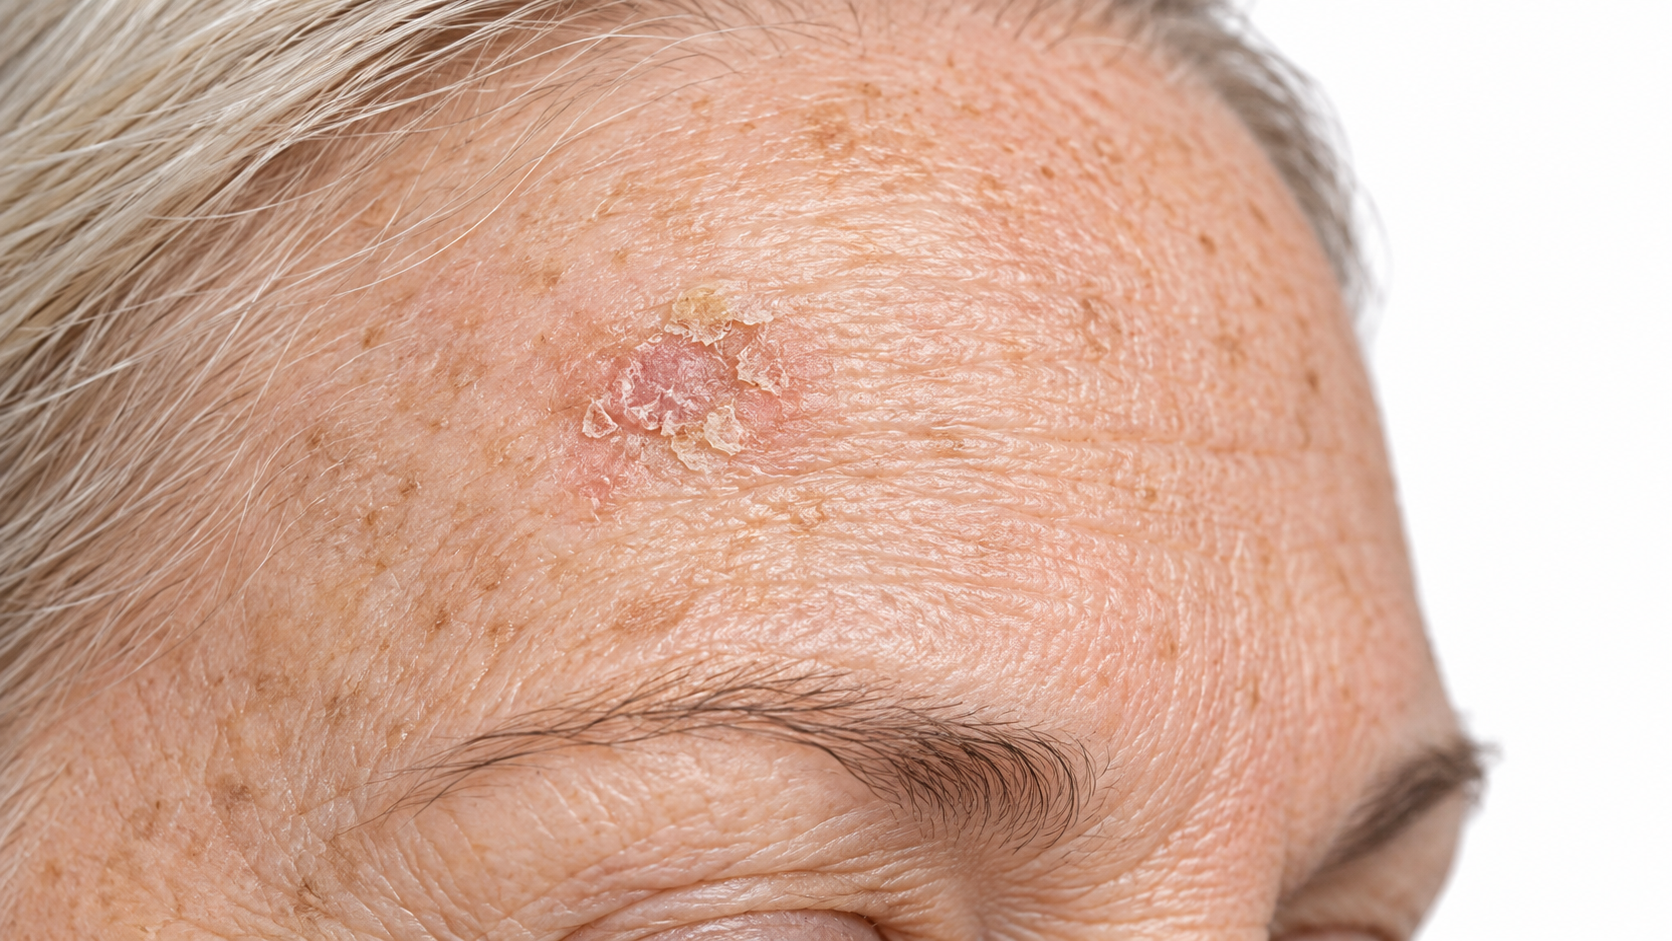
Squamous cell carcinoma in situ
Flat red scaly patch, surface only.
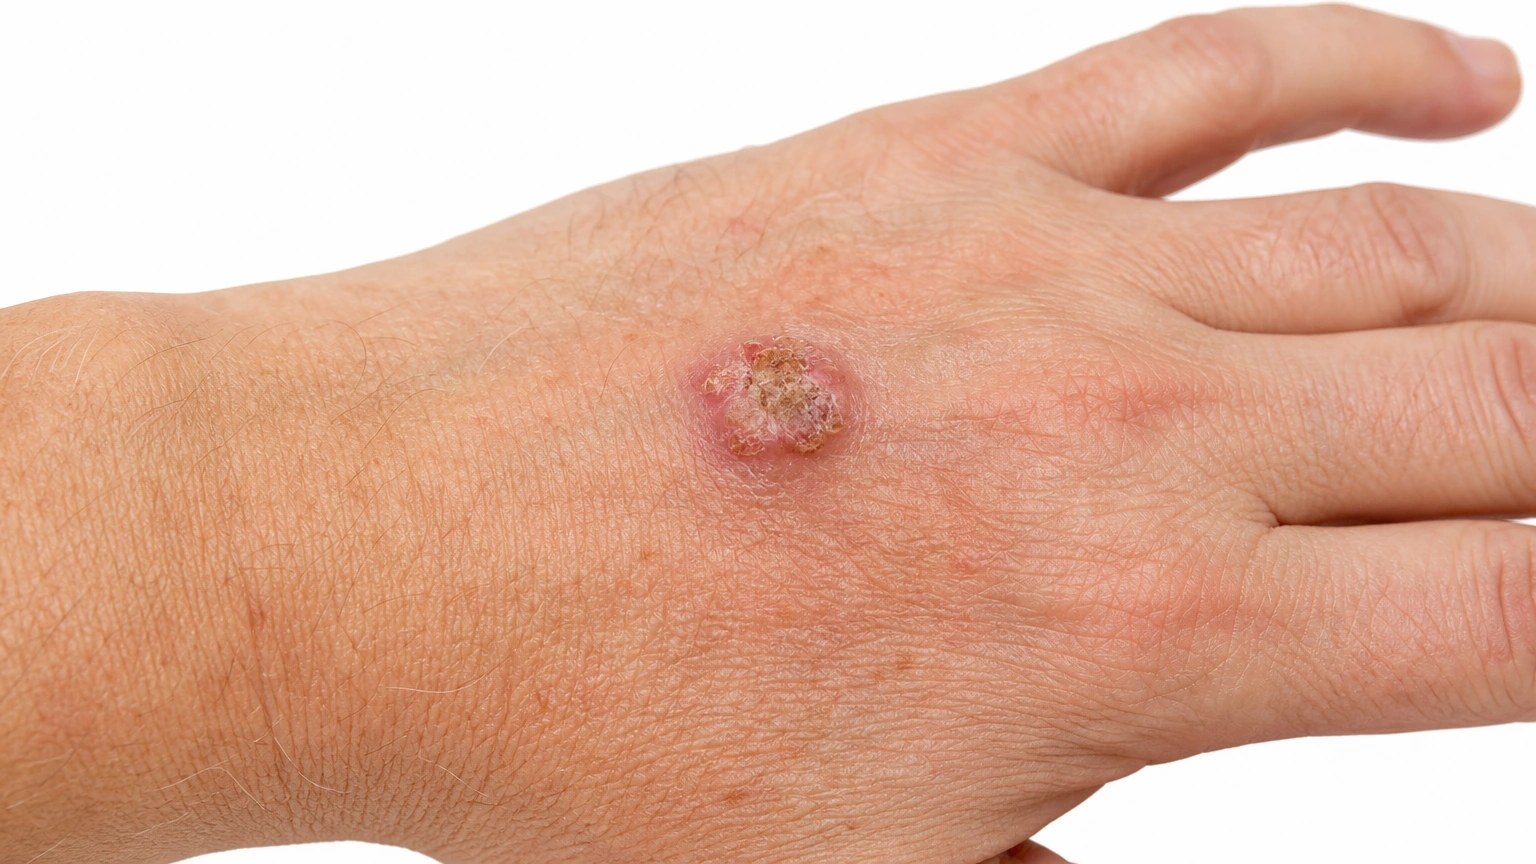
Invasive squamous cell carcinoma
Generated illustration. Firm, crusted or ulcerated bump.
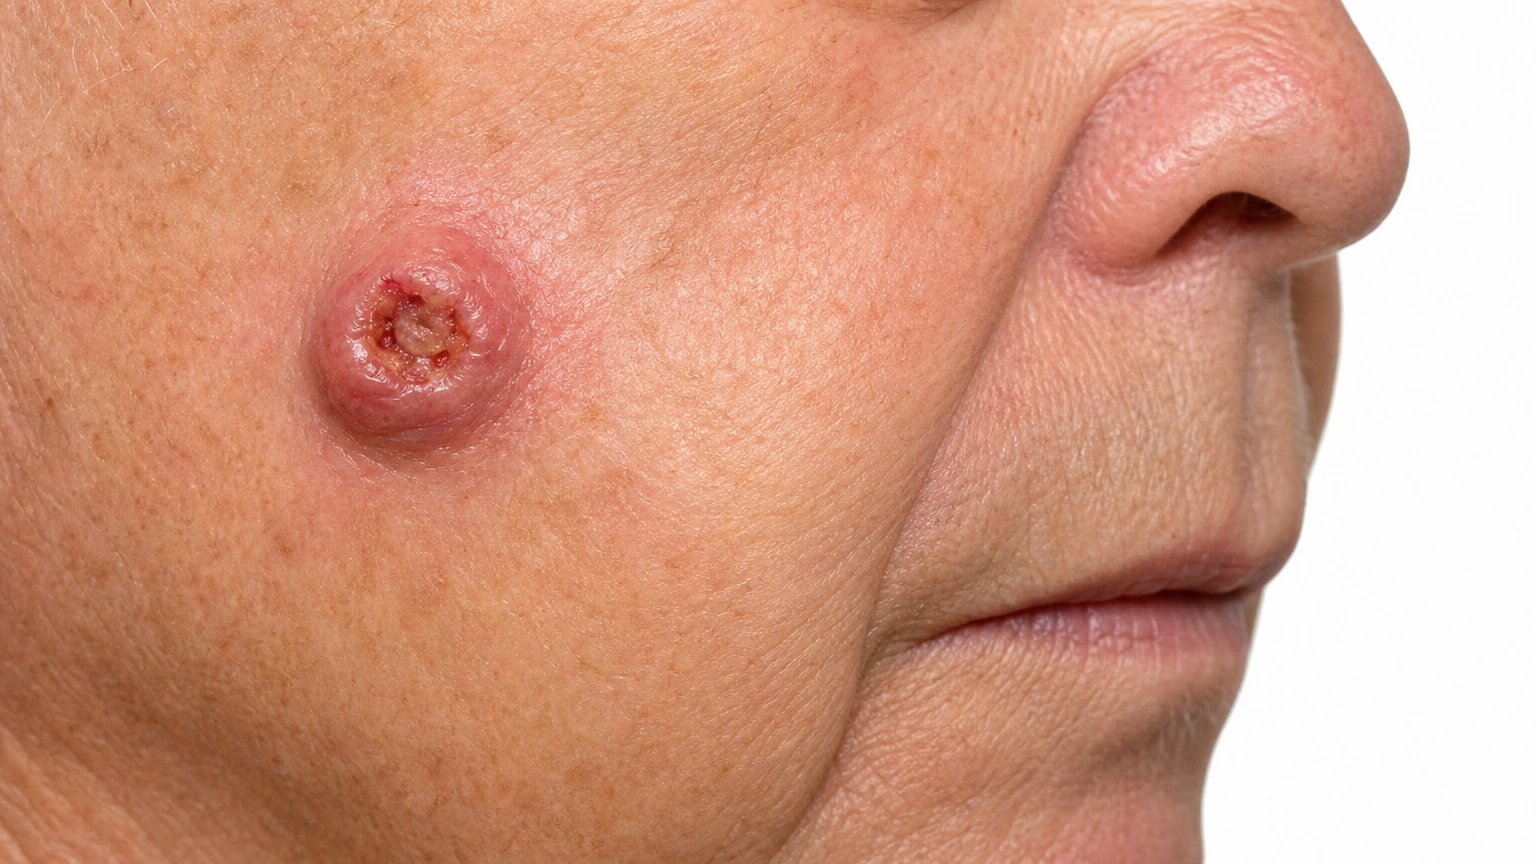
Keratoacanthoma
Fast-growing dome with a central crater.
Where it shows up
Common sites include the face, ears, scalp and backs of the hands. Other sites, including the lips, can also be affected.
Face
Facial locations.
Scalp and behind the ears
Locations on the back of the head.
Arms
Locations along the forearms.
Hands and wrists
Hand, finger or wrist locations.
On different skin tones
Squamous Cell Carcinoma on different skin tones
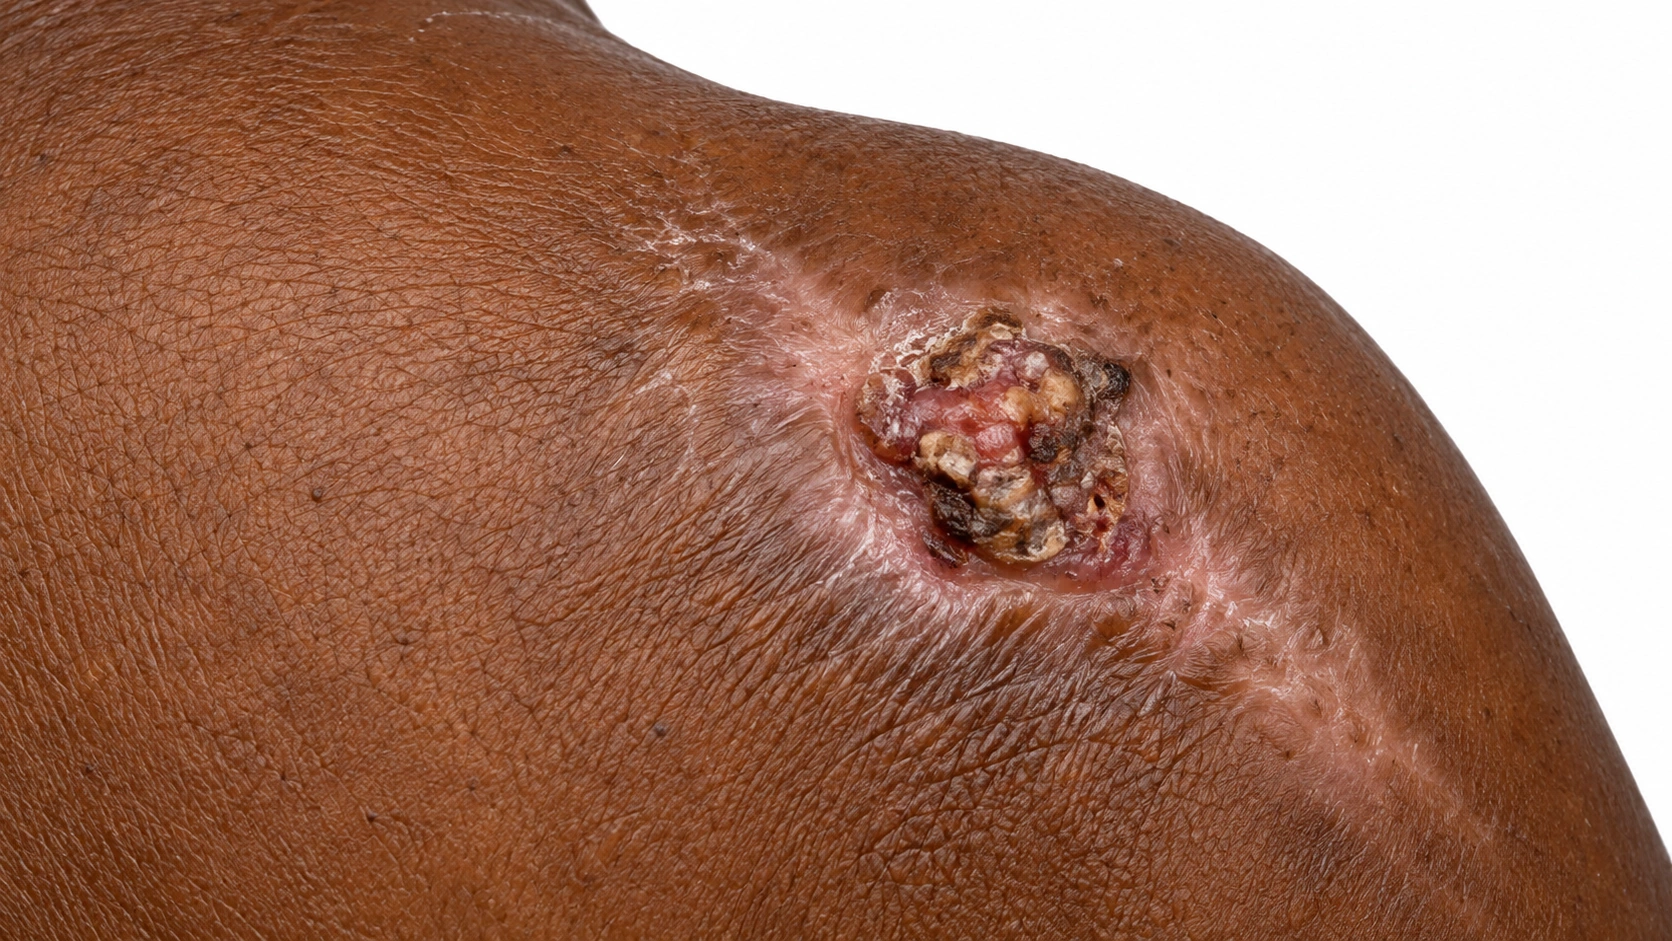
Squamous cell carcinoma is the most common skin cancer in Black skin. In lighter skin, it usually appears on sun-exposed areas. In darker skin, it more often forms in areas with little sun, such as the legs, anus and genitals, and in old scars or long-standing sores, and it is often diagnosed later.
What happens in Squamous Cell Carcinoma?

DNA changes allow abnormal surface skin cells to multiply, commonly after long-term ultraviolet damage. In invasive squamous cell carcinoma, the cancer grows through the epidermal boundary into the dermis.
- A rough or ulcerated growth forms: The surface may crust, bleed, or fail to heal.
- DNA damage changes skin cells: Ultraviolet exposure is a common cause.
- Cancer crosses into the dermis: Invasive cells grow below the epidermis.
Causes and triggers
What causes Squamous Cell Carcinoma
Causes
Why it happens
Squamous cell carcinoma starts when DNA damage makes skin cells grow out of control. Ultraviolet light is the main cause.
Fair skin that burns easily is inherited and raises the risk.
Risk factors
Raise the odds
- Fair skin
- Weakened immunity
- Actinic keratoses
- Long-standing wounds or scars
Triggers
Bring it on or make it worse
- Unprotected sun exposure (Well established)
- Tanning beds (Well established)
- HPV in some areas (Strong link)
When it usually starts
When it usually starts
Squamous Cell Carcinoma
Usually appears in older adults after cumulative sun damage; immunosuppression can lead to earlier disease.
Daily care
Daily care for Squamous Cell Carcinoma
Daily broad-spectrum sunscreen
SPF 30 or higher on face, ears, neck and hands.
Clothing, hats and shade
More than sunscreen alone, and no reapplication.
Mohs surgery
Layers checked during the appointment - spares tissue, highest cure rate.
Curettage and electrodesiccation
Small, low-risk tumors, not the face.
Radiation when surgery is not possible
Also used after aggressive tumors.
Prescription creams for the earliest forms
Fluorouracil and imiquimod treat in situ disease and actinic keratoses, not invasive tumors. If you are pregnant or breastfeeding, ask the doctor managing your pregnancy.
Treating actinic keratoses
Fewer of these cancers later.
Nicotinamide
500 mg twice a day modestly reduces new skin cancers.
Regular skin checks after treatment
How the next one is caught small.
Discuss closer monitoring if your immune system is suppressed
Faster, more aggressive tumors - ask your transplant team about surveillance, and never stop medication yourself.
Arrange prompt assessment for a tumor on the lip or ear
Higher risk of spread.
Avoid: Continuing unprotected sun exposure
Each dose raises the next cancer's odds.
Avoid: Tanning beds
A recognized cause, pointless after a diagnosis.
Avoid: Ignoring actinic keratoses
The step immediately before this cancer.
Avoid: Black salve and escharotic pastes
Destroy the surface, leave tumor at depth.
Avoid: Picking the crust off repeatedly
Keeps it looking nearly healed.
Avoid: Smoking
Lip cancer, and poorer healing after removal.
Avoid: Waiting on a spot that will not heal
The biggest factor in outcome.
Avoid: Skipping follow-up appointments
New cancers are common after the first.
Treatments
Treatments for Squamous Cell Carcinoma
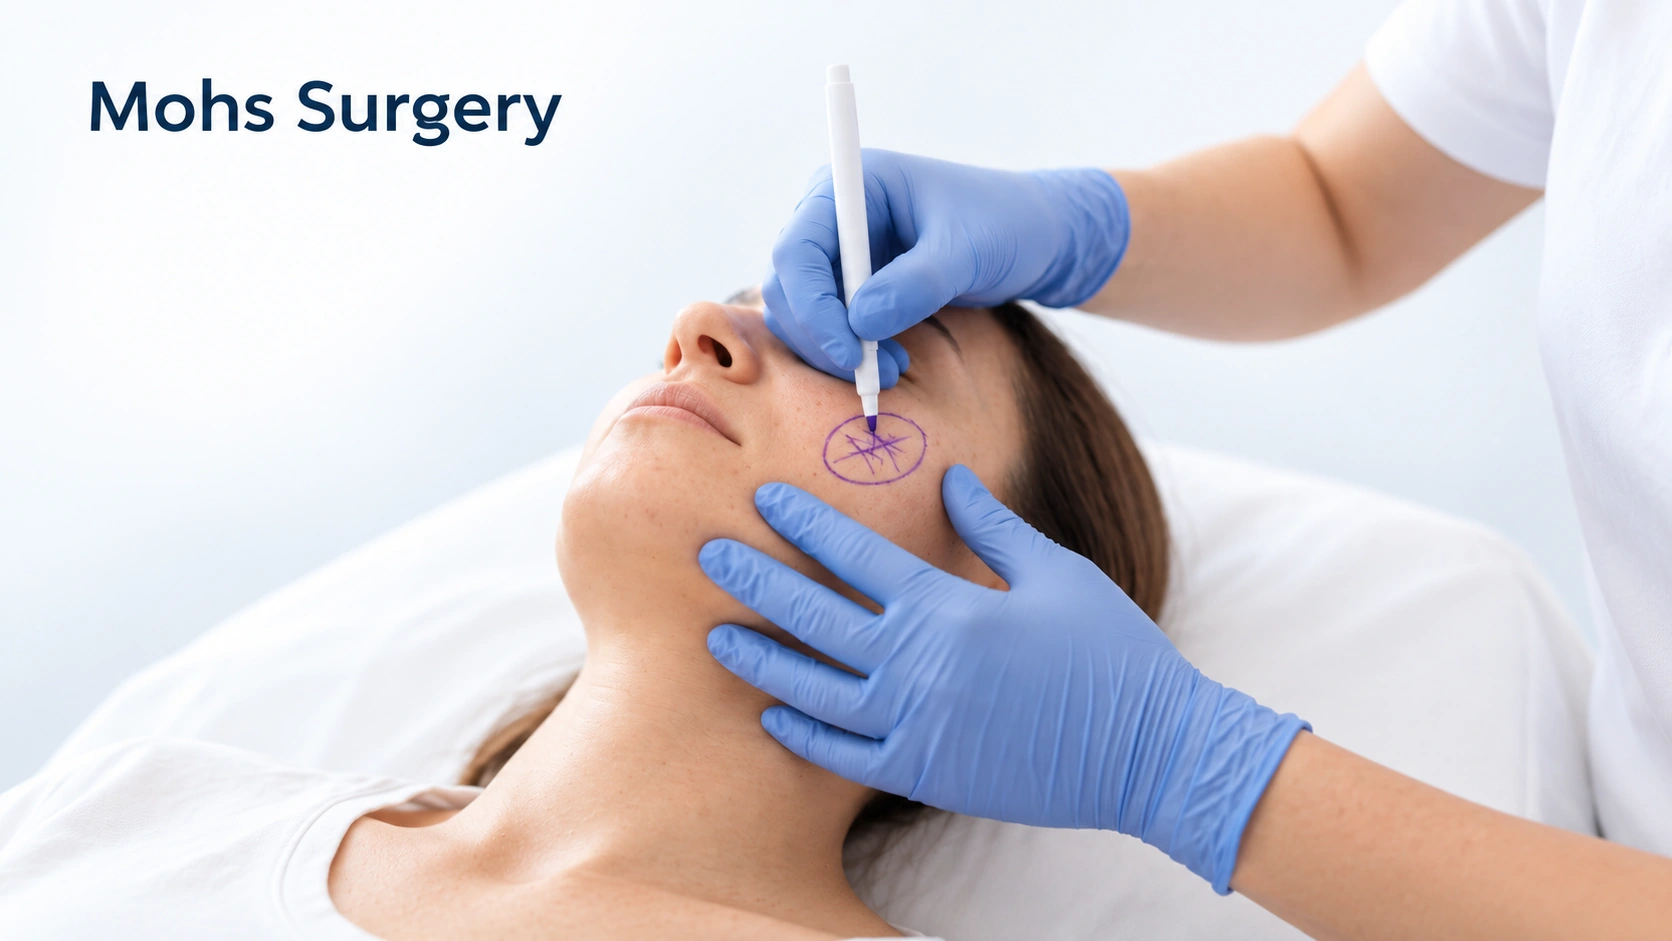
Mohs Surgery
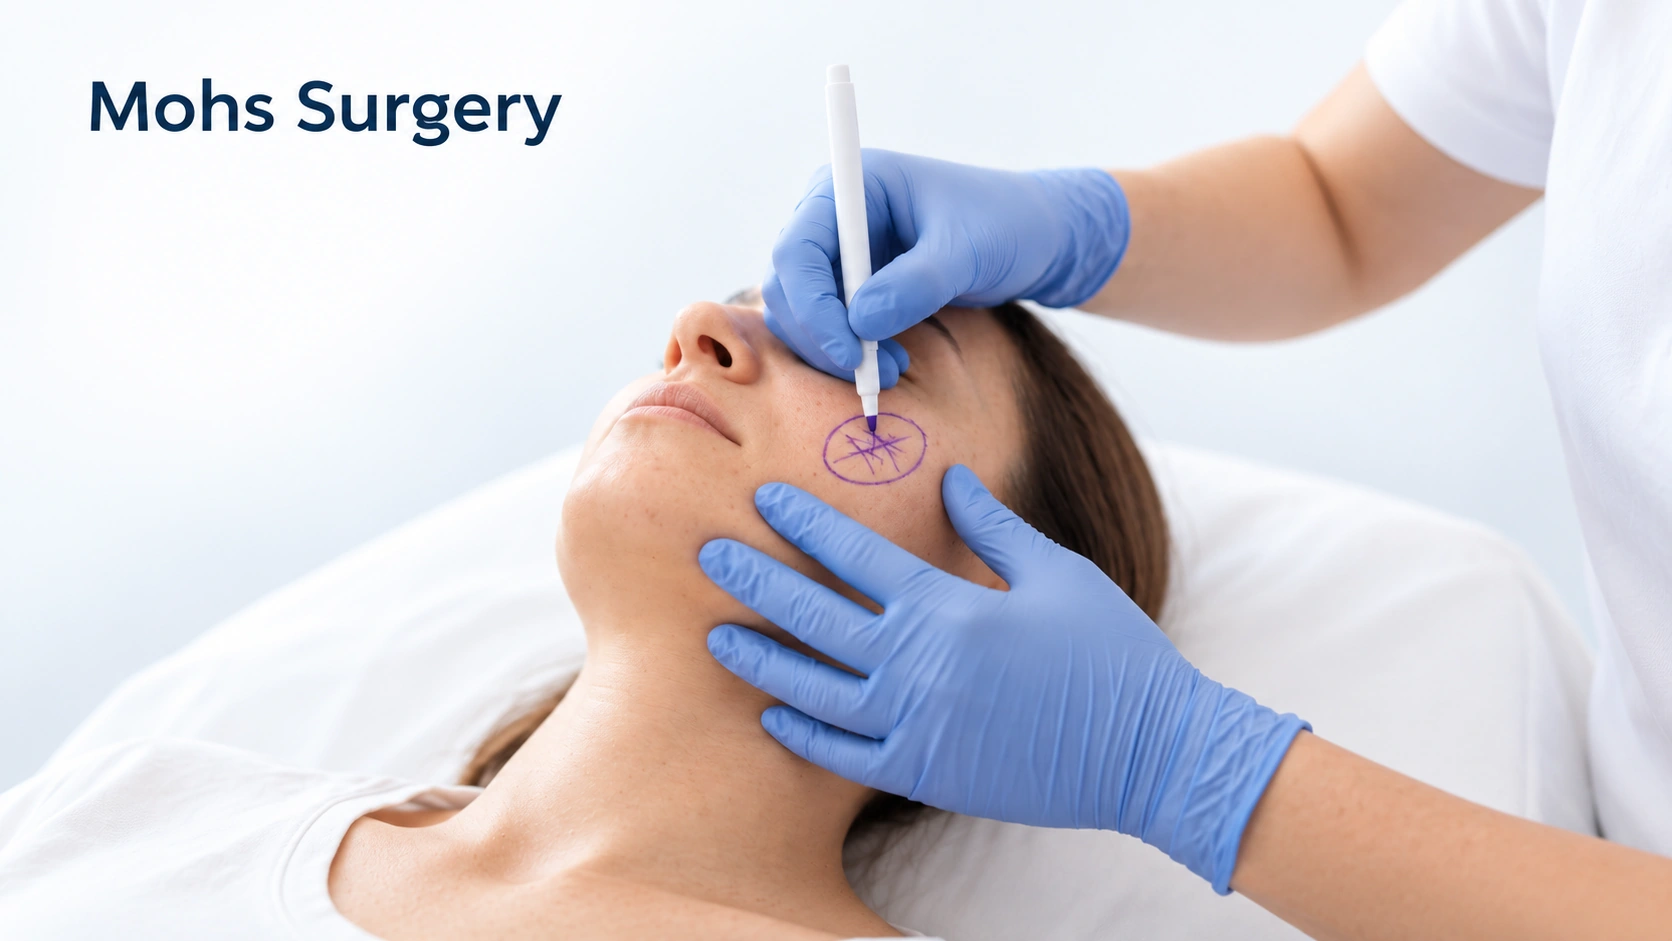
The tumor is removed a layer at a time and each layer is checked under the microscope during the same appointment, so the surgeon stops as soon as the edges are clear. It gives the highest cure rate and takes the least normal skin, which is why it is used on the face, ears, lips, hands, feet and genitals, and for large, recurrent or aggressive tumors. It is a long appointment rather than a difficult one.
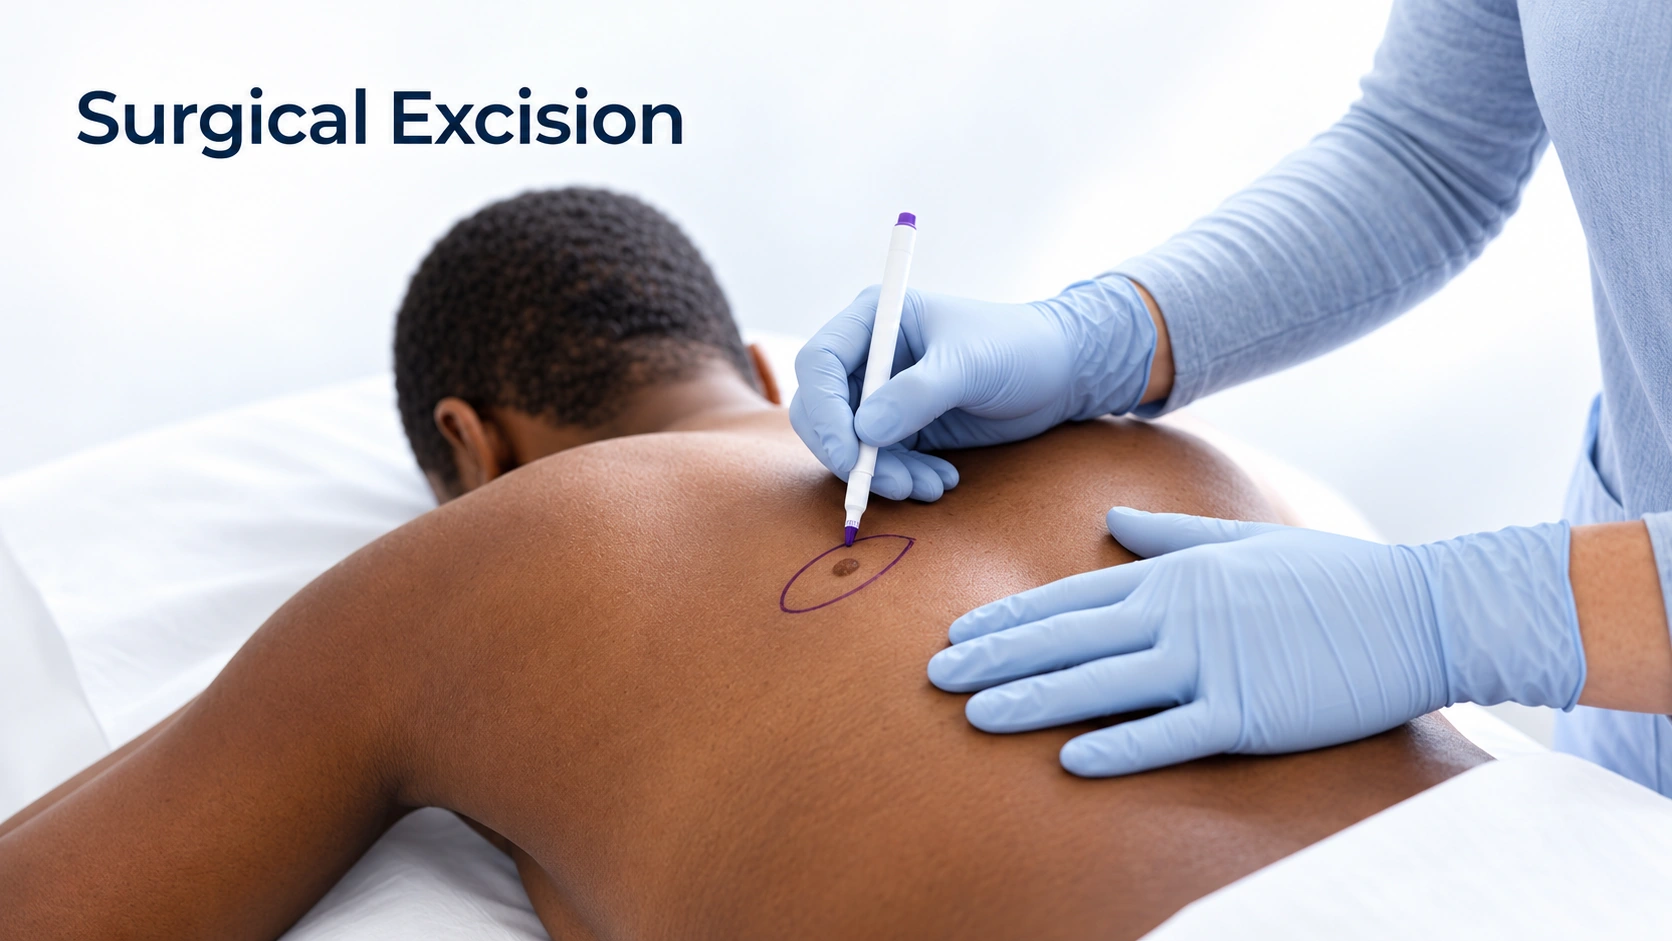
Excision
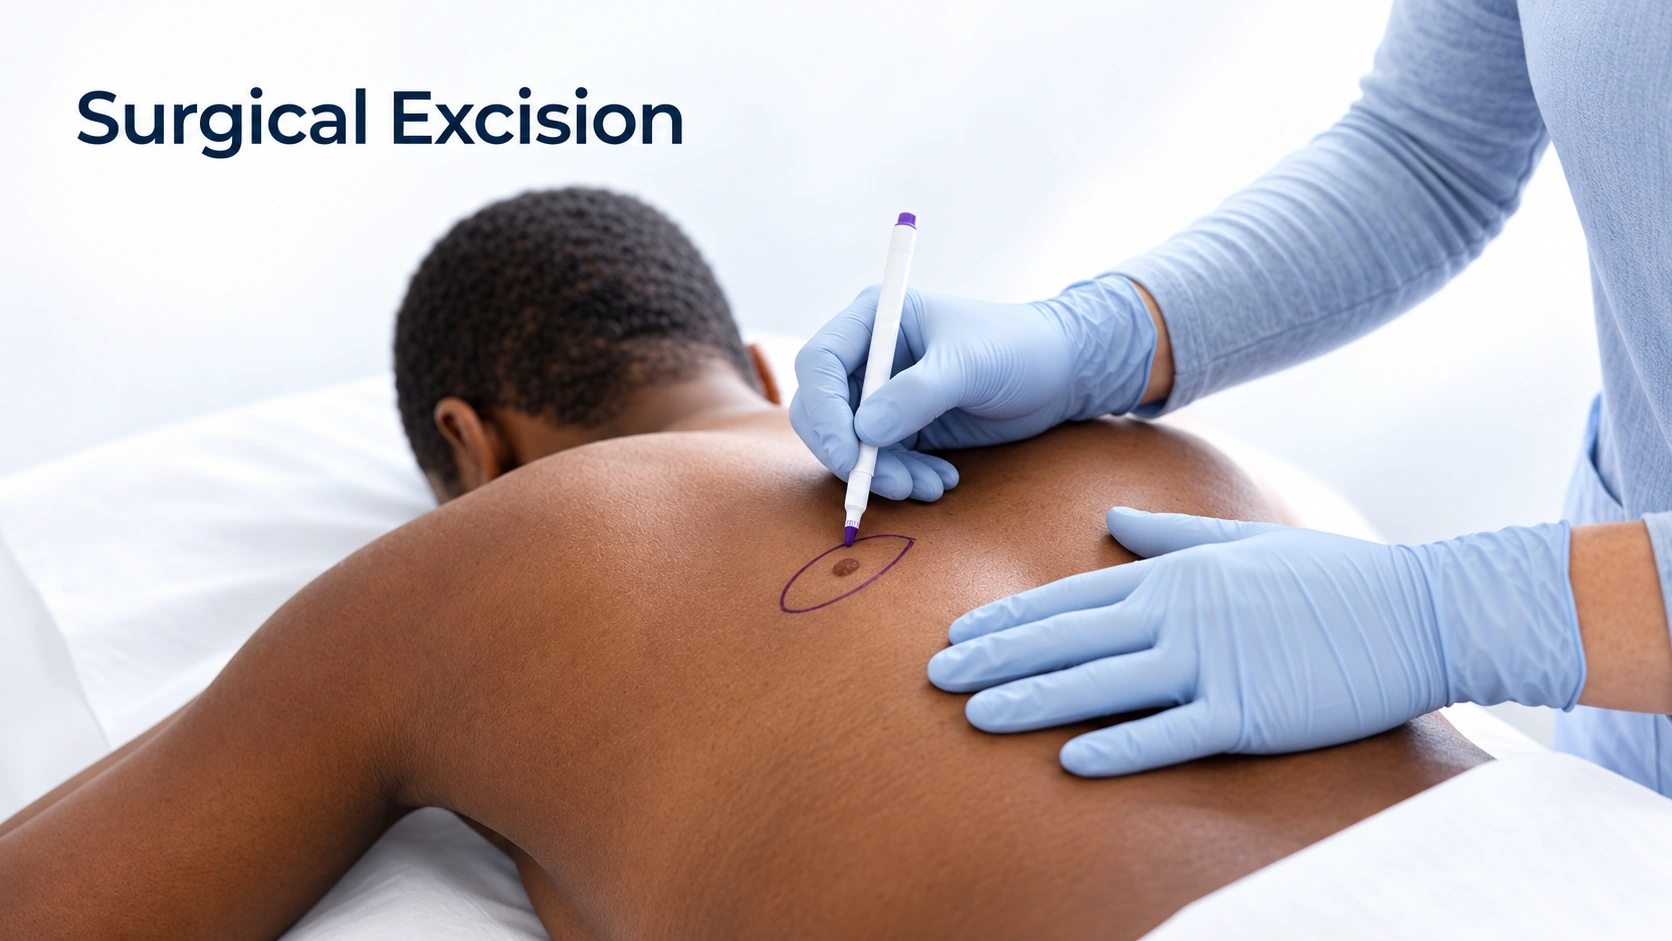
The standard removal: the tumor is cut out with a margin of normal skin around it and the wound is stitched closed, usually in one visit under local anesthetic. It cures the large majority of straightforward tumors on the trunk, arms and legs. The margins are checked afterwards rather than during, so occasionally a second procedure is needed to clear an edge.

Electrodesiccation and Curettage
The tumor is scraped out with a small loop and the base is sealed with an electric current, repeated a few times in one sitting. It is quick and effective for small, thin, low-risk tumors on the trunk and limbs. It is not used on the face, on large or recurrent tumors, or anywhere depth matters, because nothing is sent for margin checking and it leaves a round pale scar.
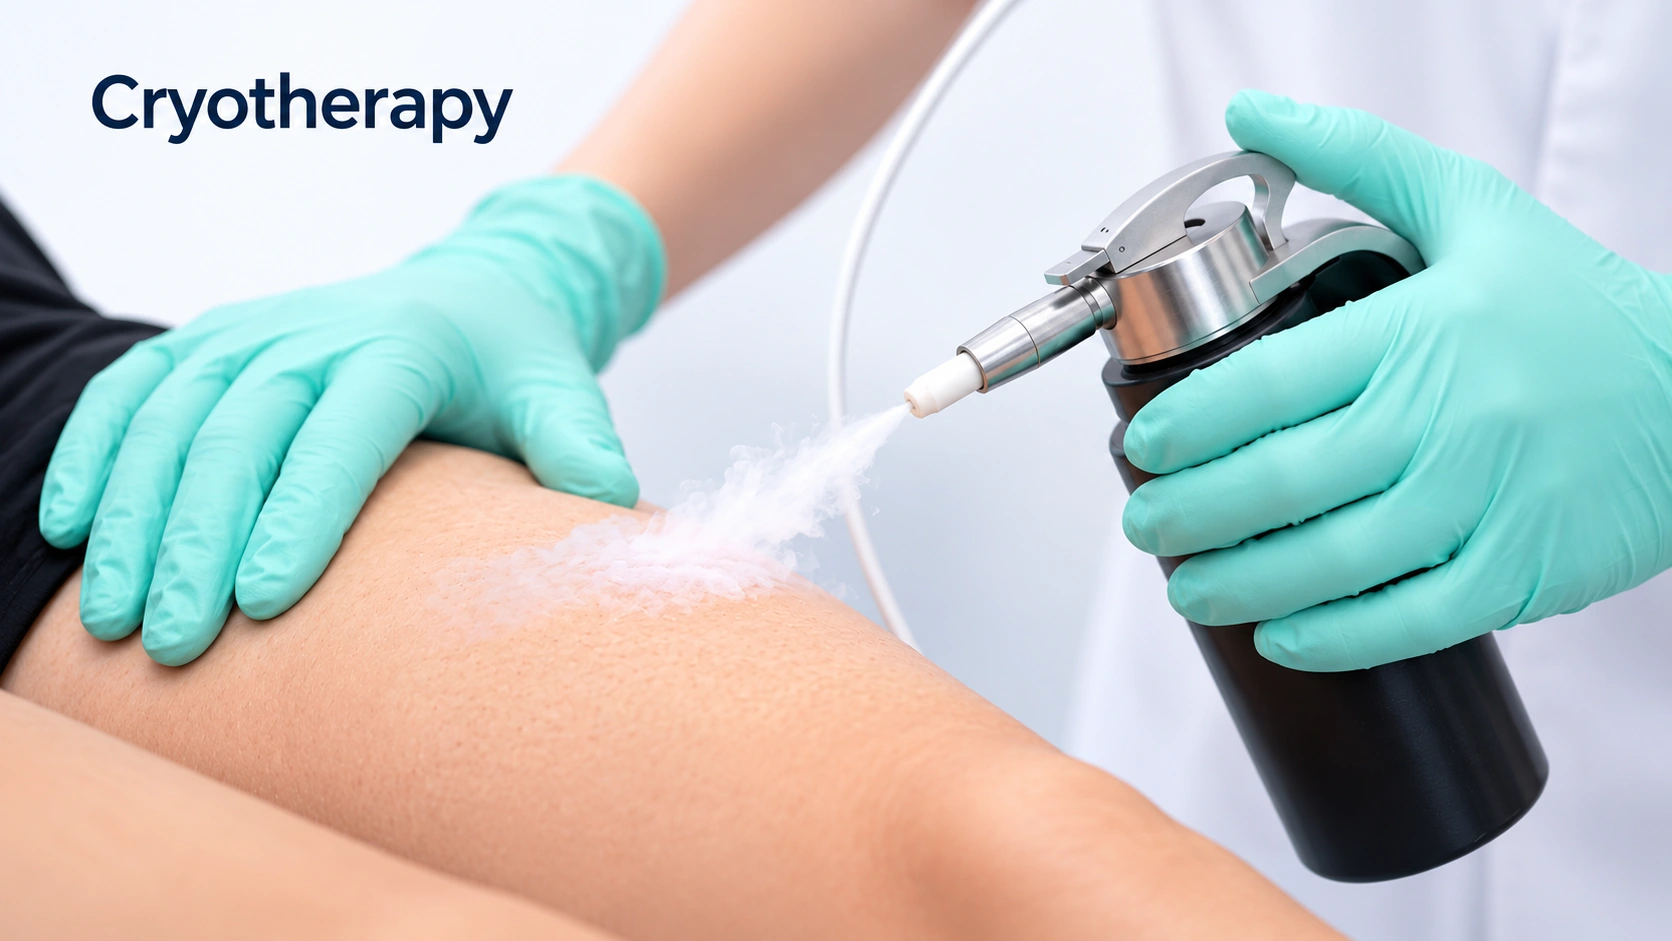
Cryotherapy
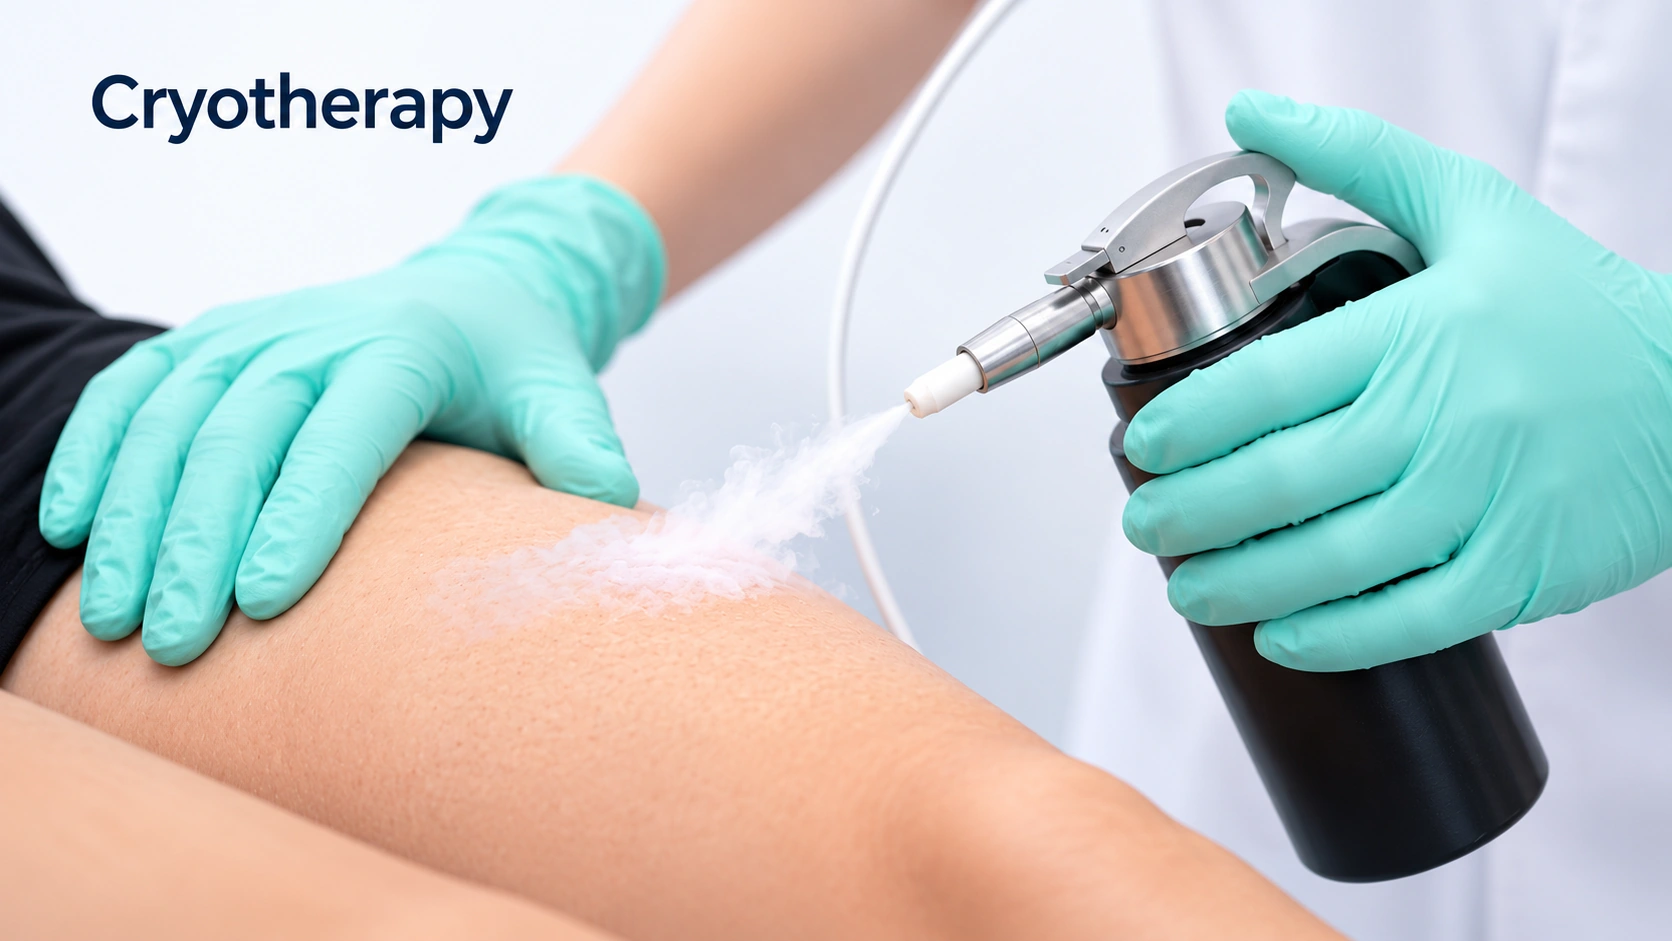
A quick freeze in clinic, used for actinic keratoses and occasionally for a small patch of carcinoma in situ. It is a treatment for the step before this cancer, not for the cancer itself. Freezing an invasive tumor leaves cells behind at depth and hides what is happening under a healing crust.

Photodynamic Therapy
A light-activated cream treatment for the earliest forms only — actinic keratoses and some cases of carcinoma in situ. It treats a whole patch of sun-damaged skin at once and heals with a good cosmetic result. It has no role in an invasive tumor, and using it on one delays proper removal.
Skin Biopsy
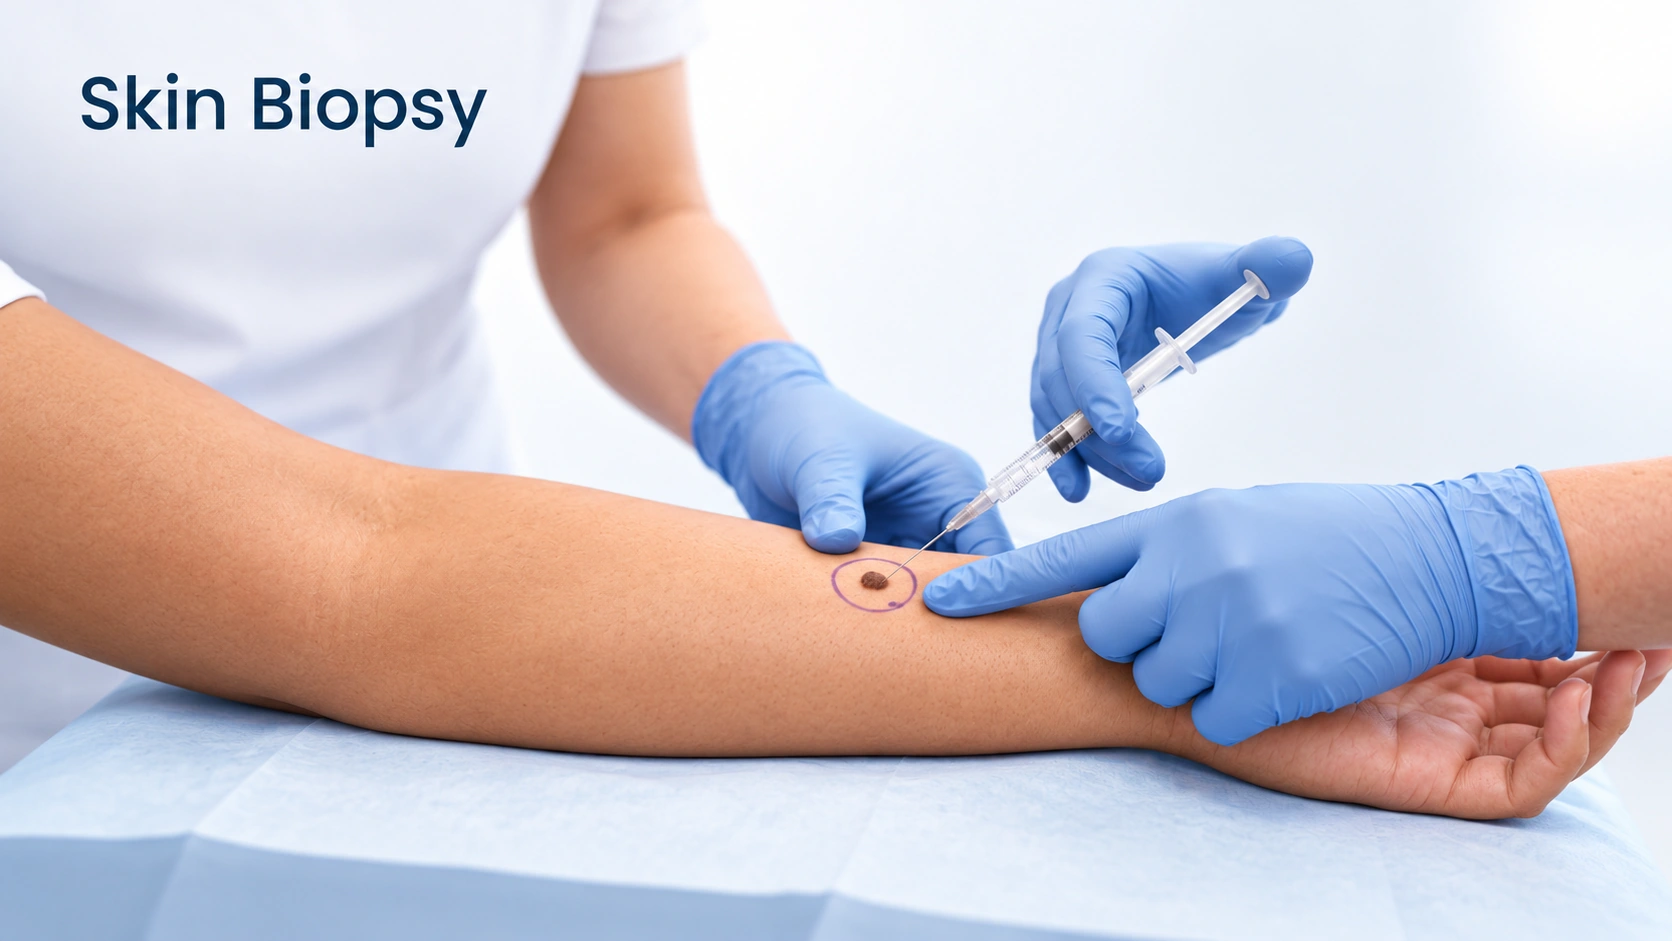
Nothing else on this page happens without it. Even an experienced dermatologist with a dermatoscope cannot settle this by looking, and the report says far more than yes or no — how deep it goes, how aggressive the cells look, whether it is tracking along a nerve. Those details choose the treatment. It takes a few minutes under local anesthetic and leaves a small wound. A biopsy does not make cancer spread.
Outlook
What to expect with Squamous Cell Carcinoma
Left alone, this follows a predictable path. It does not resolve, and the stages below take years, or weeks to months in immunosuppressed people. Most people are cured by removal, though new skin cancers are common afterward, so regular skin checks are part of the treatment.
- 1
Field damage · Years of exposure
Sun-damaged skin develops rough patches, mottled color and broken vessels. The ground is prepared, no cancer yet.
- 2
Actinic keratosis · Precancer
A rough, scaly, sandpapery patch. Any single one is unlikely to become cancer, but they mark skin that can.
- 3
Carcinoma in situ · Early cancer
A persistent scaly red or darker patch that looks like eczema or psoriasis but never responds to creams. The cells are still confined to the top layer.
- 4
Invasive tumor · Weeks to months
A firm, tender bump or a sore that will not heal, often crusted, often bleeding when caught. It grows steadily. Untreated it grows into fat, cartilage, muscle or bone and can track along nerves. That turns a small removal into a large reconstruction.
- 5
Spread · Uncommon but serious
A small percentage spread to nearby lymph nodes and occasionally further. Higher risk with large or deep tumors, ear or lip sites, recurrence, and immunosuppression.
Complications
Complications to know about
A small percentage reach the lymph nodes
A small percentage spread to nearby lymph nodes and occasionally further. Higher risk with large or deep tumors, ear or lip sites, recurrence, and immunosuppression.
When to get help
When to get help
When to seek care
Arrange prompt assessment of a persistent scaly, crusted, enlarging or non-healing lesion, especially if tender or bleeding.
Lookalikes
What else could it be?
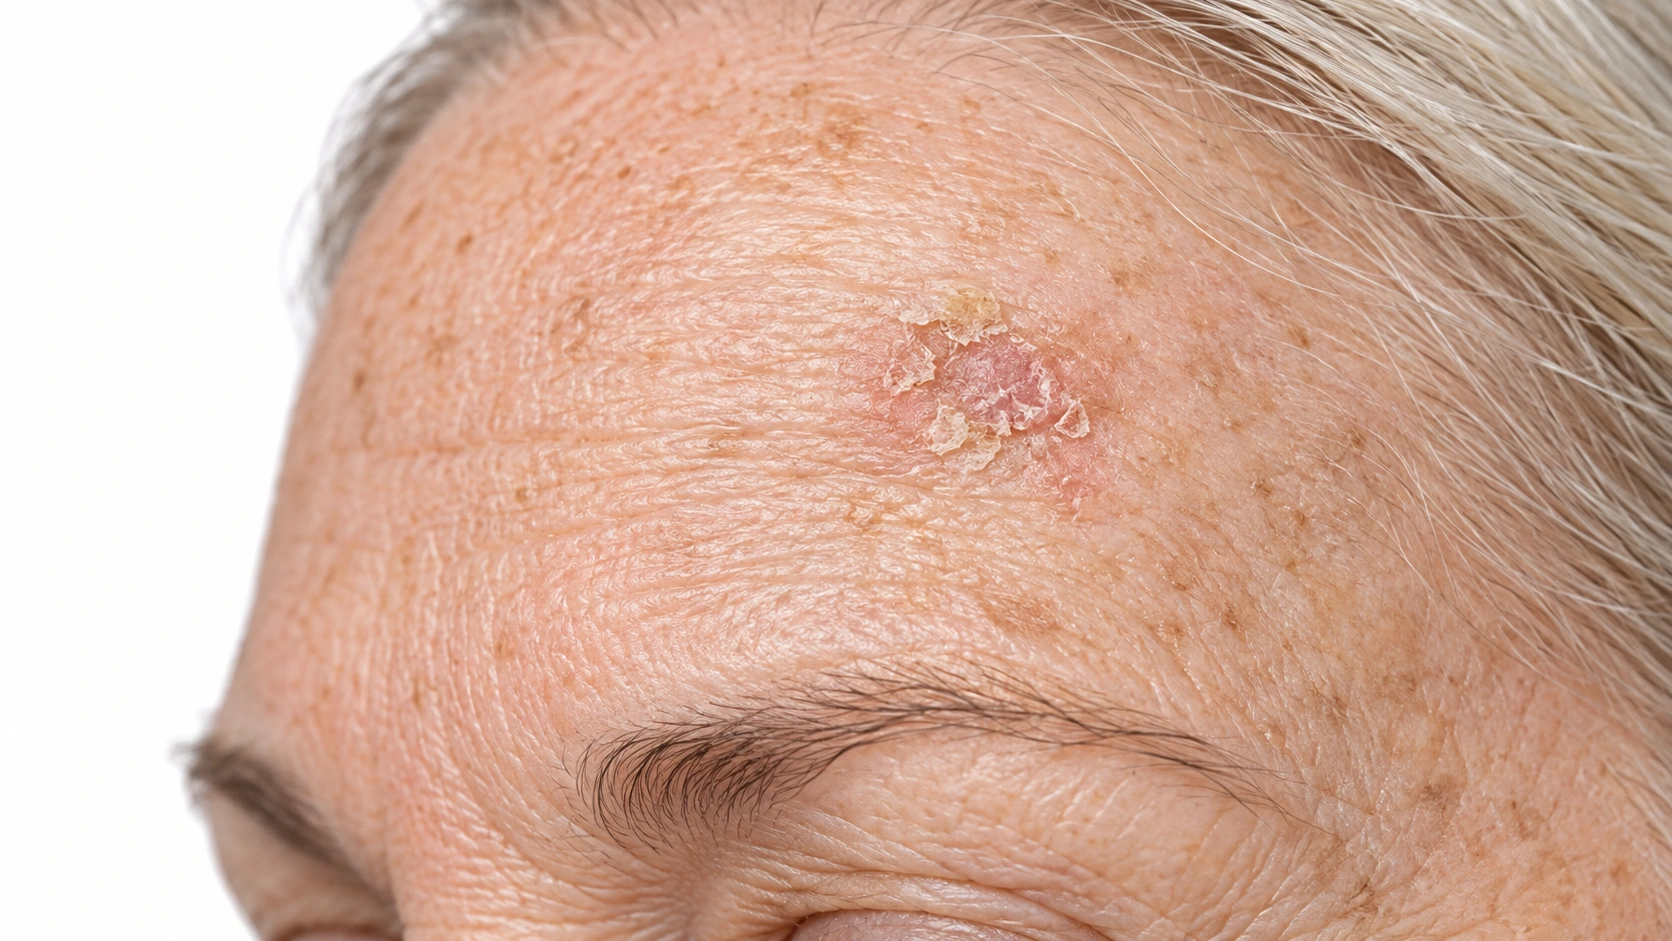
Actinic Keratosis
Actinic keratosis is often a flat, gritty patch that flakes and returns. Squamous cell cancer may thicken, become tender or bleed, and needs examination.
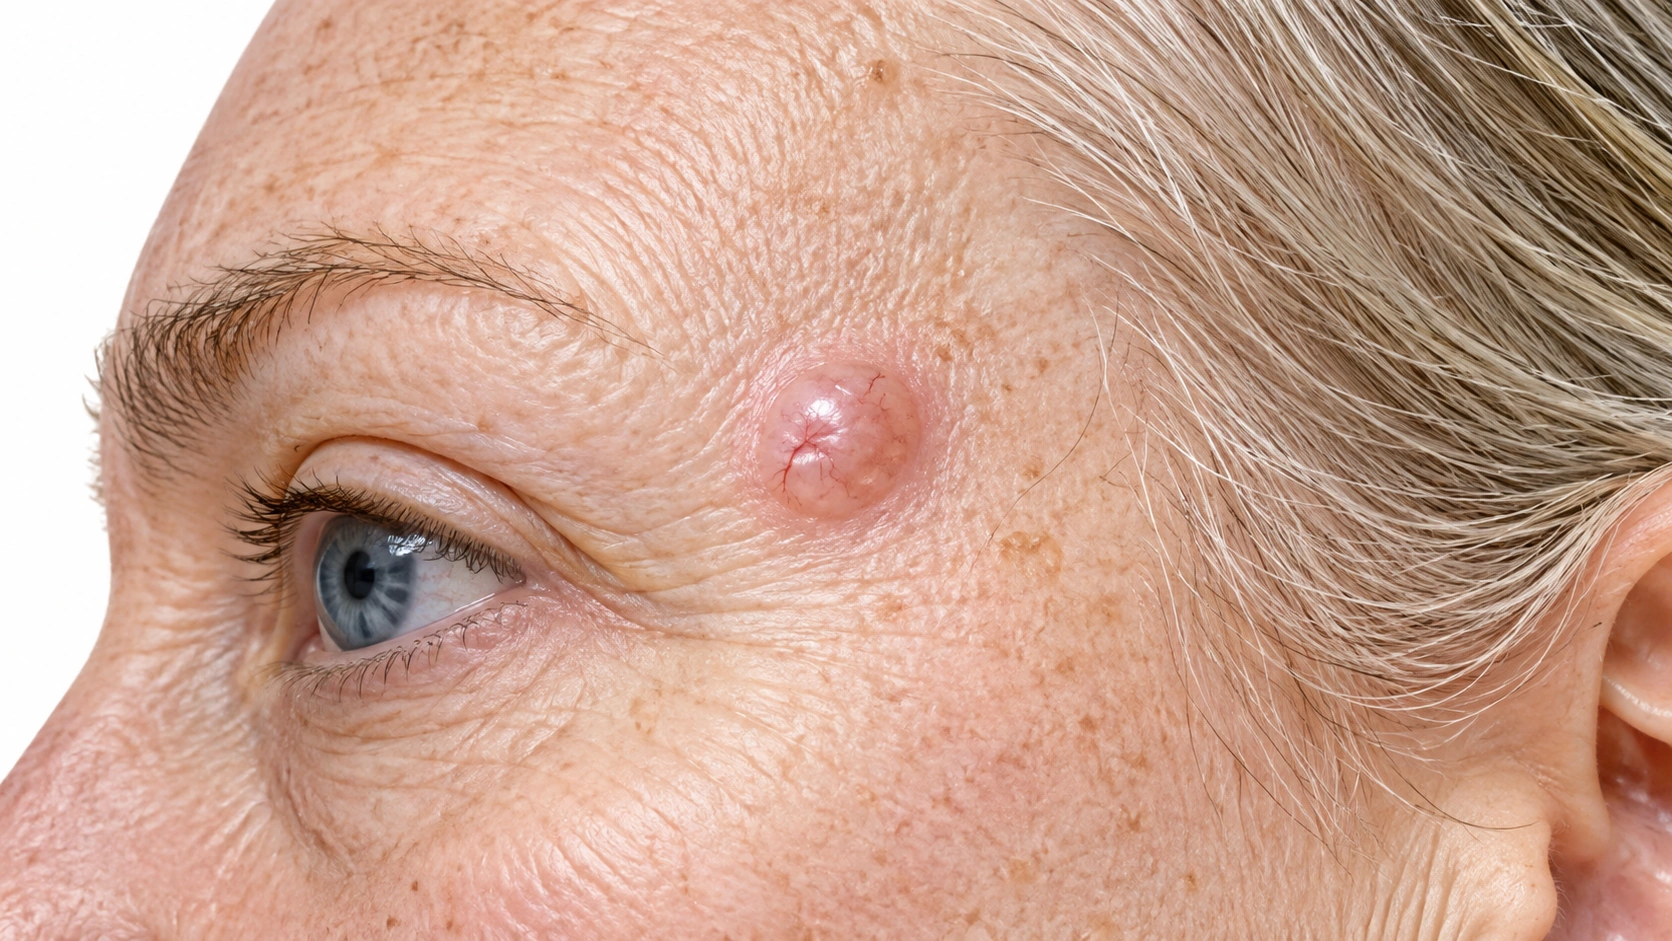
Basal Cell Carcinoma
Basal cell cancer is often shiny or pearly. Squamous cell cancer is more often rough and scaly, but a biopsy may be needed to distinguish them.

Psoriasis
Psoriasis often affects matching areas and responds to prescribed creams. One persistent patch that keeps growing or never responds needs checking for skin cancer.
Questions
Questions you might be asking.
Is squamous cell carcinoma serious?
It is a real cancer and treated as one. Most cases are cured by removal, which is why the emphasis is on early checks. Untreated, it grows into deeper structures and a small share reach lymph nodes. How serious it gets depends on how long it is left.
How fast does it grow?
Usually weeks to months rather than days or years. The keratoacanthoma variant can appear and enlarge within a few weeks. In immunosuppressed people growth can be much faster, which is why the advice for that group is more urgent.
Will I need Mohs surgery?
It depends on the site and how the tumor looks under the microscope. Mohs is generally used on the face, ears, lips, hands, feet and genitals, and for large, recurrent or aggressive tumors. Tumors on the trunk, arms and legs usually get a standard excision.
Can it come back after it is removed?
The treated one can recur, though that is uncommon when margins were clear. Far more common is a new skin cancer elsewhere, because the same damage runs through the rest of the skin. Hence follow-up after a cure.
Does having one mean I will get more?
It substantially raises the odds - many people who have one keratinocyte cancer develop another within a few years. Hence skin checks, daily sun protection and treating actinic keratoses.
Do I need a scan or a lymph node test?
Most people do not. Scans and node assessment are reserved for high-risk features - large size, deep invasion, growth along nerves, recurrence, immunosuppression - or an enlarged node. Your dermatologist decides from the pathology report and examination.
Sources
Sources and further reading
Related
Keep exploring.
Mohs Surgery

Electrodesiccation and Curettage
Surgical Excision
Basal Cell Carcinoma
Actinic Keratosis
Photodynamic Therapy
Psoriasis
Cryotherapy
Skin Biopsy
Squamous Cell Carcinoma vs Actinic Keratosis
Squamous Cell Carcinoma vs Seborrheic Keratosis