It combines scraping and heat.
A lesion is scraped with a curette and treated electrically.
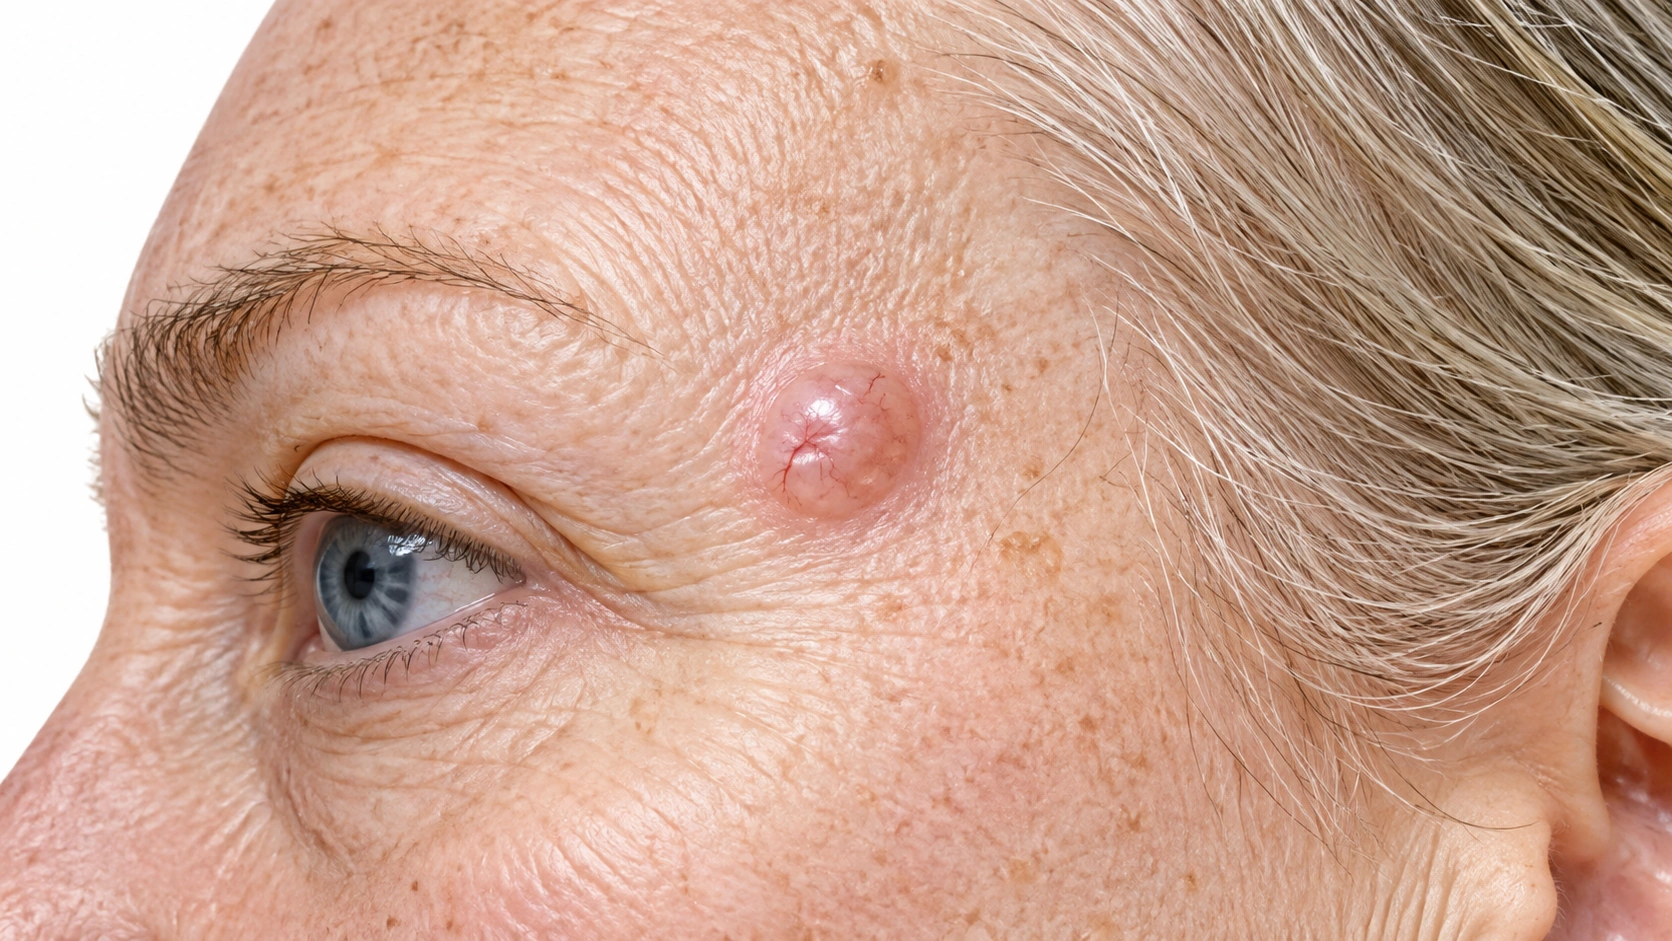
Electrodesiccation and Curettage: A small, low-risk skin cancer is scraped out with a sharp loop, and the base is then burned. It takes one visit and needs no stitches. It leaves a round pale scar, and the edges are never checked under a microscope.
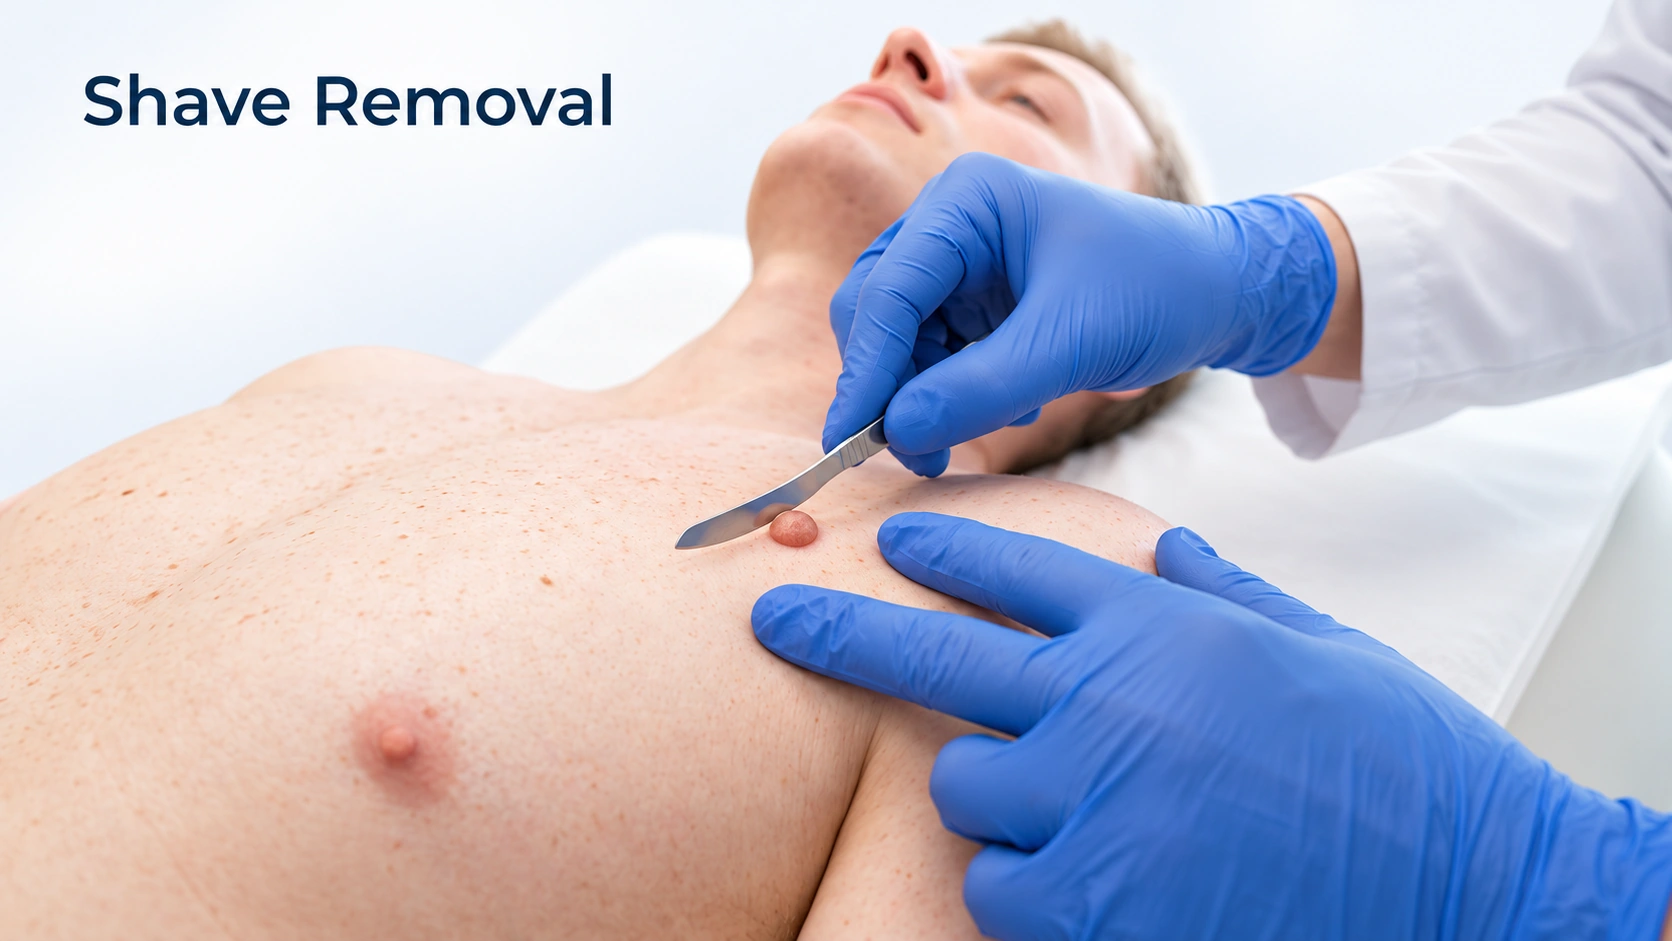
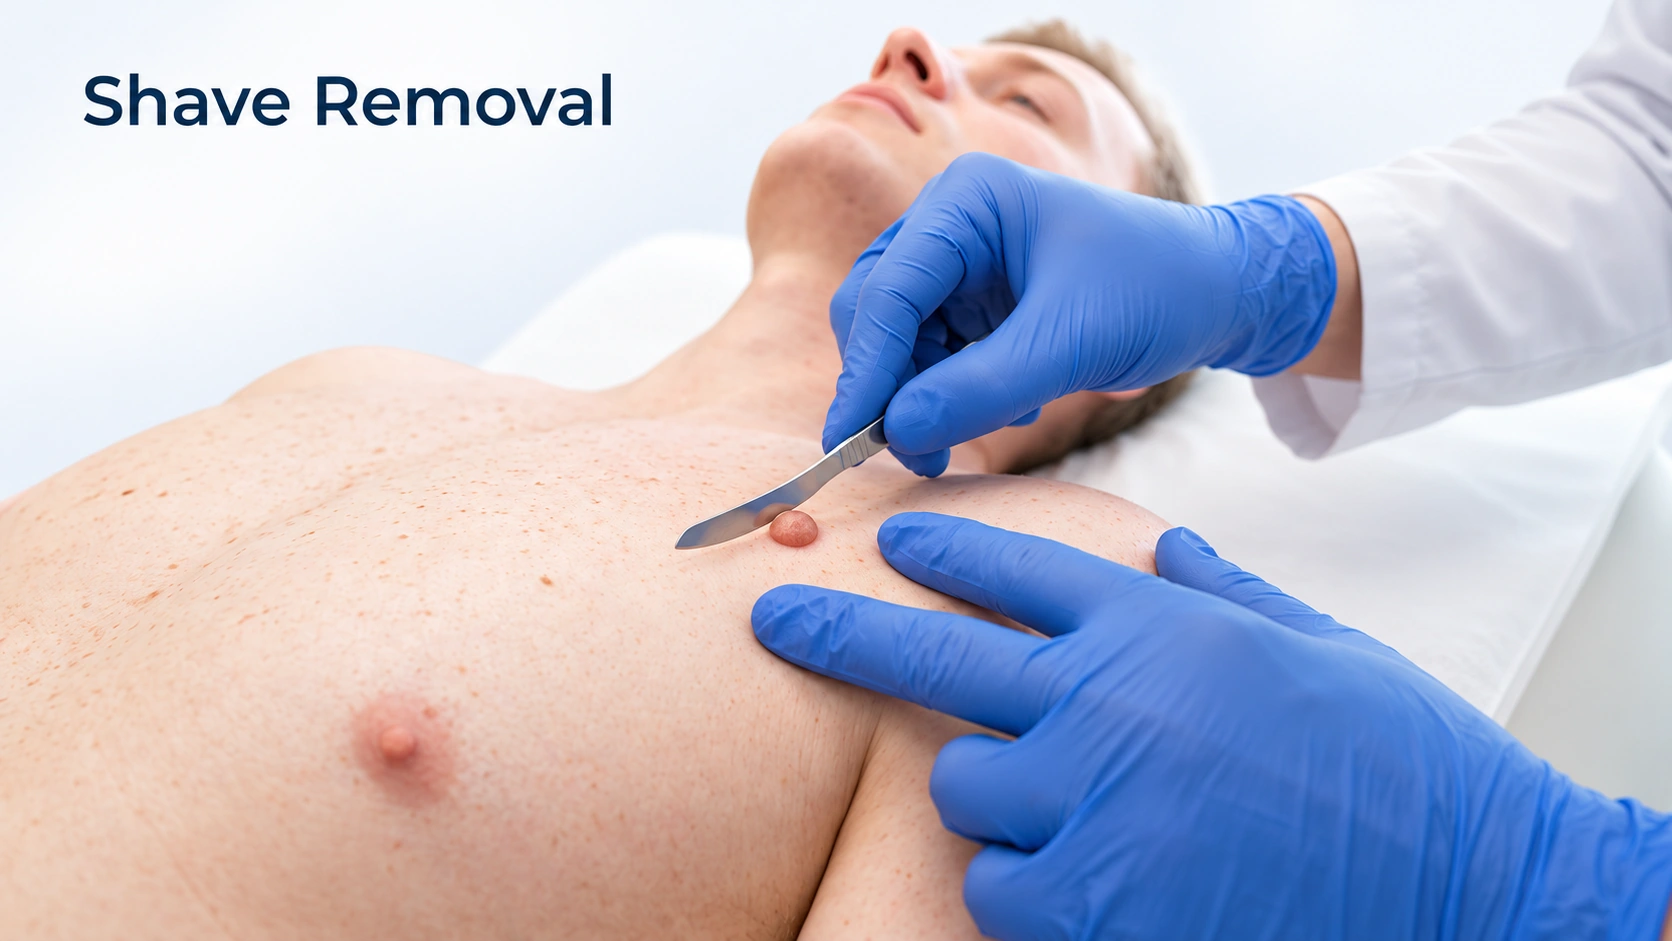
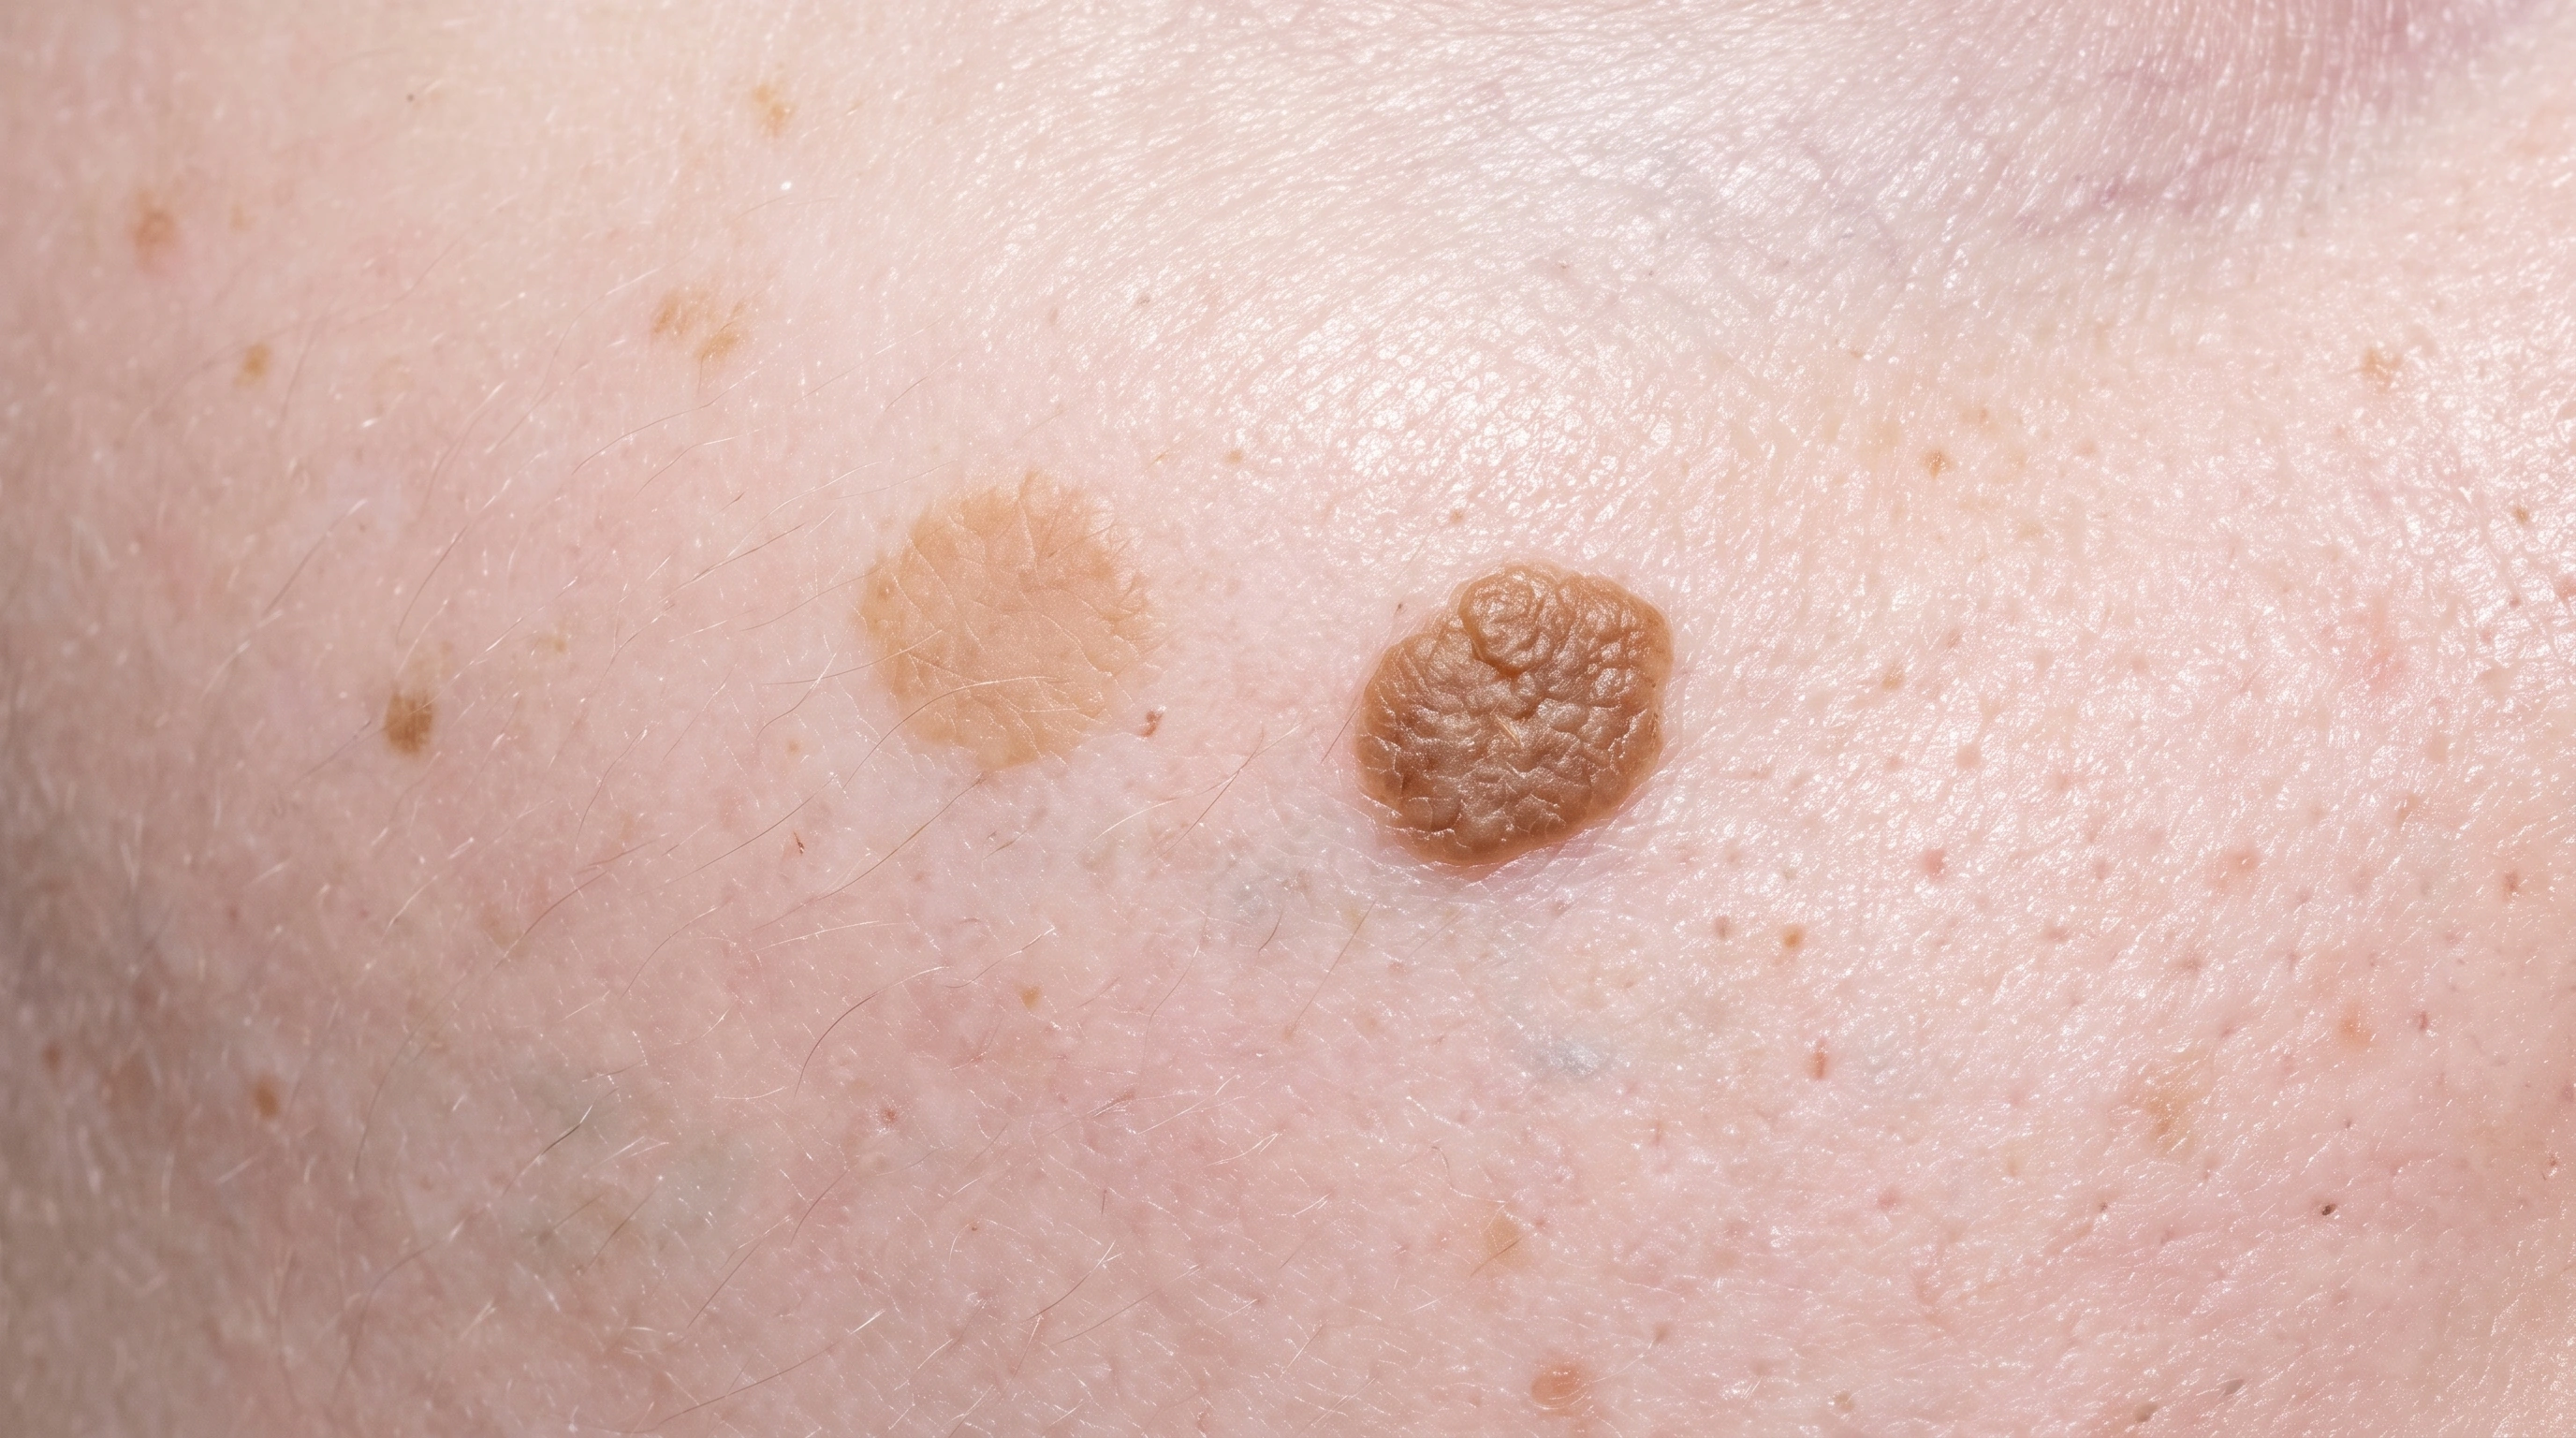
Shave Removal: A raised spot is numbed and shaved off level with the skin using a small flexible blade. No stitches and no hole — a scab that heals in a week or two. The same procedure can remove a harmless bump or take a sample for the laboratory.

Choose for a small, low-risk skin cancer on the body when one quick visit with no stitches matters more than margin checking.
Choose to remove a raised bump with no stitches — a flat mark that heals in a week or two.
Can you have both?
Often done together: a shave removes the growth and curettage cleans the base.
A lesion is scraped with a curette and treated electrically.
It can treat carefully selected low-risk skin cancers.
It lacks the margin assessment of excision or Mohs surgery.
Type, site, size and depth determine suitability.
A lesion is shaved off at a chosen depth under local anesthesia.
It can remove raised benign growths or obtain a specimen.
The clinician chooses the technique.
Cosmetic removal must not replace adequate sampling.
High cure rates for small tumors.
Removes growths quickly.
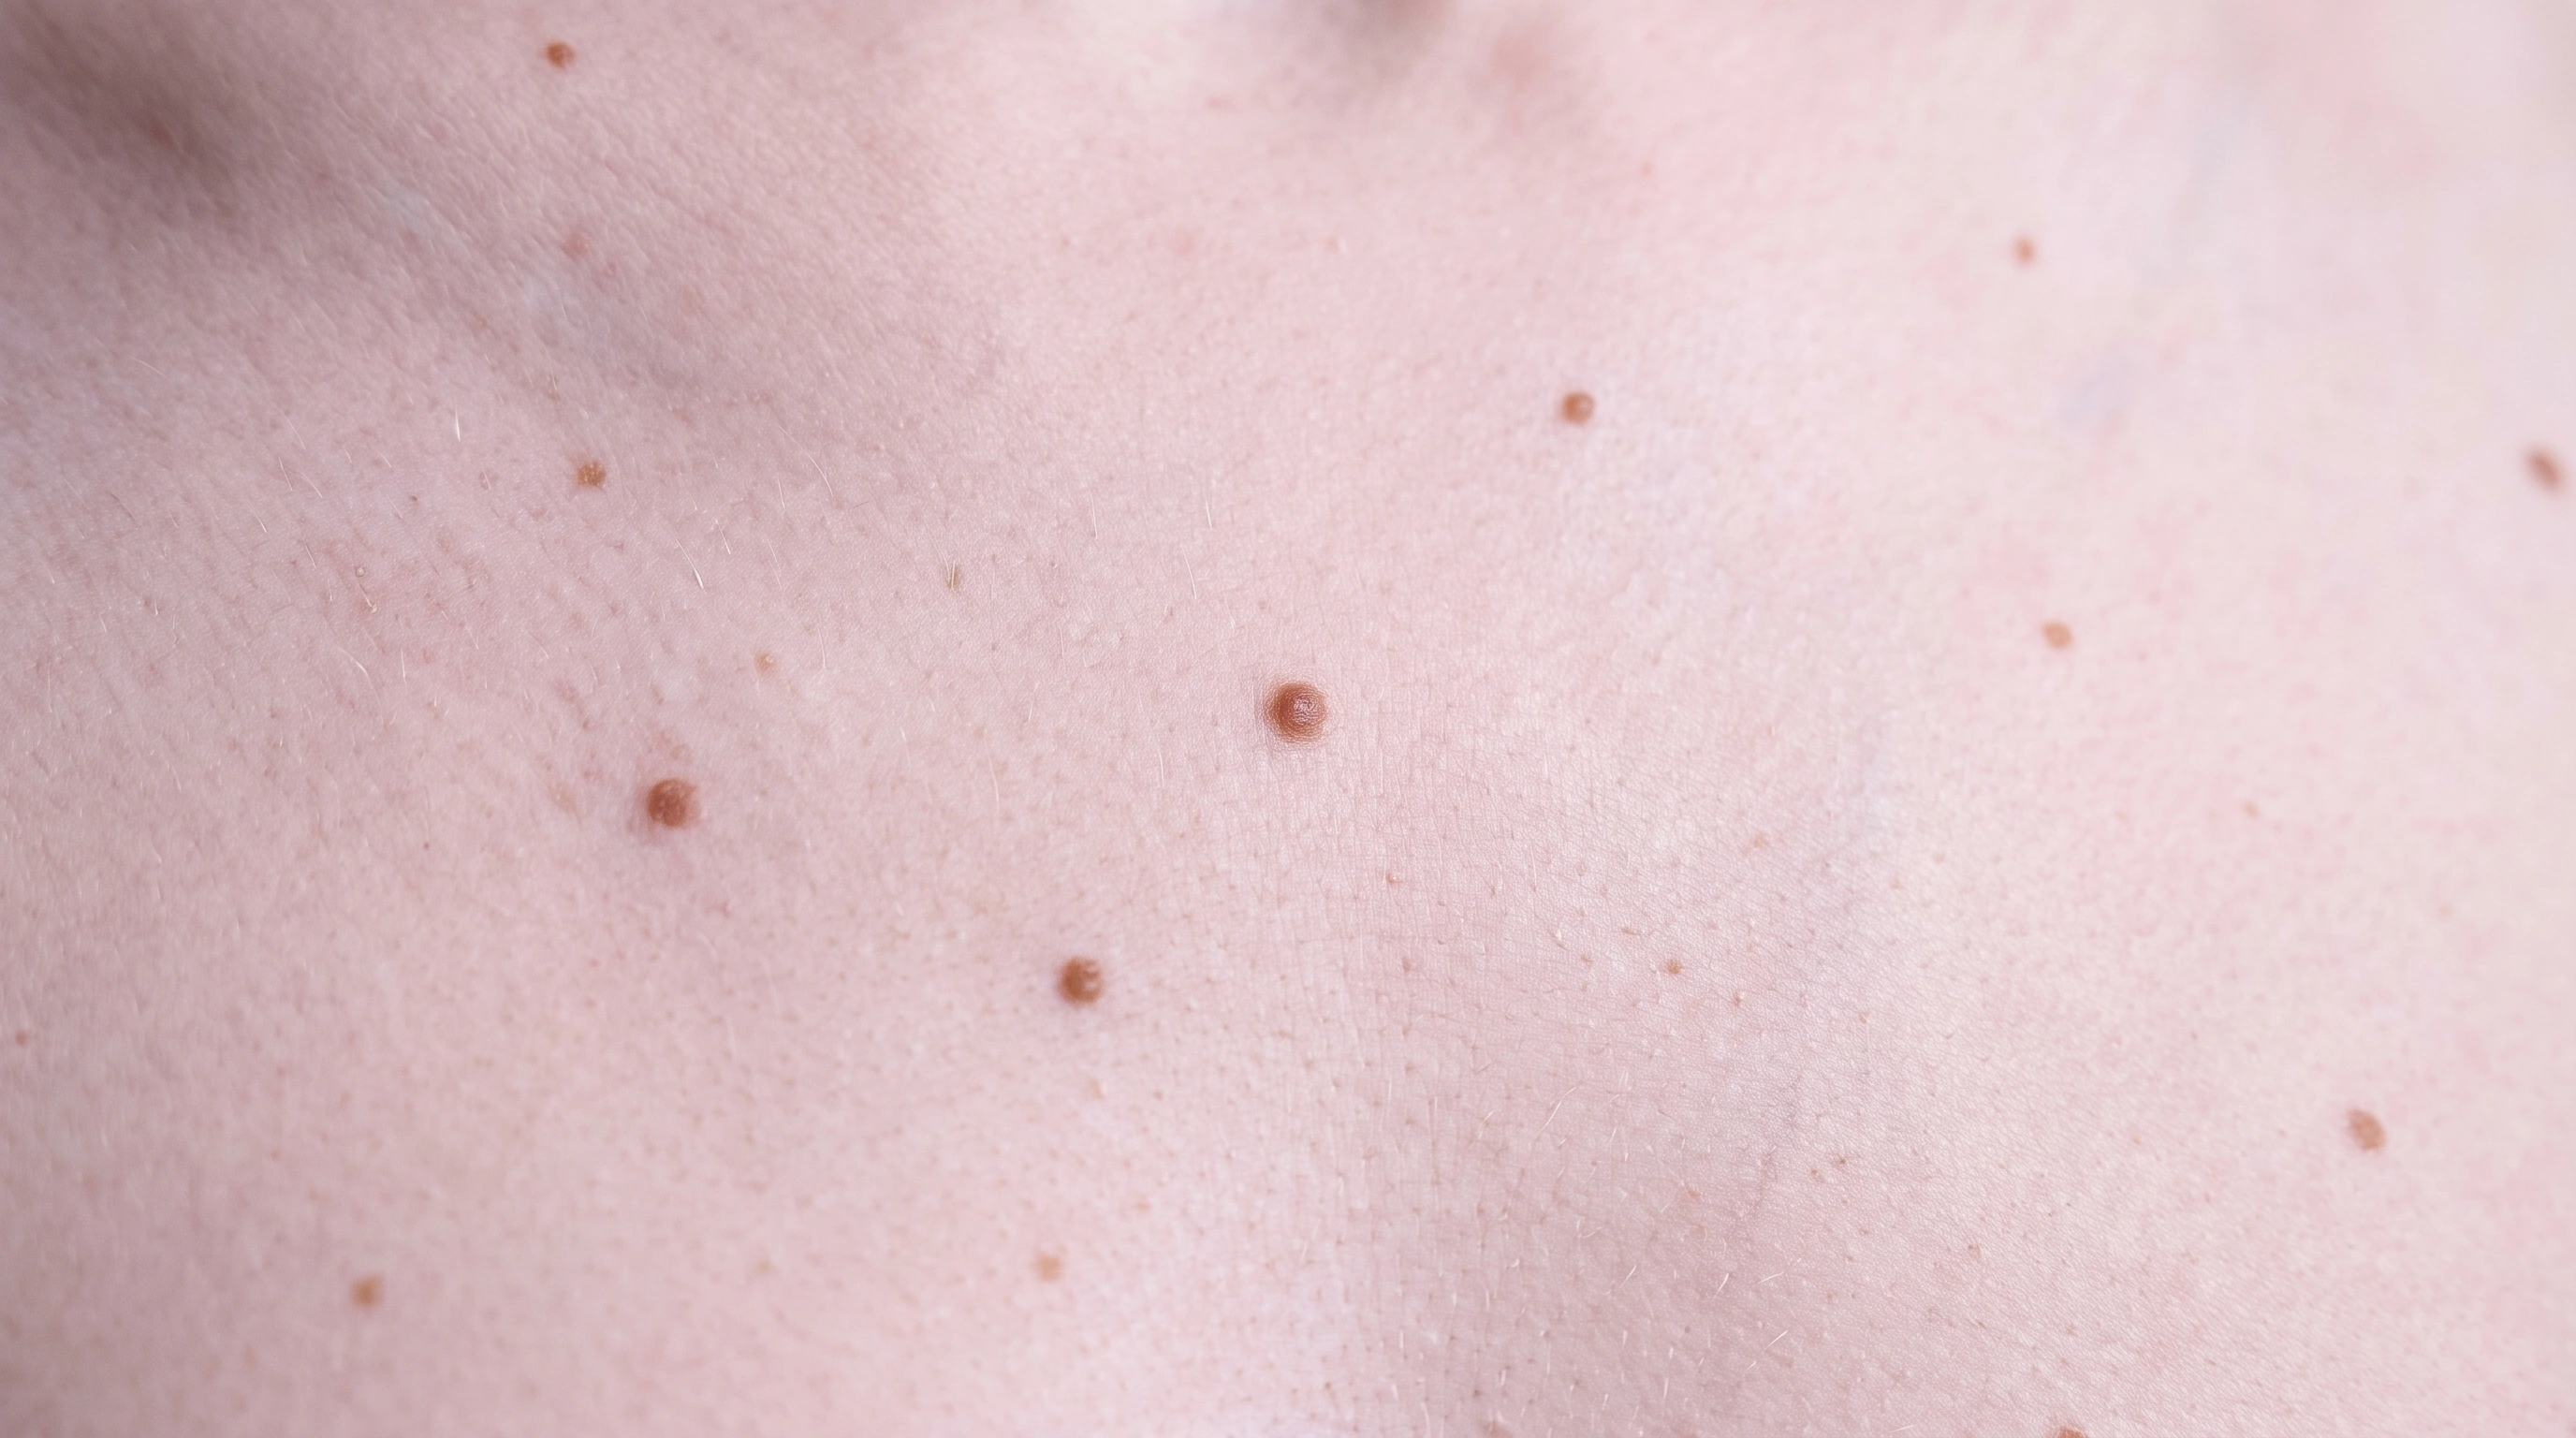
Removes raised moles.
Removes raised growths.
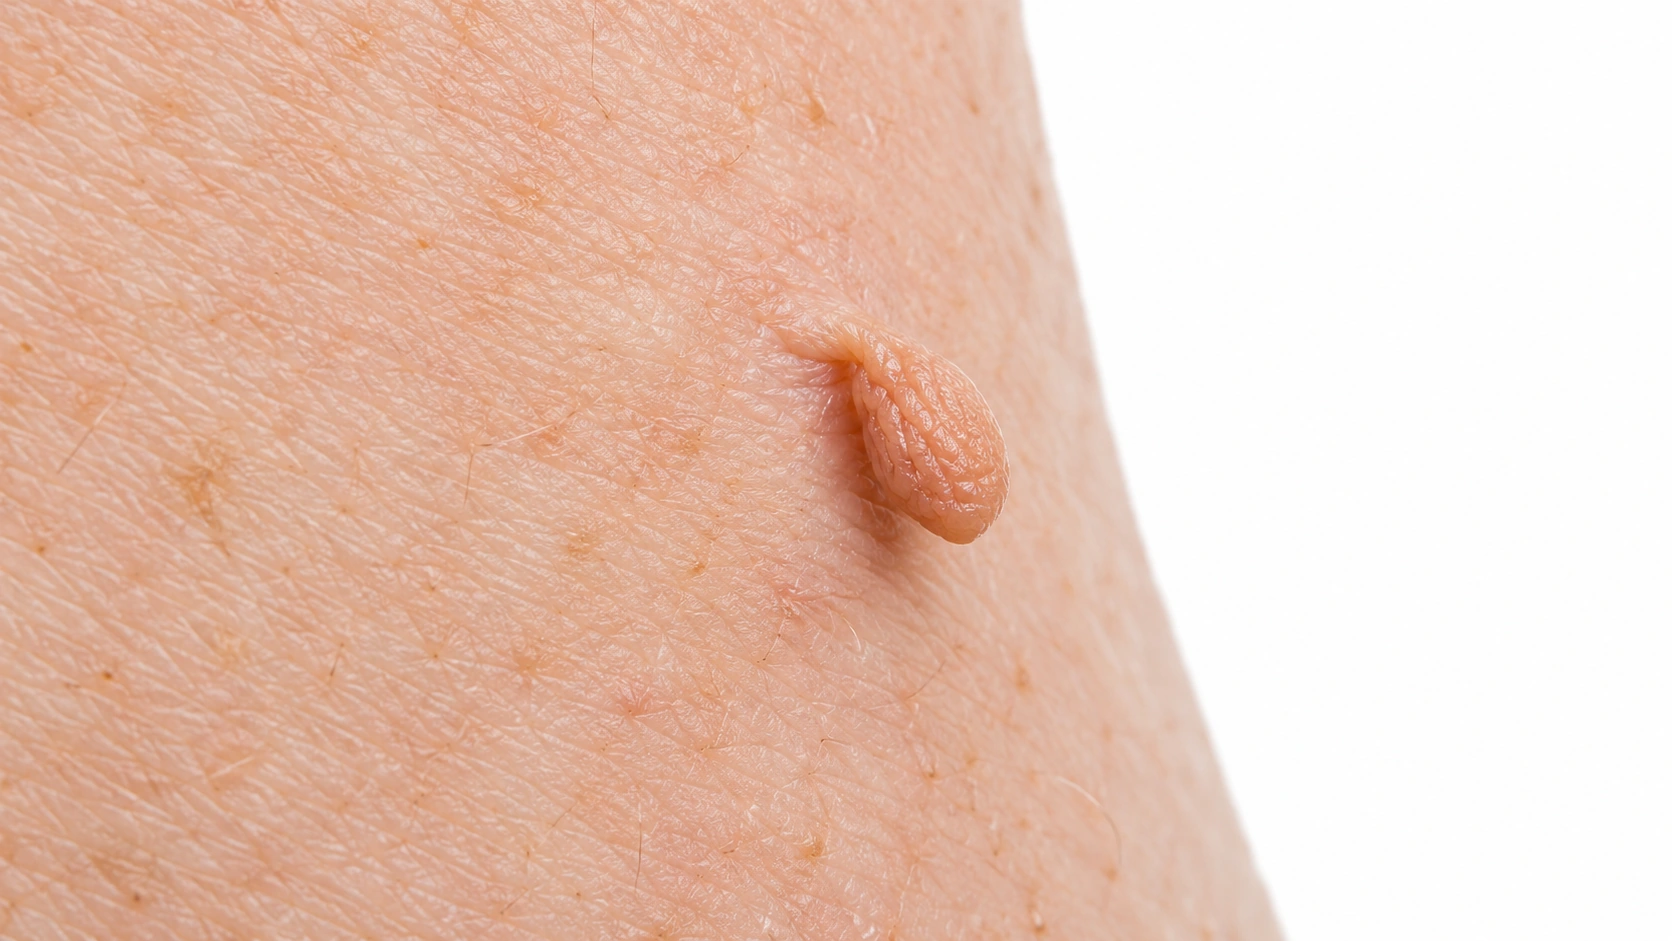
Quick removal.
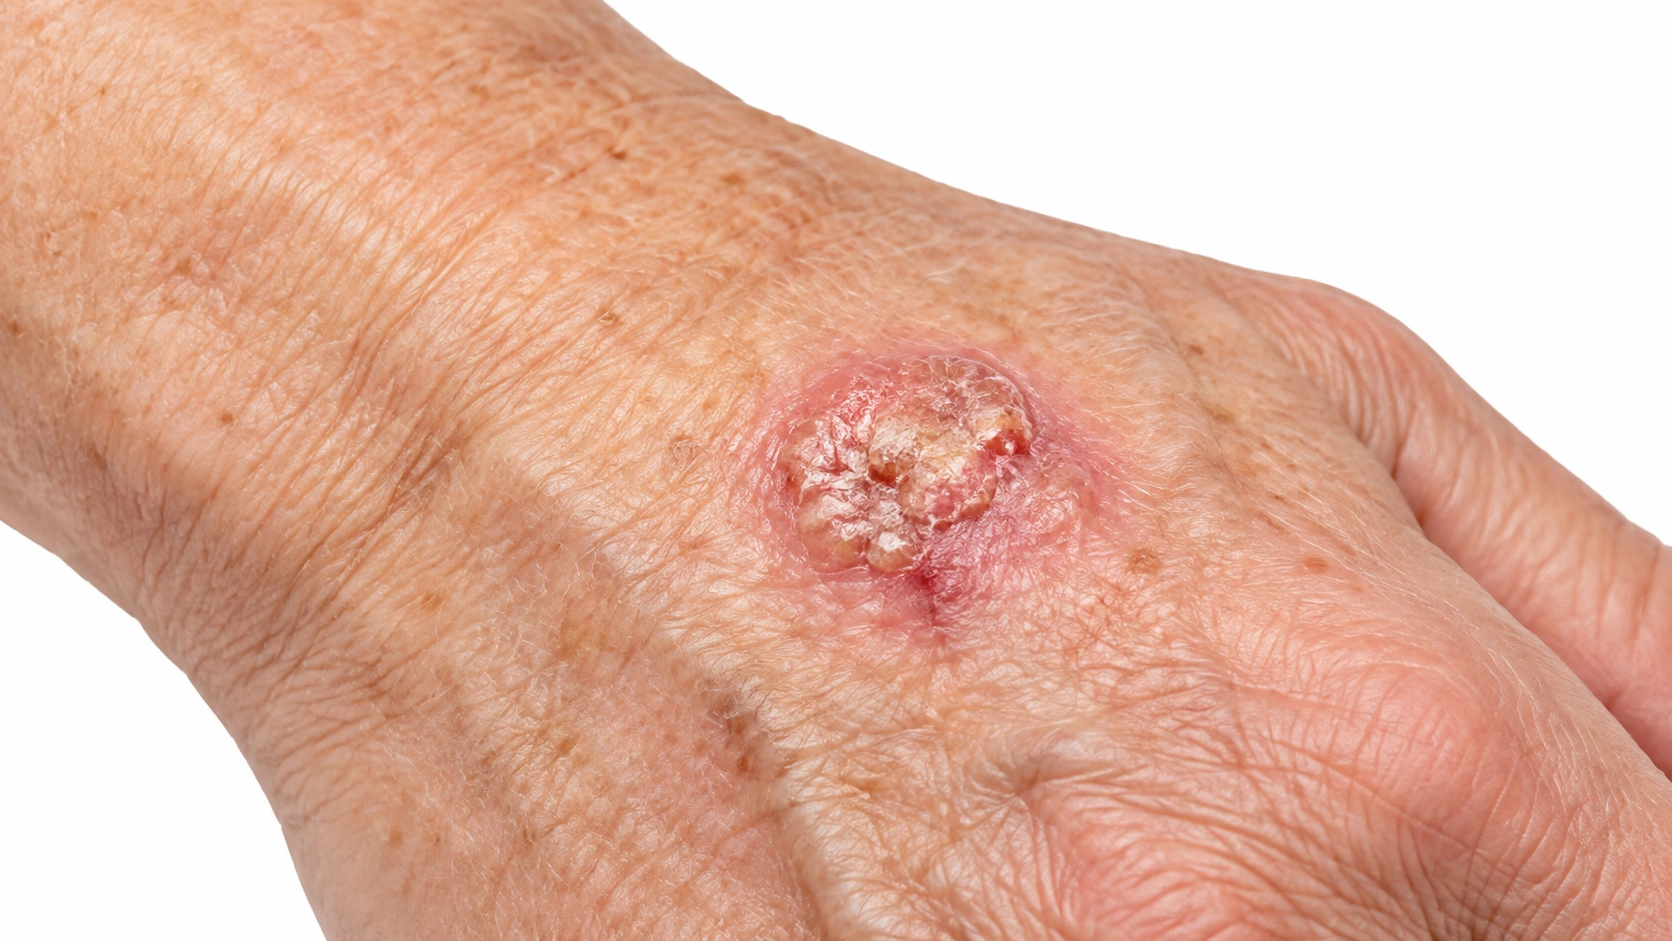
For small, low-risk tumors.
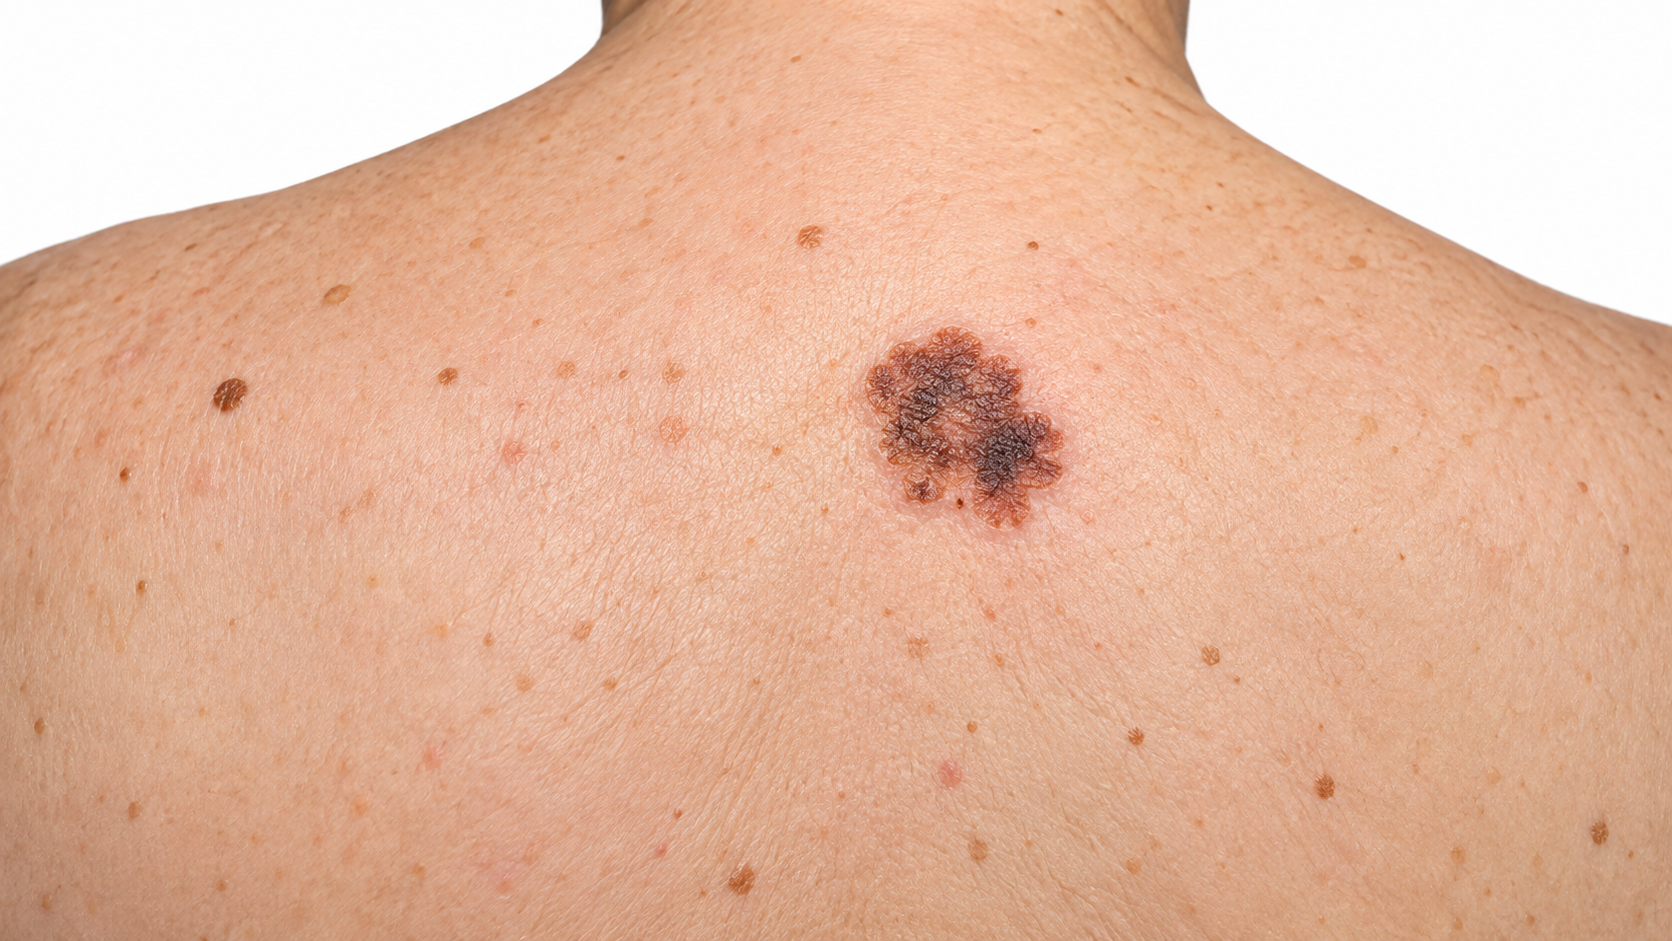
Needs excision with margins.
Needs full excision.
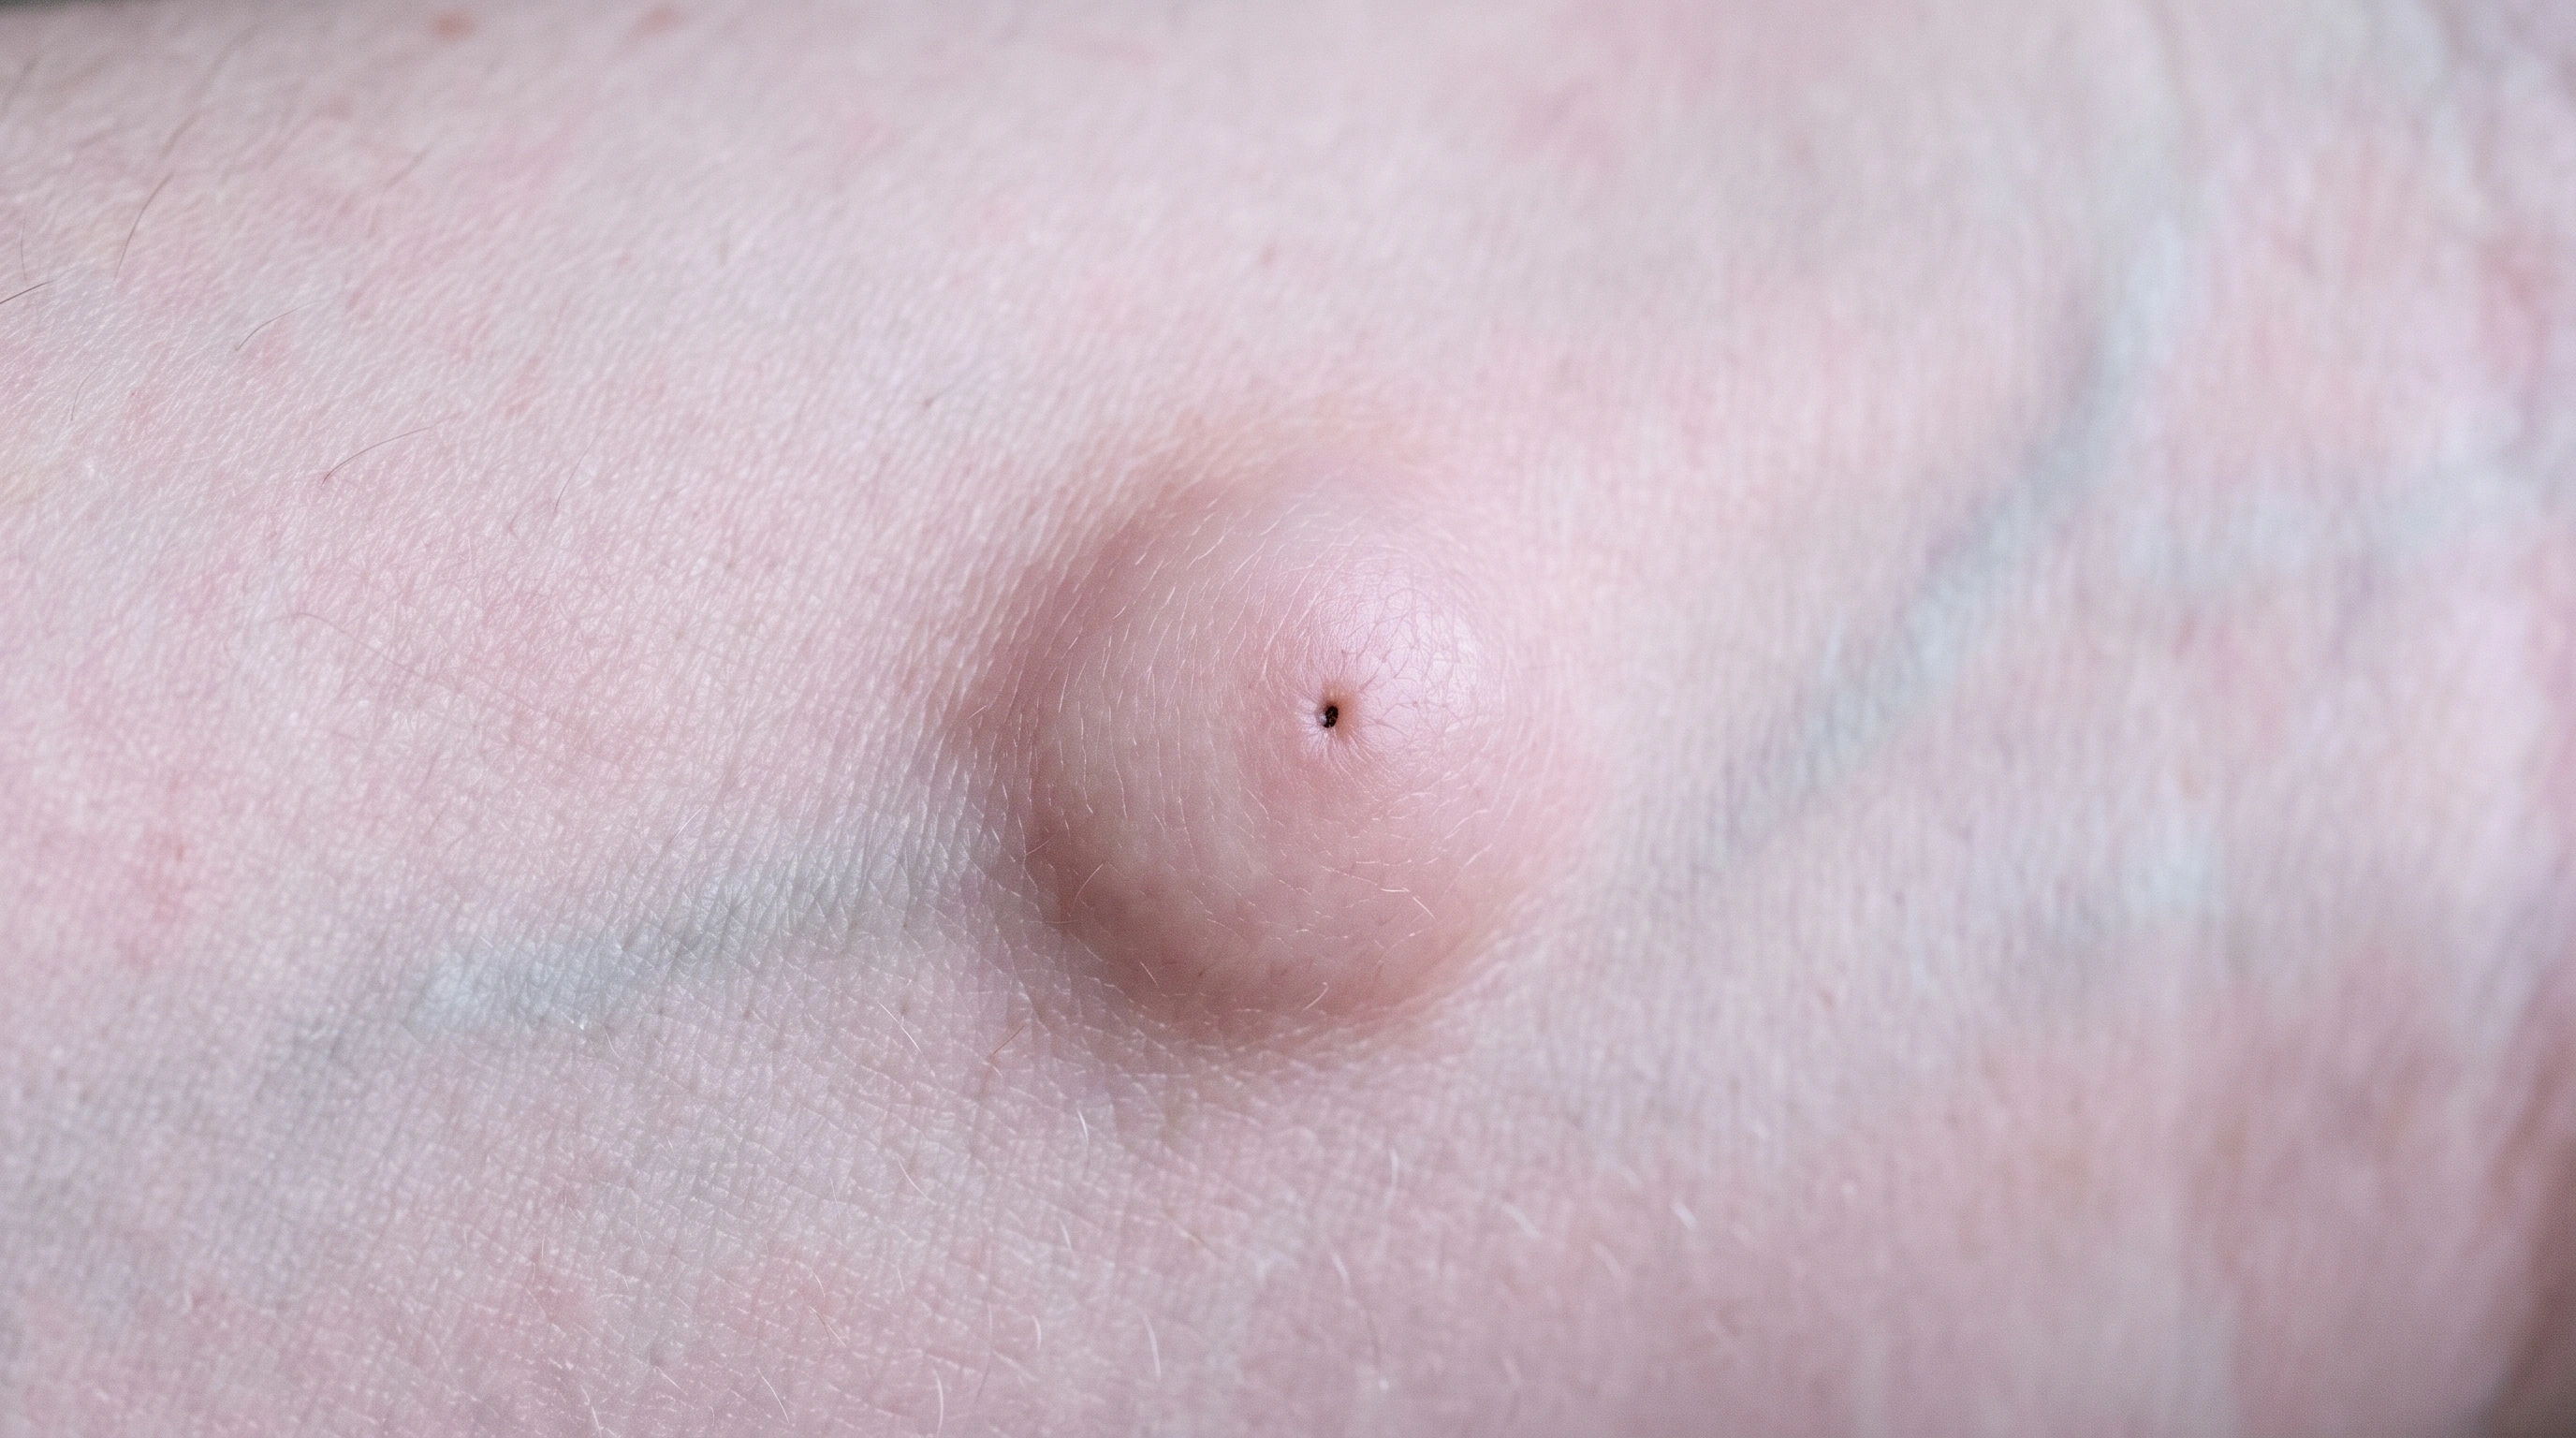
The sac stays and regrows.
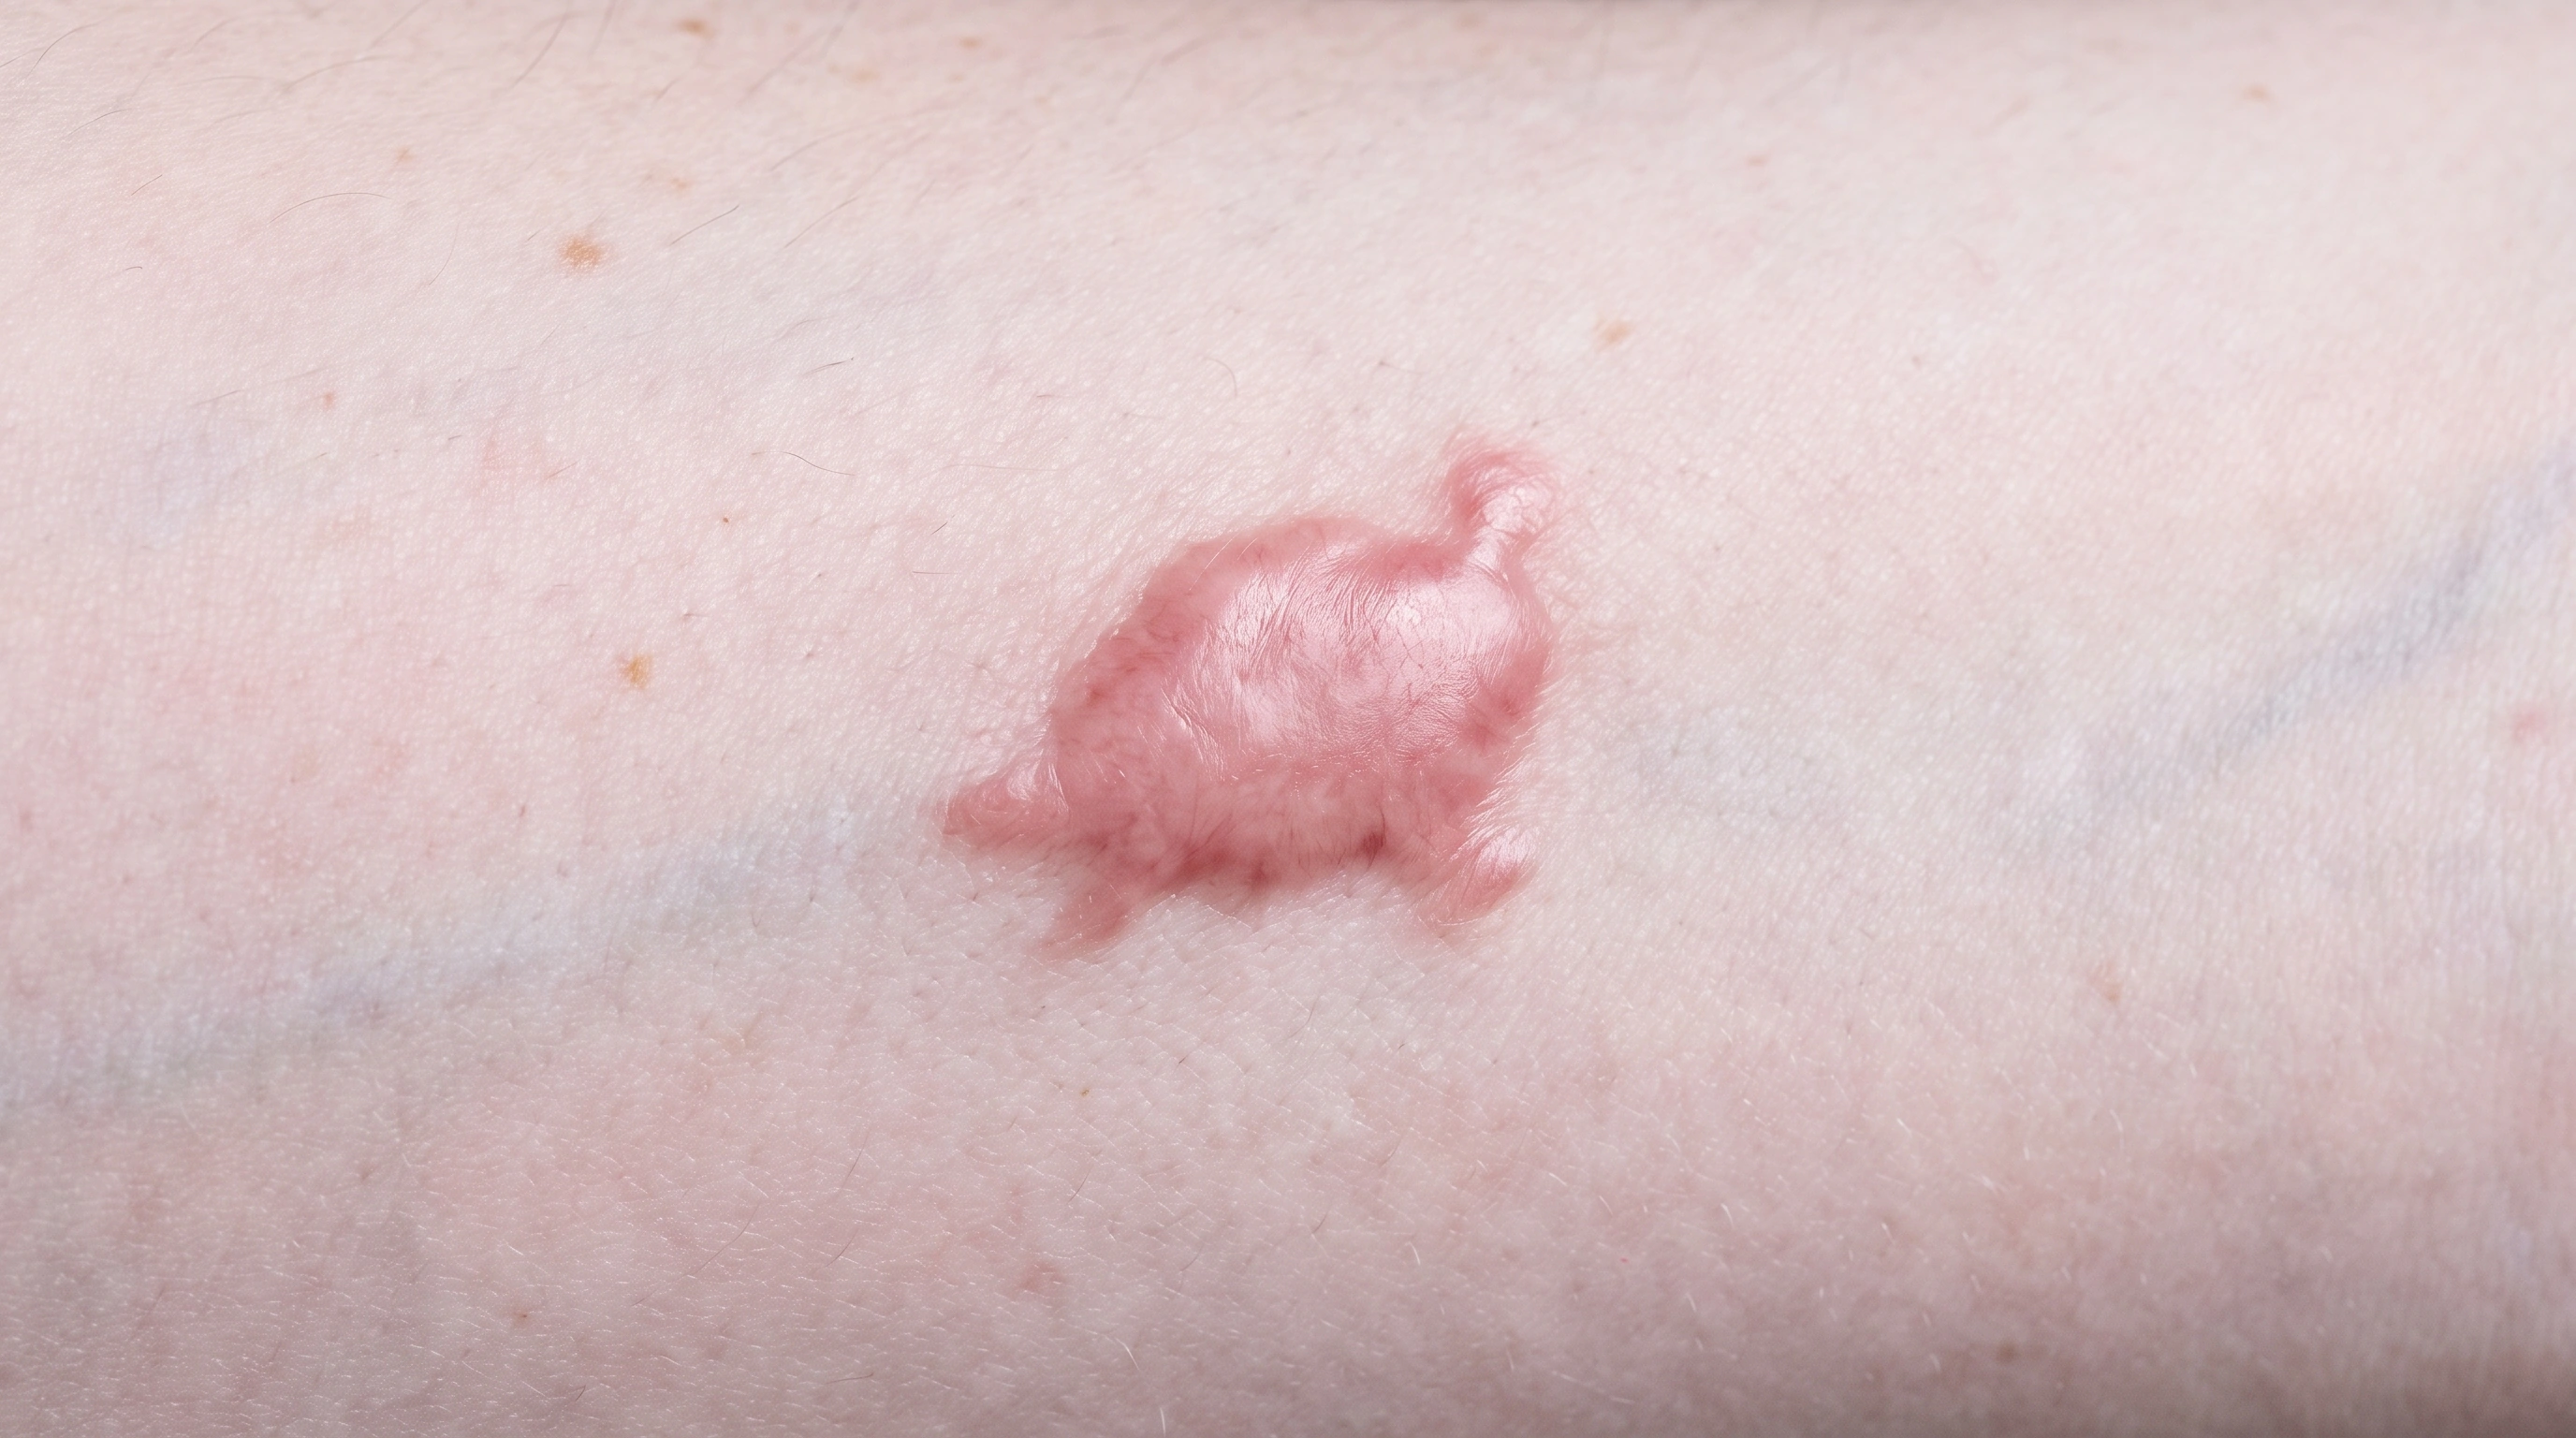
Can trigger new keloids.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.

A curette removes tissue: A clinician scrapes away the selected lesion. Electrical treatment treats the base: Energy dries or coagulates tissue in the treatment bed. The wound heals: The open area repairs with scar tissue; follow-up remains important.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
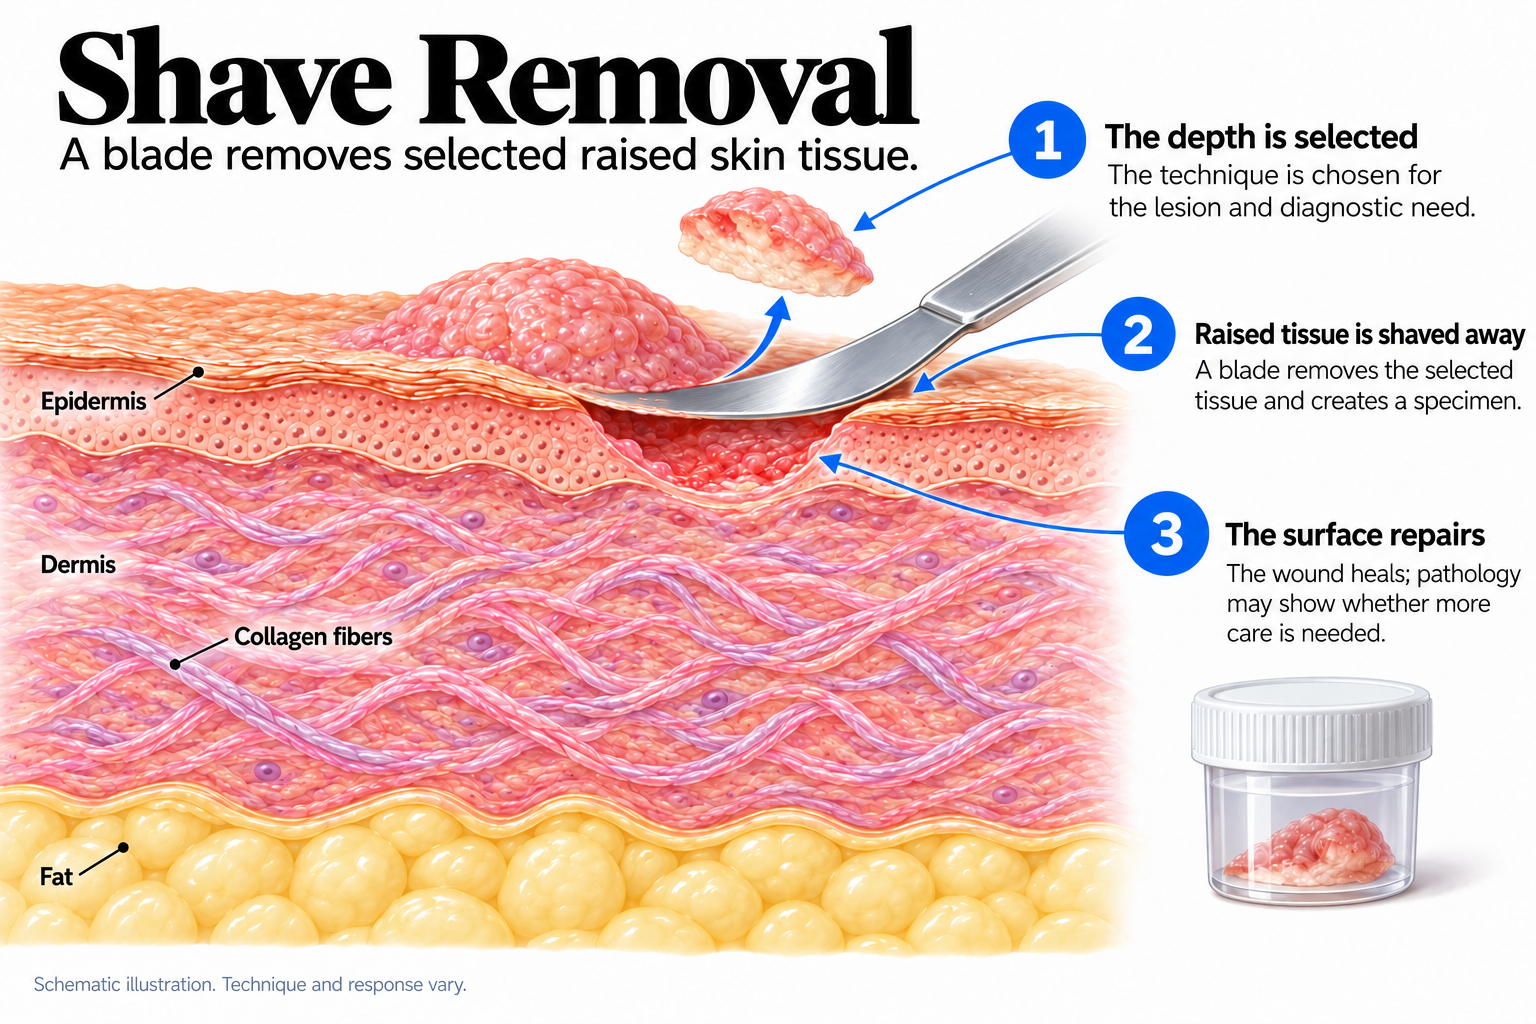
The depth is selected: The technique is chosen for the lesion and diagnostic need. Raised tissue is shaved away: A blade removes the selected tissue and creates a specimen. The surface repairs: The wound heals; pathology may show whether more care is needed.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Do not stop: Blood thinners: Aspirin, clopidogrel, warfarin, apixaban, rivaroxaban and similar are usually continued — extra oozing is easier to manage than a clot or a stroke.
Ointment and dressings: Buy plain petrolatum ointment and non-stick dressings beforehand, not on the way home.
What gets removed: Decide what you want done with each spot, and ask that anything removed goes to the laboratory.
What to wear and eat: Wear something you do not mind getting blood on.
Eating and clothes: Eat normally, take your usual medicines, and wear clothes that give easy access.
The lesion is matched against the biopsy report, photographed, and consent signed.
The spot is examined, often with a handheld magnifier, and measured or photographed.
The doctor scrapes with the curette, which feels like pressure and tugging, not pain.
The electric probe follows, with a faint buzz and a smell of burning. The pair is repeated two or three times; one lesion takes about 10 to 20 minutes. Nothing should feel sharp once you are numb, so say so if it does.
The skin is cleaned, and a blade held nearly parallel to the surface slices the lesion off in seconds.
Bleeding is stopped with a solution on a cotton bud or light cautery — it can smell faintly of burning and is not painful. You feel pressure and scraping, not cutting; say something if anything feels sharp.
A round, shallow, raw crater slightly larger than the growth, under ointment and a dressing.
A dressing, aftercare instructions, and a plan for how the result reaches you.
Day 1 to 7: The wound weeps and the base looks yellow.
Days 1 to 3: The anesthetic wears off over one to three hours, and the site is tender and may ooze.
Days 4 to 14: New skin fills the site and any scab lifts on its own.
Weeks 2 to 6: The crater shrinks and the base turns pink.
From week 2: A flat pink circle sits where the spot was, looking more obvious than the final result.
Month 2 to 12: The scar starts pink and firm, then flattens and pales over roughly a year.
Immediately
Immediately
90–95% cure for suitable cancers
Usually permanent; some moles regrow pigment
This is the least expensive way to treat a skin cancer surgically.
Removal of skin tags and keratoses sits on the line.
In the US it is billed as a destruction procedure, priced by lesion size and body site, and generally covered when it treats a diagnosed skin cancer.
In the US, cost depends on why it was done.
The numbing injection stings for under a minute. After that you feel pressure and tugging, not pain. Afterward the site is sore rather than painful, and acetaminophen is enough.
There is no intact specimen to check — the tumor is scraped away in fragments and the base burned. The method relies on the operator feeling soft tumor against firm normal tissue, which is reliable for shallow, clearly bordered tumors and unreliable for others.
A round, flat disc, usually slightly wider than the original spot and lighter than the skin around it. Some are a little sunken, some raised. Pink at first, paling over about a year. It is permanent.
About 3 to 6 weeks on the face, trunk and arms. On the lower leg it is slower, sometimes two to three months, particularly in older adults or with diabetes or poor circulation.
Sometimes, for a small superficial tumor on the cheek or forehead. Generally not for the nose, eyelids, ears, lips or the creases around them, where recurrence is higher and there is less spare skin. Ask why one is recommended over the other for your tumor.
For a well-selected, small, low-risk tumor, cure at 5 years is commonly quoted around 95 percent. That falls when the method is used on tumors it was not meant for — aggressive subtypes, recurrent tumors, unclear borders, high-risk facial sites.
No. It takes off the raised part and leaves a shallow wound level with the skin, which fills in over one to two weeks. The usual result is a flat mark, slightly paler than the skin around it.
It can. Keratoses and skin tags sometimes regrow from the base, and a shaved mole can return with color months later because pigment cells survived underneath. Have regrowth looked at, and mention that the spot was shaved.
Usually not. A shave normally samples a basal cell or squamous cell cancer rather than clearing it, and a second procedure follows. Keep that appointment even though the skin looks healed.
Often yes, if it has been examined and looks harmless. It is billed as cosmetic, and the trade is a flat pale mark instead of a raised bump. It should still go to the laboratory.
No. That is the main appeal — the wound heals from the base under a layer of petroleum jelly.
Keep the site moist with plain petroleum jelly and covered until it closes over, do not pick, and keep it out of the sun for several months. Drying out and sun are what turn a small shave site into a lasting mark.