Mohs Surgery
Skin cancer is removed one thin layer at a time, and each layer is checked under a microscope during the appointment before the next one is taken. It has the highest cure rate and removes the least normal skin, and it takes most of a day.
Key facts
Treats
Selected high-risk skin cancers
Recovery
Wound care; often 1–2 weeks initially
Treatment plan
One surgical visit, plus follow-up
Typical cost
Medical coverage varies
What is it?
It removes cancer in stages.
Each layer is mapped and examined under the microscope.
It conserves healthy tissue.
Further tissue is removed only where cancer remains.
Not every cancer needs Mohs.
Type, size, site and recurrence determine suitability.
The wound can be larger.
The final defect may exceed the visible lesion.
Treatment areas
Mohs Surgery
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Mohs Surgery
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Skin tones
Lighter skin
Low risk
A fine scar that fades over a year.
Medium skin
Low risk
Scars usually settle well.
Deeper skin
Some risk
Raised or darker scars possible; ask about scar care.
How it works

Diagram explanation
A thin tissue layer is removed: The surgeon removes visible cancer and a surrounding layer. Margins are mapped and examined: The tissue edges are checked under a microscope. Only involved areas are treated again: Stages continue as needed before planning wound repair.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Before your treatment
The week before
Supplements and alcohol: Blood-thinning supplements you do not need, such as fish oil, vitamin E and ginkgo, are commonly stopped about a week before, and alcohol the night before.
Smoking and vaping: Stop from at least a week before through the first two weeks after if you can.
Day of treatment
Before you arrive
Eat, dress and plan: Eat a normal breakfast and take your usual morning medicines unless told otherwise.
Arrival & prep
The site is confirmed against the biopsy report and photographed, and you will be asked to point to the spot yourself.
Treatment
The surgery: The tumor and a narrow margin come out in minutes.
The surgery: You then wait 45 minutes or more while the tissue is frozen, sectioned and read. If tumor remains at a mapped edge, another layer is taken there only; most finish in one to three stages. The wound is then closed with stitches, a flap or a graft, or left to heal, in 30 to 90 minutes. The injections sting; nothing else does.
Before you leave
A firm pressure dressing stays on 24 to 48 hours, with written wound-care instructions and a suture removal appointment.
After your treatment
First 24 hours
First 24 to 48 hours: Keep the dressing dry and in place, your head elevated including overnight, and ice over the dressing in short spells.
Days 2–7
Days 2 to 14: Bruising and swelling are worst around day two and can spread around the eyes.
Weeks 2–4
Week 2 to Month 12: The scar becomes a hard, raised, pink ridge.
Time to results
Same day
How long results last
About 99% cure for first basal cell cancers
Risks
When to contact your provider
Bleeding: Press firmly on the spot for 15 minutes by the clock without lifting to check.
Bleeding: Nearly all bleeding stops with this.
Serious complications are uncommon. The certainties are a scar and a long day. What follows is worth recognizing rather than expecting.
A thick or raised scar
A scar getting firmer and higher after two months rather than flattening. Steroid injections and silicone work best before it fully matures.
Numbness or tingling that is not improving
Small sensory nerves are often cut and the numbness usually recovers over months. One not changing by six months is worth reviewing.
A graft or flap turning black
Or one that is separating. Some early duskiness and crusting is expected. Loss of the whole graft is not, and it needs looking at rather than waiting.
A stitch that surfaces months later
Buried dissolving stitches sometimes work their way out and cause a small red bump. A nuisance rather than a problem, and worth having checked.
Pulling at an eyelid or lip
A repair near the eye can tug the lower lid downward, and one near the mouth can pull the lip. Mention it early. It often settles with massage, and there are options if it does not.
Cost
Typical cost
Usually covered by insurance
Pricing
Mohs is the most expensive of the standard skin cancer treatments, and the day shows why: a surgeon who is also reading the pathology, a laboratory and technician in the building, and hours of appointment time.
Insurance
It is generally covered by health insurance when the tumor meets accepted criteria for Mohs, which is why the location, size and subtype are documented before it is booked.
Alternatives
Surgical excision
Cuts the tumor out with a set margin and sends it to a laboratory, with the result in several days. Cure for a primary basal cell carcinoma is commonly quoted around 95 percent, against around 99 percent for Mohs. The appointment is far shorter and it costs less. The trades are a longer scar, because a fixed margin is taken all the way around whether or not tumor went that way, and the possibility of a call a week later saying the edges were not clear.

Electrodesiccation and curettage
For low-risk tumors only. One quick visit, the cheapest of the options, and no stitches. There is no margin check at all, an open wound for three to six weeks, and a round pale scar. A reasonable choice for a small superficial tumor on the trunk, and not for the face.
Radiation therapy
Moderate to strong evidence. No cutting, which makes it valuable for people who cannot have surgery or for tumors where surgery would be disfiguring. The trades are many appointments over weeks, a lower cure rate than Mohs, a permanently altered patch of skin, and a reluctance to use it in younger people because of long-term effects.

Topical imiquimod or 5-fluorouracil
Only for superficial basal cell carcinoma and squamous cell carcinoma in situ. No surgery and no scar. The trades are weeks of an inflamed, uncomfortable and visibly red course at home, meaningfully lower cure rates, and no way to confirm the cancer is gone.

Photodynamic therapy
Usually leaves the least visible mark afterward, and useful over a wide area of sun damage. Painful during treatment, several visits, and cure rates below surgery.
Cryotherapy
For very superficial lesions and strong evidence for precancerous spots. Quick and needs no injection. Depth is hard to control, there is no margin check, and it leaves a pale mark. It is not a substitute for Mohs on anything a Mohs surgeon would be asked to see.

What is worth doing at home
Daily broad-spectrum SPF 30 or higher, sun-protective clothing, shade, monthly self-checks, and keeping the follow-up appointments. Prevention and early detection are the parts of skin cancer care that genuinely happen at home, and they change outcomes more than anything sold as a home remedy.
Questions
Why does it take all day?
Mostly waiting. Removing a layer takes minutes; freezing, slicing, staining and reading it under a microscope takes 45 minutes to well over an hour, and that happens once for every stage. One to three stages plus a repair fills most of a day.
Will I be asleep?
No — Mohs is done under local anesthetic while you are awake. You will be numb but able to talk, eat between stages and walk to the waiting room. General anesthesia is used only in unusual cases.
How big will the scar be?
Not knowable in advance, which is uncomfortable and honest. The wound ends up as large as the tumor's roots turn out to be. Mohs removes less normal skin than any other method, so the wound is usually smaller than an excision would have produced for the same tumor, and a tumor that looked like a small spot on the surface can still be considerably wider underneath.
Should I stop my blood thinner first?
Not unless the doctor who prescribed it tells you to. Blood thinners are usually continued through Mohs. Extra bleeding during surgery is manageable; a stroke or a clot is not.
Why is Mohs recommended for the cancer on my face but not the one on my back?
Location, mainly. On the face there is little spare skin and recurrence rates are higher, so removing the least tissue with the highest certainty is worth the time and the cost. On the back a straightforward excision achieves the same result more simply. Size, an aggressive subtype under the microscope, unclear borders and a tumor that has come back before all push toward Mohs anywhere on the body.
Am I cured when I leave?
Almost certainly, and follow-up still matters. Cure at 5 years for a previously untreated basal cell carcinoma is commonly quoted around 99 percent. The bigger reason to keep coming back is that having had one skin cancer makes a new one elsewhere substantially more likely.
Related
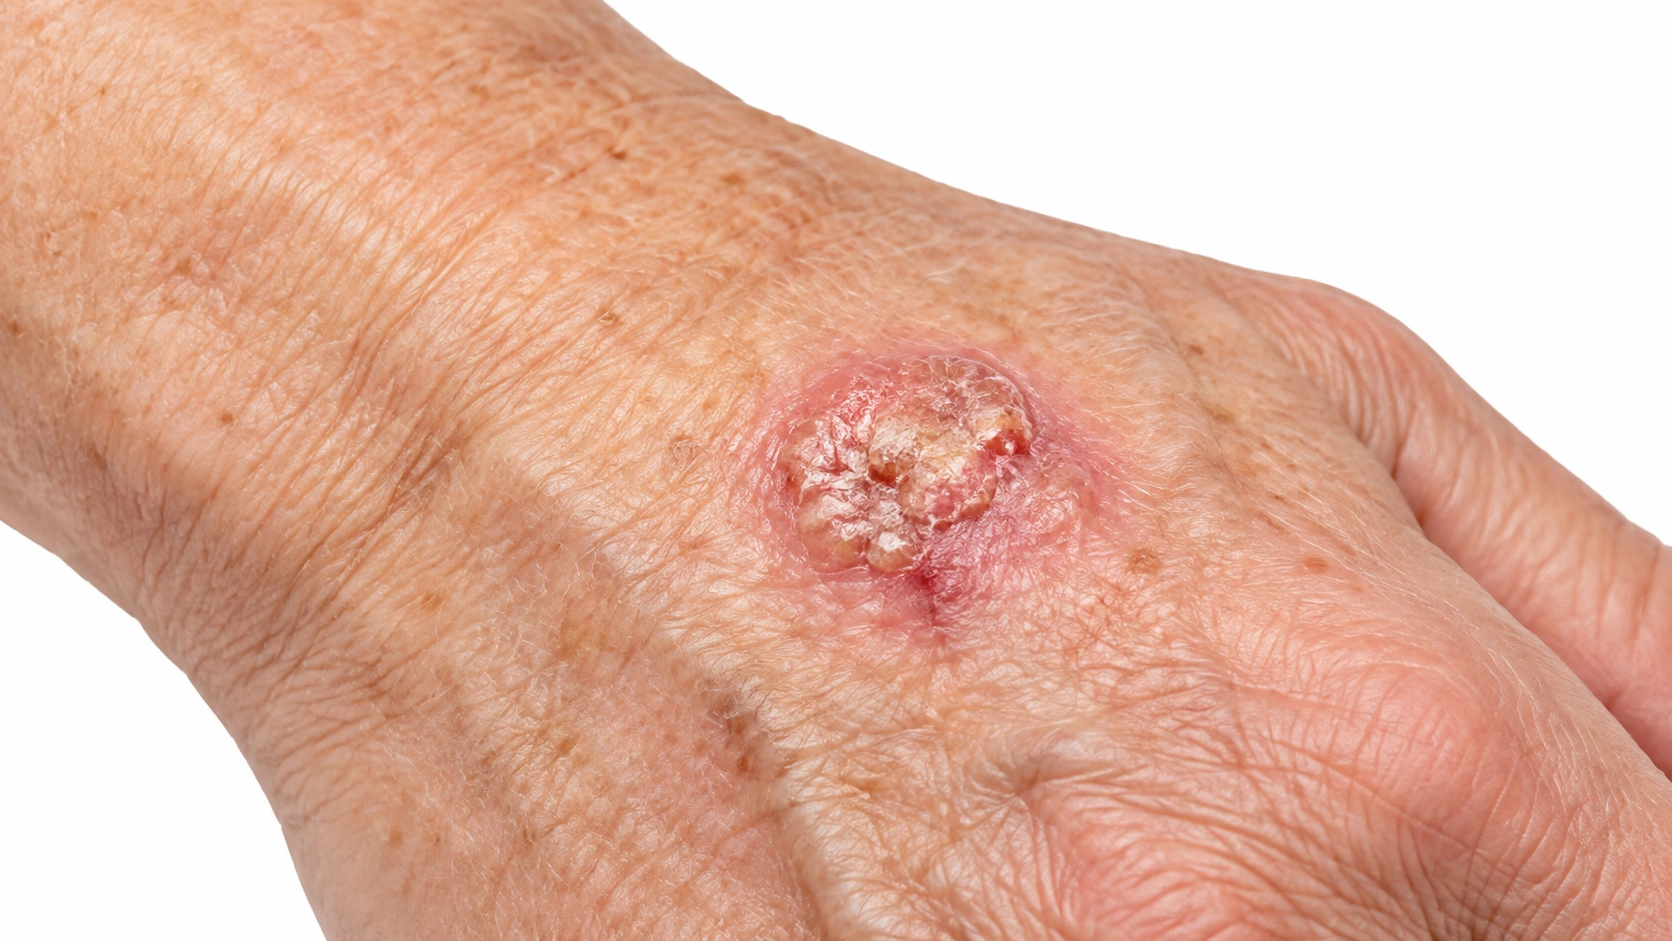
Squamous Cell Carcinoma
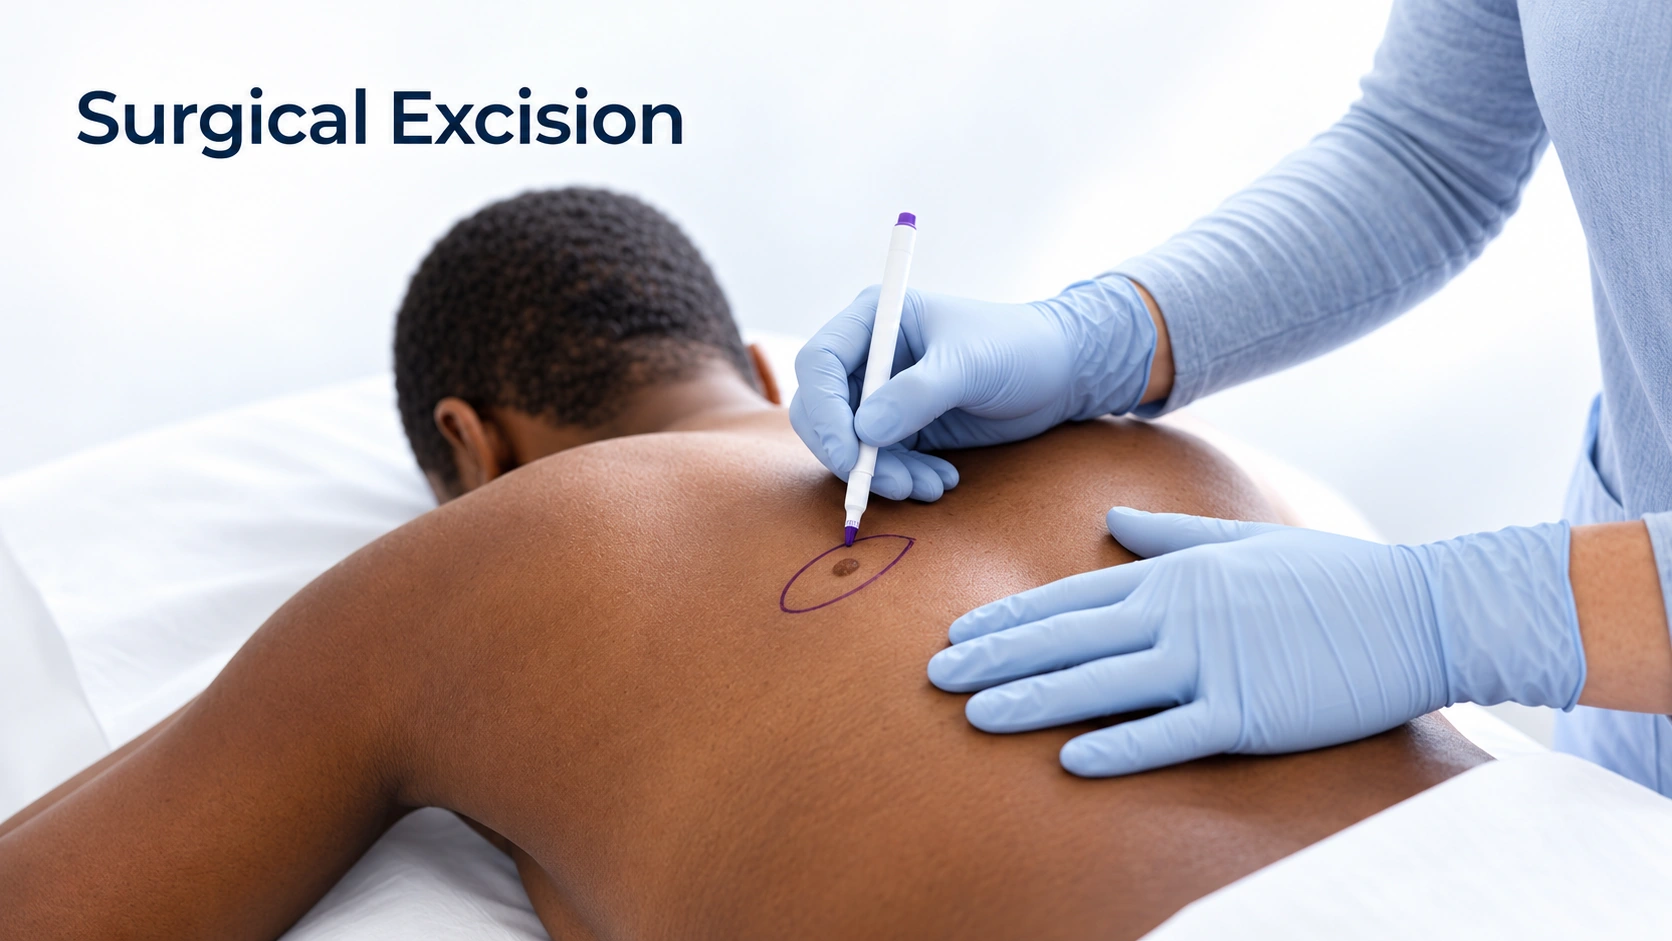
Surgical Excision

Electrodesiccation and Curettage
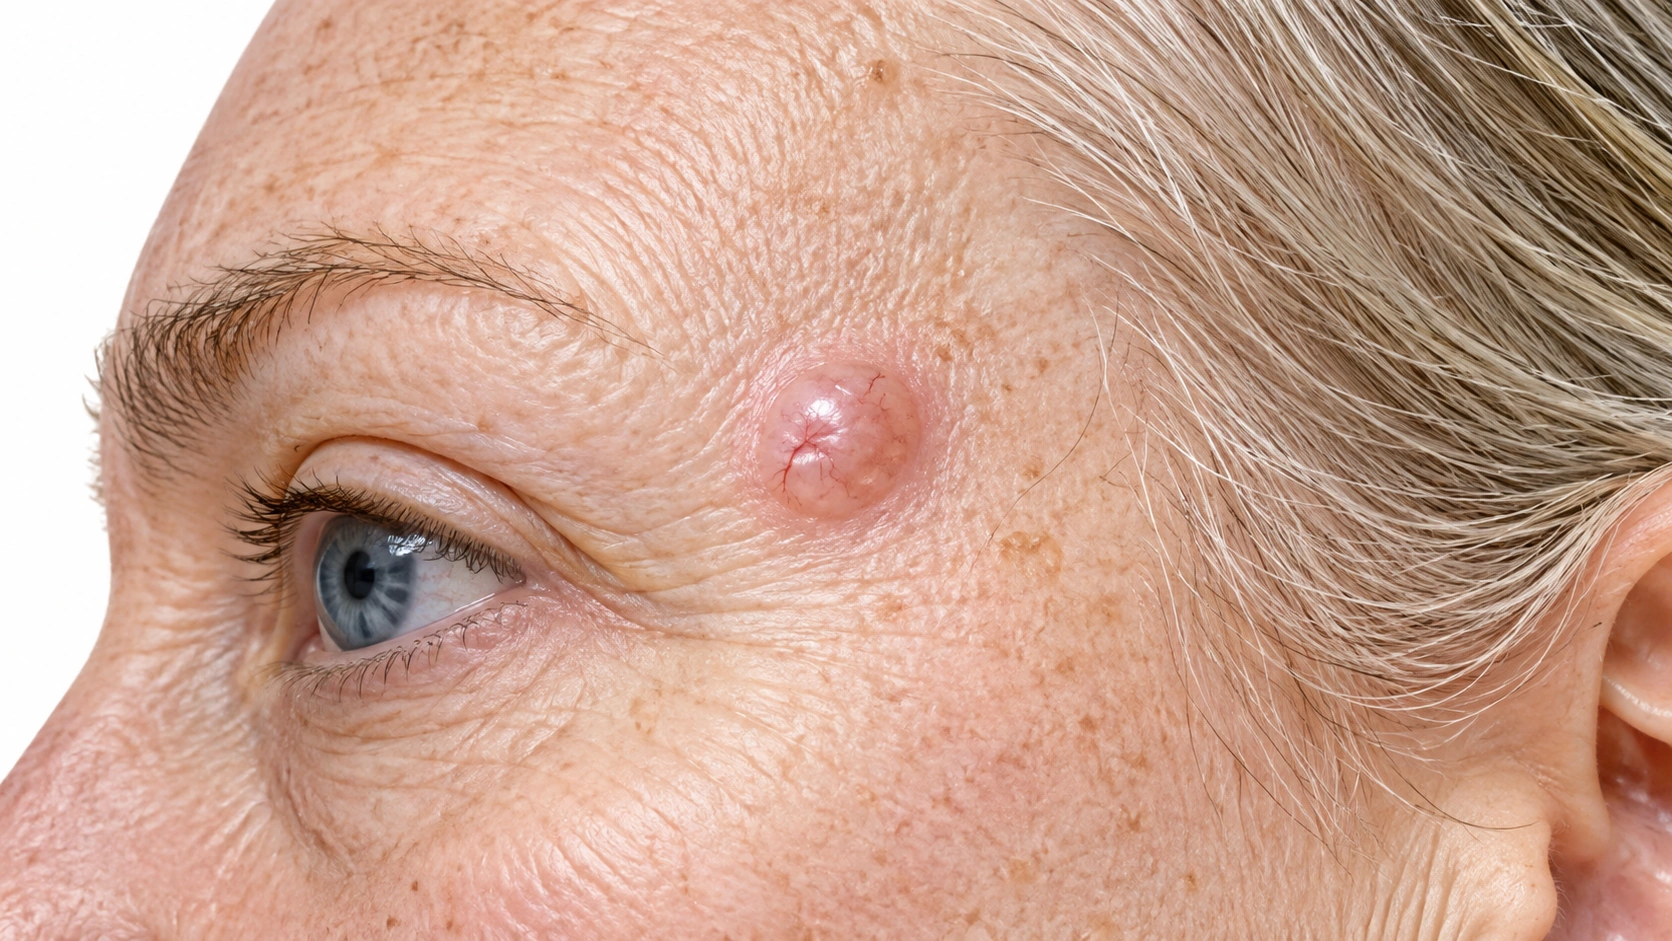
Basal Cell Carcinoma
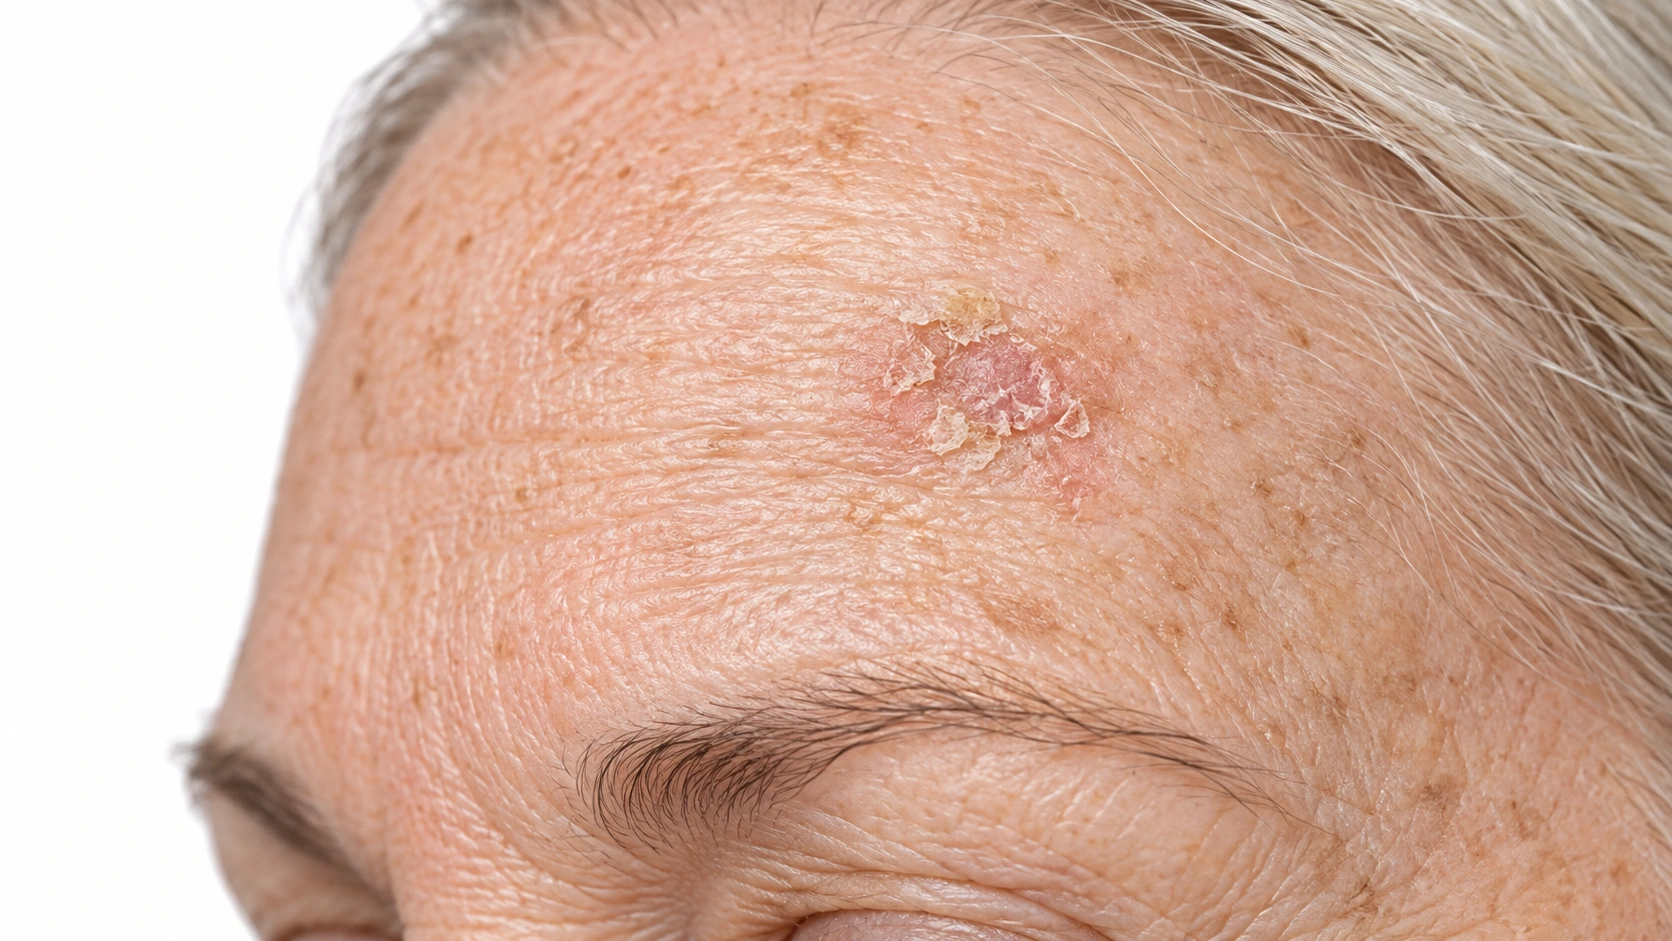
Actinic Keratosis
Photodynamic Therapy
Cryotherapy
Moles
Cryotherapy vs Mohs Surgery
Electrodesiccation and Curettage vs Mohs Surgery
Mohs Surgery vs Photodynamic Therapy