Perioral Dermatitis
Perioral dermatitis is a rash of small bumps and fine flaking around the mouth, and sometimes around the nose and eyes. Steroid creams are the most common trigger, and they are also what makes it worse in the long run. It clears with the right treatment, but slowly.
Key facts
Perioral Dermatitis at a glance.
Typical signs
Small bumps around mouth or eyes
Common locations
Mouth, nose, eyes
Expected course
Clearing takes weeks to months
Treatment options
Simplify skincare; prescription treatment
What is it?
Top things to know about Perioral Dermatitis
- It is a facial eruption. Small inflamed bumps form around the mouth, nose or eyes.
- The skin often feels uncomfortable. It may feel dry, tight, burning or scaly.
- The lip border is often spared. A narrow clear zone beside the lip is common.
- Simpler routines help. Harsh actives, heavy products and steroid self-treatment can worsen it.
What it looks like
What Perioral Dermatitis looks like
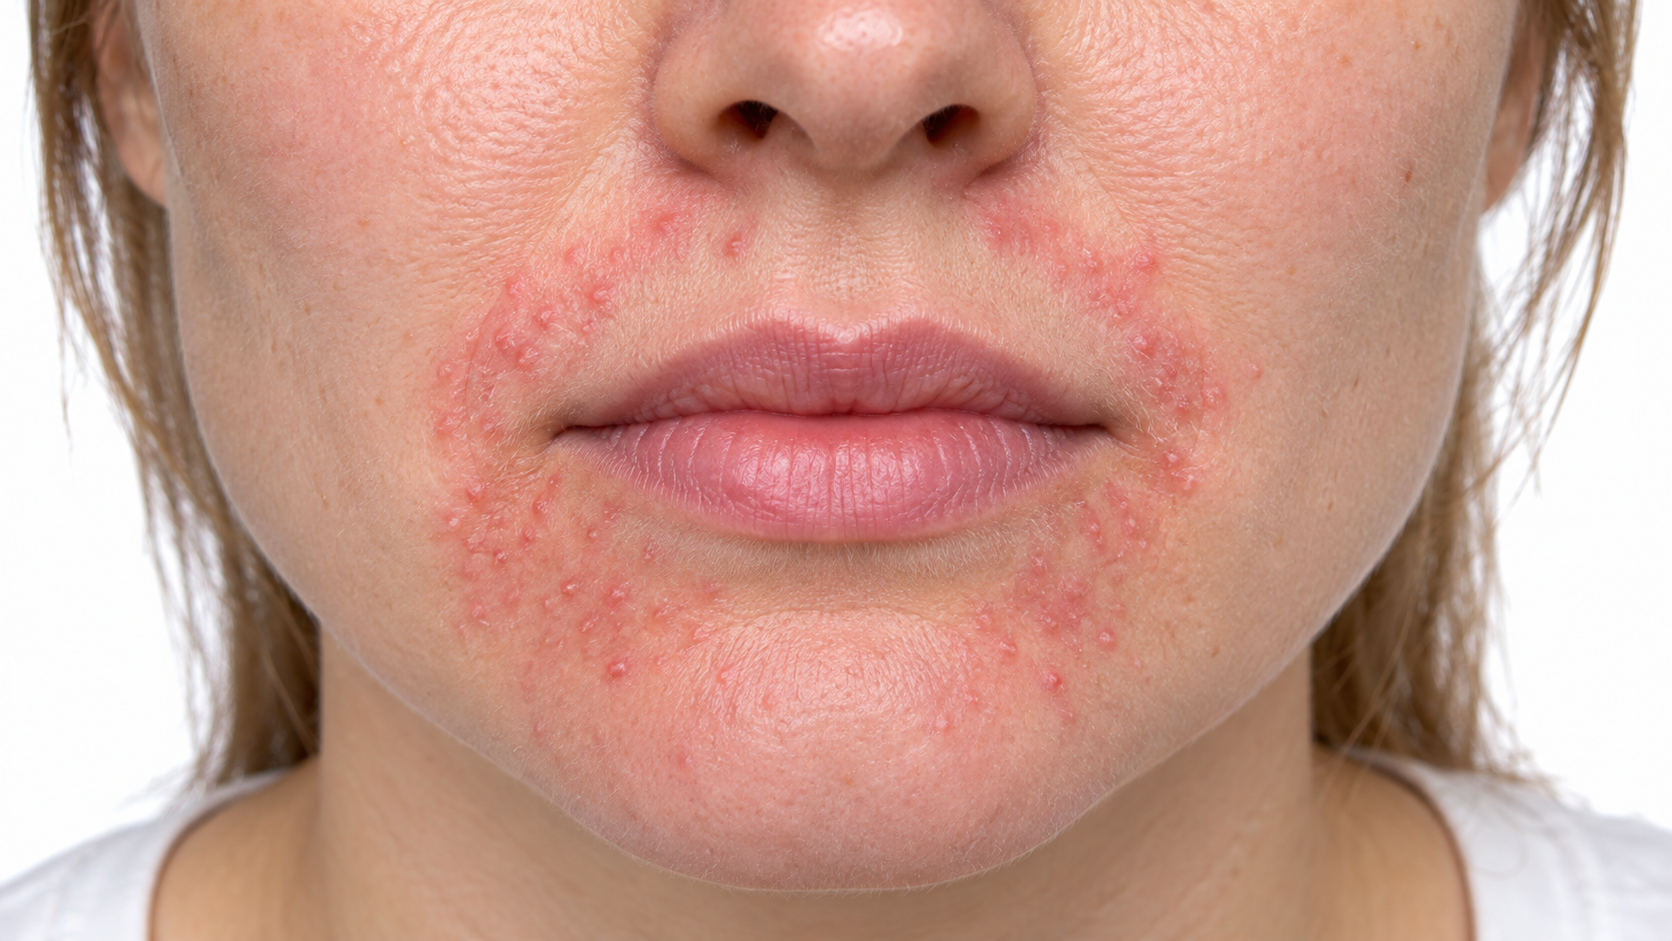
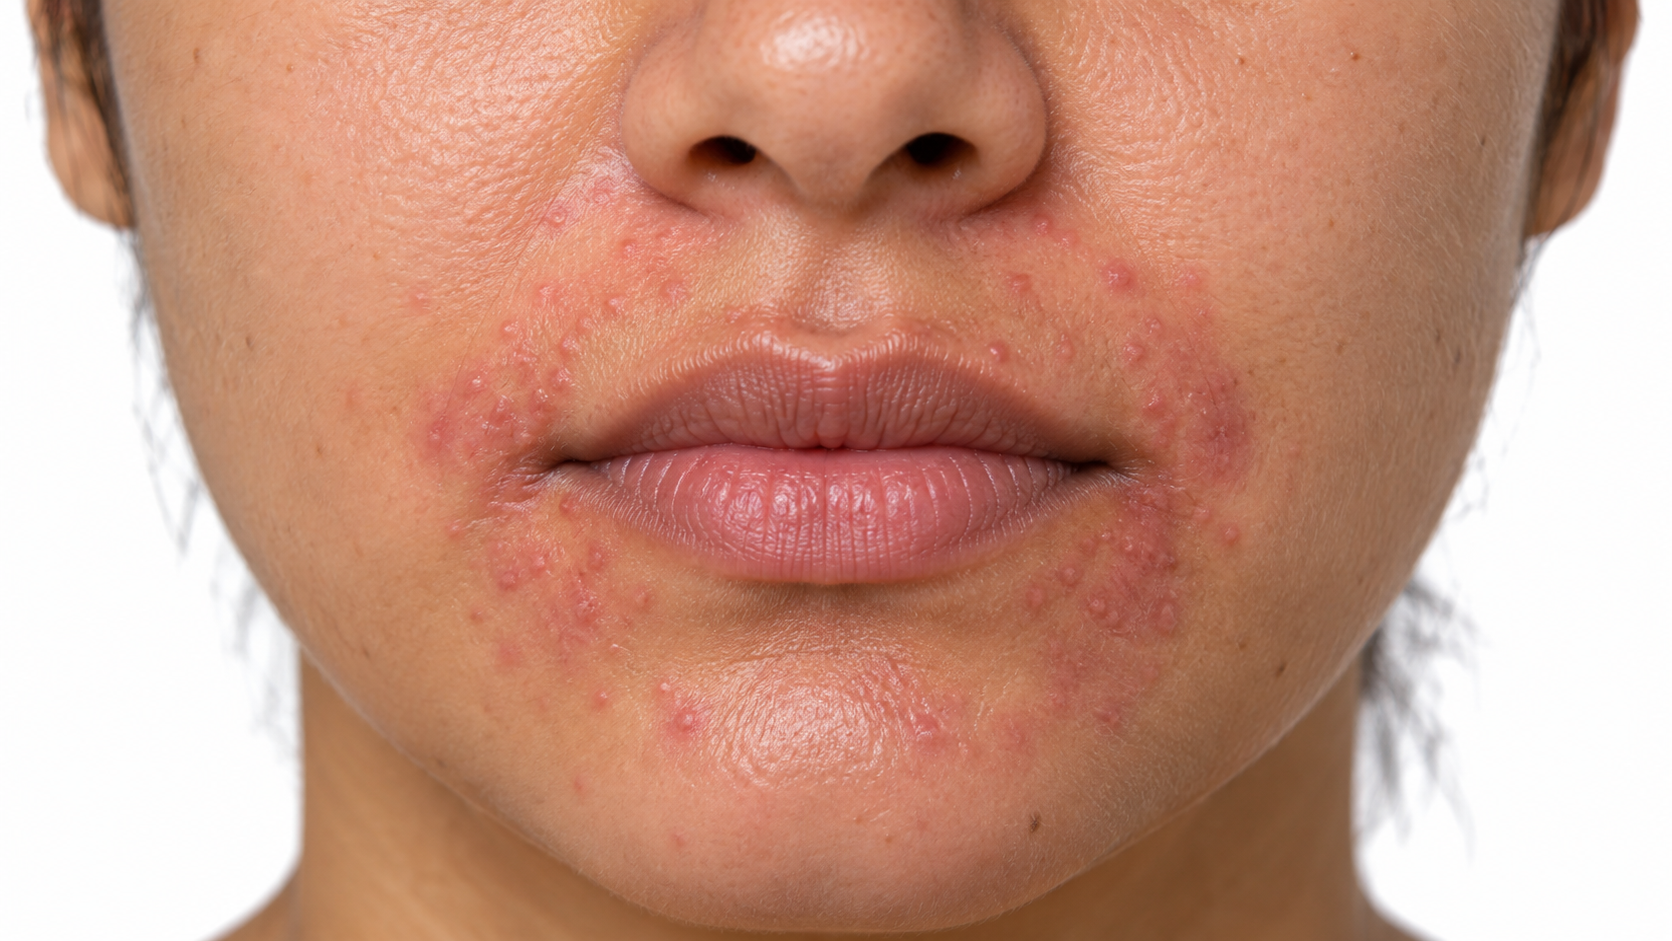
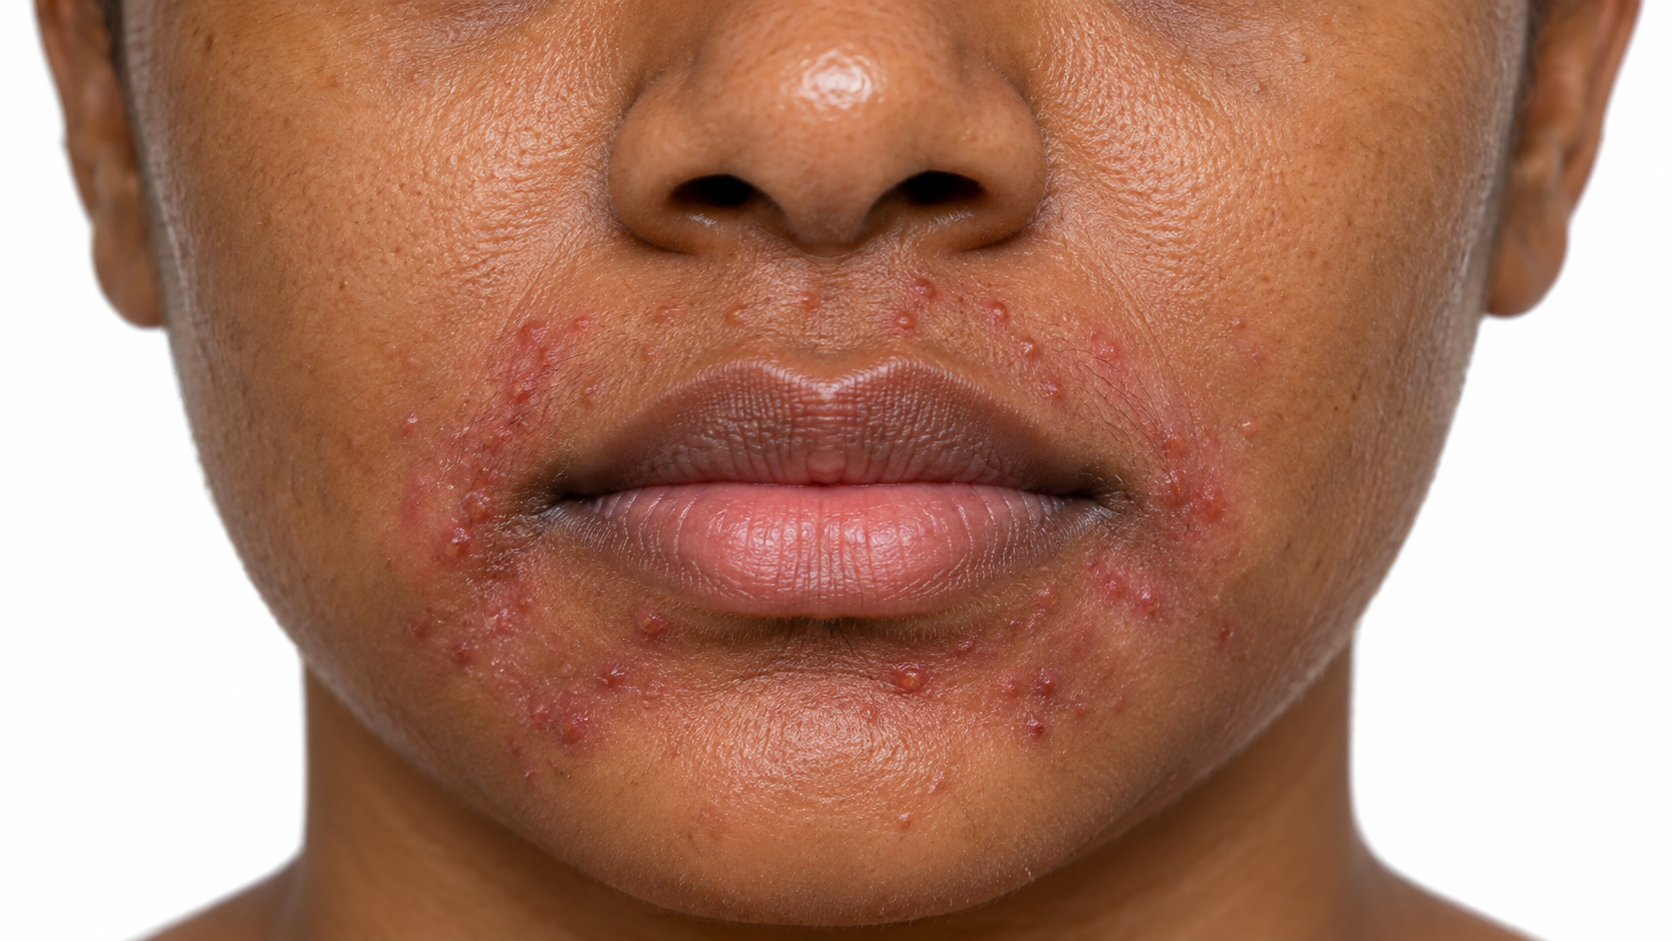
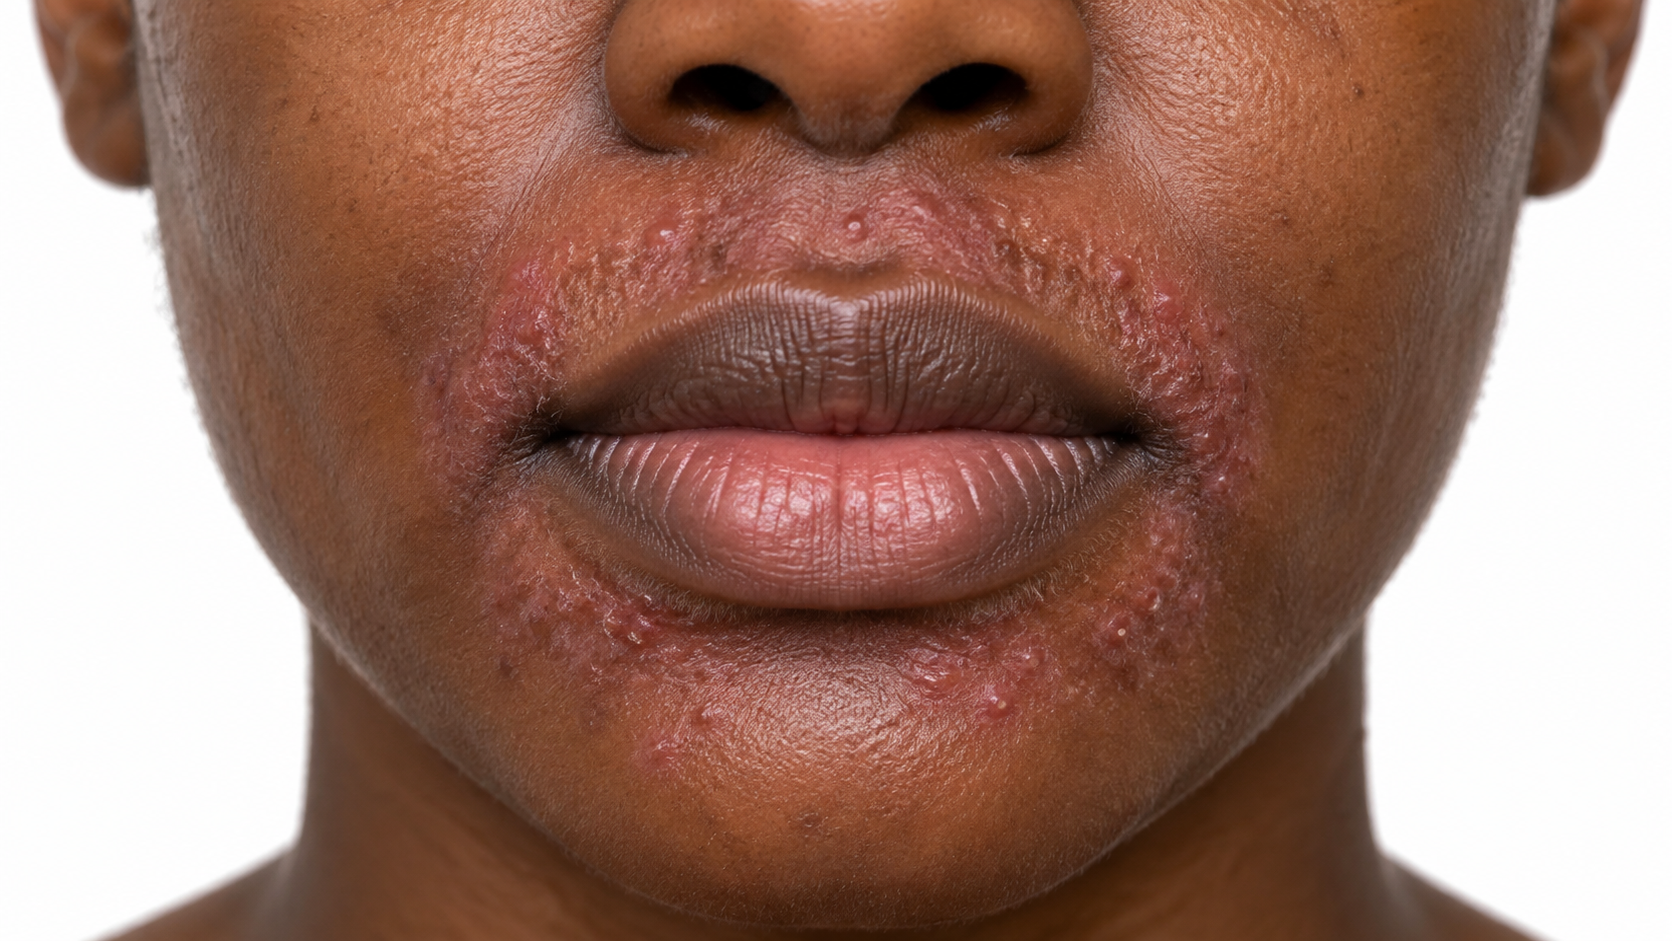
Perioral dermatitis is a rash of small red bumps and sometimes tiny pustules around the mouth. A key sign is a narrow clear band of skin right next to the lips. It can also spread to the sides of the nose and around the eyes. The skin may feel dry, burning or tight. It is often triggered or worsened by steroid creams, heavy moisturizers and some toothpastes.
Perioral dermatitis is named by where it appears.
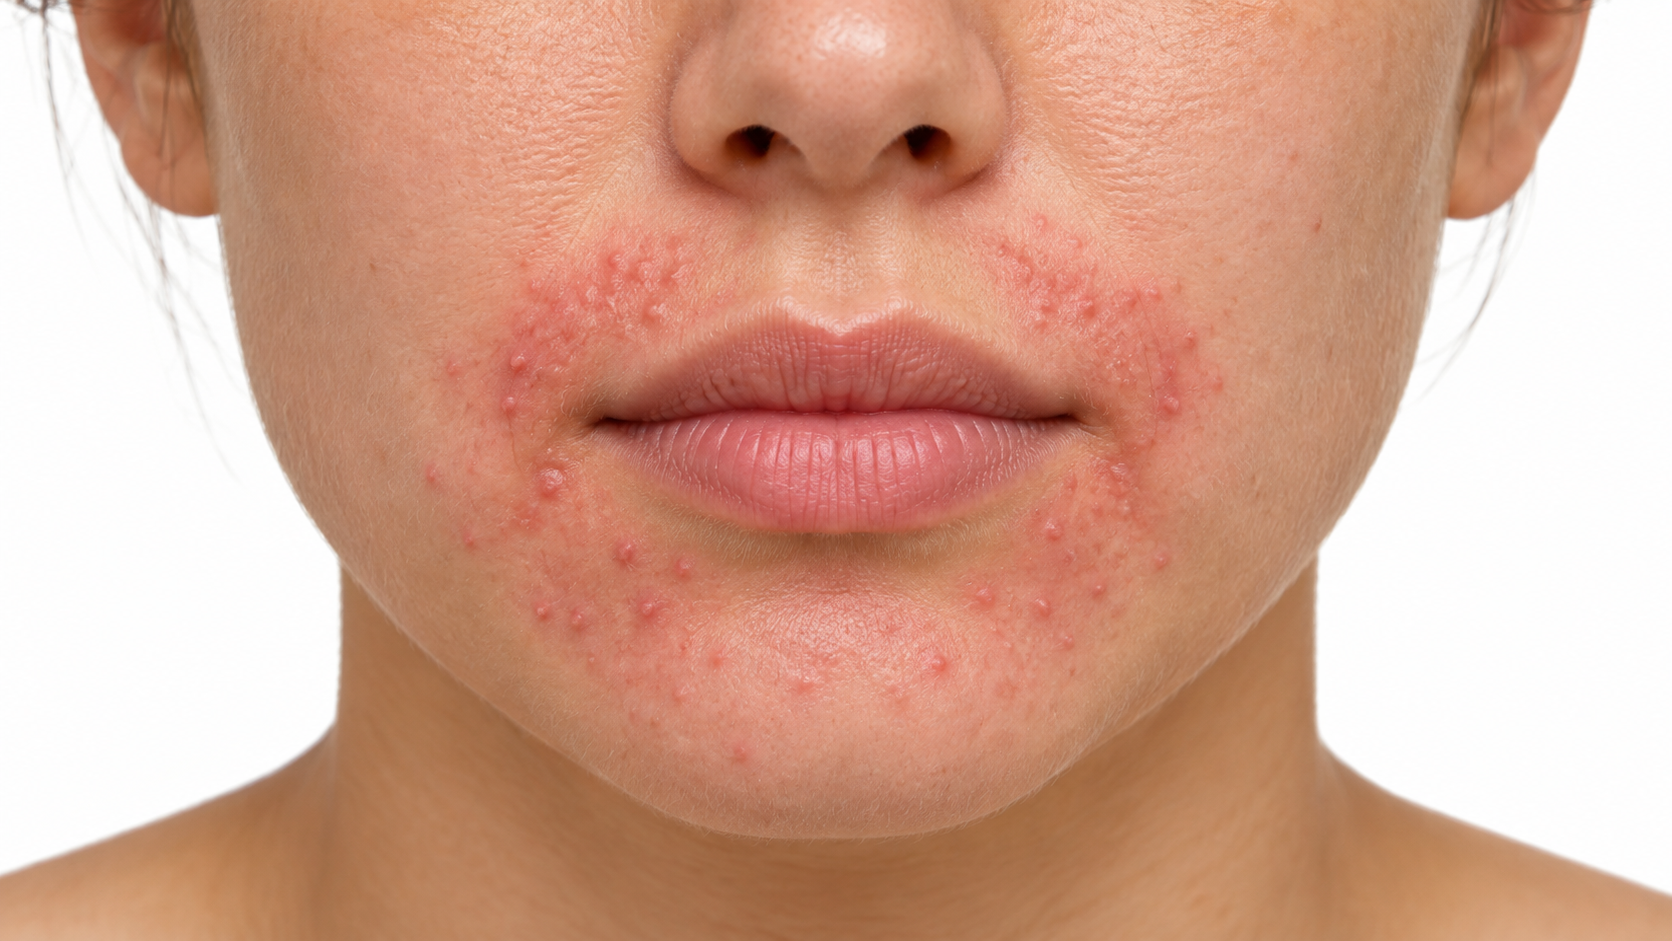
Perioral dermatitis
Around the mouth.
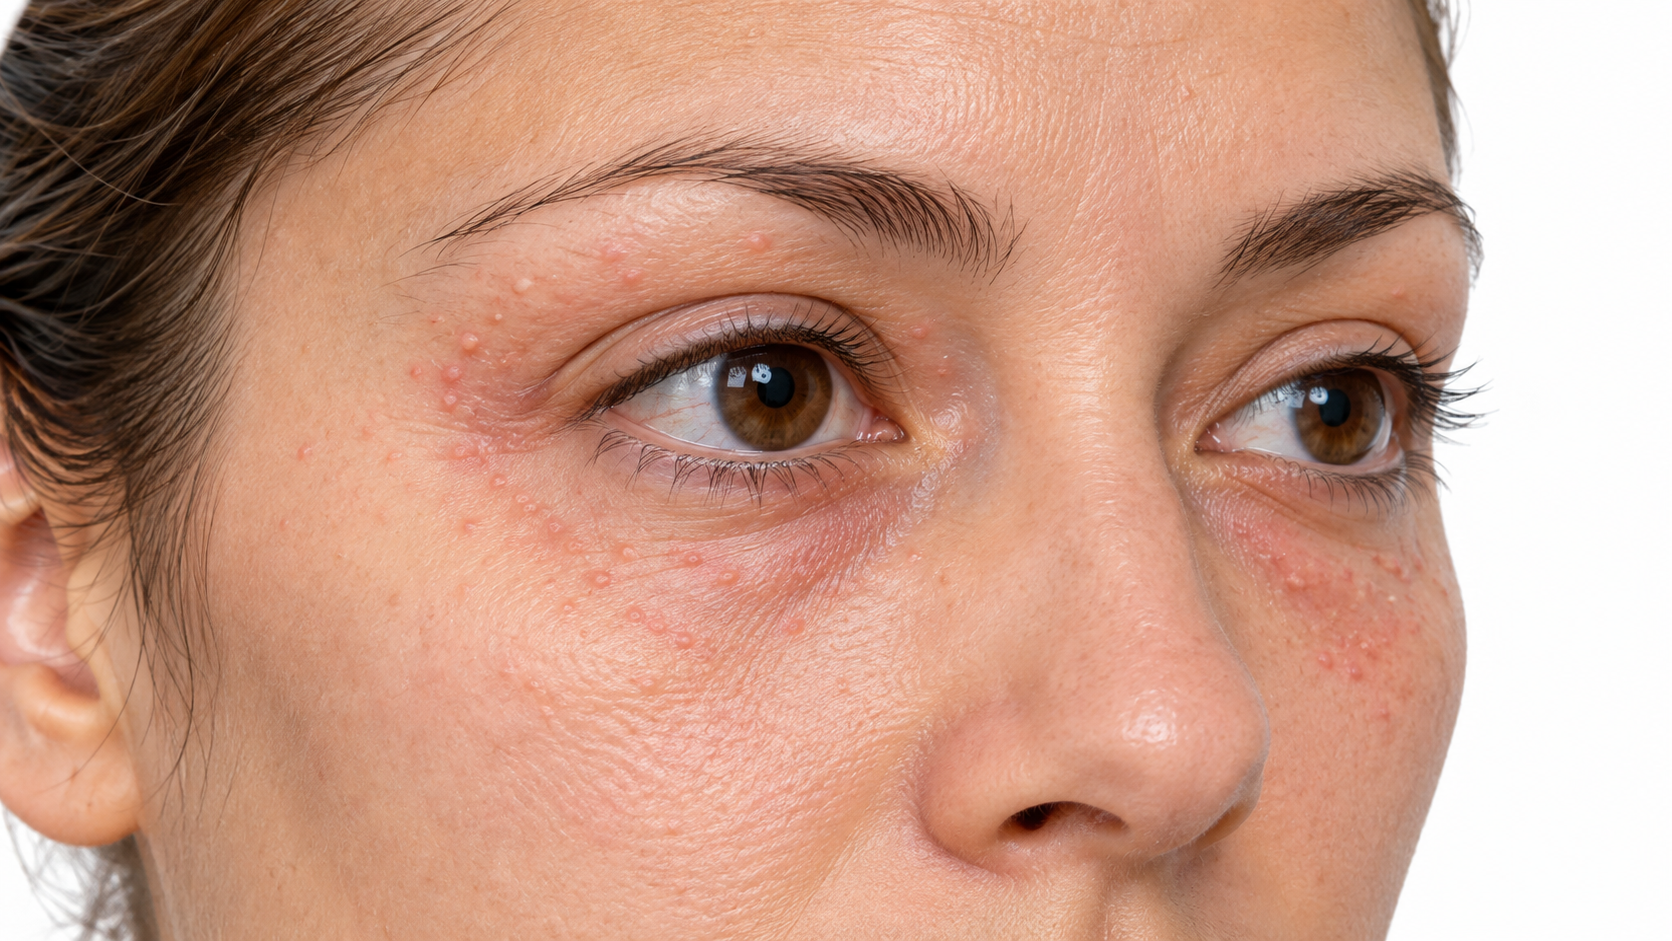
Periorbital dermatitis
Around the eyes.
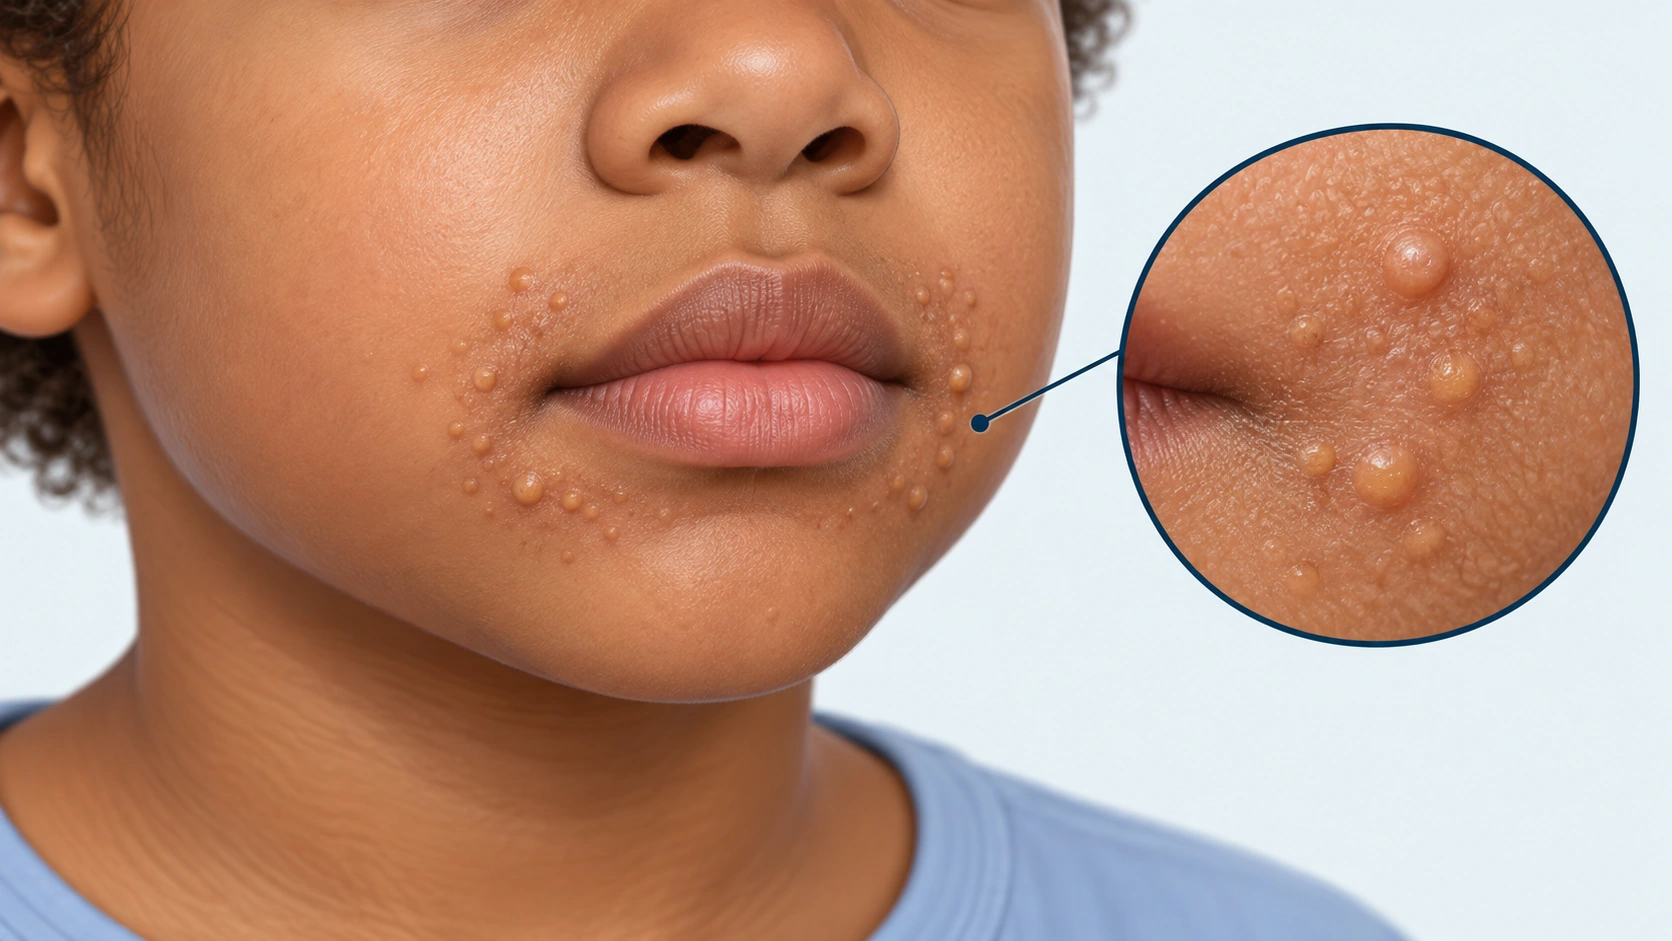
Granulomatous periorificial dermatitis
Skin-colored or yellow bumps, often in children.
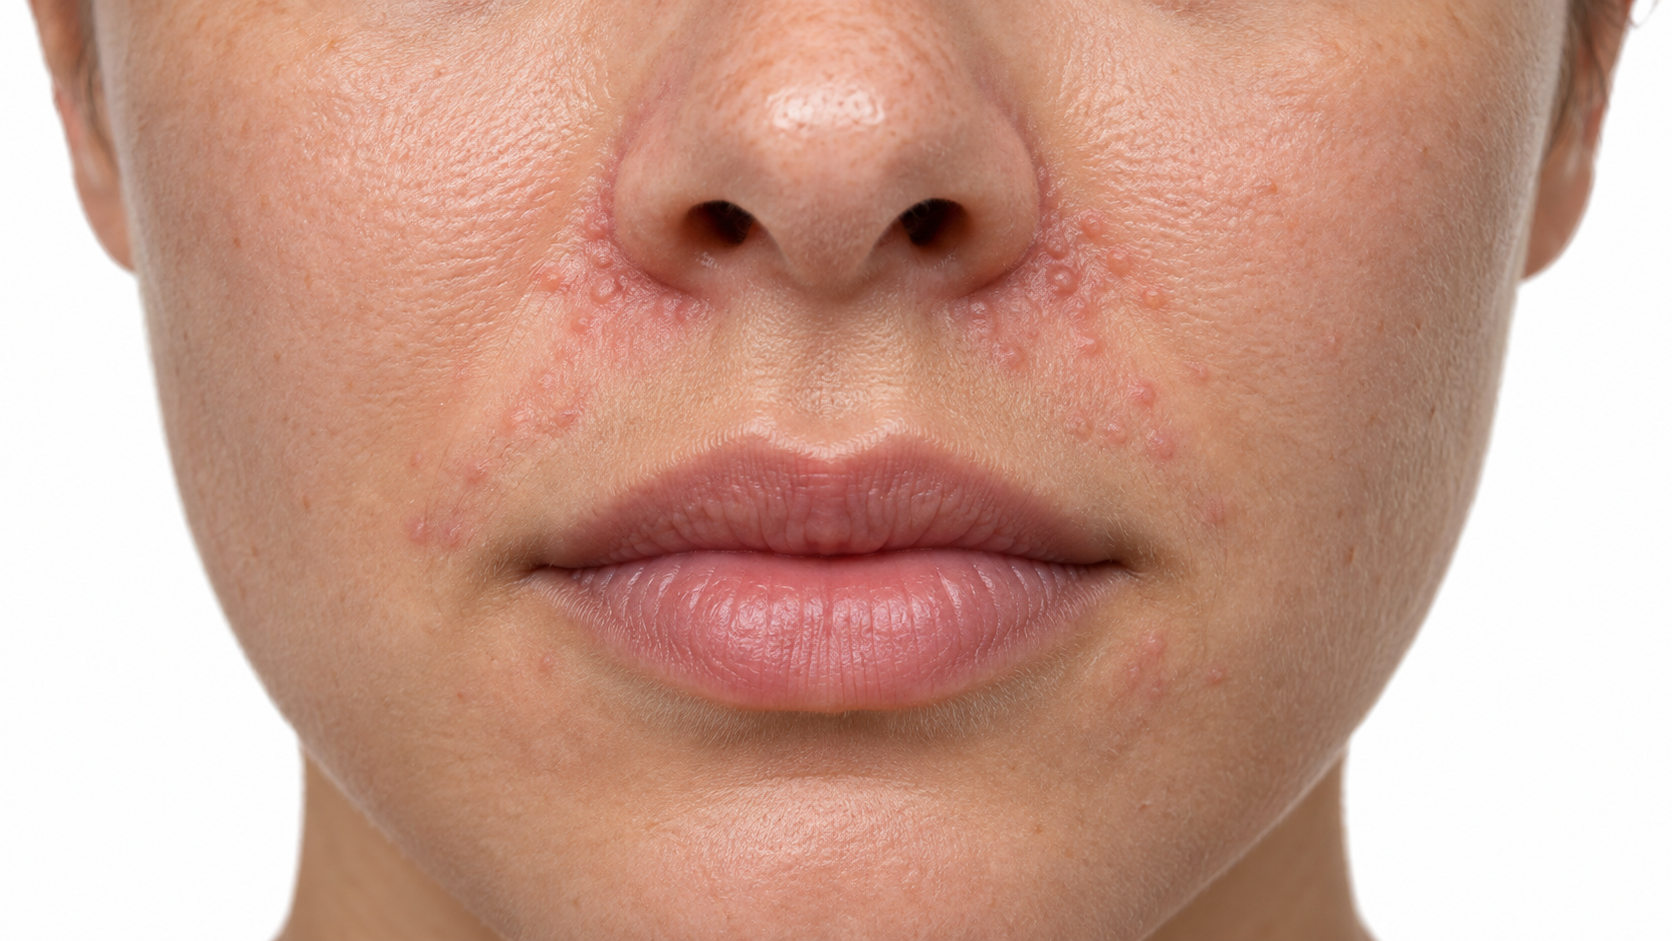
Perinasal dermatitis
Can spread to the nose folds.
Where it shows up
The eruption clusters around facial openings, often leaving a narrow clear rim next to the lips.
Face
Facial locations.
On different skin tones
Perioral Dermatitis on different skin tones
On lighter skin, perioral dermatitis looks pink to red. On brown and Black skin, the bumps are often skin-colored or darker, and the granulomatous form is more common, especially in children. The clear border at the lips remains a helpful sign on every skin tone.
What happens in Perioral Dermatitis?
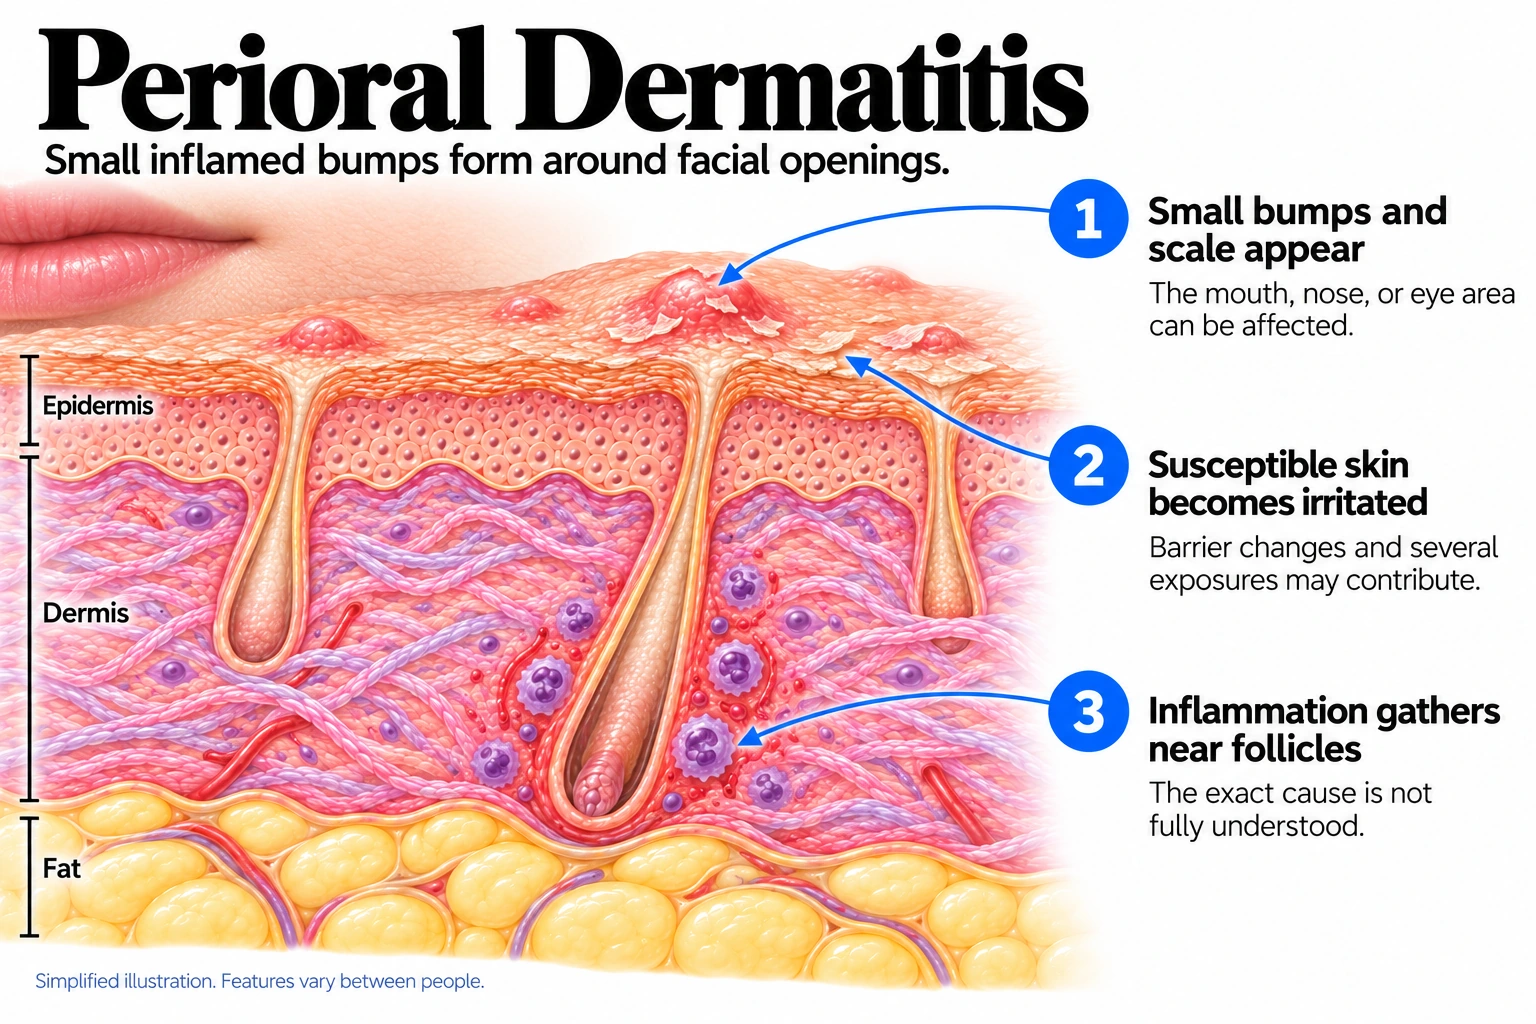
Inflammation near small facial follicles produces bumps and scale around the mouth, nose or eyes. Barrier changes and several exposures may contribute, but the exact cause is not fully understood.
- Small bumps and scale appear: The mouth, nose, or eye area can be affected.
- Susceptible skin becomes irritated: Barrier changes and several exposures may contribute.
- Inflammation gathers near follicles: The exact cause is not fully understood.
Causes and triggers
What causes Perioral Dermatitis
Causes
Why it happens
Perioral dermatitis is an inflammatory rash around the mouth. The exact cause isn't known, but it is strongly linked to steroid creams and heavy products on the face.
Risk factors
Raise the odds
- Women aged 20 to 45
- Children
- Using steroid creams on the face
Triggers
Bring it on or make it worse
- Topical or inhaled steroids (Well established)
- Heavy moisturizers and makeup (Strong link)
- Fluoride toothpaste (Possible)
- Hormone changes (Possible)
When it usually starts
When it usually starts
Perioral Dermatitis
Common in younger adult women but can also affect children and other adults.
Daily care
Daily care for Perioral Dermatitis
Strip the routine back
Gentle cleanser, light moisturizer, sunscreen, nothing else.
Rinse after your inhaler or nasal spray
Removes the residue.
Simplify makeup rather than stopping it
Light mineral makeup, removed gently.
A simple daily sunscreen
Stops the dark marks deepening.
Topical metronidazole
The long-standing first-line cream.
Topical erythromycin or clindamycin
For cases the first choice misses.
An oral tetracycline course
Clears widespread cases faster than creams.
An oral macrolide for children
Used instead of a tetracycline.
Avoid: Occlusive balms, moisturizers and oils
Thick products trap and disturb the barrier.
Avoid: Full-coverage makeup and primers
The heavier the product, the more it turns up.
Avoid: Layering actives, acids and scrubs
Stacked, they strip the barrier.
Avoid: Lip balms used constantly, and lip licking
Keeps the skin beside the lips wet.
Avoid: Face masks and anything occlusive
Heat, moisture and friction for hours.
Avoid: Hot water, harsh cleansers, over-washing
They strip a damaged barrier further.
Avoid: Fluoride toothpaste
Reported by some, though the evidence is weak.
Avoid: Stopping the prescription early
Improvement at week three is not clearance.
Avoid: Hydrocortisone
The most common self-treatment for this rash and the most common cause of it. It looks like it is working within two days, and the rash comes back worse when it stops, which pulls people into using it again. Even the mildest over-the-counter strength does this. If you are using one now, that is the thing to stop first, with your doctor's help if it was prescribed.
Avoid: Steroid creams of any strength
Prescription steroid creams do the same thing on the face as the over-the-counter one: fast improvement, then a worse rash when they stop. Stronger ones make the cycle harder to break and can thin the skin. If a steroid was prescribed for something else on your face, ask about stopping it rather than stopping it abruptly on your own.
Treatments
Treatments for Perioral Dermatitis

Acne washes, acids and scrubs
Benzoyl peroxide, strong exfoliating acids and scrubs are what most people reach for, because this looks like acne. They damage the barrier further and usually make the rash angrier. If a product is stinging more than it was on day one, that is a reason to stop it, not to push through.

Azelaic Acid
The one over-the-counter active worth using here. At 10 percent it calms the bumps and, unusually, also helps the dark marks the rash leaves behind. It is slower than the prescription version and it can sting on skin that is already burning, so start every other night.
Sulfur
A sulfur wash or lotion is a gentler option for mild cases, and it is often chosen when someone cannot use the usual prescriptions. The evidence for it in this condition is thin, and the smell puts people off. It is worth a few weeks, not a few months.
MetroGel
The long-standing first choice for perioral dermatitis, used once or twice a day for weeks. It is well tolerated on skin that is already sore, which matters here. Expect little in the first fortnight, clear improvement by weeks three to six, and keep going for two to four weeks after the skin looks clear.
Erythromycin
An antibiotic gel with a long record in this condition, often chosen for children and for people who cannot take tablets. It is mild on the skin. If you are pregnant, ask your doctor which treatment to use, since the usual alternatives are avoided.

Elidel
A non-steroid anti-inflammatory cream sometimes used to get through the rebound after a steroid is stopped, and around the eyes where other options are awkward. It calms the skin without the rebound a steroid causes. Results in this condition are mixed, and it can burn for the first few days.

Finacea
As effective as metronidazole here, and the better pick if the rash has left dark marks, because it works on both. It stings for the first week or two on inflamed skin. Applied twice a day, it is a reasonable alternative rather than a step up.
Clindamycin
An antibiotic lotion or gel kept for cases that do not settle on the first choice, sometimes paired with it. It calms the bumps rather than the flaking. It is not used on its own for long stretches, to limit resistance.

Soolantra
Used when Demodex mites around the hair follicles are thought to be part of the picture, which is more likely in a stubborn case with a lot of small pus-filled heads. Most of its evidence comes from rosacea rather than this condition. It is a second or third choice, not a starting point.

Doxycycline
A tetracycline tablet taken for six to twelve weeks, used when the rash is widespread, stubborn or around the eyes. It works here as an anti-inflammatory rather than by killing an infection, so a low dose is often enough. It makes the skin burn more easily in the sun, and it is not used in young children or in pregnancy.

Minocycline
An alternative tetracycline when doxycycline does not suit. It works about as well for this rash. It is used more cautiously because it can cause dizziness and, rarely with long use, a blue-gray discoloration of the skin.
Erythromycin
Erythromycin for children. When a child needs tablets, a macrolide is chosen instead of a tetracycline, which is avoided under about eight because of the effect on developing teeth. It clears the widespread childhood form well. Stomach upset is the usual reason people stop it.
Accutane
Accutane (isotretinoin). A low dose is occasionally used for the granulomatous form or for a case that has failed everything else, and it is rare for this condition to need it. The evidence is a handful of small reports rather than trials. It requires close monitoring and strict pregnancy prevention, and it can dry the face enough to irritate the rash at first.
Outlook
What to expect with Perioral Dermatitis
Perioral dermatitis does not usually settle by itself. The steroid cycle defines its course - a cream calms the rash within a day or two, then it returns worse once the cream stops. Once treatment starts the arc is predictable, and the first part is worse before better.
- 1
Onset · Days to two weeks
It appears over days to a couple of weeks, usually after a new product, a steroid cream, or a stretch of heavier makeup or moisturizer.
- 2
Untreated · Months
Left alone it persists for months. Steroid creams are the trap - each round calms it, then it comes back worse, needing more steroid for less benefit while the condition gets harder to treat.
- 3
Weeks one and two of treatment · The expected flare
Expect the first one to two weeks to be worse, particularly if a steroid is being withdrawn. It is temporary.
- 4
Weeks three to six · Turning the corner
This is when change becomes obvious. Stopping at the first sign of improvement is the usual cause of relapse, so finish the course.
- 5
Two to three months · Clearing
Full clearing commonly takes two to three months. This is one of the few facial rashes that genuinely goes away, and most people stay clear as long as the triggers do. When it returns the trigger is usually identifiable - a steroid cream for something else, a new heavy product, or a long routine again.
Complications
Complications to know about
The steroid rebound cycle
A steroid cream calms the rash within a day or two, then it returns worse when the cream stops. Each round tends to need more steroid for less benefit, and the condition gets harder to treat. It is the most common complication of perioral dermatitis and the main reason cases drag on for months. Stopping the steroid, and expecting one to two bad weeks, is what breaks it.
Spread around the eyes
The same rash can move up onto the eyelids and the skin around the eyes. It is uncomfortable there, it takes longer to settle, and treatment has to be chosen carefully because of how close it is to the eye. If the eyes themselves become red, gritty or sore, or your vision changes, that needs looking at on its own and soon.
Months of a visible facial rash
This rash sits in the middle of the face, it burns through the day, and it commonly takes two to three months to clear even when treatment is right. People cover it with heavier makeup, which feeds the problem, and many stop seeing friends or go to work uncomfortable. It is worth saying out loud at the appointment, because it changes nothing about the diagnosis and quite a lot about how the plan is set up.
When to get help
When to get help
When to seek care
Seek assessment for persistent facial bumps, especially after steroid cream use. Discuss a safe plan for stopping facial steroids rather than repeatedly restarting them.
Lookalikes
What else could it be?

Acne
Acne can include blackheads and whiteheads across the face, chest or back. Perioral dermatitis clusters near the mouth and usually leaves the lip border clear.

Rosacea
Rosacea usually affects the cheeks and nose and causes flushing. Perioral dermatitis clusters around the mouth, nose or eyes, often sparing a narrow lip border.
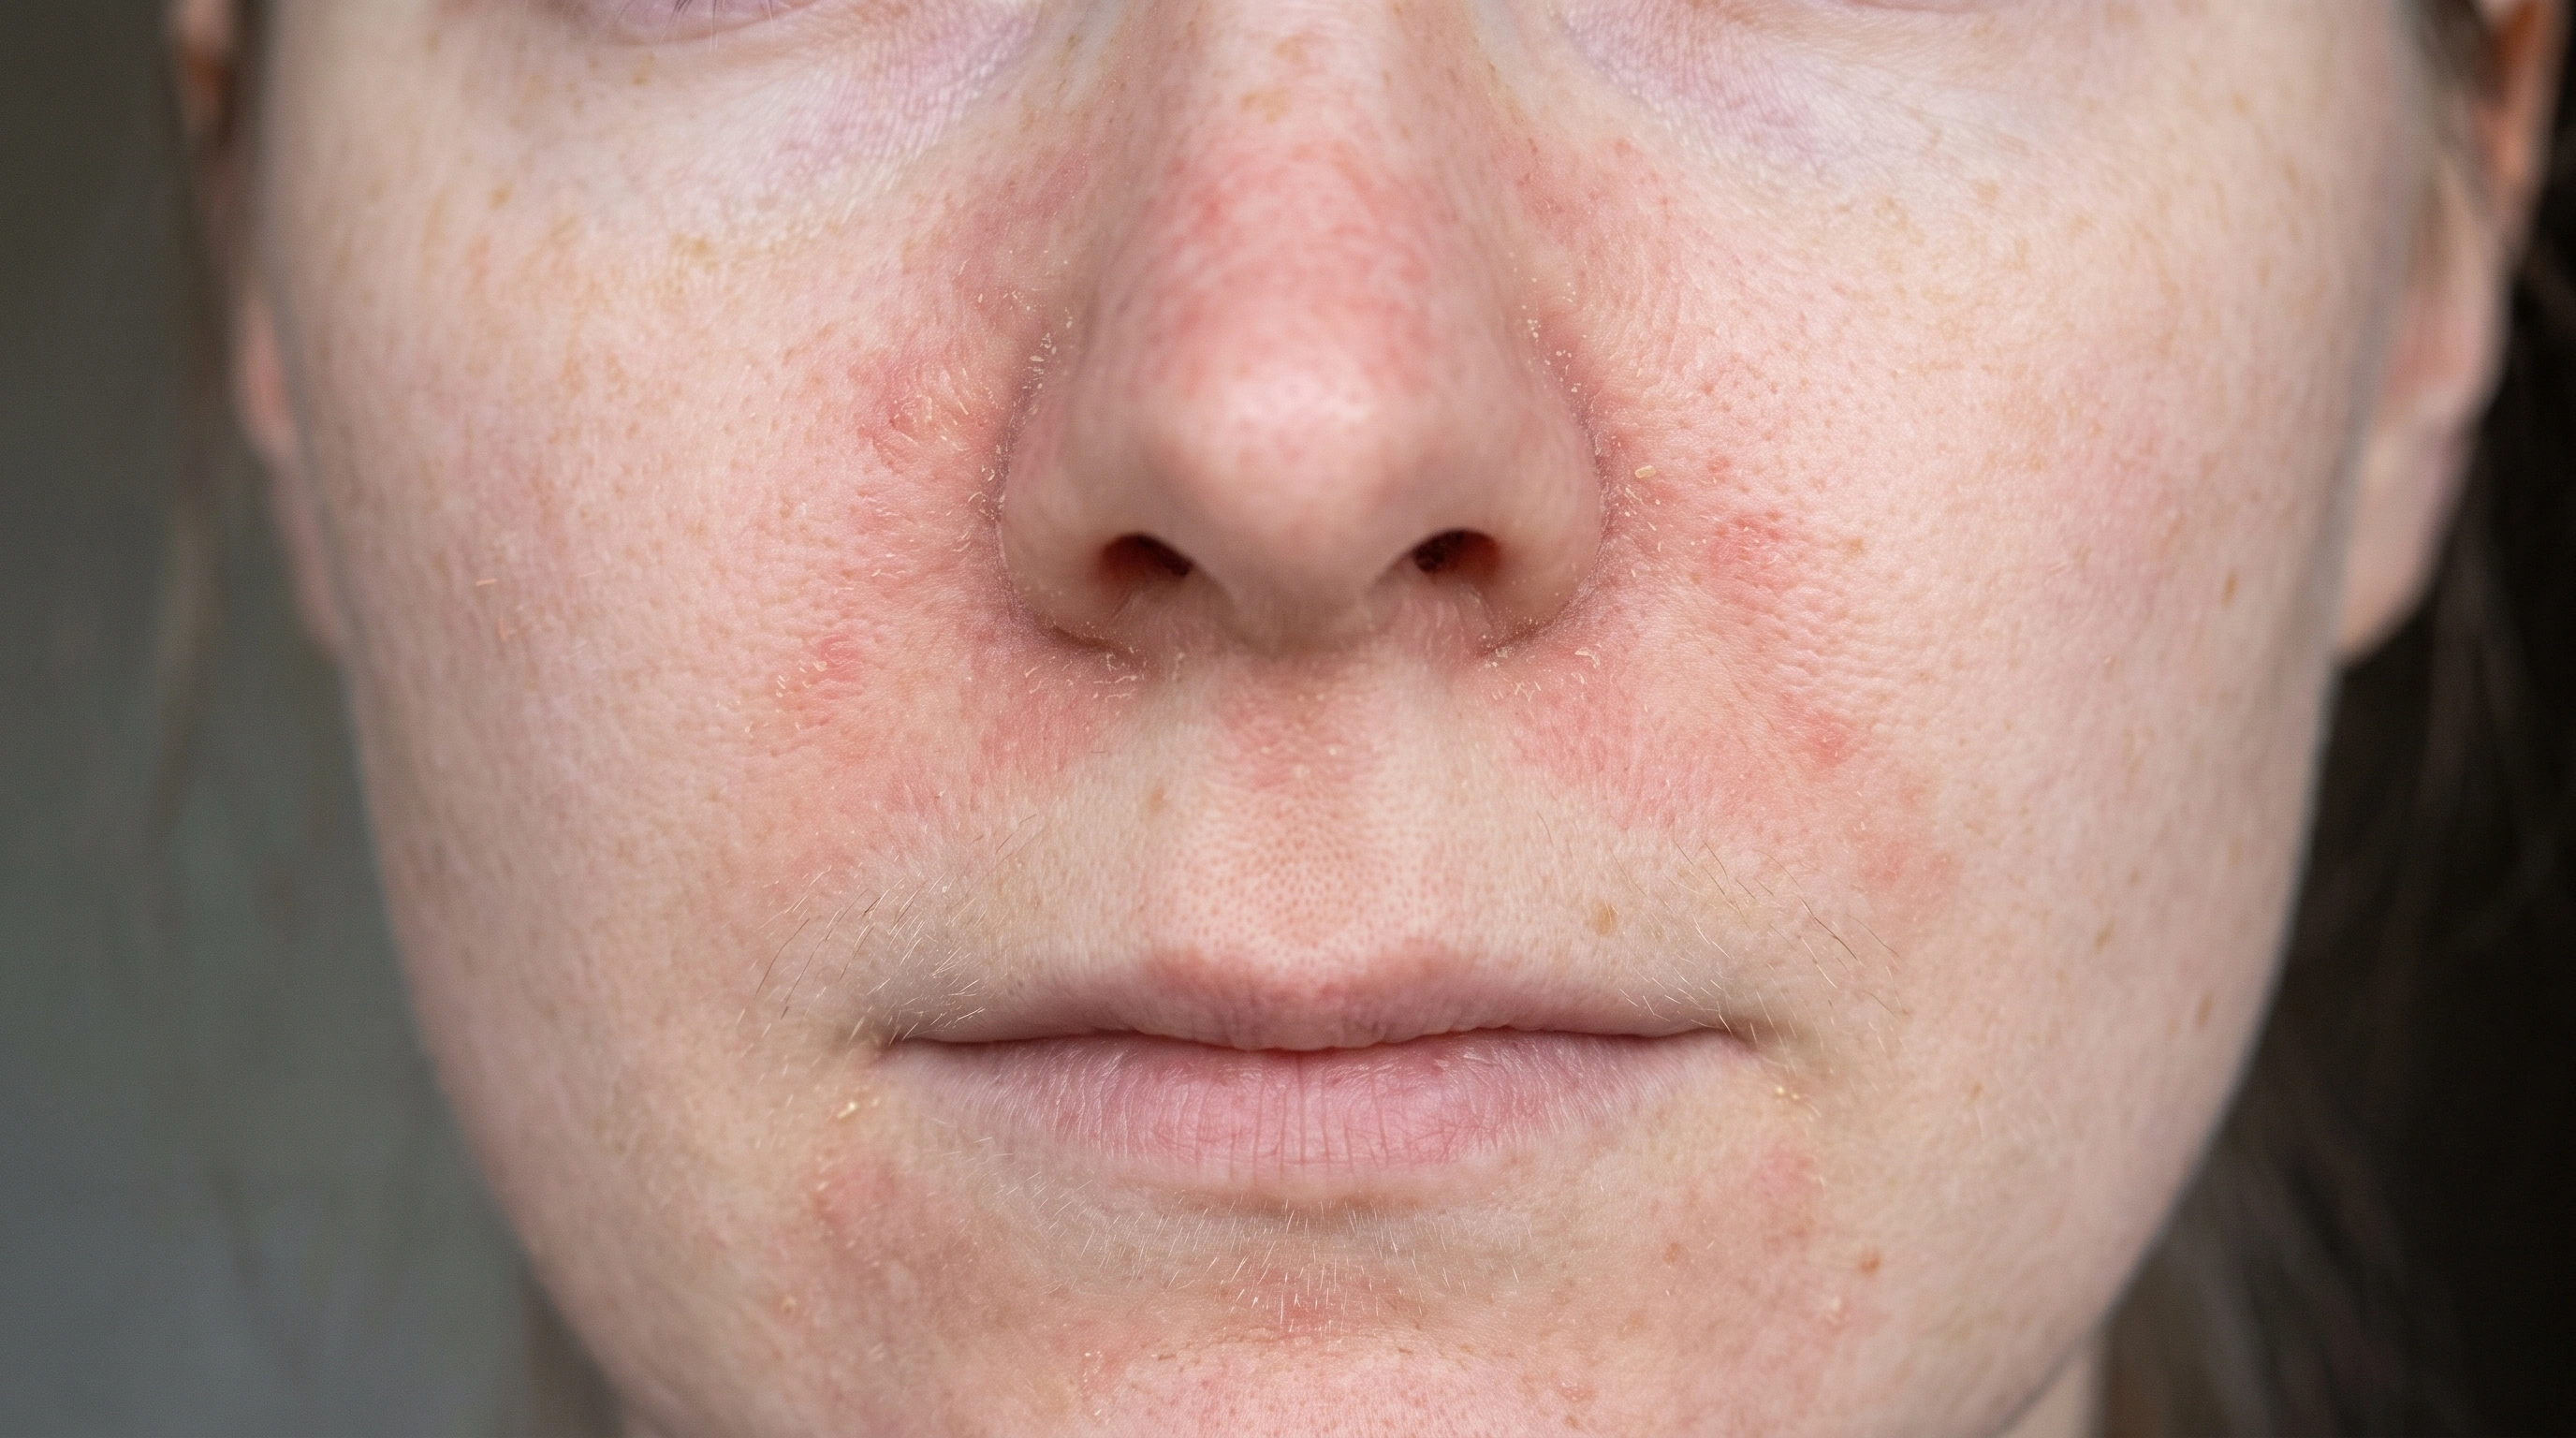
Seborrheic Dermatitis
Seborrheic dermatitis causes greasier scale, often in the eyebrows or scalp too. Perioral dermatitis is more likely to form distinct groups of small bumps.
Questions
Questions you might be asking.
Why did the steroid cream make it worse?
Steroids suppress inflammation quickly, so the rash fades within a day or two. They do nothing about what drives it, and when the cream stops the inflammation returns stronger, needing more steroid for less benefit. That is why the first step is always to stop.
How long will it take to clear?
Longer than most people expect. The first one to two weeks off a steroid are usually worse, improvement becomes clear around weeks three to six, and full clearing commonly takes two to three months. Judging at two weeks means judging it at its worst.
Is this acne?
No, though it is often treated as acne first. Acne produces blackheads and whiteheads, across the face, chest and back. Perioral dermatitis produces uniform grouped bumps around the mouth, nose or eyes, with a clear rim next to the lips, and it burns rather than itches.
Do I really have to stop all my skincare?
For a few weeks, mostly yes. Heavy occlusive products are a main trigger, and layered actives keep the barrier damaged. A gentle cleanser, a light moisturizer if needed, and sunscreen is the whole routine while it clears. Products go back one at a time afterward.
Will it come back?
Most people clear and stay clear. When it returns there is usually an identifiable reason - a steroid cream for something else, a new heavy moisturizer, or a long routine again. Knowing your trigger is most of the prevention.
Should I stop my asthma inhaler?
No. Never stop a prescribed inhaler on your own. Rinsing your mouth and washing the skin around it after every dose cuts the residue reaching your face, and your dermatologist can talk to whoever manages your asthma if the inhaler is the driver.
Sources