Melasma
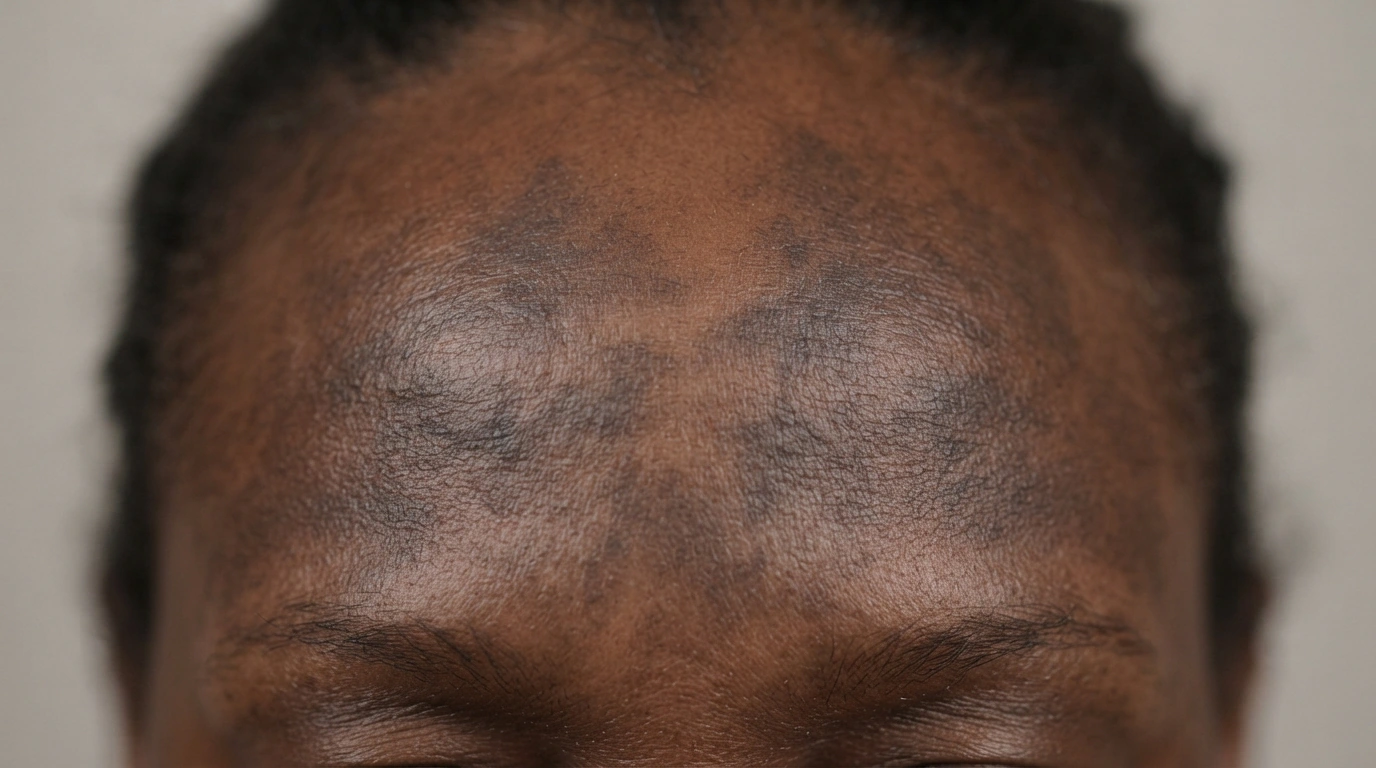
Melasma is a pigment condition that causes brown or gray-brown patches, usually across the cheeks, forehead and upper lip. It is driven by light, heat and hormones, which is why it is managed rather than cured.
Key facts
Melasma at a glance.
Typical signs
Symmetrical brown or gray patches
Common locations
Cheeks, forehead, upper lip
Expected course
Often persistent or recurrent
Treatment options
Sun protection and pigment treatments
What is it?
Top things to know about Melasma
- It is acquired facial pigmentation. It produces irregular brown or gray-brown patches, usually on both sides.
- It affects all skin tones. It is especially noticeable in more deeply pigmented skin.
- It does not cause a rash. The patches themselves usually do not scale or hurt.
- It differs from other dark marks. A single sun spot or post-rash marks need a different approach.
What it looks like
What Melasma looks like
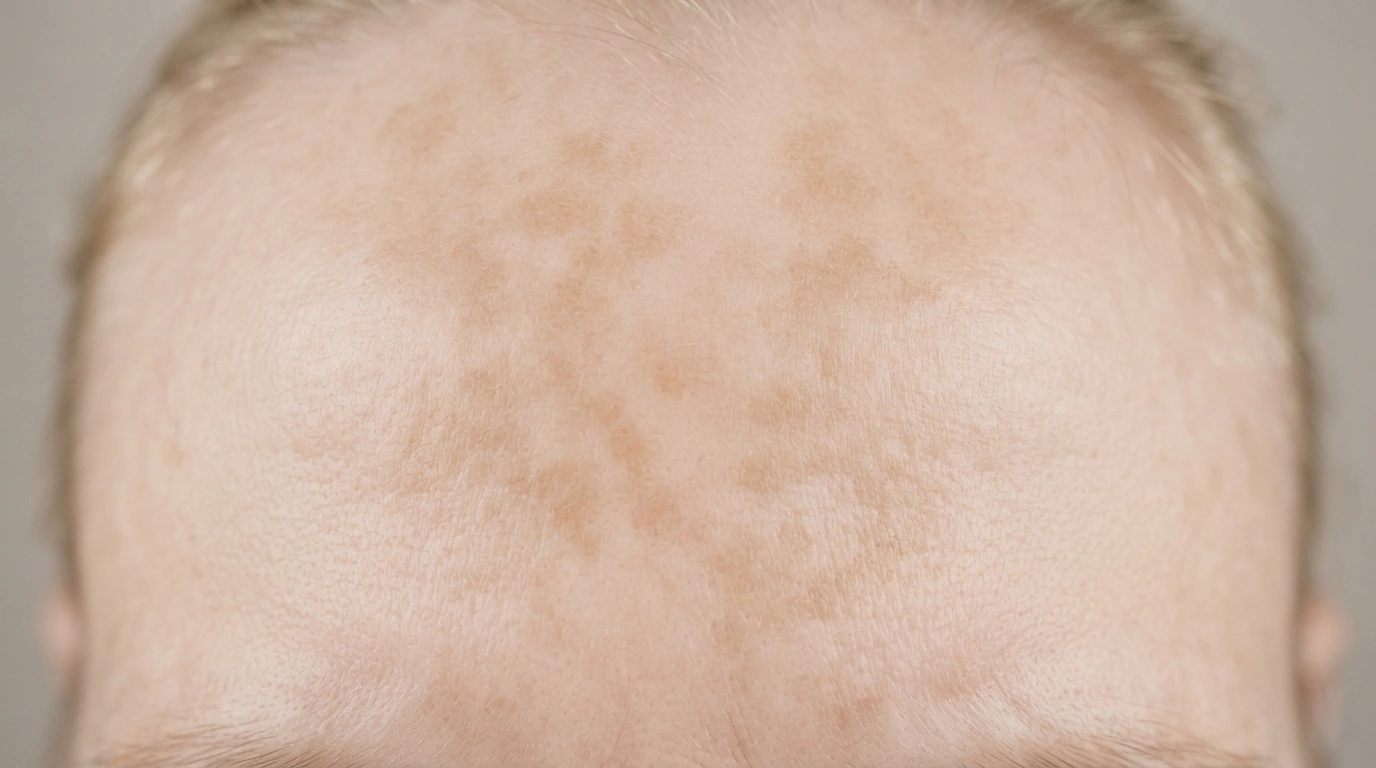
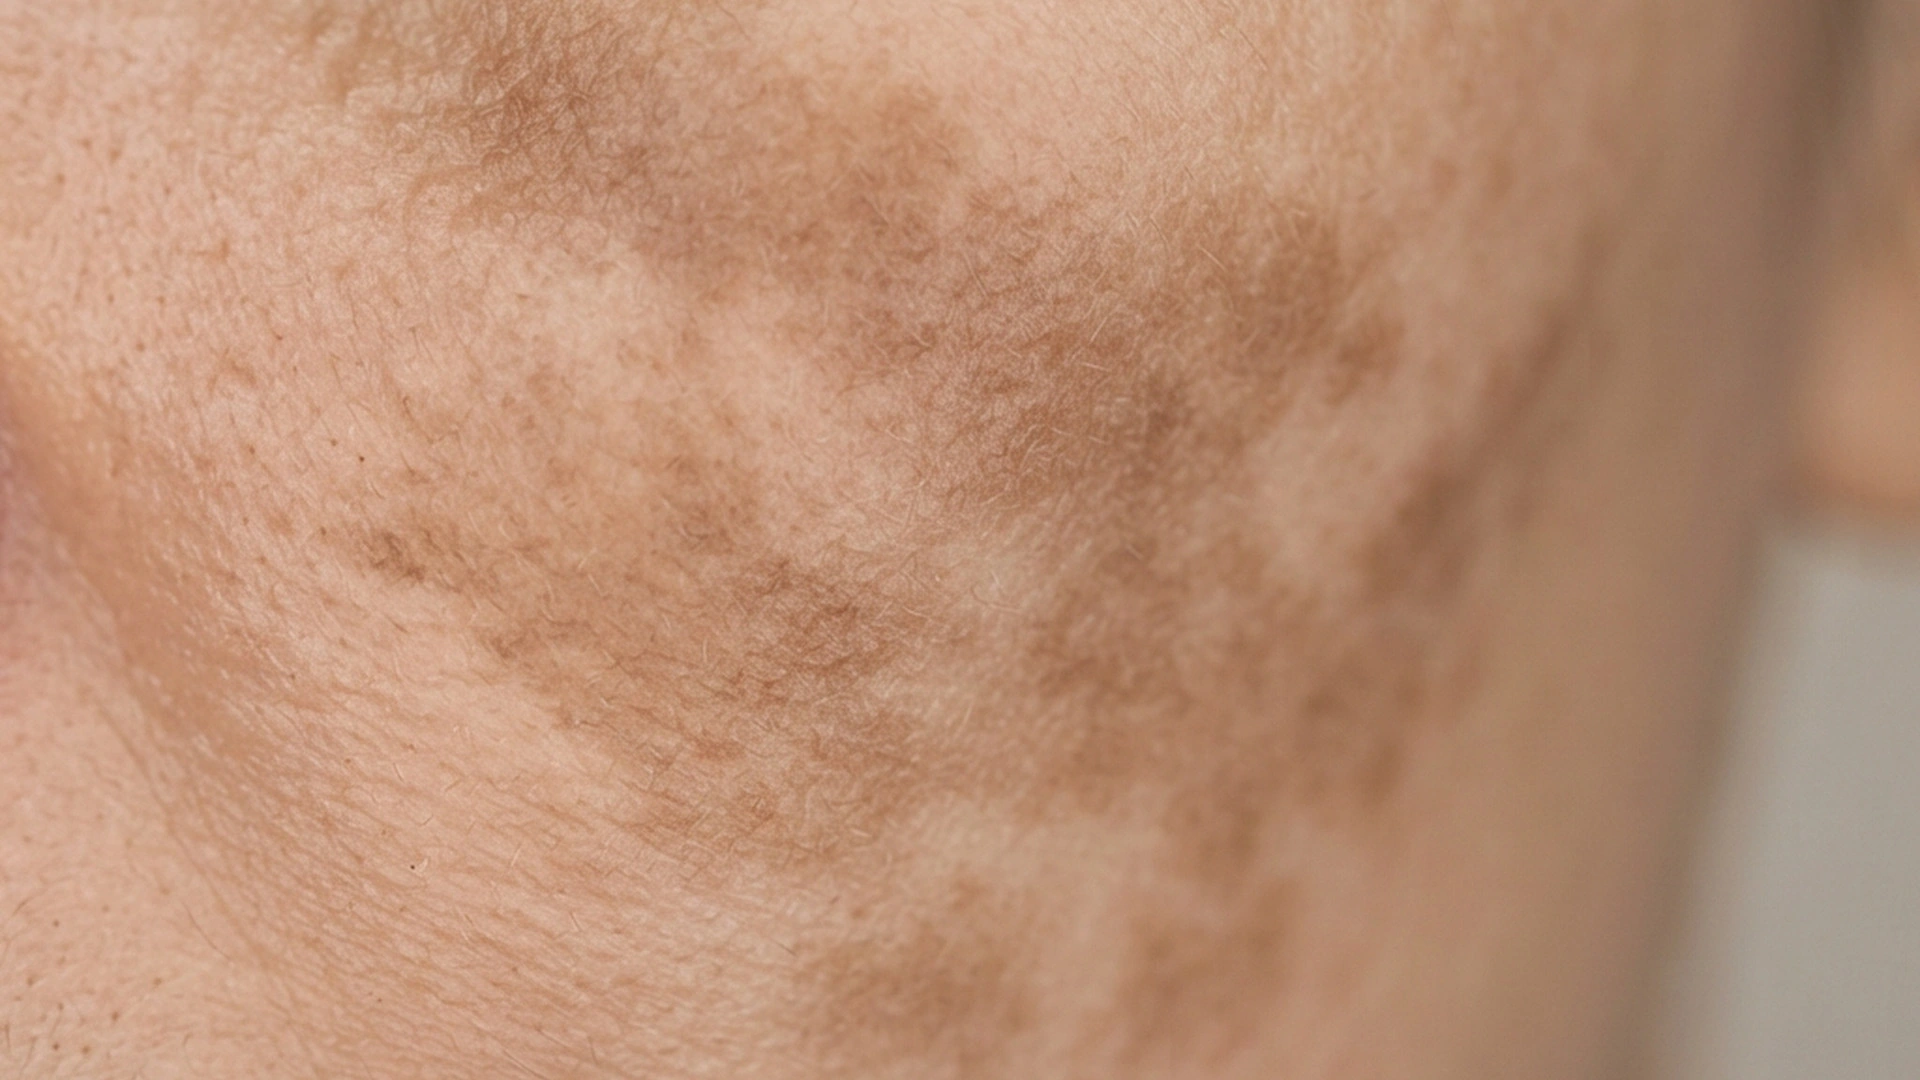
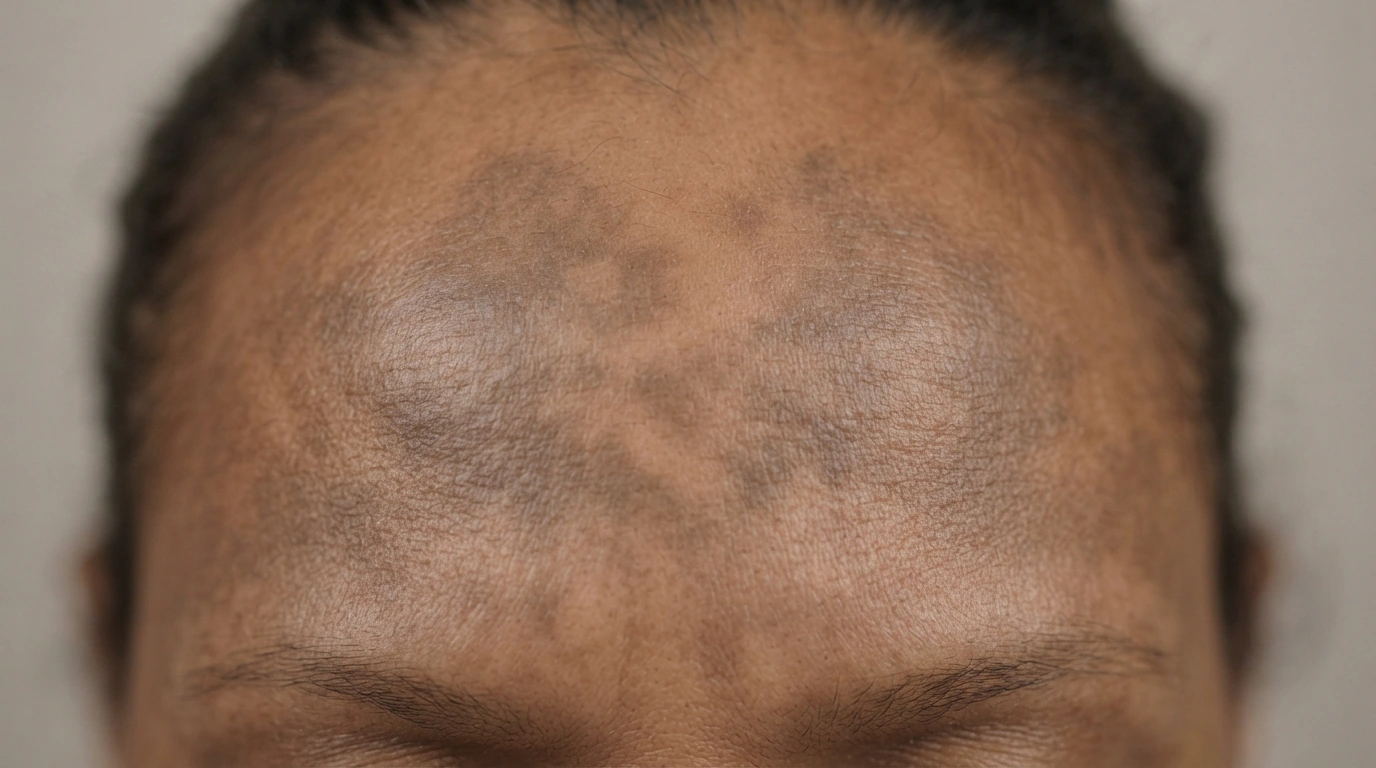
Melasma causes brown to gray-brown patches on the face, usually on both sides in a matching pattern. The most common areas are the cheeks, forehead, bridge of the nose, upper lip and chin. The patches are flat, with blurred edges, and don't itch or hurt. Melasma is much more common in women and is triggered by sunlight, visible light, heat and hormones such as pregnancy and birth control pills.
Melasma is often described by its pattern on the face or how deep the pigment sits.
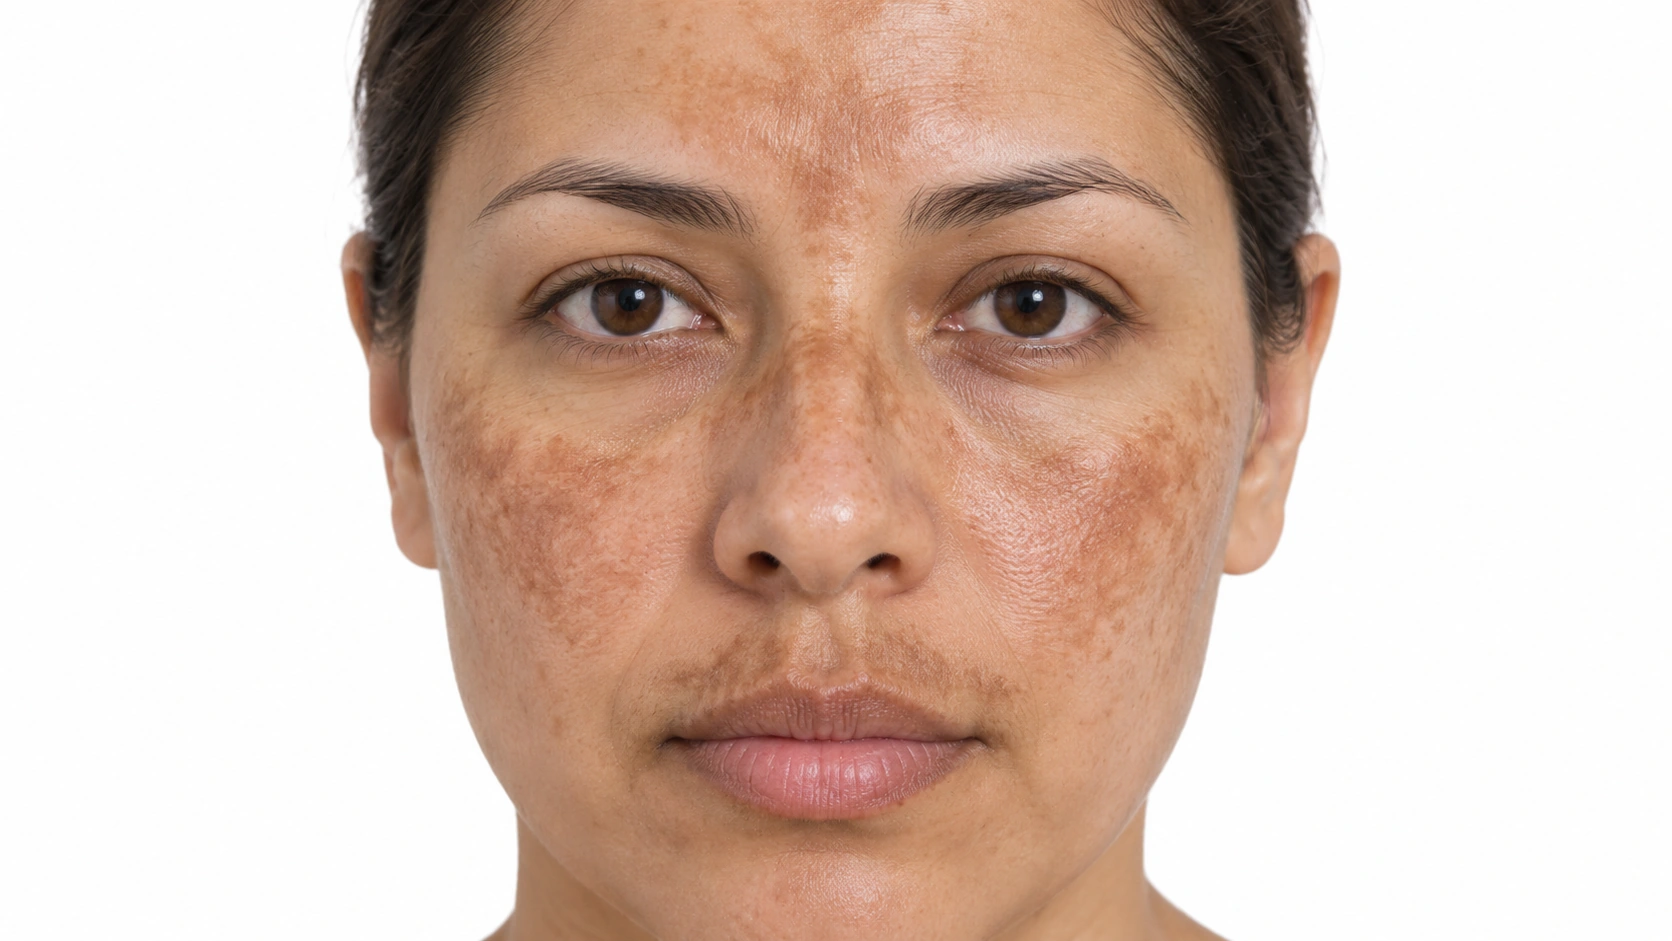
Centrofacial melasma
Forehead, cheeks, nose and lip; most common.
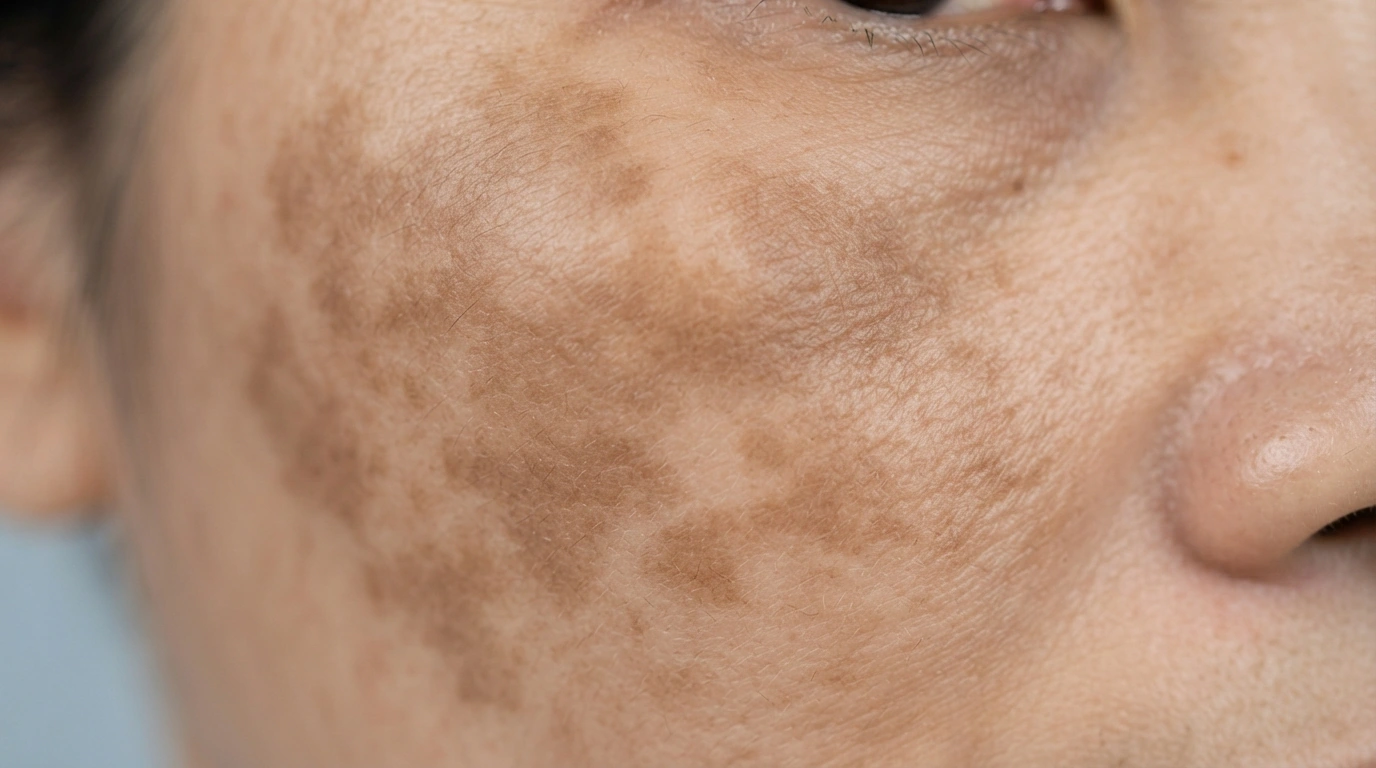
Malar melasma
Cheeks and nose.
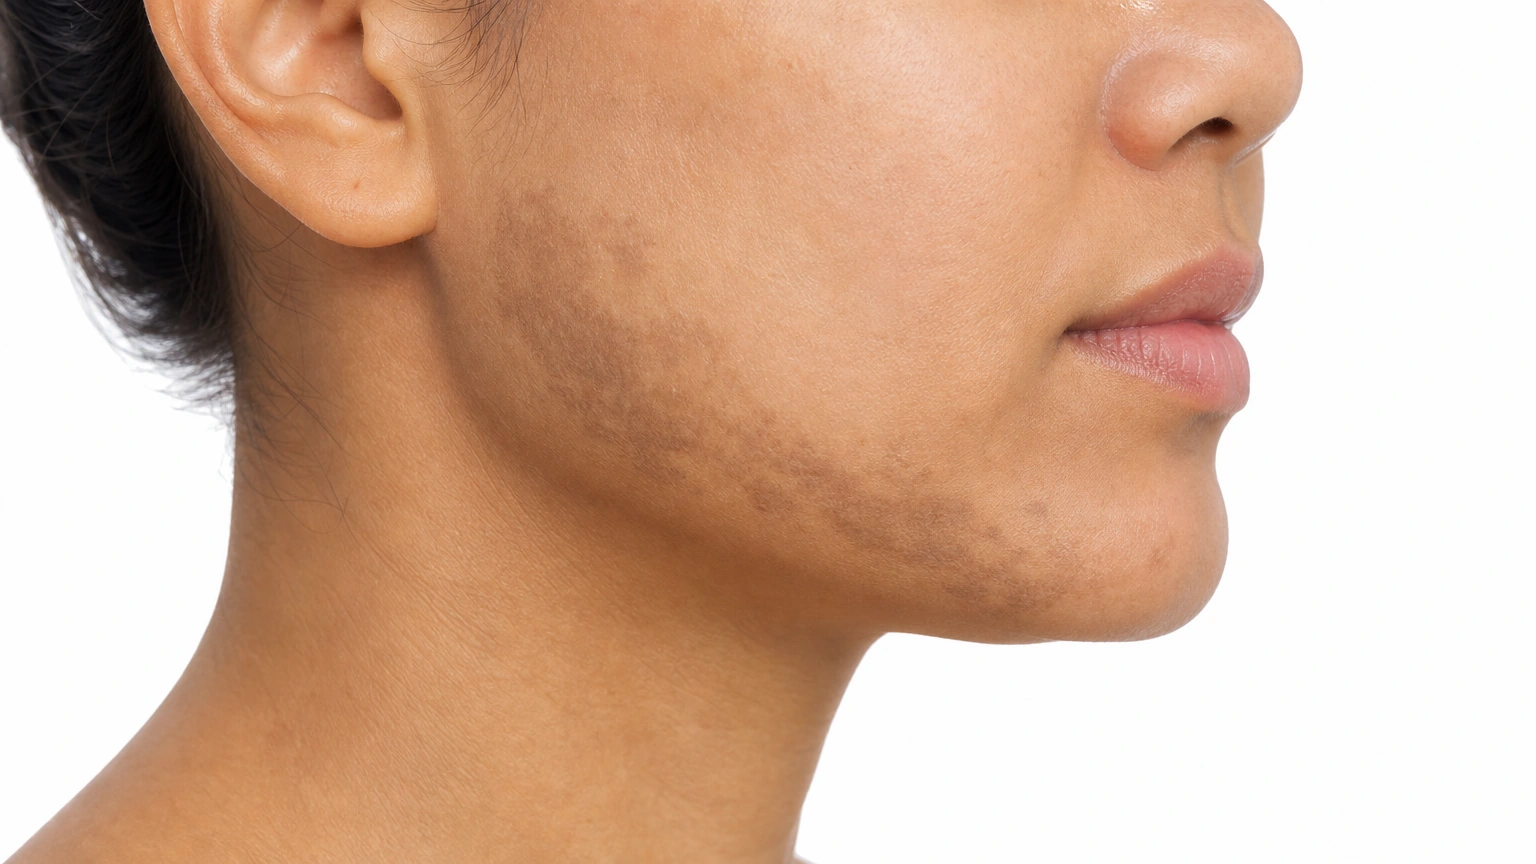
Mandibular melasma
Along the jawline.
Where it shows up
Melasma commonly forms symmetrical facial pigmentation on the cheeks, forehead and upper lip.
Face
Facial locations.
On different skin tones
Melasma on different skin tones
Melasma is more common in medium and darker skin, especially in people of Latin American, Asian, Middle Eastern, African and South Asian descent. On lighter skin, patches look light brown. On darker skin, they look darker brown or gray-brown. Darker skin needs careful treatment because harsh peels and lasers can make pigment worse.
What happens in Melasma?
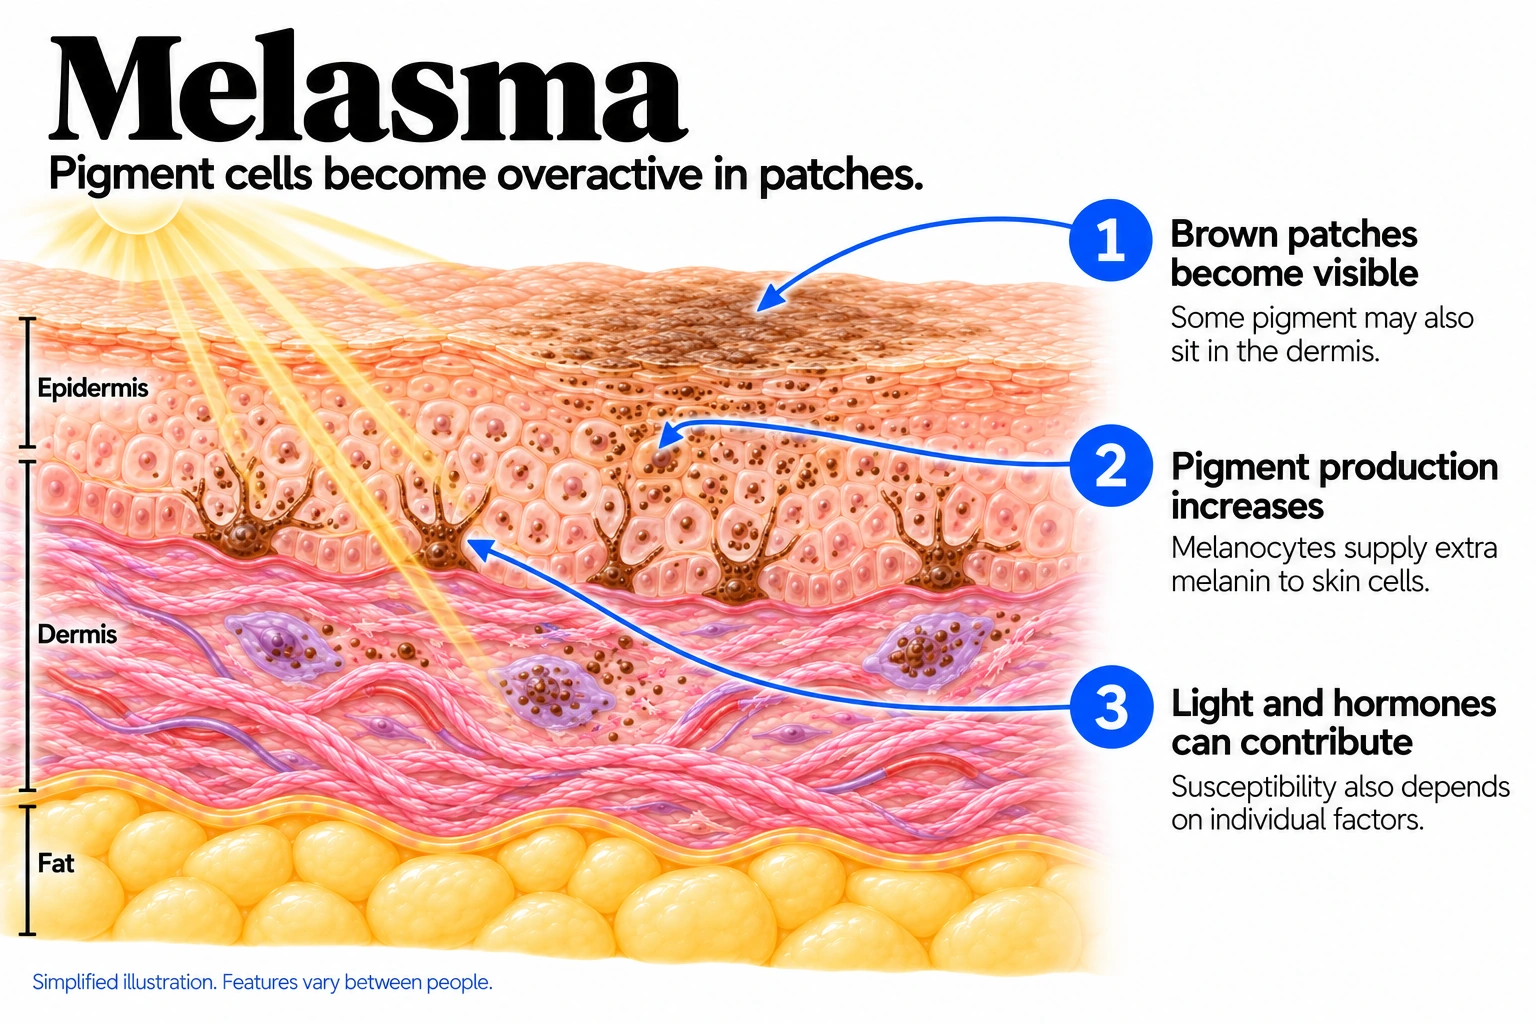
Pigment cells become more active and supply extra melanin to patches of skin. Light, hormones and individual susceptibility contribute, and some pigment may also be present deeper in the skin.
- Brown patches become visible: Some pigment may also sit in the dermis.
- Pigment production increases: Melanocytes supply extra melanin to skin cells.
- Light and hormones can contribute: Susceptibility also depends on individual factors.
Causes and triggers
What causes Melasma
Causes
Why it happens
Melasma happens when pigment cells become overactive in response to light and hormones. Visible light and heat also play a part, not just ultraviolet light.
About half of people with melasma have a family member with it.
Risk factors
Raise the odds
- Female sex
- Medium to darker skin
- Family history
Triggers
Bring it on or make it worse
- Sun and visible light (Well established)
- Pregnancy (Well established)
- Birth control pills (Strong link)
- Heat (Strong link)
- Some skincare that irritates (Possible)
When it usually starts
When it usually starts
Melasma
Usually appears in adult life and may begin during pregnancy or with hormonal changes.
Daily care
Daily care for Melasma
A tinted mineral sunscreen every day
Broad spectrum, SPF 30 or higher, with iron oxides.
Shade, a wide-brimmed hat and sunglasses
Does what no sunscreen can.
Keep the whole routine gentle
Use a gentle cleanser, moisturizer and tinted sunscreen.
Cysteamine
Over the counter, a short contact treatment.
A conversation about hormonal triggers
Ask whether an alternative makes sense.
Discuss hormonal triggers; do not stop contraception on your own
Shift the hormones that prime pigment cells — never stop one on your own.
Ask about sun precautions for photosensitizing medicines; do not stop them yourself
Ask your prescriber rather than stopping anything.
Avoid: Sun on unprotected skin
The largest driver, and it adds up all season.
Avoid: Visible light
Ordinary daylight drives melasma on deeper skin tones.
Avoid: Heat
Stoves, saunas, hot yoga, steam and hot cars activate pigment cells.
Avoid: Waxing and threading the upper lip
Repeated waxing over a patch darkens it.
Avoid: Irritating skincare
If it stings on a patch, it is adding to the problem.
Avoid: Tanning beds
All of the light, none of the upside.
Avoid: Stopping treatment when it looks better
A faded patch is still primed.
Avoid: A steroid cream on its own
Steroid creams do fade pigment for a while, which is why they turn up in unregulated lightening products, but they are not a melasma treatment. Used on the face for months they thin the skin, bring up broken vessels and can cause a rash around the mouth, and the pigment comes back when they stop. In melasma a steroid belongs only inside a supervised combination cream.
Treatments
Treatments for Melasma

Azelaic Acid
Calms overactive pigment cells without bleaching the normal skin around them, which is why it can be used for months at a time instead of in short courses. That makes it one of the better options for holding a result after a course of hydroquinone. The over-the-counter strength works slowly, and the prescription strength works better.
Cysteamine
Put on dry skin, left for about 15 minutes and then washed off rather than left on overnight. It is the over-the-counter option with the most real trial evidence in melasma, and it suits people who want to avoid hydroquinone or need something for the gaps between courses. The smell is the usual reason people give up on it.

Tranexamic Acid
Works on a different part of melasma from the pigment-blocking creams. It quietens the signals coming from blood vessels and the skin underneath, which is the fourth step and the reason patches keep returning. That makes it a useful addition for stubborn melasma rather than a first treatment on its own. Twice a day, judged at three months.

Niacinamide
Slows the handover of pigment from pigment cells to the skin cells around them. Modest on its own and not something that will clear a patch, but it is well tolerated and it does not sting, which counts for a lot in a condition where irritation makes things worse. It sits comfortably alongside the stronger treatments.
Vitamin C
Lightens surface pigment a little and helps sunscreen do its job during the day. It is a reasonable thing to try in the three months before asking for a prescription, and a reasonable thing to keep for maintenance afterwards. On its own it rarely shifts an established patch, and it does not replace sun protection.

Alpha Arbutin
A gentler relative of hydroquinone that releases a small amount of it slowly in the skin. It suits people who want a lightening step running between supervised courses of the prescription version. The effect is milder and slower, and the studies behind it in melasma are small.

Kojic Acid
Blocks the same pigment-making enzyme hydroquinone does, more weakly. It is nearly always sold combined with other lightening ingredients, and the studies showing it work are studies of those combinations rather than of kojic acid alone. It stings some people, and stinging on a melasma patch tends to darken it.

Licorice Root Extract
A common ingredient in brightening products, resting mainly on laboratory work rather than trials in people with melasma. It is gentle and unlikely to cause trouble, and it is also unlikely to be the thing that clears a patch. If a routine only has room for one active, this is not the one to pick.
Triple combination cream
Hydroquinone, a retinoid and a mild steroid in one cream, used at night on the patches. It is the most effective topical treatment for melasma and the one with the best trial evidence, given as a course of a few months rather than indefinitely. It is also the one that most needs a doctor watching it, because the steroid thins skin with long use and the hydroquinone is meant to be stopped and restarted.

Hydroquinone 4%
The most established single prescription cream for melasma, applied thinly at night to the patches only. It is used in courses of about three to four months with breaks in between, not continuously for years — unbroken long-term use at high strength is what causes the blue-black discoloration people have heard about. Expect the first month to look like nothing is happening.

Tretinoin
Speeds up how quickly pigmented skin cells are shed, and helps the other creams get in, which is why it is more often part of a combination than used alone. Used by itself it works slowly and it can irritate, and irritation darkens melasma, so it is started at a low strength a few nights a week. Ask your doctor about it if you are pregnant or trying to become pregnant.
Oral tranexamic acid
A low-dose tablet, usually taken for a few months, for melasma that has not answered creams and daily sun protection. It works on the blood vessel and signalling side of the condition rather than by bleaching, and the trials behind it are reasonable. It is not for everyone: a history of blood clots or certain other risks rules it out, so it comes after a proper history. Melasma usually returns once it is stopped, so sun protection carries on.

A review of hormonal contraception
The combined pill, the patch, the implant and menopausal hormone therapy can all set melasma off or keep it dark. Stopping sometimes helps and sometimes does not, and it can take many months to show. Never stop a prescribed hormone on your own. Ask the prescriber whether a different method makes sense, and weigh that against what the contraception is doing for you.
Chemical Peel
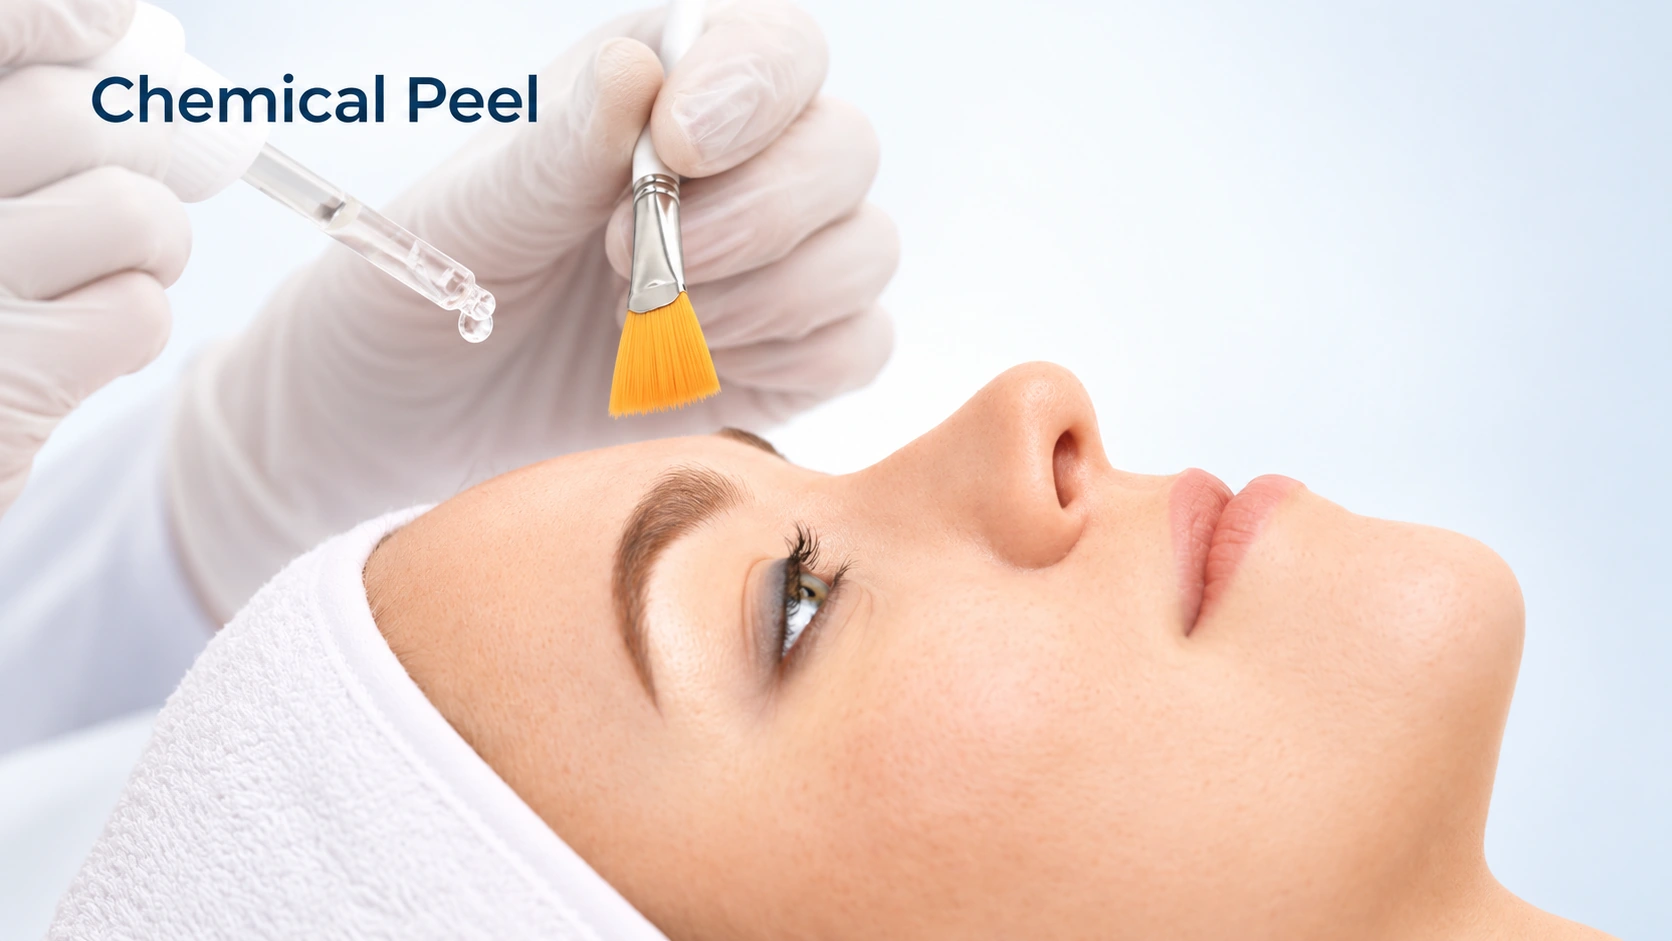
Light peels, spaced out, speed up the clearing of surface pigment when they are added to creams and sun protection. They are an addition and never a replacement. Depth is the whole issue: a peel strong enough to leave the skin red and peeling can inflame it and leave the patch darker than it started, which is one of the commonest ways melasma gets worse.
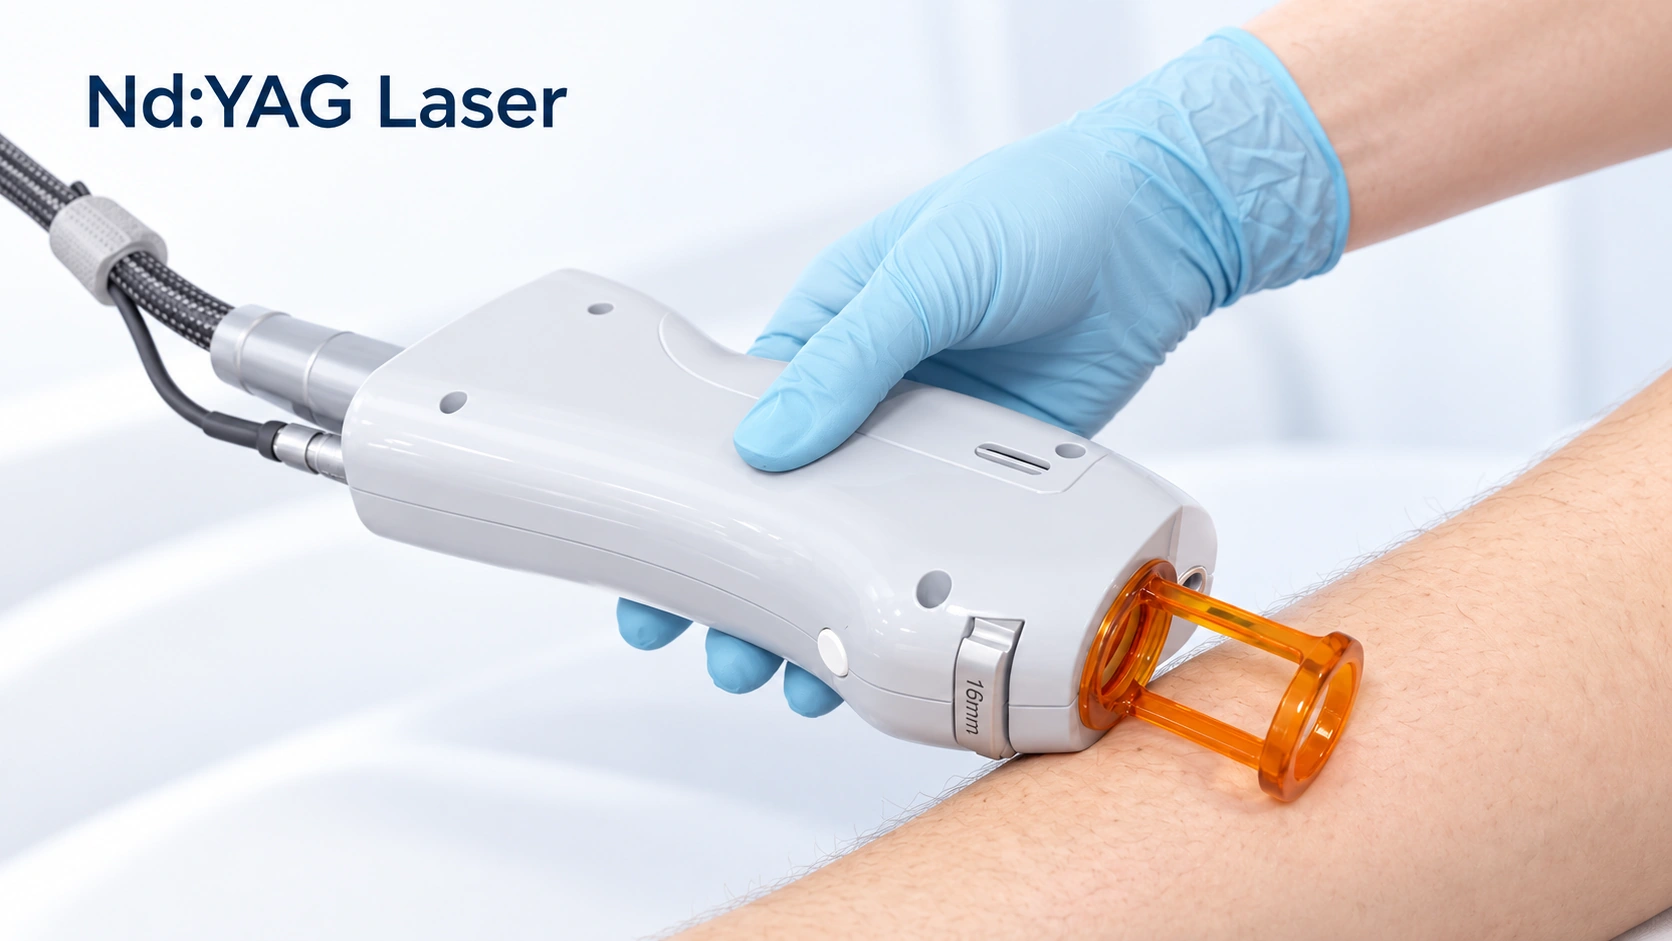
Nd:YAG Laser
Used at low energy over several sessions to break up pigment that creams reach poorly. It can lighten stubborn patches, and the improvement often fades over the following months if creams and daily sun protection are not carrying on behind it. Pushed too hard it causes patchy loss of color or rebound darkening, so settings stay low and a test patch first is sensible.
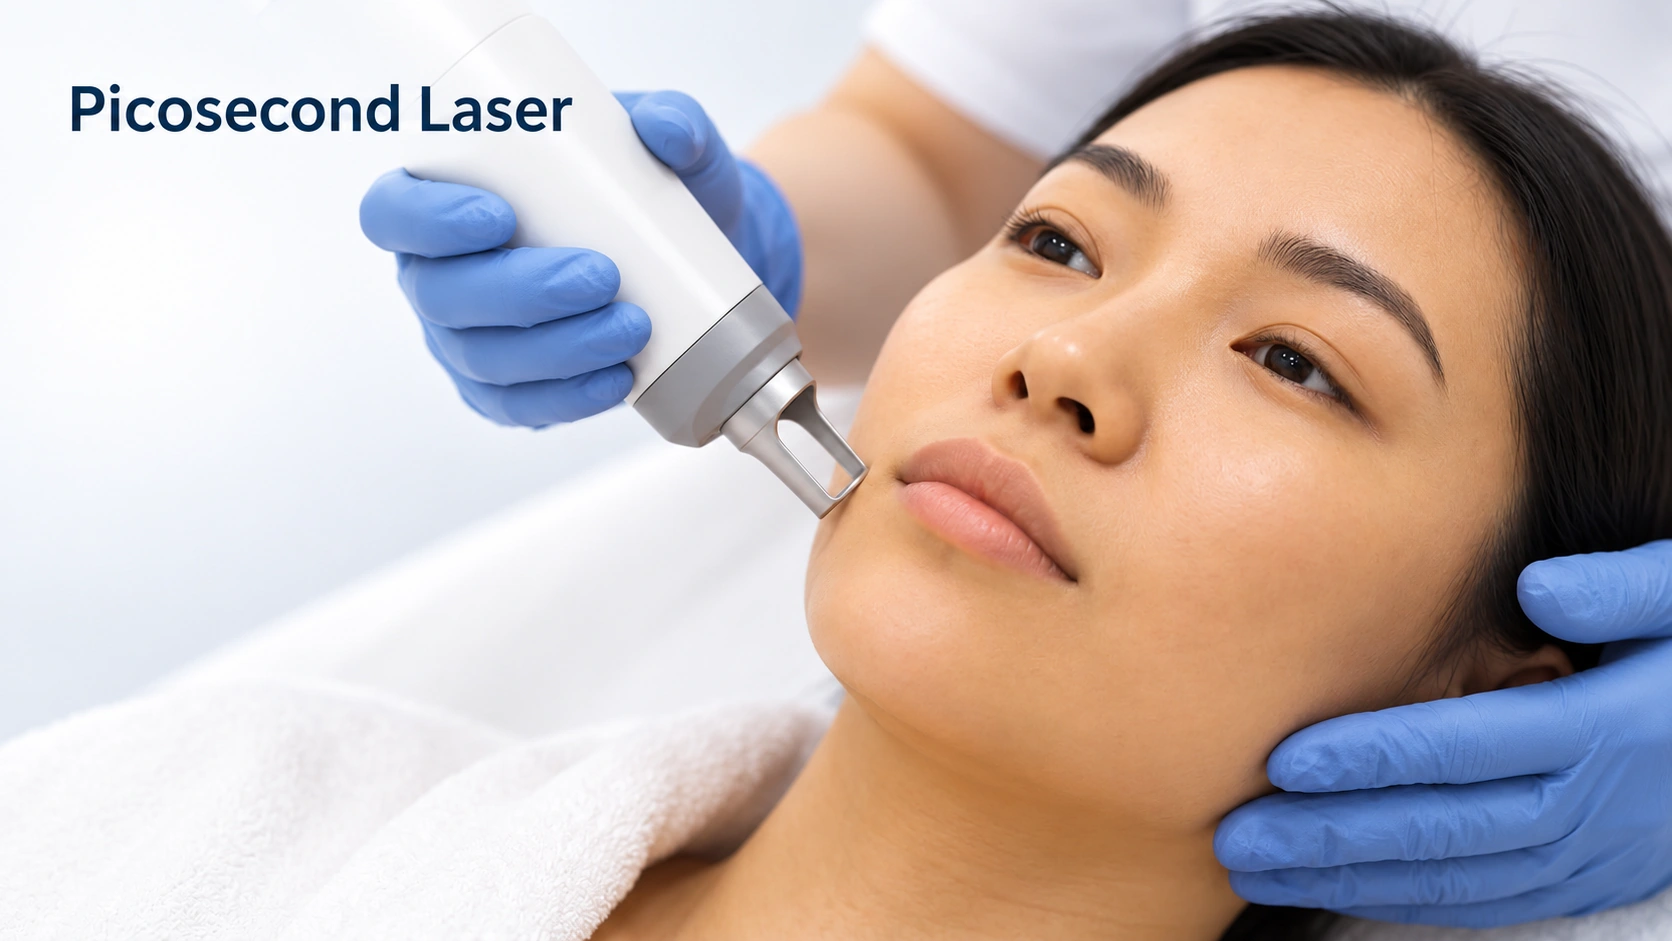
Picosecond Laser
A newer laser that delivers very short pulses at low energy, aimed at the deeper pigment creams struggle with. The melasma studies so far are small and cautiously encouraging. Like every device used here it is an addition to creams and sun protection rather than a shortcut past them, and results still fade without them.

Microneedling
Fine needles make temporary channels that help tranexamic acid or other treatments reach deeper, and that combination is where the evidence sits — not needling on its own. It has to be done gently. Aggressive needling inflames the skin, and inflamed skin with active pigment cells makes more pigment, not less.
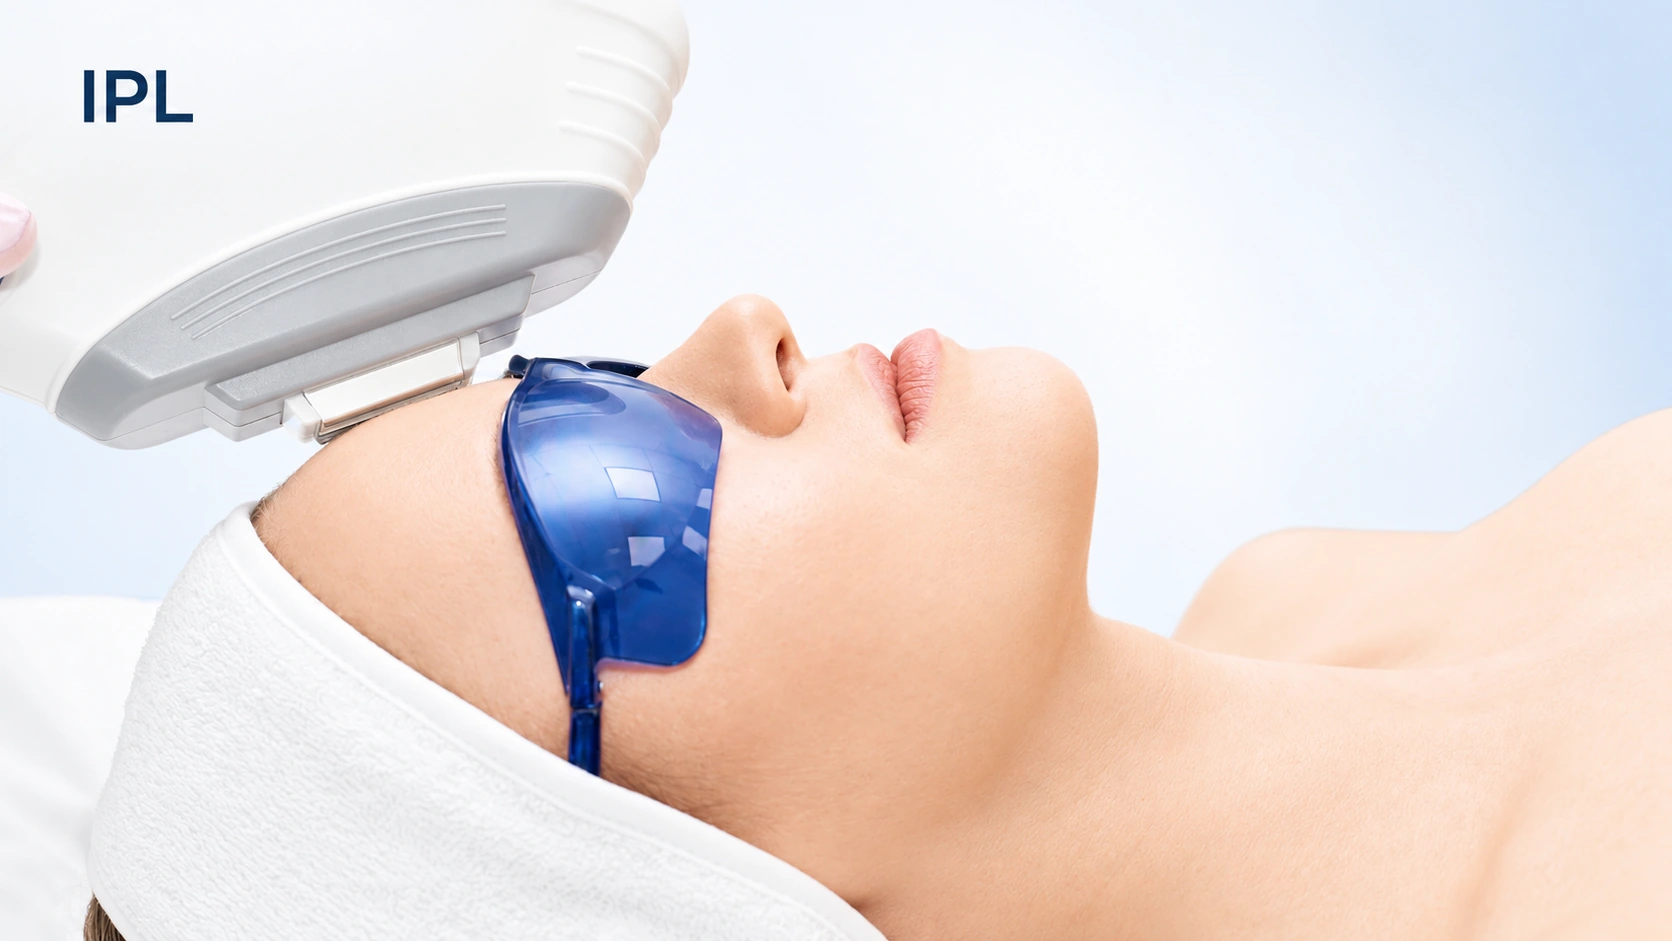
IPL
IPL. Often offered for facial pigment, and often the wrong choice for melasma. It can lighten patches briefly and then bring them back darker within weeks, because the heat it delivers is itself a trigger for pigment cells. It works far better on sun spots, which is part of why telling the two apart matters before booking anything.

Fractional CO2 Laser
An ablative resurfacing laser with a real risk of making melasma worse, particularly on medium and deep skin tones. Any benefit tends to be short-lived and the rebound darkening can last a long time. If a clinic is offering aggressive resurfacing as the answer to melasma, that is a reason to get a second opinion.
Outlook
What to expect with Melasma
Melasma follows the seasons. Patches darken through spring and summer and lighten through autumn and winter. A good winter can look like a cure, which is exactly when people stop their sunscreen and lose the ground they gained.
- 1
First appearance · Twenties to forties
Melasma rarely starts in childhood. A first appearance after menopause deserves a second look, to be sure it is melasma.
- 2
After the trigger ends · Months to a year
Pregnancy melasma often fades in the months after delivery, and many people are close to clear within a year. It does not always clear completely, and it usually returns in a later pregnancy. Melasma from the pill or hormone therapy may improve after stopping, but that takes many months, and stopping is a decision for the doctor who prescribed it.
- 3
Left alone · Years
Untreated melasma stays for years rather than clearing.
- 4
Treated · A few months
Improvement builds over a few months rather than arriving at once.
- 5
Long term · Ongoing
Relapse is expected behavior, not a sign something went wrong. Many people find melasma settles as hormone levels change with age, though sun protection still matters.
Complications
Complications to know about
Post-Inflammatory Hyperpigmentation
Melasma is the condition where pushing hard backfires most often. A strong peel, a high-energy laser or an irritating cream can inflame the skin and leave it more pigmented than it began, and that extra pigment can take many months to settle. It is the reason melasma is treated gently and slowly, and the reason a test patch is worth doing before any device is used across the whole face.
Ochronosis from lightening creams
Long, unbroken use of high-strength hydroquinone, usually from creams bought outside a doctor's care, can leave a blue-black speckled discoloration in the treated area. It is uncommon, and it is much harder to treat than the melasma was. It is avoided by using hydroquinone in supervised courses with breaks rather than continuously for years. Creams sold for lightening outside medical care may also contain strong steroids or mercury, which bring problems of their own.
Living with it day to day
Melasma does not hurt and is not dangerous, which is exactly why its effect gets underestimated. People describe avoiding photographs, spending time and money on makeup that only half covers it, and feeling worse every summer as it darkens. It is a reasonable thing to ask for treatment for, and saying it out loud in the appointment usually changes what gets offered.
When to get help
When to get help
When to seek care
Seek assessment for an uncertain pigment change or before stronger fading treatments. Review pregnancy safety and avoid unsupervised bleaching products.
Lookalikes
What else could it be?

Post-Inflammatory Hyperpigmentation
Melasma usually forms broad, matching patches on both cheeks. Post-inflammatory dark marks follow the outline of an earlier spot or rash instead.
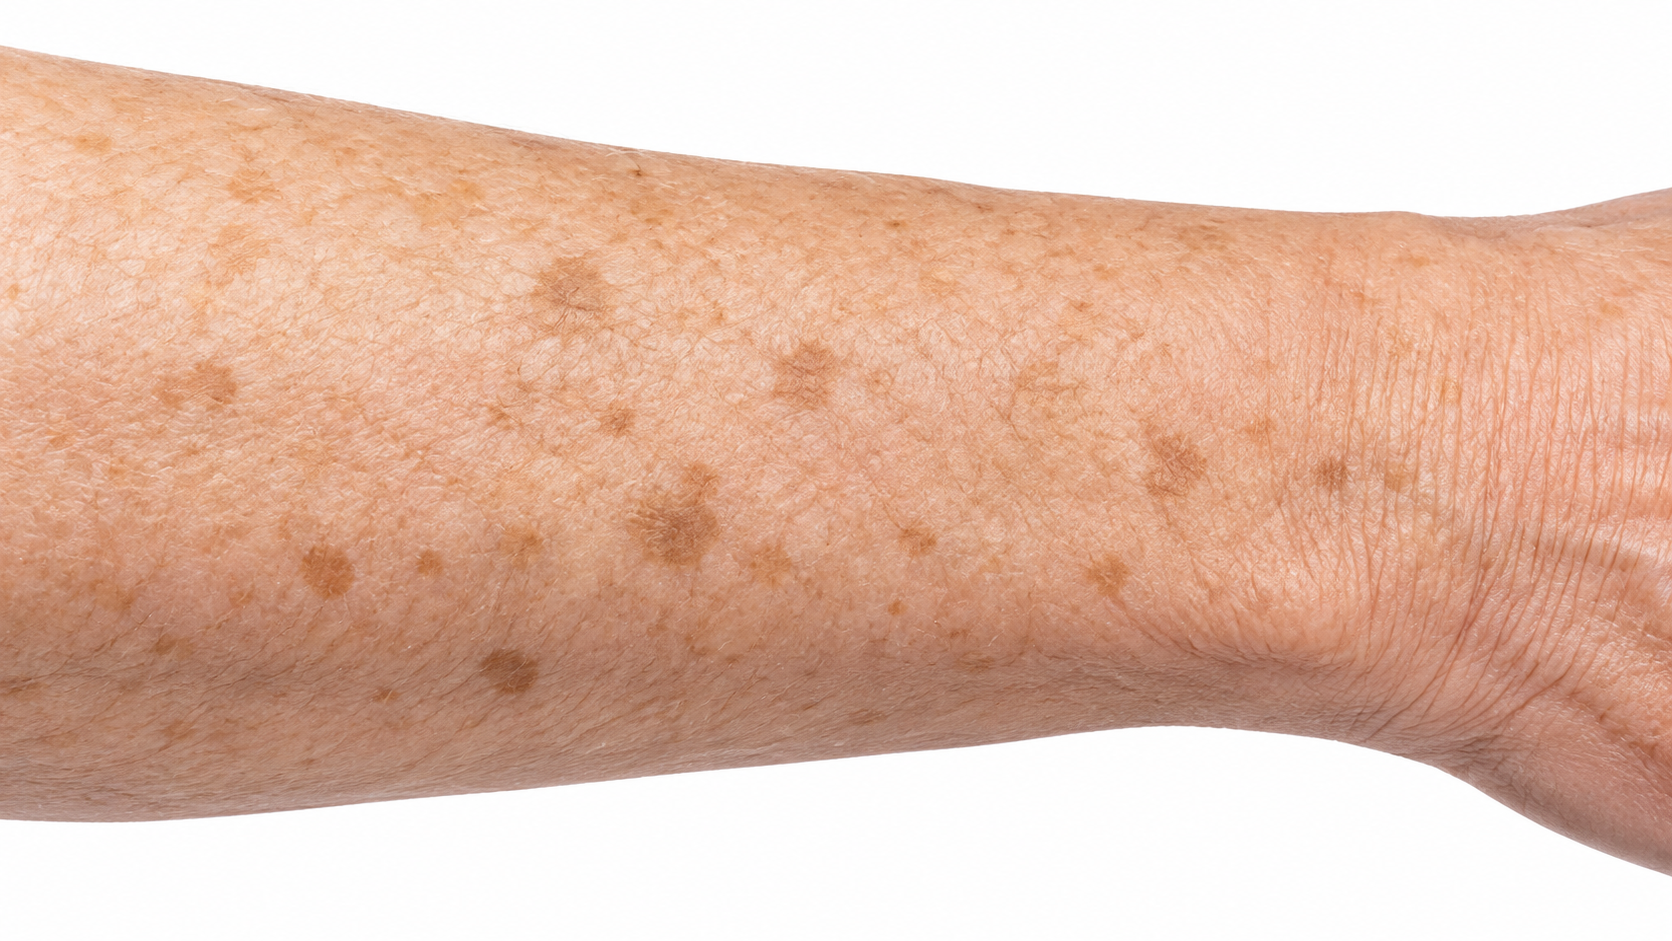
Sun Spots
Sun spots are usually small, separate marks with clear edges. Melasma forms larger patches with softer edges, often matching on both sides of the face.
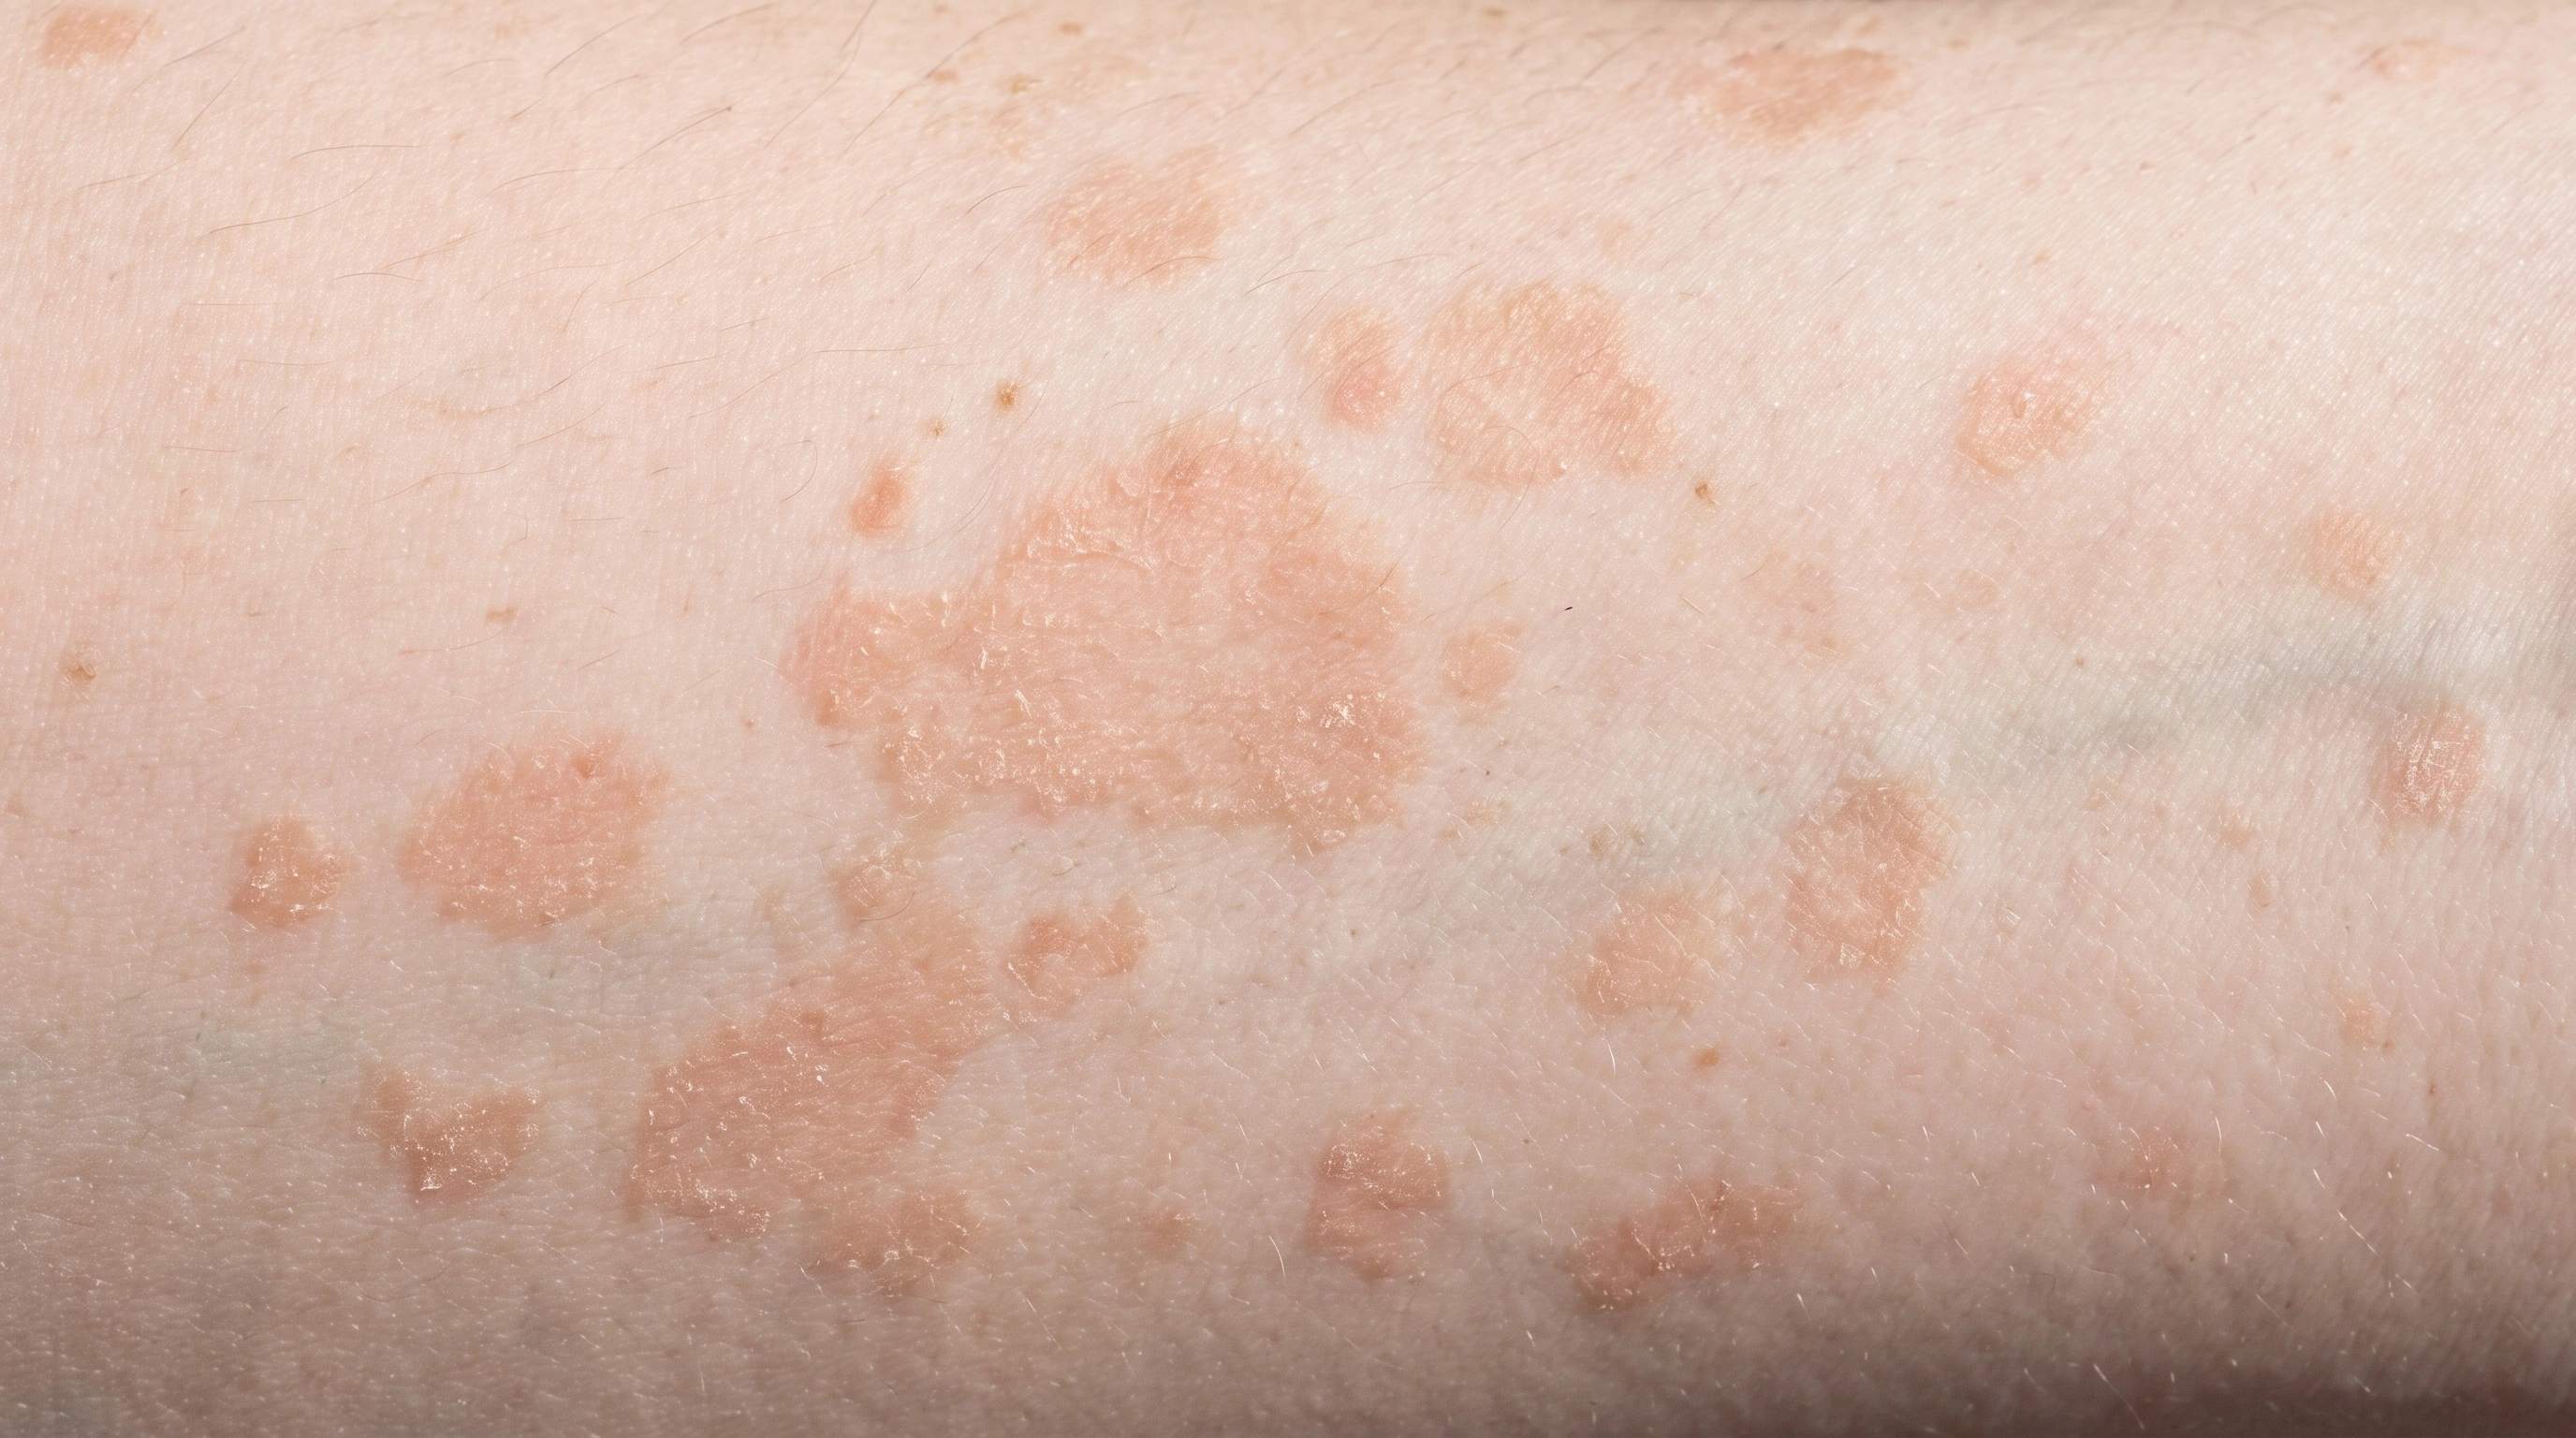
Tinea Versicolor
Tinea versicolor often affects the chest and back and has a fine, dusty scale. Melasma usually affects the face and does not have that scale.
Questions
Questions you might be asking.
Will melasma ever go away completely?
For some people yes, especially when pregnancy set it off. For most, it can be made much lighter and kept there, but the tendency stays. Aim for faded and even, then hold it with maintenance.
How long before I see anything?
Give it 12 weeks. Pigment clears slowly and the first weeks look like nothing. If nothing has changed by three months on a daily prescription treatment with proper sun protection, change the plan.
Do I really have to wear sunscreen indoors?
Near a window, yes. Glass blocks most burning ultraviolet but lets through the longer wavelengths and all visible light, and both drive melasma. A tinted sunscreen at a desk by a window is not wasted.
Is it safe to treat melasma while pregnant?
Some treatments are used in pregnancy and others avoided, and that decision belongs to the doctor managing your pregnancy. Sun protection, shade and a gentle routine are reasonable for everyone. Many people wait, since pregnancy melasma often fades in the year after delivery.
Will a laser fix it in one session?
No. Pushing hard with lasers is what makes melasma worse. Devices are used cautiously, at low settings, added to creams and sun protection. Anyone promising one-session clearance is describing a different condition.
Why did mine come back after it cleared?
The pigment cells stay primed and the skin underneath keeps signaling them. A strong summer, a new pregnancy, a hormone change or a few months without sunscreen is enough. Relapse is expected, which is why maintenance is part of the plan.
Sources
Sources and further reading
Related
Keep exploring.
Post-Inflammatory Hyperpigmentation
Alpha Arbutin
Kojic Acid
Tranexamic Acid
Hydroquinone 4%
Licorice Root Extract
Chemical Peel

Fractional CO2 Laser
Cysteamine
Azelaic Acid
Niacinamide