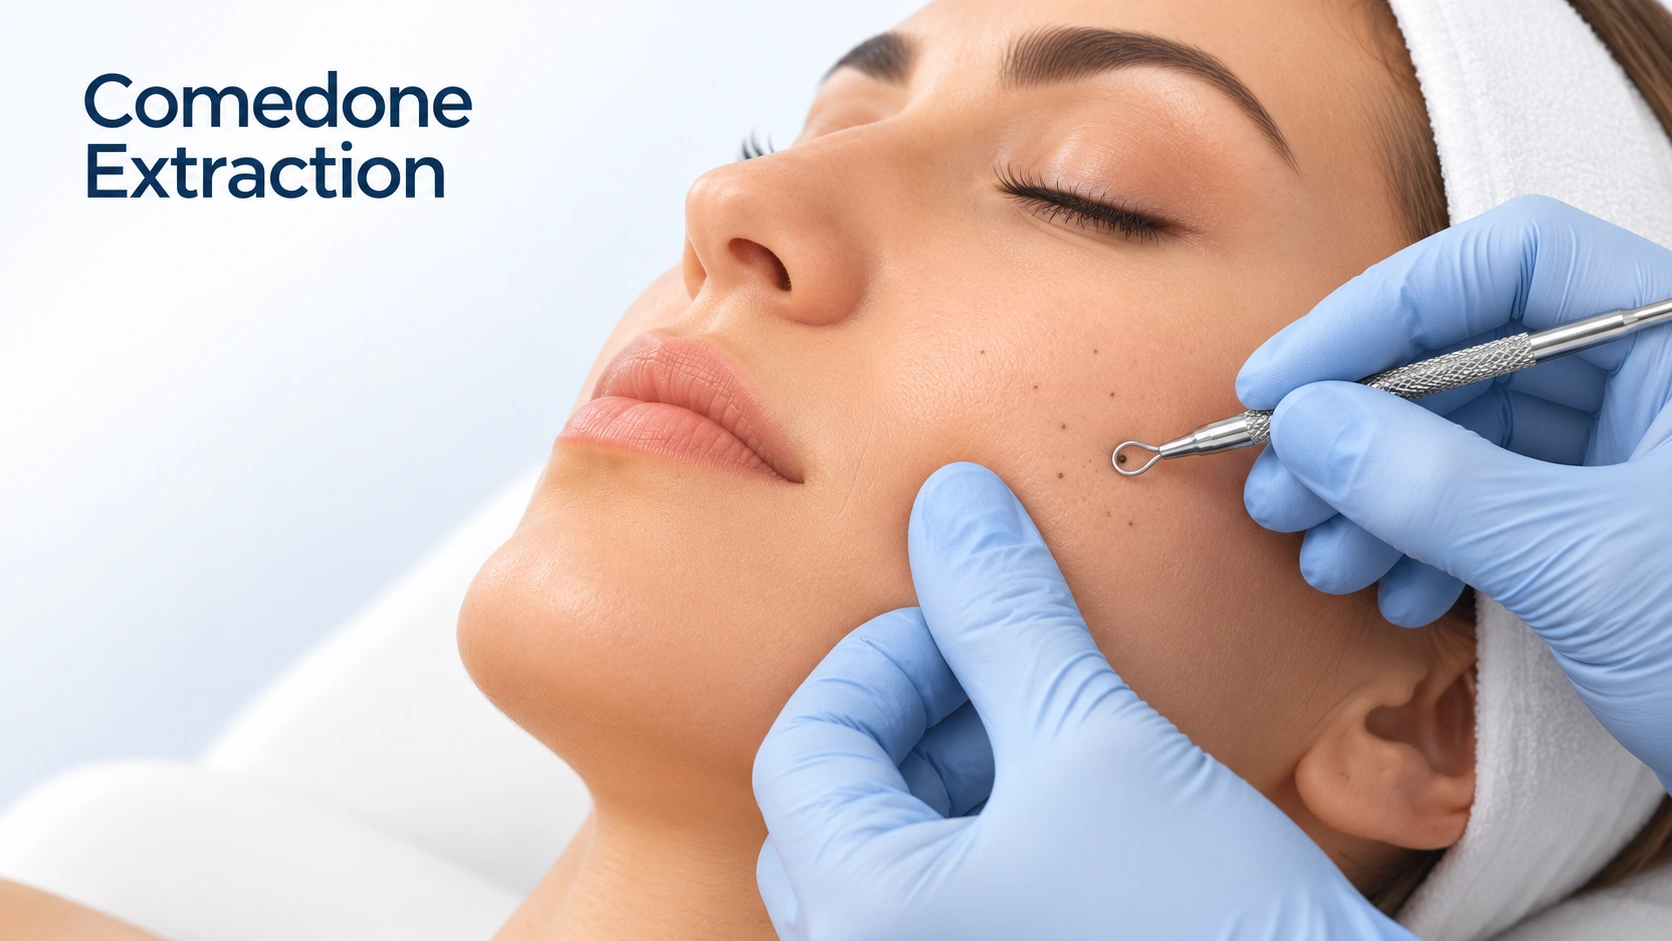
It is injected into a lesion.
An intralesional steroid calms local inflammation or scarring.
Cortisone Injection: A tiny shot of diluted steroid into one inflamed acne cyst. It flattens that spot in a few days. It treats the bump, not the acne.
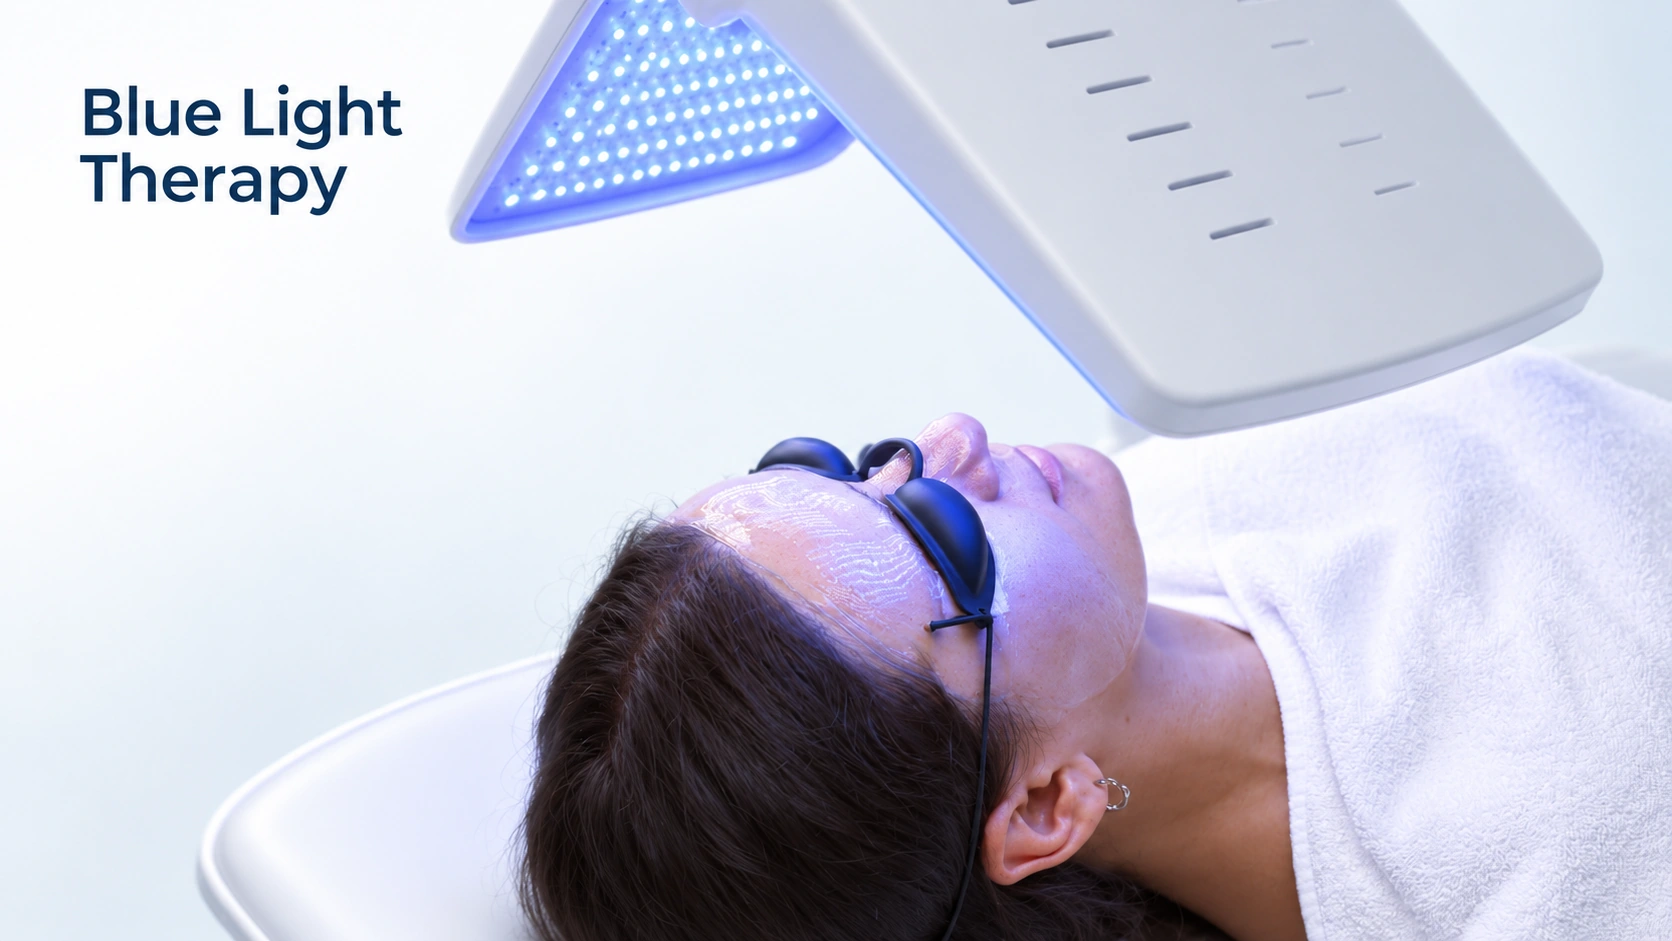
LED Light Therapy: Panels, masks, and handhelds that shine red, near-infrared, or blue light on the skin. No ultraviolet and no downtime. The science is real, the marketing runs far ahead of it, and most of the studies are small and funded by device makers.
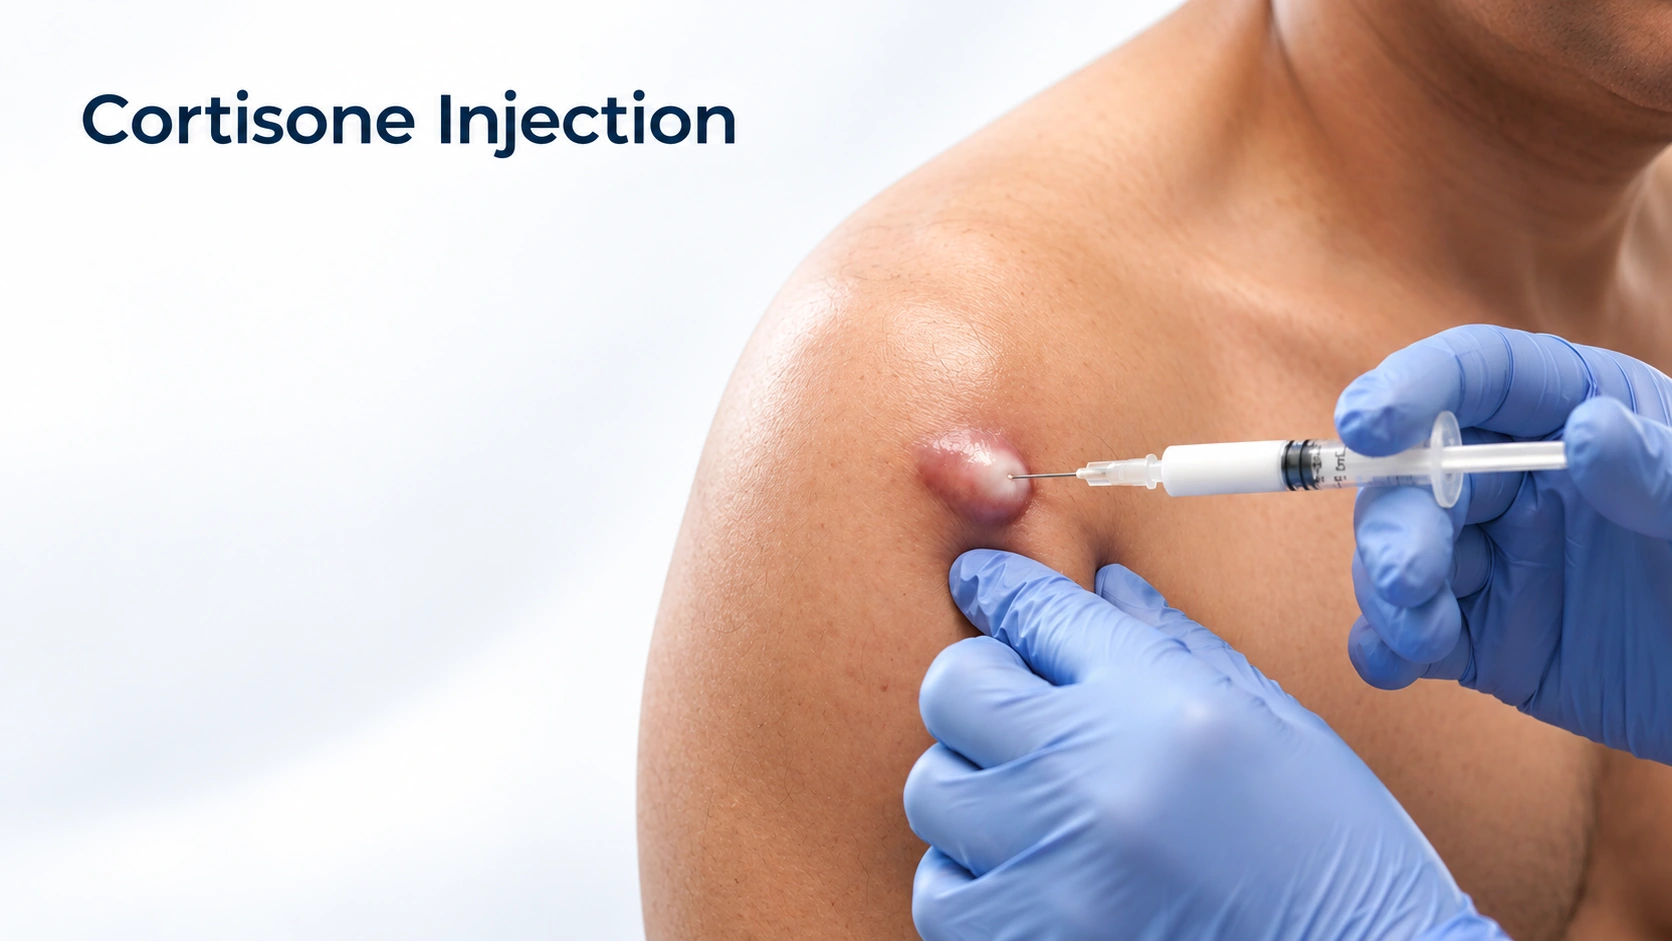

Choose for one painful acne cyst that needs to flatten fast, or for keloids and patchy hair loss.
Choose as a gentle, painless add-on for mild acne or fine lines — the marketing runs well ahead of the evidence.
Can you have both?
LED sessions and a cortisone injection for a single cyst can share an acne plan without problems.
An intralesional steroid calms local inflammation or scarring.
It is not a systemic steroid treatment.
Infected or uncertain lesions should not be injected.
Skin thinning, fat loss and pigment change may persist.
LEDs expose skin to visible or near-infrared light.
Wavelength, device and indication all matter.
It differs from UV treatment and photodynamic therapy.
A home-device clearance does not prove every claim.

Flattens a painful cyst within days.
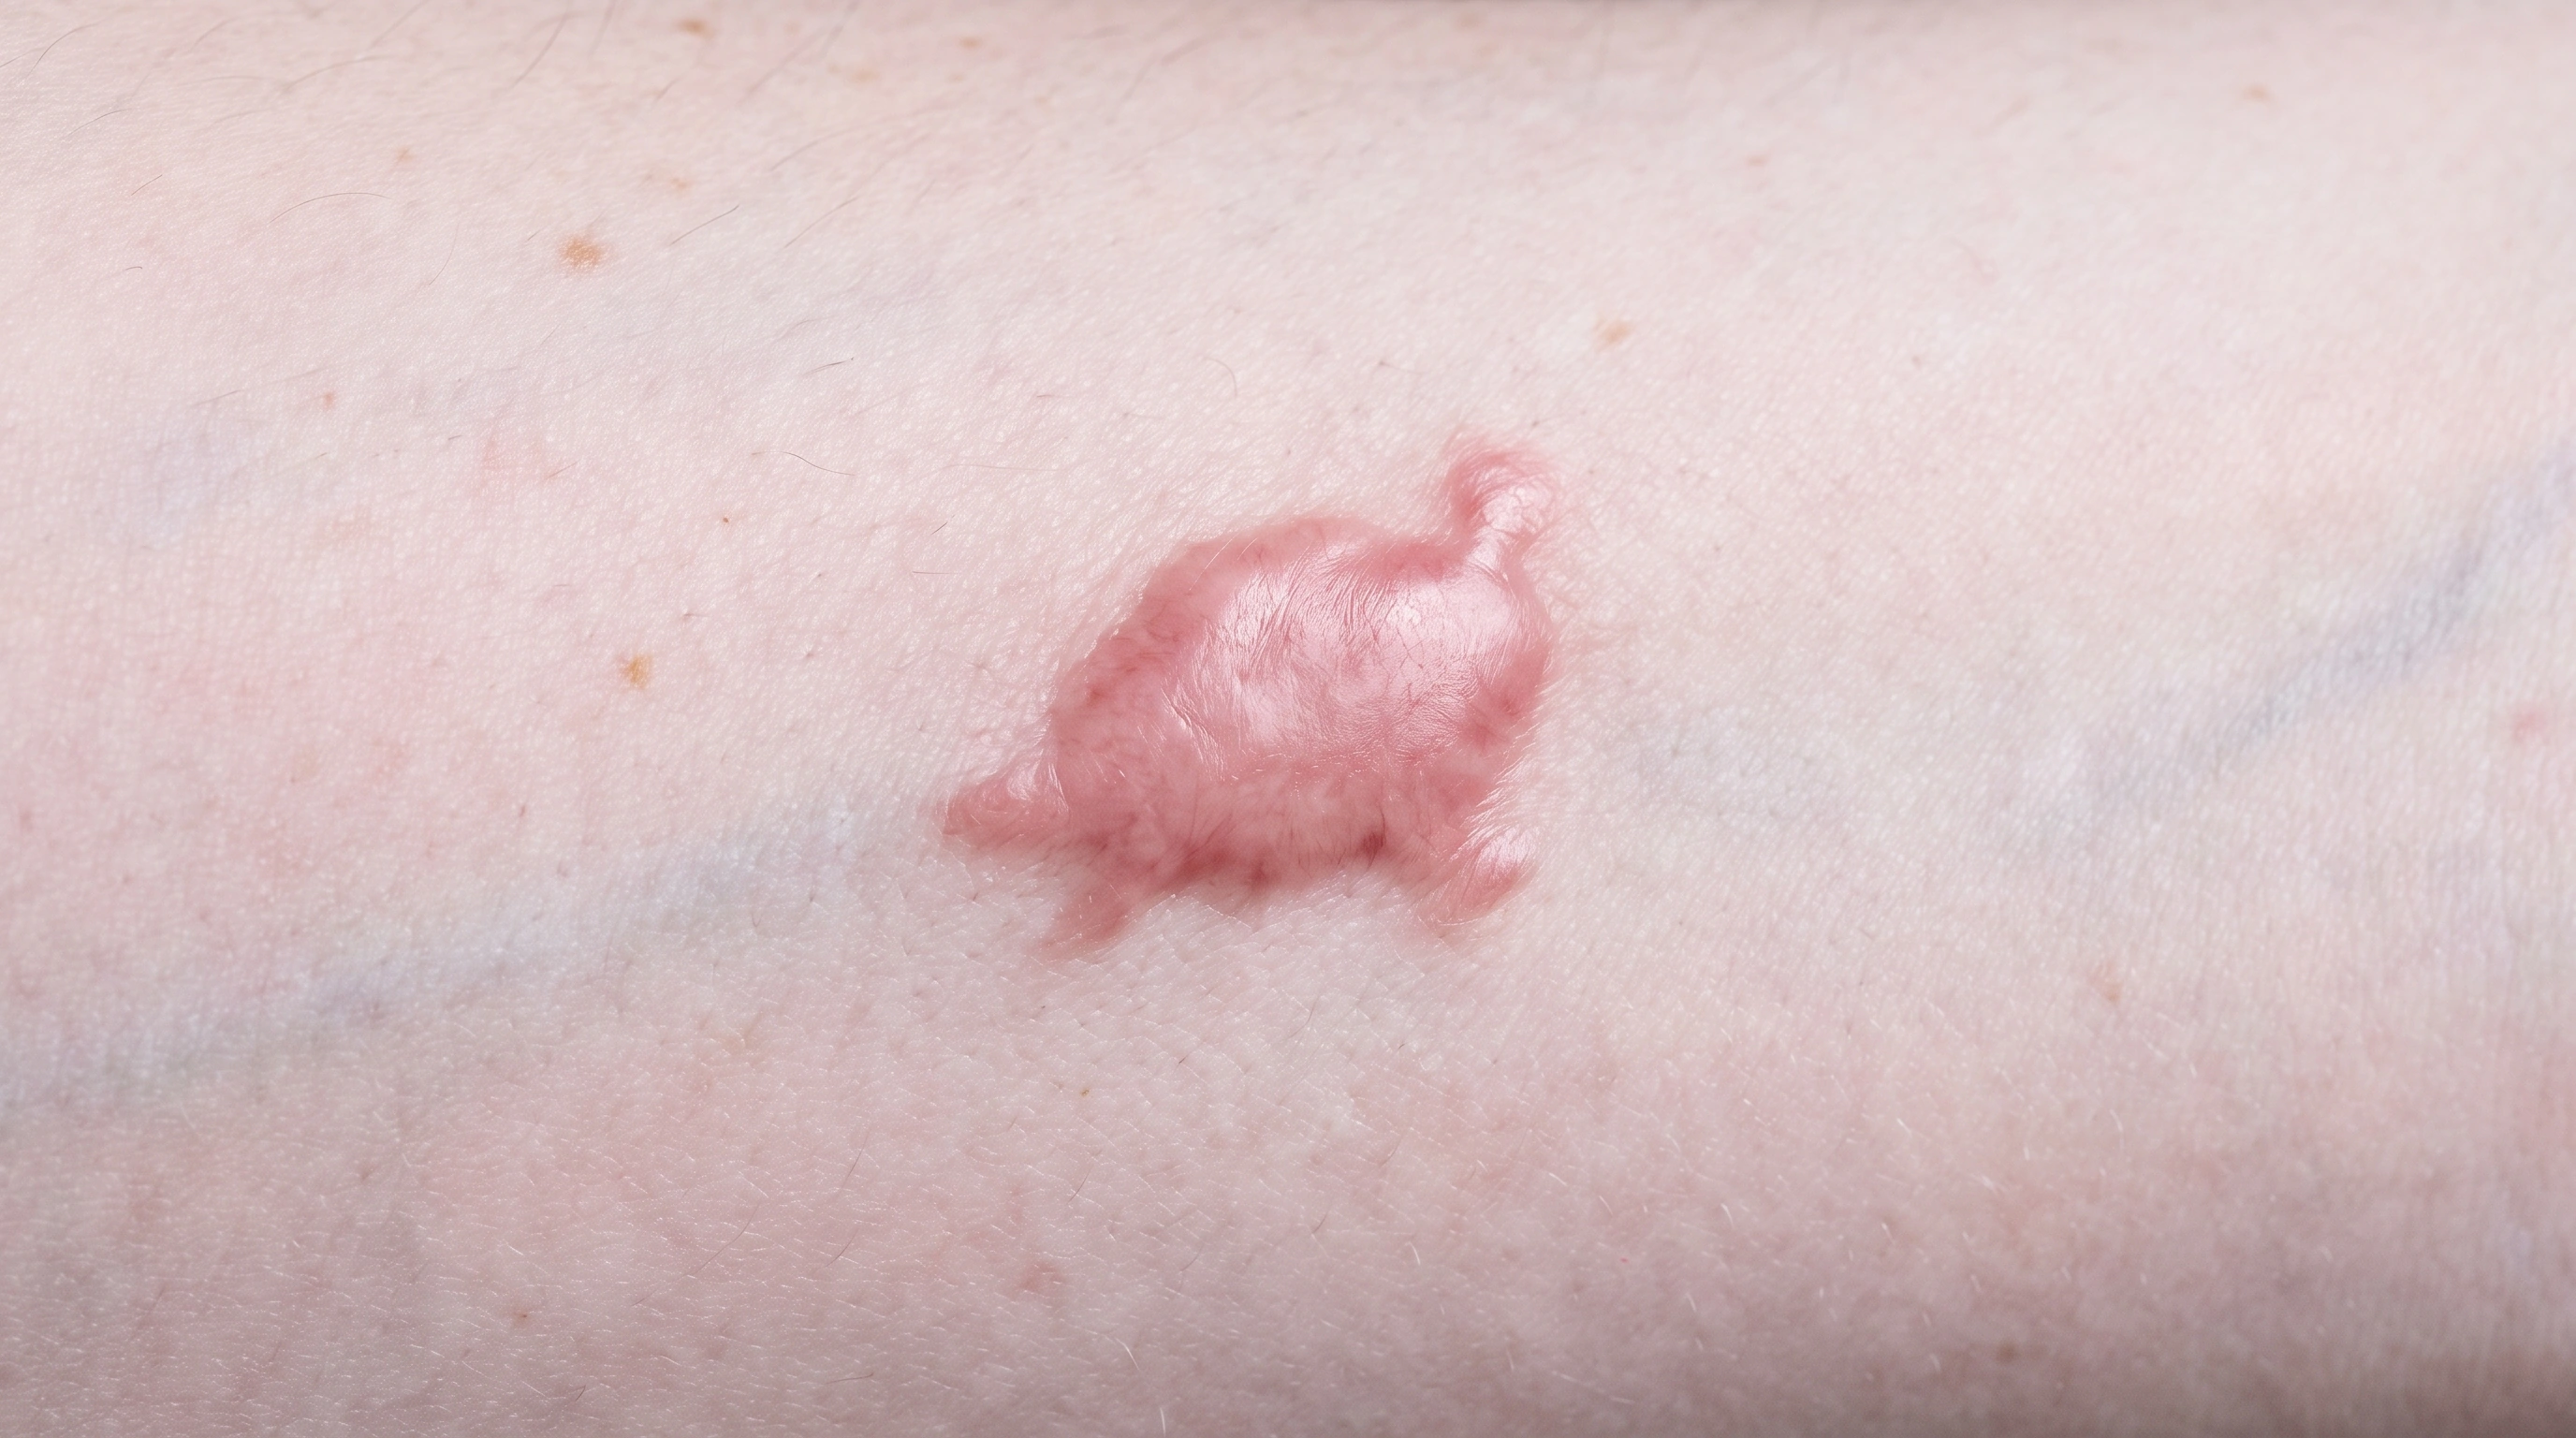
Softens and flattens raised scars.
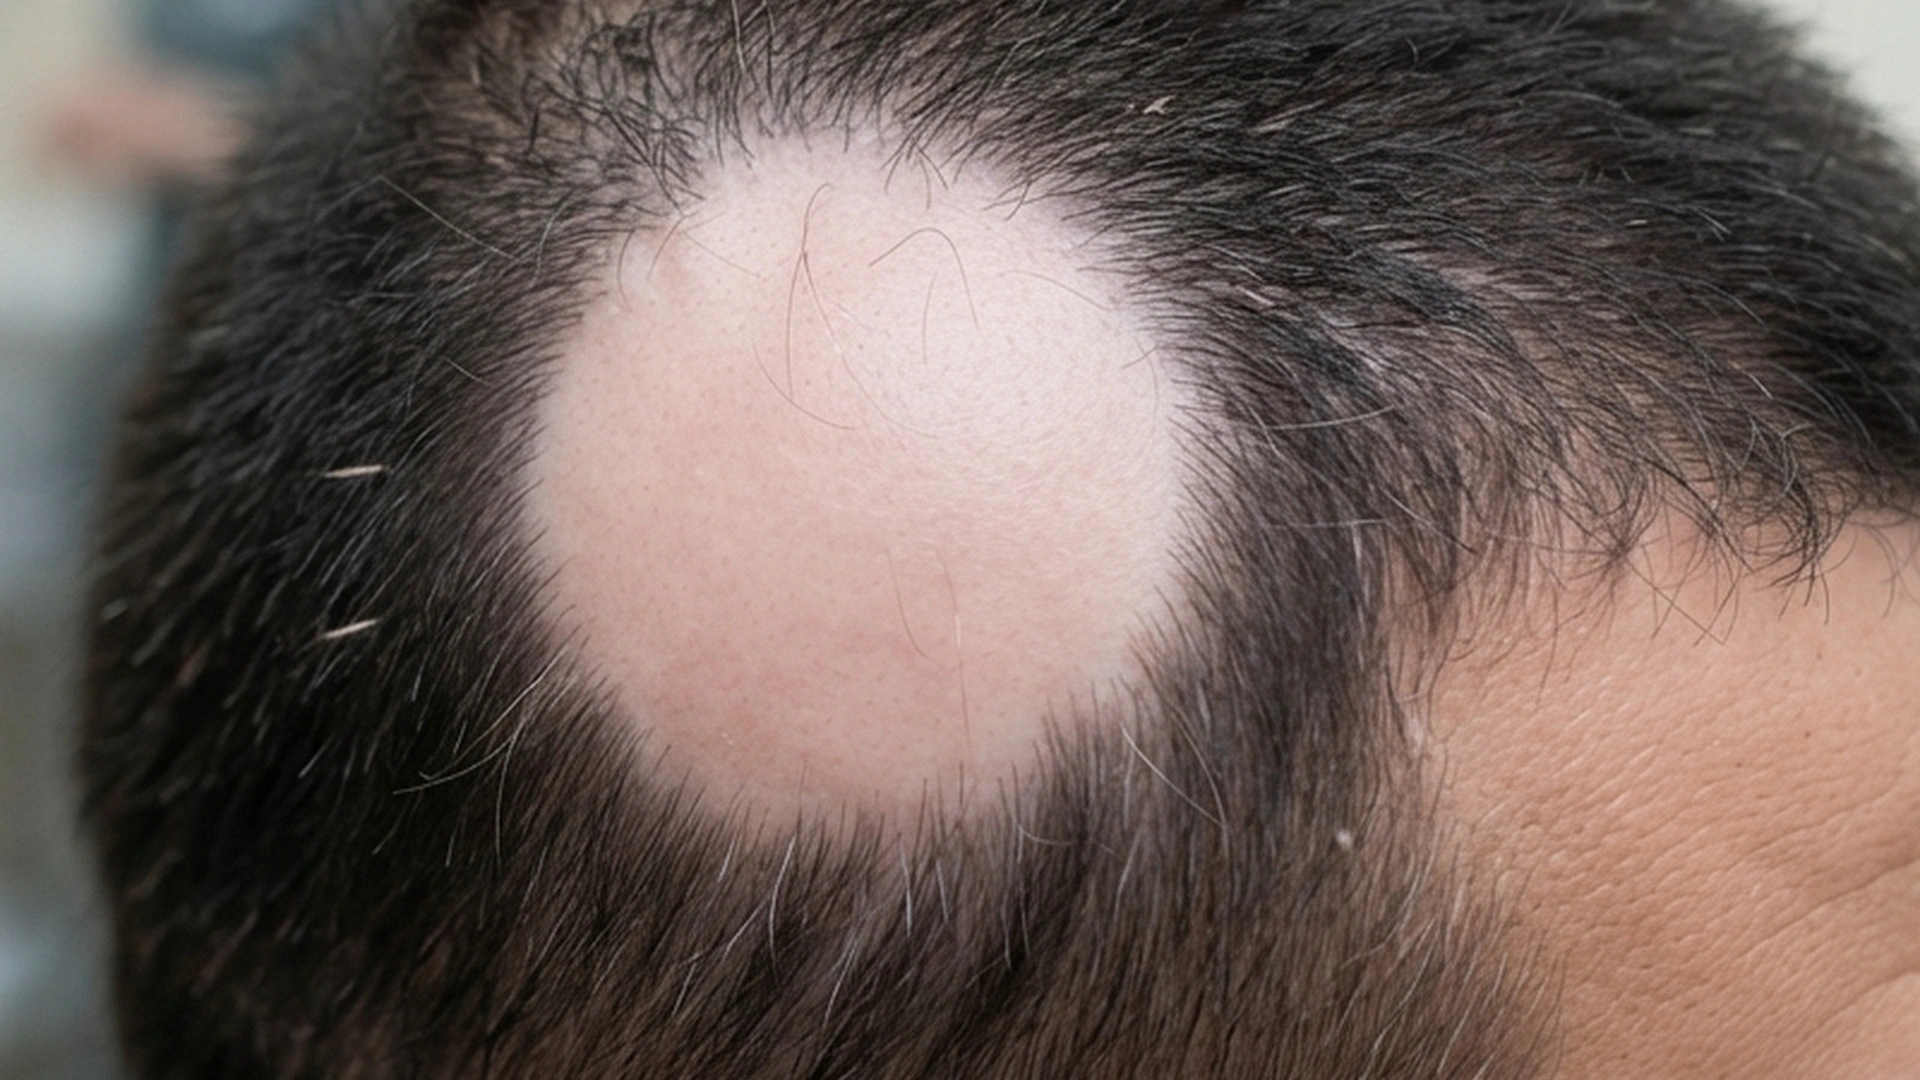
Regrows hair in patches.
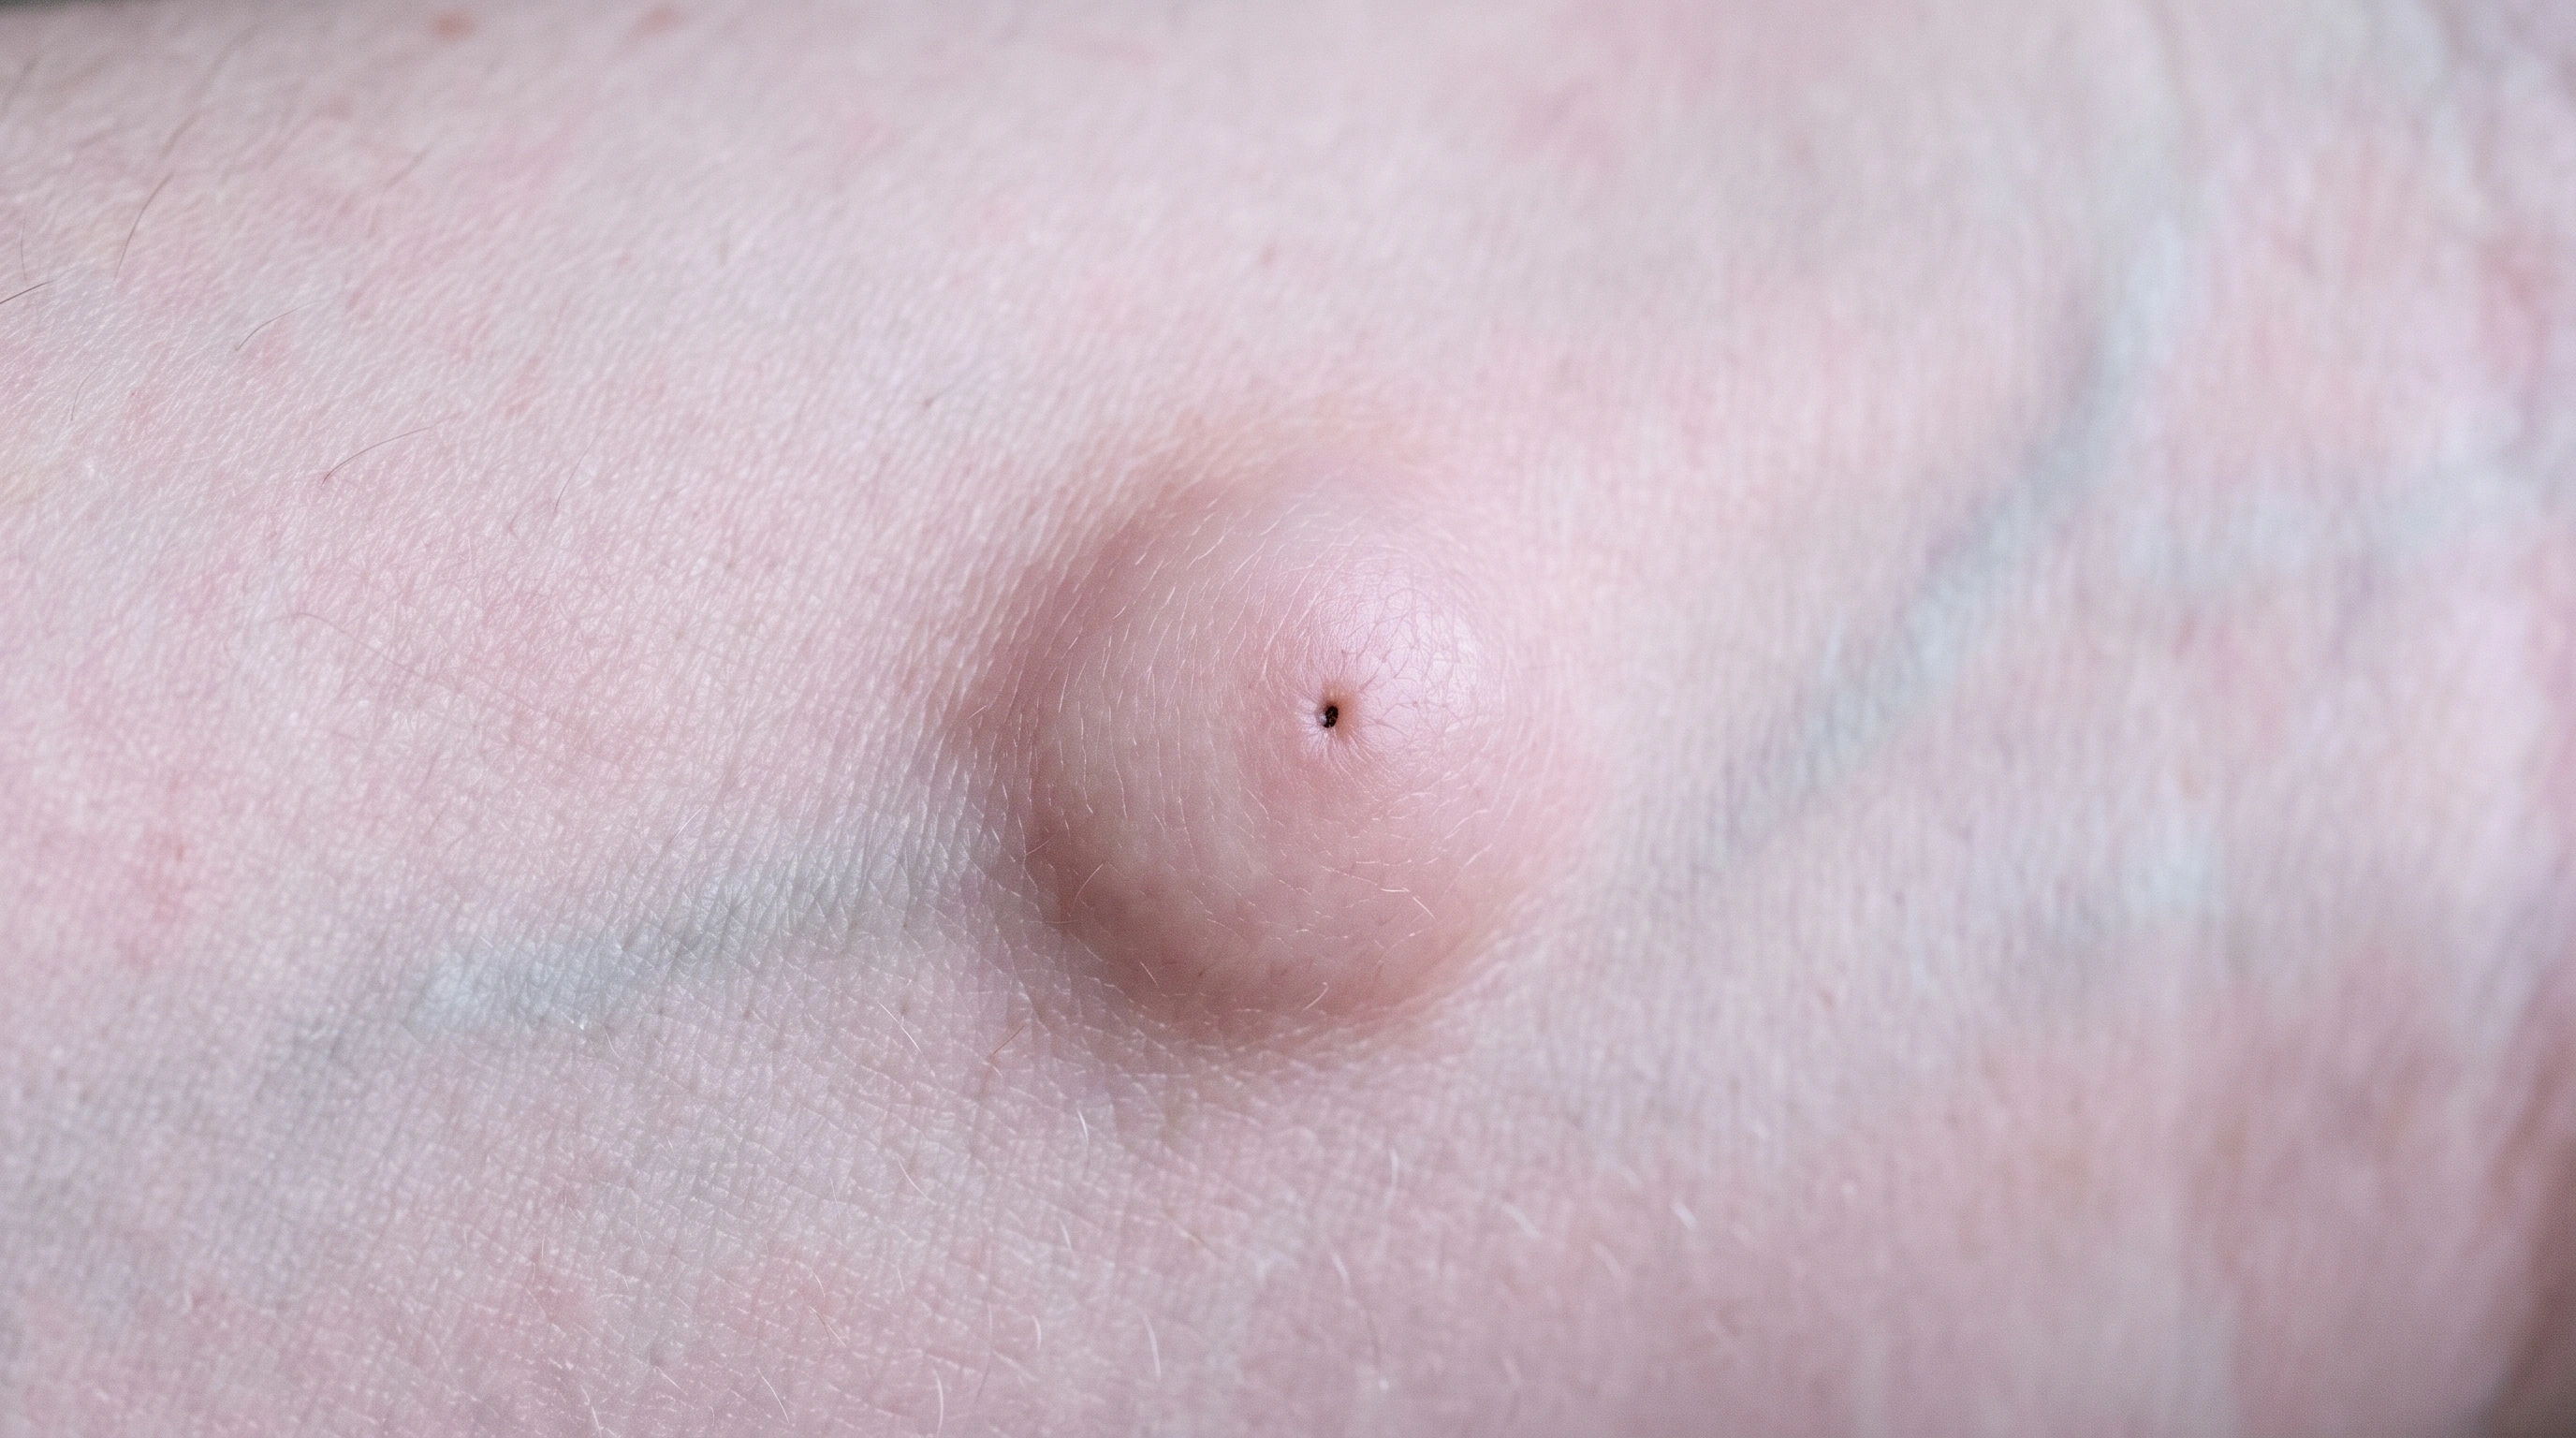
Calms an inflamed cyst.
Blue light modestly reduces spots.
Red light may slightly smooth.
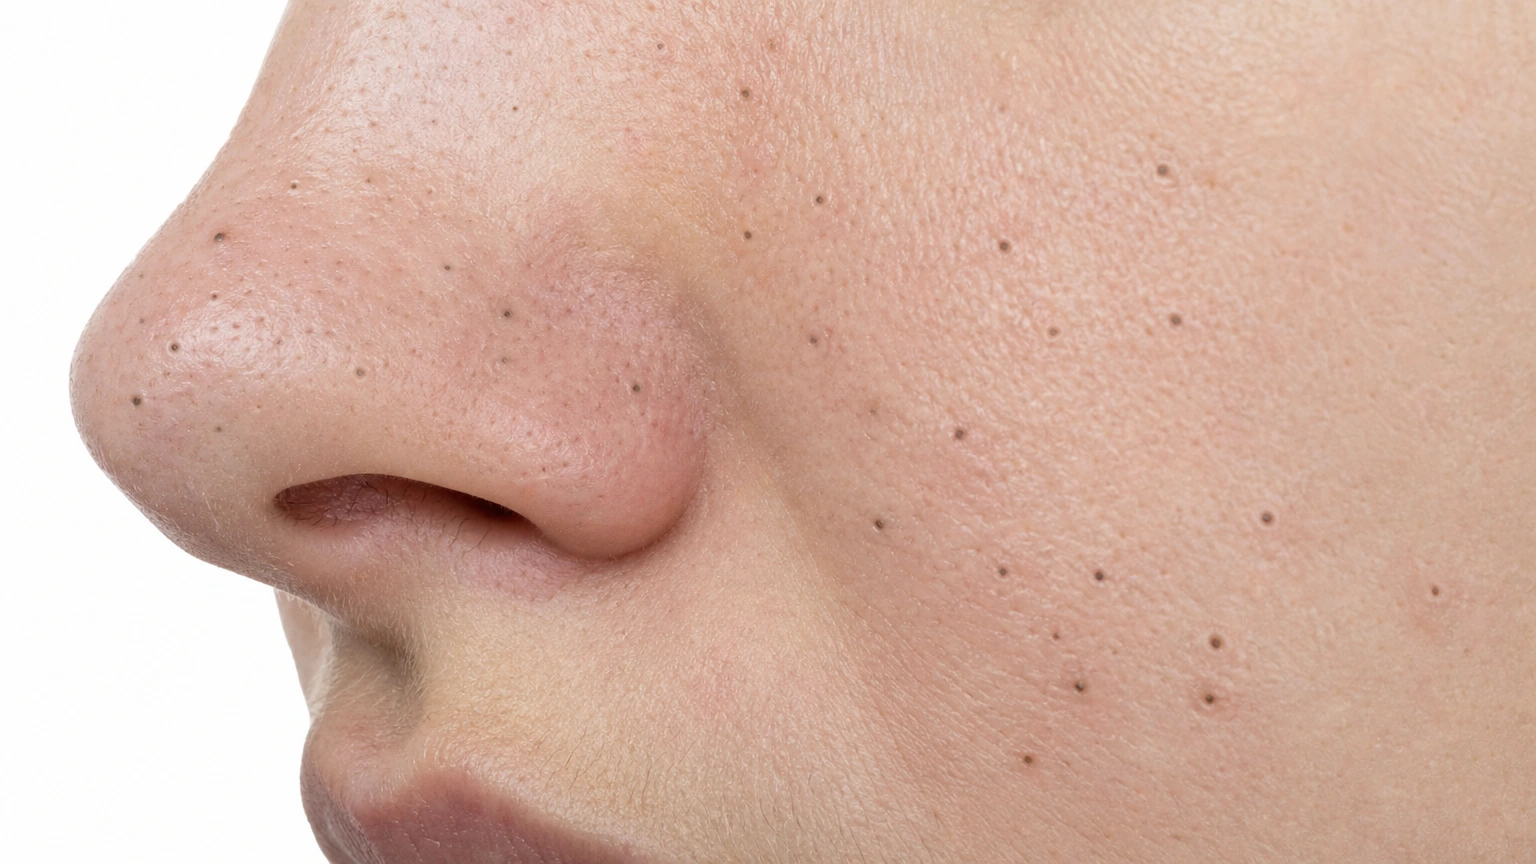
Not for clogged pores.
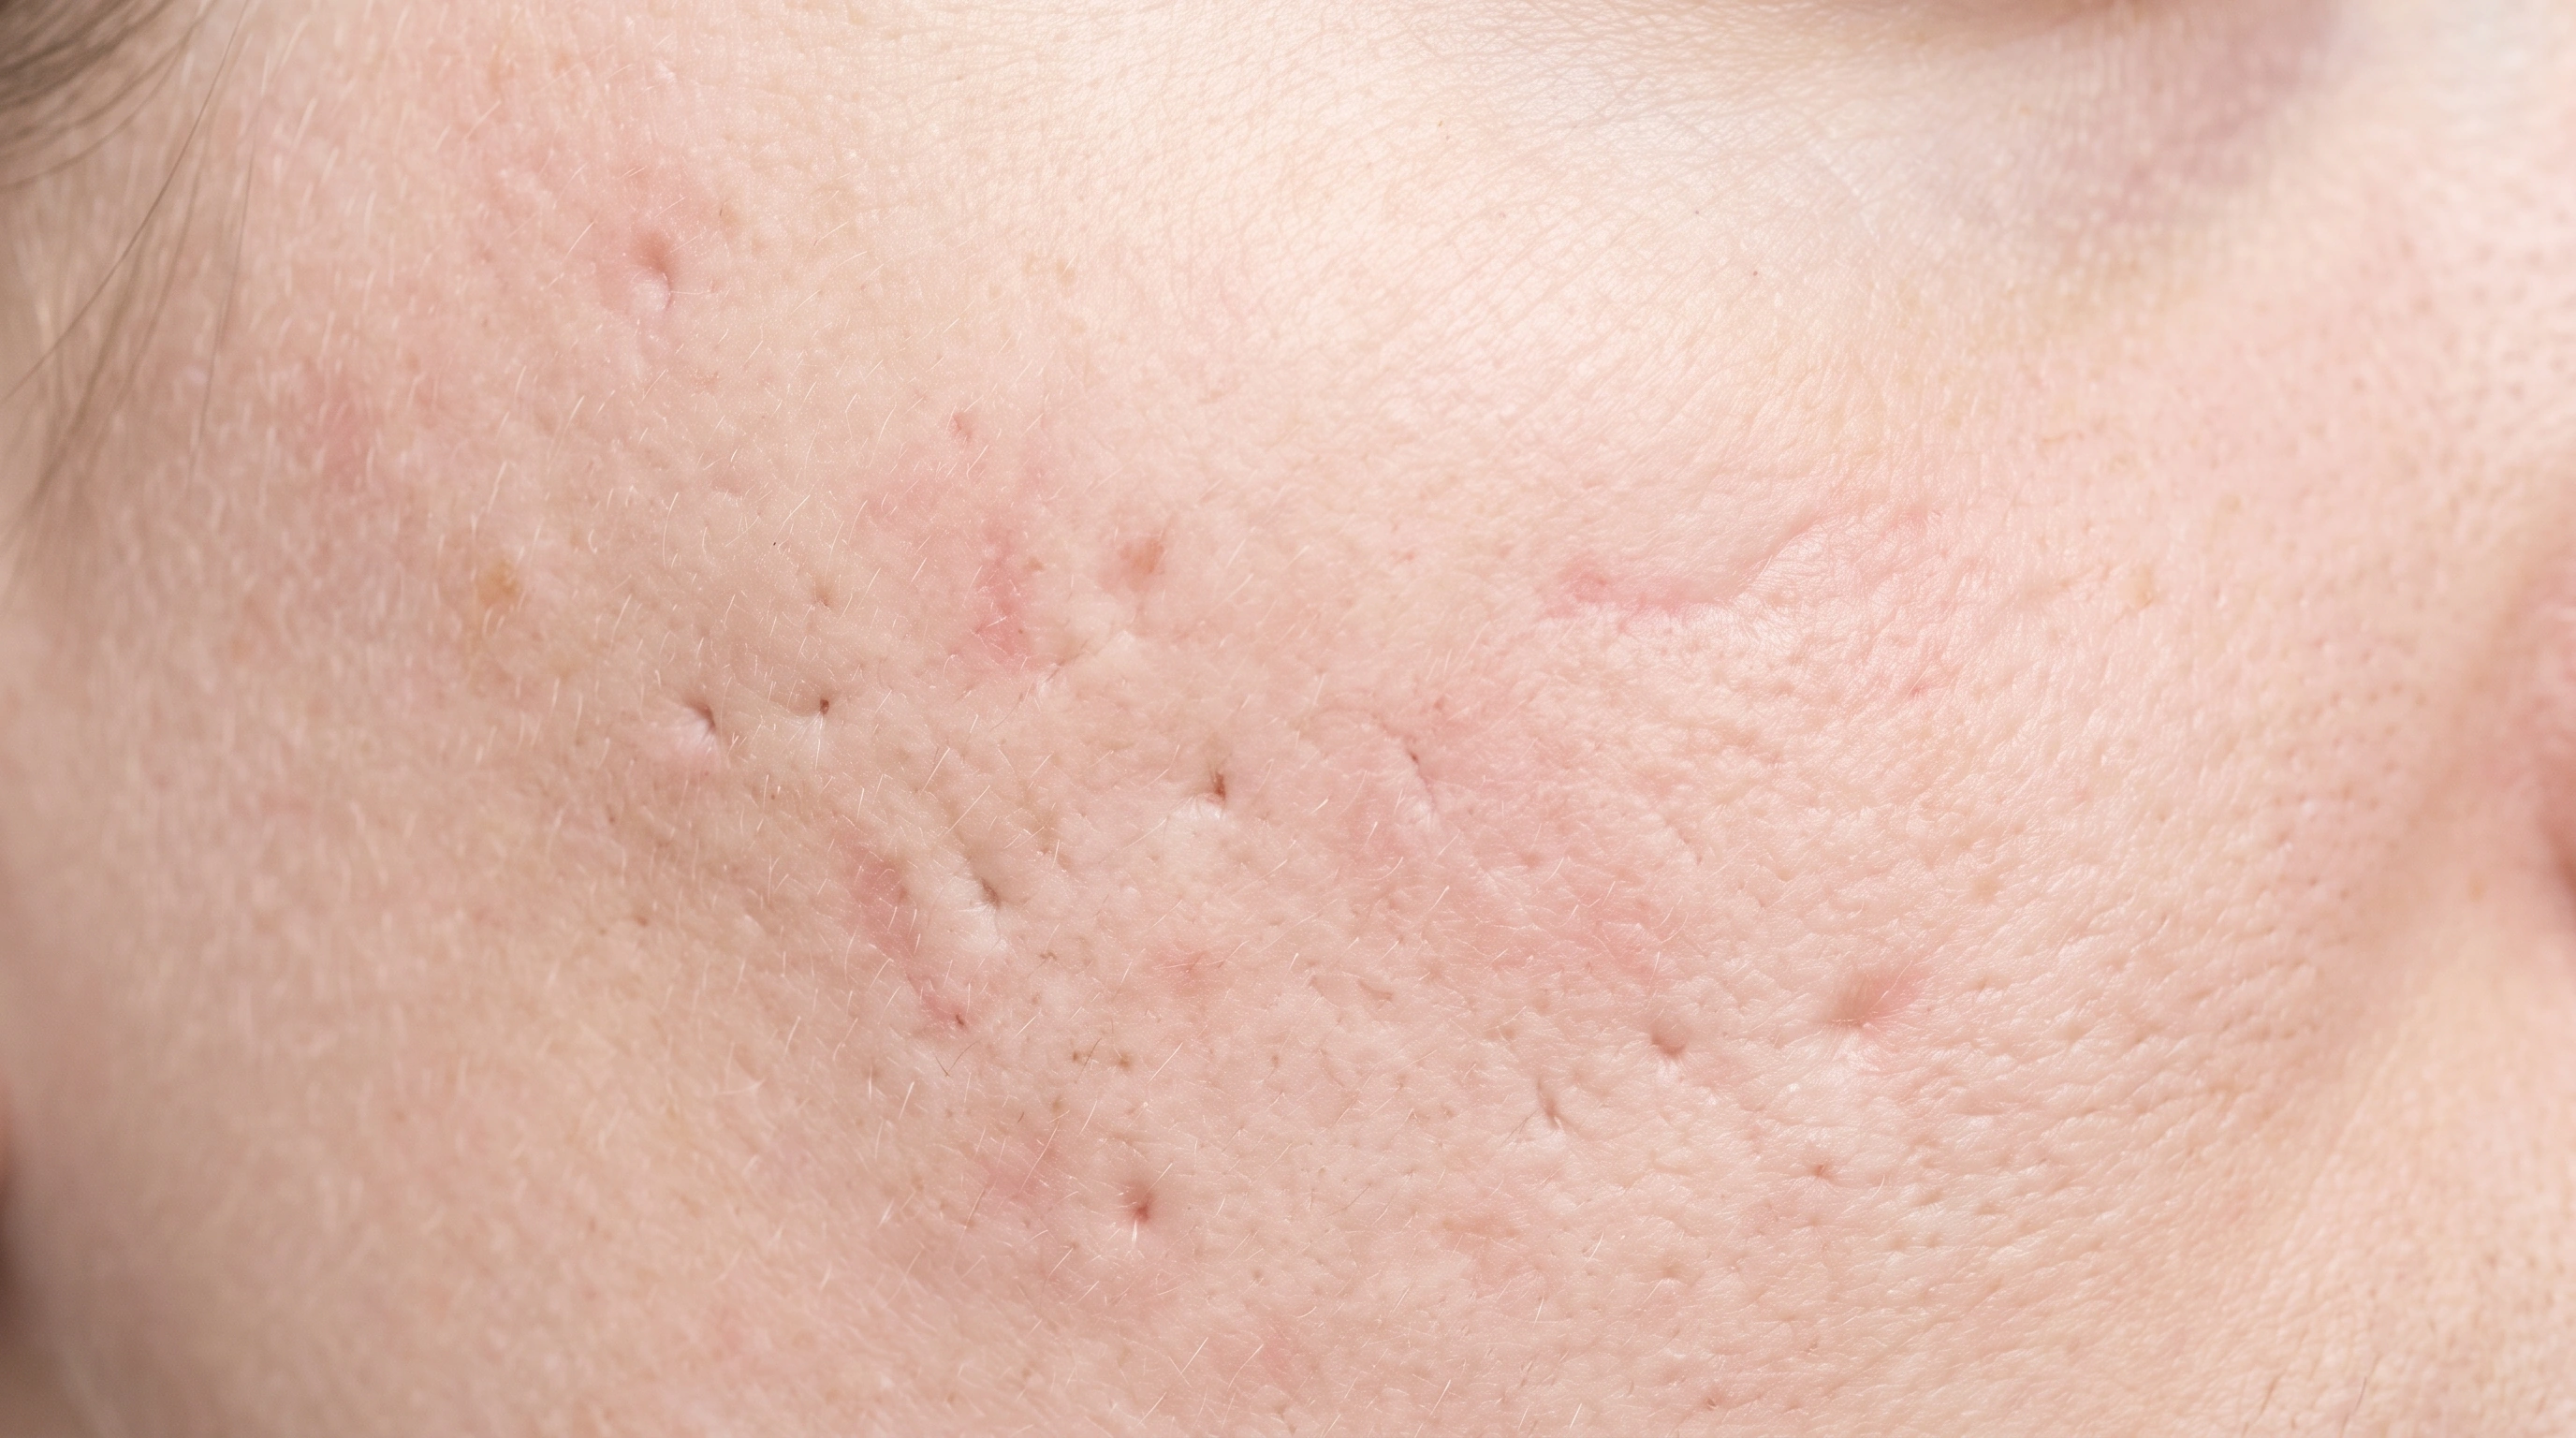
Doesn't change scars.
Can cause dents in skin.
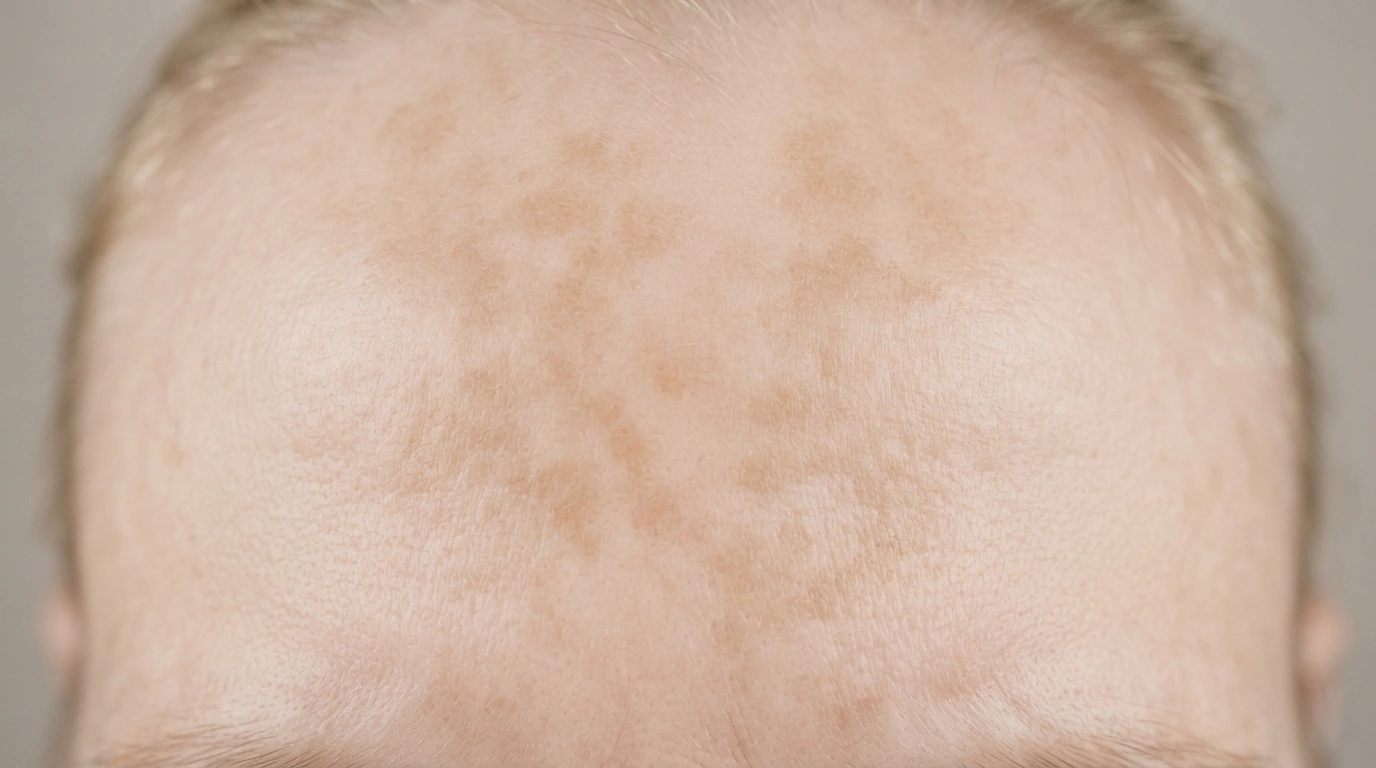
Light can darken patches.
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Face; the selected area depends on the concern and treatment plan.


Medicine is placed in a lesion: A clinician injects an appropriate corticosteroid preparation. Inflammatory signaling decreases: The steroid reduces local immune and inflammatory activity. The lesion may soften or flatten: Response depends on the condition, dose, and placement.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
LEDs deliver selected wavelengths: The device exposes skin to a planned light regimen. Light is absorbed by its targets: Effects depend on wavelength, device, and treatment goal. Response builds over a course: Some regimens may help selected skin concerns; results vary.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Do not pick: Do not pick, squeeze or heat the spot.
Ask your provider: Conditions and medicines: Ask first about lupus, porphyria, another light-sensitive condition, a retinal condition, past eye surgery or seizures.
Clean skin: Wash your face and skip makeup on the area.
Before each session: Clean skin: Sunscreen, makeup and thick moisturizer block visible light, mineral sunscreens especially, so a session over sunscreen does little.
Before session one: Baseline photo: Photograph your face in daylight, same spot, no makeup.
Shields and dose: Have the eye shields to hand before you start.
The provider checks that the spot is an inflamed acne cyst and not a boil.
In a clinic, skin is cleansed.
The skin is wiped with alcohol.
A very fine needle goes just into the bump and a small amount of fluid goes in, under 10 seconds per spot. The sting is sharp for a few seconds, worse if the cyst is already tender, but most people rate it lower than they expect. Numbing does not help much — the needle stick is the whole procedure.
The panel or mask sits close to the skin and runs for 10 to 20 minutes.
Red light is a strong glow even through closed eyes; near-infrared is invisible but feels warm. Shields stay on the whole session. It does not hurt. Expect mild warmth, and sometimes a headache after, usually from light without shields.
A tiny red dot, sometimes a small raised bleb that flattens within an hour.
Skin looks unchanged, maybe flushed for a few minutes.
Days 1 to 2: The bump softens and the ache fades.
Days 1 to 2: Dryness or a headache are uncommon and mild.
First few days: A pinprick mark, sometimes a small bruise, fading over a few days.
Days 3 to 7: Most cysts are flat.
Weeks 1 to 4: Little visible change.
Weeks 8 to 12: If a photograph in the same light shows nothing by now, more weeks will not change the answer.
24–48 hours for a cyst
8–12 weeks of regular use
Treats only that spot
Only while used
Roughly $50 to $250 per office visit in the US, usually billed as an office visit plus a procedure charge rather than per spot.
Home devices are the main market, from roughly $50 for a handheld wand to several hundred dollars for a full-face mask, and higher.
Insurance often covers it, since acne cysts count as medical rather than cosmetic.
Insurance does not cover it.
Softening begins within 24 to 48 hours and most spots are flat by day three to five. That figure traces back to one small 1983 trial — it matches what dermatologists see but has never been tested at scale. The mark left behind takes weeks longer, and the injection does not speed that up.
It can. A shallow depression happens when the dose is too strong, so a lower concentration is the main protection. It is uncommon — most dermatologists see it in well under one patient in a hundred — and it often fills in over several months. But it is not reliably temporary. About half the clinicians who do see it report it lasting more than six months, and occasionally it is permanent. That is why you ask what concentration is being used.
Yes, the most common reason people ask. Aim for three to five days ahead so the swelling has time to drop. A same-day injection rarely looks better by that evening.
No. It treats only the spot it is injected into. Preventing the next cyst needs a daily treatment plan, and the guidelines call this an add-on.
Yes. The risk is a lighter patch at the site, more noticeable and slower to fade on deeper skin tones. A lower concentration reduces it, so ask.
Not in the United States, strictly speaking. The FDA labeling lists intralesional use for keloids, alopecia areata, discoid lupus and others. Acne is not on it. Off-label use for an acne cyst is routine, legal and recommended by the American Academy of Dermatology, but almost nobody says it out loud. In the UK, NICE withdrew its recommendation in 2026 after UK-licensed triamcinolone injections stopped being available — a supply and licensing decision, not a safety one.
Partly, and modestly. The best-supported uses are blue light for mild inflammatory acne and red or near-infrared light for wound healing. For fine lines and redness there are small positive trials, usually 8 to 12 weeks long. The literature is limited by small numbers, short follow-up, devices that differ from each other, few comparisons against proven treatments, and a lot of manufacturer involvement.
They generally put out less light per minute, which is why home instructions ask for several sessions a week. Over three months a consistently used home device may deliver more total exposure than occasional clinic add-ons. What is not true is that a trial of a clinic panel tells you what a particular mask will do.
No — most are cleared as substantially equivalent to a device already on the market. That is a judgment about similarity and basic safety, not evidence of a useful result.
Yes, and it is the one safety point worth being strict about. These devices are bright, they sit close to the face, and blue wavelengths carry a recognized photochemical hazard to the retina with prolonged exposure. Keep the shields on for the whole session, and ask your doctor first if you have a retinal condition or have had eye surgery.
Give it 8 to 12 weeks of consistent use, then compare a photograph taken on day one in the same light and without makeup. Judging by memory in the mirror is how people persuade themselves either way.
No — it sits on top of those, and the gain from adding it to a good routine is small. Using it instead of treatment for a condition that scars is the one way a low-risk device causes harm.