Scalp Psoriasis vs Contact Dermatitis

Scalp psoriasis is psoriasis on the head. It causes thick, sharply edged patches with silvery scale that often itch and flake. It is the most common place for psoriasis to start, and it treats well - but the treatment has to reach the skin through the hair, which is where most people go wrong. Contact dermatitis is a rash caused by something that touched the skin. It comes in two forms - irritation from a substance that would bother anyone given enough exposure, and an allergic reaction to something only some people react to. Both clear once the cause is found and removed.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
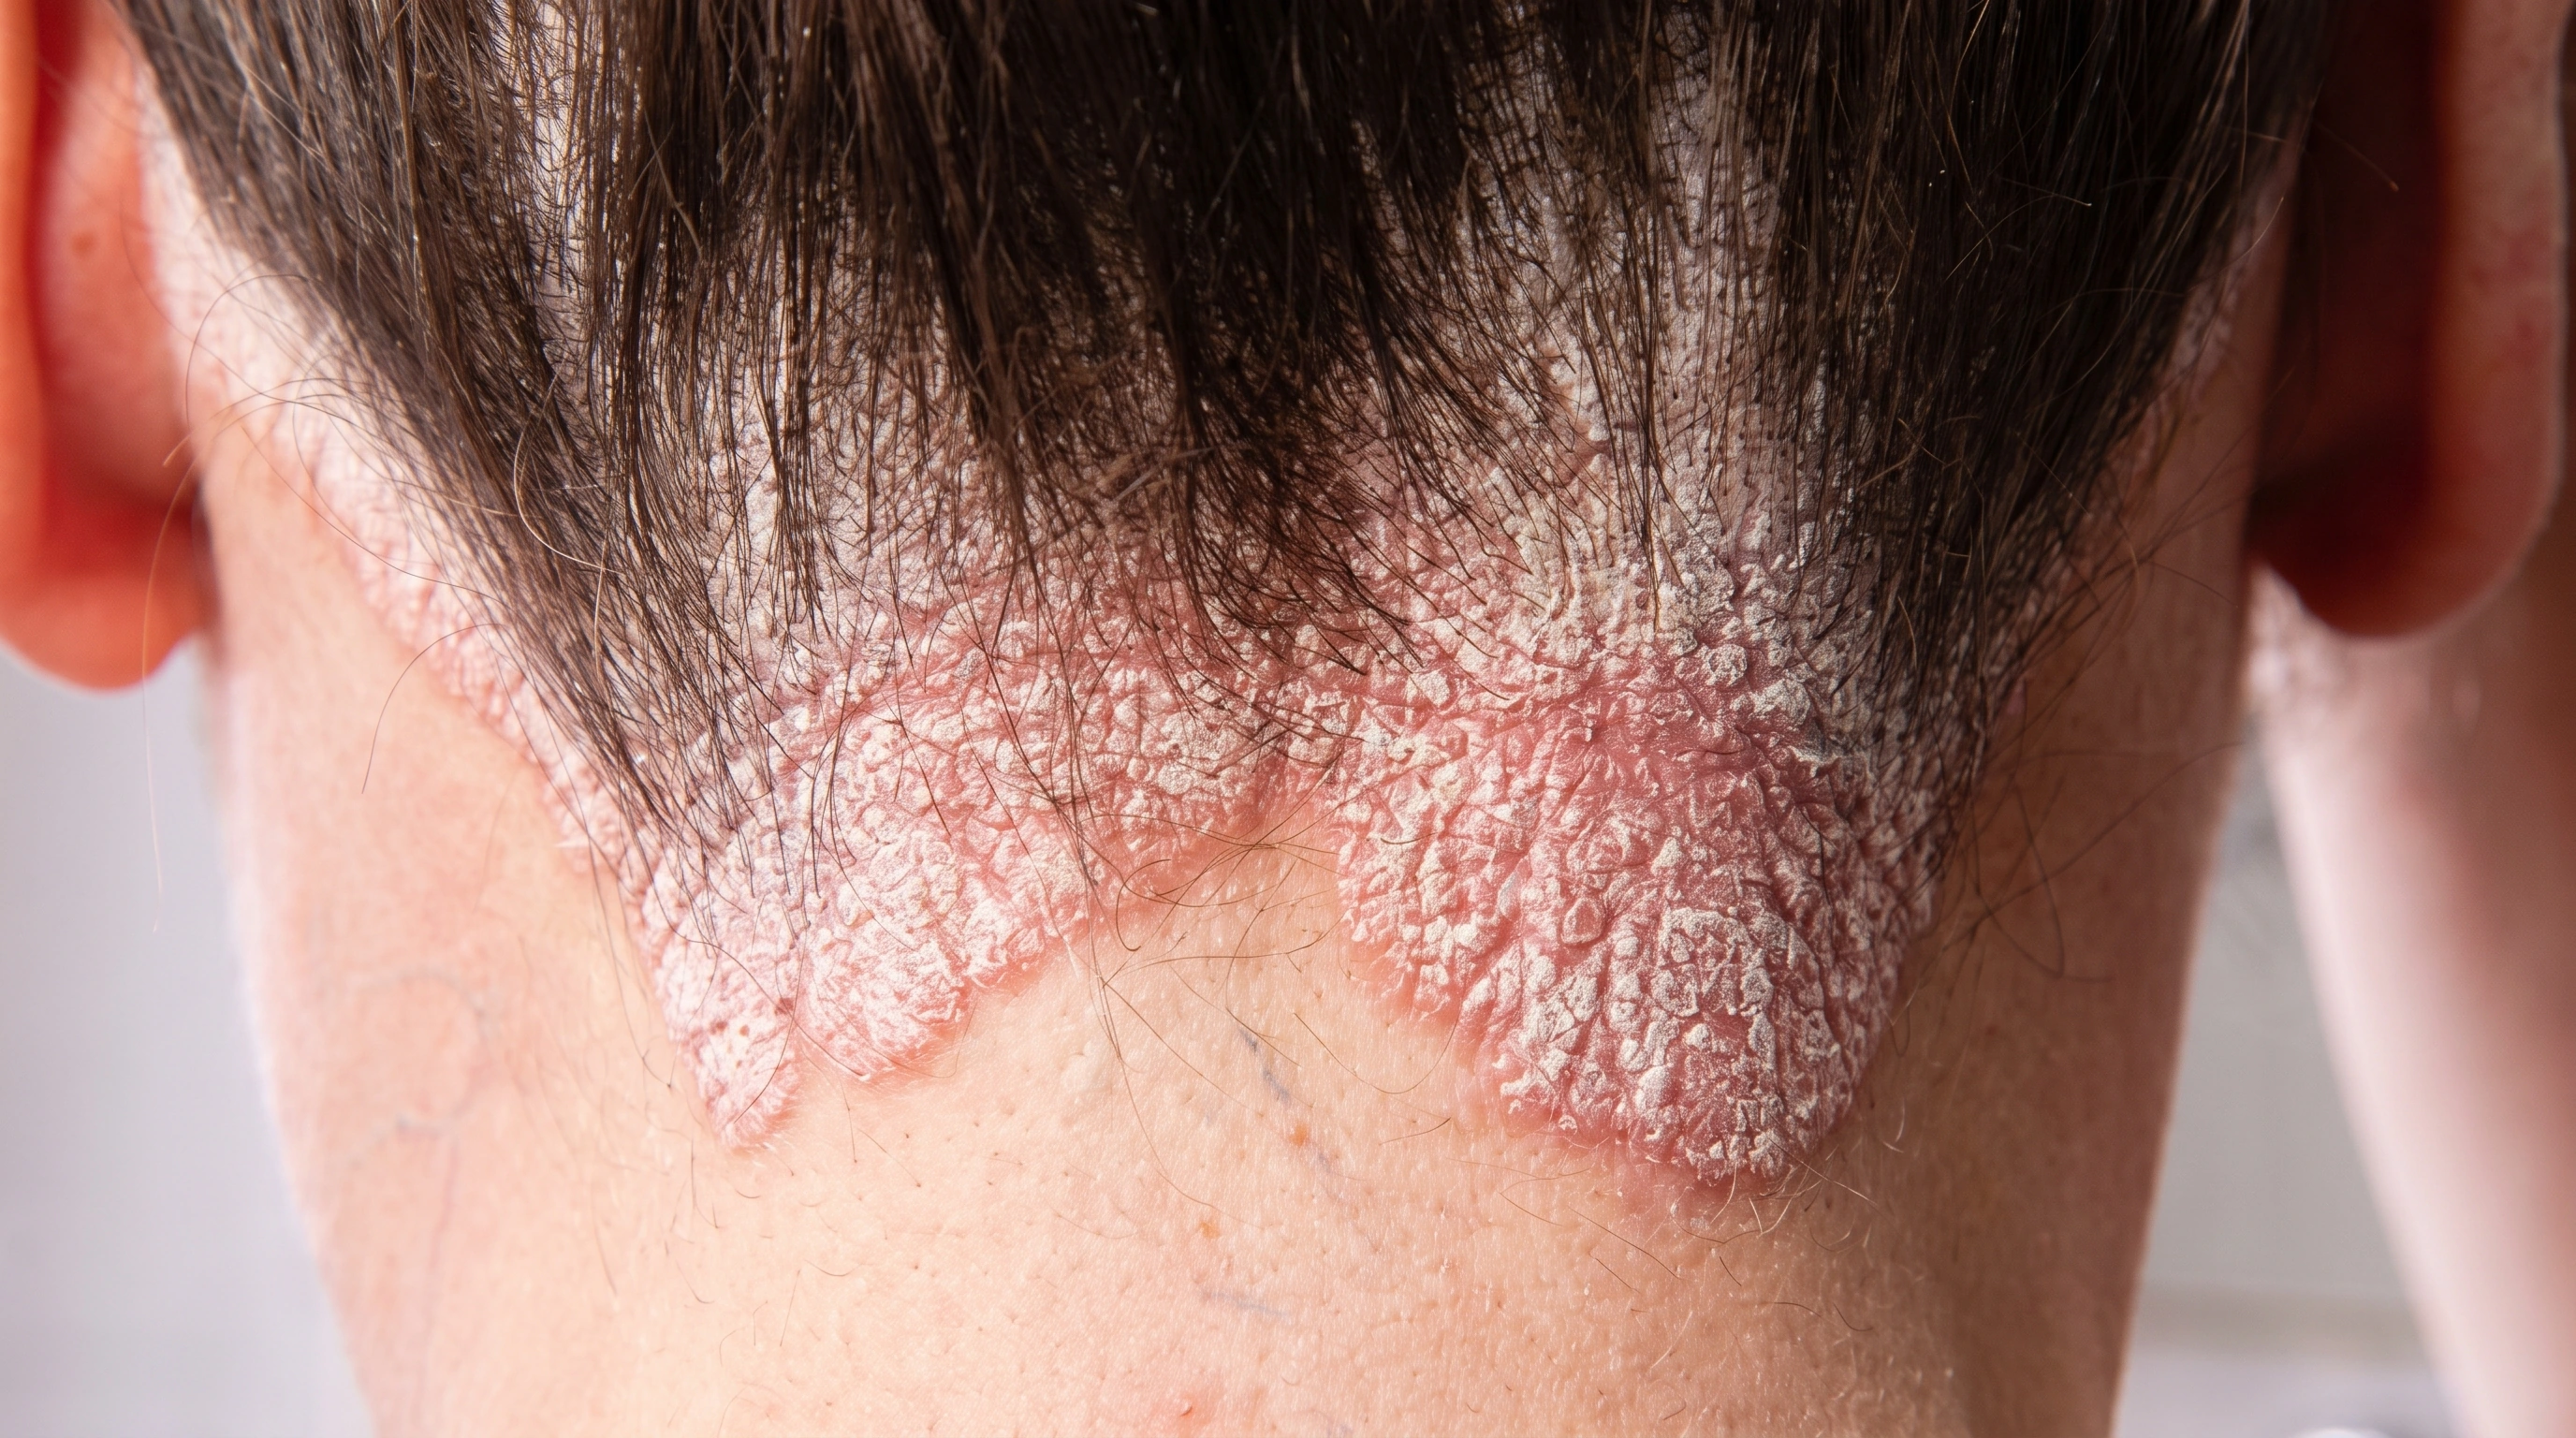
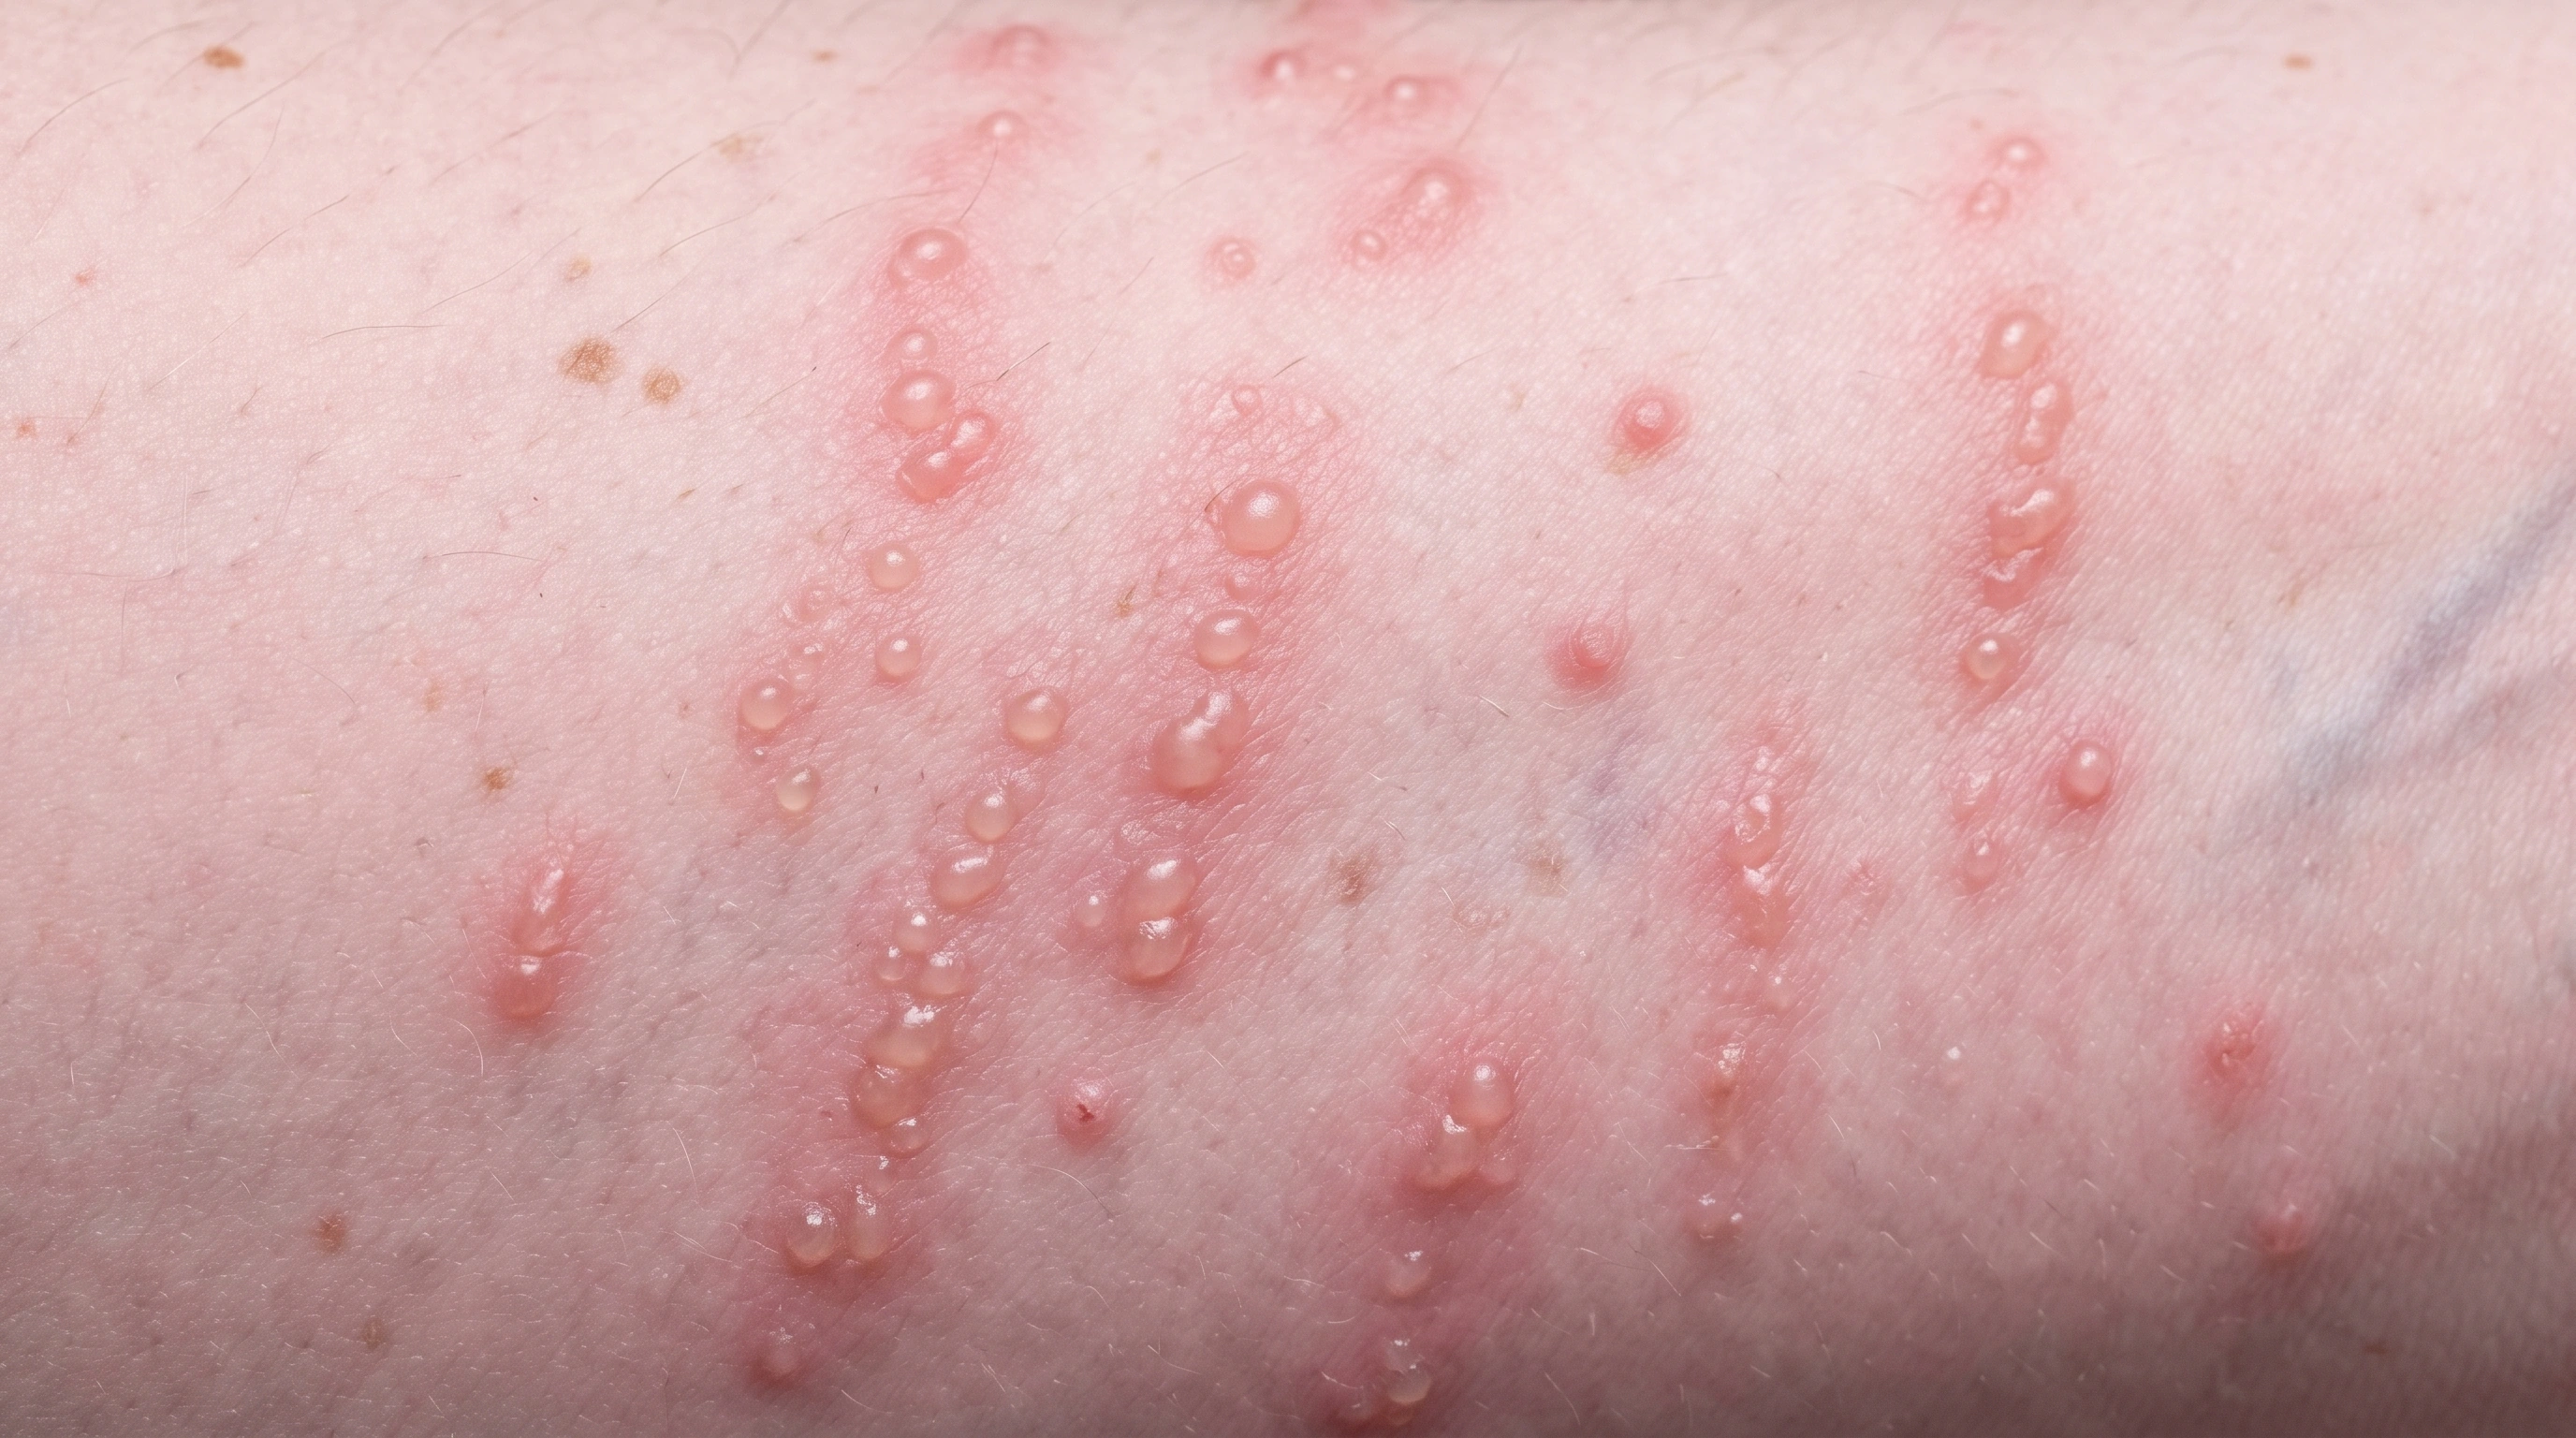
Parted hair on fair scalp skin showing a raised salmon-pink plaque topped with dry silvery-white scale, with a sharply drawn border against normal skin.The back of one hand and the wrist on pale skin. A bright pink, slightly swollen patch with tiny blisters covers the back of the hand and stops at a straight line across the wrist.

Key differences

The same eight facts on every condition comparison.

Usual age
15 to 35, or 50 to 60
Any age
Where
Scalp, hairline, behind ears
Where something touched
Main sign
Thick plaques with silvery scale
Red, itchy or burning rash
Itch or pain
Itchy
Itchy or burning
Contagious
No
No
Long term
Long-term, flares
Clears once the cause stops
Scars
No
No
Who gets it
Half or more of people with psoriasis
Anyone; wet-work jobs

What is it?

Scalp Psoriasis
Contact Dermatitis
What is it?

It is psoriasis of the scalp.
Plaques can extend beyond the hairline.

Severity varies.
Plaques may be thick and scaly or limited but very itchy.

Lookalikes are common.
Dandruff, seborrheic dermatitis and fungal infection can resemble it.

Small area, real burden.
Limited involvement can still cause significant symptoms.

It is eczema from contact.
A substance touching the skin provokes the rash.

There are two types.
Irritant dermatitis damages the barrier directly; allergic dermatitis is a delayed immune reaction.

Patch testing finds allergies.
It differs from skin-prick testing.

The exposure is part of treatment.
Identifying what touched the skin guides care.

What it looks like

Scalp Psoriasis

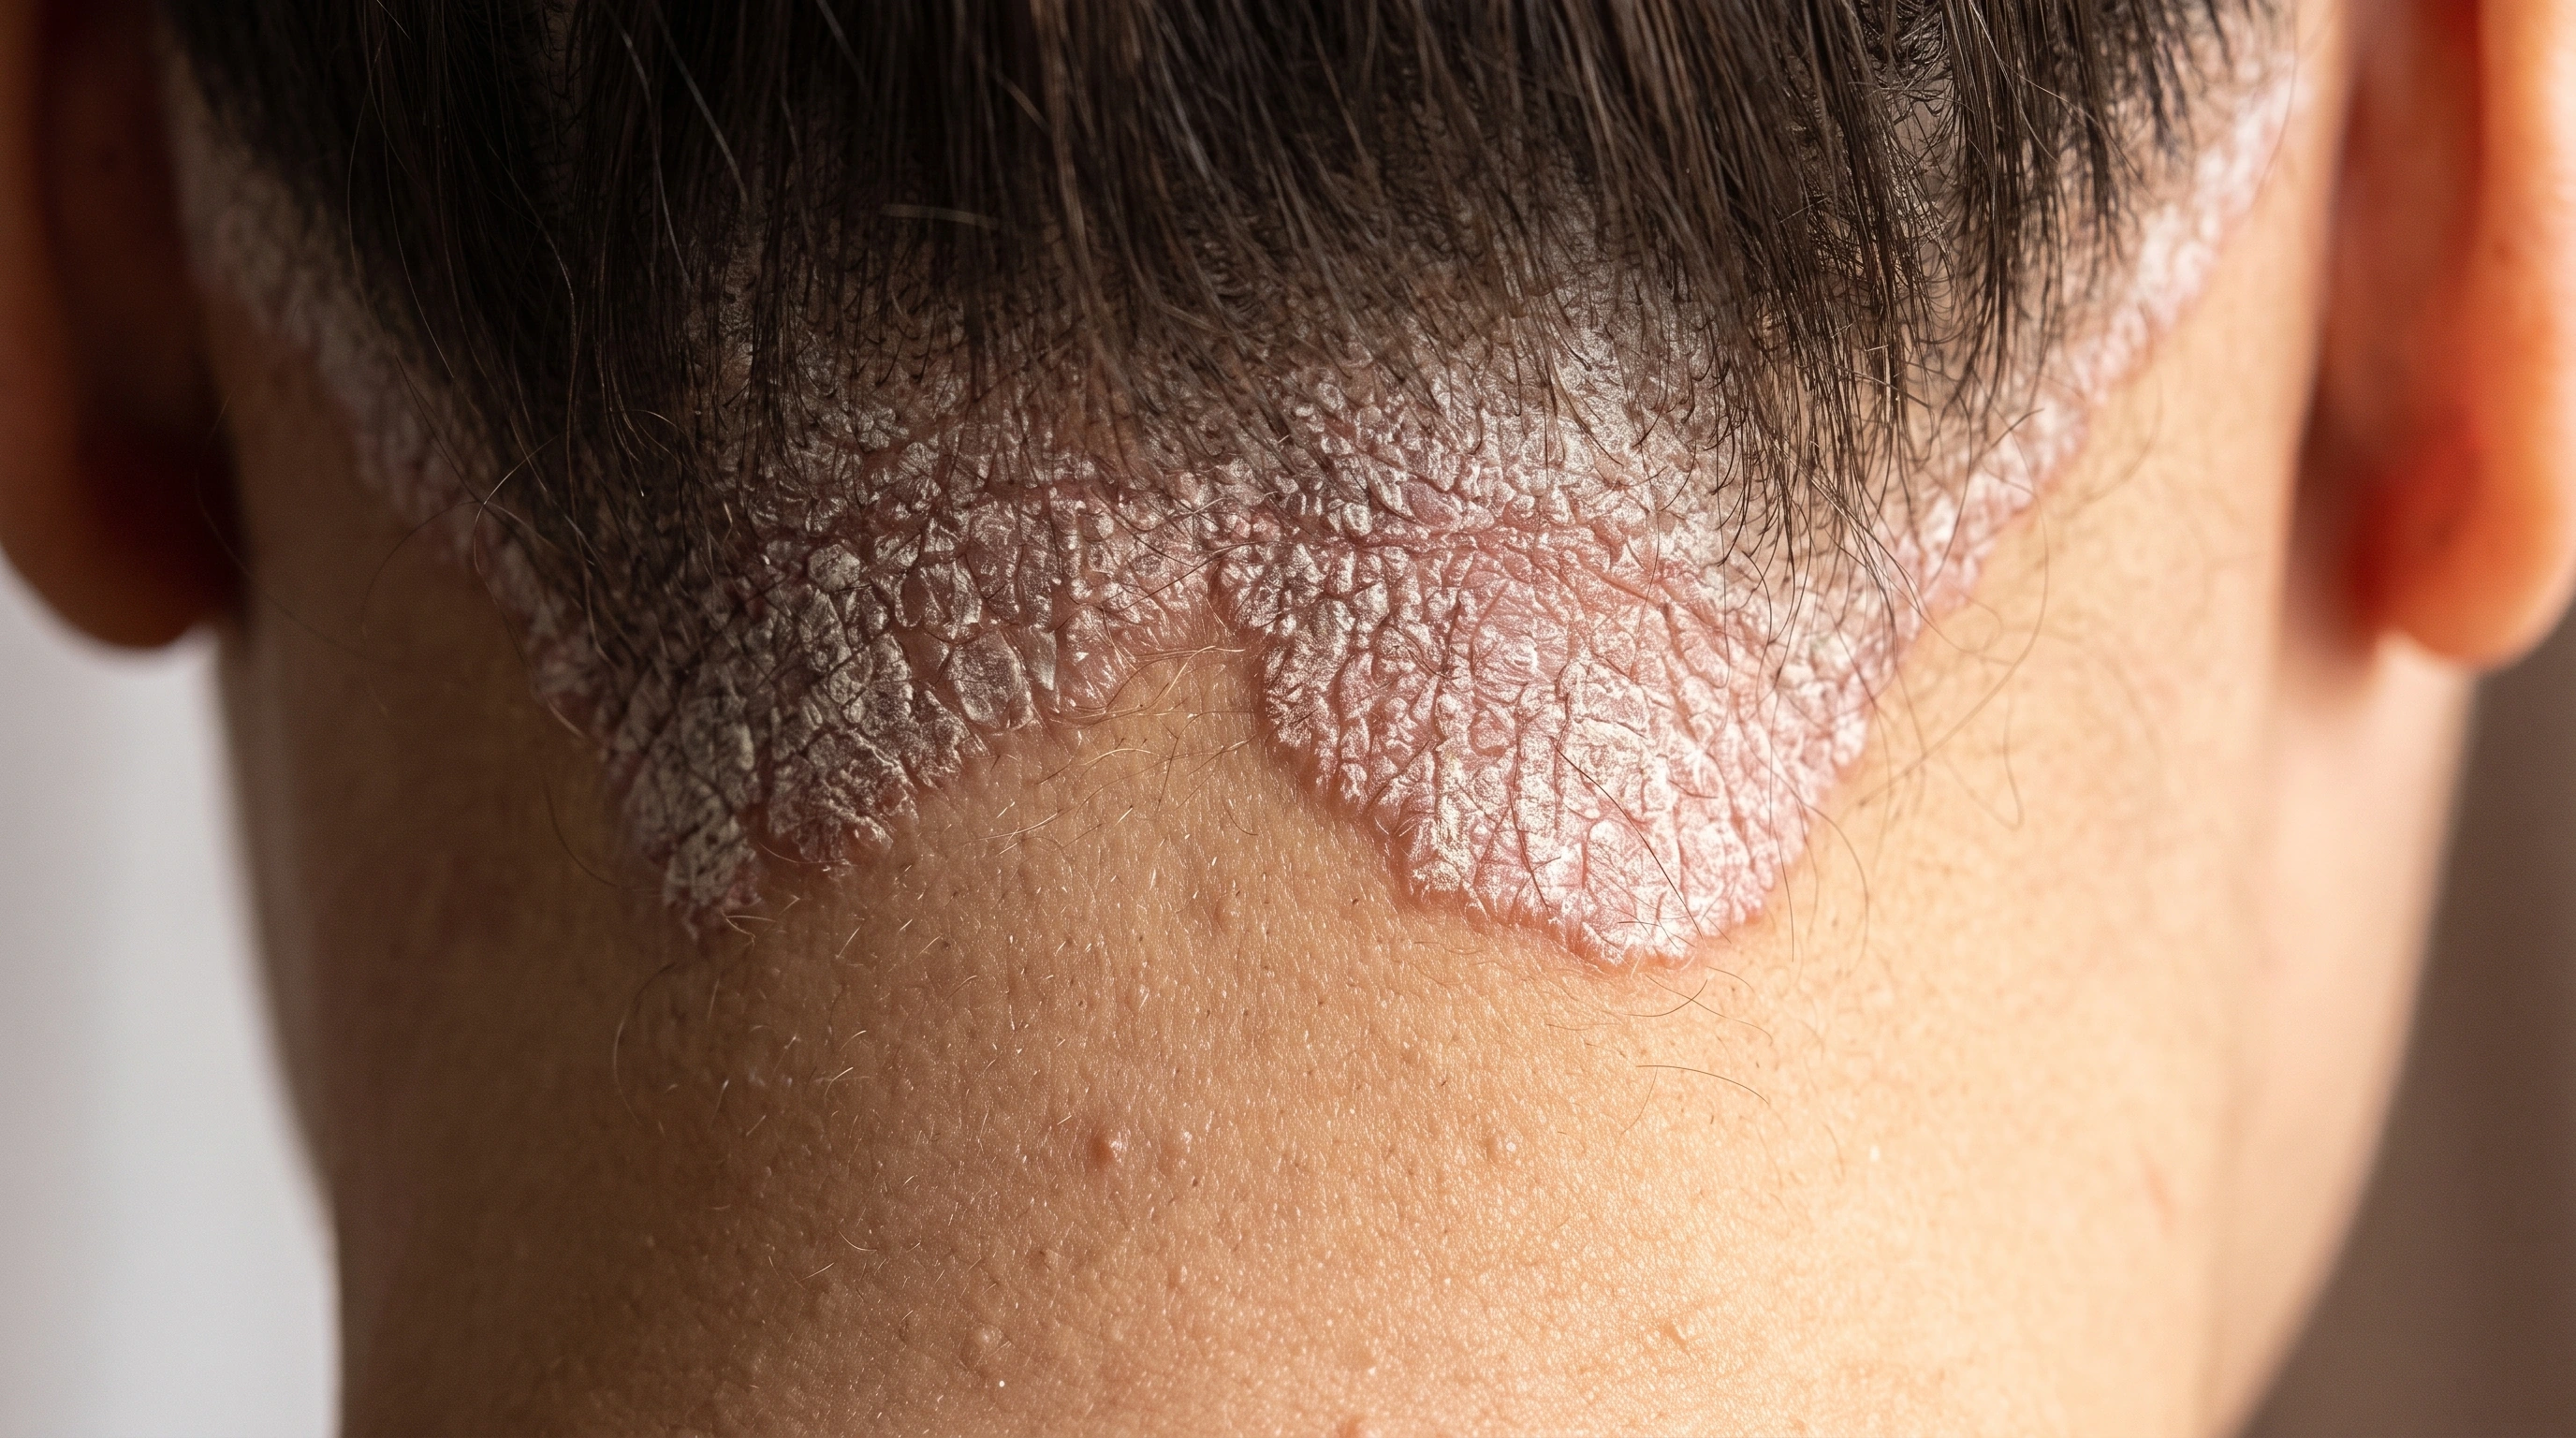
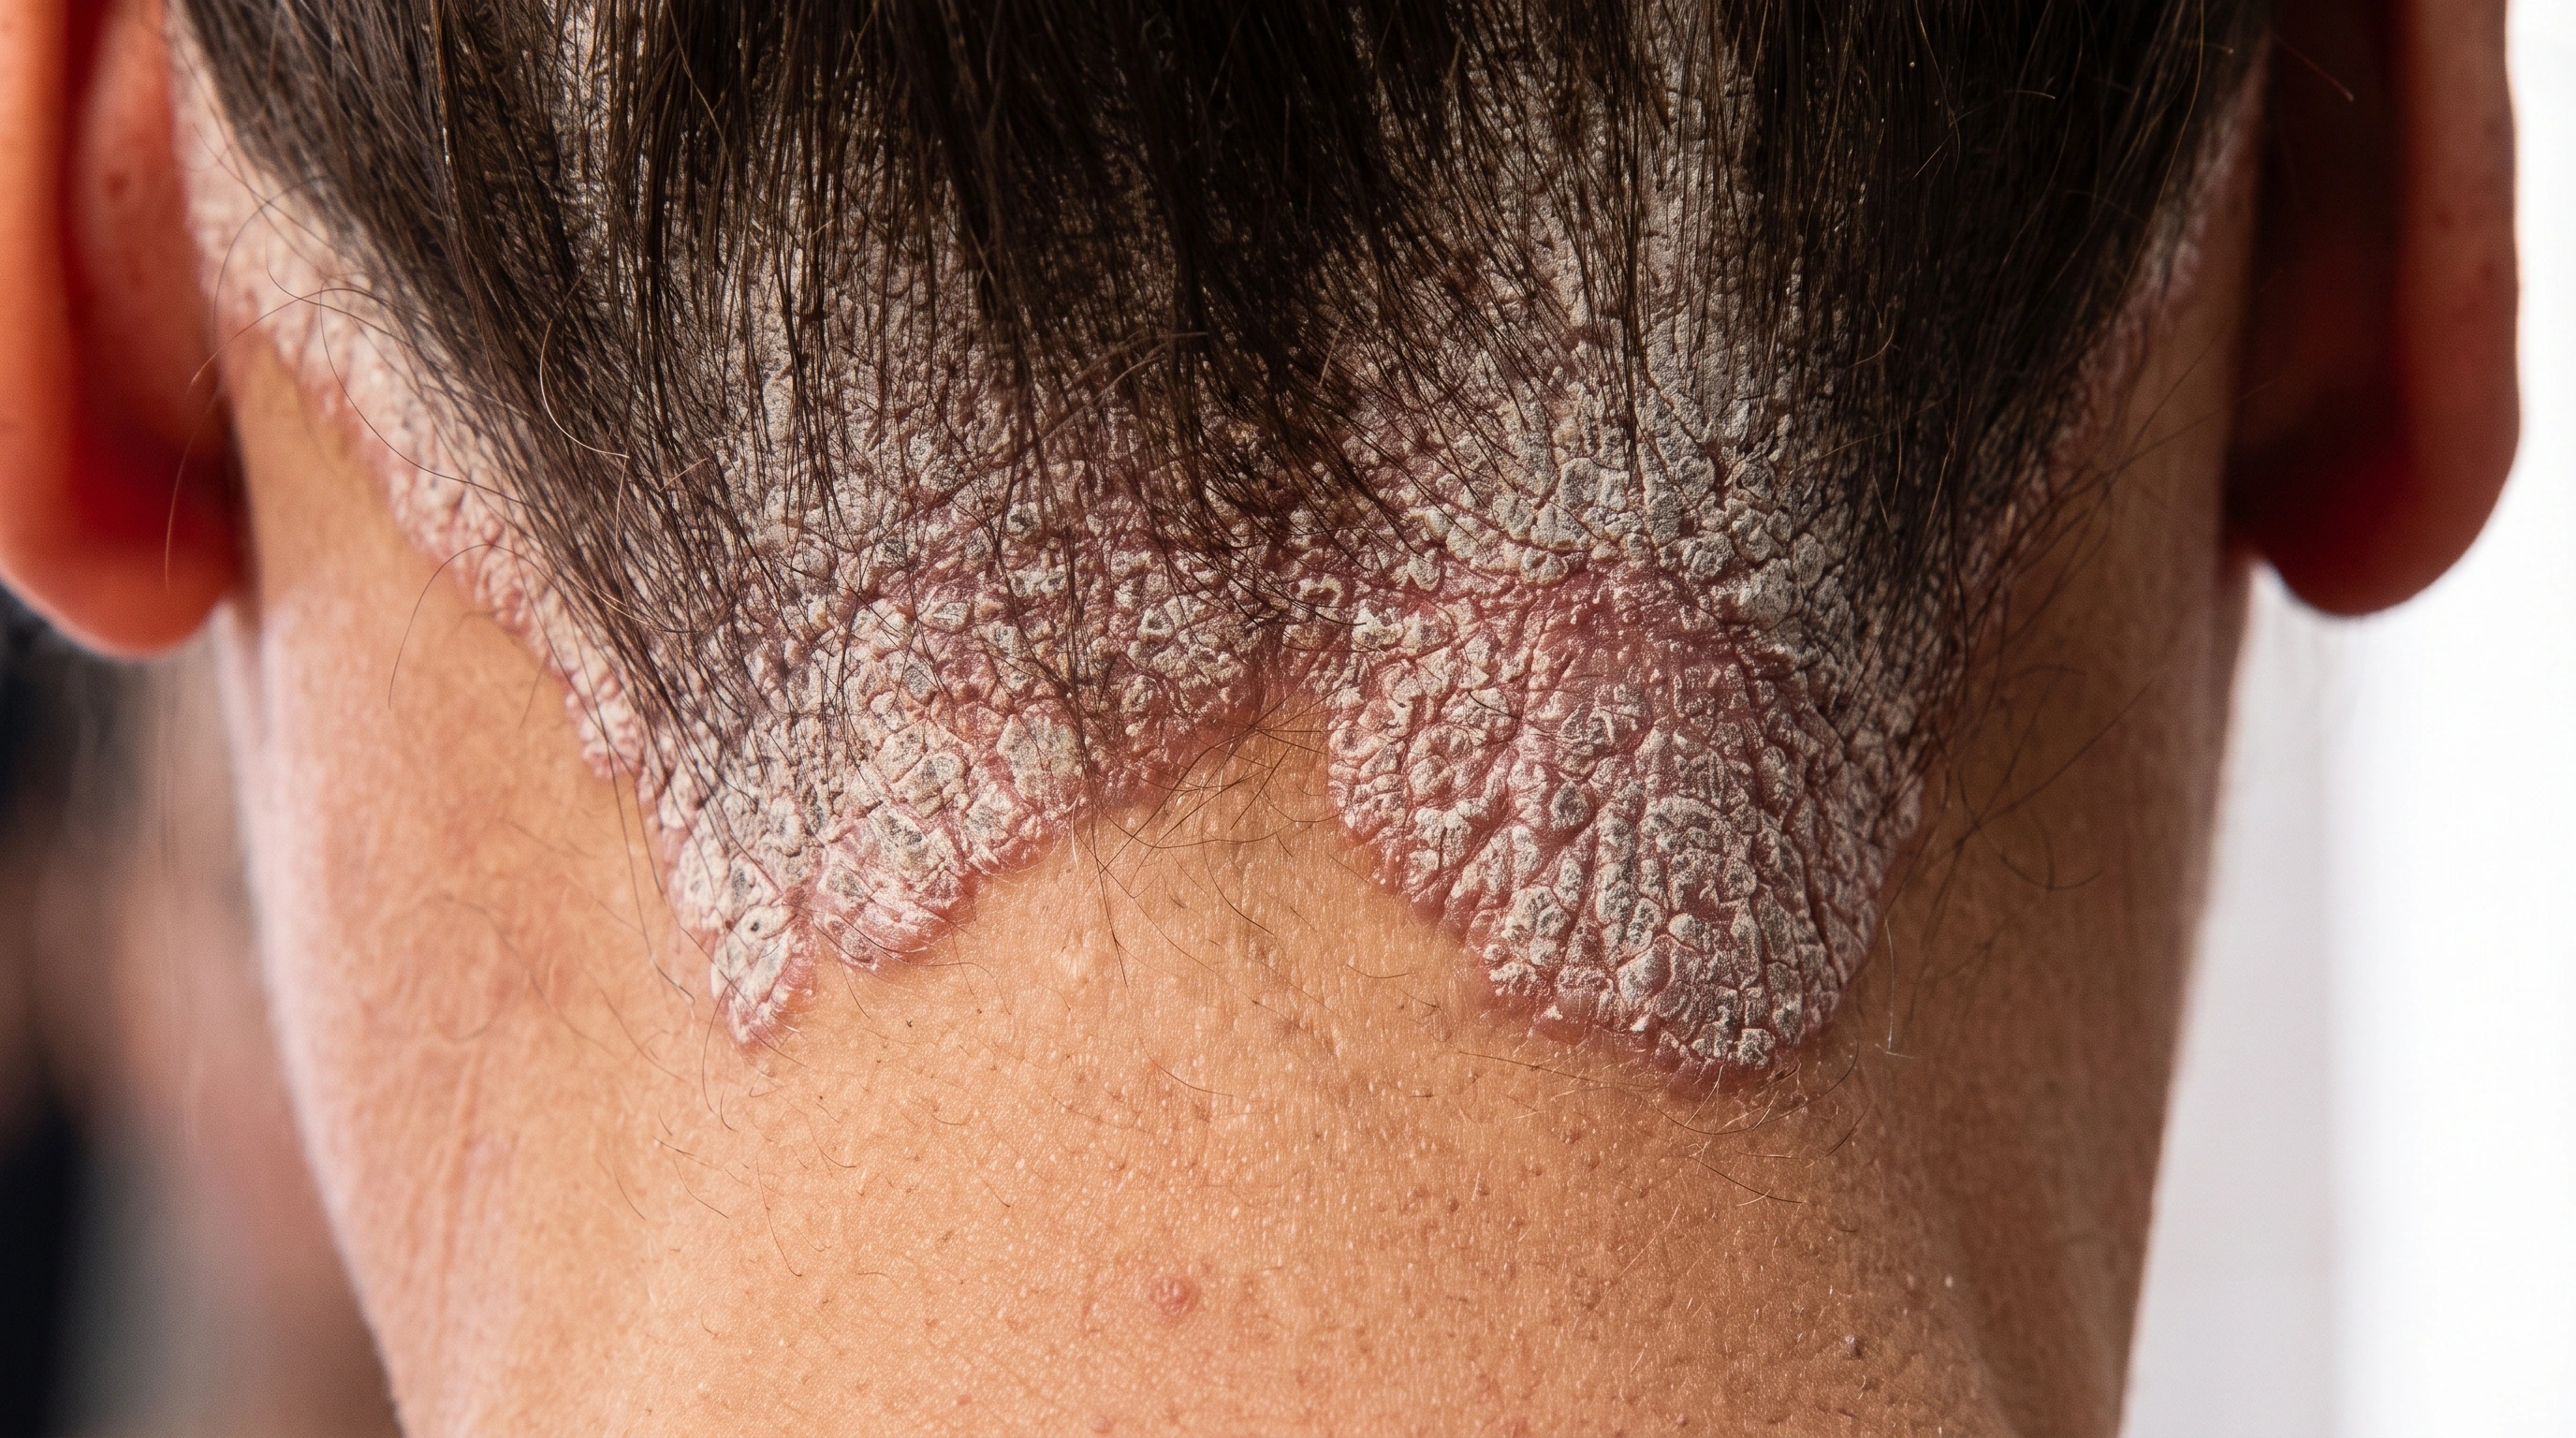
Thick white scale on pink scalp psoriasis plaques along the back hairline.

Thick scale Silvery patches on the scalp.

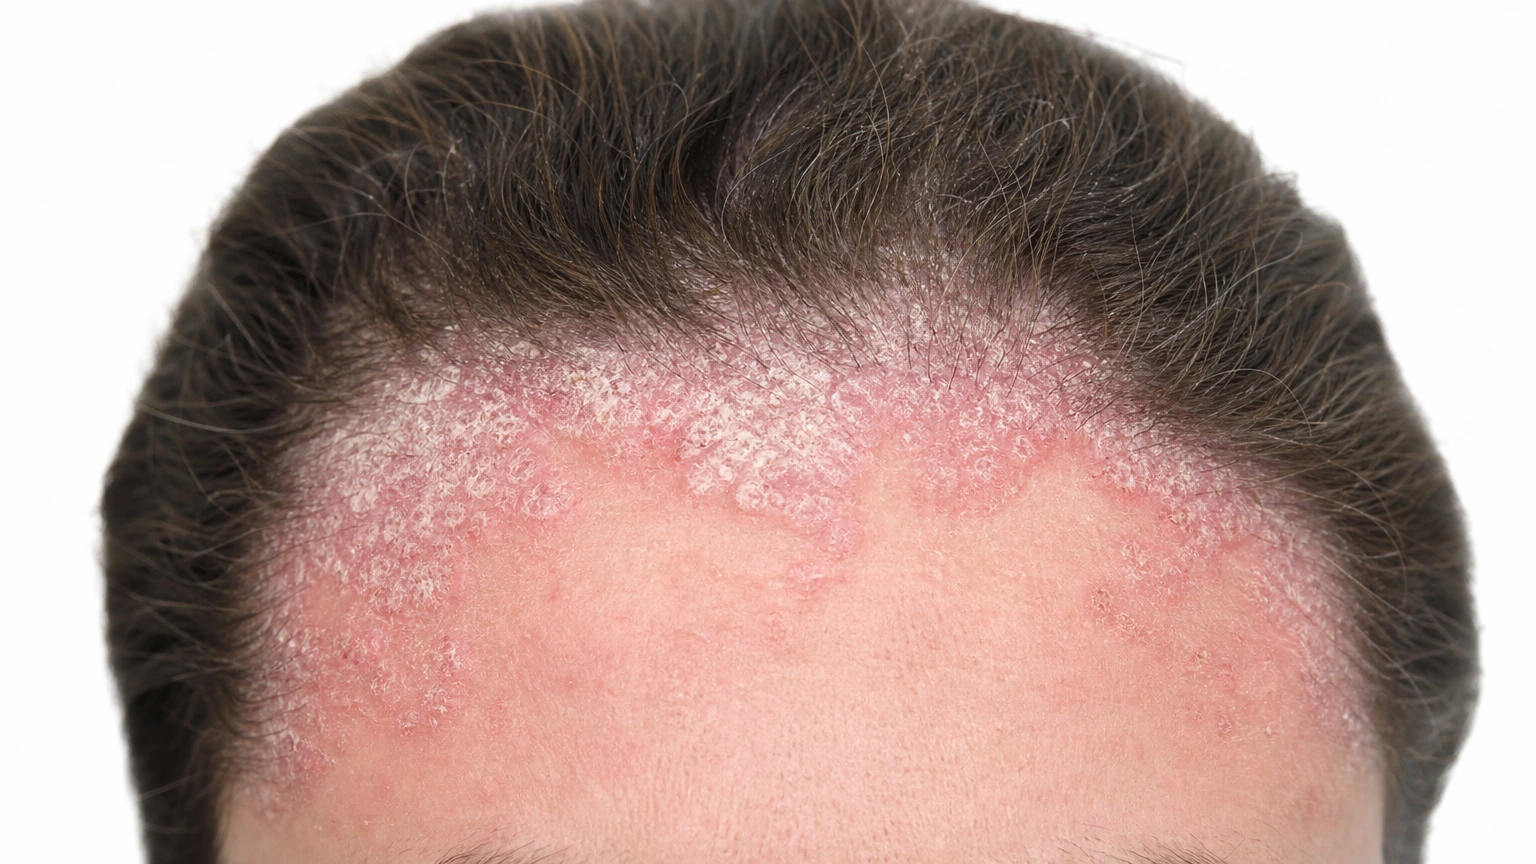
Red plaques with white scale extending from the scalp past the frontal hairline, representing scalp psoriasis.

Past the hairline Spreads onto the forehead.

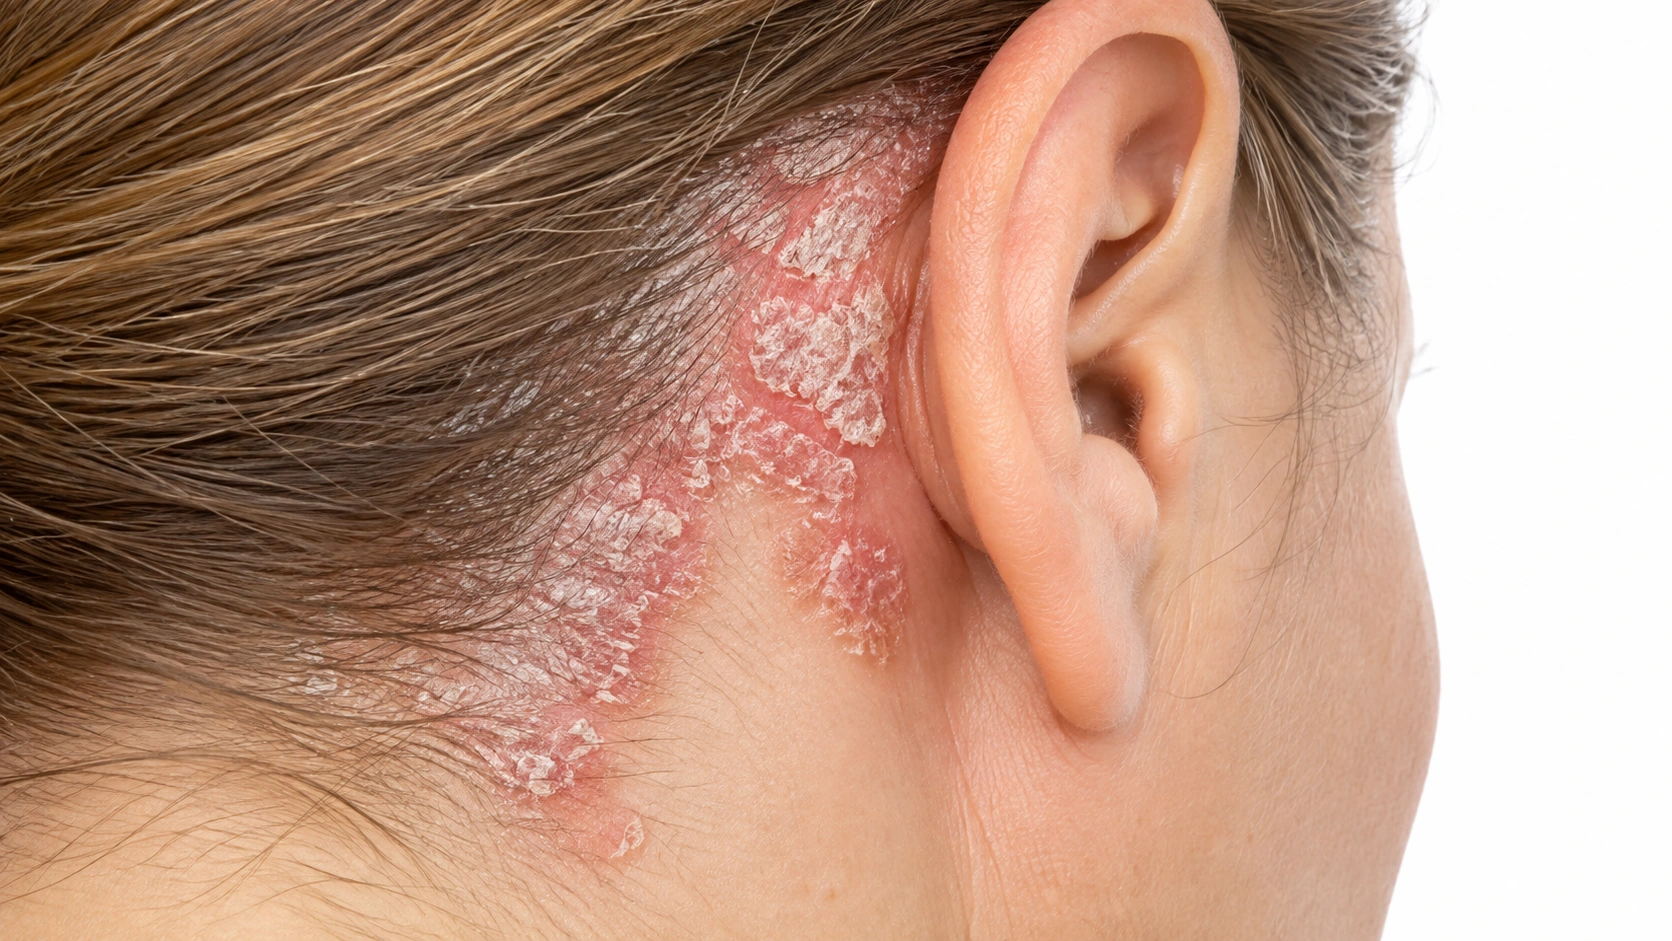
Psoriasis behind the ear.

Behind the ears Scale and redness.

Contact Dermatitis

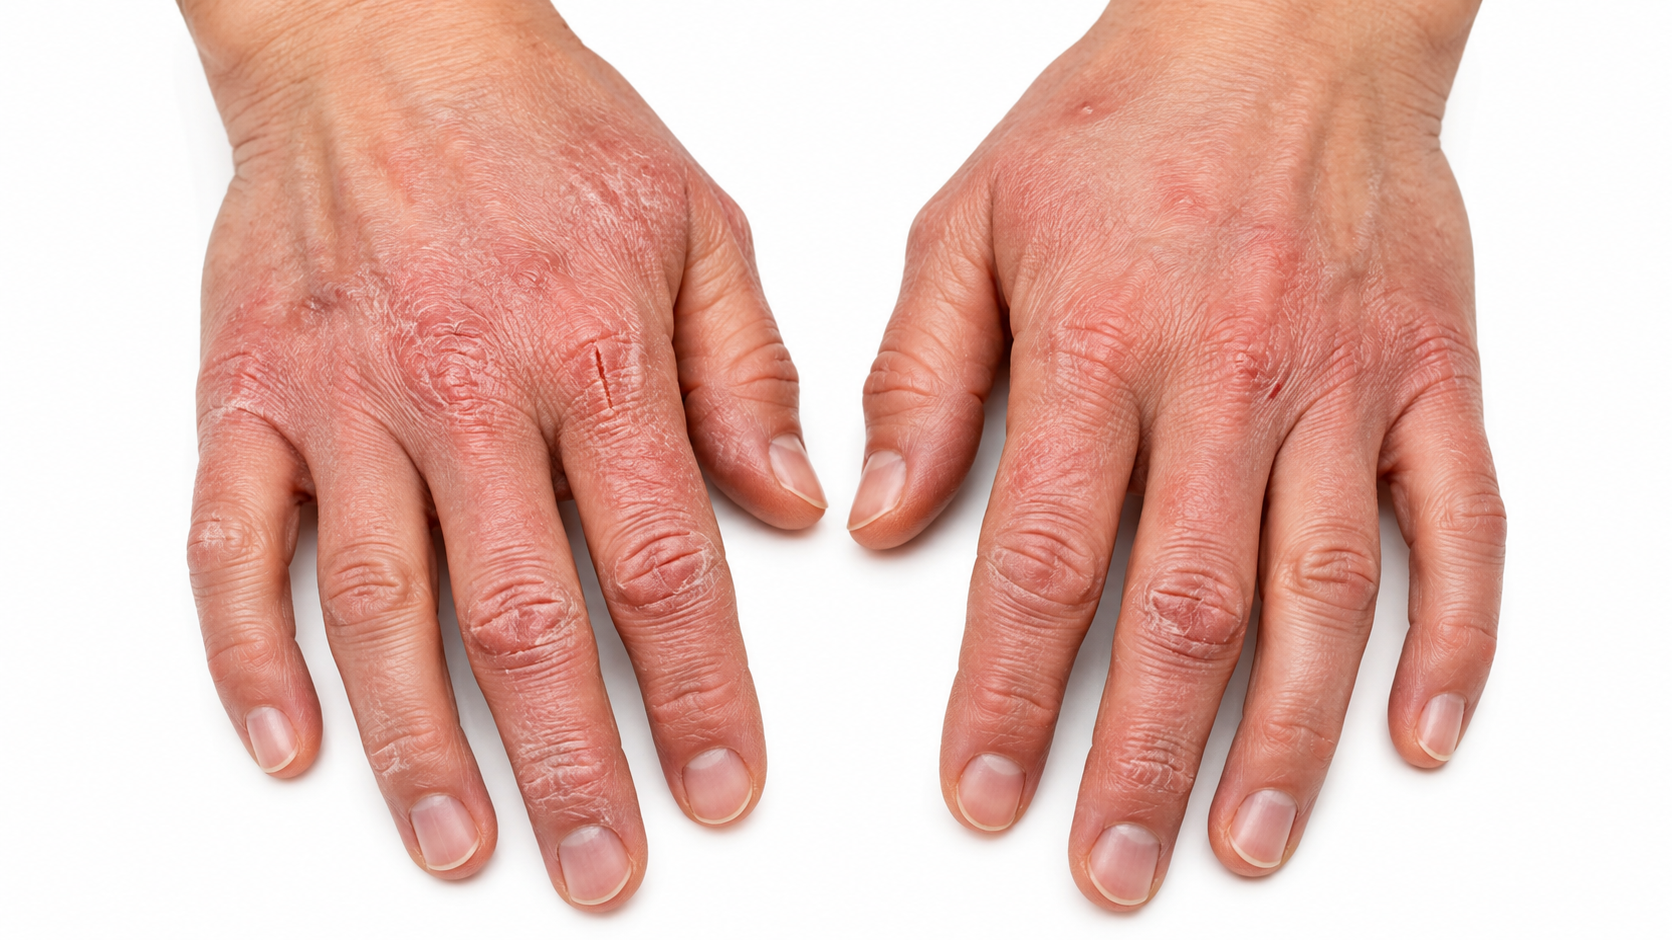
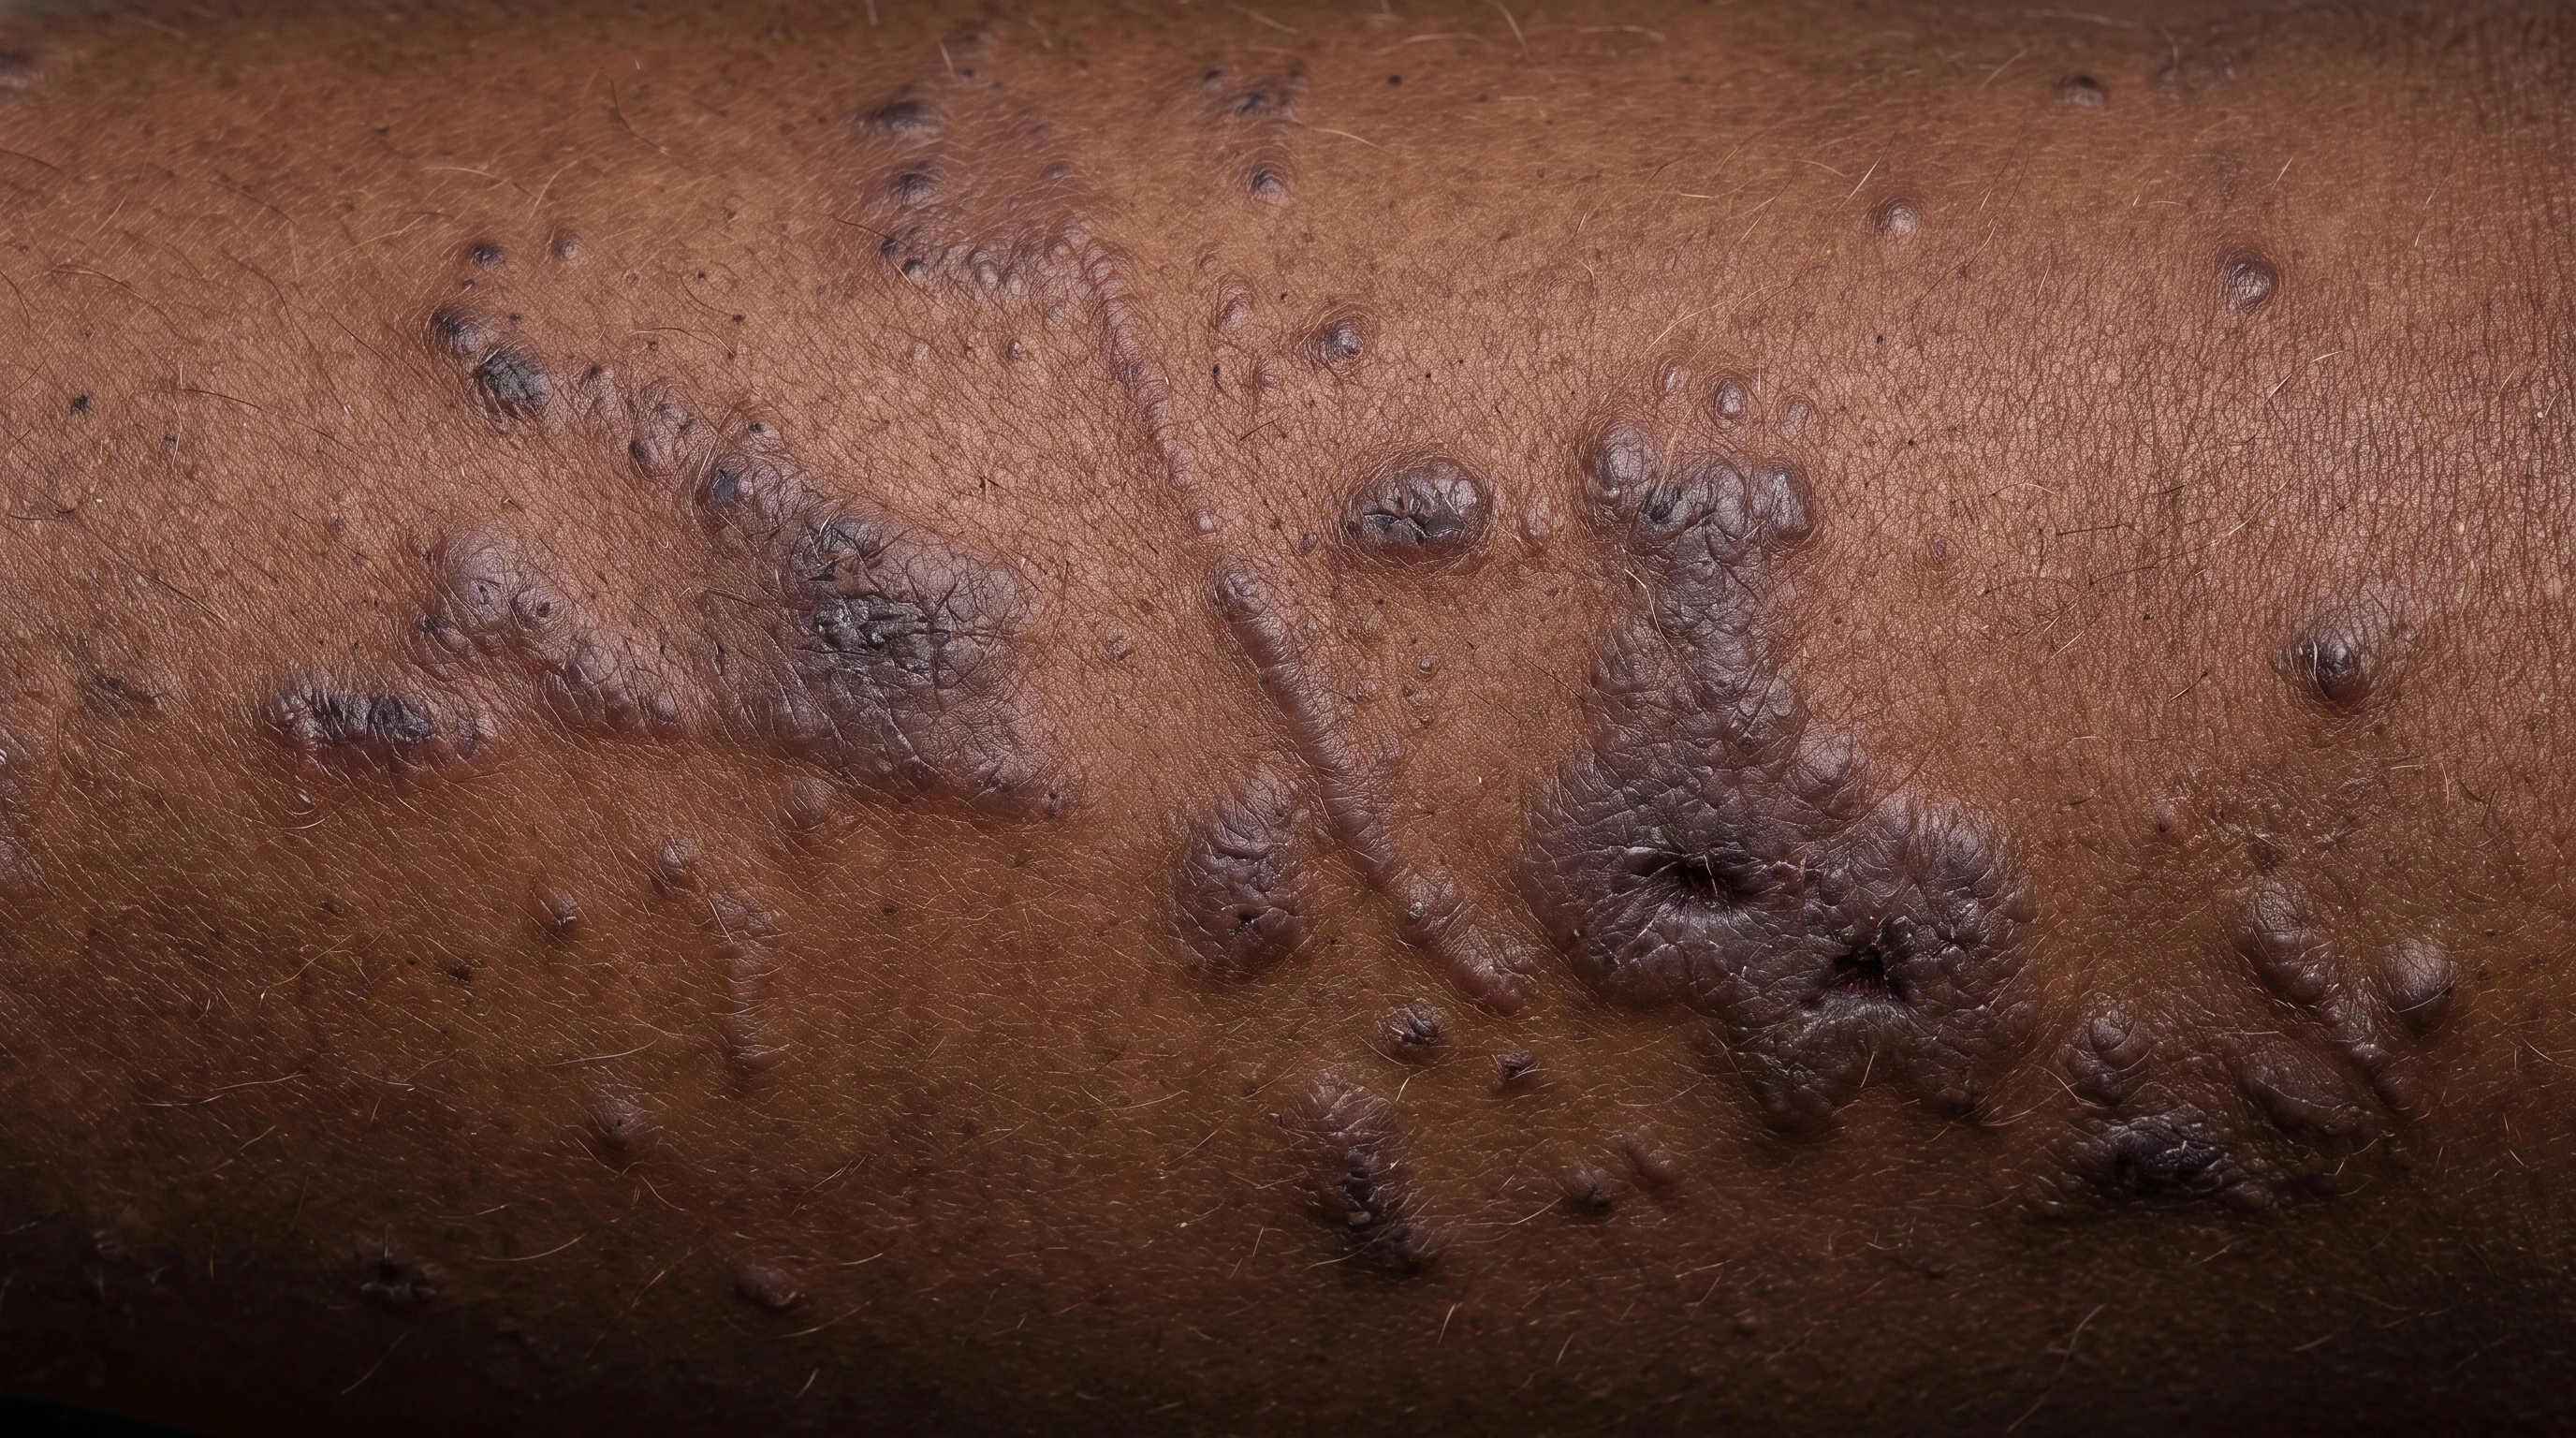
Contact Dermatitis: Dry, cracked hands; Irritant.

Irritant contact dermatitis Damage from soaps, solvents or water; most common.

Contact Dermatitis: Allergic.

Allergic contact dermatitis Immune reaction to nickel, fragrance, plants and more.

Skin tones
Parted hair on fair scalp skin showing a raised salmon-pink plaque topped with dry silvery-white scale, with a sharply drawn border against normal skin.
Parted hair on medium olive scalp skin showing a raised plaque with a dusky pink-brown base under dry silvery scale, with a clearly defined edge.
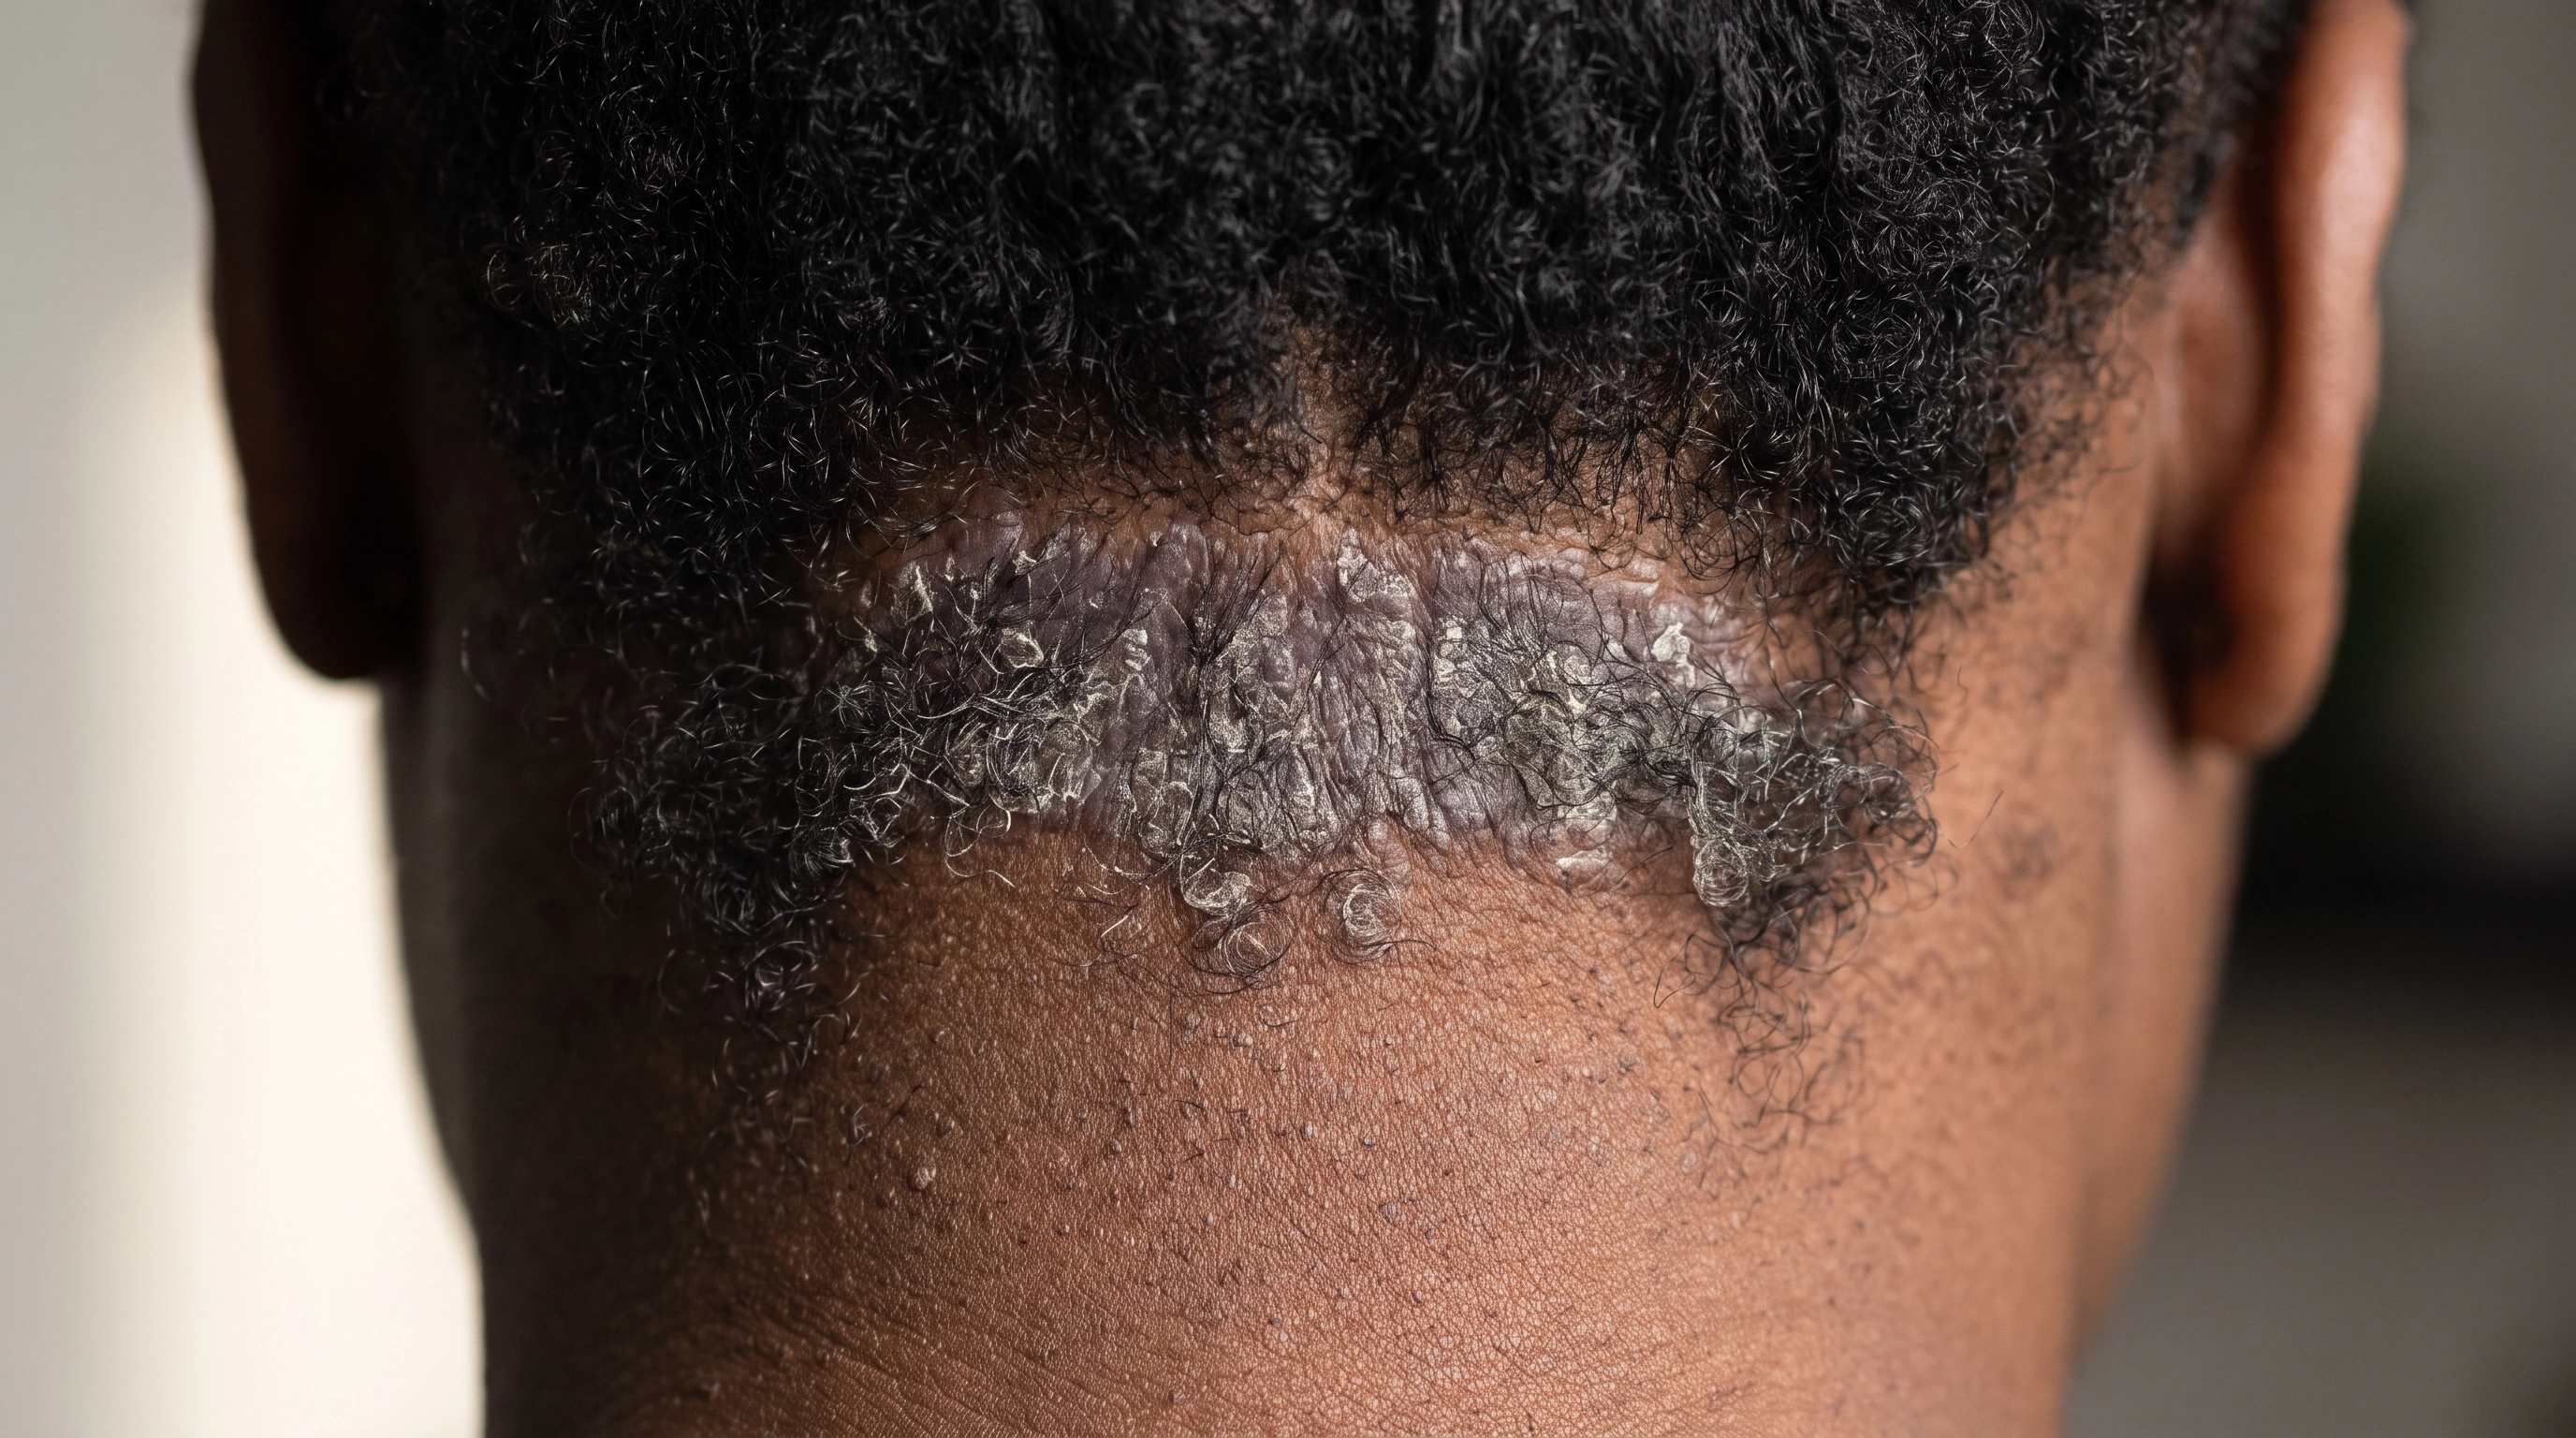
Parted hair on brown scalp skin showing a raised plaque with a violet-brown base under dry silvery scale, with a clearly drawn border and no visible redness.
Parted hair on deep brown scalp skin showing a raised gray-violet plaque topped with grayish scale, and beside it a flat lighter patch of healed skin with no scale.
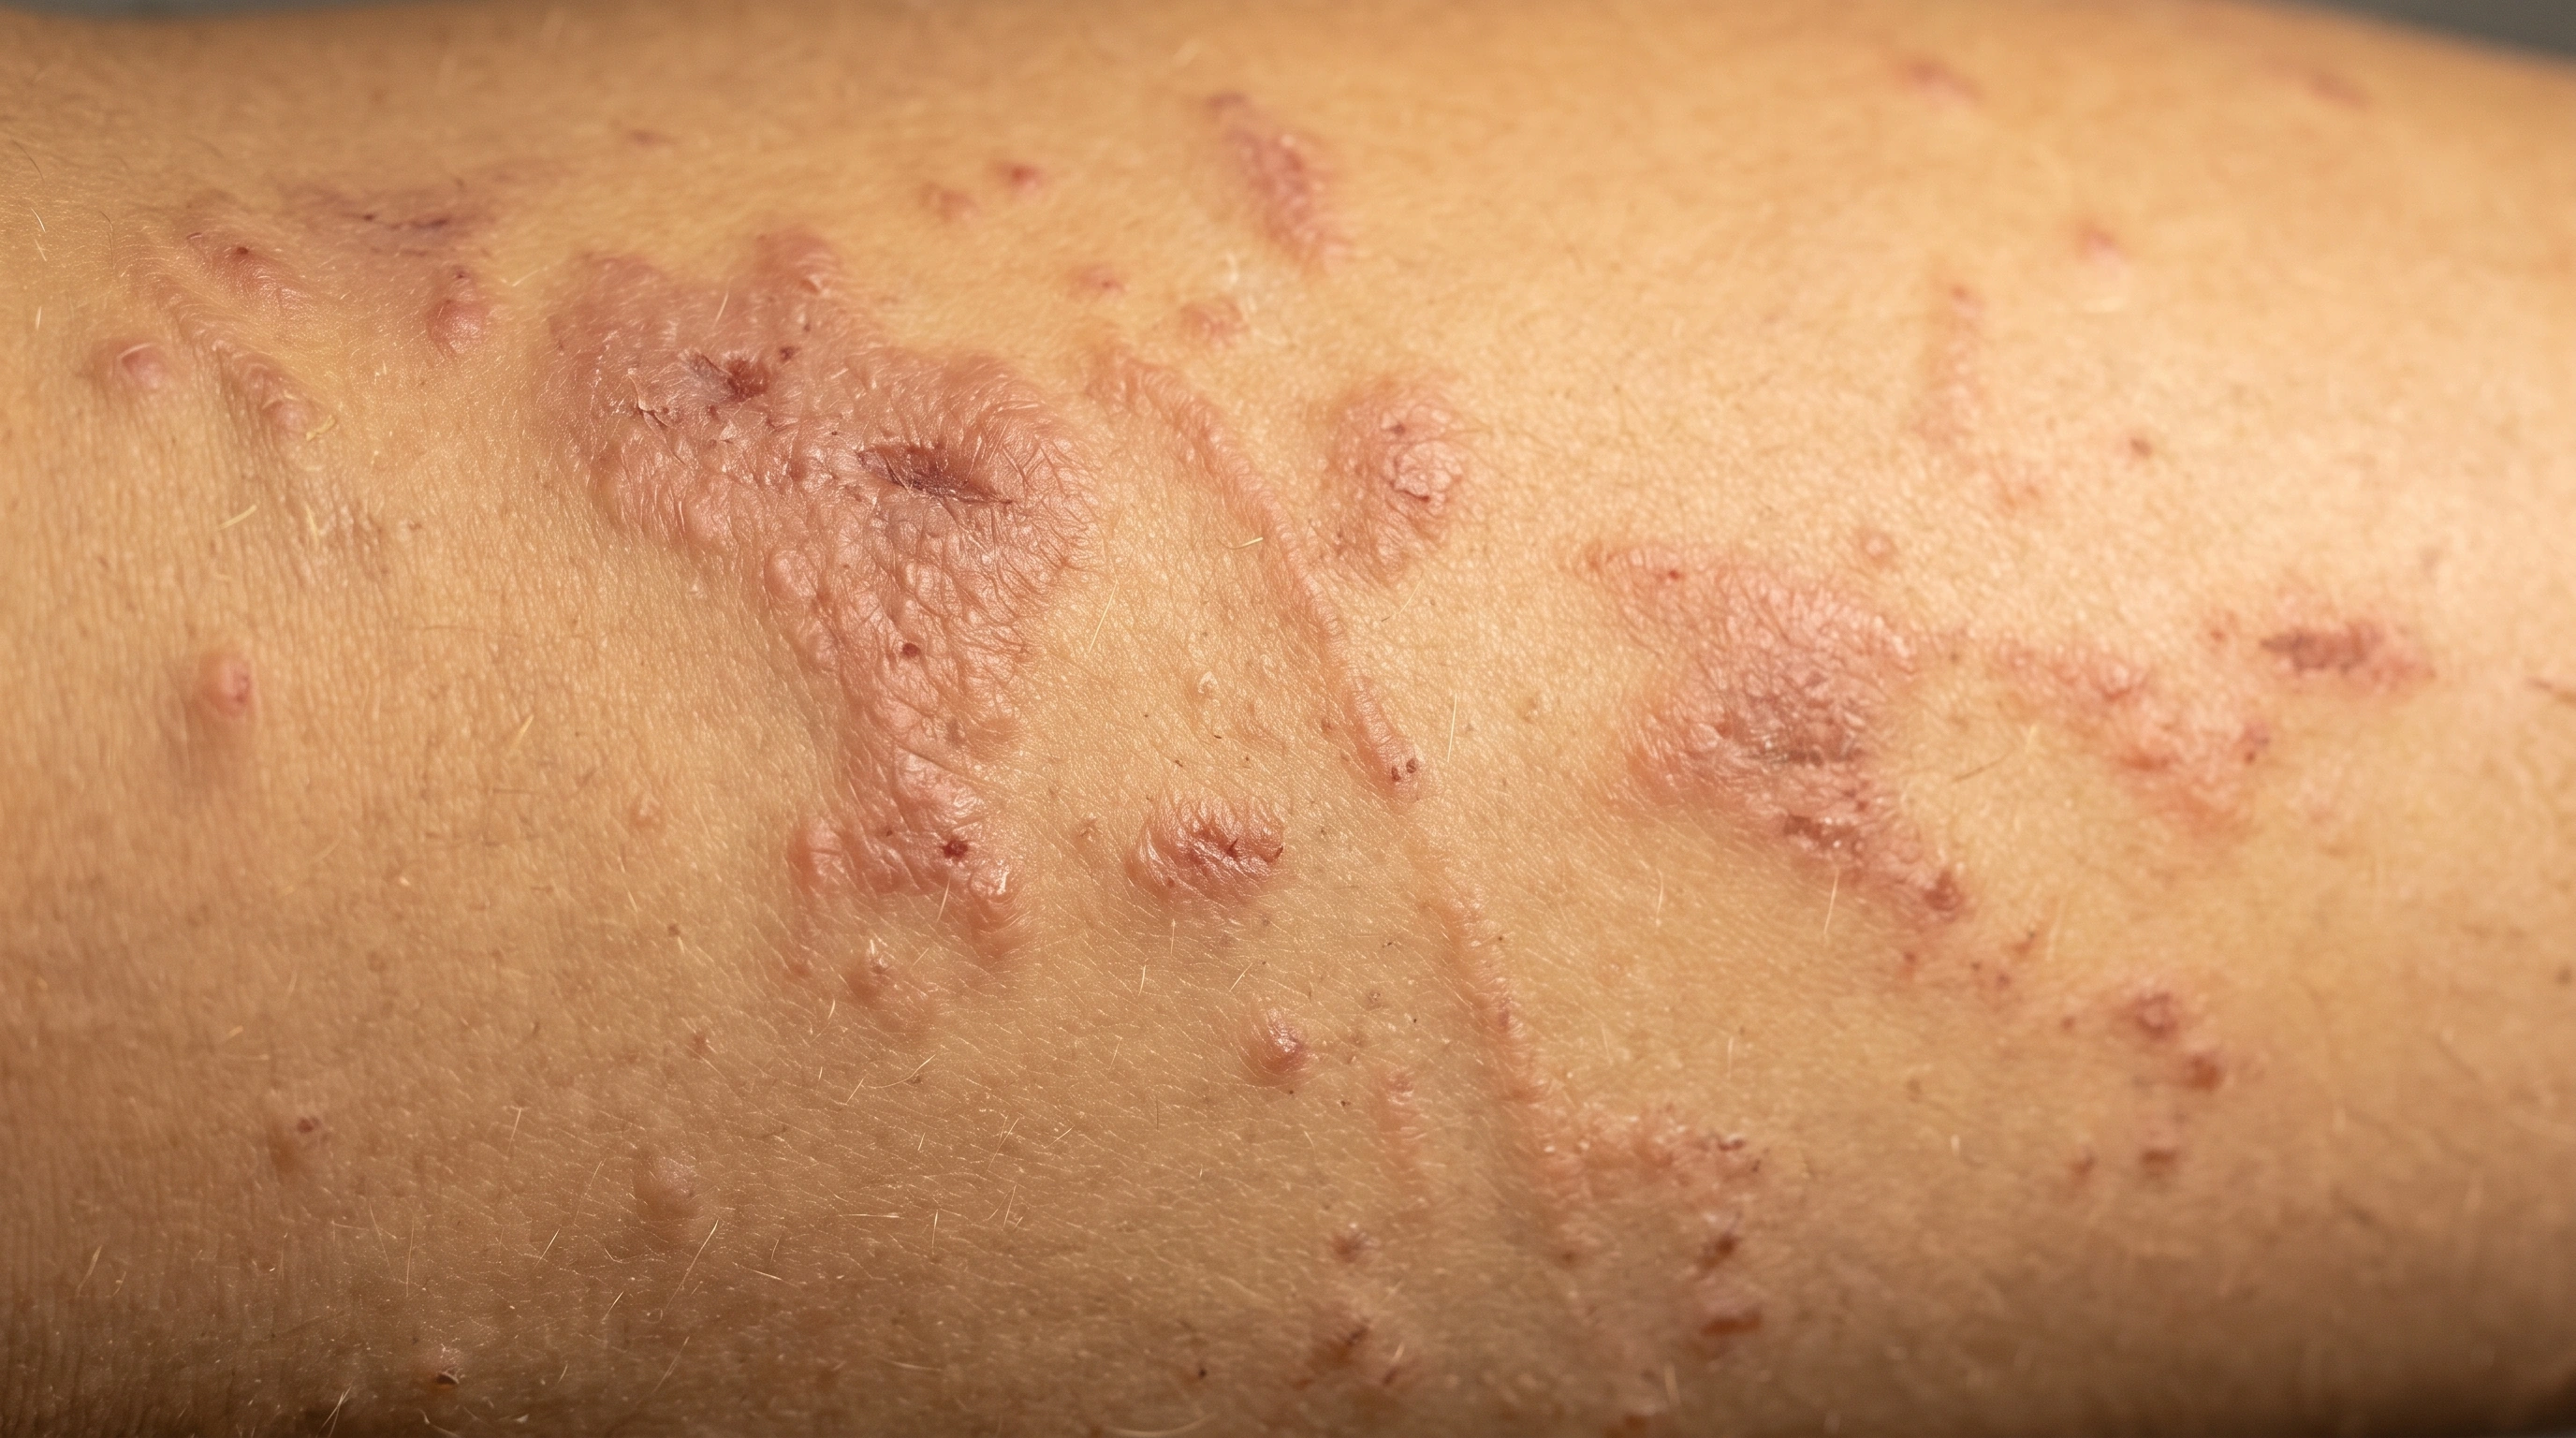
The back of one hand and the wrist on pale skin. A bright pink, slightly swollen patch with tiny blisters covers the back of the hand and stops at a straight line across the wrist.
The back of one hand and the wrist on medium olive skin. A dusky pink-brown, slightly swollen and scaly patch covers the back of the hand and stops at a straight line across the wrist.
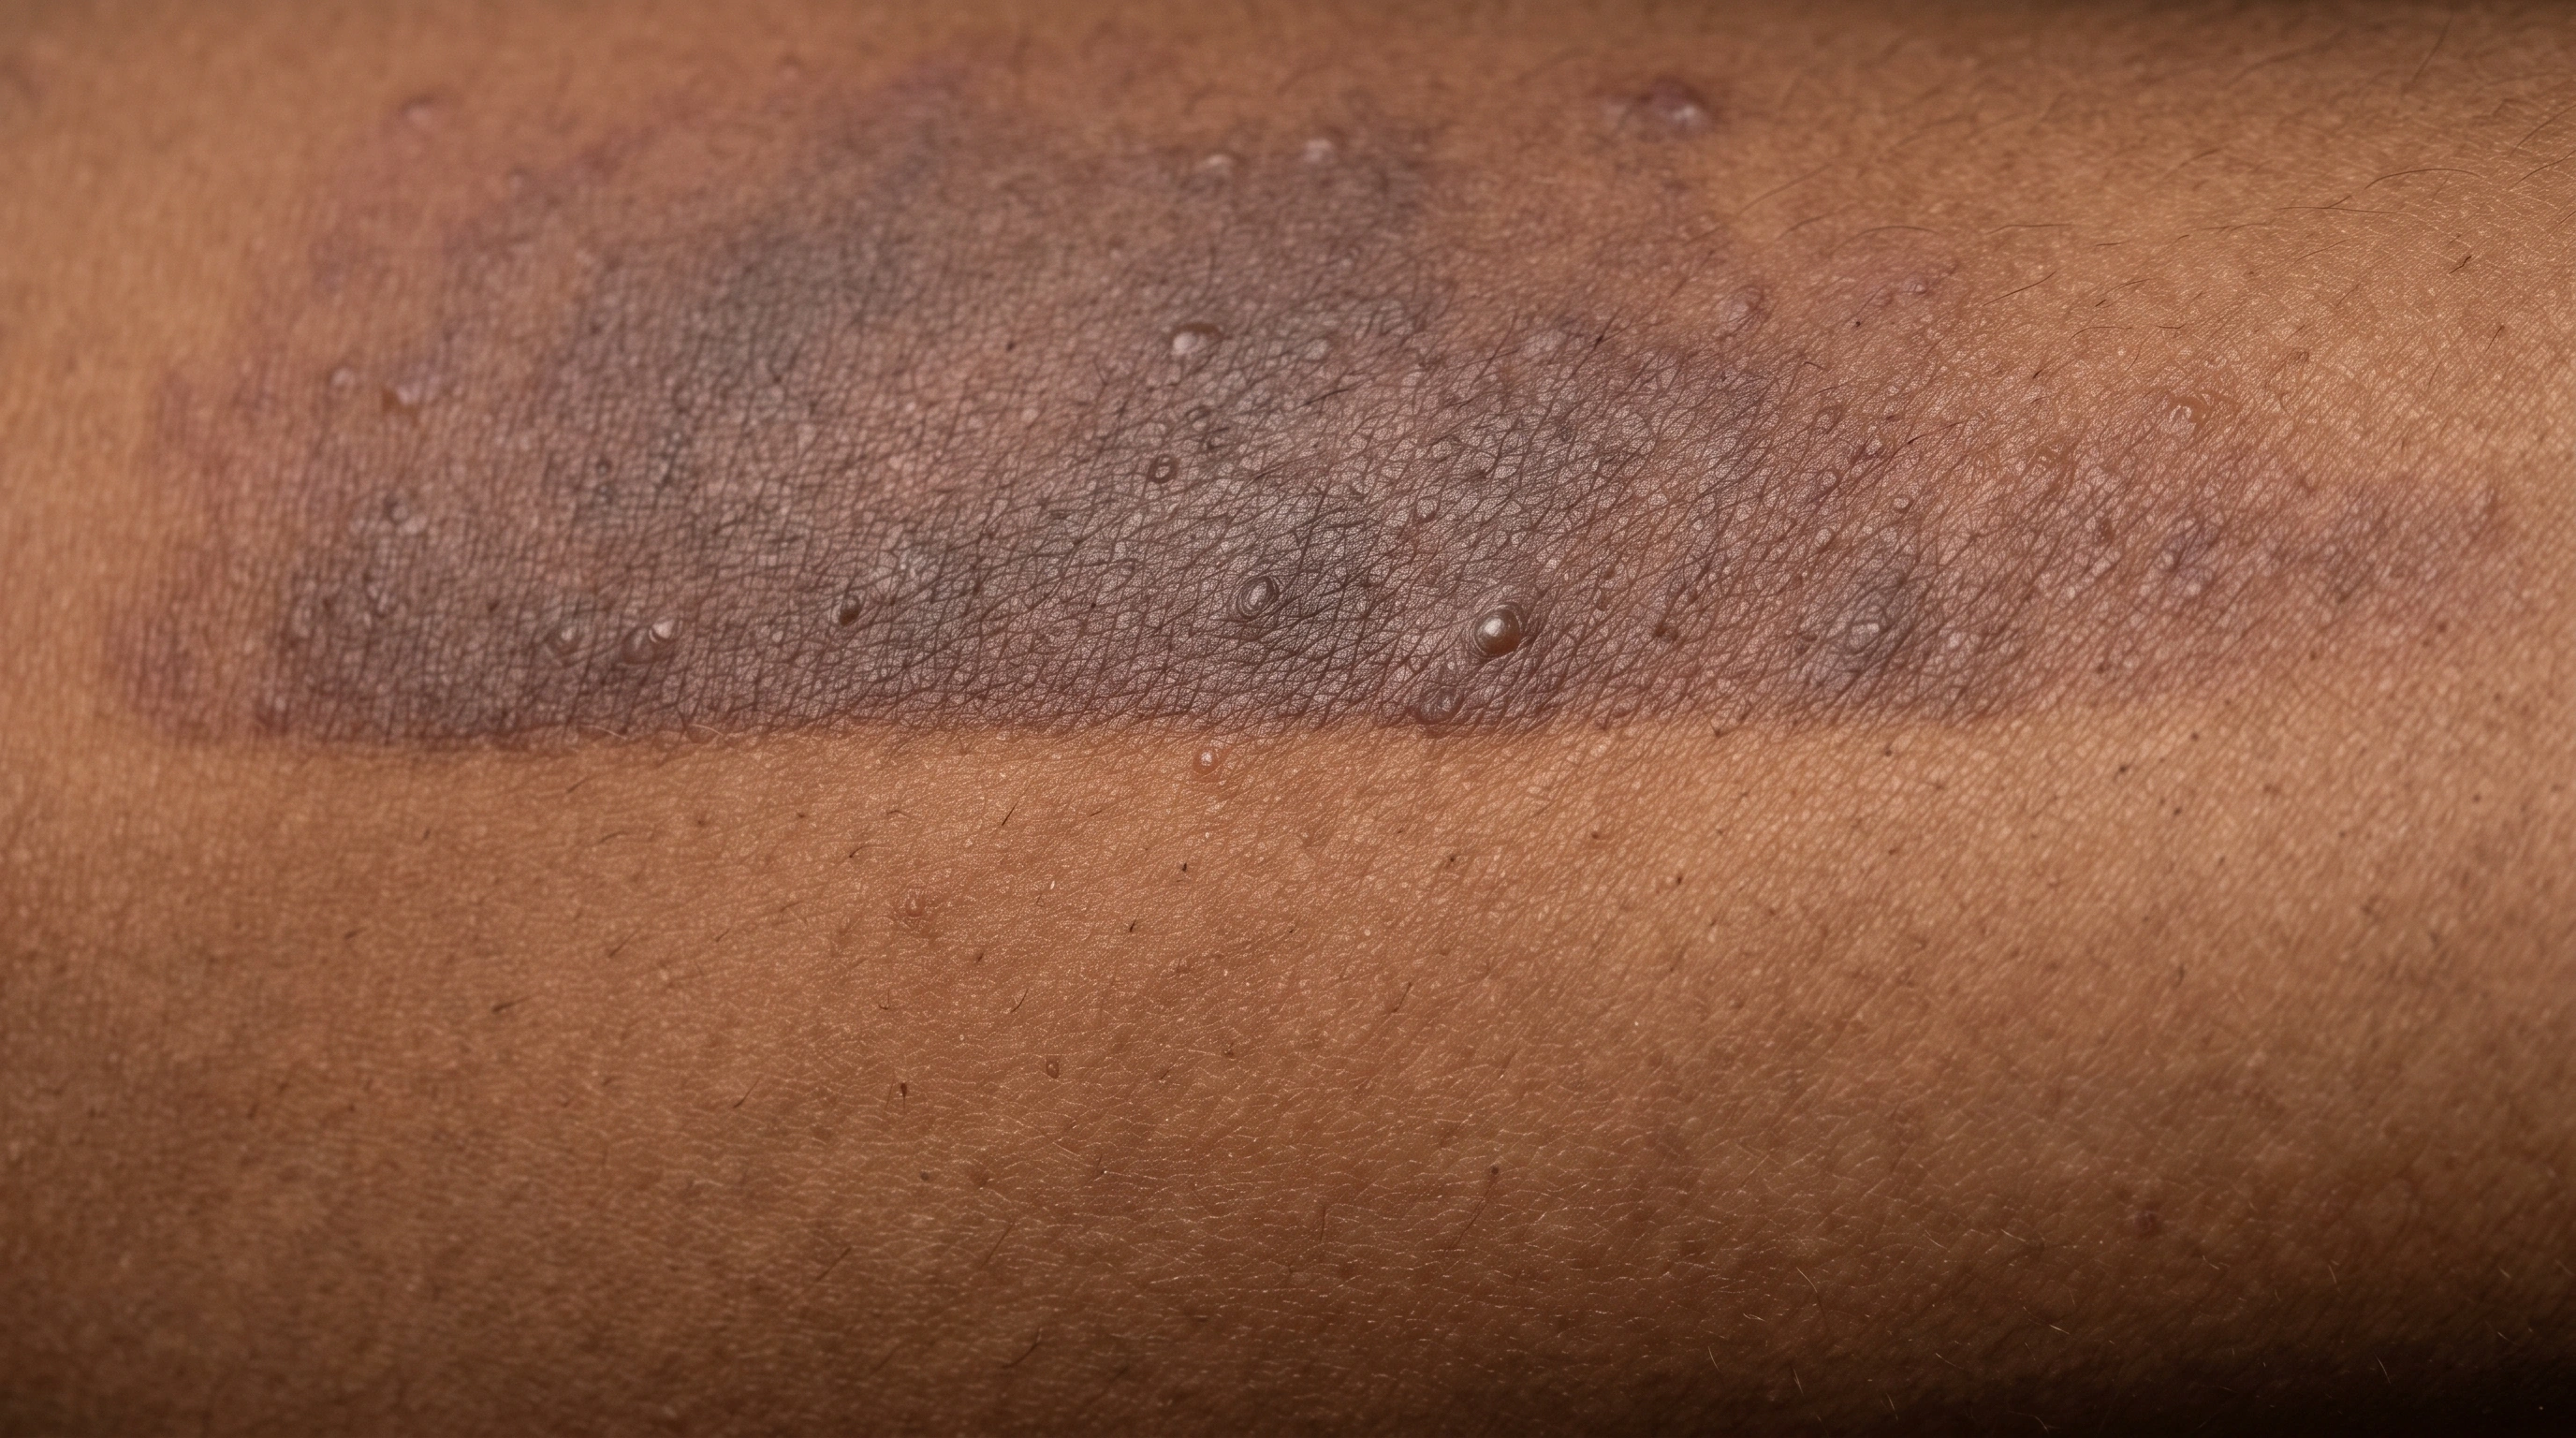
The back of one hand and the wrist on mid-brown skin. A violet-brown, swollen, slightly scaly patch covers the back of the hand and stops at a straight line across the wrist, with no red color in it.
The back of one hand and the wrist on deep brown skin. A dark violet-brown, swollen, scaly patch covers the back of the hand and stops at a straight line across the wrist, with no red color anywhere in it.
Diagram
Scalp Psoriasis mechanism diagram. Scale collects around hairs: Plaques may extend beyond the hairline. Skin cells build up too quickly: The epidermis becomes thicker. Immune signals drive inflammation: The response affects scalp skin.
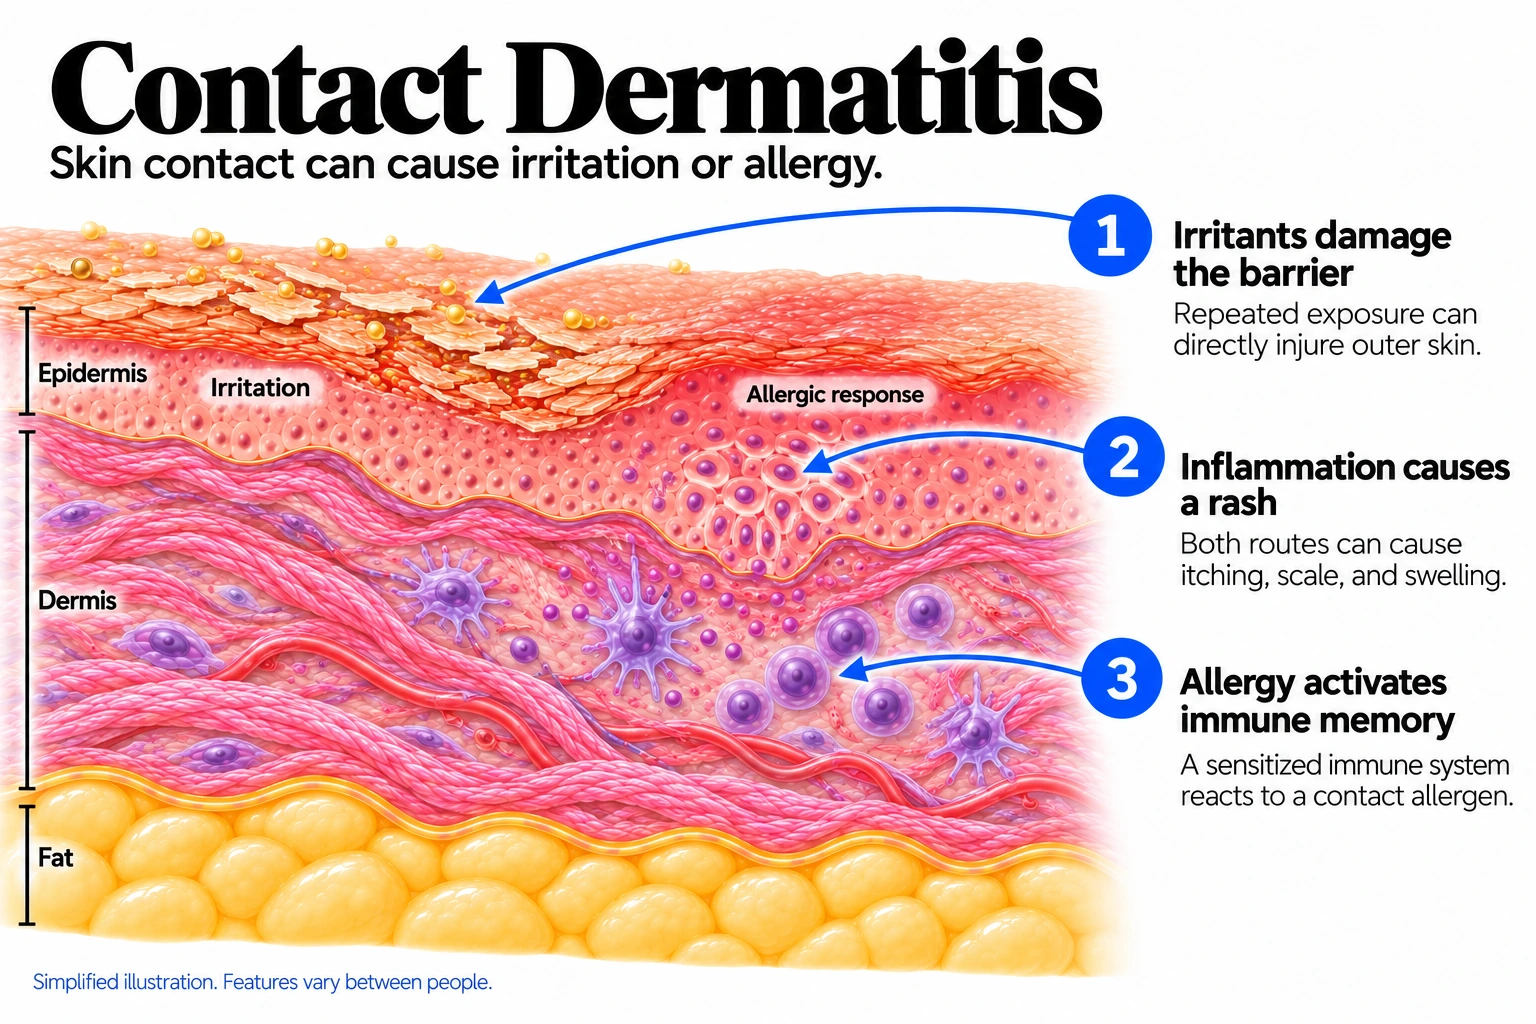
Contact Dermatitis mechanism diagram. Irritants damage the barrier: Repeated exposure can directly injure outer skin. Inflammation causes a rash: Both routes can cause itching, scale, and swelling. Allergy activates immune memory: A sensitized immune system reacts to a contact allergen.
In the skin

Overactive immune signals speed up the production of scalp skin cells. The cells accumulate in thickened plaques with scale that can collect around hairs and extend beyond the hairline.

Skin contact can cause inflammation through direct irritation or a delayed allergic reaction. These are different routes to a rash that may itch, swell, blister or scale.

Where it shows up

Scalp, hairline and behind the ears
Where the skin meets a trigger

When it usually starts

010203040506070+

Scalp Psoriasis. Can begin at any age as part of psoriasis; the scalp may be the first affected site.

Contact Dermatitis. Can begin at any age after irritation or sensitization to a contacting substance.

Causes and triggers

Causes

Scalp psoriasis is psoriasis on the scalp. The immune system speeds up skin growth there, building thick, scaly patches.

Contact dermatitis happens when something touching the skin either damages it directly or sets off an allergic reaction. The rash shows up where the contact happened.

Family tendency

It shares the same inherited tendency as other psoriasis.

People with eczema or a family history of allergies react more easily.

Risk factors
Psoriasis elsewhere, Obesity, Smoking
Eczema, Wet work, Healthcare, cleaning and hairdressing jobs, Frequent handwashing
Trigger
● Scalp Psoriasis
● Contact Dermatitis
Stress
Well established
Not listed
Scratching the scalp
Well established
Not listed
Cold, dry weather
Possible
Not listed
Strep throat
Strong link
Not listed
Nickel
Not listed
Well established
Fragrance
Not listed
Well established
Poison ivy
Not listed
Well established
Hair dye
Not listed
Strong link
Harsh soaps and solvents
Not listed
Well established
Preservatives in skincare
Not listed
Strong link

Daily Care

Scalp Psoriasis
Contact Dermatitis
Daily care

Habits that help

  • Moisturize the scalp
    Reduces tightness and the itch that drives scratching.
  • Cool it instead of scratching
    A cold, damp cloth.
  • Calcipotriene, a vitamin D treatment
    Slower than a steroid, usable for longer.
  • Soften the scale before you treat
    Oil or salicylic acid loosens it.
  • Leave medicated shampoo on for the product-specific contact time
    Contact time depends on the formulation; follow the label or prescription rather than using one fixed time for every product.
  • Report symptoms of throat or other infections
    A recognized flare trigger.
  • Review possible medicine triggers with the prescriber; do not stop medicines yourself
    Lithium, beta blockers, antimalarials — never stop one yourself.
  • Adjust moisturizing and indoor humidity during dry weather
    Dry air thickens scale.
  • Allow the label’s contact time before rinsing medicated shampoo
    Follow the product-specific contact time. Longer exposure is not always better and may irritate.

Avoid

  • Avoid: Stress
    A consistently reported flare trigger.
  • Avoid: Smoking
    More severe disease, weaker treatment response.
  • Avoid: Heavy alcohol use
    More severe psoriasis, poorer response.
  • Avoid: Picking and lifting the scale off
    Tears skin, takes hair with it.
  • Avoid: Scratching
    Psoriasis appears where skin has been injured.
  • Avoid: Fine-tooth combs and hard brushing
    Picking, spread wider.
  • Avoid: Chemical processing during a flare
    Relaxers and dyes burn inflamed skin; burns bring patches.
  • Avoid: Tight braids, weaves and extensions
    Constant pull on an inflamed scalp.
  • Avoid: Stopping treatment when it looks clear
    Controlled, not cured.
  • Avoid: Only shampooing the hair, not the scalp
    Medicated shampoo works on skin.

Habits that help

  • Find the cause and stop it
    Photograph it and list what touches it.
  • Learn the ingredient names
    One molecule hides in dozens of products.
  • Switch to fragrance-free products
    A meaningful label, unlike unscented.
  • A thick, plain moisturizer, applied often
    Barrier repair is half the treatment.
  • The right gloves, worn the right way
    Vinyl or nitrile, cotton liner, off when done.
  • Lukewarm water and a non-foaming wash
    Dry gently, moisturize straight after.
  • Barrier protection for nickel
    Clear polish short term, titanium or steel long term.
  • Cool compresses
    Gently apply a cool, damp cloth to soothe weeping or irritated skin.
  • Patch testing
    The only way to name an allergen.

Avoid

  • Avoid: Carrying on using the product
    Why most rashes last months.
  • Avoid: Frequent handwashing and hand sanitizer
    Water, detergent and alcohol strip broken skin.
  • Avoid: Occlusive gloves worn for hours
    Trapped sweat swells skin.
  • Avoid: Hot water and scrubbing
    Both strip barrier fats.
  • Avoid: Scratching
    Lets more trigger in and thickens the skin.
  • Avoid: Adding more products to soothe it
    Fragrance and botanicals cause a second reaction.
  • Avoid: Numbing and anti-itch creams
    Names ending in -caine often cause allergy.
  • Avoid: Wet wipes and moist toilet tissue
    The preservatives are known allergens.
  • Avoid: Sweat under metal
    Nickel releases faster in sweat - buckles and jewelry flare.
  • Avoid: Sunlight, for some substances
    Some ingredients only react after sunlight changes them.
  • Avoid: An allergen hiding in another product
    Nail polish on eyelids, hair dye on the neck.
  • Avoid: Stopping treatment when it looks better
    Allergic reactions take two to four weeks.
  • Avoid: Anti-itch creams ending in -caine
    Numbing ingredients such as benzocaine are another frequent cause of allergic contact dermatitis. The relief is brief, and a rash that gets worse the more cream you use is a classic story. If an anti-itch product seems to be making things worse, stop it and mention it to your doctor.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Scalp Psoriasis
● Contact Dermatitis
Over-the-counter
Ketoconazole — Header Image

Ketoconazole

Limited evidence

An antifungal shampoo that does nothing to psoriasis itself but clears the seborrheic flaking sitting on top of it, which many people with scalp psoriasis also have. It is worth adding when the flakes are greasy and yellow as well as dry and silvery. If your scale is purely psoriasis, it will not help.

Five medicated scalp products on white, including Amazon Basics tar gel, T+Plus, MG217, RoyceDerm and Nizoral

Coal Tar

Moderate evidence

The most useful thing on the shelf for scalp psoriasis. It slows the overactive cell turnover and takes down scale and itch, which no other over-the-counter option does. Apply it to the parted scalp rather than the hair, leave it five to ten minutes, and expect a smell and possible staining of light hair and towels.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Moderate evidence

A descaler, not a treatment. It dissolves the bonds holding the plate of scale together so that medicine can reach the skin underneath, which is the step most people skip. Use it before the active treatment, not instead of it, and go easy on large areas because it can make hair brittle.

Five coconut oil bottles and a jar on white, most labeled fractionated or organic virgin coconut oil

Coconut Oil

Limited evidence

Warm oil left on the scalp for an hour, or overnight under a cap, softens thick scale so it lifts in the wash instead of tearing. That is a real and useful job. It does nothing about the immune inflammation underneath, so on its own it manages the flakes and leaves the disease running.

Four dandruff shampoo bottles: DHS Zinc, Head and Shoulders Classic Clean, CeraVe Anti-Dandruff and Head and Shoulders Bare

Pyrithione Zinc

Limited evidence

The active ingredient in most ordinary anti-dandruff shampoos. It is gentler than coal tar and can settle light flaking, but it was designed for the yeast behind dandruff rather than for psoriasis. If patches are thick or sharply bordered, this is not the one to keep trying.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh.

Hydrocortisone 1%

Limited evidence

The mildest topical steroid, and enough for a small patch on the body once the contact has stopped. Use it twice a day for one to two weeks rather than dabbing it on now and then. It is often too weak for the hands or feet, and on the face or eyelids it should be short-term and worth asking about first.

Illustration: Generic oral tablet bottle and tablets.

Antihistamine tablets

Limited evidence

Contact dermatitis is not driven by histamine, so antihistamines do very little for the rash itself. A sedating one at night can help you sleep through the itching instead of scratching, which is worth something. The non-drowsy daytime ones sold for hay fever will not make much difference here.

Illustration: Generic ointment jar and translucent ointment.

OTC antibiotic ointments

Limited evidence

Worth naming because they are so often reached for. Neomycin and bacitracin are among the most common contact allergens there are, so an ointment used on an itchy rash can become the reason the rash will not go. Unless the skin is genuinely infected, plain petroleum jelly does the same job with none of the risk.

Four ointments on white: CeraVe Healing Ointment, a Vaseline jar, a petroleum jelly tube and Aquaphor

Petrolatum

Moderate evidence

Plain petroleum jelly, or any thick fragrance-free ointment, rebuilds the barrier that irritation broke. Barrier repair is genuinely half the treatment in irritant hand dermatitis, and it works because it has no fragrance, preservative or botanical in it to start a second reaction. Apply after every hand wash, not once a day.

Five colloidal oatmeal eczema products lined up on white: tubes, a jar and a pump lotion

Colloidal Oatmeal

Limited evidence

An oatmeal bath can take the edge off the itch of a widespread reaction, in cool rather than hot water. It is comfort only. Pick a plain one, because an itch product with fragrance or botanicals in it is a common way people acquire a second allergy on top of the first.

Prescription topicals
Clobetasol — Header Image

Clobetasol

Strong evidence

Clobetasol Propionate. The workhorse for an active scalp flare, as a foam, solution or shampoo made to spread through hair onto skin. It usually calms itch within days and clears patches over two to four weeks. It is used in short courses, because strong steroids used continuously thin the skin — so it breaks the flare and something gentler holds it.

Cream — stock illustration

Calcipotriene with a steroid

Strong evidence

A combined foam containing a vitamin D treatment and a steroid, applied once a day. It is the most effective single scalp product most people will be given, because it works on the immune signal and the fast cell turnover at once. It is expensive and often needs the pharmacy chased, which is worth knowing before you start.

Calcipotriene — Header Image

Calcipotriene

Strong evidence

A vitamin D treatment that slows the skin cells down. It is slower than a steroid, taking six to eight weeks, but it can be used for far longer without thinning the skin, so it is often what keeps a scalp clear after a steroid has broken the flare. It can sting on cracked skin.

Representative medication packaging labelled Zoryve, lying sideways on a white background.

Zoryve

Strong evidence

A newer non-steroid foam approved for scalp and body plaque psoriasis, used once a day. It suits people who do not want to keep returning to strong steroids, or who have been on them a long time. It is costly, and coverage is often the deciding factor rather than the medicine.

Mometasone — Header Image

Mometasone

Strong evidence

A mid-strength steroid lotion, used where clobetasol is more than the situation needs or for the thinner skin behind the ears and along the hairline. It is also a common step-down after a flare has settled. Like all steroids it is for courses, not for indefinite daily use.

Clobetasol — Header Image

Clobetasol

Moderate evidence

Clobetasol Propionate. A potent steroid ointment for hands and feet, where the skin is thick enough that milder creams barely register. It is used in short bursts of two to three weeks with breaks in between, not continuously. Nothing above the neck, and remember that hand dermatitis takes six weeks or more to settle even when the steroid is doing its job.

Representative medication packaging labelled Triamcinolone, lying sideways on a white background.

Triamcinolone Acetonide

Moderate evidence

A mid-strength steroid cream or ointment, the usual prescription for contact dermatitis on the body, arms or legs. Two weeks of it will clear most reactions once the contact has stopped. It is too strong for the eyelids and the folds, and it is a treatment for the inflammation, not for the cause.

Protopic — Header Image

Protopic

Moderate evidence

A non-steroid ointment for the eyelids, face and skin folds, where repeated steroid use thins the skin. It calms the same immune reaction without that risk, which makes it useful for eyelid dermatitis that keeps returning while the trigger is being tracked down. It stings for the first few days, and that usually passes.

16:9 hero for Desonide. Never cropped: the tone strip and the corner logo depend on the full frame.

Desonide

Limited evidence

A mild steroid stronger than over-the-counter hydrocortisone but gentle enough for the face and eyelids in short courses. It is the usual first prescription when a reaction has landed above the neck. Use it for the days it is prescribed for, not as something kept in the drawer.

16:9 hero for Elidel. Never cropped: the tone strip and the corner logo depend on the full frame.

Elidel

Limited evidence

A gentler alternative to tacrolimus for the face and eyelids, and easier to tolerate for people who cannot get past the initial burning. It is not strong enough for hand dermatitis. Like tacrolimus, it buys comfort while the actual trigger is being identified.

Prescription pills
An amber pill bottle labeled Otezla tipped over with white tablets spilling out

Otezla

Strong evidence

A tablet with trial evidence specifically in scalp psoriasis, which is unusual — most tablets are tested on the body and assumed to help the scalp. It needs no blood monitoring, which suits people who would rather not have regular tests. Nausea, loose stools and headache are common in the first fortnight and usually settle.

Existing illustration of a plain white bottle labeled Tablets beside white tablets; no medicine name or strength is shown.

Sotyktu

Strong evidence

A daily tablet that blocks one of the immune signals driving psoriasis, with scalp improvement recorded in its trials. It is generally better tolerated than methotrexate and needs less monitoring. It is newer and expensive, so it usually comes after other options have been tried.

16:9 hero for Methotrexate. Never cropped: the tone strip and the corner logo depend on the full frame.

Methotrexate

Moderate evidence

A long-established weekly tablet for psoriasis that is widespread, or scalp disease that has not budged on foams and solutions. It also treats psoriatic arthritis, which makes it a sensible choice when the joints are involved too. It needs regular blood tests, and it must not be taken in pregnancy.

An amber pill bottle labeled Cyclosporine tipped over with white tablets spilling out

Cyclosporine

Moderate evidence

Works faster than anything else in tablet form and is used to rescue a severe flare. It is a short-term measure only — usually a few months — because it raises blood pressure and can affect the kidneys over time. Something steadier is normally started underneath it.

An illustrative bottle labeled Acitretin beside plain capsules.

Acitretin

Moderate evidence

A vitamin A tablet used mainly for thick, scaly psoriasis, sometimes alongside light treatment. It works slowly and causes dry lips, dry eyes and hair thinning, which makes it an awkward fit when the complaint is the scalp. It must never be taken in pregnancy, and it stays in the body for a long time afterwards.

Prednisone — Header Image

Prednisone

Listed

Steroid tablets clear psoriasis quickly and then it commonly comes back worse as the course finishes, occasionally in a severe form. For that reason they are avoided in psoriasis. If you are already on a course for something else, do not stop it yourself — ask the doctor who prescribed it.

16:9 hero for Methotrexate. Never cropped: the tone strip and the corner logo depend on the full frame.

Methotrexate

Limited evidence

A weekly tablet sometimes used for chronic hand dermatitis when avoidance and creams have genuinely failed. The evidence in contact dermatitis specifically is thin, mostly borrowed from eczema. It needs regular blood tests, and it is a specialist decision rather than a next step.

An amber pill bottle labeled Cyclosporine tipped over with white tablets spilling out

Cyclosporine

Limited evidence

A short specialist course for severe hand dermatitis that has not responded to strong steroids and proper avoidance. It works quickly and reliably, which is exactly why it is used for a few months rather than long term — blood pressure and kidney function have to be watched throughout. It is a bridge, not an answer.

Prednisone — Header Image

Prednisone

Moderate evidence

Steroid tablets for a widespread, blistering reaction, most often poison ivy covering large areas or a rash on the face that is closing an eye. The course has to run two to three weeks with a taper; the short packs are the usual reason the rash rebounds a few days after finishing. It is for the big reactions only, not for a patch on one arm.

Antibiotic tablets for infection

Antibiotic tablets for infection

Listed

Used only when bacteria have moved into the broken skin — spreading warmth and pain, pus, or fever. They treat the infection sitting on top and do nothing to the dermatitis underneath, so the steroid and the avoidance carry on alongside them.

Injections
Skyrizi shown in recognizable white injection pen with blue and turquoise accents.

Skyrizi

Strong evidence

A biologic injection that blocks interleukin 23, one of the two signals named at the top of this page. Given every twelve weeks after the starting doses, it clears most people's psoriasis including the scalp. It is for severe or stubborn disease, needs screening for tuberculosis first, and slightly raises the risk of infections.

A silver and dark pink autoinjector pen labeled Humira lying on a white background

Humira

Strong evidence

An older biologic, injected at home every other week, and often the first one insurance will cover. It treats psoriatic arthritis as well as the skin, which makes it a good fit when joints are involved. It needs tuberculosis screening and periodic blood tests, and some people gradually stop responding to it.

Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Limited evidence

Steroid injected directly into one or two thick patches that have refused everything applied on top. It flattens them within a few weeks. It is done in clinic, it stings, and it is not a plan for a whole scalp — repeated injections in the same spot can leave a dent in the skin.

A white and green autoinjector pen labeled Dupixent lying on a plain pale background

Dupixent

Limited evidence

An injected biologic increasingly asked about for chronic hand dermatitis. Reports are encouraging for the eczema-like cases, but it is not approved for allergic contact dermatitis and some allergens appear not to respond to it. It does not replace finding and removing the trigger, and it is a specialist conversation.

Procedures
Editorial illustration for Excimer Laser, based on the entry’s treatment or equipment reference.

Excimer Laser

Moderate evidence

A focused ultraviolet beam aimed at individual patches, useful when only a few areas of scalp or hairline are involved. It treats the patch without exposing the rest of the skin. Hair blocks the beam, so it works best on the hairline and on thinner, shorter hair.

Editorial illustration for Phototherapy, based on the entry’s treatment or equipment reference.

Phototherapy

Limited evidence

Narrowband UVB delivered by a hand-held comb that parts the hair to reach the scalp skin. It suits people who would rather not take tablets, and it fits with the way many people find their psoriasis improves in summer. It means clinic visits two or three times a week for a couple of months, which is the main reason people stop.

None listed

Outlook

Long term

Scalp psoriasis commonly alternates between flares and quieter periods. Treatment can control scale, itch and inflammation, but symptoms may return when treatment stops. Ongoing scalp care and a maintenance plan can help sustain improvement.

Timing is the best clue to which form you have. The rash is temporary; the allergy is not - sensitization is generally lifelong, so avoidance is permanent. Once the substance is named and avoided, most people stay clear.

Complications

Possible complications
  • Psoriatic arthritis
  • Nail Psoriasis
  • Infection in a cracked scalp
More details

Psoriatic arthritis
A joint condition that develops in some people with psoriasis, often years after the skin. Scalp and nail involvement are both linked to a higher chance of it. The signs are joint pain, swelling, morning stiffness lasting more than half an hour, or a whole finger or toe swelling up. Report them early rather than waiting, because treating it early is what protects the joints.

Nail Psoriasis
Psoriasis often turns up in the nails of people who have it on the scalp. The nail develops small pits like pinpricks, yellow-brown patches like a drop of oil under the plate, crumbling, or lifting away from the nail bed. It is worth pointing out at an appointment, because nail changes are also linked to a higher chance of joint disease.

Infection in a cracked scalp
A plaque that has been picked, scratched or split can let bacteria in. The signs are weeping, honey-colored crust, a sore hot area, or swollen glands in the neck. It is uncommon and it treats easily with antibiotics, but it needs to be looked at rather than covered with more steroid. Softening the scale instead of lifting it off is what prevents it.

  • Infection in the broken skin
  • Chronic hand dermatitis
  • Time off work
More details

Infection in the broken skin
Weeping, cracked or scratched skin gives bacteria an opening, most often on the hands. The signs are honey-colored crusts, pus, increasing pain, or redness and warmth spreading outward. It is common and it is treatable, but it needs antibiotics rather than more steroid cream, so it is worth being seen rather than waiting it out.

Chronic hand dermatitis
When the exposure carries on, hand dermatitis stops settling between flares. The skin thickens, the normal lines deepen, and painful cracks open across the fingertips and knuckles that catch on everything and are slow to close. It is the reason contact dermatitis is a leading work-related skin problem, and it is largely preventable by naming the cause early instead of treating the rash for months.

Time off work
Hand dermatitis is one of the leading work-related health problems, and for people in wet or chemical work it can mean weeks of light duties, a change of role, or leaving a trade. It is also the part most often left out of the conversation. Naming the cause early, and getting the right gloves and routine in place, is what keeps the job.

When to get help

When to get help

Seek help for persistent thick scale, bleeding, sleep-disrupting itch or hair loss. Joint symptoms should also be assessed.

Seek help for persistent or recurrent rash; patch testing may identify contact allergy. Pain, spreading warmth, pus or fever require prompt assessment.

Common questions

Scalp Psoriasis:Will my hair grow back?

In almost all cases, yes. Hair thins over an active patch because thick scale lifts hairs out as it sheds and scratching breaks them. Once the inflammation and scale are treated, the follicles are intact and hair regrows over the following months. Scarring hair loss is rare, and more likely in a long-picked patch.

Scalp Psoriasis:How do I tell scalp psoriasis from dandruff?

Look at the edges and the color. Psoriasis makes a patch you can feel the border of, with dry silvery-white scale, and it commonly runs past the hairline onto the forehead or behind the ears. Dandruff makes softer, greasier, yellower flakes that fade into normal skin. If both are present, which is common, treatment needs to cover both.

Scalp Psoriasis:Can I dye or relax my hair?

When the scalp is calm, usually yes. When it is flaring, cracked or sore, chemical processing can burn inflamed skin, and burned skin is exactly where new psoriasis appears. Wait until it settles, tell your stylist what is going on, and ask for a patch test.

Scalp Psoriasis:Do I have to use the shampoo forever?

Not at flare-level intensity, but most people do better on maintenance. A shampoo once or twice a week keeps a scalp clear far more comfortably than clearing a thick flare every few months. It is ongoing management, not a course you finish.

Scalp Psoriasis:Why does it come back as soon as I stop?

Treatment controls the immune signal driving the disease, it does not switch it off. Stop the treatment and the signal is still there. That is expected, not failure, and it is why dermatologists step treatment down rather than stopping it.

Scalp Psoriasis:Does having it on my scalp mean I will get it elsewhere?

It raises the chance without guaranteeing it - plenty of people have scalp psoriasis and nothing else for decades. Scalp and nail involvement are both linked to a higher chance of psoriatic arthritis, so joint pain, swelling or morning stiffness lasting more than half an hour should be mentioned to a doctor.

Contact Dermatitis:How do I figure out what caused it?

Start with location and shape, not a list of products. Photograph the rash, note where its edges are, and look for an object or habit that matches that outline. An allergic reaction shows up one to three days after contact, so look at what happened two days before, not that morning. Include things you have used for years - those are the likeliest candidates, not the least. If a few weeks of attention does not settle it, patch testing ends the guessing.

Contact Dermatitis:How long does it take to clear up?

An irritant reaction improves within days of contact stopping. An allergic reaction takes two to four weeks to settle even with treatment, because the immune cells doing the damage take that long to stand down. Hands are slowest, often six weeks or more, because the skin there is used and washed constantly. Judging it at day three tells you very little.

Contact Dermatitis:Is it contagious?

No. This is your own skin reacting to a substance, not an infection. You cannot pass it on by touch. If two people in a household get the same rash, they were both exposed to the same thing.

Contact Dermatitis:Will the allergy ever go away?

Generally no. Once your immune system has learned a substance, that memory is permanent, and tiny amounts can trigger a reaction years later. In practice it is less grim than it sounds - people who know their allergen and avoid it stay clear indefinitely, and the avoidance is usually narrower than they feared.

Contact Dermatitis:Why did this appear on my eyelids when I never put anything there?

Eyelid skin is the thinnest on your body, so it reacts to amounts the rest of your skin ignores. Nail polish, hair products, face creams and airborne particles reach the eyelids from your hands or from your scalp. When a rash is on the eyelids alone, the cause is usually somewhere else.

Contact Dermatitis:Can I just use hydrocortisone from the pharmacy?

For a small, mild patch on the body, often yes, alongside stopping the contact. Over-the-counter hydrocortisone is a mild strength and rarely clears thicker skin on hands or feet. On the face and eyelids keep it short-term, and ask first. It treats the inflammation, not the cause - if the rash returns each time you stop, find the trigger.
Sources

Sources and further reading

  1. DermNet
  2. DermNet
Dermapedia on YouTube