Cyclosporine
A strong oral immune-suppressing drug used in short bursts for severe eczema and psoriasis. It works faster than anything else, and blood pressure and kidney function set a hard limit on how long anyone stays on it.

Key facts
Cyclosporine at a glance.
Used for
Severe eczema or psoriasis flares
Results
2–6 weeks
Treatment commitment
Time-limited course with monitoring
Key precautions
Kidney and blood pressure checks
What is it?
Top things to know about Cyclosporine
- It suppresses the immune system. Cyclosporine blocks calcineurin-related T-cell signaling.
- It is used for severe disease. Dermatologists use it when fast systemic control is needed.
- It is labeled for severe psoriasis. Other skin uses may be off-label.
- It needs an exit plan. Treatment should have a set duration and specialist monitoring.




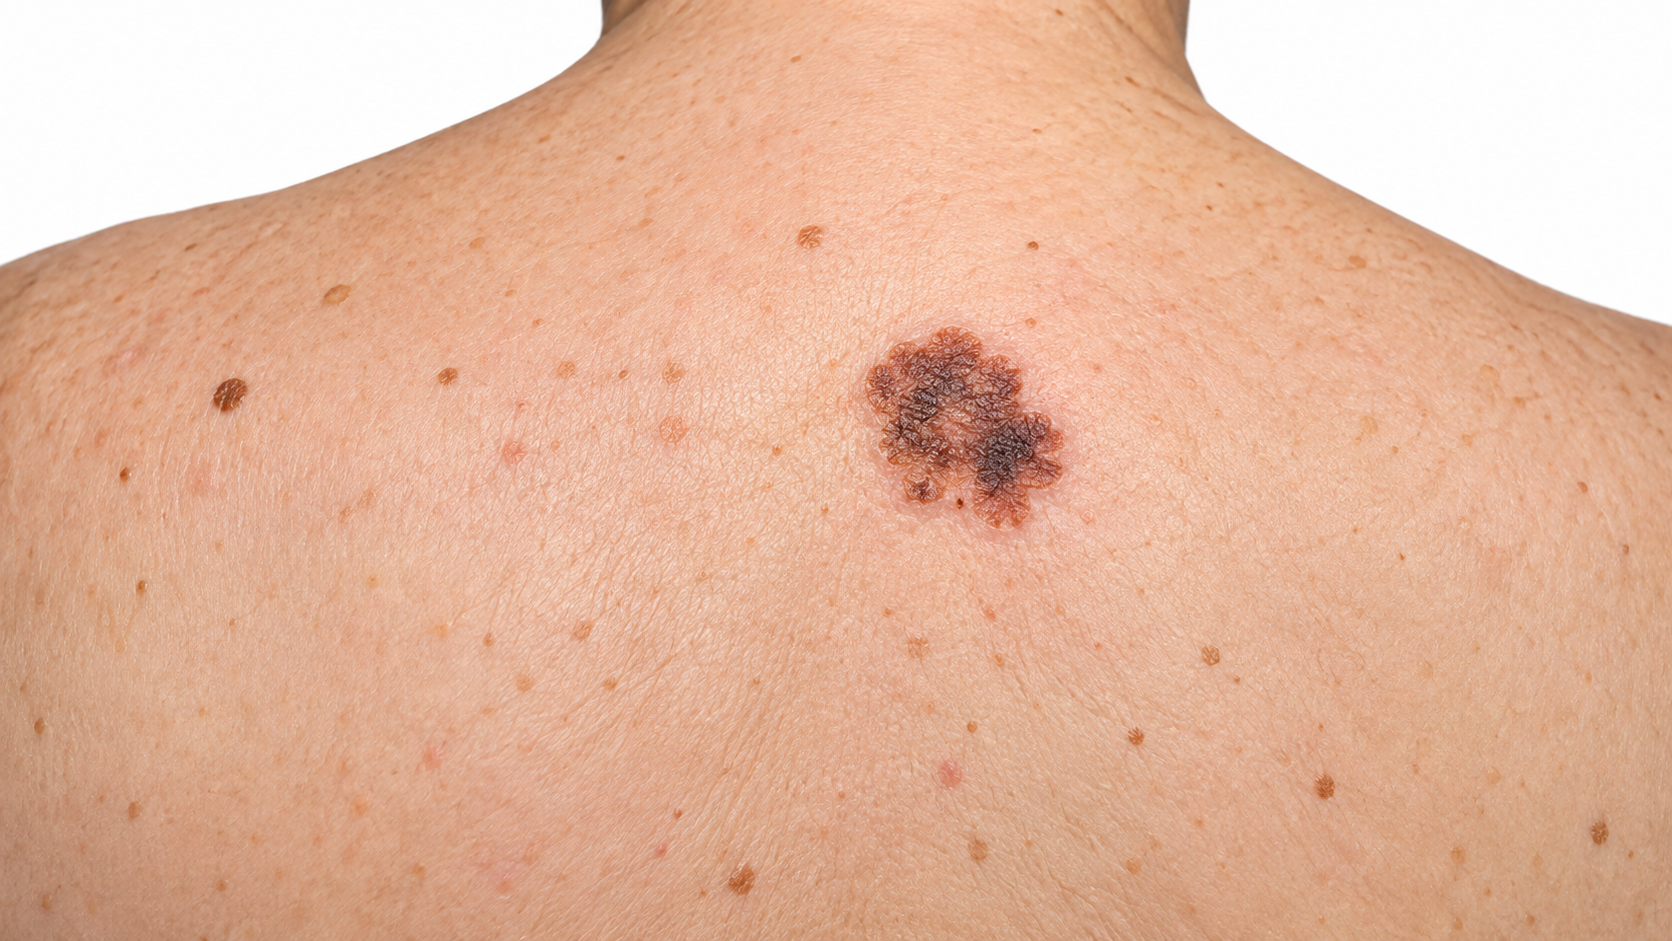
HOW IT WORKS
How Cyclosporine works

Diagram explanation and sources
Inhibits calcineurin: Binds cyclophilin to block a T-cell activation switch. Reduces IL-2 signals: Limits a messenger that helps T cells become active. Calms skin inflammation: Overactive immune responses in skin decrease.
Cyclosporine binds cyclophilin; that complex inhibits calcineurin and T-cell cytokine production. This is a simplified skin-focused explanation of systemic immunosuppression.
Types
Types of Cyclosporine
Modified cyclosporine
Products such as Neoral and Gengraf use a modified formulation with different absorption from nonmodified cyclosporine.
Nonmodified cyclosporine
Sandimmune is the reference example. Modified and nonmodified products are not bioequivalent. Do not switch between them milligram for milligram without the prescriber’s instructions and monitoring.
Brands
Brands of Cyclosporine
Brand names and available preparations vary by country. The examples below identify specific labeled products.
Neoral
Modified cyclosporine. It is not bioequivalent to nonmodified Sandimmune.
Gengraf
Modified cyclosporine. Check the exact prescribed formulation when comparing it with other cyclosporine products.
Sandimmune
Nonmodified cyclosporine. Switching between it and modified cyclosporine requires prescriber supervision.
Strengths
Cyclosporine strengths
Cyclosporine dosing is weight-based; capsule strength is not the whole daily dose. Modified and nonmodified formulations are not automatically bioequivalent or interchangeable. The cited modified product also has a 100 mg/mL oral solution, which must be measured accurately rather than compared with a capsule by volume.
25 mg
50 mg
100 mg
A smaller capsule strength that may be combined to make the prescribed divided daily dose.
The number of capsules depends on body weight, diagnosis, kidney function, blood pressure and monitoring.
A higher capsule strength, not a default psoriasis starting dose. Follow the exact formulation on the prescription.
Forms
Cyclosporine forms
Capsule
Medicine enclosed in a hard or soft shell. Swallowing comfort and release properties vary by formulation.

Oral solution
A liquid with medicine dissolved in it. Taste, thickness and the measuring device affect ease of use.
How to use it
Your treatment, step by step.
How to take it
- 01
When to take it
Twice a day, about 12 hours apart, at the same times daily. Be consistent about food: always with meals or always without, because switching changes absorption. Swallow capsules whole and leave them in the foil until you take them.
On the liquid, mix it with orange or apple juice in a glass cup, stir and drink it straight away, then rinse the cup with more juice and drink that too. Never use grapefruit juice. - 02
If you miss a dose
Take it when you remember unless the next dose is close, then skip it. Never take two at once. Tell the prescriber if you miss more than a dose or two, or vomit soon after taking it, because the dose is built around your blood level.
Monitoring & follow-up
Cyclosporine is monitored more closely than any other skin drug, and that monitoring is why it can be used at all. Blood pressure is measured at every visit, often at home. Kidney function is checked by blood test, twice before starting for a reliable baseline, then every couple of weeks for a month or two, then monthly once the dose is steady. The same draws cover potassium, magnesium, uric acid, liver enzymes, blood counts and cholesterol. Drug blood levels are routine in transplant care, not usually needed at dermatology doses.
Two numbers drive the decisions. A rise in creatinine of about a quarter above your baseline, confirmed on a repeat test, means dropping the dose; about half means stopping. New high blood pressure means lowering the dose or adding a blood pressure medicine, and the choice matters: diltiazem and verapamil push levels up, amlodipine does not.
The interaction list is long. Drugs that raise levels include the azole antifungals, clarithromycin and erythromycin, and some HIV and hepatitis C medicines. Drugs that lower it include rifampin, phenytoin, carbamazepine and St John's wort. It also raises statin levels, so that dose is often reduced, and it interacts with colchicine, digoxin, methotrexate and potassium-sparing water tablets. Bring every prescription, supplement and herbal product to the first visit.
The time limit is the point of all this. Kidney damage builds with continuous use and part of it can be permanent, so guidelines cap continuous treatment at about a year and most dermatology courses are far shorter. Long or repeated use also raises the risk of skin cancer, lymphoma and serious infection, so skin checks continue afterward.
What to expect
How things change over time.
Starting
Itch settles first, often within days, and sleep improves. Tingling or burning in the hands and feet, headache and mild nausea are common early. Blood pressure and kidney tests get checked.
Working
Redness, weeping and thickness improve clearly. Chronic hives that antihistamines do not control usually settle within a month. Extra hair growth on the face, arms and body and swollen or tender gums start now; both are dose-related and reverse after stopping.
Plaque psoriasis
Large improvement, often near-clear at the higher end of the dose range. Usually where the course ends and another treatment takes over.
Severe inflammatory ulcers
In pyoderma gangrenosum it stops the ulcer spreading while healing catches up. Response times differ a lot.
The tests
Blood pressure creeping up and kidney numbers drifting decide whether the dose drops or the drug stops. Neither causes symptoms, which is why the tests are not optional.
- First 2 weeks
- Weeks 2 to 6
- Weeks 8 to 16
- Variable
- Throughout
When you stop
There is no withdrawal syndrome, but the dose steps down over a few weeks rather than stopping outright, because stopping abruptly brings the disease back faster.
Relapse is expected. Eczema and psoriasis return within weeks to a few months unless something else is running, so the taper is timed around the next treatment: a biologic, methotrexate, phototherapy or a strong topical routine.
Most side effects reverse. Extra hair growth fades, gum swelling settles, tingling and headaches go quickly, blood pressure returns toward baseline. Kidney function often recovers after a short course, but some loss can persist after long or repeated ones — the main argument for short courses.
What it Pairs with
Cyclosporine + your routine
| Product or situation | With Cyclosporine | What to know |
|---|---|---|
| Grapefruit, grapefruit juice, pomelo and Seville oranges | Avoid | They block the enzyme that clears cyclosporine, so blood levels rise unpredictably. The one food restriction that genuinely matters. |
| St John's wort | Avoid | The opposite: it clears the drug faster, so it can stop working with no warning. |
| Potassium supplements and salt substitutes | Use care | Cyclosporine already raises potassium, and these add to it. |
| Anti-inflammatory painkillers | Avoid | Ibuprofen and naproxen strain the same part of the kidney cyclosporine does. Ask which painkiller to use instead. |
| Sun protection | Mandatory | Skin cancer risk rises on cyclosporine, especially after a lot of PUVA. Sunscreen and covering up matter more than usual. |
| Live vaccines | Avoid | Usually avoided while the immune system is suppressed. Check before any travel vaccine or nasal flu vaccine. |
| Stopping or restarting on your own | Avoid | The monitoring is built around your blood level, so changes belong with the prescriber. |
| If you are pregnant, breastfeeding or planning a pregnancy | Use care | Ask the doctor managing your pregnancy before starting or continuing, and do not stop alone. |
| If you have kidney disease, or blood pressure that is not well controlled | Use care | These are most likely to rule it out or change the dose. |
| If you take a statin for cholesterol | Use care | Cyclosporine raises statin levels and the risk of muscle damage, so the statin dose is usually lowered or changed. |
| If you are prescribed an antibiotic | Use care | An antifungal counts too. Several common ones move levels sharply, even short courses for something unrelated. |
| If you have had skin cancer | Use care | A lot of past PUVA counts too. Immune suppression raises the risk of new skin cancers, and PUVA adds to it. |
| If you have an infection now | Use care | A history of tuberculosis or hepatitis counts too. Sort these out before suppressing the immune system. |
| If you are due any vaccine | Use care | Live vaccines are avoided during treatment, and others may work less well. |
| If you have gout or high uric acid | Use care | Cyclosporine raises uric acid and can bring on an attack. |
| If you take anything off prescription | Use care | Supplements, herbal products and over-the-counter painkillers all count. |
Side effects & when to get help
It works faster than almost anything else, and the trade-off is blood pressure, kidneys and infection risk. That is why courses are kept short and the blood tests are not optional.
Common
Higher blood pressure: Common enough to check at every visit.
Tingling in the hands and feet: Often early on.
Tremor: A fine shake, usually in the hands.
Gum swelling: Brushing and flossing well helps.
More hair on the face and body
Headache and nausea: Easier with food.
Tell your doctor
Blood pressure that keeps climbing
Swelling in the ankles or less urine: Can point to the kidneys.
An infection that lingers
Rising creatinine or potassium: From your routine blood tests.
A new lump or a changing mole: Skin cancer risk rises with long use.
Any new medicine or supplement: Cyclosporine interacts with a long list, grapefruit included.
Stop and get care
Fever with shaking chills or feeling very ill: Infection needs treating fast on this drug.
Severe headache with confusion or a seizure
Barely passing urine
Getting it and cost
Getting Cyclosporine.
Cost & access
Generic capsules are cheap next to biologics, part of why the drug is still used. Branded versions cost more without working better.
What affects the cost
The visible cost is not the whole cost. Repeated blood tests, blood pressure checks and appointments add up, and none are optional. It is cheaper per month than a biologic but taken for only a few months, so the comparison depends on what comes after.
What affects the cost
Insurance generally covers it for severe psoriasis. Eczema coverage varies more in the United States, where that use is off-label.
Alternatives
Other options to consider.

Methotrexate
Much slower, taking two to three months, but it can be continued for years, and it needs liver and blood count monitoring. Not for use in pregnancy.
Biologic injections
For psoriasis or eczema these have strong evidence and are better suited to long-term use, with higher clearance rates than cyclosporine achieves. They are injected, cost far more, and take longer to work, which is why cyclosporine is sometimes used to bridge the gap while a biologic starts.
Dupilumab, for eczema
And no blood test monitoring. Slower to act and given by injection. For most people it is the more sustainable long-term option, with cyclosporine reserved for getting a severe flare under control first.

Oral JAK inhibitors, for eczema
And nearly as fast as cyclosporine. They carry their own boxed warnings and require blood monitoring, and they are far more expensive.

Acitretin
In psoriasis, useful in the pustular form. Slower and drying, but it does not suppress the immune system. It cannot be used by anyone who could become pregnant.

Phototherapy
No internal side effects at all. It needs two or three clinic visits a week for months, which is the reason people give it up.

Oral steroids
Fast, but not a comparable option in psoriasis. Stopping them can trigger a severe flare, and they are avoided for this reason.
Questions
Questions you might be asking.
How quickly will it work?
Faster than anything else for these conditions. Itch improves within days, clearing by four to six weeks.
How long can I stay on it?
Most courses run months. Guidelines cap continuous use at about one year, because kidney effects build and some can be permanent.
Why do I need my blood pressure checked so often?
It raises blood pressure in a meaningful share of people, and that causes no symptoms. Catching it early usually means lowering the dose rather than stopping.
Can I drink grapefruit juice?
No. Grapefruit, pomelo and Seville oranges block the enzyme that clears it, so levels rise unpredictably. Other citrus is fine.
Why is hair growing where it did not before, and why are my gums sore?
Both are dose-related. Not dangerous, usually better if the dose comes down, and gone after stopping.
Will my skin flare again when I stop?
Usually, within weeks to a few months, unless another treatment is running. Planning that before the taper is the point of the short course.
Related



