Excimer Laser
A 308 nm ultraviolet B laser aimed at one patch of skin at a time. Used mainly for stubborn psoriasis plaques and for vitiligo. Because only the affected skin is treated, the rest of the body is spared the light.

Key facts
Treats
Localized psoriasis or vitiligo
Recovery
Usually no downtime
Treatment plan
10–20+ sessions, 2–3 times weekly
Typical cost
Coverage varies by indication
What is it?
It is targeted UVB.
Excimer delivers ultraviolet B at around 308 nm to selected patches.
It treats psoriasis and vitiligo.
It is used for localized disease.
It is not eye surgery.
Dermatologic excimer differs from excimer eye procedures.
It is still phototherapy.
Light sensitivity, medicines and skin cancer history are reviewed.
Treatment areas
Excimer Laser
Selected psoriasis or vitiligo patches; treatment follows the affected skin rather than a fixed body area.
Excimer Laser
Selected psoriasis or vitiligo patches; treatment follows the affected skin rather than a fixed body area.
Skin tones
Lighter skin
Low risk
Possible small sunburn.
Medium skin
Low risk
Surrounding skin may tan.
Deeper skin
Some risk
Darkening around patches can make vitiligo edges stand out at first.
How it works

Diagram explanation
UVB is aimed at a skin patch: A device delivers targeted 308 nm ultraviolet light. Immune activity is reduced: The light changes inflammatory activity in the treated skin. The patch may improve: Repeated treatment can help selected conditions such as psoriasis.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Before your treatment
2–4 weeks before
2 weeks before: Sun and self-tanner: No sunburn and no self-tanner on the area for 2 weeks.
Day of treatment
Before you arrive
Clean skin and scale: Come with the area clean, with no makeup or thick creams.
Arrival & prep
For vitiligo: Photographs: Expect photographs at the start and every couple of months.
The area is looked at and often photographed.
Treatment
You and the operator wear ultraviolet goggles.
The handpiece goes over the patch and light comes in bursts of a few seconds per spot. No smell, no noise beyond the machine, no feeling beyond mild warmth. Doses are written down each visit so the next can be adjusted. If the dose was too high you feel it hours later, like a small sunburn.
Before you leave
Straight back to work.
After your treatment
First 24 hours
Day 1 to 2: Tenderness, deeper redness or mild peeling means the dose ran ahead of what your skin tolerated.
Time to results
1–3 months
How long results last
Months; vitiligo color can be lasting
After several sessions
Treated skin darkens.
After weeks
Psoriasis plaques flatten and shed less.
Risks
When to contact your provider
Report a burn: Tell the office before the next visit if the area blistered or stayed sore more than a day.
Most of what happens is expected and mild
warmth, pink skin, tanning of the treated squares, and dryness. Risk rises when doses are raised quickly, and when something else has made the skin light-sensitive.
A burn
Soreness, deep redness, or blistering a day after a session. The dose needs lowering, not repeating.
A cold sore
Ultraviolet light can set one off on the face. Antiviral treatment works best started early.
Dark patches
New darkening at the edge of the treated area, most often on deeper skin tones. It usually fades. Flag it early rather than at the end of the course.
A new medicine
Any new prescription started mid-course; some make the same dose behave like a much bigger one.
Long term
Ultraviolet exposure carries a theoretical skin cancer risk. Studies of narrowband UVB have not shown a clear increase, and the excimer exposes far less skin than a cabinet. Keep a record of your sessions.
Cost
Typical cost
Per session; often covered
Pricing
Ask the office for a written estimate of the whole course before starting, and ask what happens to the price if a second area is added later.
Insurance
Insurance in the US often covers targeted phototherapy for psoriasis and vitiligo, usually after prior authorization and often only once topical treatment has been tried.
Alternatives

Narrowband UVB cabinet
The same biology delivered to the whole body, which is the better choice once disease is widespread. The trade is that unaffected skin gets the ultraviolet too, doses per session are lower, and courses tend to run longer.

Topical steroids and vitamin D creams
Cheap, done at home, and the first step for limited psoriasis. Slower on thick plaques, and long unbroken use of strong steroids thins skin, which is one reason light is added.

Topical calcineurin and ruxolitinib
Creams for vitiligo. Strong evidence for ruxolitinib cream, moderate for tacrolimus. Used at home, no visits, and combining them with light works better than either alone in studies. Cost and insurance approval are the obstacles.
Biologics and systemic drugs
For psoriasis. Strong evidence. Far better for widespread or joint disease. For two plaques on the elbows, most people would rather not take a systemic drug, which is exactly the gap the excimer fills.

PUVA
Largely superseded. A drug plus ultraviolet A, with more side effects, strict eye protection afterward, and a clearer long-term skin cancer signal than narrowband UVB.
Surgical grafting for stable vitiligo
For patches that will not repigment with light and have been stable for a year or more. A procedure rather than a course, done by a small number of centers.
Home narrowband UVB cabinets and panels
Full-size or half-size units prescribed for home use, with the dosing schedule set by the dermatologist. The main route for people who cannot get to an office two or three times a week. Needs a prescription, insurance work, and discipline about the log.

Handheld narrowband UVB wands
Combs too. Small 311 nm devices for scalp and limited patches. Closest thing at home to what the excimer does in the office, at a lower dose per second, so sessions run longer.

Sunlight
Deliberate sun exposure helps some people with psoriasis and vitiligo, but the dose is uncontrolled, it exposes skin that does not need treating, and burns set both conditions back. Discuss it rather than improvising it.
Questions
How is this different from a narrowband UVB cabinet?
Only in where the light goes; the wavelength and biology are the same. The excimer treats defined patches at a higher dose each and leaves the rest untouched, which suits limited disease. A cabinet treats everything at once, which suits widespread disease.
Does it hurt?
Not much — a few seconds of warmth per spot. If the dose was pushed too far you feel it hours later, like a small sunburn.
How many sessions before I know if it is working?
For psoriasis, roughly 10 to 20. For vitiligo, 20 to 30 before judging at all. Stopping earlier is the most common reason people conclude it did not work for them.
Will the results last?
Nobody can promise that. Psoriasis plaques usually return after treatment stops. Vitiligo repigmentation often holds, especially on the face and when the disease is quiet, and is more likely to be lost while it is still active.
Is it safe on deeper skin tones?
It is used at every skin tone. The starting dose is higher, treated skin tends to tan, and the outcome to avoid is a burn, since dark marks from a burn last longer at deeper skin tones.
Does it cause skin cancer?
Ultraviolet exposure carries a theoretical long-term risk. Studies of narrowband UVB have not shown a clear increase, and the excimer exposes a fraction of the skin a cabinet does. Keep a record of your sessions and mention it at skin checks.
Related

Eczema

Psoriasis
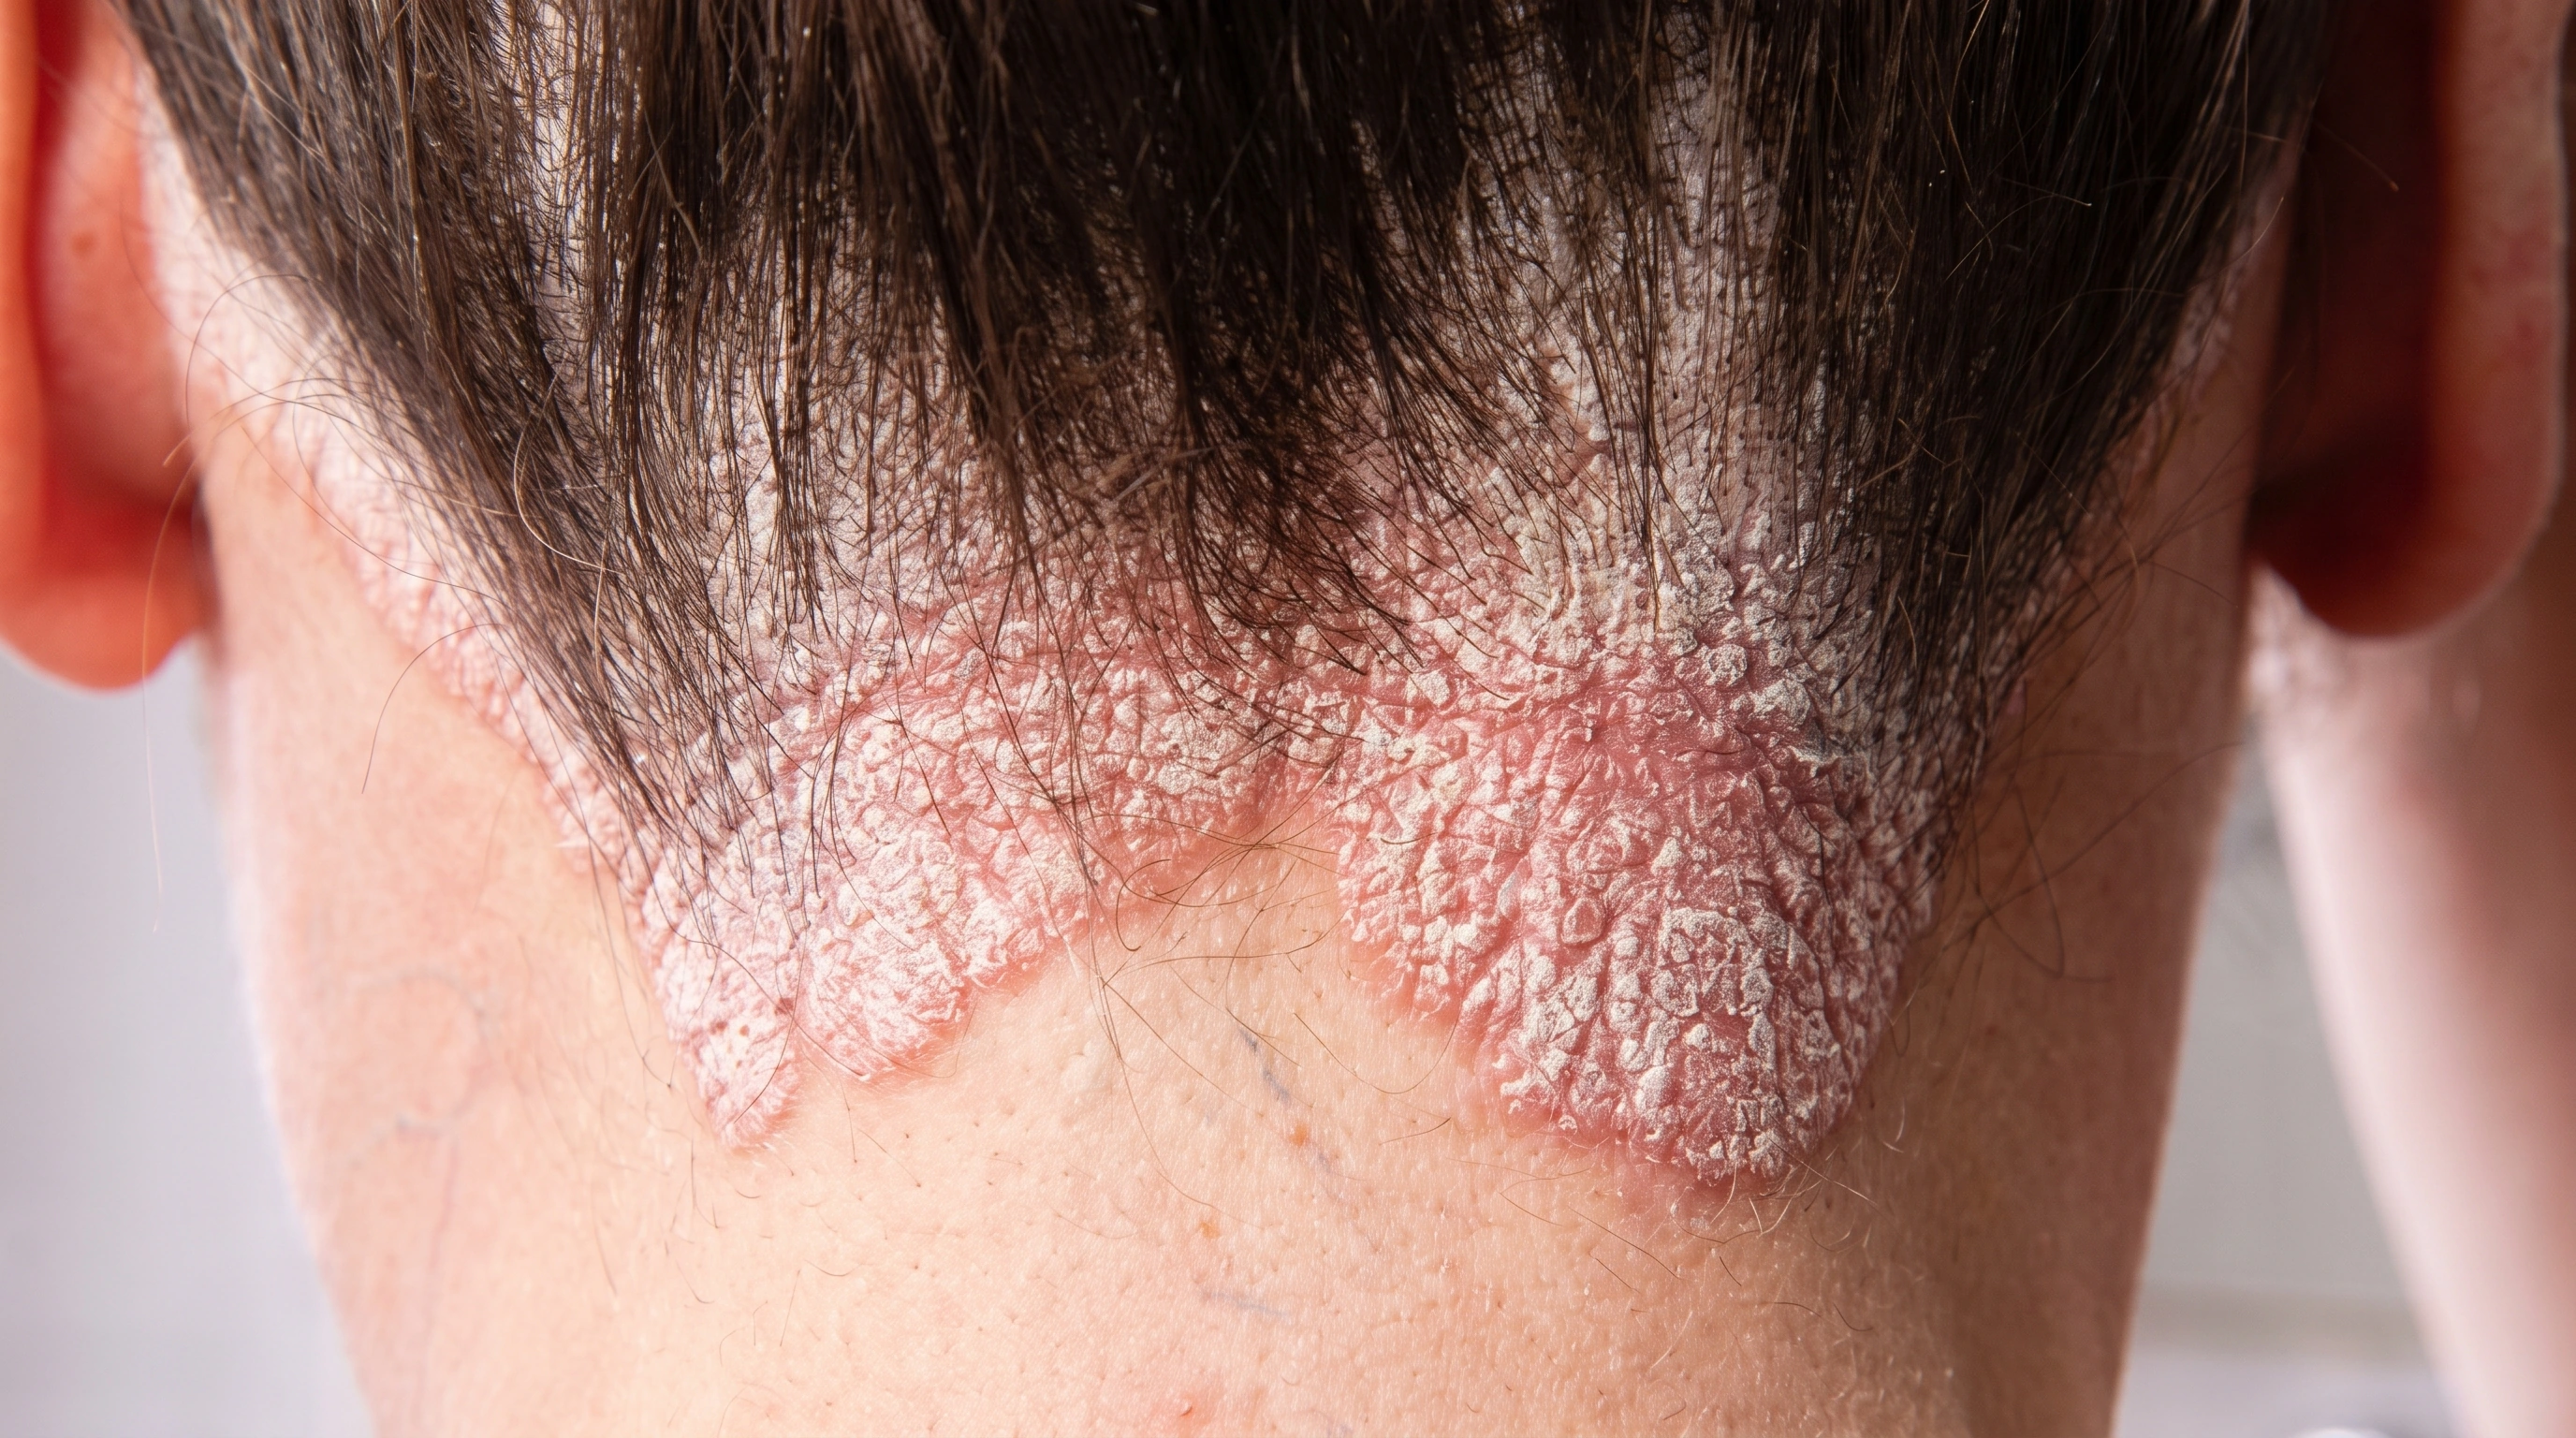
Scalp Psoriasis
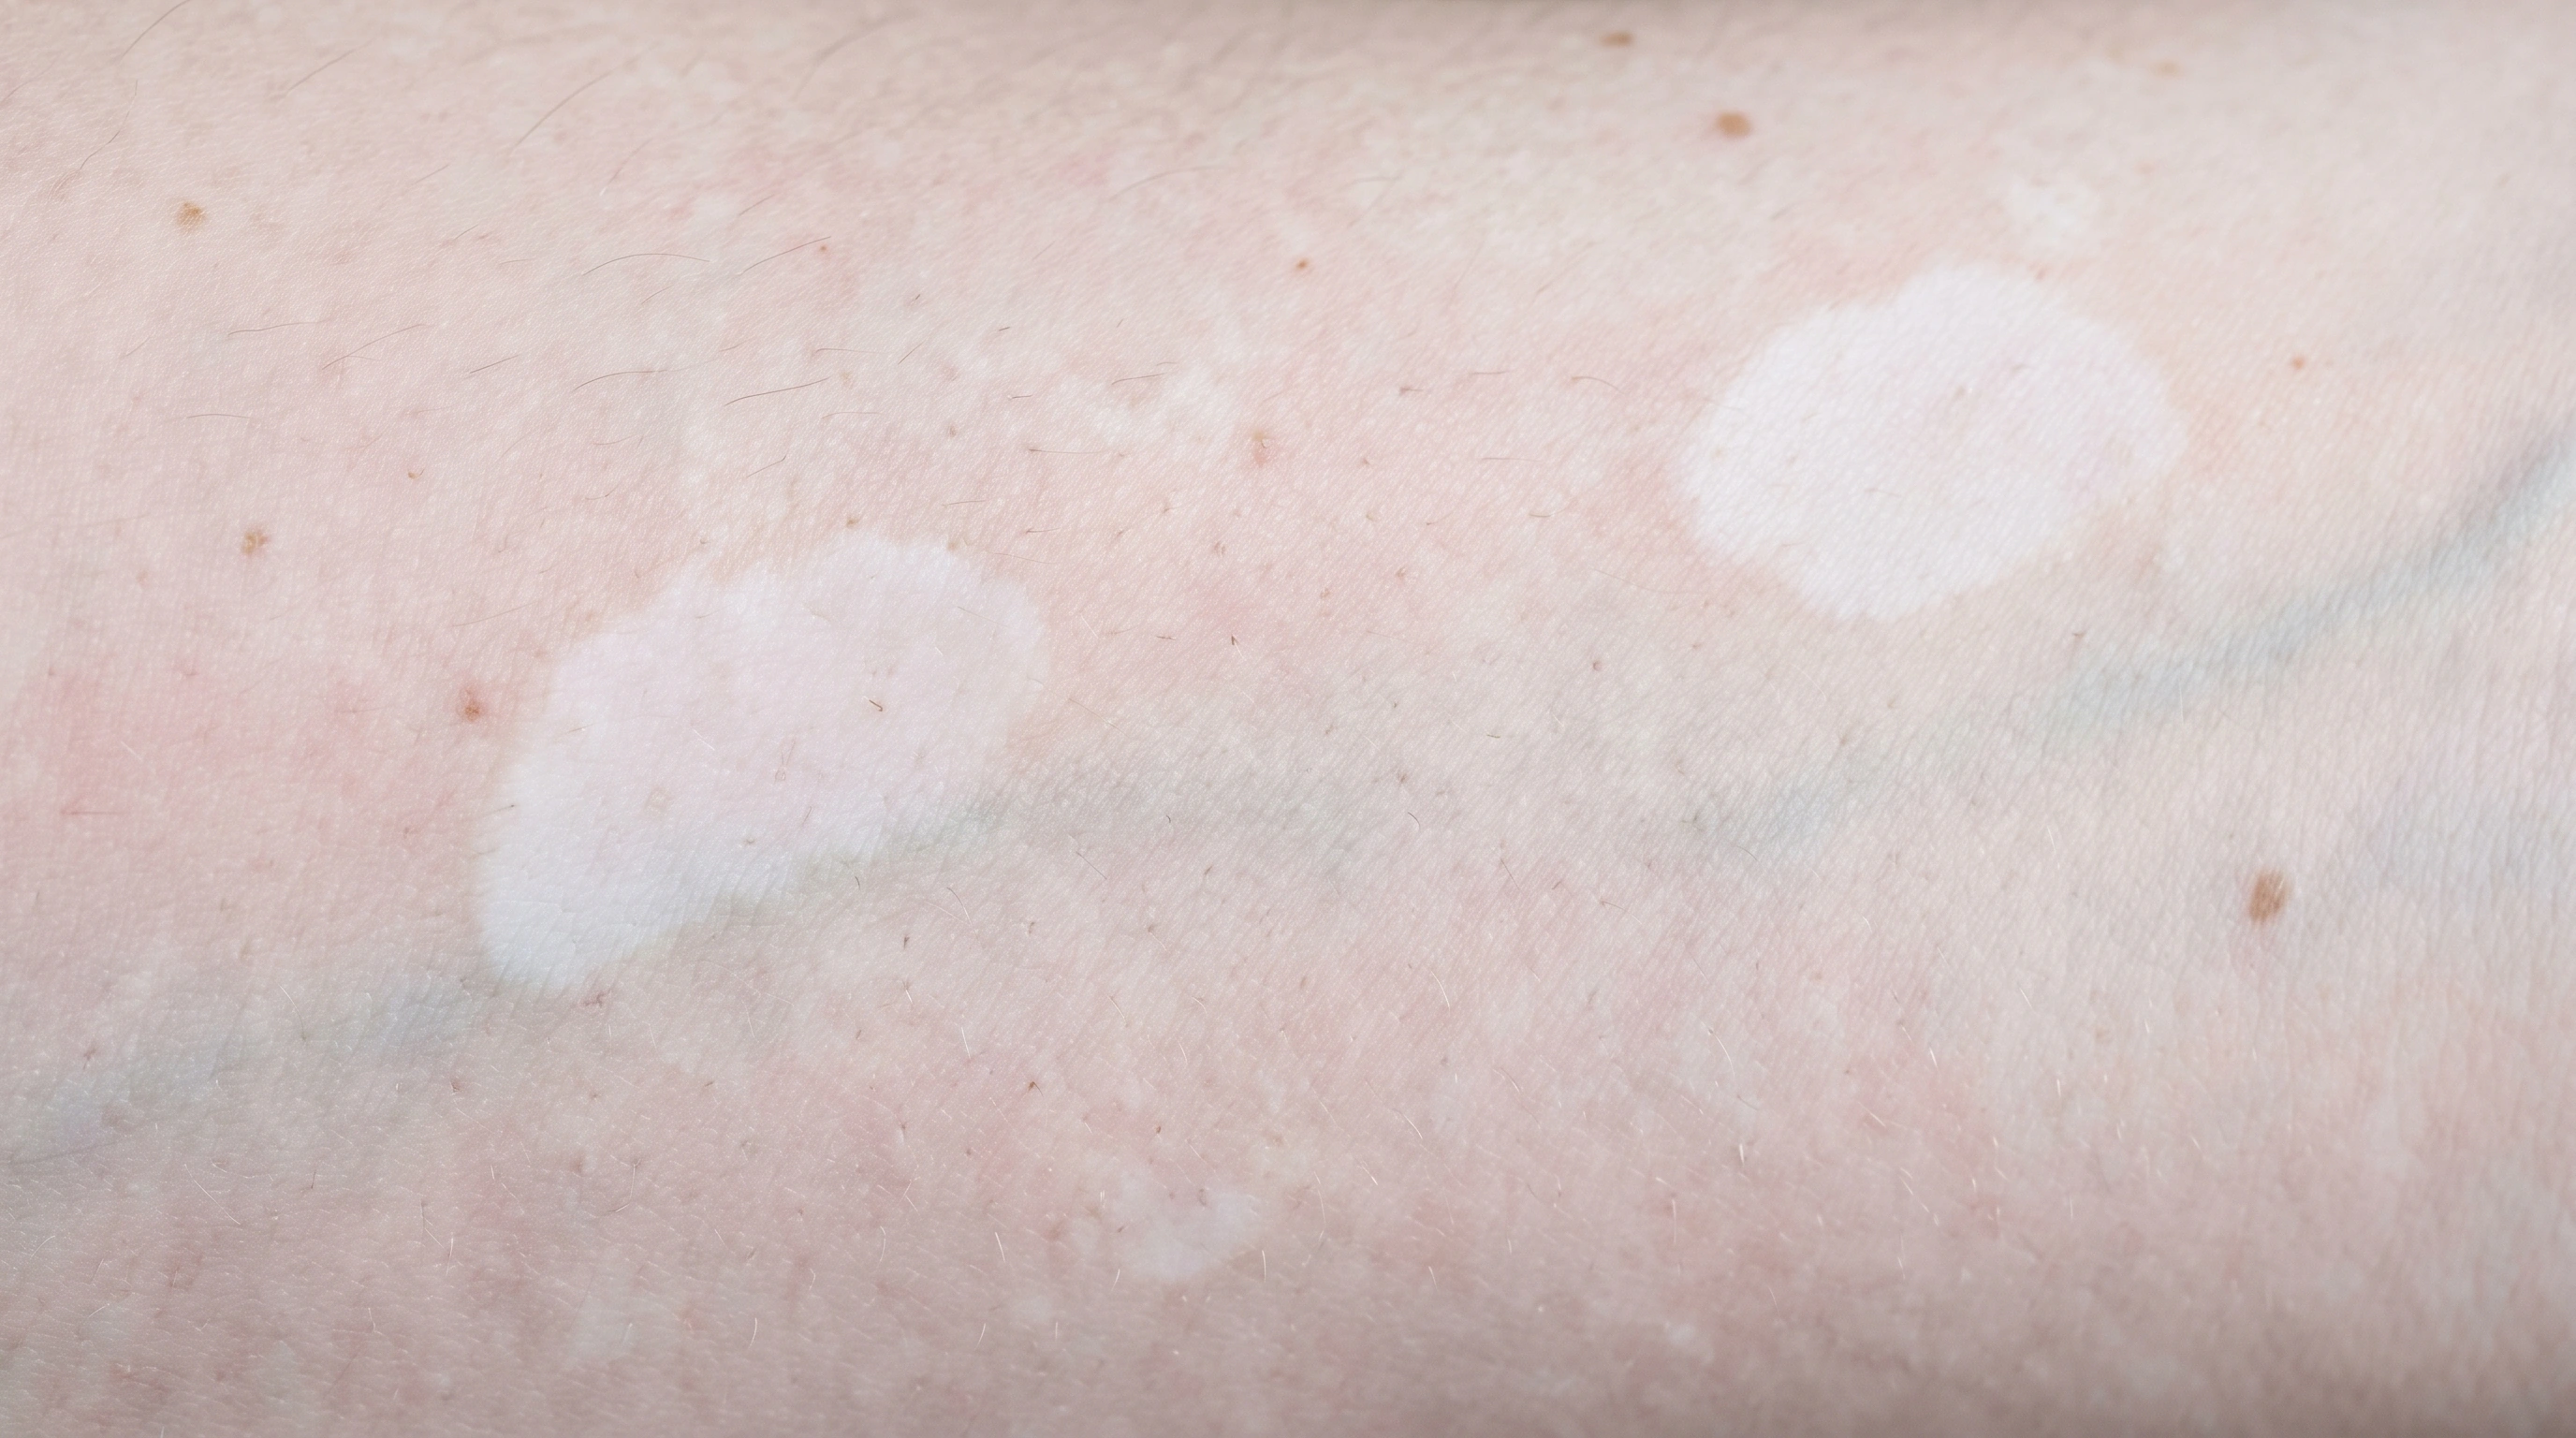
Vitiligo
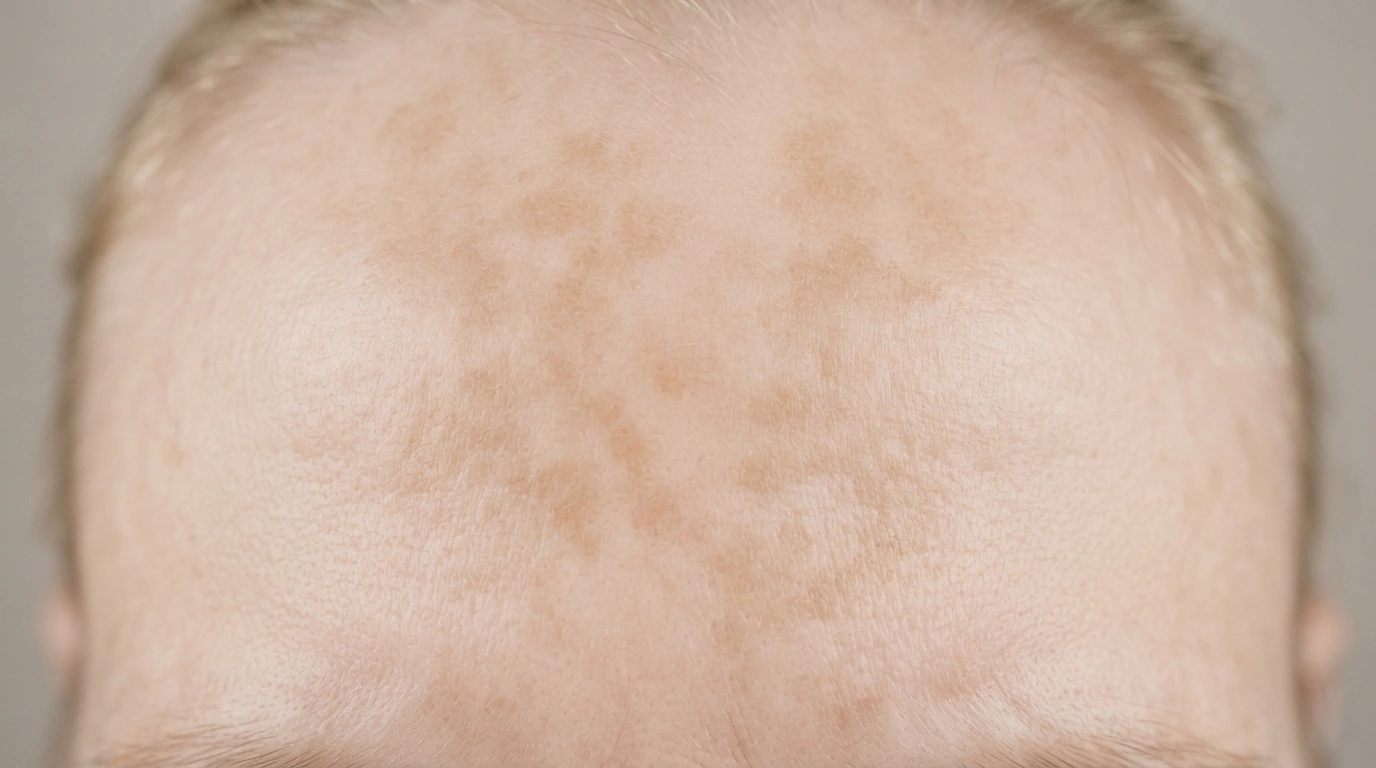
Melasma

Excimer Laser vs Phototherapy

Excimer Laser vs Punch Biopsy
Psoriasis vs Eczema
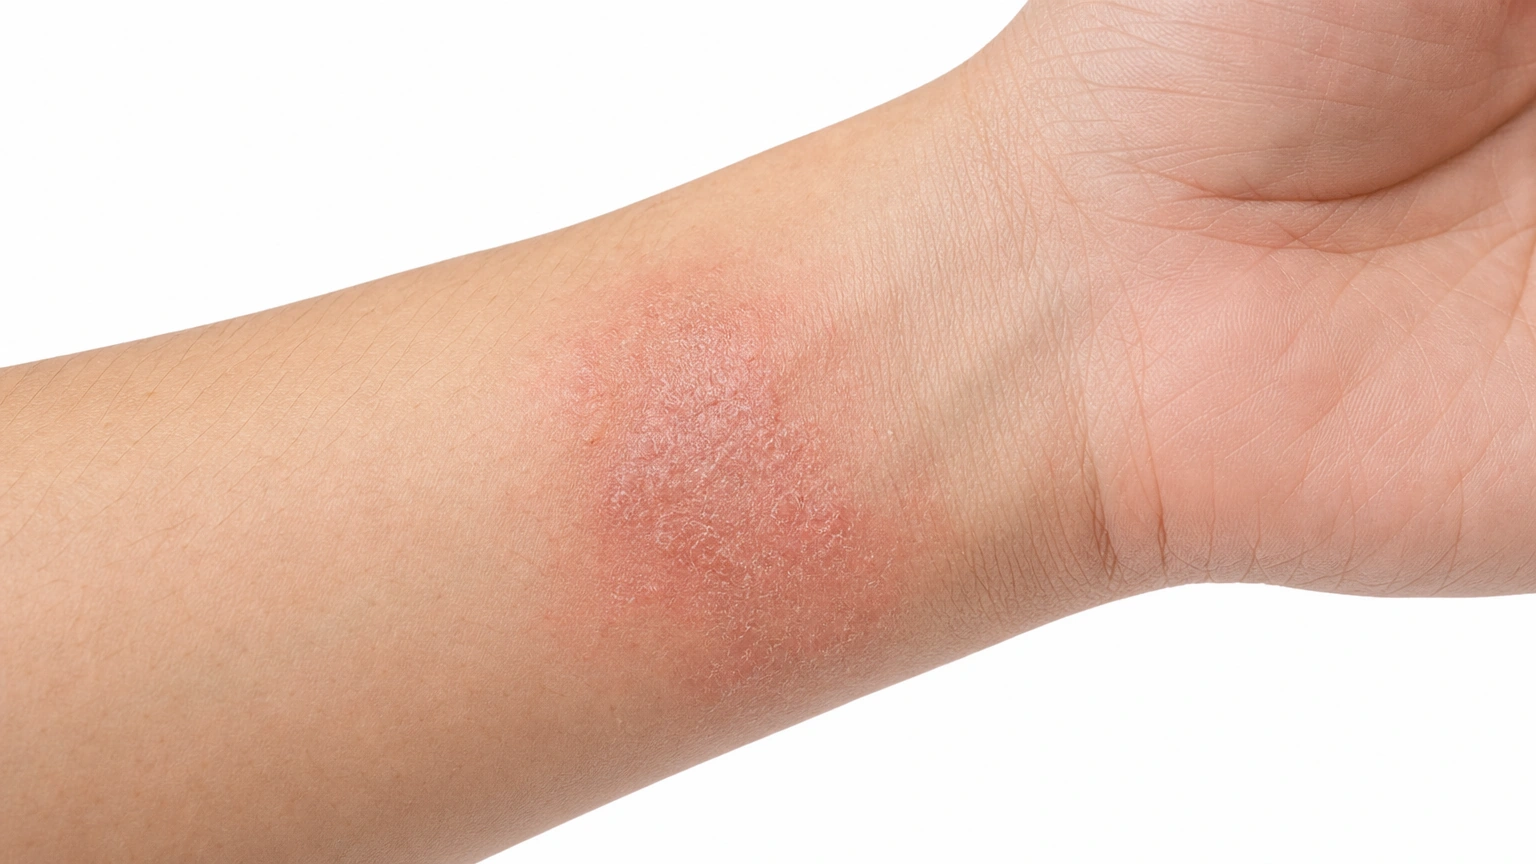
Allergic Contact Dermatitis vs Eczema
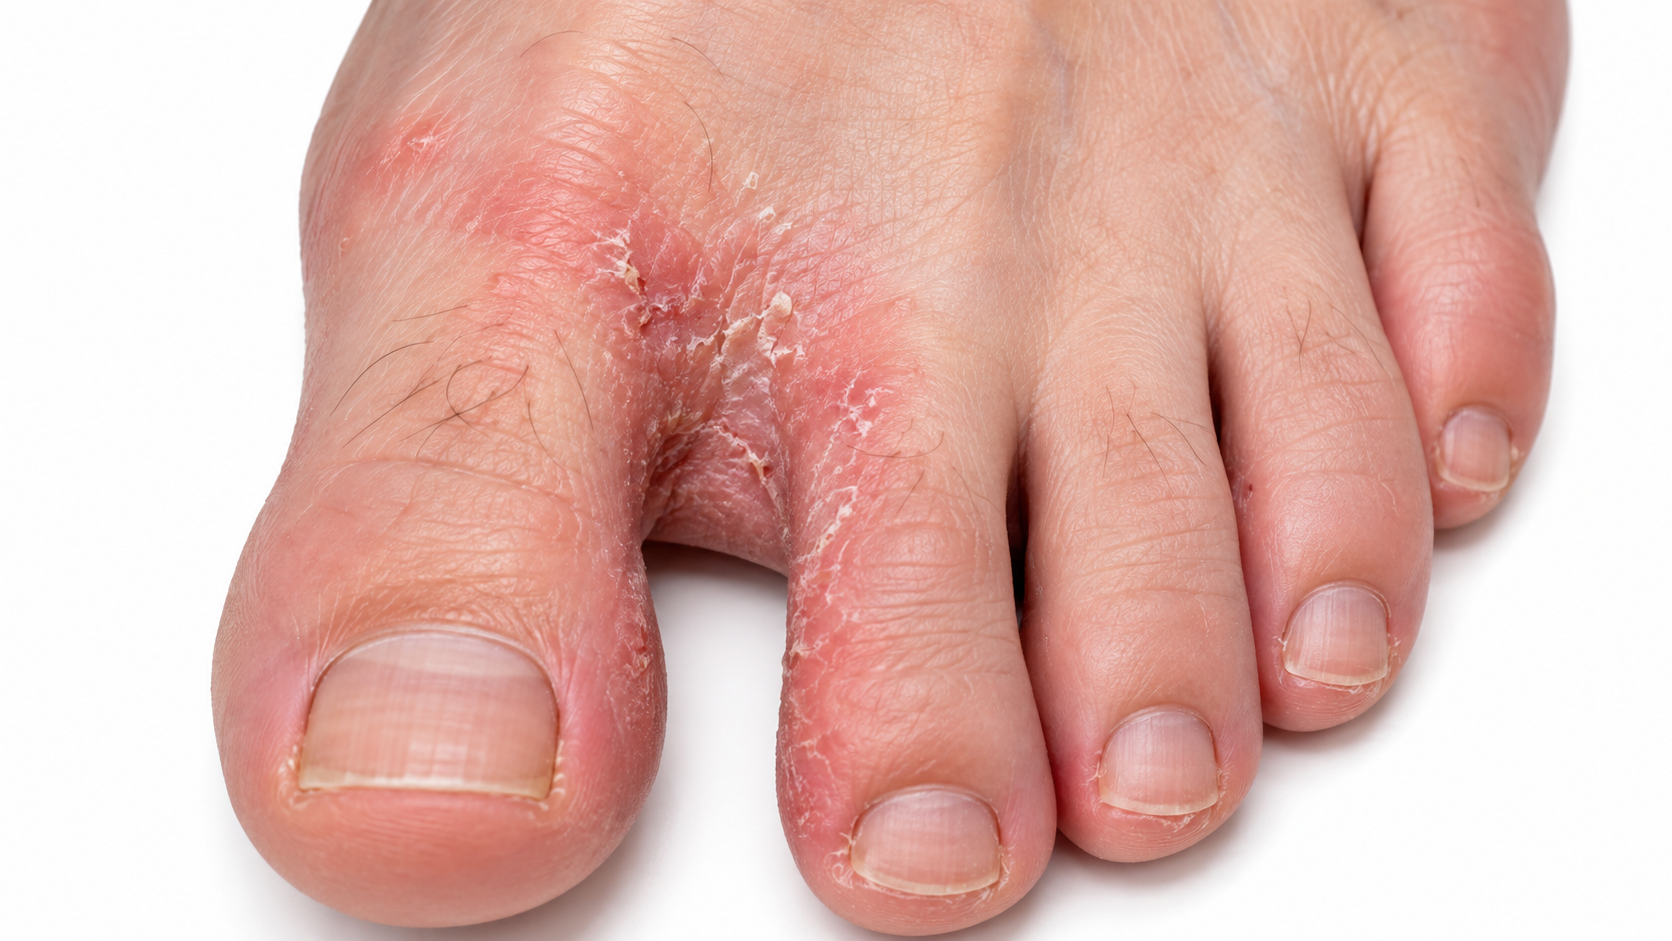
Athlete's Foot vs Psoriasis

Baby Acne vs Eczema