Phototherapy
A prescribed medical light treatment that uses a narrow band of ultraviolet B, usually two or three times a week, to calm psoriasis and eczema and to bring color back in vitiligo. A tanning bed is a different thing and is not a substitute.

Key facts
Treats
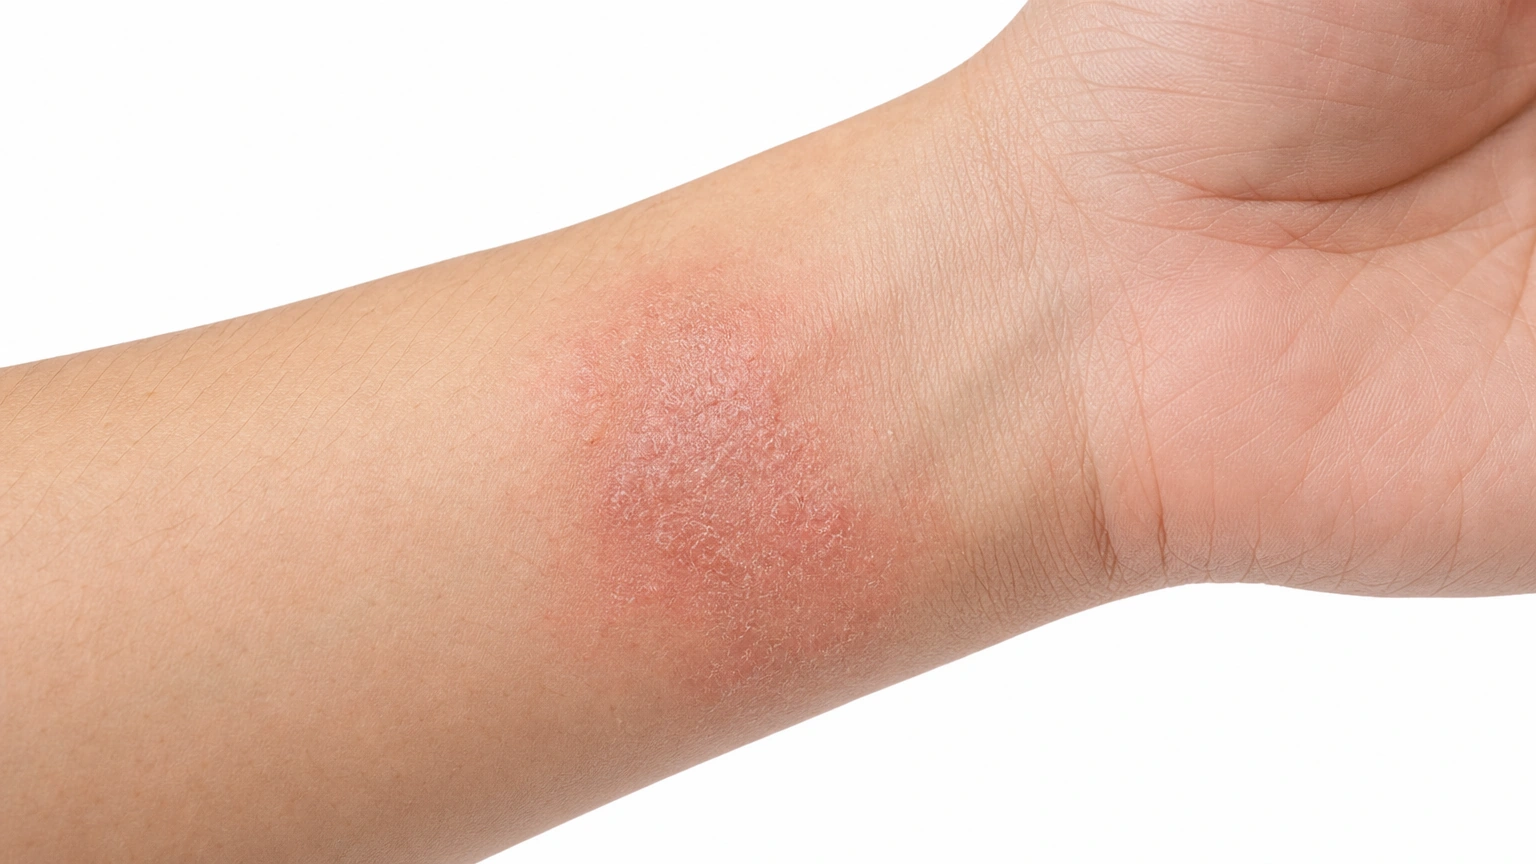
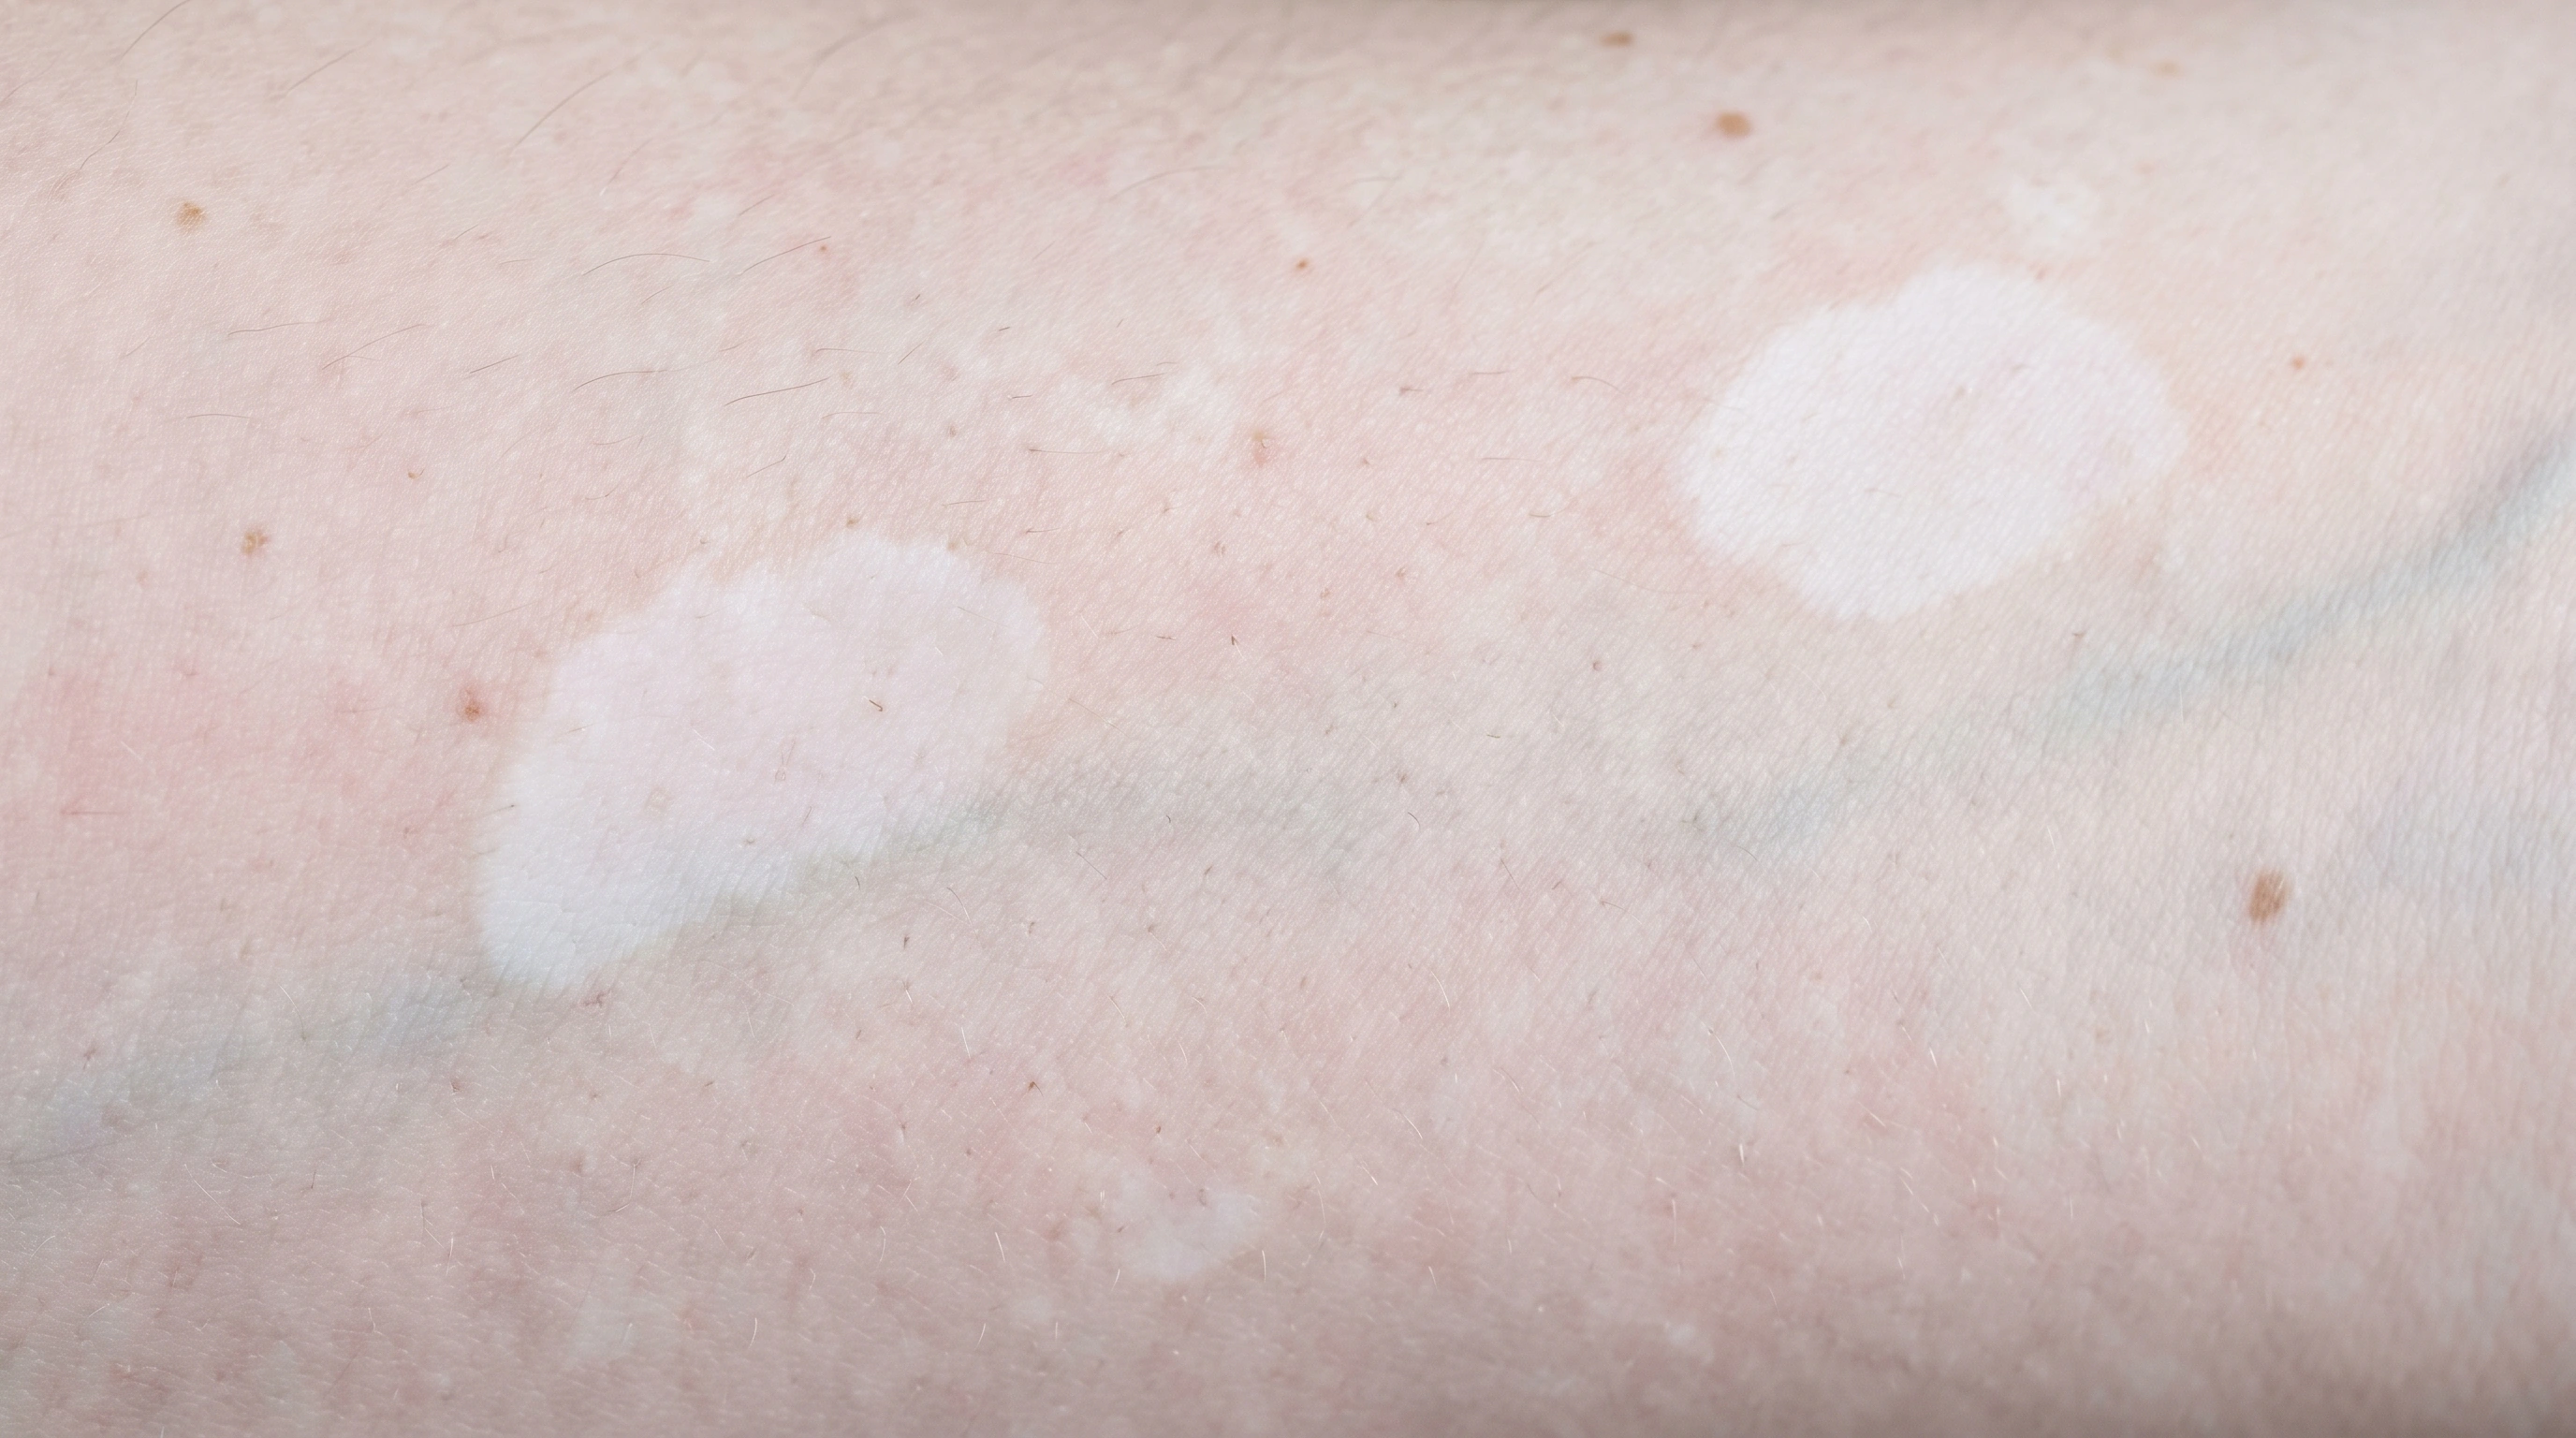
Psoriasis, eczema or vitiligo
Recovery
Usually no downtime
Treatment plan
Often 2–3 visits weekly; course varies
Typical cost
Per-session cost; medical coverage varies
What is it?
It is medical ultraviolet light.
Controlled UV exposure treats selected inflammatory skin diseases.
Narrowband UVB is most common.
PUVA combines a light-sensitizing medicine with UVA.
Tanning beds are not a substitute.
They are not equivalent to medical phototherapy.
History is reviewed.
Medicines, skin cancer history and cumulative exposure are checked.



Treatment areas
Phototherapy
Affected skin may be treated in a whole-body booth or with a smaller unit; unaffected areas may be shielded.
Phototherapy
Affected skin may be treated in a whole-body booth or with a smaller unit; unaffected areas may be shielded.
Skin tones
Lighter skin
Some risk
Burns more easily; lower starting doses.
Medium skin
Low risk
Tanning of untreated skin.
Deeper skin
Low risk
Tans darker; vitiligo edges may stand out at first.
How it works

Diagram explanation
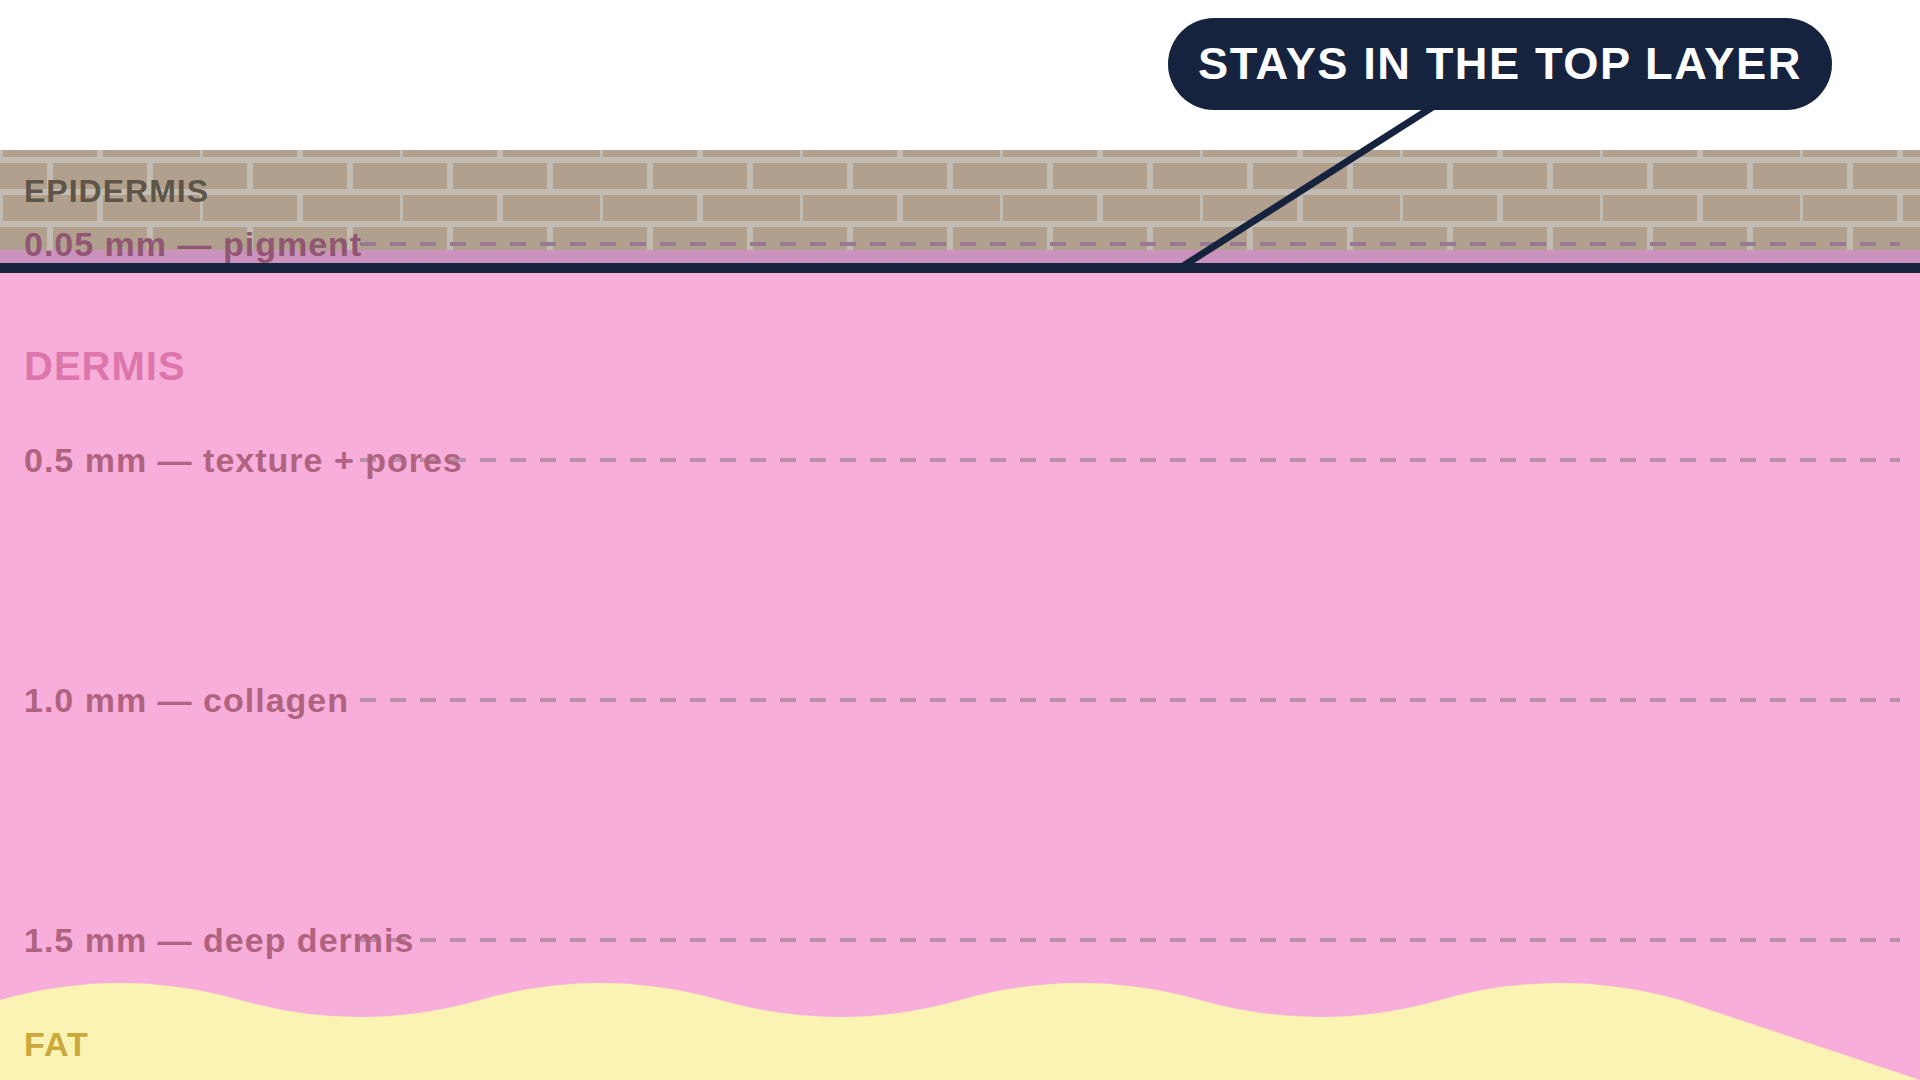
Measured UV light reaches skin: A clinician selects and monitors the light exposure. Inflammatory activity changes: UV treatment can reduce overactive immune activity in skin. Skin symptoms may improve: Repeated treatment can help selected inflammatory conditions.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Types
Several types of ultraviolet light treatment are used for skin disease. Narrowband UVB is the most common today.
Narrowband UVB
Whole-body or partial treatment in a light booth.
- Sessions
- 2–3 a week
- Used for
- Psoriasis, eczema, vitiligo

PUVA
UVA light after a psoralen pill or soak.
- Sessions
- 2–3 a week
- Used for
- Thick psoriasis, some rare conditions
- Caution
- Higher long-term skin cancer risk
Home UVB
A prescribed unit used at home.
- Sessions
- Same schedule as clinic
- Benefit
- No travel
Before your treatment
The week before
Between sessions: Sun and tanning: No sunbathing, no tanning beds.
Day of treatment
Before you arrive
Clean skin: Emollient on plaques only if told to.
Goggles and shielding: Know which areas will be shielded, and bring your own goggles if you have them.
Arrival & prep
You are asked whether your skin burned, stung or went pink after the last session.
Treatment
You undress to the treated areas, put on goggles, and step into the cabinet.
Men get genital shielding — standard, not optional. The face is covered if it is not affected. Lamps run from a few seconds early in a course to several minutes later. You stand still and turn if asked. It does not hurt, and most people feel only warmth.
Before you leave
Skin may look slightly pink and feel warm, like light sun.
After your treatment
First 24 hours
Days 1 to 2: A faint pink that fades by the next day is expected, and it is how the dose is judged.
Time to results
3–4 weeks to start
How long results last
Months; vitiligo color can be lasting
Weeks into the course
Treated skin dries out and tans.
After a missed session
Gaps matter.
Risks
When to contact your provider
Report every burn: Tell the unit before the next session if skin was sore, pink the next day, or blistered.
Report every burn: The dose can be adjusted.
Report every burn: It is not a complaint.
Most side effects are the ones sun causes, because this is a controlled dose of ultraviolet. Redness, warmth, dryness, itch and tanning on treated areas are expected. Serious problems are uncommon and mostly avoidable by reporting burns and keeping the team current on your medicines.
Skin cancer deserves a straight answer. PUVA, the older tablet-plus-UVA treatment, clearly raises risk at high cumulative doses. For narrowband UVB, studies have not shown a clear increase, but long-term data are thin. That is why units count your lifetime sessions, shield the unaffected face, and keep up skin checks.
A sunburn reaction
Sore skin, or skin still red the day after, means the dose was too high. Easily adjusted, never something to push through.
Cold sores appearing
Ultraviolet triggers them in people who get them. Antivirals work best started early, and some people take them preventively.
Itching that is getting worse
Rising itch can mean the skin is drying out or the dose is climbing too fast.
New or changing moles
Repeated ultraviolet treatment means skin checks, and anything new deserves a look sooner.
Eye irritation or vision change
Report it, and say if the goggles slipped.
Polymorphic light eruption
An itchy bumpy rash on treated areas early in a course. Manageable, but the unit needs to know.
Cost
Typical cost
Per session; usually covered
Pricing
Written estimate: Ask whether the quoted fee includes assessment, anesthesia, supplies, pathology when relevant, follow-up, and any planned repeat treatments.
Insurance
This is one of the few treatments here that insurance often pays for, because it treats a medical condition.
Alternatives

Topical steroids and vitamin D creams
First-line for limited psoriasis and eczema, cheap and done at home. They become impractical when a large area of skin is involved, which is exactly where phototherapy takes over.

Excimer laser or light at 308 nm
Delivers a higher dose to a patch while sparing the rest of the skin, so it needs fewer and shorter sessions. Only practical for limited areas, and less consistently covered by insurance.

PUVA
A tablet plus ultraviolet A, more powerful for stubborn disease, but it needs eye protection for the rest of the day and carries a documented increase in skin cancer risk at high cumulative doses. Largely replaced by narrowband UVB for this reason.
Biologics and oral immune treatments
Often more effective than light for moderate to severe psoriasis and eczema, with no travel and no schedule, at the cost of acting on the whole immune system and needing monitoring. Frequently the next step when phototherapy is not practical or has stopped working.
Ruxolitinib cream, for vitiligo
A prescription cream approved for nonsegmental vitiligo. Slow, applied at home, and commonly used with phototherapy rather than instead of it.

Sunlight
Limited and hard to control. Real sunlight contains the useful wavelengths mixed with a lot that is not useful, at a dose that changes with season, weather and time of day. Some people genuinely improve in summer, but it cannot be dosed or tracked.

Tanning beds
Not a substitute. A different mix of ultraviolet, an uncontrolled dose, no shielding protocol, and a clear skin cancer risk.
Prescribed full-body home cabinet or panel
Home phototherapy is a real medical option, not a workaround. It uses the same narrowband lamps as the clinic, with the dosing schedule written by your dermatologist and reviewed at follow-up visits. A cabinet costs several thousand dollars, often with insurance help, and needs space and a prior authorization. The reason to have one is that it removes the travel that ends most courses.

Prescribed handheld or targeted home unit
For limited areas such as elbows, knees, patches of vitiligo, or the scalp with a comb attachment. Much less expensive than a cabinet and easier to fit into a day, but slow for large areas.
Prescribed hand and foot unit
Built for palms and soles, which are difficult to treat any other way. Hands and feet respond slowly to light and often need something else alongside.

Emollients and prescribed topicals
Daily moisturizer, and steroid, vitamin D or tacrolimus creams as prescribed. Applied after sessions rather than before, unless you have been told otherwise, because a layer of product blocks the light.
Sunlight, in a planned way
Some dermatologists suggest short, timed sun exposure where phototherapy is out of reach. If that is offered it should come with specific times and precautions from your own doctor, not from a general rule.
Questions
Is narrowband UVB the same as a tanning bed?
No. Tanning beds emit mostly ultraviolet A with a little UVB; this uses a narrow band around 311 nanometers chosen to keep the benefit and cut the burning wavelengths. Phototherapy doses are prescribed, recorded and adjusted, and areas that do not need treating are shielded. Tanning beds carry an established skin cancer risk.
How long before I see a difference?
Psoriasis usually starts improving by the third or fourth week and often clears over roughly 20 to 36 sessions. Eczema is slower, six to twelve weeks, with itch settling before the rash. Vitiligo cannot be judged before three months and often takes six to twelve months.
How often do I have to go?
Two or three times a week for most of a course. This is the hardest part, and the most common reason people stop, so be honest with yourself before starting and ask about a home unit if it will not work.
Does it cause skin cancer?
PUVA, the older tablet-plus-UVA treatment, clearly raises risk at high cumulative doses. Narrowband UVB studies have not shown a clear increase, but long-term data are limited, which is why lifetime sessions are counted, unaffected skin is shielded, and skin checks continue.
Can I do it at home?
Yes, with a prescription. Home units use the same lamps and dosing protocol, your dermatologist writes the schedule and reviews progress, and insurance sometimes pays because a unit costs less than a long series of office visits.
Will it come back after I stop?
Psoriasis and eczema usually return over weeks to months, and the length of the break varies a lot. Some people go onto a lower maintenance frequency instead of stopping. Pigment regained in vitiligo is often kept, though it can be lost if the condition is still active.