Mometasone
A mid-strength prescription steroid applied once a day for eczema, psoriasis and other itchy rashes. Strong enough to settle a flare, measured enough for short courses on most of the body.

Key facts
Mometasone at a glance.
Used for
Eczema or psoriasis on the body
Results
3–14 days
Treatment commitment
Short prescribed courses
Key precautions
Overuse can thin skin
What is it?
Top things to know about Mometasone
- It is a topical corticosteroid. Mometasone furoate relieves inflammation and itch.
- Vehicles differ. Cream, ointment and lotion vary in potency.
- The ointment is labeled from age two. Evidence for prolonged pediatric use is limited.
- Other forms are not for skin. Nasal and veterinary labels do not guide skin treatment.
HOW IT WORKS
How Mometasone works
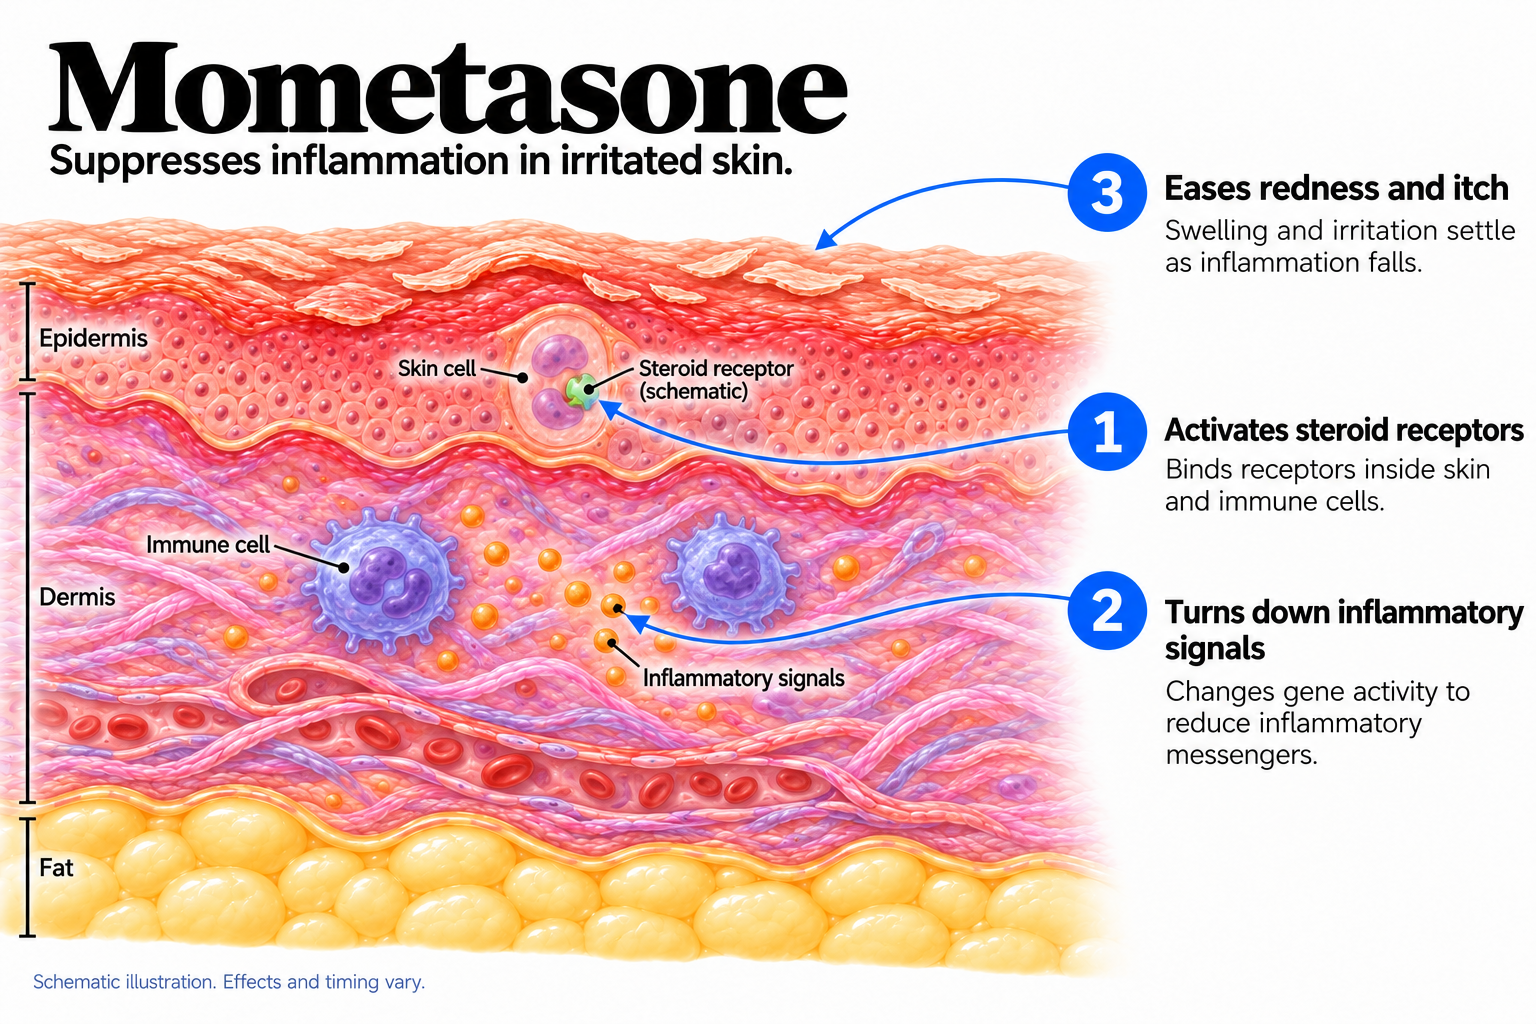
Diagram explanation and sources
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
Strengths
Mometasone strengths
Mometasone furoate skin products use 0.1%, including cream, ointment and lotion. The same concentration in different bases does not guarantee the same potency or absorption.
0.1%
The cited skin-product labels use a thin film once daily. Choose the vehicle and treatment site with the prescriber.
Forms
Mometasone forms

Cream
Richer and more moisturizing; often suits dry skin. The full formula still affects comfort.

Ointment
A greasy, protective base that helps hold moisture in. Often comfortable on very dry skin, but can feel heavy or sticky.

Lotion
Thinner than a cream and easy to spread over larger or hair-bearing areas. May feel less rich on dry skin.
How to use it
Your treatment, step by step.
How to apply it
- 01
When to Apply
Once a day, a thin film on the rash only, not the skin around it. A fingertip length covers roughly two flat palms. Moisturizer can go on the same skin at other times.
- 02
How to Start
Once daily from day one until the skin is smooth and not itchy, usually a few days to two weeks. Under-using it is the commoner mistake. Then stop, or step down to twice a week if your doctor set that up.
- 03
If It Irritates
A short sting on cracked or raw skin is common and settles as the skin heals. Moisturizing twenty minutes before or after helps. Burning that worsens over days can mean infection, a reaction to the base, or the wrong diagnosis.
- 04
If It’s Not Working
Two weeks of daily use with no change means something else is going on — too little applied, a fungal or infected rash that steroids make worse, or a rash needing a stronger cream or a different drug. Do not keep going past that without a review.
Monitoring & follow-up
No blood tests for ordinary use. Monitoring is looking at the skin: is the treated area thinner or shinier than the skin beside it, are small veins showing, are there stretch marks in the folds or pus bumps around hair follicles.
The exception is large-area, long-term or covered use, and use in small children, where enough can be absorbed to affect the body’s own steroid production. Uncommon, and why a doctor sets an area and a time limit.
The checkpoint is a review at two to four weeks. Using it most weeks over months means the question is no longer the cream but what long-term treatment should be doing this job.
What to expect
How things change over time.
Applying it
A thin layer once a day, on the affected skin only.
Itch first
Itch eases before the rash looks different. Normal, and not a reason to add more.
Working
Redness fades, scale flattens, weeping stops. Most short courses finish here, and moisturizer keeps going after the steroid stops.
Judge it here
If it is clear, stop or move to twice-weekly maintenance.
Psoriasis plaques
Scale lifts and plaques flatten. Something else usually runs alongside, since steroids rarely hold psoriasis on their own.
Thickened, leathery patches
Skin rubbed and scratched for a long time takes longest, because the thickening itself has to reverse.
The risks
Thinning skin, visible small veins, stretch marks in folds, small pus bumps around hair follicles. Uncommon on short courses, and why long courses are planned rather than drifted into.
- First few minutes
- Days 1 to 3
- Days 3 to 14
- Weeks 2 to 4
- Weeks 2 to 6
- Weeks to months
- Beyond a few weeks of continuous use
When you stop
Short courses can stop as soon as the skin is clear. There is no taper, unlike oral steroids.
What people run into is the rash coming back, sometimes within days, because the steroid treated the inflammation and not the cause. For eczema that is why moisturizer and trigger control continue after the cream stops, and why many doctors set up maintenance — the same cream twice a week on the spots that always flare, which lowers flare frequency.
Two situations need more care. Potent steroids over large areas of psoriasis can rebound worse if stopped abruptly, so they are stepped down. And prolonged potent use on the face or genitals can leave skin red, burning and sensitive on stopping, sometimes called topical steroid withdrawal — uncommon, tied to long unsupervised use, and a reason to plan an exit.
What it Pairs with
Mometasone + your routine
| Product or situation | With Mometasone | What to know |
|---|---|---|
| Moisturizer | Can pair | Moisturizer can go on the same skin at other times. |
| Using it as a moisturizer | Avoid | It treats a defined flare. Open-ended daily use is what creates the problems people associate with steroid creams. |
| Eyelids, face, armpits and groin | Avoid | Unless your doctor said so. Skin is thin there, absorbs far more, and shows thinning first. Near the eyes, steroids can also raise eye pressure. |
| Covering the treated skin | Avoid | Plastic wrap, tight dressings or a diaper multiply how much drug gets in. Only if you were told to. |
| Putting it on a possible infection | Avoid | A rash that might be fungal, or is crusted and weeping. Steroids calm the redness while the infection spreads. |
| Using someone else’s tube | Avoid | A steroid that fits one rash on one site can be wrong for another. |
| Refilling it for months without review | Avoid | The repeat prescription is the quiet route to a long course nobody chose. |
| If you are pregnant or breastfeeding | Use care | Including planning a pregnancy. Ask the doctor managing your pregnancy how much skin to treat and for how long. |
| If you have used it for weeks | Use care | More than a few weeks, or on a large area, needs a plan rather than a repeat prescription. |
| If the rash is spreading or weeping | Use care | Crusting, blistering or pain counts too. These can mean infection, which a steroid alone will not treat. |
| If you are treating a young child | Use care | Especially the face or the diaper area. Children absorb proportionally more, so a doctor sets the site and duration. |
| If you are using it on or near the eyelids | Use care | Steroids near the eye can raise pressure inside it over time. |
| If you use steroids in any other form | Use care | Tablets, inhalers or nasal sprays, or if you have diabetes. The effects add up. |
| If the treated skin changes | Use care | Stretch marks, thinning or small pus bumps mean stop and get it looked at. |
Getting it and cost
Getting Mometasone.
Cost & access
Generic mometasone is inexpensive and widely stocked, and the cream and ointment are on most low-cost generic lists. The Elocon brand costs considerably more for the same molecule.
What affects the cost
The lotion and scalp solution usually cost more, and are sometimes the versions a plan will not cover. If cost is the issue, ask whether a different base at the same 0.1% would do the job.
Alternatives
Other options to consider.

Hydrocortisone 1%
Much milder and available without a prescription in many places. Safer for the face and for children, and often not strong enough for an established eczema flare.

Triamcinolone 0.1%
A similar band of strength, dosed twice a day rather than once. Cheap, widely used and largely interchangeable in practice.

Clobetasol or betamethasone dipropionate
A clear step stronger, used for thick plaques, hands and feet, and short bursts on stubborn disease. More capable and less forgiving over time.

Tacrolimus ointment and pimecrolimus cream
Not steroids, so no skin thinning, which makes them useful for the face, eyelids and folds and for long-term maintenance. Many people get a burning sensation in the first week, and they cost more.

Crisaborole ointment
Non-steroid, mild, for mild to moderate eczema. Also stings for some people and is priced well above generic steroids.
Roflumilast and ruxolitinib creams
Newer non-steroid options with real evidence in eczema and psoriasis. Cost and insurance coverage are the usual barriers.
Mometasone’s case is the middle ground
once-daily dosing, mid-range strength, and a price that is not an obstacle.
Questions
Questions you might be asking.
How long can I use it?
Two to four weeks on a defined area. Longer should be your doctor's decision, usually as twice-weekly maintenance.
Can I use it on my face?
Only if your doctor said so, and briefly. Facial skin absorbs far more and shows thinning first. Milder or non-steroid creams are usually chosen there.
Can I use moisturizer with it?
Yes, and you should — at a different time of day, so you are not diluting the steroid or spreading it beyond the rash.
Why has the rash come back?
The steroid treated the inflammation, not the cause. Expected in eczema and psoriasis, and why maintenance and steady moisturizing matter.
Is once a day really enough?
Yes. It was developed for once-daily use and the trials were done that way. Twice a day adds side effect risk without benefit.
What if it stings?
A short sting on broken skin is common and settles. Burning that builds over days, or a worsening rash, can mean infection or a reaction to the base.
Related
Keep exploring.
Scalp Psoriasis
Hydrocortisone

Eczema

Psoriasis
Ringworm

Rosacea
Hydrocortisone vs Mometasone

Calcipotriene vs Mometasone

Clobetasol vs Mometasone

Cyclosporine vs Mometasone

Desonide vs Mometasone