Calcipotriene
A vitamin D-like cream or ointment for plaque psoriasis. It slows the overgrowth of skin cells that makes plaques thick and scaly, and it is not a steroid.

Key facts
Calcipotriene at a glance.
Used for
Plaque psoriasis, including scalp
Results
6–8 weeks
Treatment commitment
Ongoing as prescribed
Key precautions
Limit amounts; avoid inappropriate sites
What is it?
Top things to know about Calcipotriene
- It is a vitamin D analogue. Calcipotriene is a synthetic form of vitamin D.
- It normalizes skin-cell growth. It helps correct abnormal plaque development in psoriasis.
- It treats plaque psoriasis. The plain cream is labeled for adults.
- Combinations add steroid risks. Products with betamethasone carry corticosteroid precautions.
Often used for
What Calcipotriene is used for
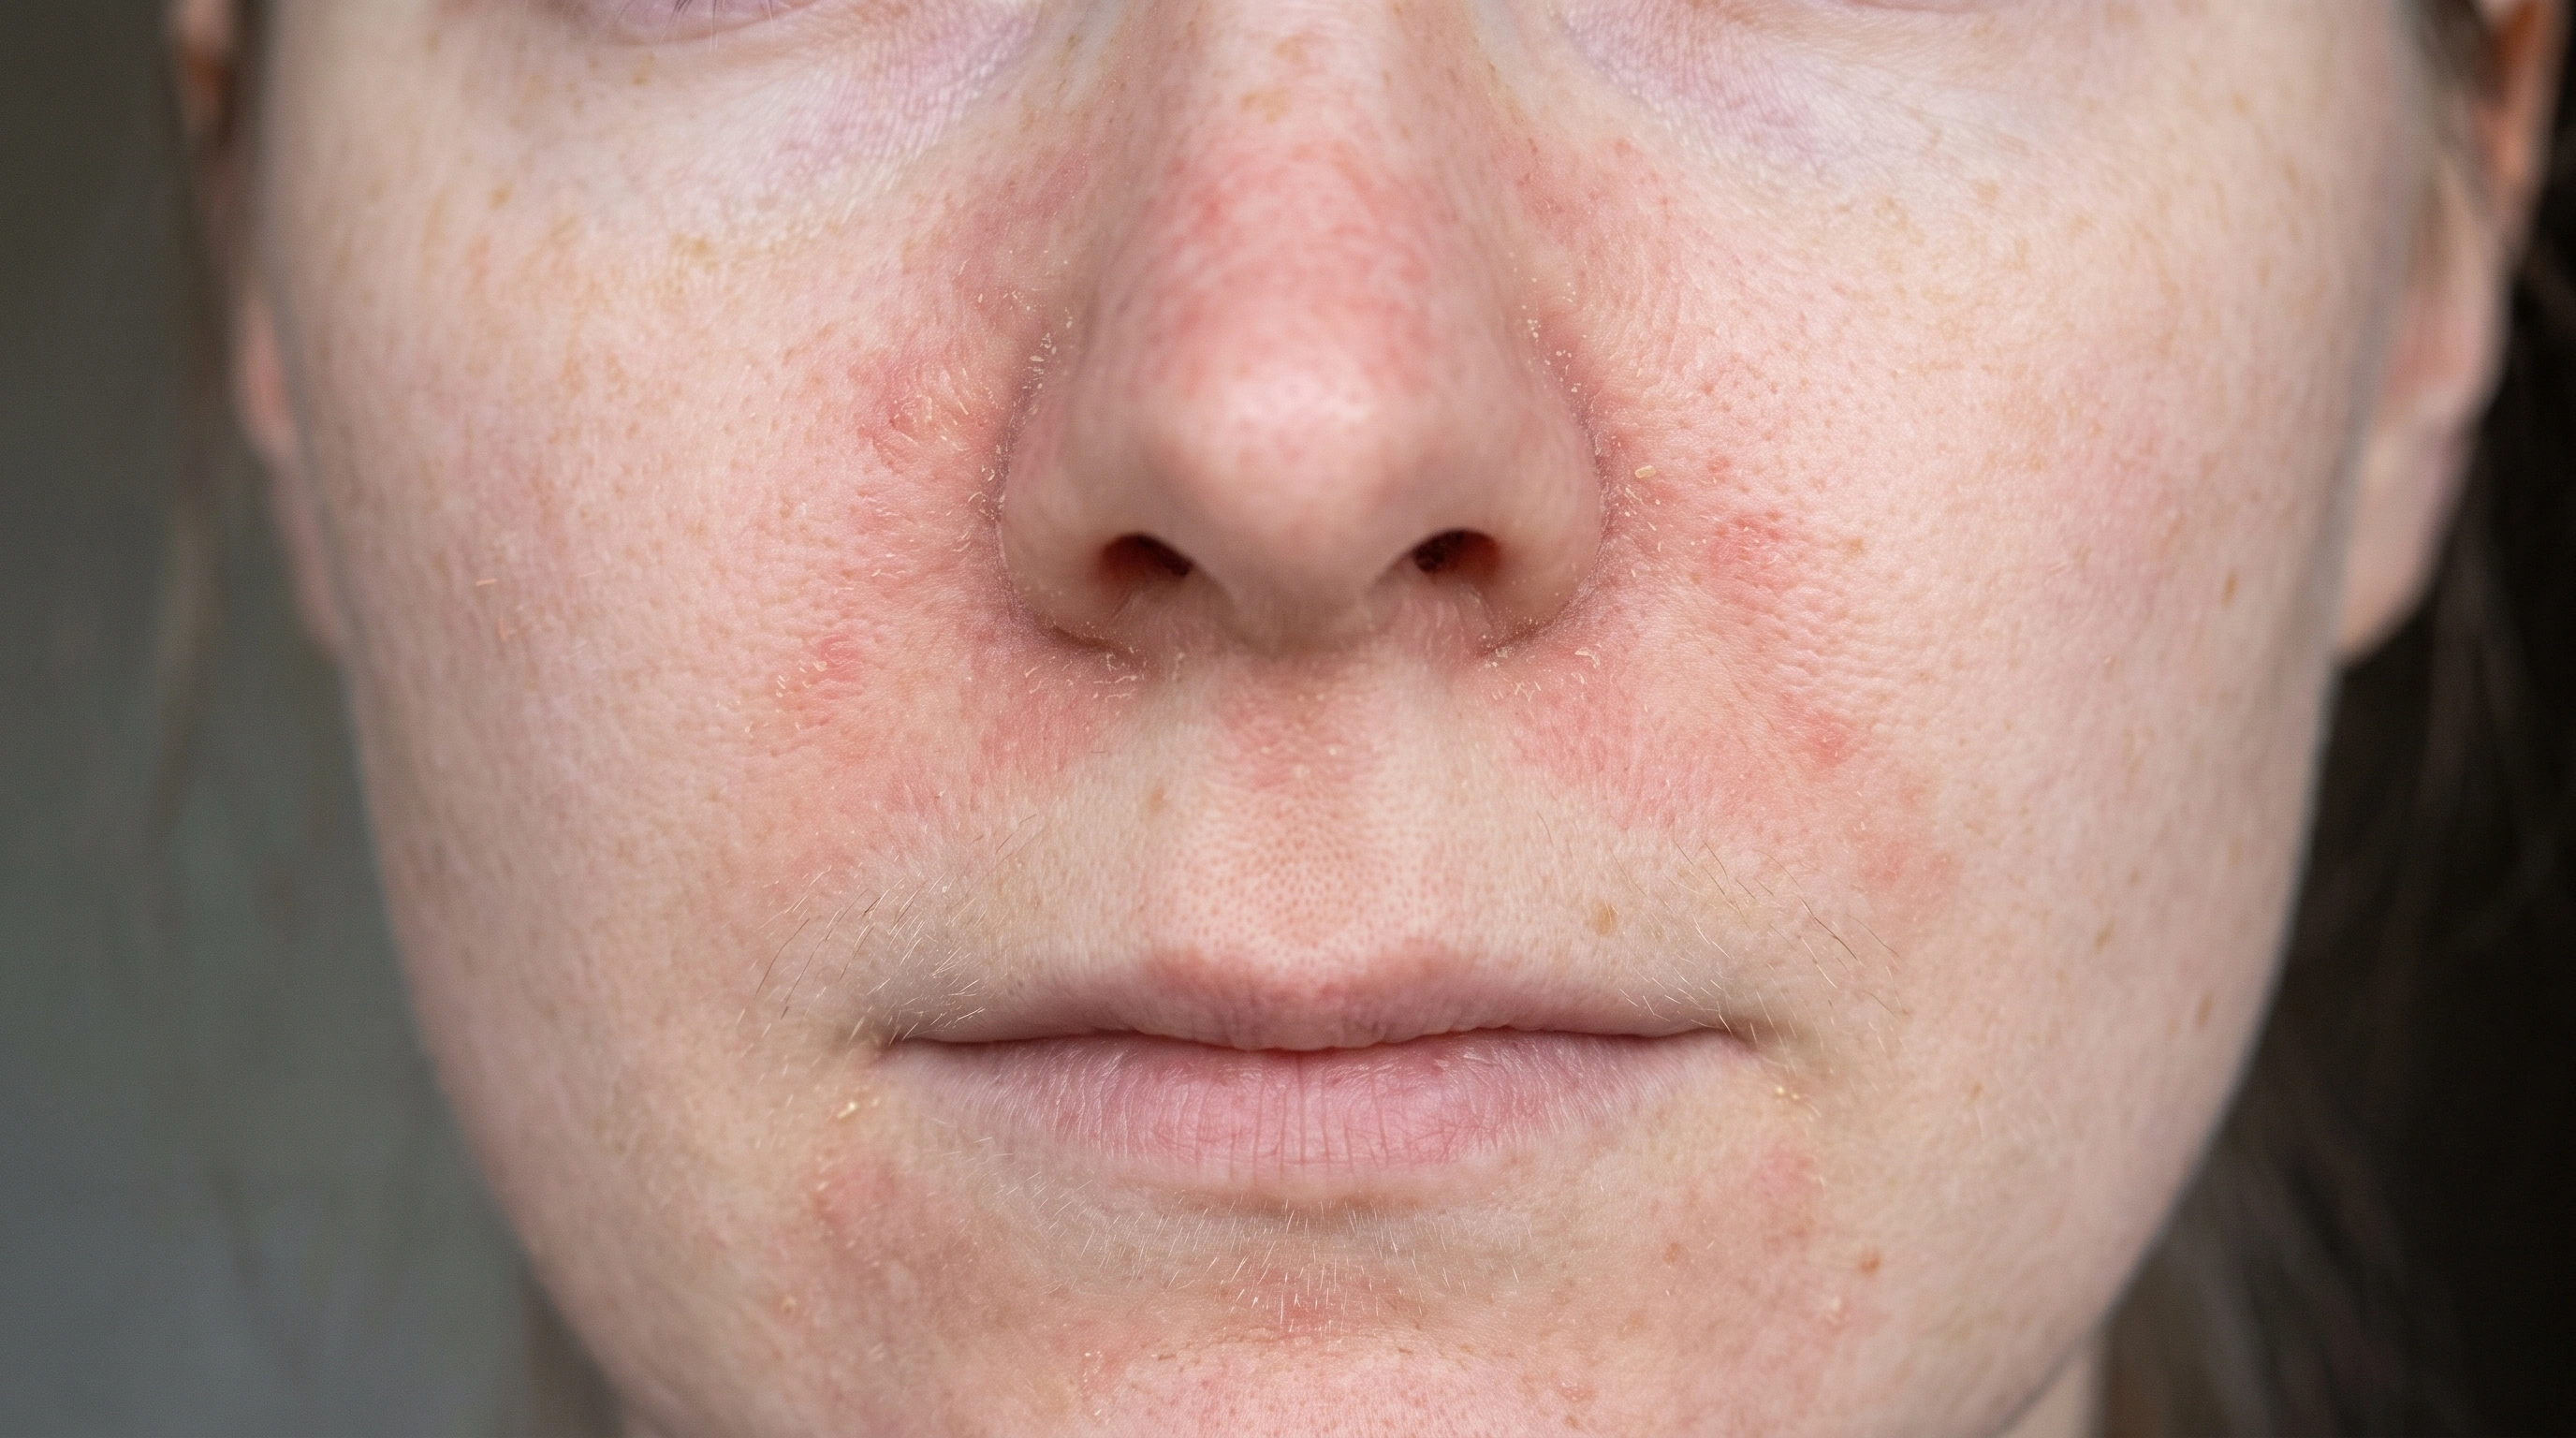
HOW IT WORKS
How Calcipotriene works

Diagram explanation and sources
Activates vitamin D receptors: Changes signals inside skin cells. Slows excess cell growth: Helps reduce the rapid buildup seen in psoriasis. Improves cell maturation: Helps cells develop into more normal skin layers. Reduces plaque scale: Thick, scaly patches gradually become flatter.
Calcipotriene is a vitamin D analog with effects on cell proliferation and differentiation. Its complete antipsoriatic mechanism is not established; this is a simplified overview.
Strengths
Calcipotriene strengths
Single-ingredient calcipotriene commonly uses 0.005%, equivalent to 50 micrograms per gram. Cream, ointment, foam and scalp solution have their own directions; combination products containing a steroid are separate medicines.
0.005%
A topical psoriasis concentration. Formulation-specific age, application and body-area instructions still apply.
Forms
Calcipotriene forms

Cream
Richer and more moisturizing; often suits dry skin. The full formula still affects comfort.

Ointment
A greasy, protective base that helps hold moisture in. Often comfortable on very dry skin, but can feel heavy or sticky.

Solution
A fluid with the active ingredient dissolved in its base. Spreads easily through hair; some solvent-based formulas can sting or dry skin.

Foam
Easy to spread through hair or over larger areas. Moisturizing feel and stinging vary with the formula.
How to use it
Your treatment, step by step.
How to apply it
- 01
When to Apply
Twice a day for the plain product, thinly onto the plaques only. Once a day for the combined calcipotriene-and-steroid products. Do not use more than about 100 grams a week, and do not treat more than roughly a third of the body surface. With phototherapy, apply it after the session, not before.
- 02
How to Start
Full dose from day one, on the plaques only. Many start on a combined calcipotriene-and-steroid product for the first few weeks to settle redness, then continue on calcipotriene alone.
- 03
If It Irritates
Burning and stinging in the first days is usual and often settles. Moisturizer first, or once a day for a week, helps. Irritation on the face, eyelids, groin or under the breasts is not one to push through — thin skin, and this drug is not made for it. Sharp burning on broken skin means waiting for it to close over.
- 04
If It’s Not Working
There is only one strength, so nothing can be increased. Give it six to eight weeks. If plaques are still thick, the next steps are the combined product with a steroid, switching cream for ointment, adding phototherapy, or a tablet or injection. Also check what else is going on the skin — salicylic acid inactivates calcipotriene.
Monitoring & follow-up
No routine blood tests when it is used normally: plaques only, within the weekly amount, healthy kidneys.
The one thing watched for is raised blood calcium. It is rare, and it comes from using far more than recommended, treating very large areas, or kidney disease that stops the body clearing the extra calcium. Calcium may be checked if any of those apply, or if you take high-dose vitamin D or calcium supplements. Symptoms are unusual thirst, passing more urine than usual, nausea, constipation, muscle weakness and confusion.
Monitoring is otherwise clinical — the skin at six to eight weeks, and how much of a tube is used per week. With the combined steroid product, the review also covers how long the steroid has run.
Long term, calcipotriene alone is a drug you can stay on. Nothing accumulates and it does not thin skin, which is why it is the usual maintenance between steroid courses.
What to expect
How things change over time.
Applying it
Stinging or burning, if it happens, is worst at the start and eases.
Starting
Early flattening and less scale. Its strongest effect, and what people notice first.
The steady phase
Plaques thin and the silvery scale falls away. Redness fades more slowly than thickness, the main reason calcipotriene and a steroid are combined. Itch improves, slower than with a steroid.
Judge it here
Roughly where the effect plateaus in trials.
Where it is used most
The scalp solution and the combined foam or gel work well here.
Maintenance
Used between steroid courses, it holds the result. Stopped, plaques return over weeks to months.
- First few minutes
- Weeks 1 to 2
- Weeks 2 to 6
- Weeks 6 to 8
- Scalp
- Long term
When you stop
No taper and no withdrawal from calcipotriene itself.
Psoriasis is long-term, so plaques generally come back after stopping, over weeks to months — the disease returning, not a rebound caused by the drug.
Rebound matters when it has been part of a combined product with a strong steroid. Stopping a potent steroid abruptly after a long run can cause a flare, which is why the plan is to come off the steroid and continue calcipotriene alone.
What it Pairs with
Calcipotriene + your routine
| Product or situation | With Calcipotriene | What to know |
|---|---|---|
| Moisturizer | Can pair | Moisturizer first, or once a day for a week, helps. |
| The face, eyelids, groin and under the breasts | Avoid | Thin skin burns and stings there. Wash your hands after applying, so it is not carried to your face. |
| Using more than about 100 grams a week | Avoid | Enough absorbed at once can raise blood calcium. More is not better and not safer. |
| Treating very large areas of the body | Avoid | Roughly a third of the body surface is the ceiling. Widespread psoriasis calls for a different treatment, not more cream. |
| Salicylic acid products at the same time | Avoid | Salicylic acid inactivates calcipotriene. Keep a scale softener well apart in the day, or ask about a different one. |
| Applying it before phototherapy | Avoid | Ultraviolet light breaks the drug down. Apply it after the session. |
| Erythrodermic or pustular psoriasis | Avoid | These widespread, unstable forms carry a real risk of raised blood calcium with vitamin D analogs, and need urgent care rather than a tube. |
| Open, cracked or weeping skin | Avoid | Absorption goes up and stinging is much worse. |
| If you have kidney disease or a history of high blood calcium | Use care | Absorbed calcipotriene is cleared less well, and this is where blood calcium genuinely matters. |
| If you take high-dose vitamin D or calcium supplements | Use care | The effects add up. |
| If you are pregnant, planning a pregnancy or breastfeeding | Use care | Ask the doctor managing your pregnancy. Do not apply it to the chest if breastfeeding. |
| If you develop unusual thirst, are passing more urine than usual, or feel nauseated, weak or confused | Use care | These are the symptoms of raised blood calcium. |
| If your psoriasis is widespread, bright red over most of the body, or breaking out in pustules | Use care | These unstable forms need urgent assessment, not a topical. |
| If you are having phototherapy | Use care | Ultraviolet light breaks the drug down. |
Getting it and cost
Getting Calcipotriene.
Cost & access
Generic calcipotriene is cheap and widely available; cost is rarely the barrier for the plain ointment or cream.
What affects the cost
The branded combination products, and the foam and suspension forms, cost substantially more and often need prior authorization. Plans usually want a topical steroid, and often generic calcipotriene, tried first.
What affects the cost
If cost decides it, generic ointment or cream plus a separate generic steroid does much the same job, at the price of two tubes.
Alternatives
Other options to consider.

Topical steroids
faster on redness and itch, cheaper, and stronger evidence for short-term clearing. The trade-off is skin thinning with long use and a flare when they are stopped, neither of which calcipotriene causes.

Calcipotriene combined with a steroid
better evidence than either alone, once-daily dosing, and the standard way psoriasis plaques are started now. It costs more, and the steroid half still carries steroid limits.
Vtama and roflumilast creams
newer, steroid-free, once daily, and usable on the face and skin folds where calcipotriene is not. Both cost far more, and neither has calcipotriene's decades of use behind it.

Coal tar
inexpensive with a long history, but messy, strong-smelling and stains fabric. Used far less now.

Salicylic acid
softens and removes scale rather than treating the psoriasis. It also inactivates calcipotriene, so the two do not belong in the same routine at the same time.
Phototherapy and systemic drugs
for psoriasis too widespread for any cream. Calcipotriene is often continued alongside them for stubborn patches.
Questions
Questions you might be asking.
Is calcipotriene a steroid?
No. A vitamin D analog. It does not thin skin, which is why it can be used long term and is often the maintenance treatment after a steroid course.
Can I use it on my face?
No. The face, eyelids, groin and under the breasts all sting badly — thin skin. Ask about a different product for those areas.
How much can I use?
About 100 grams a week, and about a third of the body surface. That limit keeps blood calcium from rising.
Why does it burn?
Irritation is the most common side effect, worst in the first days. Moisturizer first, or once a day for a week or two, settles it.
Can I use a salicylic acid scale remover with it?
Not at the same time. Salicylic acid inactivates calcipotriene. Keep them well apart in the day or ask about an alternative.
Do I need blood tests?
Not for normal use with healthy kidneys. Calcium may be checked with kidney disease, very large amounts, or high-dose vitamin D.
Related
Keep exploring.

Psoriasis
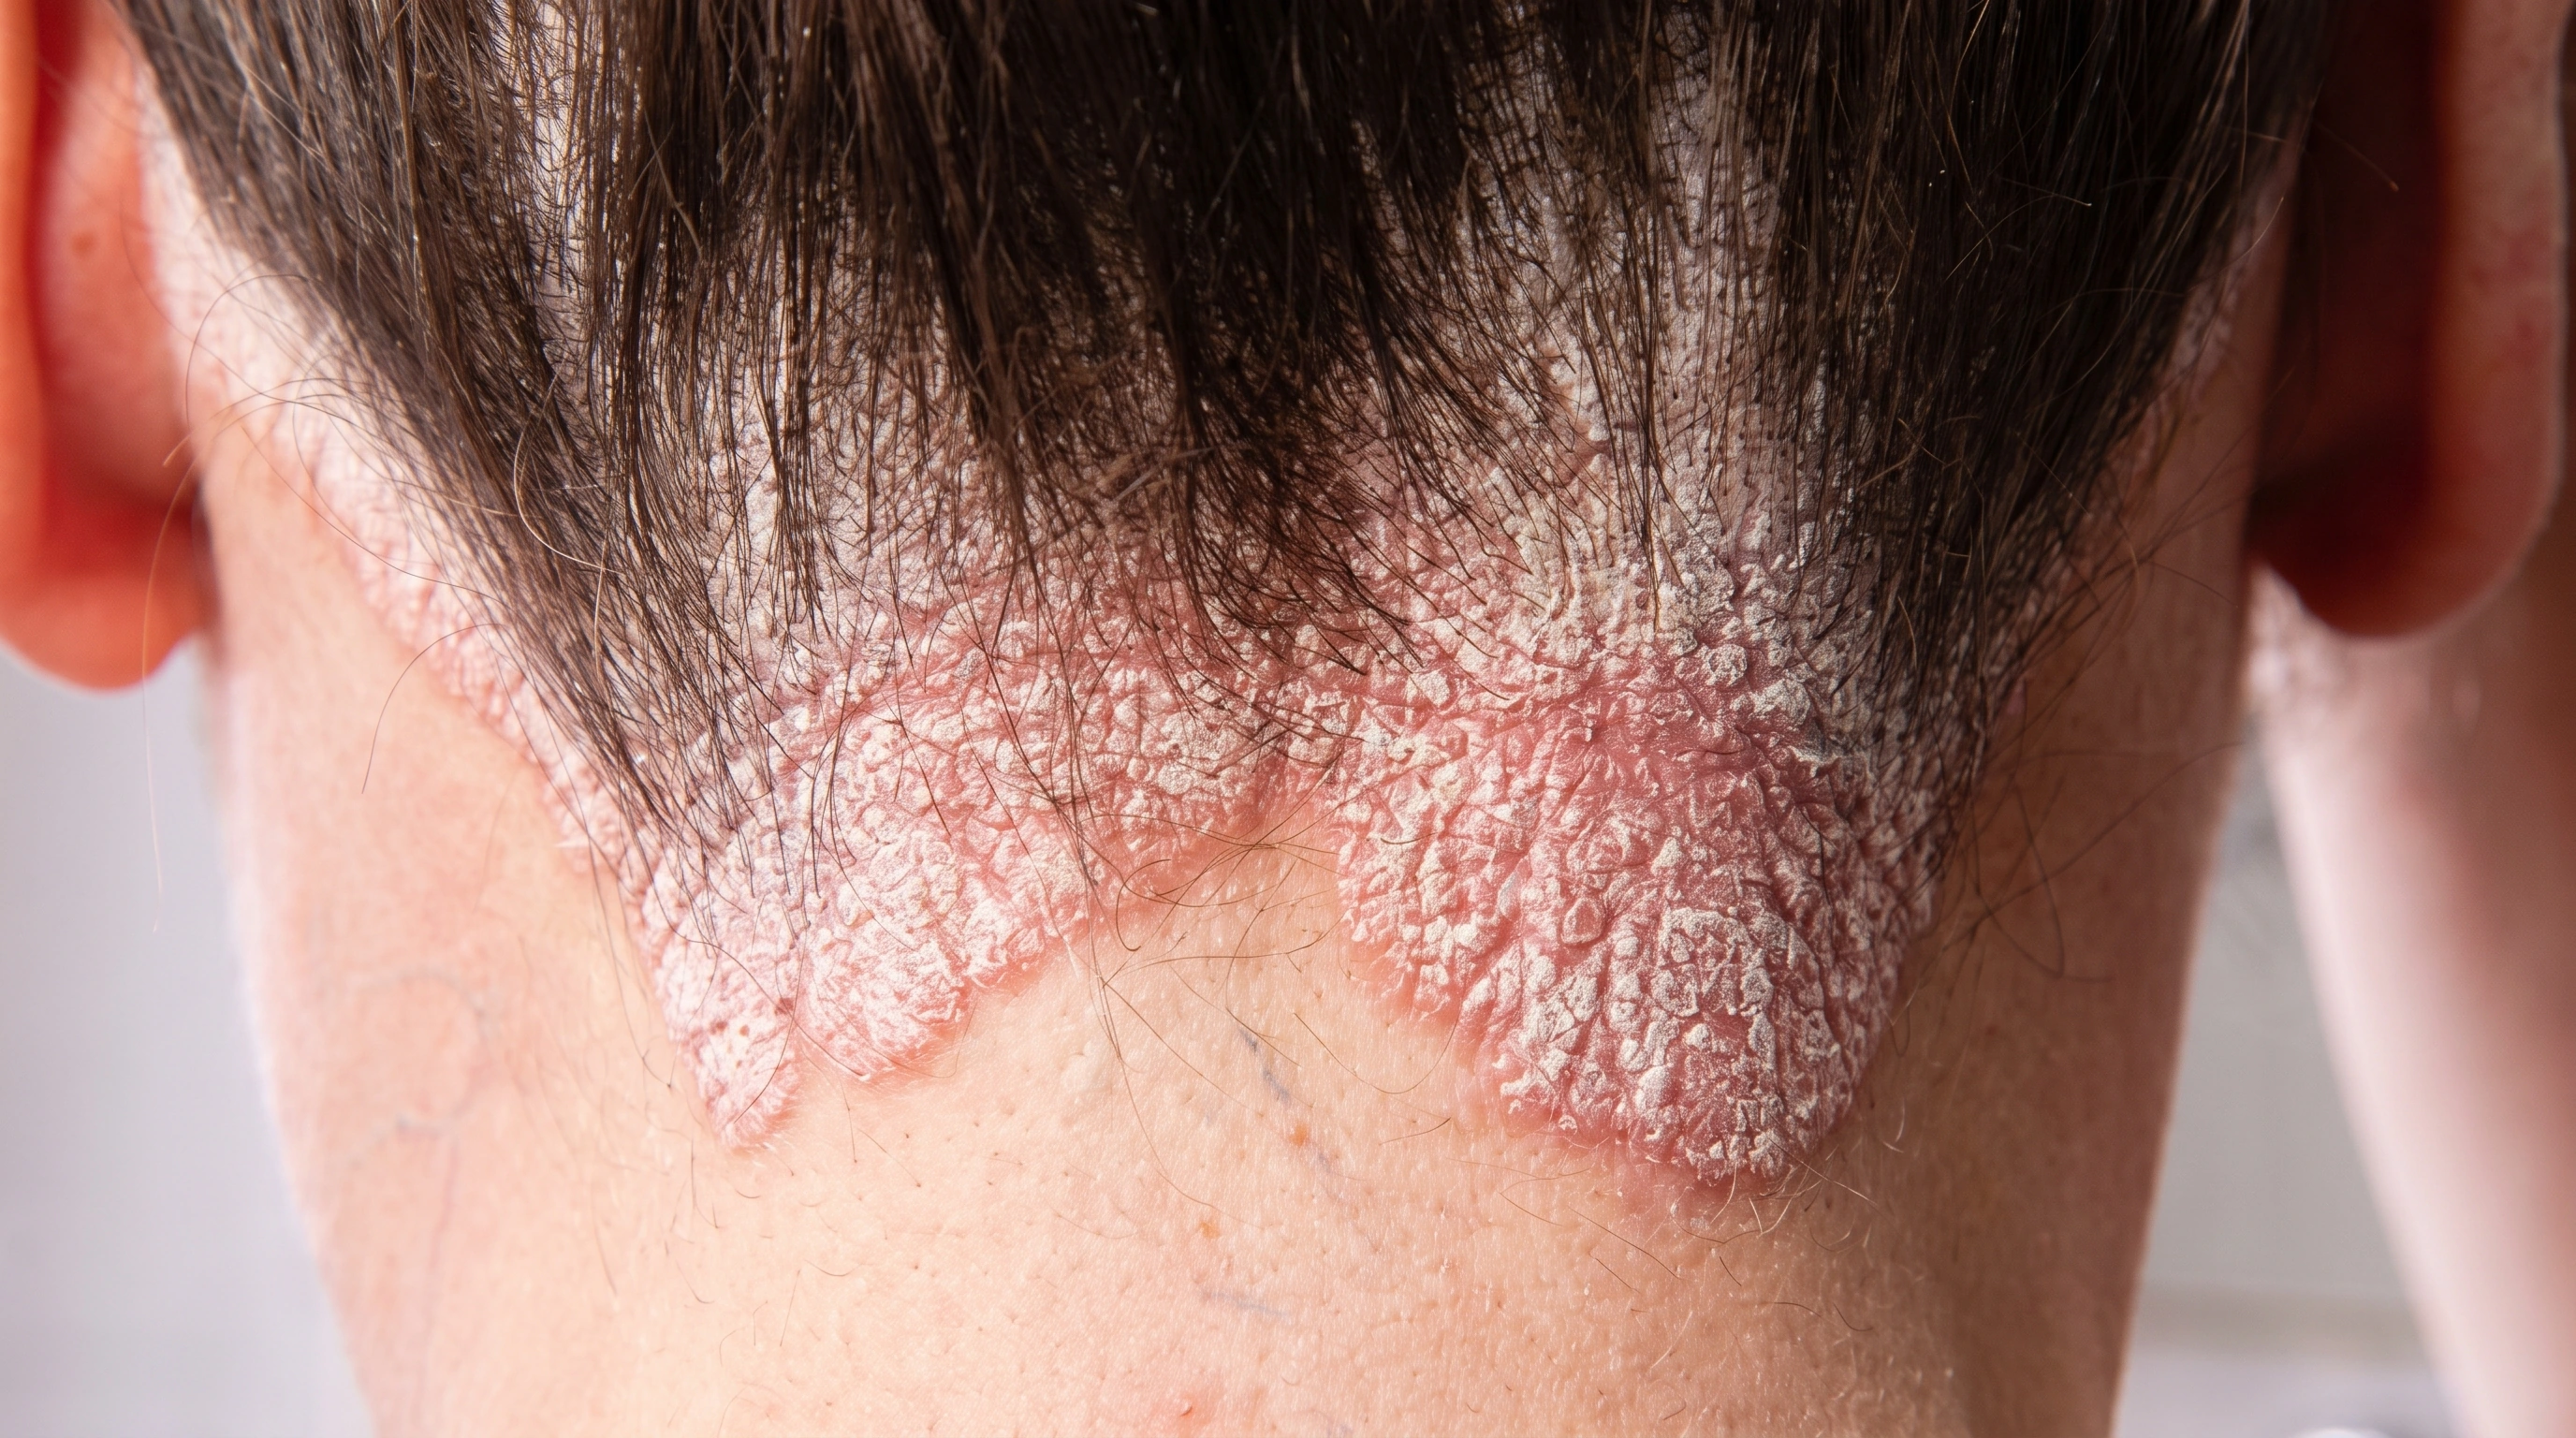
Scalp Psoriasis
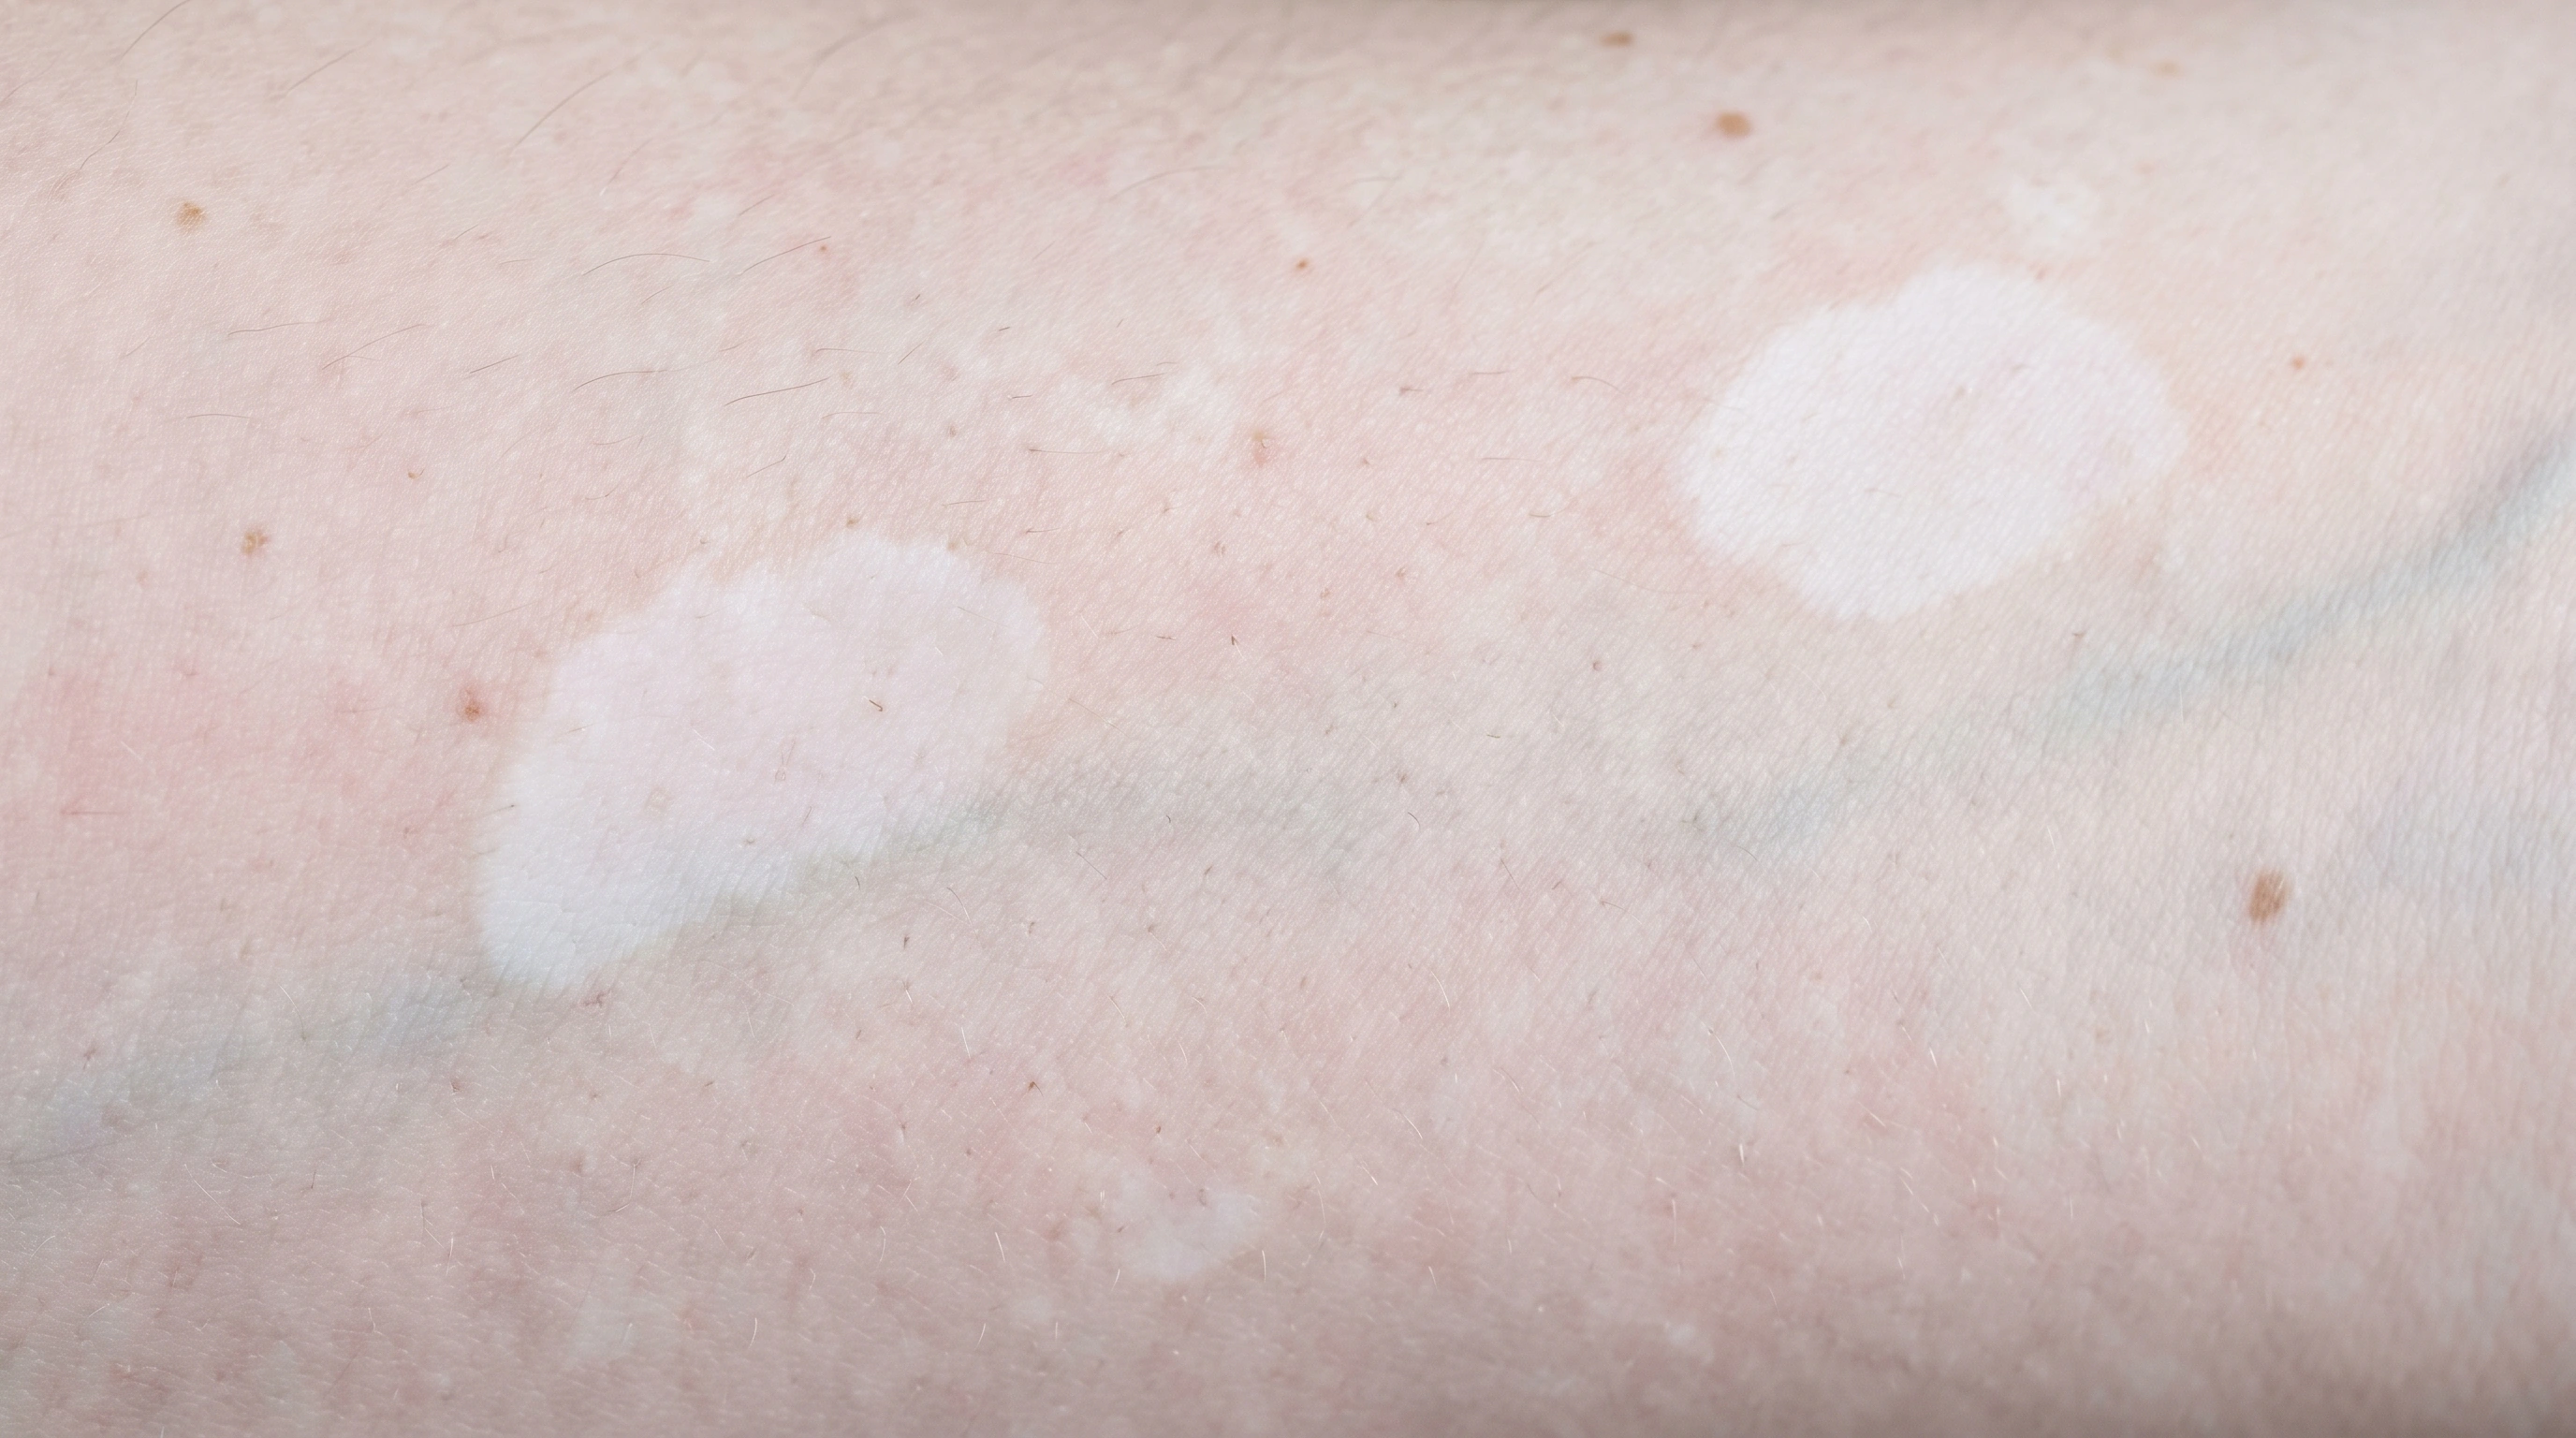
Vitiligo
Coal Tar
Seborrheic Dermatitis

Eczema
Salicylic Acid


Calcipotriene vs Clobetasol

Calcipotriene vs Cyclosporine

Calcipotriene vs Elidel
Calcipotriene vs Humira
