Perioral Dermatitis vs Eczema

Perioral dermatitis is a rash of small bumps and fine flaking around the mouth, and sometimes around the nose and eyes. Steroid creams are the most common trigger, and they are also what makes it worse in the long run. It clears with the right treatment, but slowly. Eczema is a group of long-term conditions in which the skin barrier leaks moisture and the immune system in the skin overreacts. Atopic dermatitis is the most common kind. The result is skin that is dry, itchy and inflamed, in flares that come and go. It is controlled rather than cured, and most of it responds well to treatment used properly.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
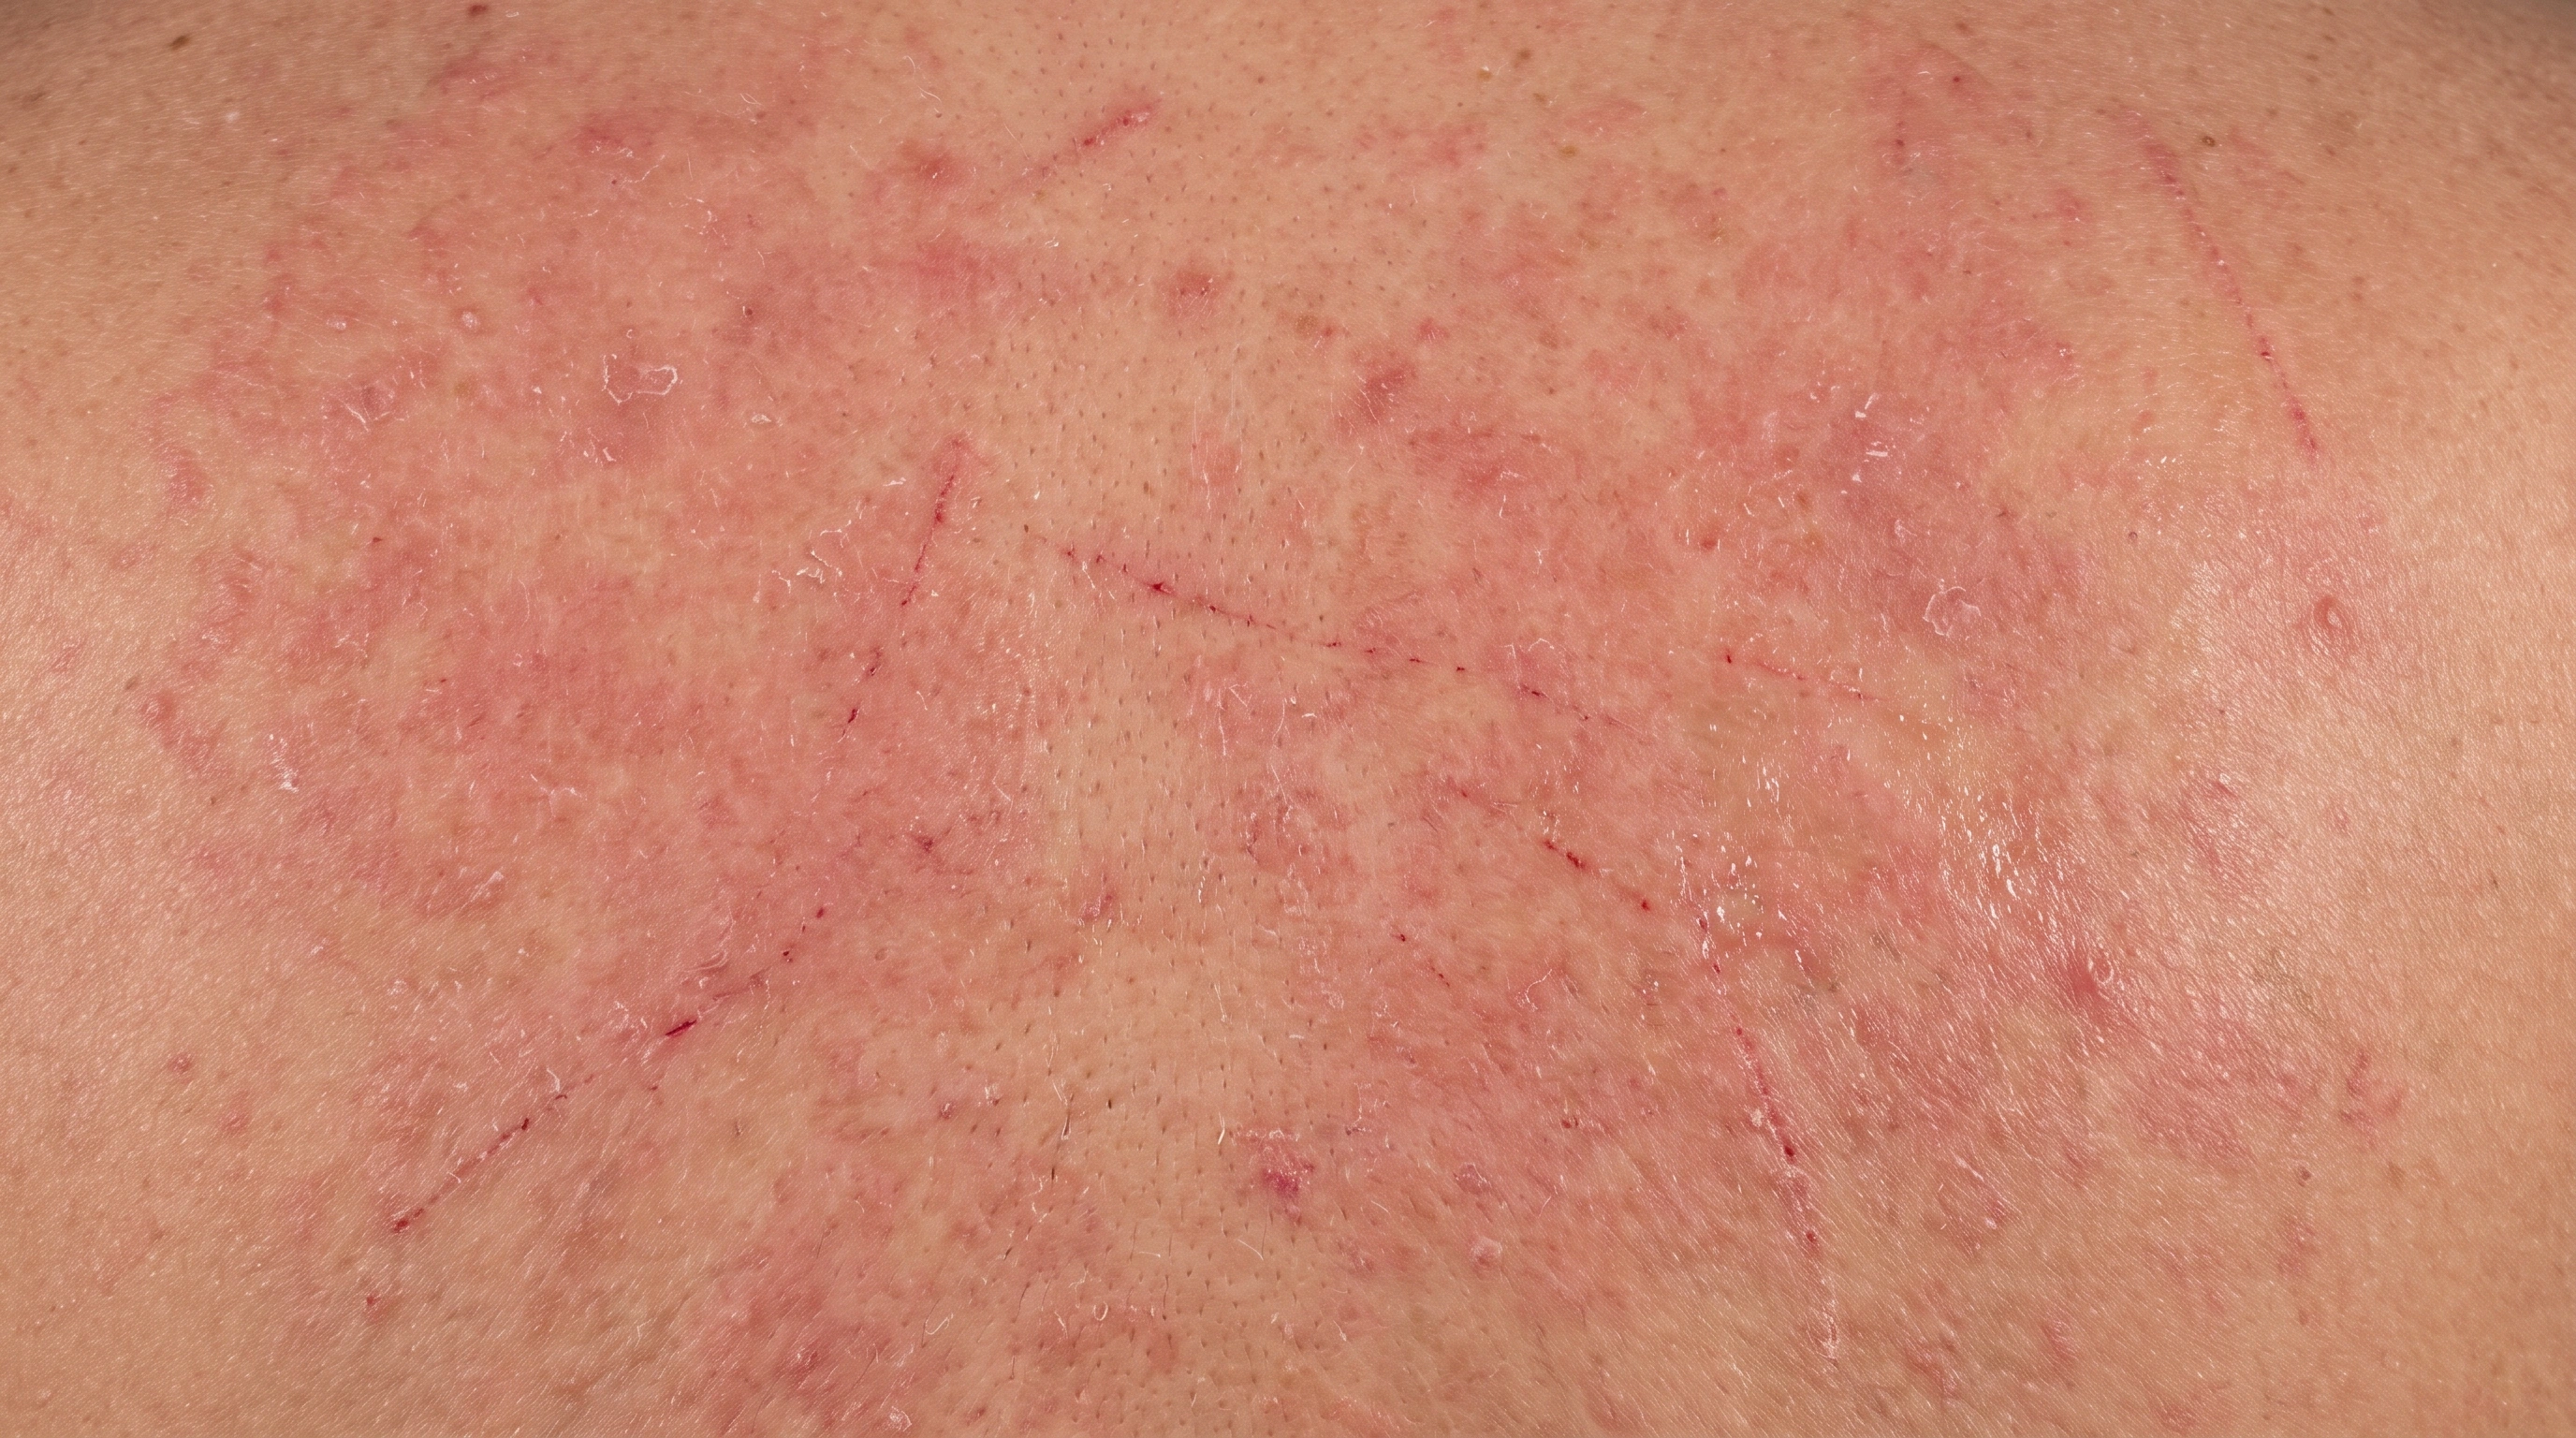
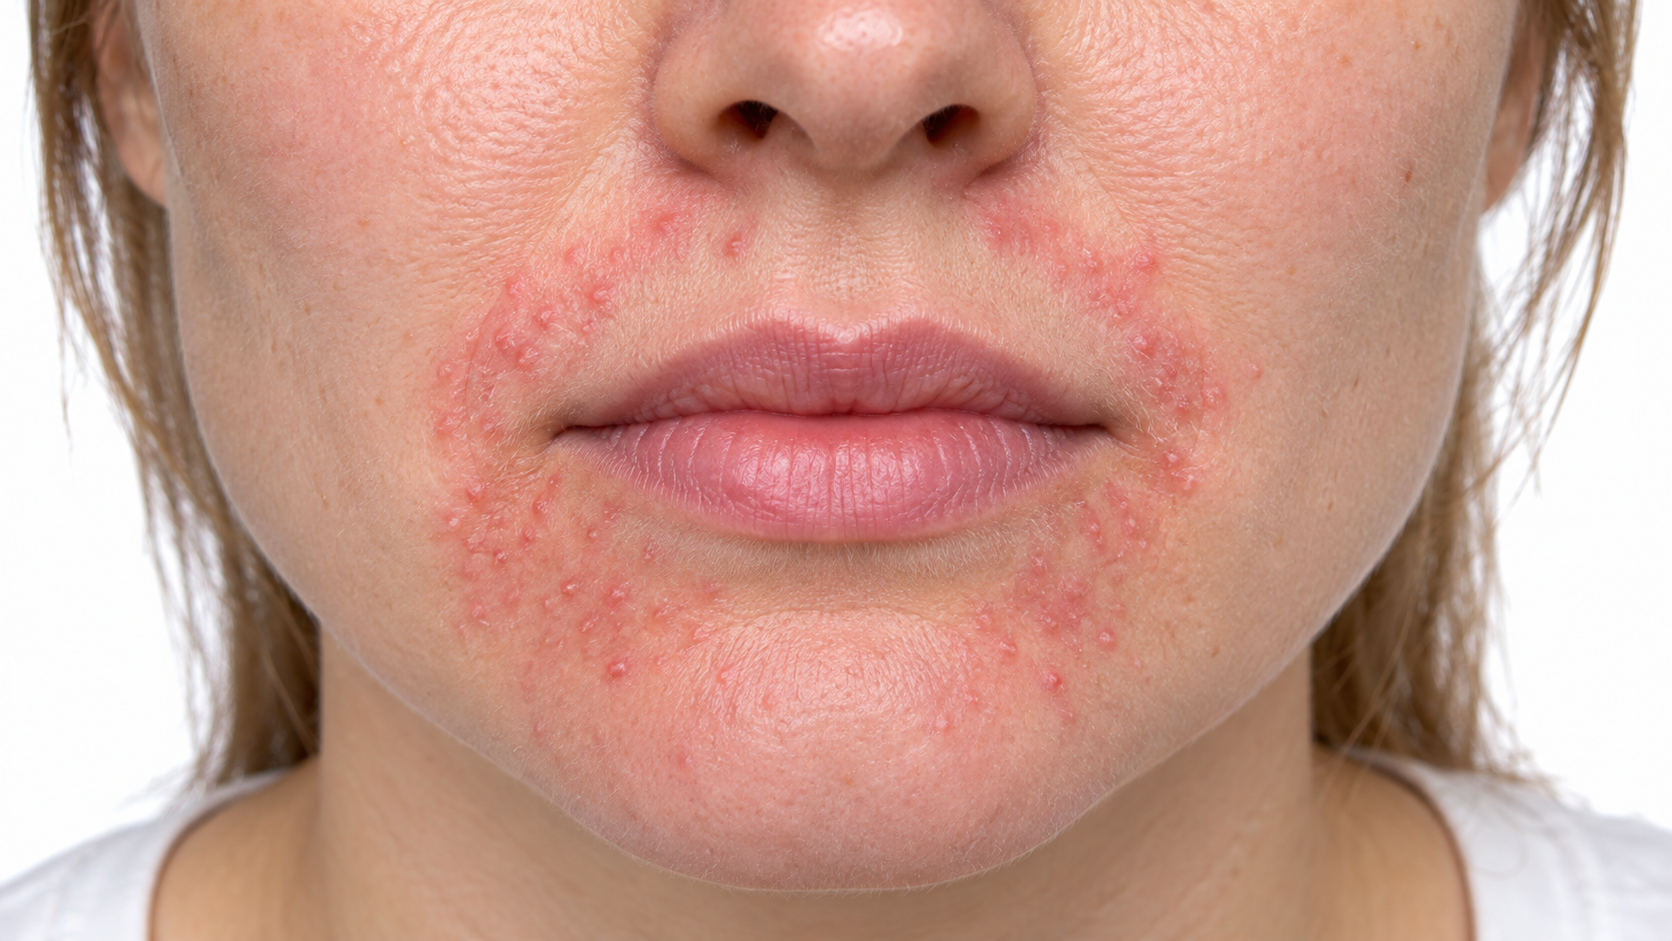
AI-generated educational illustration of Perioral Dermatitis: 1. Perioral Dermatitis Header — Light Skin; Lighter skin. Not a clinical photograph.Extreme close-up of light skin in an active eczema flare, too close to tell which part of the body it is. Blotchy pink-red inflammation covers the whole frame with no clear edge, with small raised bumps, fine dry scale and a few fresh scratch marks.

Key differences

The same eight facts on every condition comparison.

Usual age
20 to 45
Infancy and childhood
Where
Around mouth, nose, eyes
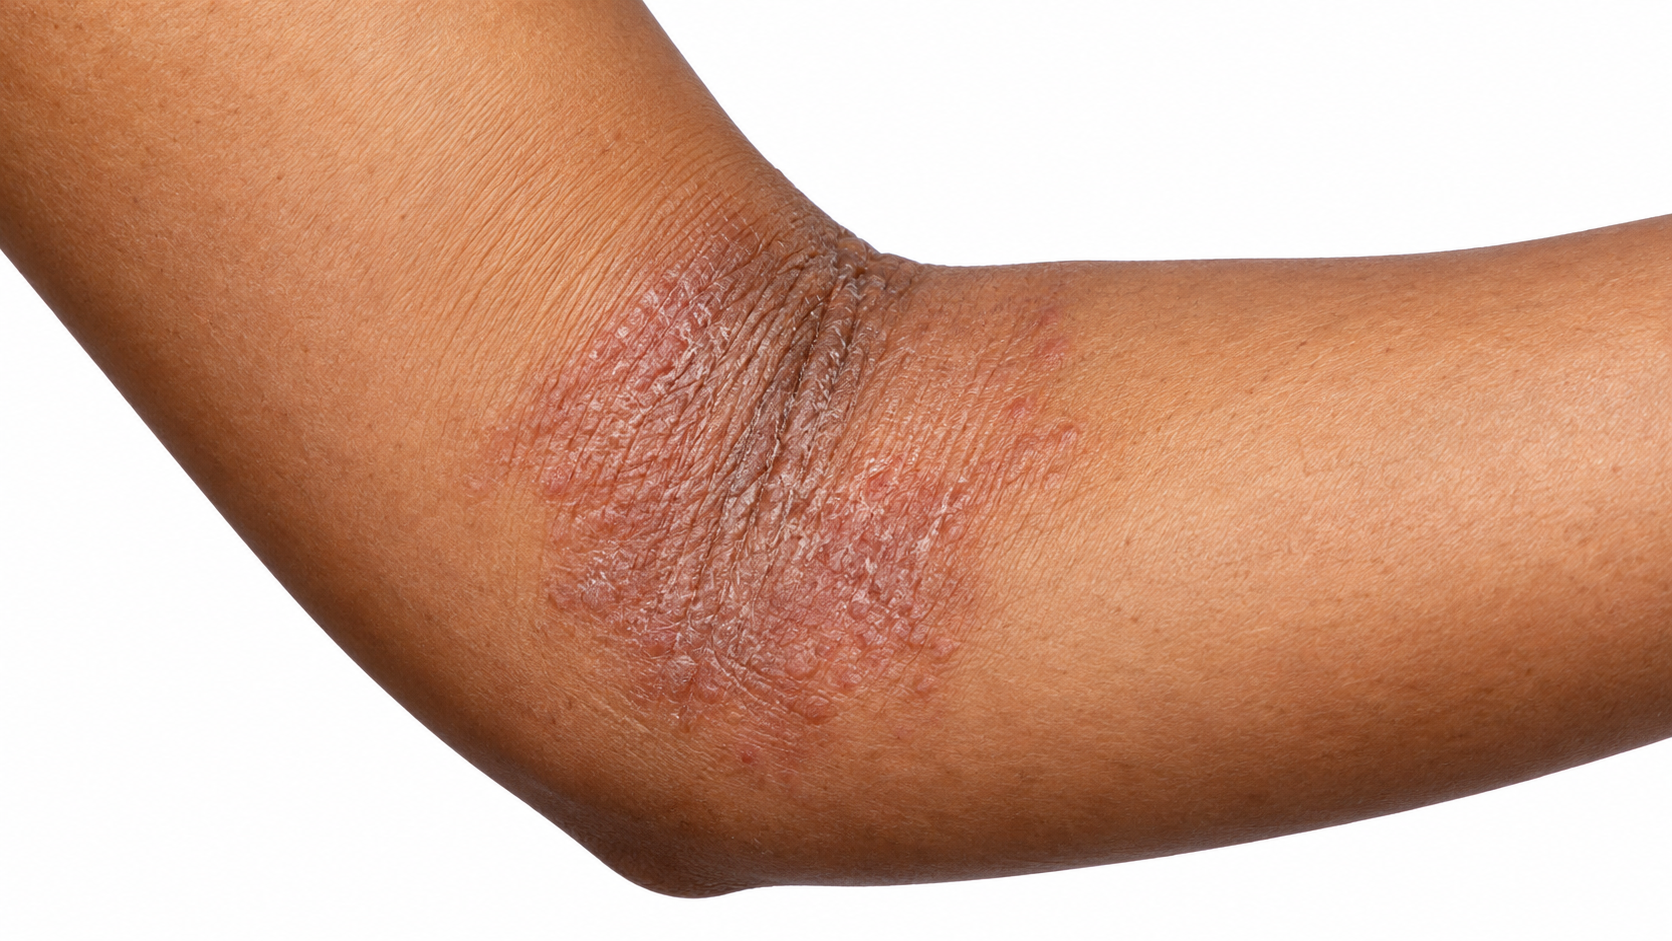
Elbow and knee creases, face, hands
Main sign
Tiny bumps with a clear rim by the lips
Dry, itchy, inflamed patches
Itch or pain
Burning more than itch
Very itchy
Contagious
No
No
Long term
Clears in weeks to months
Comes and goes; often improves with age
Scars
No
No
Who gets it
Mostly women; steroid cream users
Family history of eczema, asthma, hay fever

What is it?

Perioral Dermatitis
Eczema
What is it?

It is a facial eruption.
Small inflamed bumps form around the mouth, nose or eyes.

The skin often feels uncomfortable.
It may feel dry, tight, burning or scaly.

The lip border is often spared.
A narrow clear zone beside the lip is common.

Simpler routines help.
Harsh actives, heavy products and steroid self-treatment can worsen it.

It is a recurring inflammatory condition.
Atopic eczema involves a vulnerable barrier and an itch–scratch cycle.

Several factors reinforce each other.
Dryness, irritants, inflammation and scratching feed one another.

It is not about cleanliness.
Vigorous cleansing can make eczema worse.

Care has two parts.
Emollients protect the barrier, while anti-inflammatory treatment settles active flares.

What it looks like

Perioral Dermatitis

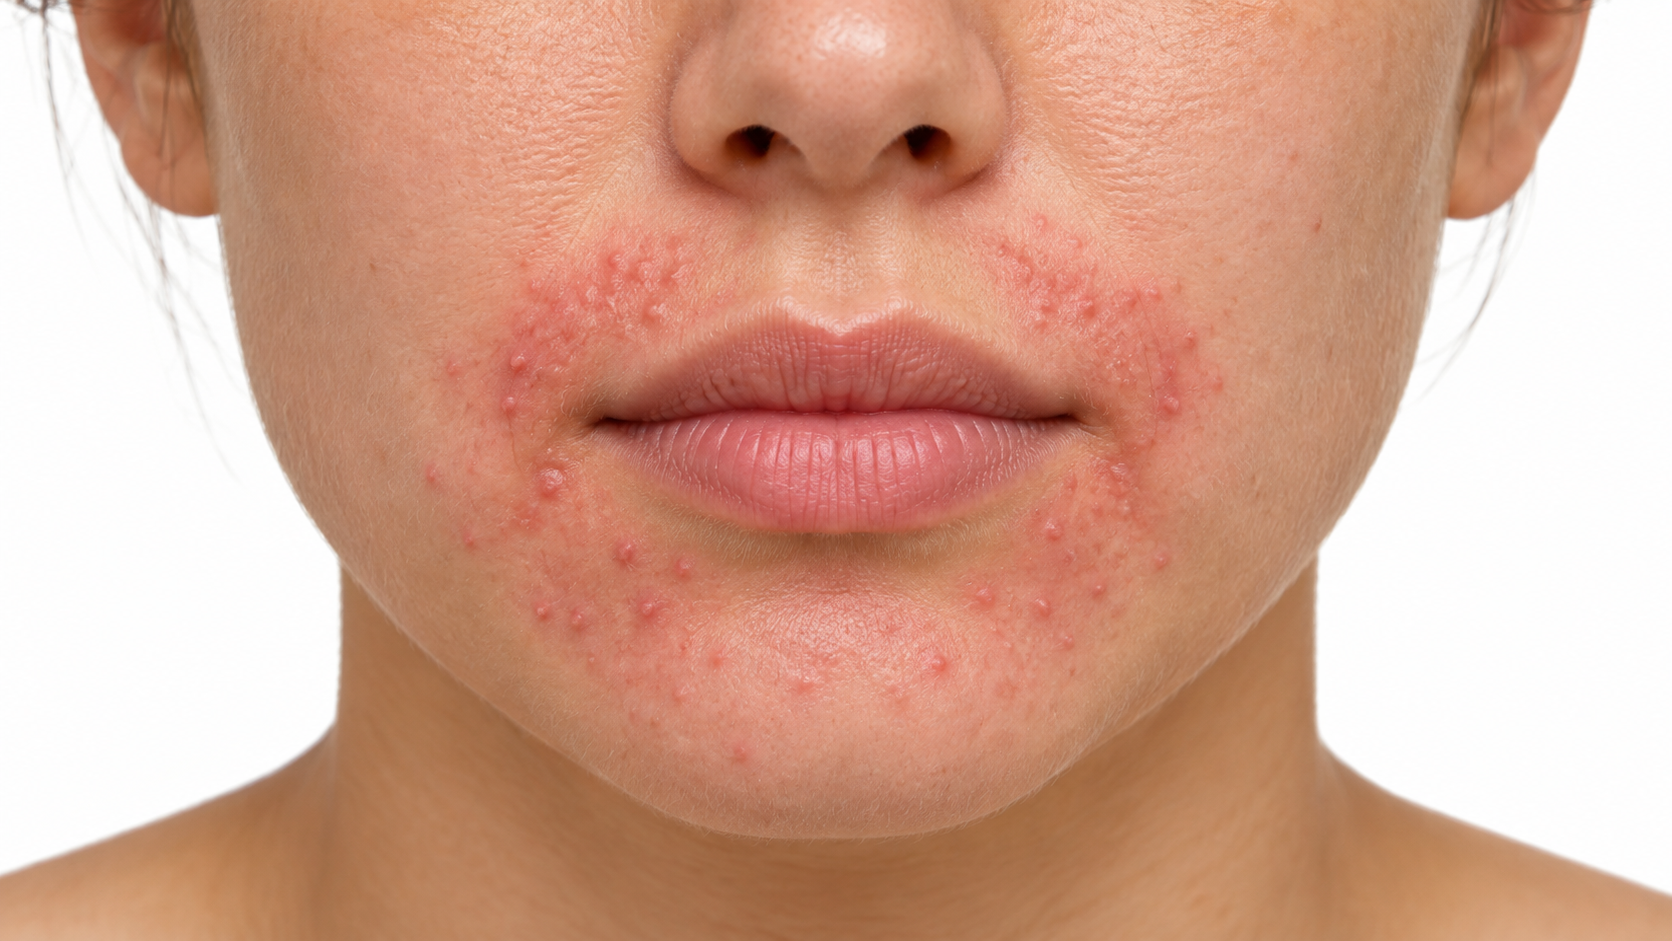
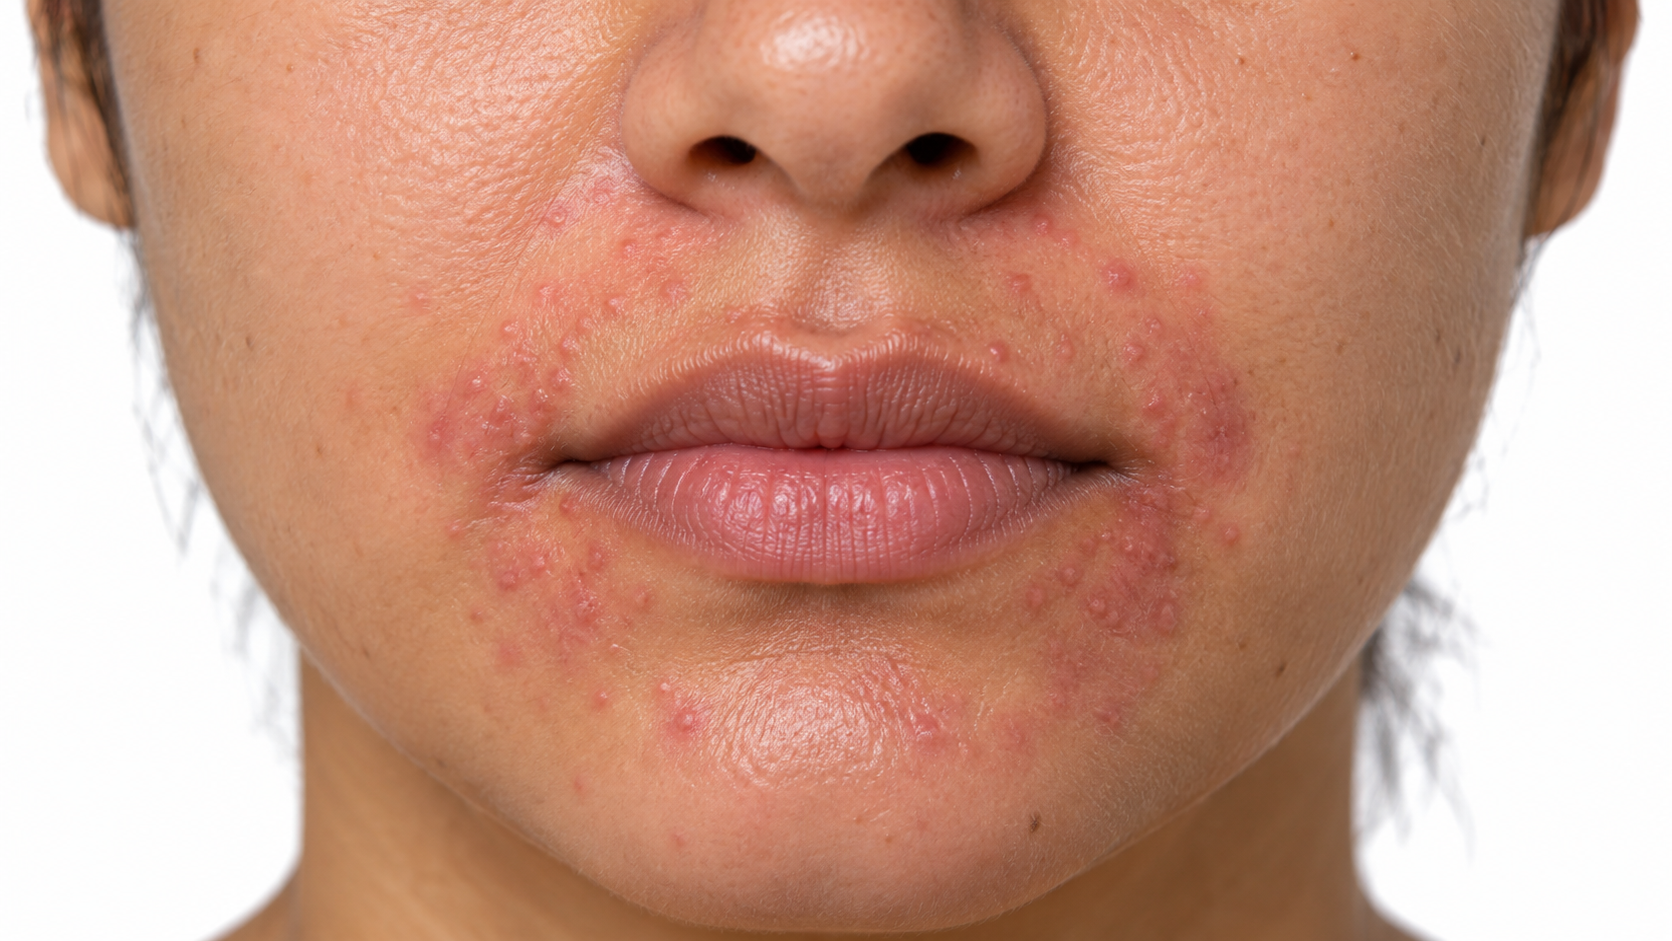
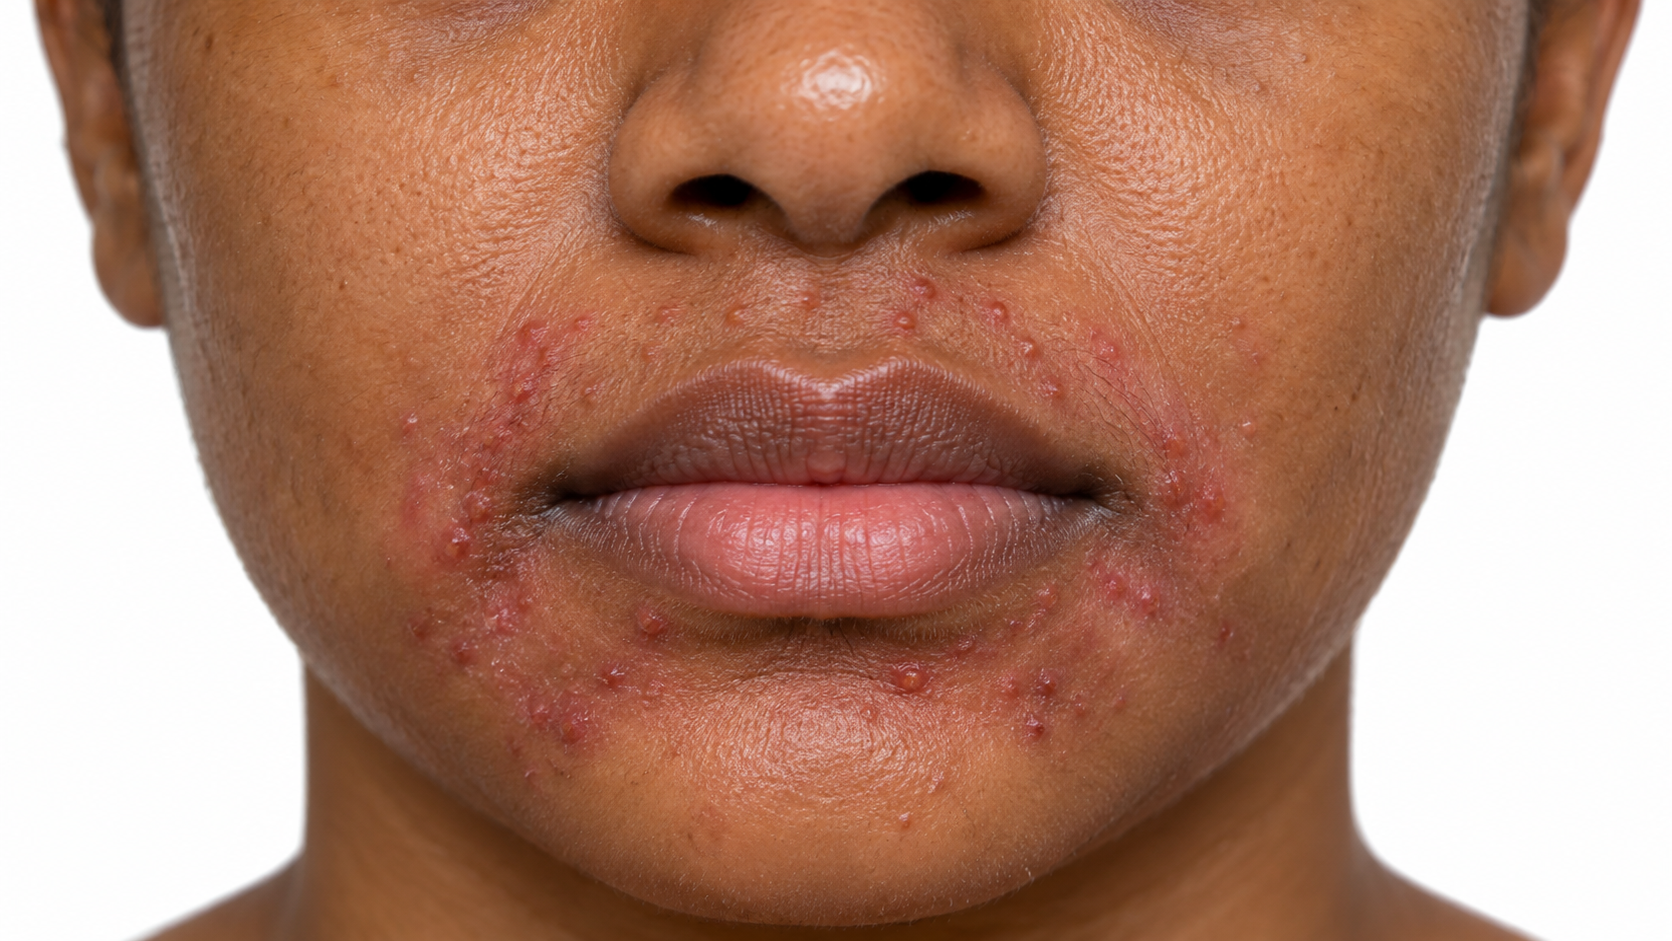
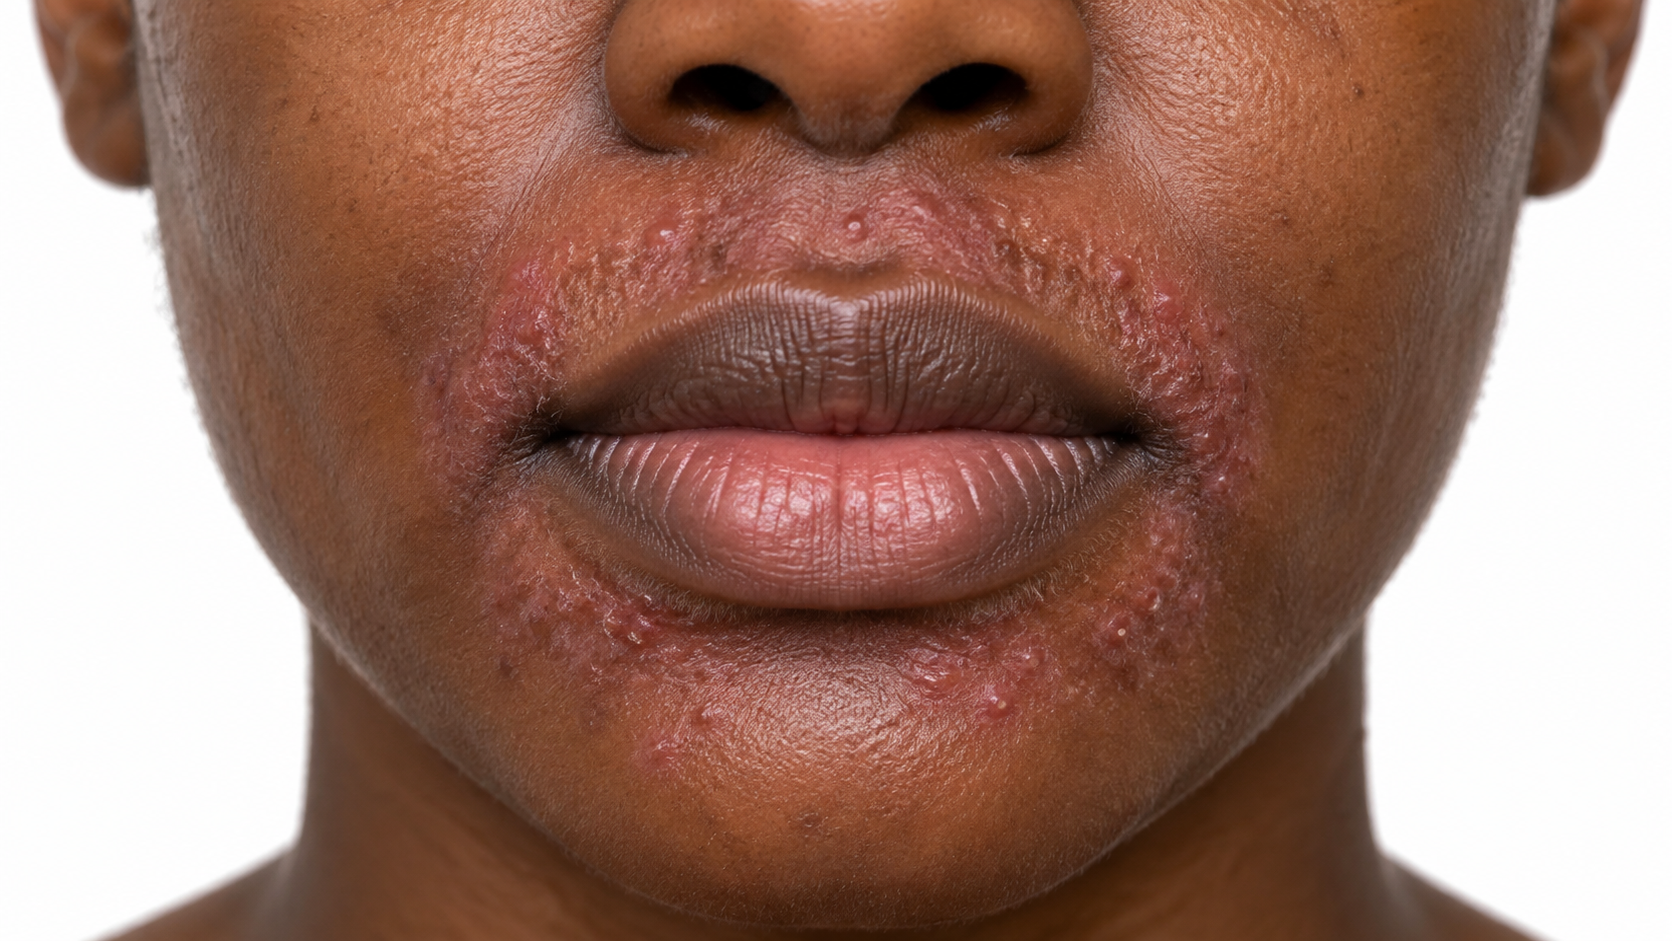
Perioral Dermatitis: Bumps around the mouth; Clear lip border; Perioral.

Perioral dermatitis Around the mouth.

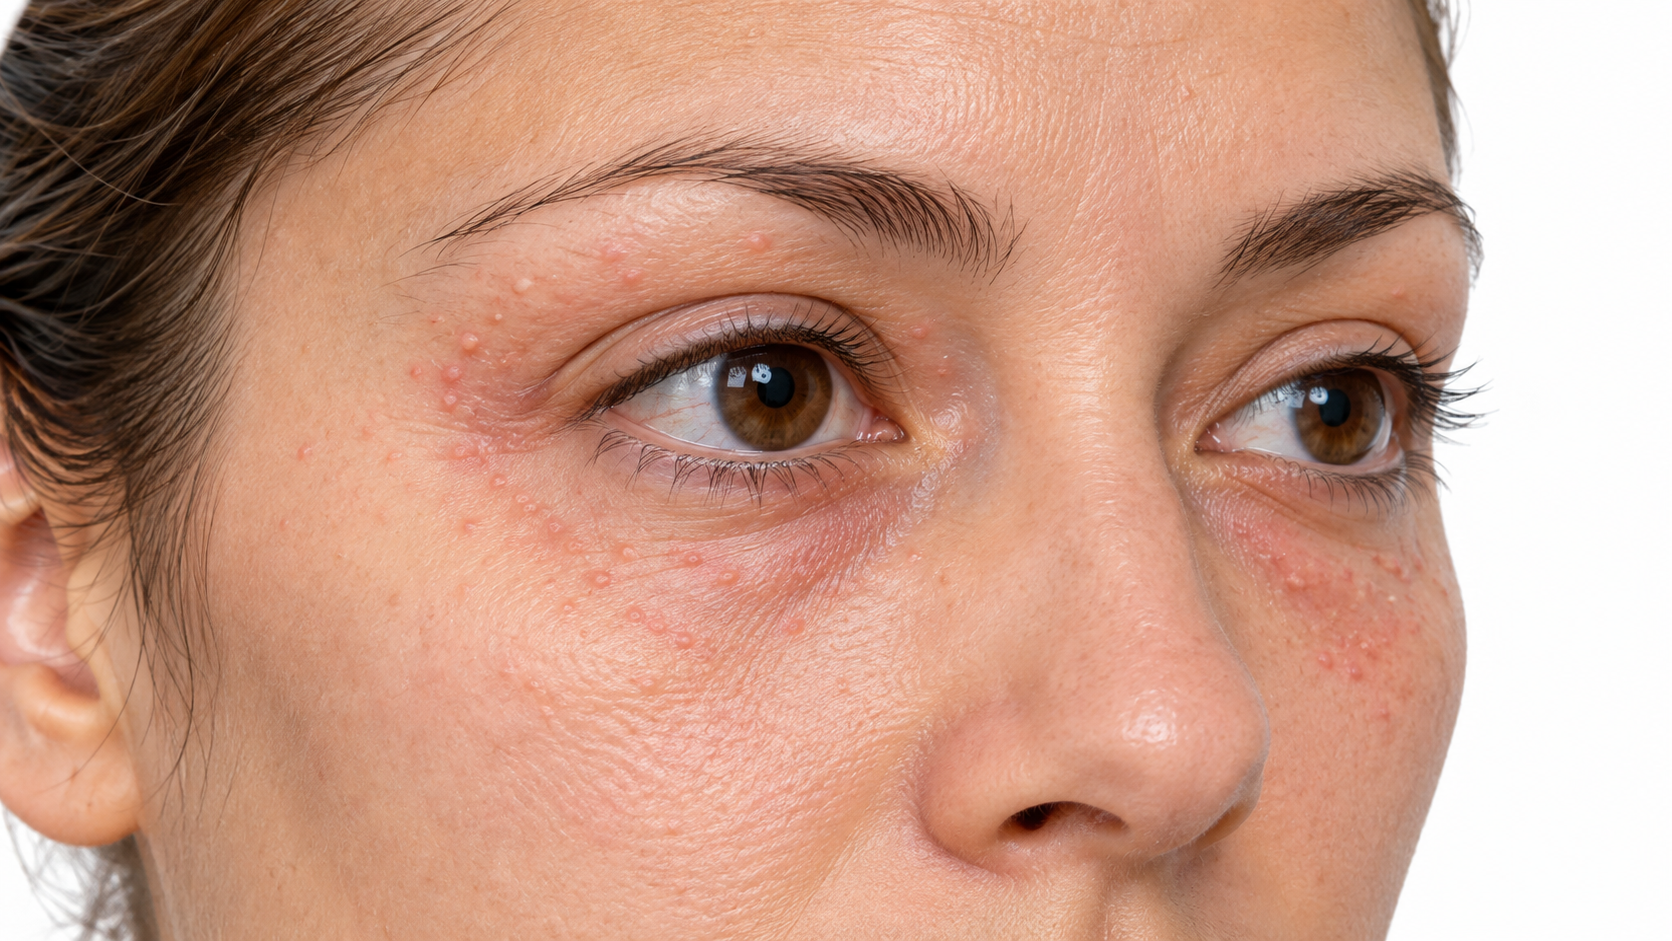
Perioral Dermatitis: Periorbital.

Periorbital dermatitis Around the eyes.

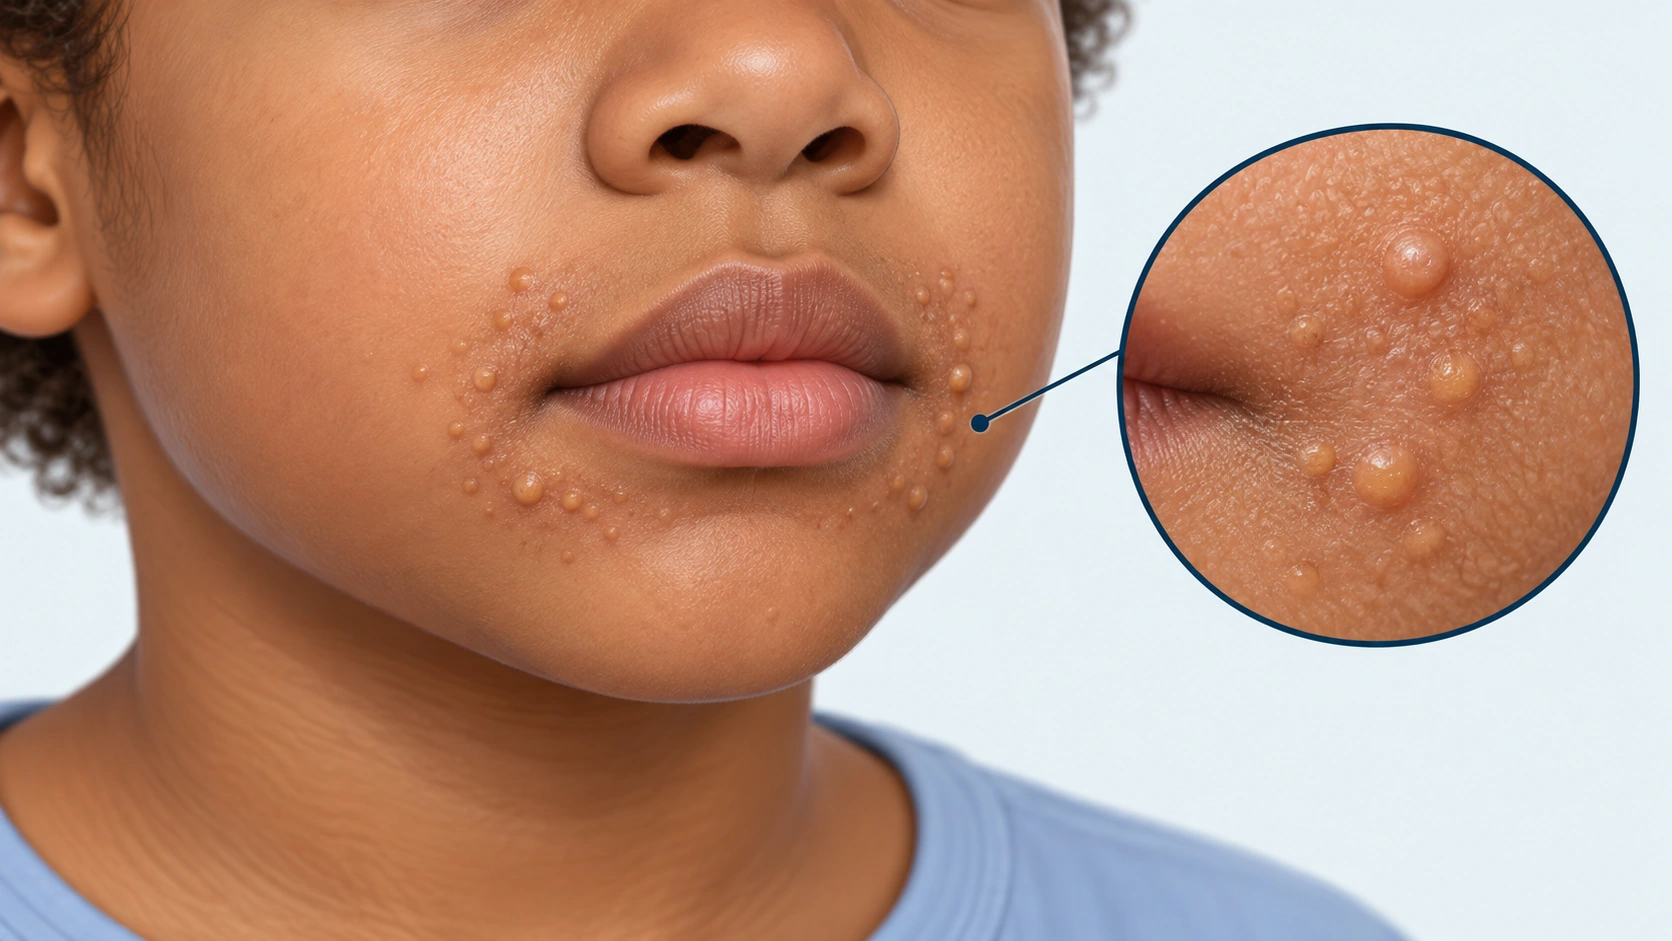
for Granulomatous (Perioral Dermatitis).

Granulomatous periorificial dermatitis Skin-colored or yellow bumps, often in children.

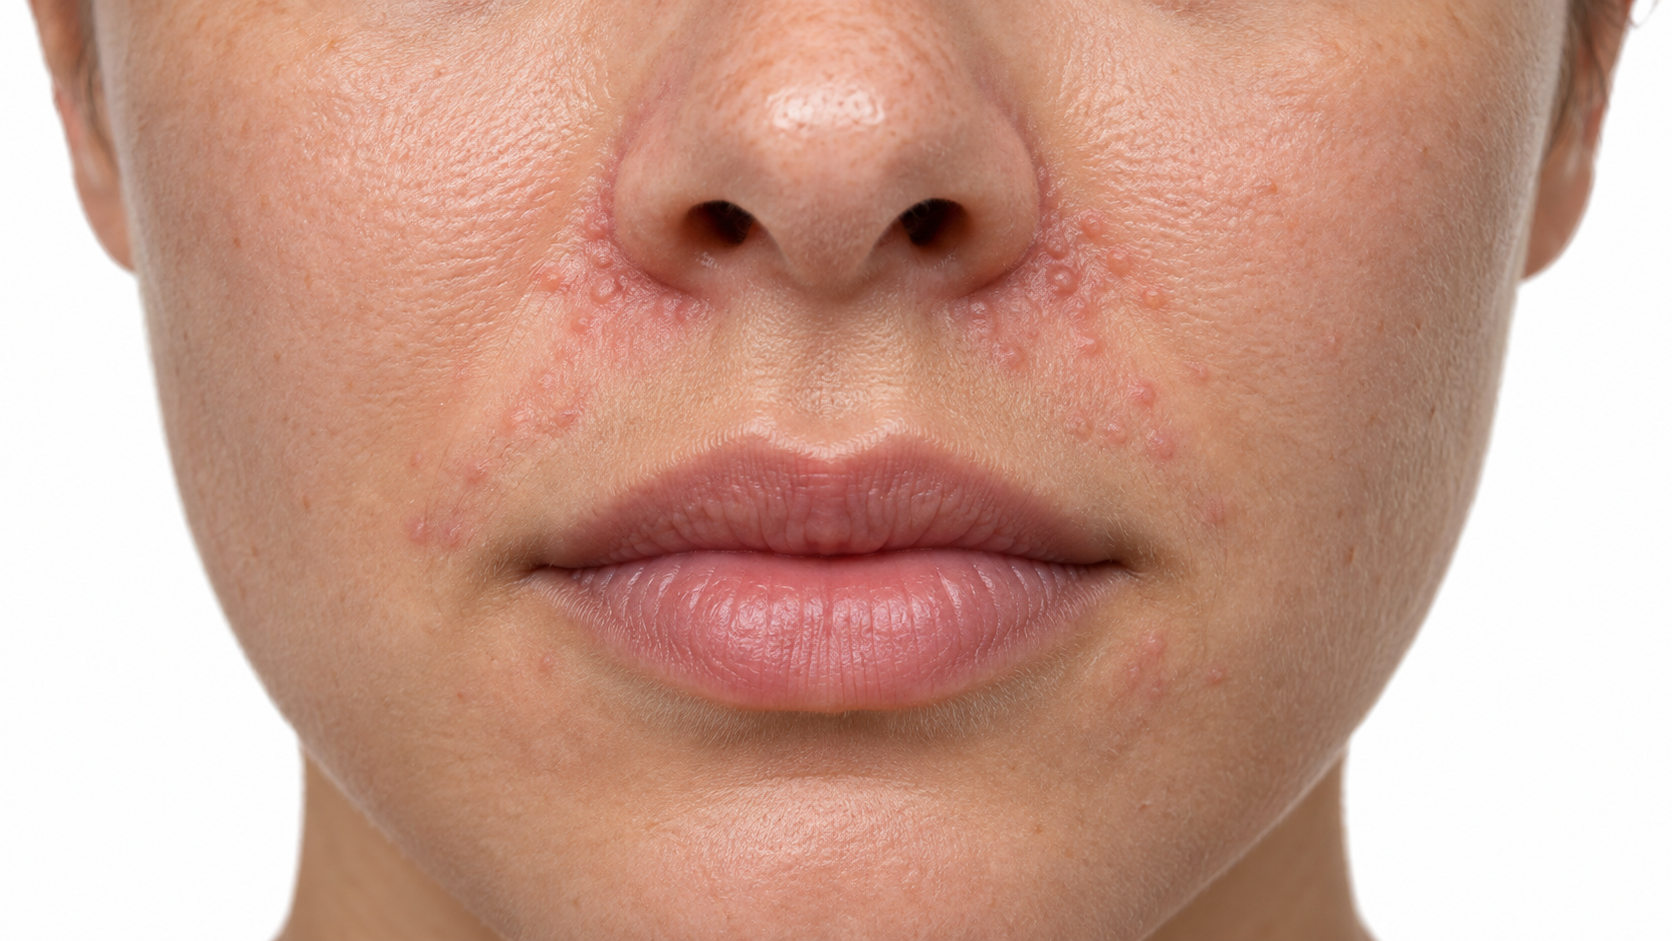
Perioral Dermatitis: Around the nose.

Perinasal dermatitis Can spread to the nose folds.

Eczema

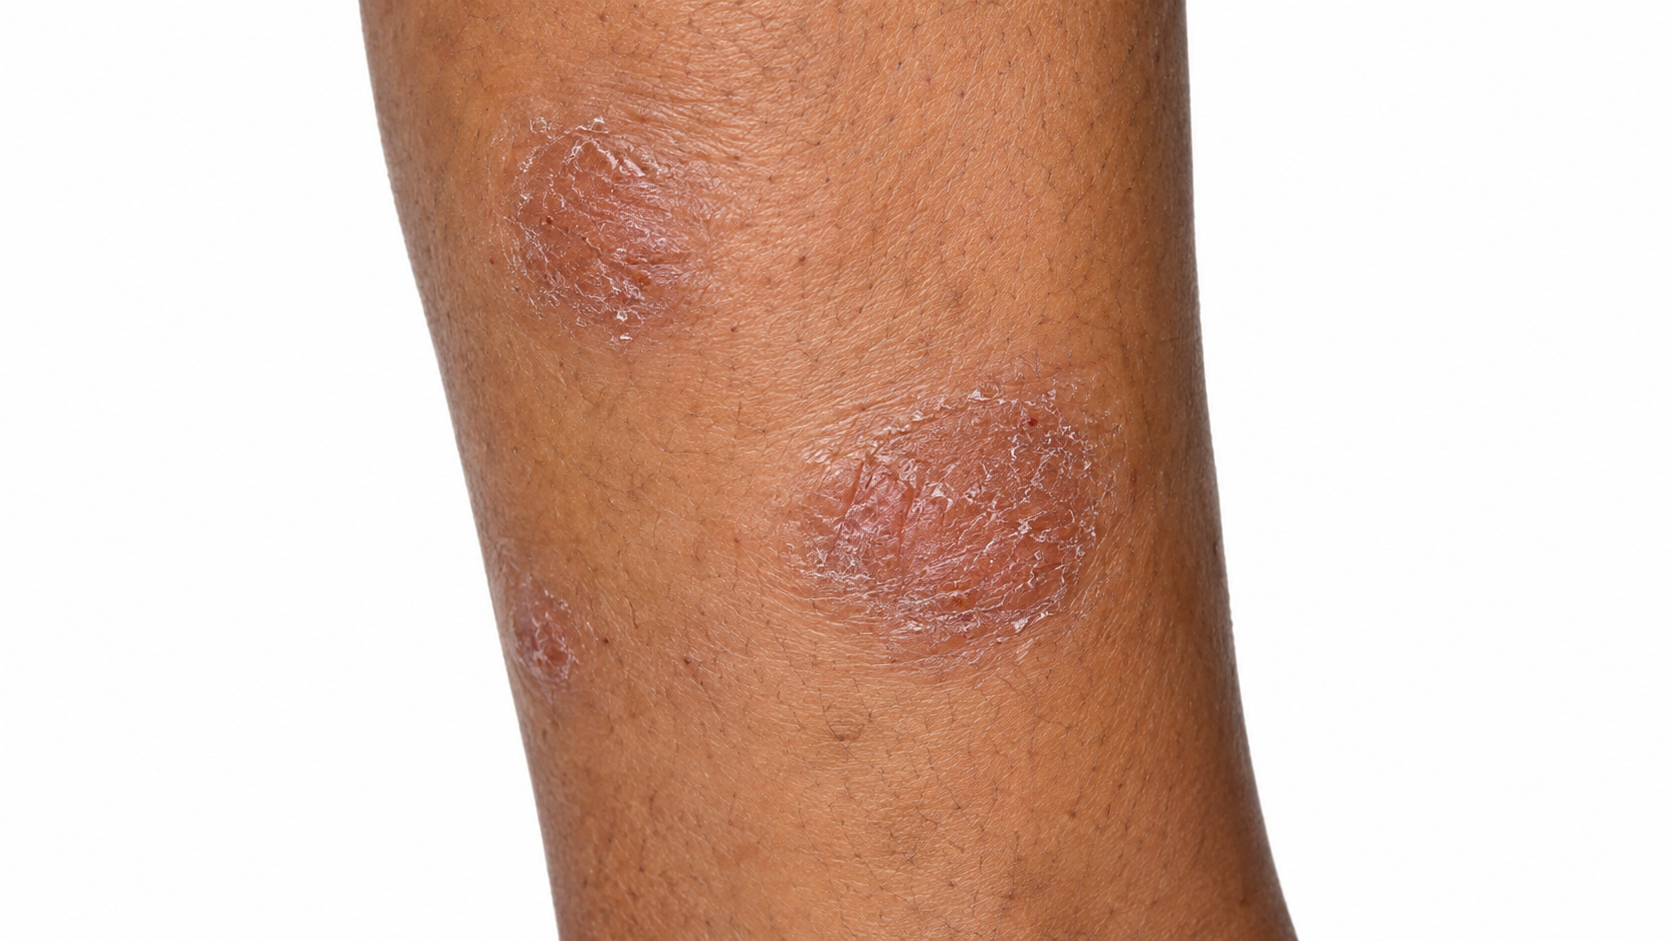
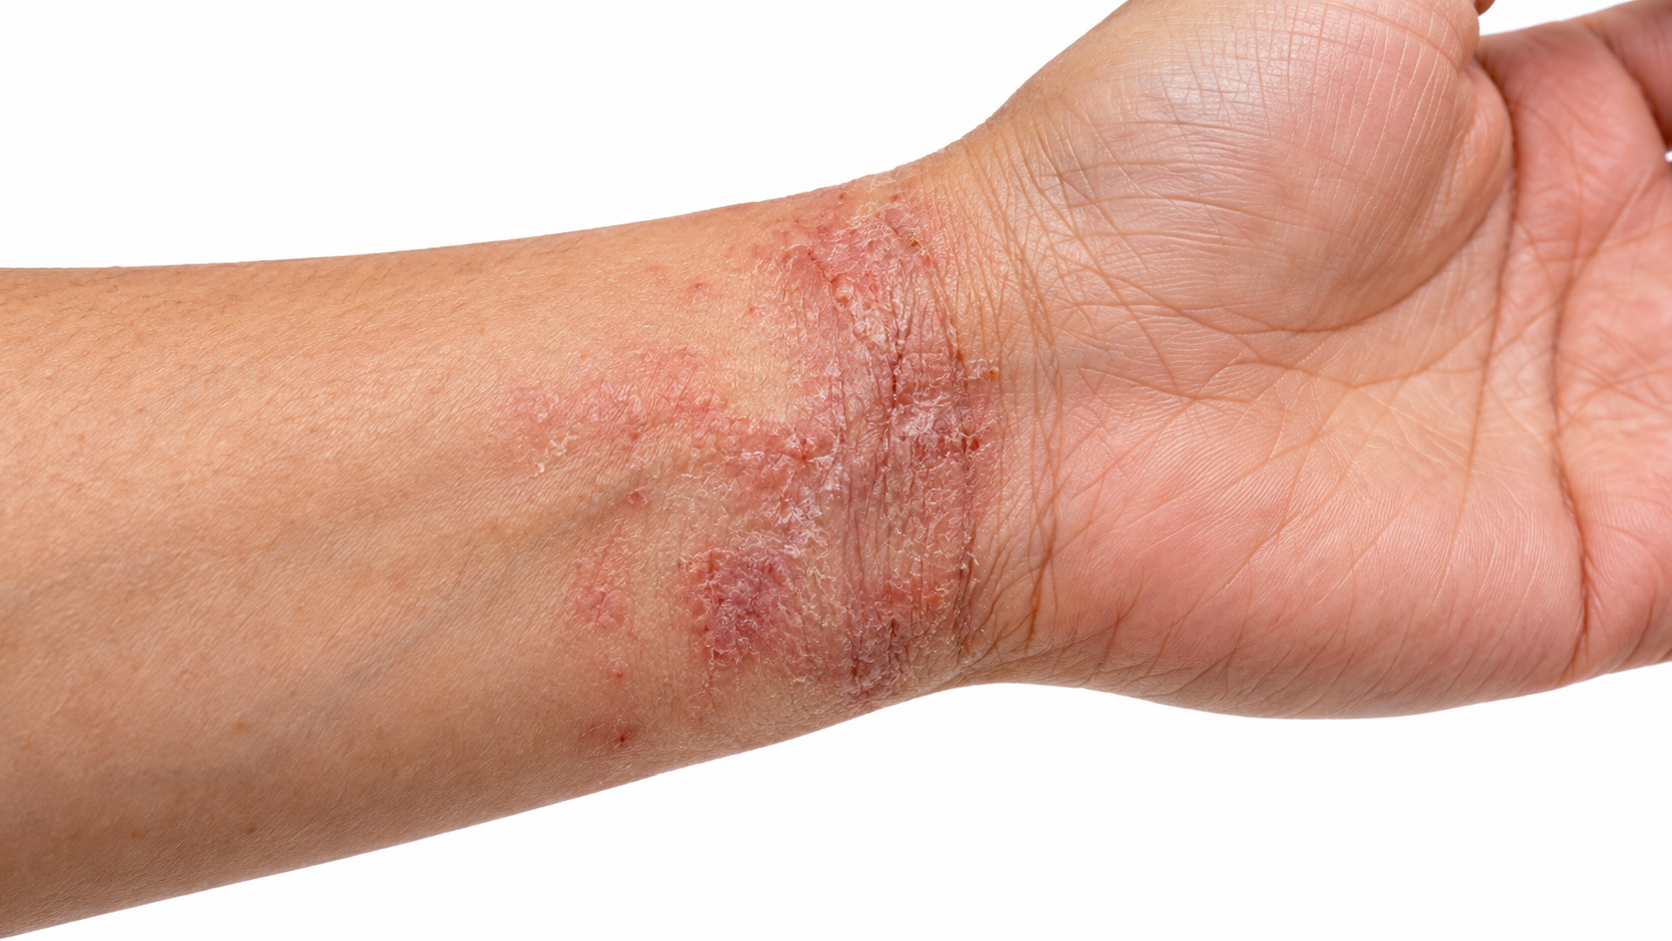
Eczema: Dry, itchy patches.

Atopic dermatitis Long-term, starts in childhood.

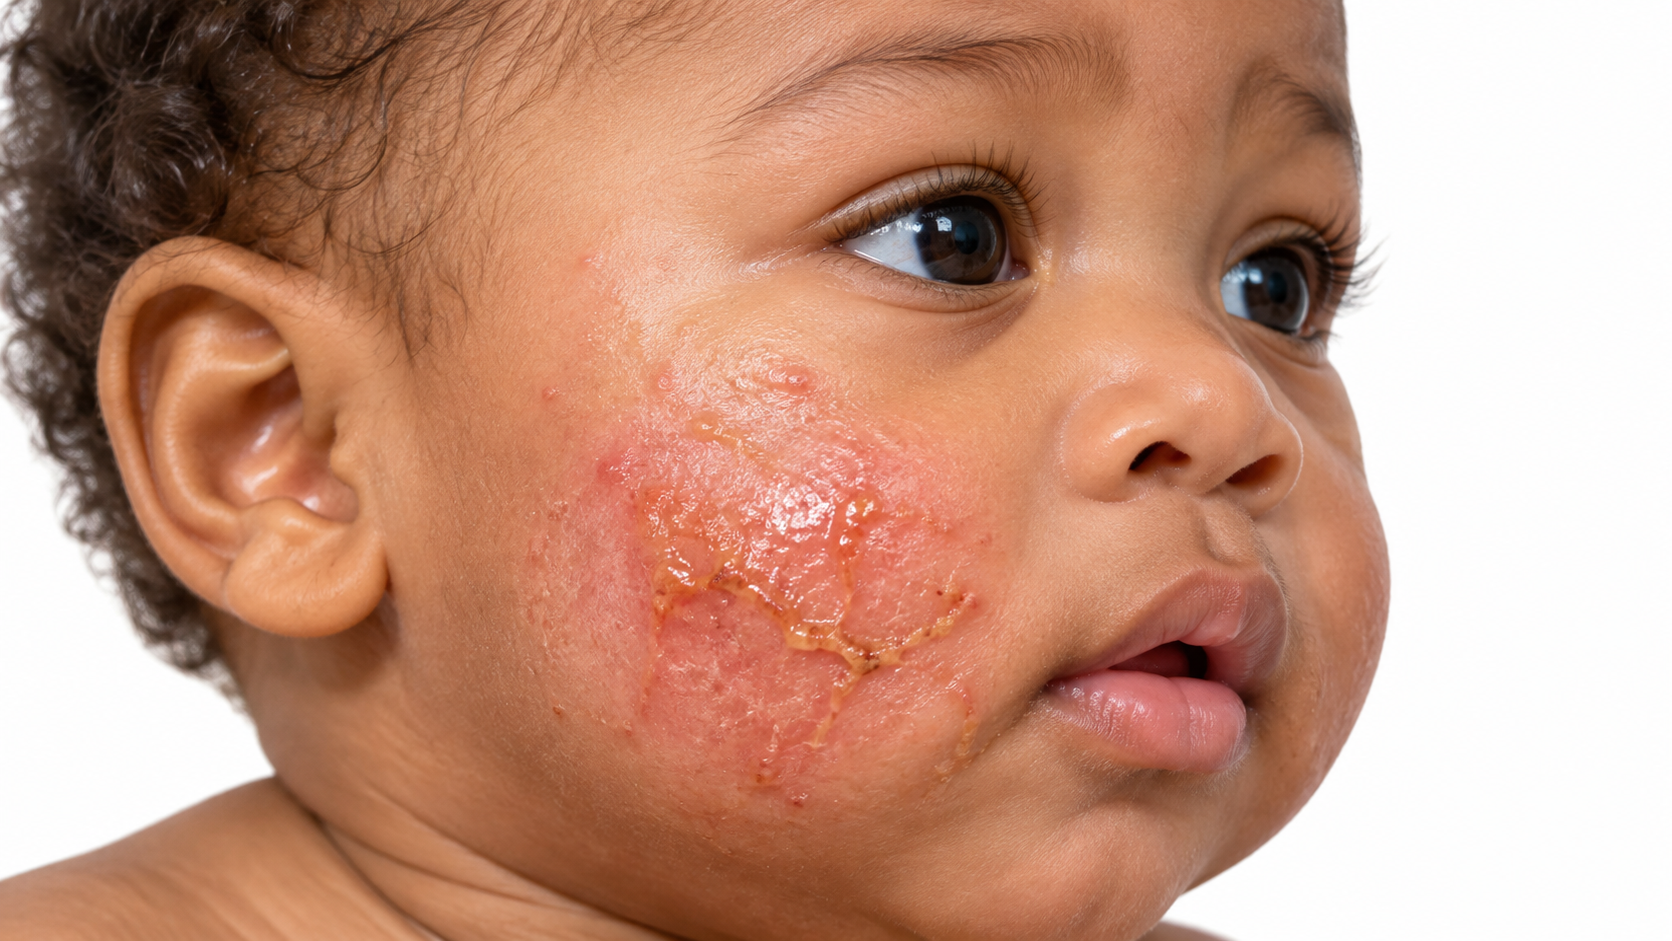
Inflamed, rough patches affect the cheeks.

Infant facial eczema Inflamed, rough patches affect the cheeks.

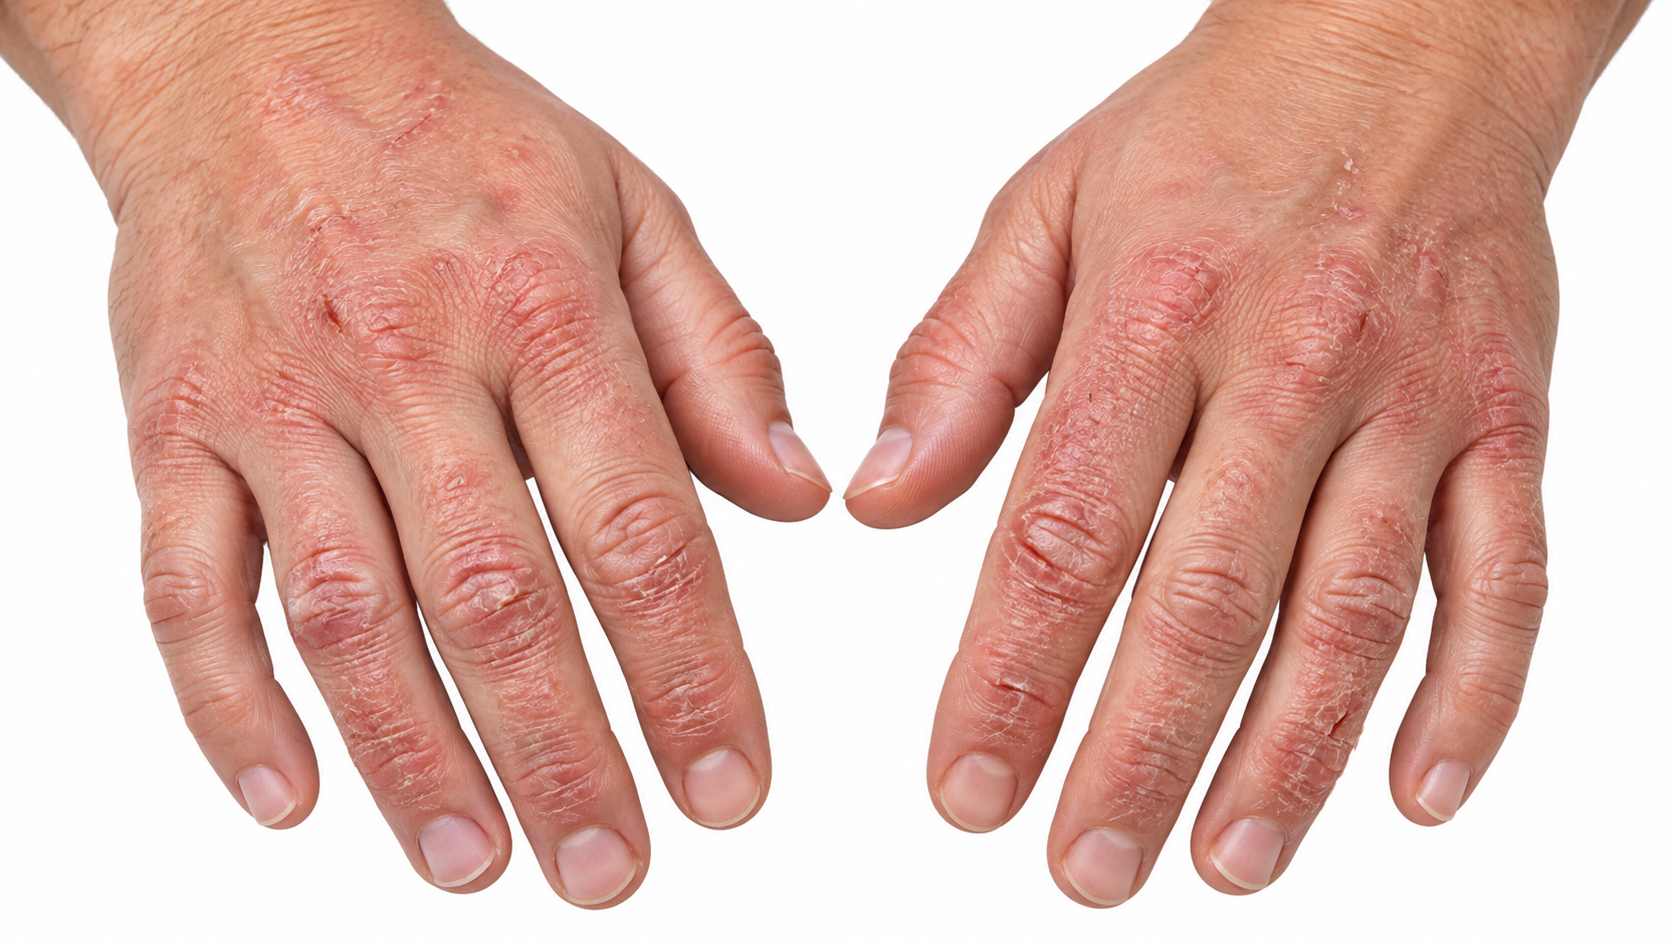
Eczema: Hand.

Hand eczema Dry, cracked or blistered hands.

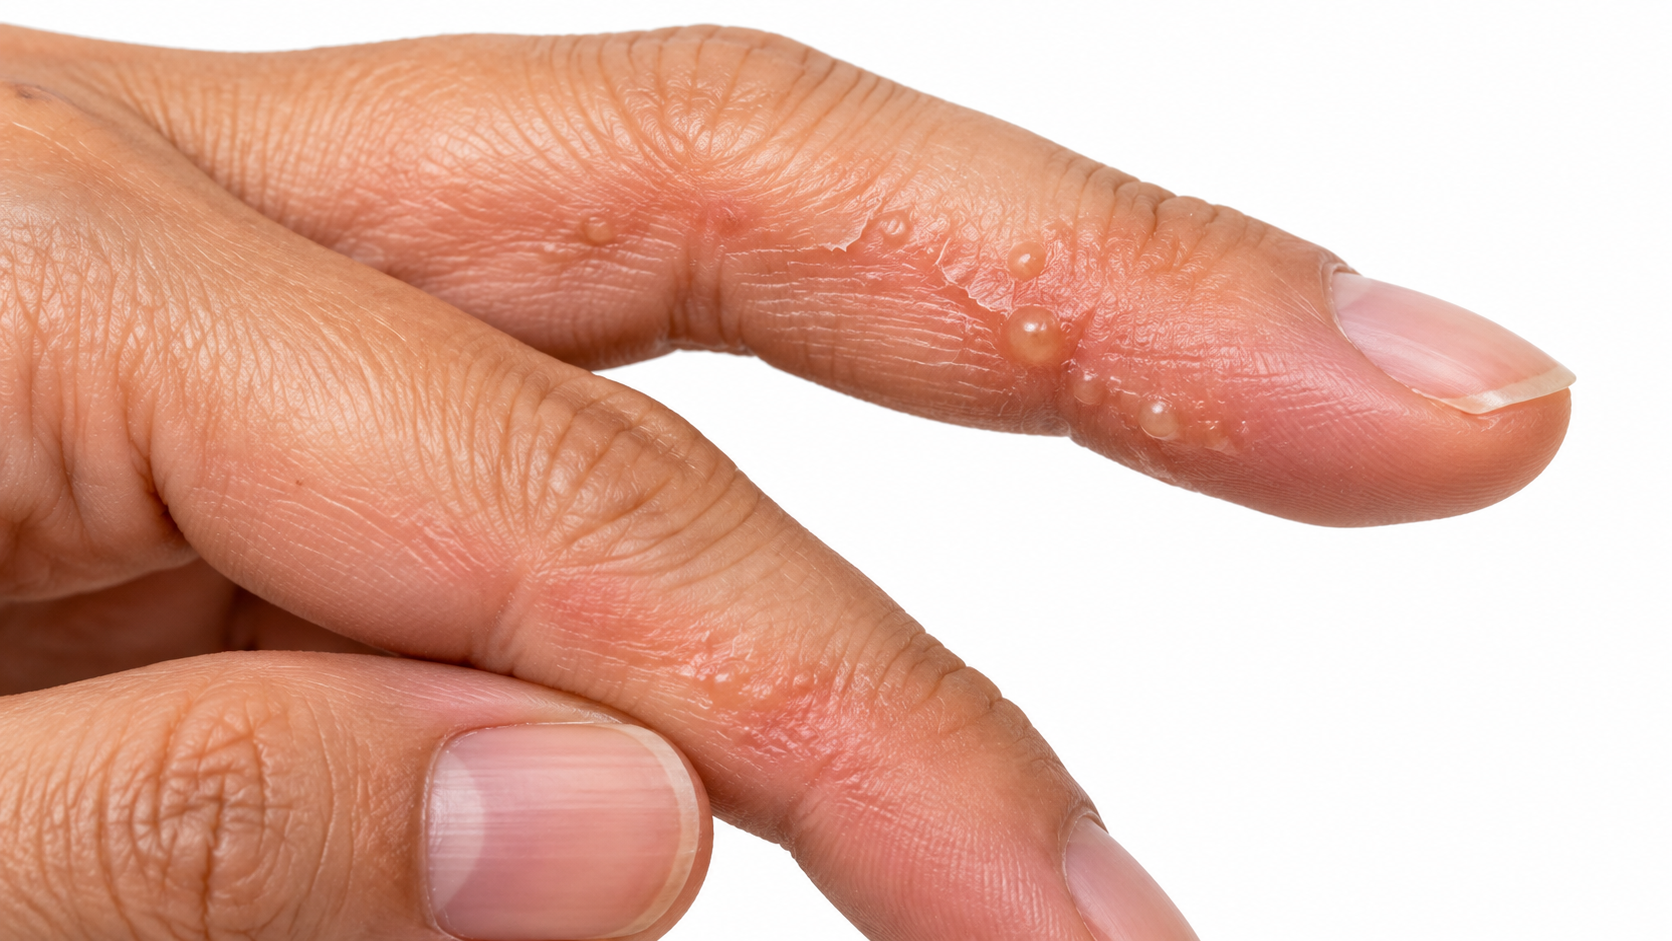
Eczema: Dyshidrotic.

Dyshidrotic eczema Tiny itchy blisters on fingers and palms.

Eczema: Nummular.

Nummular eczema Coin-shaped patches.

Eczema: Contact.

Contact dermatitis Triggered by something touching the skin.

Skin tones
Perioral Dermatitis: 1. Perioral Dermatitis Header — Light Skin; Lighter skin.
Perioral Dermatitis: 2. Perioral Dermatitis Header — Medium Skin; Medium skin.
Perioral Dermatitis: 3. Perioral Dermatitis Header — Brown Skin; Brown skin.
Perioral Dermatitis: 4. Perioral Dermatitis Header — Deep Skin; Darker skin.
Extreme close-up of light skin in an active eczema flare, too close to tell which part of the body it is. Blotchy pink-red inflammation covers the whole frame with no clear edge, with small raised bumps, fine dry scale and a few fresh scratch marks.
Extreme close-up of medium, olive-toned skin in an active eczema flare, too close to tell which part of the body it is. Blotchy brick-red inflammation covers the whole frame with no clear edge, with small raised bumps, fine dry scale and a few fresh scratch marks.
Extreme close-up of brown skin in an active eczema flare, too close to tell which part of the body it is. Blotchy violet-brown inflammation covers the whole frame with no clear edge, and the raised bumps and dry scale show more clearly than the color change does.
Extreme close-up of deep, dark brown skin in an active eczema flare, too close to tell which part of the body it is. Almost no redness is visible - the whole frame reads slightly darker and grayish, with raised bumps, dry scale and fresh scratch marks giving it away.
Diagram
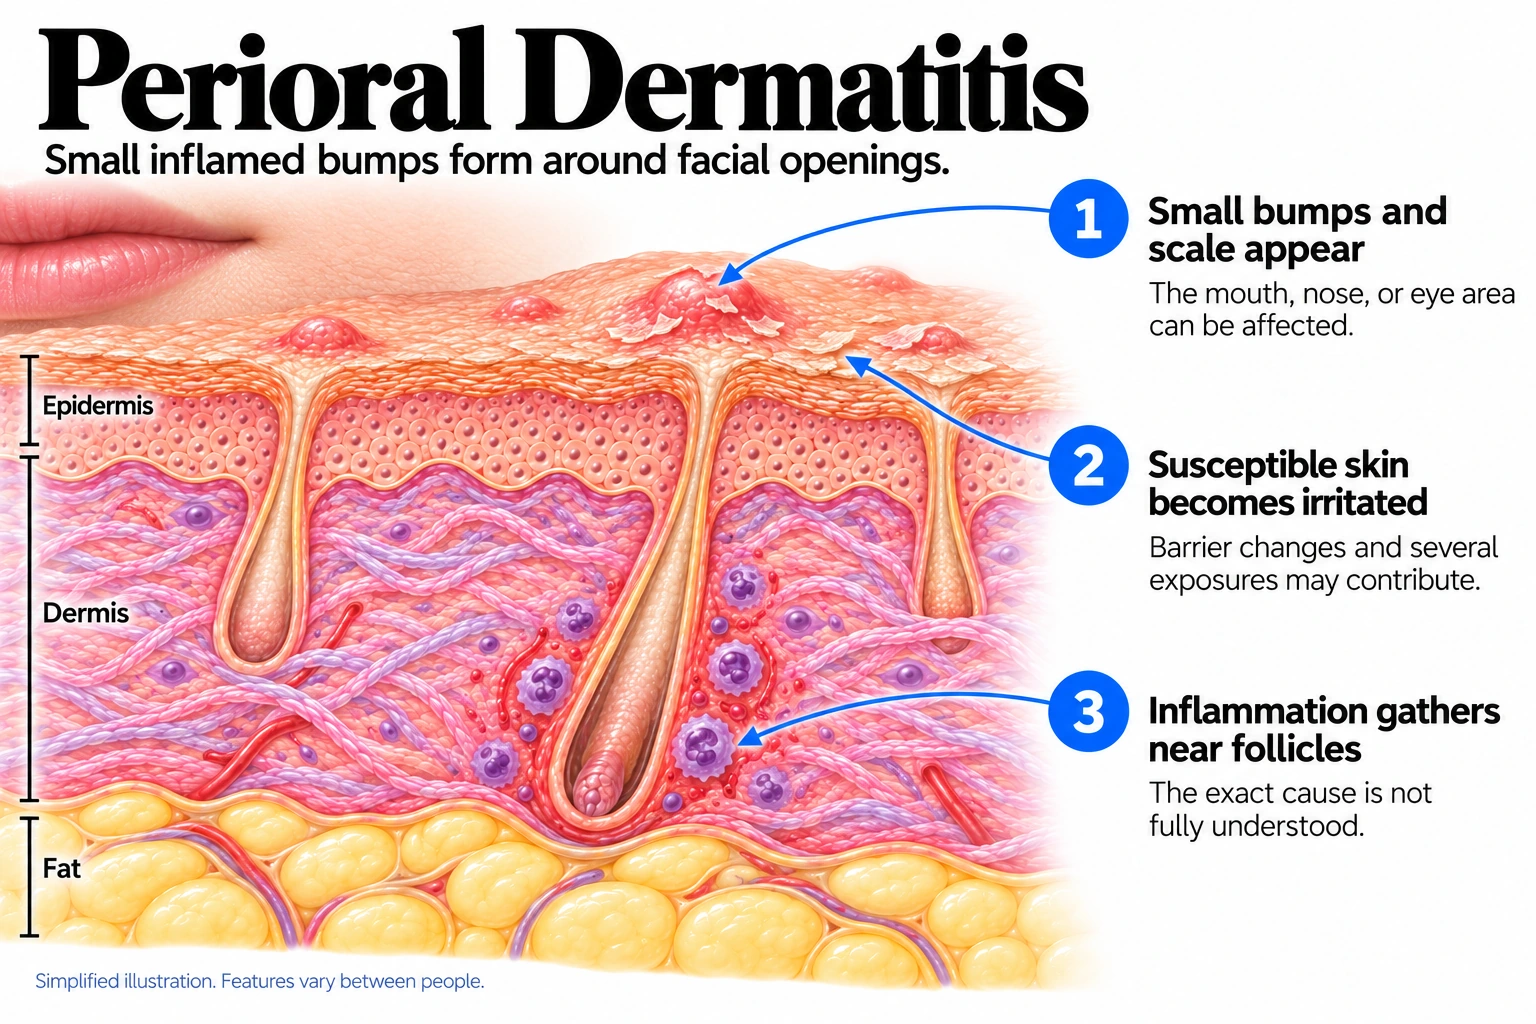
Perioral Dermatitis mechanism diagram. Small bumps and scale appear: The mouth, nose, or eye area can be affected. Susceptible skin becomes irritated: Barrier changes and several exposures may contribute. Inflammation gathers near follicles: The exact cause is not fully understood.
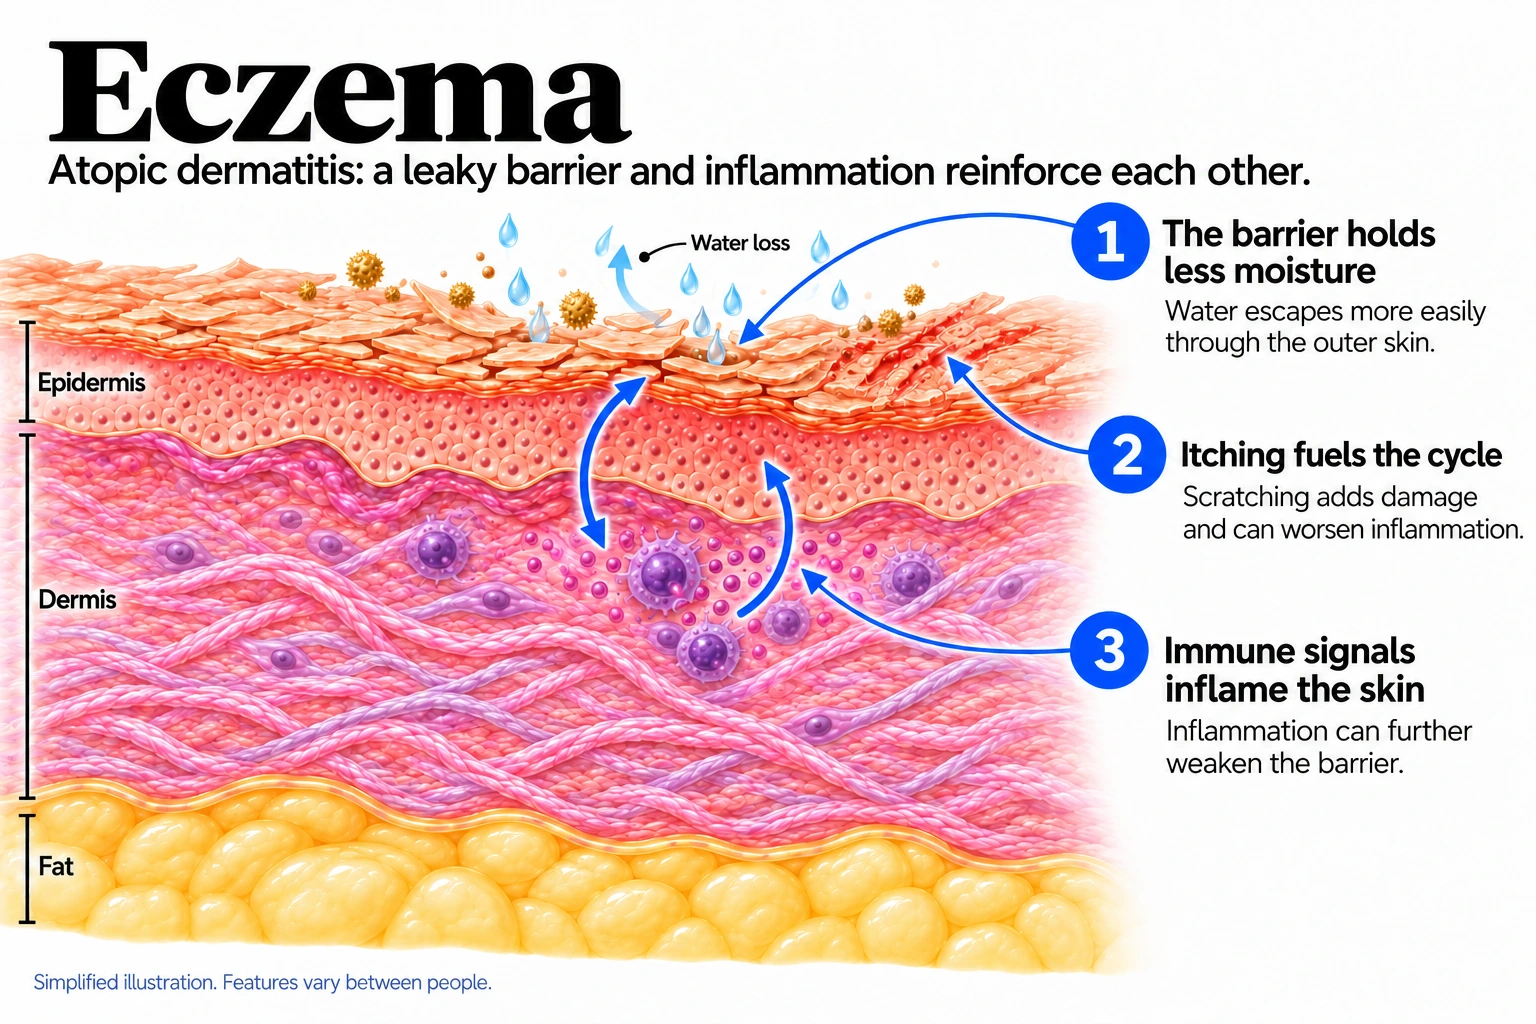
Atopic dermatitis showing water loss through a disrupted outer barrier, scratch damage, and inflammatory immune activity.
In the skin

Inflammation near small facial follicles produces bumps and scale around the mouth, nose or eyes. Barrier changes and several exposures may contribute, but the exact cause is not fully understood.

In atopic dermatitis, a less effective skin barrier and overactive immune signals reinforce each other. Water escapes more easily, and itching and scratching can add damage and prolong inflammation.

Where it shows up

Around the mouth, nose or eyes
A pattern that changes with age

Eczema often affects the inner elbows and backs of the knees. In adults, the hands, face and neck may also be involved.

When it usually starts

010203040506070+

Perioral Dermatitis. Common in younger adult women but can also affect children and other adults.

Eczema. Often starts in infancy or childhood, though it can first develop in adulthood.

Causes and triggers

Causes

Perioral dermatitis is an inflammatory rash around the mouth. The exact cause isn't known, but it is strongly linked to steroid creams and heavy products on the face.

Eczema comes from a weak skin barrier combined with an overactive immune response. Moisture escapes, irritants get in and the skin becomes itchy and inflamed.

Family tendency

Changes in the filaggrin gene, which helps build the skin barrier, are a major risk. Eczema often runs in families with asthma and hay fever.

Risk factors
Women aged 20 to 45, Children, Using steroid creams on the face
Family history of allergies, Asthma or hay fever, Living in cities or dry climates, Infancy
Trigger
● Perioral Dermatitis
● Eczema
Topical or inhaled steroids
Well established
Not listed
Heavy moisturizers and makeup
Strong link
Not listed
Fluoride toothpaste
Possible
Not listed
Hormone changes
Possible
Not listed
Dry air and cold weather
Not listed
Well established
Harsh soaps and fragrance
Not listed
Well established
Sweat and heat
Not listed
Strong link
Wool and rough fabrics
Not listed
Strong link
Stress
Not listed
Strong link
Dust mites and pet dander
Not listed
Possible

Daily Care

Perioral Dermatitis
Eczema
Daily care

Habits that help

  • Strip the routine back
    Gentle cleanser, light moisturizer, sunscreen, nothing else.
  • Rinse after your inhaler or nasal spray
    Removes the residue.
  • Simplify makeup rather than stopping it
    Light mineral makeup, removed gently.
  • A simple daily sunscreen
    Stops the dark marks deepening.
  • Topical metronidazole
    The long-standing first-line cream.
  • Topical erythromycin or clindamycin
    For cases the first choice misses.
  • An oral tetracycline course
    Clears widespread cases faster than creams.
  • An oral macrolide for children
    Used instead of a tetracycline.

Avoid

  • Avoid: Occlusive balms, moisturizers and oils
    Thick products trap and disturb the barrier.
  • Avoid: Full-coverage makeup and primers
    The heavier the product, the more it turns up.
  • Avoid: Layering actives, acids and scrubs
    Stacked, they strip the barrier.
  • Avoid: Lip balms used constantly, and lip licking
    Keeps the skin beside the lips wet.
  • Avoid: Face masks and anything occlusive
    Heat, moisture and friction for hours.
  • Avoid: Hot water, harsh cleansers, over-washing
    They strip a damaged barrier further.
  • Avoid: Fluoride toothpaste
    Reported by some, though the evidence is weak.
  • Avoid: Stopping the prescription early
    Improvement at week three is not clearance.
  • Avoid: Hydrocortisone
    The most common self-treatment for this rash and the most common cause of it. It looks like it is working within two days, and the rash comes back worse when it stops, which pulls people into using it again. Even the mildest over-the-counter strength does this. If you are using one now, that is the thing to stop first, with your doctor's help if it was prescribed.
  • Avoid: Steroid creams of any strength
    Prescription steroid creams do the same thing on the face as the over-the-counter one: fast improvement, then a worse rash when they stop. Stronger ones make the cycle harder to break and can thin the skin. If a steroid was prescribed for something else on your face, ask about stopping it rather than stopping it abruptly on your own.

Habits that help

  • Moisturize generously, every day
    An artificial barrier.
  • Short, lukewarm showers
    Gentle cleanser, pat dry, moisturizer straight after.
  • A humidifier in winter
    If your eczema is seasonal.
  • Cool the skin
    Cool compresses and a cooler bedroom quiet it.
  • Short nails and gloves at night
    Limits scratching in your sleep.
  • Cotton and loose clothing
    Less triggering all day.
  • Use a clinician-agreed maintenance plan on recurrent eczema sites
    Twice a week on flare-prone spots lengthens the gaps.
  • Treat early
    A flare caught early takes far less treatment.
  • Injected and oral treatments
    For severe eczema, under a specialist.
  • Seek assessment for signs of skin infection
    New pain, spreading redness, fever or crusting may need assessment. Not every weeping eczema flare needs antibiotics.
  • Hypochlorous acid spray
    Lowers skin bacteria, does not sting.
  • Diluted bleach baths
    Only if your doctor recommends it.
  • Plan for nighttime itch
    Body heat rises, itch gets louder.
  • Seek assessment for new weeping, yellow crusts or worsening soreness
    These can signal infection but also occur with inflammation. Ask for assessment rather than automatically starting an antibiotic.

Avoid

  • Avoid: Scratching
    Tears the gaps wider.
  • Avoid: Long, hot showers
    Strip the fats holding the barrier.
  • Avoid: Soap and foaming cleansers
    Heavy foam strips barrier fats.
  • Avoid: Frequent handwashing
    The main driver of hand eczema.
  • Avoid: Dry indoor air in winter
    Heating drops indoor humidity.
  • Avoid: Fragrance
    A top irritant.
  • Avoid: Sweat and overheating
    A very reliable itch trigger.
  • Avoid: Wool and rough fabrics
    Set the itch off directly.
  • Avoid: Stress and poor sleep
    Raise existing inflammation.
  • Avoid: Dust mites, pollen, pet dander
    Matter if you have hay fever or asthma.
  • Avoid: Stopping moisturizer
    The top reason a flare returns.
  • Avoid: Stopping treatment early
    Undertreated flares return faster.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Perioral Dermatitis
● Eczema
Filter by type
All types
Eczema type

Select one or more.

Over-the-counter
Educational still life: shampoo.

Acne washes, acids and scrubs

Avoid

Benzoyl peroxide, strong exfoliating acids and scrubs are what most people reach for, because this looks like acne. They damage the barrier further and usually make the rash angrier. If a product is stinging more than it was on day one, that is a reason to stop it, not to push through.

Five azelaic acid tubes and bottles on white, most marked 10 percent, from Peach Slices, Paula's Choice, Facetheory, The Ordinary and Naturium

Azelaic Acid

Limited evidence

The one over-the-counter active worth using here. At 10 percent it calms the bumps and, unusually, also helps the dark marks the rash leaves behind. It is slower than the prescription version and it can sting on skin that is already burning, so start every other night.

Four sulfur acne products: Kate Somerville EradiKate, De La Cruz 10% sulfur ointment, The Ordinary and Thayers

Sulfur

Limited evidence

A sulfur wash or lotion is a gentler option for mild cases, and it is often chosen when someone cannot use the usual prescriptions. The evidence for it in this condition is thin, and the smell puts people off. It is worth a few weeks, not a few months.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh.

Hydrocortisone 1%

Moderate evidence

The one steroid you can buy without a prescription, and the only step in this routine that treats rather than protects. A thin layer twice a day on the itchy patches, for up to two weeks at a time. Mild enough for the face and the eyelids for a few days, and too mild for skin that has gone thick and leathery.

Existing illustration of Hypochlorous acid spray.

Hypochlorous acid spray

Limited evidence

A spray that lowers the amount of staph sitting on eczema skin, aimed at step four rather than at the inflammation itself. It does not sting, which makes it easier on children than a bleach bath. It is a helper for skin that keeps getting infected, not a treatment for the flare.

Illustration: Generic oral tablet bottle and tablets.

A sedating antihistamine at night

Limited evidence

Taken at bedtime it helps you sleep through the itch, which is the honest reason to use it. It does not treat the itch of eczema — that comes from immune signals rather than histamine — so a non-drowsy antihistamine in the daytime does very little. Ask your doctor before using one in a young child.

Four ointments on white: CeraVe Healing Ointment, a Vaseline jar, a petroleum jelly tube and Aquaphor

Petrolatum

Strong evidence

Plain ointment, over damp skin, as the moisturizer rather than beside it. It seals water in rather than adding any. It is the one thing that is safe to put on eyelids as often as you like, and on a weeping flare it is usually the best thing on the shelf.

Five colloidal oatmeal eczema products lined up on white: tubes, a jar and a pump lotion

Colloidal Oatmeal

Moderate evidence

An old remedy that holds up. It calms itch and helps the barrier, in a cream or in a lukewarm bath. It will not clear a flare, and it is a sensible everyday moisturizer for skin that is calm but easily set off.

Five white jars of 40% urea cream lined up, several also listing 2% salicylic acid

Urea

Moderate evidence

A moisturizer with urea in it, for patches that have gone thick and leathery from years of scratching. 10% and above. It stings on raw or weeping skin, so it belongs to the dry, cracked stage rather than the sore one.

Four ceramide moisturizers lined up on white: two tubes, a CeraVe tub and a blue jar

Ceramides

Moderate evidence

The fats that hold the outer wall of the skin together, and the ones eczema skin is short of. A ceramide cream used daily reduces how often flares happen and how much prescription cream you end up needing over a year. It will not clear an active flare on its own — it is the maintenance step, used on calm skin as much as on sore skin.

Prescription topicals
MetroGel — Header Image

MetroGel

Moderate evidence

The long-standing first choice for perioral dermatitis, used once or twice a day for weeks. It is well tolerated on skin that is already sore, which matters here. Expect little in the first fortnight, clear improvement by weeks three to six, and keep going for two to four weeks after the skin looks clear.

16:9 hero for Elidel. Never cropped: the tone strip and the corner logo depend on the full frame.

Elidel

Moderate evidence

A non-steroid anti-inflammatory cream sometimes used to get through the rebound after a steroid is stopped, and around the eyes where other options are awkward. It calms the skin without the rebound a steroid causes. Results in this condition are mixed, and it can burn for the first few days.

Finacea — Header Image

Finacea

Limited evidence

As effective as metronidazole here, and the better pick if the rash has left dark marks, because it works on both. It stings for the first week or two on inflamed skin. Applied twice a day, it is a reasonable alternative rather than a step up.

A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Limited evidence

An antibiotic lotion or gel kept for cases that do not settle on the first choice, sometimes paired with it. It calms the bumps rather than the flaking. It is not used on its own for long stretches, to limit resistance.

Soolantra — Header Image

Soolantra

Limited evidence

Used when Demodex mites around the hair follicles are thought to be part of the picture, which is more likely in a stubborn case with a lot of small pus-filled heads. Most of its evidence comes from rosacea rather than this condition. It is a second or third choice, not a starting point.

16:9 hero for Elidel. Never cropped: the tone strip and the corner logo depend on the full frame.

Elidel

Strong evidence

Elidel. The gentler cousin of tacrolimus, in a cream rather than an ointment. Suited to mild eczema on the face and the eyelids. It stings less, and it does less.

Representative medication packaging labelled Triamcinolone, lying sideways on a white background.

Triamcinolone Acetonide

Strong evidence

Triamcinolone. A mid-strength steroid ointment, twice a day for one to two weeks. It is the usual next step when hydrocortisone is not enough. Not for the face, the eyelids or the armpits - the skin there is thin already.

Protopic — Header Image

Protopic

Strong evidence

Protopic. An ointment that calms the same immune signal a steroid does, without being one. It does not thin skin, so it suits the eyelids, the face and the folds, and it can be used twice a week to stop flares coming back. Expect stinging for the first week or so.

16:9 hero for Desonide. Never cropped: the tone strip and the corner logo depend on the full frame.

Desonide

Strong evidence

A low-strength steroid made for thin skin - the face, the eyelids, the folds, and young children. Twice a day for a week or two.

Representative medication packaging labelled Eucrisa, lying sideways on a white background.

Eucrisa

Strong evidence

Eucrisa. A steroid-free ointment for mild to moderate eczema, approved down to three months old. It burns on application for some people, which is the main reason it gets abandoned.

Opzelura shown in recognizable white topical cream squeeze tube with muted green bands.

Opzelura

Strong evidence

Opzelura. A newer steroid-free cream that takes the itch down quickly. It is meant for short courses on a limited area of the body, and it carries the warnings that come with the JAK class.

Clobetasol — Header Image

Clobetasol

Strong evidence

One of the strongest steroids there is, kept for thick, stubborn patches and for palms and soles. Two weeks at a time, then a break. Long stretches thin the skin.

Vtama — Header Image

Vtama

Moderate evidence

A steroid-free cream applied once a day, approved for eczema down to two years old. It calms the inflammation without thinning skin, and in trials the improvement often held for a while after stopping. Folliculitis — small spots around the hair openings — and headache are the side effects that come up, and it is newer and more expensive than a steroid.

Representative medication packaging labelled Zoryve, lying sideways on a white background.

Zoryve

Moderate evidence

Zoryve. Another steroid-free once-daily cream, approved for eczema down to six years old. It is well tolerated on the face and the folds, and it does not sting the way tacrolimus does in the first week. Like the other newer creams, the barrier is cost and coverage rather than whether it works.

Prescription pills
Cream — stock illustration

Erythromycin

Moderate evidence

Erythromycin for children. When a child needs tablets, a macrolide is chosen instead of a tetracycline, which is avoided under about eight because of the effect on developing teeth. It clears the widespread childhood form well. Stomach upset is the usual reason people stop it.

An amber prescription bottle lying on its side on a white background with a plain white label reading Doxycycline, and six small round white tablets spilled out in front of it.

Doxycycline

Moderate evidence

A tetracycline tablet taken for six to twelve weeks, used when the rash is widespread, stubborn or around the eyes. It works here as an anti-inflammatory rather than by killing an infection, so a low dose is often enough. It makes the skin burn more easily in the sun, and it is not used in young children or in pregnancy.

16:9 hero for Minocycline. Never cropped: the tone strip and the corner logo depend on the full frame.

Minocycline

Moderate evidence

An alternative tetracycline when doxycycline does not suit. It works about as well for this rash. It is used more cautiously because it can cause dizziness and, rarely with long use, a blue-gray discoloration of the skin.

A white blister pack photographed flat on a white background, holding eight white oblong capsules in two rows of four under clear domes. ACCUTANE is printed in blue capitals on the empty left half of the foil.

Accutane

Limited evidence

Accutane (isotretinoin). A low dose is occasionally used for the granulomatous form or for a case that has failed everything else, and it is rare for this condition to need it. The evidence is a handful of small reports rather than trials. It requires close monitoring and strict pregnancy prevention, and it can dry the face enough to irritate the rash at first.

Existing representative illustration of Rinvoq medicine packaging and tablets.

Oral JAK inhibitors

Strong evidence

Tablets for severe eczema that has not answered creams — they work fast, often taking the itch down within days. They need blood tests, and the class carries warnings about infection, blood clots and heart problems, so they are prescribed with a proper discussion of who they suit. Usually considered alongside the injections rather than before them.

An amber pill bottle labeled Cyclosporine tipped over with white tablets spilling out

Cyclosporine

Moderate evidence

Works fast on a severe flare, which is what it is for - weeks to months, not years. It raises blood pressure and strains the kidneys, so both are checked while you are taking it.

16:9 hero for Methotrexate. Never cropped: the tone strip and the corner logo depend on the full frame.

Methotrexate

Moderate evidence

A weekly tablet for long-running eczema. Cheaper than the injections and slower to work, with blood tests every few months. Ask your doctor about it before trying to conceive, and if you are pregnant or breastfeeding.

Prednisone — Header Image

Prednisone

Avoid

Oral steroids clear eczema quickly and it usually returns worse within weeks of stopping. Most dermatologists avoid them for that reason, and use them only to break a severe flare while something slower is started.

Antibiotics for infected eczema

Antibiotics for infected eczema

Listed

A short course when a flare is weeping or carrying golden-yellow crusts, which usually means staph has taken hold. It clears the infection so the eczema treatment can work again. It is not a treatment for eczema itself, and taking it for every flare is how resistance builds, so it is used when there is something to treat.

Injections
None listed
A white and green autoinjector pen labeled Dupixent lying on a plain pale background

Dupixent

Strong evidence

Dupixent. An injection every two weeks, for eczema that covers a lot of skin and has not answered creams. It is not a steroid and it needs no blood monitoring. Eye irritation is the side effect people actually get.

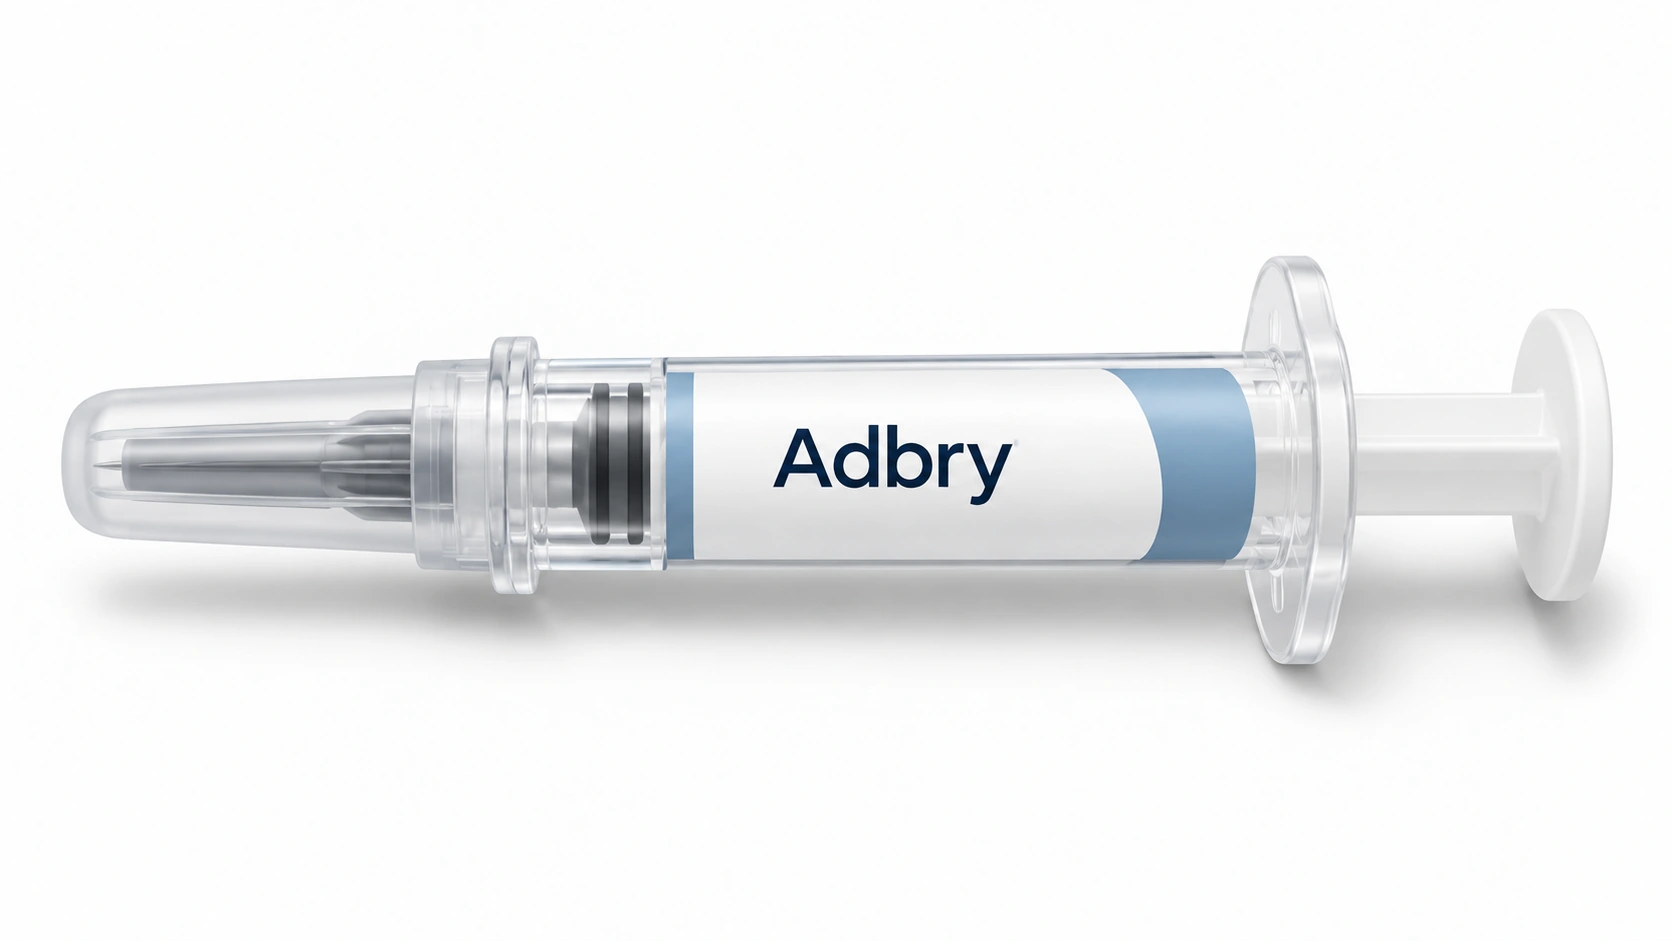
An illustrative capped prefilled syringe labeled Adbry; packaging is conceptual.

Adbry

Strong evidence

An injection every two weeks for moderate to severe eczema, blocking one of the same immune signals Dupixent does. It is the usual next thing to try when Dupixent has not worked well enough or has not been tolerated. No blood monitoring, and eye irritation is the side effect to know about, as with Dupixent.

Procedures
None listed
Editorial illustration for Phototherapy, based on the entry’s treatment or equipment reference.

Phototherapy

Moderate evidence

Measured doses of ultraviolet light in a booth, two or three times a week for a couple of months. It works. The cost is time, because it means getting to the office that often.

Editorial illustration for Excimer Laser, based on the entry’s treatment or equipment reference.

Excimer Laser

Limited evidence

The same idea as the light booth, aimed at one patch instead of the whole body. Useful when a few stubborn areas are all that is left.

Outlook

Long term

Perioral dermatitis does not usually settle by itself. The steroid cycle defines its course - a cream calms the rash within a day or two, then it returns worse once the cream stops. Once treatment starts the arc is predictable, and the first part is worse before better.

Eczema comes in flares - calm skin, then days or weeks of itching and inflammation, then calm. Most people eventually name their own pattern: the season, the stress, the job, the week before a period. Underneath that, it follows a longer arc.

Complications

Possible complications
  • The steroid rebound cycle
  • Spread around the eyes
  • Months of a visible facial rash
More details

The steroid rebound cycle
A steroid cream calms the rash within a day or two, then it returns worse when the cream stops. Each round tends to need more steroid for less benefit, and the condition gets harder to treat. It is the most common complication of perioral dermatitis and the main reason cases drag on for months. Stopping the steroid, and expecting one to two bad weeks, is what breaks it.

Spread around the eyes
The same rash can move up onto the eyelids and the skin around the eyes. It is uncomfortable there, it takes longer to settle, and treatment has to be chosen carefully because of how close it is to the eye. If the eyes themselves become red, gritty or sore, or your vision changes, that needs looking at on its own and soon.

Months of a visible facial rash
This rash sits in the middle of the face, it burns through the day, and it commonly takes two to three months to clear even when treatment is right. People cover it with heavier makeup, which feeds the problem, and many stop seeing friends or go to work uncomfortable. It is worth saying out loud at the appointment, because it changes nothing about the diagnosis and quite a lot about how the plan is set up.

  • Impetigo
  • Sleep loss, fatigue and low mood
  • Thickened, leathery skin
  • Dark or light marks after a flare
  • New allergies to products
  • Eye problems
  • Hand eczema that gets in the way of work
  • The atopic march in children
More details

Impetigo
Bacteria getting into skin that scratching has broken open. It shows as weeping and golden-yellow crusts sitting on top of an eczema patch, and it can turn a settled flare much worse in a day or two. It needs an antibiotic alongside the usual eczema treatment - more moisturizer will not clear it.

Sleep loss, fatigue and low mood
Itch is at its worst at night, so eczema costs sleep - for the person who has it, and often for the rest of the house. Months of broken sleep bring daytime fatigue and poor concentration, and anxiety and depression are more common in people with moderate or severe eczema. It is worth telling your doctor. Treating the eczema properly is usually what fixes the sleep.

Thickened, leathery skin
Months of rubbing and scratching the same patch thicken it into leathery skin with the normal lines cut deeper. Doctors call it lichenification. It itches on its own, and it takes far longer to settle than a fresh flare - stopping the scratching is the only thing that reverses it.

Dark or light marks after a flare
Settled patches often leave flat marks that are darker than the skin around them, and sometimes lighter patches where pigment has dropped out. Neither is a scar, and neither is caused by the treatment. They fade on their own, but over months rather than weeks, and they are more noticeable and longer-lasting on deeper skin tones.

New allergies to products
Broken skin meets far more of whatever is put on it, so people with eczema pick up contact allergies more easily - to preservatives, fragrance, and sometimes to the eczema creams themselves. Suspect it when a treatment that used to work starts to sting or spread the rash. Patch testing is how it is confirmed.

Eye problems
Eyelid eczema and constant rubbing lead to itchy, swollen lids and red, irritated eyes. In severe, long-standing eczema, a change in the shape of the cornea called keratoconus and early cataracts are uncommon but recognized. If the eyes are involved often, it is worth an eye check.

Hand eczema that gets in the way of work
Cracked, sore hands are hard to hide and hard to rest. In wet work - healthcare, food, cleaning, hairdressing, childcare - it can mean time off or a change of job. Treating it early and protecting the hands through the working day is what keeps it from getting that far.

The atopic march in children
Children with eczema are more likely than other children to go on to develop asthma, hay fever and food allergy, often in that order. Doctors call the pattern the atopic march. It is a tendency, not a certainty - most children with eczema do not get all of it.

When to get help

When to get help

Seek assessment for persistent facial bumps, especially after steroid cream use. Discuss a safe plan for stopping facial steroids rather than repeatedly restarting them.

Seek help for sleep-disrupting itch, recurrent flares or infection. Rapidly worsening painful skin with clustered blisters, fever or eye involvement needs urgent care.

Common questions

Perioral Dermatitis:Why did the steroid cream make it worse?

Steroids suppress inflammation quickly, so the rash fades within a day or two. They do nothing about what drives it, and when the cream stops the inflammation returns stronger, needing more steroid for less benefit. That is why the first step is always to stop.

Perioral Dermatitis:How long will it take to clear?

Longer than most people expect. The first one to two weeks off a steroid are usually worse, improvement becomes clear around weeks three to six, and full clearing commonly takes two to three months. Judging at two weeks means judging it at its worst.

Perioral Dermatitis:Is this acne?

No, though it is often treated as acne first. Acne produces blackheads and whiteheads, across the face, chest and back. Perioral dermatitis produces uniform grouped bumps around the mouth, nose or eyes, with a clear rim next to the lips, and it burns rather than itches.

Perioral Dermatitis:Do I really have to stop all my skincare?

For a few weeks, mostly yes. Heavy occlusive products are a main trigger, and layered actives keep the barrier damaged. A gentle cleanser, a light moisturizer if needed, and sunscreen is the whole routine while it clears. Products go back one at a time afterward.

Perioral Dermatitis:Will it come back?

Most people clear and stay clear. When it returns there is usually an identifiable reason - a steroid cream for something else, a new heavy moisturizer, or a long routine again. Knowing your trigger is most of the prevention.

Perioral Dermatitis:Should I stop my asthma inhaler?

No. Never stop a prescribed inhaler on your own. Rinsing your mouth and washing the skin around it after every dose cuts the residue reaching your face, and your dermatologist can talk to whoever manages your asthma if the inhaler is the driver.

Eczema:Will my child grow out of eczema?

Many children improve a great deal by school age, and more through the teenage years. Complete, permanent clearance happens but is not the rule. What usually remains is dry, easily irritated skin that can flare again later, often on the hands. Treating it well in childhood does not guarantee it goes, but it means fewer flares, less scratching, less thickened skin.

Eczema:Are topical steroids safe for my child?

Used as prescribed, yes. The rules are simple - mild strengths on the face, eyelids and skin folds, stronger ones for the body and limbs, and courses that run the length of a flare rather than indefinitely. Thinned skin and stretch marks come from strong steroids on thin skin for months without review. If you are using one more or less continuously, go back and ask about a non-steroid option.

Eczema:Is a food causing this?

Usually not, and this is a common wrong turn. Food allergy is more common in children with eczema, but because both come from the same atopic tendency, not because food drives the rash. Removing foods rarely clears eczema, and long elimination diets can cause nutritional problems and even make a true allergy more likely. A clear, repeatable reaction within a couple of hours is worth investigating. A vague suspicion is not.

Eczema:Why is it so much worse at night?

Several things line up after dark. Body temperature rises in the evening, and heat triggers itch directly. The distractions that kept you from noticing it are gone. Cortisol, which damps inflammation, is at its lowest overnight. And scratching in your sleep is unconscious, so damage piles up unchecked. A cooler bedroom, moisturizer right before bed, short nails and cotton layers help more than they sound.

Eczema:Can I use the same cream on my face?

Not always. Facial skin, eyelid skin especially, is much thinner and absorbs more of what you put on it. A steroid strong enough for your shins can thin the skin around your eyes within weeks. Face and eyelid eczema is treated with a mild steroid for a short stretch, or a non-steroid cream that can be used long term. Ask before moving a body prescription to your face.


Eczema:Do I still need moisturizer when the skin looks normal?

Yes. This is the single habit that separates people who flare four times a year from people who flare monthly. Skin that looks normal in eczema is still leaky - the barrier defect is there whether or not there is a rash. Daily moisturizer on calm skin keeps the next flare further off and smaller. It is maintenance, not first aid.

Sources

Sources and further reading

  1. DermNet
  2. DermNet
Dermapedia on YouTube