Eucrisa
A non-steroid ointment for mild to moderate eczema. It can be used on the face and in skin folds, and there is no limit on how long it can be used.

Key facts
Eucrisa at a glance.
Used for
Mild to moderate eczema
Results
Up to 4 weeks
Treatment commitment
As prescribed, with response review
Key precautions
Application-site burning
What is it?
Top things to know about Eucrisa
- It is a PDE4 inhibitor. Crisaborole increases cyclic AMP to reduce inflammation.
- It treats mild to moderate eczema. It offers a non-steroid topical option.
- Its mechanism is not fully defined. The label notes uncertainty about how it works.
- It does not replace moisturizer. Regular moisturizing remains part of care.
Often used for
What Eucrisa is used for



HOW IT WORKS
How Eucrisa works
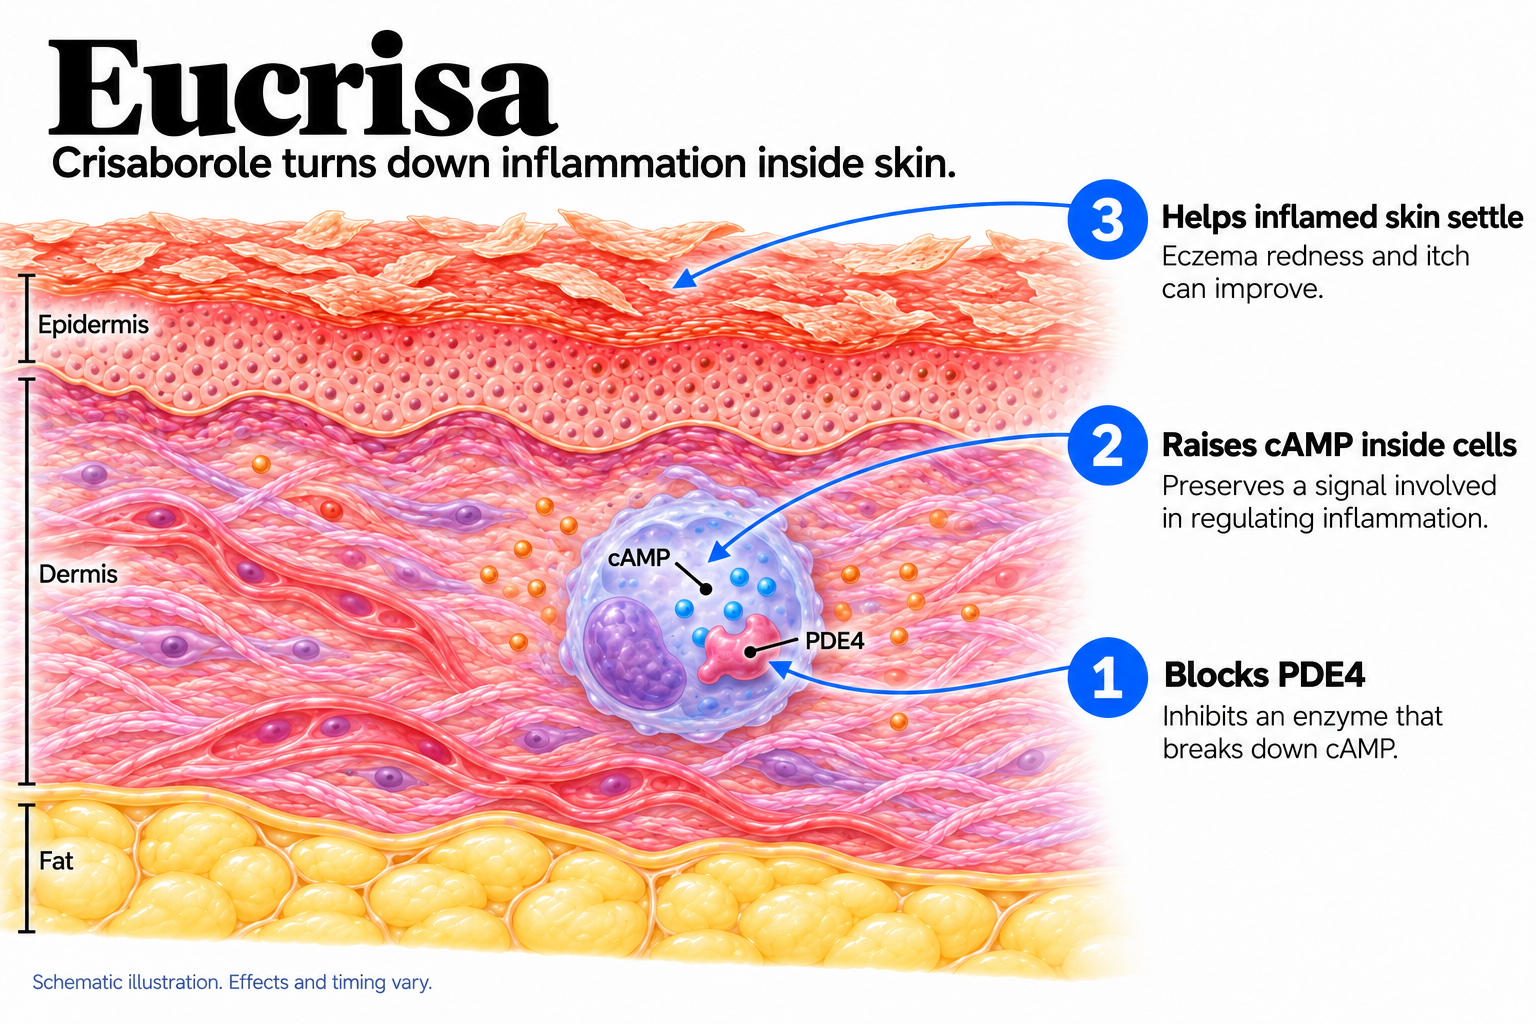
Diagram explanation and sources
Blocks PDE4: Inhibits an enzyme that breaks down cAMP. Raises cAMP inside cells: Preserves a signal involved in regulating inflammation. Helps inflamed skin settle: Eczema redness and itch can improve.
PDE4 inhibition and increased intracellular cAMP are established. The exact link to clinical improvement is not fully defined; this is a simplified overview, not every downstream pathway.
Strengths
Crisaborole strengths
Crisaborole is supplied as 2% ointment for mild-to-moderate atopic dermatitis in patients aged 3 months and older. There is no usual sequence of stronger crisaborole percentages.
2%
The label starts with twice-daily application. Once a clinical effect is achieved, the prescriber may consider once-daily use.
Strength sources
Forms
Crisaborole forms

Ointment
A greasy, protective base that helps hold moisture in. Often comfortable on very dry skin, but can feel heavy or sticky.
How to use it
Your treatment, step by step.
How to apply it
- 01
When to Apply
A thin layer twice a day on the inflamed areas, on clean dry skin. Moisturizer goes everywhere, including over the top once it has settled.
- 02
How to Start
Twice daily from day one, on the flaring areas only, not over the whole body as a preventive. If the stinging is hard to tolerate, moisturize first and use the ointment straight from the fridge. The stinging usually fades within the first week.
- 03
If It Irritates
Burning or stinging for a few minutes after applying is the commonest effect, and usually not an allergy. It settles as the skin heals. Redness spreading beyond where you applied it, or stinging that gets worse rather than better after two weeks, should be reviewed.
- 04
If It's Not Working
There is one strength, so there is nothing to increase. Four weeks of proper twice-daily use is a fair trial. After that: a different non-steroid, a short steroid course to break the flare, or a look at what else is driving the rash.
Monitoring & follow-up
No blood tests and no routine monitoring. Very little reaches the bloodstream, and what does is broken down quickly, so nothing accumulates.
Monitoring is a review at about four weeks to decide whether it is working. Long term, this is a drug people can stay on: no maximum duration, no limit on the area treated, no rest period. That is the practical difference between it and a topical steroid.
The one thing worth watching is whether it is quietly standing in for treatment that would actually control the disease. Eczema that keeps escaping it needs a different plan, not more months of the same ointment.
What to expect
How things change over time.
Applying it
A thin layer twice a day. Stinging or warmth for a few minutes is common, worst in week one.
Adjusting
Stinging is at its worst now. Itch eases before the rash looks different.
Settling
Redness and scaling fade. Most of the stinging has gone.
Judge it here
The point the trials measured. A meaningful share of people reach clear or almost clear skin; a meaningful share do not. No change by four weeks means more time will not help.
Face, eyelids and folds
Its strongest case. Use it on and off as needed: no cumulative limit, no rest period, none of the thinning that limits steroids on thin skin.
- First few minutes
- Days 1 to 7
- Week 2
- Week 4
- Ongoing
When you stop
There is no taper, no rebound, no withdrawal. Stop and restart freely: on during flares, off in between.
Eczema relapses, so the rash tends to come back when treatment stops, generally within weeks. That is the disease returning, not an effect of stopping this drug. Moisturizer through the gaps is what makes the gaps longer.
What it Pairs with
Eucrisa + your routine
| Product or situation | With Eucrisa | What to know |
|---|---|---|
| Moisturizer | Can pair | Moisturizer goes everywhere, including over the top once it has settled. |
| Eyes, inside the mouth, and the vagina | Avoid | Skin only. If it gets into an eye, rinse with water. |
| Open, weeping, or broken skin | Avoid | Absorption and stinging are both greater there; broken skin needs something else first. |
| Treating a widespread flare with it alone | Avoid | Not strong enough for a bad flare across the body. It holds skin better than it rescues. |
| Using it instead of moisturizer | Avoid | It is medicine for the inflamed patches. Moisturizer everywhere else still has to happen. |
| Wrapping the treated area tightly | Avoid | Occlusion increases absorption, and the base already holds heat. |
| If you are pregnant or breastfeeding | Use care | Little is absorbed, but the data are limited. Ask the doctor managing your pregnancy, and keep it off the nipple if breastfeeding. |
| If the stinging has not settled | Use care | By two weeks it should be easing. Stinging that worsens, or redness spreading beyond the treated area, needs review. |
| If the rash is weeping or crusted | Use care | Golden crusting counts too. That suggests infection, treated first — this does not treat it. |
| If you are using it over a large area | Use care | More than a small share of your body. Licensed for mild to moderate disease; widespread eczema needs another plan. |
| If nothing has changed by four weeks | Use care | The point to change something, not keep going. |
Getting it and cost
Getting Eucrisa.
Cost & access
Cost is the obstacle here, not safety. It has been brand-name with no stocked generic for most of its life, and the cash price for a large tube is high. Generic availability changes, so ask the pharmacy.
What affects the cost
Prior authorization is common. Plans usually want a topical steroid first, sometimes a calcineurin inhibitor too, which is cheaper as a generic. A savings card exists for people with commercial insurance, with terms that change often.
What affects the cost
Tube size matters more than with most creams, because it goes on twice a day over an area. A small tube covering a child's whole body lasts days. Ask for the size that matches the area treated.
Alternatives
Other options to consider.

Topical steroids
stronger, faster, cheap, generic, and backed by decades of evidence. The trade-off is thinning and visible vessels with prolonged use on the face, eyelids, and folds — which is precisely where crisaborole is used instead.

Tacrolimus and pimecrolimus
the other non-steroid options for thin skin, with a longer track record and available as generics. They carry a boxed warning about a theoretical cancer risk that long-term follow-up has not borne out, and they sting early too.
Ruxolitinib cream
a topical JAK inhibitor, more effective in trials than crisaborole, with a boxed warning carried over from the oral drugs in its class and limits on how much and how long it can be used.

Roflumilast cream
a newer PDE4 inhibitor working the same way, applied once a day, with less application-site stinging reported. Also expensive and also brand-only in most places.

Moisturizer alone
less a rival than the floor everything else stands on. It reduces flares by itself and continues underneath all of the above.
Questions
Questions you might be asking.
Why does it sting?
Probably the drug itself acting on inflamed skin, not the base. It is the commonest complaint, worst in the first days, and fades within a week.
Can I use it on my eyelids?
Thin skin is where it makes the most sense and it is used there, but not in the eye itself. Keep it off the lid margin.
Is it as good as a steroid cream?
No, it is milder. Its advantage is delicate skin and long stretches without the thinning that limits steroids.
How long can I use it for?
There is no set limit. On during flares, off in between, for as long as it helps.
Can children use it?
It is licensed from three months of age.
Does it work for anything other than eczema?
Licensed for atopic dermatitis. Doctors sometimes use it off-label for other inflammatory rashes, where the evidence is thinner.