Eczema
Calms flares on the body.
Hydrocortisone: The mildest topical steroid, and the only one sold without a prescription. It is the usual starting point for the face, for skin folds and for young children. Mometasone: A mid-strength prescription steroid applied once a day for eczema, psoriasis and other itchy rashes. Strong enough to settle a flare, measured enough for short courses on most of the body.


Choose as the first step for mild rashes on the face, folds or young children — the only steroid sold without a prescription.
Choose to settle an eczema or psoriasis flare on the body with a once-daily, mid-strength steroid.
Can you take them together?
Both are topical steroids. Hydrocortisone is mild for the face, folds and children; mometasone is stronger for the body. Use each where prescribed.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.
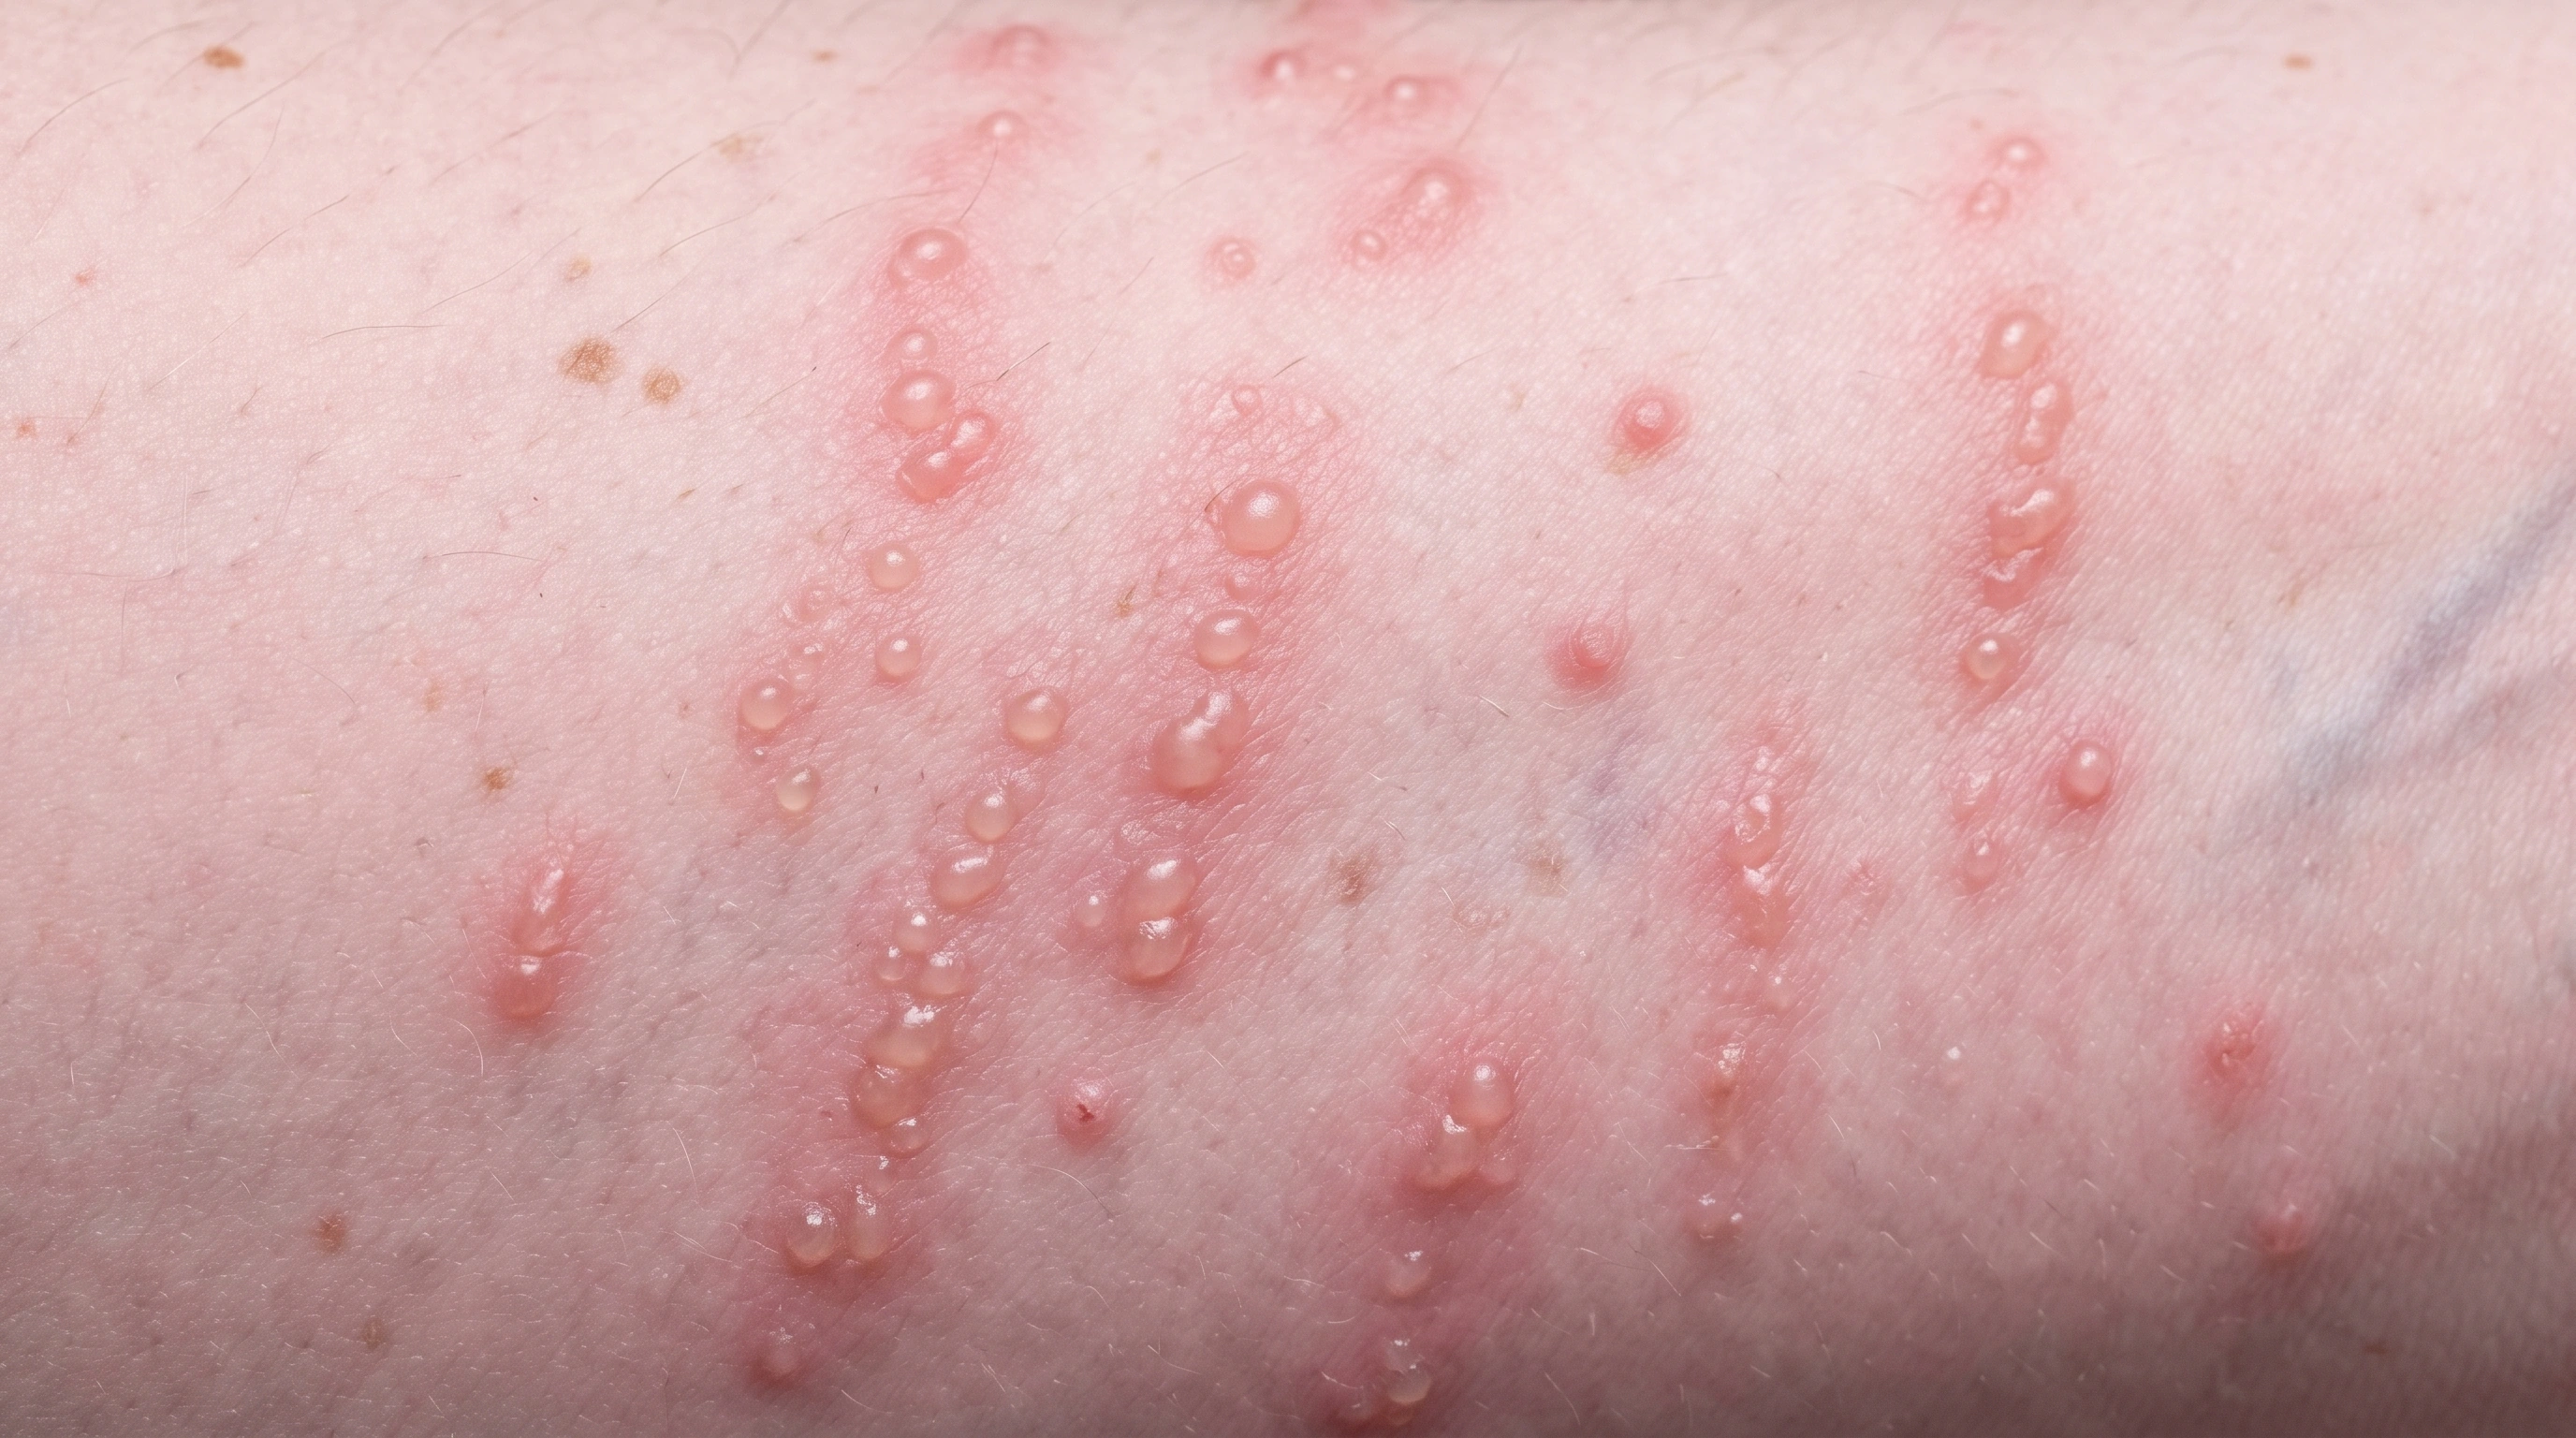

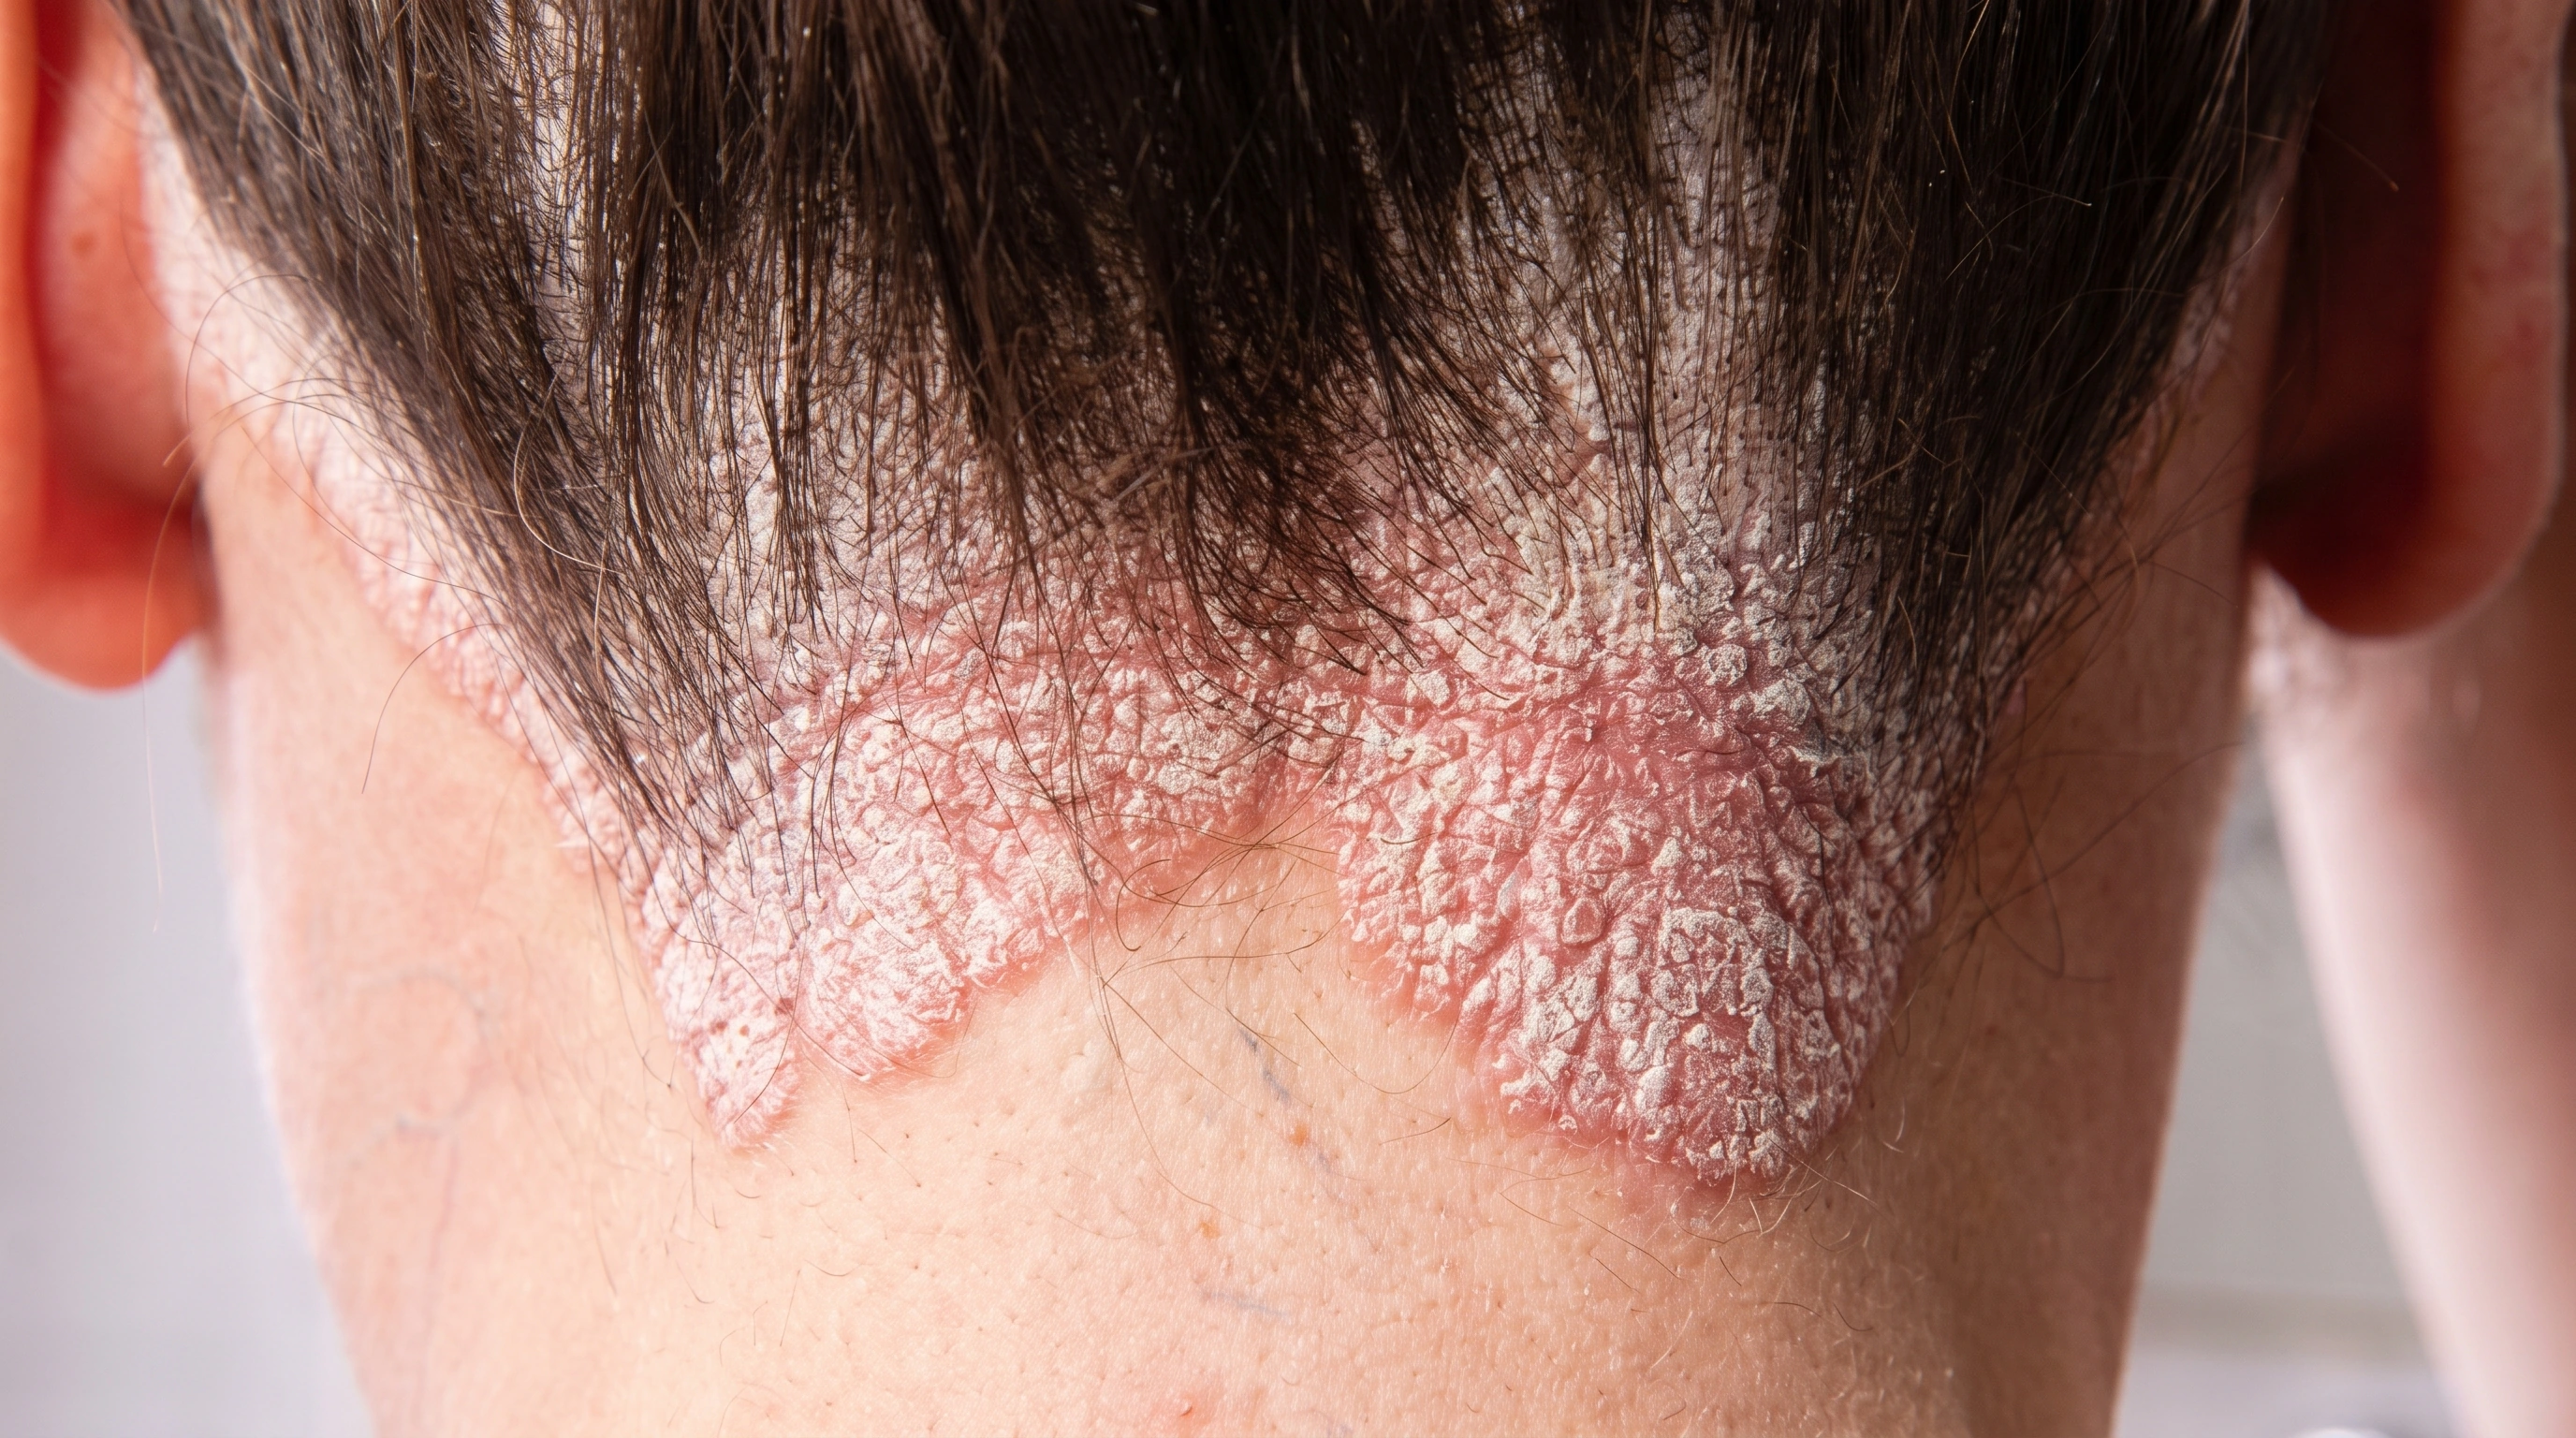
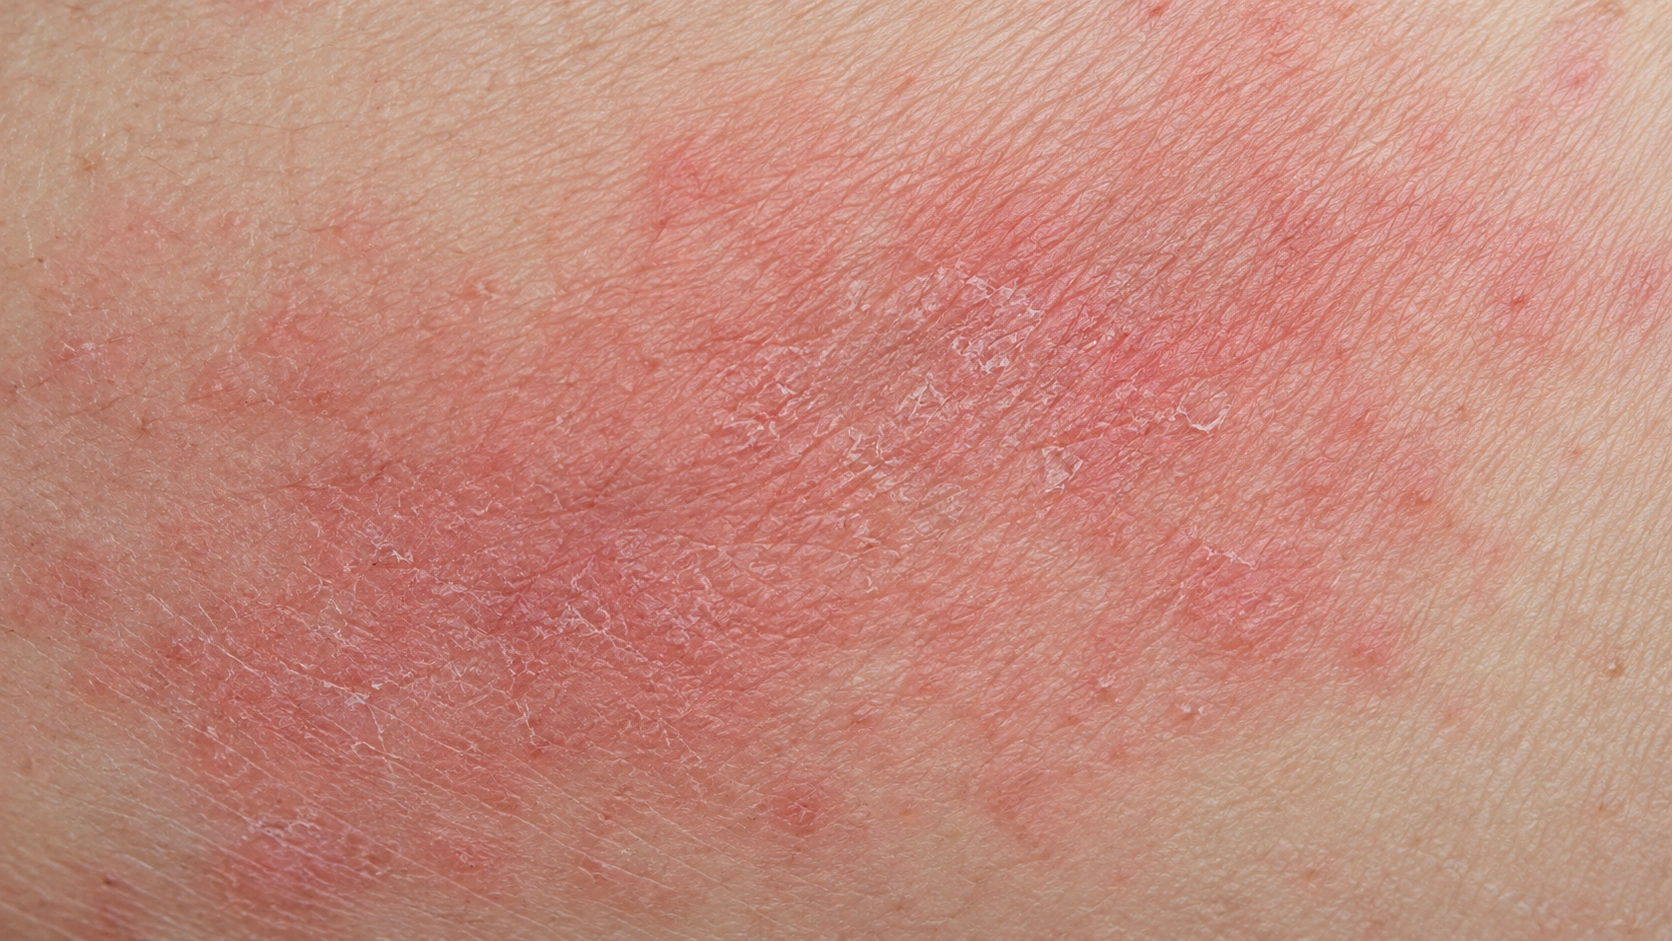

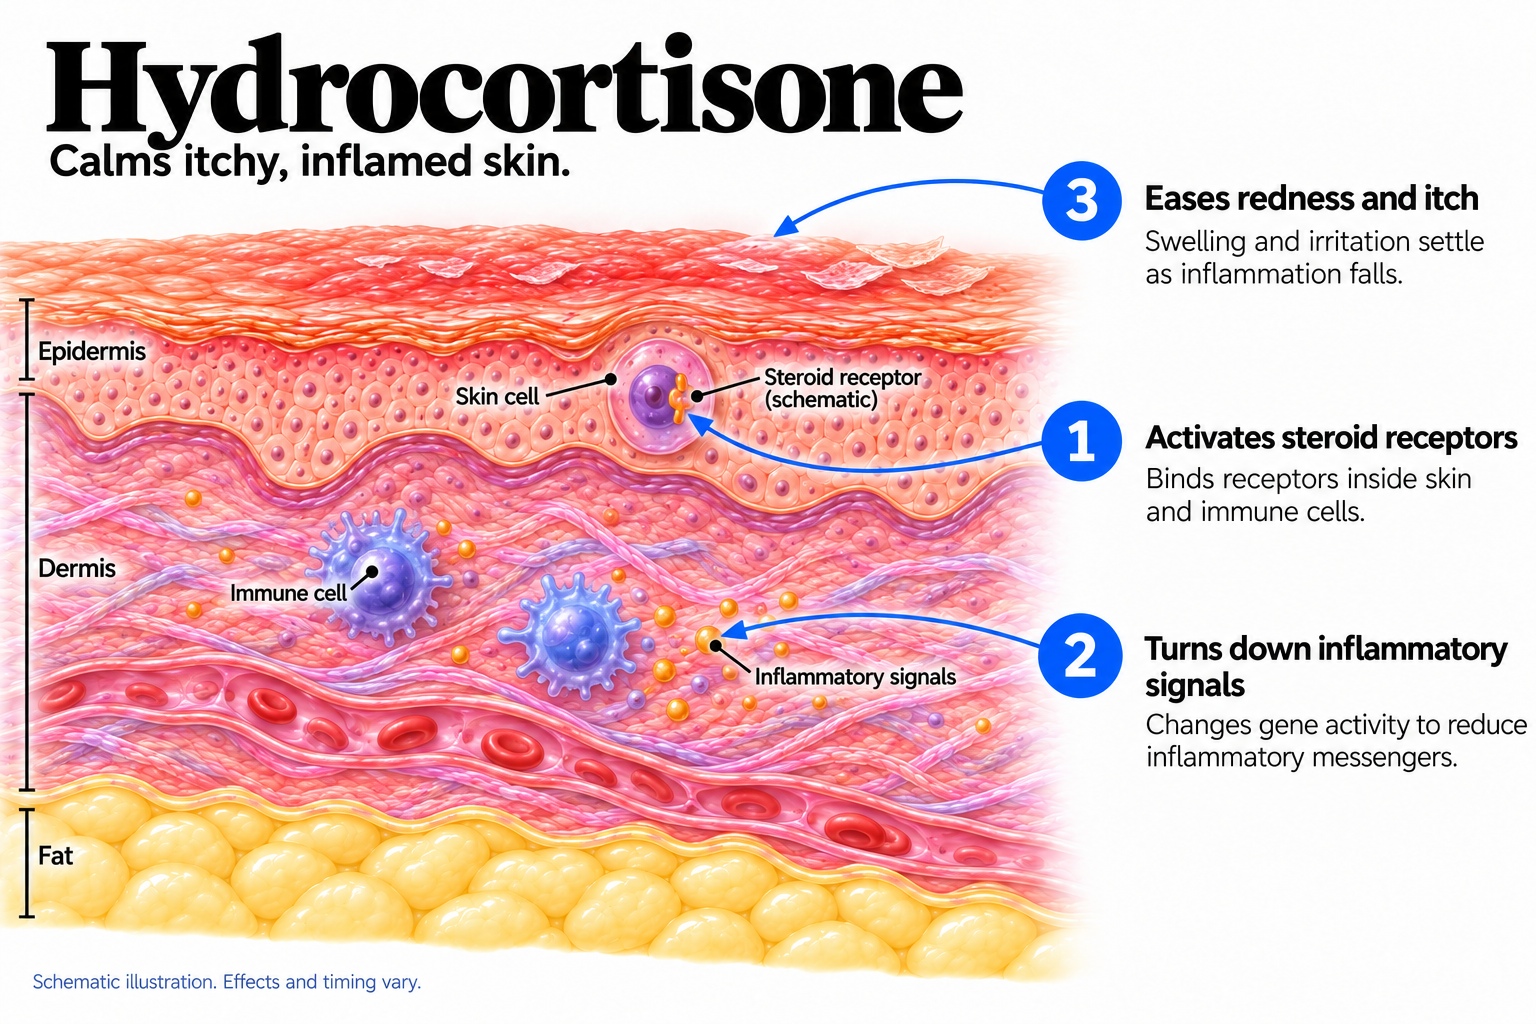
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
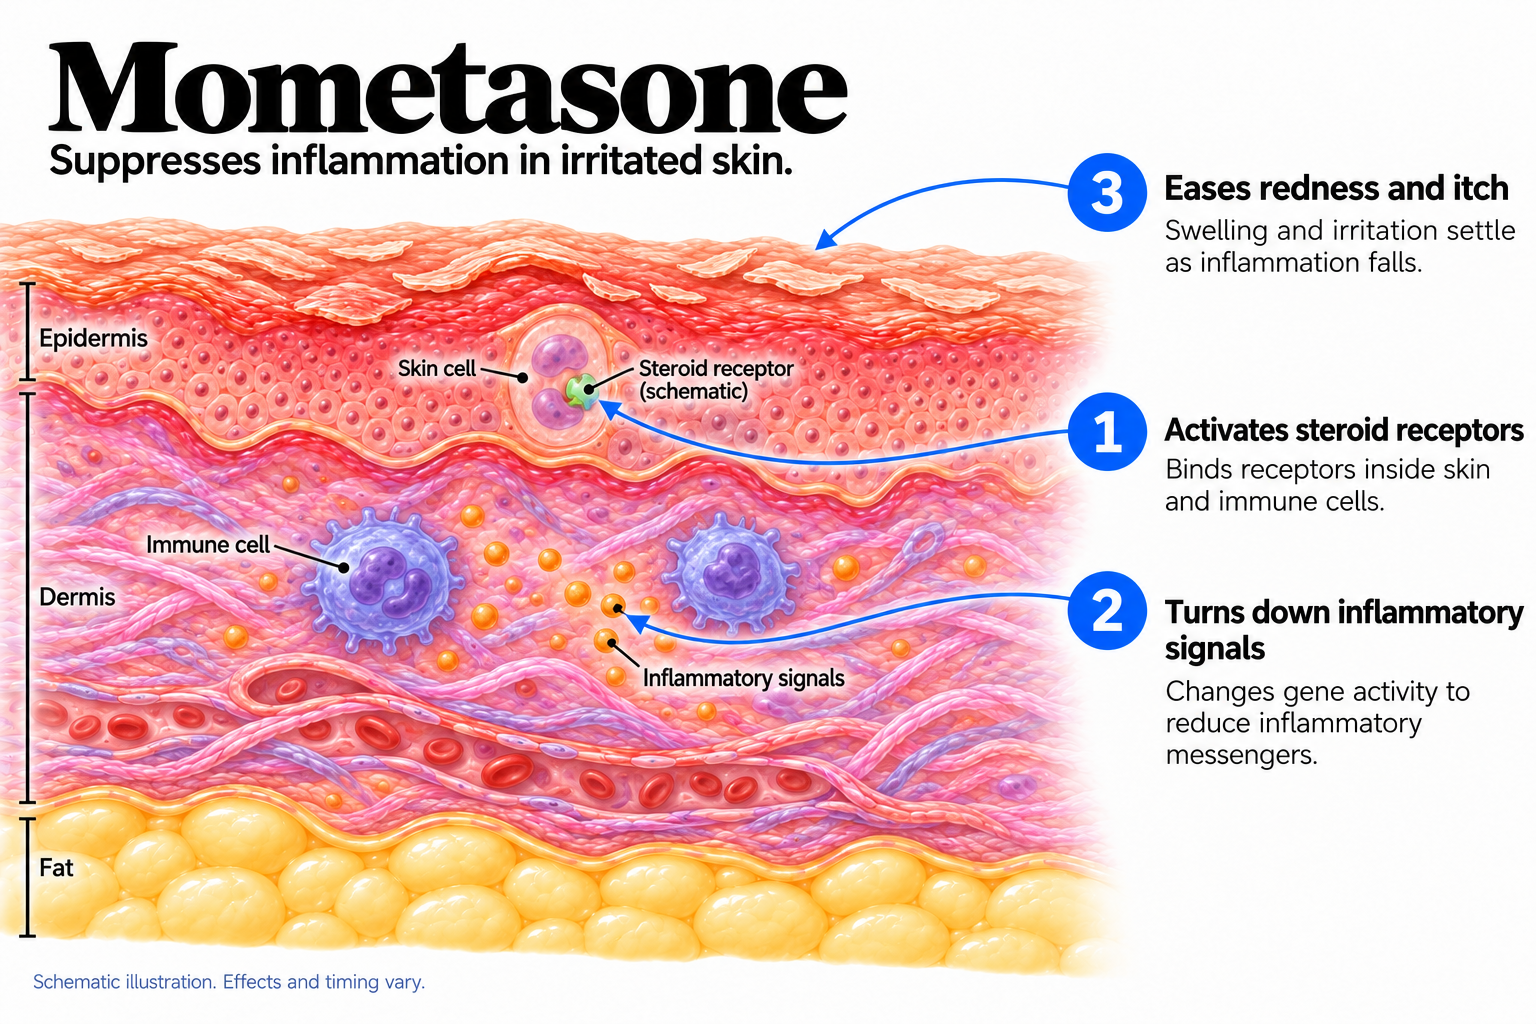
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
When to Apply: Twice a day, on the rash only, on clean dry skin. A thin film that makes the skin look shiny is enough. One fingertip unit, the amount along the last joint of an adult index finger, covers about two adult palms. Moisturizer can go on a few minutes before or after.
How to Start: Twice daily from day one, until the rash is flat rather than merely better. Usually three to seven days. Two weeks is the outer limit for one stretch without seeing a clinician, less on the face.
If It Irritates: Stinging on application is usually the base, not the steroid, and is more likely on broken skin or from an alcohol-containing gel or spray. An ointment often settles it. Itch or redness that worsens over days can mean an allergy to something in the product, which does happen with steroids.
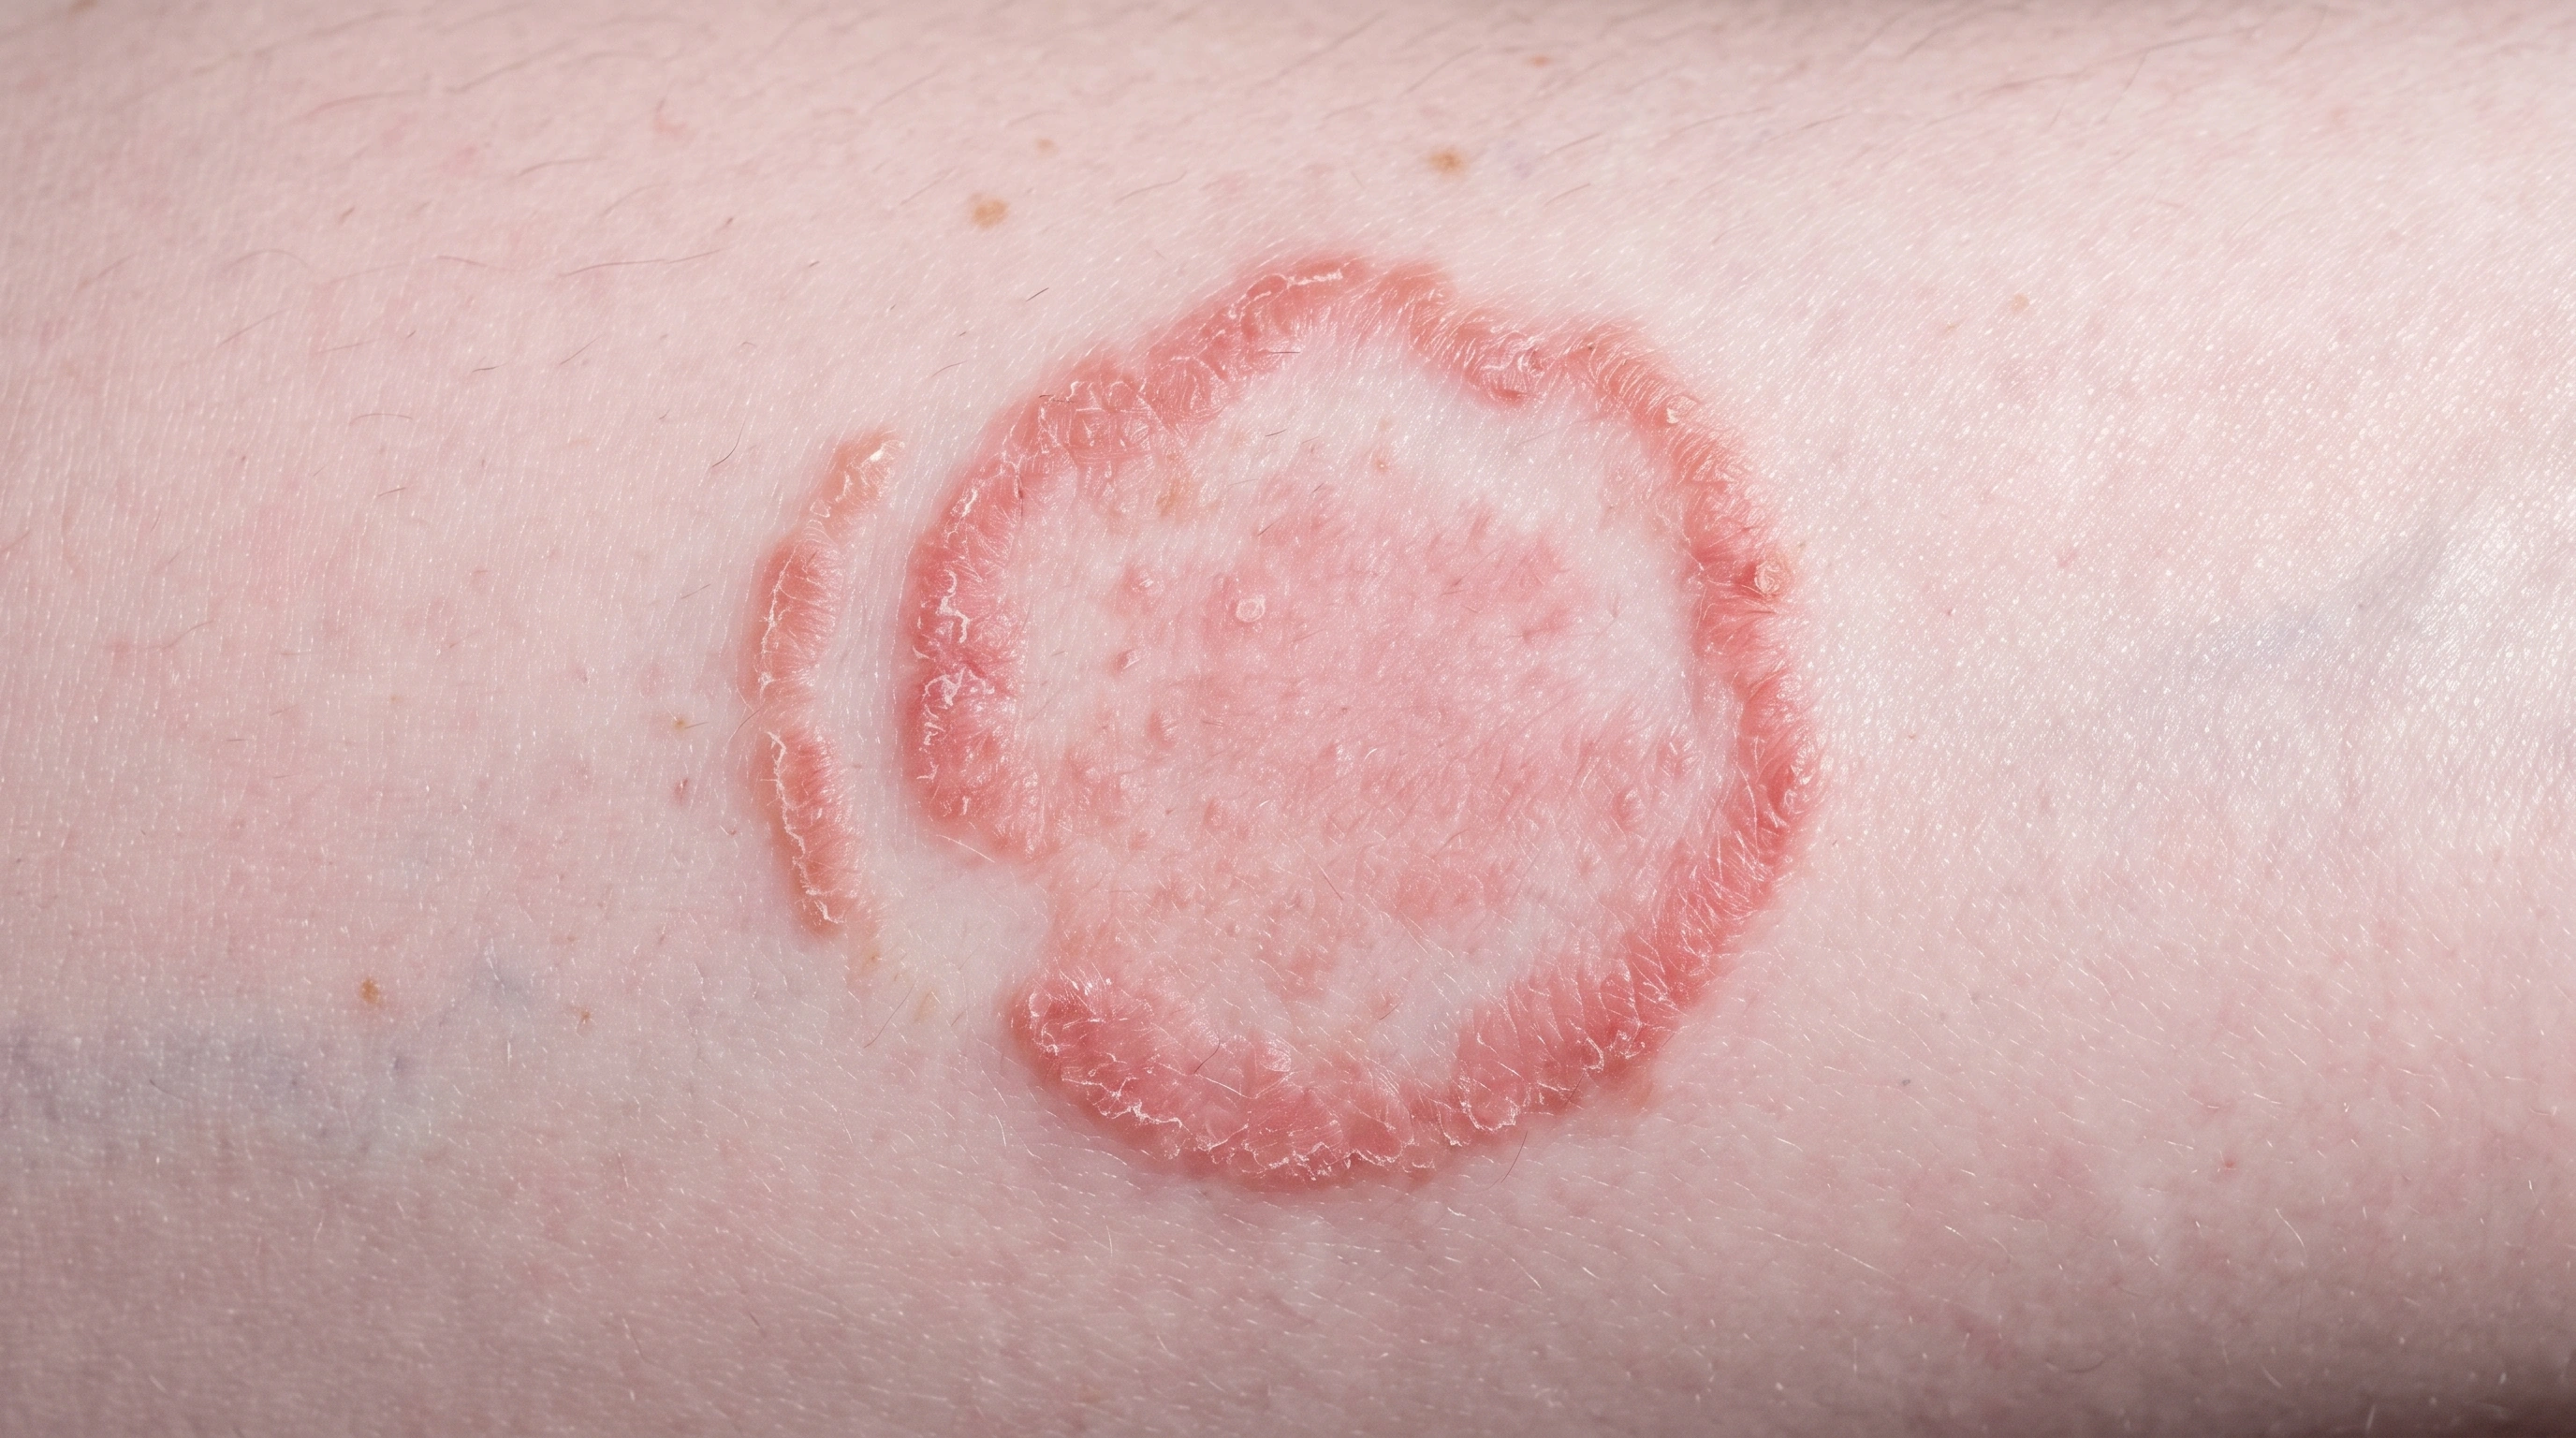
If It Is Not Working: Stop after about a week and reassess. A rash that does not respond to hydrocortisone is often not eczema. Ringworm, a yeast rash in a fold and psoriasis all look plausible and all need something different.
When to Apply: Once a day, a thin film on the rash only, not the skin around it. A fingertip length covers roughly two flat palms. Moisturizer can go on the same skin at other times.
How to Start: Once daily from day one until the skin is smooth and not itchy, usually a few days to two weeks. Under-using it is the commoner mistake. Then stop, or step down to twice a week if your doctor set that up.
If It Irritates: A short sting on cracked or raw skin is common and settles as the skin heals. Moisturizing twenty minutes before or after helps. Burning that worsens over days can mean infection, a reaction to the base, or the wrong diagnosis.
If It’s Not Working: Two weeks of daily use with no change means something else is going on — too little applied, a fungal or infected rash that steroids make worse, or a rash needing a stronger cream or a different drug. Do not keep going past that without a review.
No blood tests are needed for ordinary short courses in a healthy adult. Monitoring means looking at the skin: did the rash clear, has the skin gone thin or shiny, have small blood vessels appeared, are stretch marks forming in the folds.
Children absorb proportionally more because they have more skin surface for their size, so a doctor watches how much is used and over how large an area. Anyone applying a steroid to large areas most days for months should be under review rather than repeating over-the-counter purchases.
Hydrocortisone is not a drug to stay on continuously. Where a condition needs ongoing control, the plan is short bursts for flares, emollients doing the daily work, or a switch to a treatment designed for maintenance.
No blood tests for ordinary use. Monitoring is looking at the skin: is the treated area thinner or shinier than the skin beside it, are small veins showing, are there stretch marks in the folds or pus bumps around hair follicles.
The exception is large-area, long-term or covered use, and use in small children, where enough can be absorbed to affect the body’s own steroid production. Uncommon, and why a doctor sets an area and a time limit.
The checkpoint is a review at two to four weeks. Using it most weeks over months means the question is no longer the cream but what long-term treatment should be doing this job.
Approximate windows, not promises.
First few minutesApplying it: A thin layer on the affected skin. The mildest steroid strength, which is why it is sold over the counter.
First few minutesApplying it: A thin layer once a day, on the affected skin only.
Days 1 to 2Itch first: Itching and stinging ease before the rash looks different, the earliest sign it is working. Insect bites and minor irritation settle in a day or two, and that is the whole course.
Days 3 to 7Clearing: Redness fades and the skin flattens. A mild eczema flare settles here; cracked skin takes longer than skin that was only red. Weeping or crusting should be settling, not spreading.
Weeks 1 to 2Judge it here: A mild rash should be gone or nearly gone. Contact dermatitis clears steadily once the trigger is gone.
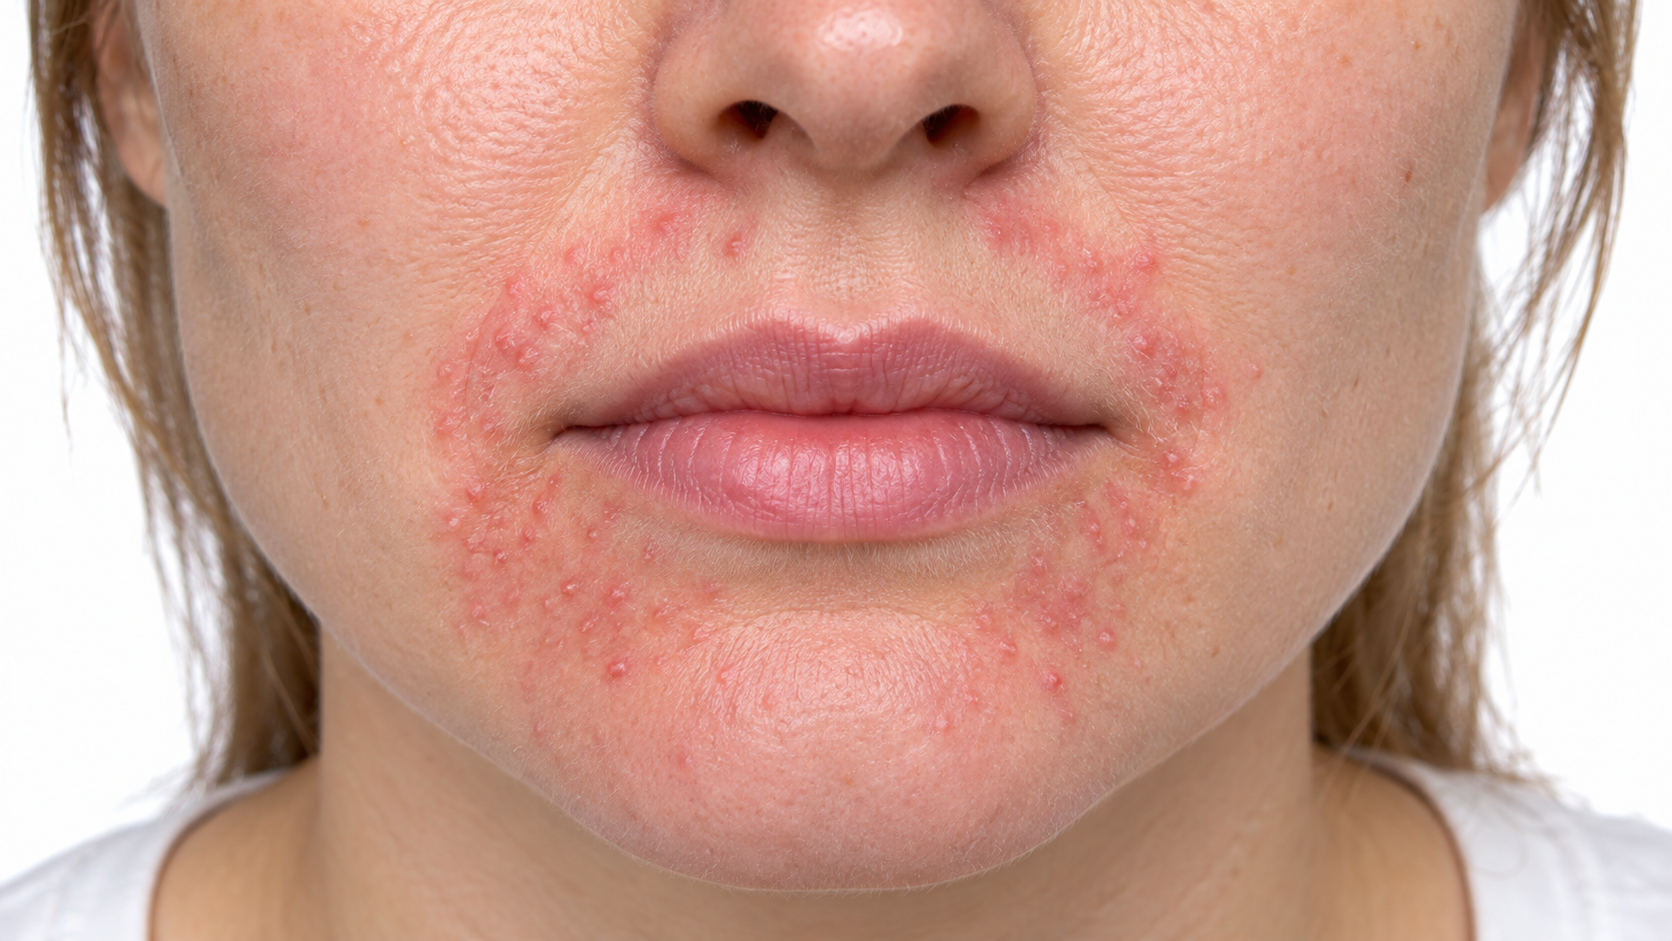
Weeks 2 to 4Mild seborrheic dermatitis: Redness and flaking around the nose and brows improve.
Weeks 2 to 4Judge it here: If it is clear, stop or move to twice-weekly maintenance.
After stoppingMarks stay behind: Brown or gray patches where the rash was are pigment change, not scarring. They fade over weeks to months.
Days 1 to 3Itch first: Itch eases before the rash looks different. Normal, and not a reason to add more.
Days 3 to 14Working: Redness fades, scale flattens, weeping stops. Most short courses finish here, and moisturizer keeps going after the steroid stops.
Weeks 2 to 6Psoriasis plaques: Scale lifts and plaques flatten. Something else usually runs alongside, since steroids rarely hold psoriasis on their own.
Weeks to monthsThickened, leathery patches: Skin rubbed and scratched for a long time takes longest, because the thickening itself has to reverse.
Beyond a few weeks of continuous useThe risks: Thinning skin, visible small veins, stretch marks in folds, small pus bumps around hair follicles. Uncommon on short courses, and why long courses are planned rather than drifted into.
Sorted by what to do about them.
Hydrocortisone is cheap. Store-brand 1% cream is the same drug at the same strength as the branded tube, usually for much less. Anti-itch versions with added ingredients cost more without treating the inflammation any better.
Prescription 2.5% is generic and also cheap, though the visit costs more than the tube. Ointments and creams are the cheapest vehicles. Foams and sprays cost more.
Generic mometasone is inexpensive and widely stocked, and the cream and ointment are on most low-cost generic lists. The Elocon brand costs considerably more for the same molecule.
The lotion and scalp solution usually cost more, and are sometimes the versions a plan will not cover. If cost is the issue, ask whether a different base at the same 0.1% would do the job.
About a week at a time on the body for an over-the-counter tube, less on the face. A rash that needs it longer than two weeks is a reason to be seen, not to buy more.
For a few days, yes, and it is the mildest option there. Facial skin is thin and absorbs well, so weeks of daily use causes thinning, redness and small bumps around the mouth.
No. It is the bottom of the potency ladder. If a week of it has not worked, question the diagnosis.
A short course on the body will not. Thinning comes from stronger steroids over long periods, especially on the face, eyelids, groin and armpits. Early changes usually recover over months. Stretch marks are permanent.
It can. Pale patches on treated skin show up more on deeper skin tones, and usually fade slowly after stopping. Untreated inflammation also leaves light and dark marks, so avoiding treatment is not a way around it.
Not on its own. A steroid makes ringworm and yeast harder to recognize while they keep spreading. Diaper areas are covered, so absorption is higher, worth having a child's rash there looked at.
Two to four weeks on a defined area. Longer should be your doctor's decision, usually as twice-weekly maintenance.
Only if your doctor said so, and briefly. Facial skin absorbs far more and shows thinning first. Milder or non-steroid creams are usually chosen there.
Yes, and you should — at a different time of day, so you are not diluting the steroid or spreading it beyond the rash.
The steroid treated the inflammation, not the cause. Expected in eczema and psoriasis, and why maintenance and steady moisturizing matter.
Yes. It was developed for once-daily use and the trials were done that way. Twice a day adds side effect risk without benefit.
A short sting on broken skin is common and settles. Burning that builds over days, or a worsening rash, can mean infection or a reaction to the base.