Psoriasis
Thins plaques, best with a steroid.
Calcipotriene: A vitamin D-like cream or ointment for plaque psoriasis. It slows the overgrowth of skin cells that makes plaques thick and scaly, and it is not a steroid. Mometasone: A mid-strength prescription steroid applied once a day for eczema, psoriasis and other itchy rashes. Strong enough to settle a flare, measured enough for short courses on most of the body.


Choose for long-term psoriasis control without a steroid, often after a short combined course settles redness.
Choose to settle an eczema or psoriasis flare on the body with a once-daily, mid-strength steroid.
Can you take them together?
A common psoriasis pairing: mometasone calms plaques quickly and calcipotriene helps keep them clear, for example steroid on weekends and calcipotriene on weekdays.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

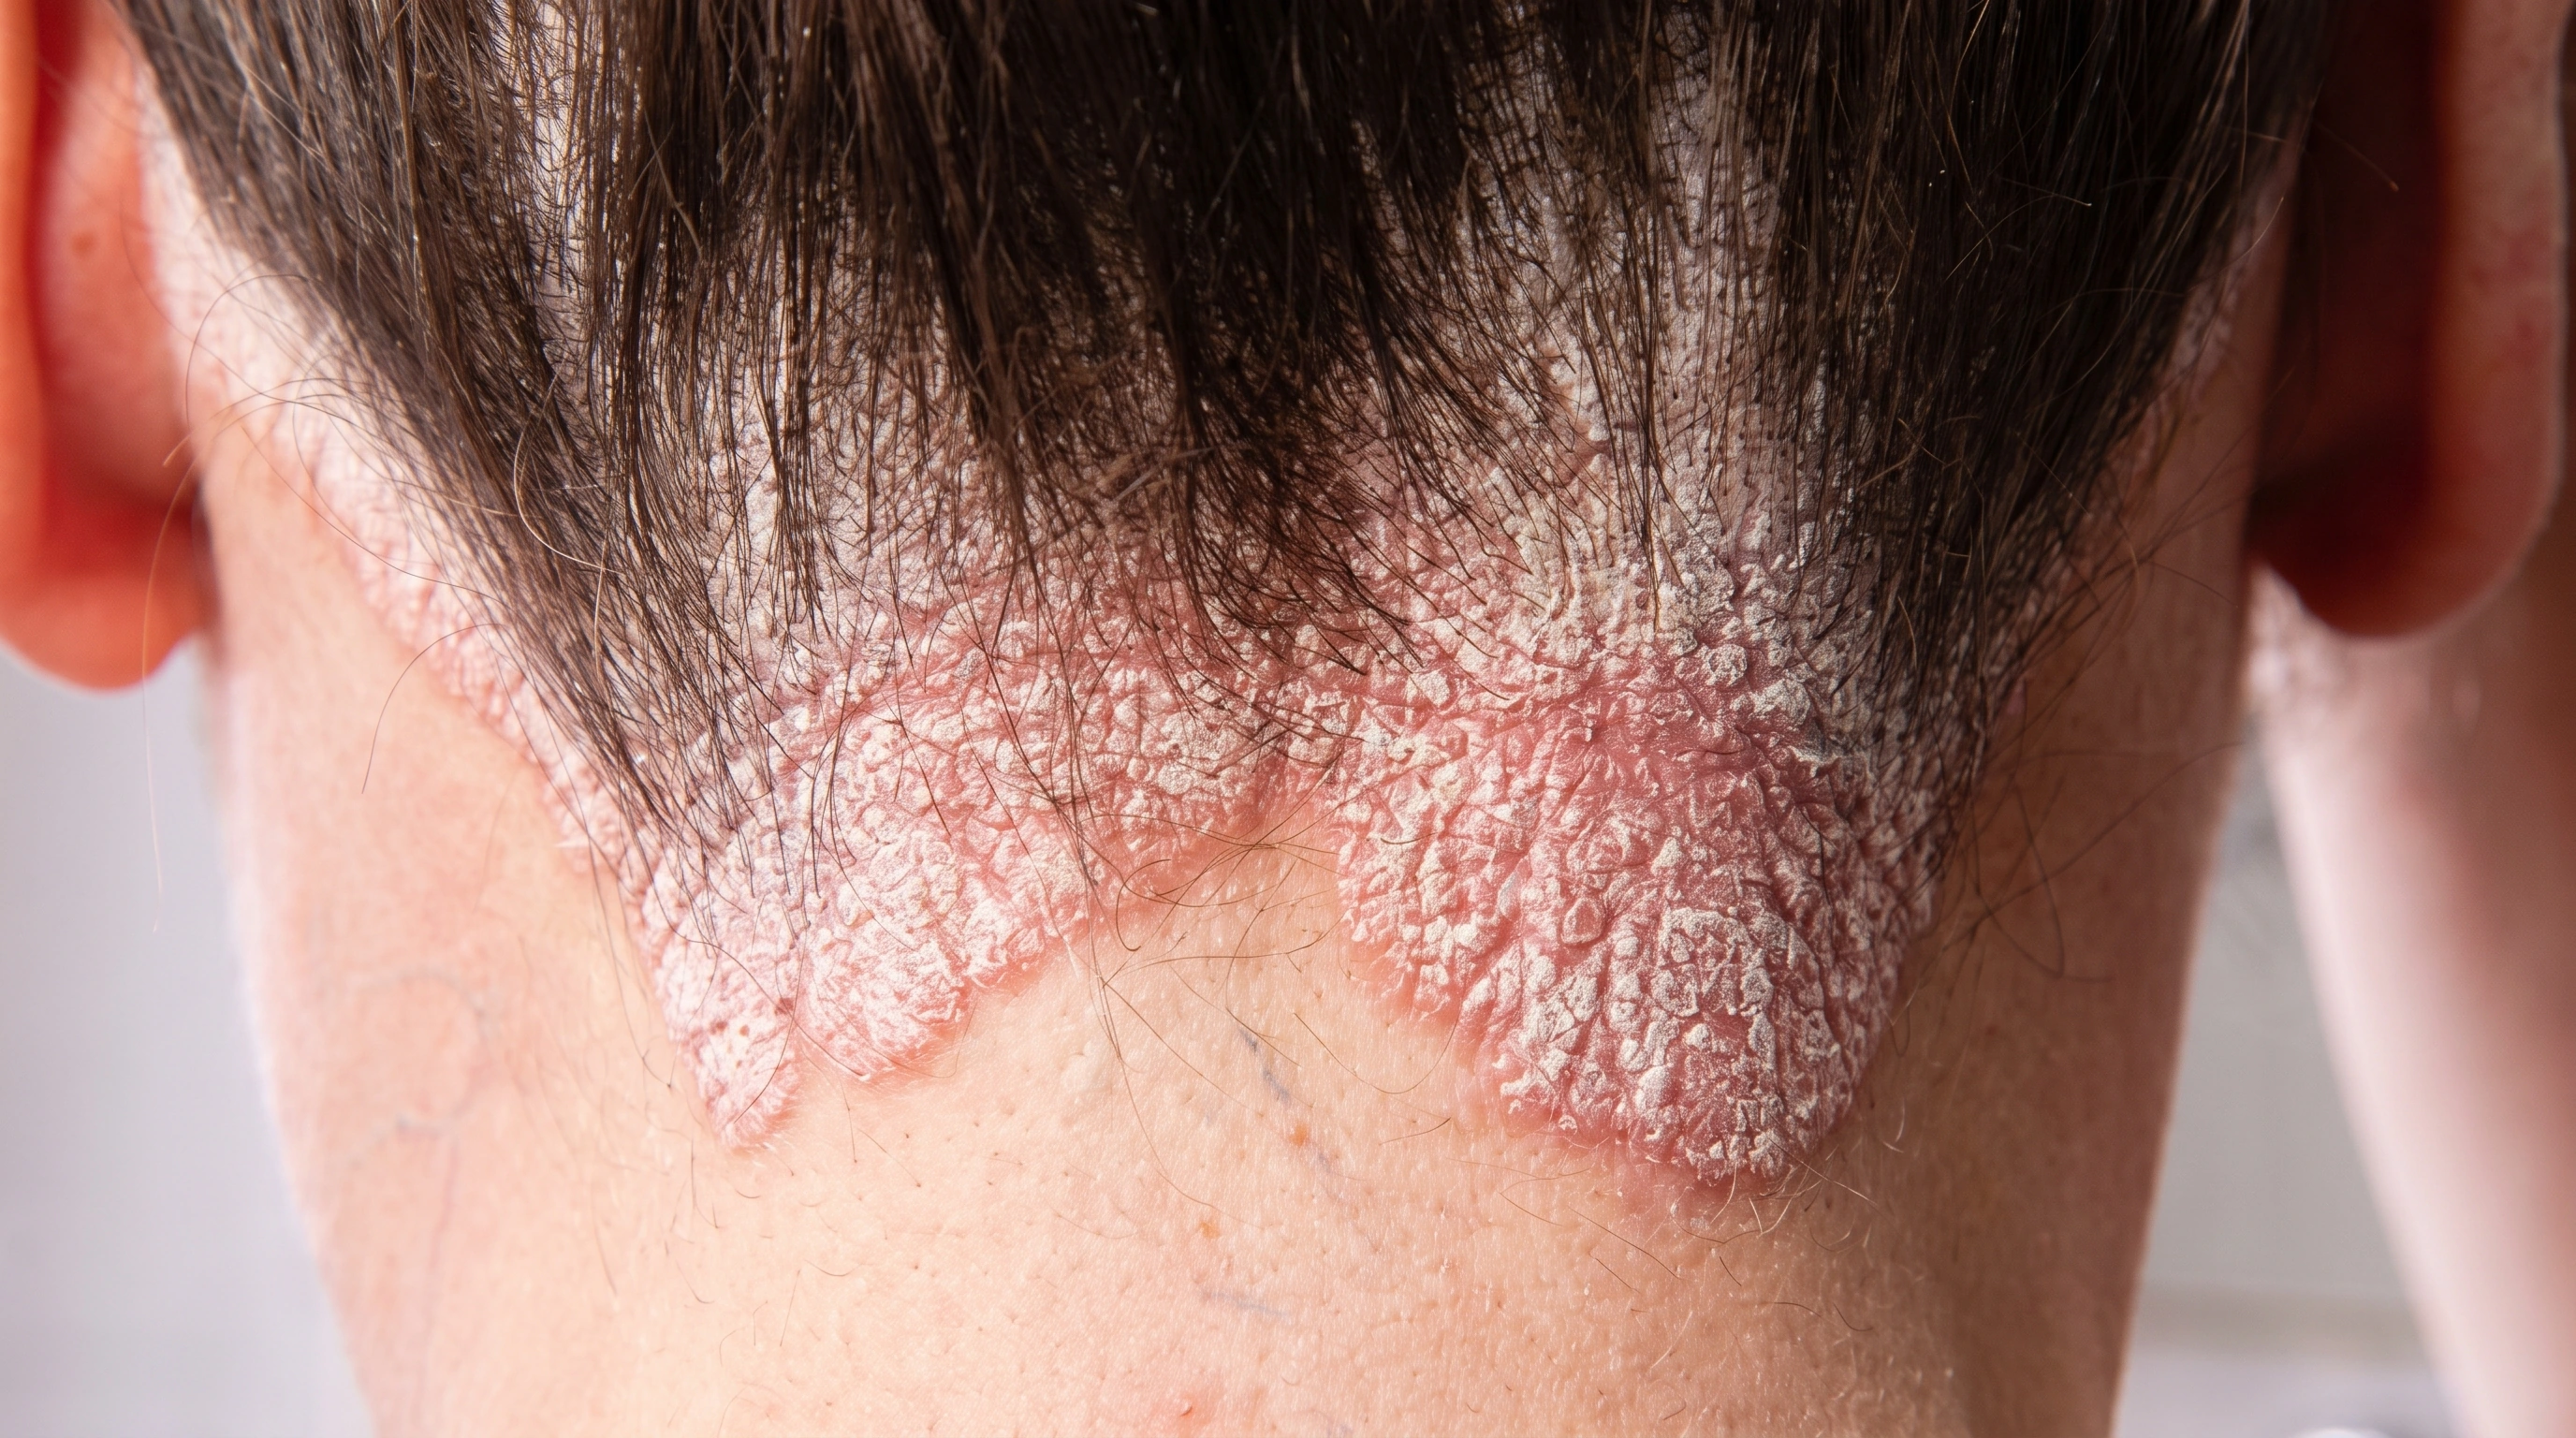
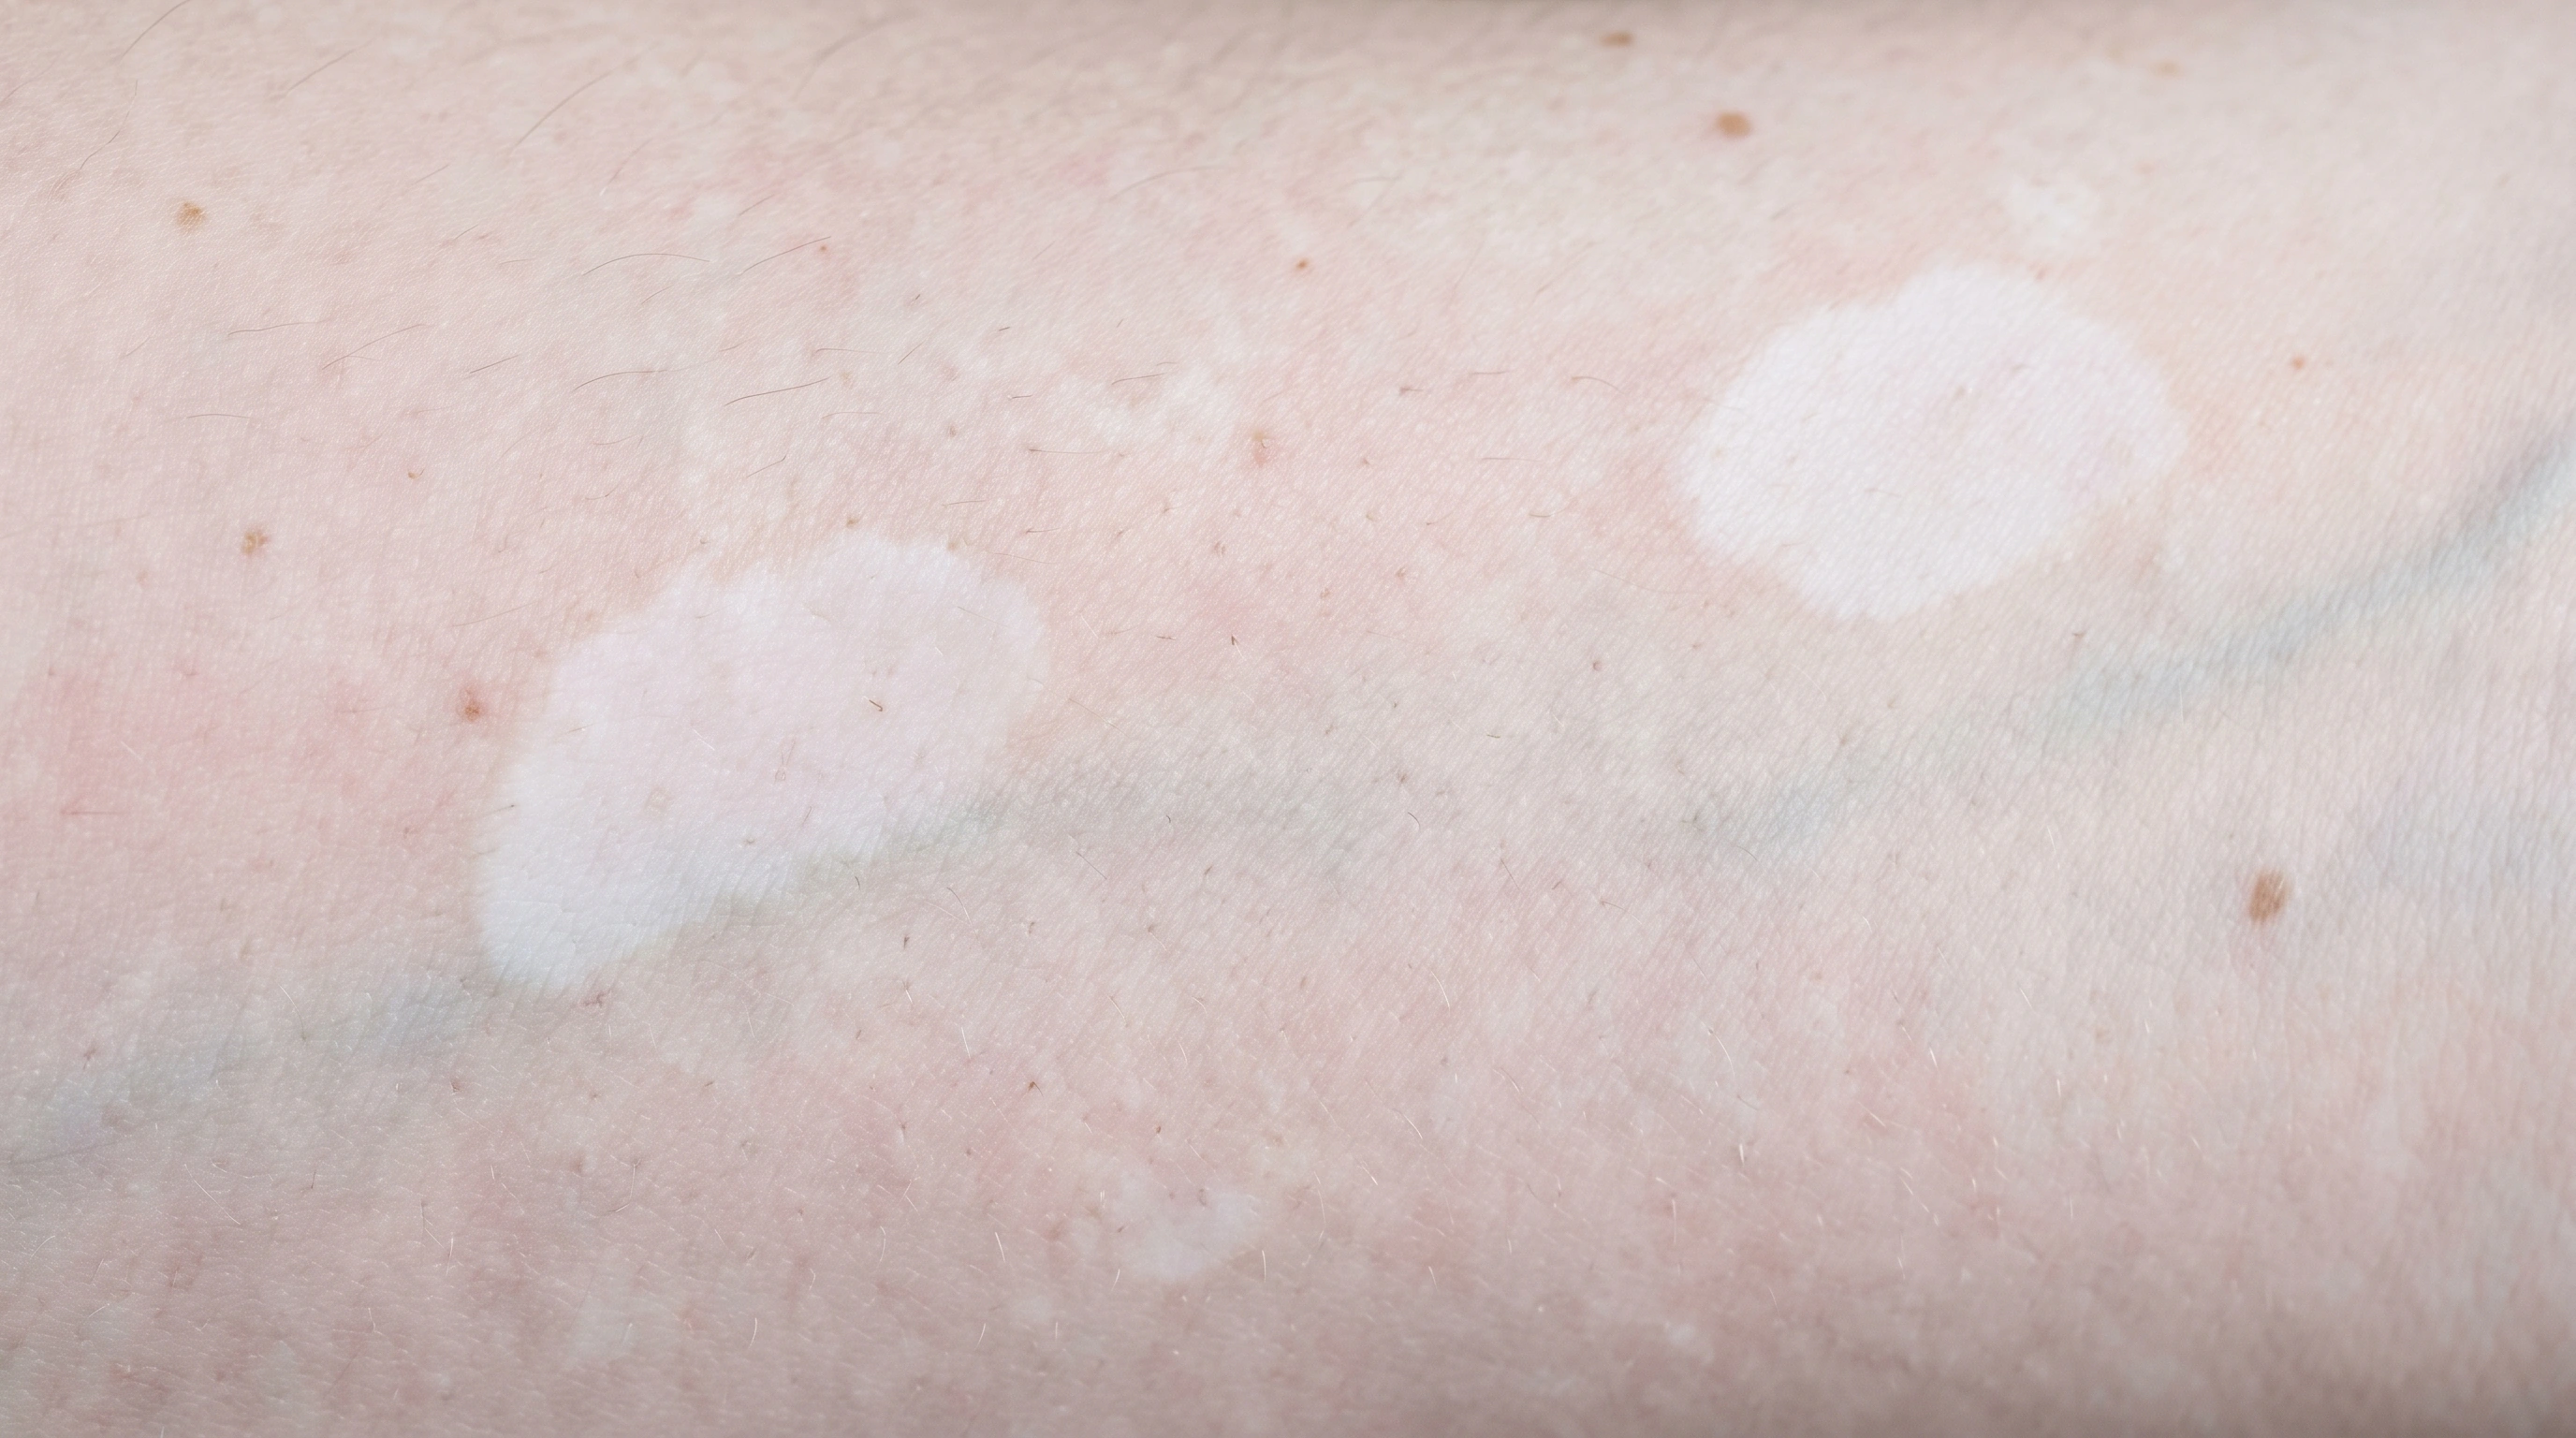
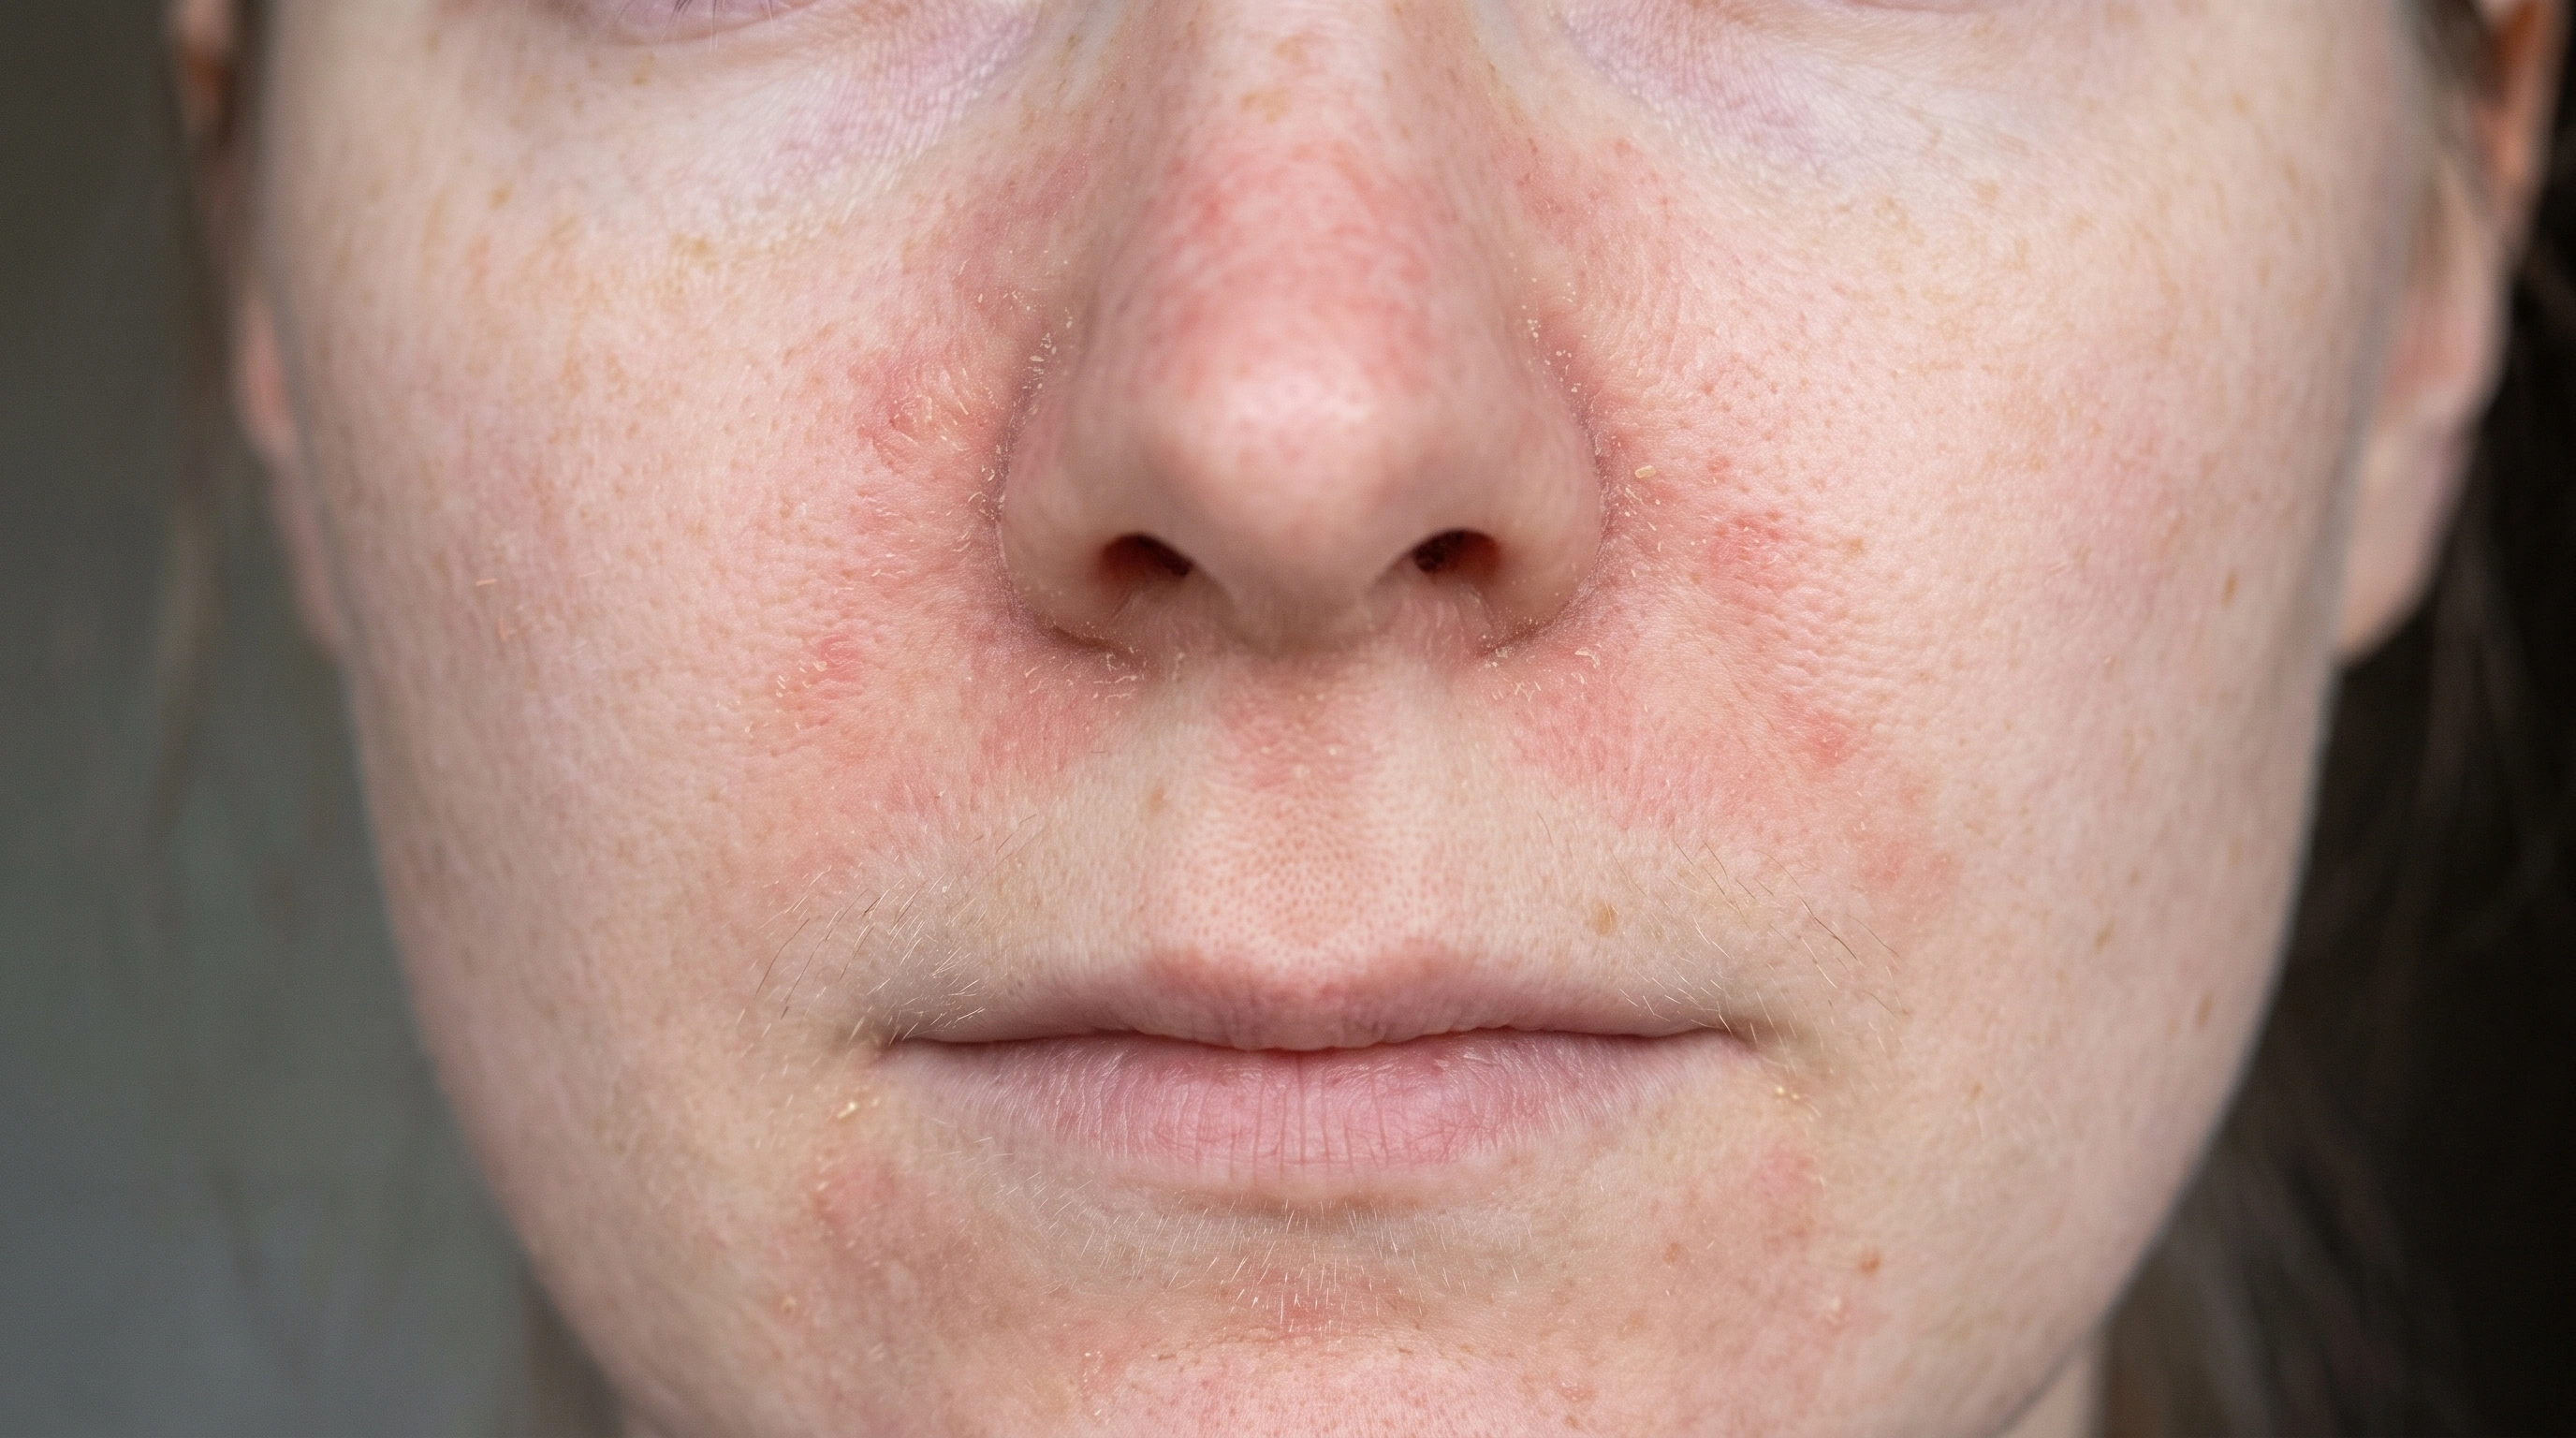

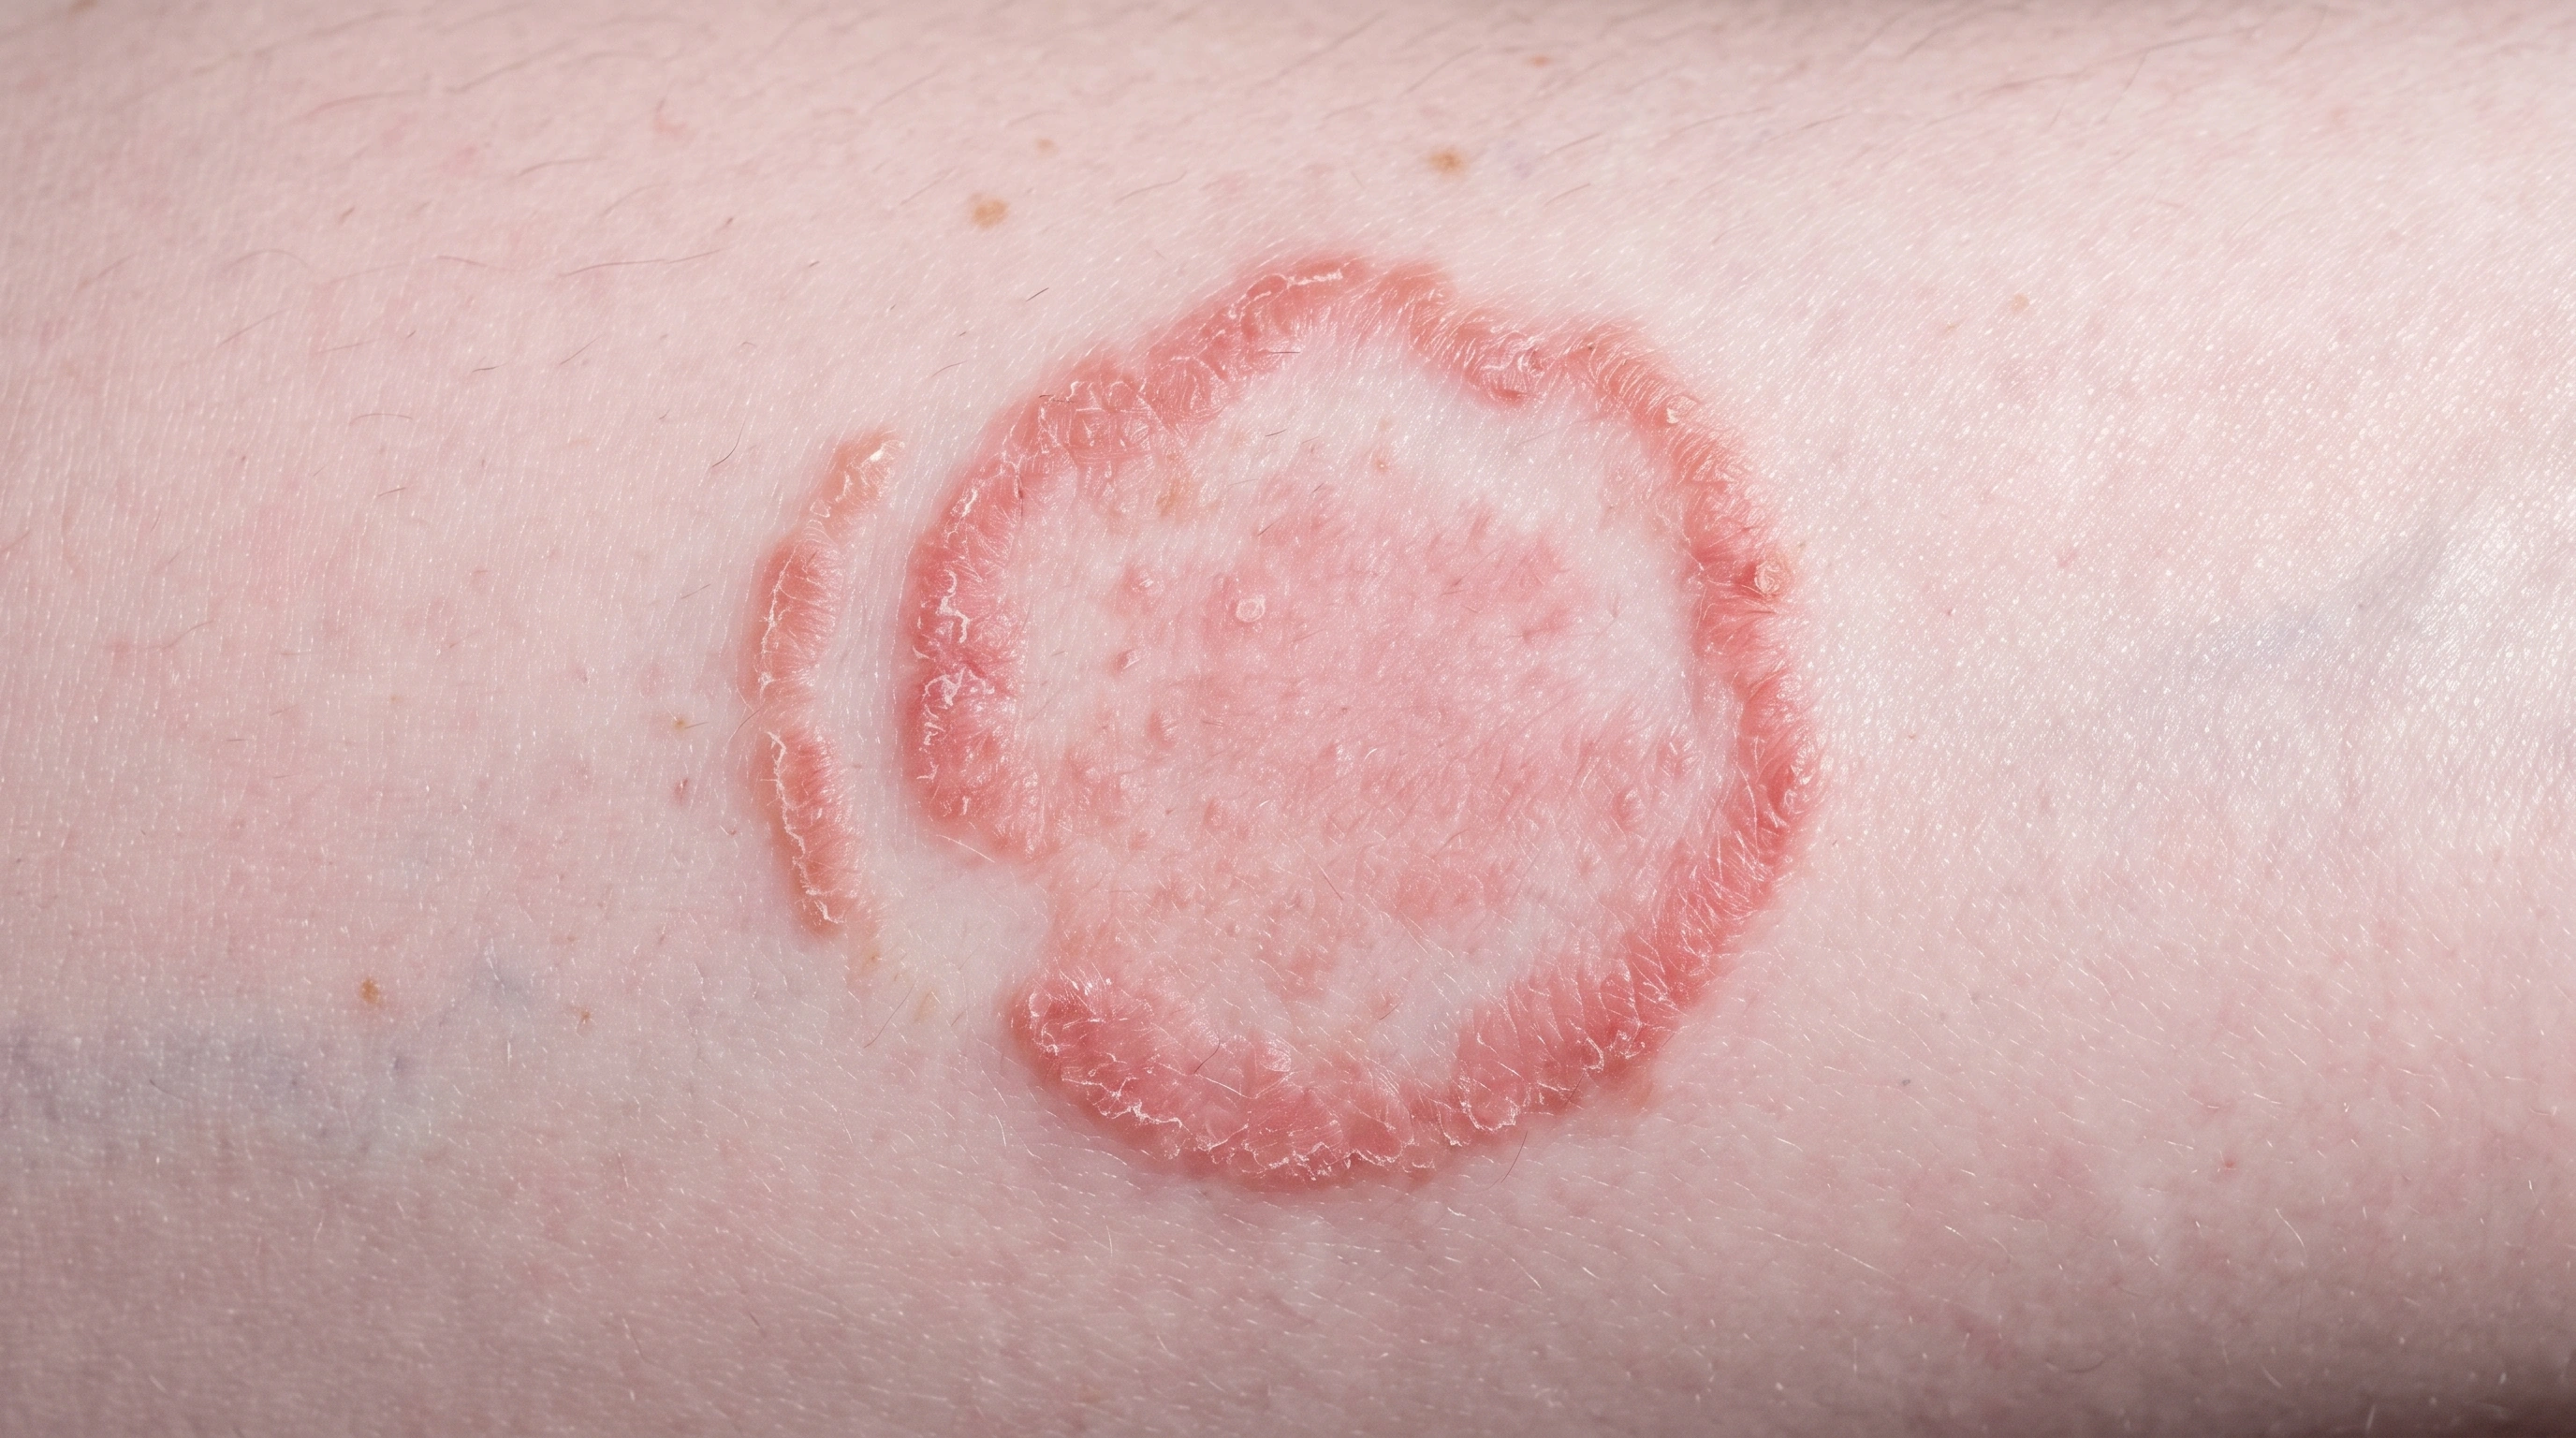

Activates vitamin D receptors: Changes signals inside skin cells. Slows excess cell growth: Helps reduce the rapid buildup seen in psoriasis. Improves cell maturation: Helps cells develop into more normal skin layers. Reduces plaque scale: Thick, scaly patches gradually become flatter.
Calcipotriene is a vitamin D analog with effects on cell proliferation and differentiation. Its complete antipsoriatic mechanism is not established; this is a simplified overview.
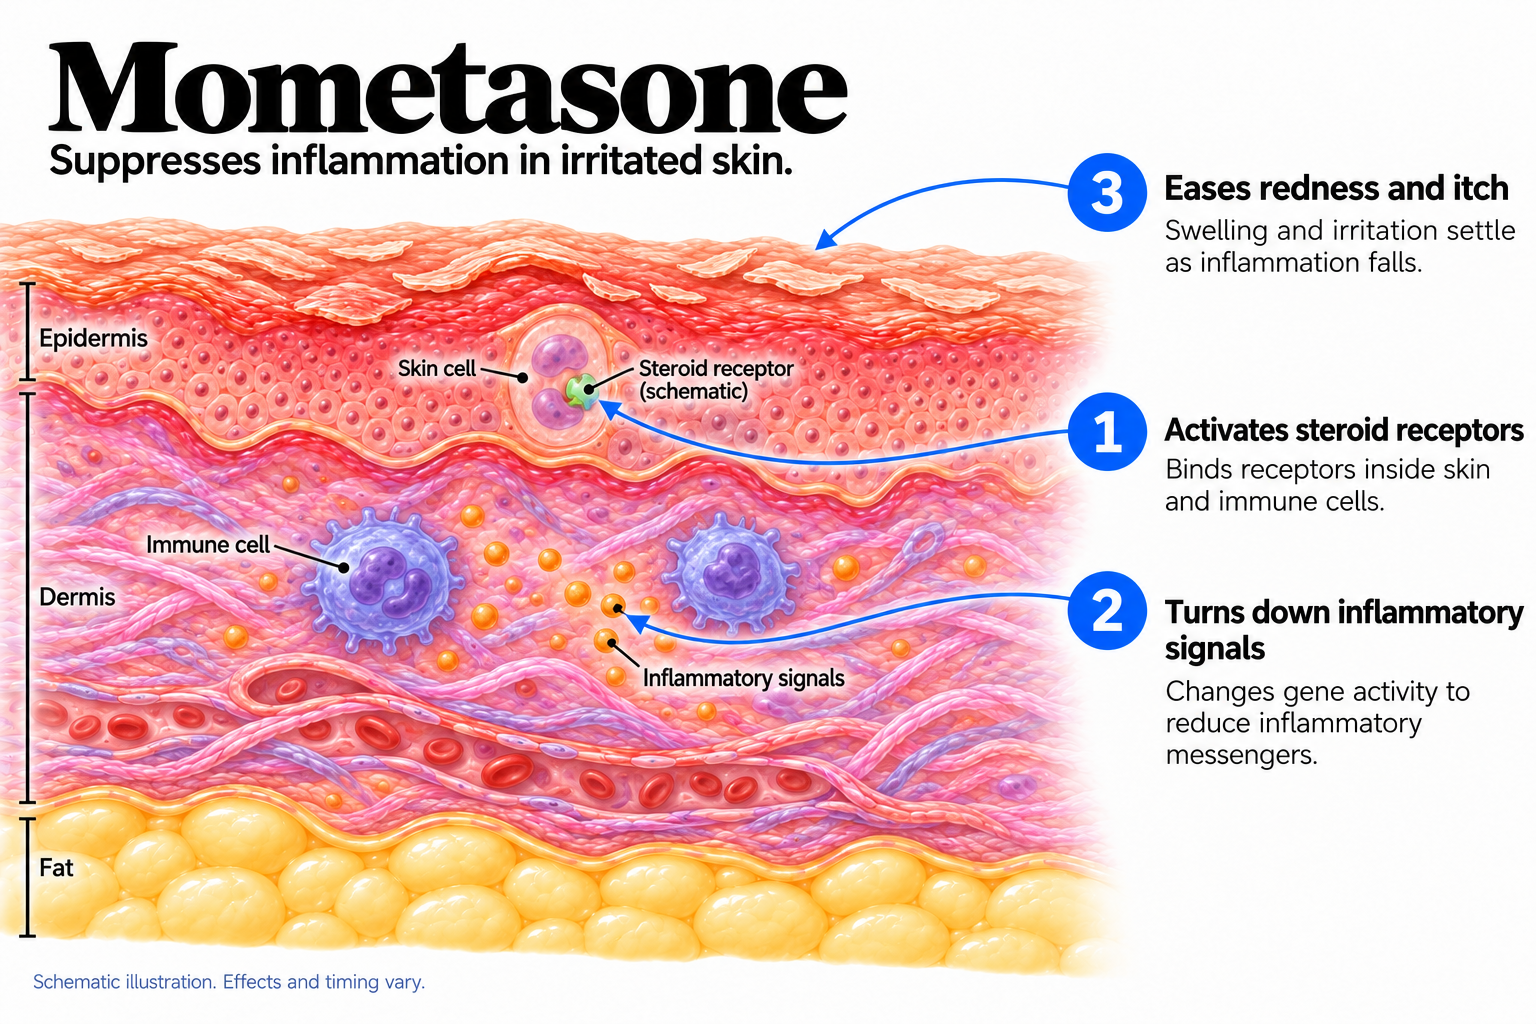
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
When to Apply: Twice a day for the plain product, thinly onto the plaques only. Once a day for the combined calcipotriene-and-steroid products. Do not use more than about 100 grams a week, and do not treat more than roughly a third of the body surface. With phototherapy, apply it after the session, not before.
How to Start: Full dose from day one, on the plaques only. Many start on a combined calcipotriene-and-steroid product for the first few weeks to settle redness, then continue on calcipotriene alone.
If It Irritates: Burning and stinging in the first days is usual and often settles. Moisturizer first, or once a day for a week, helps. Irritation on the face, eyelids, groin or under the breasts is not one to push through — thin skin, and this drug is not made for it. Sharp burning on broken skin means waiting for it to close over.
If It’s Not Working: There is only one strength, so nothing can be increased. Give it six to eight weeks. If plaques are still thick, the next steps are the combined product with a steroid, switching cream for ointment, adding phototherapy, or a tablet or injection. Also check what else is going on the skin — salicylic acid inactivates calcipotriene.
When to Apply: Once a day, a thin film on the rash only, not the skin around it. A fingertip length covers roughly two flat palms. Moisturizer can go on the same skin at other times.
How to Start: Once daily from day one until the skin is smooth and not itchy, usually a few days to two weeks. Under-using it is the commoner mistake. Then stop, or step down to twice a week if your doctor set that up.
If It Irritates: A short sting on cracked or raw skin is common and settles as the skin heals. Moisturizing twenty minutes before or after helps. Burning that worsens over days can mean infection, a reaction to the base, or the wrong diagnosis.
If It’s Not Working: Two weeks of daily use with no change means something else is going on — too little applied, a fungal or infected rash that steroids make worse, or a rash needing a stronger cream or a different drug. Do not keep going past that without a review.
No routine blood tests when it is used normally: plaques only, within the weekly amount, healthy kidneys.
The one thing watched for is raised blood calcium. It is rare, and it comes from using far more than recommended, treating very large areas, or kidney disease that stops the body clearing the extra calcium. Calcium may be checked if any of those apply, or if you take high-dose vitamin D or calcium supplements. Symptoms are unusual thirst, passing more urine than usual, nausea, constipation, muscle weakness and confusion.
Monitoring is otherwise clinical — the skin at six to eight weeks, and how much of a tube is used per week. With the combined steroid product, the review also covers how long the steroid has run.
Long term, calcipotriene alone is a drug you can stay on. Nothing accumulates and it does not thin skin, which is why it is the usual maintenance between steroid courses.
No blood tests for ordinary use. Monitoring is looking at the skin: is the treated area thinner or shinier than the skin beside it, are small veins showing, are there stretch marks in the folds or pus bumps around hair follicles.
The exception is large-area, long-term or covered use, and use in small children, where enough can be absorbed to affect the body’s own steroid production. Uncommon, and why a doctor sets an area and a time limit.
The checkpoint is a review at two to four weeks. Using it most weeks over months means the question is no longer the cream but what long-term treatment should be doing this job.
Approximate windows, not promises.
First few minutesApplying it: Stinging or burning, if it happens, is worst at the start and eases.
First few minutesApplying it: A thin layer once a day, on the affected skin only.
Weeks 1 to 2Starting: Early flattening and less scale. Its strongest effect, and what people notice first.
Weeks 2 to 6The steady phase: Plaques thin and the silvery scale falls away. Redness fades more slowly than thickness, the main reason calcipotriene and a steroid are combined. Itch improves, slower than with a steroid.
Weeks 2 to 6Psoriasis plaques: Scale lifts and plaques flatten. Something else usually runs alongside, since steroids rarely hold psoriasis on their own.
Weeks 6 to 8Judge it here: Roughly where the effect plateaus in trials.
ScalpWhere it is used most: The scalp solution and the combined foam or gel work well here.
Long termMaintenance: Used between steroid courses, it holds the result. Stopped, plaques return over weeks to months.
Days 1 to 3Itch first: Itch eases before the rash looks different. Normal, and not a reason to add more.
Days 3 to 14Working: Redness fades, scale flattens, weeping stops. Most short courses finish here, and moisturizer keeps going after the steroid stops.
Weeks 2 to 4Judge it here: If it is clear, stop or move to twice-weekly maintenance.
Weeks to monthsThickened, leathery patches: Skin rubbed and scratched for a long time takes longest, because the thickening itself has to reverse.
Beyond a few weeks of continuous useThe risks: Thinning skin, visible small veins, stretch marks in folds, small pus bumps around hair follicles. Uncommon on short courses, and why long courses are planned rather than drifted into.
Sorted by what to do about them.
Generic calcipotriene is cheap and widely available; cost is rarely the barrier for the plain ointment or cream.
The branded combination products, and the foam and suspension forms, cost substantially more and often need prior authorization. Plans usually want a topical steroid, and often generic calcipotriene, tried first.
If cost decides it, generic ointment or cream plus a separate generic steroid does much the same job, at the price of two tubes.
Generic mometasone is inexpensive and widely stocked, and the cream and ointment are on most low-cost generic lists. The Elocon brand costs considerably more for the same molecule.
The lotion and scalp solution usually cost more, and are sometimes the versions a plan will not cover. If cost is the issue, ask whether a different base at the same 0.1% would do the job.
No. A vitamin D analog. It does not thin skin, which is why it can be used long term and is often the maintenance treatment after a steroid course.
No. The face, eyelids, groin and under the breasts all sting badly — thin skin. Ask about a different product for those areas.
About 100 grams a week, and about a third of the body surface. That limit keeps blood calcium from rising.
Irritation is the most common side effect, worst in the first days. Moisturizer first, or once a day for a week or two, settles it.
Not at the same time. Salicylic acid inactivates calcipotriene. Keep them well apart in the day or ask about an alternative.
Not for normal use with healthy kidneys. Calcium may be checked with kidney disease, very large amounts, or high-dose vitamin D.
Two to four weeks on a defined area. Longer should be your doctor's decision, usually as twice-weekly maintenance.
Only if your doctor said so, and briefly. Facial skin absorbs far more and shows thinning first. Milder or non-steroid creams are usually chosen there.
Yes, and you should — at a different time of day, so you are not diluting the steroid or spreading it beyond the rash.
The steroid treated the inflammation, not the cause. Expected in eczema and psoriasis, and why maintenance and steady moisturizing matter.
Yes. It was developed for once-daily use and the trials were done that way. Twice a day adds side effect risk without benefit.
A short sting on broken skin is common and settles. Burning that builds over days, or a worsening rash, can mean infection or a reaction to the base.