Eczema
Rapidly controls severe flares.
Cyclosporine: A strong oral immune-suppressing drug used in short bursts for severe eczema and psoriasis. It works faster than anything else, and blood pressure and kidney function set a hard limit on how long anyone stays on it. Hydrocortisone: The mildest topical steroid, and the only one sold without a prescription. It is the usual starting point for the face, for skin folds and for young children.


Choose for a fast, short burst of control in severe eczema or psoriasis while a longer-term treatment is set up.
Choose as the first step for mild rashes on the face, folds or young children — the only steroid sold without a prescription.
Can you take them together?
Hydrocortisone can be used on the face or folds during a cyclosporine course. They do not interact.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.



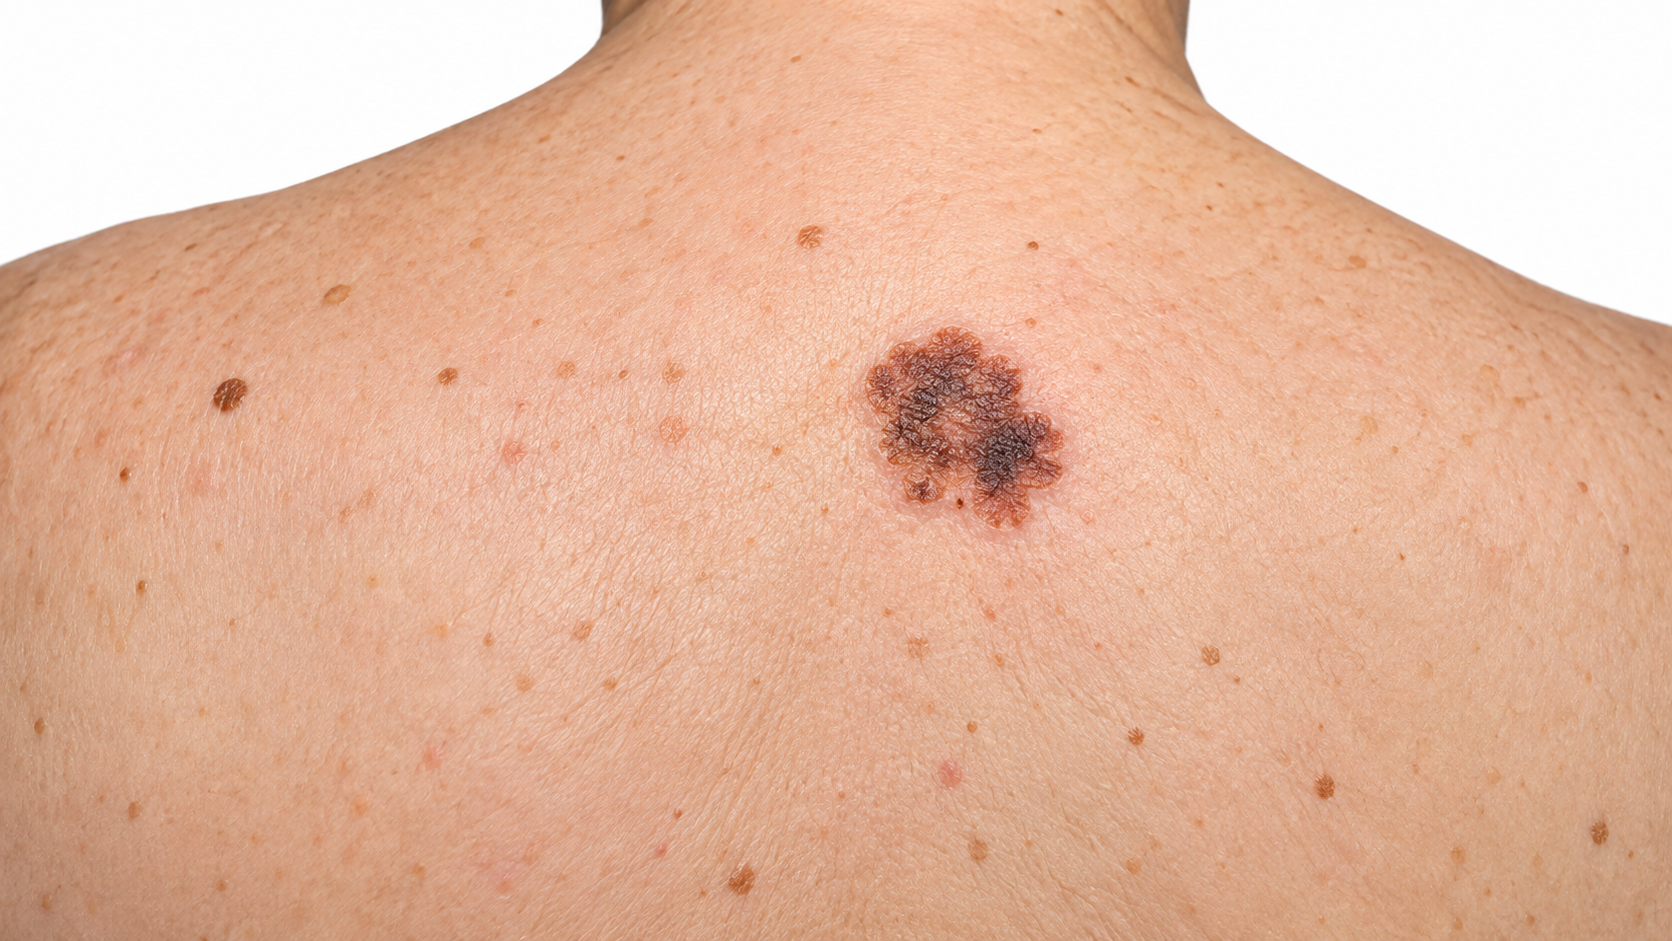
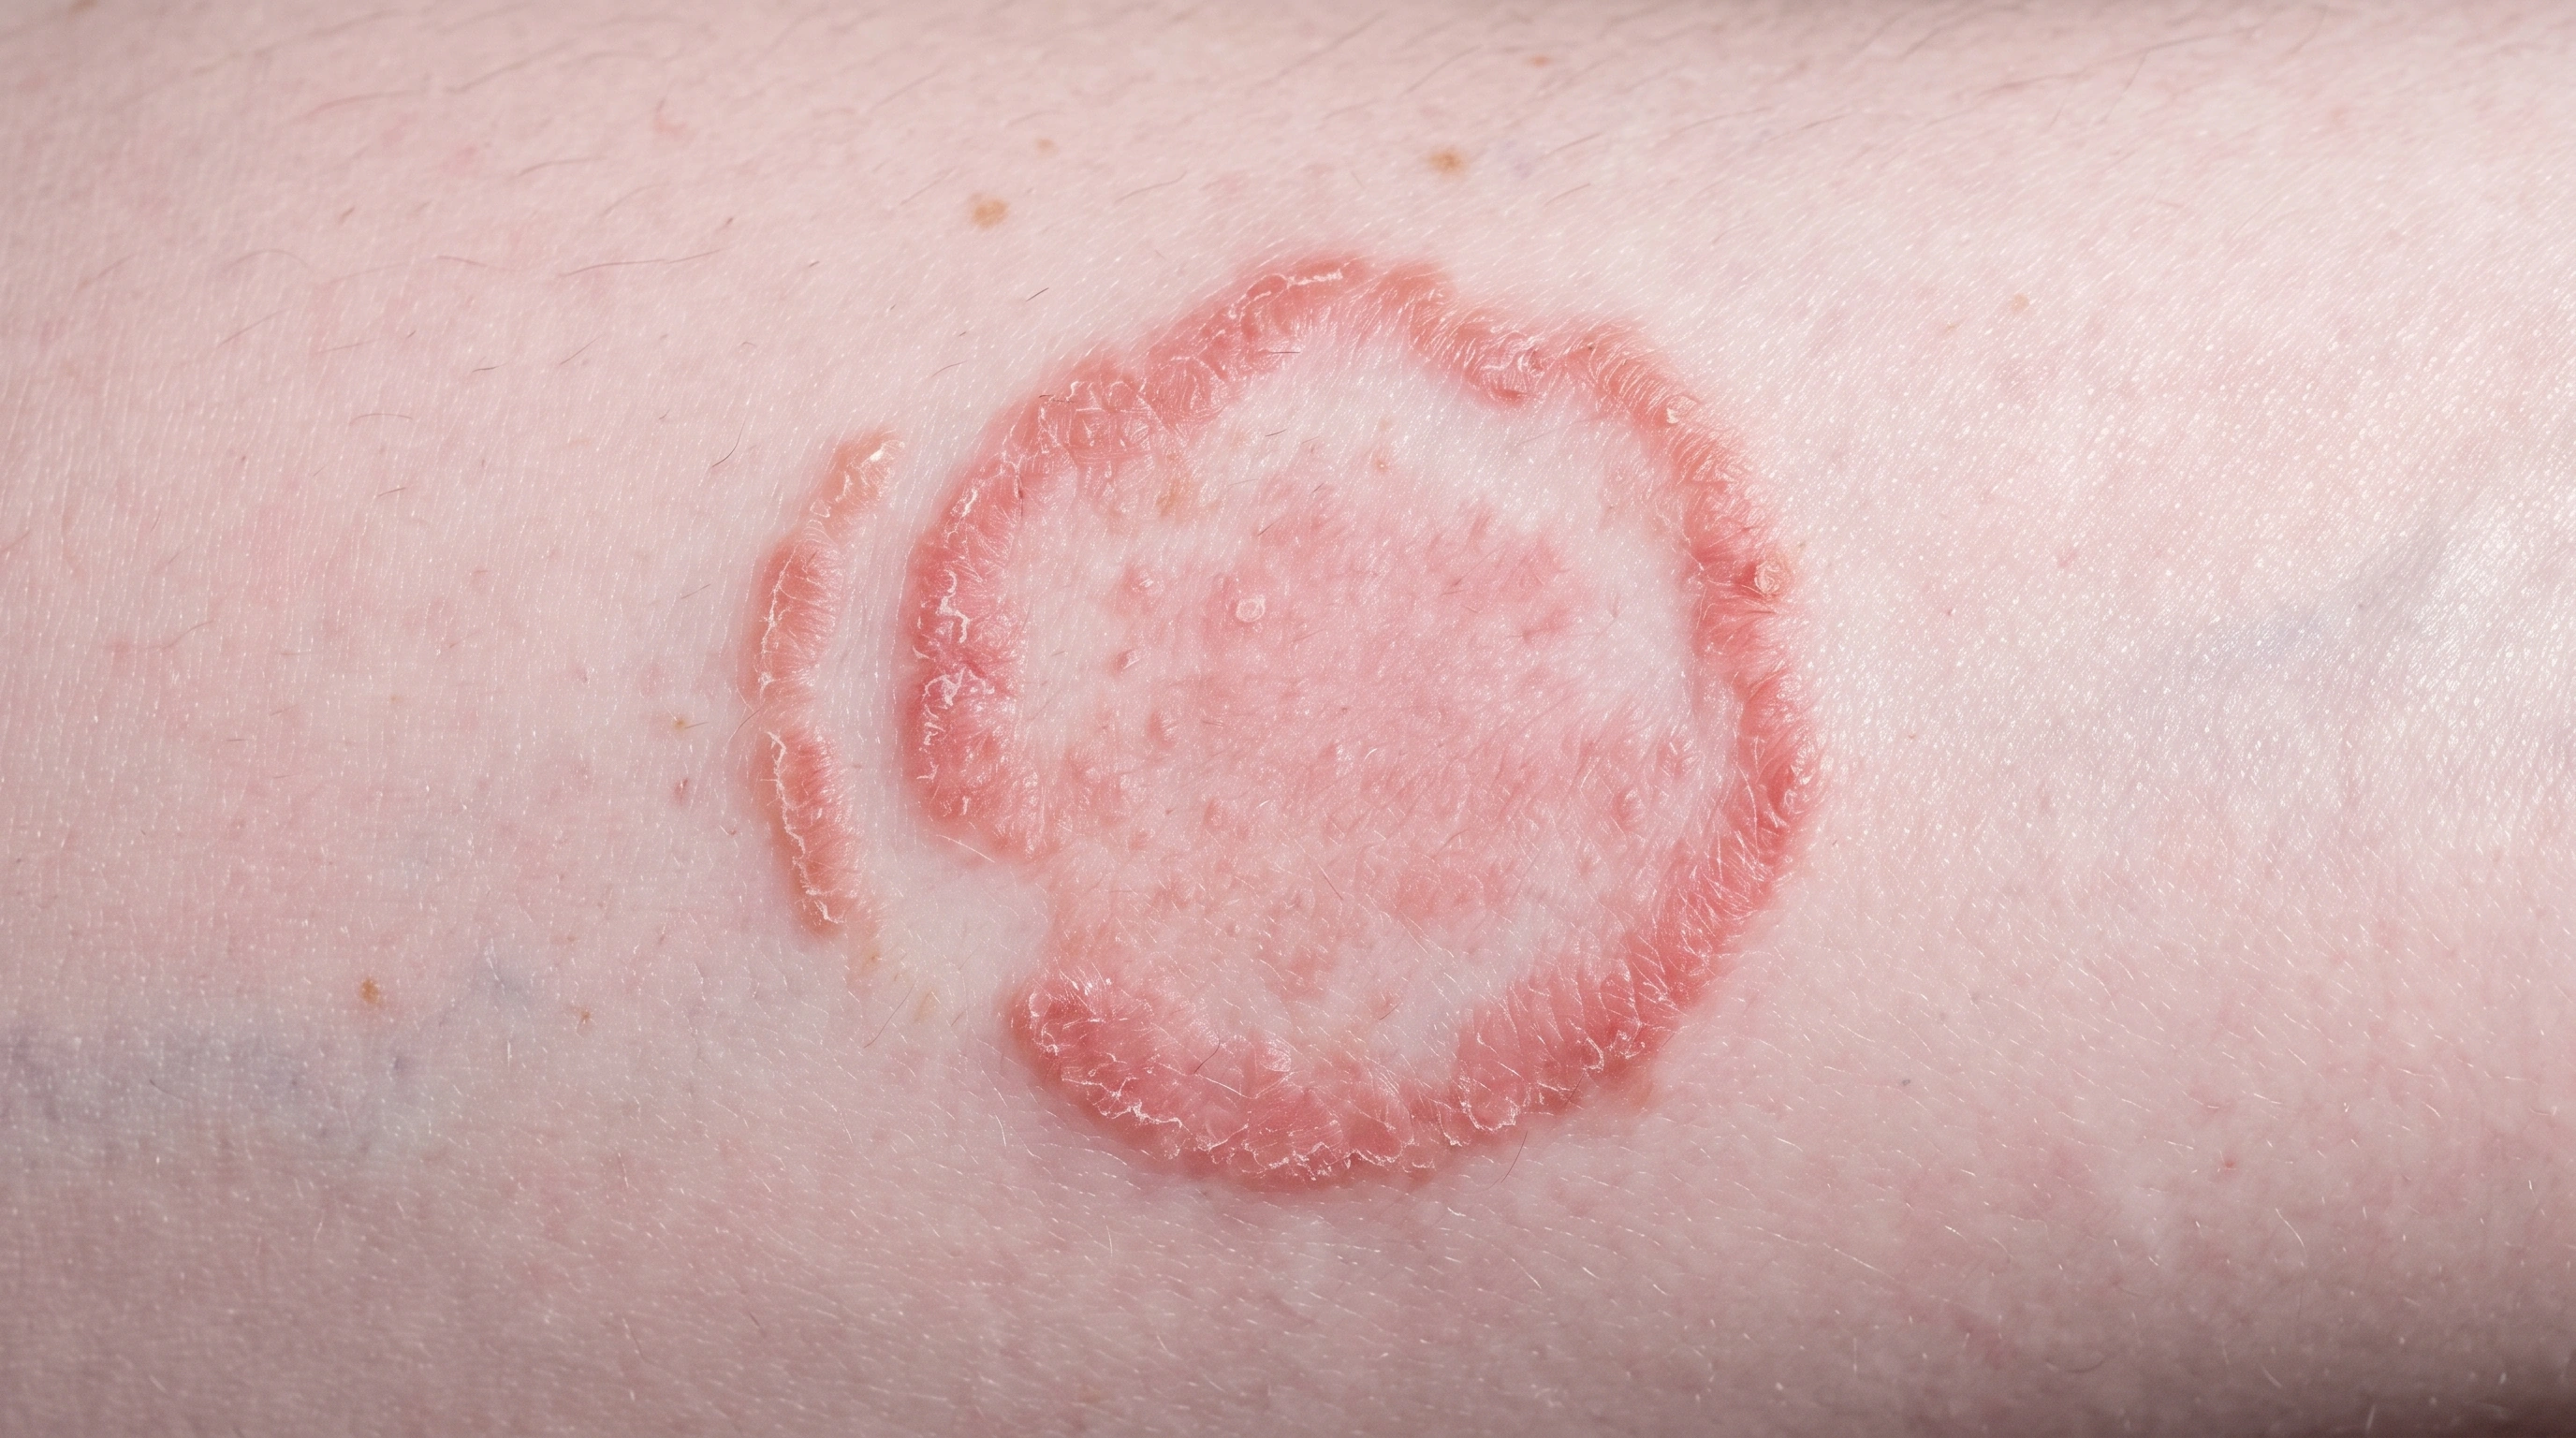
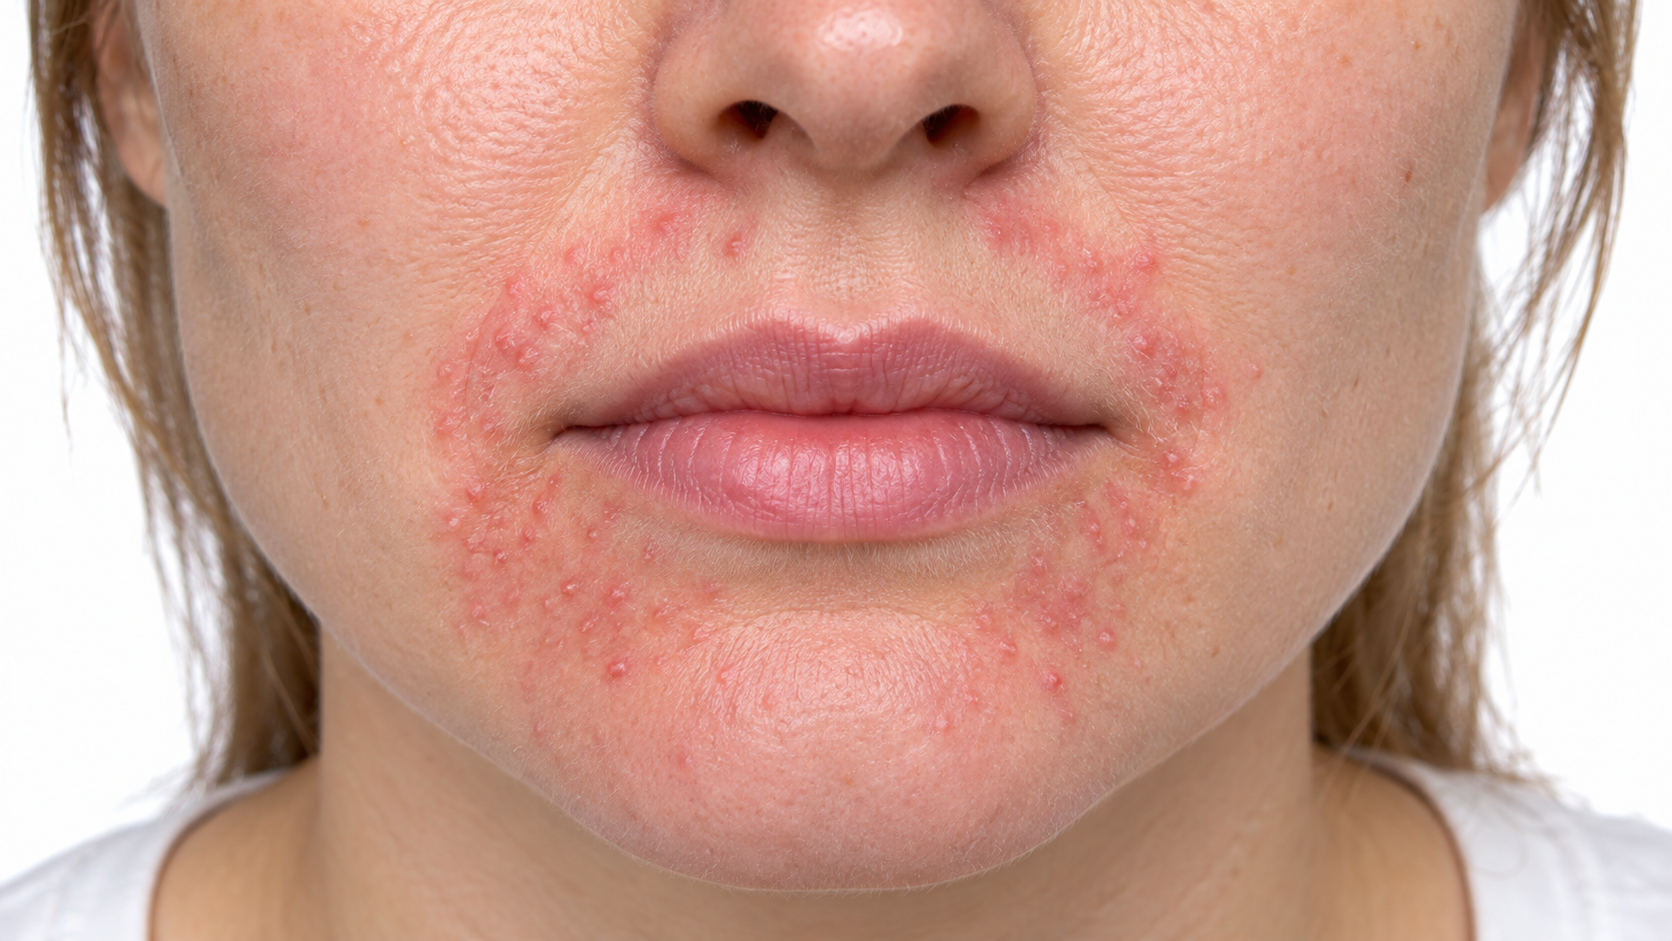

Inhibits calcineurin: Binds cyclophilin to block a T-cell activation switch. Reduces IL-2 signals: Limits a messenger that helps T cells become active. Calms skin inflammation: Overactive immune responses in skin decrease.
Cyclosporine binds cyclophilin; that complex inhibits calcineurin and T-cell cytokine production. This is a simplified skin-focused explanation of systemic immunosuppression.
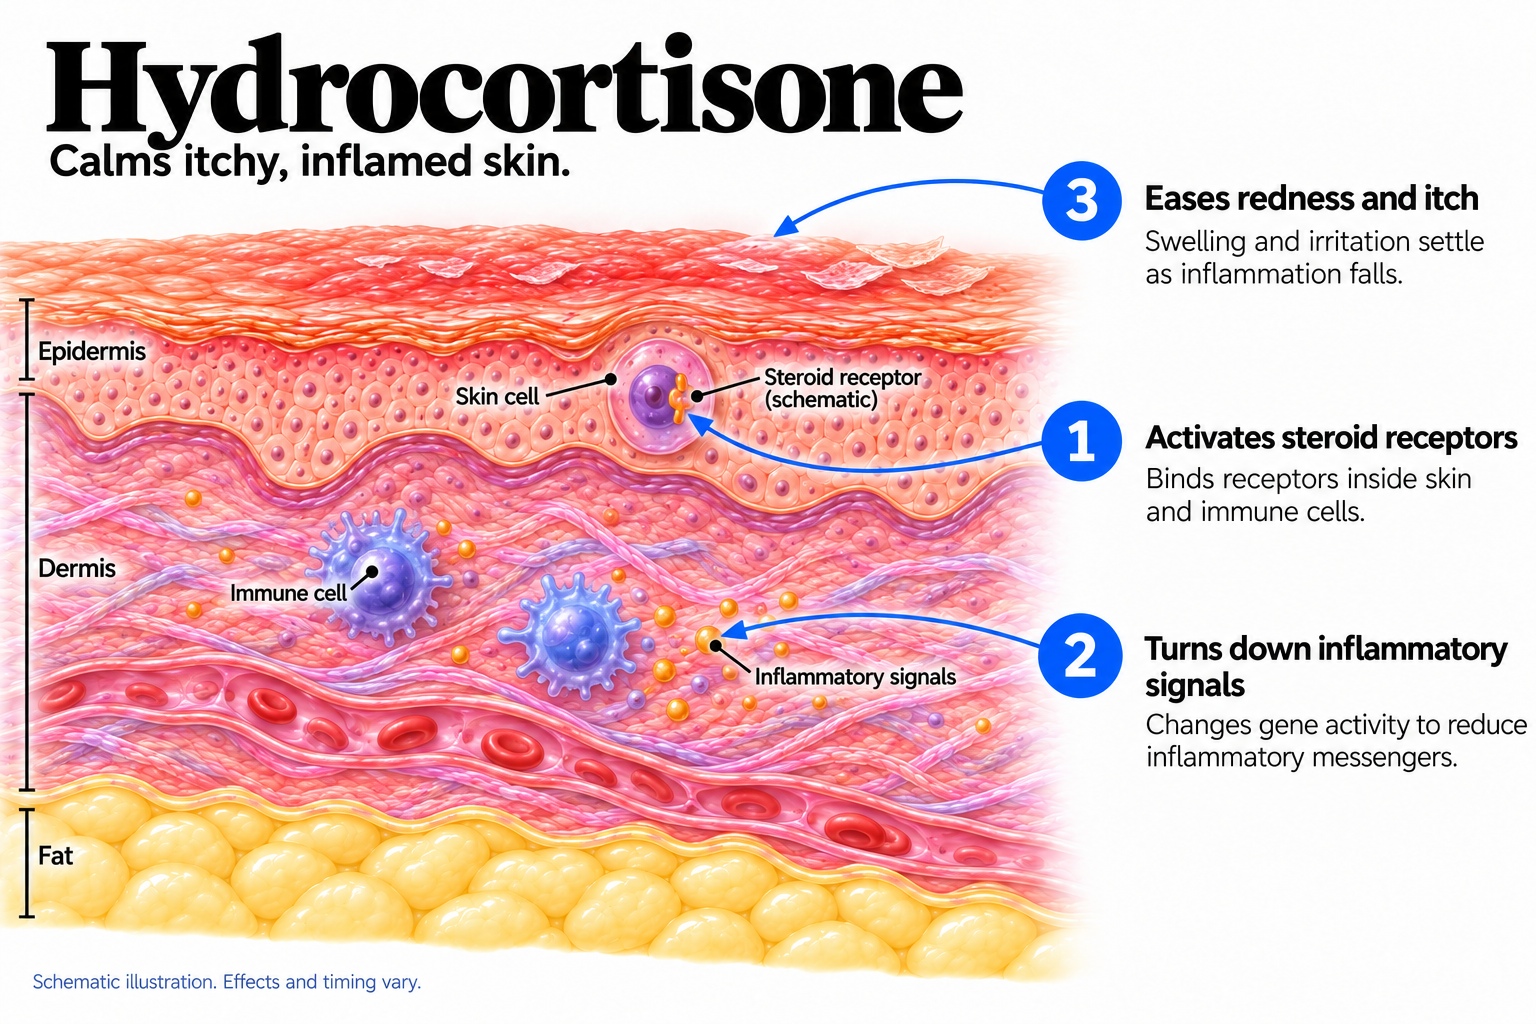
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
The dose is set by body weight, then adjusted by blood pressure and kidney tests, not by how the skin looks.
Starting dose: About 2.5 mg per kilogram of body weight a day, split into two doses. A severe flare may start around 4 to 5 mg per kilogram a day to get control quickly.
Going up: Raised in small steps every two to four weeks if response is poor, and only if the tests are stable.
Coming down: Once the skin is calm, the dose comes down in stages, to give the next treatment time to work.
Total course: Short by design. Many courses run 8 to 16 weeks. Guidelines advise no more than about a year of continuous treatment, less where possible.
When to Apply: Twice a day, on the rash only, on clean dry skin. A thin film that makes the skin look shiny is enough. One fingertip unit, the amount along the last joint of an adult index finger, covers about two adult palms. Moisturizer can go on a few minutes before or after.
How to Start: Twice daily from day one, until the rash is flat rather than merely better. Usually three to seven days. Two weeks is the outer limit for one stretch without seeing a clinician, less on the face.
If It Irritates: Stinging on application is usually the base, not the steroid, and is more likely on broken skin or from an alcohol-containing gel or spray. An ointment often settles it. Itch or redness that worsens over days can mean an allergy to something in the product, which does happen with steroids.
If It Is Not Working: Stop after about a week and reassess. A rash that does not respond to hydrocortisone is often not eczema. Ringworm, a yeast rash in a fold and psoriasis all look plausible and all need something different.
Twice a day, about 12 hours apart, at the same times daily. Be consistent about food: always with meals or always without, because switching changes absorption. Swallow capsules whole and leave them in the foil until you take them.
On the liquid, mix it with orange or apple juice in a glass cup, stir and drink it straight away, then rinse the cup with more juice and drink that too. Never use grapefruit juice.
Take it when you remember unless the next dose is close, then skip it. Never take two at once. Tell the prescriber if you miss more than a dose or two, or vomit soon after taking it, because the dose is built around your blood level.
Cyclosporine is monitored more closely than any other skin drug, and that monitoring is why it can be used at all. Blood pressure is measured at every visit, often at home. Kidney function is checked by blood test, twice before starting for a reliable baseline, then every couple of weeks for a month or two, then monthly once the dose is steady. The same draws cover potassium, magnesium, uric acid, liver enzymes, blood counts and cholesterol. Drug blood levels are routine in transplant care, not usually needed at dermatology doses.
Two numbers drive the decisions. A rise in creatinine of about a quarter above your baseline, confirmed on a repeat test, means dropping the dose; about half means stopping. New high blood pressure means lowering the dose or adding a blood pressure medicine, and the choice matters: diltiazem and verapamil push levels up, amlodipine does not.
The interaction list is long. Drugs that raise levels include the azole antifungals, clarithromycin and erythromycin, and some HIV and hepatitis C medicines. Drugs that lower it include rifampin, phenytoin, carbamazepine and St John's wort. It also raises statin levels, so that dose is often reduced, and it interacts with colchicine, digoxin, methotrexate and potassium-sparing water tablets. Bring every prescription, supplement and herbal product to the first visit.
The time limit is the point of all this. Kidney damage builds with continuous use and part of it can be permanent, so guidelines cap continuous treatment at about a year and most dermatology courses are far shorter. Long or repeated use also raises the risk of skin cancer, lymphoma and serious infection, so skin checks continue afterward.
No blood tests are needed for ordinary short courses in a healthy adult. Monitoring means looking at the skin: did the rash clear, has the skin gone thin or shiny, have small blood vessels appeared, are stretch marks forming in the folds.
Children absorb proportionally more because they have more skin surface for their size, so a doctor watches how much is used and over how large an area. Anyone applying a steroid to large areas most days for months should be under review rather than repeating over-the-counter purchases.
Hydrocortisone is not a drug to stay on continuously. Where a condition needs ongoing control, the plan is short bursts for flares, emollients doing the daily work, or a switch to a treatment designed for maintenance.
Approximate windows, not promises.
First 2 weeksStarting: Itch settles first, often within days, and sleep improves. Tingling or burning in the hands and feet, headache and mild nausea are common early. Blood pressure and kidney tests get checked.
Weeks 2 to 6Working: Redness, weeping and thickness improve clearly. Chronic hives that antihistamines do not control usually settle within a month. Extra hair growth on the face, arms and body and swollen or tender gums start now; both are dose-related and reverse after stopping.
Weeks 8 to 16Plaque psoriasis: Large improvement, often near-clear at the higher end of the dose range. Usually where the course ends and another treatment takes over.
VariableSevere inflammatory ulcers: In pyoderma gangrenosum it stops the ulcer spreading while healing catches up. Response times differ a lot.
ThroughoutThe tests: Blood pressure creeping up and kidney numbers drifting decide whether the dose drops or the drug stops. Neither causes symptoms, which is why the tests are not optional.
First few minutesApplying it: A thin layer on the affected skin. The mildest steroid strength, which is why it is sold over the counter.
Days 1 to 2Itch first: Itching and stinging ease before the rash looks different, the earliest sign it is working. Insect bites and minor irritation settle in a day or two, and that is the whole course.
Days 3 to 7Clearing: Redness fades and the skin flattens. A mild eczema flare settles here; cracked skin takes longer than skin that was only red. Weeping or crusting should be settling, not spreading.
Weeks 1 to 2Judge it here: A mild rash should be gone or nearly gone. Contact dermatitis clears steadily once the trigger is gone.
Weeks 2 to 4Mild seborrheic dermatitis: Redness and flaking around the nose and brows improve.
After stoppingMarks stay behind: Brown or gray patches where the rash was are pigment change, not scarring. They fade over weeks to months.
Sorted by what to do about them.
Generic capsules are cheap next to biologics, part of why the drug is still used. Branded versions cost more without working better.
The visible cost is not the whole cost. Repeated blood tests, blood pressure checks and appointments add up, and none are optional. It is cheaper per month than a biologic but taken for only a few months, so the comparison depends on what comes after.
Insurance generally covers it for severe psoriasis. Eczema coverage varies more in the United States, where that use is off-label.
Hydrocortisone is cheap. Store-brand 1% cream is the same drug at the same strength as the branded tube, usually for much less. Anti-itch versions with added ingredients cost more without treating the inflammation any better.
Prescription 2.5% is generic and also cheap, though the visit costs more than the tube. Ointments and creams are the cheapest vehicles. Foams and sprays cost more.
Faster than anything else for these conditions. Itch improves within days, clearing by four to six weeks.
Most courses run months. Guidelines cap continuous use at about one year, because kidney effects build and some can be permanent.
It raises blood pressure in a meaningful share of people, and that causes no symptoms. Catching it early usually means lowering the dose rather than stopping.
No. Grapefruit, pomelo and Seville oranges block the enzyme that clears it, so levels rise unpredictably. Other citrus is fine.
Both are dose-related. Not dangerous, usually better if the dose comes down, and gone after stopping.
Usually, within weeks to a few months, unless another treatment is running. Planning that before the taper is the point of the short course.
About a week at a time on the body for an over-the-counter tube, less on the face. A rash that needs it longer than two weeks is a reason to be seen, not to buy more.
For a few days, yes, and it is the mildest option there. Facial skin is thin and absorbs well, so weeks of daily use causes thinning, redness and small bumps around the mouth.
No. It is the bottom of the potency ladder. If a week of it has not worked, question the diagnosis.
A short course on the body will not. Thinning comes from stronger steroids over long periods, especially on the face, eyelids, groin and armpits. Early changes usually recover over months. Stretch marks are permanent.
It can. Pale patches on treated skin show up more on deeper skin tones, and usually fade slowly after stopping. Untreated inflammation also leaves light and dark marks, so avoiding treatment is not a way around it.
Not on its own. A steroid makes ringworm and yeast harder to recognize while they keep spreading. Diaper areas are covered, so absorption is higher, worth having a child's rash there looked at.