
Eczema
Reduces itch and clears skin.
Dupixent: An injected biologic for moderate to severe eczema. It blocks two of the immune signals that drive the itch, and it is taken long term rather than as a course. Hydrocortisone: The mildest topical steroid, and the only one sold without a prescription. It is the usual starting point for the face, for skin folds and for young children.
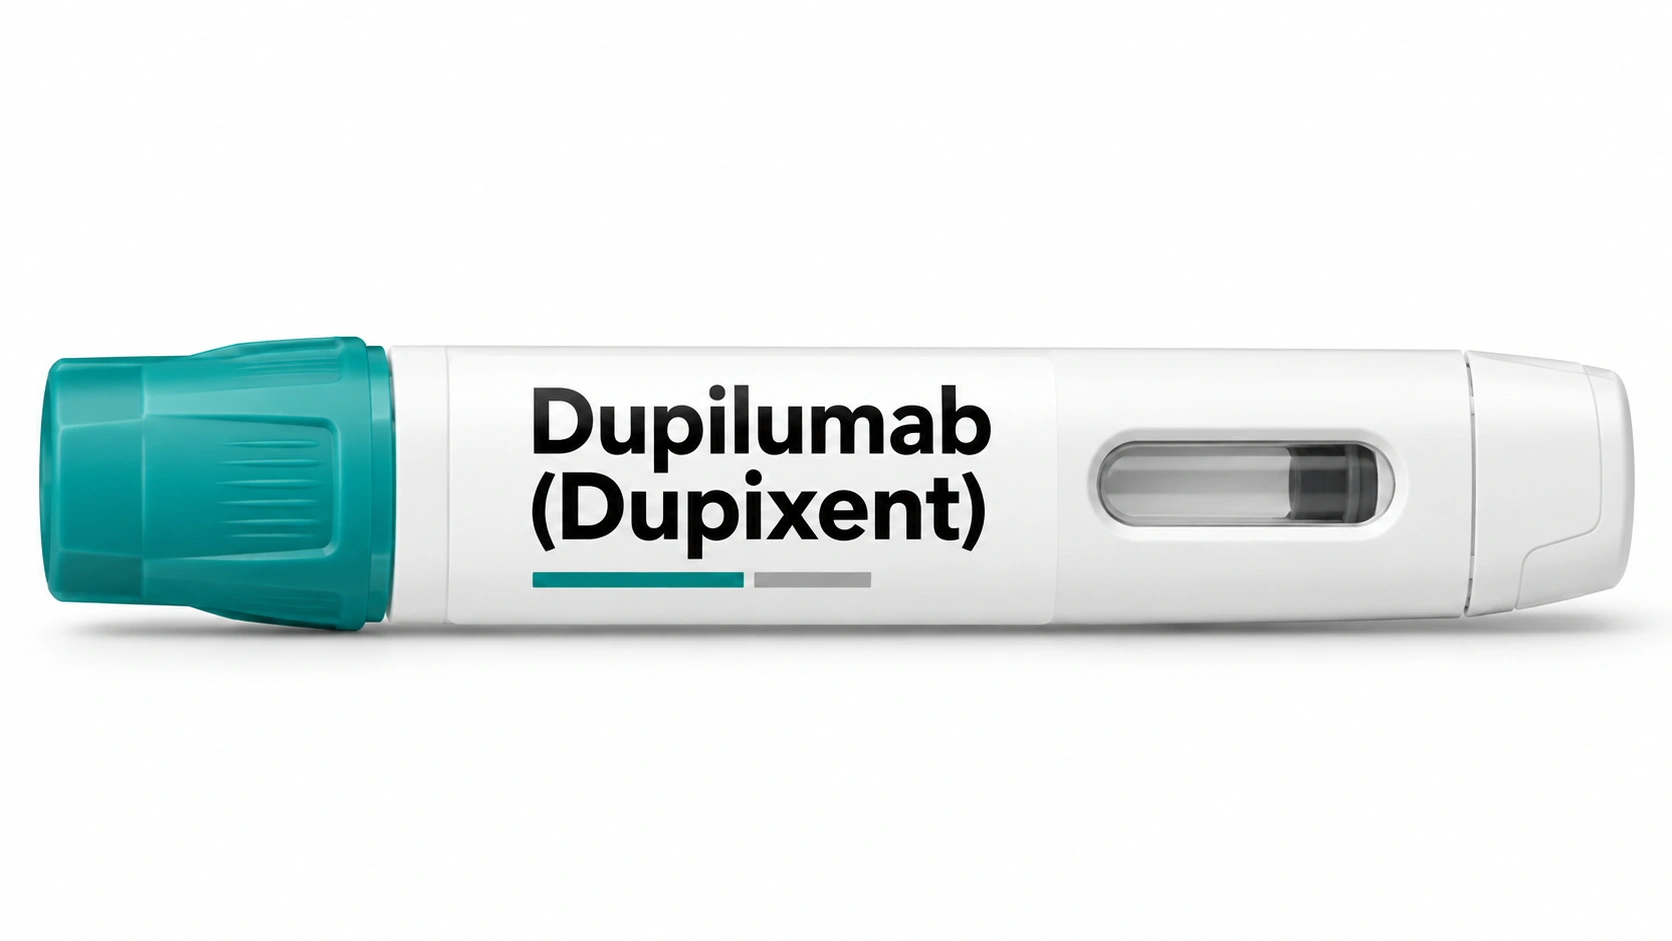

Choose for moderate to severe eczema that creams can't control, as a long-term treatment without blood tests.
Choose as the first step for mild rashes on the face, folds or young children — the only steroid sold without a prescription.
Can you take them together?
Dupixent is usually used alongside topical treatment. Hydrocortisone is a gentle option for mild flares on the face and folds.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.




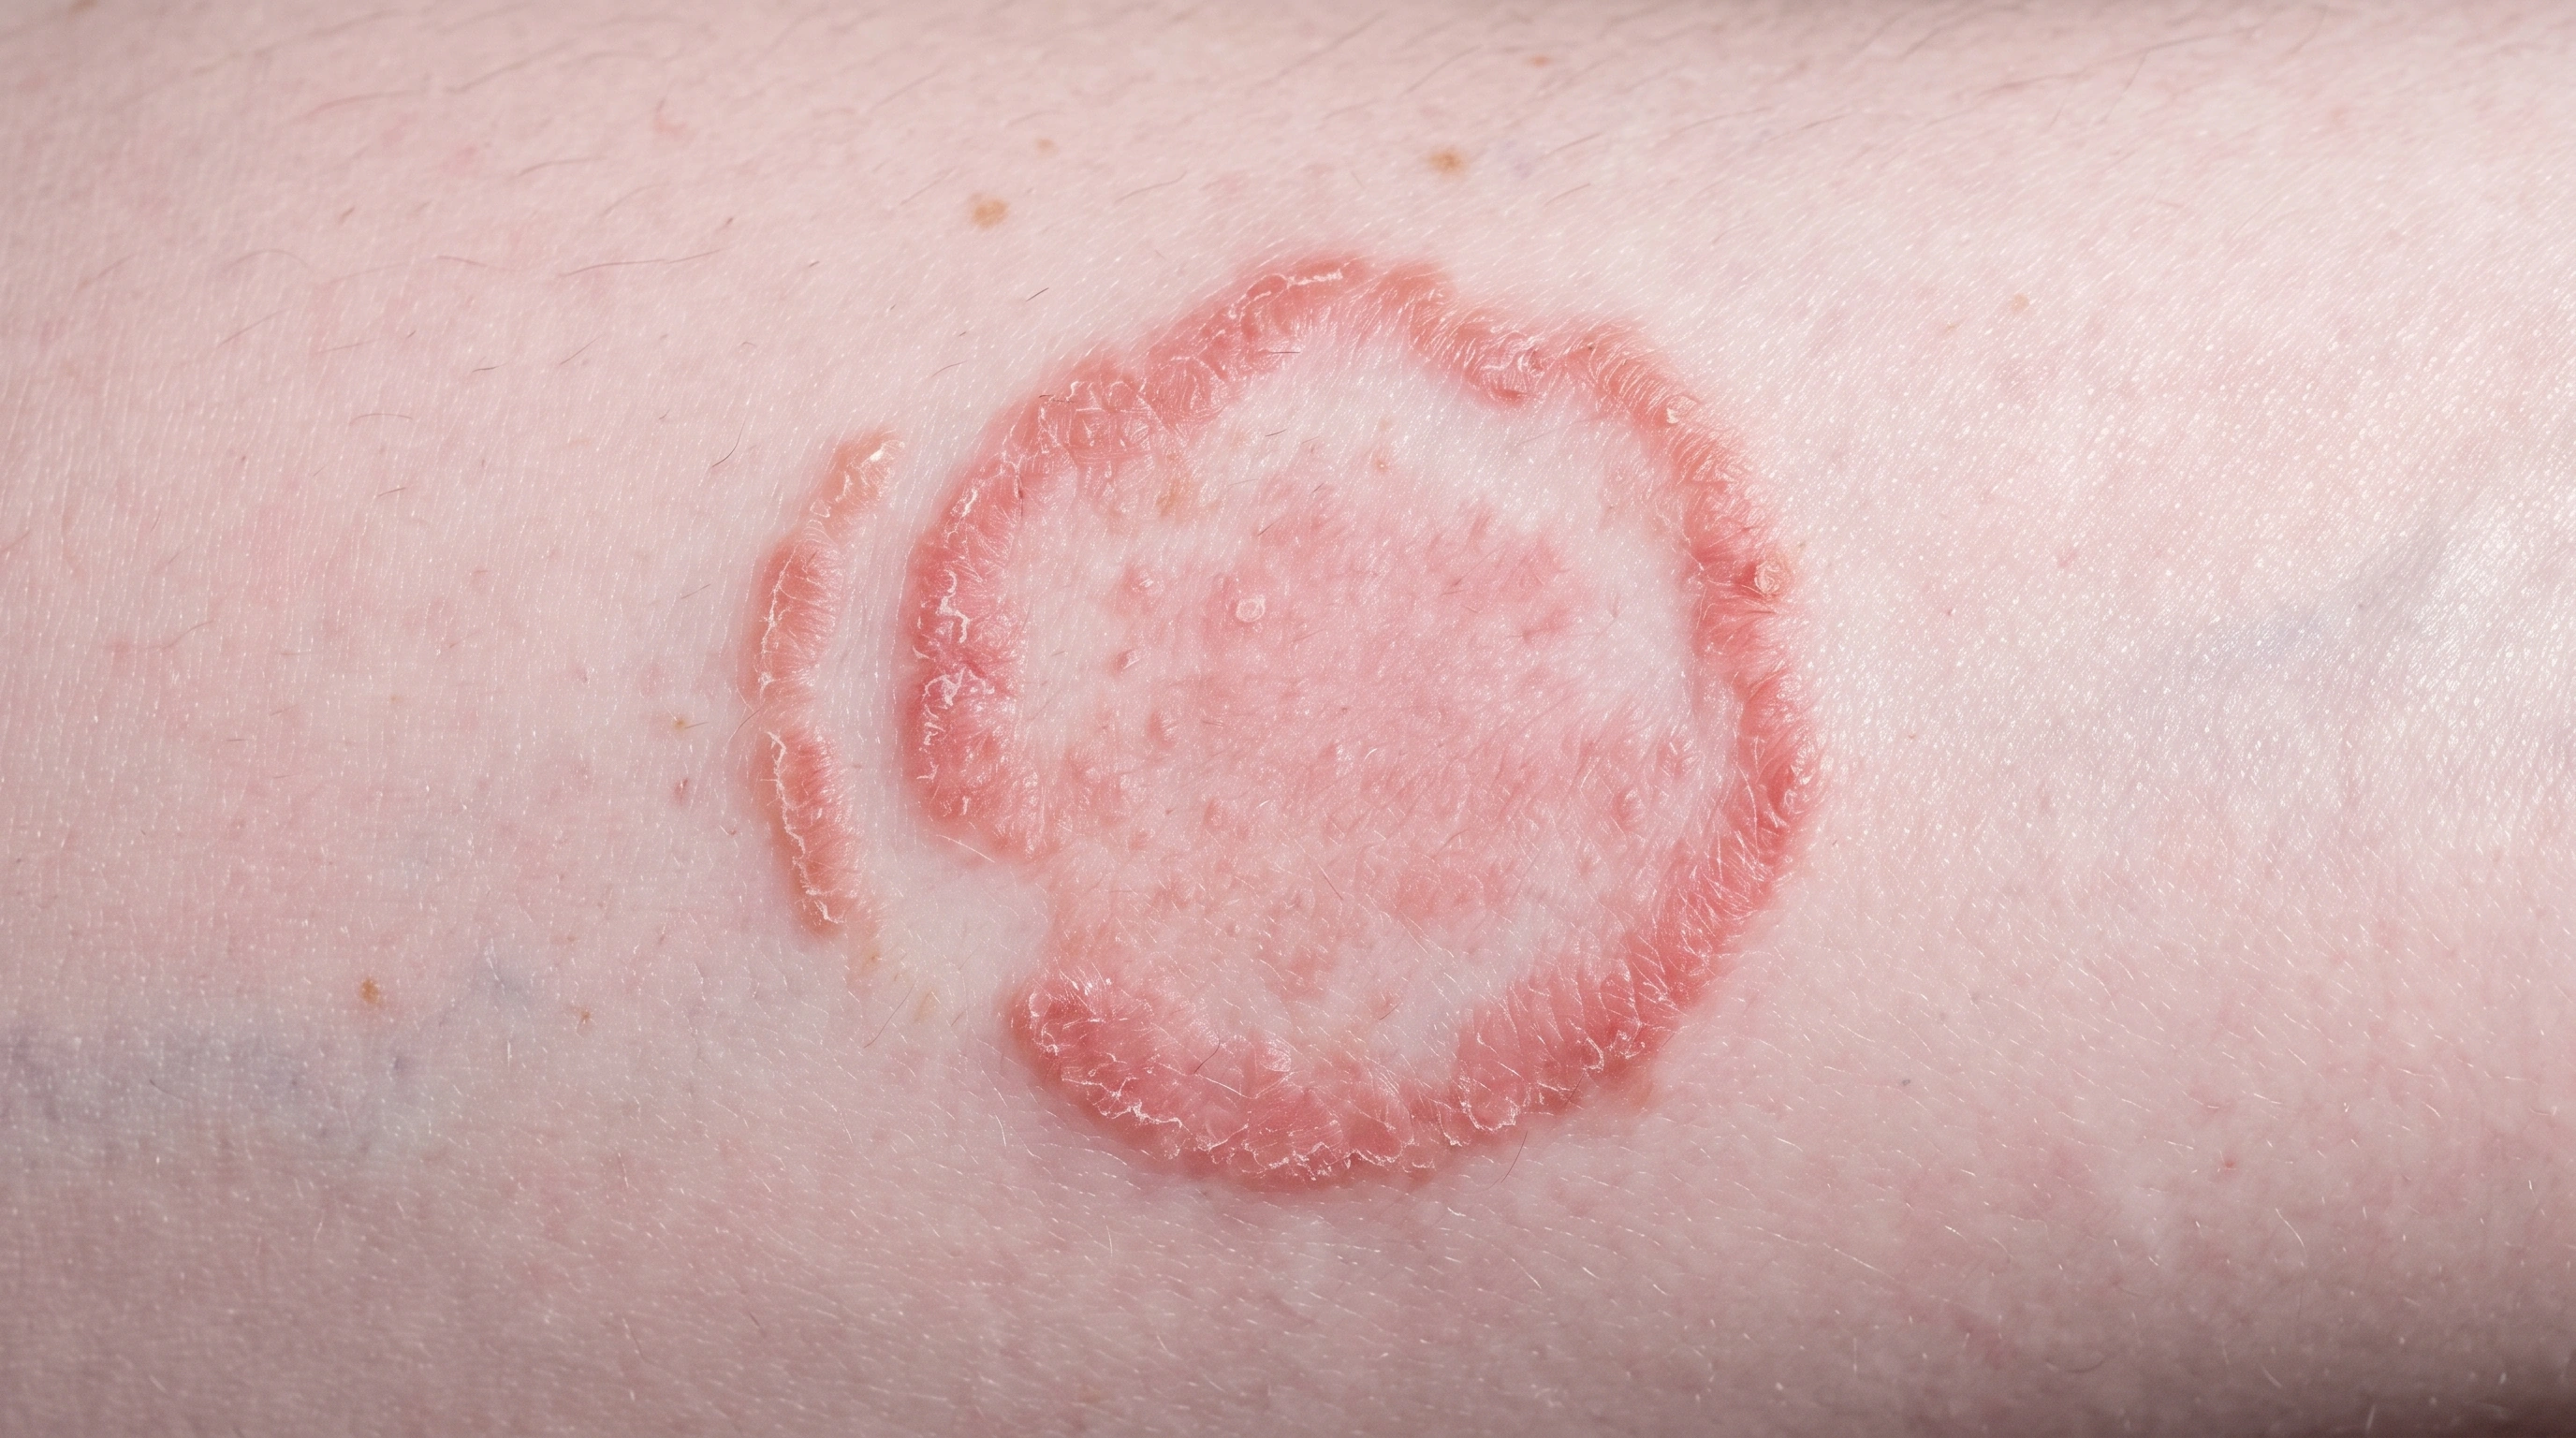
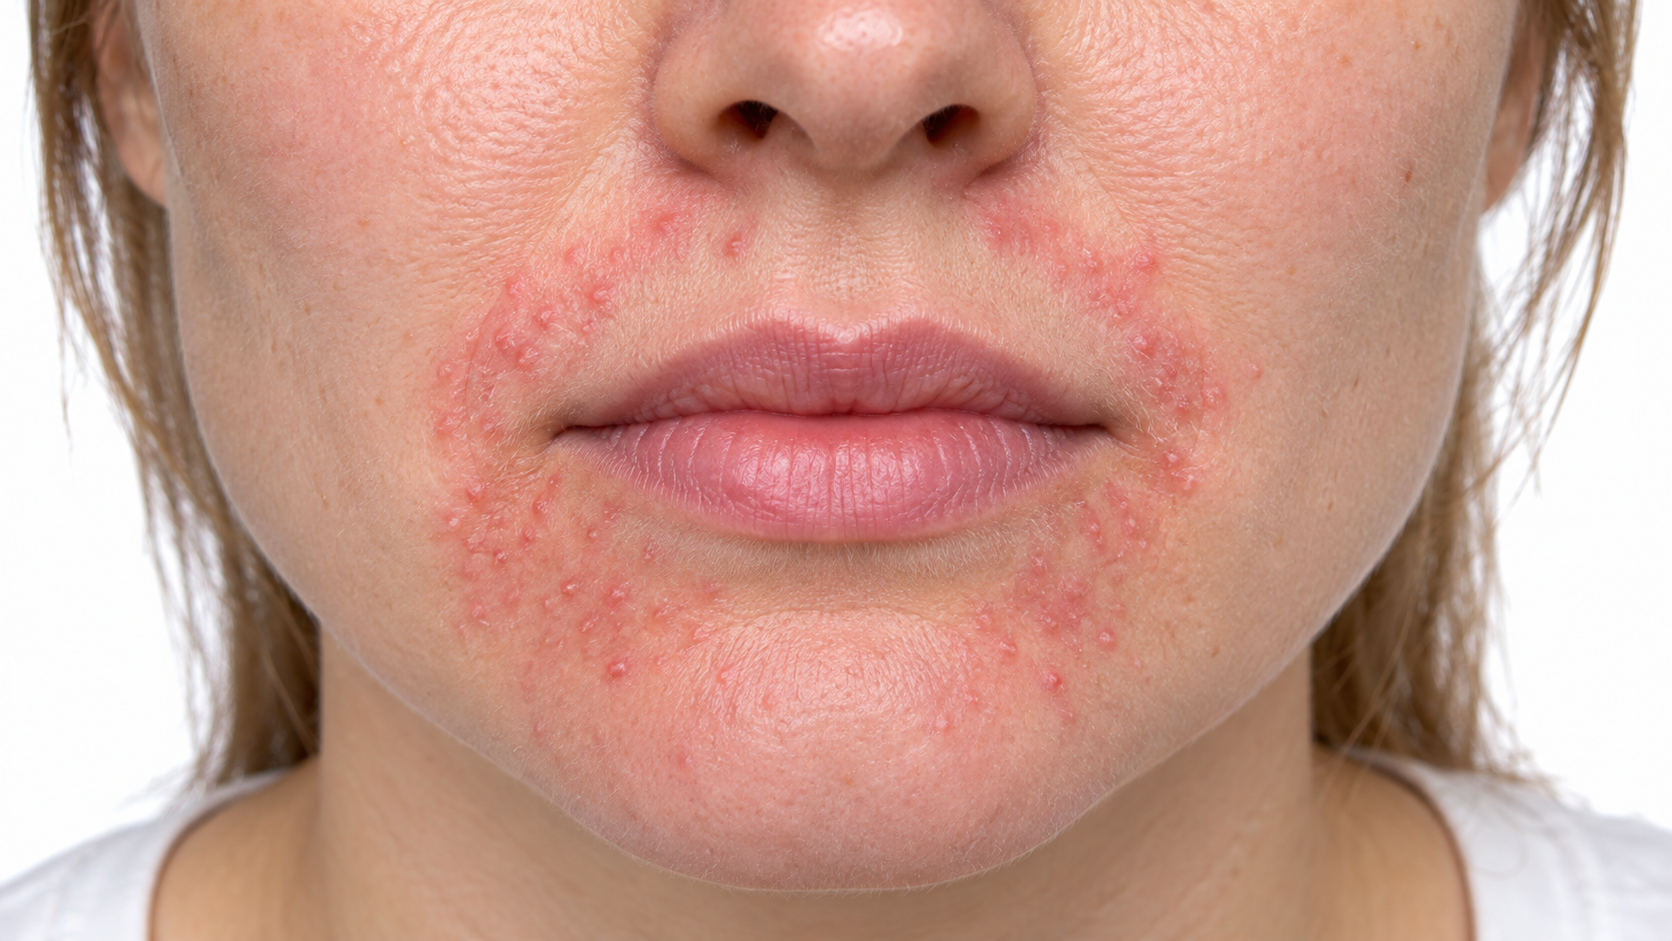

Blocks IL-4 and IL-13 signals: Binds their shared receptor to interrupt these messages. Calms type 2 inflammation: Reduces immune signaling that drives eczema. Eases eczema and itch: Inflamed skin and itch improve as signaling falls.
Dupilumab binds IL-4 receptor alpha, inhibiting IL-4 and IL-13 signaling. Diagram focuses on atopic dermatitis; it does not show every approved indication or all downstream effects.
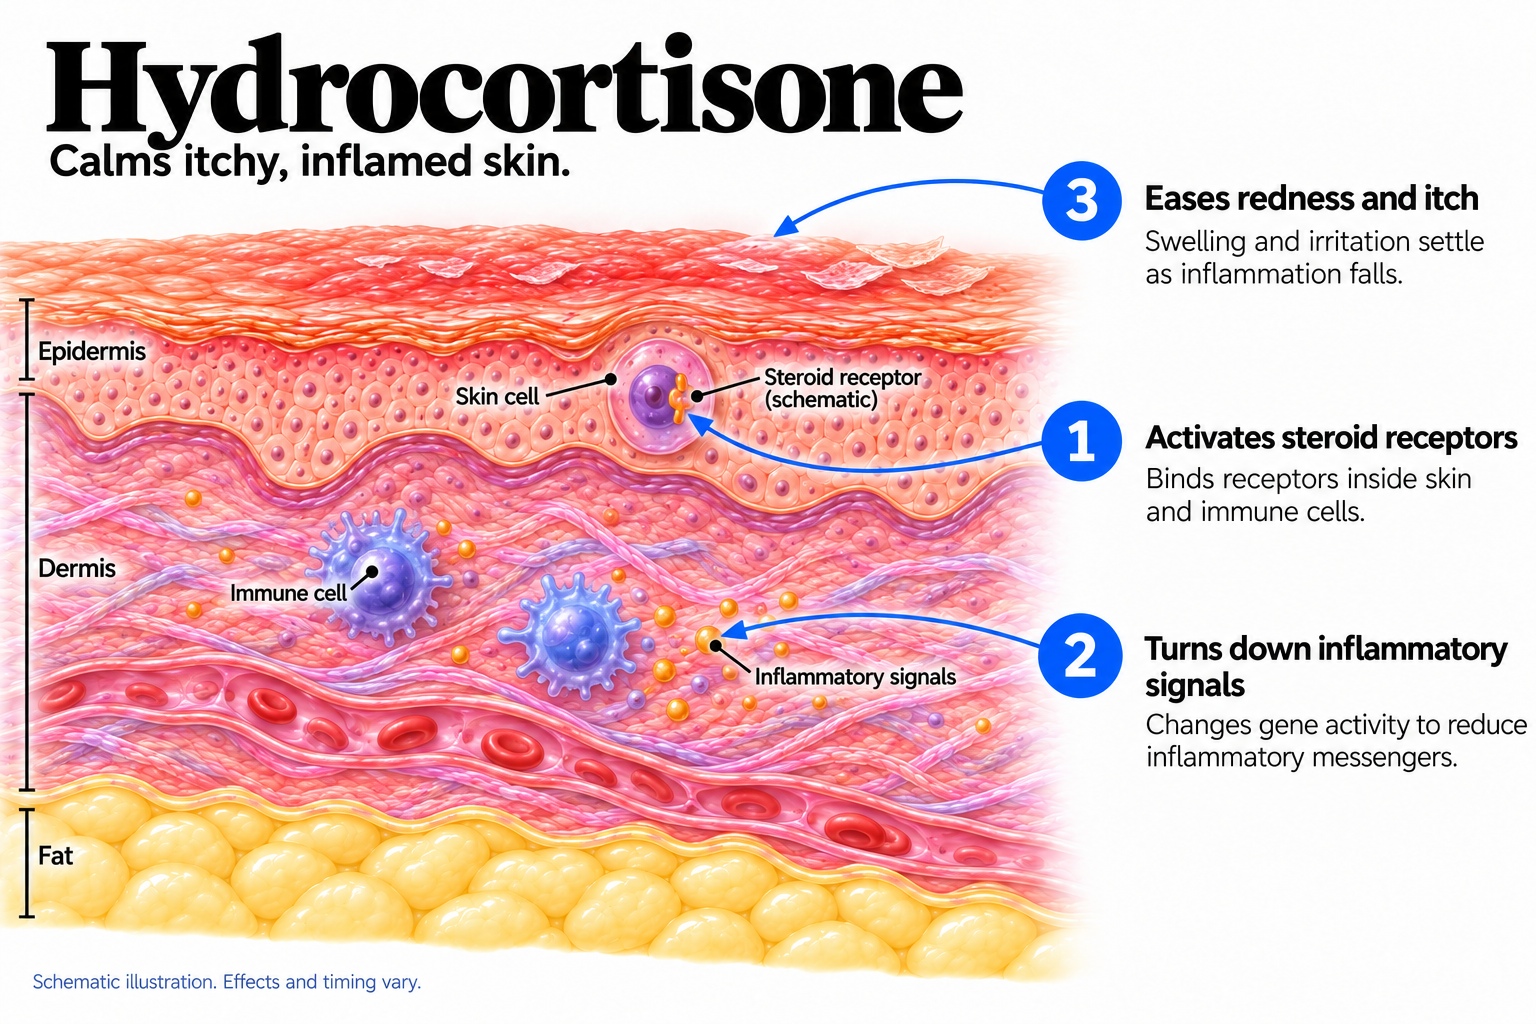
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
There is no titration. The number is fixed by age and weight; the only variable is how often you inject.
Loading dose: Adults start with two 300 mg injections the same day at two different spots — 600 mg total. That front-loading reaches a working level quickly.
Usual dose: 300 mg every two weeks for adults. Adolescents 12 and over who weigh about 60 kg or more use the same schedule.
Children and smaller adolescents: Dose is set by weight, and the youngest children inject every four weeks rather than every two. Go by the prescription.
Going up: There is nothing higher. If it is not working at sixteen weeks, the conversation is about a different treatment, not a bigger dose.
Total course: Open-ended. This is maintenance, not a course — people stay on it for years when it works.
When to Apply: Twice a day, on the rash only, on clean dry skin. A thin film that makes the skin look shiny is enough. One fingertip unit, the amount along the last joint of an adult index finger, covers about two adult palms. Moisturizer can go on a few minutes before or after.
How to Start: Twice daily from day one, until the rash is flat rather than merely better. Usually three to seven days. Two weeks is the outer limit for one stretch without seeing a clinician, less on the face.
If It Irritates: Stinging on application is usually the base, not the steroid, and is more likely on broken skin or from an alcohol-containing gel or spray. An ointment often settles it. Itch or redness that worsens over days can mean an allergy to something in the product, which does happen with steroids.
If It Is Not Working: Stop after about a week and reassess. A rash that does not respond to hydrocortisone is often not eczema. Ringworm, a yeast rash in a fold and psoriasis all look plausible and all need something different.
Pick a day of the week and keep it. Take the pen or syringe out of the fridge 30 to 45 minutes ahead and let it warm to room temperature on its own — never in hot water, on a radiator, or in a microwave. A cold injection stings much more, and that one step explains most of the difference between people.
Inject into the front of the thigh or the abdomen, at least two inches from the navel. The upper arm works if someone else is injecting. Change the spot each time and avoid skin that is bruised, tender, scarred, or flaring. If the dose is two injections, give them one after the other in two different spots.
Give it as soon as you remember, as long as that is within about a week of the due day, then go back to your schedule. If longer than that, skip it and take the next on the usual day. Never double up to catch up. One missed injection does not undo months of treatment.
No routine blood tests are required — no liver, kidney, or blood count checks, which is a real advantage over the older systemic eczema drugs. Monitoring is a conversation about the skin, the itch, and the eyes.
Ask about the eyes at every visit. Conjunctivitis affects roughly one in ten people treated for eczema, more often with severe skin or eyelid involvement, and usually responds to lubricating drops or a short prescription course. Eye pain or changed vision goes to an eye doctor rather than being watched. Eosinophil counts rise in some people without causing anything, so a count taken for another reason should be read with that in mind.
Nothing builds up over the years, and there is no ceiling on how long you can stay on it. The recurring problem is insurance renewal, not safety.
No blood tests are needed for ordinary short courses in a healthy adult. Monitoring means looking at the skin: did the rash clear, has the skin gone thin or shiny, have small blood vessels appeared, are stretch marks forming in the folds.
Children absorb proportionally more because they have more skin surface for their size, so a doctor watches how much is used and over how large an area. Anyone applying a steroid to large areas most days for months should be under review rather than repeating over-the-counter purchases.
Hydrocortisone is not a drug to stay on continuously. Where a condition needs ongoing control, the plan is short bursts for flares, emollients doing the daily work, or a switch to a treatment designed for maintenance.
Approximate windows, not promises.
First few minutesThe injection: A sting for a few seconds, then redness or aching. Common early, and it settles with later doses.
First few minutesApplying it: A thin layer on the affected skin. The mildest steroid strength, which is why it is sold over the counter.
Weeks 1 to 2Itch lifts: Often within days, before anything shows in the mirror. The earliest and most reliable change.
Weeks 1 to 2Judge it here: A mild rash should be gone or nearly gone. Contact dermatitis clears steadily once the trigger is gone.
Weeks 2 to 8Working: Sleep improves, scratching drops, and the skin looks calmer. Red or gritty eyes, if they happen, start here.
Weeks 12 to 16Judge it here: Trials measured their main result at sixteen weeks. Most responders reach their best skin here and a good number get close to clear; people only partly better at twelve often kept improving.
Weeks 12 to 24Sleep and daily life: These follow the itch, on a similar timeline, and trials measured them separately from the rash.
After 6 monthsThe face and neck: A stubborn pink patch appears here in a minority, usually after the rest of the skin has cleared. It is treatable and not a sign the drug has stopped working.
Days 1 to 2Itch first: Itching and stinging ease before the rash looks different, the earliest sign it is working. Insect bites and minor irritation settle in a day or two, and that is the whole course.
Days 3 to 7Clearing: Redness fades and the skin flattens. A mild eczema flare settles here; cracked skin takes longer than skin that was only red. Weeping or crusting should be settling, not spreading.
Weeks 2 to 4Mild seborrheic dermatitis: Redness and flaking around the nose and brows improve.
After stoppingMarks stay behind: Brown or gray patches where the rash was are pigment change, not scarring. They fade over weeks to months.
Sorted by what to do about them.
Cost decides access here more often than anything medical. Dupilumab is a biologic with no generic and no biosimilar in the United States, and the list price runs to tens of thousands of dollars a year. Almost nobody pays that, and almost everybody has to do the paperwork that brings it down.
Prior authorization is close to universal. Plans want a diagnosis, a record of how much of the body is affected, and evidence that prescription topicals were tried and could not hold the disease — usually a mid- or high-strength steroid, often a calcineurin inhibitor too. Some add phototherapy or an older systemic drug first. First-pass denials are common and appeals often succeed, so a denial is a step, not the end. Ask the prescribing office who handles appeals.
The manufacturer's copay program cuts the monthly cost sharply for people with commercial insurance, and a separate program covers people with no insurance. Copay cards cannot be used with Medicare, Medicaid, or other government plans, which is where the largest out-of-pocket gaps sit. Terms change every year, so a plan that refused last year is worth asking again.
Hydrocortisone is cheap. Store-brand 1% cream is the same drug at the same strength as the branded tube, usually for much less. Anti-itch versions with added ingredients cost more without treating the inflammation any better.
Prescription 2.5% is generic and also cheap, though the visit costs more than the tube. Ointments and creams are the cheapest vehicles. Foams and sprays cost more.
Itch often improves within two weeks. The skin takes longer — sixteen weeks is the fair point to judge.
It stings for a few seconds. Letting it reach room temperature first makes the biggest difference.
Roughly one in ten get red or gritty eyes, more often with severe eczema or eyelid involvement. Most settle with drops.
No routine tests, which is unusual for a drug of this kind.
Some people do, and some keep a good stretch. Eczema usually returns eventually, and restarting normally works.
Yes. Most people need far less, but flares still get topical treatment, and moisturizer continues indefinitely.
About a week at a time on the body for an over-the-counter tube, less on the face. A rash that needs it longer than two weeks is a reason to be seen, not to buy more.
For a few days, yes, and it is the mildest option there. Facial skin is thin and absorbs well, so weeks of daily use causes thinning, redness and small bumps around the mouth.
No. It is the bottom of the potency ladder. If a week of it has not worked, question the diagnosis.
A short course on the body will not. Thinning comes from stronger steroids over long periods, especially on the face, eyelids, groin and armpits. Early changes usually recover over months. Stretch marks are permanent.
It can. Pale patches on treated skin show up more on deeper skin tones, and usually fade slowly after stopping. Untreated inflammation also leaves light and dark marks, so avoiding treatment is not a way around it.
Not on its own. A steroid makes ringworm and yeast harder to recognize while they keep spreading. Diaper areas are covered, so absorption is higher, worth having a child's rash there looked at.




