Ingrown Toenail vs Nail Fungus

A nail edge presses into the surrounding skin, causing pain and inflammation. Nail fungus is a slow infection of the nail itself, usually a toenail. It makes the nail thick, yellow-brown, crumbly and lifted away from the skin underneath. It is treatable, but treatment is measured in months, because the damaged nail has to grow out before anything looks better.

Research updated 2026-10-23
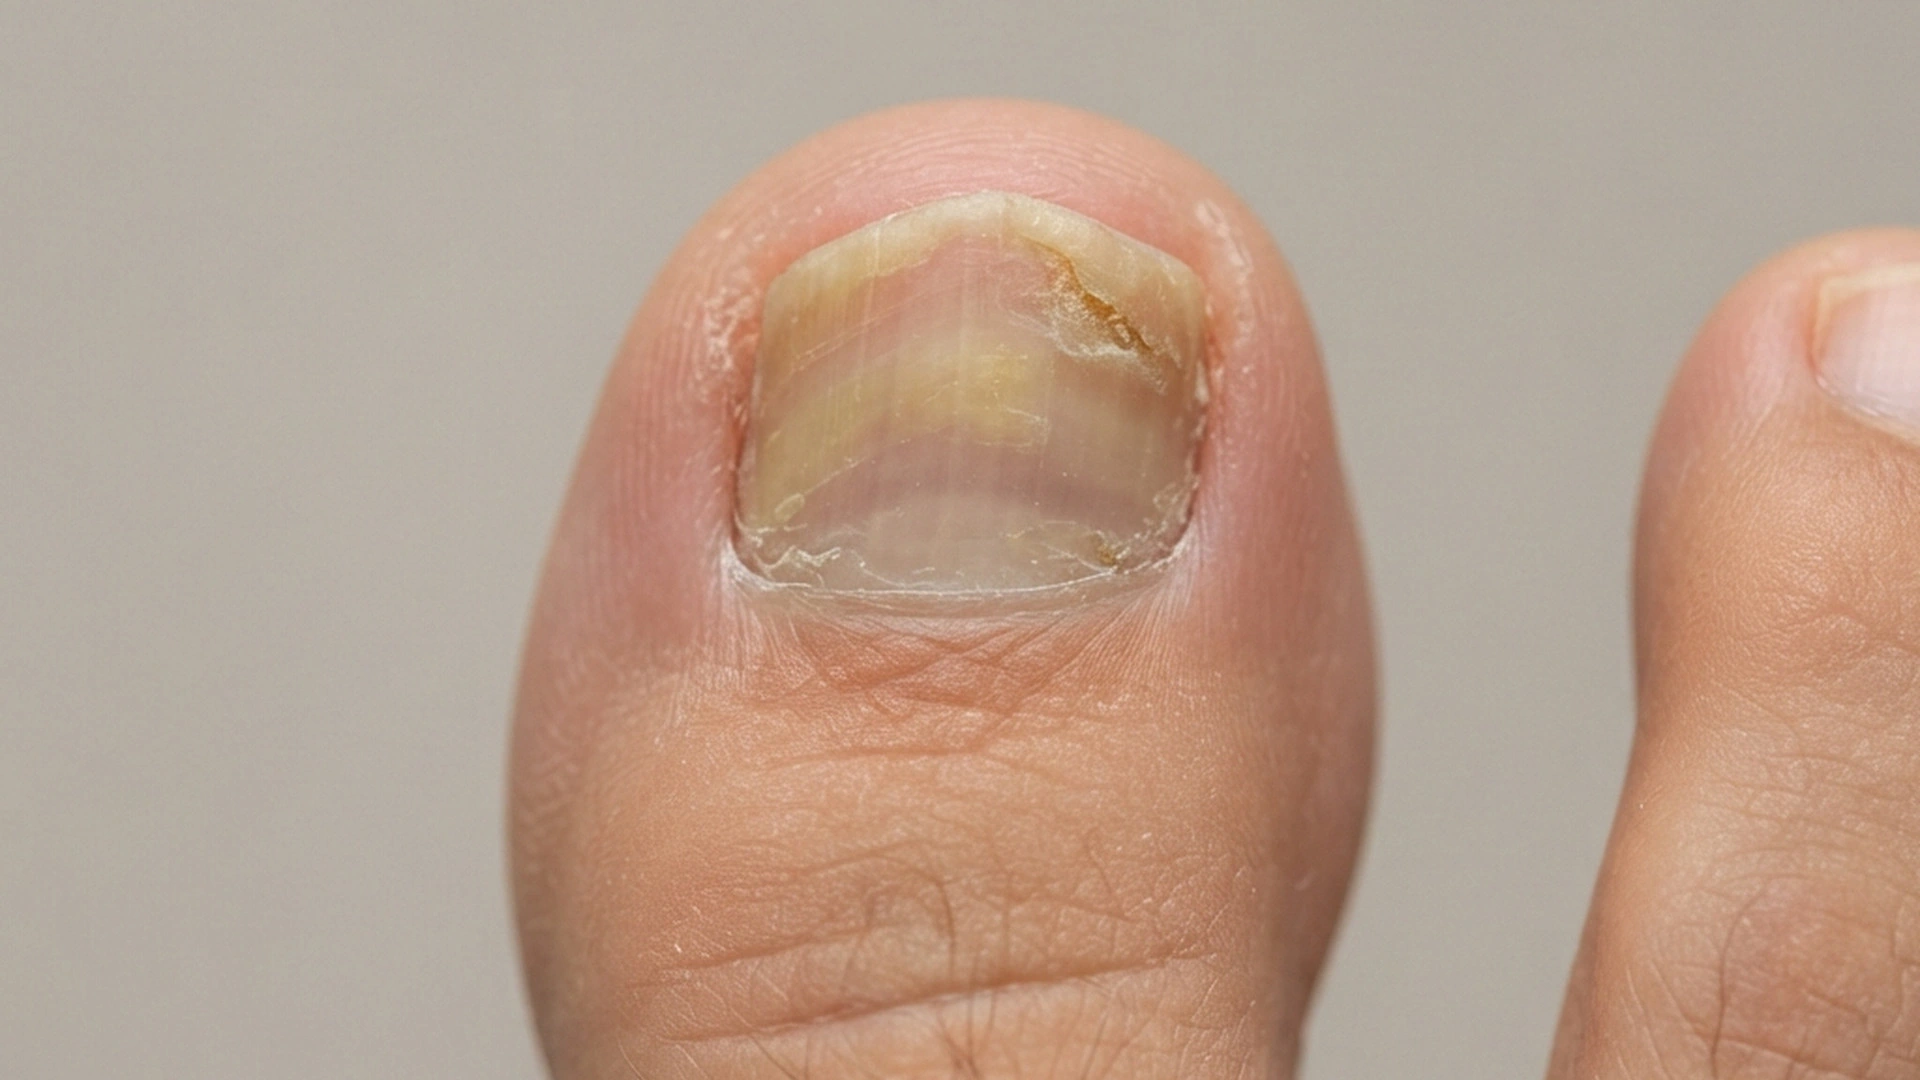
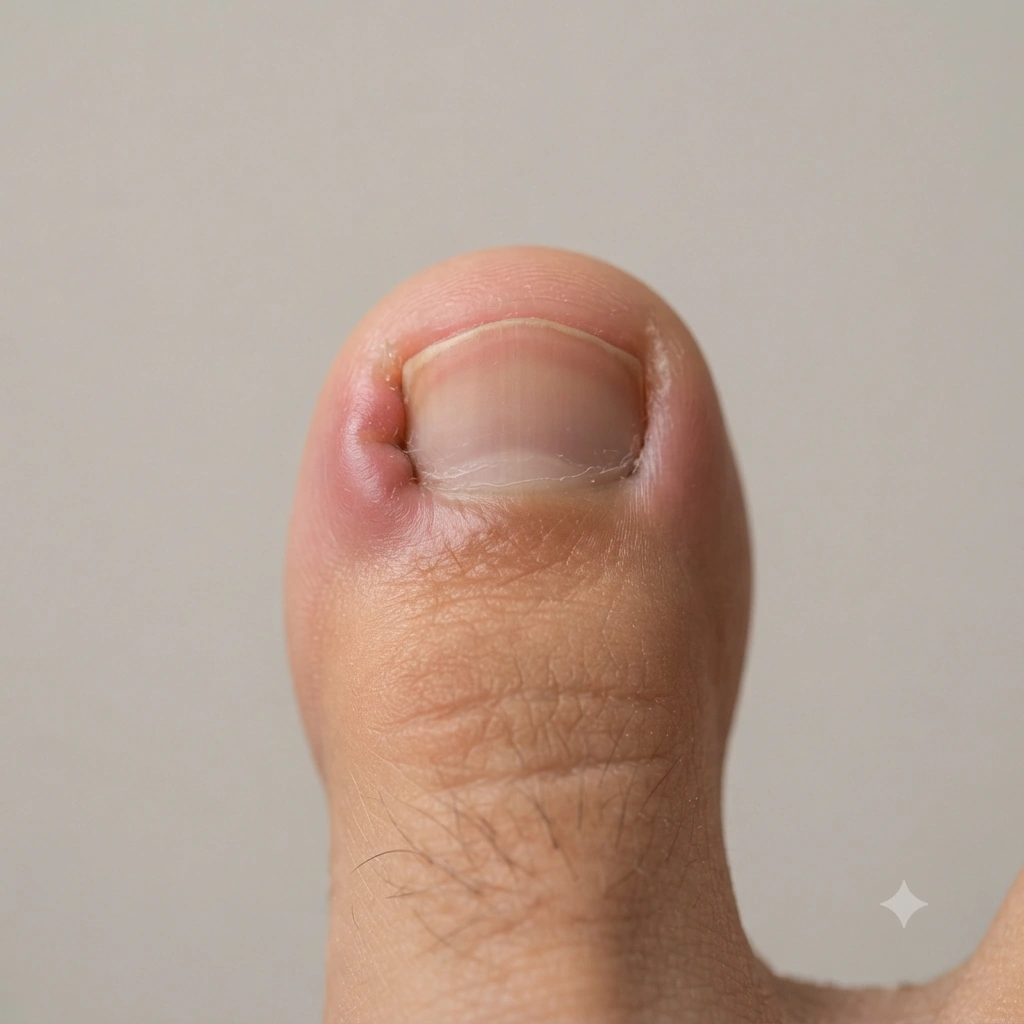
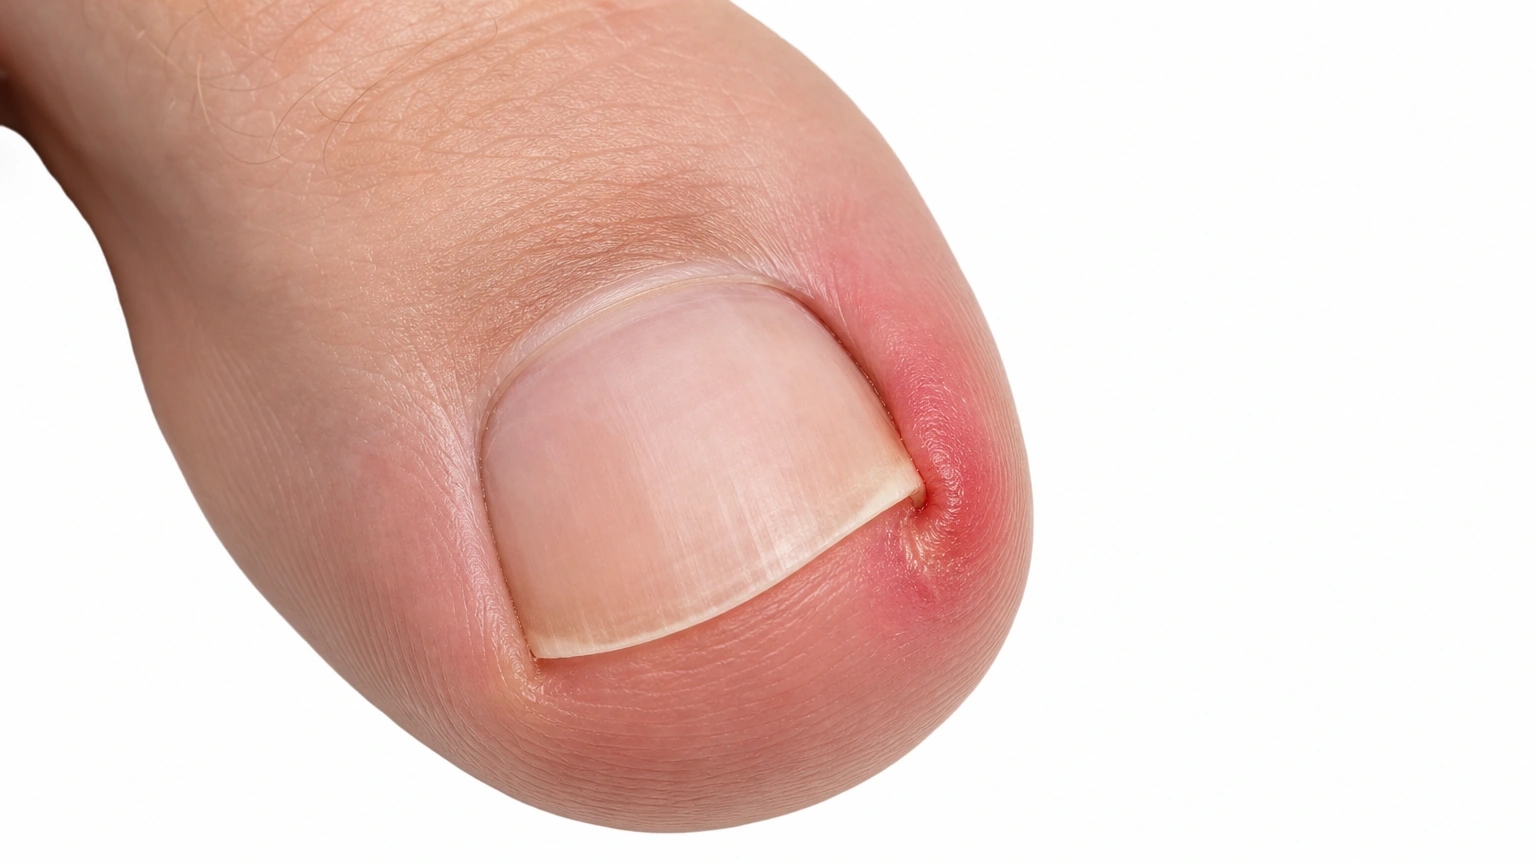
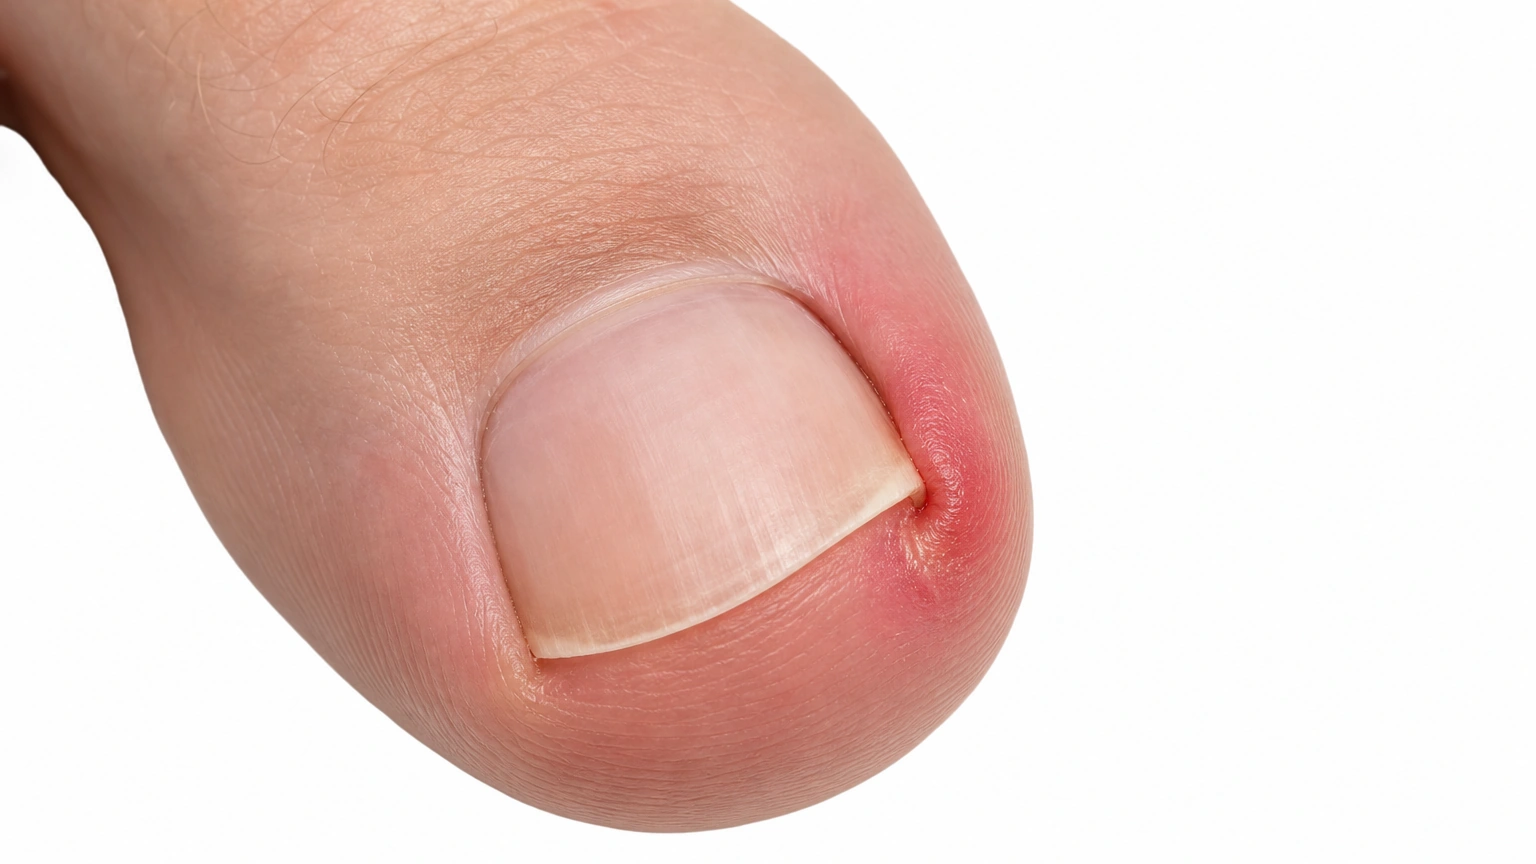
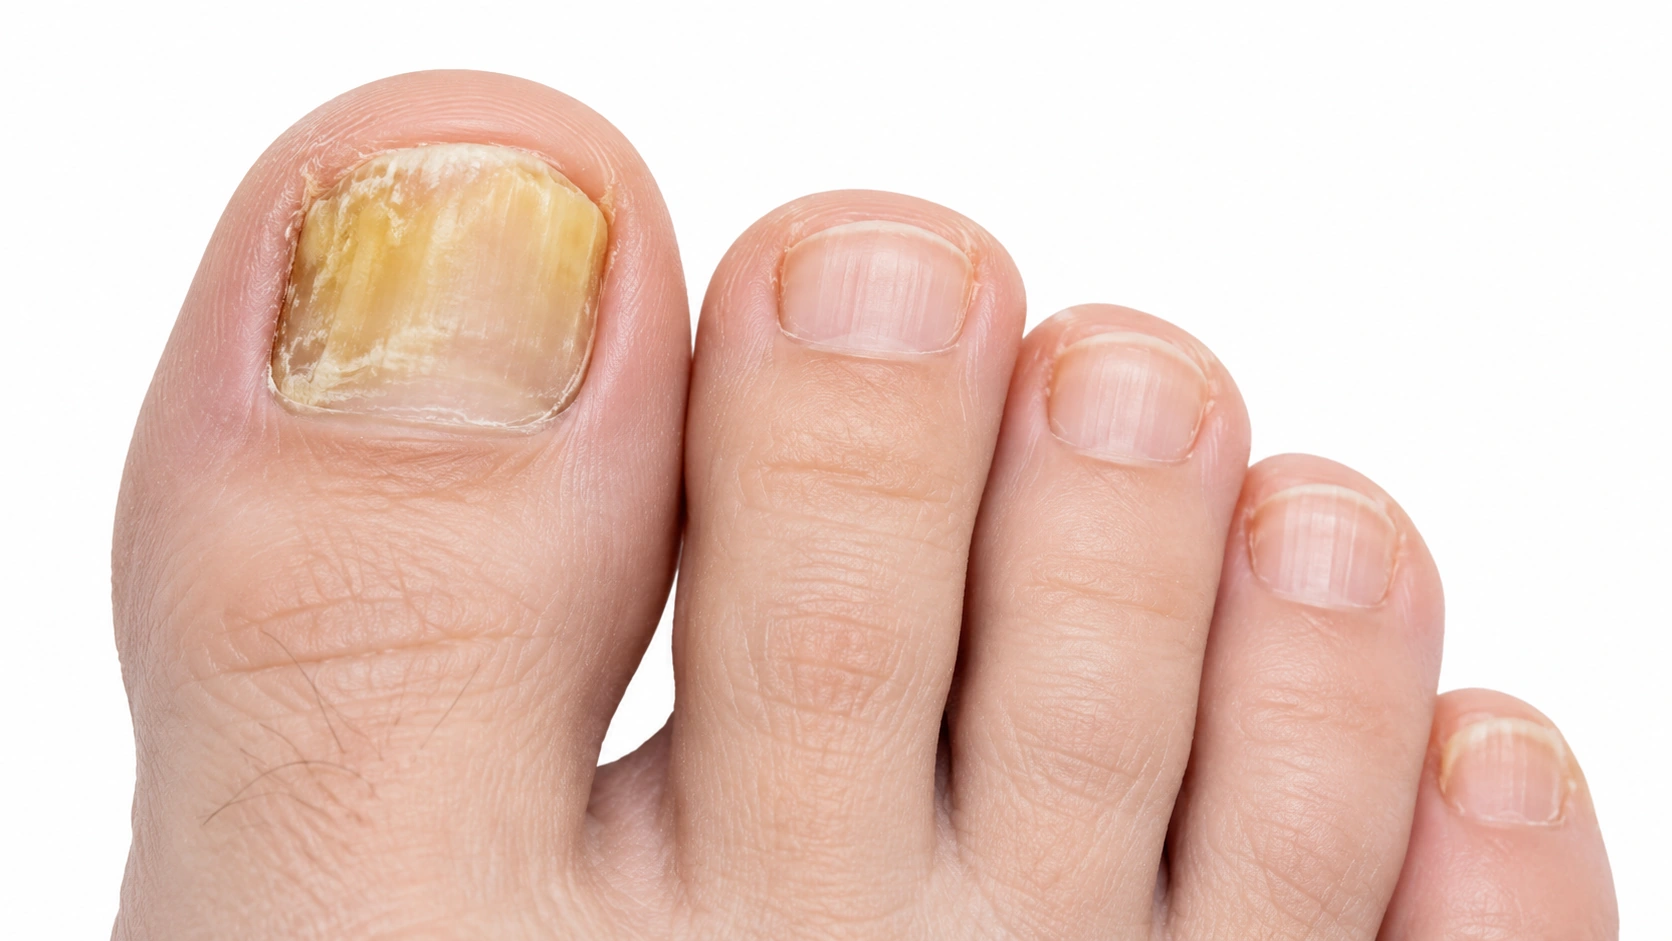
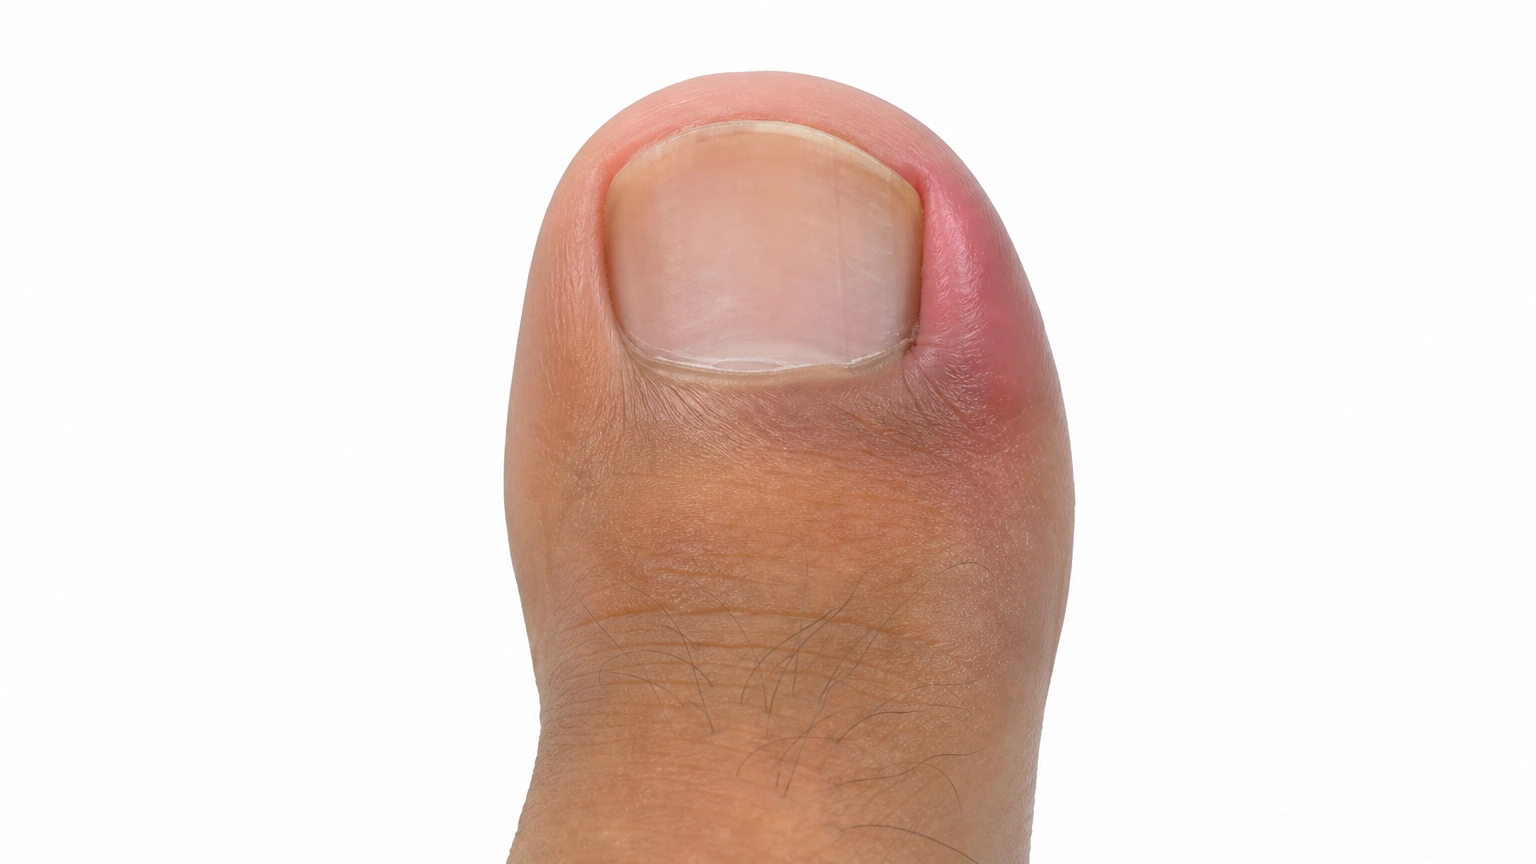
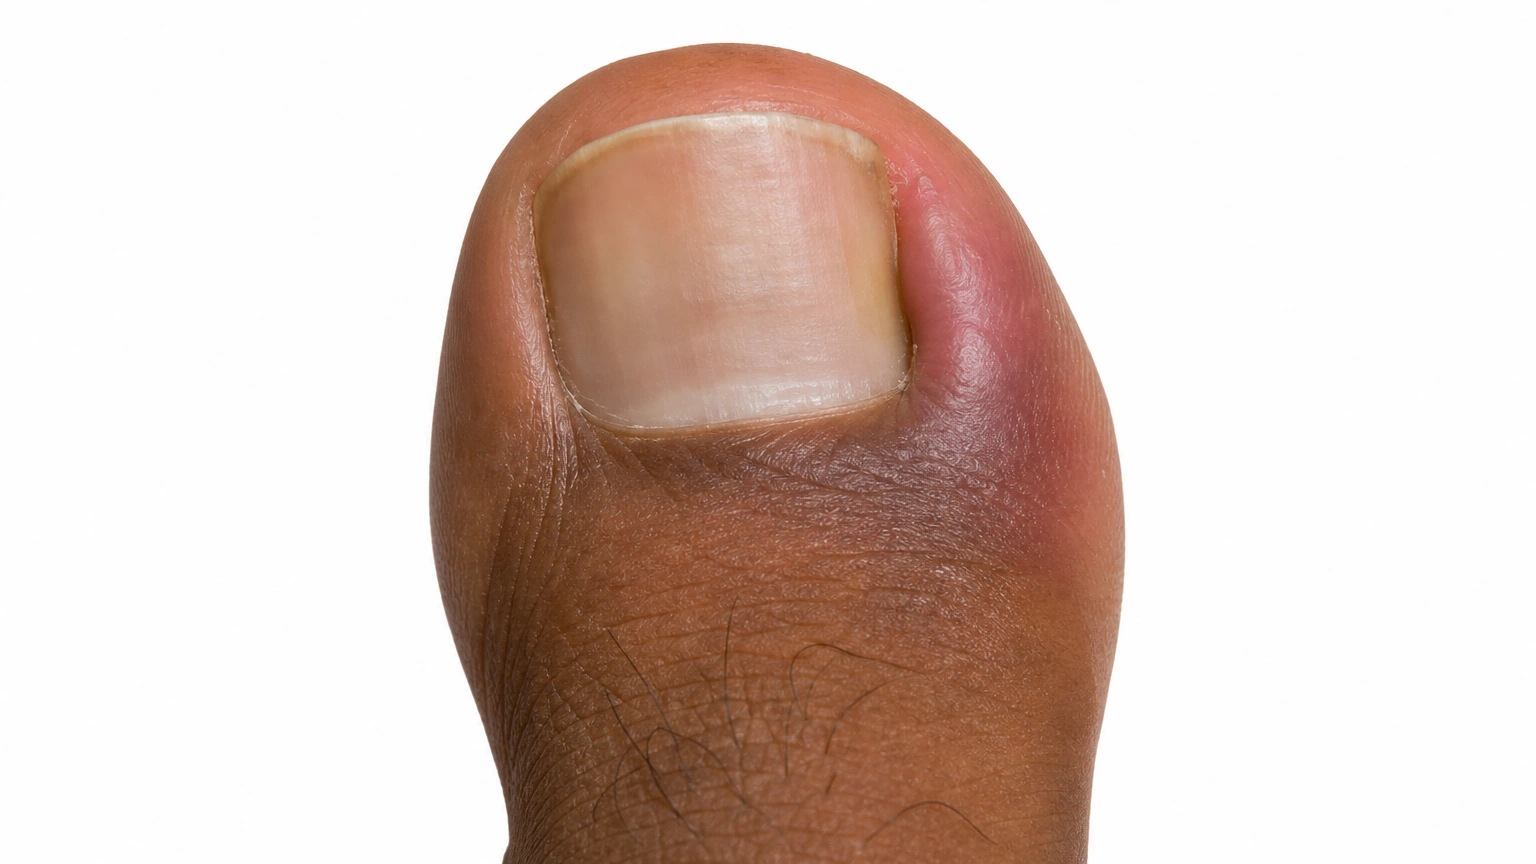
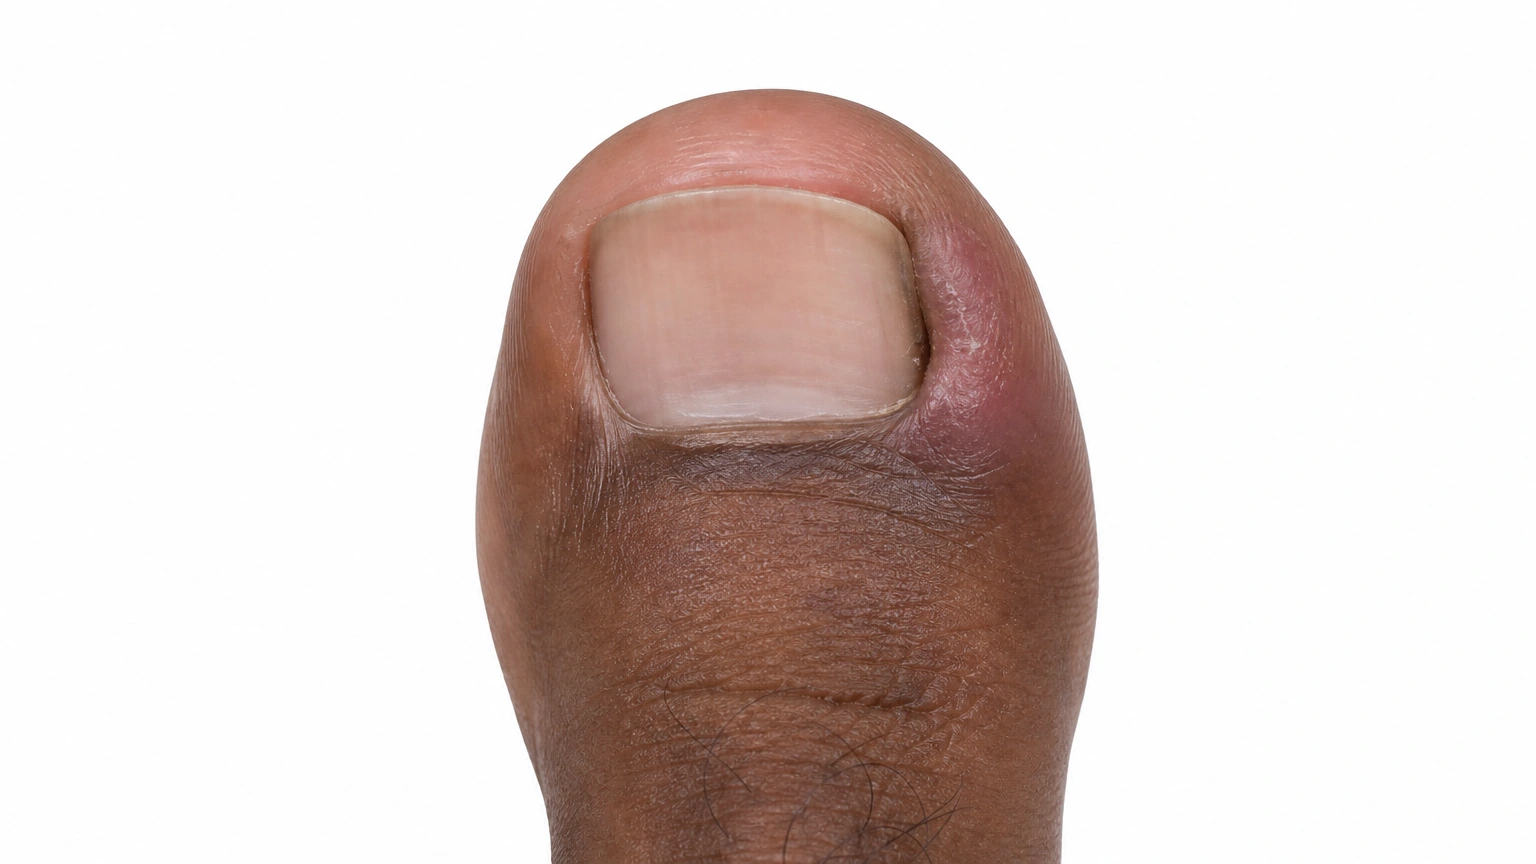
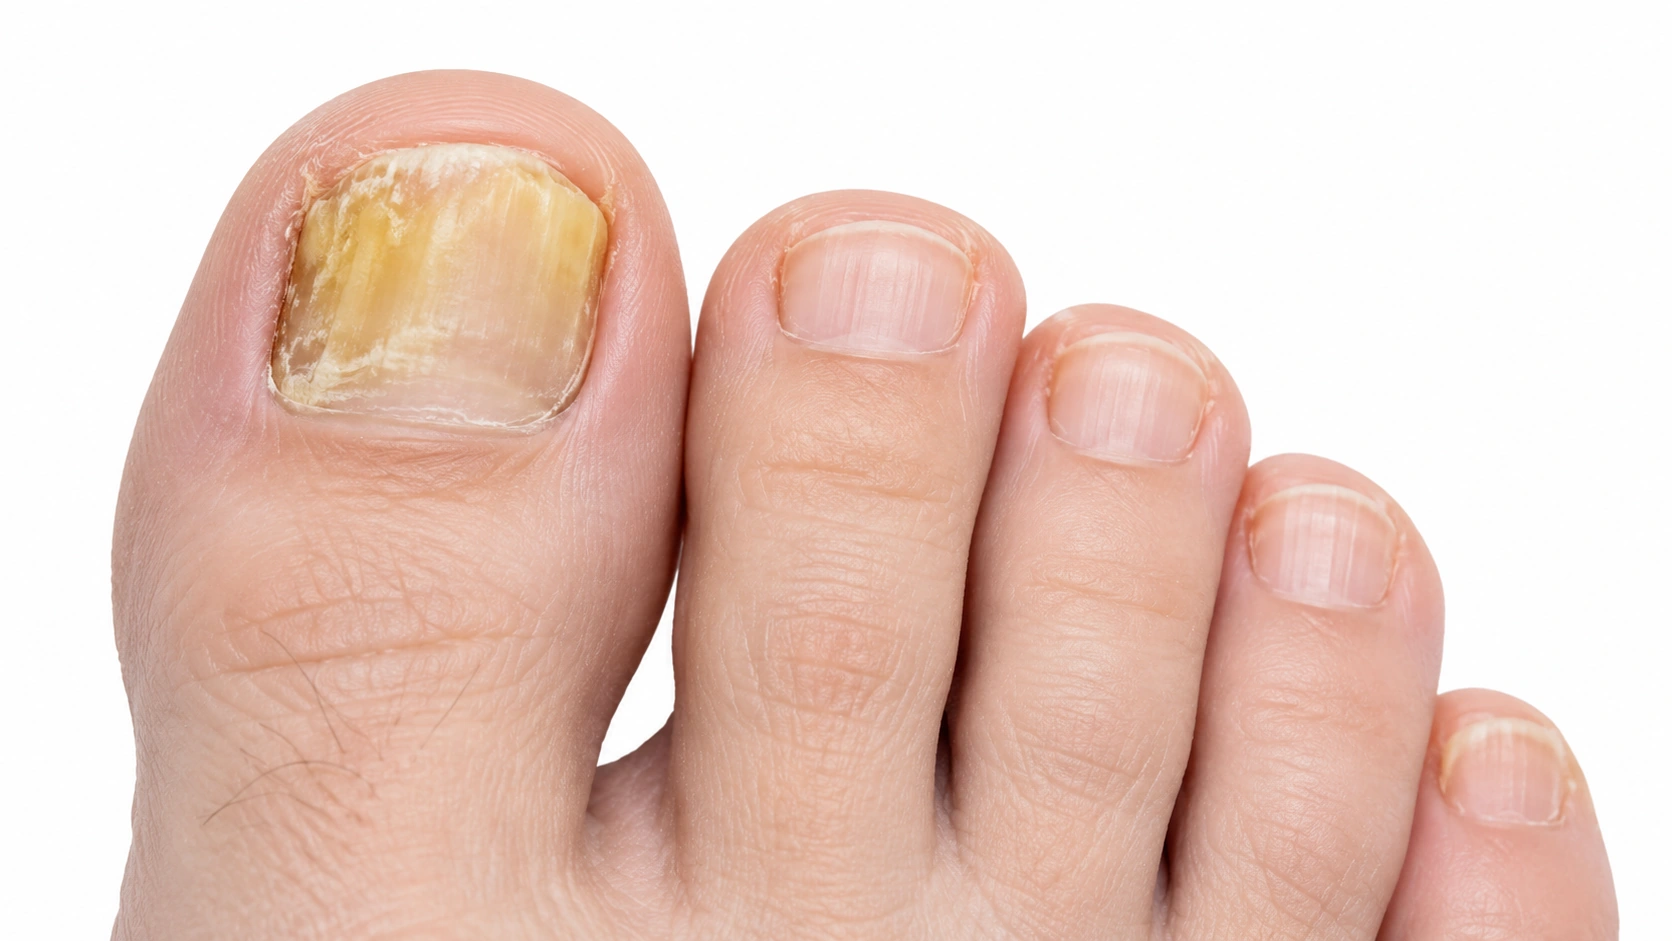
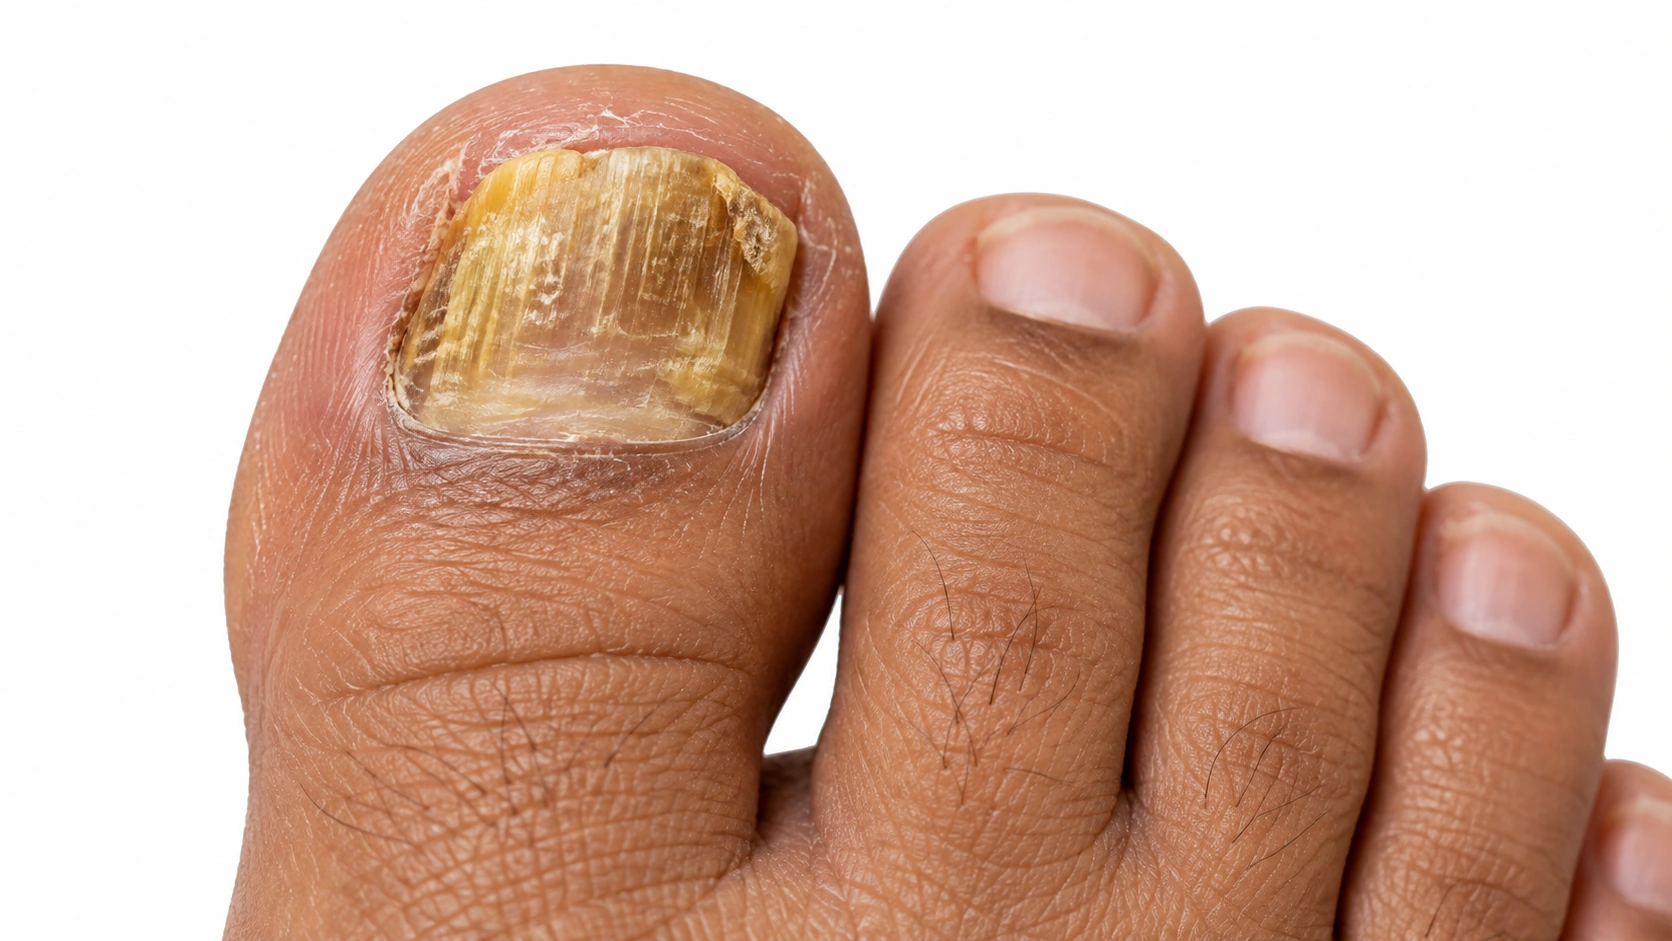
AI-generated educational illustration: Adult great toe with lateral nail edge pressing into an inflamed red nail fold, mild localized swelling; no surgery or bleeding.Thickened yellow great toenail on a light-skinned foot.

Key differences

The same eight facts on every condition comparison.

Usual age
Teens and young adults
Adults; more with age
Where
Big toenail
Toenails more than fingernails
Main sign
Red, swollen nail edge
Thick, yellow, crumbly nail
Itch or pain
Painful
Usually painless
Contagious
No
Yes, mildly
Long term
Recurs without proper trimming or procedure
Slow to clear; can return
Scars
No
No
Who gets it
Curved nails, tight shoes
Older adults, athlete's foot, diabetes

What is it?

Ingrown Toenail
Nail Fungus
What is it?
  • What it is
    A nail edge presses into the surrounding skin, causing pain and inflammation.
  • Several organisms can cause it.
    Dermatophytes, yeasts or molds can invade nail keratin.
  • It is not always trivial.
    Thickened nails can be painful in shoes and affect mobility.
  • Testing confirms it.
    Nail clippings help distinguish infection from trauma, psoriasis and other nail disease.
  • Some changes are not fungus.
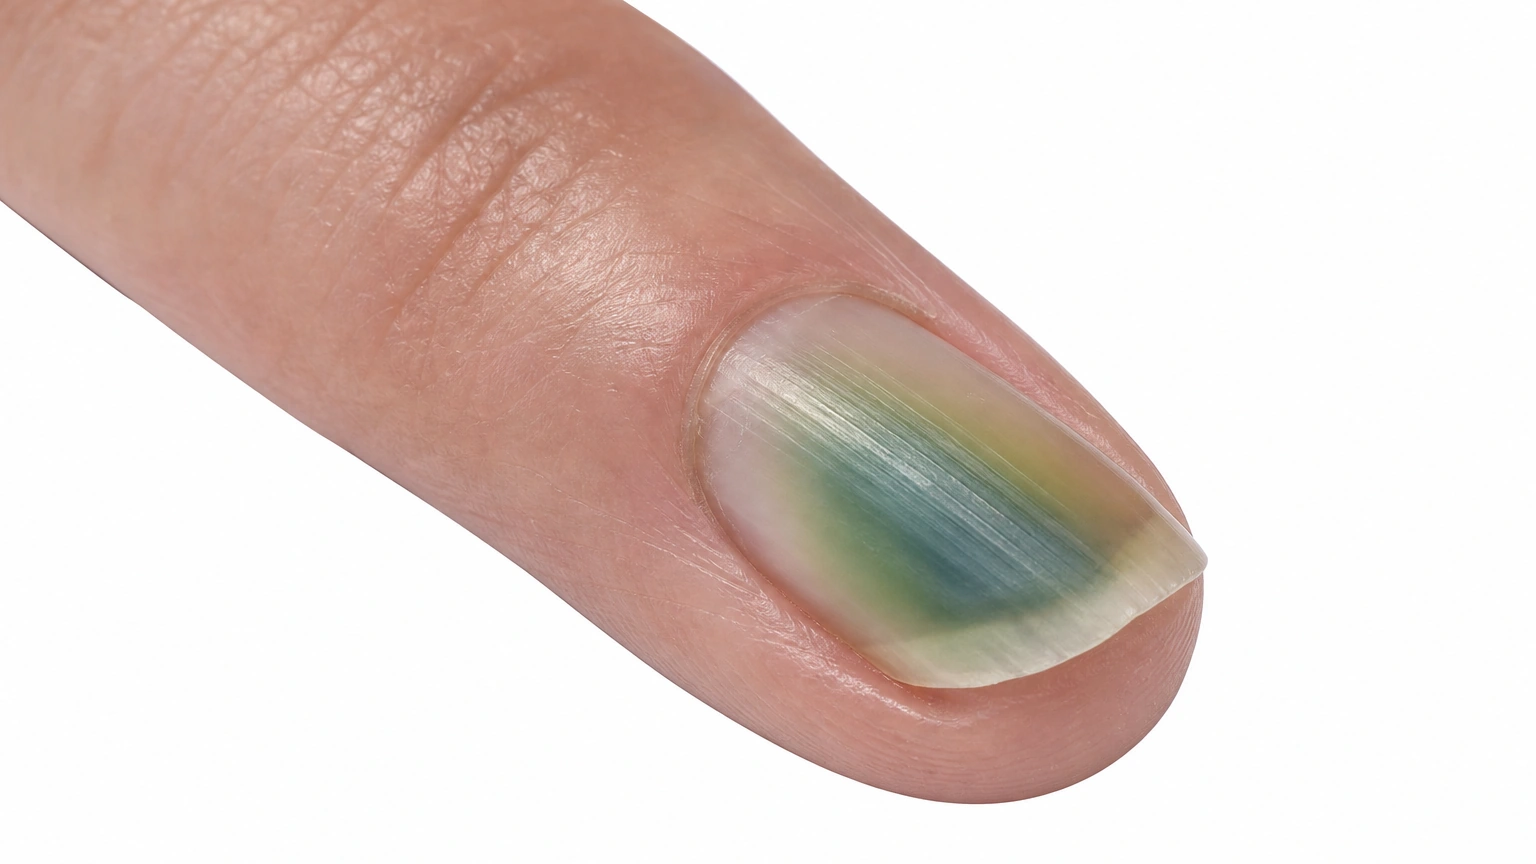
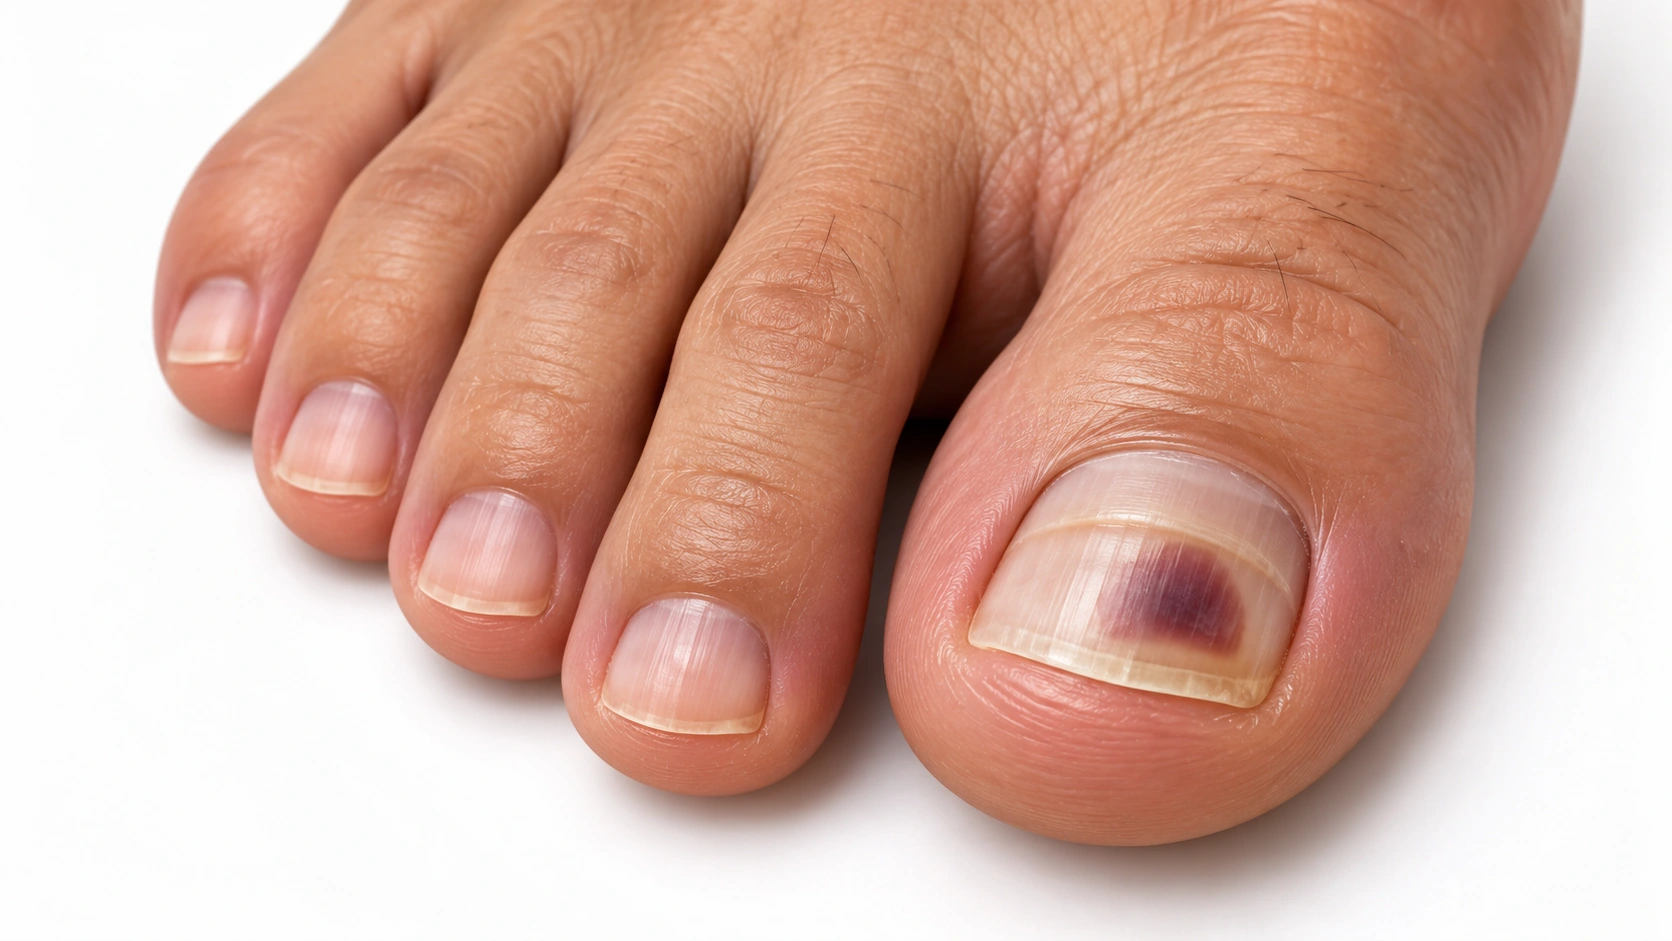
    A new dark band, bleeding or destructive change should be examined, not assumed fungal.

What it looks like

Ingrown Toenail

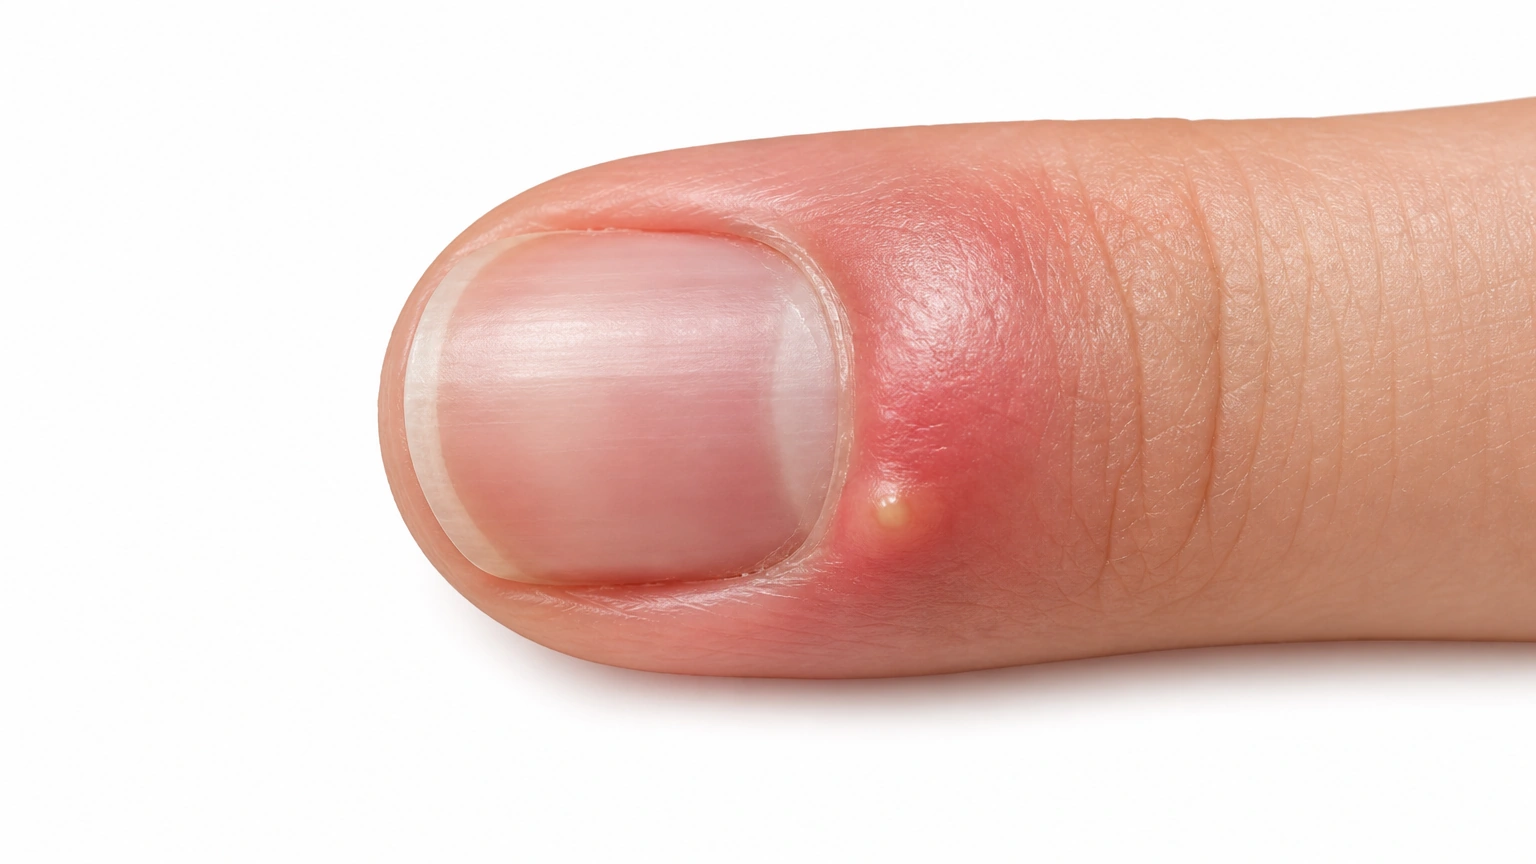
A big toe with redness and swelling along the side of the nail.

Ingrown Toenail One side of the large toenail presses into swollen-looking surrounding skin.

Nail Fungus

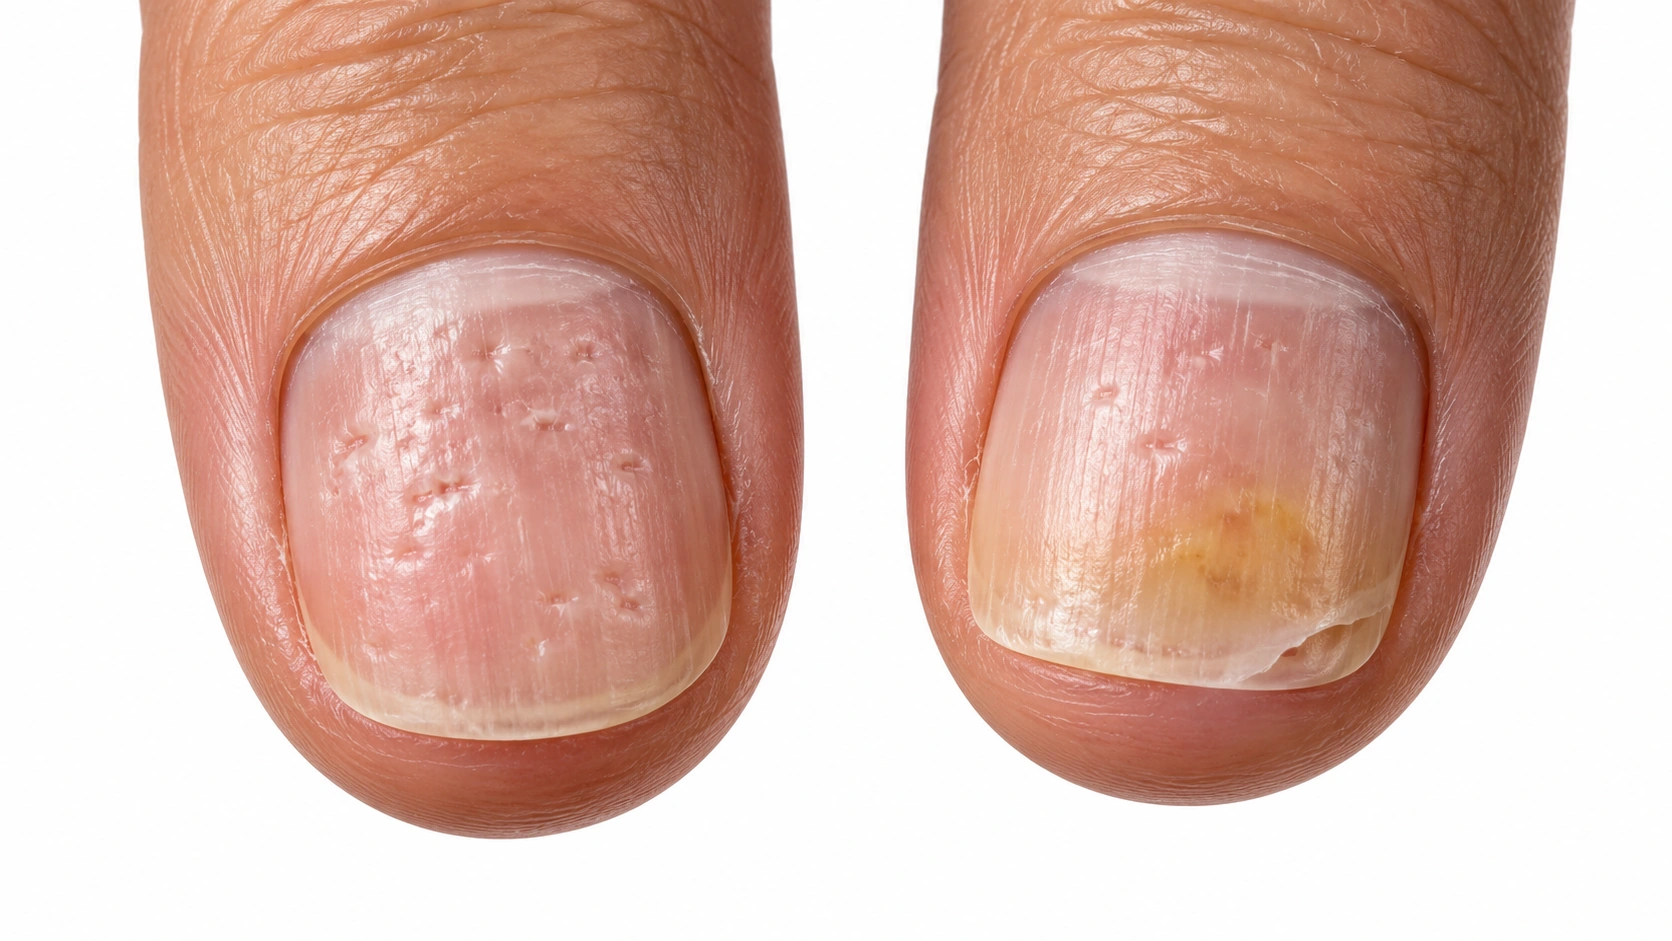
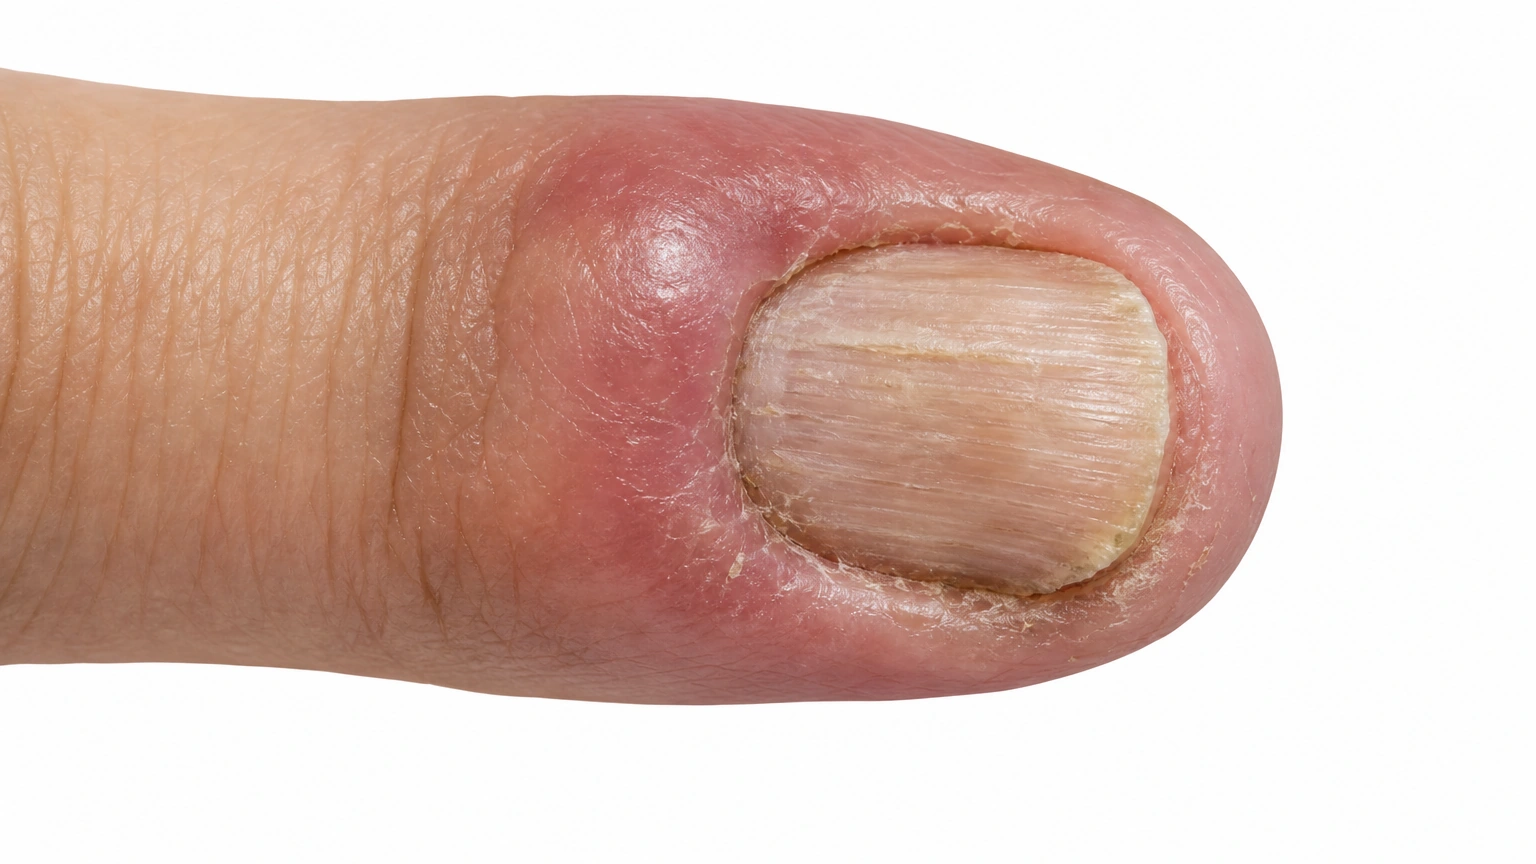
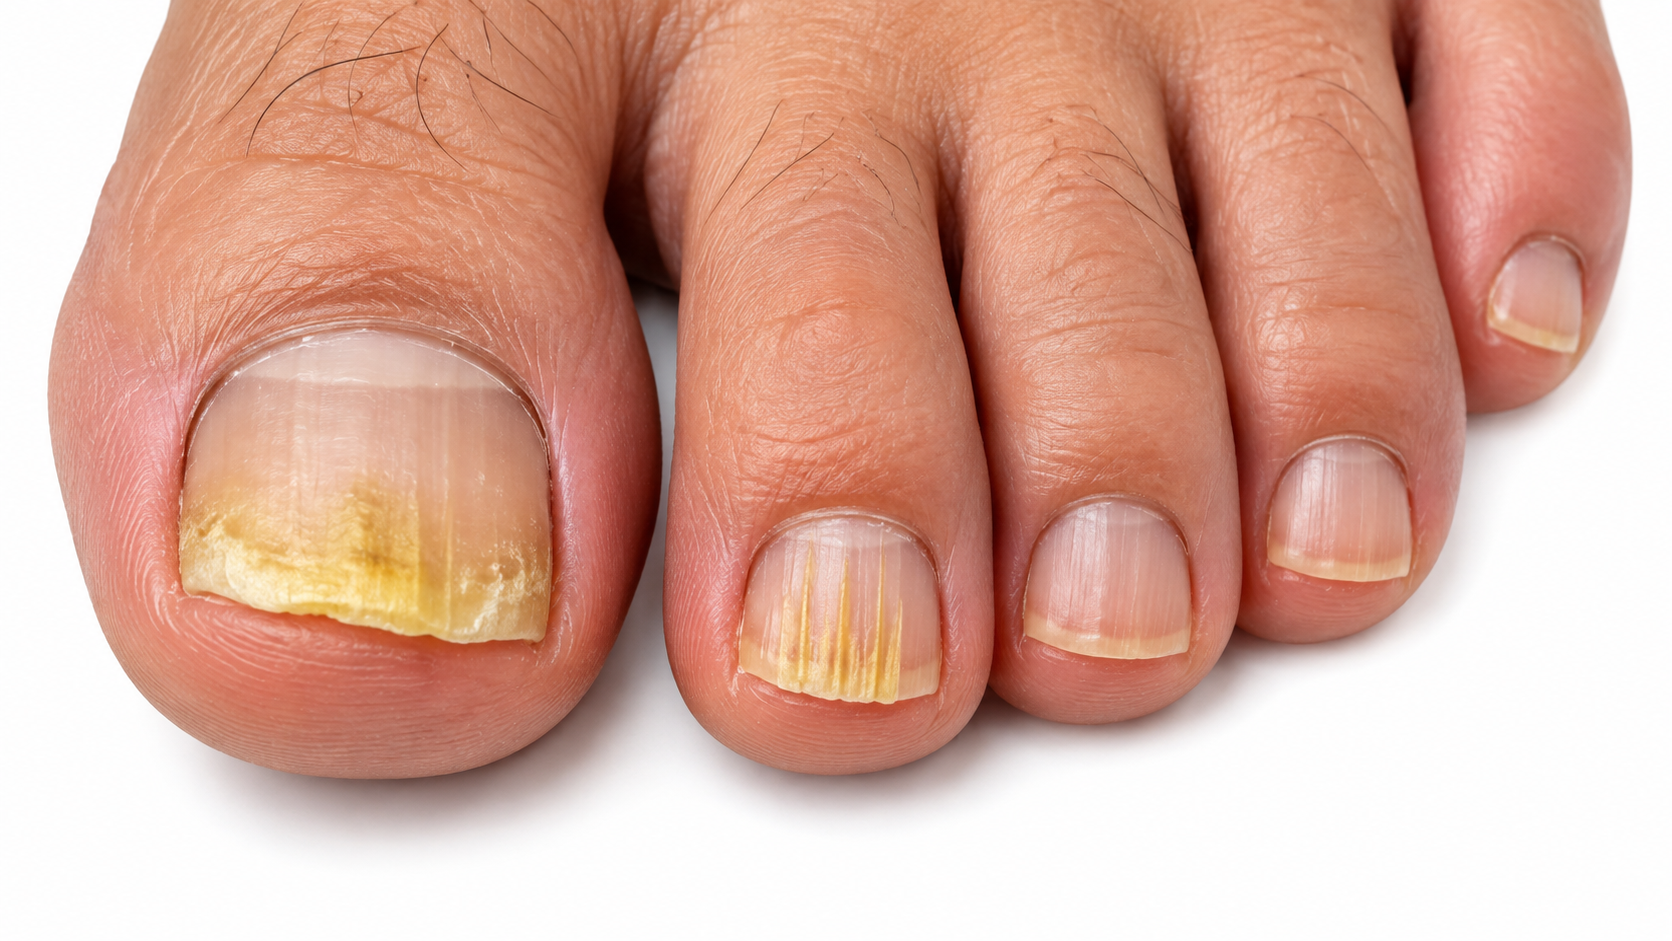
Nail Fungus: Yellow discoloration; Distal subungual.

Distal subungual onychomycosis The most common type, starting at the tip.

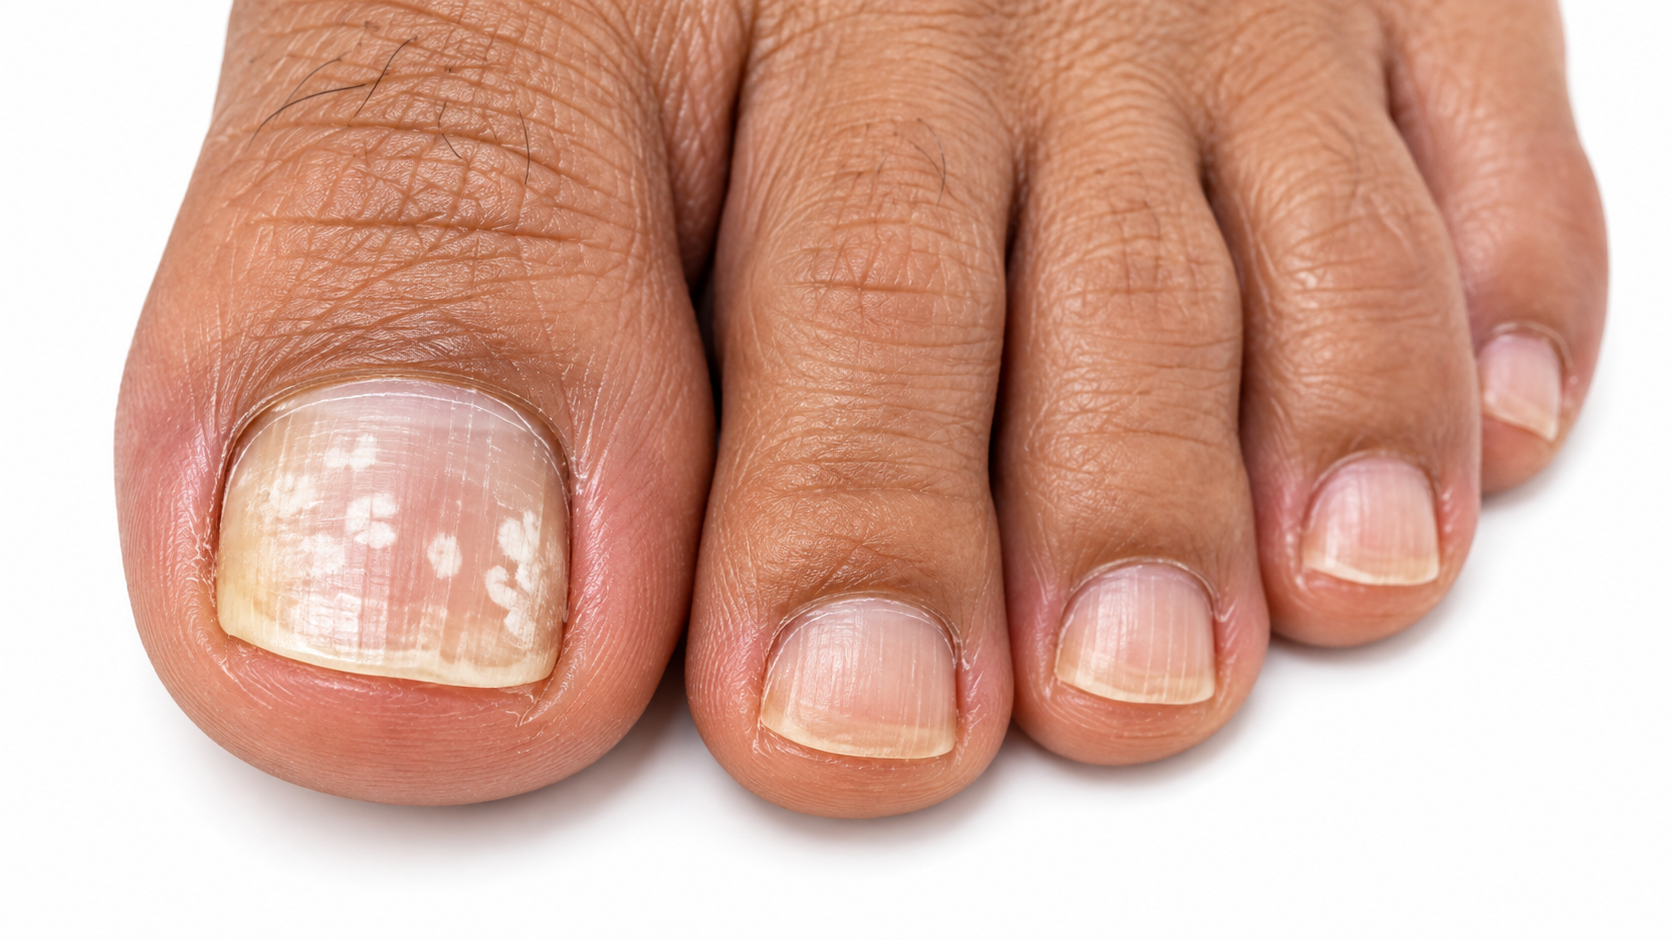
Nail Fungus: White superficial.

White superficial onychomycosis Chalky white patches on the nail surface.

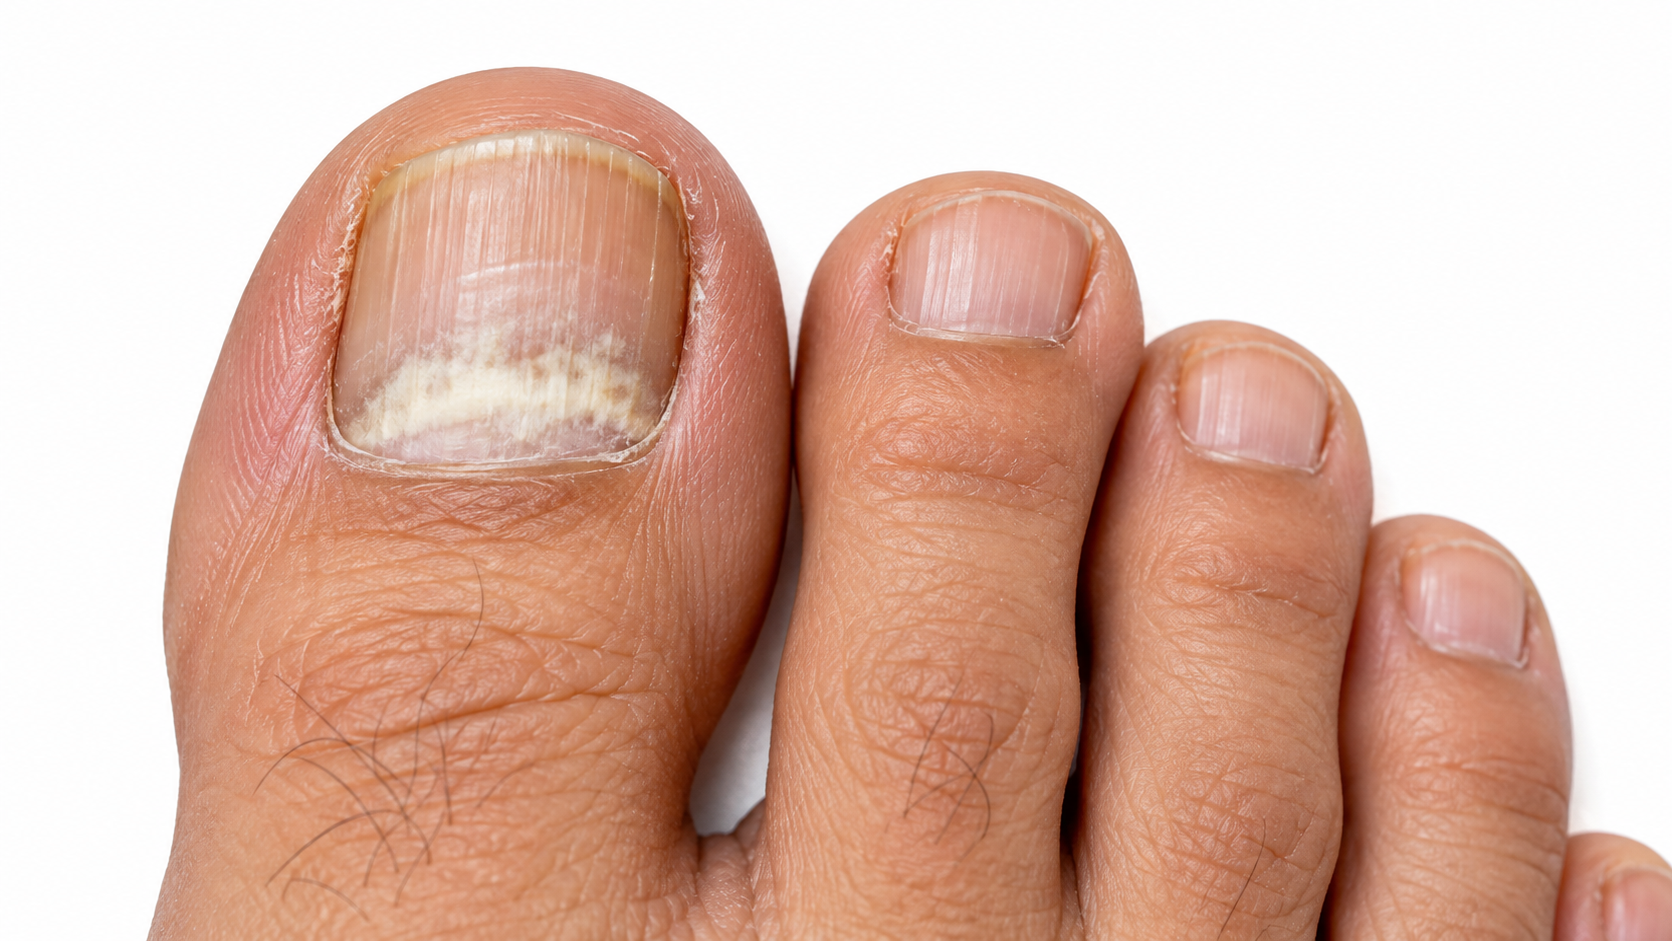
Nail Fungus: Proximal subungual.

Proximal subungual onychomycosis Starts near the cuticle; rarer.

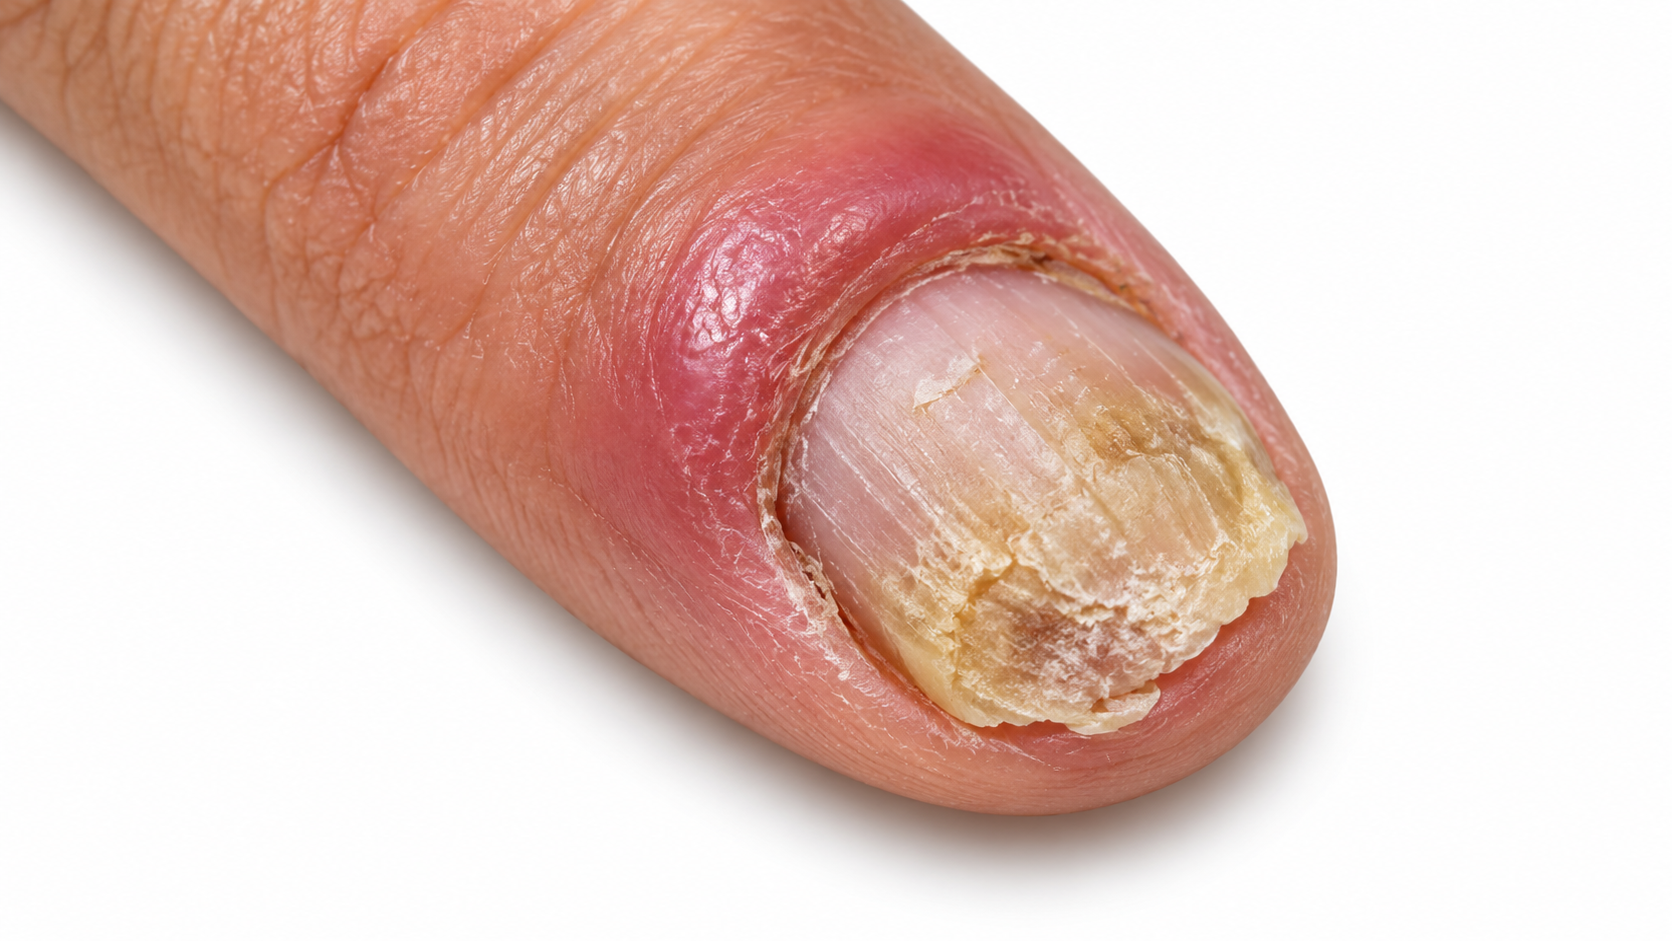
Nail Fungus: Candidal.

Candidal nail infection Caused by yeast, usually on fingernails.

Skin tones
Adult great toe with lateral nail edge pressing into an inflamed red nail fold, mild localized swelling; no surgery or bleeding.
Ingrown Toenail on medium skin.
Ingrown Toenail on brown skin.
Ingrown Toenail on deep skin.
Thickened yellow great toenail on a light-skinned foot.
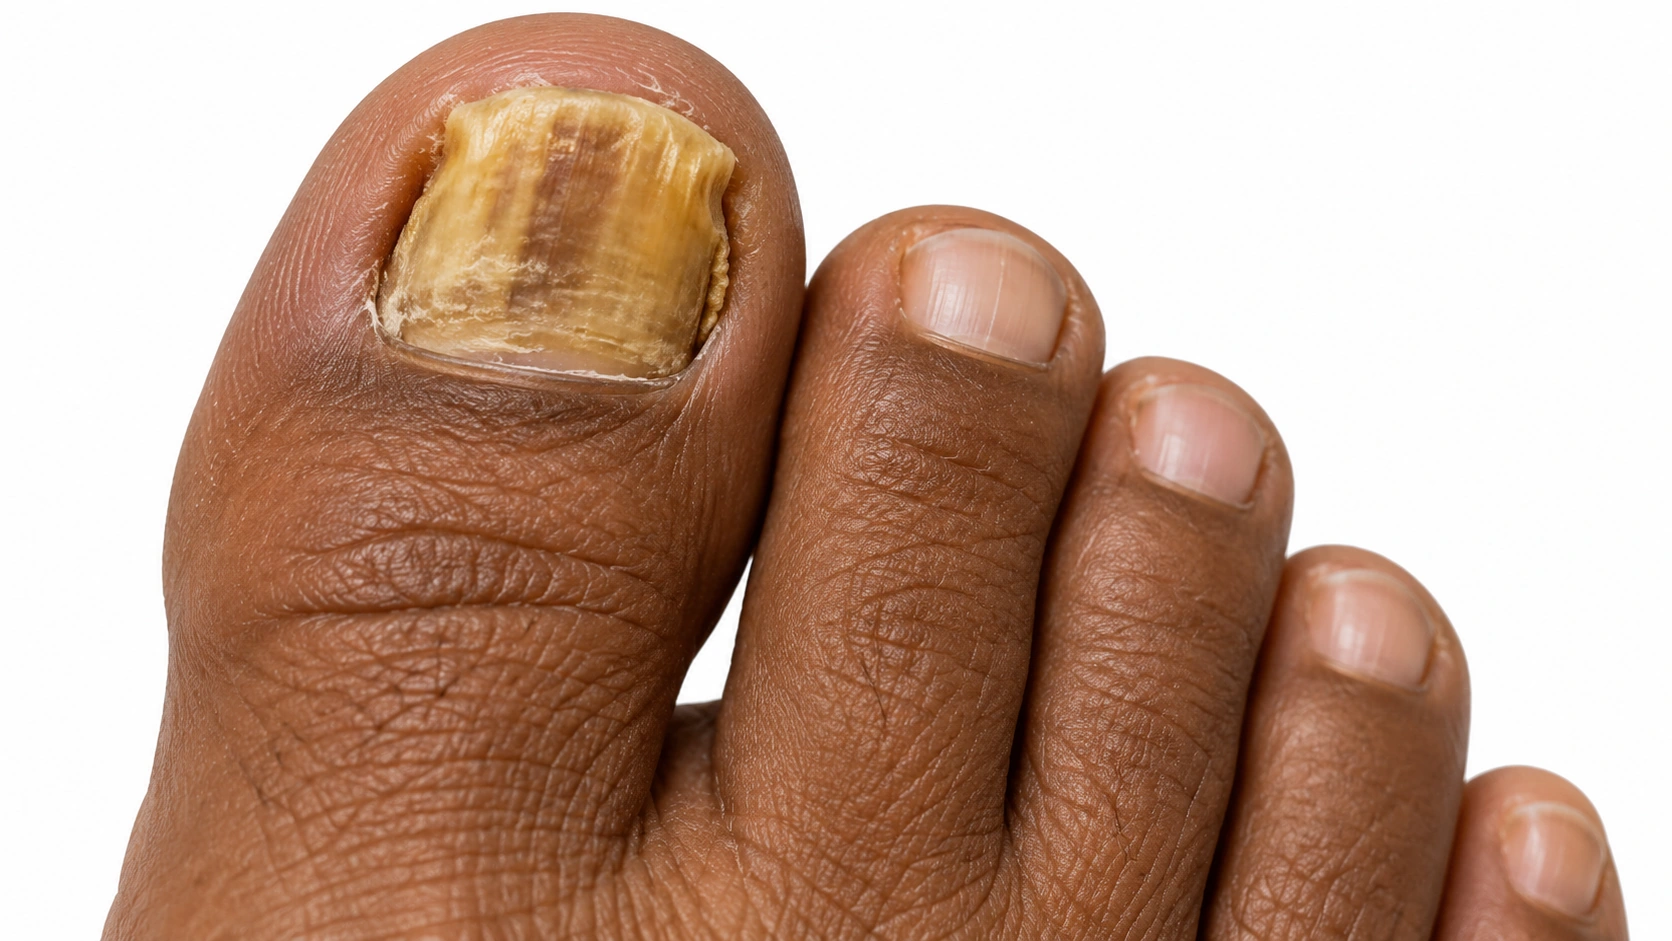
Thickened yellow-brown great toenail on a medium-toned foot.
a thickened yellow-brown great toenail on brown skin, representing nail fungus.
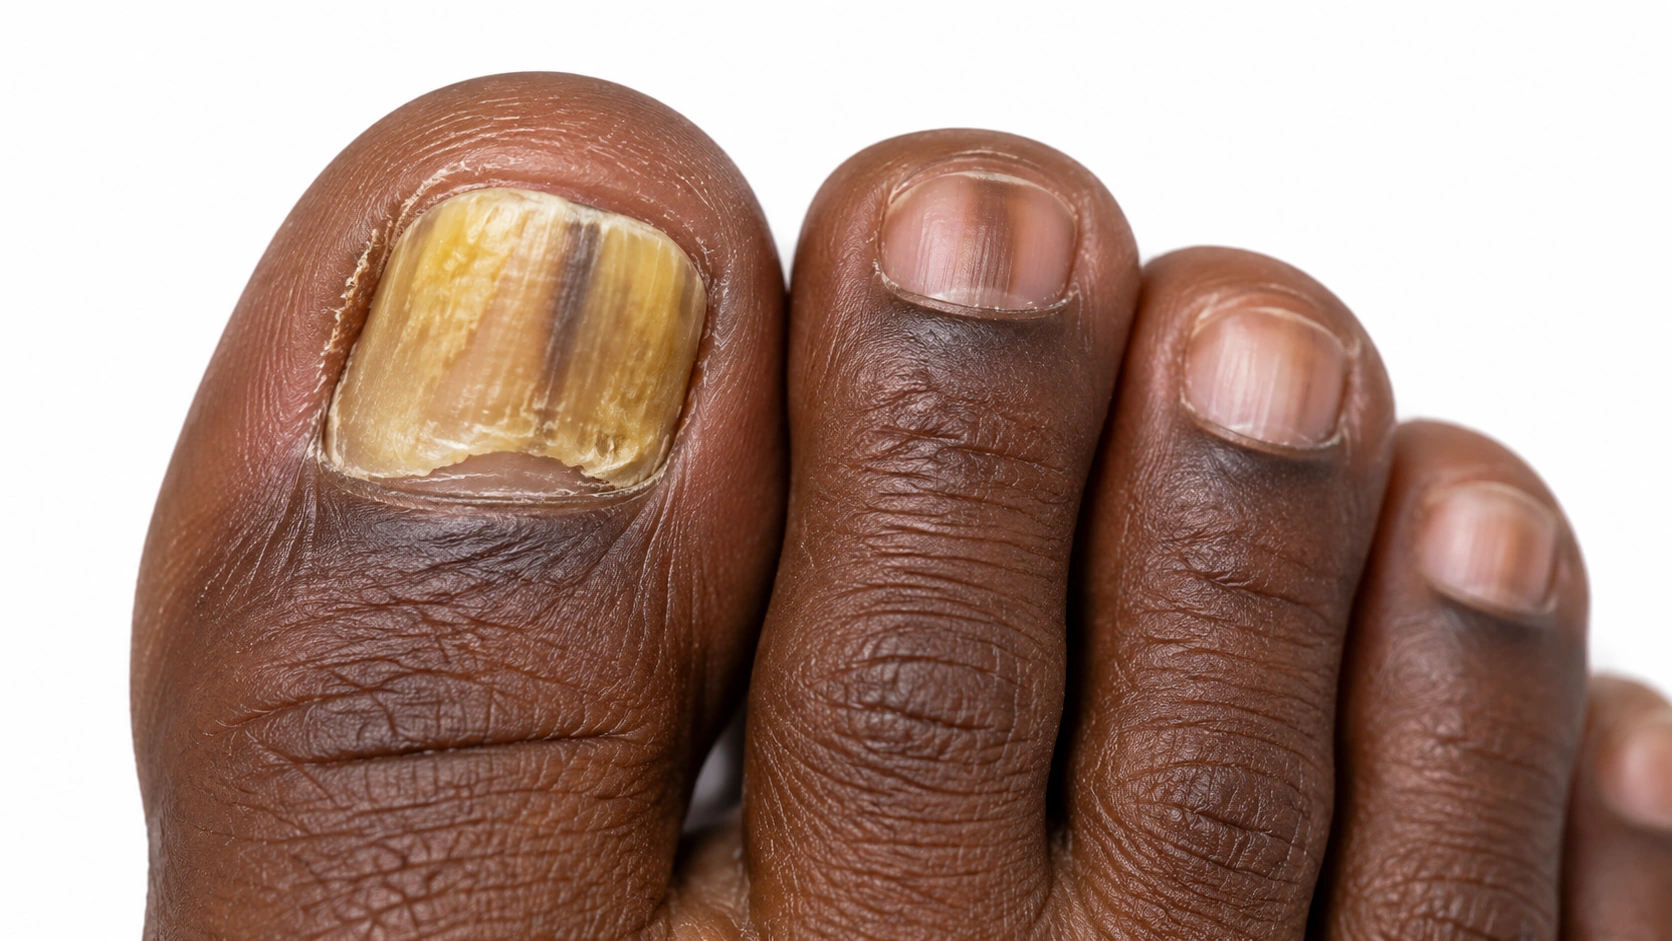
a thick yellow-brown great toenail on deep brown skin, representing fungal nail changes.
Diagram
Nail Fungus mechanism diagram. Fungi enter the nail: Infection often begins near an edge. Keratin becomes damaged: Fungal growth disrupts the nail structure. The nail thickens or lifts: Debris can collect beneath a discolored nail.
In the skin

The nail edge presses into or penetrates the adjacent soft tissue. Repeated irritation causes inflammation, and secondary infection may develop in the damaged fold.

Fungi invade the keratin that makes up the nail, often entering near an edge or a small break. Damage and debris can make the nail discolored, thickened or separated from its bed.

When it usually starts

010203040506070+

Ingrown Toenail. Can occur at any age, commonly during adolescence and young adulthood.

Nail Fungus. Can occur at any age but becomes more common in older adults.

Causes and triggers

Causes

The nail edge and adjacent soft tissue irritate one another.

Nail fungus is caused by fungi, usually the same ones behind athlete's foot. They get into the nail through small cracks or the skin around it, then grow slowly.

Family tendency

Some families are more prone to fungal nail infections, likely because of inherited differences in skin immunity.

Risk factors
Curved nails, Tight shoes, Traumatic trimming
Age over 60, Diabetes, Athlete's foot, Poor circulation, Weakened immunity
How it spreads
  • Untreated athlete's foot — Well established
  • Damp shoes and socks — Strong link
  • Barefoot in shared showers and pools — Strong link
  • Nail injury — Strong link
Trigger
● Ingrown Toenail
● Nail Fungus
Shoe pressure
Can contribute
Not listed
Cutting nail corners too short
Can contribute
Not listed

Daily Care

Ingrown Toenail
Nail Fungus
Daily care

Habits that help

  • Wear roomy shoes or open footwear that avoids pressure
    Tight shoes can push the nail edge further into sore skin.
  • Keep the toe clean and dry between washing
    Follow separate wound-care instructions after any nail procedure.
  • Let the nail grow beyond the sore edge before routine trimming
    Cut nails straight across rather than rounding the corners very short.
  • Protect the toe from repeated knocks
    Change damp socks and avoid activities that worsen pain.
  • Seek early foot-care advice for pus, spreading redness or a high-risk foot
    Diabetes, reduced sensation or poor circulation makes professional care safer.

Avoid

  • Avoid: Digging down the side or cutting a deep V in the nail
    This does not correct the underlying pressure and can create further injury.

Habits that help

  • Keep feet dry and rotate shoes
    Dry between the toes, let each pair dry.
  • Shoes in communal wet areas
    Where people acquire it.
  • Cut nails straight across
    Less trauma, fewer splits.
  • Judge by the new nail at the base
    Look for a clear band growing from the nail base.
  • Oral itraconazole
    The alternative, but it interacts with many medicines.
  • Prescription topical treatments
    Months of painting, low cure rates.
  • Treat the athlete's foot too
    This is what stops reinfection.

Avoid

  • Avoid: Wearing the same shoes every day
    They stay damp longer than you think.
  • Avoid: Damp socks and sweaty feet
    Synthetic socks, wet trainers, feet never dried.
  • Avoid: Nail trauma
    Knocks and short shoes lift the nail.
  • Avoid: Cutting or filing corners aggressively
    Digging the sides creates splits.
  • Avoid: Covering it with nail polish
    Traps moisture, hides the new nail.
  • Avoid: Sharing clippers and files
    Fungus transfers on tools easily.
  • Avoid: Walking barefoot in communal wet areas
    Where most people pick it up.
  • Avoid: Leaving athlete's foot untreated
    The skin between your toes reseeds it.
  • Avoid: Stopping because nothing has changed
    Tablets work before the nail looks better.
  • Avoid: Very thick nails left unthinned
    Medicine cannot get through.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Ingrown Toenail
● Nail Fungus
Filter by type
All types
Nail fungus type

Select one or more.

Over-the-counter
None listed
PurOrganica Urea 40% Foot Cream product.

Urea 40% nail softener

Limited evidence

A strong urea cream or patch softens a thick nail so more of it can be filed or cut away. It kills nothing on its own. Its job here is to reduce the amount of dense nail sitting between a painted-on treatment and the fungus, and to make an uncuttable nail manageable.


Illustration: Generic topical cream tube and white cream.

Terbinafine cream for the feet

Listed

This will not cure the nail, but it clears the athlete's foot on the skin that keeps reseeding it. Use it on the whole sole and between the toes, not just the itchy bit, and carry on for a week or two after the skin looks normal. Treating the skin is the single cheapest thing you can do to stop the nail coming back after a course of tablets.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Limited evidence

It does have antifungal activity in the laboratory, and the small studies in nails have shown some improvement in appearance. None have shown reliable cure of an established nail infection. It also cannot get through a thick nail, and it can irritate the skin around it.

Prescription topicals
None listed
An illustrative Jublia nail-solution bottle with brush applicator.

Jublia

Moderate evidence

Jublia. A solution painted on the nail once a day for about a year. It penetrates nail better than the older lacquers, and it suits mild infection, one or two nails, or people who cannot take tablets. Complete cure rates are still well below tablets, so it is a reasonable choice rather than the strongest one.

An illustrative Kerydin nail-solution bottle and dropper; packaging is conceptual.

Kerydin

Moderate evidence

Kerydin. Another daily paint-on solution used for about a year, with a small molecule that gets through the nail plate. Results are similar to the other topicals: many nails look better, far fewer clear completely. It works best on thin nails with the infection limited to the tip.

Ciclopirox

Moderate evidence

Penlac. The oldest of the prescription nail paints, applied daily with the built-up layers removed weekly with alcohol. Complete cure rates are low, in single figures in the original studies. It is cheap and safe, and it is mostly used when tablets are not an option.

Prescription pills
None listed
Terbinafine — Header Image

Terbinafine

Strong evidence

The first choice for dermatophyte nail infection and the option with the best cure rate: usually 12 weeks for toenails and 6 for fingernails. It binds into the nail and keeps working there for months after the last tablet. A liver blood test is standard, taste changes are a known side effect, and nothing will look different while you are taking it.

Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Strong evidence

The main alternative, and the better option when a yeast or a mould is grown rather than a dermatophyte. It is often given as pulses, a week on and three weeks off. It interacts with a long list of common medicines and is avoided in some heart conditions, so your doctor needs everything you take, including anything bought over the counter.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Moderate evidence

Taken once a week rather than daily, which suits people who struggle with a long daily course. Cure rates sit below terbinafine and it usually has to be continued until the nail has grown out, which can be a year. It also interacts with a number of other medicines.

Illustration: Generic oral tablet bottle and tablets.

Griseofulvin

Limited evidence

The old antifungal tablet, now largely replaced for nails. It needs 12 to 18 months of daily treatment, it clears fewer nails than terbinafine, and relapse afterwards is common. It is still occasionally used in children or when the newer drugs cannot be taken.

Procedures

Partial nail avulsion

Listed

Persistent or recurrent disease may need removal of the offending edge, sometimes with matrix treatment.

Nail Debridement

Limited evidence

Thinning and clipping the nail. Cutting the nail back and filing or drilling down the thickened part, usually by a podiatrist. It is painless and it does two things: it takes pressure off a sore toe, and it removes dense nail and any packed clump of fungus that medicine cannot get through. Done alongside tablets or a nail paint, it makes them work better; done alone, it does not treat the infection.

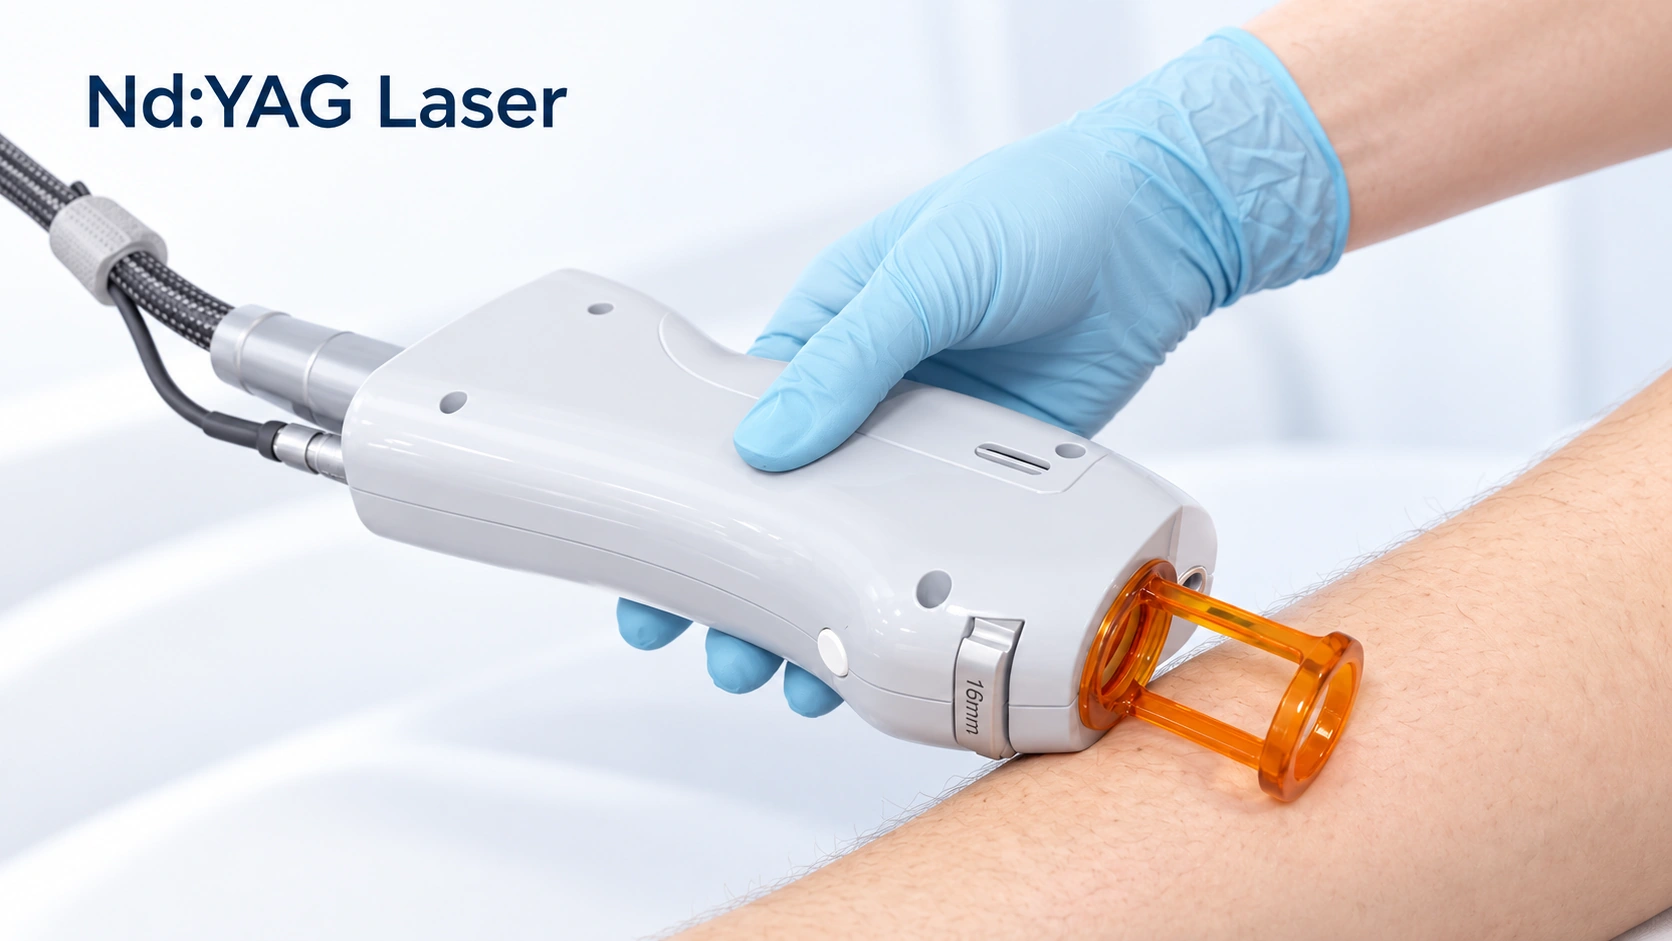
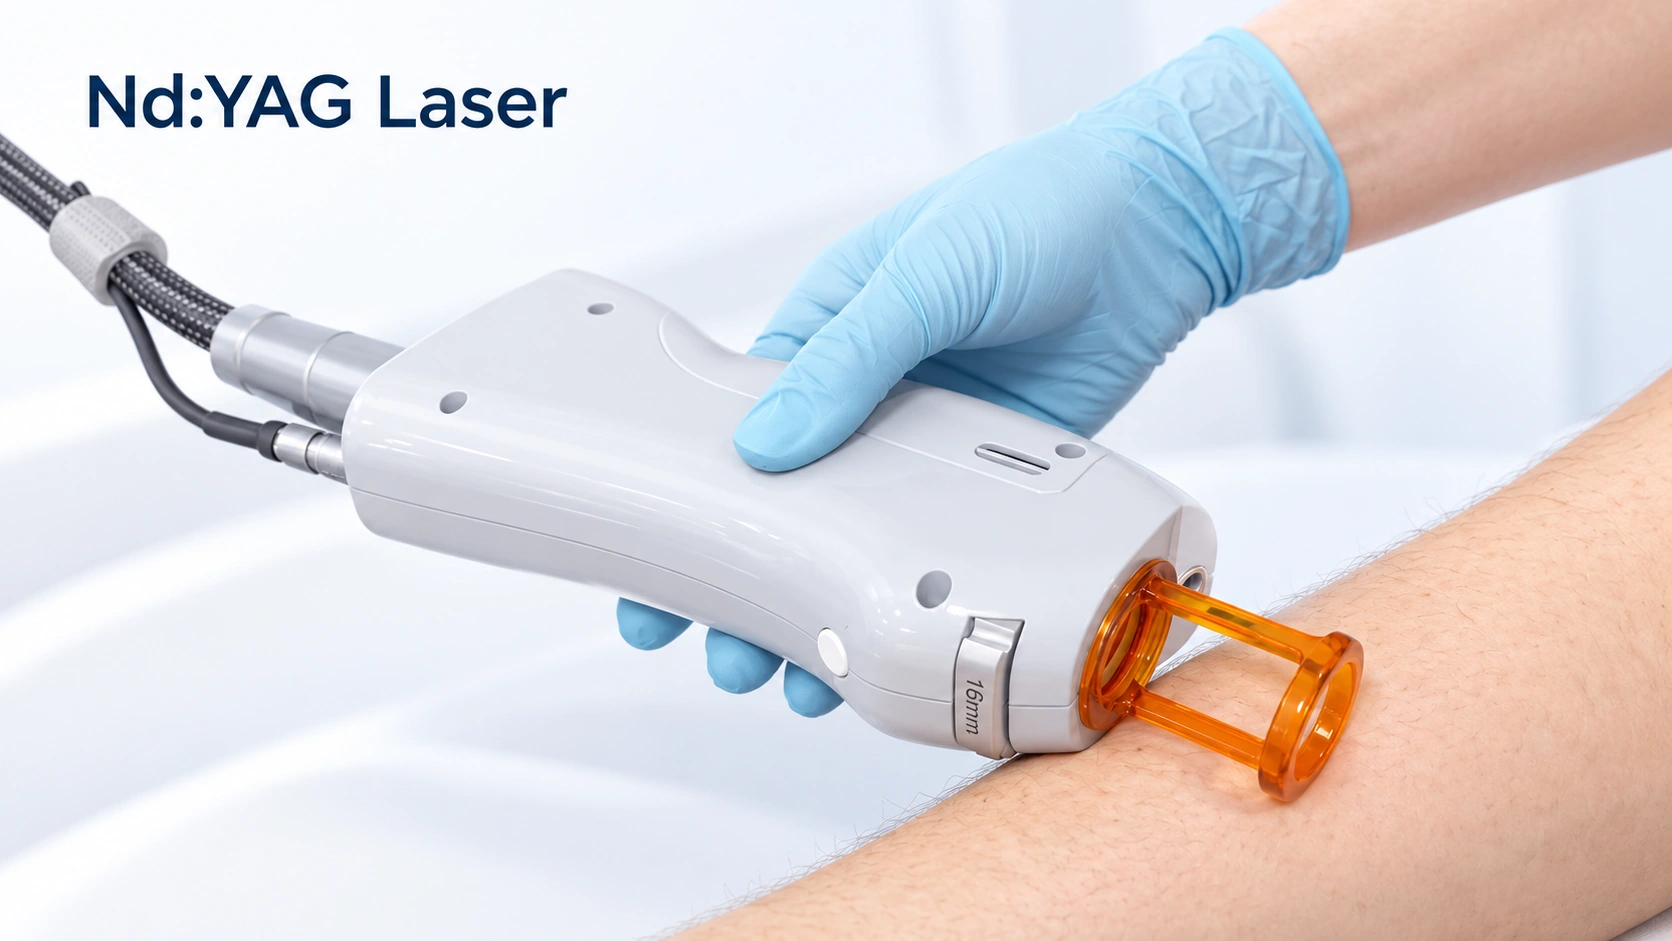
Editorial illustration for Nd:YAG Laser, based on the entry’s treatment or equipment reference.

Nd:YAG Laser

Limited evidence

Laser devices are cleared to temporarily increase the amount of clear nail, which is not the same thing as curing the infection. Studies are small, short and mostly measure appearance rather than clearance, and the fungus commonly returns. It is usually several sessions, paid for out of pocket, and it is a reasonable thing to consider only when tablets are genuinely not an option.

Nail Removal

Limited evidence

Removing the nail. Taking off part or all of the nail, either surgically or with a strong urea paste. It is not a cure on its own, because the fungus is also in the nail bed and the new nail grows back into it. It is kept for a nail that is painful, hopelessly thick, or holding a dense clump of fungus, and it is done alongside tablets rather than instead of them.

Outlook

Long term

Symptoms can settle when the nail edge and pressure are managed appropriately. Recurrence is common if the cause remains; repeated episodes may benefit from a nail procedure.

Nail fungus does not clear on its own. Left alone it takes over more of the nail and, over years, more nails. Once treatment starts, nail growth sets the timeline, so watch the base.

Complications

Possible complications

Local infection may develop; diabetes or poor circulation changes the care needed.

  • Cellulitis
  • Spread to other nails and the skin
  • Permanent nail damage
More details

Cellulitis
A thickened, cracked nail and the split skin around it give bacteria a way into the leg. The result is a spreading area of hot, swollen, tender skin, usually with feeling unwell and a fever, and it needs antibiotics quickly. It matters most for people with diabetes, poor circulation in the legs or a weakened immune system, which is why fungal nails are treated more actively in those situations.

Spread to other nails and the skin
Left alone, one infected nail slowly seeds the others, and the same fungus keeps the skin of the sole and the gaps between the toes scaly and itchy. This is athlete's foot and nail fungus feeding each other. Treating the nail while ignoring the skin is the usual reason people end up doing the whole course twice.

Permanent nail damage
If the infection has been there for years, the tissue that makes the nail can be scarred by the time it clears. The nail then grows back ridged, short or misshapen even though the fungus is gone. It is not common, and it is a reason to treat sooner rather than later rather than a reason to expect it.

When to get help

When to get help

Get prompt care for infection, severe pain, diabetes or poor circulation.

Confirm the diagnosis before long treatment courses. Seek care sooner for diabetes, poor circulation, painful swelling or infection around the nail.

Common questions

Ingrown Toenail:What is Ingrown Toenail?

A nail edge presses into the surrounding skin, causing pain and inflammation.

Ingrown Toenail:What can I do day to day?

Wear roomy footwear and avoid digging into nail corners. Trim nails straight across.

Ingrown Toenail:When should I get medical advice?

Get prompt care for infection, severe pain, diabetes or poor circulation.

Nail Fungus:How long before my nail looks normal?

Longer than almost anyone expects. The medicine protects new nail as it forms, and a toenail takes roughly 12 to 18 months to replace itself, a fingernail about 4 to 6. Progress is a widening band of clear nail at the cuticle, not the tip.

Nail Fungus:Do I really need tablets, or can I use something on the nail?

It depends how much nail is involved. Prescription topicals suit mild infection, one or two nails, or when tablets are not suitable, and they avoid blood tests. Cure rates are distinctly lower and they need daily use for close to a year. For thick nails, several nails, or infection at the cuticle, tablets are what work.

Nail Fungus:Are the tablets dangerous?

Most healthy adults tolerate them well and serious problems are uncommon. Terbinafine can affect the liver, so a blood test before or during the course is standard, and taste changes are common. Itraconazole interacts with a long list of medicines and is avoided in some heart conditions. Your doctor needs a full list of what else you take.

Nail Fungus:Can I still paint my nails?

While you are being tested, no - polish makes sampling harder and hides what is happening. During treatment it is not forbidden, but it hides the new nail you are meant to be watching, and gel removal damages the plate. Going bare is more useful.

Nail Fungus:Will it come back?

It can, and in a meaningful number of people it does. The strongest protection is not another course of tablets - it is treating the athlete's foot, keeping feet dry, rotating shoes, and wearing something in communal wet areas.

Nail Fungus:Can I give it to my family?

It spreads within a household more than between strangers - shared floors, towels, bath mats and clippers. Use your own clippers and file, keep a separate foot towel, and treat any athlete's foot in the house. Ordinary contact is very unlikely.

Sources

Sources and further reading

  1. Ingrown toenail
  2. DermNet
Dermapedia on YouTube