Ingrown Toenail

An ingrown toenail is a mechanical problem at the edge of the nail. The corner of the nail presses into the skin beside it, and that one spot turns red, swollen and sore. Toenail fungus is an infection inside the nail itself. The nail turns thick, yellow-brown and crumbly, and it usually does not hurt at all. Pain on one side of the toe points to an ingrown nail. A nail that looks wrong but feels fine points to fungus.
| The difference | Ingrown Toenail | Nail Fungus (Onychomycosis) |
|---|---|---|
| What it is | The nail corner grows into the skin | A fungus living inside the nail |
| What it looks like | Red, puffy skin on one side | Thick, yellow-brown, crumbly nail |
| Does it hurt | Yes, and quickly | Usually not |
| What it does over time | Worse until the pressure changes | Slowly worse over months |
| Treatment | Take the pressure off the edge | Antifungal treatment, then wait |

Side by side
Ingrown Toenail
The nail corner grows into the skin
The edge of the nail pushes into the soft skin fold beside it. The skin reacts like it would to a splinter. Nothing is infected at the start.
Nail Fungus (Onychomycosis)
A fungus living inside the nail
Fungus gets under the nail, usually from the free edge, and feeds on the keratin the nail is made of. The nail is being slowly eaten from within.
Ingrown Toenail
Red, puffy skin on one side
The nail itself looks normal. The skin next to it is swollen, shiny and sometimes has a small bead of yellow fluid at the corner.
Nail Fungus (Onychomycosis)
Thick, yellow-brown, crumbly nail
The skin around it looks normal. The nail thickens, lifts away from the nail bed, and the edge crumbles when you cut it.
Nail fungus makes the nail thick, yellow and crumbly. It usually starts at the tip and spreads back.
Ingrown Toenail
Yes, and quickly
Throbs in a tight shoe, hurts when the bedsheet presses on it, and is tender to touch on that one side.
Nail Fungus (Onychomycosis)
Usually not
Most people notice the colour and thickness long before they feel anything. A very thick nail can start to press and ache inside a shoe.
Ingrown Toenail
One edge, usually the big toe
Almost always the outer or inner corner. One side at a time.
Nail Fungus (Onychomycosis)
The whole nail plate
Starts at the outer corner or the tip, then spreads back toward the base. Often more than one toe.
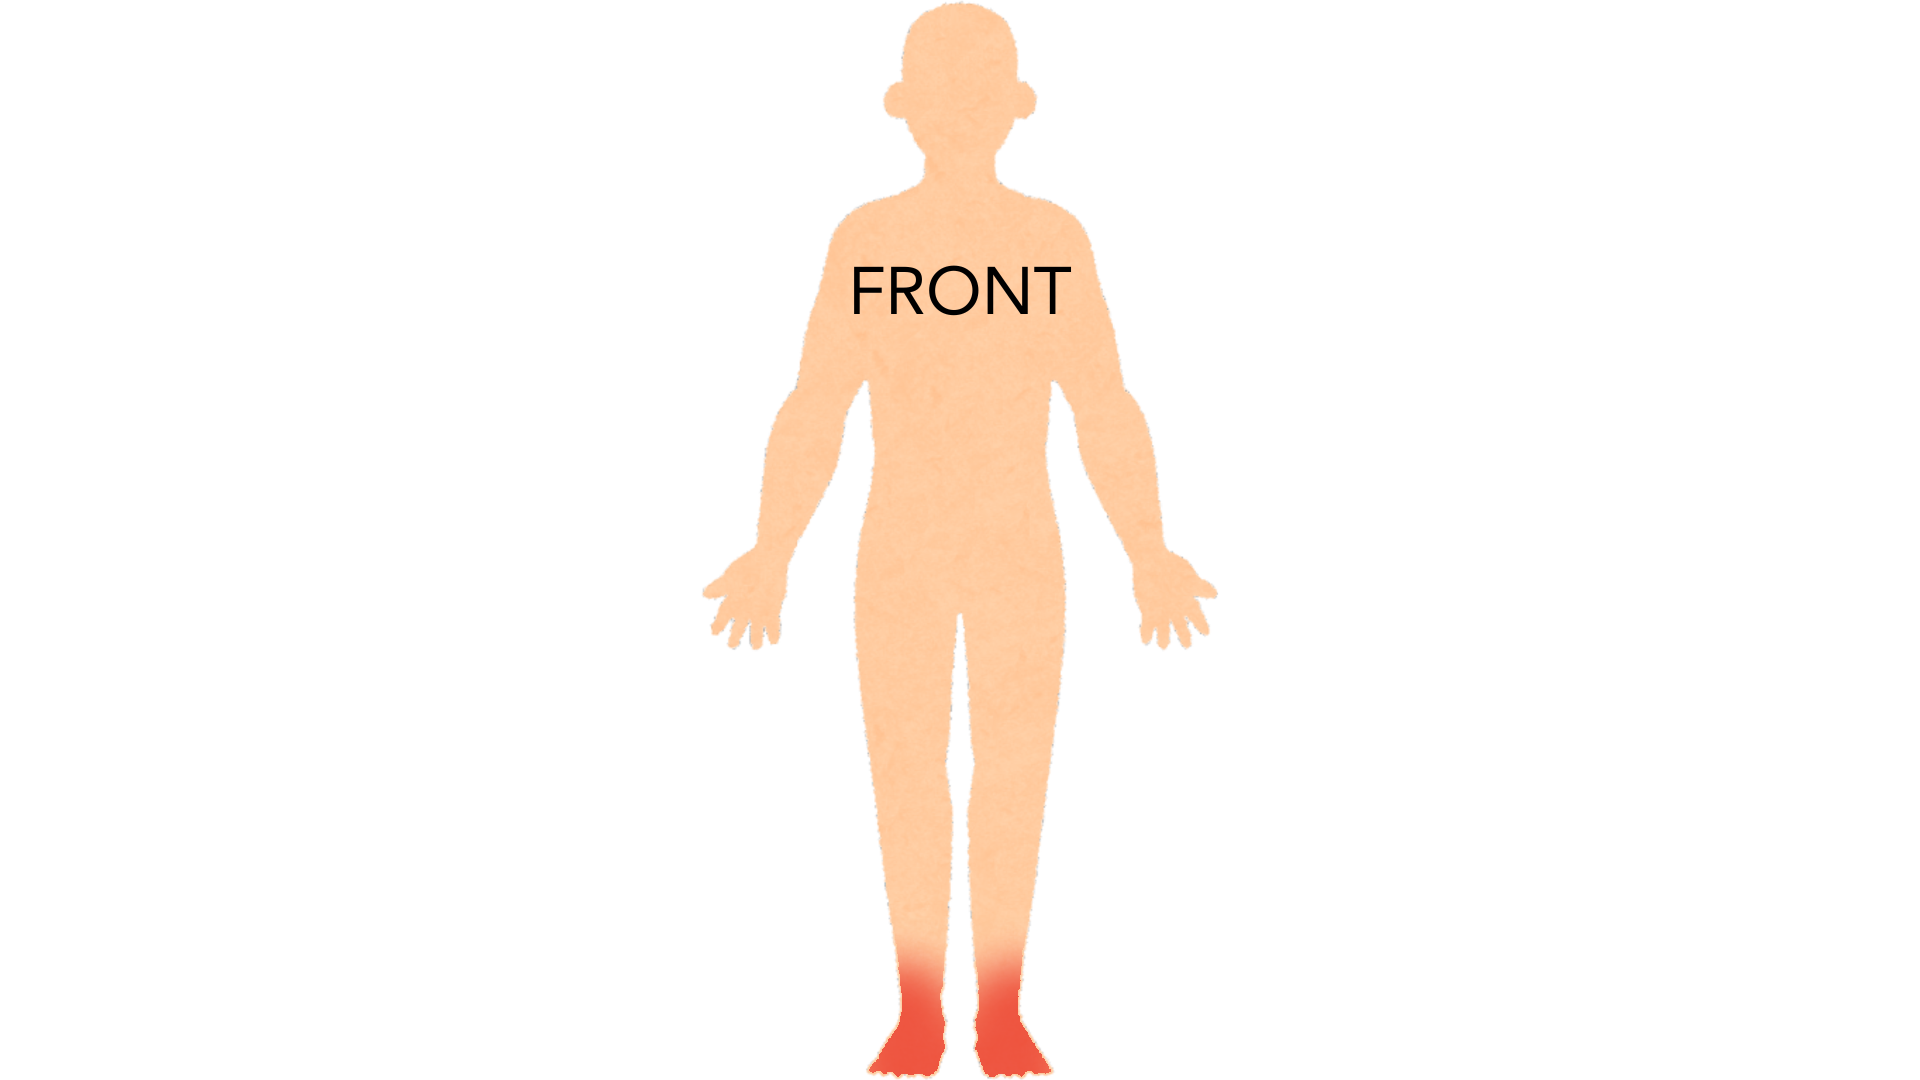
Toenails are affected far more often than fingernails, and the big toe is usually the first and the worst. It normally starts at the far edge or the side of the nail and works back toward the base. Look at the skin between the toes at the same time — athlete's foot is usually there too, and it is where the fungus came from.

Fingernails are affected less often, and usually on one hand only, spread there from the feet. A fingernail problem on both hands at once is more likely to be something else, such as psoriasis or damage from wet work.
Ingrown Toenail
Worse until the pressure changes
Days to weeks. The skin can pile up over the nail edge and start to weep. It settles fast once the nail stops digging in.
Nail Fungus (Onychomycosis)
Slowly worse over months
Fungus does not clear on its own. It creeps back along the nail and often spreads to the neighbouring toes.
Ingrown Toenail
Take the pressure off the edge
Warm salt-water soaks, roomier shoes, and a clinician lifting or trimming the offending corner. A stubborn one is treated by numbing the toe and removing a narrow strip of nail edge.
Nail Fungus (Onychomycosis)
Antifungal treatment, then wait
A prescription tablet course, usually about twelve weeks, or a medicated nail lacquer for milder cases. The medicine kills the fungus; the damaged nail still has to grow out.

This will not cure the nail, but it clears the athlete's foot on the skin that keeps reseeding it. Use it on the whole sole and between the toes, not just the itchy bit, and carry on for a week or two after the skin looks normal. Treating the skin is the single cheapest thing you can do to stop the nail coming back after a course of tablets.

A strong urea cream or patch softens a thick nail so more of it can be filed or cut away. It kills nothing on its own. Its job here is to reduce the amount of dense nail sitting between a painted-on treatment and the fungus, and to make an uncuttable nail manageable.

It does have antifungal activity in the laboratory, and the small studies in nails have shown some improvement in appearance. None have shown reliable cure of an established nail infection. It also cannot get through a thick nail, and it can irritate the skin around it.

Both are recommended constantly online and the evidence behind them is thin. At best they slow surface fungus a little. The real cost is time: months spent soaking are months the nail could have been growing out clear under treatment that works.

Laser devices are cleared to temporarily increase the amount of clear nail, which is not the same thing as curing the infection. Studies are small, short and mostly measure appearance rather than clearance, and the fungus commonly returns. It is usually several sessions, paid for out of pocket, and it is a reasonable thing to consider only when tablets are genuinely not an option.
The first choice for dermatophyte nail infection and the option with the best cure rate: usually 12 weeks for toenails and 6 for fingernails. It binds into the nail and keeps working there for months after the last tablet. A liver blood test is standard, taste changes are a known side effect, and nothing will look different while you are taking it.
The main alternative, and the better option when a yeast or a mould is grown rather than a dermatophyte. It is often given as pulses, a week on and three weeks off. It interacts with a long list of common medicines and is avoided in some heart conditions, so your doctor needs everything you take, including anything bought over the counter.
Taken once a week rather than daily, which suits people who struggle with a long daily course. Cure rates sit below terbinafine and it usually has to be continued until the nail has grown out, which can be a year. It also interacts with a number of other medicines.

The old antifungal tablet, now largely replaced for nails. It needs 12 to 18 months of daily treatment, it clears fewer nails than terbinafine, and relapse afterwards is common. It is still occasionally used in children or when the newer drugs cannot be taken.

A solution painted on the nail once a day for about a year. It penetrates nail better than the older lacquers, and it suits mild infection, one or two nails, or people who cannot take tablets. Complete cure rates are still well below tablets, so it is a reasonable choice rather than the strongest one.

Another daily paint-on solution used for about a year, with a small molecule that gets through the nail plate. Results are similar to the other topicals: many nails look better, far fewer clear completely. It works best on thin nails with the infection limited to the tip.

The oldest of the prescription nail paints, applied daily with the built-up layers removed weekly with alcohol. Complete cure rates are low, in single figures in the original studies. It is cheap and safe, and it is mostly used when tablets are not an option.
Ingrown Toenail
Days to a few weeks
Nail Fungus (Onychomycosis)
Twelve to eighteen months
A toenail grows roughly a millimetre a month, so even a cured nail looks bad for a year while the healthy nail replaces it.
Nail Fungus (Onychomycosis)
Look at the nail, then look at the skin.
A nail clipping settles it. If the picture is mixed, a clinician can send a small clipping to be examined for fungus. That matters, because antifungal tablets are a three-month commitment and plenty of thick, discoloured nails turn out not to be fungal at all.
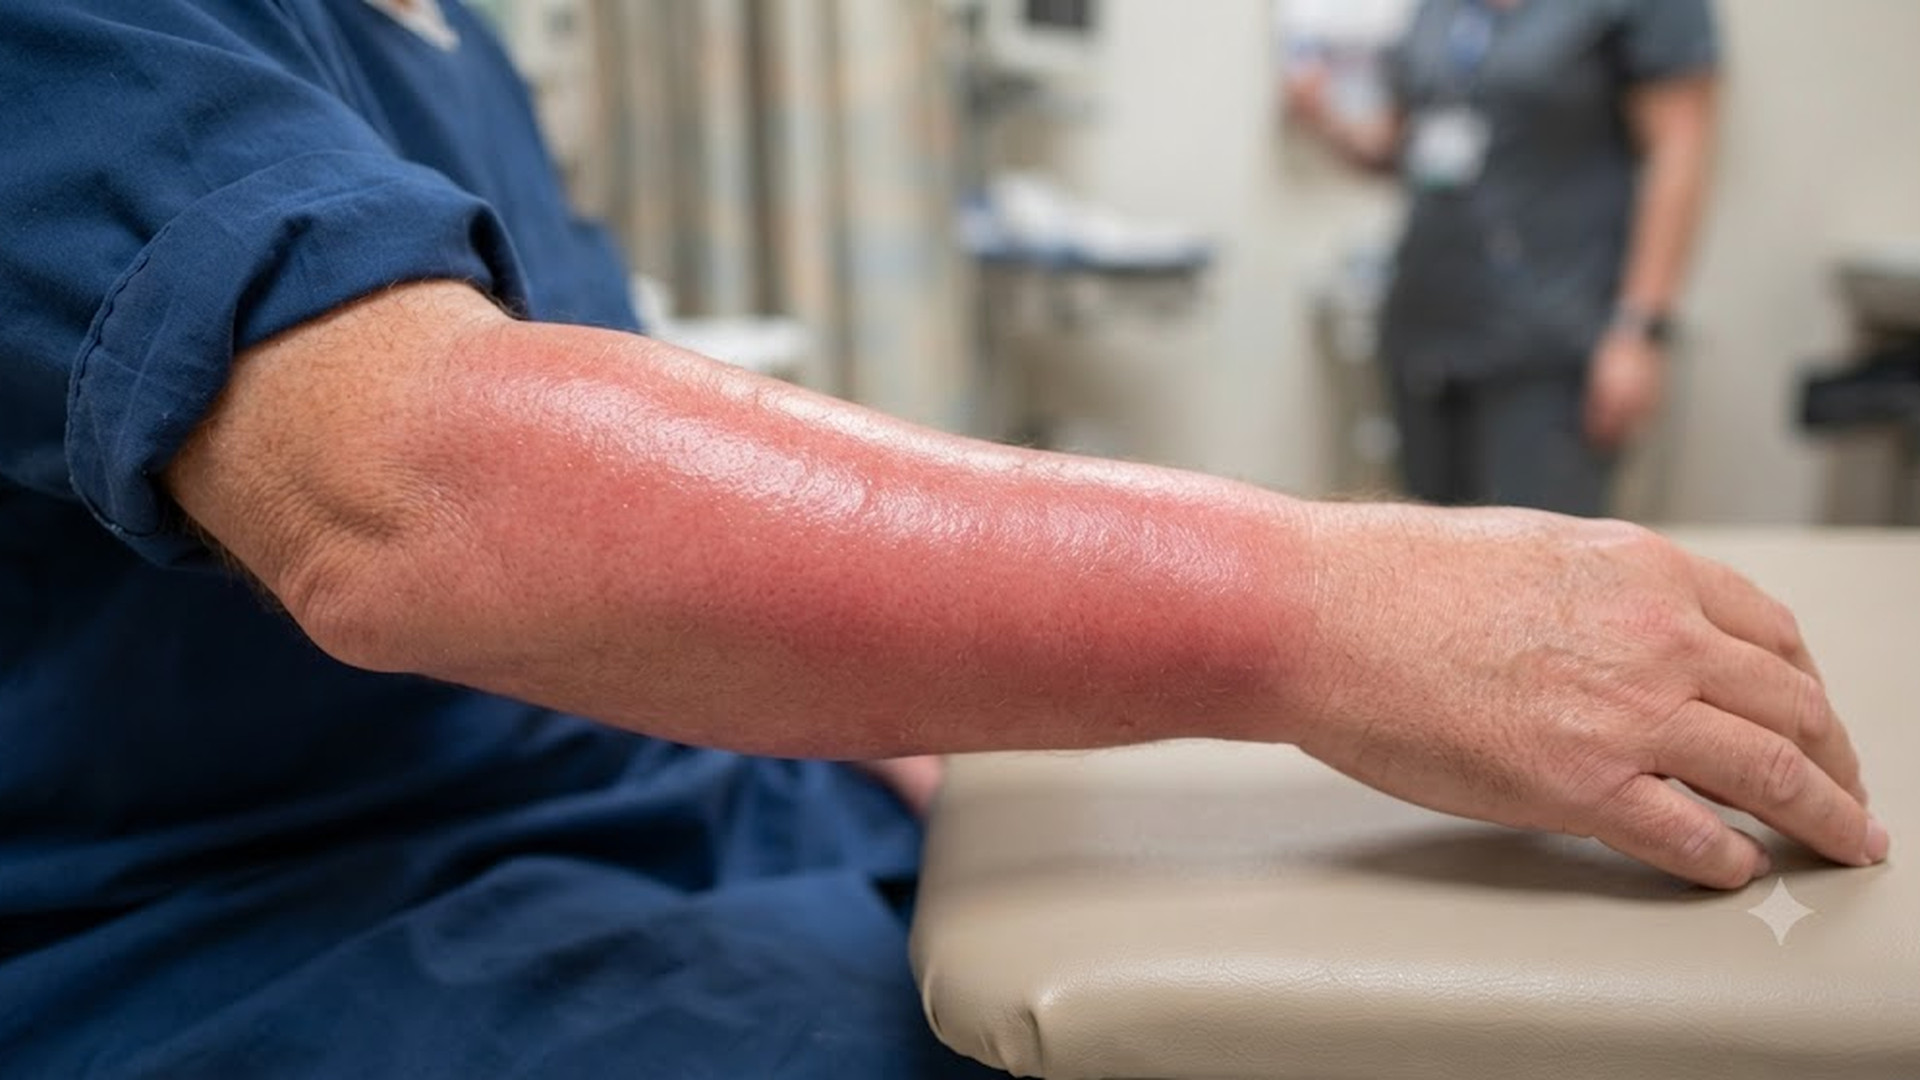
A thickened, cracked nail and the split skin around it give bacteria a way into the leg. The result is a spreading area of hot, swollen, tender skin, usually with feeling unwell and a fever, and it needs antibiotics quickly. It matters most for people with diabetes, poor circulation in the legs or a weakened immune system, which is why fungal nails are treated more actively in those situations.
Common questions