Terbinafine
An oral antifungal tablet for stubborn fungal infections of the nails, scalp and skin. It is the first choice for nail fungus, and it needs a liver check before starting.

Key facts
Terbinafine at a glance.
Used for
Nail fungus; topical forms treat skin
Results
Toenail growth: 9–12 months
Treatment commitment
Nail tablets: usually 6–12 weeks
Key precautions
Tablets require liver assessment
What is it?
Top things to know about Terbinafine
- It is an antifungal. Terbinafine blocks fungal ergosterol production.
- It works best on dermatophytes. It is not right for every yeast infection.
- Nail infection needs confirmation. The tablet label calls for lab testing before treatment.
- Creams do not reach nails. Topical forms cannot replace tablets for nail infection.
Often used for
What Terbinafine is used for
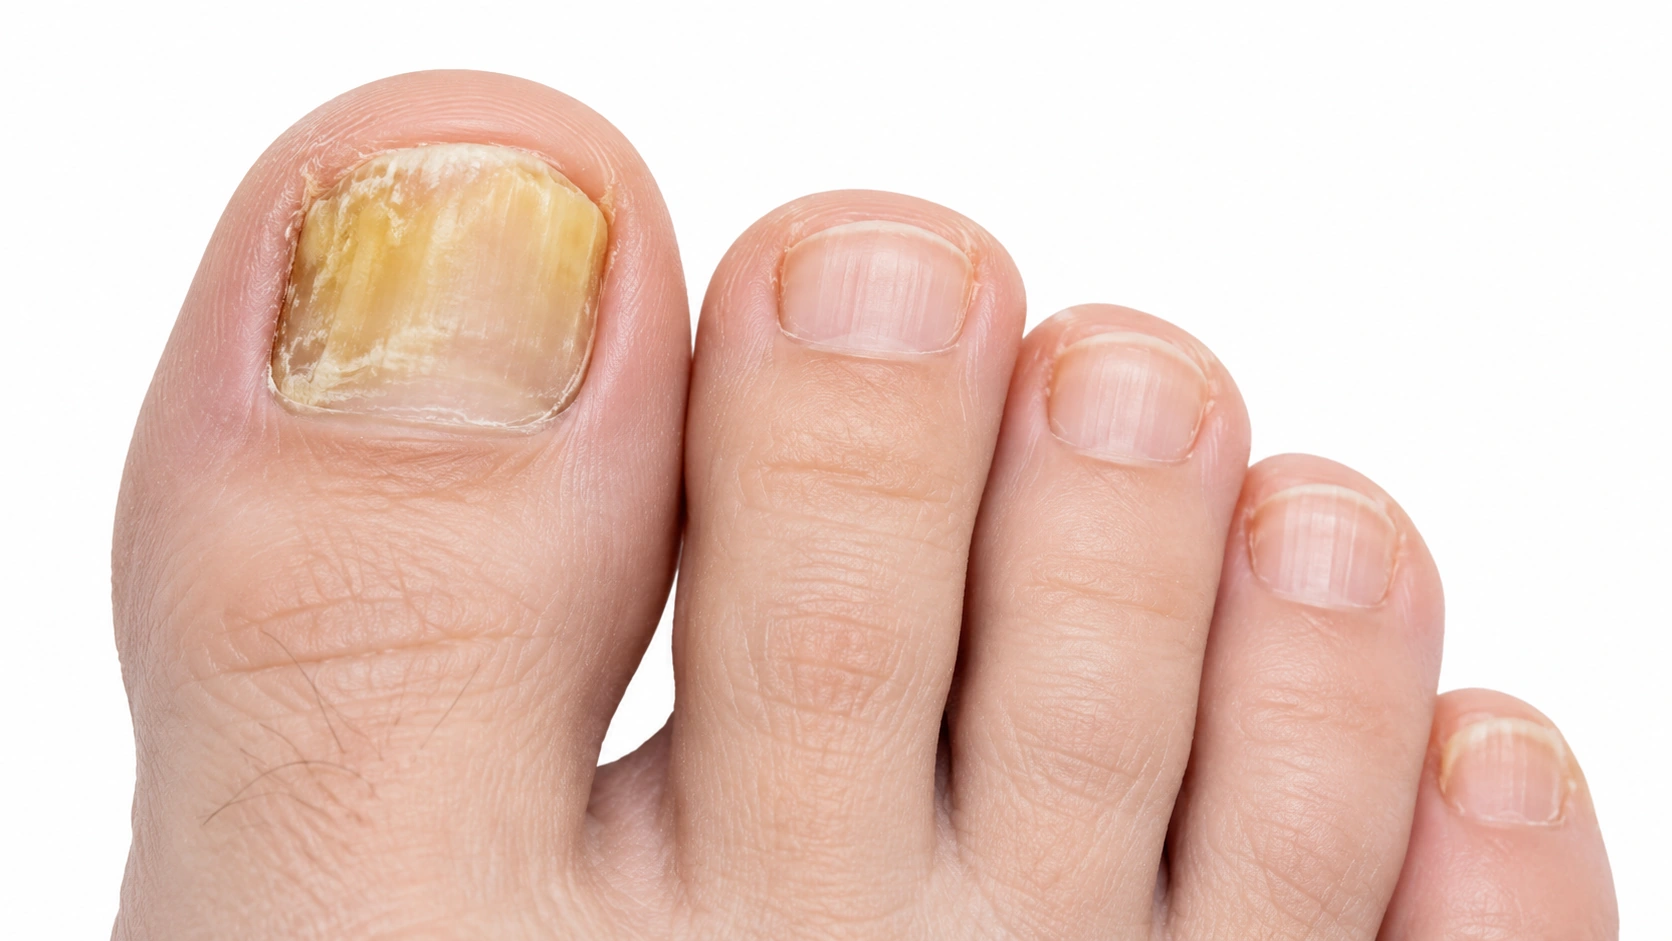
Nail Fungus
The most effective tablet for toenails.
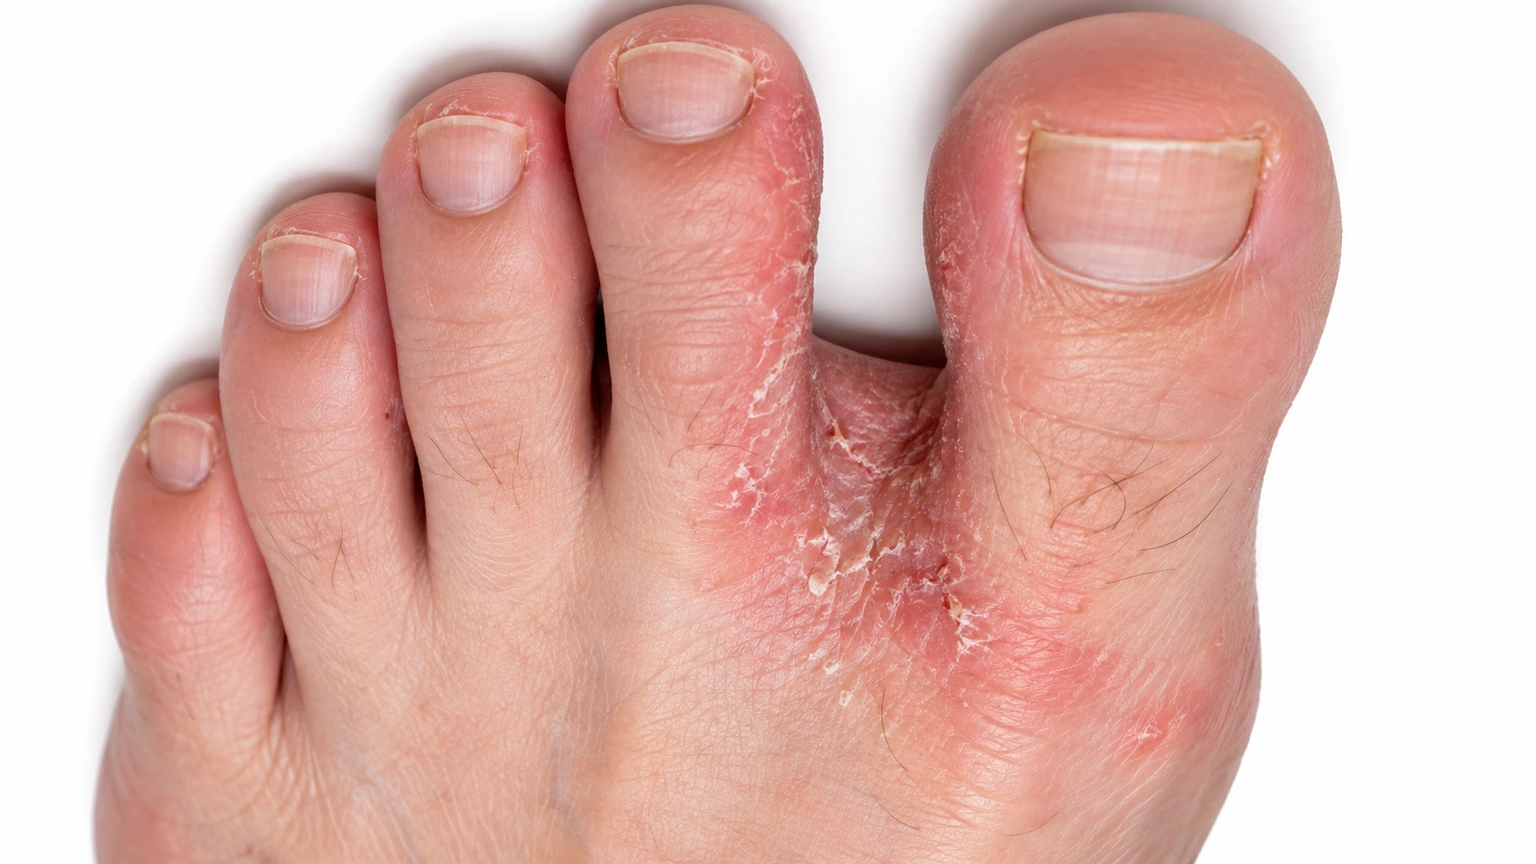
Athlete’s Foot
Creams clear most cases in 1–2 weeks.
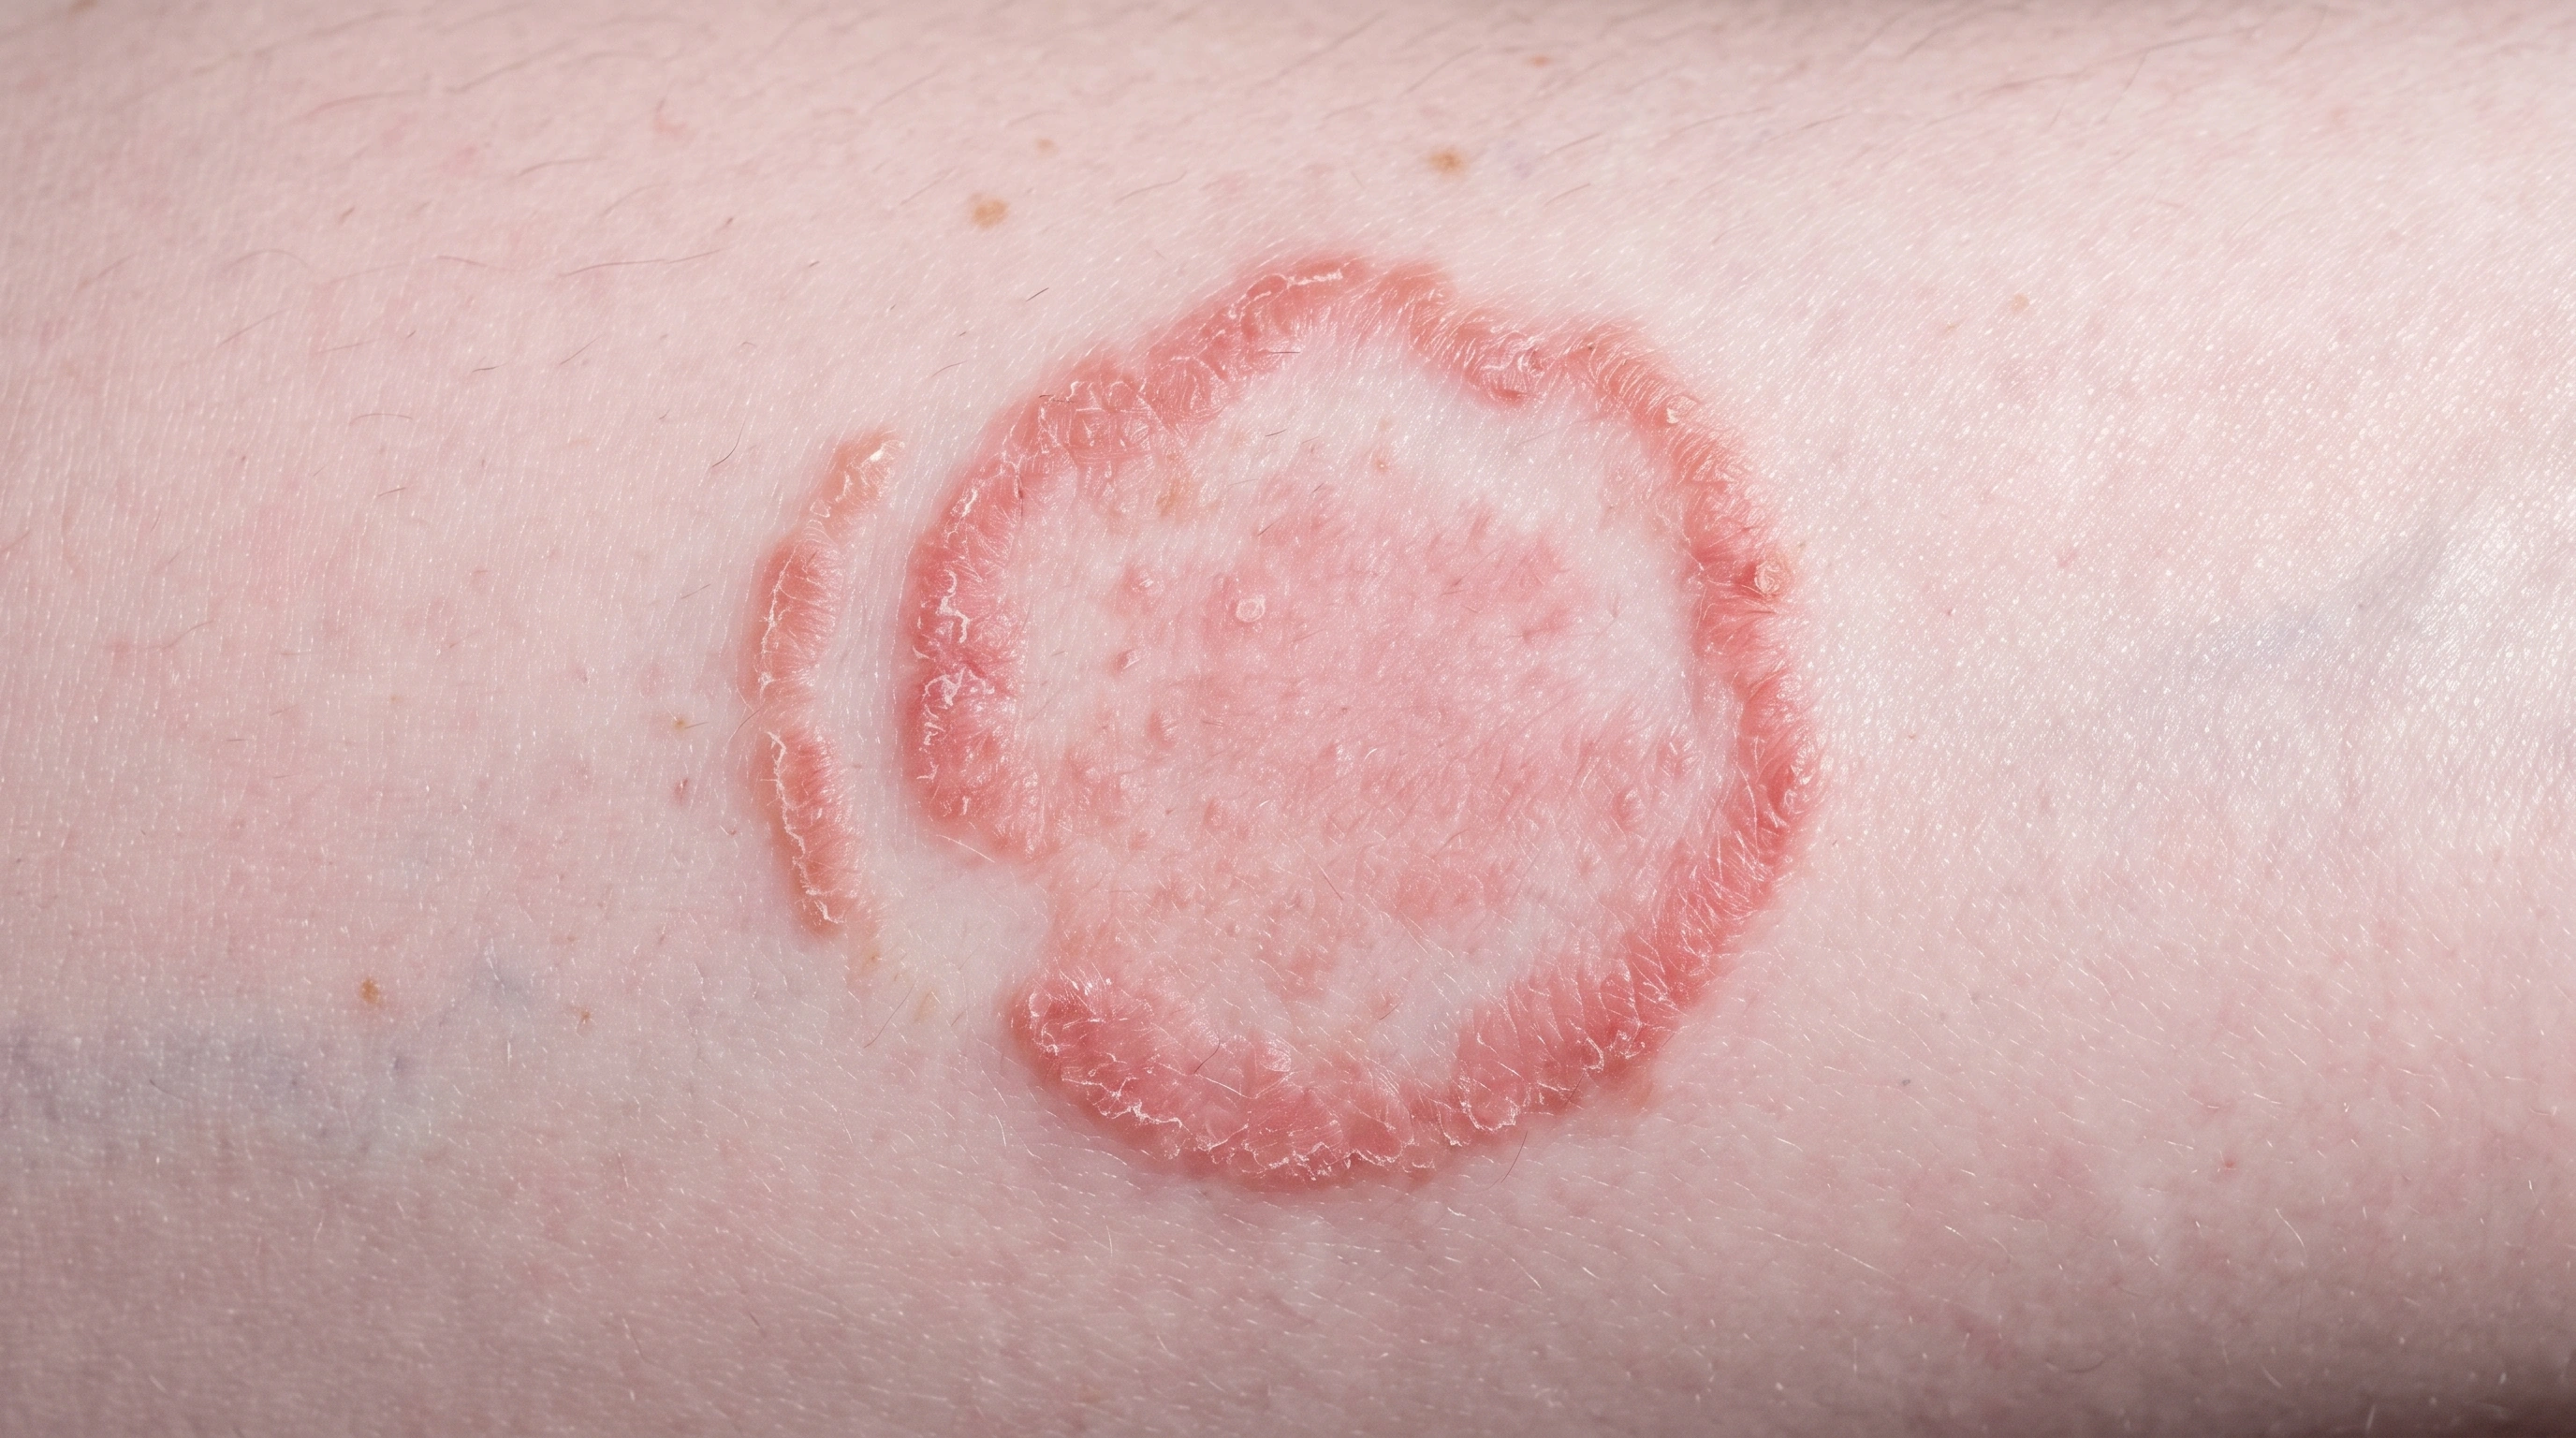
Ringworm
Creams or tablets clear the rash.
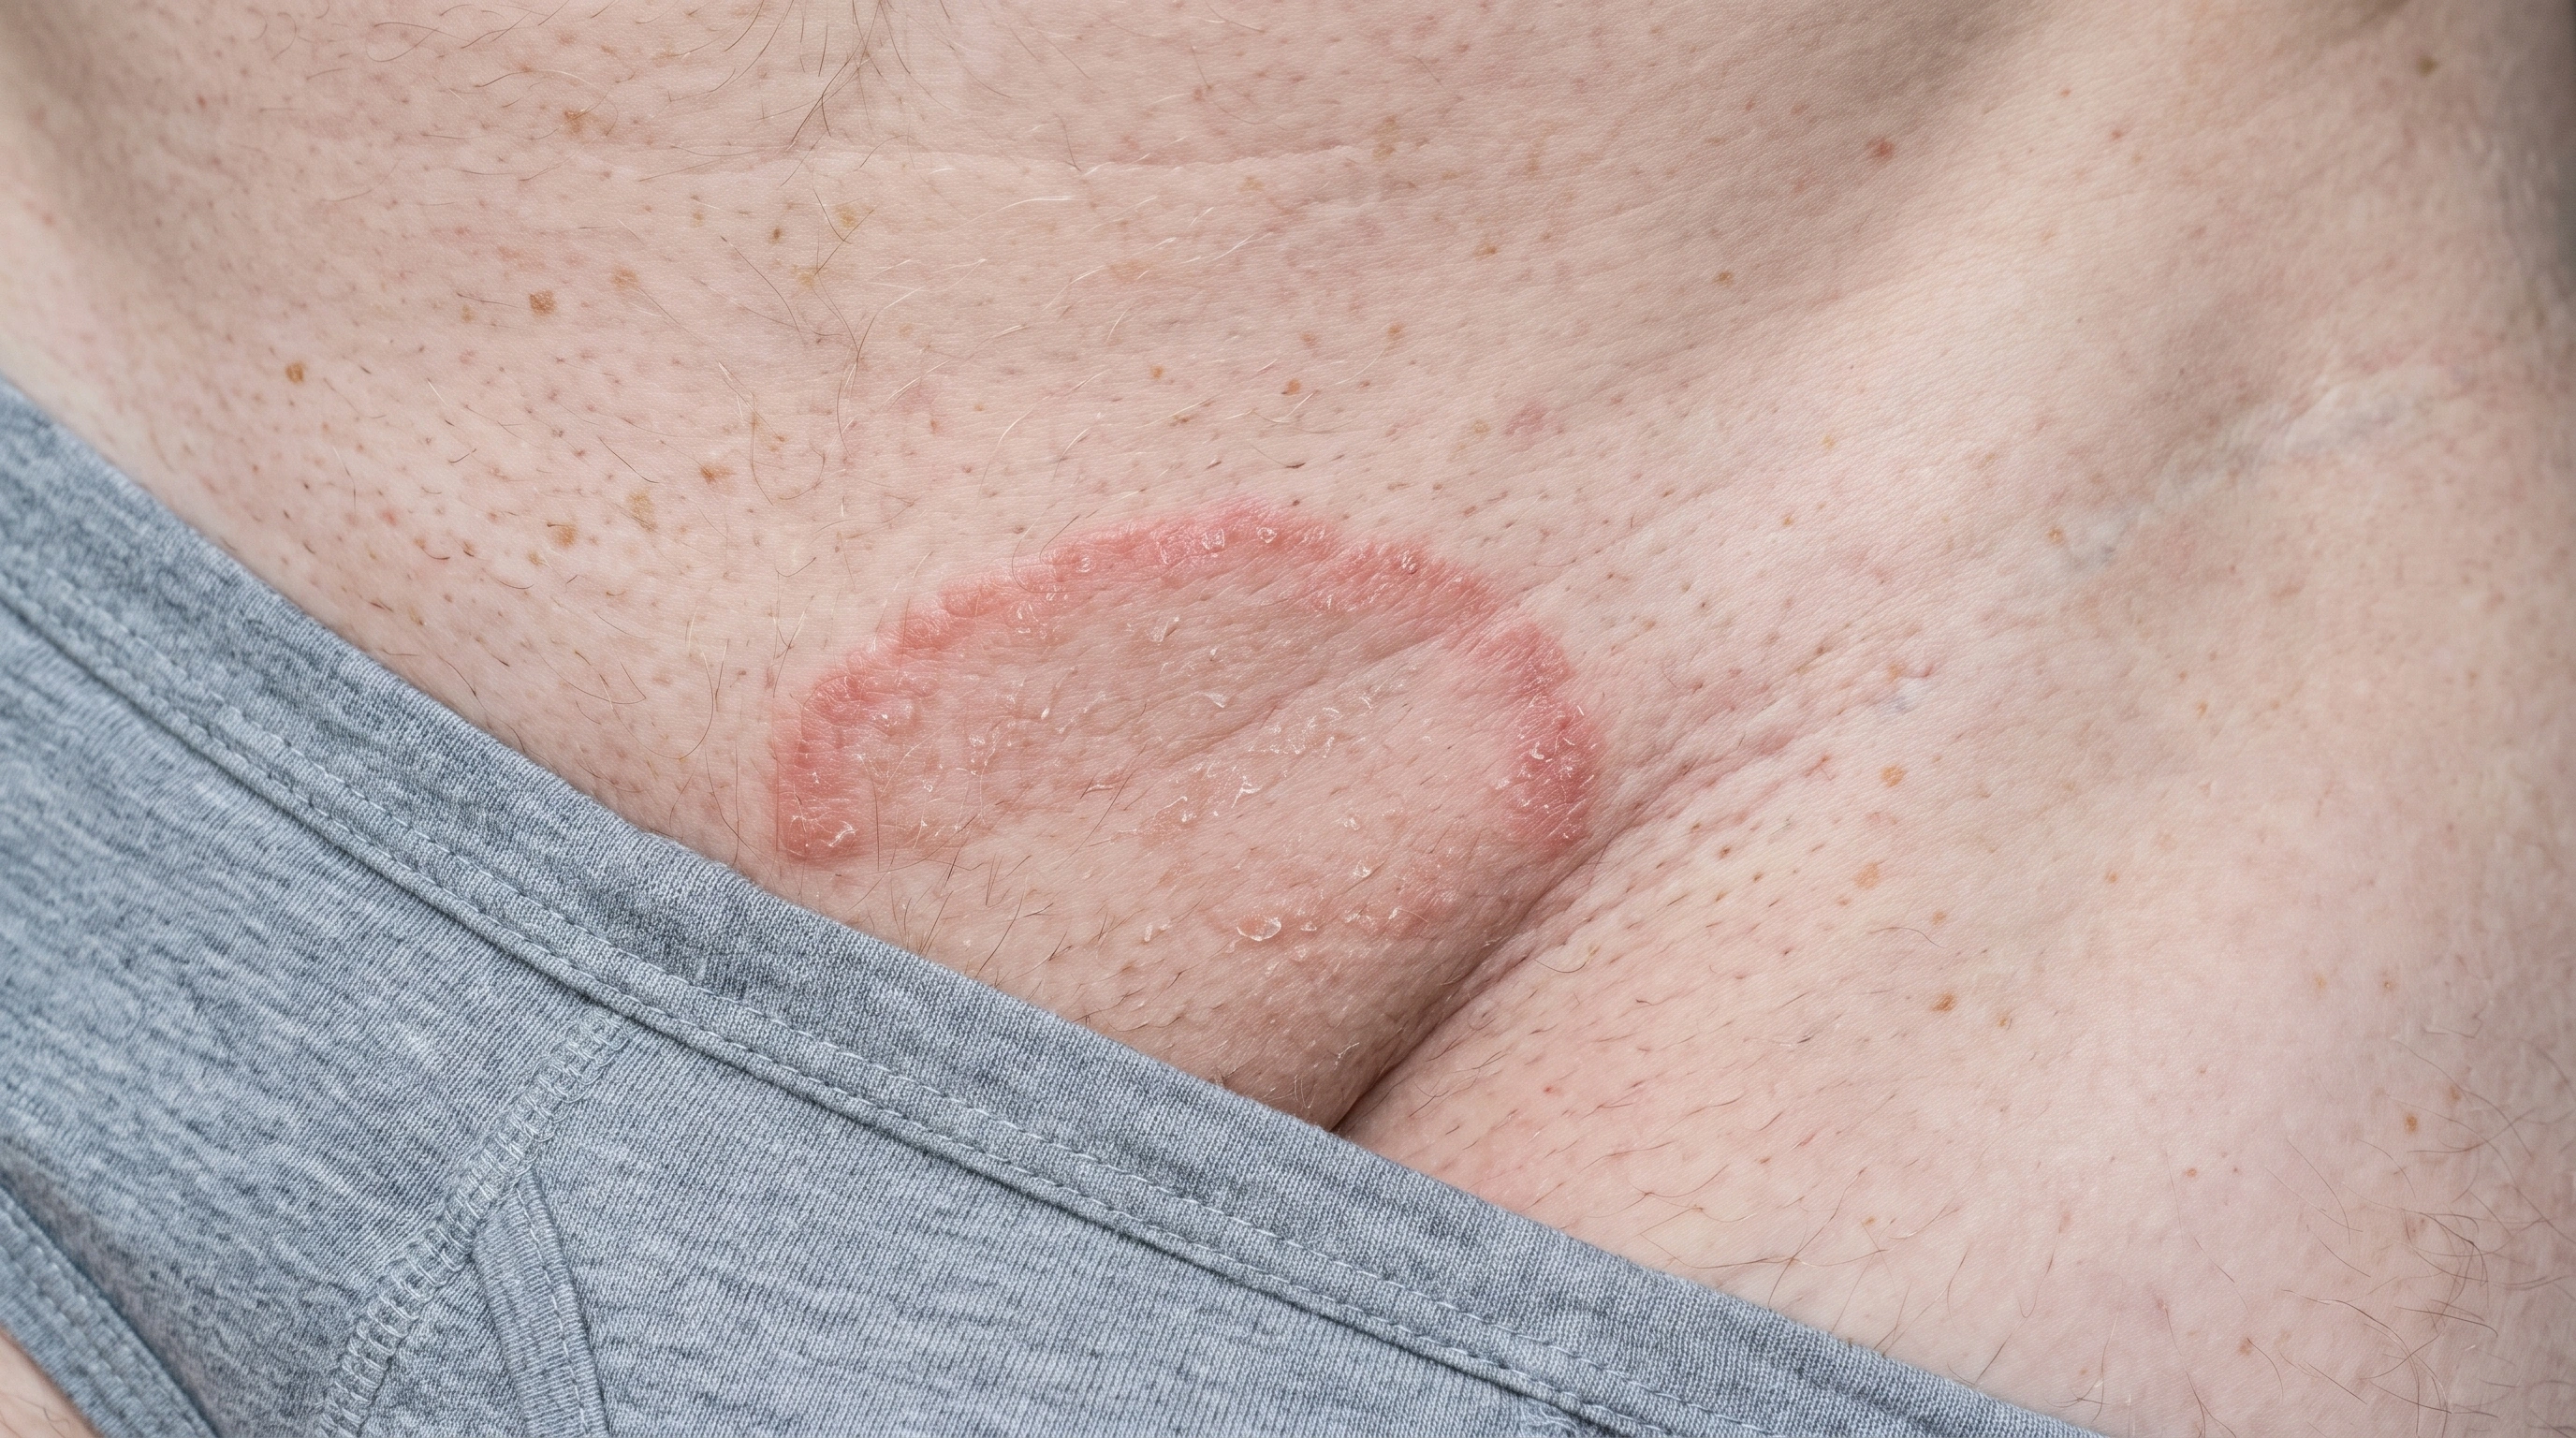
Jock Itch
Creams clear most cases.
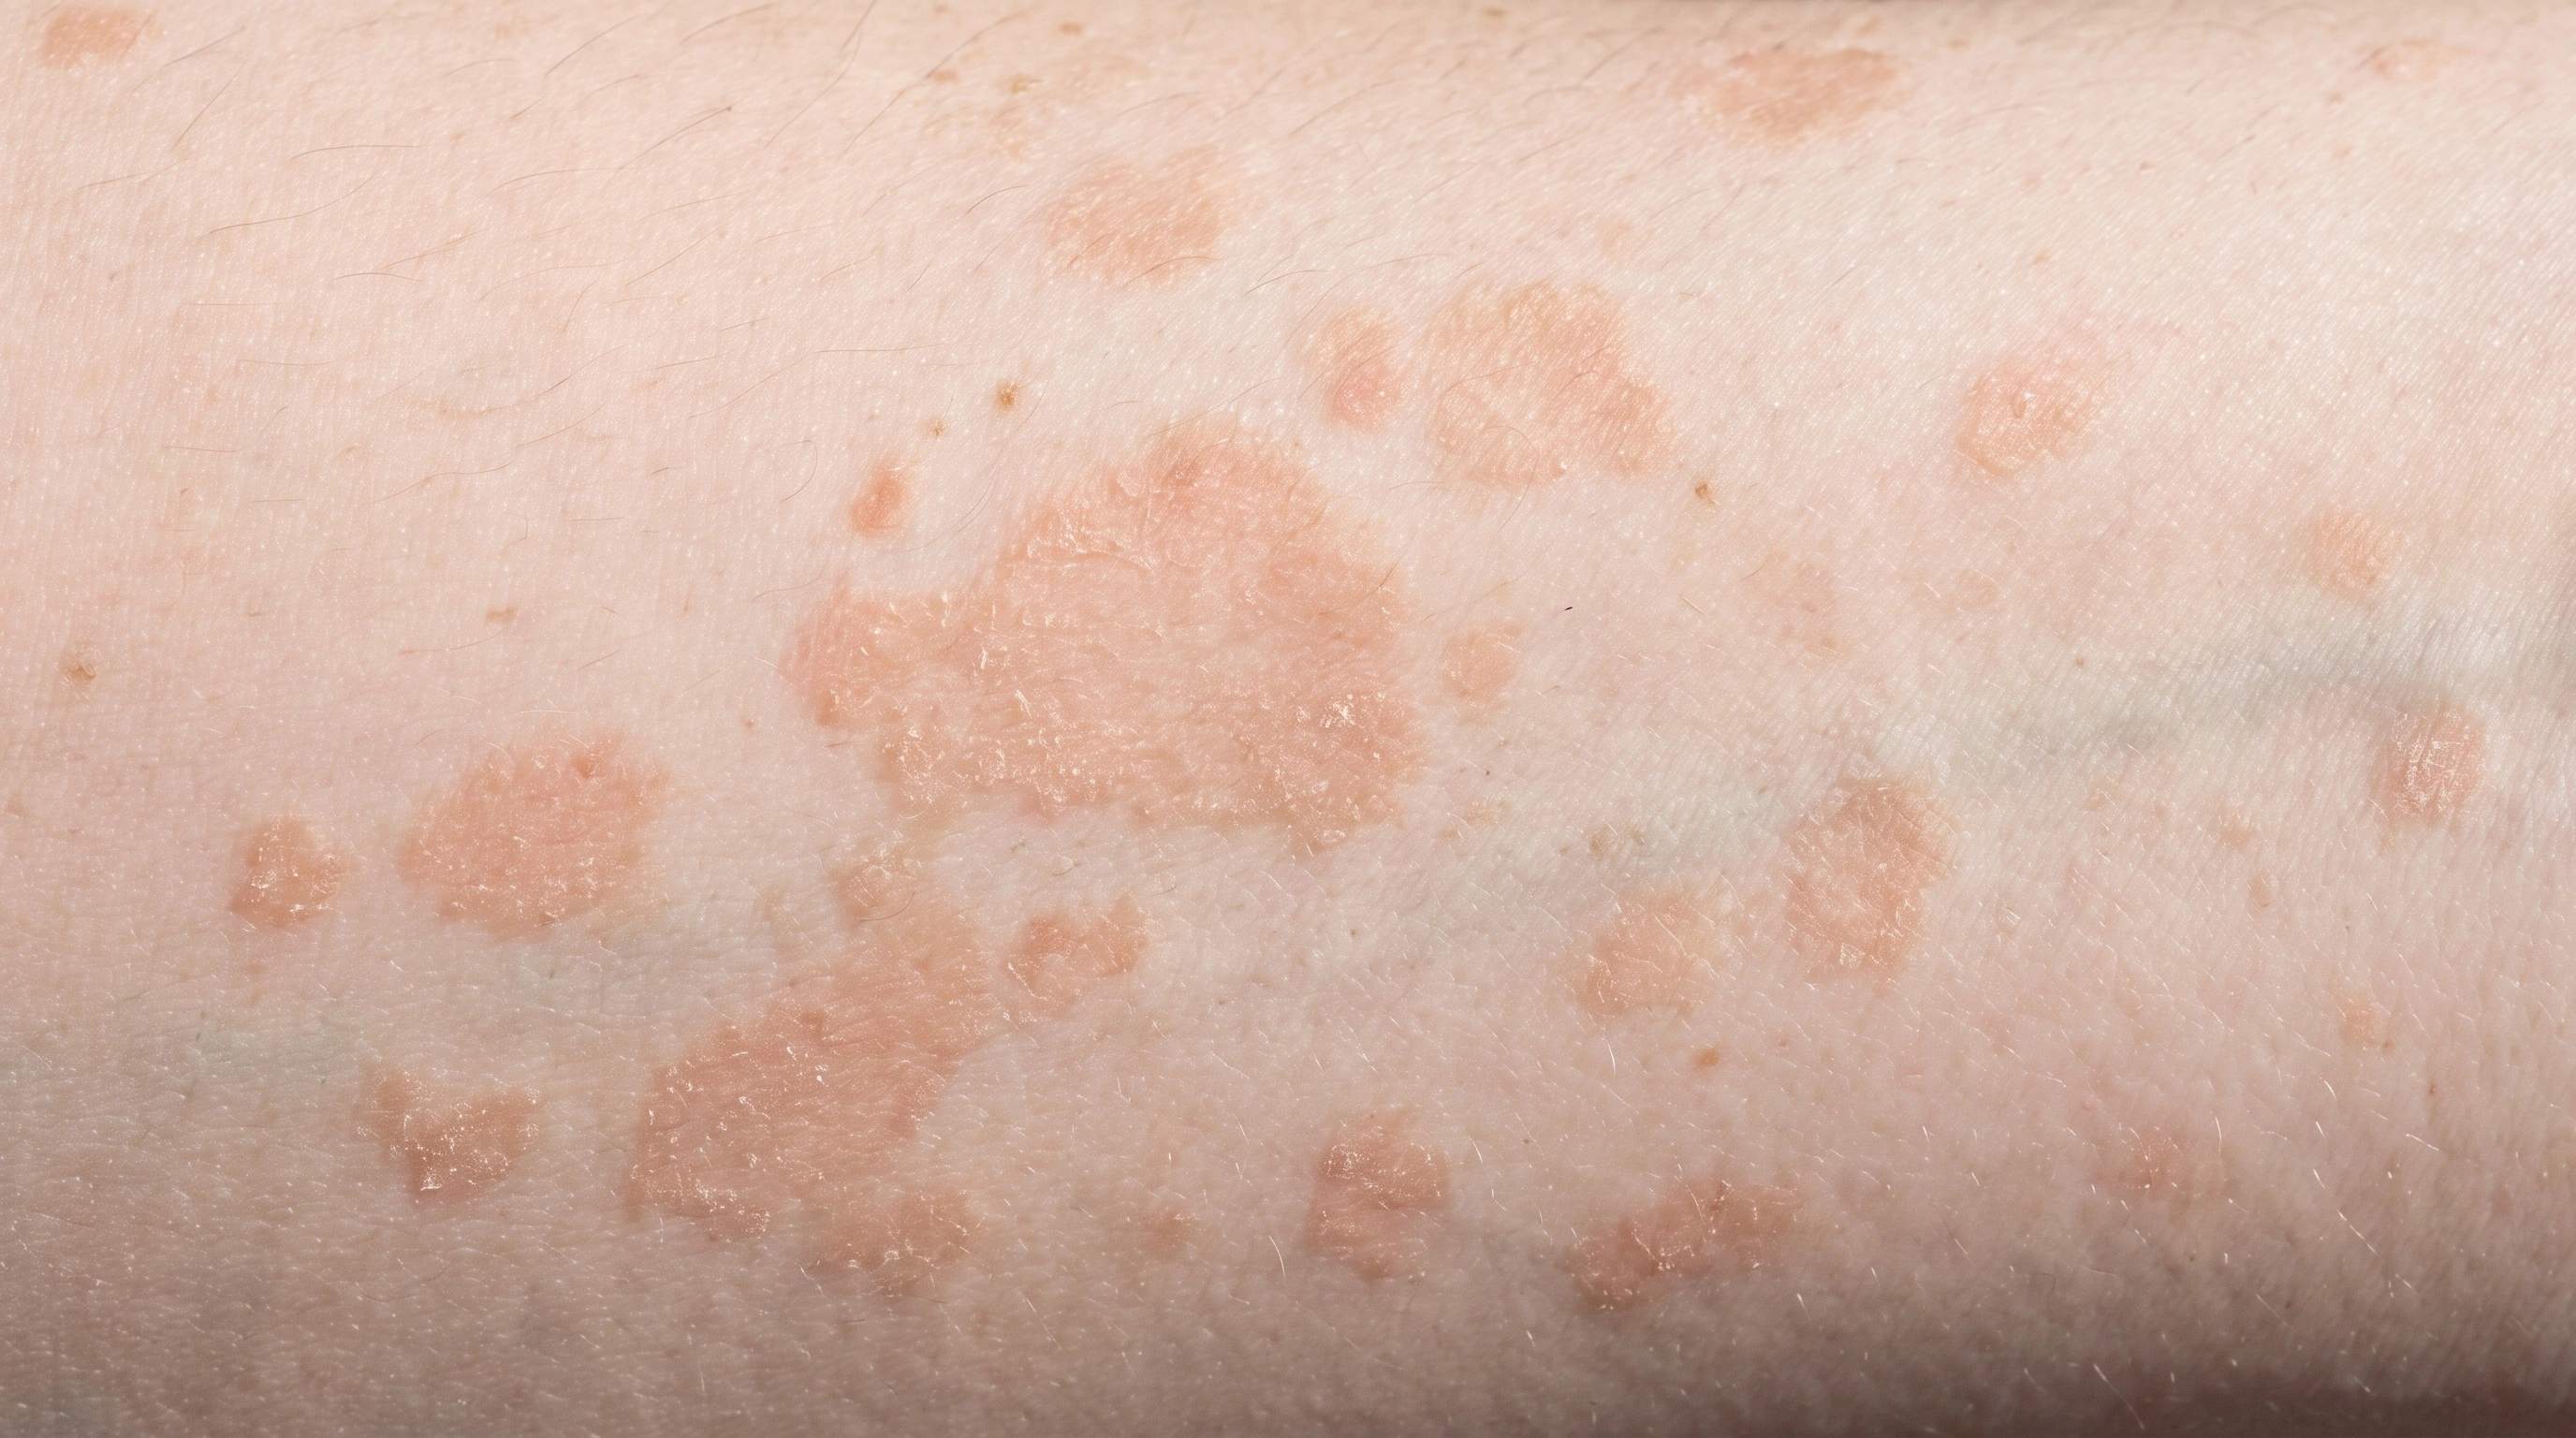
Tinea Versicolor
Tablets don't work for this yeast.
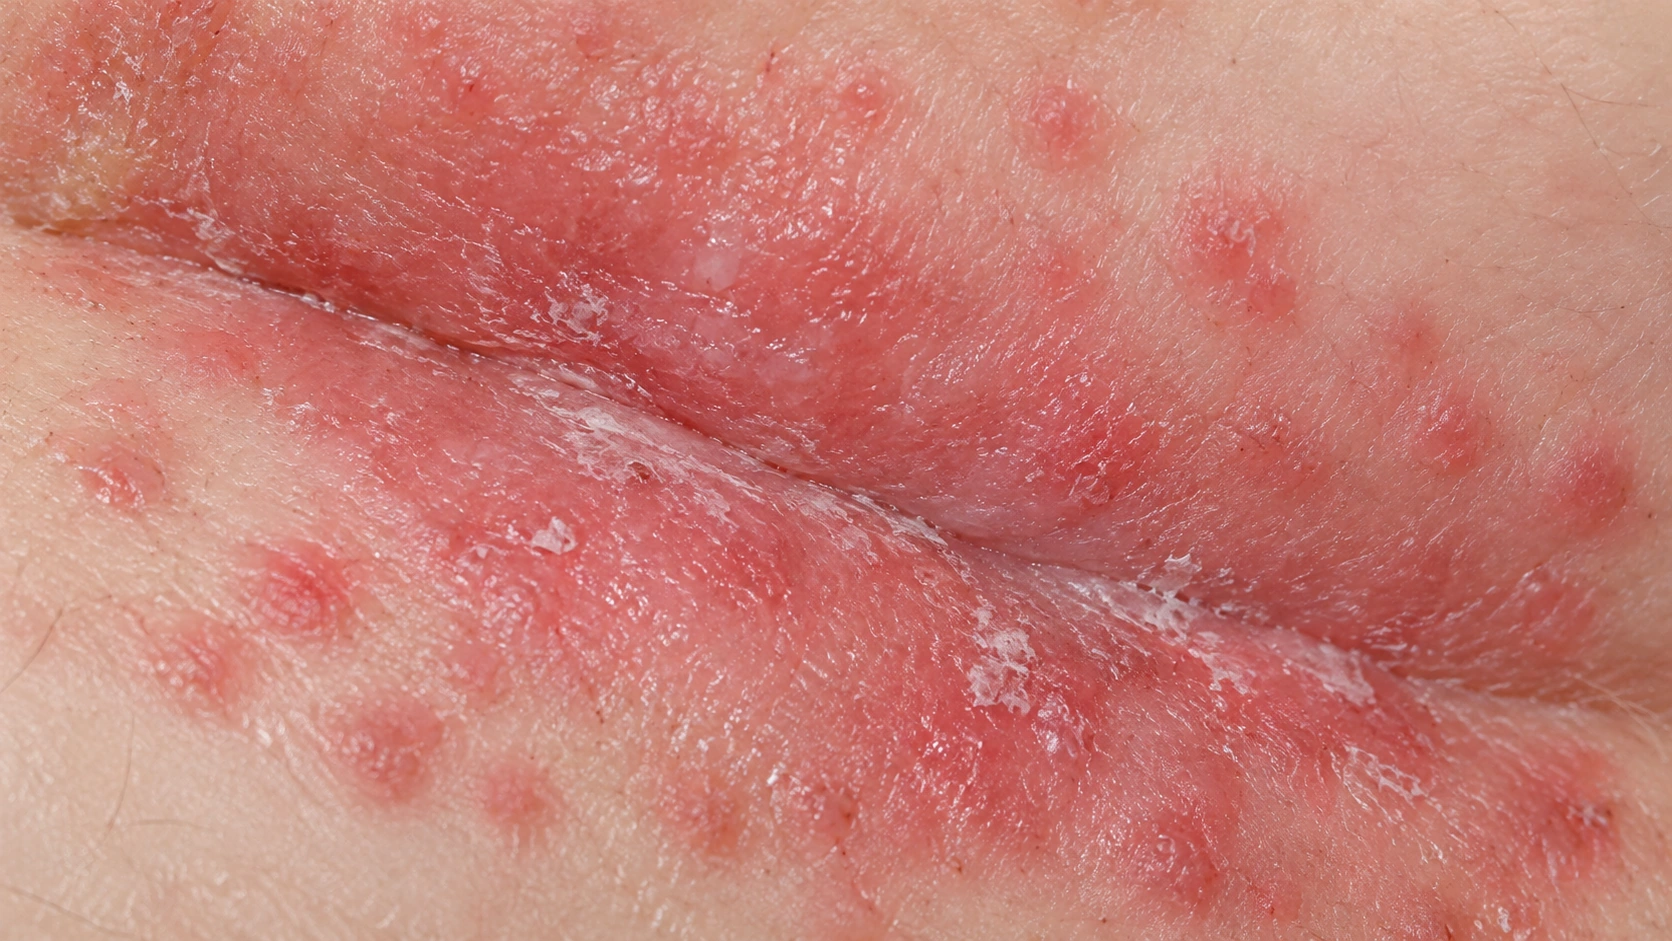
Vaginal Yeast Infection
Doesn't treat Candida well.
HOW IT WORKS
How Terbinafine works
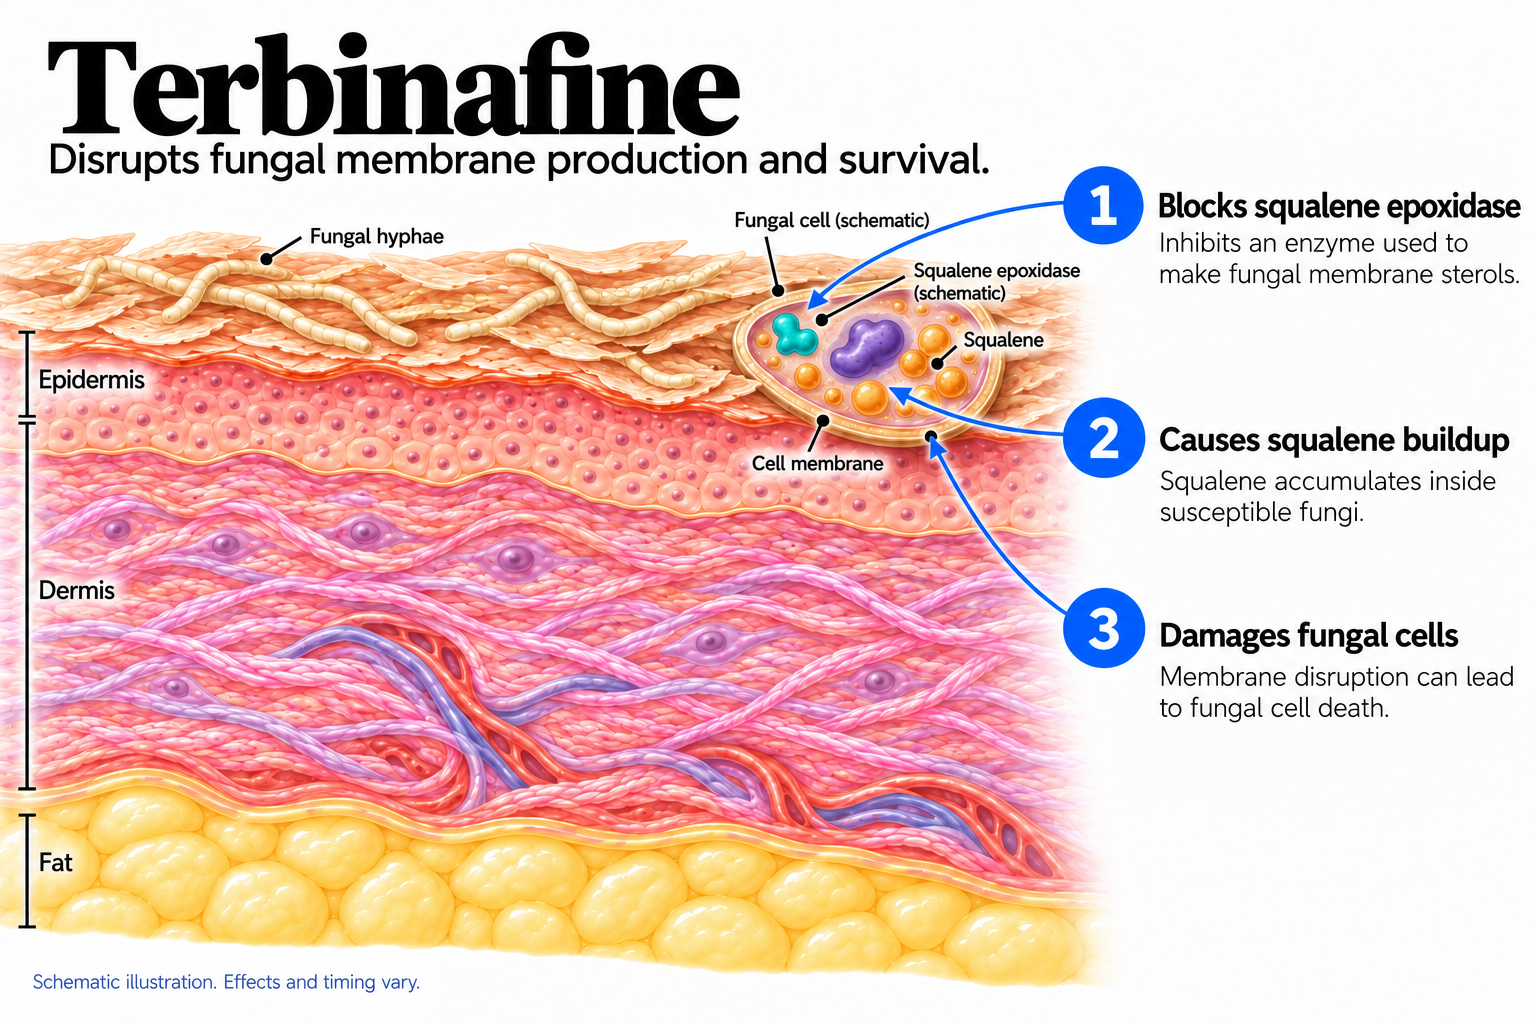
Diagram explanation and sources
Blocks squalene epoxidase: Inhibits an enzyme used to make fungal membrane sterols. Causes squalene buildup: Squalene accumulates inside susceptible fungi. Damages fungal cells: Membrane disruption can lead to fungal cell death.
Squalene-epoxidase inhibition both reduces ergosterol synthesis and increases squalene accumulation. The latter is an important contributor to membrane permeability and fungal death. The image is a skin mechanism, not a nail-treatment timeline.
Strengths
Terbinafine strengths
Terbinafine tablets and skin products are different treatments: the oral tablet commonly contains 250 mg, while topical creams commonly contain 1%. The tablet label treats confirmed dermatophyte nail fungus; a skin cream is not an equivalent treatment for an infected nail.
250 mg
The cited adult regimen is once daily for six weeks for fingernails or twelve weeks for toenails. Diagnosis, liver assessment and interactions require prescribing review.
Forms
Terbinafine forms

Tablet
A solid oral form. Size, coating and ease of swallowing vary by product.

Cream
Richer and more moisturizing; often suits dry skin. The full formula still affects comfort.

Spray
A liquid applied as droplets or mist, useful through hair or over larger areas. Some solvent-based formulas can sting or feel drying.
How to use it
Your treatment, step by step.
How to take it
- 01
When to take it
Once a day, at whatever time you will remember. Food does not matter, though it may reduce nausea. Pick a time you can repeat — for nails this is a daily tablet for three months, and missed days are why a course underperforms.
Alcohol is not a direct interaction, but the liver processes terbinafine, so avoid heavy drinking during a course. - 02
If you miss a dose
Take it when you remember, unless the next one is nearly due. Never double up. An occasional missed day will not undo the course; missing whole weeks will.
Monitoring & follow-up
A liver blood test before starting is standard, and this drug is not used in active or chronic liver disease. Many doctors repeat liver tests at about four to six weeks on a nail course.
Serious liver injury is very rare but can be severe, which is the reason for testing. The warning signs are yellowing of the eyes or skin, dark urine, pale stools, persistent nausea, right-sided upper abdominal pain, or unusual tiredness. Any of those means stop the tablet and call your doctor the same day.
Terbinafine also blocks the liver enzyme CYP2D6, which matters for a specific set of medicines — tricyclic antidepressants, some SSRIs, some beta blockers, some heart-rhythm drugs and tamoxifen. Give a full medicine list before starting.
Rarer problems worth naming: lasting change or loss of taste and smell, a drop in blood cell counts, a lupus-like reaction, and severe skin reactions. A widespread rash, mouth ulcers, blistering or peeling means stop and get seen.
What to expect
How things change over time.
Taking it
One tablet a day, with or without food. Stomach upset, mild nausea or headache shows up in the first fortnight and eases.
Skin clears
Ringworm, jock itch and athlete's foot clear in this range, fast and reliably. Scalp infection calms, with an antifungal shampoo alongside to reduce spread.
The nail course runs
Nails look exactly the same. Normal, not failure. A healthy band may show at the base near the end.
Growing out
Tablets finished, drug still in the nail. A clear line grows down from the cuticle as the damaged part moves to the tip.
Judge it here
A toenail takes this long to replace itself. Most people clear the fungus. Fingernails do better than toenails, younger nails better than older.
- First dose
- Weeks 2 to 4
- Weeks 4 to 12
- Months 3 to 6
- Months 9 to 12
When you stop
No withdrawal, no taper. When the course finishes, you stop.
For nails, stopping is not the end of treatment. Terbinafine stays bound in the nail keratin for months, so the nail carries on clearing after the last tablet. That is the whole design of the short course.
For skin infections, the improvement holds if the conditions that caused it are dealt with — damp feet, shared mats, untreated athlete's foot between the toes. A nail infection that returns is usually reinfection from the surrounding skin rather than a failed tablet.
What it Pairs with
Terbinafine + your routine
| Product or situation | With Terbinafine | What to know |
|---|---|---|
| Stopping early because nothing looks better | Avoid | Nails do not change during the course. Finishing the full 6 or 12 weeks determines the result. |
| Heavy drinking during the course | Use care | Alcohol is not a direct interaction, but the liver clears this drug and heavy drinking adds to the load. |
| Treating a nail without a diagnosis | Avoid | Confirm it is fungus. Roughly half of abnormal-looking nails are damaged, not infected, and a lab clipping avoids three pointless months. |
| Going back into the same shoes | Avoid | Fungal spores survive in footwear. Rotating shoes, drying them, and changing socks daily is part of the treatment. |
| Skipping days | Avoid | A daily tablet for weeks. Gaps are the usual reason a course does not deliver. |
| If you have liver disease, or have had hepatitis | Use care | Not used in active or chronic liver disease. |
| If you take a tricyclic antidepressant, an SSRI, a beta blocker, a heart-rhythm drug or tamoxifen | Use care | It blocks the enzyme clearing several of these; doses may need changing. |
| If you have lupus or a history of a lupus-like drug reaction | Use care | It can trigger or worsen it. |
| If you have kidney disease | Use care | The dose is reduced, or another drug chosen. |
| If you are pregnant or breastfeeding | Use care | Planning counts too. Ask the doctor managing your pregnancy first; nail treatment is rarely urgent. |
| If your taste or smell changes | Use care | Report it, do not push through. |
| If you develop a widespread rash | Use care | Mouth ulcers or blistering too. Be seen the same day. |
Side effects & when to get help
Courses run for months, which is why this is one of the few skin drugs with a blood test attached. Taste changes are the side effect nobody expects.
Common
Stomach upset or diarrhea
Headache
Rash: Usually mild.
Loss of taste, or a metallic taste: Can take weeks to come back after stopping.
Tell your doctor
Taste or smell that has not returned: It usually does, but slowly.
Rising liver enzymes: Checked before and during a long course.
A rash that is spreading
Low mood: Reported, and worth raising.
Any other medicine you take: Terbinafine changes how some antidepressants and beta blockers are cleared.
Stop and get care
Yellowing of the eyes or skin: With dark urine, pale stools or deep tiredness.
A rash that blisters or peels
Fever with a widespread rash and swollen glands
Getting it and cost
Getting Terbinafine.
Cost & access
Generic terbinafine tablets are inexpensive and widely stocked. A twelve-week course is usually one of the cheaper parts of treating nail fungus.
The costs that catch people out are around it rather than in it
the lab clipping and the blood test before starting both carry their own charges, and some insurers will not cover nail treatment without a positive lab result.
What affects the cost
The children's granules cost considerably more than tablets. Laser and cosmetic nail treatments are not covered and have far weaker evidence.
Alternatives
Other options to consider.

Itraconazole
the main alternative tablet for nails, and stronger against yeasts. Evidence for dermatophyte nail infection favors terbinafine, and itraconazole has more drug interactions and cannot be used in heart failure.

Fluconazole
taken weekly, which some people prefer, but it is not approved for nail infection in the United States and works less well against dermatophytes.

Griseofulvin
an older tablet, mainly kept for scalp ringworm in children, particularly Microsporum infections. Needs a longer course and fatty food to be absorbed.

Topical antifungal creams
Terbinafine, clotrimazole or miconazole are fully effective for ordinary athlete's foot and ringworm on the skin, and the right first step there. Not effective for nails or scalp.

Medicated nail lacquers
Such as ciclopirox, efinaconazole or tavaborole, applied daily for up to a year, with no blood tests and no interactions. Cure rates are lower than with terbinafine, and cost is often much higher.
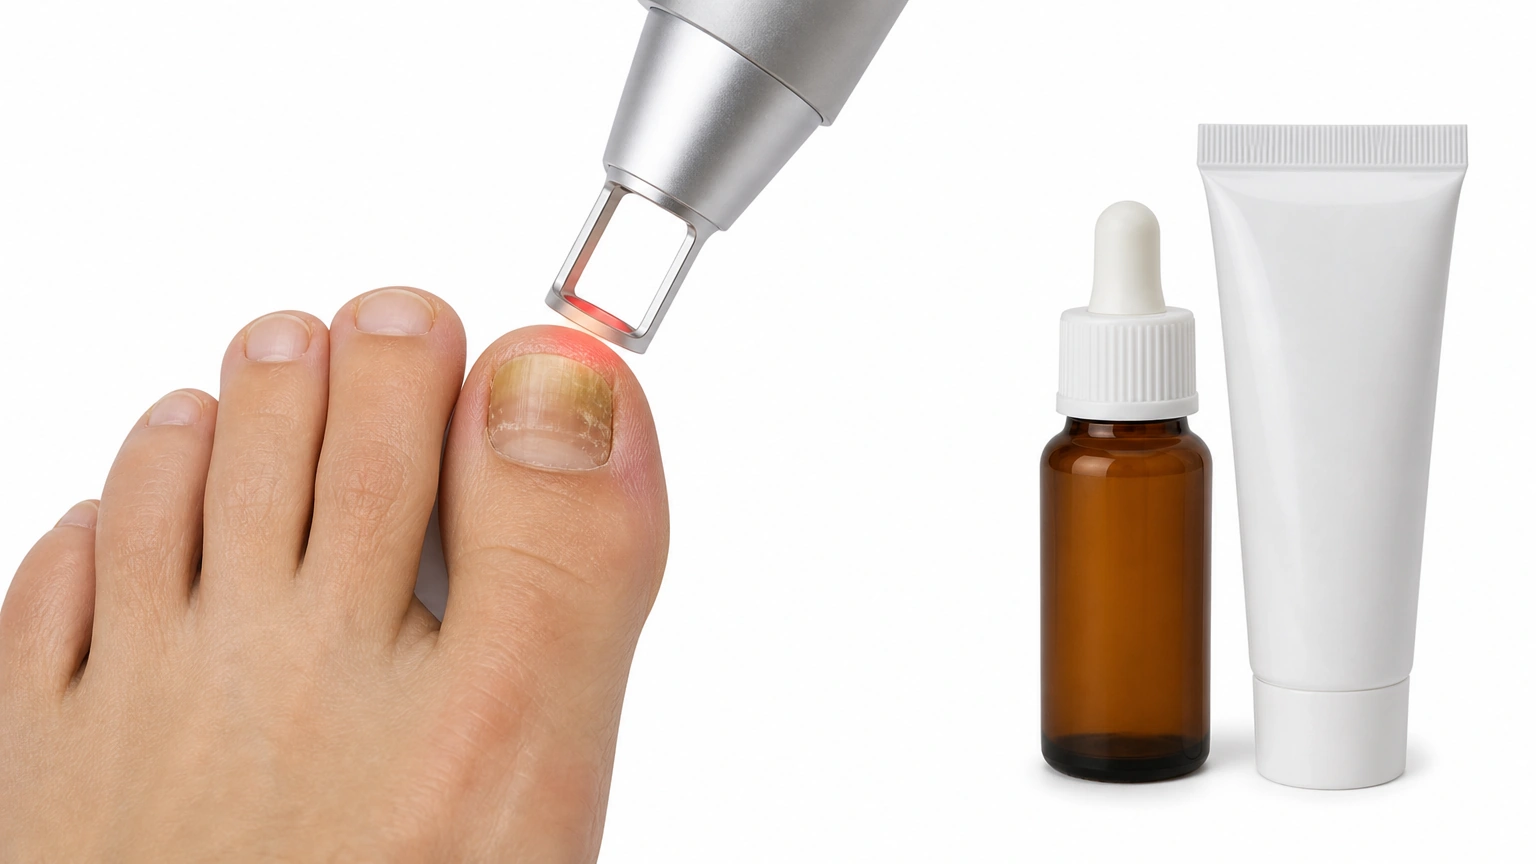
Laser and over-the-counter nail treatments
evidence is weak, and improvement is usually cosmetic rather than curing the infection.
Questions
Questions you might be asking.
How long until my nail looks normal?
Twelve weeks of tablets for toenails, but the nail needs nine to twelve months to grow out. Judge it at a year.
Do I really need a blood test first?
Yes, for a nail course. Serious liver injury is rare but serious, and a baseline test is what makes prescribing reasonable.
Can I drink alcohol on it?
An occasional drink is not dangerous. Avoid heavy drinking, because the liver is clearing the drug.
Will it treat my athlete's foot too?
Yes, and it should. Untreated fungus between the toes is the usual source of reinfection.
Why did my doctor send a nail clipping to the lab?
Because about half of thick, discolored nails are not fungal. Confirming it avoids months of an unnecessary tablet, and many insurers require it.
Can it come back?
Yes. Recurrence over the years is common, especially without attention to shoes, socks and the skin between the toes.
Related
Keep exploring.
Fluconazole
Athlete’s Foot
Jock Itch
Ringworm
Nail Fungus
Tinea Versicolor
Fluconazole vs Terbinafine
Ringworm vs Tinea Versicolor
Seborrheic Dermatitis

Eczema vs Ringworm

Acne vs Fungal Acne