
Guttate Psoriasis vs Tinea Versicolor

A sudden crop of small drop-like psoriasis spots, often after a throat infection. Tinea versicolor is a common, harmless rash caused by a yeast that already lives on everyone's skin. It leaves flat, finely scaly patches on the chest, back and shoulders that are lighter, darker or pinker than the skin around them. Treatment clears it quickly, the color takes months to even out, and it often returns in warm weather.

Research updated 2026-10-23
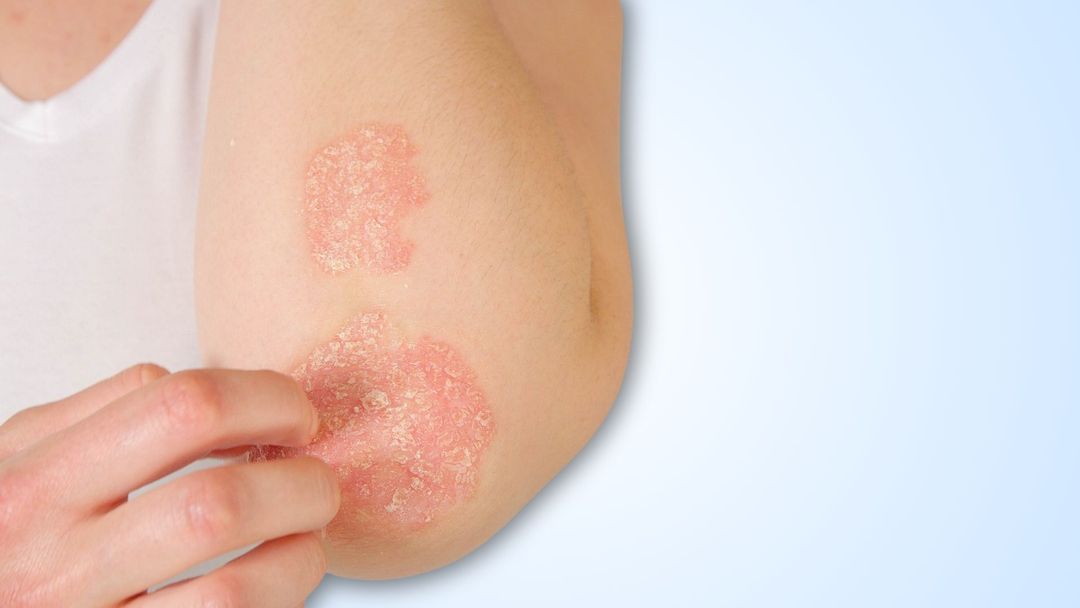
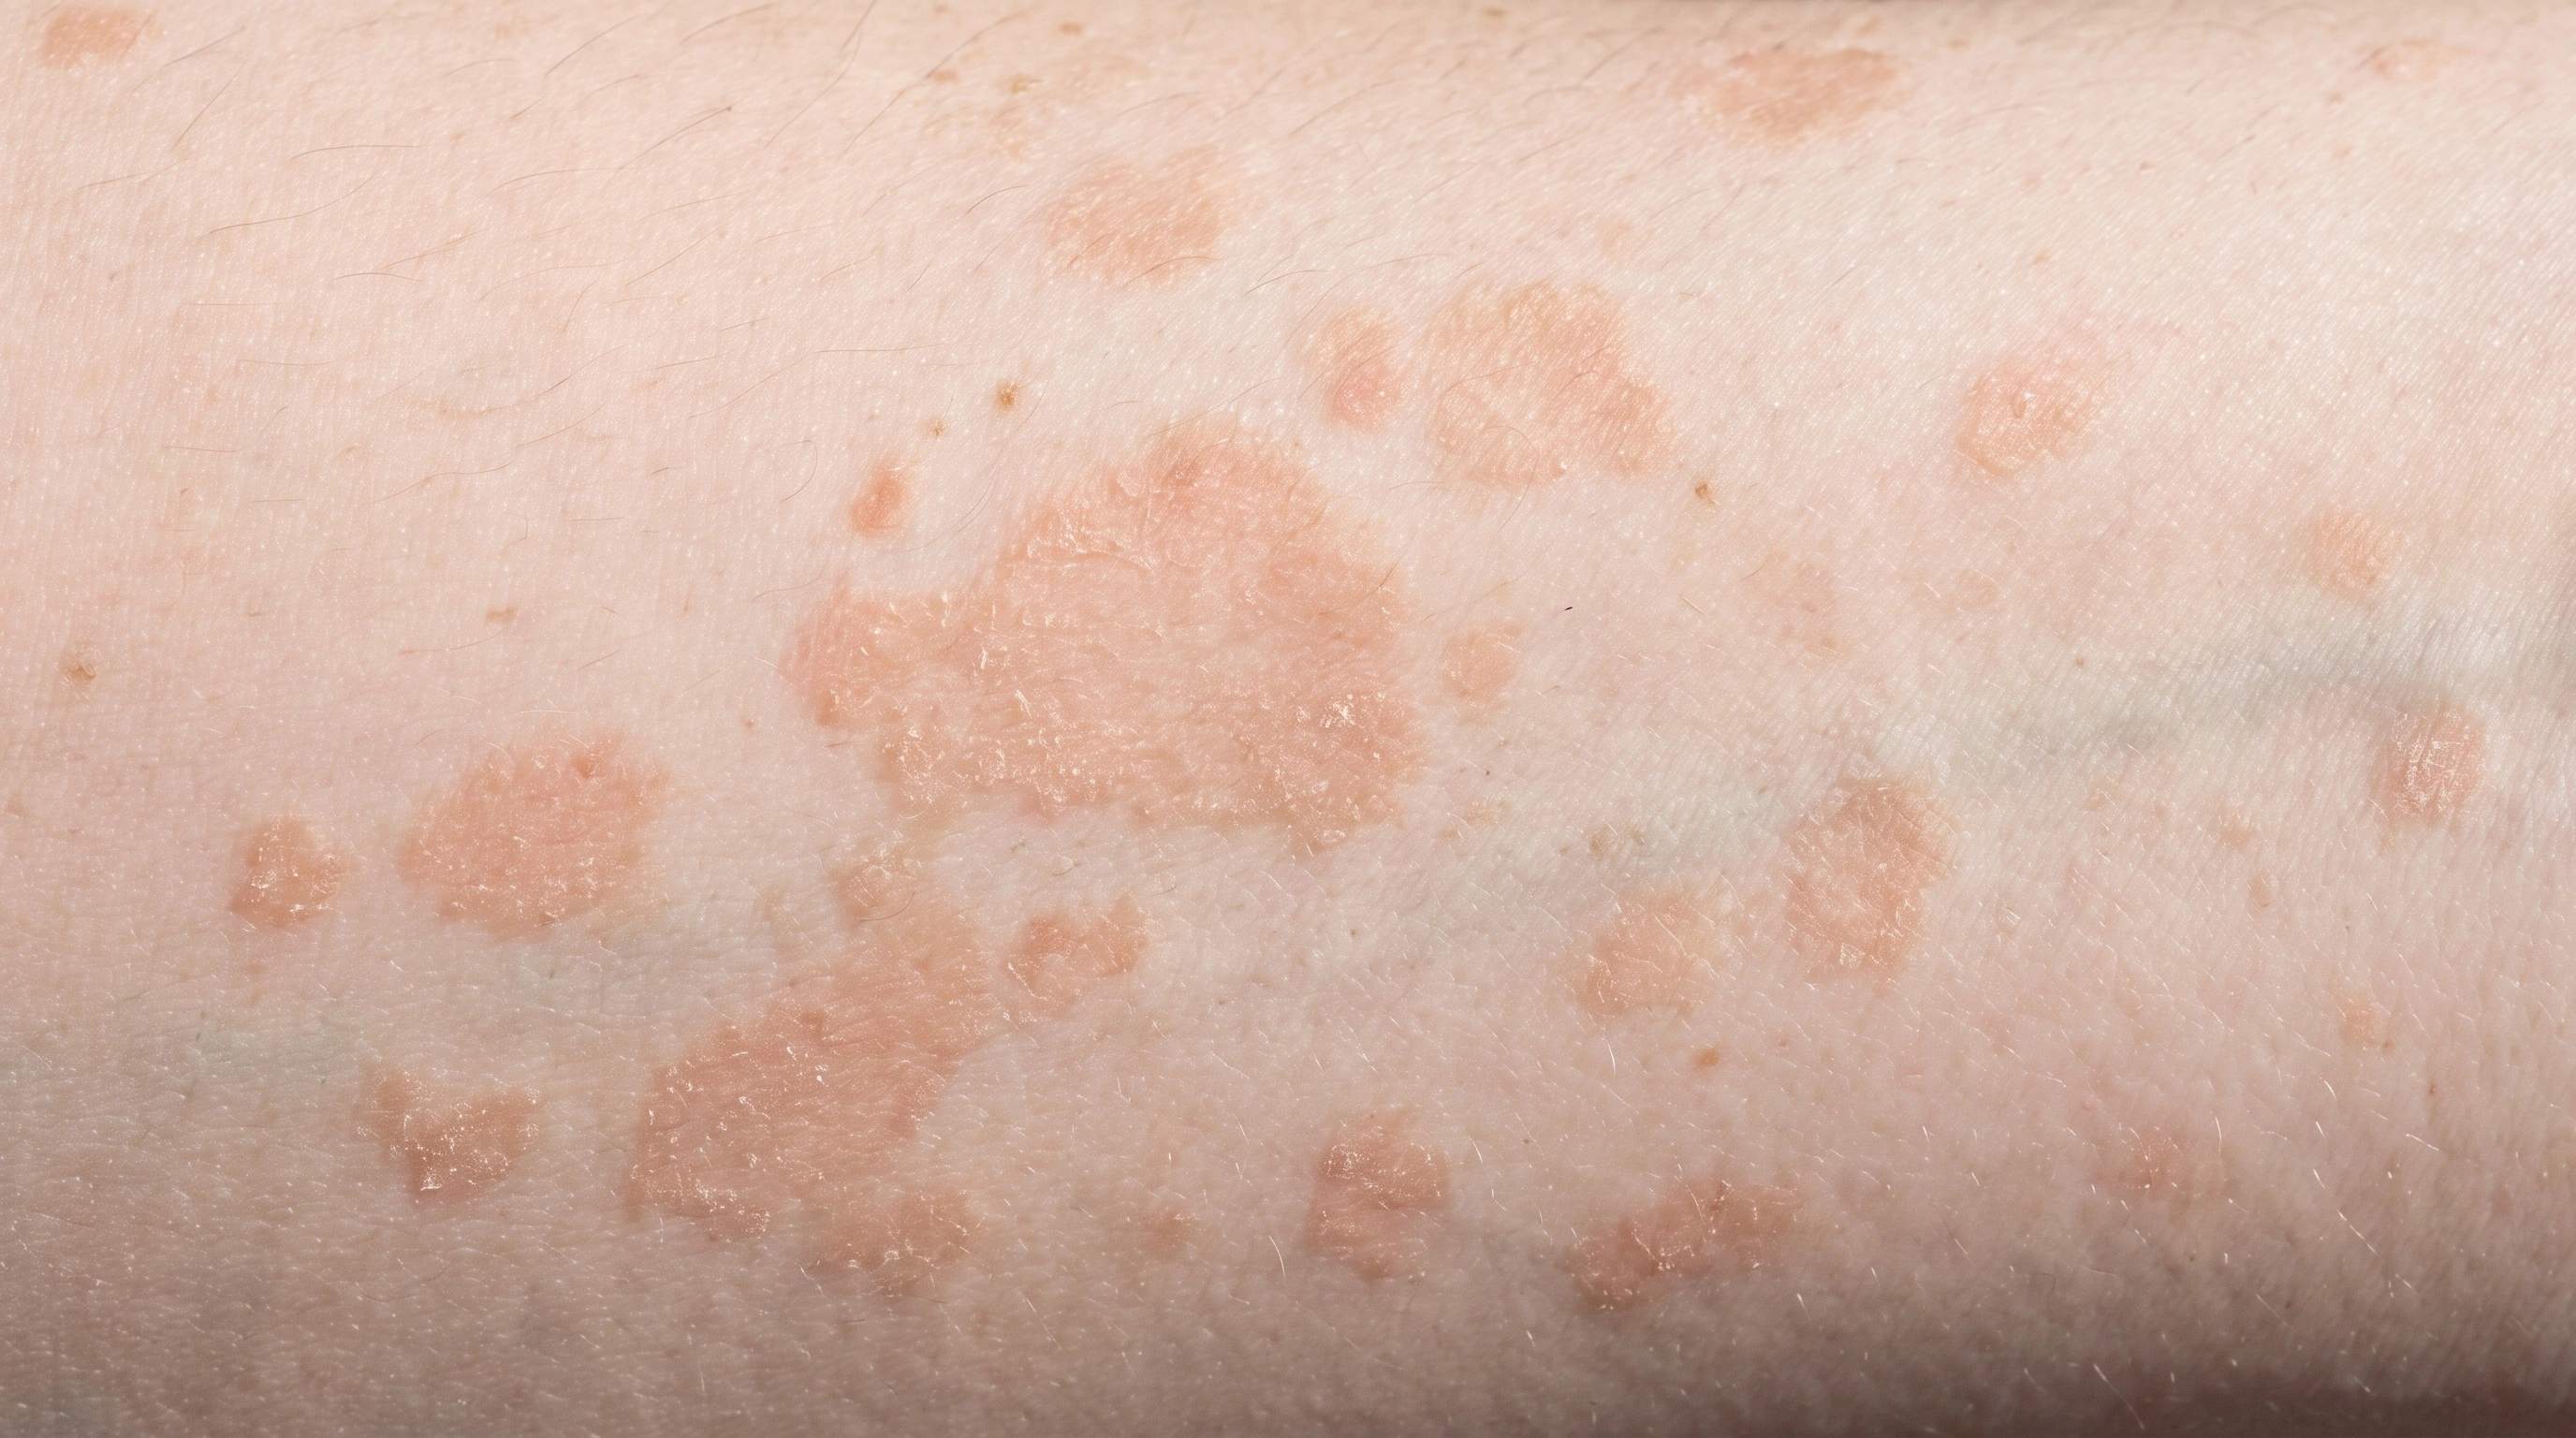
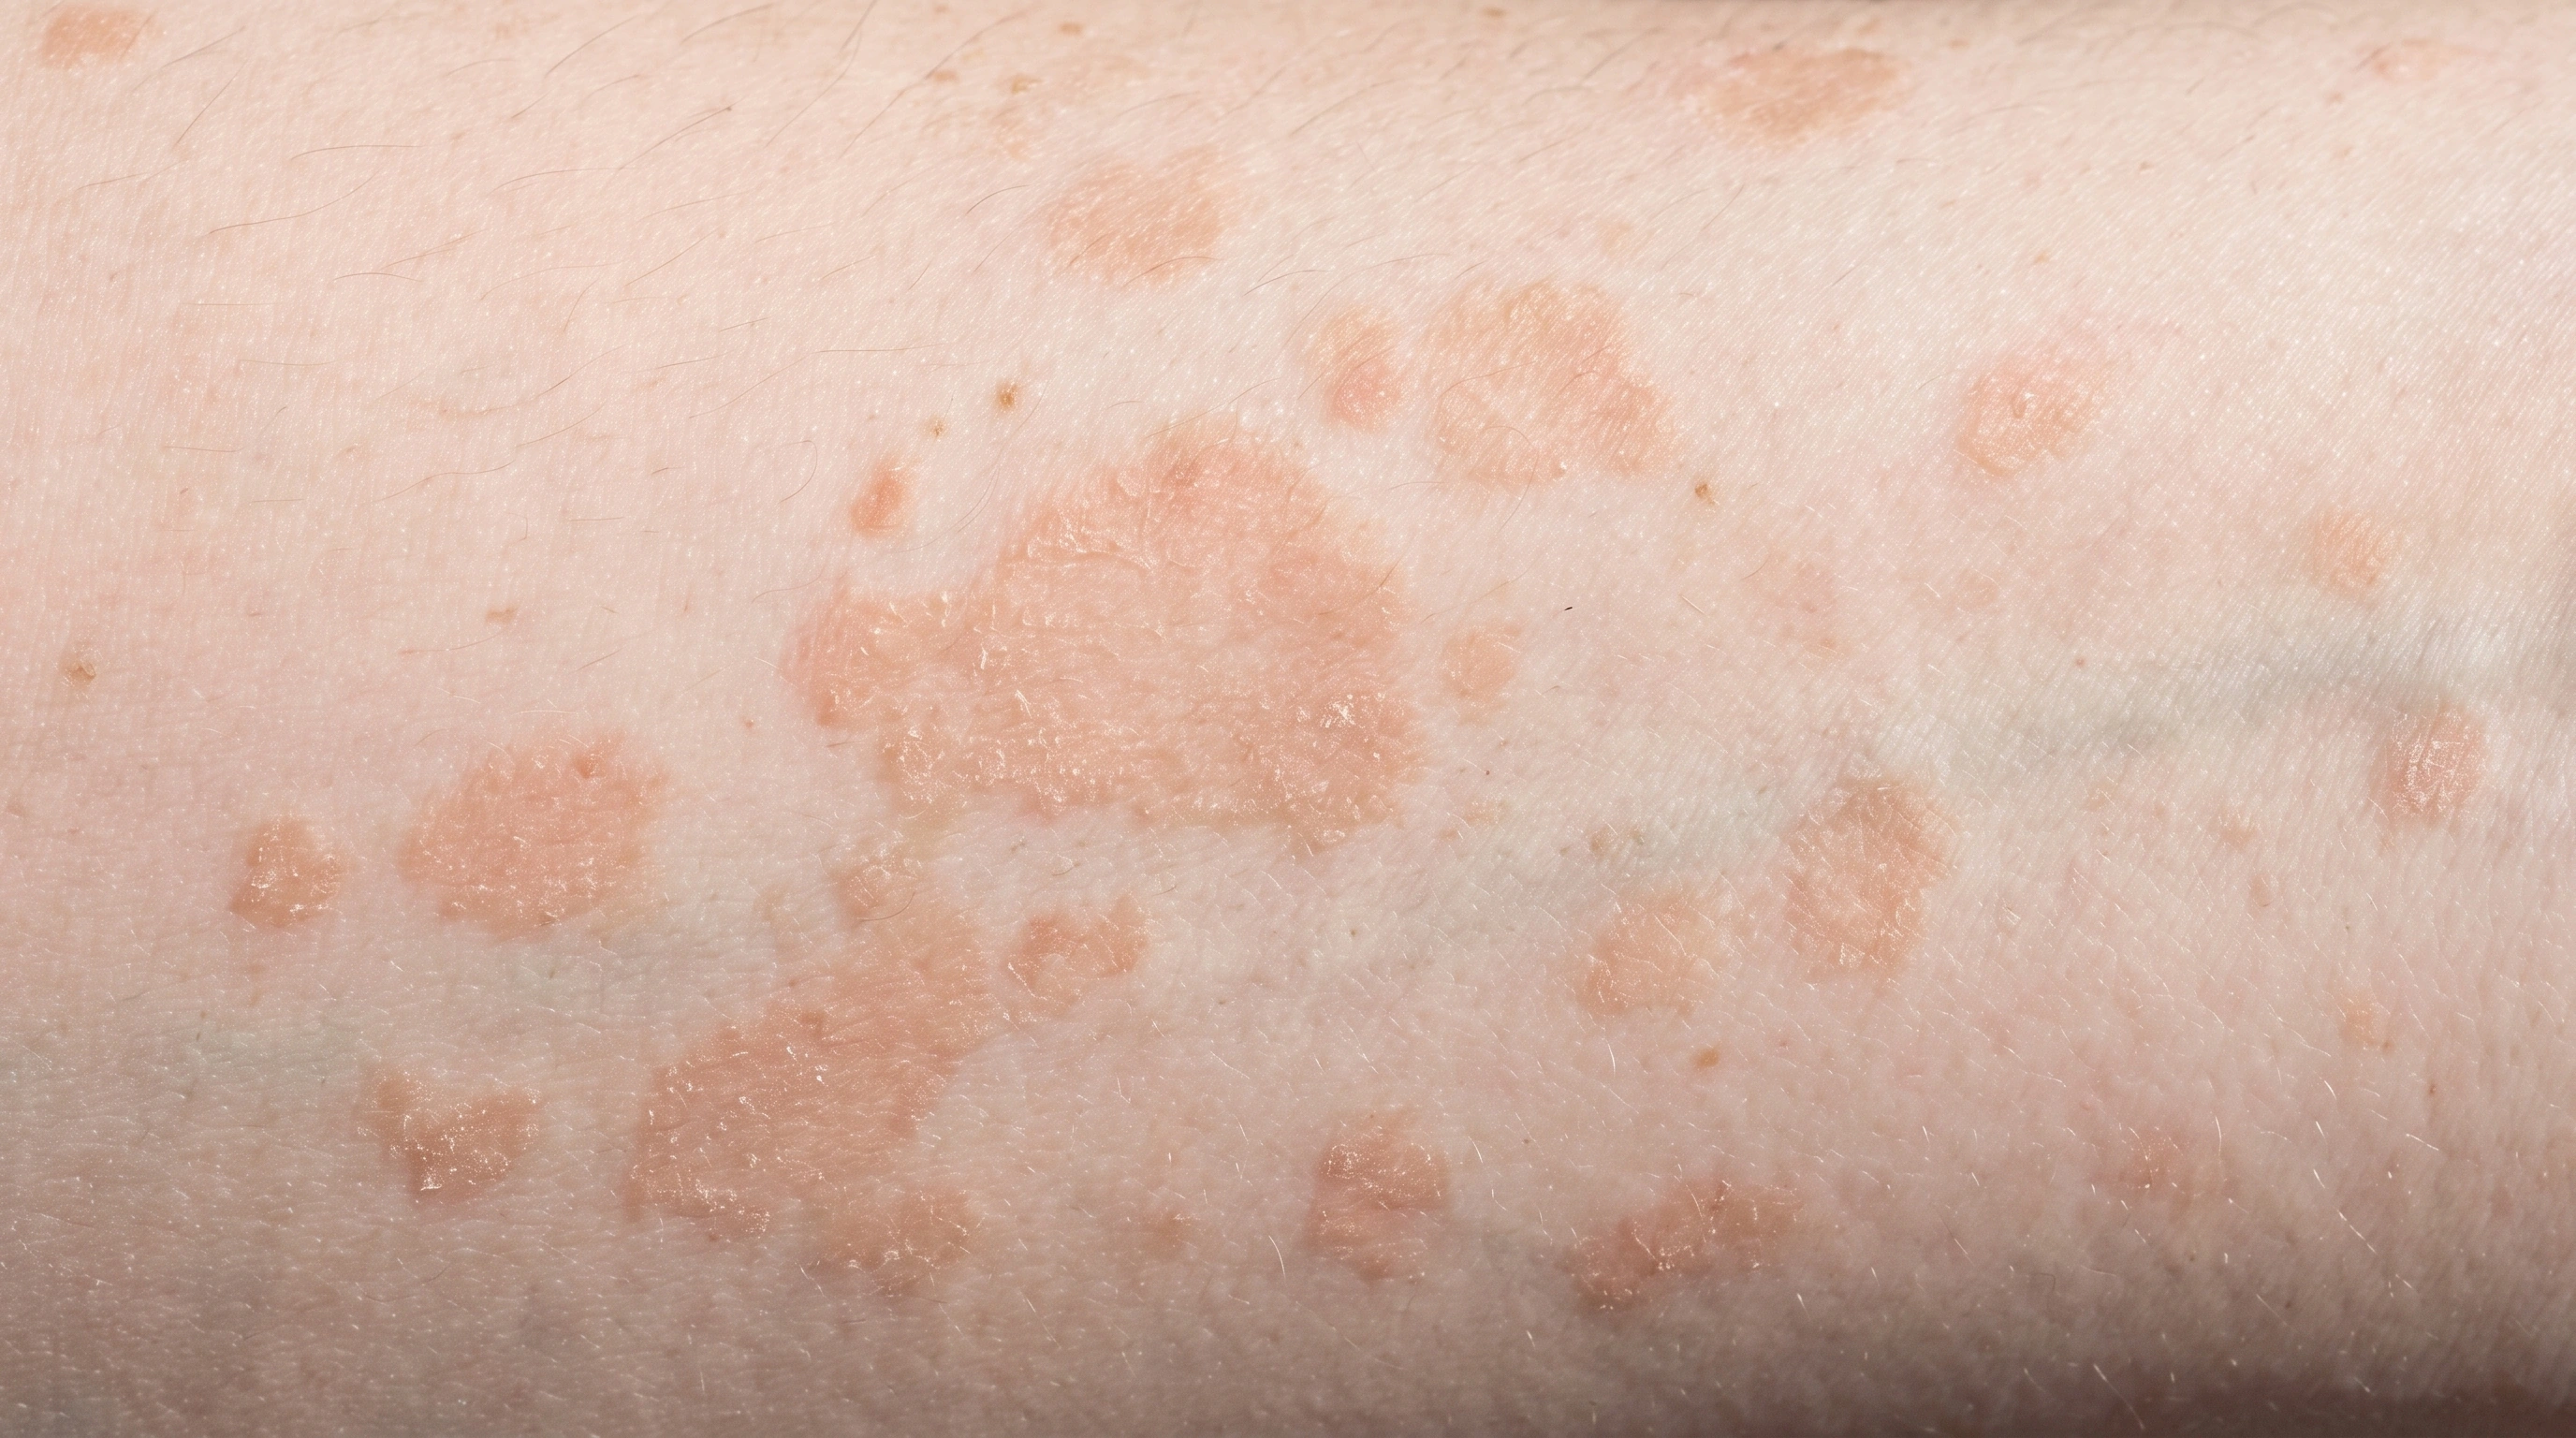
Guttate PsoriasisFlat oval patches in pink and light tan scattered across an upper chest and shoulder on light skin, several joined into larger areas, with a fine dusty scale on the surface.

Key differences

The same eight facts on every condition comparison.

Usual age
Children and young adults
15 to 35
Where
Trunk and limbs
Chest, back, shoulders
Main sign
Many small, drop-shaped scaly spots
Lighter or darker fine-scaly patches
Itch or pain
Mildly itchy
Mild itch at most
Contagious
No
No
Long term
Often clears in months; can recur
Clears fast, often returns
Scars
No
No
Who gets it
After strep throat
Teens and young adults; warm climates

What is it?

Guttate Psoriasis
Tinea Versicolor
What is it?
  • What it is
    A sudden crop of small drop-like psoriasis spots, often after a throat infection.
  • It is a surface yeast condition.
    Also called pityriasis versicolor, it affects only the outer skin layer.
  • It changes skin color.
    Small patches can merge across the upper chest, back, neck or upper arms.
  • Fine scale is a clue.
    Surface scale helps distinguish active disease from other pigment changes.
  • Color returns more slowly.
    Pigment can take longer to even out after the yeast has been treated.

What it looks like

Guttate Psoriasis

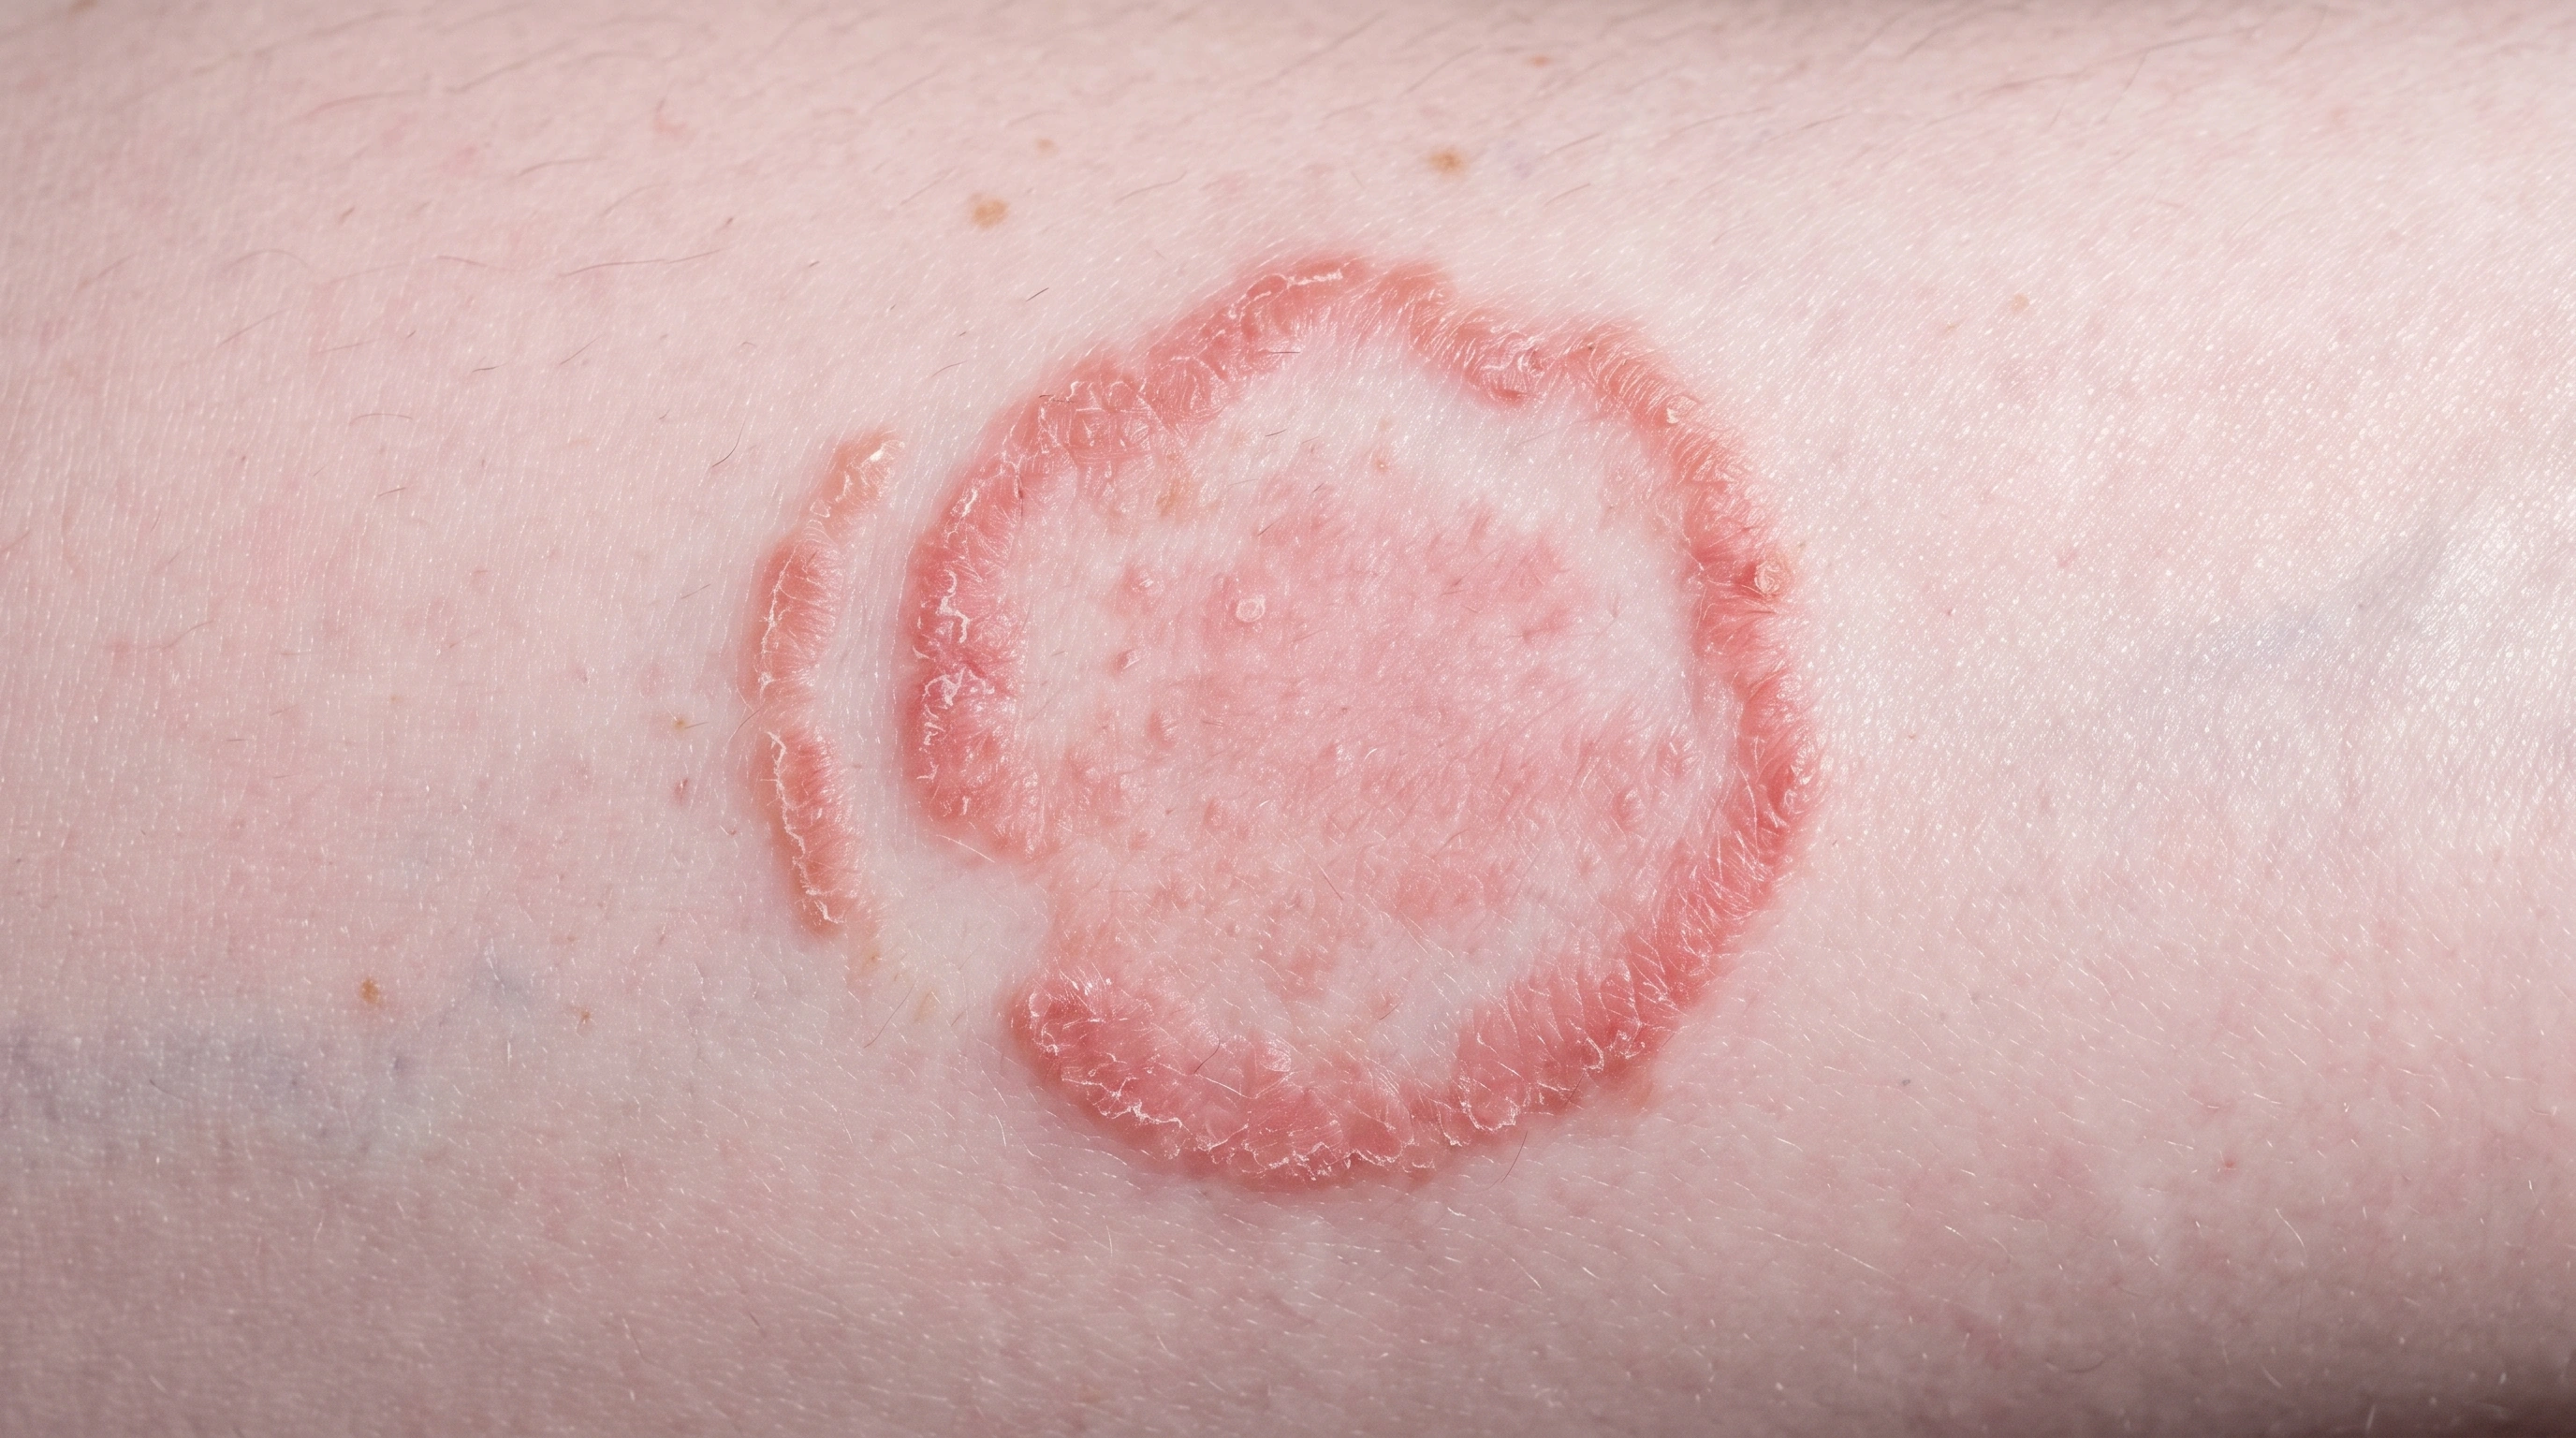
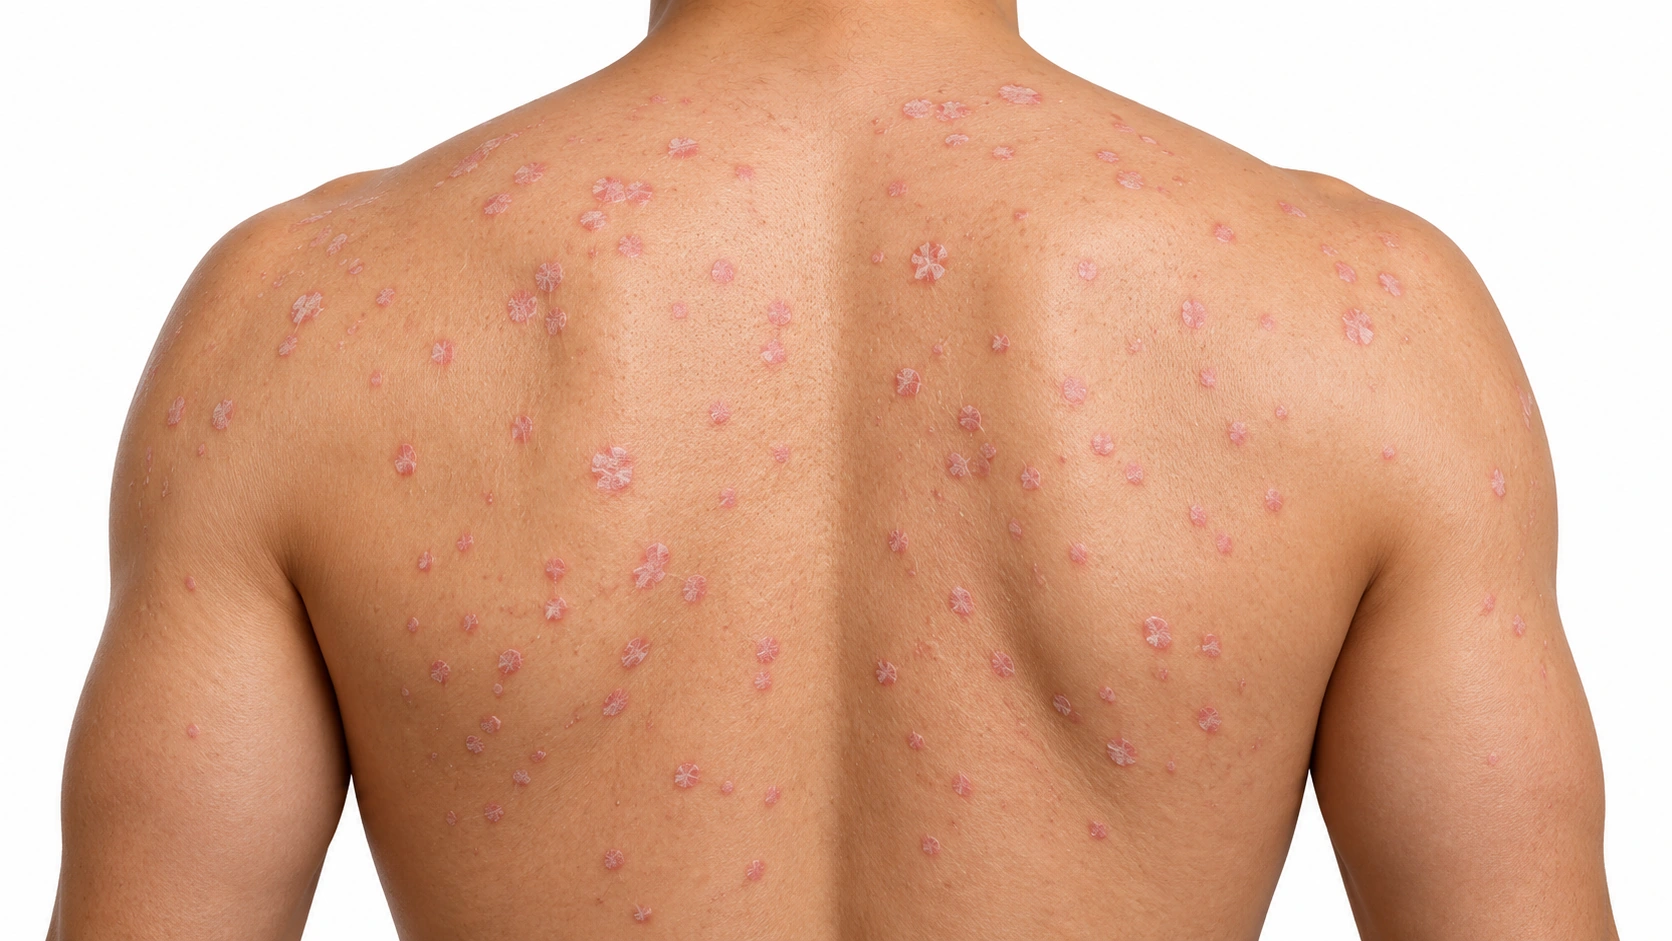
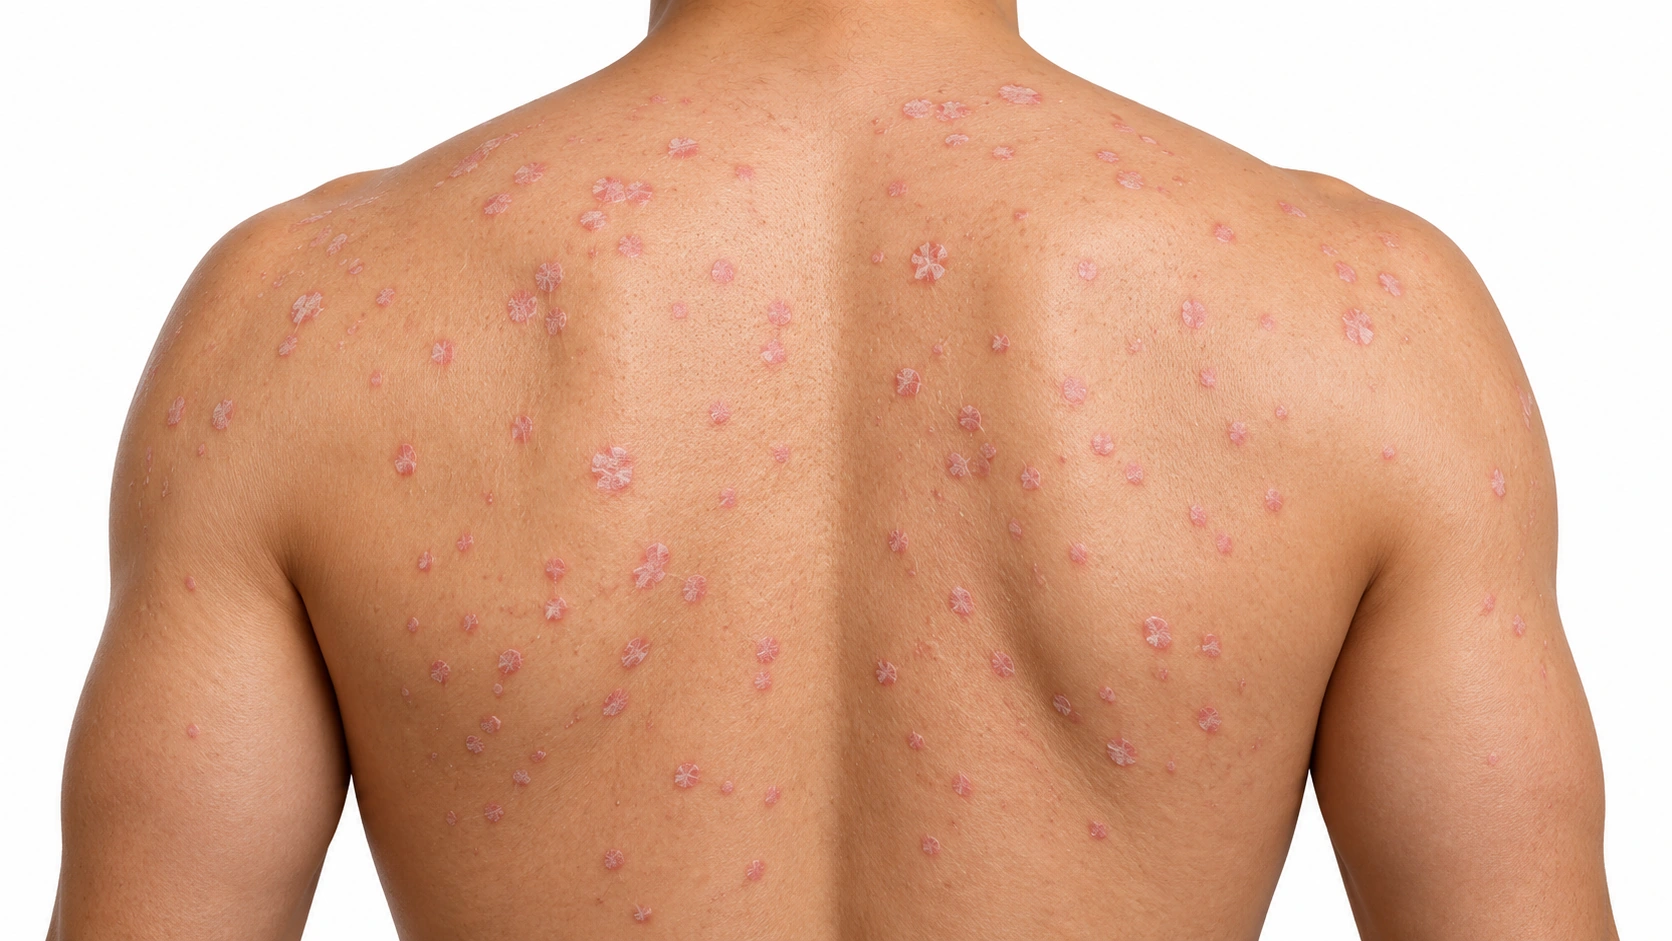
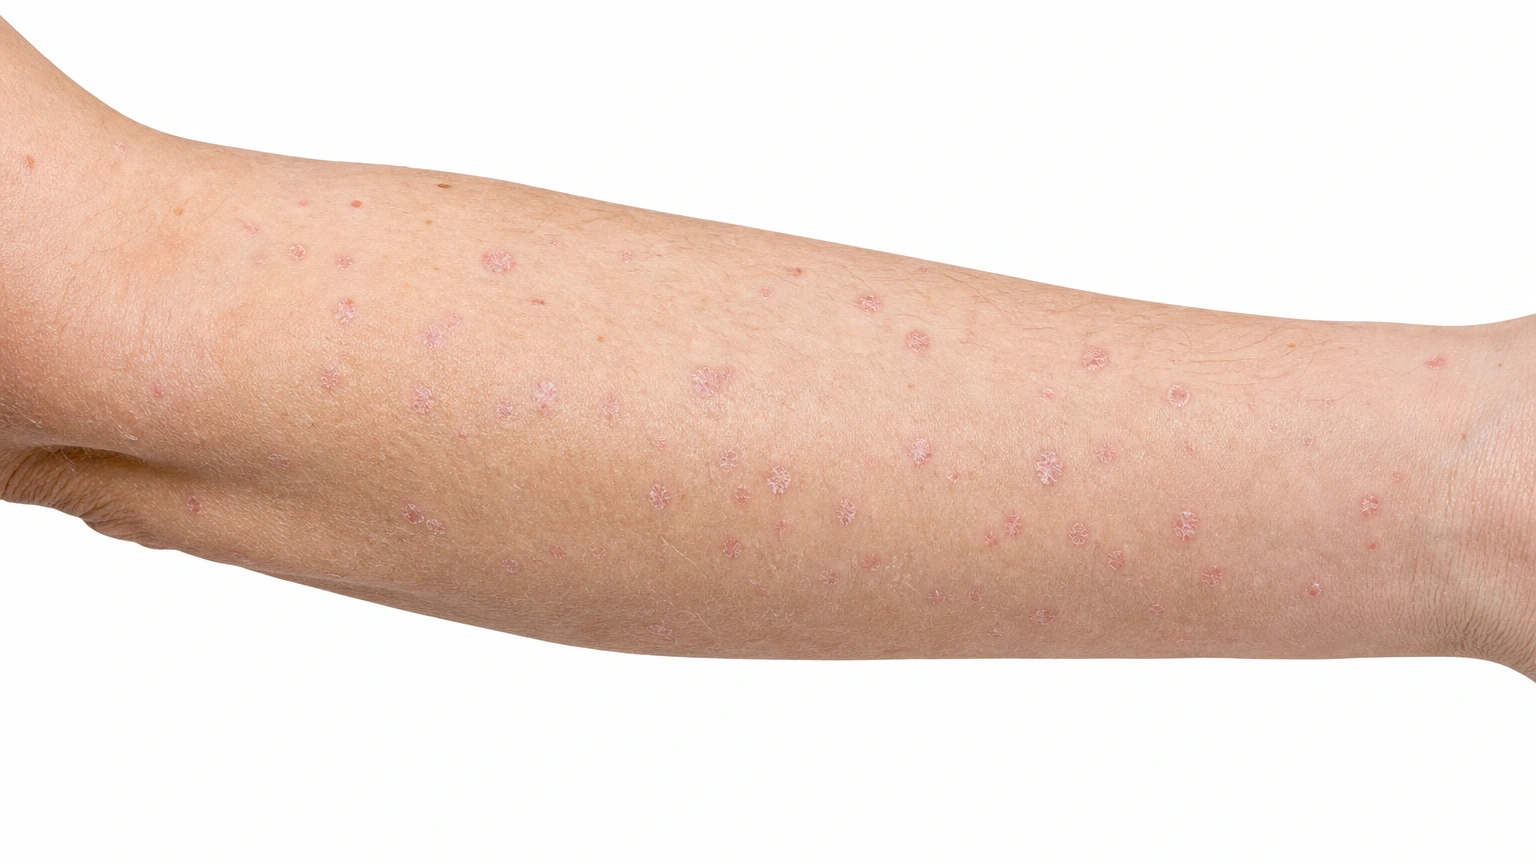
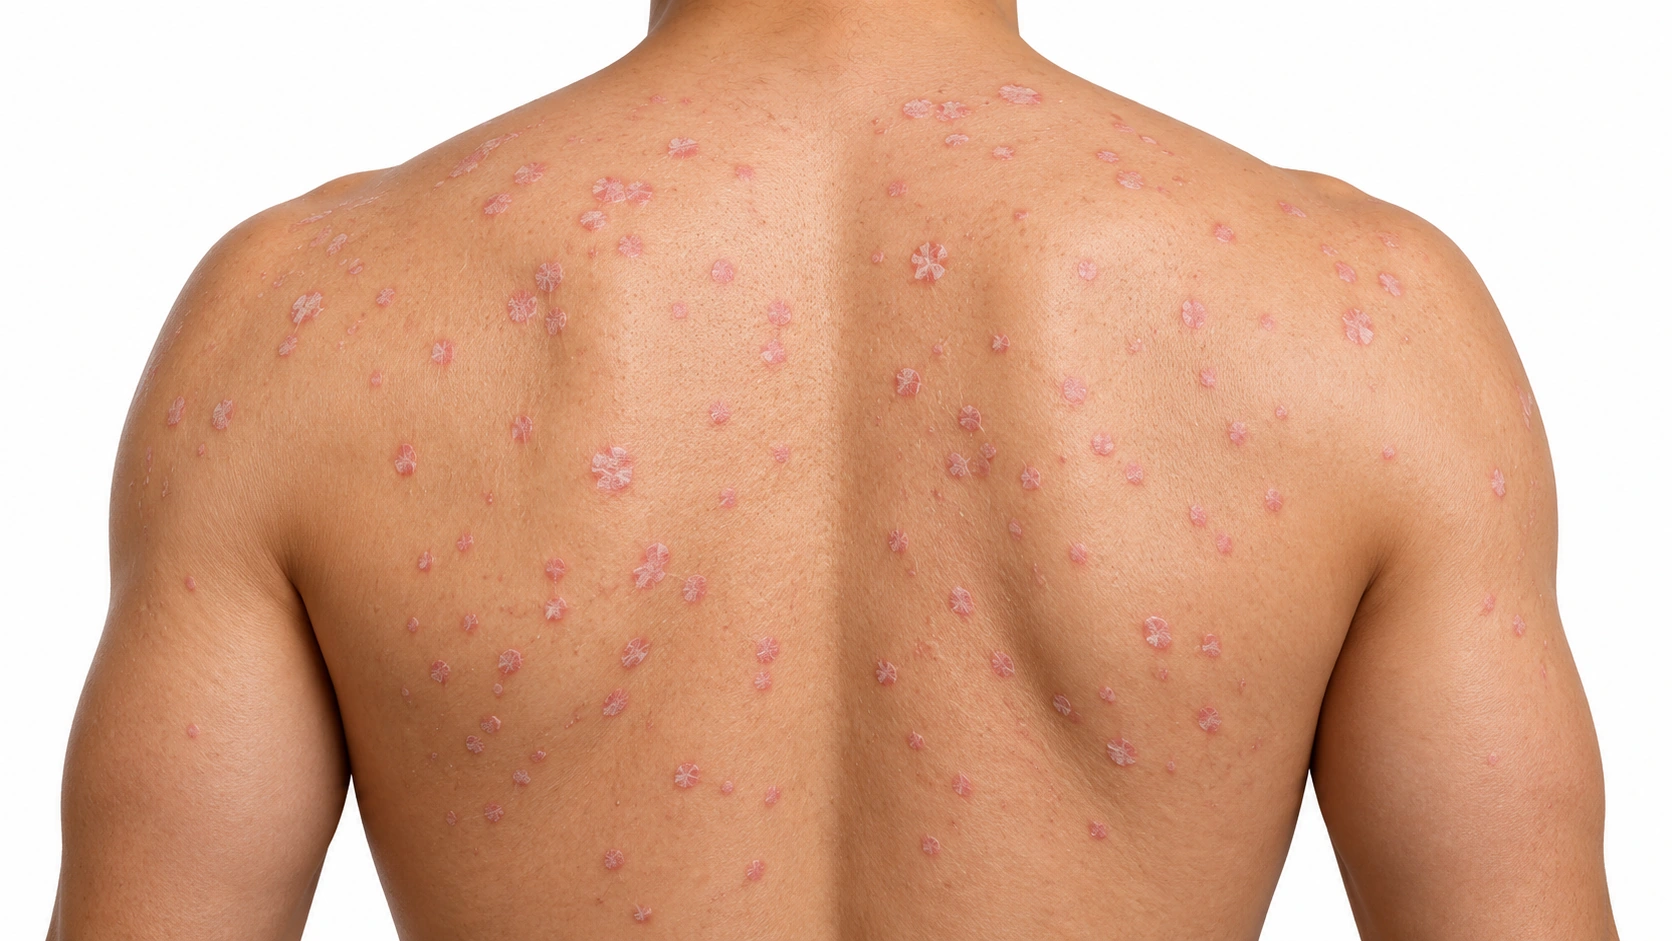
A back covered with small scattered pink scaly patches.

Guttate Psoriasis Many separate pink spots with surface scale are spread across the back.

Tinea Versicolor

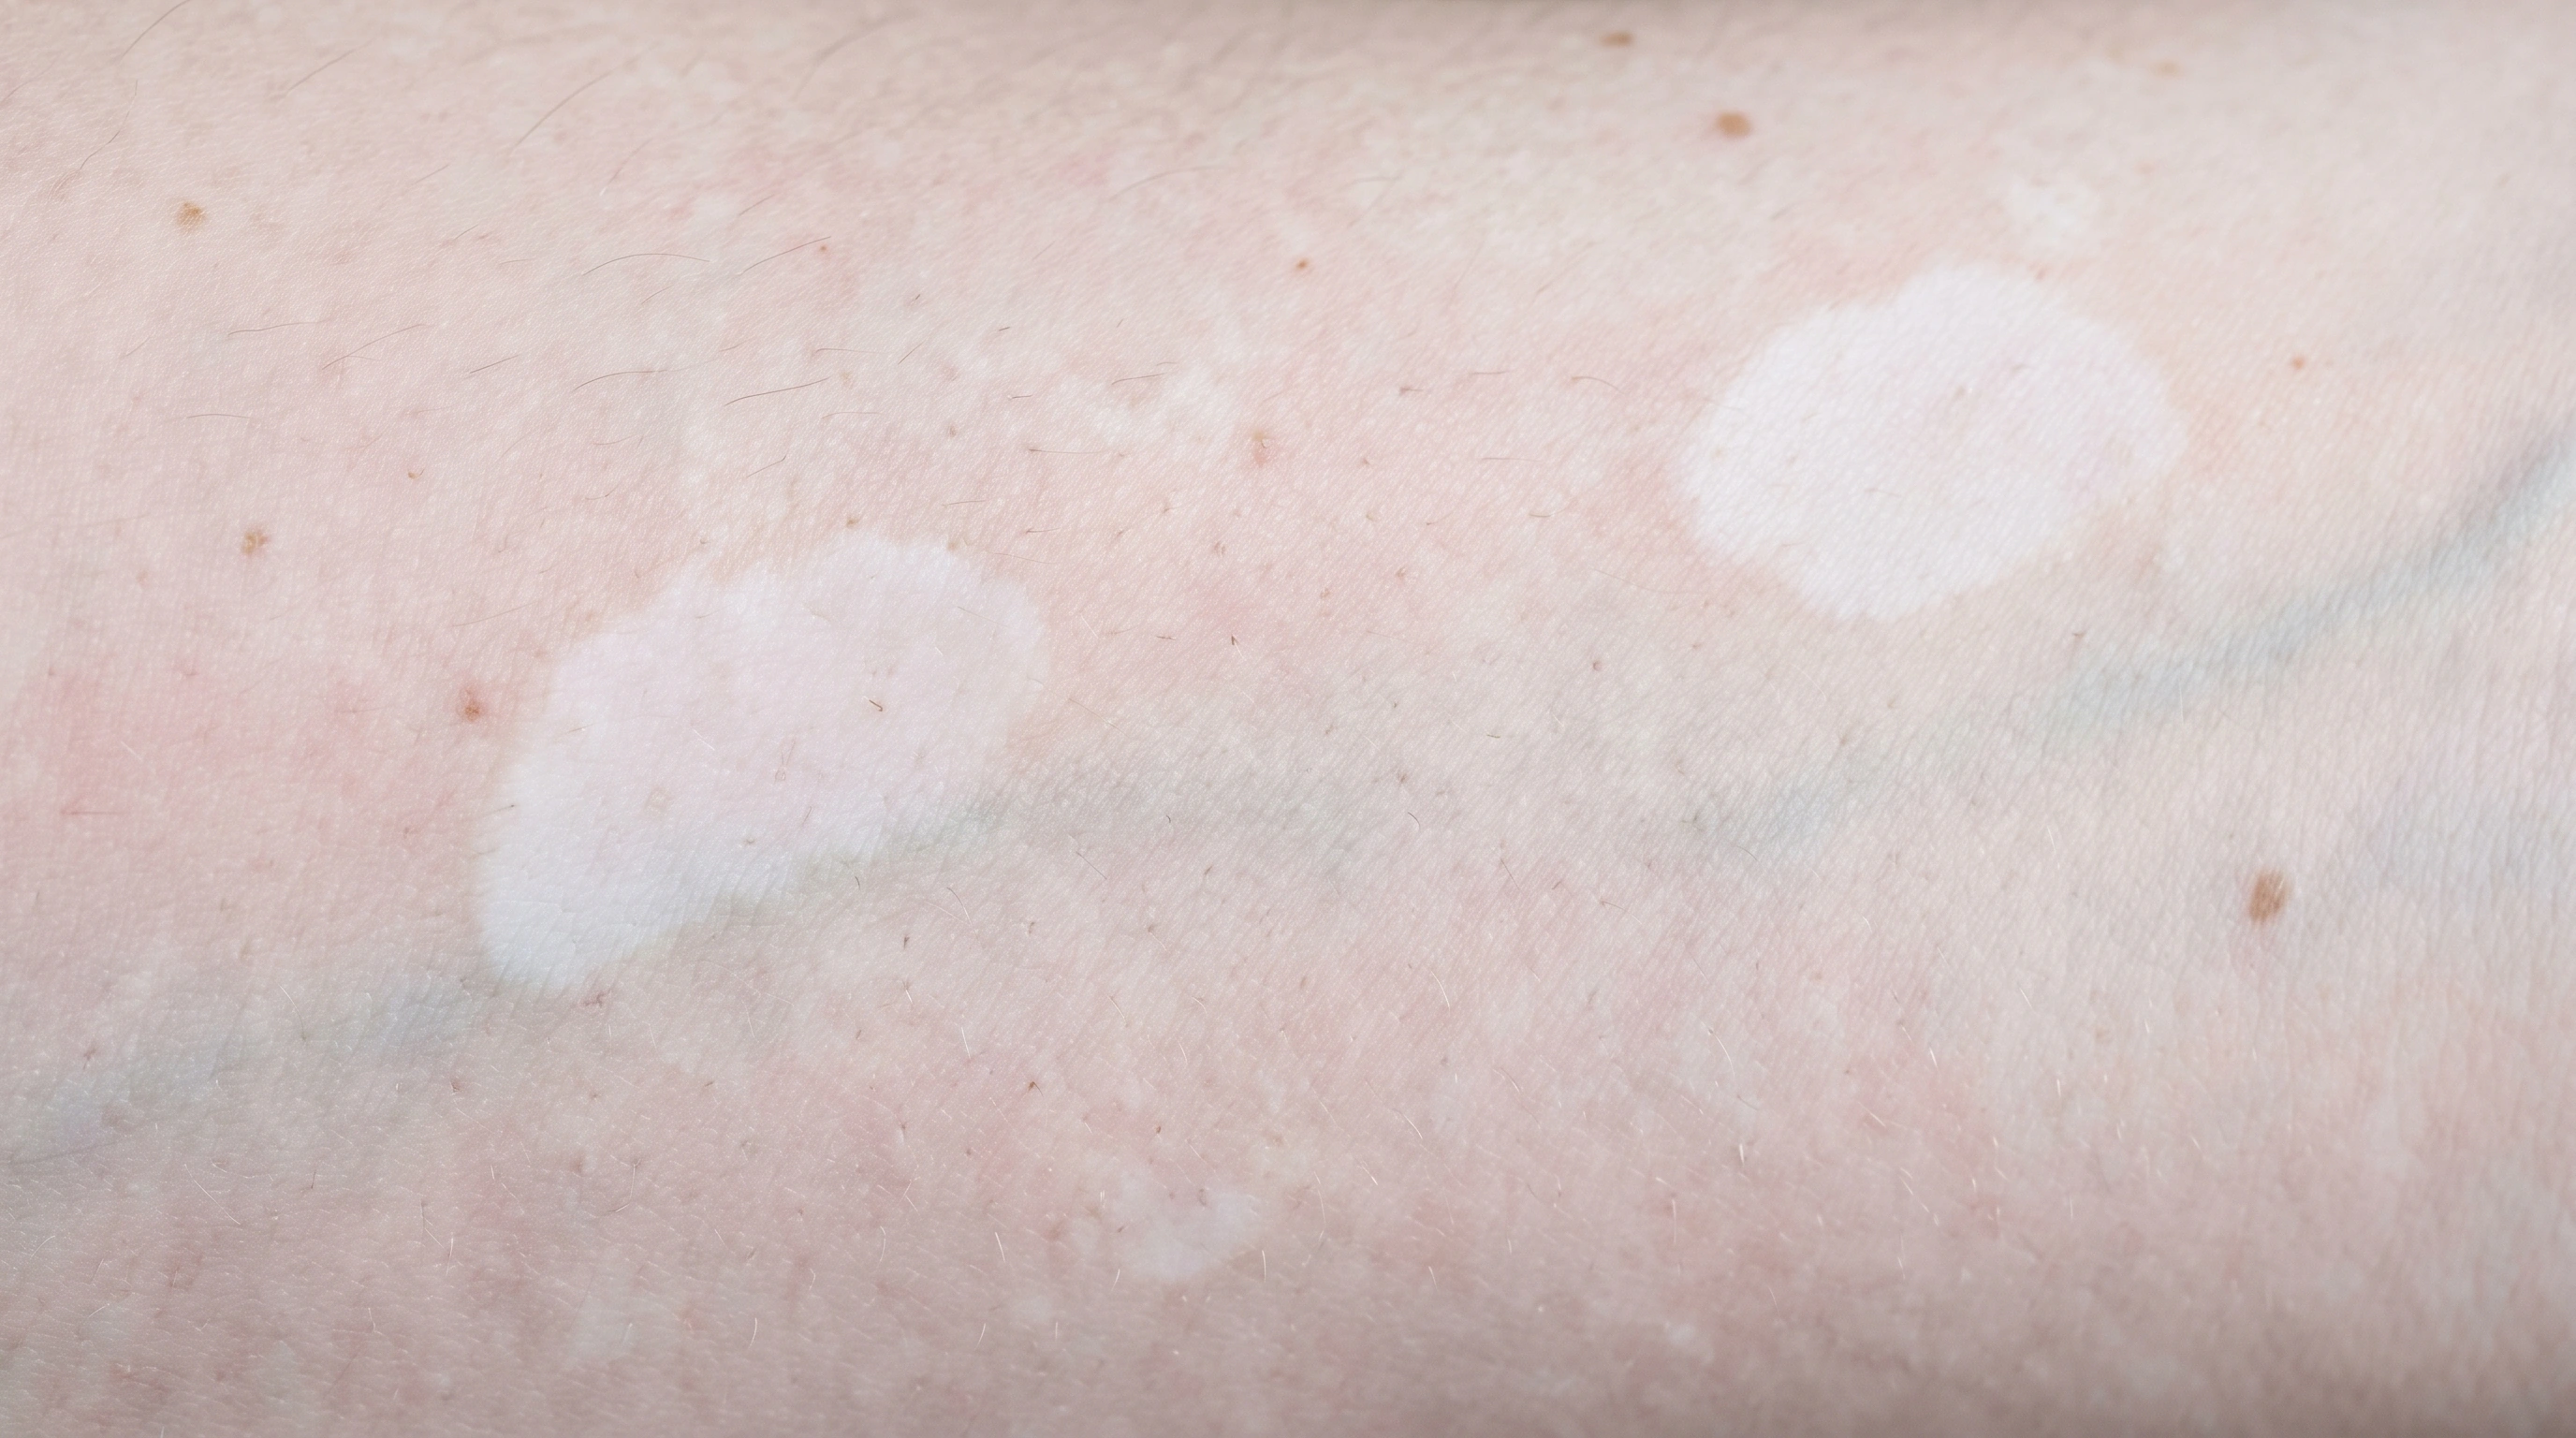
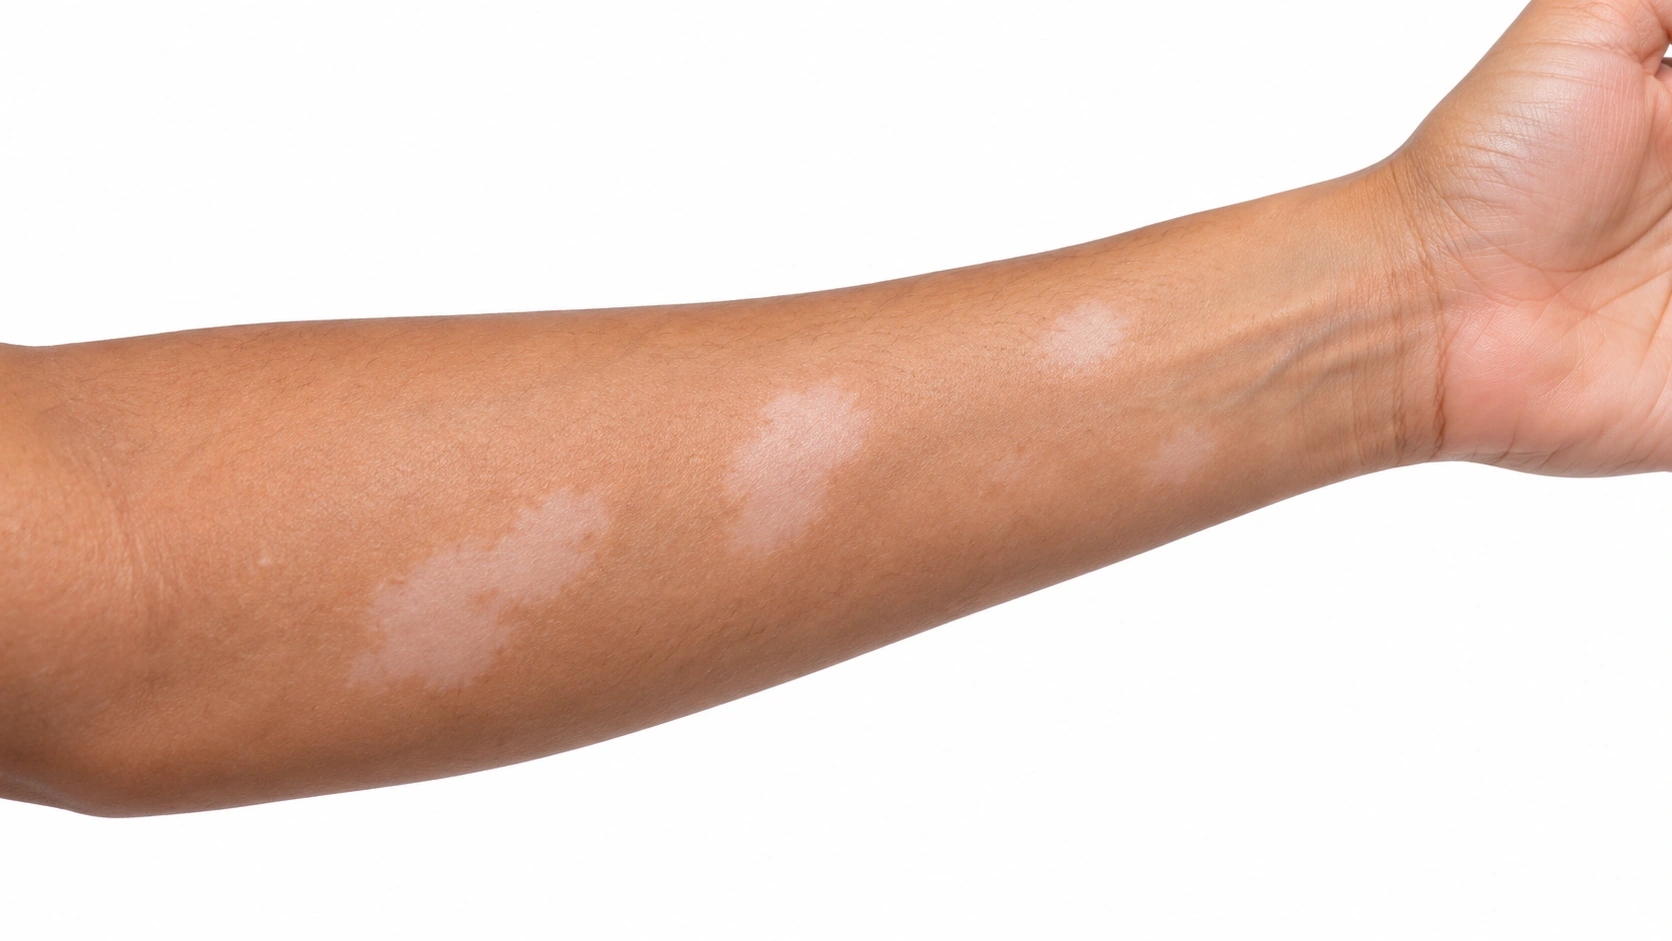
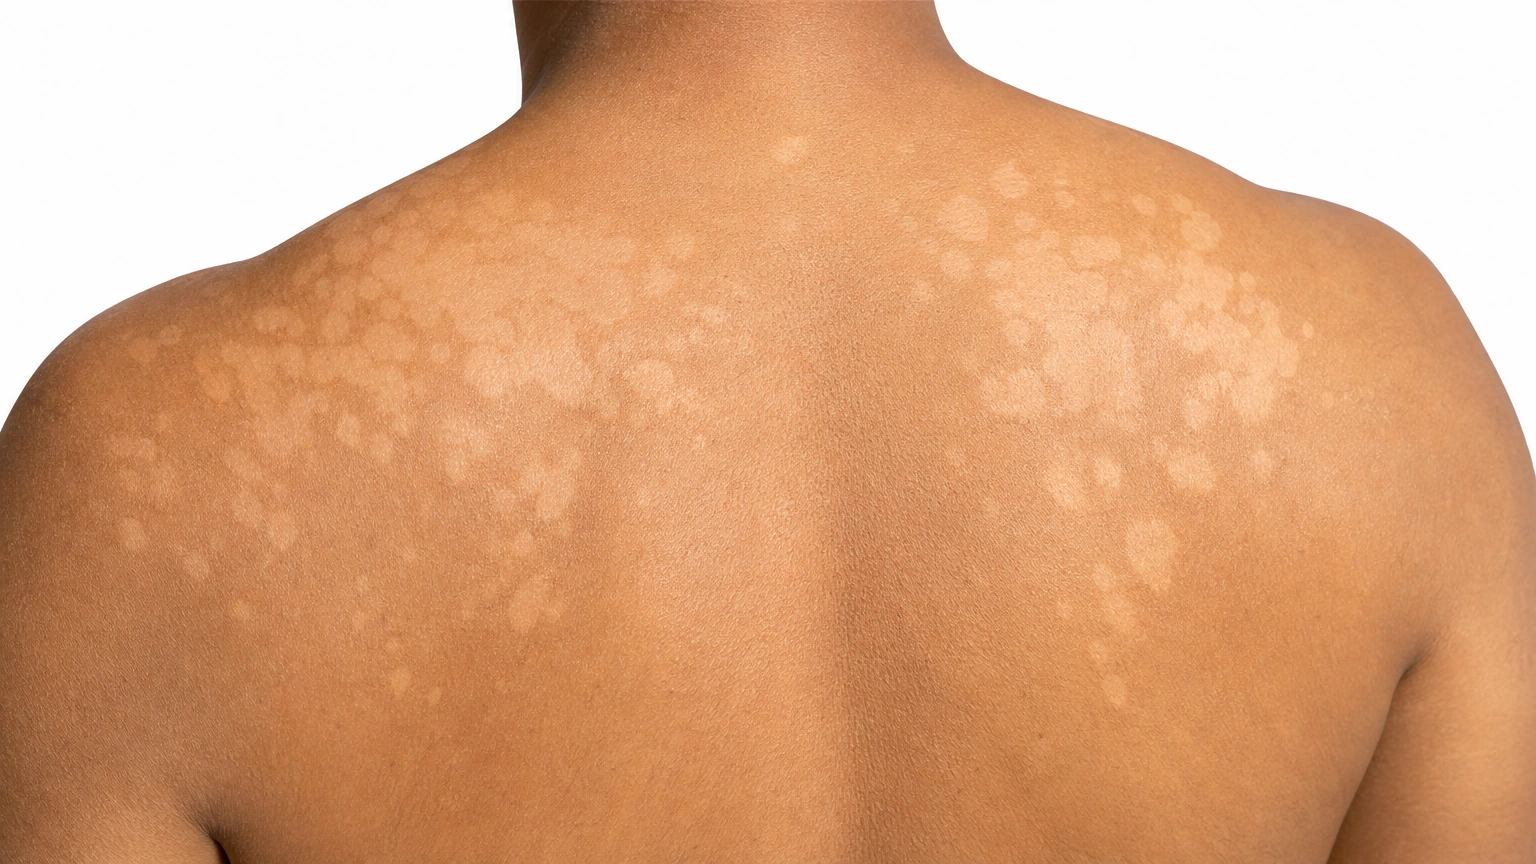
Multiple pale patches over the shoulders and upper back, representing hypopigmented tinea versicolor.

Hypopigmented tinea versicolor Lighter patches; most common.

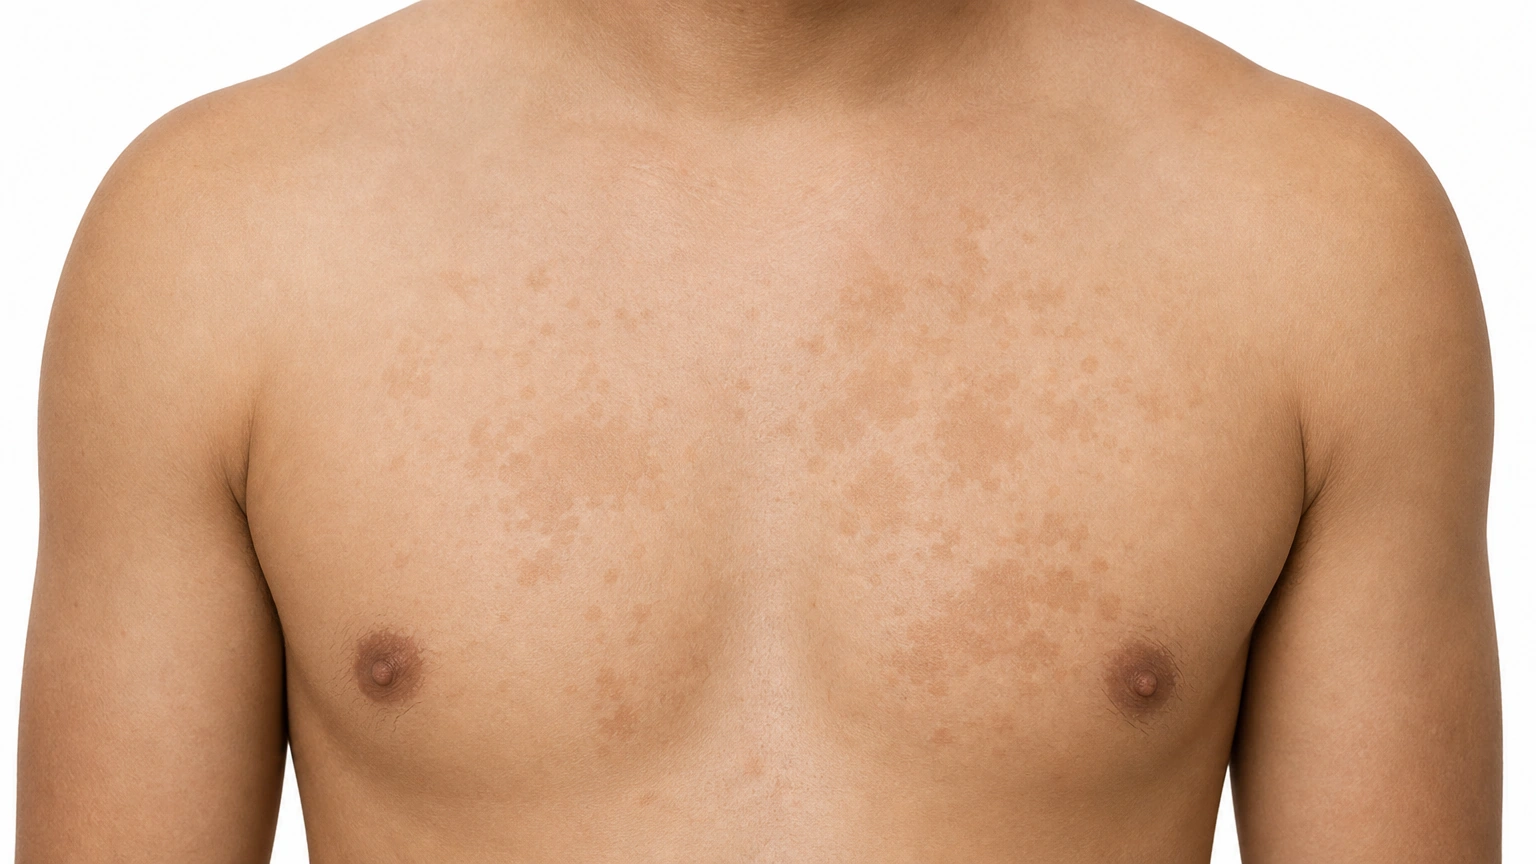
Irregular tan patches on the upper chest, representing tinea versicolor.

Hyperpigmented tinea versicolor Darker or pinkish patches.

Skin tones
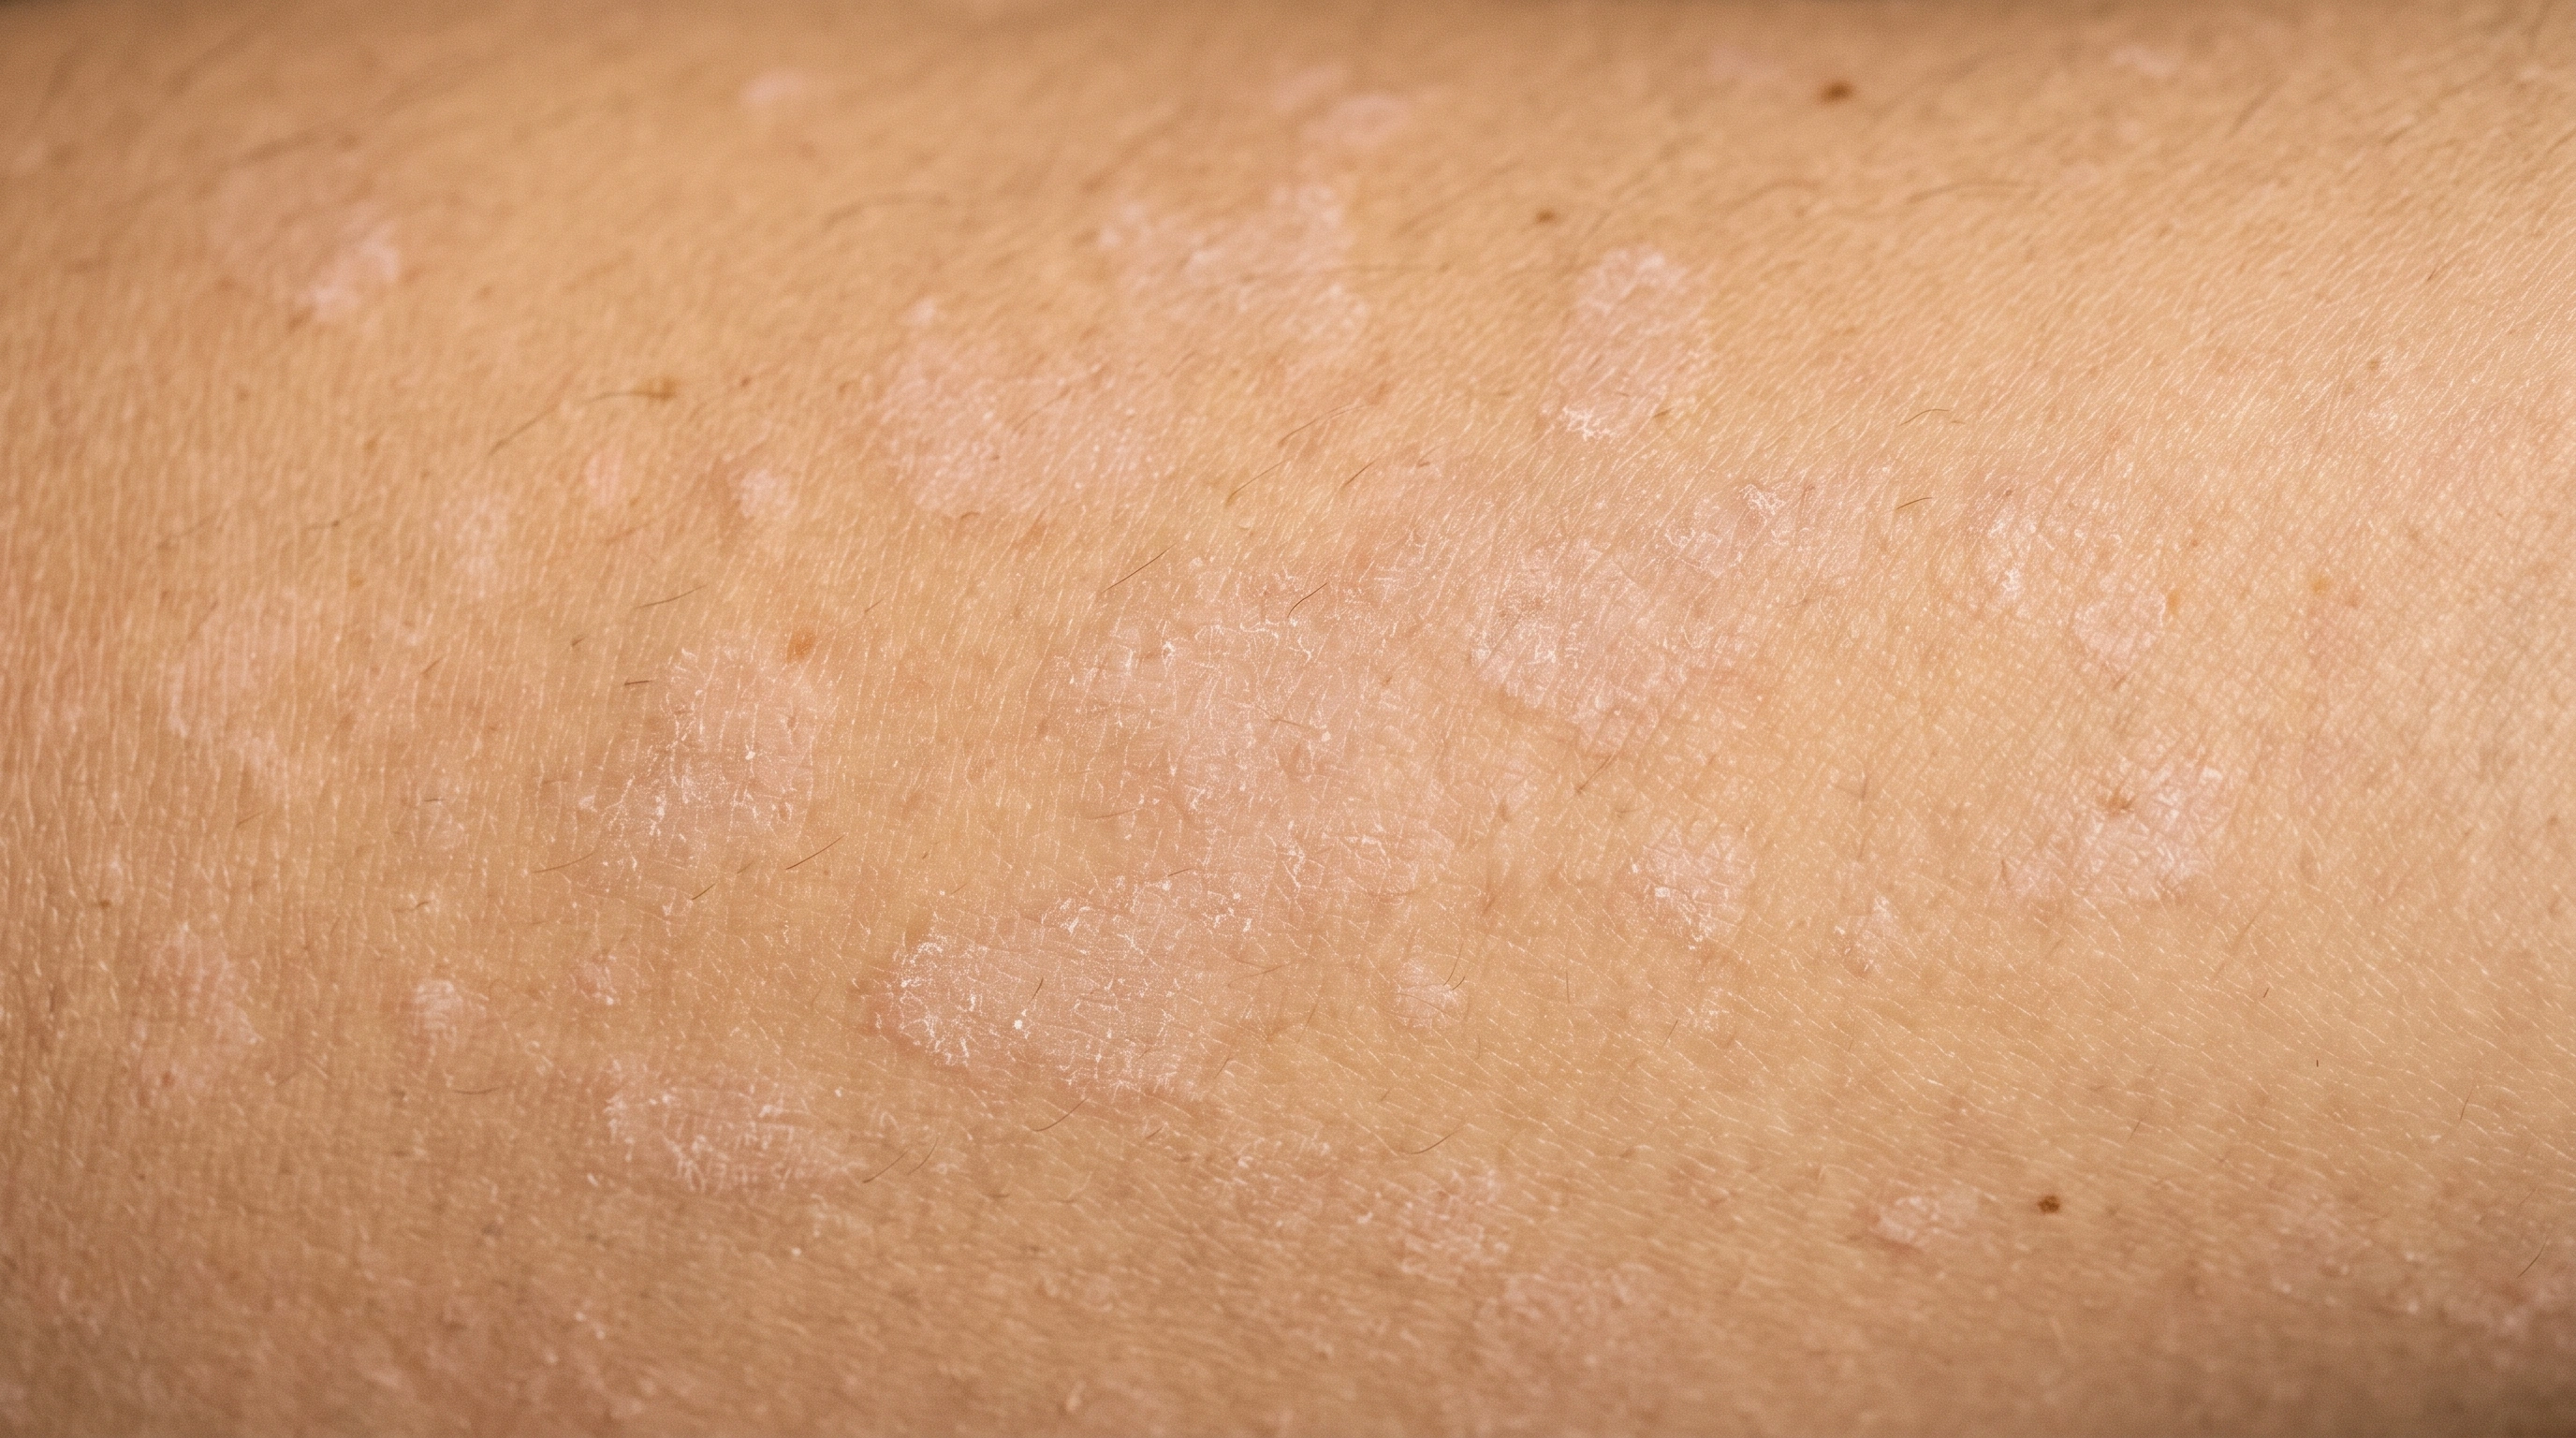
Guttate Psoriasis on light skin.
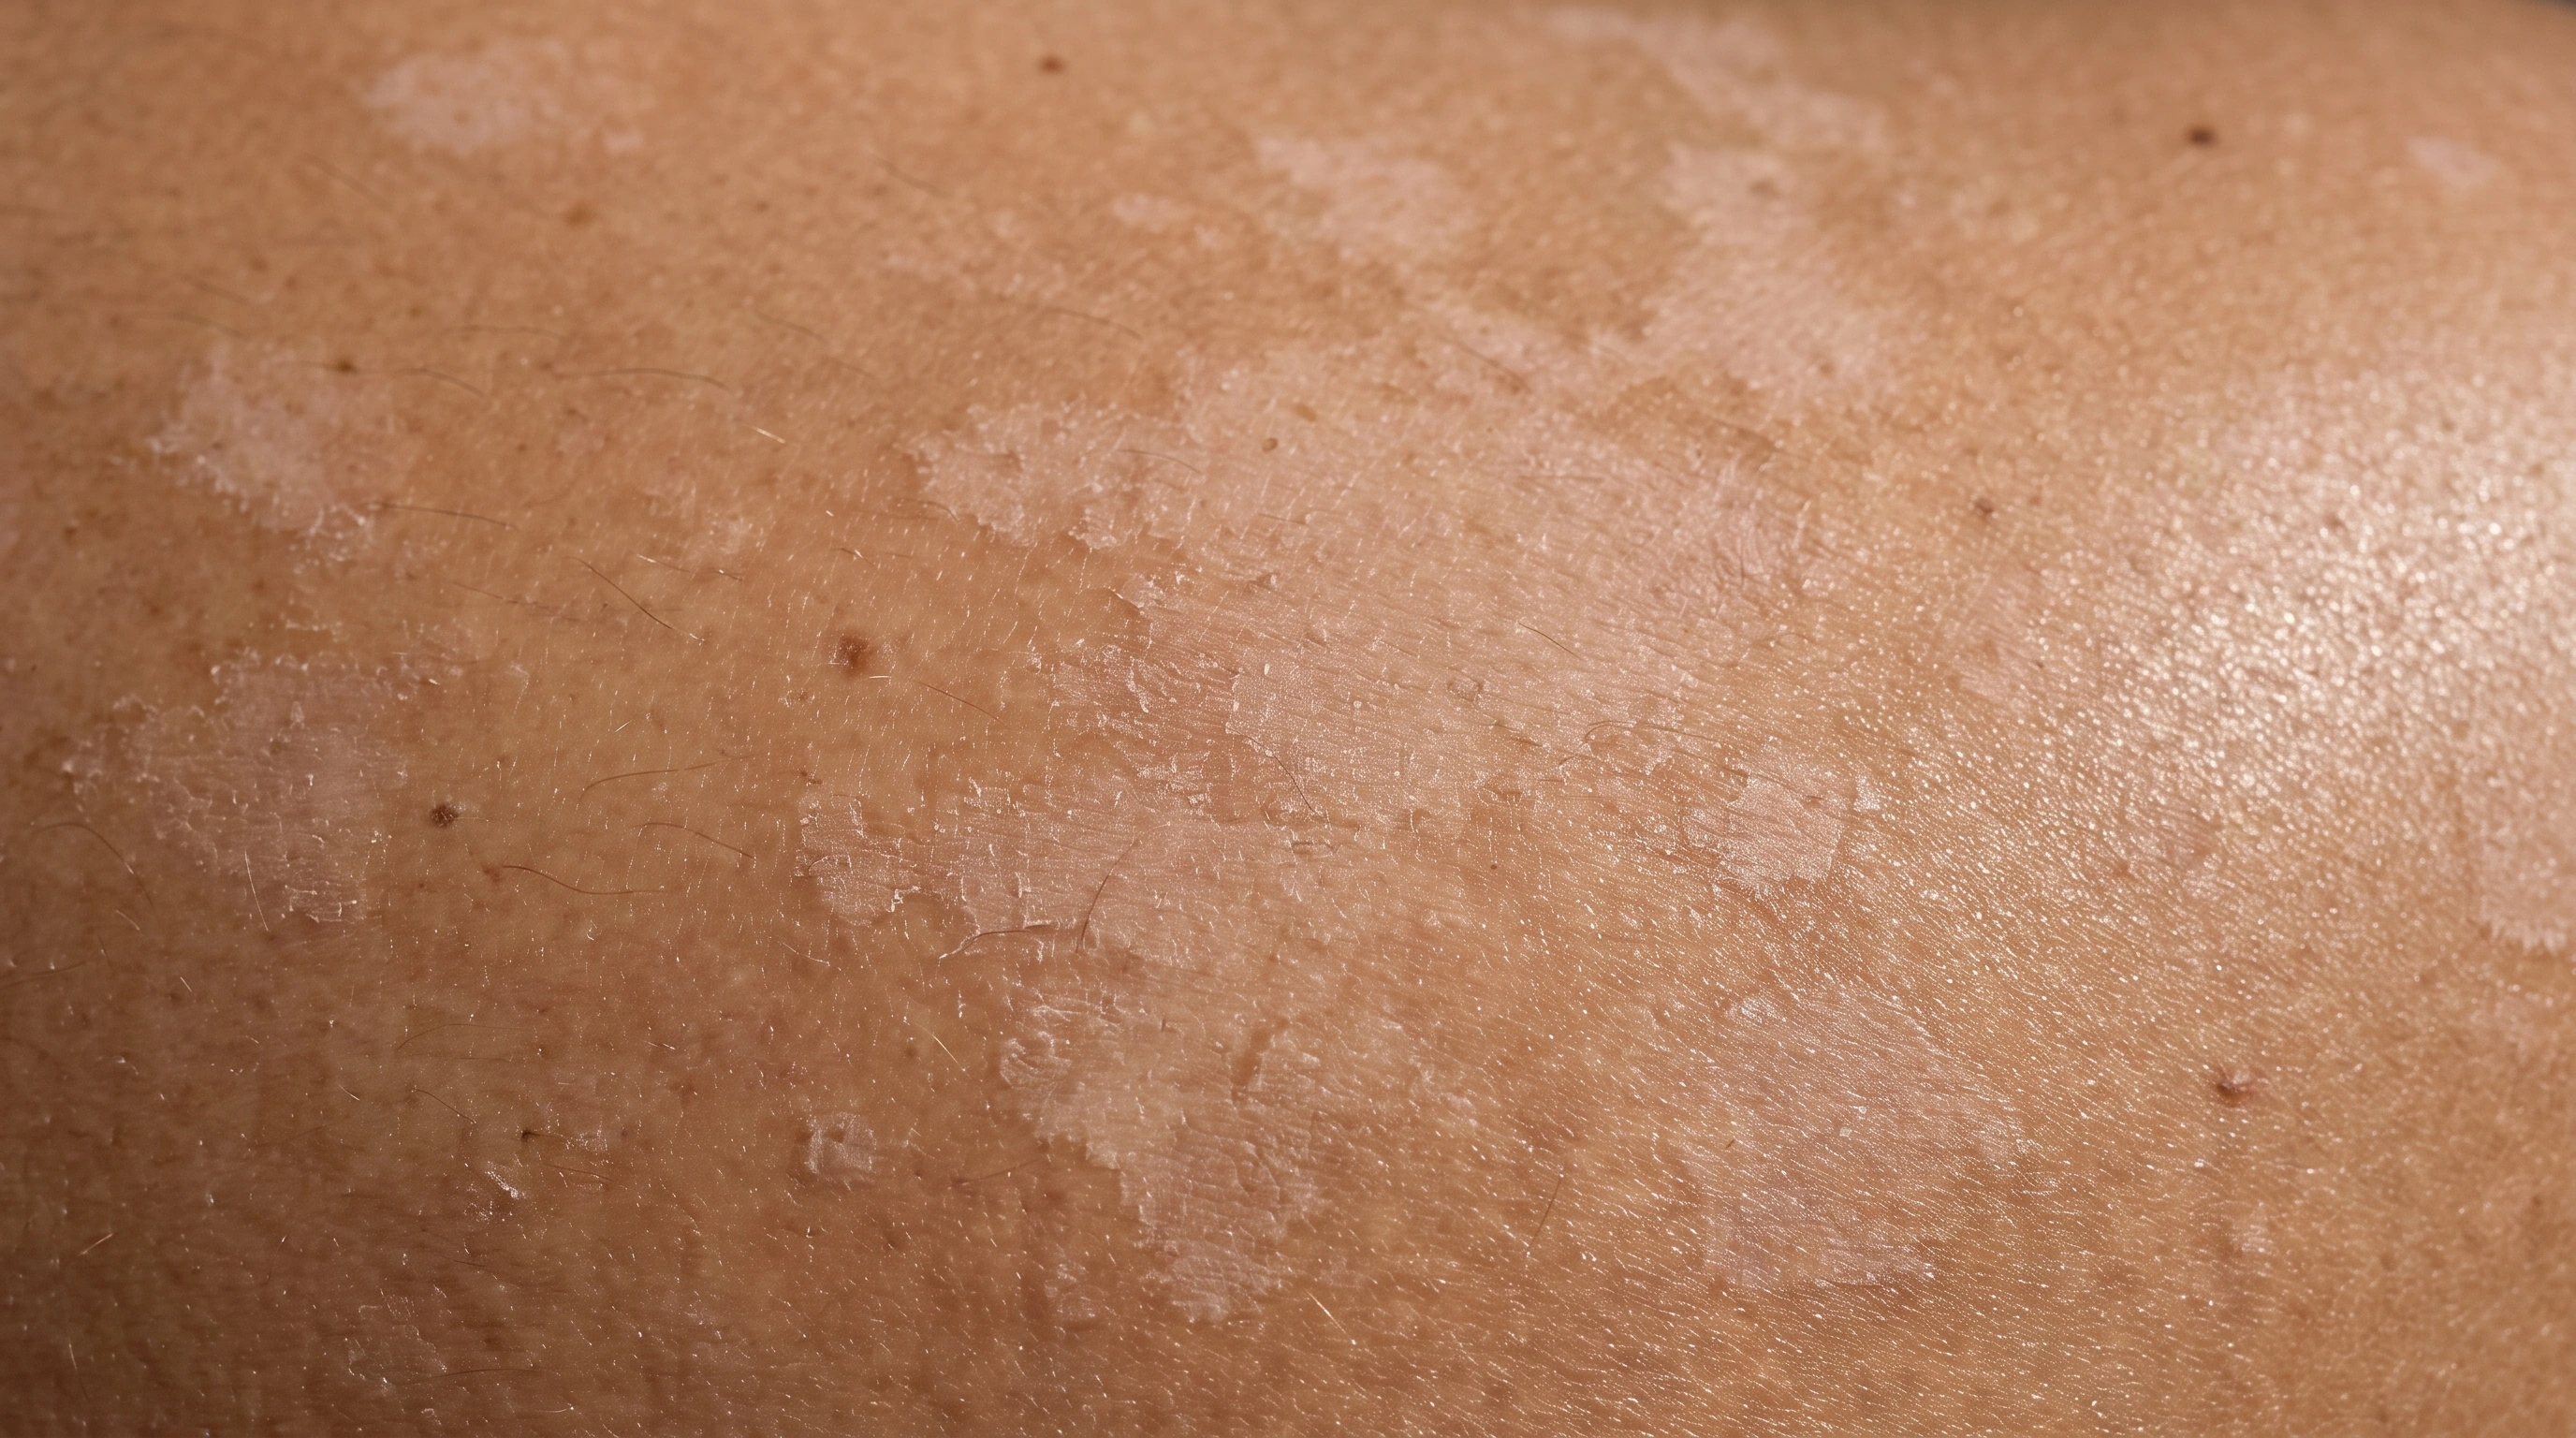
Guttate Psoriasis on medium skin.
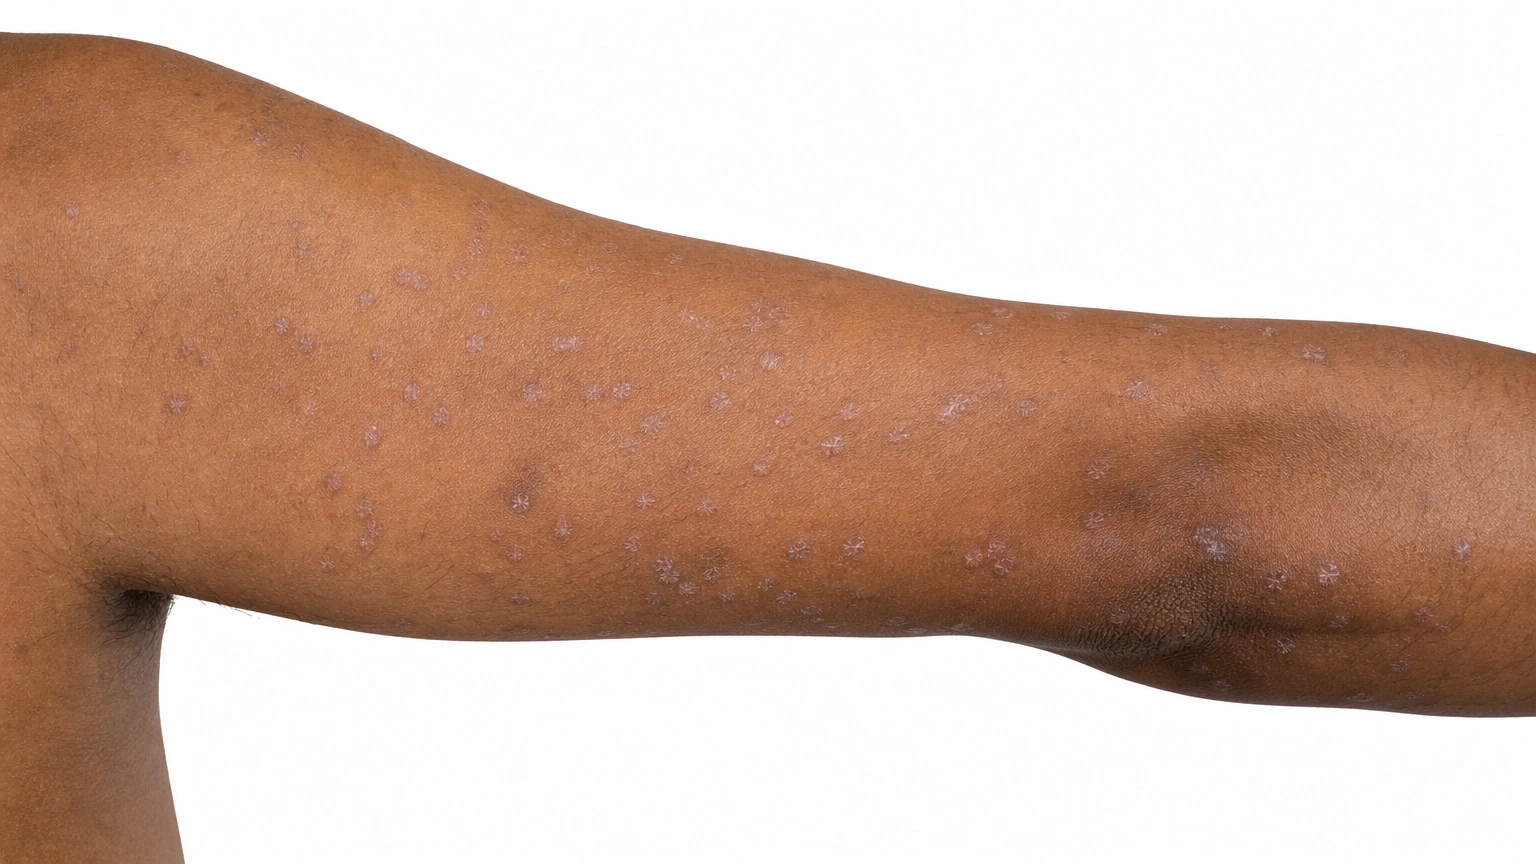
Guttate Psoriasis on brown skin.
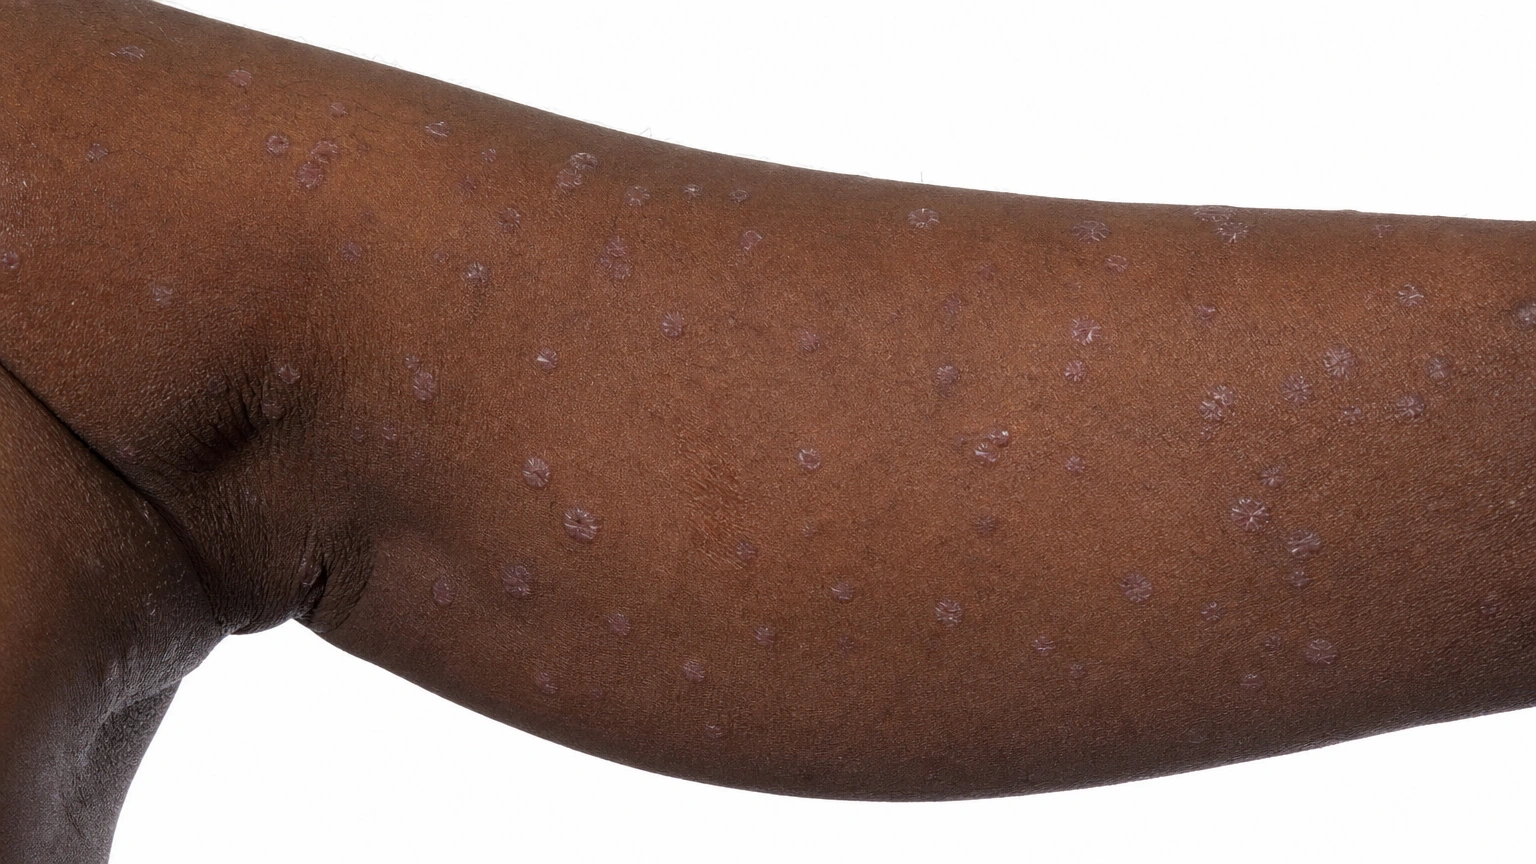
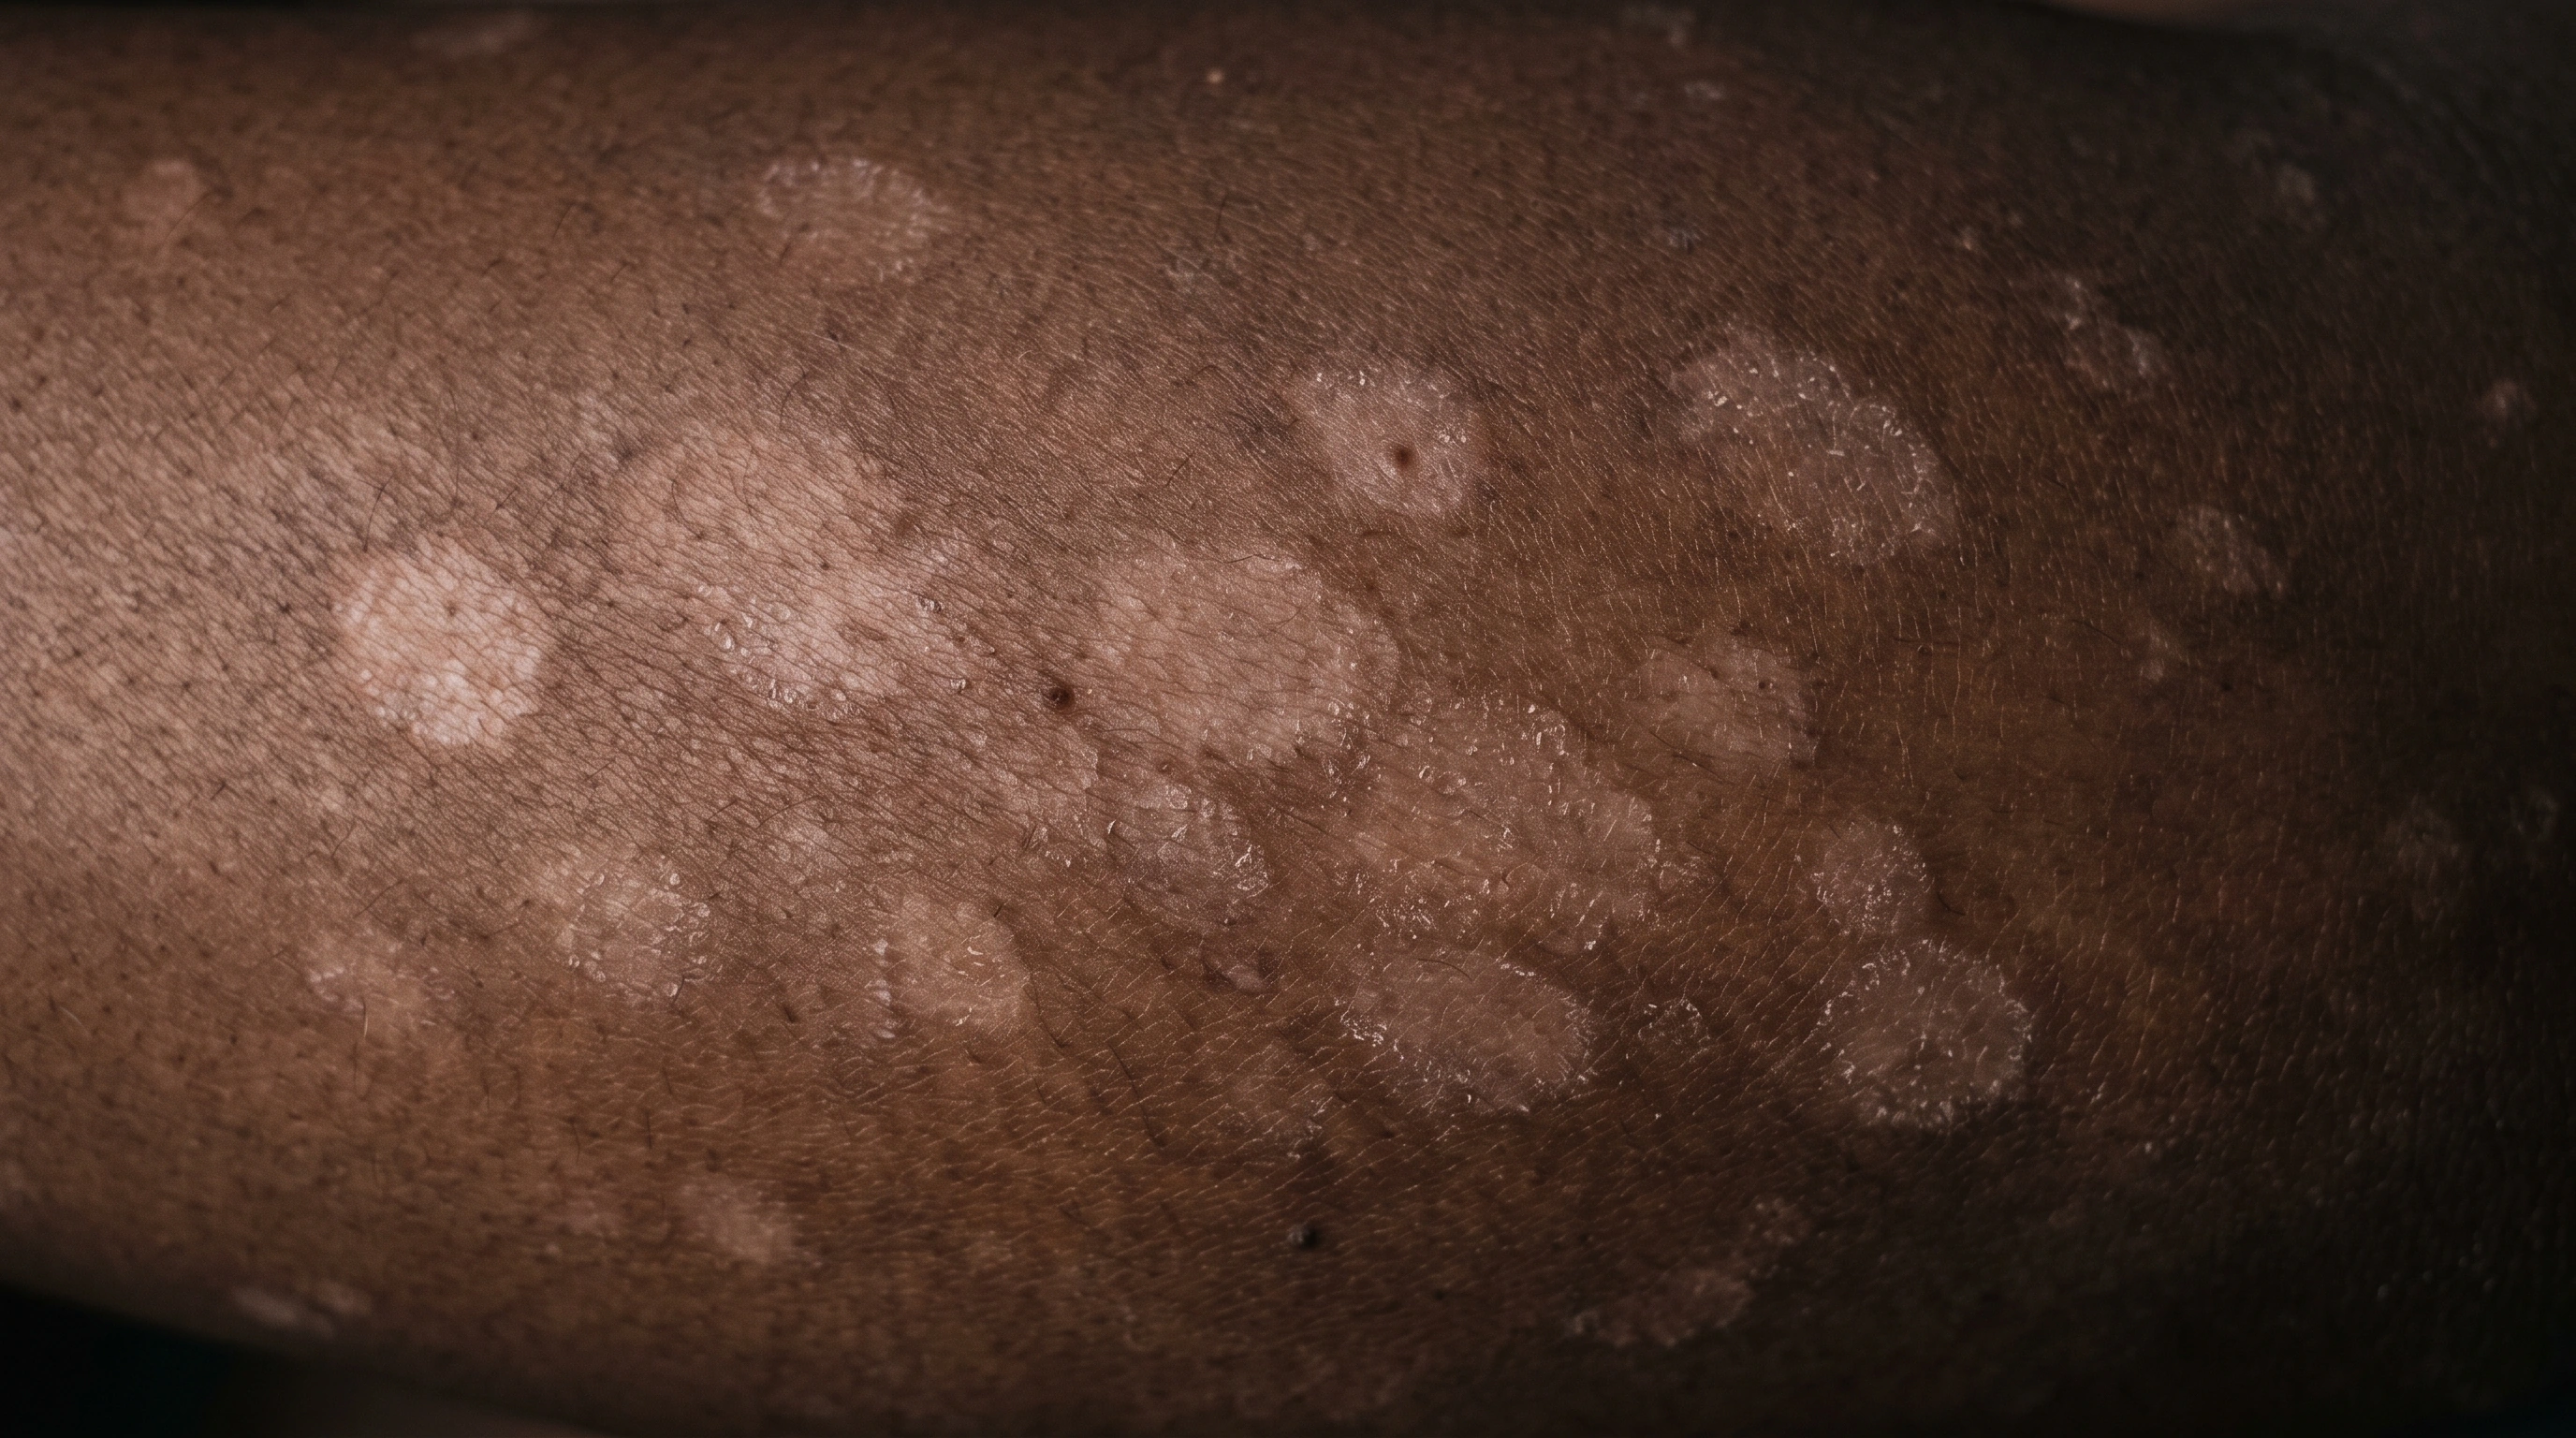
Guttate Psoriasis on deep skin.
Flat oval patches in pink and light tan scattered across an upper chest and shoulder on light skin, several joined into larger areas, with a fine dusty scale on the surface.
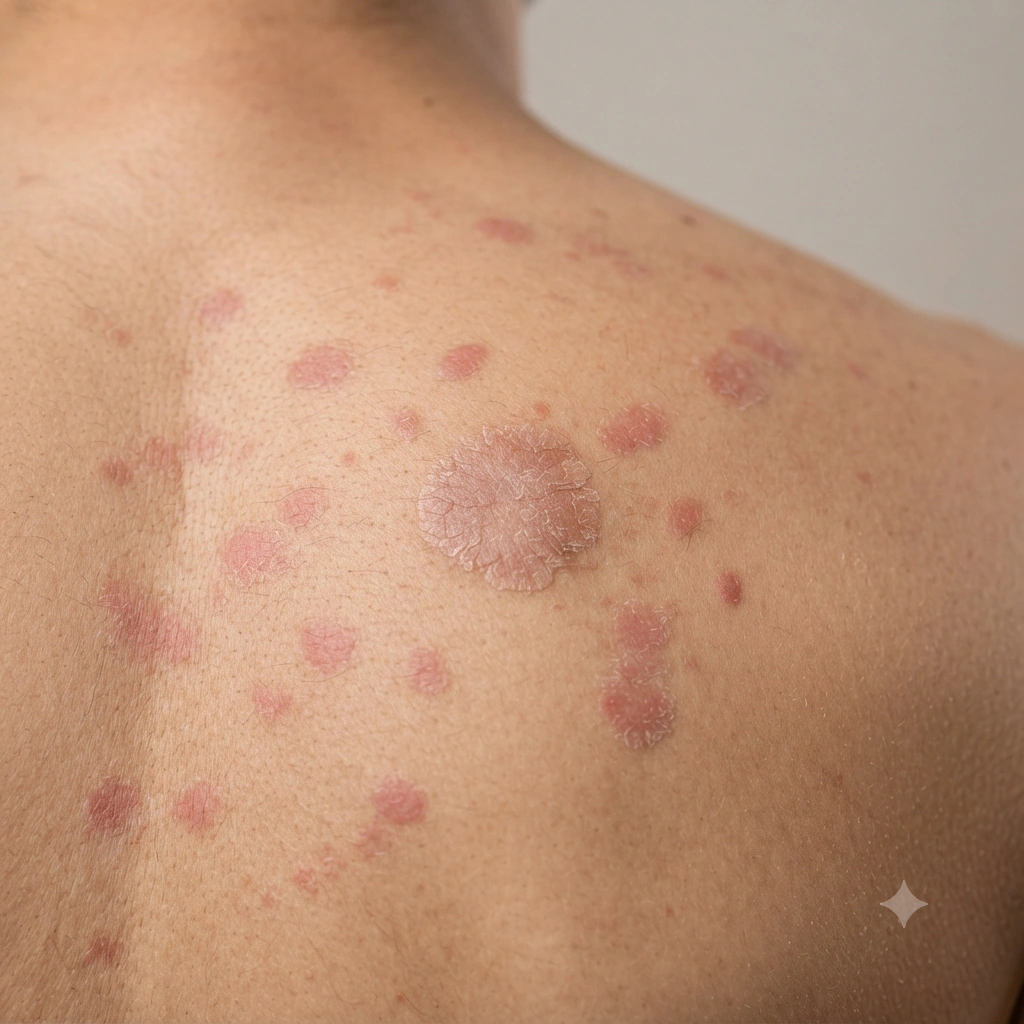
Tanned upper back on medium olive skin with pale oval patches standing out against the tan, some still carrying a fine surface scale and some merging into larger shapes.
Flat oval patches several shades lighter than the surrounding brown skin, spread across an upper back and merging into larger shapes, with a grayish ashy scale on the surface.
Widespread pale oval patches across an upper back and shoulders on deep brown skin, standing out strongly against the surrounding skin, with a fine scale on the newer ones.
Diagram
Tinea Versicolor mechanism diagram. Yeast grows at the surface: Malassezia normally lives on the skin. Pigment balance changes: Affected patches can look lighter or darker. Fine scale develops: The outer layer sheds in tiny flakes.
In the skin

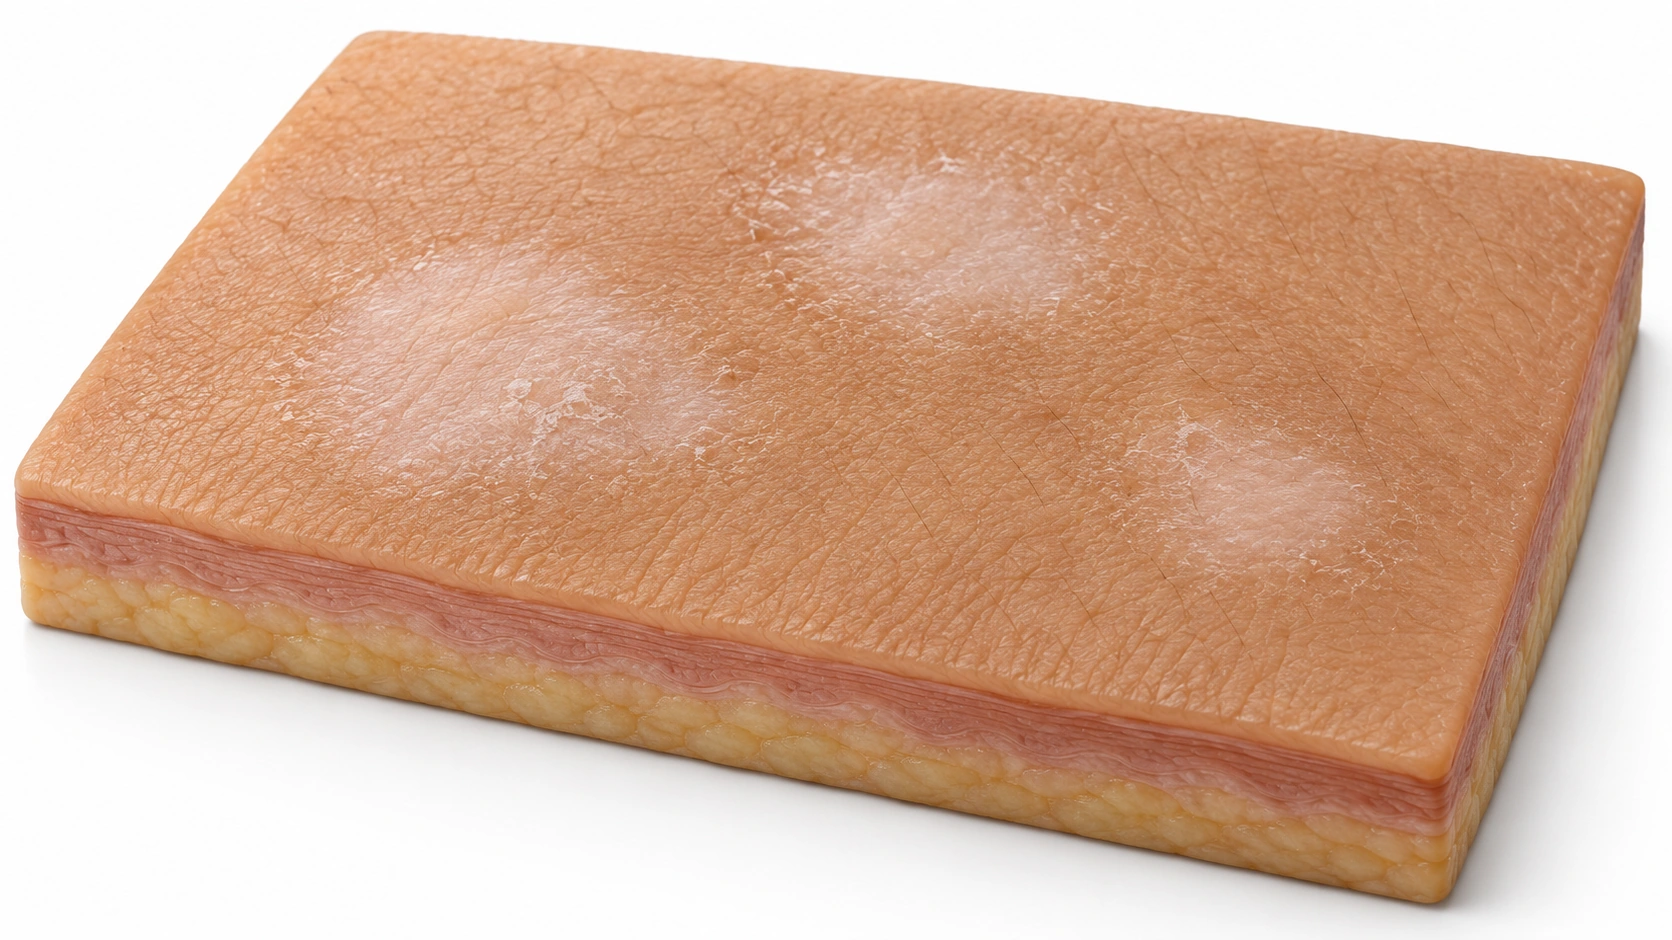
Immune inflammation accelerates skin-cell production and shedding. Small, scattered scaly patches develop; the rash itself is not contagious.

Malassezia yeast overgrows in the outer skin and disturbs the usual pigment balance. Affected areas develop fine scale and may look lighter or darker than surrounding skin.

When it usually starts

010203040506070+

Guttate Psoriasis. Most often starts in children or young adults after an infection.

Tinea Versicolor. Most common in adolescents and young adults, especially in warm humid climates.

Causes and triggers

Causes

Immune inflammation speeds skin-cell turnover; psoriasis is not contagious.

Tinea versicolor is an overgrowth of Malassezia, a yeast that normally lives on the skin. The yeast interferes with pigment, leaving lighter or darker patches.

Family tendency

It tends to run in families.

Risk factors
Recent streptococcal infection, Family tendency
Teens and young adults, Oily skin, Weakened immunity
Trigger
● Guttate Psoriasis
● Tinea Versicolor
Streptococcal infection
Can contribute
Not listed
Skin injury
Can contribute
Not listed
Hot, humid weather
Not listed
Well established
Heavy sweating
Not listed
Strong link
Oily skin products
Not listed
Possible

Daily Care

Guttate Psoriasis
Tinea Versicolor
Daily care

Habits that help

  • Moisturize regularly with a plain fragrance-free product
    Apply after washing and when skin feels dry or tight.
  • Keep washing gentle and water lukewarm
    Use a non-soap cleanser and pat dry rather than rubbing.
  • Protect sore skin from friction and minor injury
    Comfortable clothing and gentle handling reduce avoidable irritation.
  • Keep a manageable record of flares and symptoms
    Note new medicines, infections or joint symptoms to discuss at review.
  • Report a recent sore throat or signs of infection
    Assessment may be needed; skin moisturization does not treat an active throat infection.
  • Follow the guttate psoriasis care plan
    Use bland moisturizer, avoid rubbing and follow a site-appropriate treatment plan.

Avoid

  • Avoid: Picking scale or scratching plaques
    Injury can worsen psoriasis and create breaks in the skin.
  • Avoid: Unsupervised tanning or harsh home exfoliation
    Sunburn and irritation can trigger worsening; prescribed phototherapy is different from tanning.

Habits that help

  • Shower and change promptly after sweating
    Less time damp, less time in the yeast's conditions.
  • Lighter, non-oily products
    On the chest, back and shoulders, sunscreen included.
  • Loose, breathable clothing in hot weather
    Cotton and looser fits over synthetics.
  • Daily sunscreen on the affected areas
    Stops the surrounding skin darkening further.
  • Take a photograph when you start
    The color changes too slowly to see day to day.
  • Leave the patches alone
    The color is not on the surface; it recovers on its own.
  • Antifungal creams for limited areas
    Fine on a small area, impractical across a back.
  • Reduce prolonged heat and dampness when possible
    The clearest pattern there is — it returns every summer.
  • Discuss flares associated with pregnancy or hormonal changes
    Linked to flares, through oil production.

Avoid

  • Avoid: Heavy sweating
    Damp clothing keeps skin in the state the yeast prefers.
  • Avoid: Body oils and rich lotions
    Malassezia feeds on the fats in many oils.
  • Avoid: Occlusive synthetic clothing
    Holds sweat and heat against the trunk.
  • Avoid: Sun exposure while the patches are pale
    They do not tan, so the difference gets obvious.
  • Avoid: Deliberately tanning to even it out
    It widens the gap.
  • Avoid: Scrubbing the patches
    Nothing for the color, and irritated skin recovers slower.
  • Avoid: Skin-lightening or bleaching products
    They do not fix the mismatch, and many contain undisclosed strong steroids.
  • Avoid: Stopping after a single course
    The yeast is permanent, and in a hot climate it regrows within months.
  • Avoid: Judging the treatment at two weeks
    Why people cycle through four products when the first already worked.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Guttate Psoriasis
● Tinea Versicolor
Over-the-counter
None listed
Ketoconazole shampoo.

Ketoconazole shampoo

Strong evidence

The usual first choice, used as a body wash rather than on the hair. Lather it over the chest, back and shoulders, leave it on for about five minutes so it has contact time, then rinse, daily for one to two weeks. Contact time matters more than strength here — the 1% is on the shelf and the 2% is on prescription, and people who rinse straight off usually conclude it did not work.


Illustration: Generic oral tablet bottle and tablets.

Terbinafine cream, not the tablets

Moderate evidence

The cream works well on a small number of patches, applied twice a day for a couple of weeks, but covering a whole back with it is impractical and expensive. The tablets are the odd exception in this condition. They clear athlete's foot and ringworm and do nothing at all here, because this is a yeast rather than the fungi those tablets are built for.

Illustration: Generic topical cream tube and white cream.

Skin-lightening creams

Limited evidence

Sold for evening out patchy skin, and the wrong tool here, because the problem is a patch that is too light rather than skin that is too dark. They do not speed the pigment up. Creams bought without a prescription are also a common source of undisclosed strong steroids, which thin the skin over time. The patches recover on their own once the yeast is controlled.

Two Selsun Blue bottles, two Head and Shoulders Clinical Strength bottles and a Vichy Dercos bottle and box

Selenium Sulfide

Strong evidence

Just as effective as ketoconazole for this and usually cheaper, spread over the affected area, left on for five to ten minutes and washed off. It has a noticeable sulfur smell that lingers, and it can discolor fabric and light hair, so old clothes and a thorough rinse are worth planning for.

Four dandruff shampoo bottles: DHS Zinc, Head and Shoulders Classic Clean, CeraVe Anti-Dandruff and Head and Shoulders Bare

Pyrithione Zinc

Limited evidence

A gentler wash, better suited to keeping this away than to clearing a flare. It is the one most people find easy enough to keep using twice a month right through the summer, which is the part that actually prevents the next episode. On a widespread flare it is slower than ketoconazole or selenium sulfide.

Prescription topicals
None listed
Illustration: Generic topical cream tube and white cream.

Prescription antifungal creams

Listed

Ciclopirox, econazole or ketoconazole 2% cream, applied to the patches for two to four weeks. They are a reasonable choice when only a small area is involved, or when a medicated wash has irritated the skin. Across a whole back they are expensive and hard to apply properly, which is the point at which tablets are the sensible option.

Prescription pills
None listed
Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Moderate evidence

The usual tablet when the area is too large to treat by hand or topical treatment has genuinely failed, given as a short course of a few days. It clears the yeast quickly and does nothing to speed up the color, which still takes months. It interacts with a long list of other medicines, so the prescriber needs your full list.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Moderate evidence

The other short-course tablet, sometimes given as a single dose repeated a week later. It works about as well as itraconazole for a widespread rash. Neither tablet stops it coming back, so the monthly wash is still the plan afterwards. If you are pregnant or breastfeeding, ask the doctor managing your pregnancy before taking either.

Outlook

Long term

Many episodes clear within about 3–4 months. It can recur, and some people later develop persistent plaque psoriasis; follow-up is useful if spots do not settle.

Tinea versicolor is harmless, and treatment runs in two stages. The infection stops within a week or two; the color takes months longer. Patchy skin is not the same as infected skin.

Complications

Possible complications

Psoriasis can accompany inflammatory joint disease. Report persistent joint stiffness or swelling.

  • It persists and slowly spreads
  • The active infection stops fast
  • Recurrence is the norm rather than the exception
More details

It persists and slowly spreads
Patches merge and cover more of the trunk over months. In temperate climates it often eases in winter and returns each summer.

The active infection stops fast
Within one to two weeks of a proper course the scaling stops and the patches stop expanding. The condition is treated at that point, even though the skin does not look normal.

Recurrence is the norm rather than the exception
A large share of people get it again, particularly in hot climates and in people who sweat heavily. The yeast is permanent, so treatment reduces it rather than removing it, and maintenance — a medicated wash once or twice a month in warm months — keeps most people clear.

When to get help

When to get help

Arrange assessment for a first widespread eruption or a recent sore throat; antibiotics treat confirmed infection rather than reliably clearing the rash.

Seek assessment if the diagnosis is uncertain or treatment fails. Color may take months to normalize after the yeast has been treated.

Common questions

Guttate Psoriasis:What is Guttate Psoriasis?

A sudden crop of small drop-like psoriasis spots, often after a throat infection.

Guttate Psoriasis:What can I do day to day?

Use bland moisturizer, avoid rubbing and follow a site-appropriate treatment plan.

Guttate Psoriasis:When should I get medical advice?

Arrange assessment for a first widespread eruption or a recent sore throat; antibiotics treat confirmed infection rather than reliably clearing the rash.

Tinea Versicolor:Is it contagious?

No. The yeast already lives on essentially everyone's skin. You cannot give it to a partner, a child or a housemate. Whether someone develops the rash depends on their own skin oil, the climate and their own susceptibility.

Tinea Versicolor:Why are the patches still there after I finished the treatment?

Because the color and the infection run on different timelines. Treatment stops the yeast within a week or two; the pigment takes months. Scratch a patch lightly — if fine scale lifts it is still active, and if the skin is smooth and simply a different color, the treatment worked.

Tinea Versicolor:Will it come back?

Most likely, particularly in a hot, humid climate or if you sweat heavily. That is normal behavior, not treatment failure, because the yeast is a permanent resident. A medicated wash once or twice a month through the warm months prevents most recurrences and is far less work than treating a full flare.

Tinea Versicolor:Can I sunbathe to even out the color?

No, and it makes it more obvious. The patches cannot tan, so the surrounding skin darkens and the gap widens. Sunscreen while the pigment recovers works better, along with time.

Tinea Versicolor:Is it the same fungus as athlete's foot?

No. Athlete's foot comes from dermatophytes, picked up from the environment. This comes from Malassezia, a yeast that lives on everyone. That is why terbinafine tablets clear athlete's foot but do nothing for this, even though terbinafine cream helps.

Tinea Versicolor:Do I need tablets?

Not usually — topical treatment clears most cases. Ask about tablets when a large area of the trunk is involved and applying a wash properly is impractical, when it keeps coming back, or when topical treatment has genuinely failed. They clear it faster but do not speed up the color or prevent recurrence, so you still need a maintenance plan.

Sources

Sources and further reading

  1. Guttate psoriasis
  2. DermNet
Dermapedia on YouTube