Vitiligo vs Tinea Versicolor

Vitiligo is a condition where the immune system destroys the cells that give skin its color, leaving smooth white patches. It is not painful, not contagious and not caused by anything you did, and treatment can bring color back to many patches if it is given long enough. Tinea versicolor is a common, harmless rash caused by a yeast that already lives on everyone's skin. It leaves flat, finely scaly patches on the chest, back and shoulders that are lighter, darker or pinker than the skin around them. Treatment clears it quickly, the color takes months to even out, and it often returns in warm weather.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
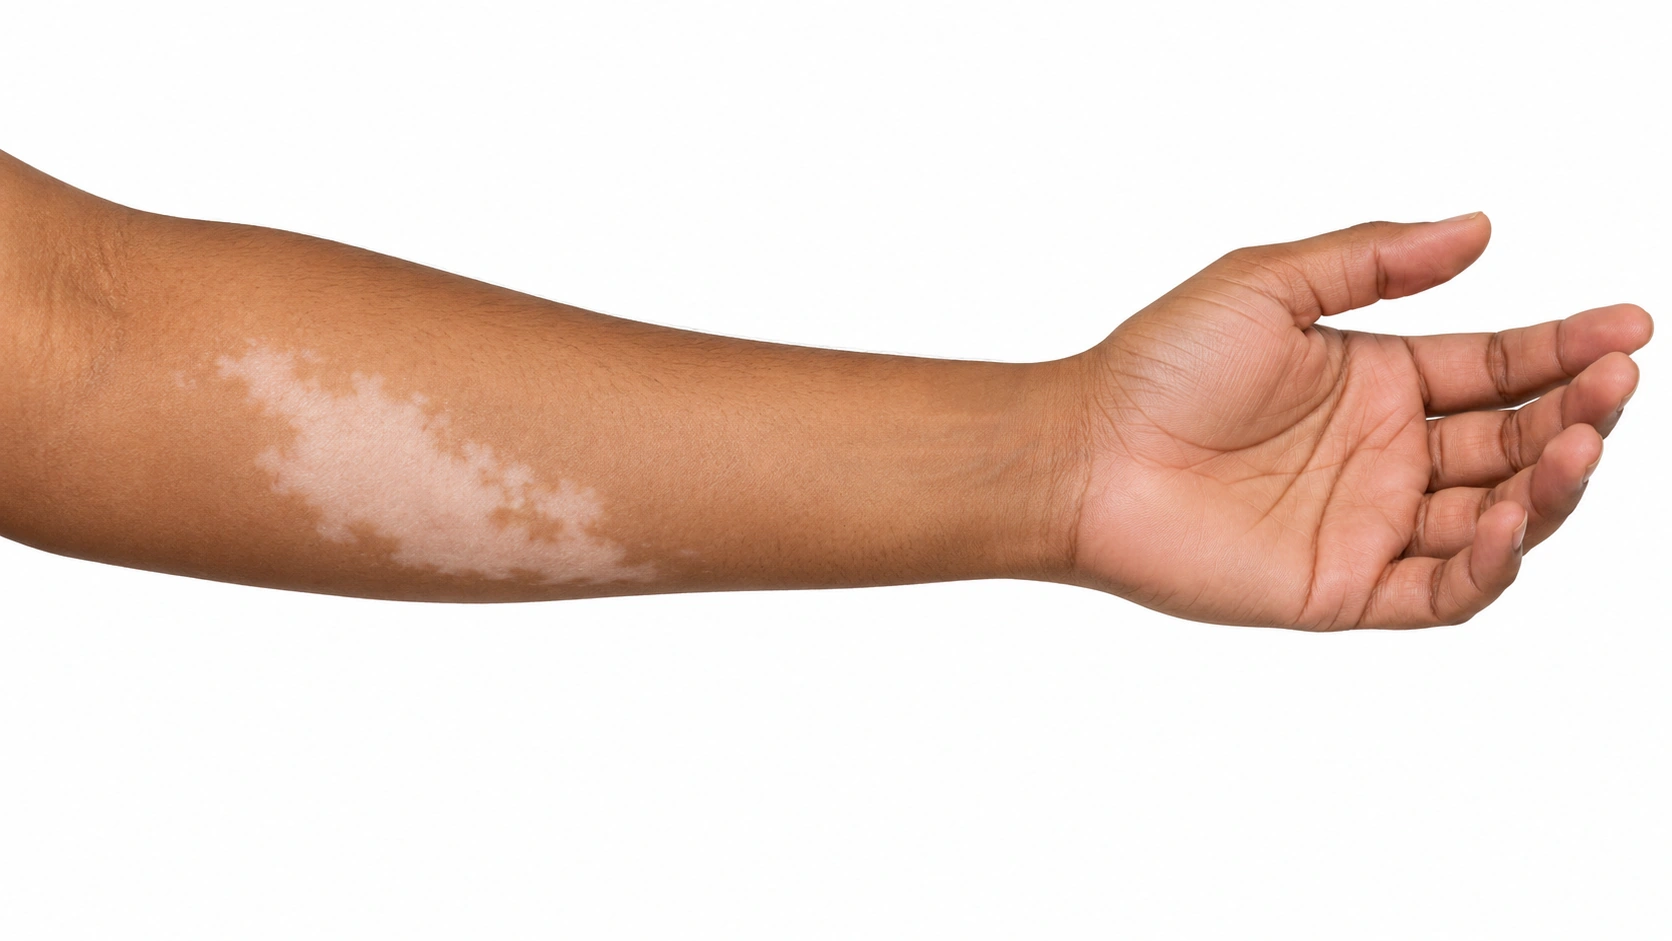
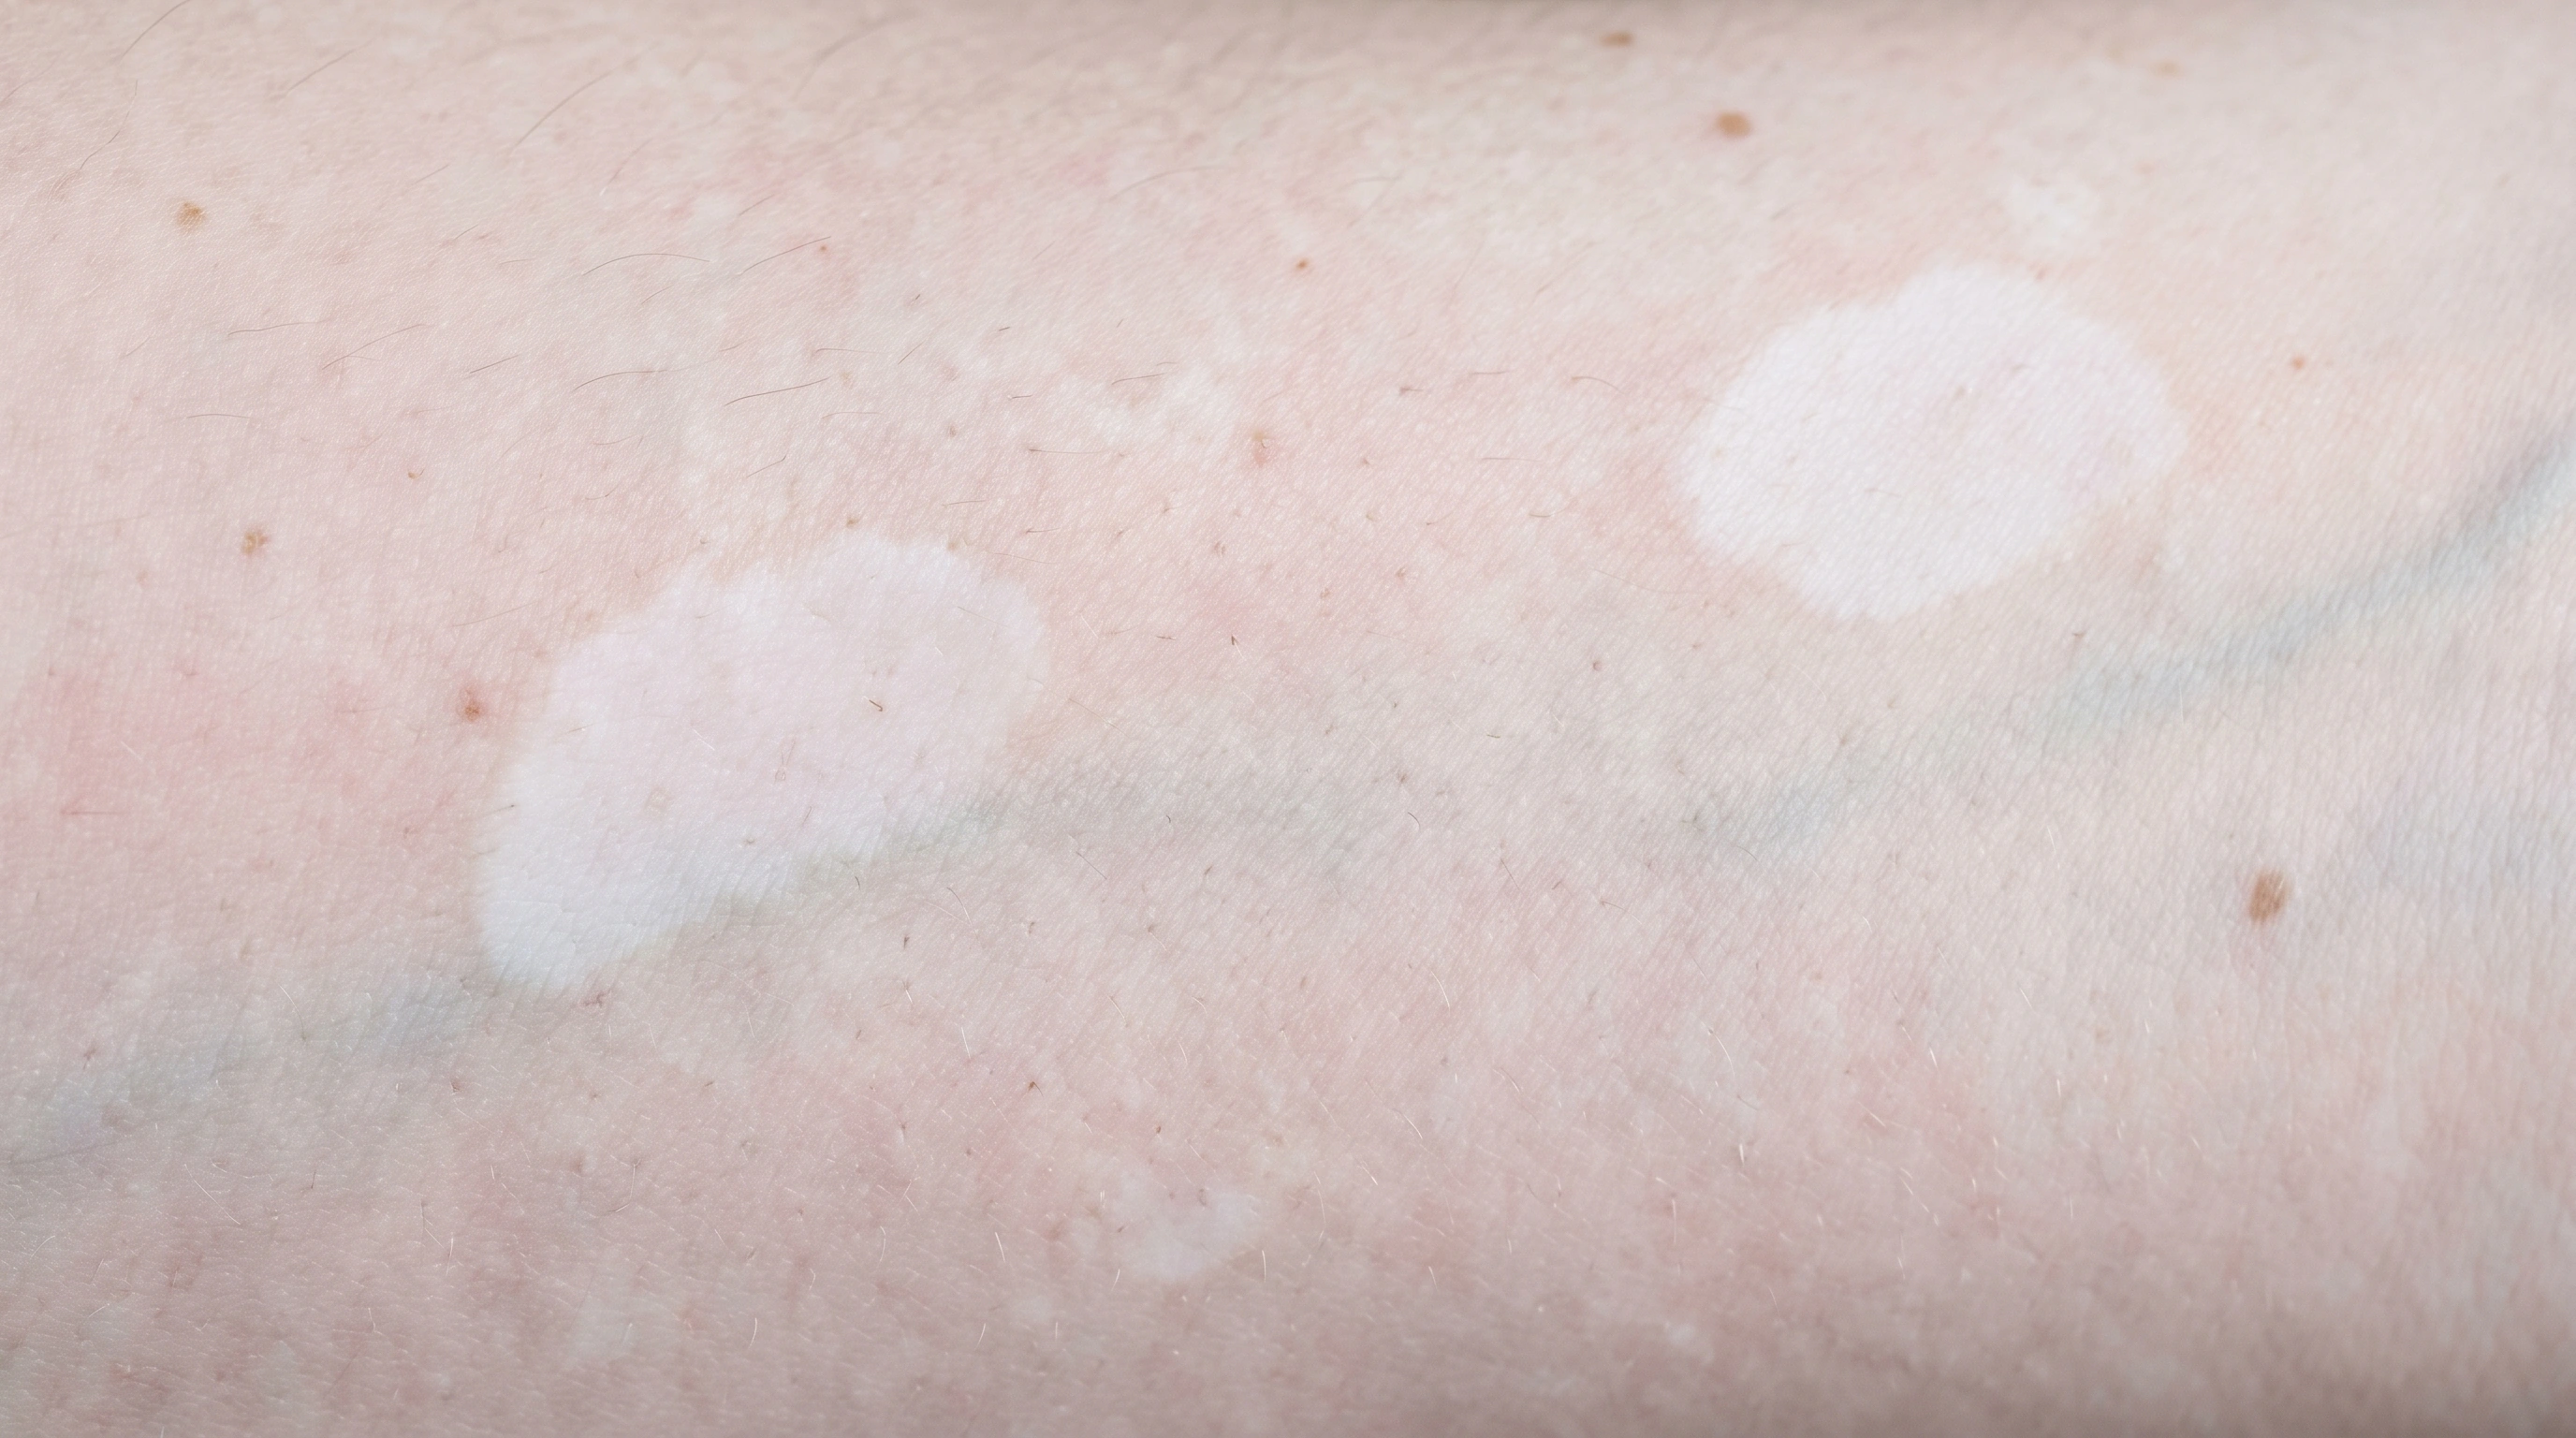
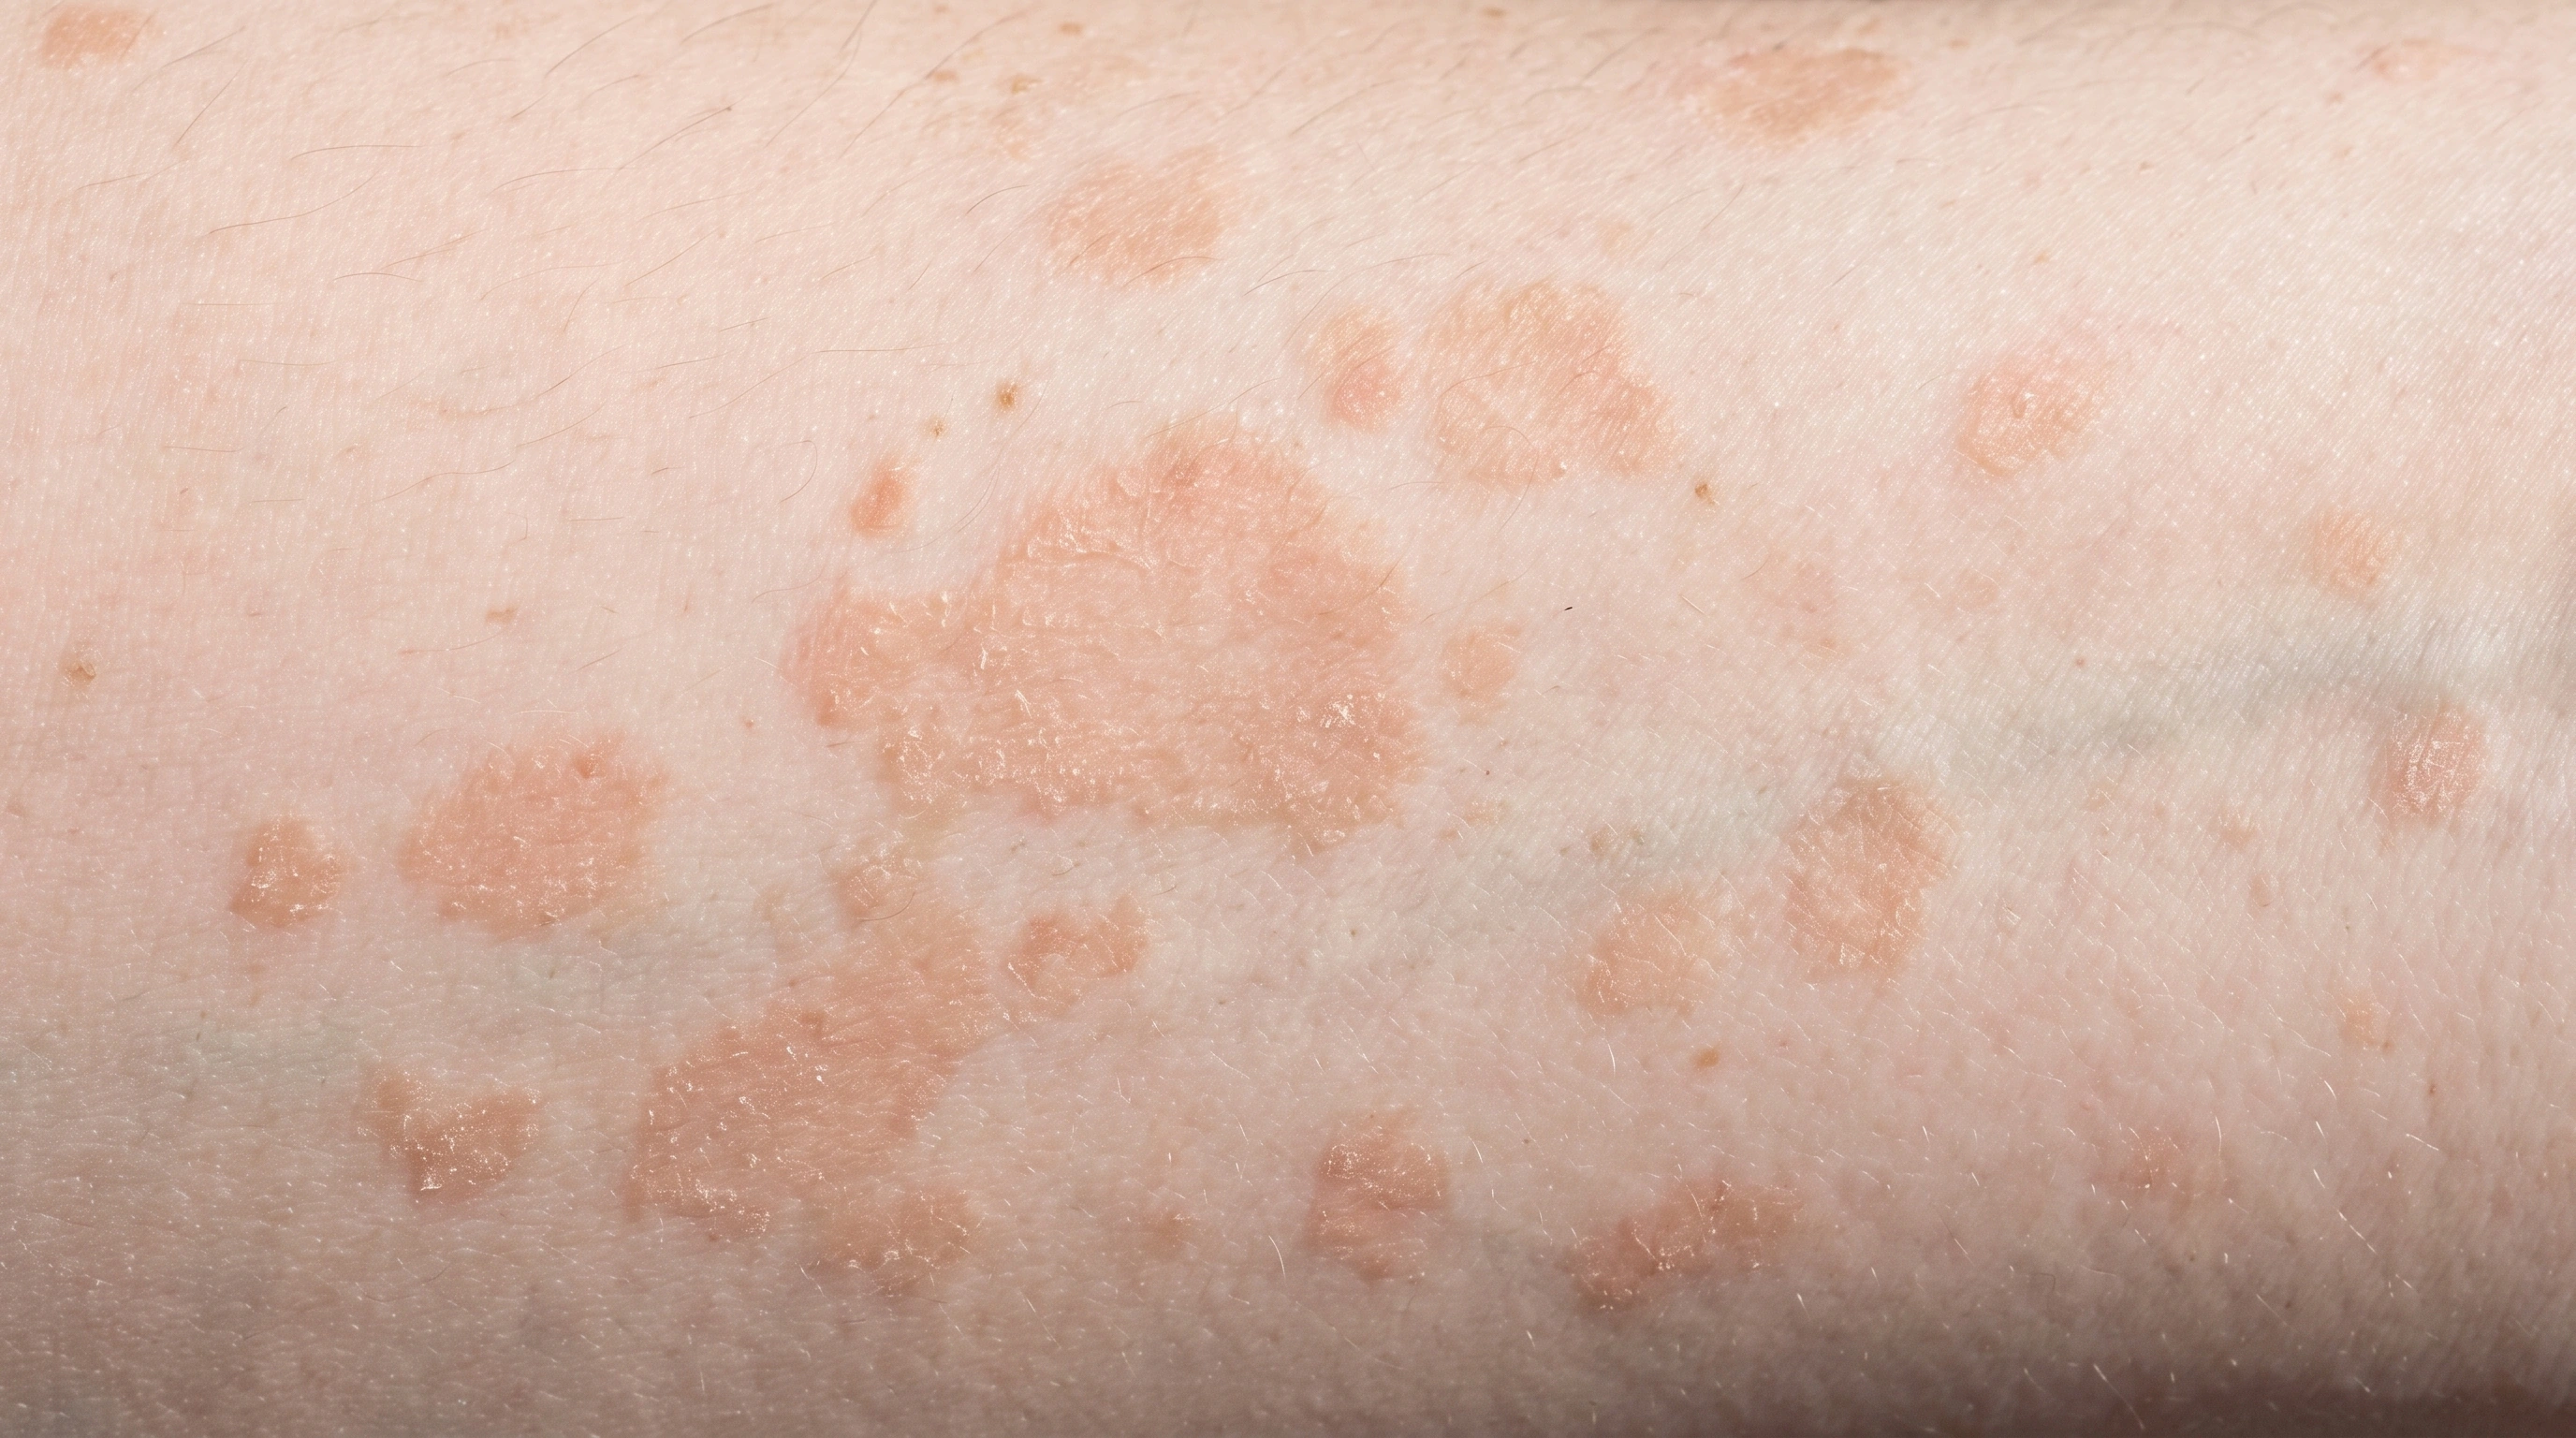
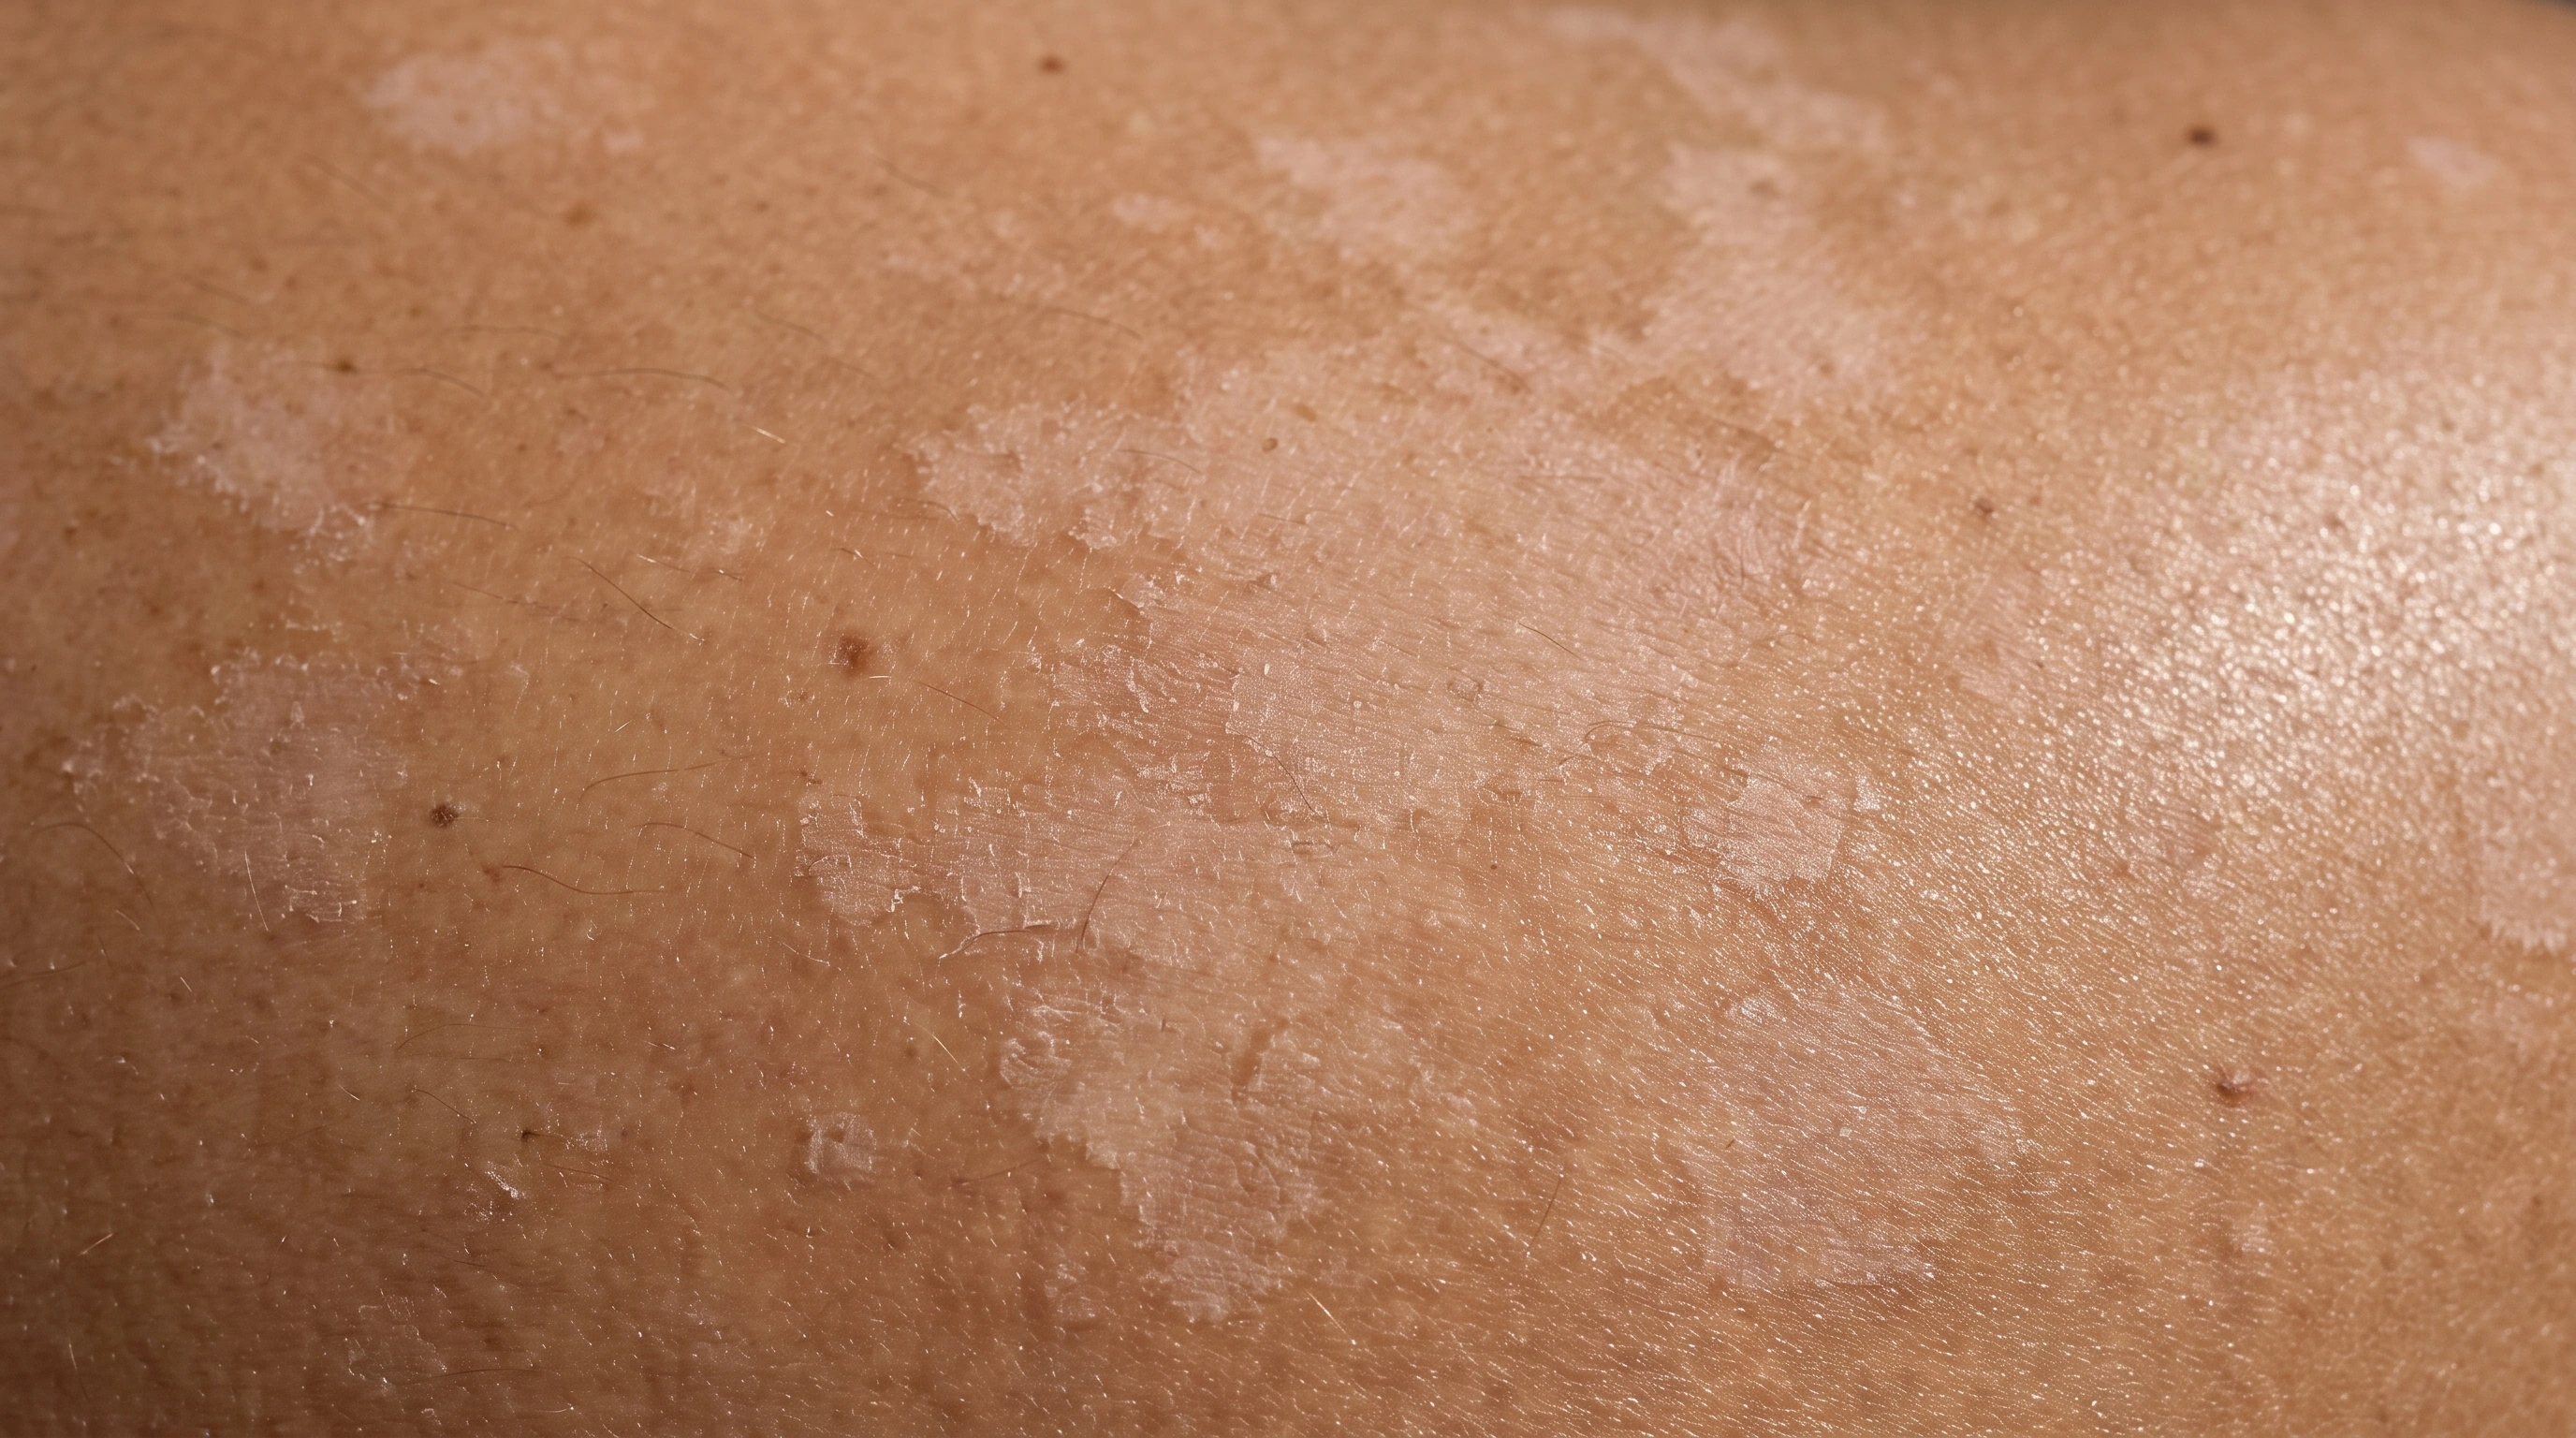
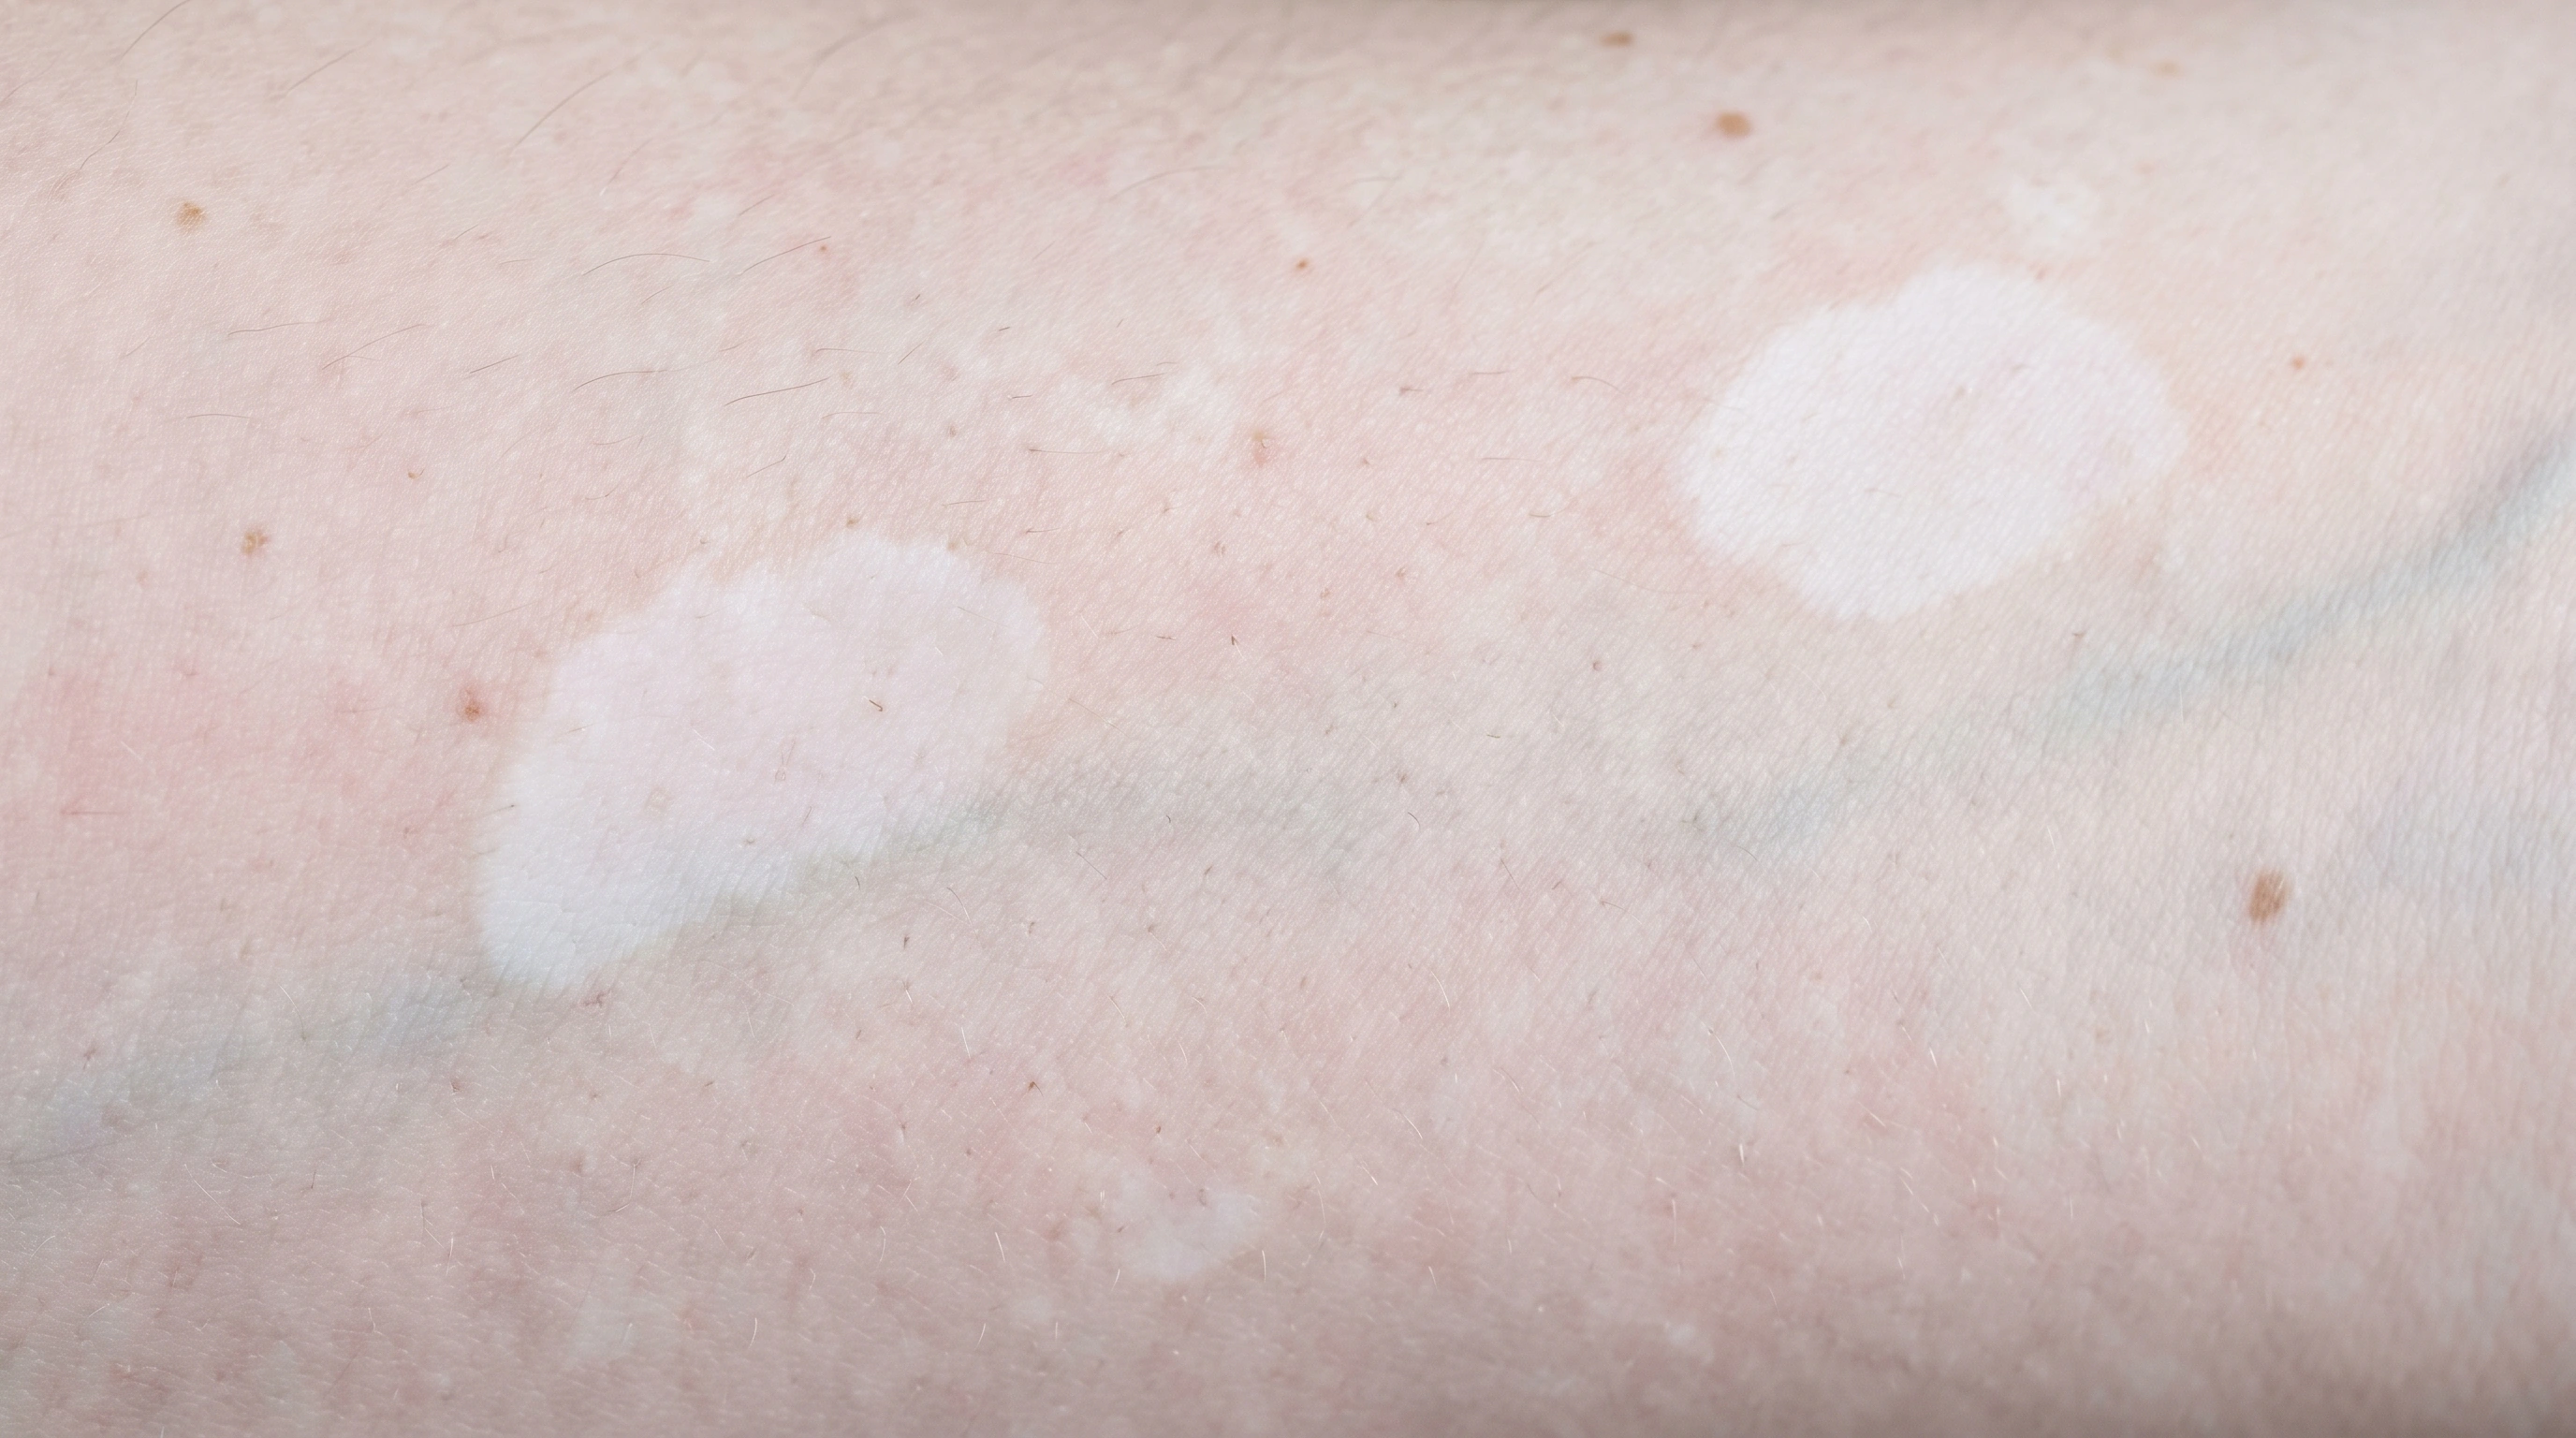
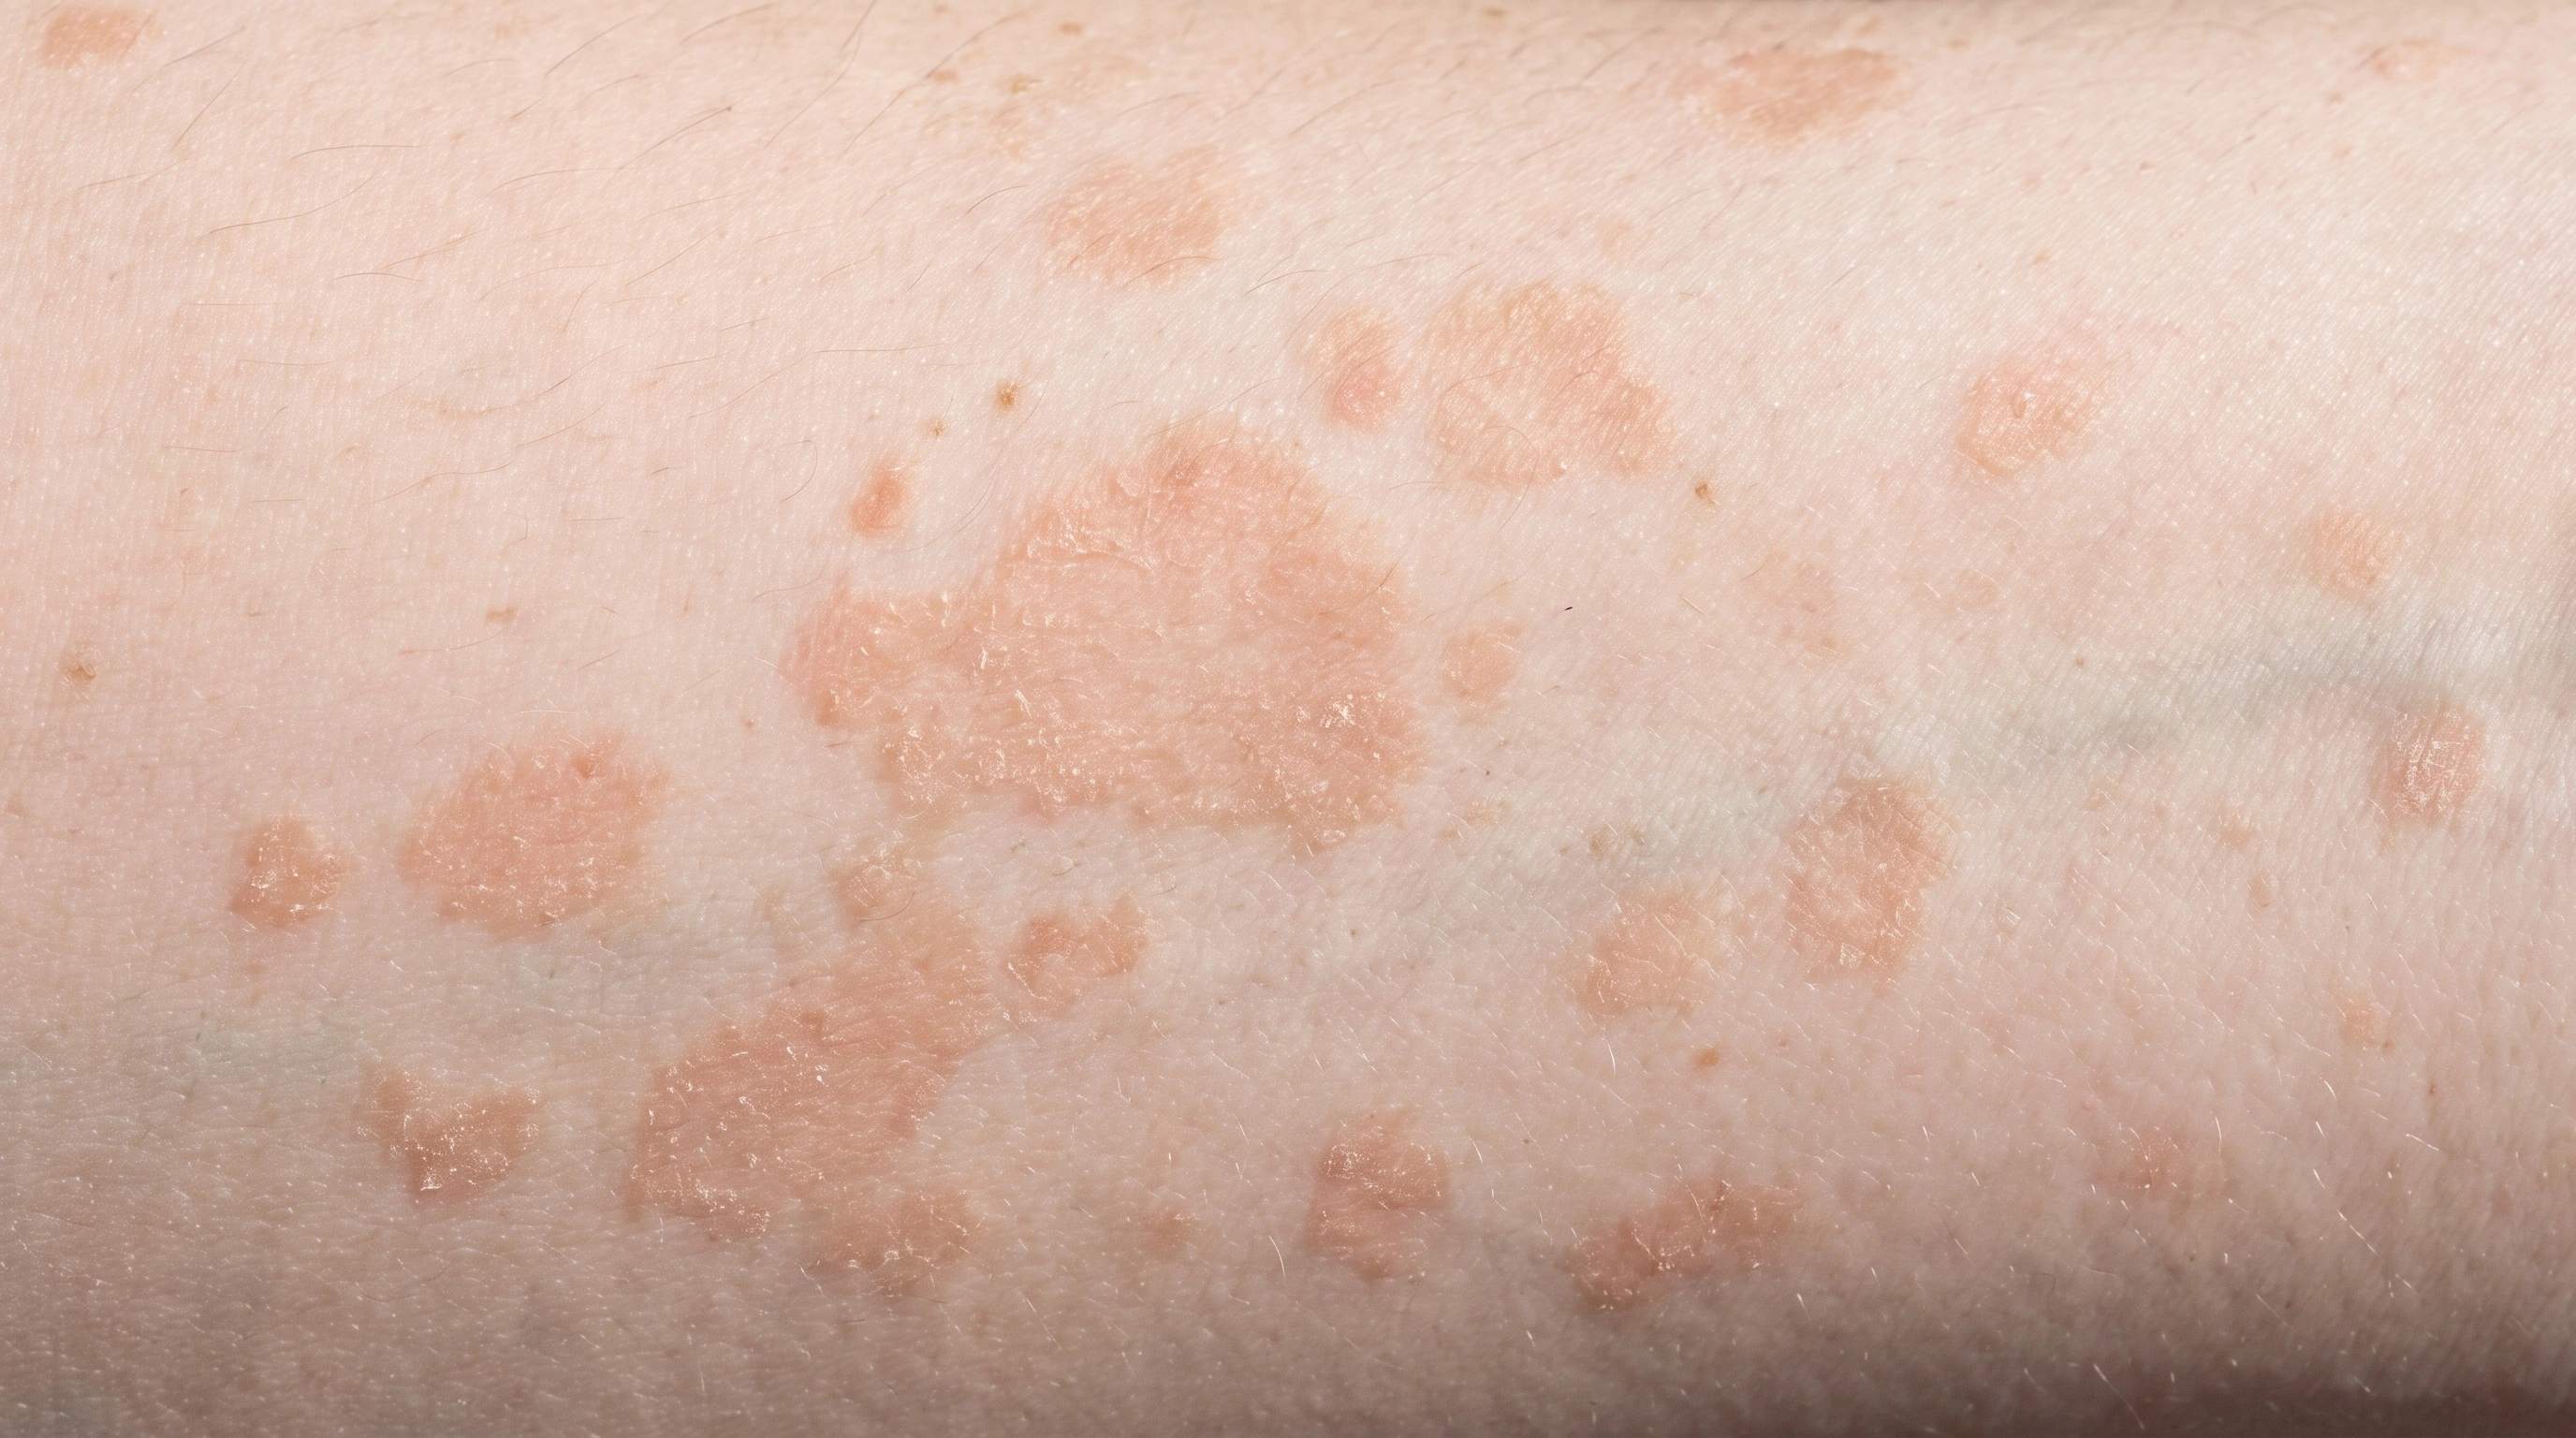
The front of a forearm on fair skin. Two pale patches with sharp edges sit against lightly tanned skin, and the difference between the patch and the skin around it is subtle.Flat oval patches in pink and light tan scattered across an upper chest and shoulder on light skin, several joined into larger areas, with a fine dusty scale on the surface.

Key differences

The same eight facts on every condition comparison.

Usual age
Before 30
15 to 35
Where
Face, hands, folds, around openings
Chest, back, shoulders
Main sign
Smooth chalk-white patches
Lighter or darker fine-scaly patches
Itch or pain
Neither
Mild itch at most
Contagious
No
No
Long term
Long-term; can repigment
Clears fast, often returns
Scars
No
No
Who gets it
About 1 in 100; all skin tones
Teens and young adults; warm climates

What is it?

Vitiligo
Tinea Versicolor
What is it?

It causes loss of pigment.
Defined white patches form when melanocytes are lost or stop working.

It is often autoimmune.
Nonsegmental vitiligo commonly involves autoimmune mechanisms.

Hair can turn white.
White hairs may grow within a patch.

Its impact is real.
The emotional effect can be significant regardless of how much skin is involved.

It is a surface yeast condition.
Also called pityriasis versicolor, it affects only the outer skin layer.

It changes skin color.
Small patches can merge across the upper chest, back, neck or upper arms.

Fine scale is a clue.
Surface scale helps distinguish active disease from other pigment changes.

Color returns more slowly.
Pigment can take longer to even out after the yeast has been treated.

What it looks like

Vitiligo

Similar irregular depigmented patches on both hands, representing non-segmental vitiligo.

Non-segmental vitiligo Patches on both sides; most common.

Representative image of segmental depigmentation. It is not a diagnostic reference or an exact depiction of every subtype, stage or location.

Segmental vitiligo One side or one area only.

A focal depigmented white patch on the back of the hand, representing vitiligo.

Focal vitiligo A few patches in one area.

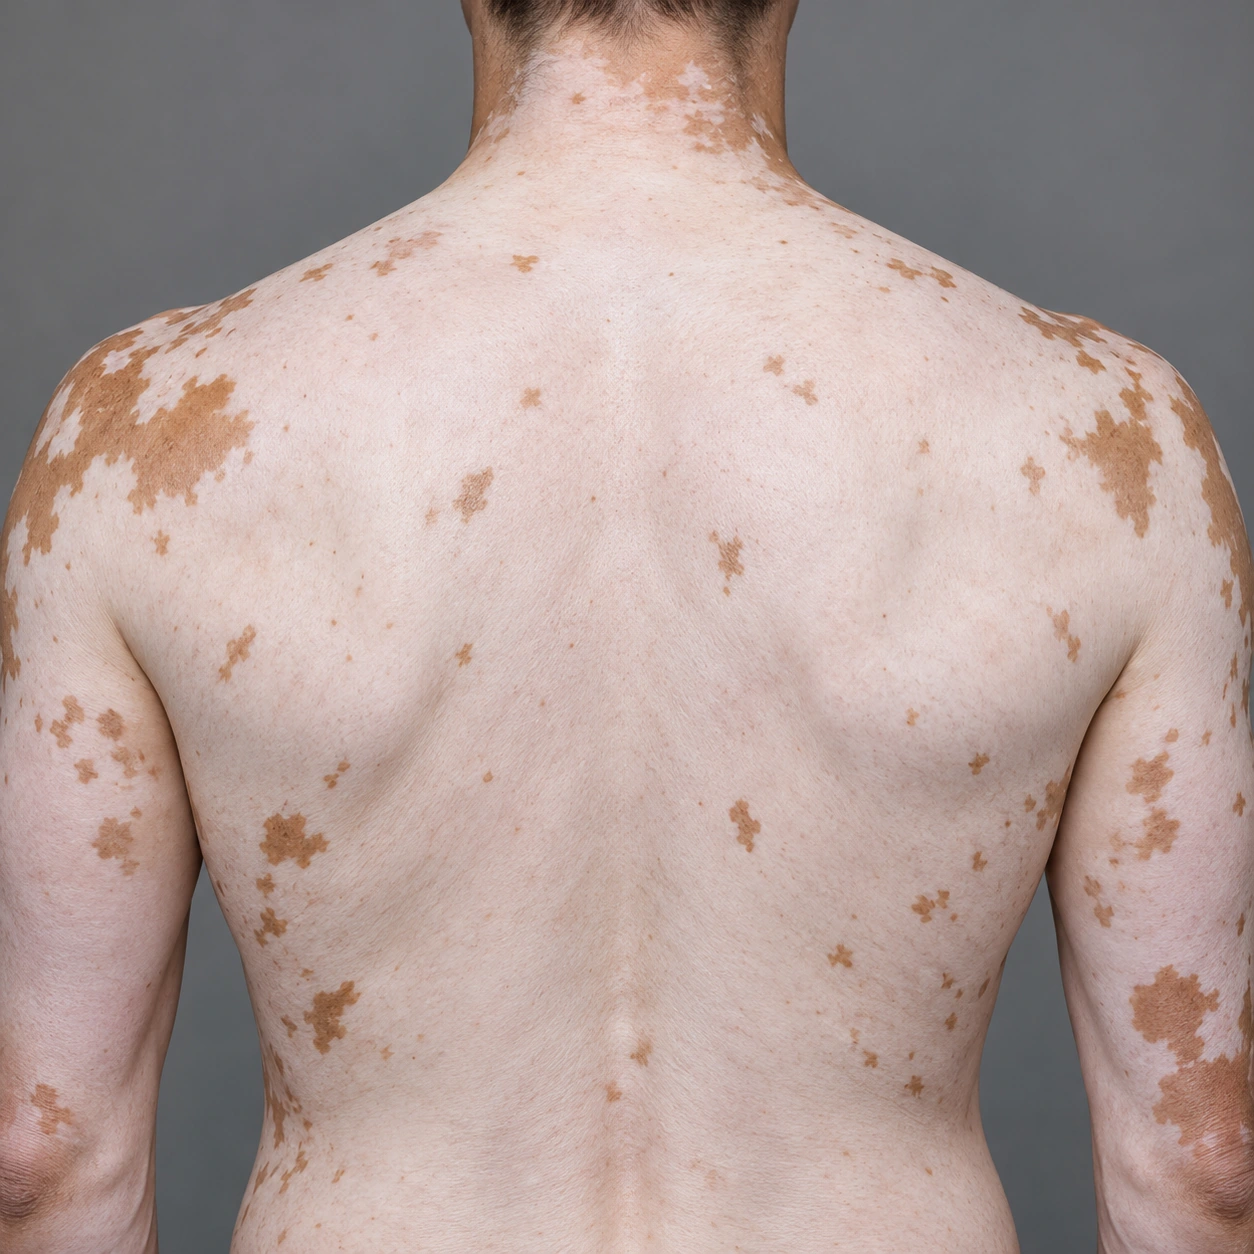
Generated image: Widespread vitiligo covering most of the skin. Not a patient photograph.

Universal vitiligo Generated illustration. Most of the body.

Tinea Versicolor

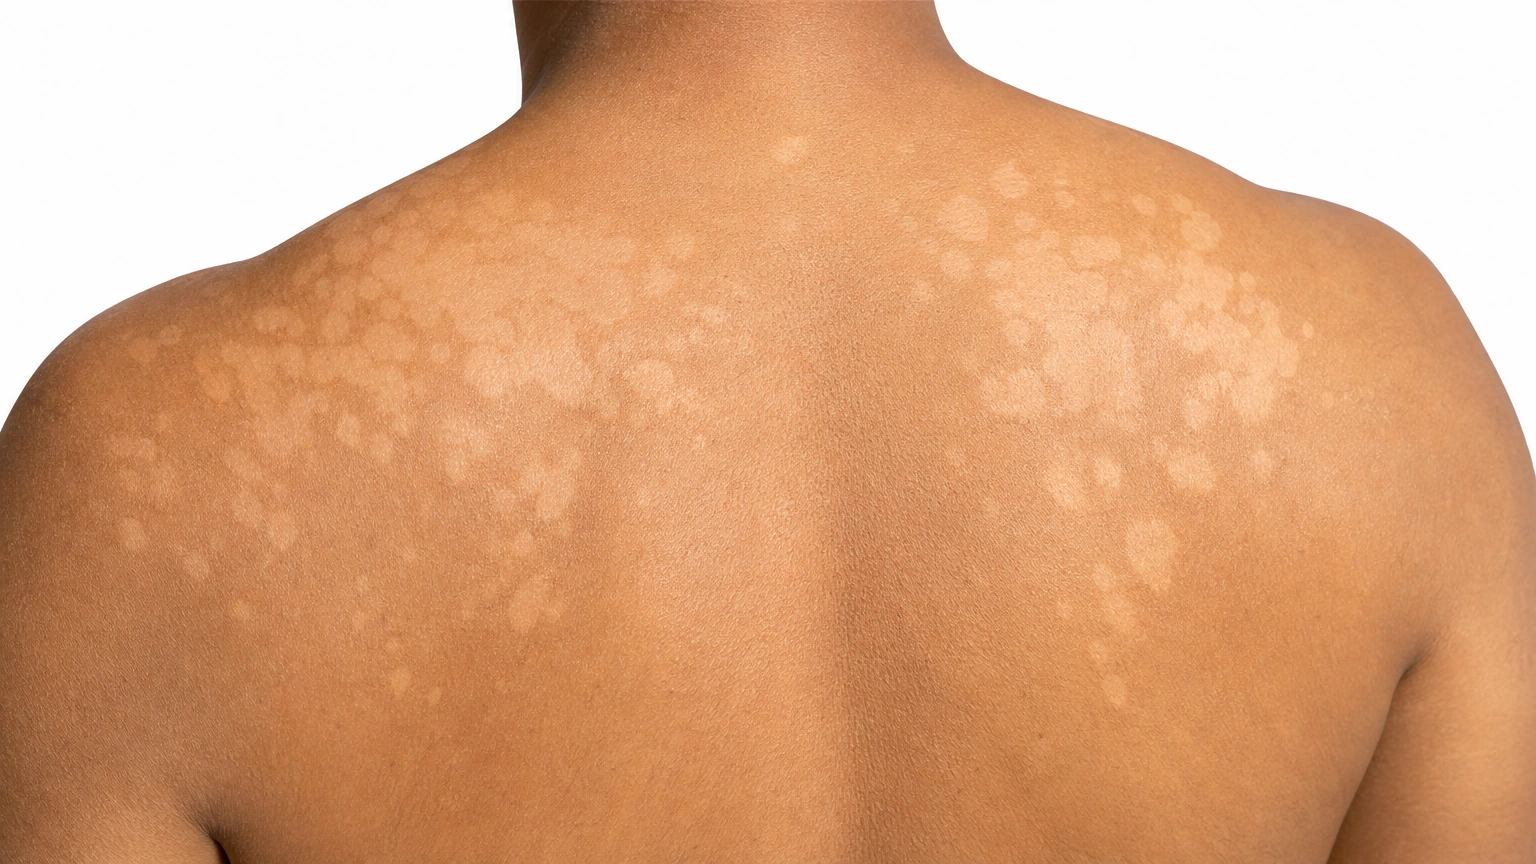
Multiple pale patches over the shoulders and upper back, representing hypopigmented tinea versicolor.

Hypopigmented tinea versicolor Lighter patches; most common.

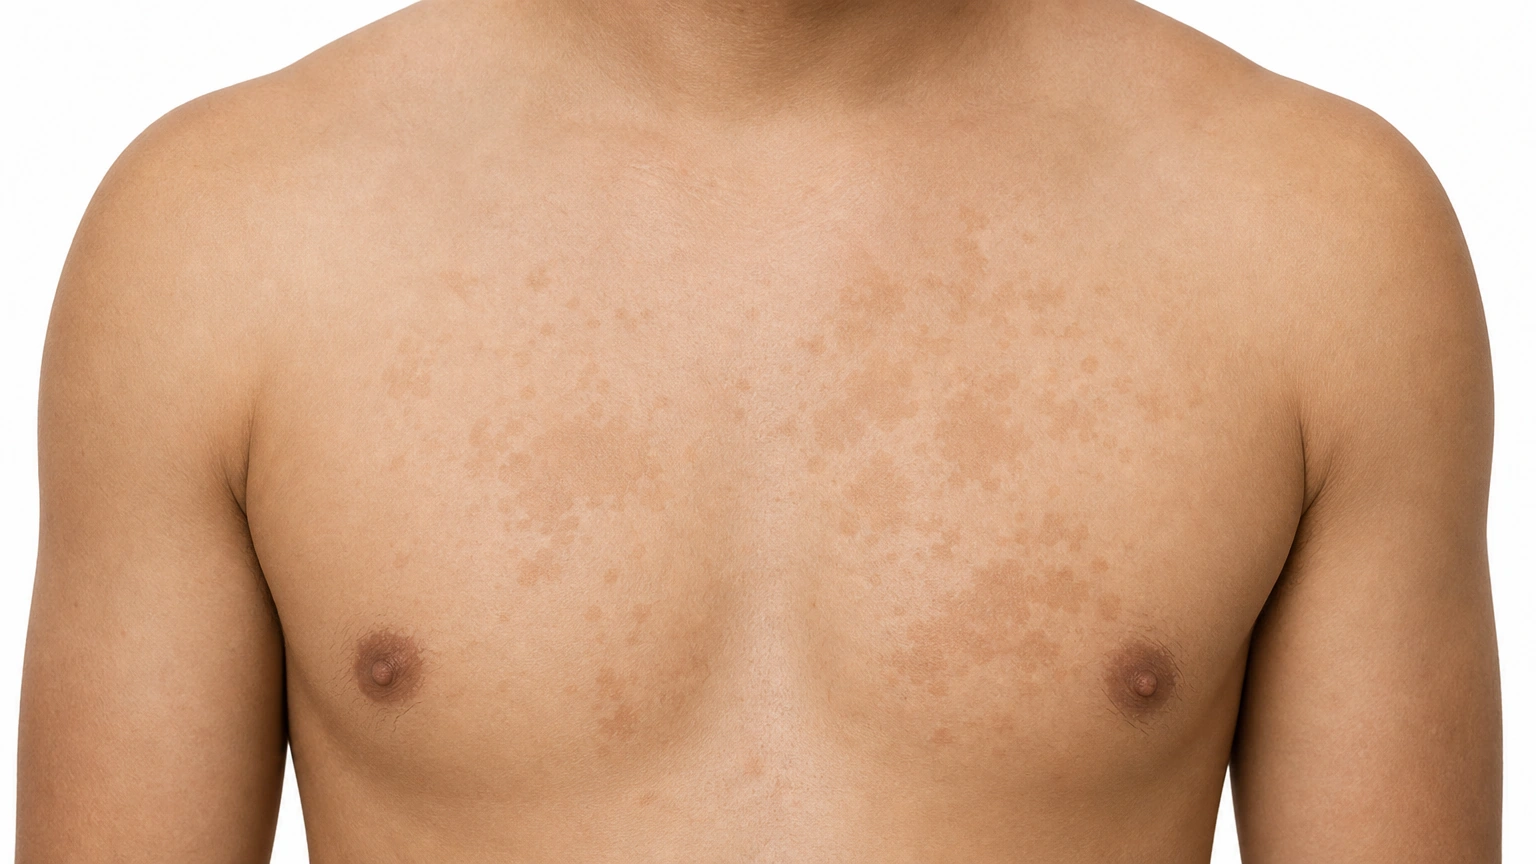
Irregular tan patches on the upper chest, representing tinea versicolor.

Hyperpigmented tinea versicolor Darker or pinkish patches.

Skin tones
The front of a forearm on fair skin. Two pale patches with sharp edges sit against lightly tanned skin, and the difference between the patch and the skin around it is subtle.
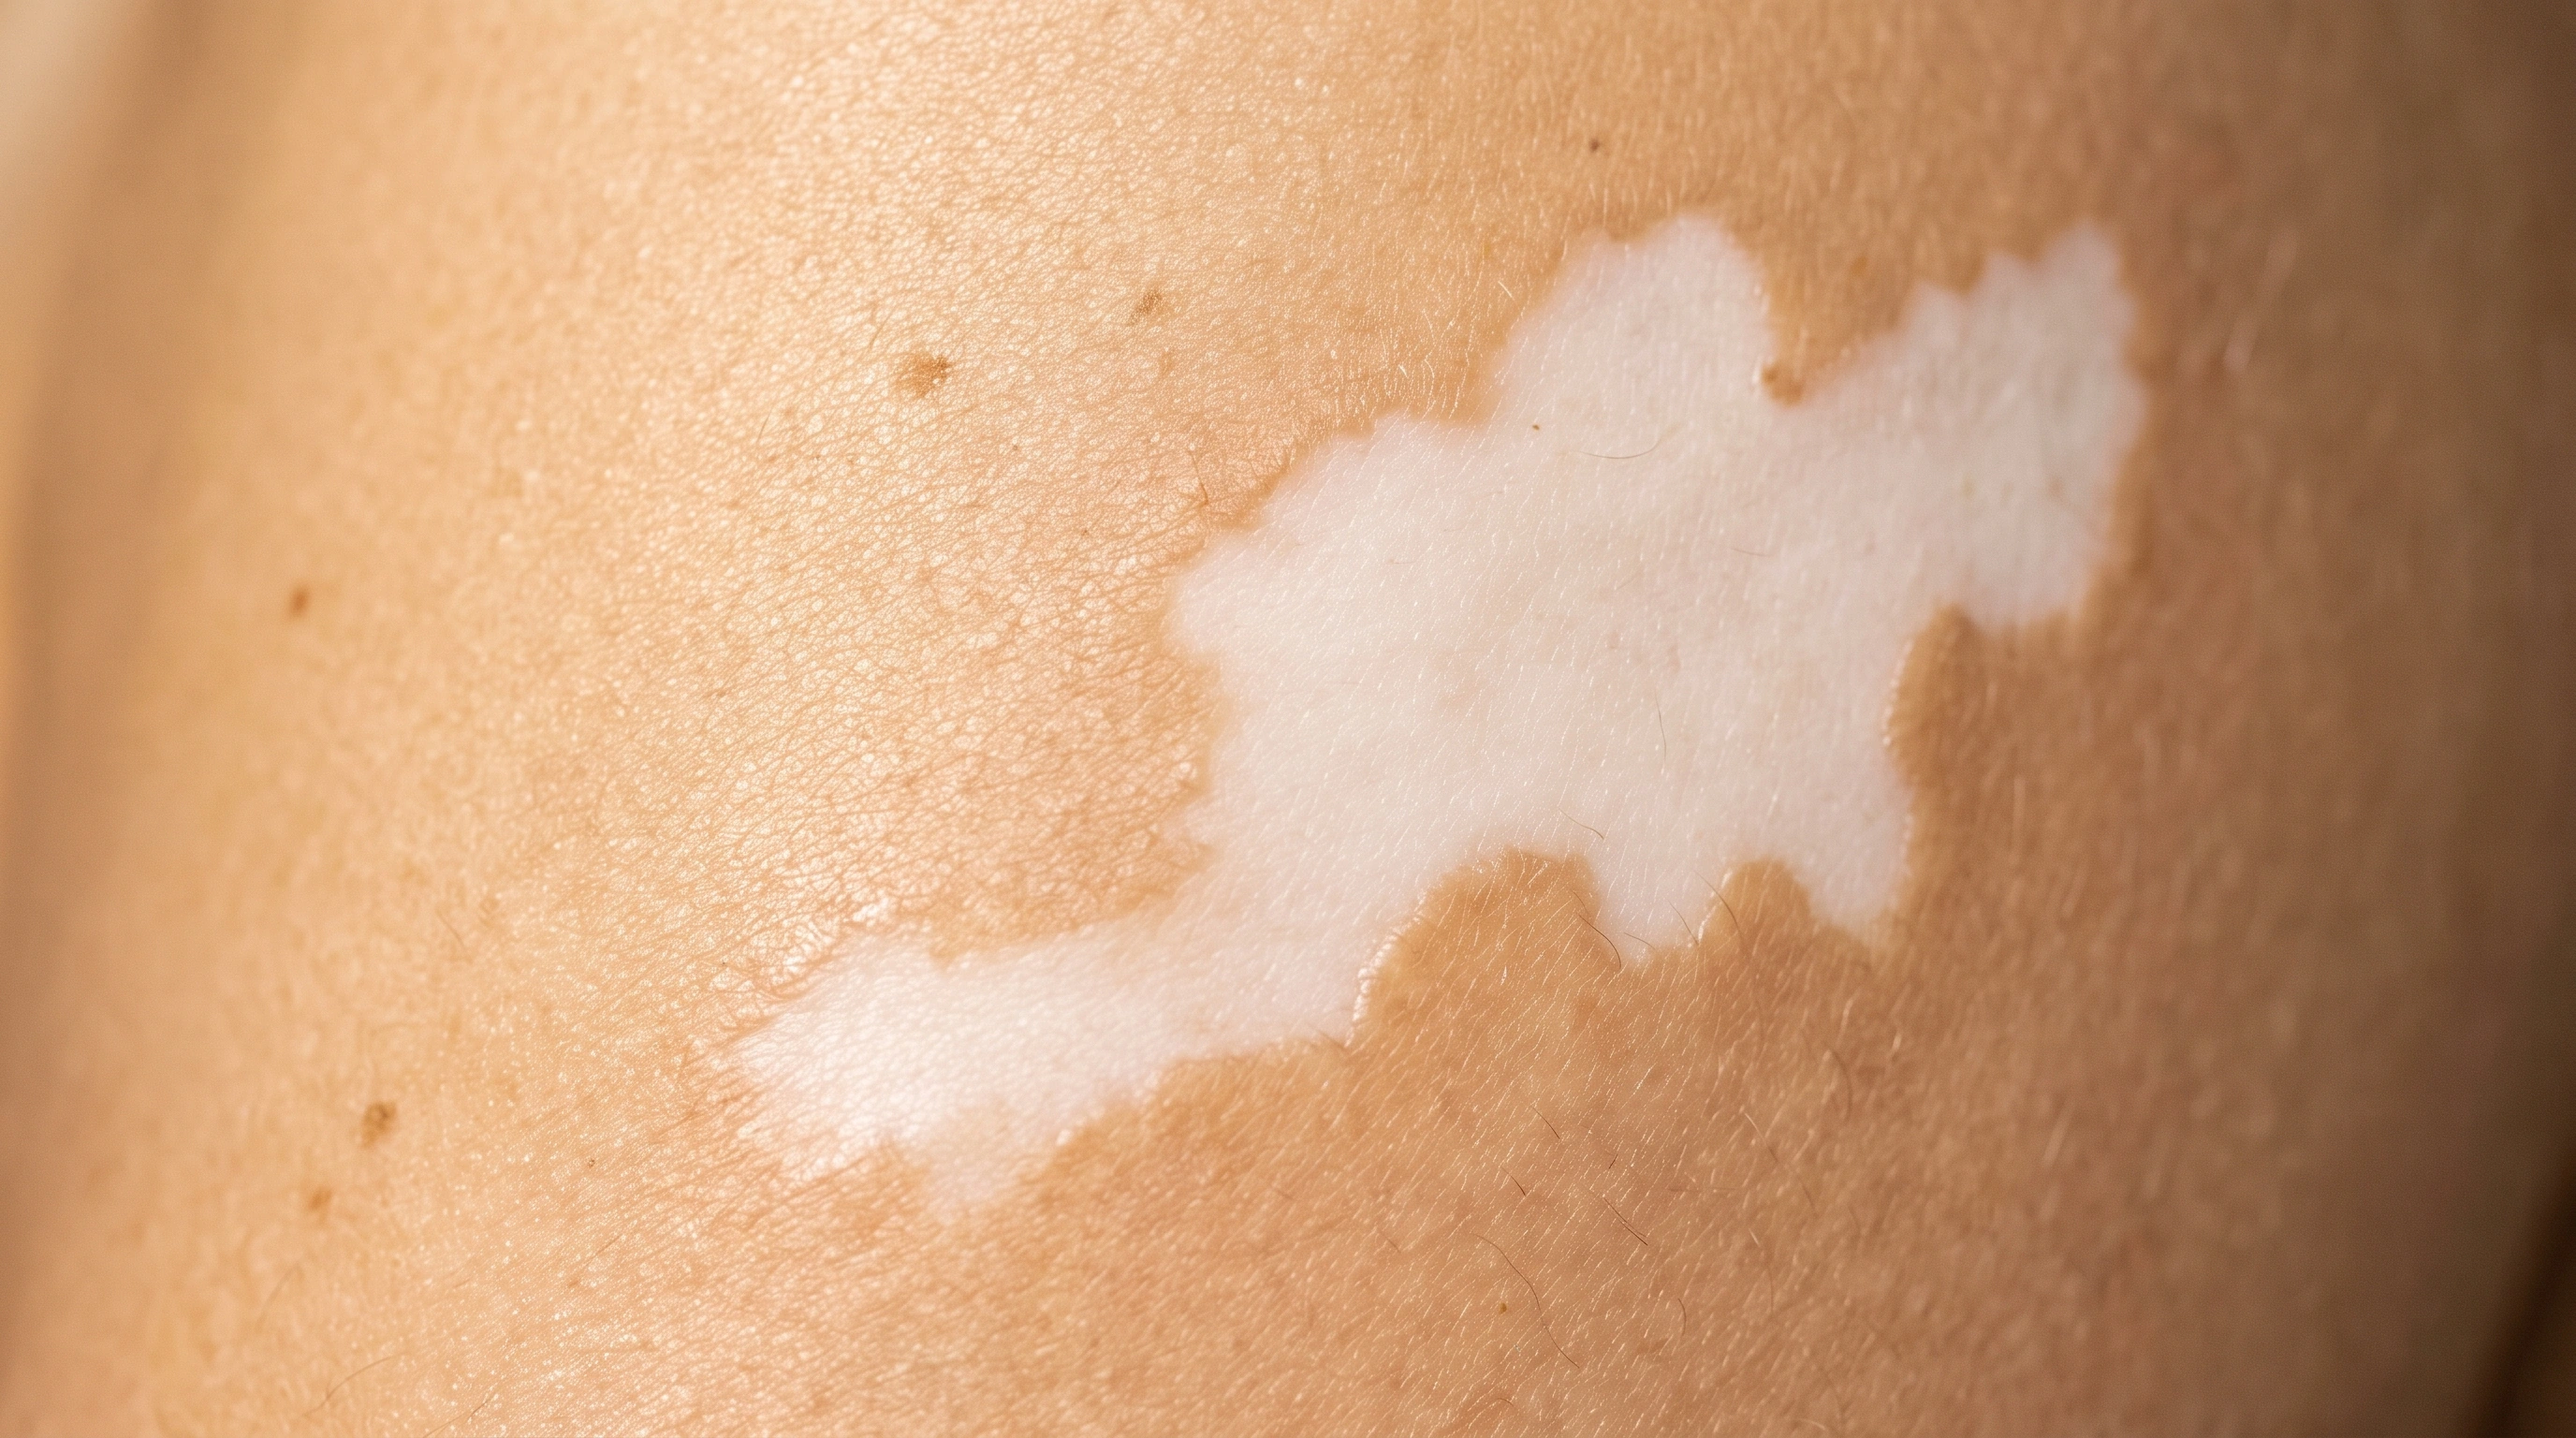
The area around the mouth and chin on medium olive skin. A white patch with a sharp, scalloped border sits above the upper lip and runs onto the chin, with no scale or roughness inside it.
The backs of the fingers and knuckles of one hand on brown skin. Sharp-edged milk white patches cover the knuckles and the sides of two fingers, standing out strongly against the surrounding brown skin.
A white vitiligo patch on the forearm of deep brown skin, with dozens of small dark brown dots appearing inside it around the hair openings and a rim of returning color at the edge.
Flat oval patches in pink and light tan scattered across an upper chest and shoulder on light skin, several joined into larger areas, with a fine dusty scale on the surface.
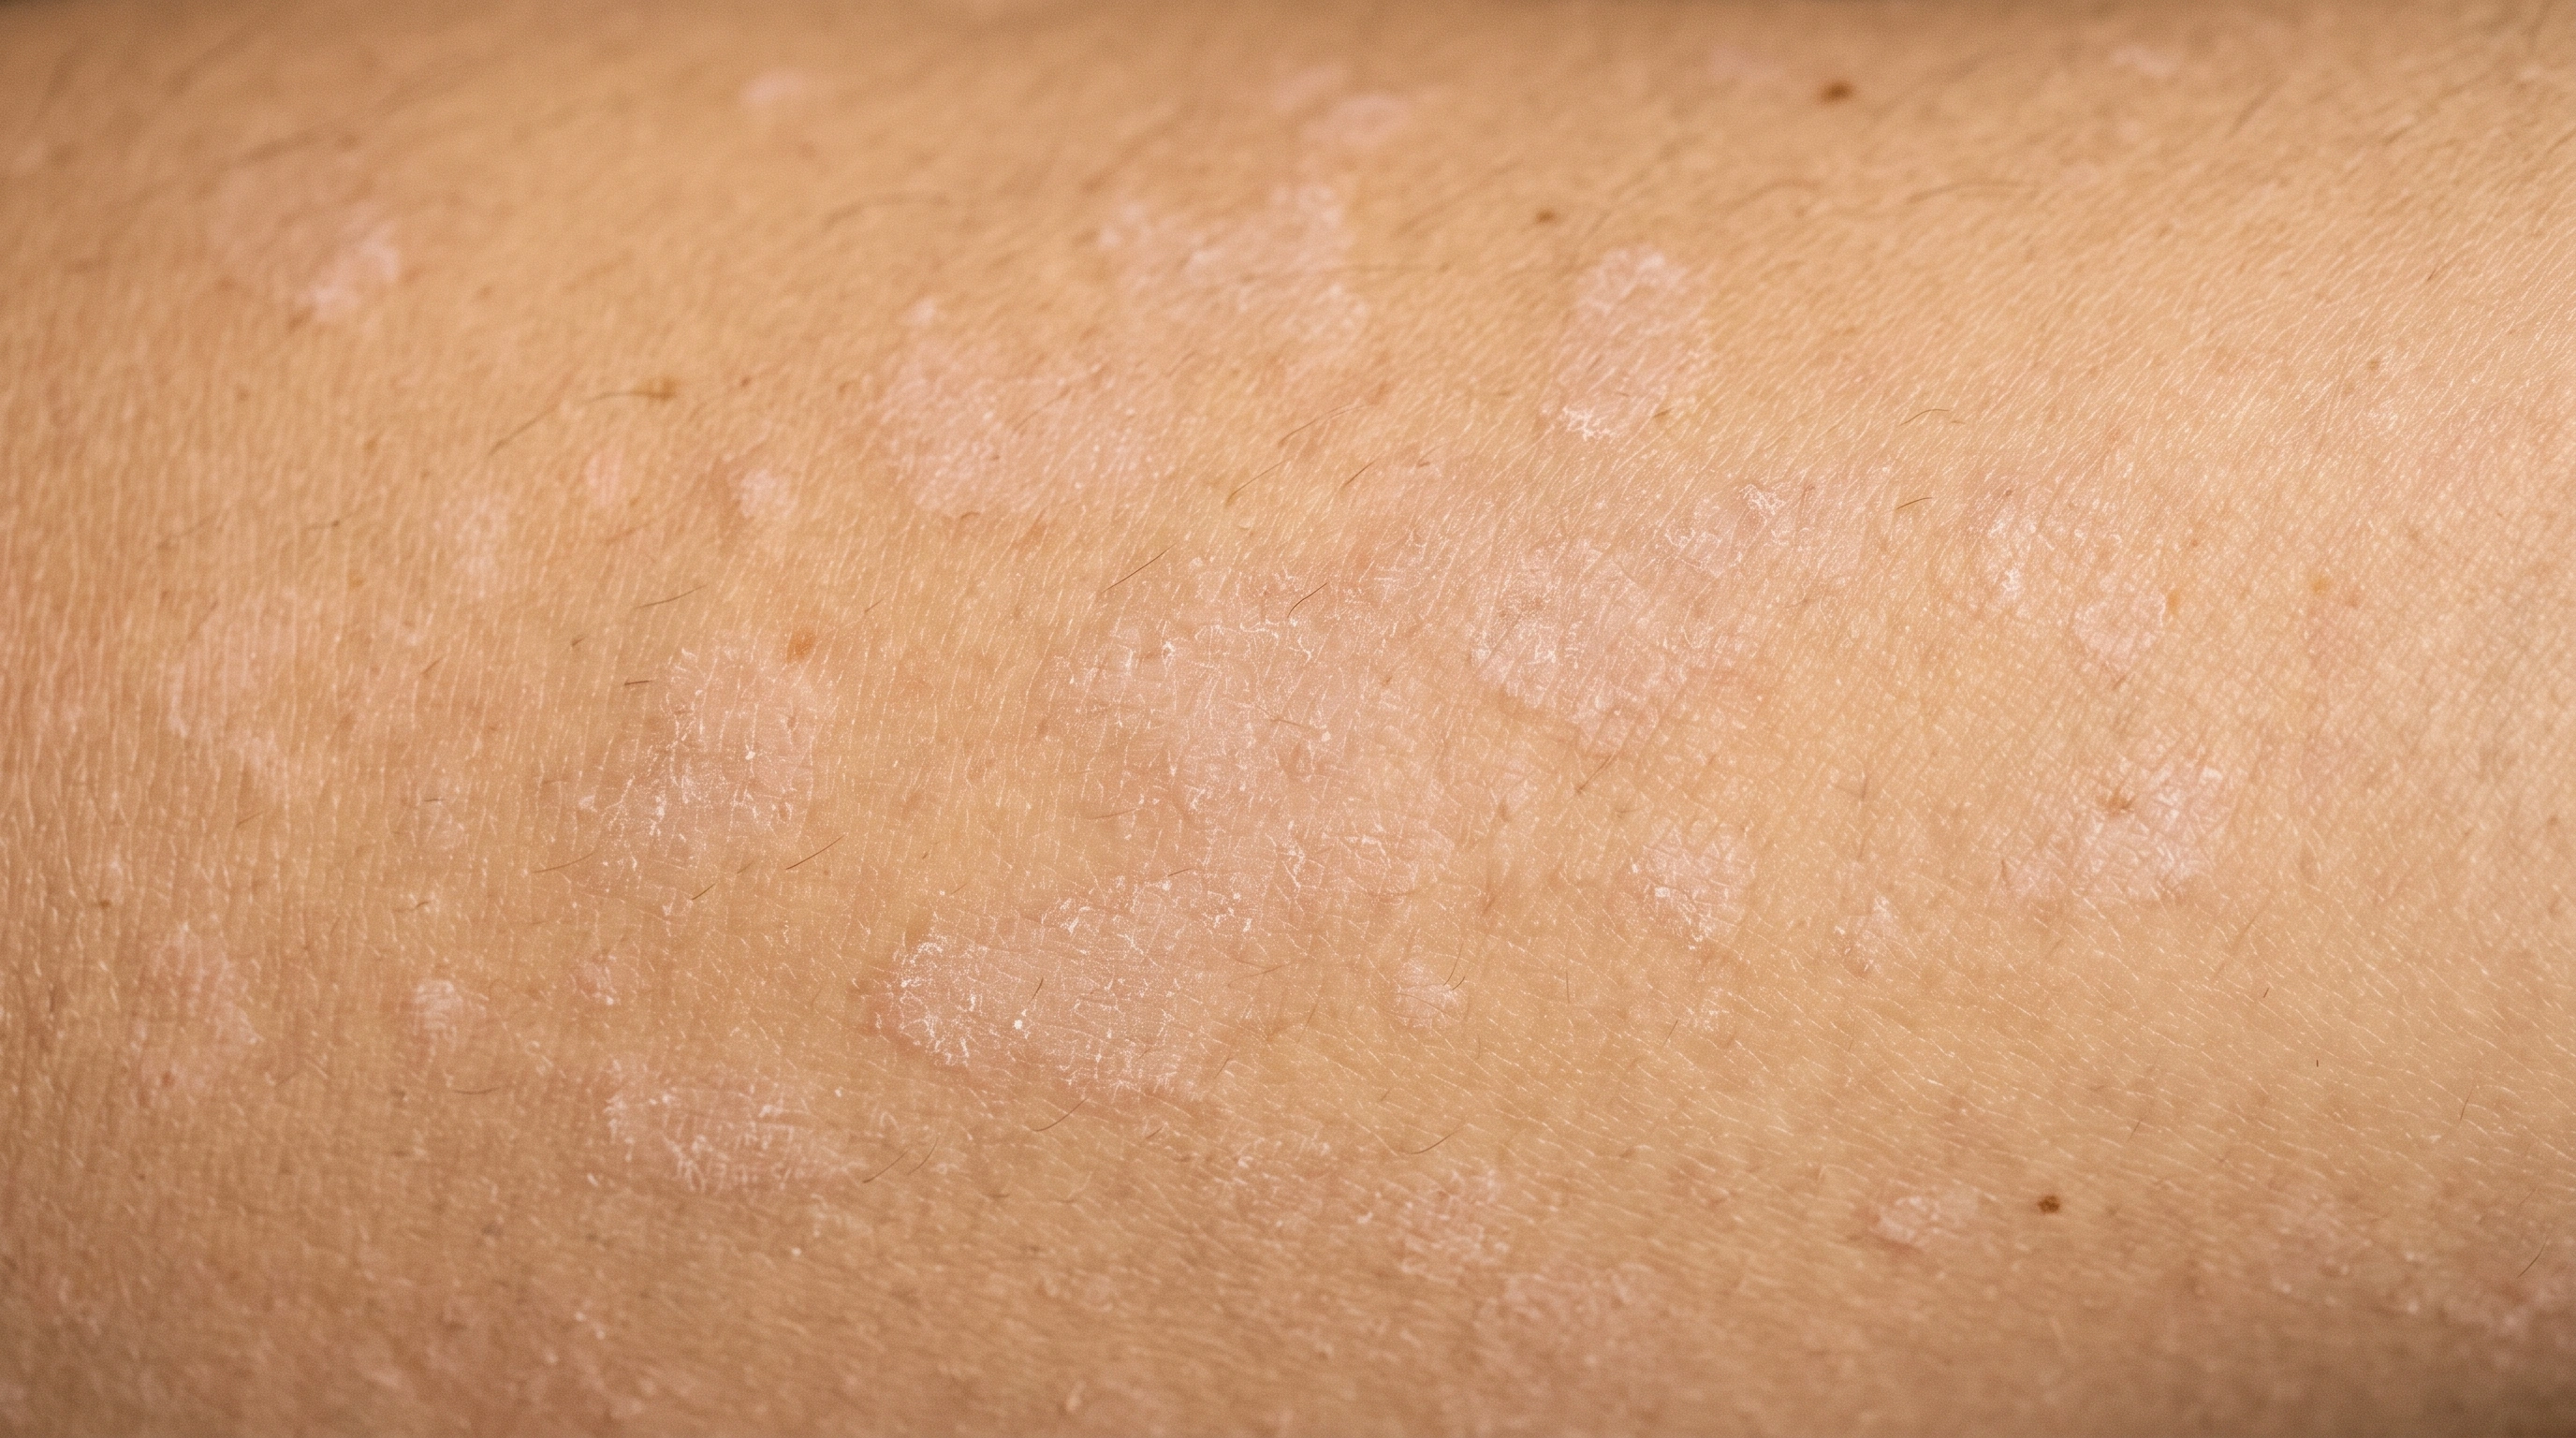
Tanned upper back on medium olive skin with pale oval patches standing out against the tan, some still carrying a fine surface scale and some merging into larger shapes.
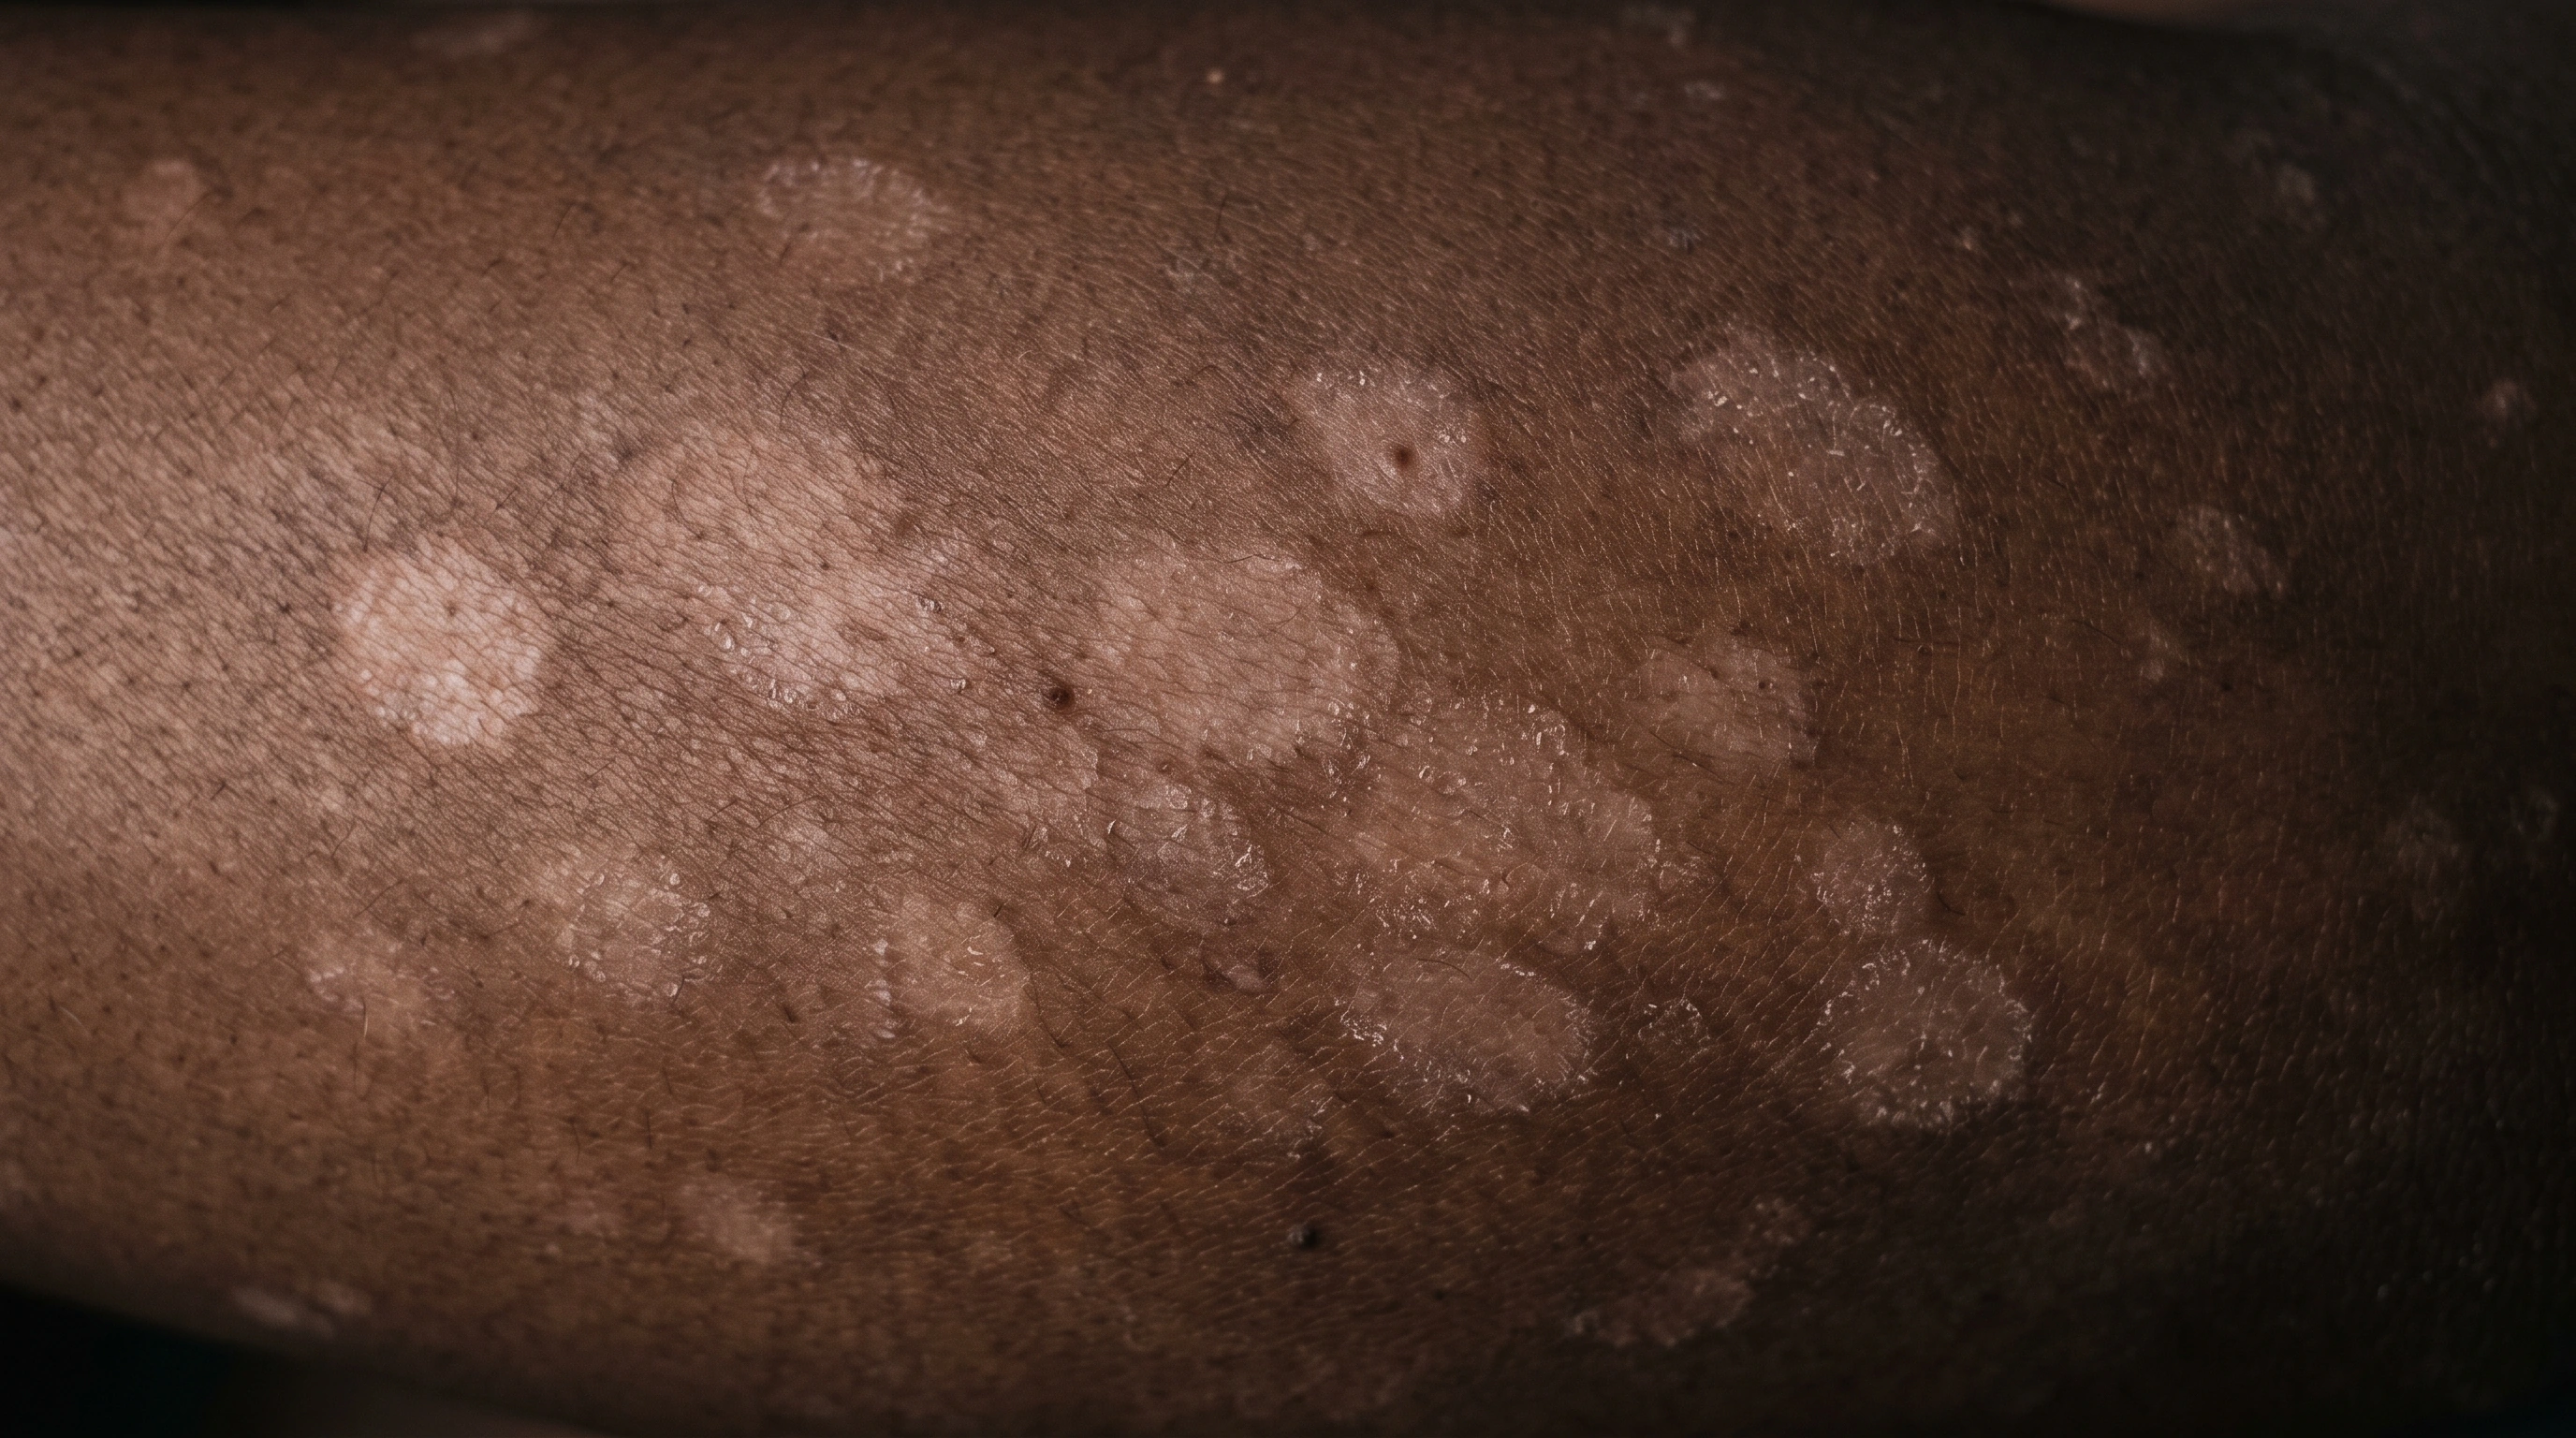
Flat oval patches several shades lighter than the surrounding brown skin, spread across an upper back and merging into larger shapes, with a grayish ashy scale on the surface.
Widespread pale oval patches across an upper back and shoulders on deep brown skin, standing out strongly against the surrounding skin, with a fine scale on the newer ones.
Diagram
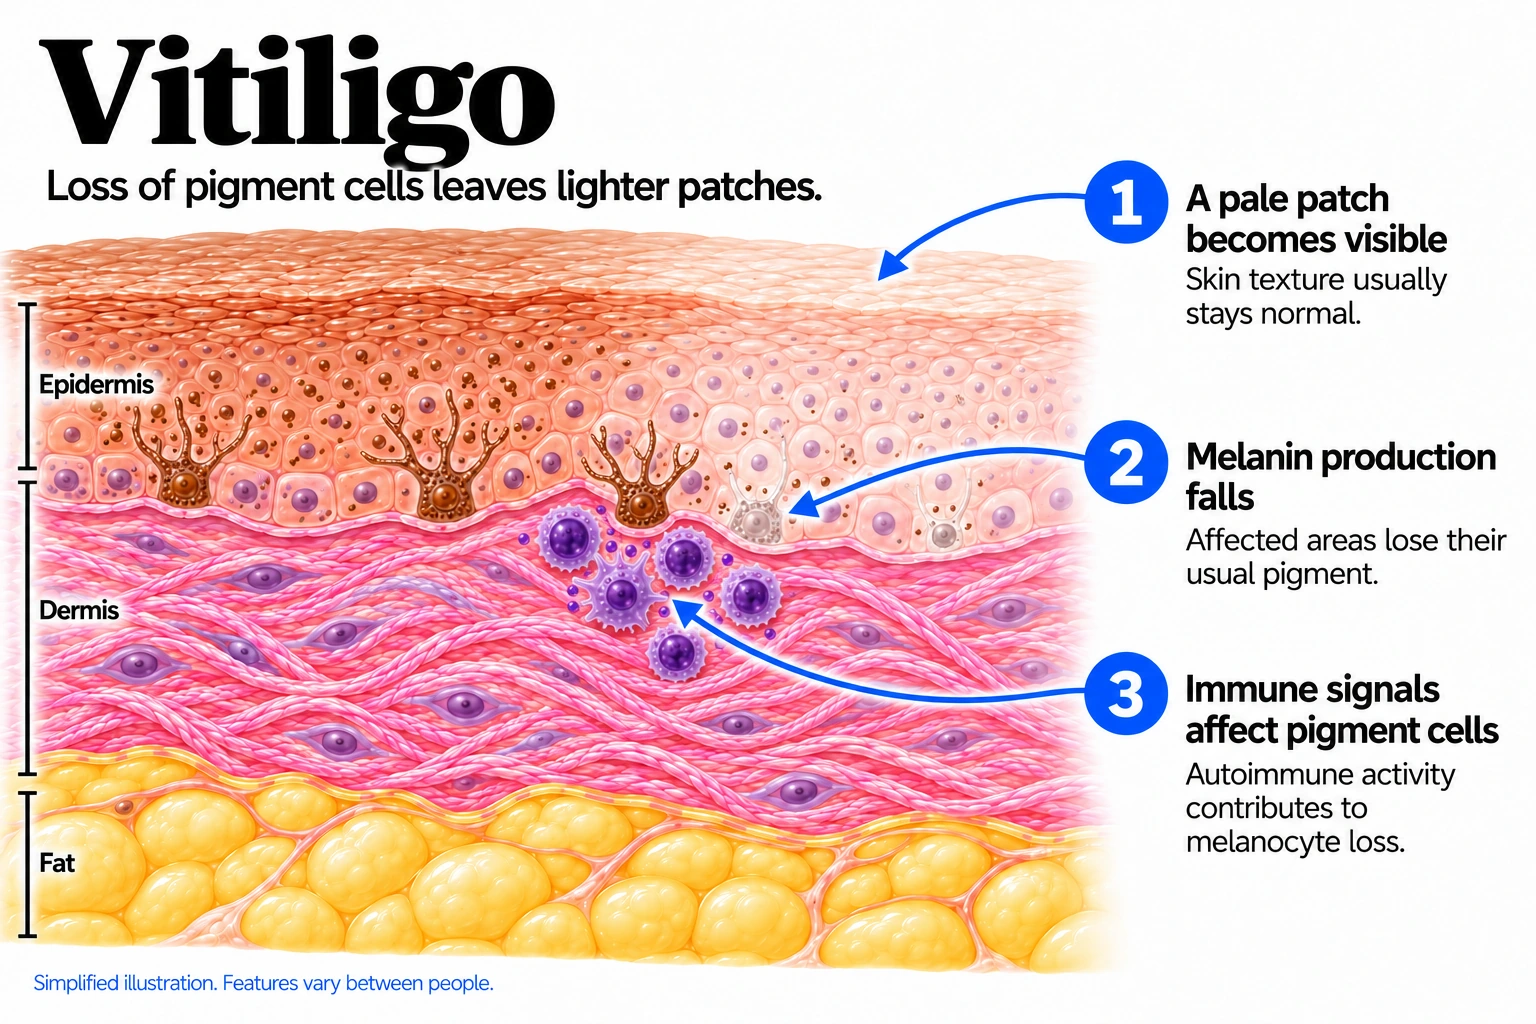
Vitiligo mechanism diagram. A pale patch becomes visible: Skin texture usually stays normal. Melanin production falls: Affected areas lose their usual pigment. Immune signals affect pigment cells: Autoimmune activity contributes to melanocyte loss.
Tinea Versicolor mechanism diagram. Yeast grows at the surface: Malassezia normally lives on the skin. Pigment balance changes: Affected patches can look lighter or darker. Fine scale develops: The outer layer sheds in tiny flakes.
In the skin

Immune activity contributes to the loss of pigment-producing cells in affected skin. With less melanin, pale patches become visible while the skin's texture usually remains normal.

Malassezia yeast overgrows in the outer skin and disturbs the usual pigment balance. Affected areas develop fine scale and may look lighter or darker than surrounding skin.

Where it shows up

Variable patterns of pigment loss
Upper chest, back and upper arms

When it usually starts

010203040506070+

Vitiligo. Can begin at any age, commonly before early adulthood.

Tinea Versicolor. Most common in adolescents and young adults, especially in warm humid climates.

Causes and triggers

Causes

Vitiligo is an autoimmune condition. The immune system attacks the pigment cells in patches of skin, leaving them white.

Tinea versicolor is an overgrowth of Malassezia, a yeast that normally lives on the skin. The yeast interferes with pigment, leaving lighter or darker patches.

Family tendency

About 1 in 5 people with vitiligo have a relative with it.

It tends to run in families.

Risk factors
Family history, Thyroid disease, Other autoimmune conditions
Teens and young adults, Oily skin, Weakened immunity
Trigger
● Vitiligo
● Tinea Versicolor
Skin injury
Strong link
Not listed
Severe sunburn
Possible
Not listed
Stress
Possible
Not listed
Chemicals like some hair dyes
Possible
Not listed
Hot, humid weather
Not listed
Well established
Heavy sweating
Not listed
Strong link
Oily skin products
Not listed
Possible

Daily Care

Vitiligo
Tinea Versicolor
Daily care

Habits that help

  • Daily sunscreen on exposed patches
    Prevents triggering burns and limits the contrast.
  • Camouflage and self-tanner
    Changes nothing underneath, but makes daily life easier meanwhile.
  • Topical calcineurin inhibitors
    Tacrolimus and pimecrolimus calm the same attack without thinning skin.
  • Ruxolitinib cream
    A prescription JAK inhibitor cream approved to restore pigment, used for months.
  • Narrowband UVB light therapy
    The mainstay for widespread vitiligo, two or three sessions a week.
  • Combining light therapy with a cream
    Repigments more skin than either alone.
  • Checking the thyroid
    Thyroid disease is common alongside vitiligo and often silent.

Avoid

  • Avoid: Injuring the skin
    Cuts, burns, tight straps, surgery and tattoos bring out new patches at that exact spot.
  • Avoid: Sunburn
    An injury and a chemical stress at once, and depigmented skin burns faster.
  • Avoid: Constant friction and pressure
    Belt lines, bra straps, watch bands, rubbing shoes.
  • Avoid: Certain chemicals
    Some phenol and catechol compounds destroy pigment cells directly, including in some lightening creams.
  • Avoid: Physical or emotional stress
    It does not cause vitiligo, but it can make an existing tendency act up.
  • Avoid: Stopping treatment when color returns
    Without maintenance, many repigmented patches lose color again.
  • Avoid: Waiting to be seen
    Patches white for years respond much less well than fresh ones.

Habits that help

  • Shower and change promptly after sweating
    Less time damp, less time in the yeast's conditions.
  • Lighter, non-oily products
    On the chest, back and shoulders, sunscreen included.
  • Loose, breathable clothing in hot weather
    Cotton and looser fits over synthetics.
  • Daily sunscreen on the affected areas
    Stops the surrounding skin darkening further.
  • Take a photograph when you start
    The color changes too slowly to see day to day.
  • Leave the patches alone
    The color is not on the surface; it recovers on its own.
  • Antifungal creams for limited areas
    Fine on a small area, impractical across a back.
  • Reduce prolonged heat and dampness when possible
    The clearest pattern there is — it returns every summer.
  • Discuss flares associated with pregnancy or hormonal changes
    Linked to flares, through oil production.

Avoid

  • Avoid: Heavy sweating
    Damp clothing keeps skin in the state the yeast prefers.
  • Avoid: Body oils and rich lotions
    Malassezia feeds on the fats in many oils.
  • Avoid: Occlusive synthetic clothing
    Holds sweat and heat against the trunk.
  • Avoid: Sun exposure while the patches are pale
    They do not tan, so the difference gets obvious.
  • Avoid: Deliberately tanning to even it out
    It widens the gap.
  • Avoid: Scrubbing the patches
    Nothing for the color, and irritated skin recovers slower.
  • Avoid: Skin-lightening or bleaching products
    They do not fix the mismatch, and many contain undisclosed strong steroids.
  • Avoid: Stopping after a single course
    The yeast is permanent, and in a hot climate it regrows within months.
  • Avoid: Judging the treatment at two weeks
    Why people cycle through four products when the first already worked.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Vitiligo
● Tinea Versicolor
Filter by type
Vitiligo type

Select one or more.

All types
Over-the-counter
Illustration: Generic oral tablet bottle and tablets.

Antioxidant supplements

Limited evidence

Ginkgo biloba and polypodium leucotomos extract are the two most often asked about. Small studies suggest they may slow spread a little or add slightly to light therapy, but the trials are small and the results are inconsistent. They are not a treatment on their own, and no supplement has been shown to bring color back.

Existing illustration of Camouflage makeup.

Camouflage makeup and self-tanner

Listed

Cover creams made for skin conditions, and self-tanning lotions containing dihydroxyacetone, color the surface of a white patch for a few days at a time. They change nothing underneath and they do not interfere with treatment. For many people they make daily life easier during the year or more that repigmentation takes.

Ketoconazole shampoo.

Ketoconazole shampoo

Strong evidence

The usual first choice, used as a body wash rather than on the hair. Lather it over the chest, back and shoulders, leave it on for about five minutes so it has contact time, then rinse, daily for one to two weeks. Contact time matters more than strength here — the 1% is on the shelf and the 2% is on prescription, and people who rinse straight off usually conclude it did not work.

Illustration: Generic oral tablet bottle and tablets.

Terbinafine cream, not the tablets

Moderate evidence

The cream works well on a small number of patches, applied twice a day for a couple of weeks, but covering a whole back with it is impractical and expensive. The tablets are the odd exception in this condition. They clear athlete's foot and ringworm and do nothing at all here, because this is a yeast rather than the fungi those tablets are built for.

Illustration: Generic topical cream tube and white cream.

Skin-lightening creams

Limited evidence

Sold for evening out patchy skin, and the wrong tool here, because the problem is a patch that is too light rather than skin that is too dark. They do not speed the pigment up. Creams bought without a prescription are also a common source of undisclosed strong steroids, which thin the skin over time. The patches recover on their own once the yeast is controlled.

Two Selsun Blue bottles, two Head and Shoulders Clinical Strength bottles and a Vichy Dercos bottle and box

Selenium Sulfide

Strong evidence

Just as effective as ketoconazole for this and usually cheaper, spread over the affected area, left on for five to ten minutes and washed off. It has a noticeable sulfur smell that lingers, and it can discolor fabric and light hair, so old clothes and a thorough rinse are worth planning for.

Four dandruff shampoo bottles: DHS Zinc, Head and Shoulders Classic Clean, CeraVe Anti-Dandruff and Head and Shoulders Bare

Pyrithione Zinc

Limited evidence

A gentler wash, better suited to keeping this away than to clearing a flare. It is the one most people find easy enough to keep using twice a month right through the summer, which is the part that actually prevents the next episode. On a widespread flare it is slower than ketoconazole or selenium sulfide.

Prescription topicals
Opzelura shown in recognizable white topical cream squeeze tube with muted green bands.

Opzelura

Strong evidence

A JAK inhibitor cream approved specifically to restore pigment in vitiligo, applied twice a day. In trials about a third of people had most of the color back on the face by six months, and results keep improving past a year. It is slow, it is expensive, and color can be lost again if it is stopped, so it is usually continued about twice a week afterwards.

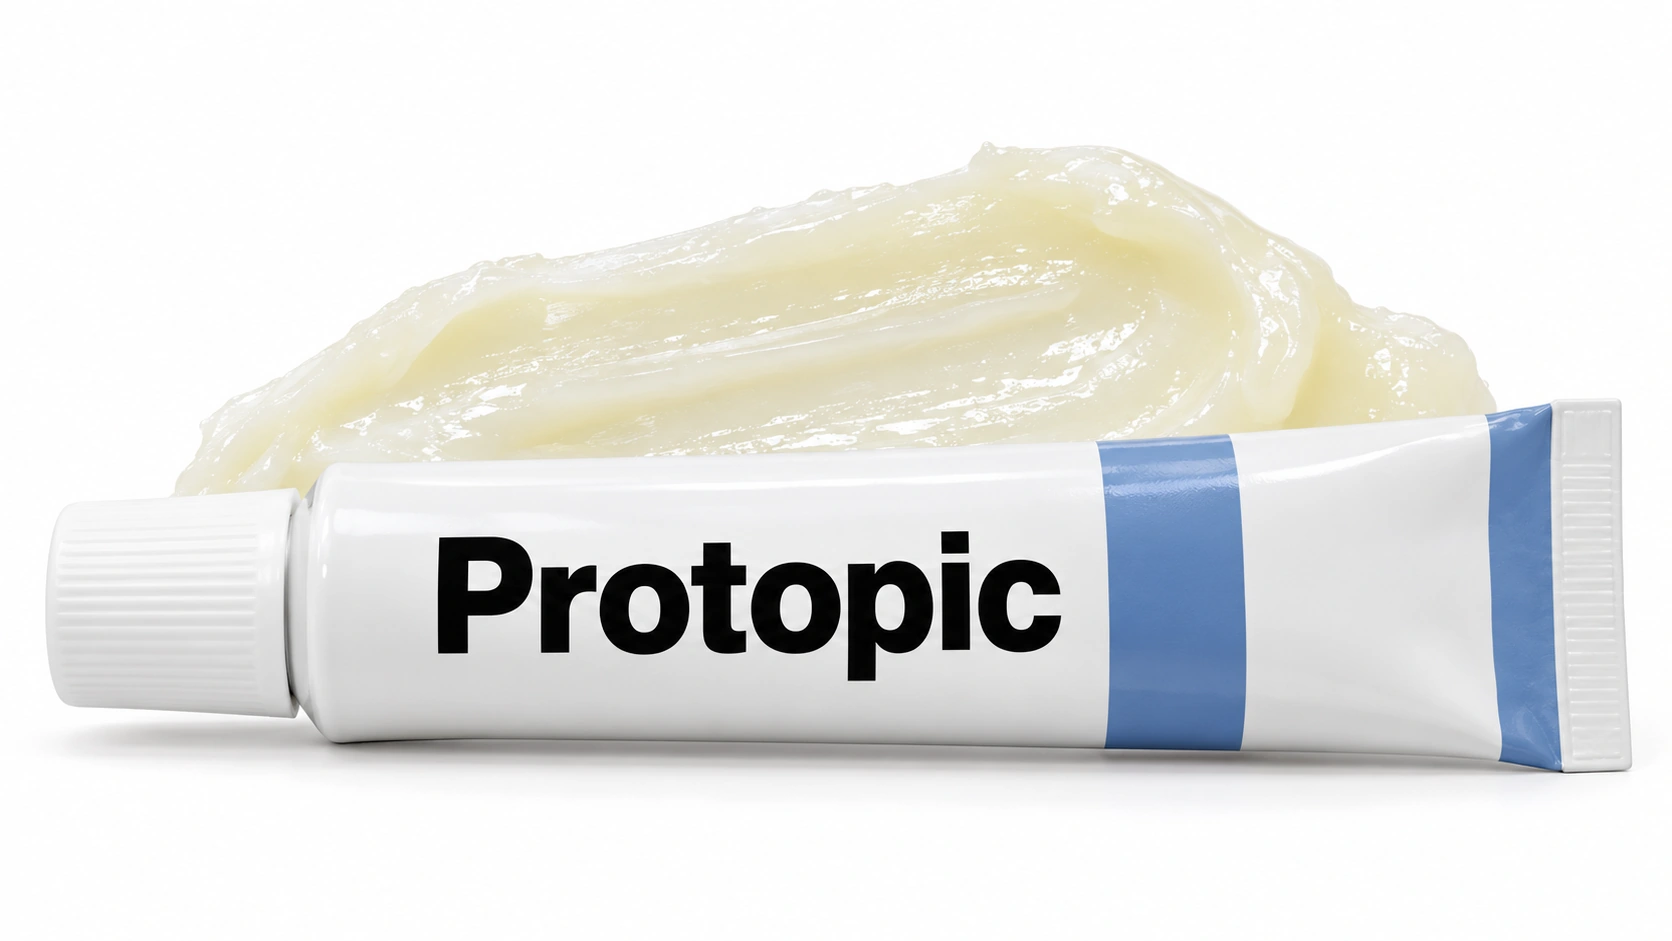
Protopic — Header Image

Protopic

Moderate evidence

The usual choice for vitiligo on the face, eyelids, neck and skin folds, because it quiets the immune attack without thinning the skin, so it can be used in those places for months. It stings or feels warm for the first week or two in some people. It works best on the face and much less well on hands and feet.

Clobetasol — Header Image

Clobetasol

Moderate evidence

Clobetasol Propionate. A strong steroid cream, the standard first treatment for a small number of patches on the body. It is used in courses with breaks, often a few weeks on and a few weeks off, because continuous use thins the skin and leaves stretch marks. It is not used on the face or eyelids, where tacrolimus is chosen instead.

16:9 hero for Elidel. Never cropped: the tone strip and the corner logo depend on the full frame.

Elidel

Moderate evidence

A gentler relative of tacrolimus, used on the same delicate areas and often preferred for children or for people who find tacrolimus too stinging. It works the same way on the immune attack. It is generally a little less effective than tacrolimus for vitiligo.

Calcipotriene — Header Image

Calcipotriene

Limited evidence

A vitamin D cream sometimes added to a steroid or to light therapy, on the idea that it helps pigment cells return. On its own it does very little for vitiligo. Its value is as a partner treatment, and the evidence for even that is mixed.

Photo needed: A white cream tube on a white background, with a plain white label reading Monobenzone and a blue swoosh beneath it.

"Bleaching" cream

Listed

Monobenzone cream removes the pigment that is left, so the skin ends up one even color. It is only considered when vitiligo already covers most of the body and repigmenting is not realistic. The change is permanent and cannot be reversed, and the skin afterwards has no protection from the sun at all, so it is a decision taken slowly and never as a first step.

Illustration: Generic topical cream tube and white cream.

Prescription antifungal creams

Listed

Ciclopirox, econazole or ketoconazole 2% cream, applied to the patches for two to four weeks. They are a reasonable choice when only a small area is involved, or when a medicated wash has irritated the skin. Across a whole back they are expensive and hard to apply properly, which is the point at which tablets are the sensible option.

Prescription pills
Existing representative illustration of Rinvoq medicine packaging and tablets.

Oral JAK inhibitors

Moderate evidence

Tablets in the same family as ruxolitinib cream. Trials show real repigmentation, particularly when they are combined with light therapy, and they are the most active area of vitiligo research right now. They are not yet standard treatment for vitiligo, and they carry more risk than a cream, so they are used through a specialist or a trial.

Prednisone — Header Image

Prednisone

Limited evidence

Prednisone in short pulses. Low-dose steroid tablets taken on two days a week for a few months are used for one purpose in vitiligo: to stop pigment loss that is spreading quickly. It is a brake, not a way to bring color back, so it is paired with a cream or light therapy. Blood sugar, blood pressure and mood are watched while it is running.

Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Moderate evidence

The usual tablet when the area is too large to treat by hand or topical treatment has genuinely failed, given as a short course of a few days. It clears the yeast quickly and does nothing to speed up the color, which still takes months. It interacts with a long list of other medicines, so the prescriber needs your full list.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Moderate evidence

The other short-course tablet, sometimes given as a single dose repeated a week later. It works about as well as itraconazole for a widespread rash. Neither tablet stops it coming back, so the monthly wash is still the plan afterwards. If you are pregnant or breastfeeding, ask the doctor managing your pregnancy before taking either.

Procedures
Editorial illustration for Phototherapy, based on the entry’s treatment or equipment reference.

Phototherapy

Strong evidence

Narrowband UVB, two or three sessions a week in a cabinet at the clinic, is the mainstay for vitiligo that covers more than a few small patches. It calms the immune attack and coaxes pigment cells out of the hair openings. Expect three to six months before the face shows change and a year or more for a full course, and better results when it is combined with a cream.

Editorial illustration for Excimer Laser, based on the entry’s treatment or equipment reference.

Excimer Laser

Moderate evidence

The same wavelength as narrowband UVB delivered through a handpiece, so it treats one patch and leaves the skin around it alone. It suits a small number of patches, especially on the face, and it is the practical option for children who cannot stand still in a cabinet. Sessions are usually twice a week, and it is not used for widespread vitiligo.

Editorial illustration for Surgical pigment grafting, based on the entry’s treatment or equipment reference.

Surgical pigment grafting

Moderate evidence

Pigment cells are taken from normal skin and moved into a white patch, either as tiny grafts or as a cell suspension. It is the best option for segmental vitiligo and for patches that have been completely stable for a year or more, including patches where the hair has gone white. It is never done while vitiligo is spreading, because the graft is attacked in turn.

None listed

Outlook

Long term

Vitiligo is unpredictable, which is one of the hardest things about it. Non-segmental vitiligo, the common type, moves in waves — an active spell, a long still period, then another. Segmental vitiligo spreads within one area on one side over roughly six months to two years, then stops for good.

Tinea versicolor is harmless, and treatment runs in two stages. The infection stops within a week or two; the color takes months longer. Patchy skin is not the same as infected skin.

Complications

Possible complications
  • Sunburn inside the patches
  • Thyroid and other autoimmune disease
  • The weight of being looked at
More details

Sunburn inside the patches
Skin inside a vitiligo patch has no melanin at all, so it burns quickly and can burn badly while the skin around it is fine. A burn is also an injury, and injuries can bring out new patches, so a bad burn can make things worse in two ways at once. Daily broad-spectrum sunscreen on exposed patches prevents it, and it counts as treatment rather than an extra.

Thyroid and other autoimmune disease
The same immune tendency that causes vitiligo makes other autoimmune conditions more likely, and thyroid disease is the common one. It is often silent for a long time, which is why a thyroid blood test is standard at the first visit and is sometimes repeated later. Type 1 diabetes, pernicious anemia and alopecia areata also appear more often than average.

The weight of being looked at
Vitiligo does not make you unwell, but it is visible, and being looked at all day is tiring. Anxiety, low mood and avoiding ordinary things are common, and they are worse where the contrast is greater or the patches are on the face and hands. This counts as a medical reason to treat, not a cosmetic one, and it is worth saying out loud at the appointment.

  • It persists and slowly spreads
  • The active infection stops fast
  • Recurrence is the norm rather than the exception
More details

It persists and slowly spreads
Patches merge and cover more of the trunk over months. In temperate climates it often eases in winter and returns each summer.

The active infection stops fast
Within one to two weeks of a proper course the scaling stops and the patches stop expanding. The condition is treated at that point, even though the skin does not look normal.

Recurrence is the norm rather than the exception
A large share of people get it again, particularly in hot climates and in people who sweat heavily. The yeast is permanent, so treatment reduces it rather than removing it, and maintenance — a medicated wash once or twice a month in warm months — keeps most people clear.

When to get help

When to get help

Seek assessment of new white patches or spreading pigment loss. Discuss associated symptoms, sun protection and whether targeted autoimmune screening is appropriate.

Seek assessment if the diagnosis is uncertain or treatment fails. Color may take months to normalize after the yeast has been treated.

Common questions

Vitiligo:Will my color ever come back?

Often, at least partly. Face, neck and trunk repigment well for a substantial proportion of people. Hands, fingers, feet and lips do poorly, and patches where the hair has gone white usually do not refill, because the pigment cells that restock a patch live in the hair openings. Nobody can promise a result, which is why photographs at the start are worth taking.

Vitiligo:How long does treatment take?

Longer than almost anyone expects. The first visible change on the face usually takes about three to six months, and a full course often runs a year or more. Judging a treatment at week six is judging it before it has done anything.

Vitiligo:Is vitiligo dangerous?

Not to your body. It does not shorten life, damage organs or turn into anything else. Two points matter: depigmented skin burns easily, and autoimmune conditions such as thyroid disease are more common alongside it, which is why blood tests are usually done.

Vitiligo:Will it spread over my whole body?

Most likely not. Vitiligo moves in waves, and losing pigment over almost the entire body is uncommon. Nothing predicts the course from the first patch, which is why active spread is treated promptly.

Vitiligo:Can my children get it?

Higher than average, but still low. Vitiligo runs in families through a group of immune genes rather than one, so most children of a parent with vitiligo never develop it.

Vitiligo:Does stress cause vitiligo?

No — the underlying immune tendency is genetic. But major stress, illness or surgery frequently lines up with the start of an active spell. Managing stress is worth doing for its own sake, and it is not a substitute for treatment.

Tinea Versicolor:Is it contagious?

No. The yeast already lives on essentially everyone's skin. You cannot give it to a partner, a child or a housemate. Whether someone develops the rash depends on their own skin oil, the climate and their own susceptibility.

Tinea Versicolor:Why are the patches still there after I finished the treatment?

Because the color and the infection run on different timelines. Treatment stops the yeast within a week or two; the pigment takes months. Scratch a patch lightly — if fine scale lifts it is still active, and if the skin is smooth and simply a different color, the treatment worked.

Tinea Versicolor:Will it come back?

Most likely, particularly in a hot, humid climate or if you sweat heavily. That is normal behavior, not treatment failure, because the yeast is a permanent resident. A medicated wash once or twice a month through the warm months prevents most recurrences and is far less work than treating a full flare.

Tinea Versicolor:Can I sunbathe to even out the color?

No, and it makes it more obvious. The patches cannot tan, so the surrounding skin darkens and the gap widens. Sunscreen while the pigment recovers works better, along with time.

Tinea Versicolor:Is it the same fungus as athlete's foot?

No. Athlete's foot comes from dermatophytes, picked up from the environment. This comes from Malassezia, a yeast that lives on everyone. That is why terbinafine tablets clear athlete's foot but do nothing for this, even though terbinafine cream helps.

Tinea Versicolor:Do I need tablets?

Not usually — topical treatment clears most cases. Ask about tablets when a large area of the trunk is involved and applying a wash properly is impractical, when it keeps coming back, or when topical treatment has genuinely failed. They clear it faster but do not speed up the color or prevent recurrence, so you still need a maintenance plan.
Sources

Sources and further reading

  1. DermNet

  2. DermNet
Dermapedia on YouTube