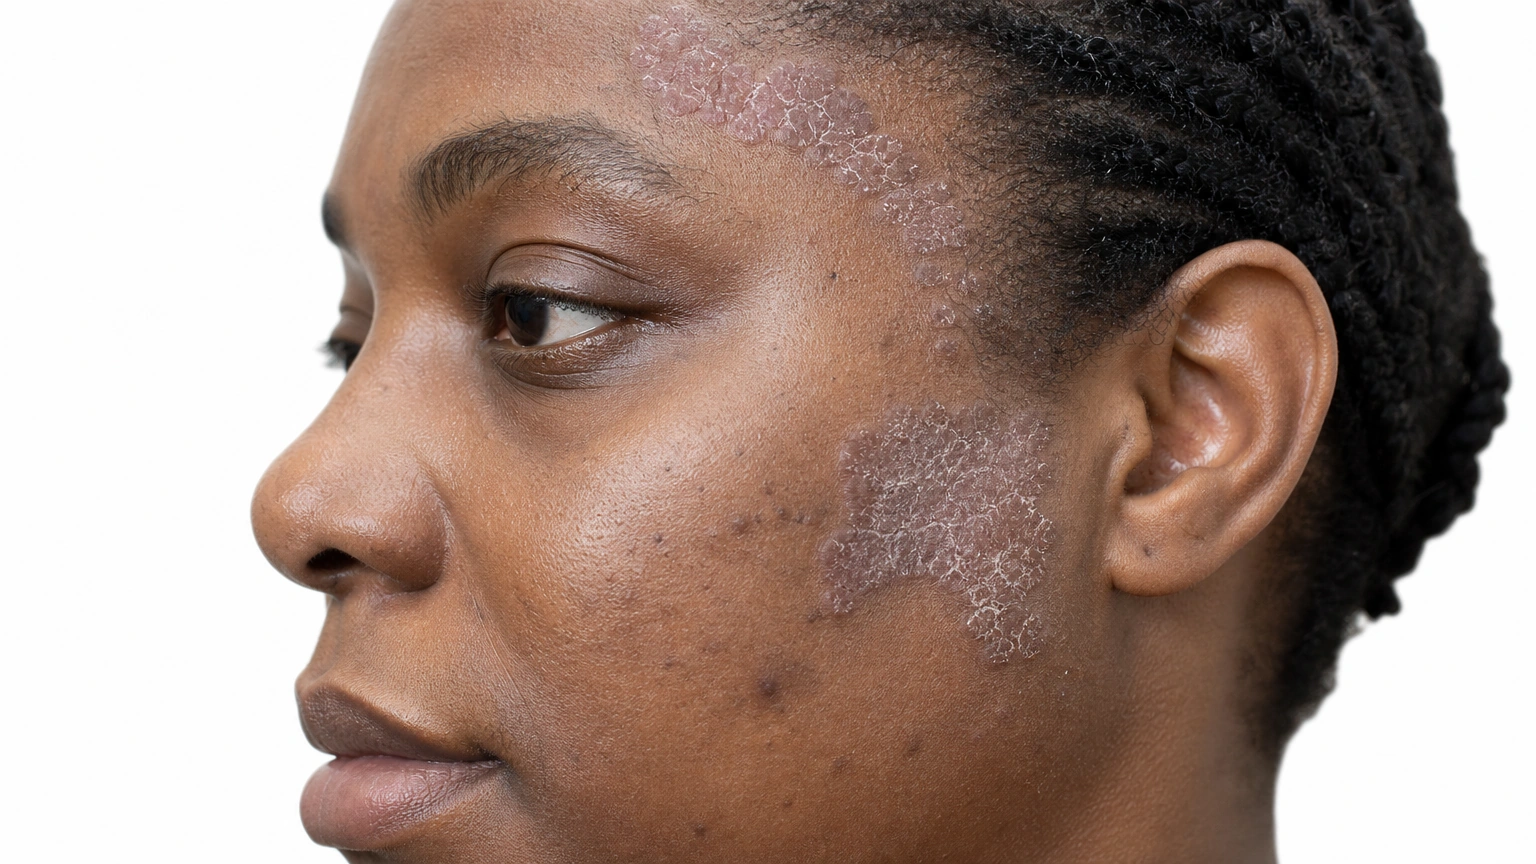Facial Psoriasis vs Tinea Faciei

Psoriasis affecting facial skin, often with psoriasis elsewhere. Ringworm infection of non-bearded facial skin.

Research updated 2026-10-23
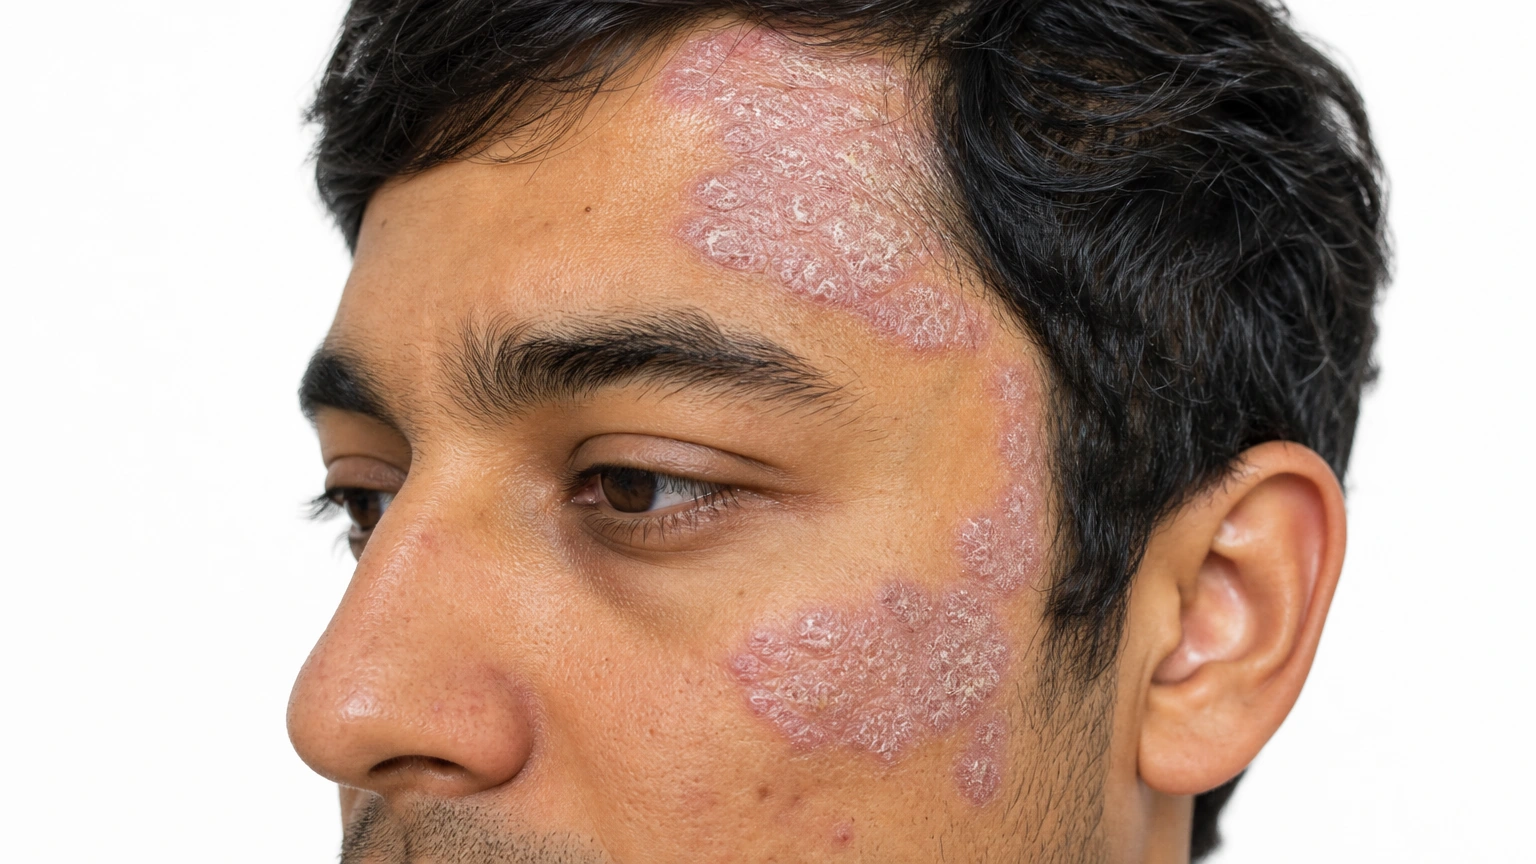
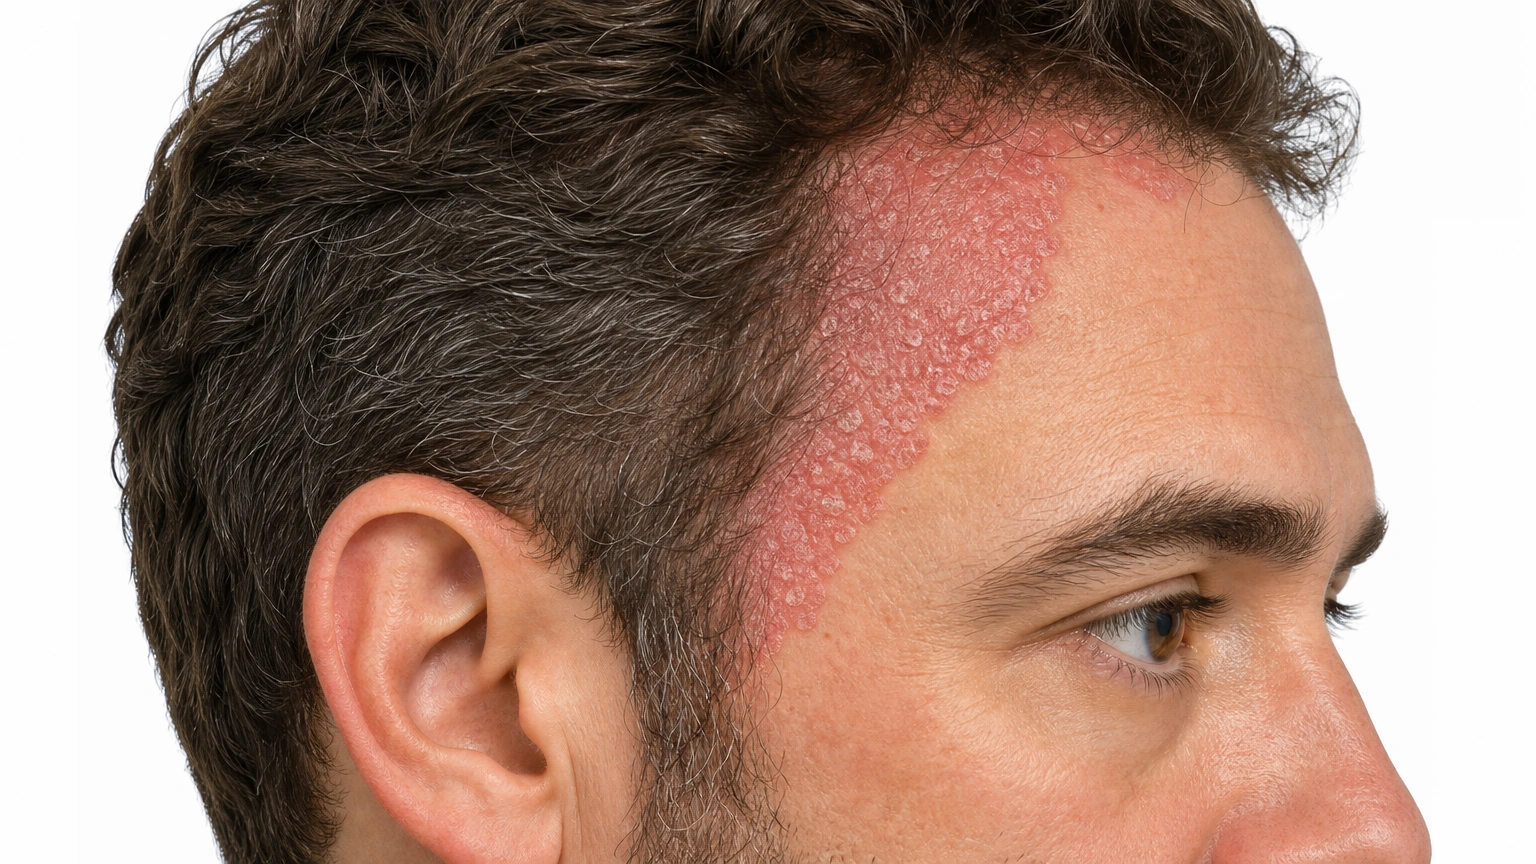
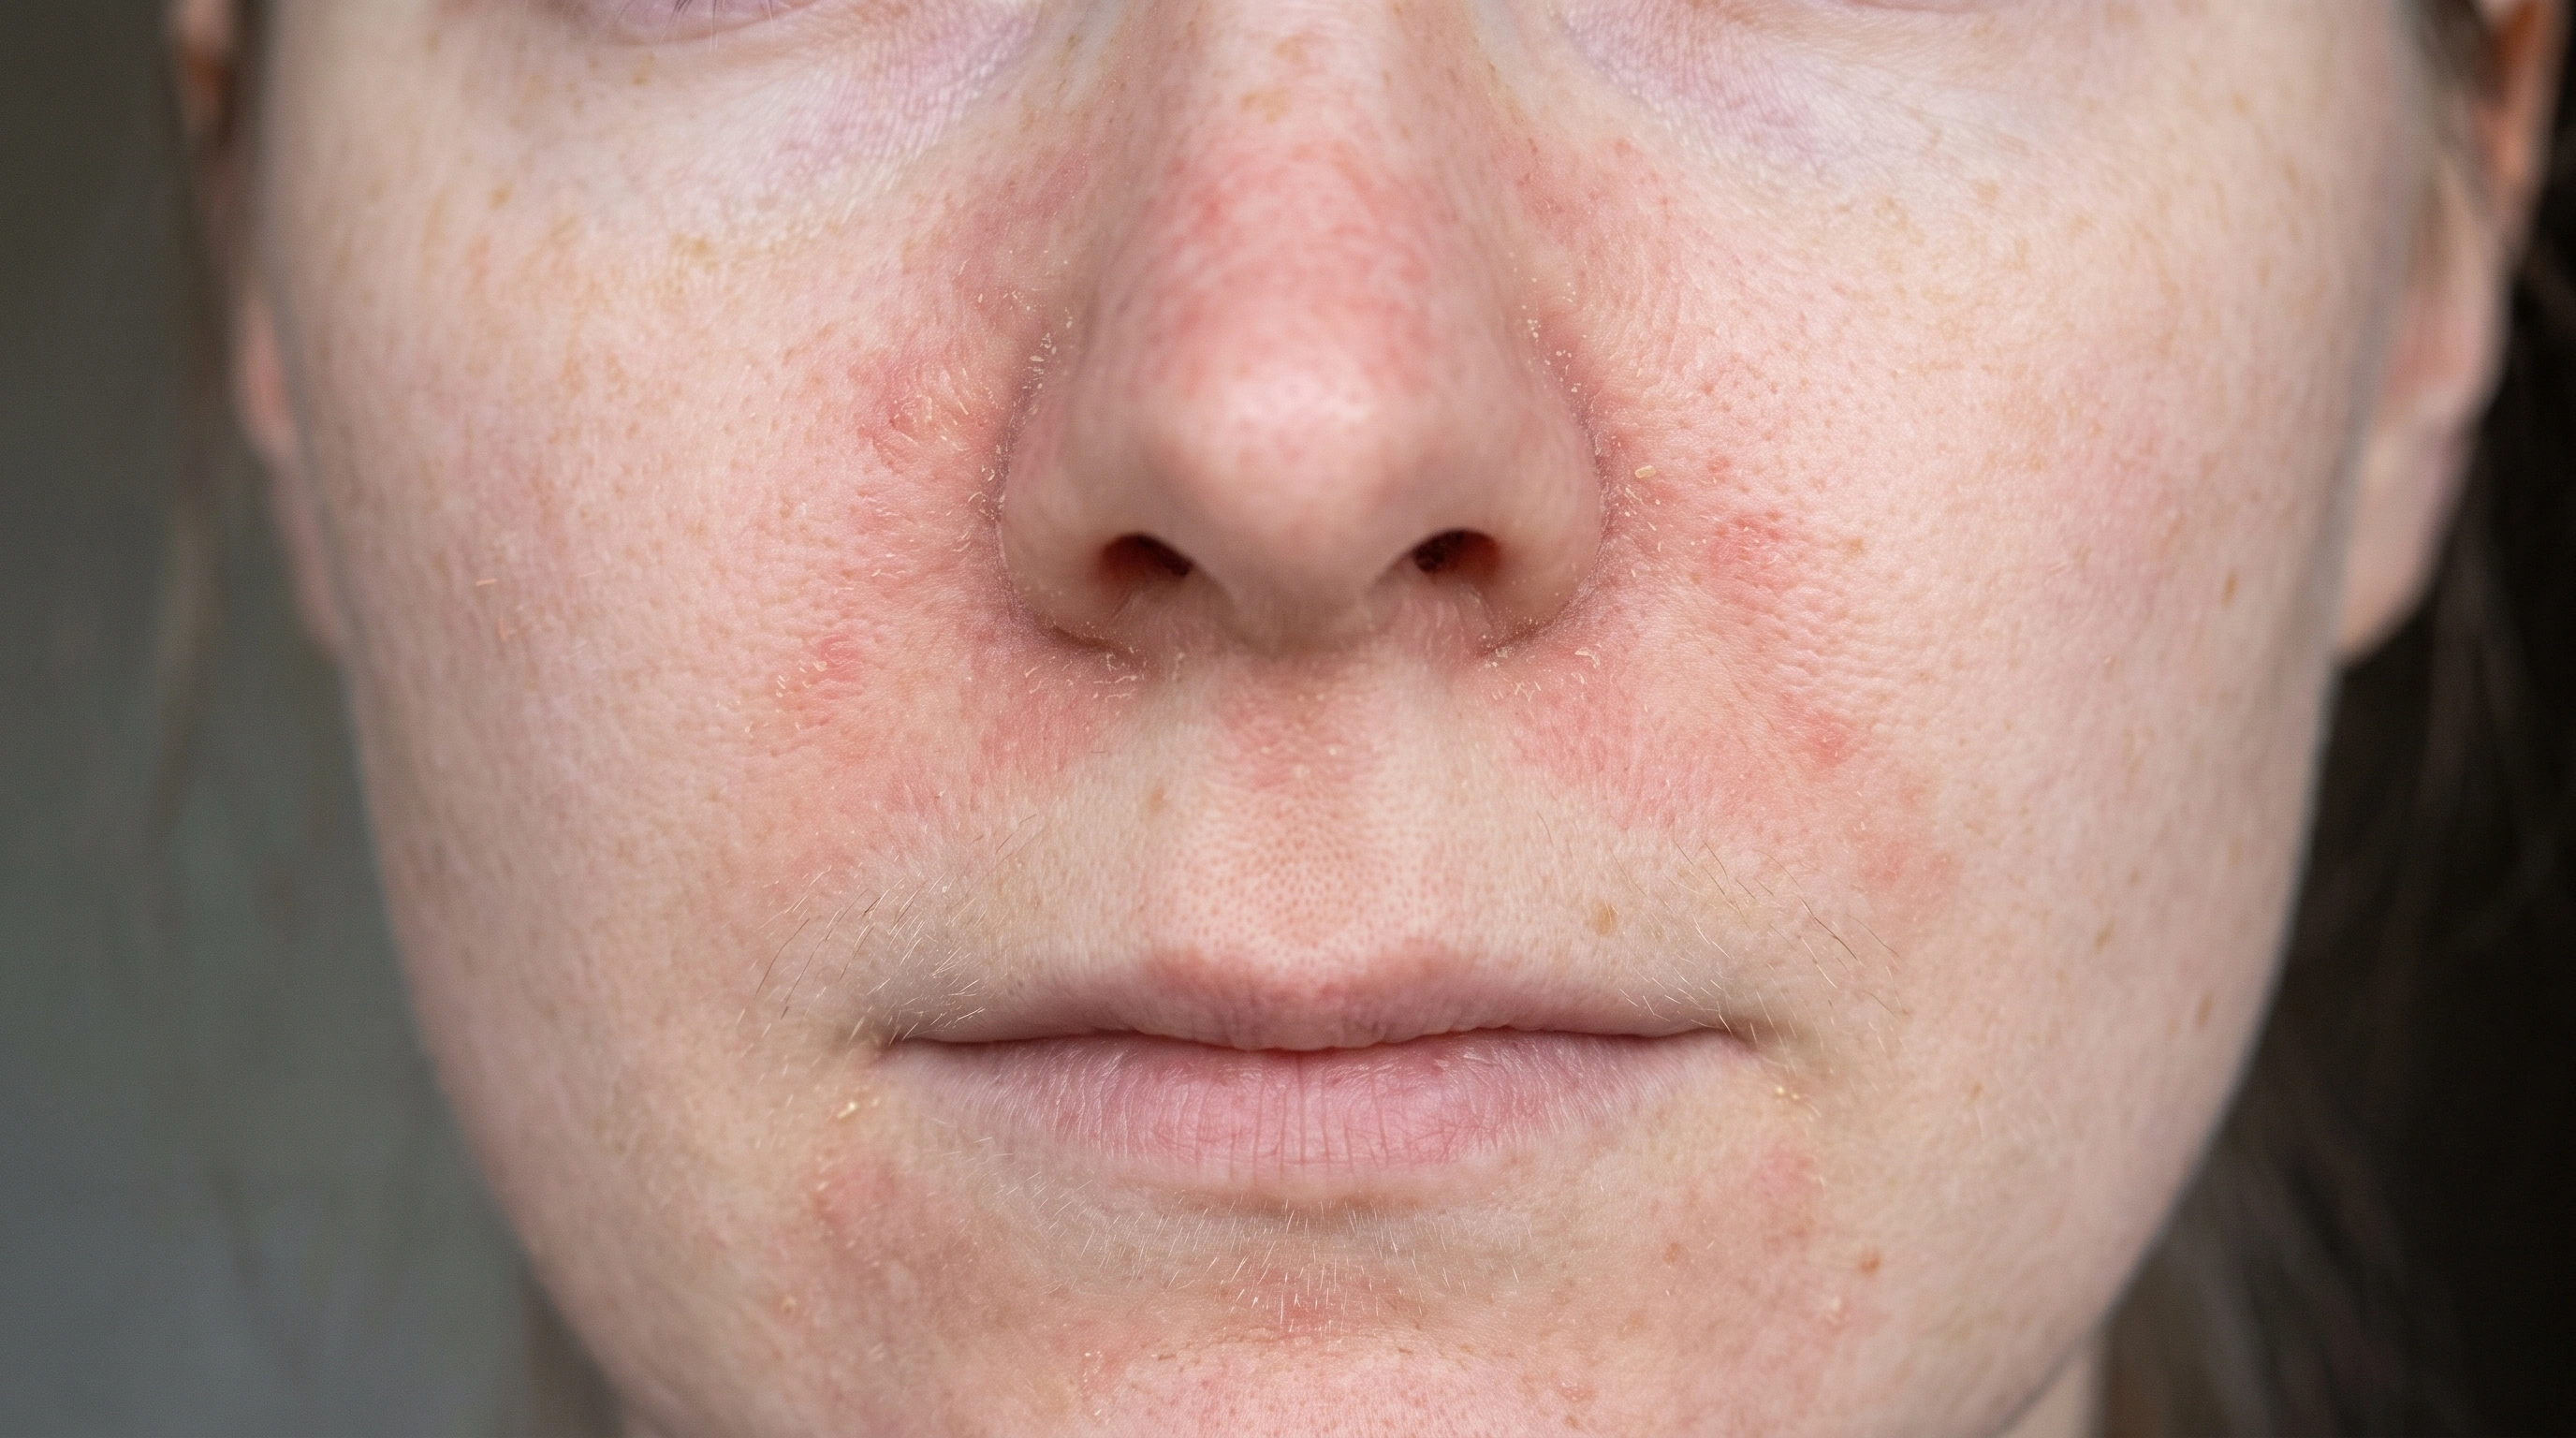
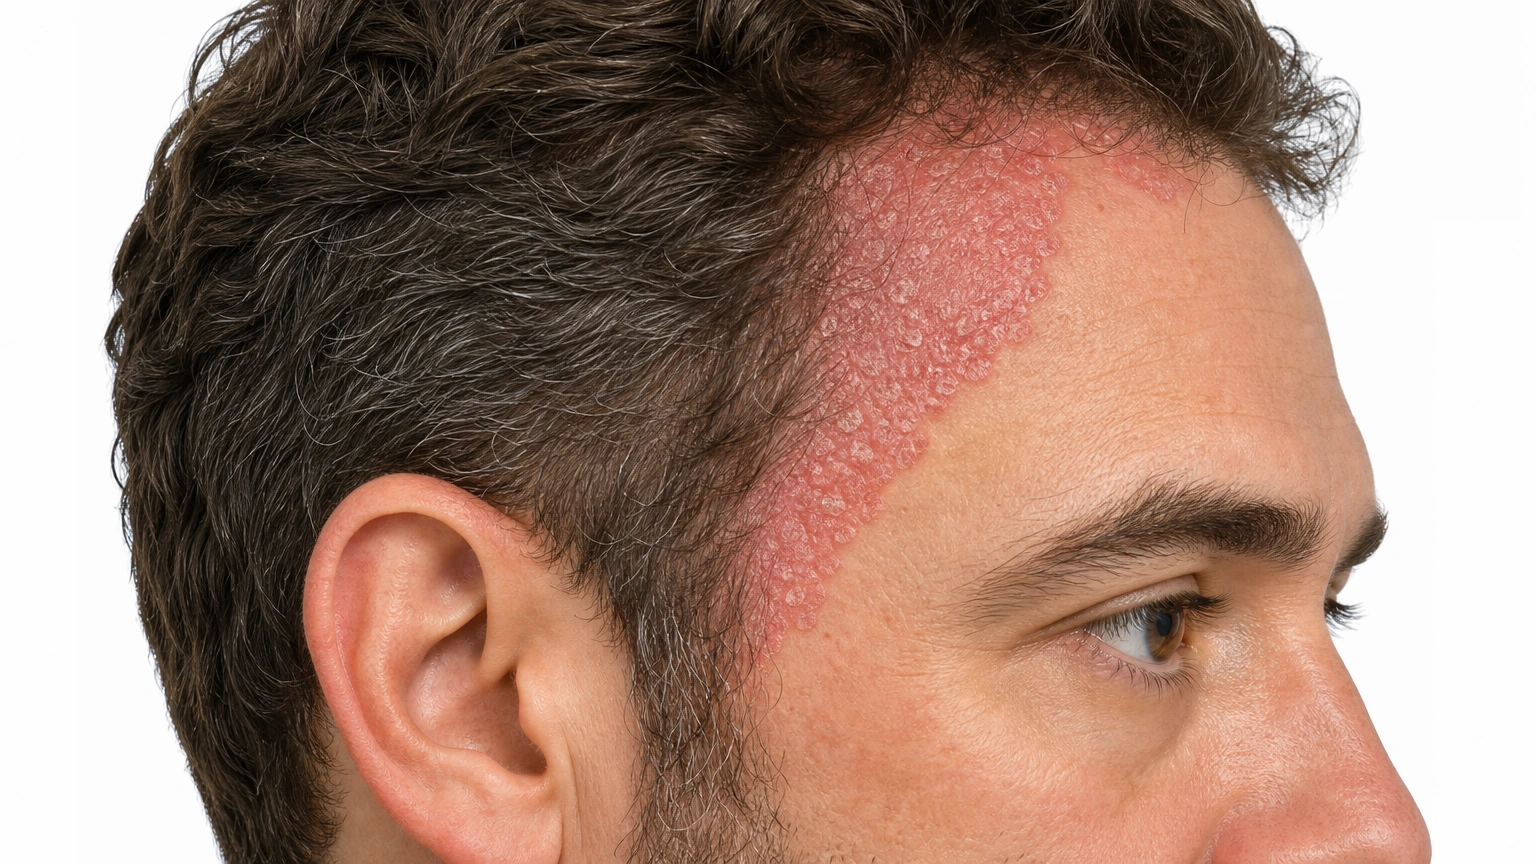
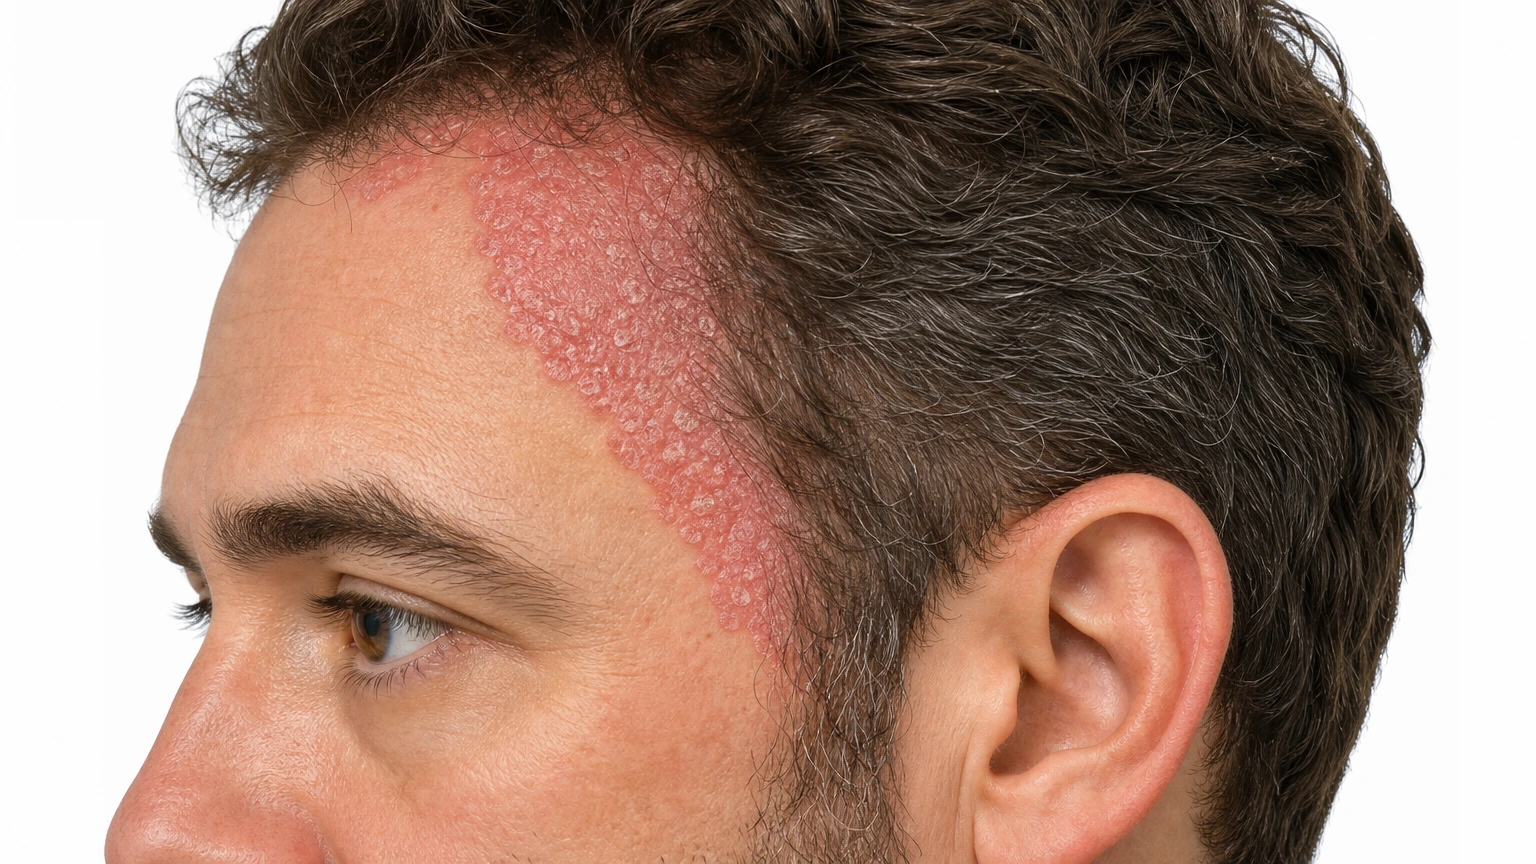
AI-generated educational illustration: Sharply bordered pink-red scaly psoriasis plaque at the adult facial hairline and temple, intact skin, no greasy dandruff-only scale. Not a clinical photograph.Tinea Faciei

Key differences

The same eight facts on every condition comparison.

Usual age
Any age
Any age
Where
Hairline, brows, behind ears, face
Face
Main sign
Pink scaly patches
Red patch with a raised edge
Itch or pain
Mildly itchy
Itchy, worse in sun
Contagious
No
Yes
Long term
Long-term; flares
Clears with antifungals
Scars
No
No
Who gets it
People with psoriasis elsewhere
Children, pet owners

What is it?

Facial Psoriasis
Tinea Faciei
What is it?
  • What it is
    Psoriasis affecting facial skin, often with psoriasis elsewhere.
  • What it is
    Ringworm infection of non-bearded facial skin.

What it looks like

Facial Psoriasis

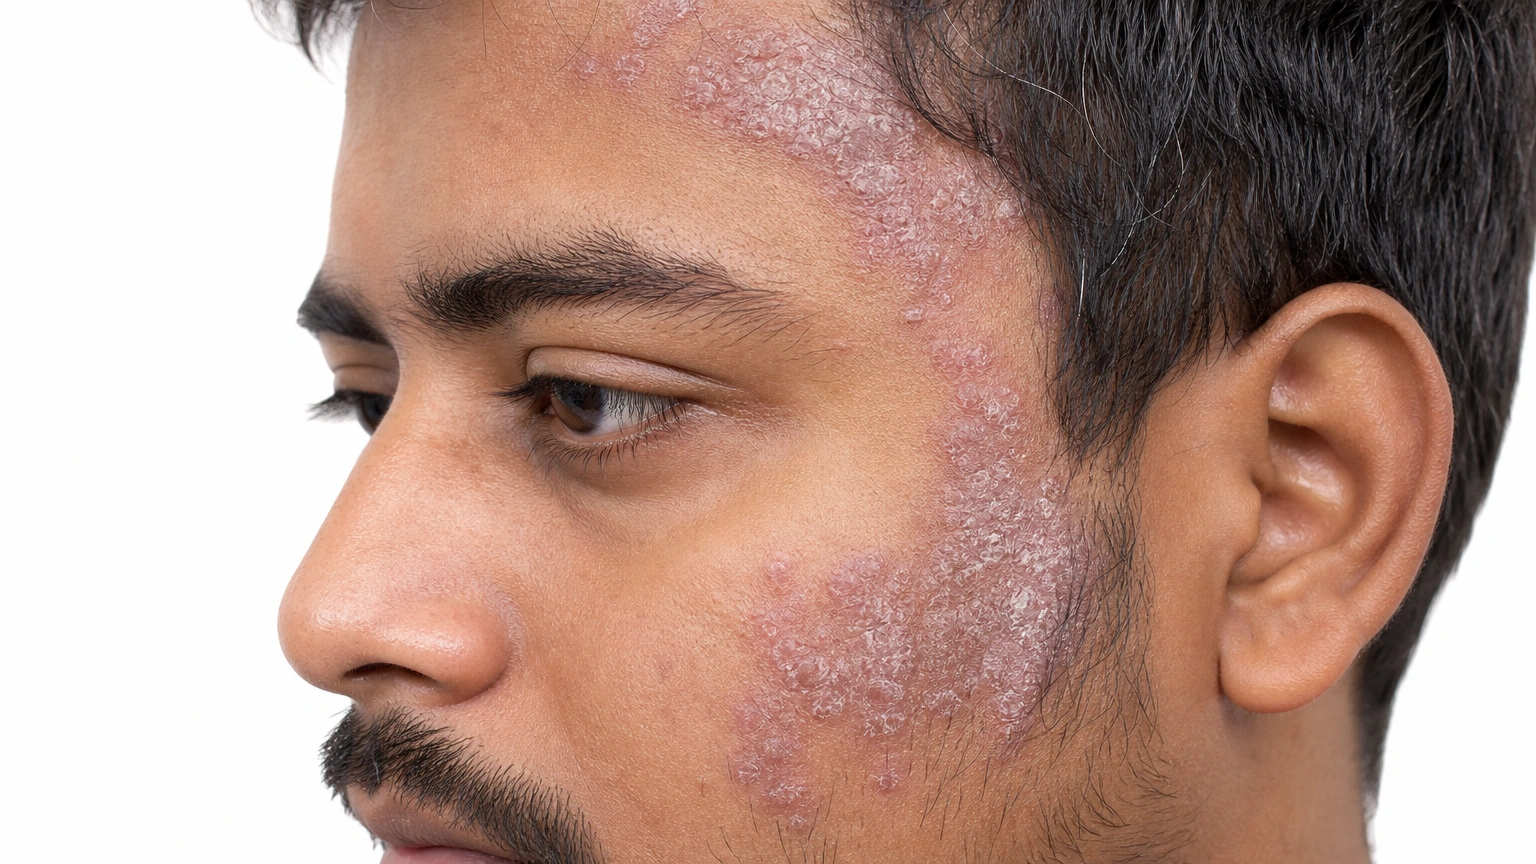
A red scaly plaque along the temple and front hairline.

Facial Psoriasis A sharply outlined patch extends from the scalp onto the forehead.

Tinea Faciei

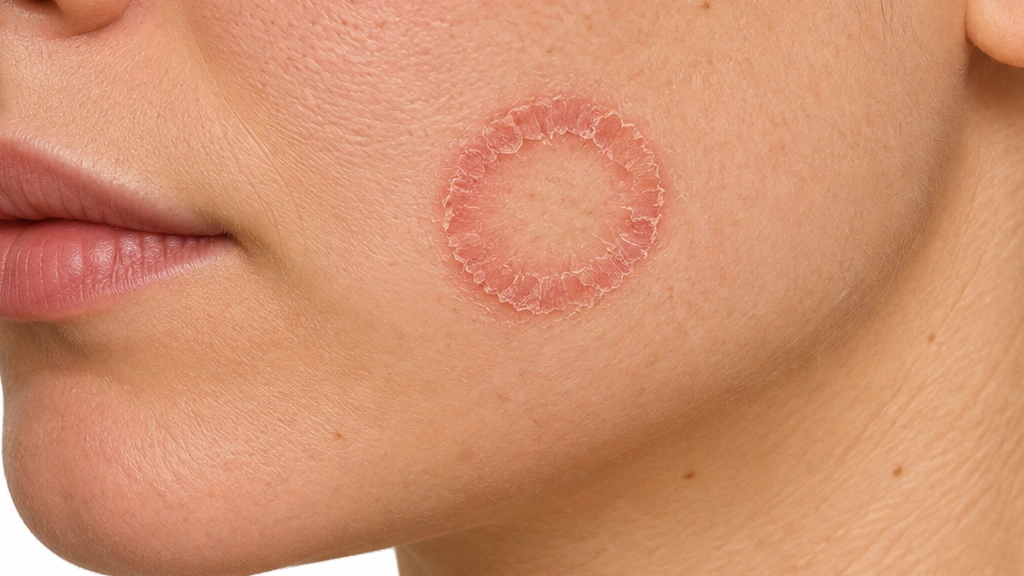
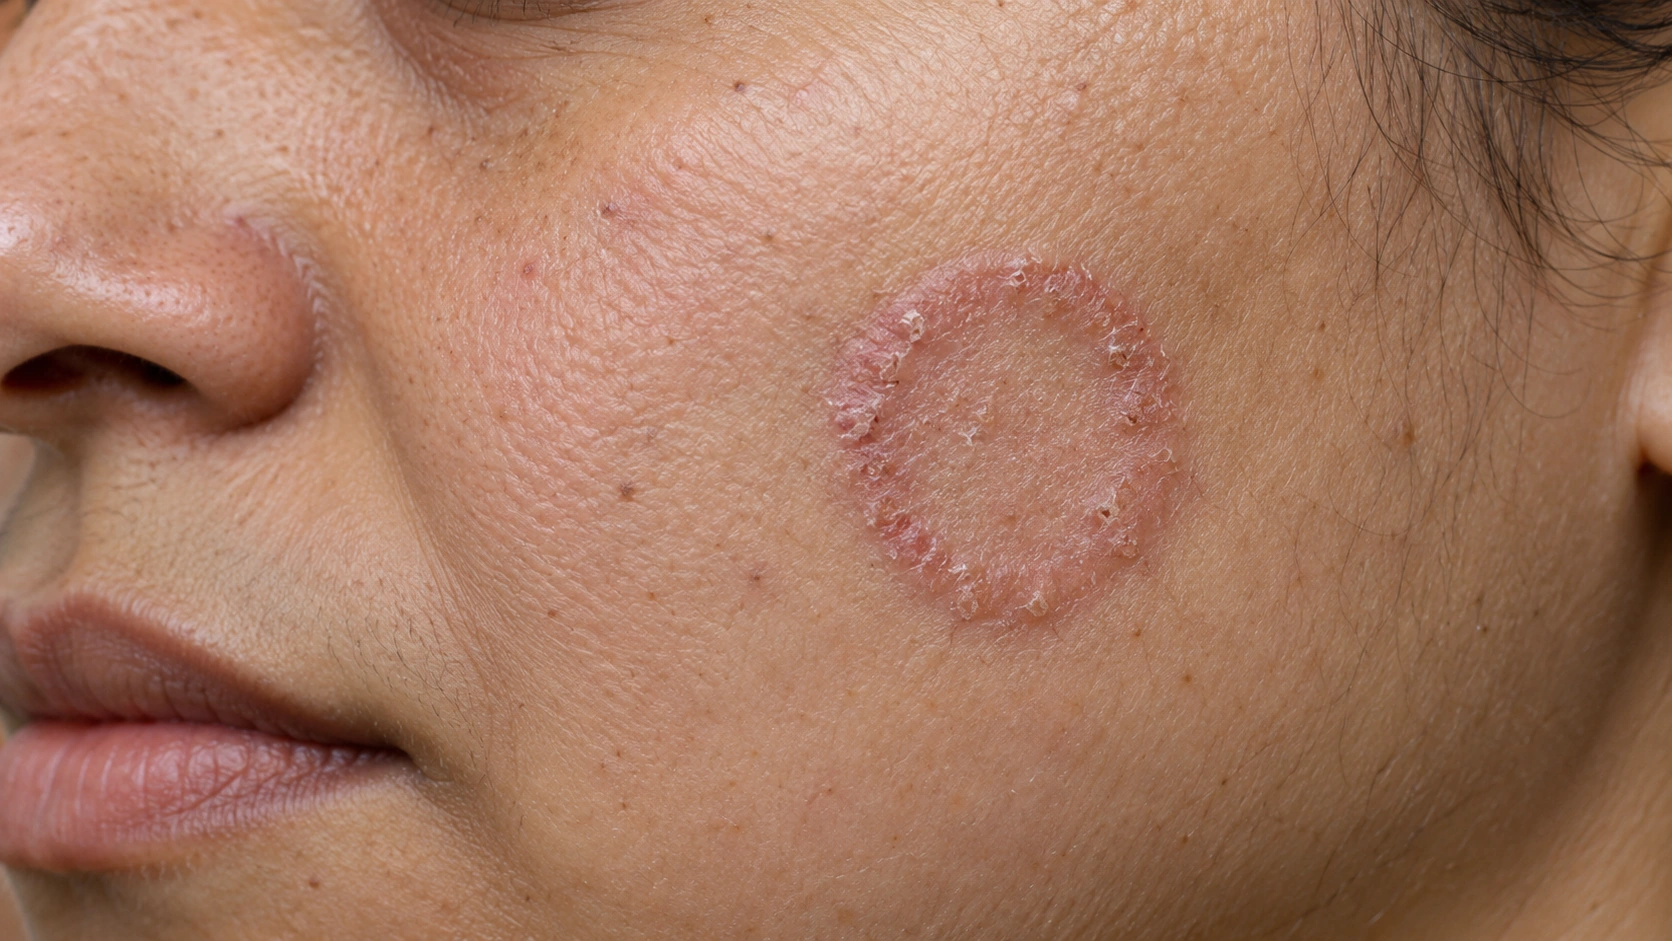
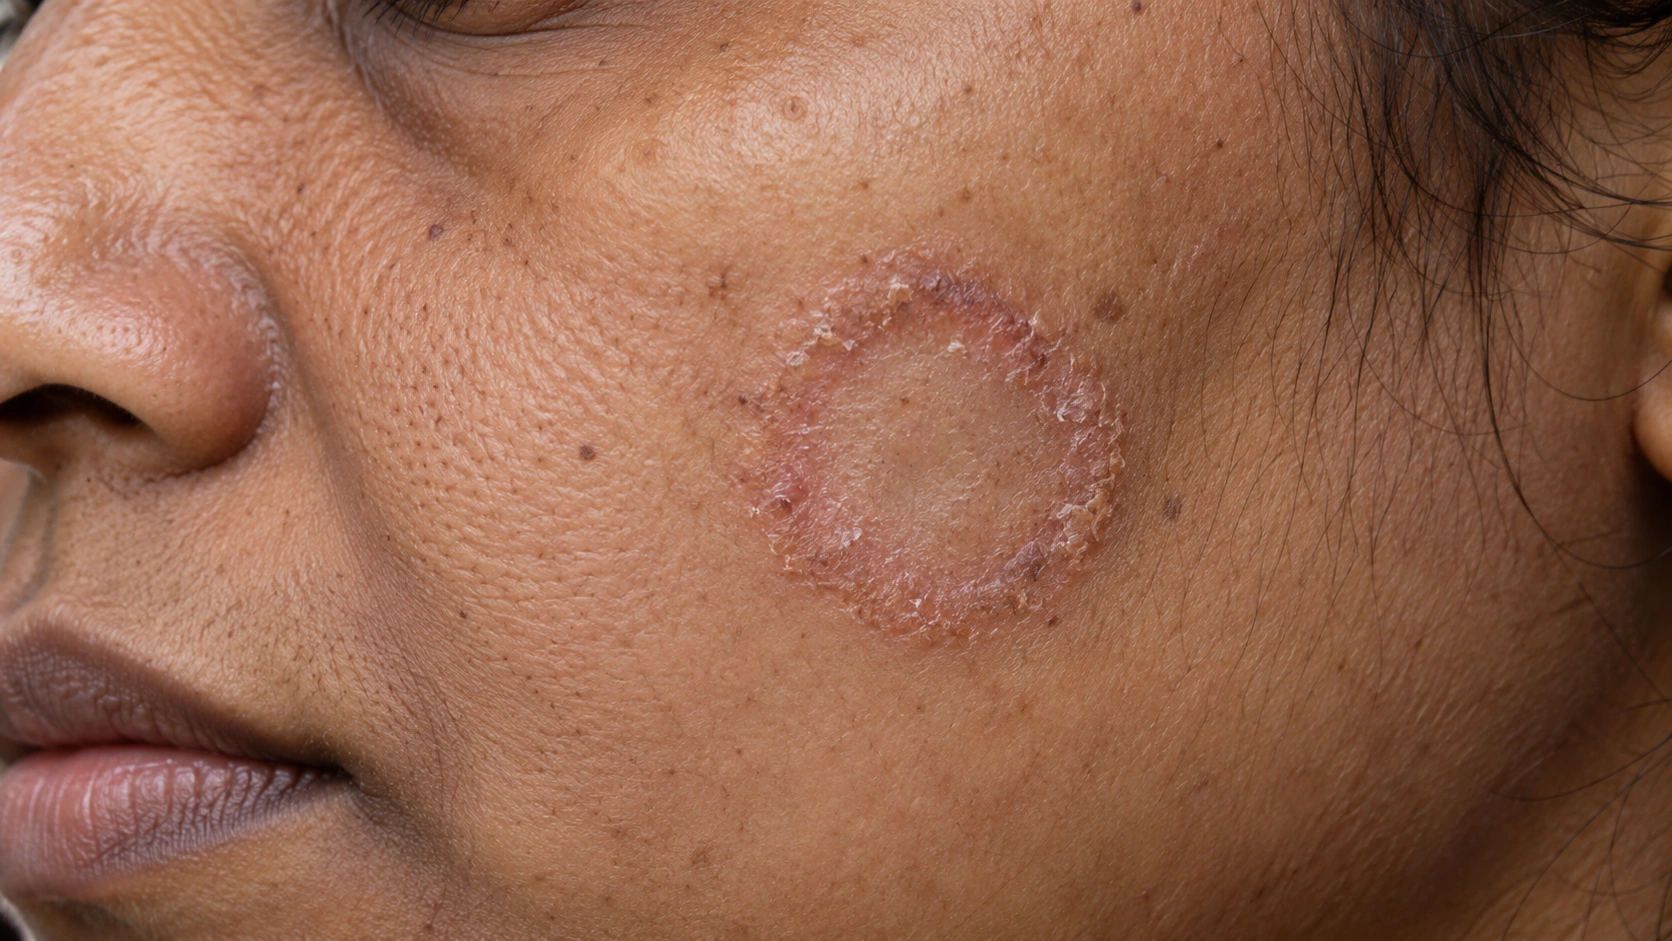
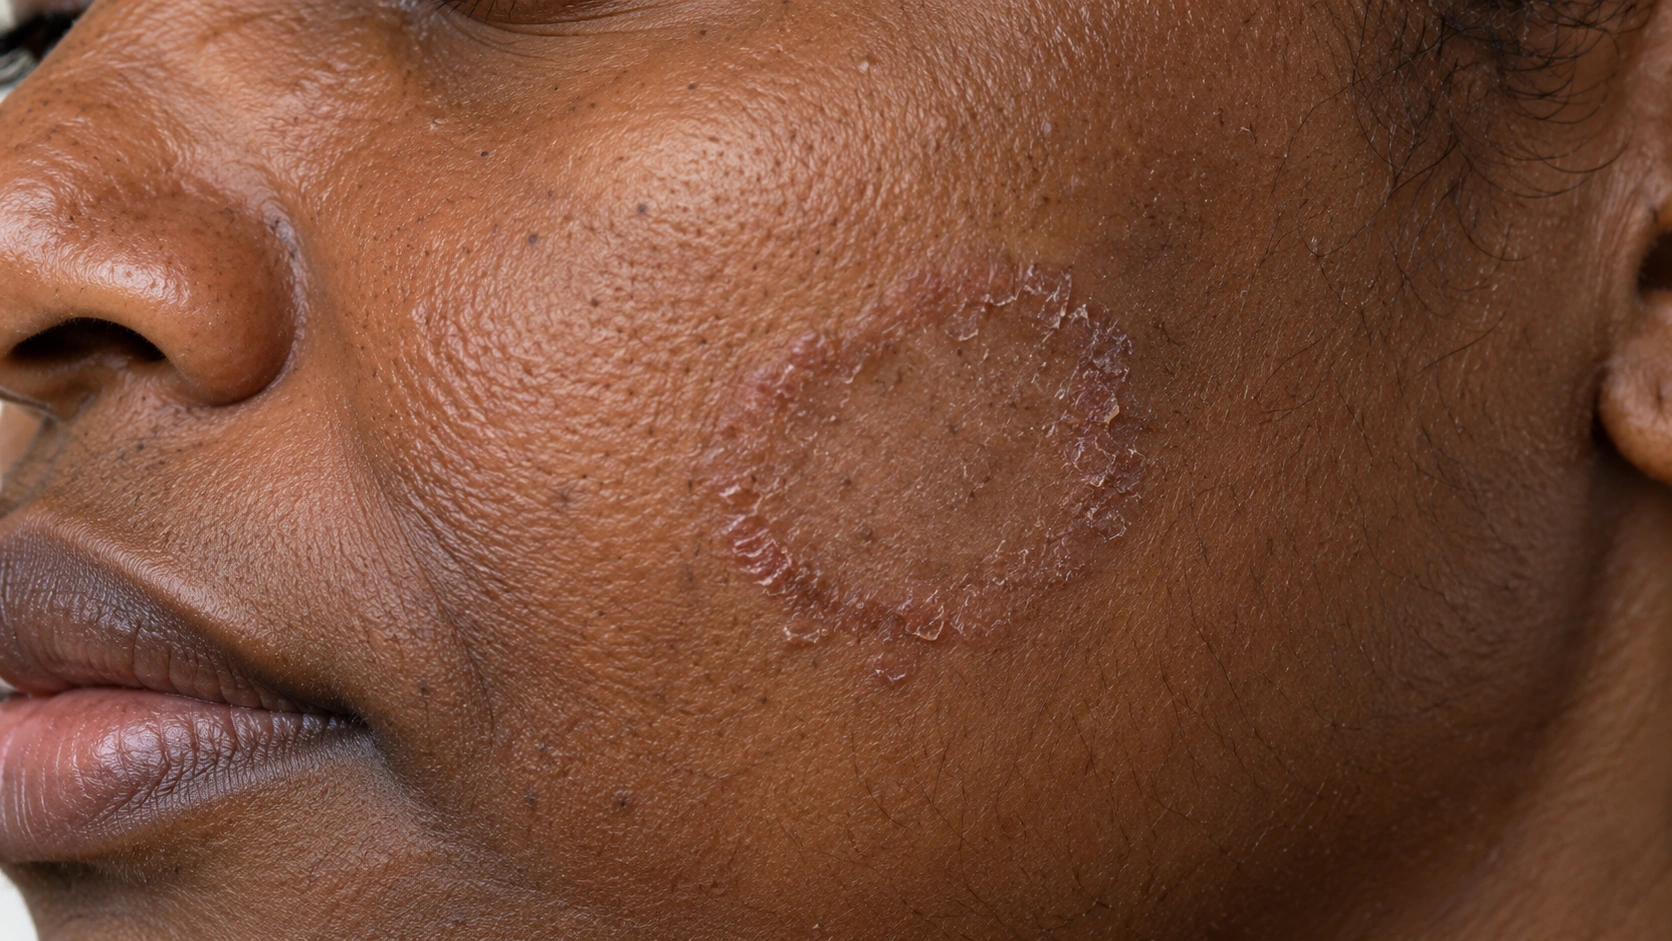
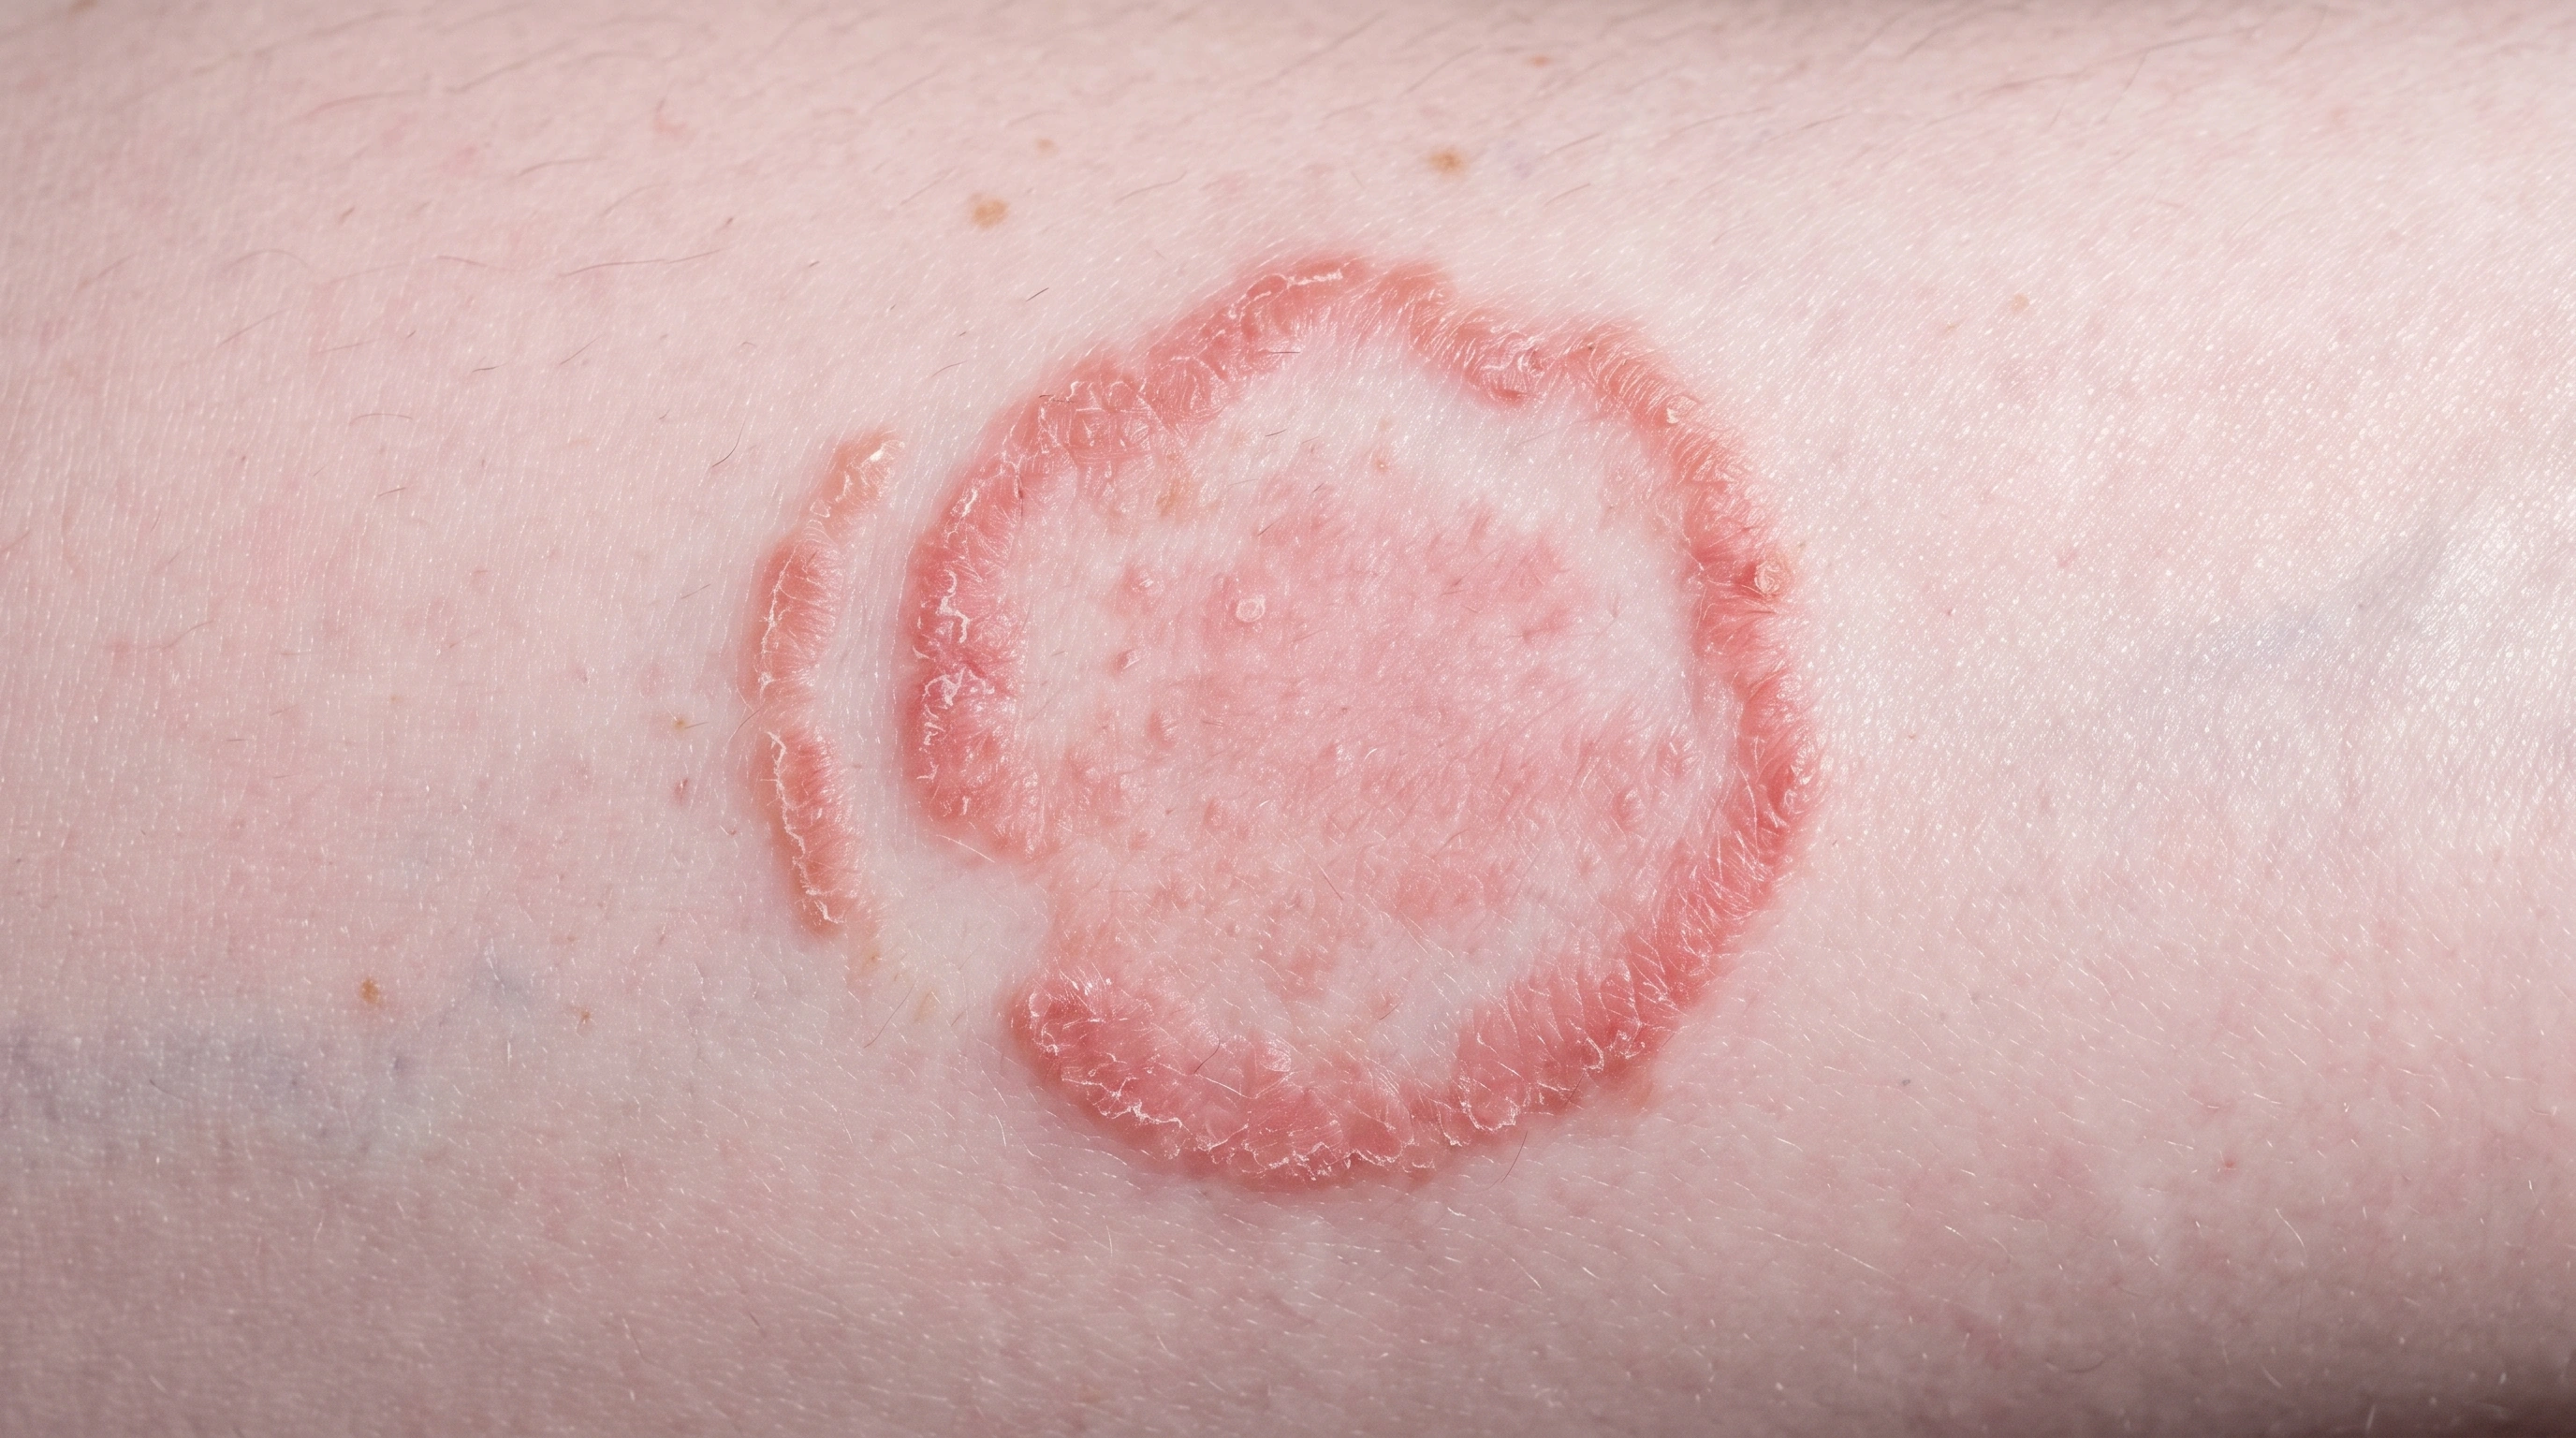
A cheek with a circular red scaly ring and relatively clear center.

Tinea Faciei A red outer rim surrounds a paler center.
Skin tones
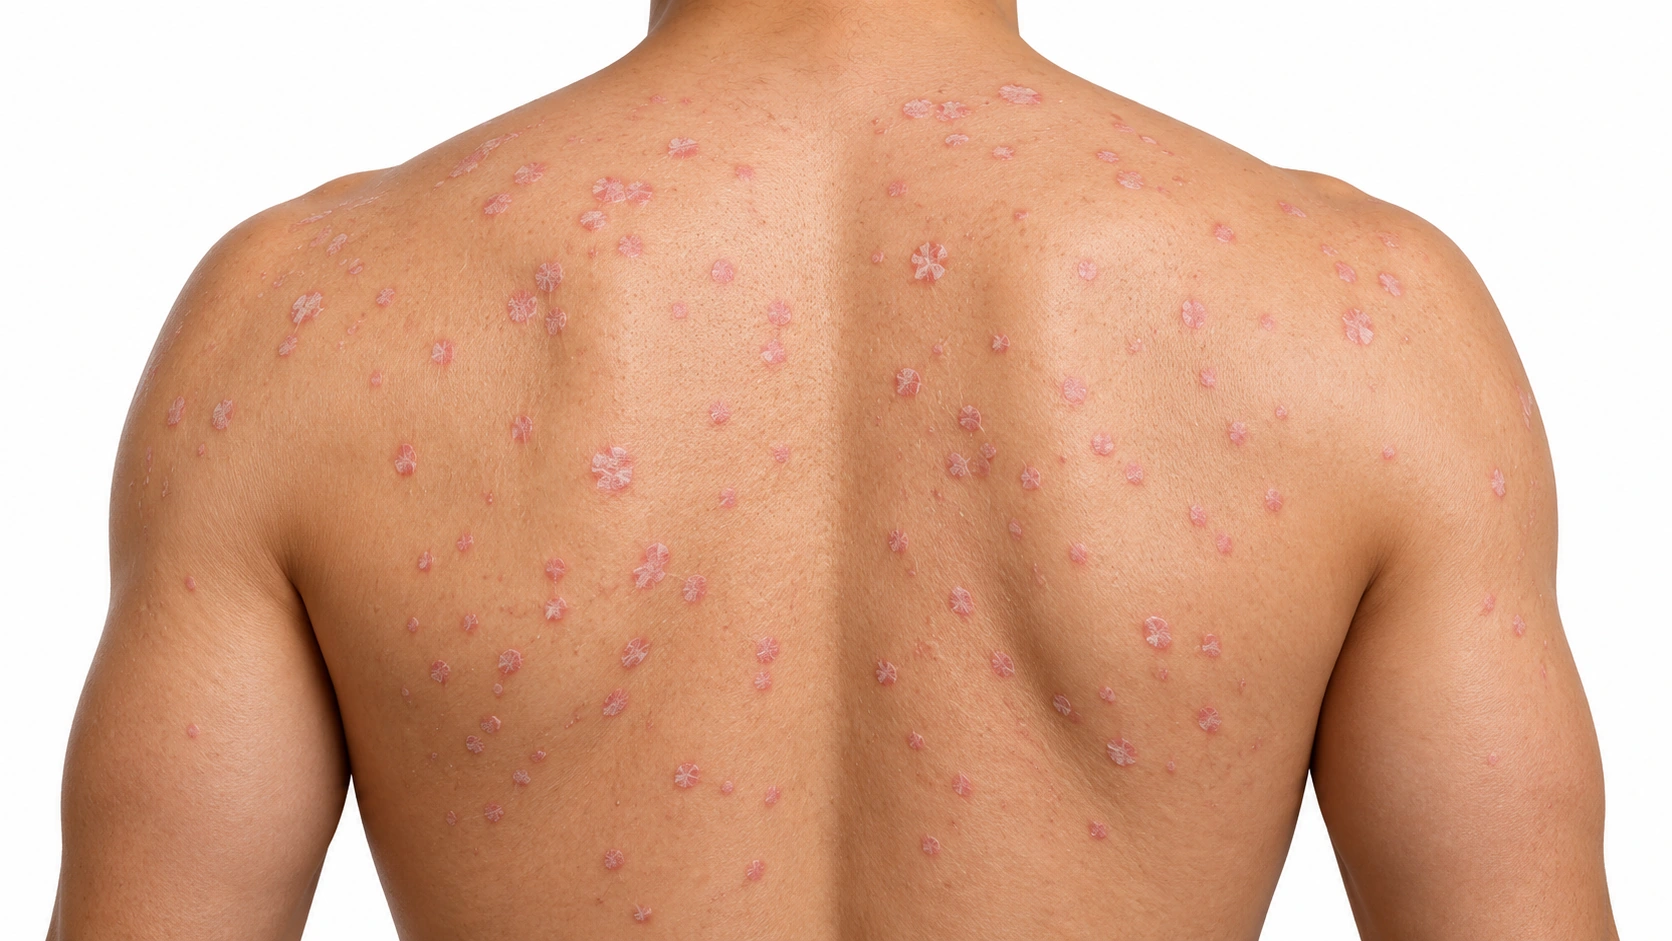
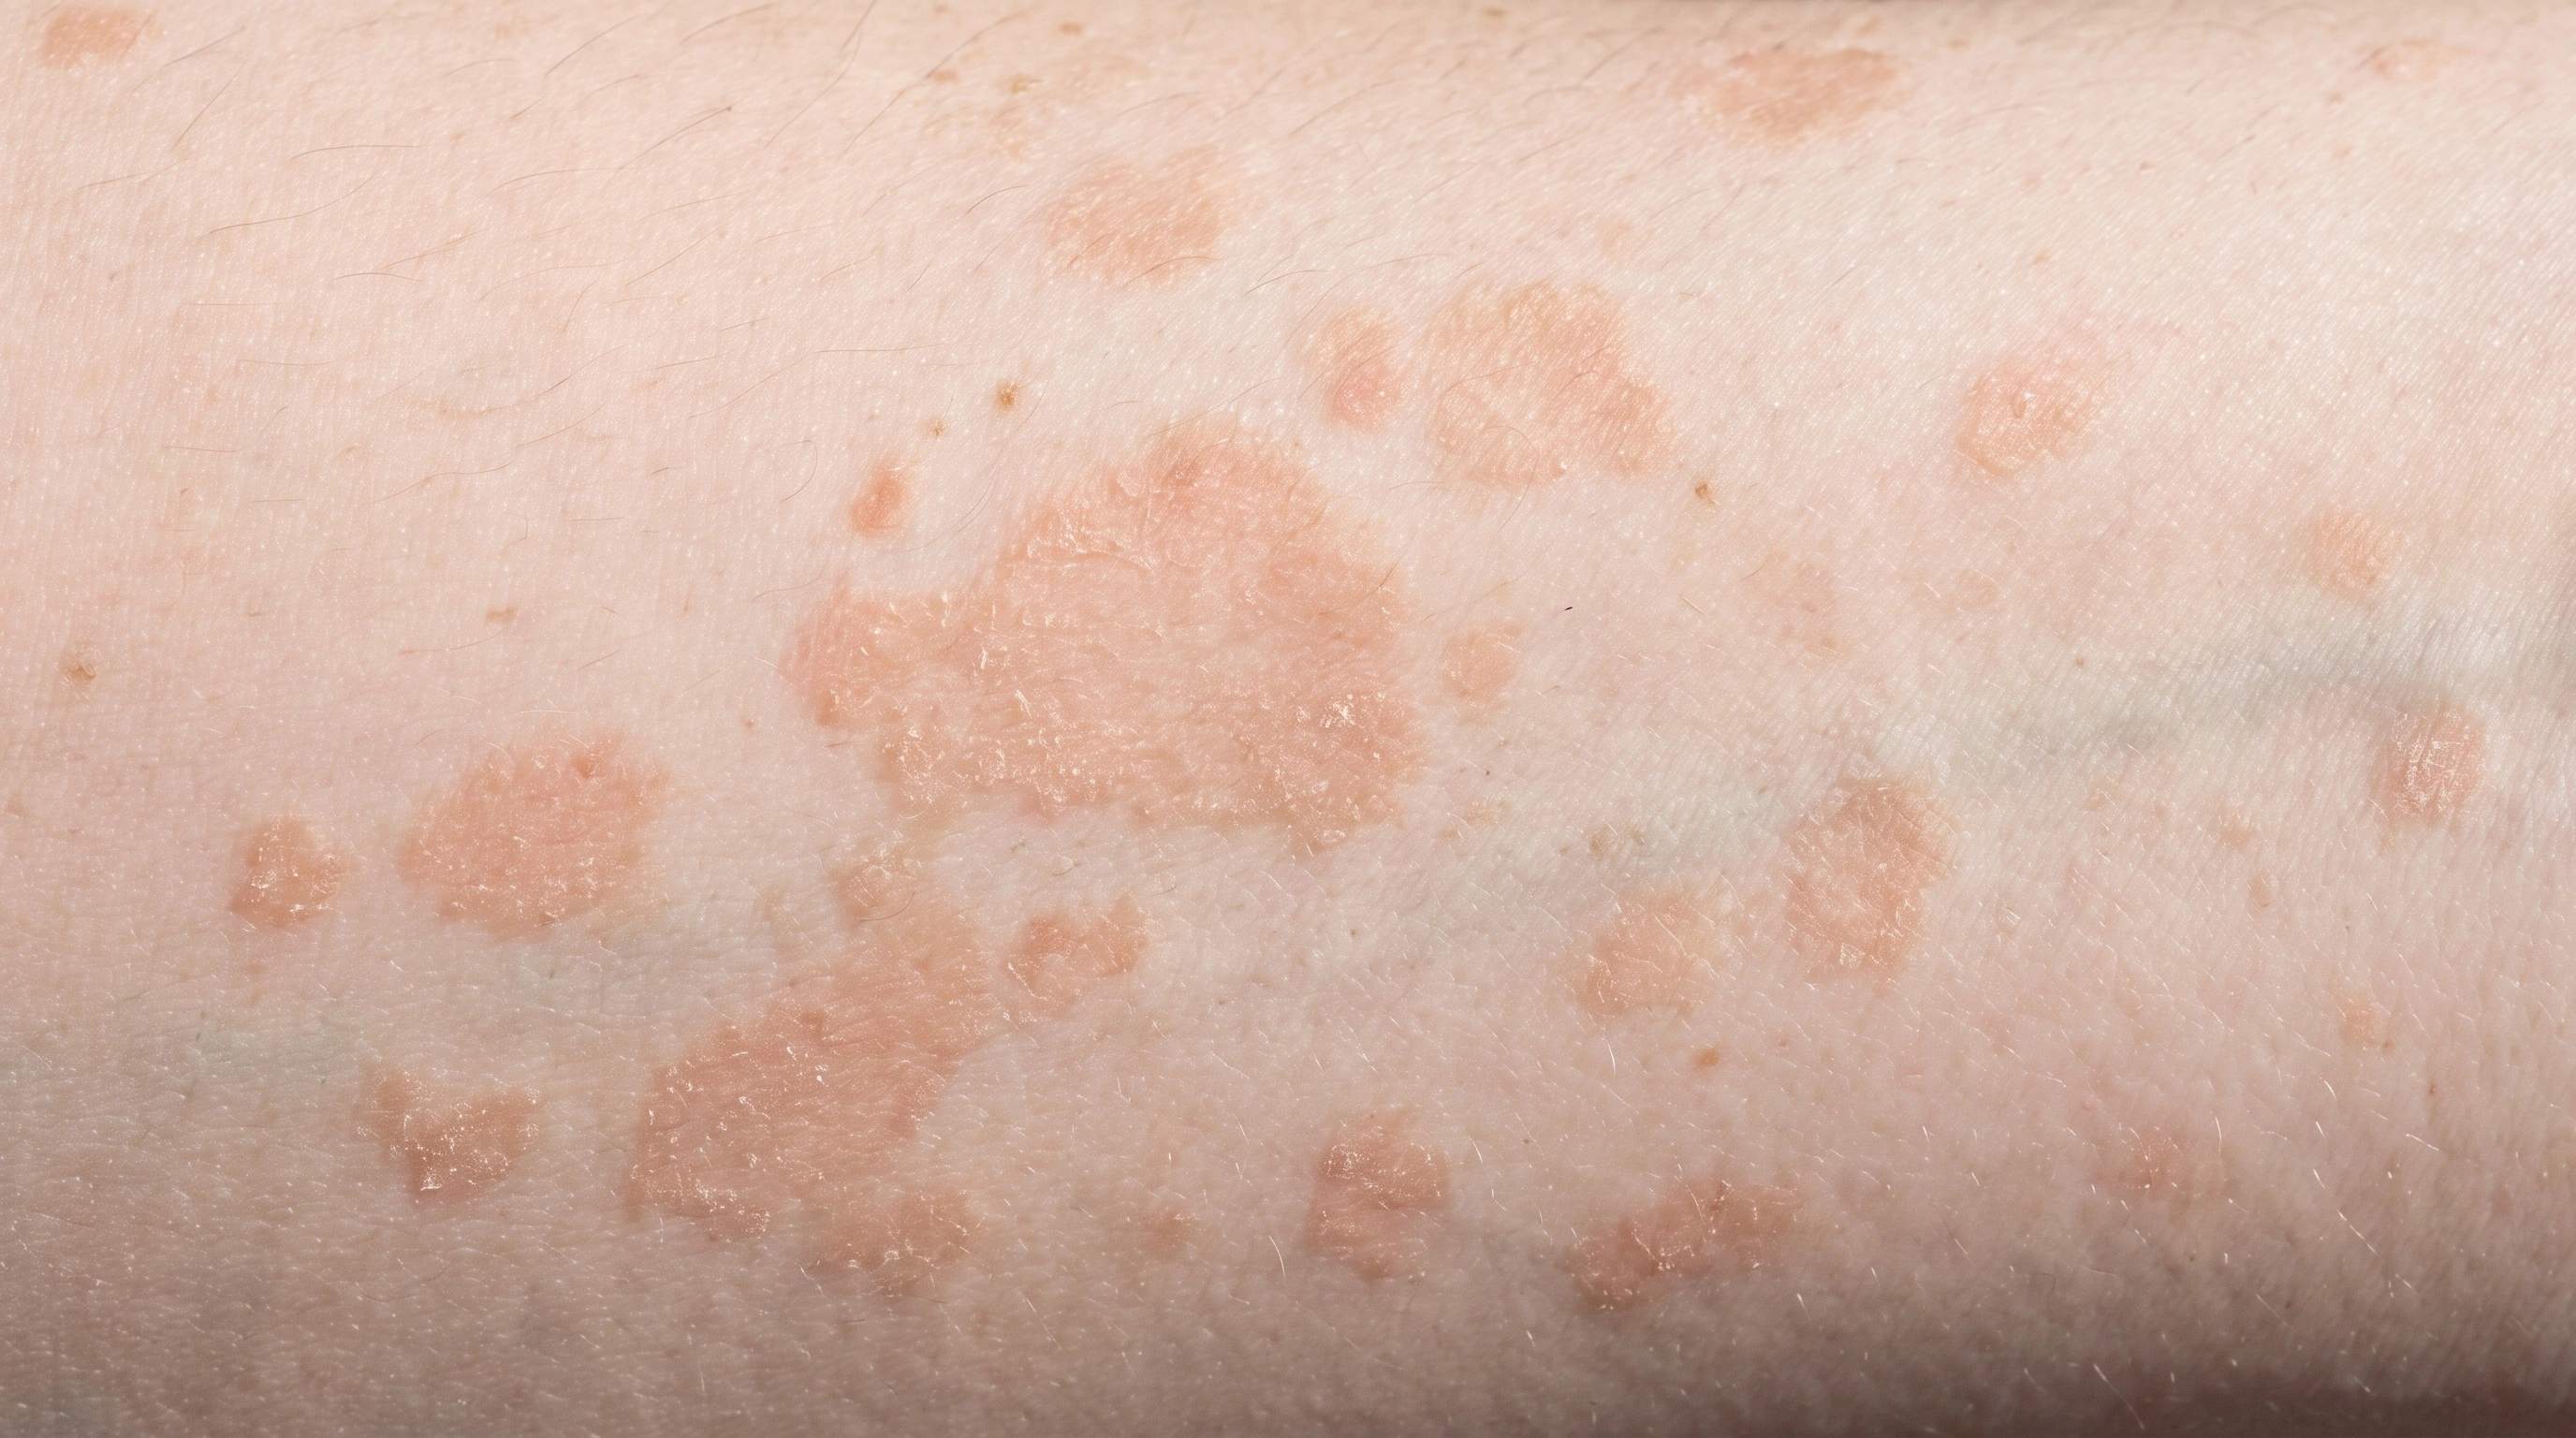
Facial Psoriasis on light skin.
Facial Psoriasis on medium skin.
Facial Psoriasis on brown skin.
Facial Psoriasis on deep skin.
Tinea Faciei on light skin.
An annular scaly patch with relative central clearing on the cheek.
In the skin

Immune inflammation accelerates skin-cell production in affected facial skin. The buildup of cells and inflammation create patches whose scale and appearance vary by location.

Dermatophyte fungi grow in the keratin of facial skin. The local inflammatory response can produce a scaly patch with an expanding edge.

When it usually starts

010203040506070+

Facial Psoriasis. Can start at any age, with different patterns at different life stages.

Tinea Faciei. Can occur at any age after exposure.

Causes and triggers

Causes

Immune inflammation speeds skin-cell turnover; psoriasis is not contagious.

Dermatophyte fungi infect keratin-containing skin or hair.

Risk factors
Family tendency, Immune susceptibility
Contact with an infected person or animal, Fungal infection elsewhere
Trigger
● Facial Psoriasis
● Tinea Faciei
Skin injury
Can contribute
Not listed
Stress
Can contribute
Not listed
Infection
Can contribute
Not listed
Fungal exposure
Not listed
Can contribute
Sharing contaminated items
Not listed
Can contribute

Daily Care

Facial Psoriasis
Tinea Faciei
Daily care

Habits that help

  • Moisturize regularly with a plain fragrance-free product
    Apply after washing and when skin feels dry or tight.
  • Keep washing gentle and water lukewarm
    Use a non-soap cleanser and pat dry rather than rubbing.
  • Protect sore skin from friction and minor injury
    Comfortable clothing and gentle handling reduce avoidable irritation.
  • Keep a manageable record of flares and symptoms
    Note new medicines, infections or joint symptoms to discuss at review.
  • Use only a face-specific prescribed treatment plan
    Facial skin is vulnerable to irritation and thinning; do not transfer a strong body steroid to the face.
  • Follow the facial psoriasis care plan
    Use gentle moisturizer and clinician-selected facial treatment; potent body steroids are unsuitable for routine facial use.

Avoid

  • Avoid: Picking scale or scratching plaques
    Injury can worsen psoriasis and create breaks in the skin.
  • Avoid: Unsupervised tanning or harsh home exfoliation
    Sunburn and irritation can trigger worsening; prescribed phototherapy is different from tanning.

Habits that help

  • Keep the affected area gently clean and dry
    Pat rather than rub and change clothing or headwear that stays damp.
  • Keep towels, combs, brushes and razors for your own use
    Wash shared fabrics and clean personal tools to reduce spread.
  • Wash hands after touching affected skin
    Avoid scratching or moving fungal material to other areas.
  • Complete the prescribed antifungal plan
    Symptoms may improve before infection has fully cleared.

Avoid

  • Avoid: Steroid cream alone on a suspected fungal rash
    It can hide the appearance and allow infection to spread.
  • Avoid: Relying on hygiene alone to clear the infection
    Persistent disease needs the correct diagnosis and antifungal treatment.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Facial Psoriasis
● Tinea Faciei
Over-the-counter
None listed
Existing educational treatment illustration: Spinosad

Terbinafine cream

Listed

A topical antifungal option for localised dermatophyte skin infection; follow the product course and avoid eyes.

Prescription topicals

Site-specific anti-inflammatory treatment

Listed

A brief mild steroid or a steroid-sparing agent may be selected for face, folds or genital skin; avoid potent body steroids without guidance.

None listed
Prescription pills
None listed

Oral antifungal assessment

Listed

Widespread or persistent infection may require a prescription after confirming the diagnosis.

Outlook

Long term

Facial psoriasis commonly follows a long-term pattern of flares and improvement. Suitable treatment can control it, but the sensitive facial skin needs a site-specific plan and review.

Facial ringworm generally clears with appropriate antifungal treatment. Reinfection can occur if a source remains; a rash altered by steroid use may need testing and a revised plan.

Complications

Possible complications

Psoriasis can accompany inflammatory joint disease. Report persistent joint stiffness or swelling.

An untreated infection can spread to contacts or other sites; inflamed hair infection can scar.

When to get help

When to get help

Seek care for painful cracks, widespread flares, joint symptoms or uncertain diagnosis.

Seek assessment if the diagnosis is uncertain; painful swollen scalp or beard lesions need prompt care.

Common questions

Facial Psoriasis:What is Facial Psoriasis?

Psoriasis affecting facial skin, often with psoriasis elsewhere.

Facial Psoriasis:What can I do day to day?

Use gentle moisturizer and clinician-selected facial treatment; potent body steroids are unsuitable for routine facial use.

Facial Psoriasis:When should I get medical advice?

Seek care for painful cracks, widespread flares, joint symptoms or uncertain diagnosis.

Tinea Faciei:What is Tinea Faciei?

Ringworm infection of non-bearded facial skin.

Tinea Faciei:What can I do day to day?

Avoid steroid treatment alone; it can disguise and worsen fungal infection. Do not share towels.

Tinea Faciei:When should I get medical advice?

Seek assessment if the diagnosis is uncertain; painful swollen scalp or beard lesions need prompt care.

Sources
Sources and further reading

  1. Facial psoriasis
  2. Tinea faciei
Dermapedia on YouTube