Eczema
Calms flares on the body.
Eucrisa: A non-steroid ointment for mild to moderate eczema. It can be used on the face and in skin folds, and there is no limit on how long it can be used. Triamcinolone: The mid-strength topical steroid most rashes on the body get treated with. Cheap, effective, and not meant for the face, eyelids or skin folds.


Choose for mild to moderate eczema when you want a non-steroid you can use anywhere, for as long as needed.
Choose for most rashes on the body — cheap and effective, but not for the face, eyelids or folds.
Can you take them together?
A common pairing: triamcinolone for body flares, Eucrisa for steroid-free maintenance.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.



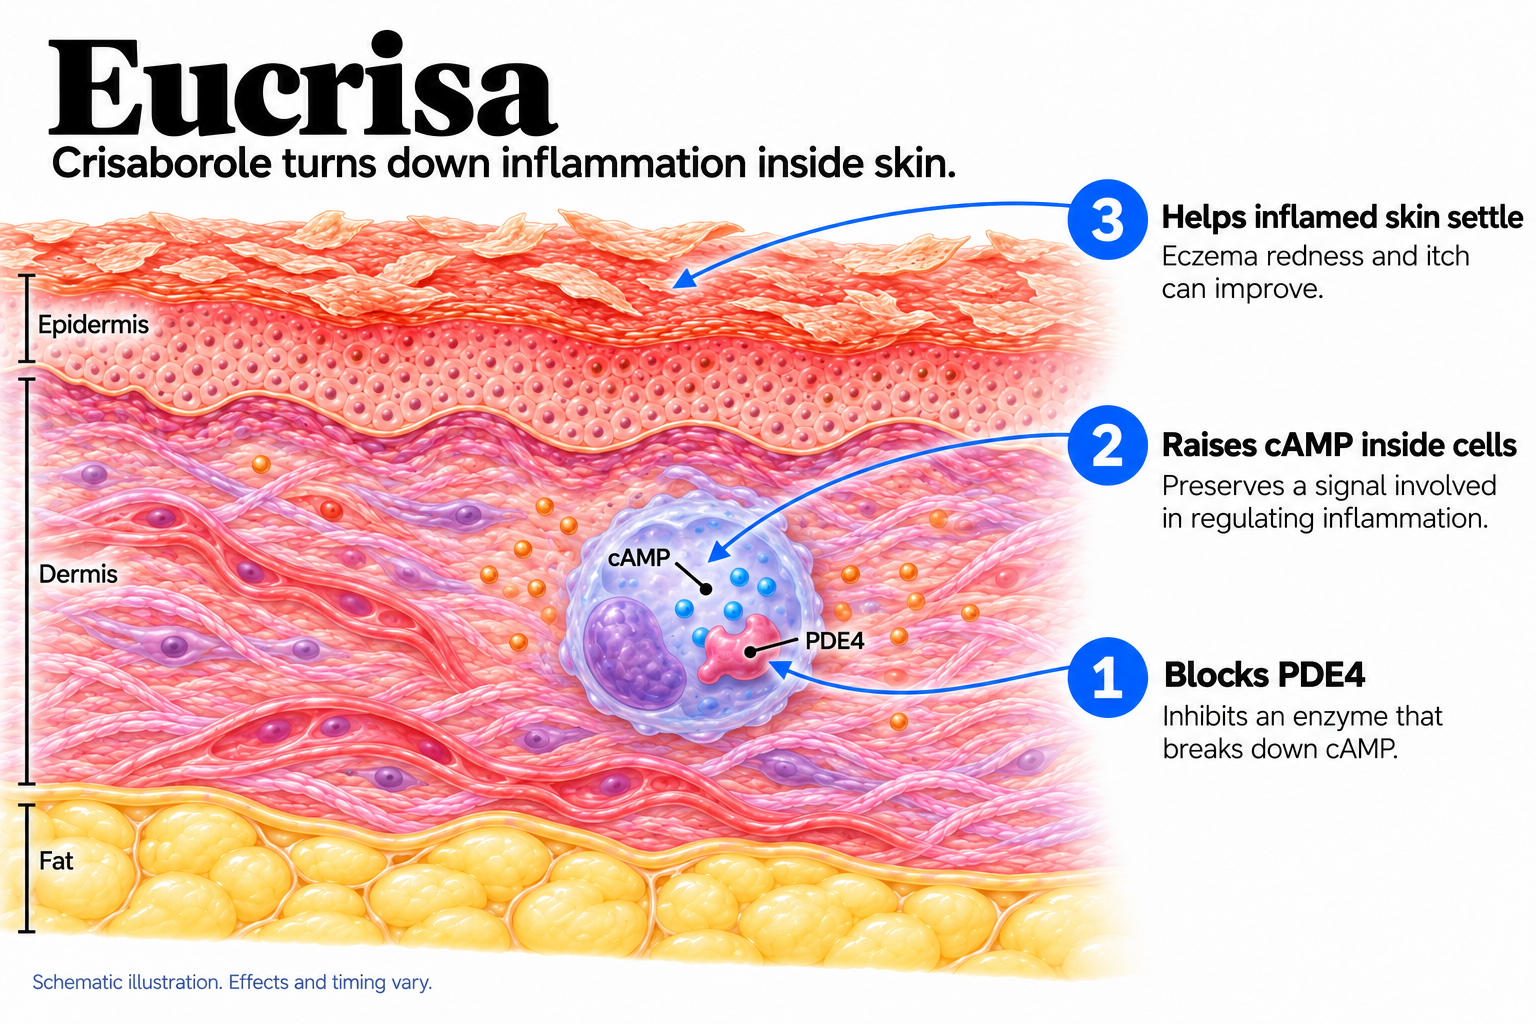
Blocks PDE4: Inhibits an enzyme that breaks down cAMP. Raises cAMP inside cells: Preserves a signal involved in regulating inflammation. Helps inflamed skin settle: Eczema redness and itch can improve.
PDE4 inhibition and increased intracellular cAMP are established. The exact link to clinical improvement is not fully defined; this is a simplified overview, not every downstream pathway.
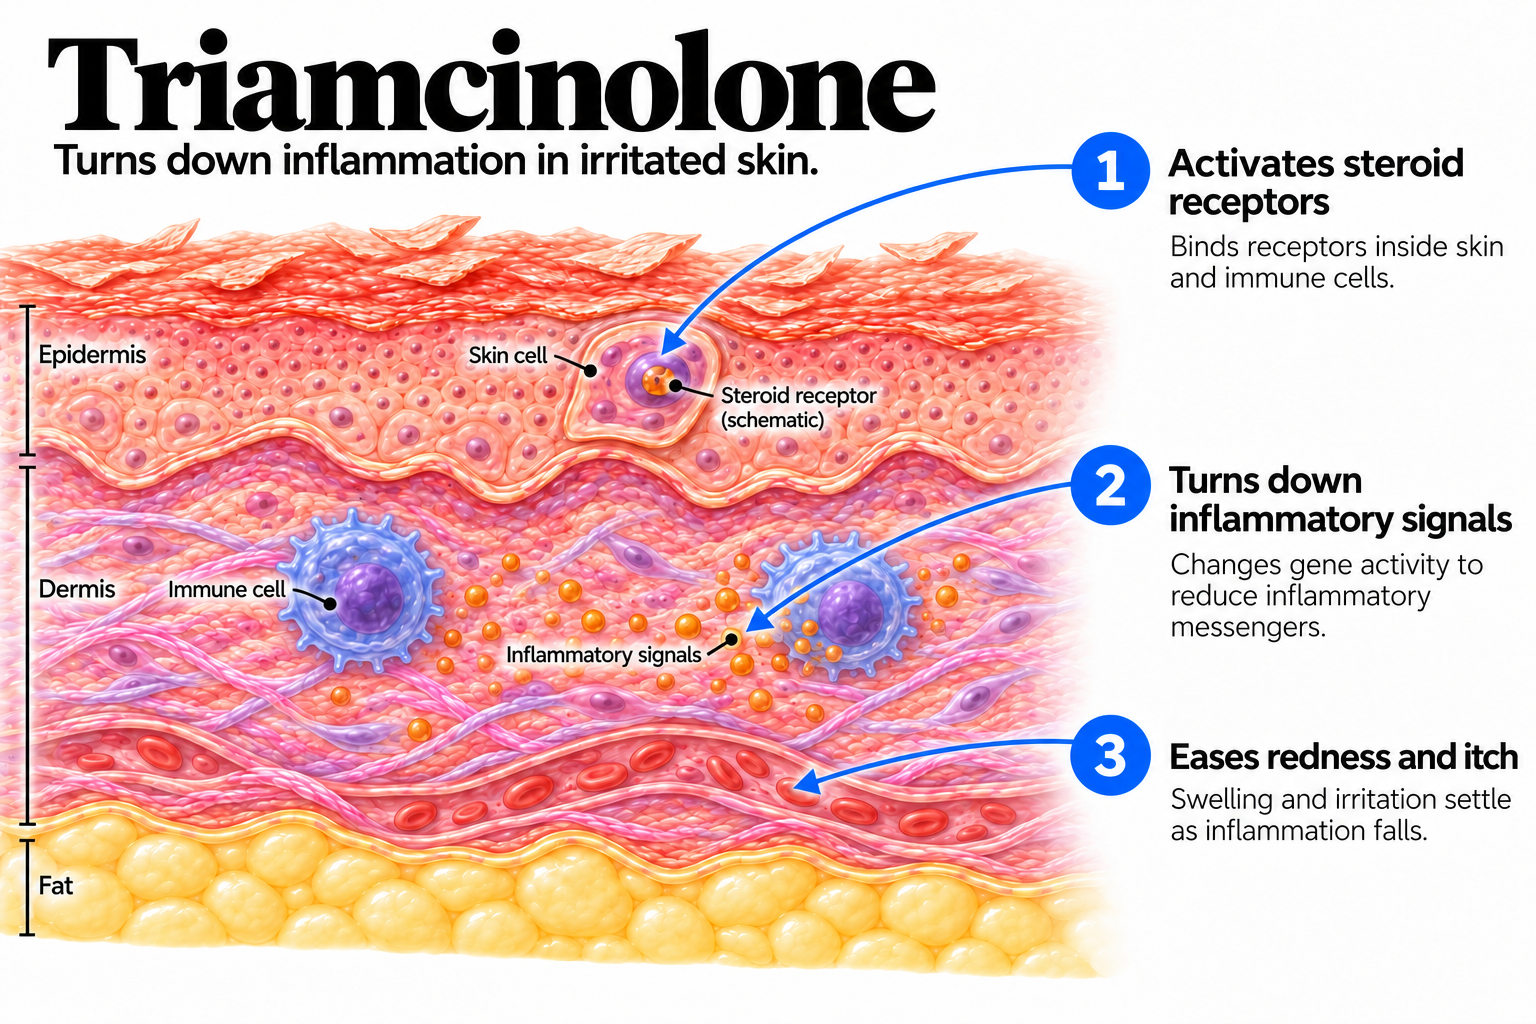
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.
When to Apply: A thin layer twice a day on the inflamed areas, on clean dry skin. Moisturizer goes everywhere, including over the top once it has settled.
How to Start: Twice daily from day one, on the flaring areas only, not over the whole body as a preventive. If the stinging is hard to tolerate, moisturize first and use the ointment straight from the fridge. The stinging usually fades within the first week.
If It Irritates: Burning or stinging for a few minutes after applying is the commonest effect, and usually not an allergy. It settles as the skin heals. Redness spreading beyond where you applied it, or stinging that gets worse rather than better after two weeks, should be reviewed.
If It's Not Working: There is one strength, so there is nothing to increase. Four weeks of proper twice-daily use is a fair trial. After that: a different non-steroid, a short steroid course to break the flare, or a look at what else is driving the rash.
When to Apply: Twice a day, on affected skin only, on trunk and limbs. A thin film is enough — one fingertip unit, the amount along the last joint of an index finger, covers about two adult palms. Moisturizer goes on separately, and continues after the steroid stops.
How to Start: Twice daily from day one, until the rash is flat rather than merely calmer — usually one to two weeks. Two to four weeks is the outer limit before review. Not on the face, eyelids, armpits or groin unless a clinician has told you to and for how long.
If It Irritates: Stinging usually comes from the base on cracked skin or the alcohol in a spray, and an ointment settles it. Itch and redness that worsen over a week can mean an allergy to the steroid or a preservative — a different product, not more of this one.
If It Is Not Working: Two weeks of proper twice-daily use is a fair test; more weeks rarely help. The usual reasons are a wrong diagnosis, a fungal rash the steroid is feeding, an untreated infection, or skin thick enough to need a stronger steroid or an ointment.
No blood tests and no routine monitoring. Very little reaches the bloodstream, and what does is broken down quickly, so nothing accumulates.
Monitoring is a review at about four weeks to decide whether it is working. Long term, this is a drug people can stay on: no maximum duration, no limit on the area treated, no rest period. That is the practical difference between it and a topical steroid.
The one thing worth watching is whether it is quietly standing in for treatment that would actually control the disease. Eczema that keeps escaping it needs a different plan, not more months of the same ointment.
No blood tests for a standard course in a healthy adult. Monitoring is a skin check — did the rash clear, has the skin thinned or gone shiny, have stretch marks or small blood vessels appeared, and how much of the tube is going each week.
Children and anyone treating large areas need closer attention. Enough steroid absorbed over enough time can suppress the body's own cortisol, and children reach that point on smaller amounts because they have more skin for their size.
This is not a drug to stay on continuously. For a recurring condition, use short courses for flares with emollients doing the daily work, or an agreed schedule such as two set days a week for a stubborn area. That should be a deliberate decision, not a prescription that keeps refilling.
Approximate windows, not promises.
First few minutesApplying it: A thin layer twice a day. Stinging or warmth for a few minutes is common, worst in week one.
First few minutesApplying it: A thin layer on affected skin. Mid-strength — stronger than hydrocortisone, milder than clobetasol.
Days 1 to 7Adjusting: Stinging is at its worst now. Itch eases before the rash looks different.
Week 2Settling: Redness and scaling fade. Most of the stinging has gone.
Week 4Judge it here: The point the trials measured. A meaningful share of people reach clear or almost clear skin; a meaningful share do not. No change by four weeks means more time will not help.
OngoingFace, eyelids and folds: Its strongest case. Use it on and off as needed: no cumulative limit, no rest period, none of the thinning that limits steroids on thin skin.
Days 1 to 3Itch first: Itching and soreness ease before the rash changes appearance.
Days 3 to 10Clearing: Redness fades, weeping stops and thickened areas soften. Most simple eczema flares are largely settled here; contact dermatitis clears once the trigger is gone.
Weeks 2 to 4Judge it here: Psoriasis plaques flatten and scale lifts here. Lichen planus and other stubborn itchy rashes are slower, often needing an ointment or the 0.5% strength. Leathery skin from long scratching takes longest.
After stoppingMarks stay behind: Brown or gray patches where the rash was are pigment change from the inflammation, not scars. They fade over weeks to months.
Sorted by what to do about them.
Cost is the obstacle here, not safety. It has been brand-name with no stocked generic for most of its life, and the cash price for a large tube is high. Generic availability changes, so ask the pharmacy.
Prior authorization is common. Plans usually want a topical steroid first, sometimes a calcineurin inhibitor too, which is cheaper as a generic. A savings card exists for people with commercial insurance, with terms that change often.
Tube size matters more than with most creams, because it goes on twice a day over an area. A small tube covering a child's whole body lasts days. Ask for the size that matches the area treated.
Triamcinolone is generic and among the least expensive prescription steroids. Large jars of cream or ointment are the cheapest way to treat widespread rashes, and most plans cover them.
Sprays, aerosols and branded versions cost noticeably more. The dental paste for mouth ulcers is a separate product, priced separately. When cost is a problem, ask for a larger jar rather than several small tubes.
Probably the drug itself acting on inflamed skin, not the base. It is the commonest complaint, worst in the first days, and fades within a week.
Thin skin is where it makes the most sense and it is used there, but not in the eye itself. Keep it off the lid margin.
No, it is milder. Its advantage is delicate skin and long stretches without the thinning that limits steroids.
There is no set limit. On during flares, off in between, for as long as it helps.
It is licensed from three months of age.
Licensed for atopic dermatitis. Doctors sometimes use it off-label for other inflammatory rashes, where the evidence is thinner.
Mid-strength. Several steps above hydrocortisone, several below clobetasol. Usually the right level to start at for body skin, and too much for the face.
Generally no, unless a clinician has said so and for how long. Facial skin is thin and absorbs well — weeks of it there cause thinning, visible vessels and bumps around the mouth.
Two to four weeks at a stretch for most body rashes, then a review. Longer should be a deliberate plan, such as fixed days each week.
It can, with continuous use, especially on thin skin and in folds. A two-week course on an arm or leg is not what causes it. Early thinning usually recovers over months. Stretch marks do not.
Effectively yes, at the same percentage. It holds moisture in and drives more drug in, which is why it suits dry, thickened rashes.
Same drug, different route and dose. An injection into a joint, keloid or bald patch is a separate treatment.