
Cold Sores vs Canker Sores

Cold sores are small clusters of blisters on or around the lip, caused by the herpes simplex virus. The virus stays in the body for life, but episodes get shorter when treatment starts early, and for most people they become less frequent over the years. Aphthous ulcers are painful non-contagious sores inside the mouth.

Research updated 2026-10-23
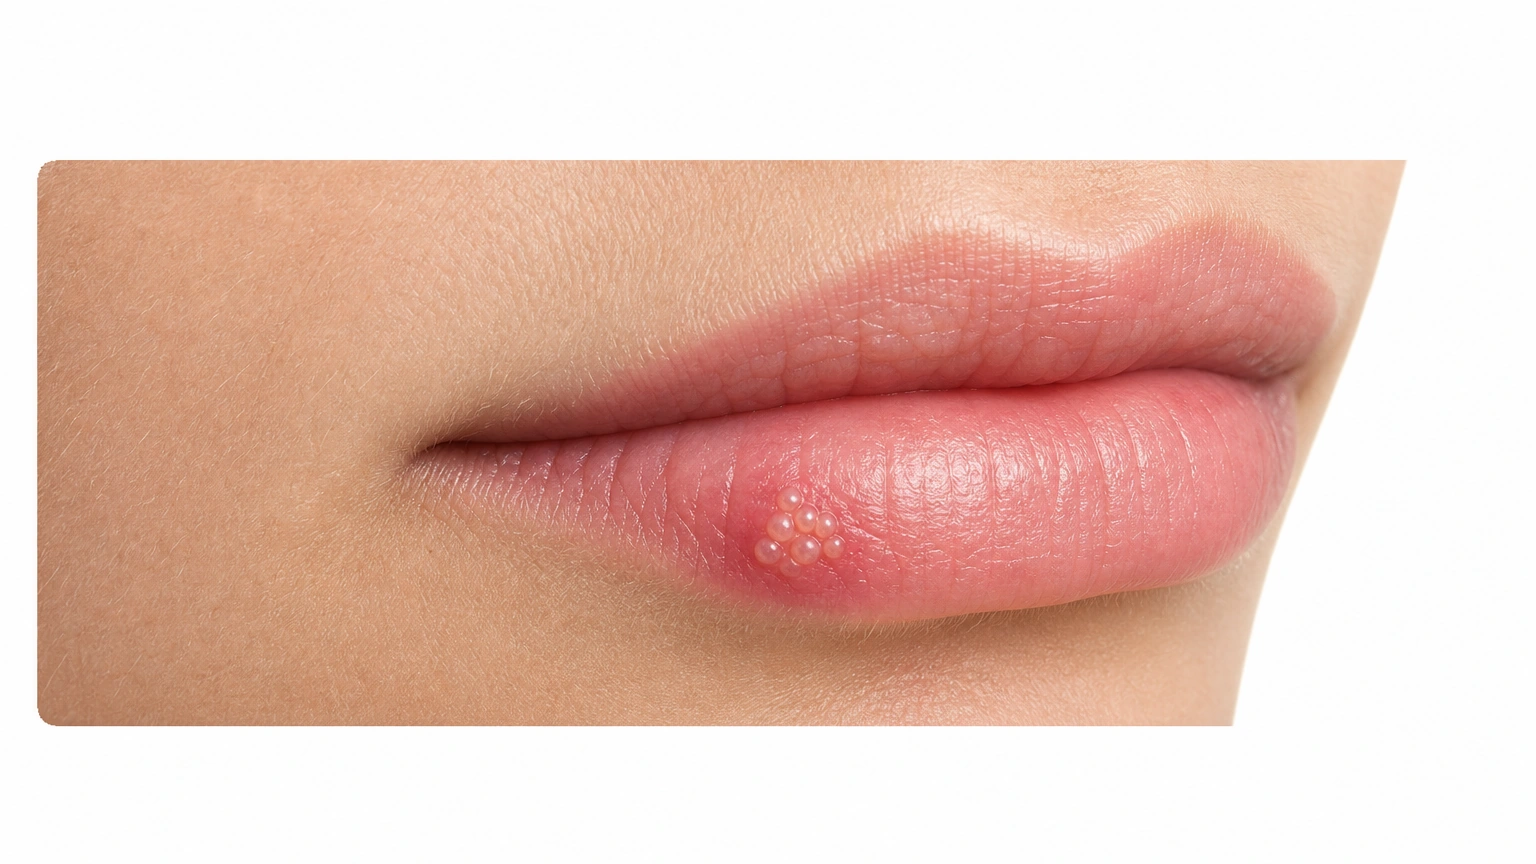
Small grouped blisters at the lip margin on light skin.Canker Sores

Key differences

The same eight facts on every condition comparison.

Usual age
First catch often in childhood
Childhood onward
Where
Lip border
Inside the mouth
Main sign
Tingling, then a cluster of blisters
Painful round white ulcers
Itch or pain
Tingling and sore
Painful
Contagious
Yes, until crusted
No
Long term
Lifelong virus; recurs
Heals in 1–2 weeks; recurs
Scars
Rarely
No (minor ones)
Who gets it
Most adults carry the virus
Anyone; runs in families

What is it?

Cold Sores
Canker Sores
What is it?
  • They are caused by herpes simplex.
    The virus stays latent for life after the first exposure.
  • They recur in the same place.
    Reactivation produces small blisters near the lip border.
  • A first infection can differ.
    It may cause painful mouth and gum inflammation with fever.
  • Unusual sores need review.
    A persistent ulcer should be reassessed, not treated repeatedly.
  • What it is
    Aphthous ulcers are painful non-contagious sores inside the mouth.

What it looks like

Cold Sores

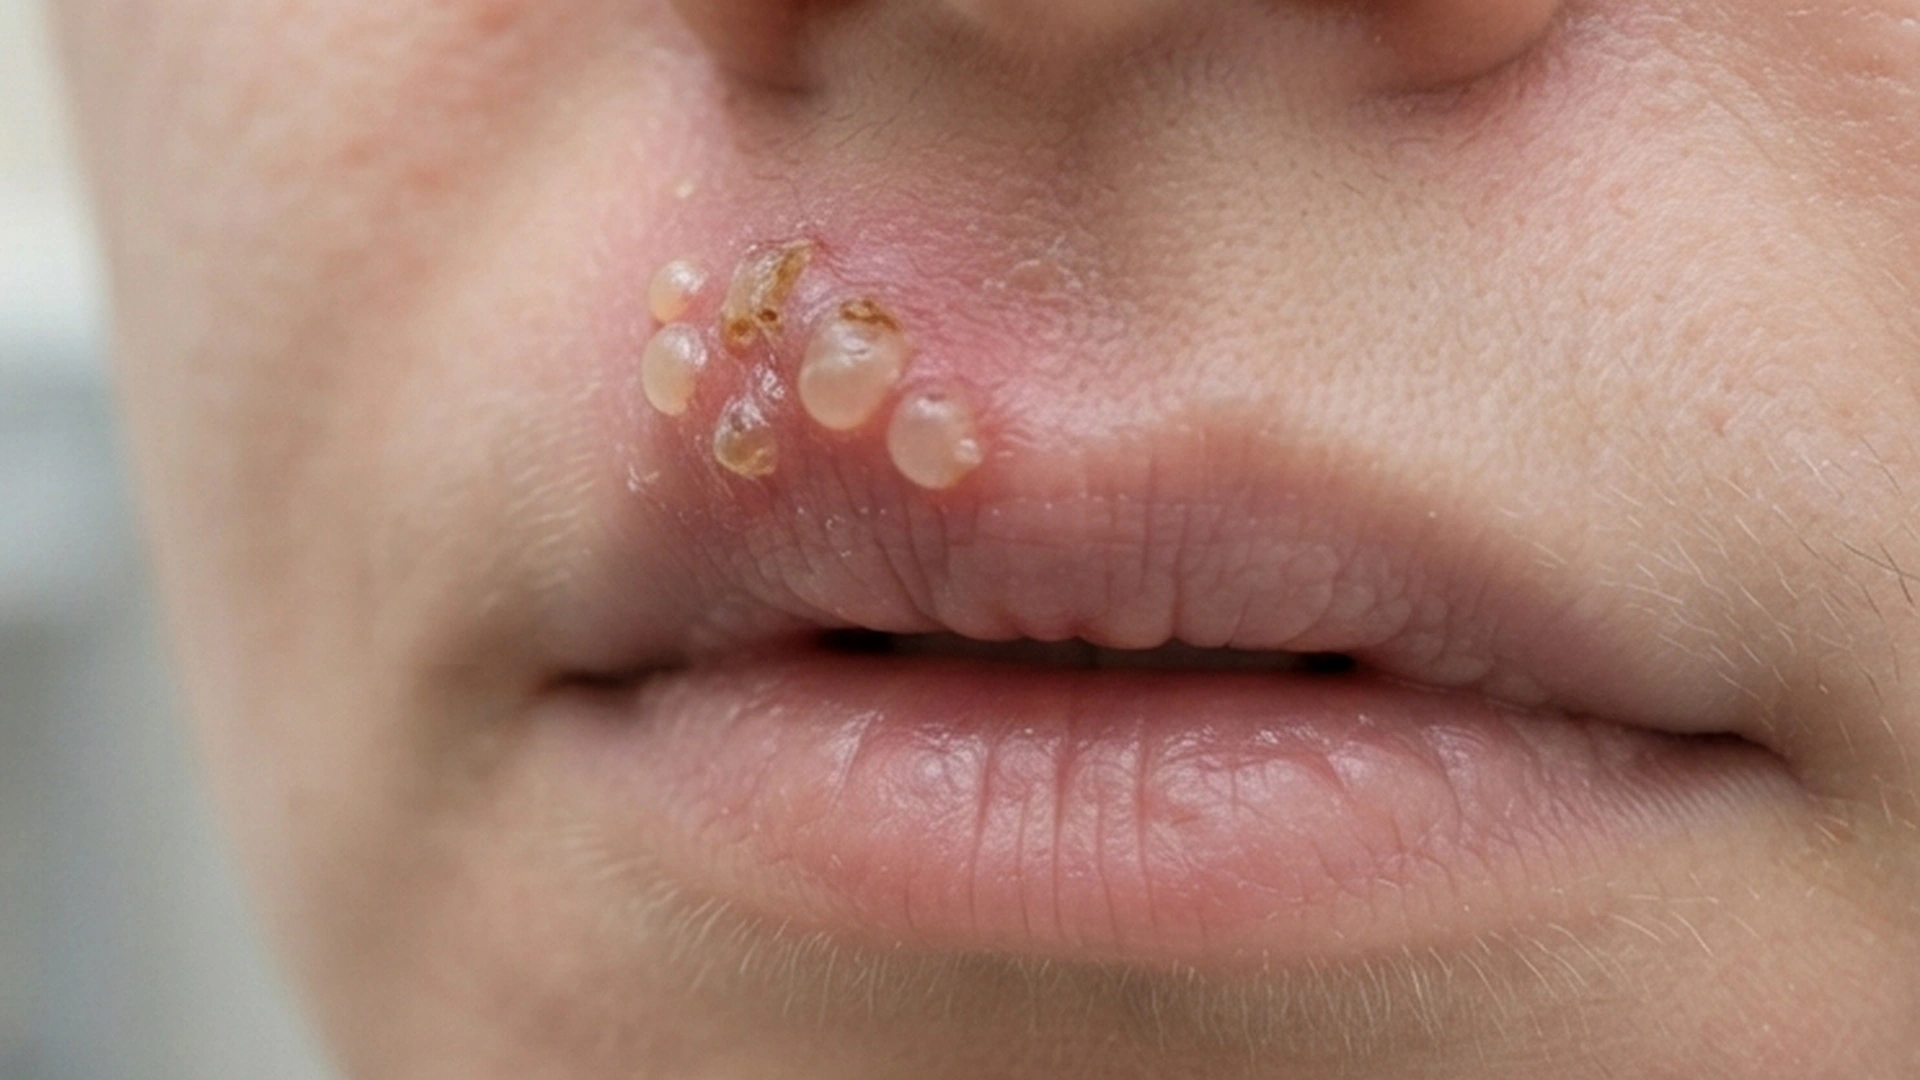
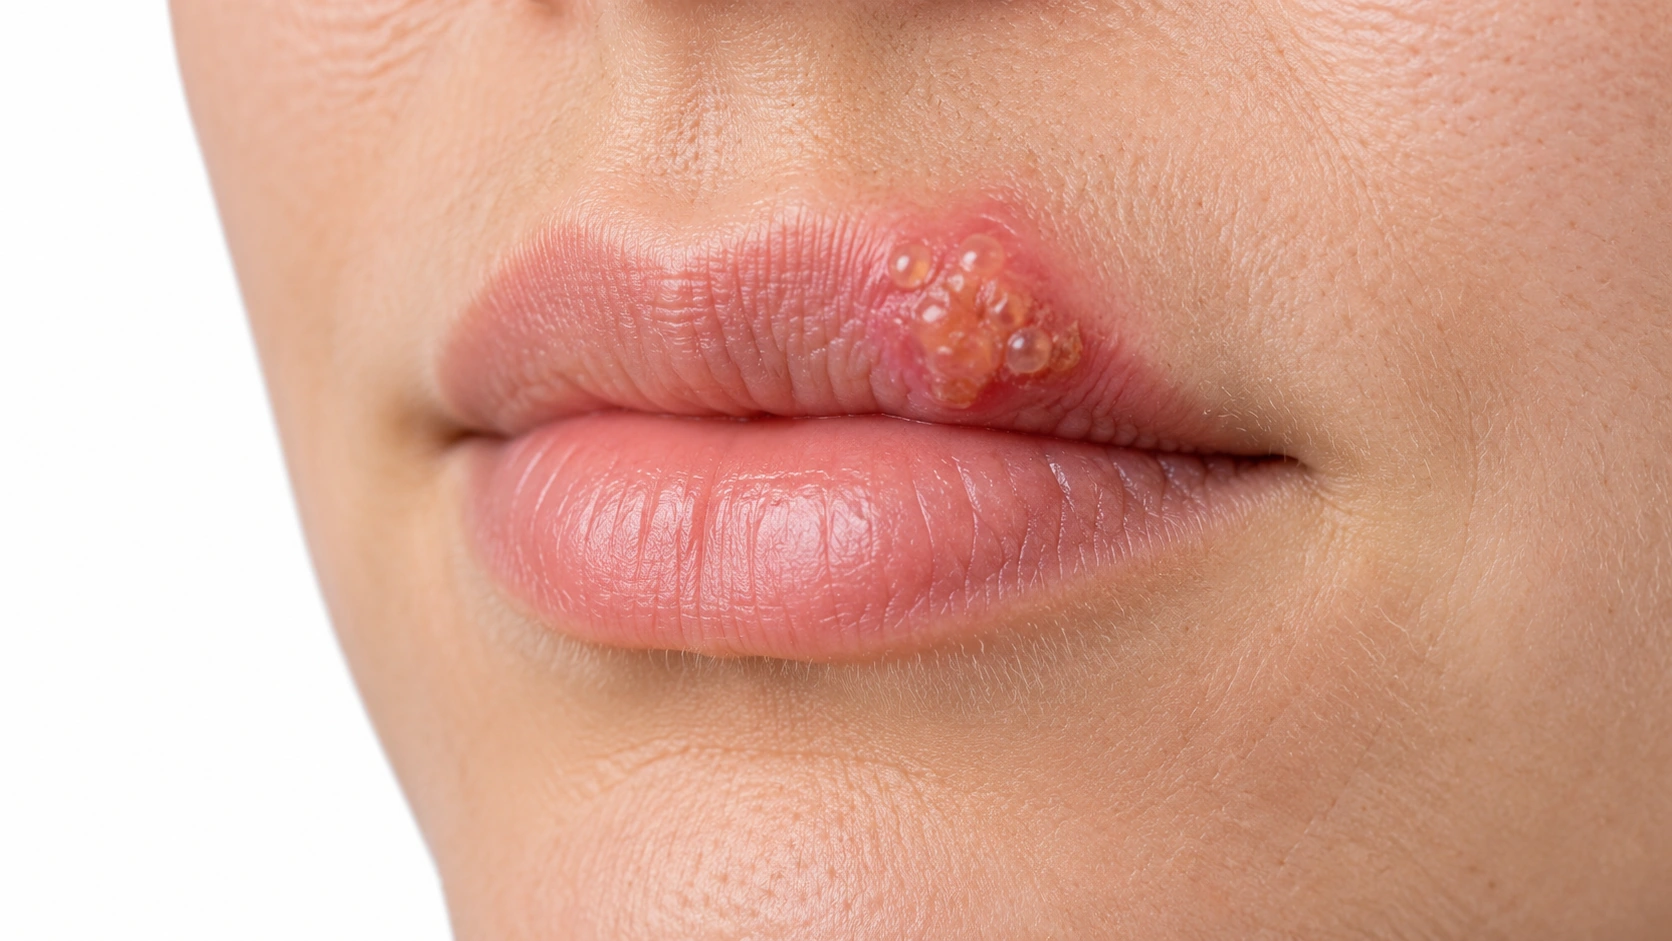
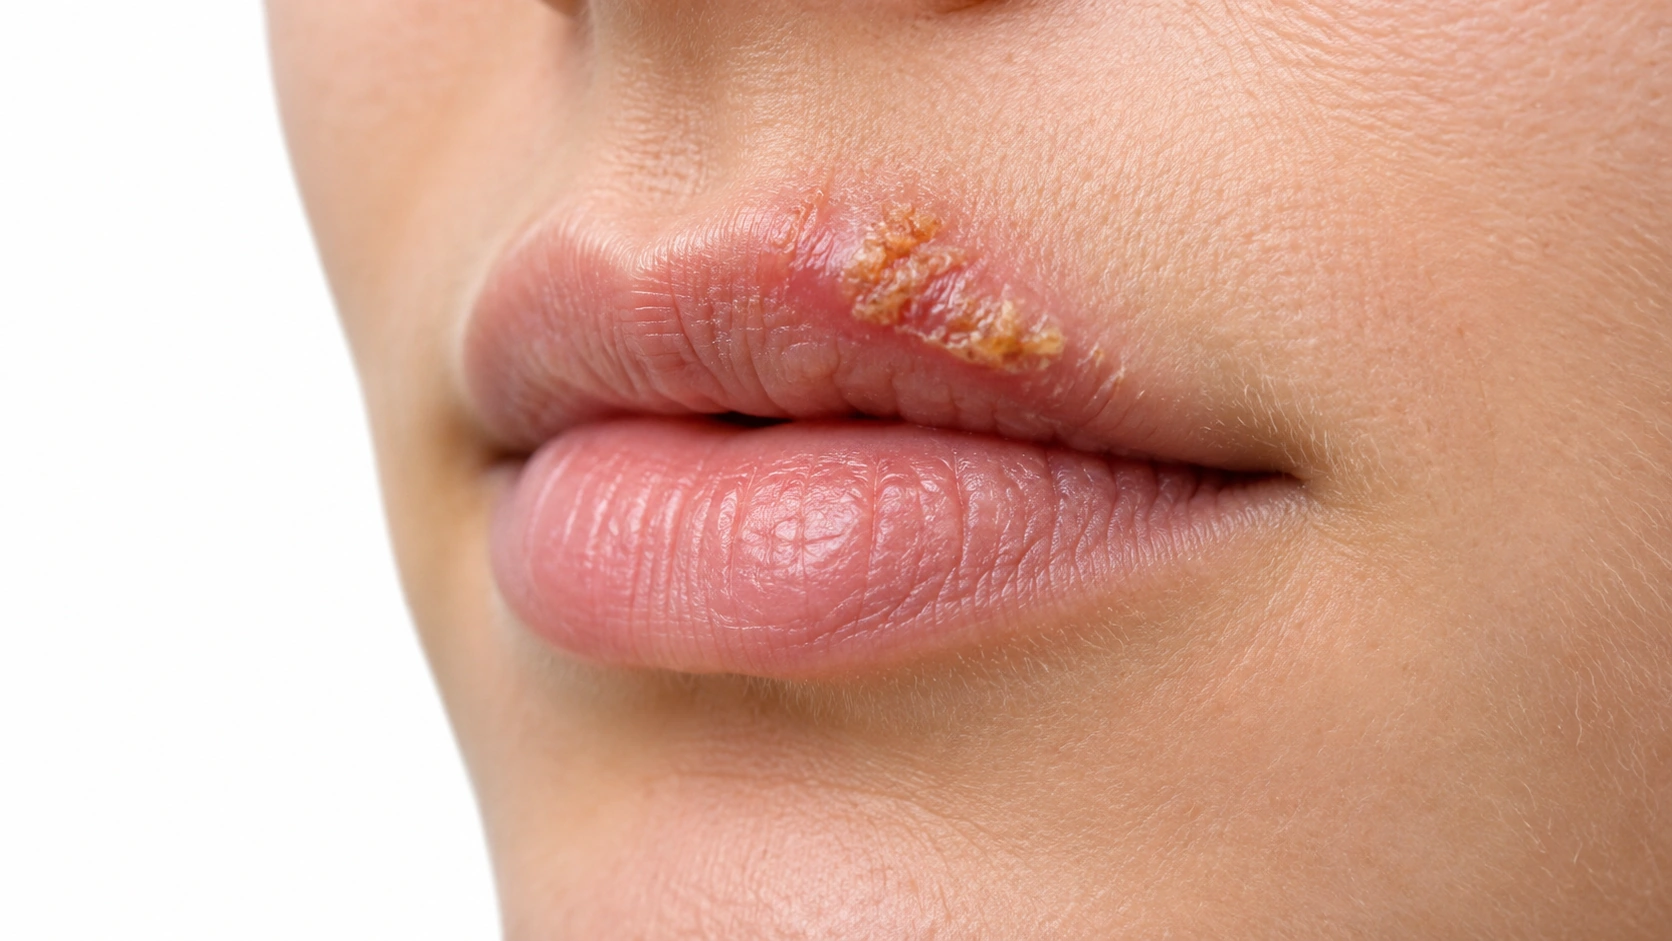
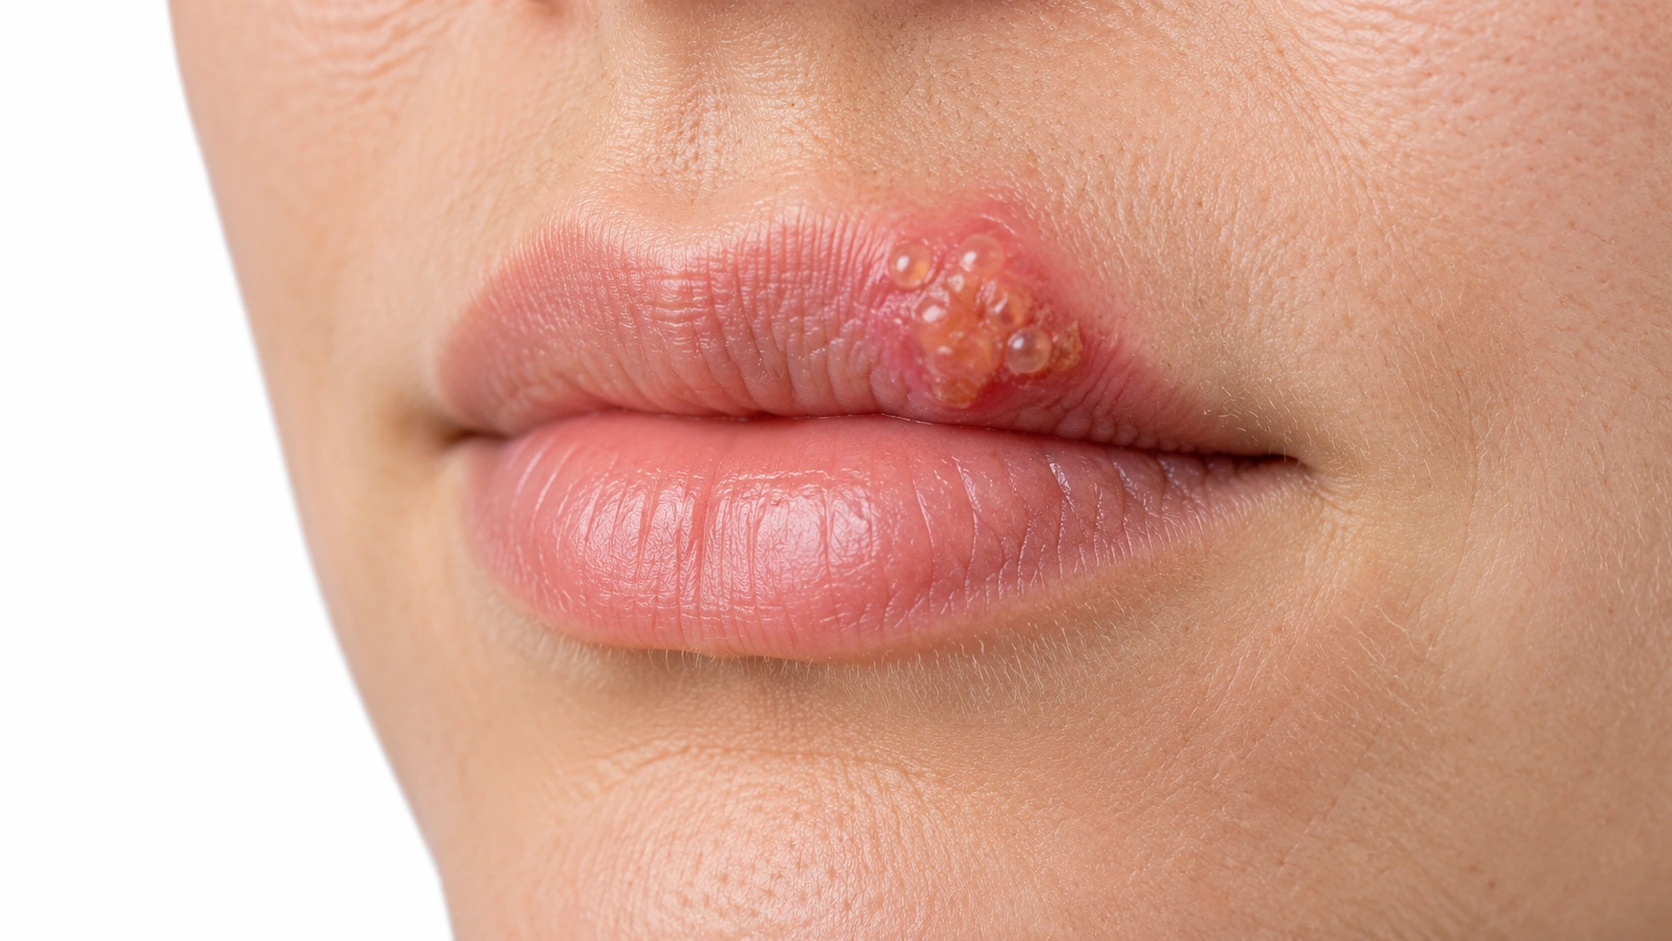
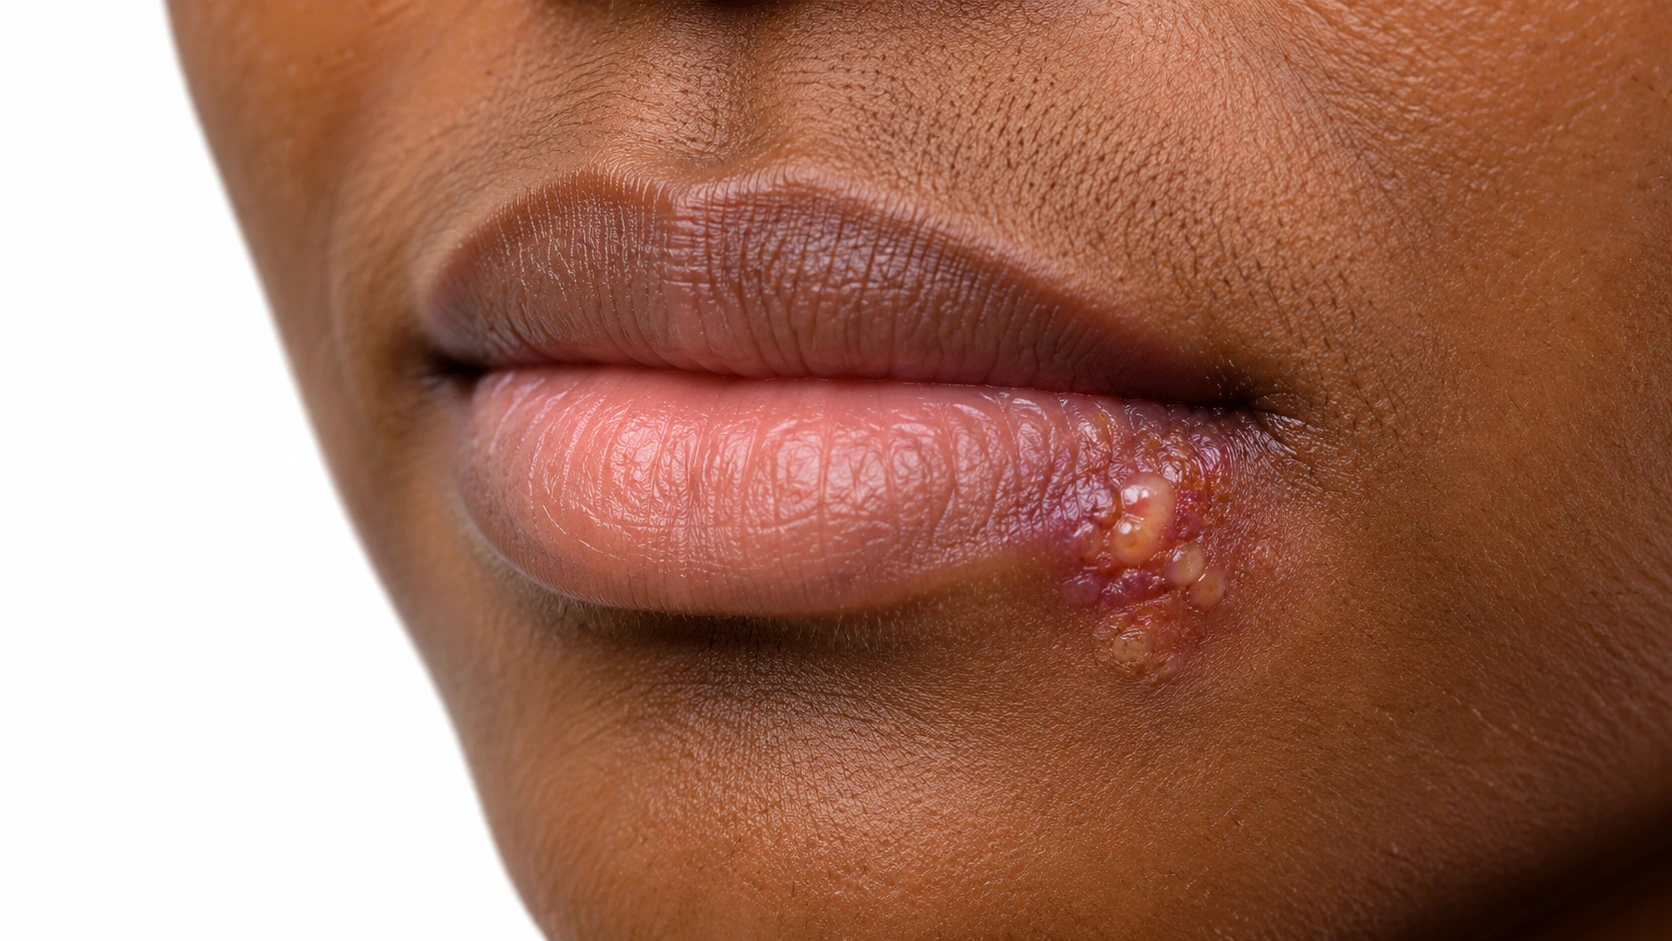
A small cluster of clear vesicles at the lower lip border, representing the blister stage of a cold sore.

Blister cluster Small blisters on the lip edge.

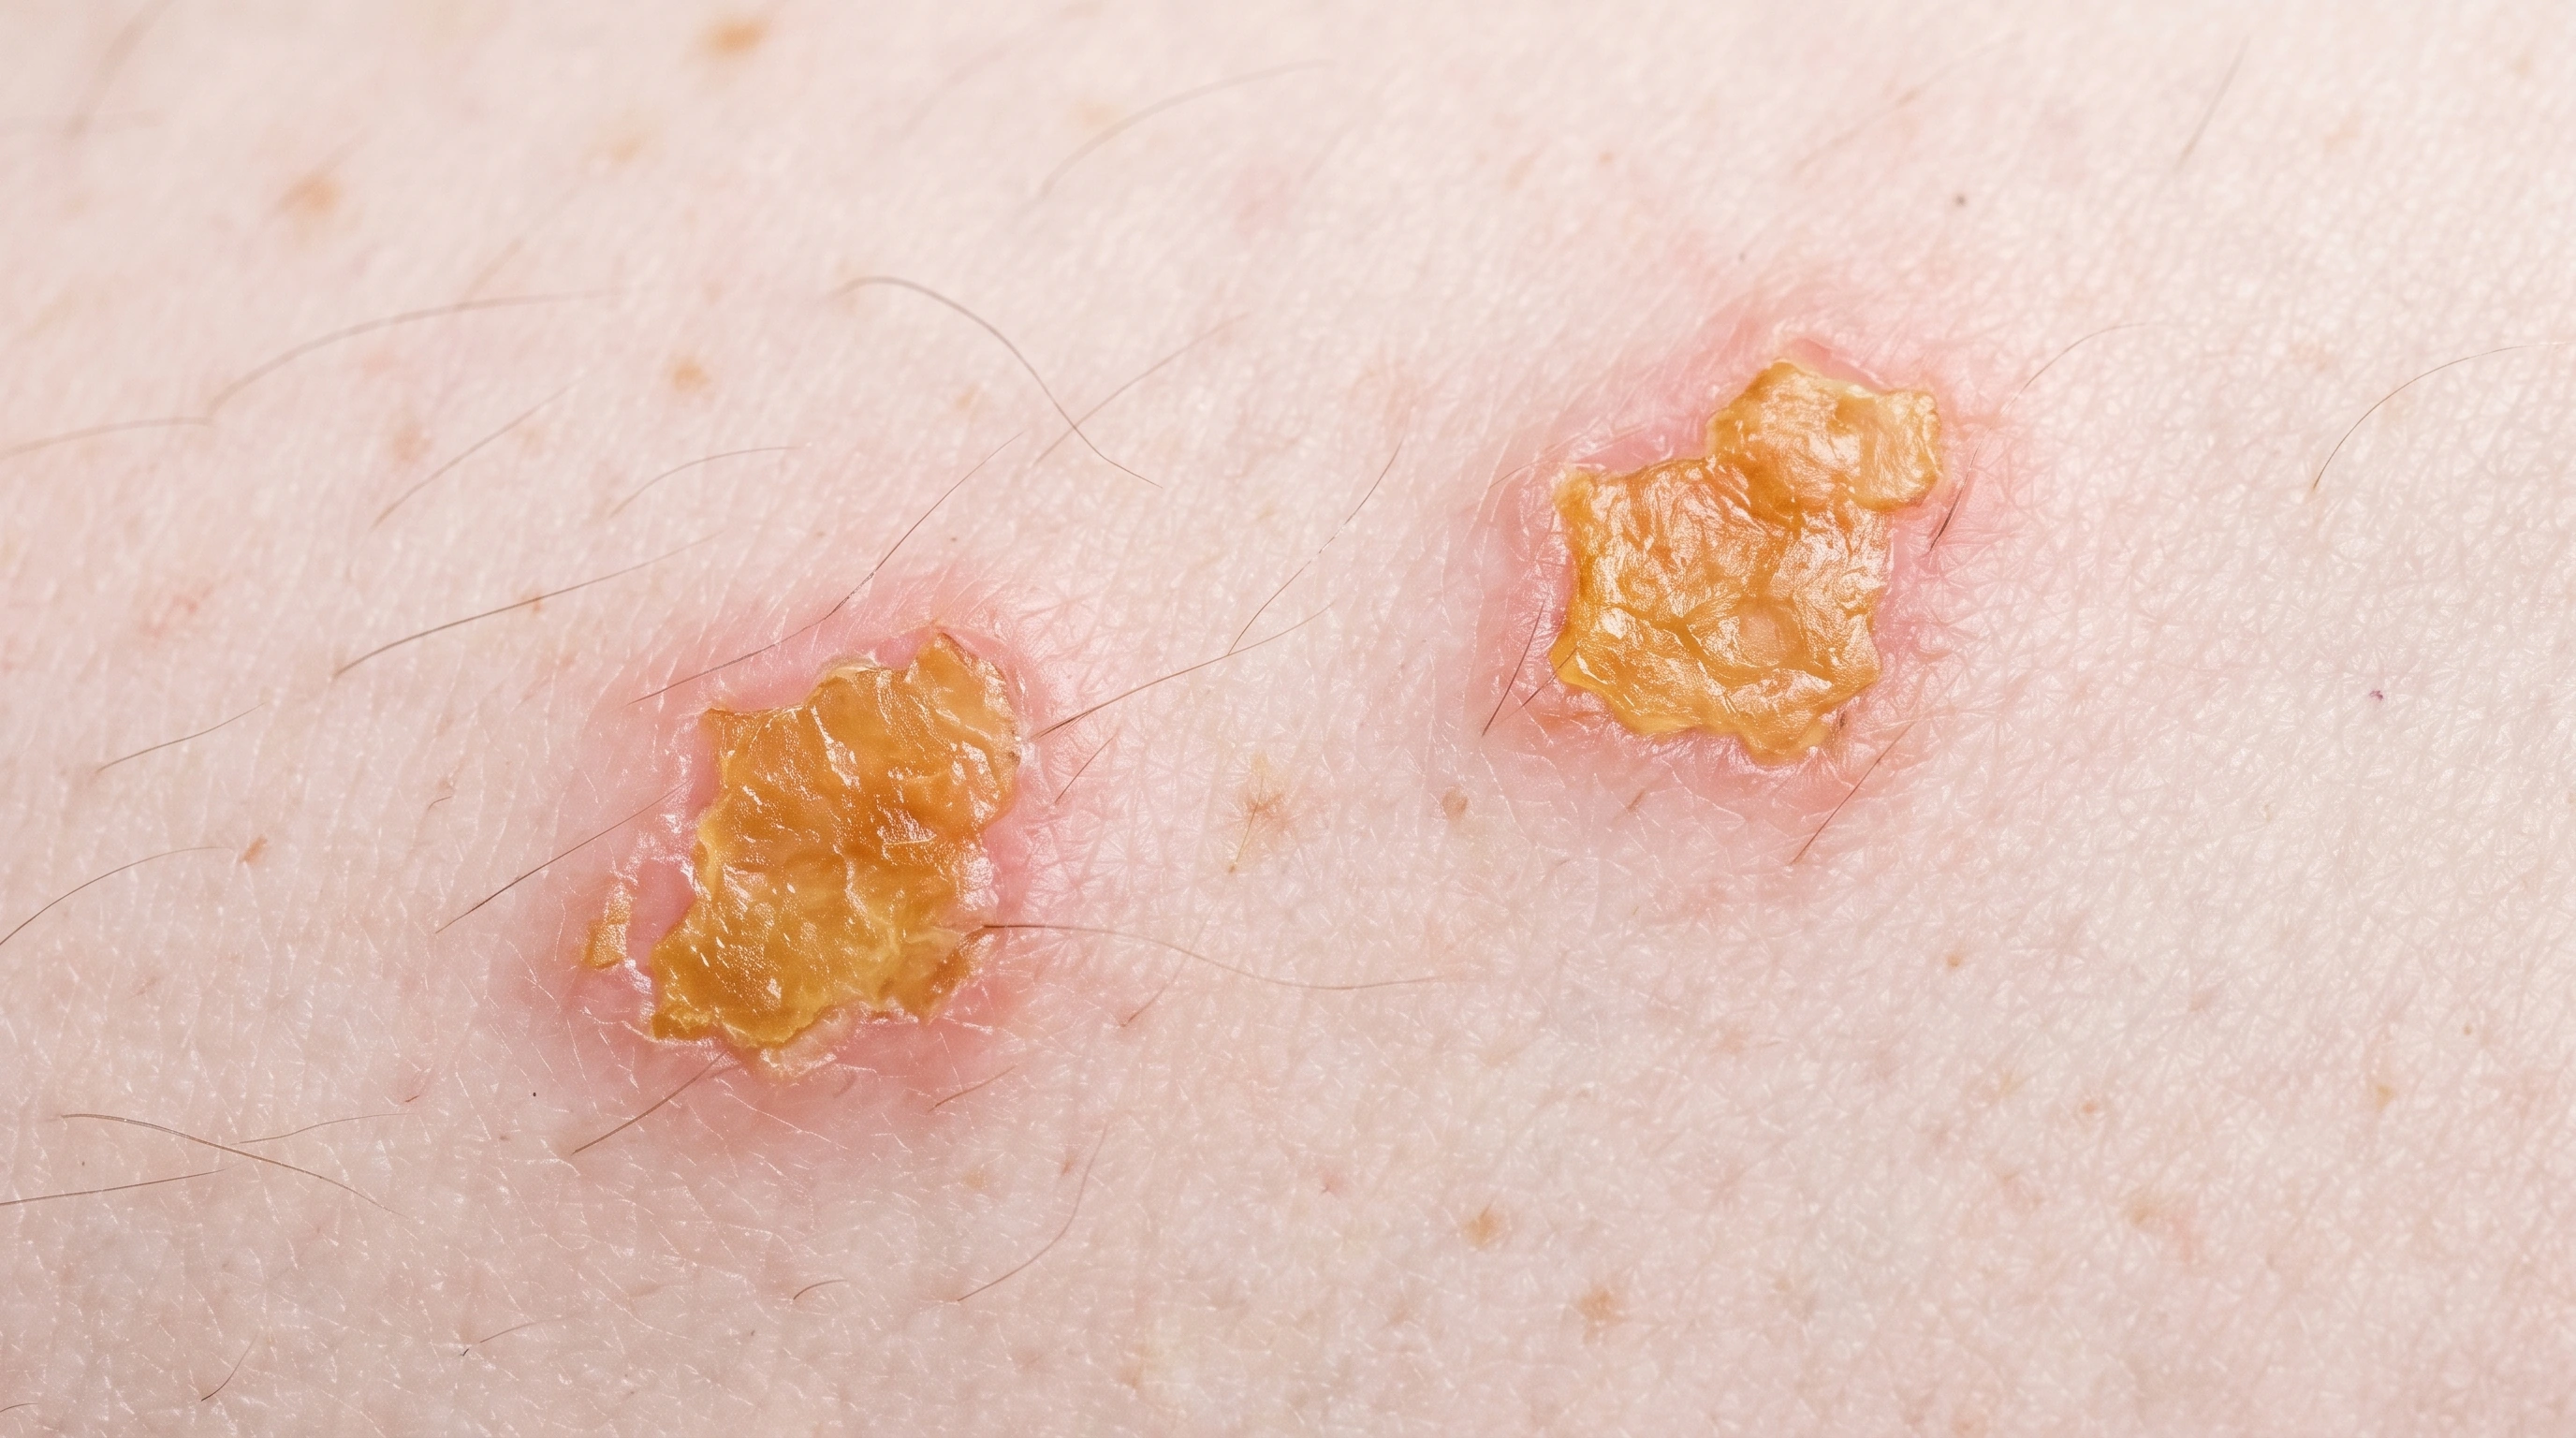
Crusted cold sore on the lip.

Crusting Yellow crust as it heals.

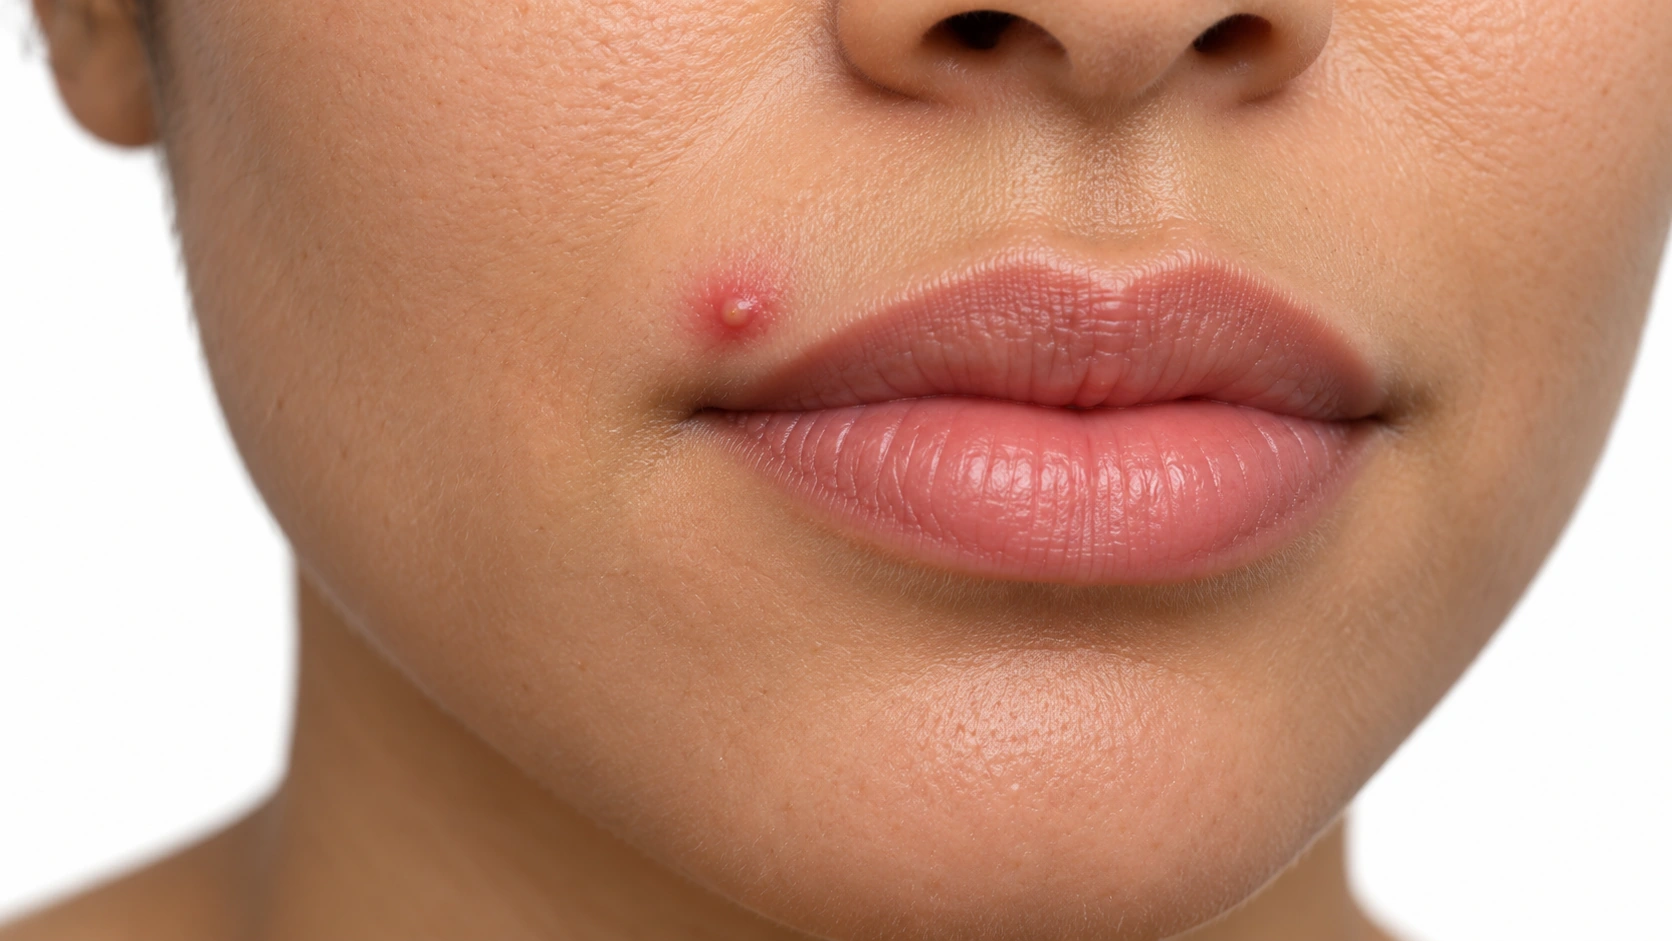
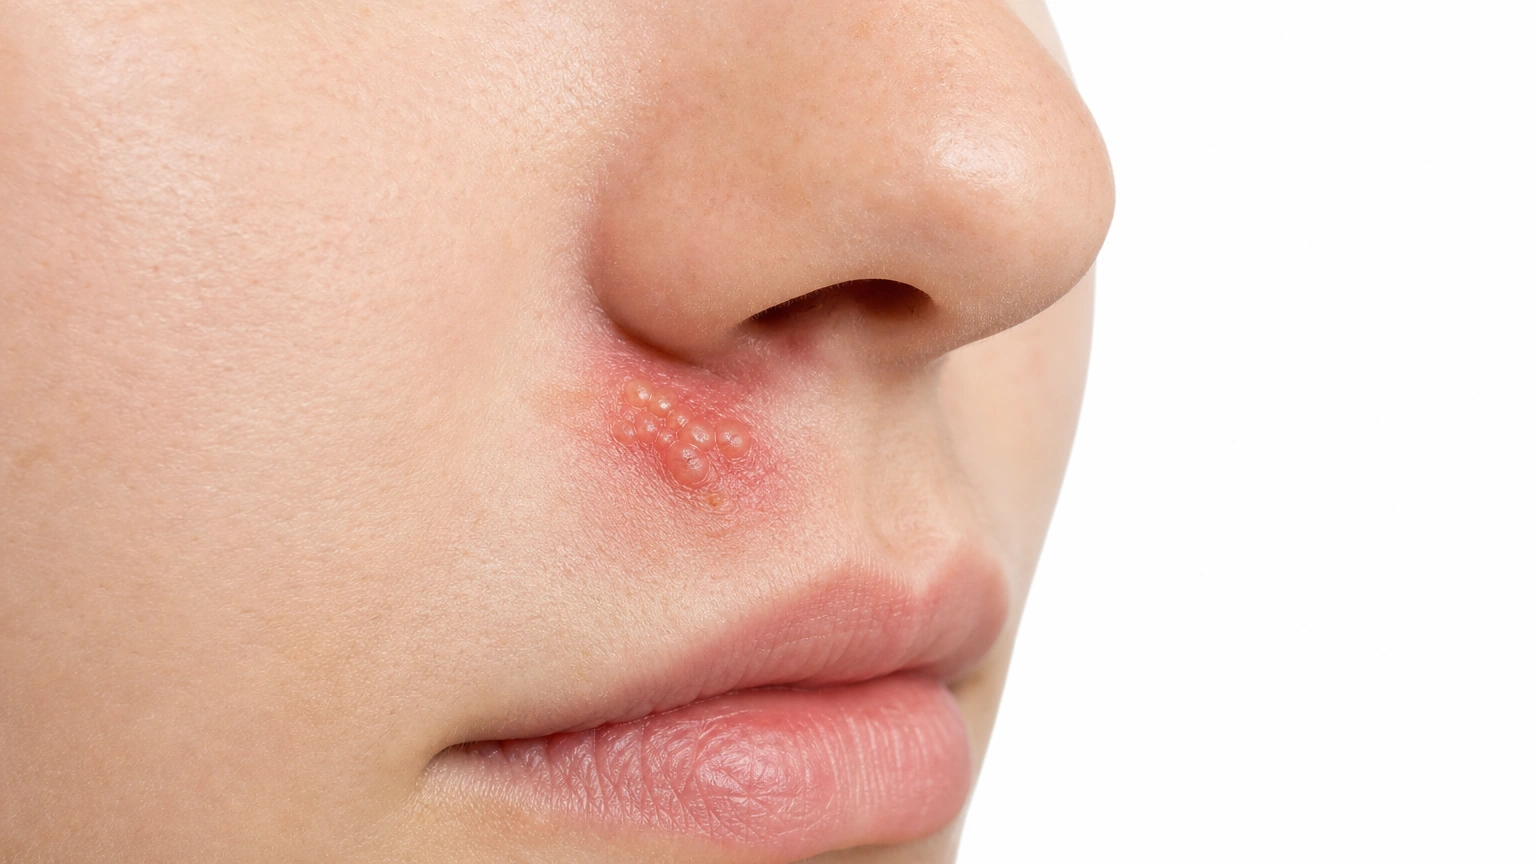
A small cluster of clear vesicles on a red patch beside the nostril, representing a cold sore.

Near the nose Can appear around the nostrils.

Canker Sores

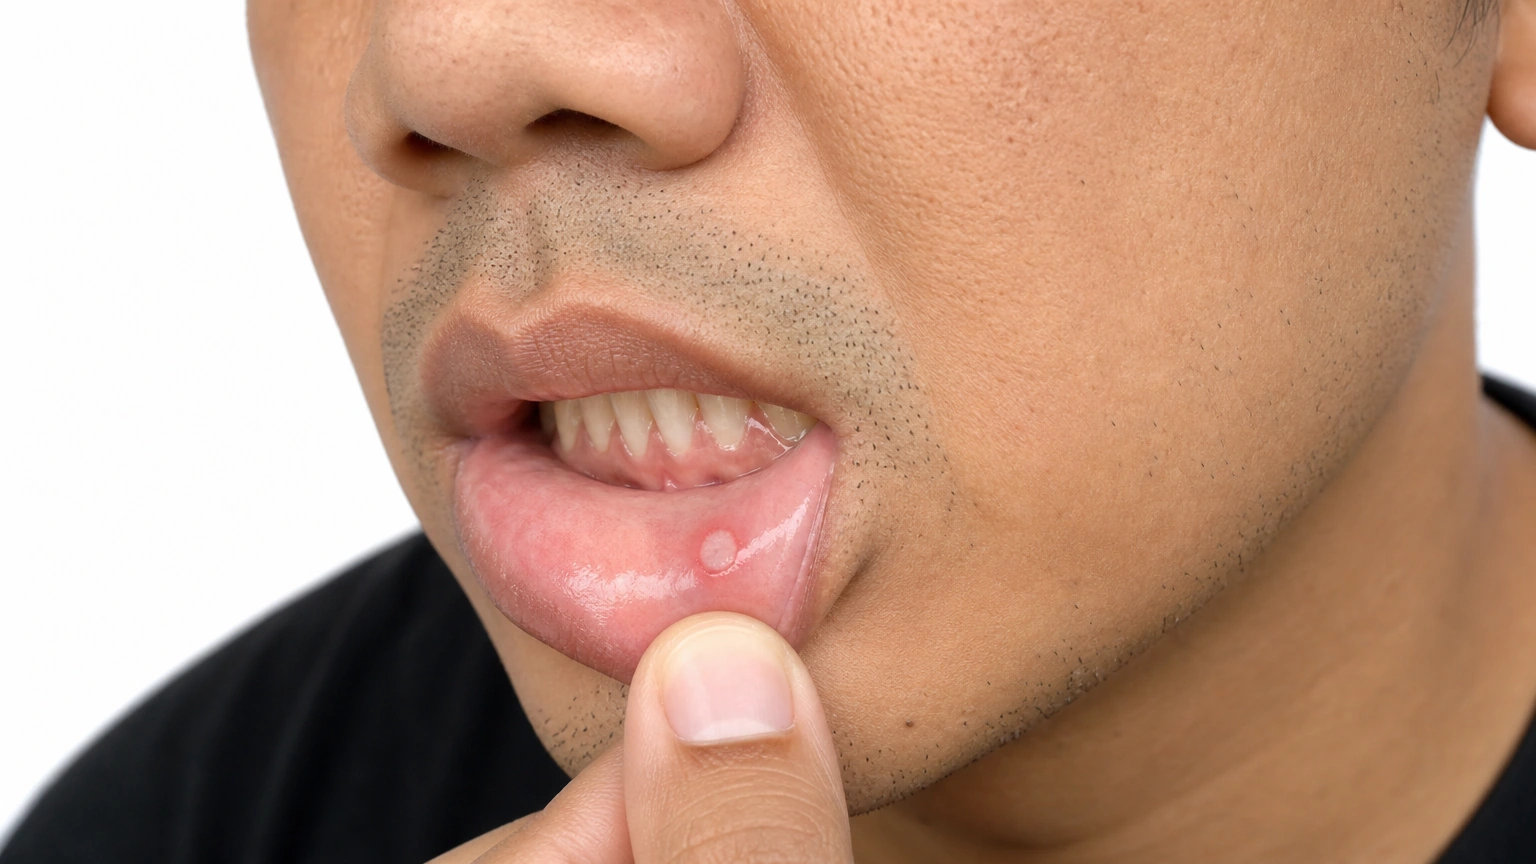
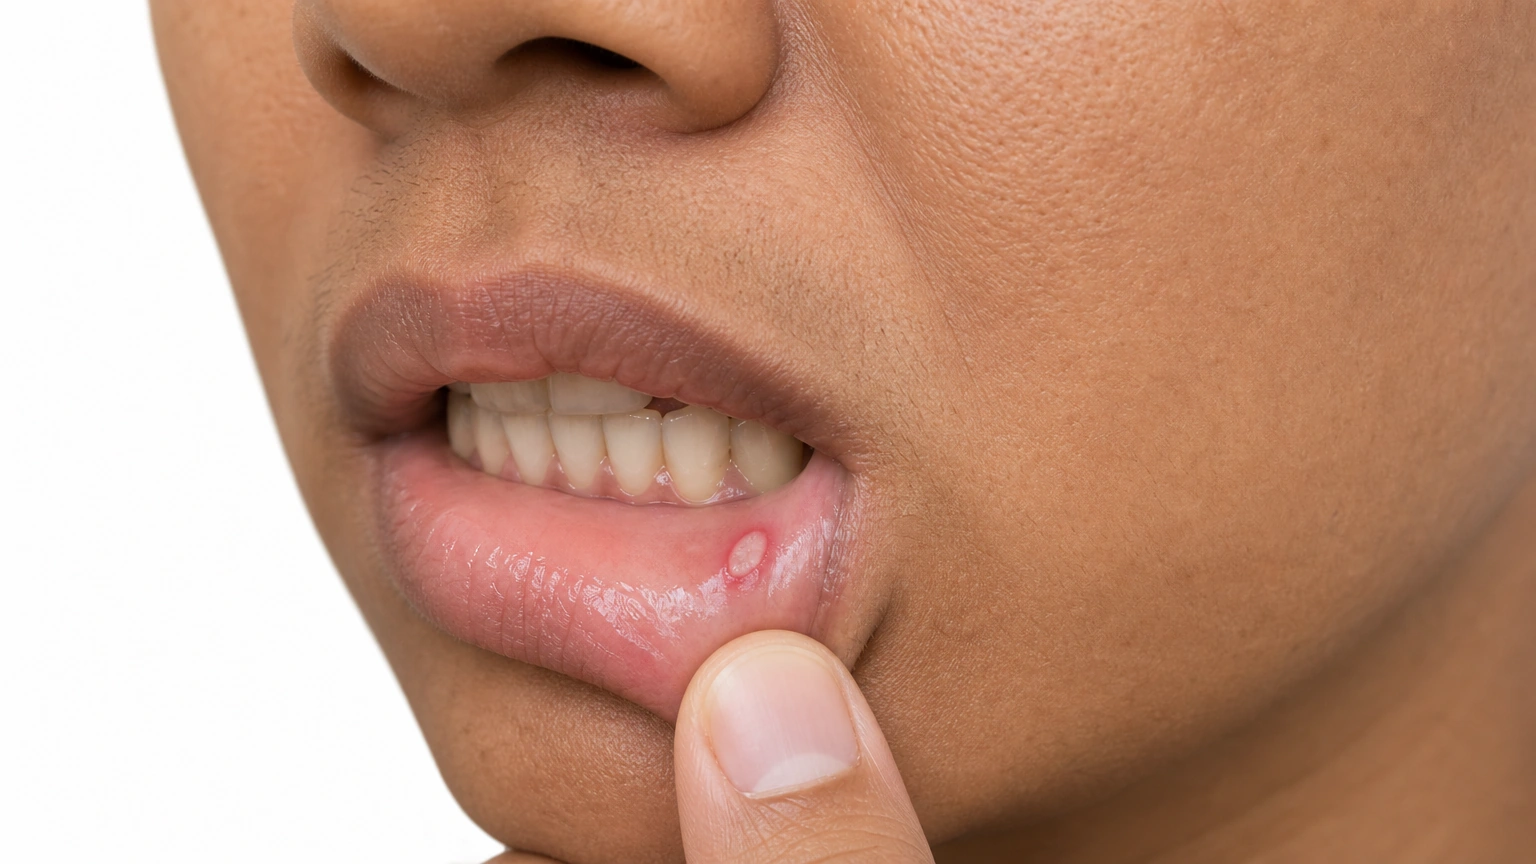
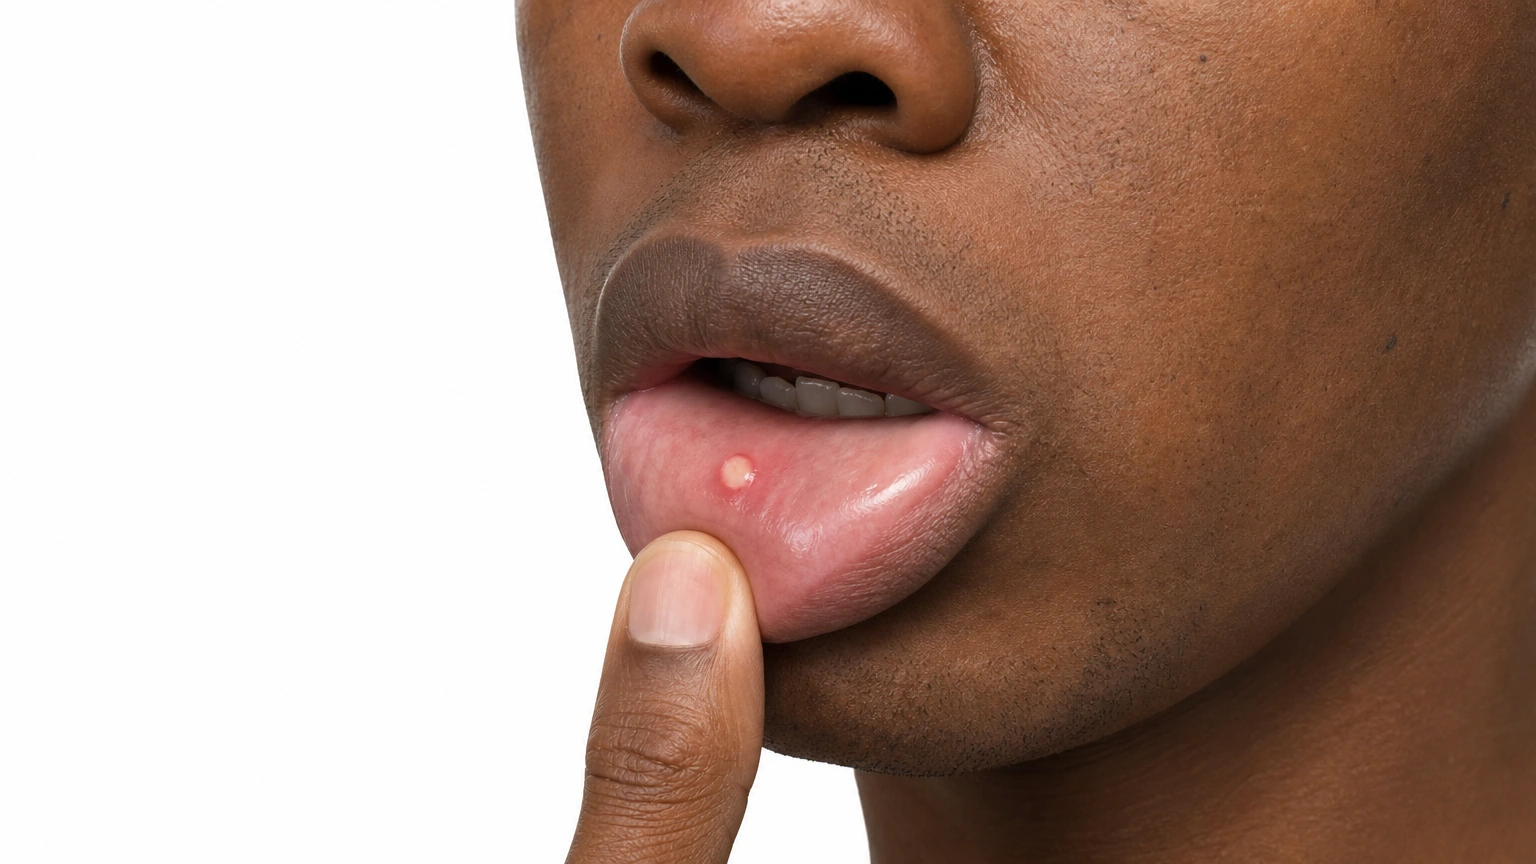
An inner lower lip held open to show a round pale ulcer with a red border.

Canker Sores A small shallow ulcer has a red rim and a lighter center.

Skin tones
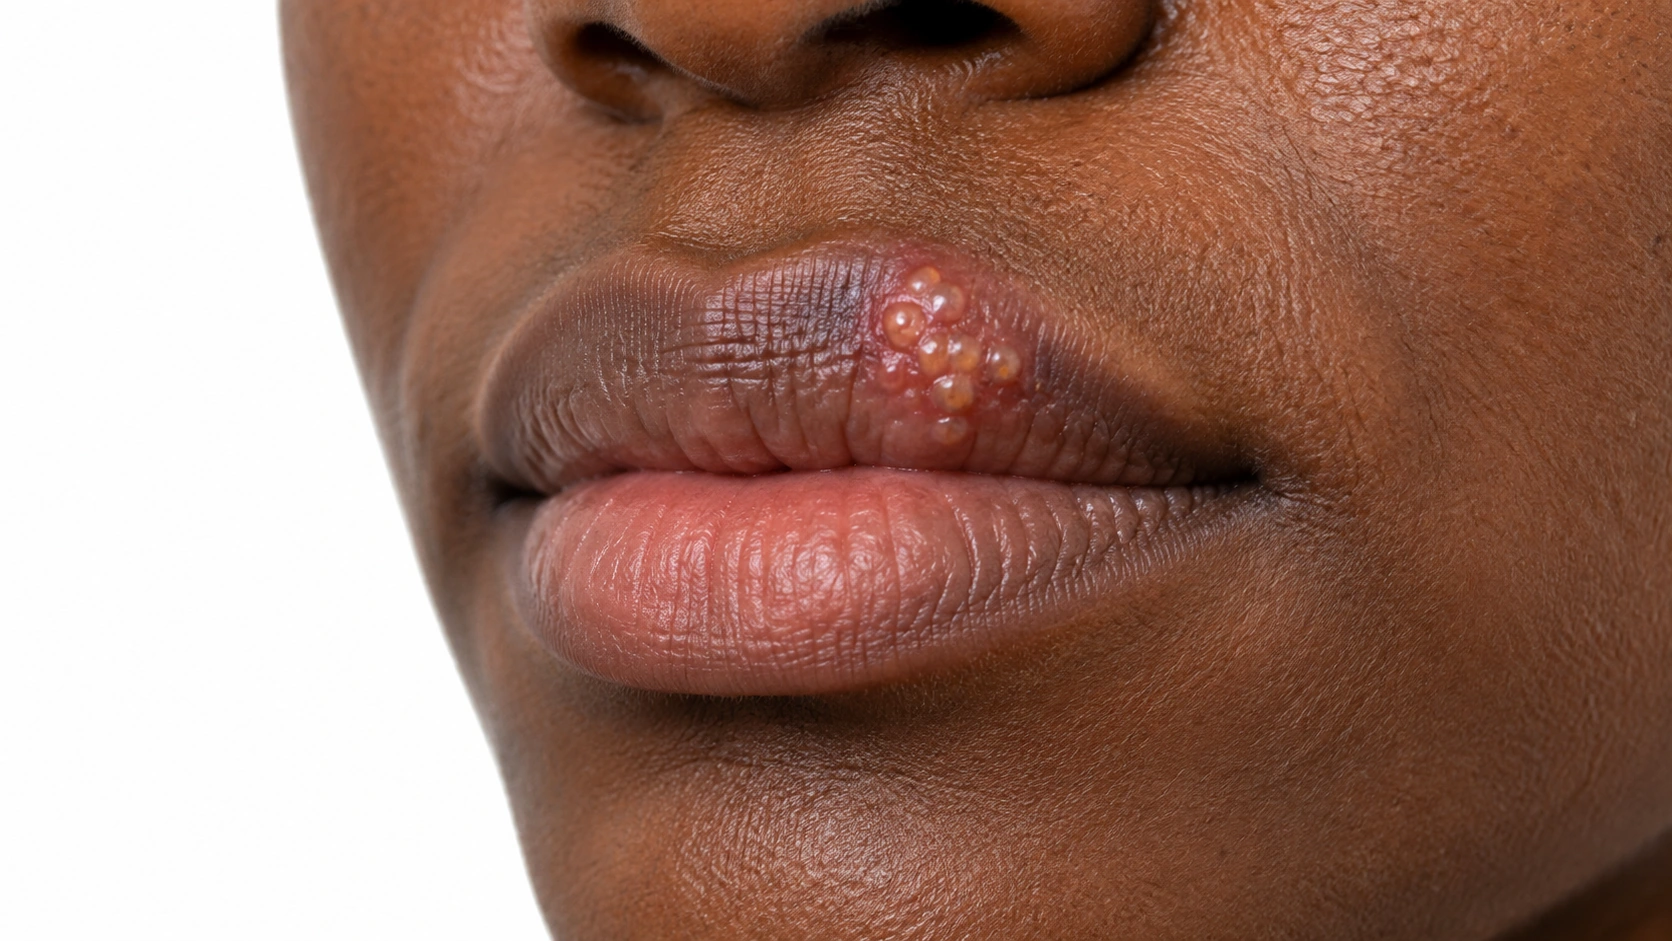
Small grouped blisters at the lip margin on light skin.
Grouped small blisters beside the lip on medium skin.
a small grouped blister and crust at the lip margin on brown skin.
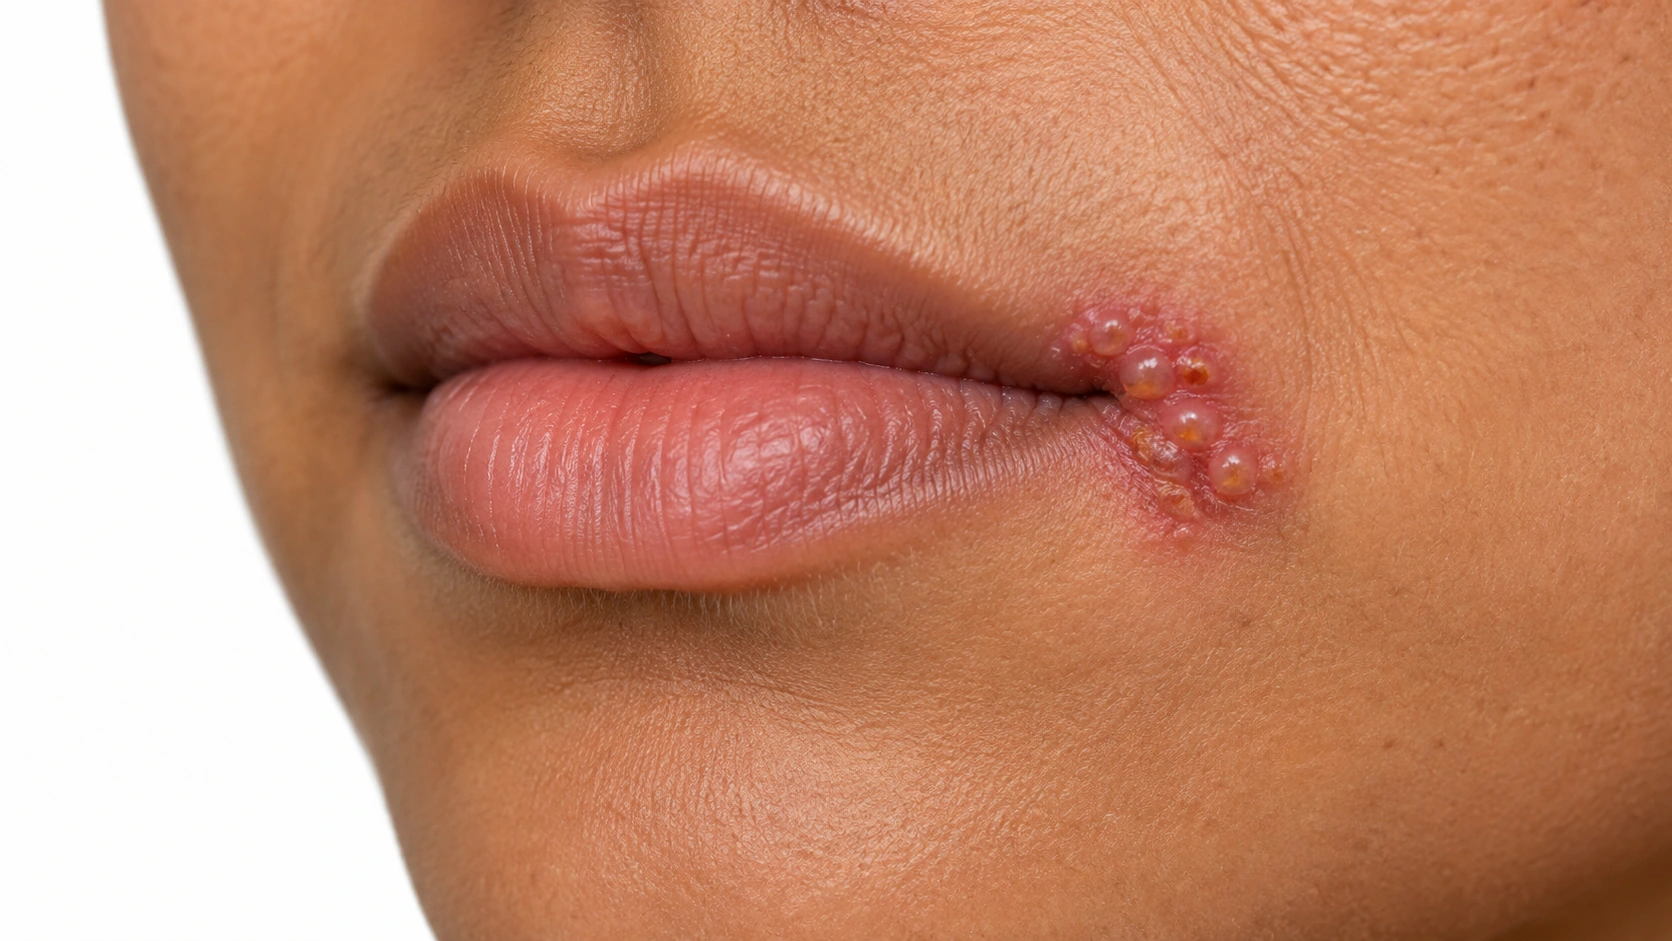
grouped small lip-margin blisters on deep brown skin.
Educational illustration of one small shallow pale-centered ulcer inside the lower lip on light skin.
Educational illustration of one small shallow pale-centered ulcer inside the lower lip on medium skin.
Educational illustration of one small shallow pale-centered ulcer inside the lower lip on brown skin.
Educational illustration of one small shallow pale-centered ulcer inside the lower lip on deep skin.
Diagram
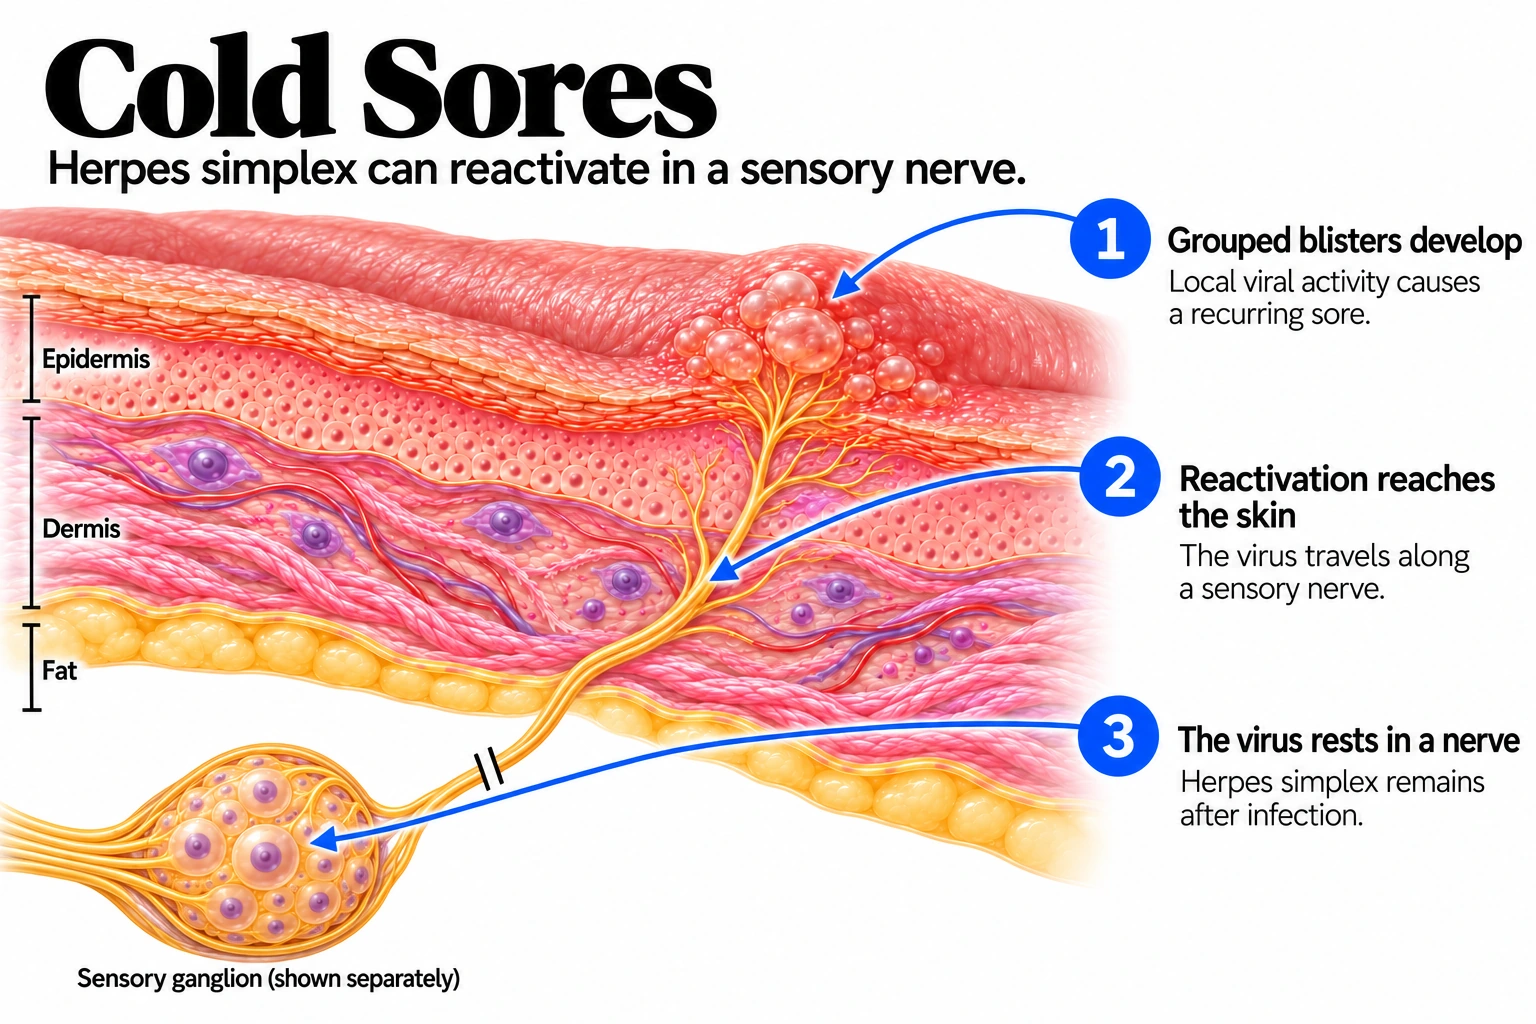
Cold Sores mechanism diagram. Grouped blisters develop: Local viral activity causes a recurring sore. Reactivation reaches the skin: The virus travels along a sensory nerve. The virus rests in a nerve: Herpes simplex remains after infection.
In the skin

Herpes simplex virus remains in sensory nerves after the initial infection. Reactivation brings the virus back to nearby skin, where local viral activity can produce grouped blisters.

Local inflammation damages the mouth's surface lining and forms an ulcer. The exact cause is often uncertain, and several triggers may contribute.

When it usually starts

010203040506070+

Cold Sores. The first infection often occurs early in life; recurrent episodes can occur at any age afterward.

Canker Sores. Often begins in childhood or adolescence and may recur.

Causes and triggers

Causes

Cold sores are caused by the herpes simplex virus. After the first infection, the virus stays in nerves and can reactivate.

A local inflammatory ulcer develops; the cause is often uncertain.

Risk factors
Past infection, Weakened immunity
Family tendency, Local trauma, Iron or vitamin deficiency in some cases
How it spreads
  • Kissing — Well established
  • Sharing cups, razors and lip balm — Strong link
Trigger
● Cold Sores
● Canker Sores
Sun exposure
Well established
Not listed
Fever or colds
Well established
Not listed
Stress
Strong link
Can contribute
Periods
Possible
Not listed
Local trauma
Not listed
Can contribute

Daily Care

Cold Sores
Canker Sores
Daily care

Habits that help

  • A lip balm with SPF, used daily
    Prevention if your episodes follow sun.
  • Leave the crust alone
    Picking slows healing.
  • Plain petrolatum ointment over the sore
    Keeps the crust from splitting.
  • Hand washing and not sharing
    Worth it around newborns and anyone with eczema.
  • Cool compresses
    Use a cool, damp cloth for temporary comfort; it does not shorten the episode.
  • Start an agreed cold-sore antiviral plan at the first warning symptoms
    Tablets in the warning stage shorten the episode.
  • Docosanol cream, over the counter
    Shortens an episode modestly.
  • Daily suppressive antiviral treatment
    For six or more episodes a year.
  • Use the agreed early-treatment plan rather than waiting for a full cold-sore blister
    An agreed antiviral plan may work best at the warning stage. Later symptoms can still need review and treatment.

Avoid

  • Avoid: Strong sun on the lips
    The most predictable trigger.
  • Avoid: Being run down
    Fever, flu or a heavy cold keeps the immune system busy.
  • Avoid: Stress and short sleep
    Both make reactivation more likely.
  • Avoid: Picking the crust
    Restarts healing and leaves a longer mark.
  • Avoid: Touching the sore and then your eye
    Herpes simplex in the eye does real damage.
  • Avoid: Sharing during an episode
    Lip balm, drinks, utensils, towels.
  • Avoid: Kissing while a sore is open
    Especially near a newborn or anyone with eczema.
  • Avoid: Injury to the lip
    Dental work, waxing, fillers, laser.
  • Avoid: Letting the area dry out and crack
    A split crust heals slower.
  • Avoid: Steroid cream on its own
    A steroid cream calms the redness and swelling, which looks like improvement, while leaving the virus free to spread further. It also changes the appearance enough to make the sore hard to recognize later. There is a combination cream that pairs a steroid with an antiviral, but a steroid alone on a cold sore is a step backwards.

Habits that help

  • Choose soft, bland foods while the ulcer is sore
    Cool foods and fluids may be easier to tolerate.
  • Brush gently with a soft toothbrush
    Keep the mouth clean without repeatedly scraping the ulcer.
  • Consider a toothpaste without sodium lauryl sulfate if it irritates
    An individual trigger matters more than changing every oral-care product.
  • Drink enough fluid and use a mouth-safe barrier product if advised
    Products intended for the mouth can reduce contact pain.
  • Seek review for an ulcer lasting more than three weeks
    Frequent, unusually large or widespread sores also need assessment.

Avoid

  • Avoid: Acidic, spicy or sharp foods that sting
    Skip foods that repeatedly reopen or irritate the sore.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Cold Sores
● Canker Sores
Over-the-counter
Abreva.

Abreva

Moderate evidence

The only over-the-counter cream shown to shorten an episode, and only by about half a day. It has to go on at the first tingle and be reapplied five times a day. It is a reasonable thing to keep in a bag, but antiviral tablets started at the same moment do considerably more.

Existing illustration of Lip balm with SPF.

Lip balm with SPF

Moderate evidence

Strong sun on the lips is one of the most reliable triggers there is, so for anyone whose episodes follow skiing, a beach holiday or long days outdoors, a daily SPF lip balm is genuine prevention rather than lip care. Use it every day rather than only when an episode is due, and keep using it while the mark left behind fades, since sun makes that darker and slower.

Hydrocolloid cold sore patches.

Hydrocolloid cold sore patches

Limited evidence

A thin gel patch worn over the sore. It keeps the area moist so the crust splits less, it stops fingers reaching the sore, and it contains the fluid that spreads the virus. It does not shorten the episode itself, and it is easier to use once the blisters have opened than at the tingle stage.

Illustration: Generic oral tablet bottle and tablets.

Lysine supplements

Limited evidence

A popular supplement for preventing episodes, but the studies behind it are small, old and inconsistent. It is not dangerous and some people are convinced by it. It is not a substitute for an antiviral, and it is not something to rely on if your episodes are frequent.

Four ointments on white: CeraVe Healing Ointment, a Vaseline jar, a petroleum jelly tube and Aquaphor

Petrolatum

Listed

Plain ointment dabbed over the crust keeps it soft so it does not split each time you talk or eat, which hurts less and leaves less of a mark. Drying the sore out does the opposite of what people expect. Apply it with a clean fingertip or a cotton bud and wash your hands afterwards - it does nothing to the virus itself.

None listed
Prescription topicals

Penciclovir

Moderate evidence

Penciclovir cream. A prescription antiviral cream applied every two hours while awake for four days. It shortens an episode by around half a day to a day, so a little more than the over-the-counter cream and a lot less than tablets. It is a reasonable option for someone who cannot take the tablets.

Topical Acyclovir

Moderate evidence

Acyclovir cream. The cream version of the tablet, five times a day for four days. The virus is multiplying deep in the skin cells and traveling in a nerve, so a cream only reaches part of the problem, and the benefit is measured in hours rather than days. If you can take the tablets, take the tablets.

Oral topical corticosteroid

Listed

A clinician may recommend a mouth-specific preparation for troublesome recurrent ulcers.

Prescription pills
Valacyclovir — Header Image

Valacyclovir

Strong evidence

The usual first choice, and for a cold sore it is a single day of treatment - two large doses twelve hours apart, started at the first tingle. Taken then, it shortens the episode and can stop a blister forming at all. Started after the blister is out it does much less, which is the whole argument for keeping a course at home.

Representative medication packaging labelled Famciclovir, lying sideways on a white background.

Famciclovir

Strong evidence

An equally effective alternative, taken as a single dose at the first tingle, which suits people who will not manage a second dose later in the day. It is used where valacyclovir does not suit or is not available. It is usually the more expensive of the two.

Tablets — stock illustration

Acyclovir

Moderate evidence

The oldest of the antiviral tablets and the cheapest. It works, but it has to be taken five times a day for five days, which is a lot of doses for something that lasts a week anyway. The dose is lowered if your kidneys are not working well.

Valacyclovir — Header Image

Daily suppressive treatment

Listed

A low dose of the same antiviral taken every day, rather than only during an episode, for people getting roughly six or more a year. It reduces how often they happen substantially and lowers the amount of virus shed in between. The effect stops when the tablets stop, and doctors usually review it after six to twelve months.

None listed

Outlook

Long term

Most episodes run a week to ten days. People settle into a rhythm - one or two a year, or several, and some have one episode and never another. Frequency drops with age.

Most minor canker sores heal within 1–2 weeks without scarring, but episodes can recur. A persistent, unusually large or repeatedly troublesome ulcer needs assessment.

Complications

Possible complications

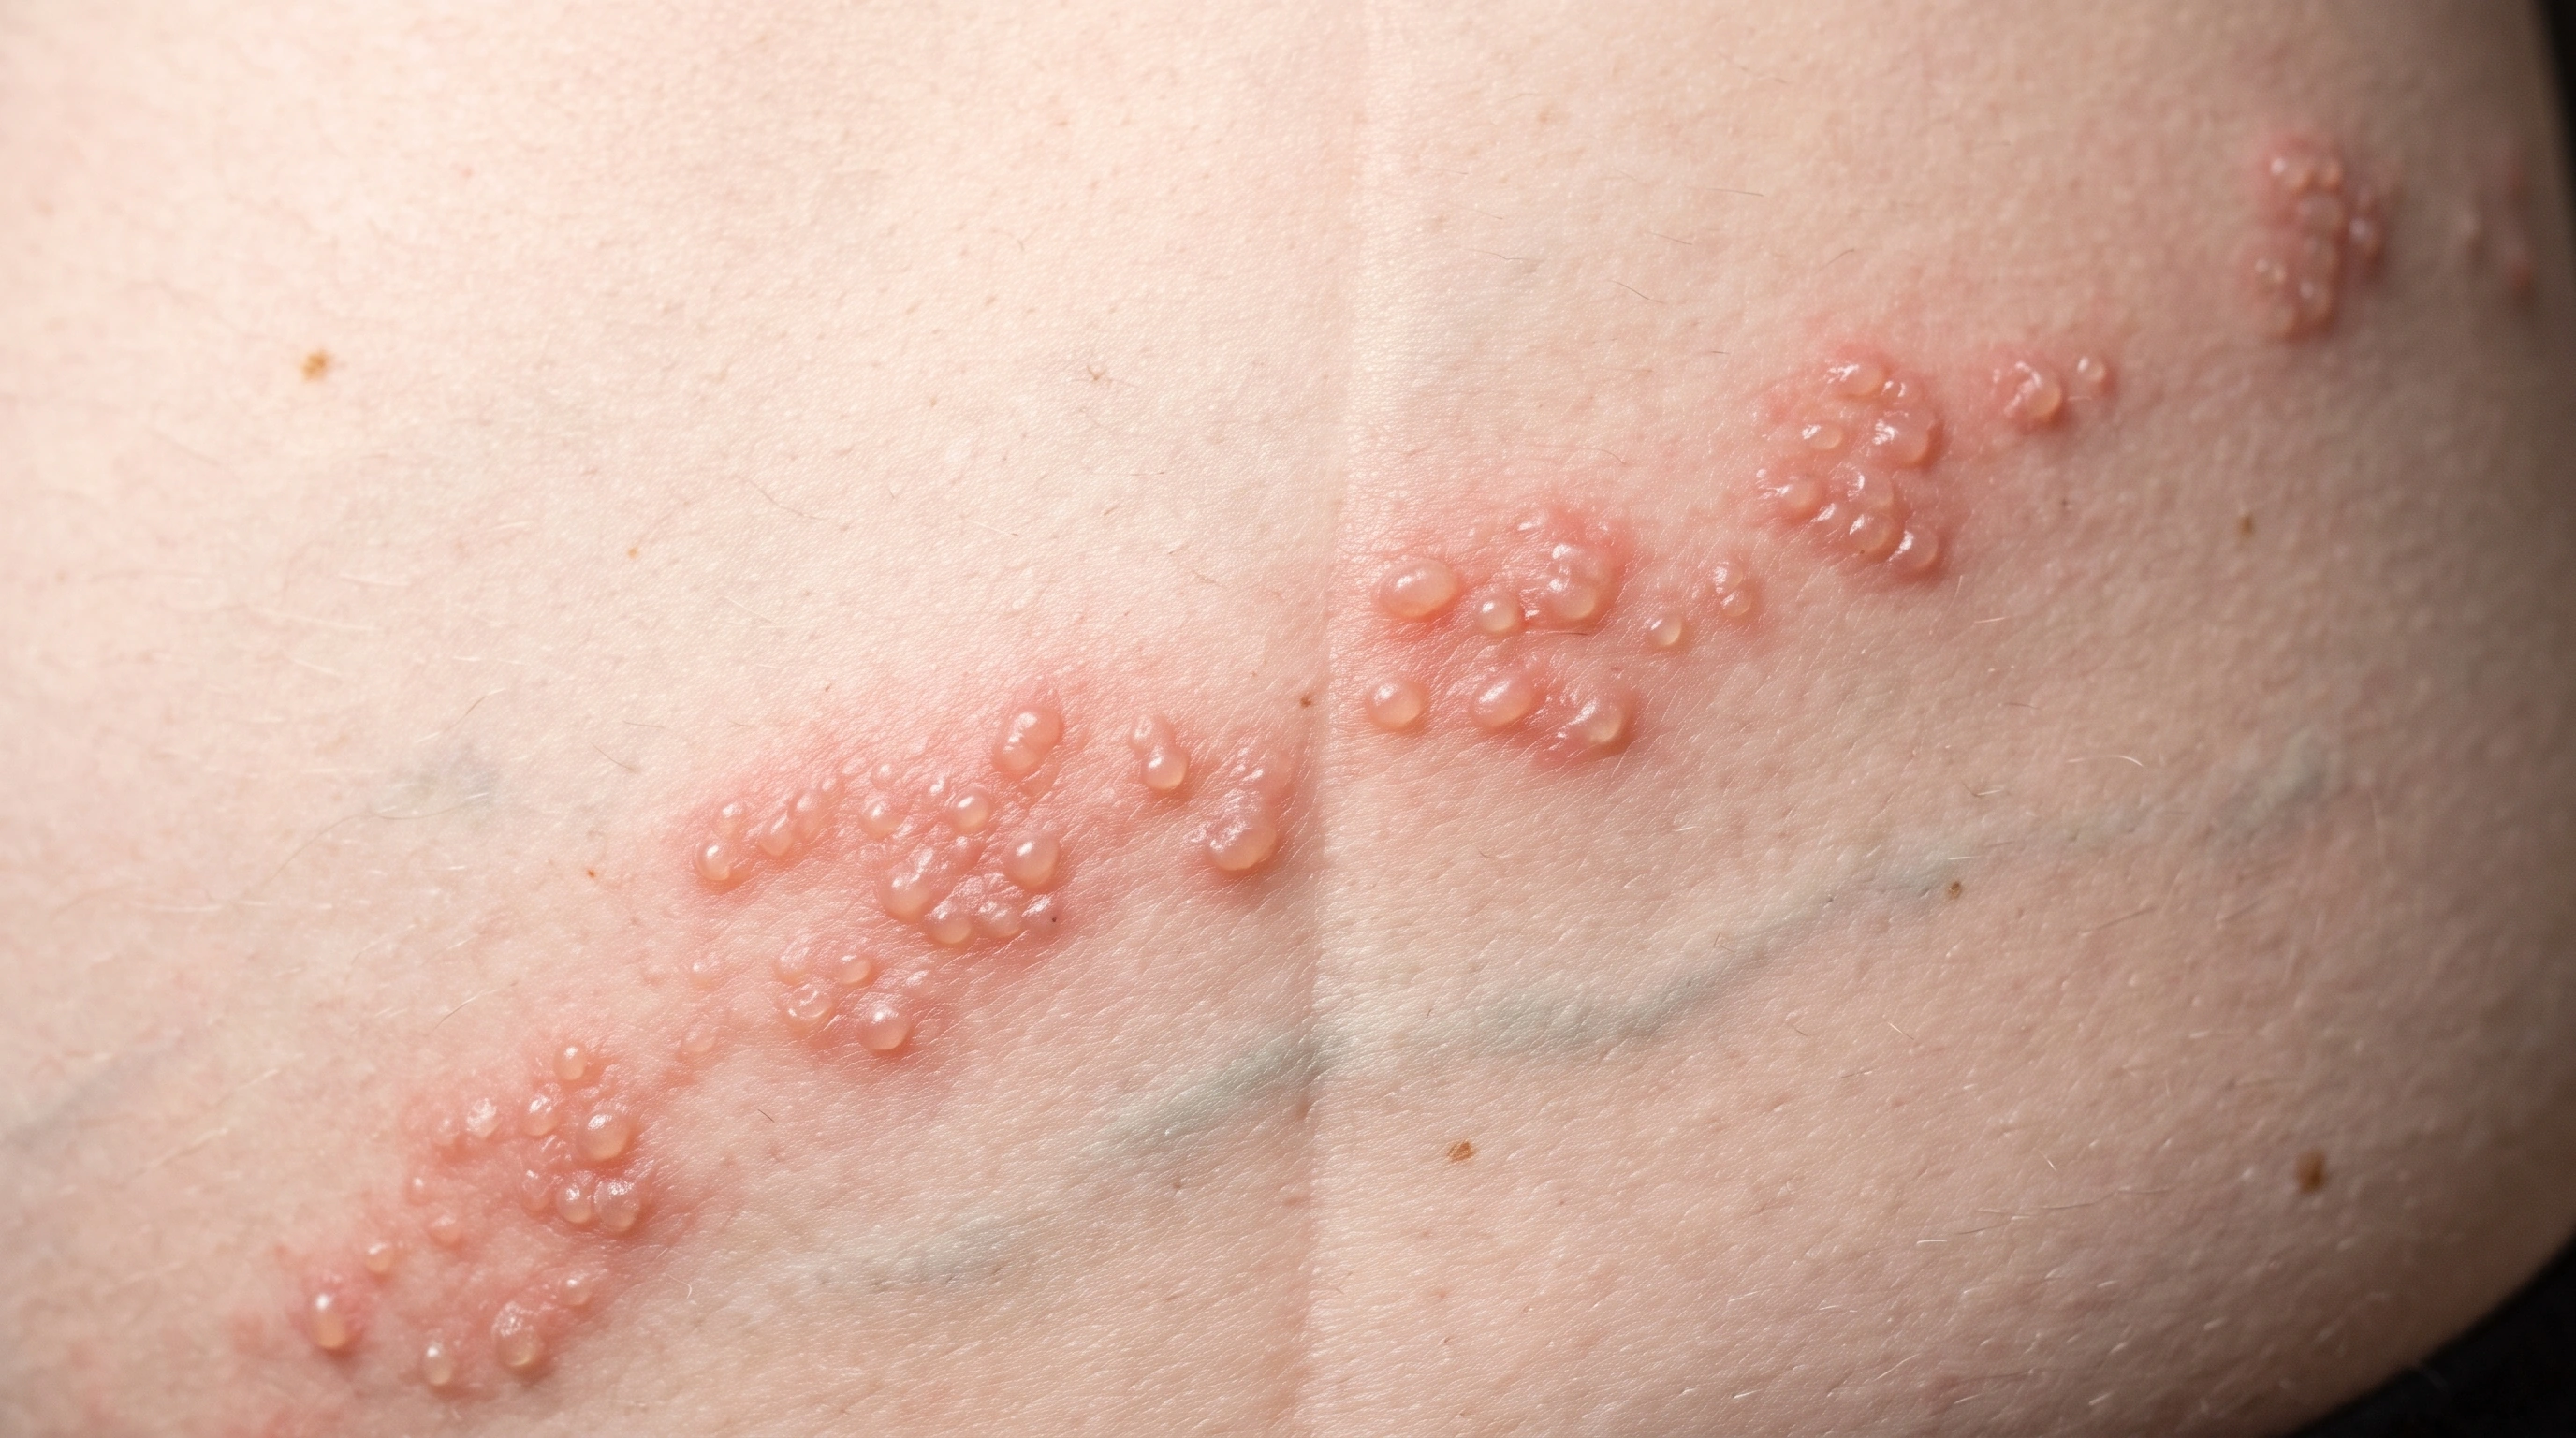
Herpes can occasionally spread to the eye or extensively through eczema-affected skin. Eye pain, widespread painful blisters, or exposure of a newborn requires prompt medical advice.

Frequent severe ulcers can accompany nutritional deficiency or inflammatory disease.

When to get help

When to get help

Seek care for severe, frequent or persistent episodes. Eye pain or redness, widespread blisters with eczema, or illness in a newborn needs urgent assessment.

Have an ulcer lasting over two to three weeks, frequent severe episodes or ulcers with other symptoms assessed.

Common questions

Cold Sores:How did I get this?

Almost certainly in childhood, from ordinary contact with someone who carried the virus - a kiss, a shared cup or spoon. Most people have no memory of it, because the first infection often causes nothing. It is not about hygiene or anything you did.

Cold Sores:How long am I contagious?

Most easily passed on from when blisters appear until the sore has fully crusted - roughly the first four to five days. Small amounts are shed when nothing is visible. Precautions matter most around newborns, eczema and anyone immune-suppressed.

Cold Sores:Why do I always get it in exactly the same place?

Because the virus lives in one nerve, which supplies one small patch of skin. When it reactivates it travels down to that patch. Some people have two or three usual spots.

Cold Sores:Will it ever go away for good?

The virus stays in the body permanently, so there is no cure. But episodes usually become less frequent over the years, and daily suppressive treatment can reduce them a great deal. Plenty of people effectively stop having them.

Cold Sores:Is it safe to kiss my baby?

Not while you have an active sore. Herpes simplex is dangerous in newborns in a way it is not in older children or adults. Do not kiss the baby, wash your hands before handling them, and cover the sore. If a newborn develops blisters or a fever, or becomes unusually sleepy or floppy, that is an emergency.

Cold Sores:Does the treatment work if I start it late?

Less well. Antiviral tablets stop the virus multiplying, and by the time blisters are out most of that has happened. Still worth taking for a severe episode, but the benefit is in the first 24 hours.

Canker Sores:What is Canker Sores?

Aphthous ulcers are painful non-contagious sores inside the mouth.

Canker Sores:What can I do day to day?

Avoid irritating foods and traumatic brushing; use a gentle oral-care routine.

Canker Sores:When should I get medical advice?

Have an ulcer lasting over two to three weeks, frequent severe episodes or ulcers with other symptoms assessed.

Sources

Sources and further reading

  1. DermNet
  2. Aphthous ulcer
Dermapedia on YouTube