Adapalene
Strong evidenceThe strongest thing you can buy without a prescription, and the best first move for most acne. It unclogs pores before they inflame, which is why it prevents spots rather than treating them.
Basal cell carcinoma is the most common cancer in people. It grows slowly and very rarely spreads to other organs, but it does not heal on its own, and left alone it keeps growing into the skin and tissue around it.
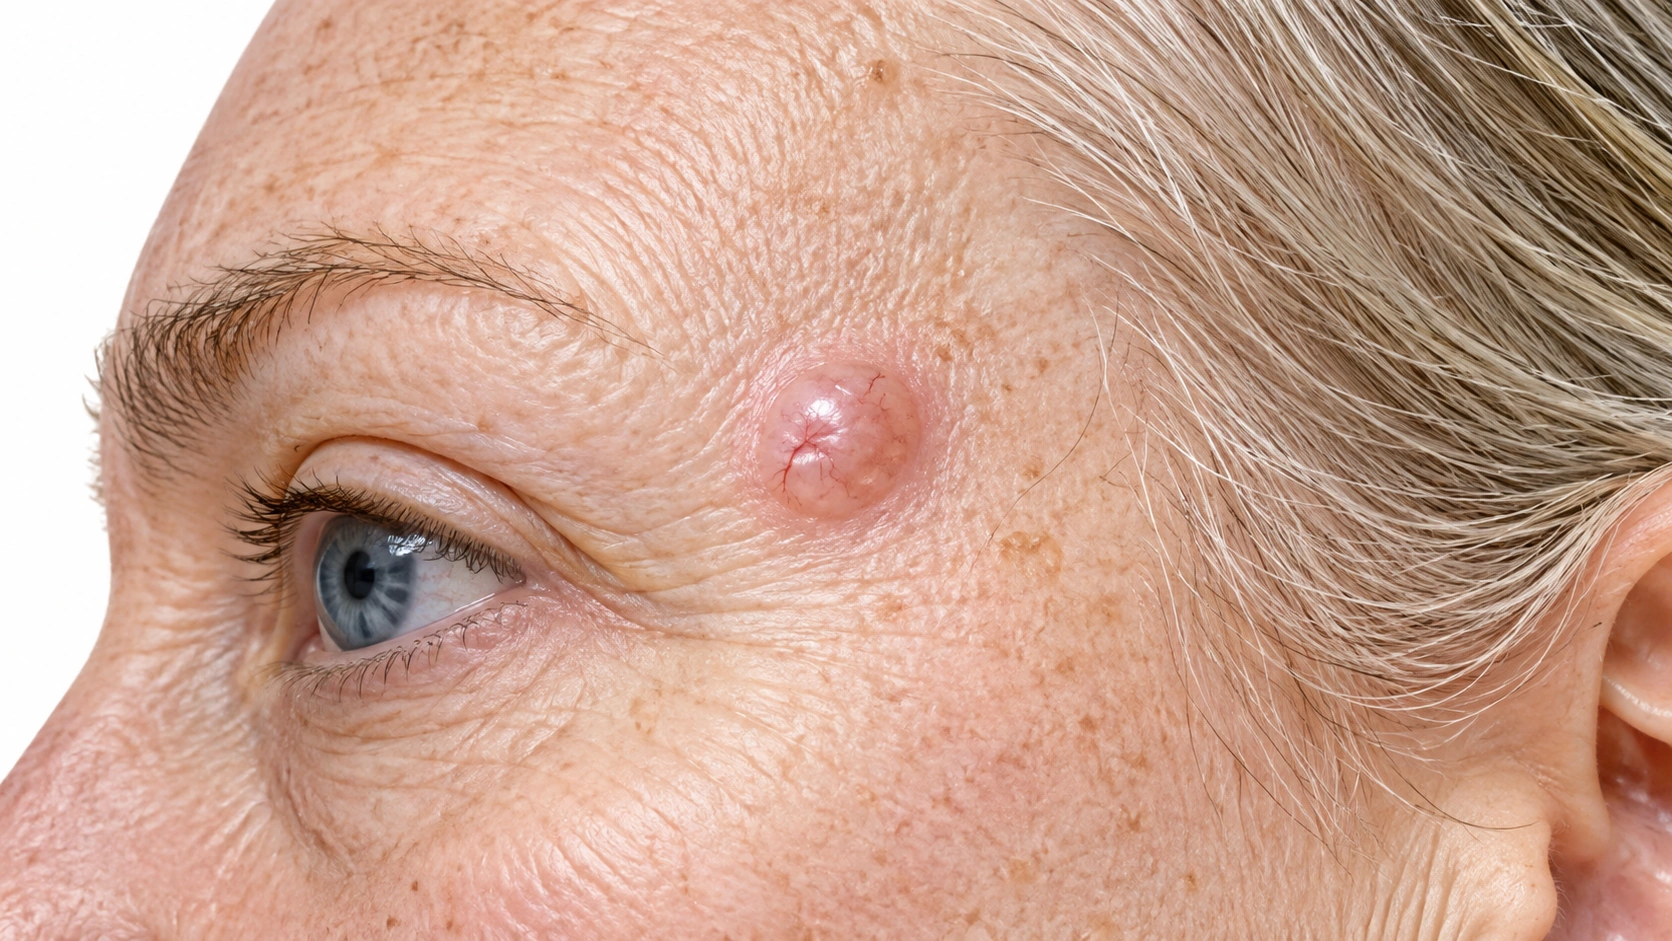

The same eight facts on every condition comparison.
It is a common skin cancer.
It usually grows locally and can damage surrounding tissue.
It looks different in different people.
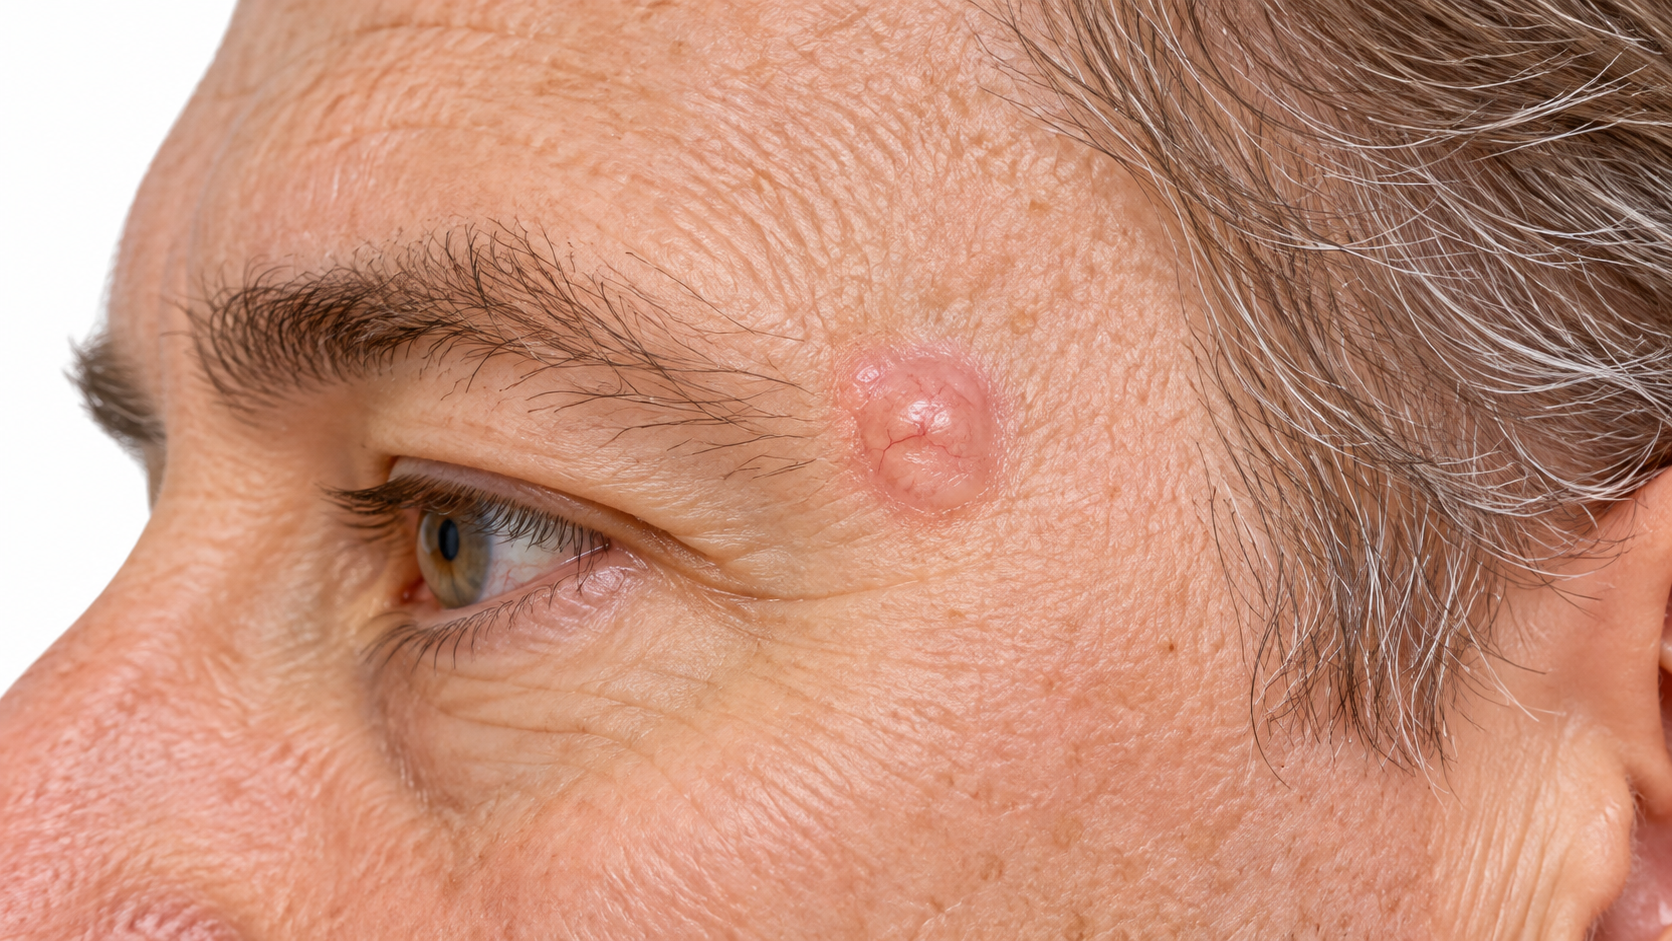
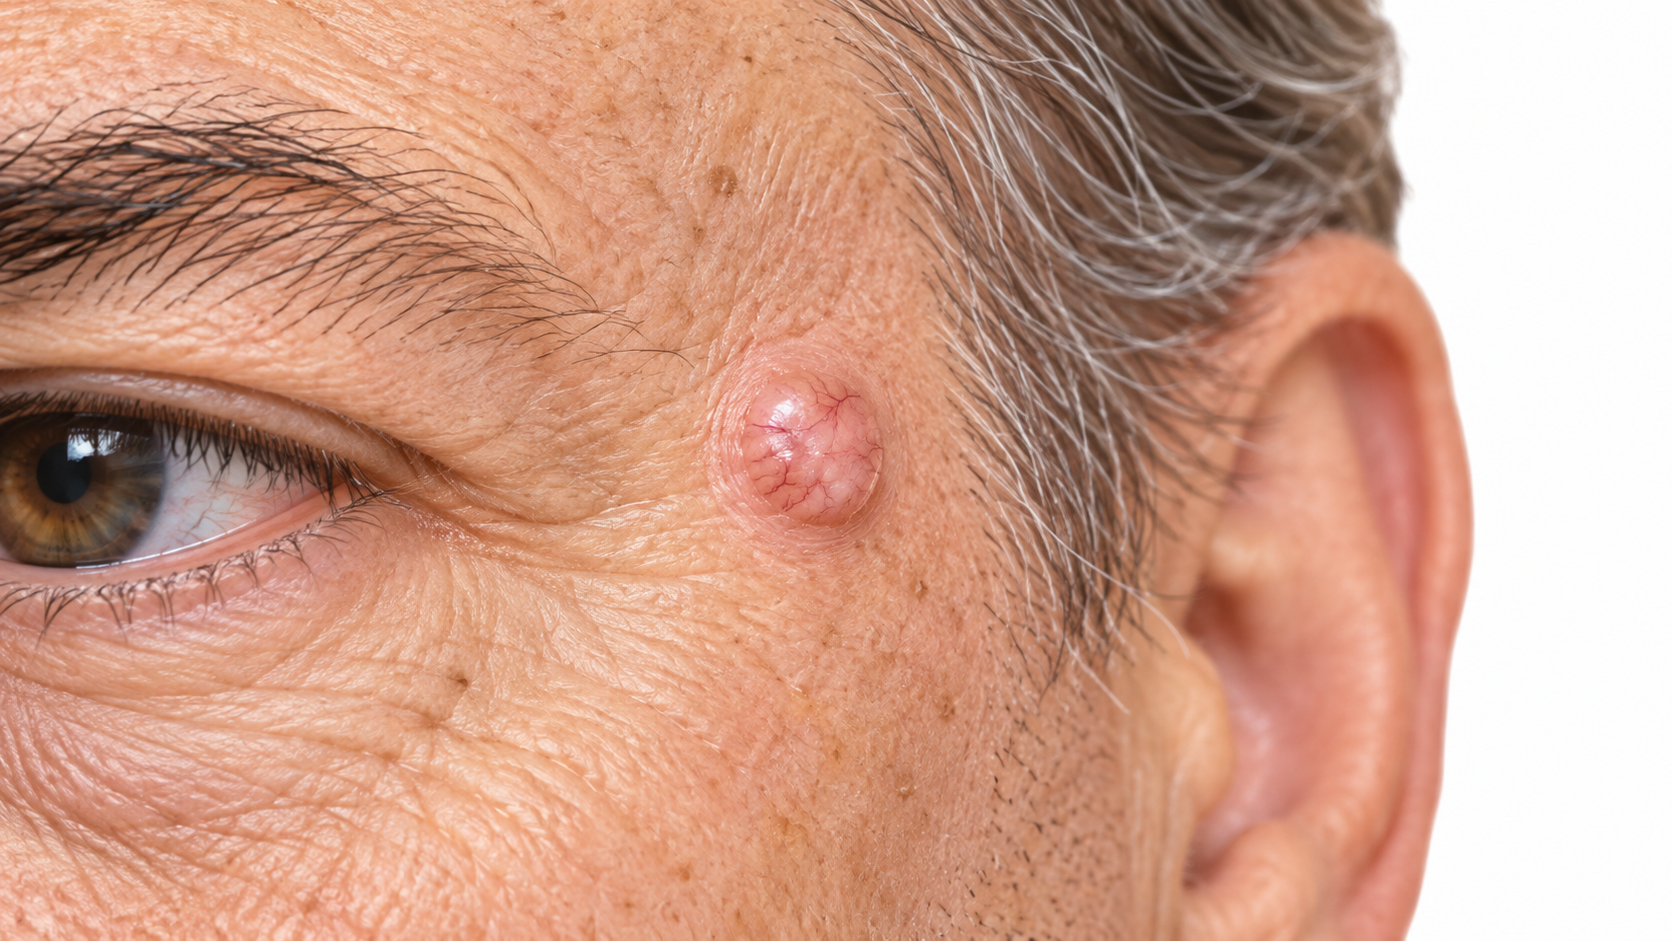
It may be a pearly bump, scaly patch or sore that bleeds and heals.
It rarely spreads.
Distant spread is rare, but it still needs treatment.
Biopsy guides treatment.
Location, size, subtype and history shape the treatment plan.
It starts in the follicle.
Acne affects the hair follicle and its oil gland.
Spots take several forms.
Plugs form blackheads or whiteheads; inflammation forms pimples and deeper lumps.
It is not about dirt.
Bacteria are only one part of the process.
Tests are rarely needed.
An unusual pattern or hormonal symptoms may call for assessment.
Overview
Oil and dead skin cells block hair follicles. This can cause blackheads, whiteheads, pimples, or deeper painful lumps.
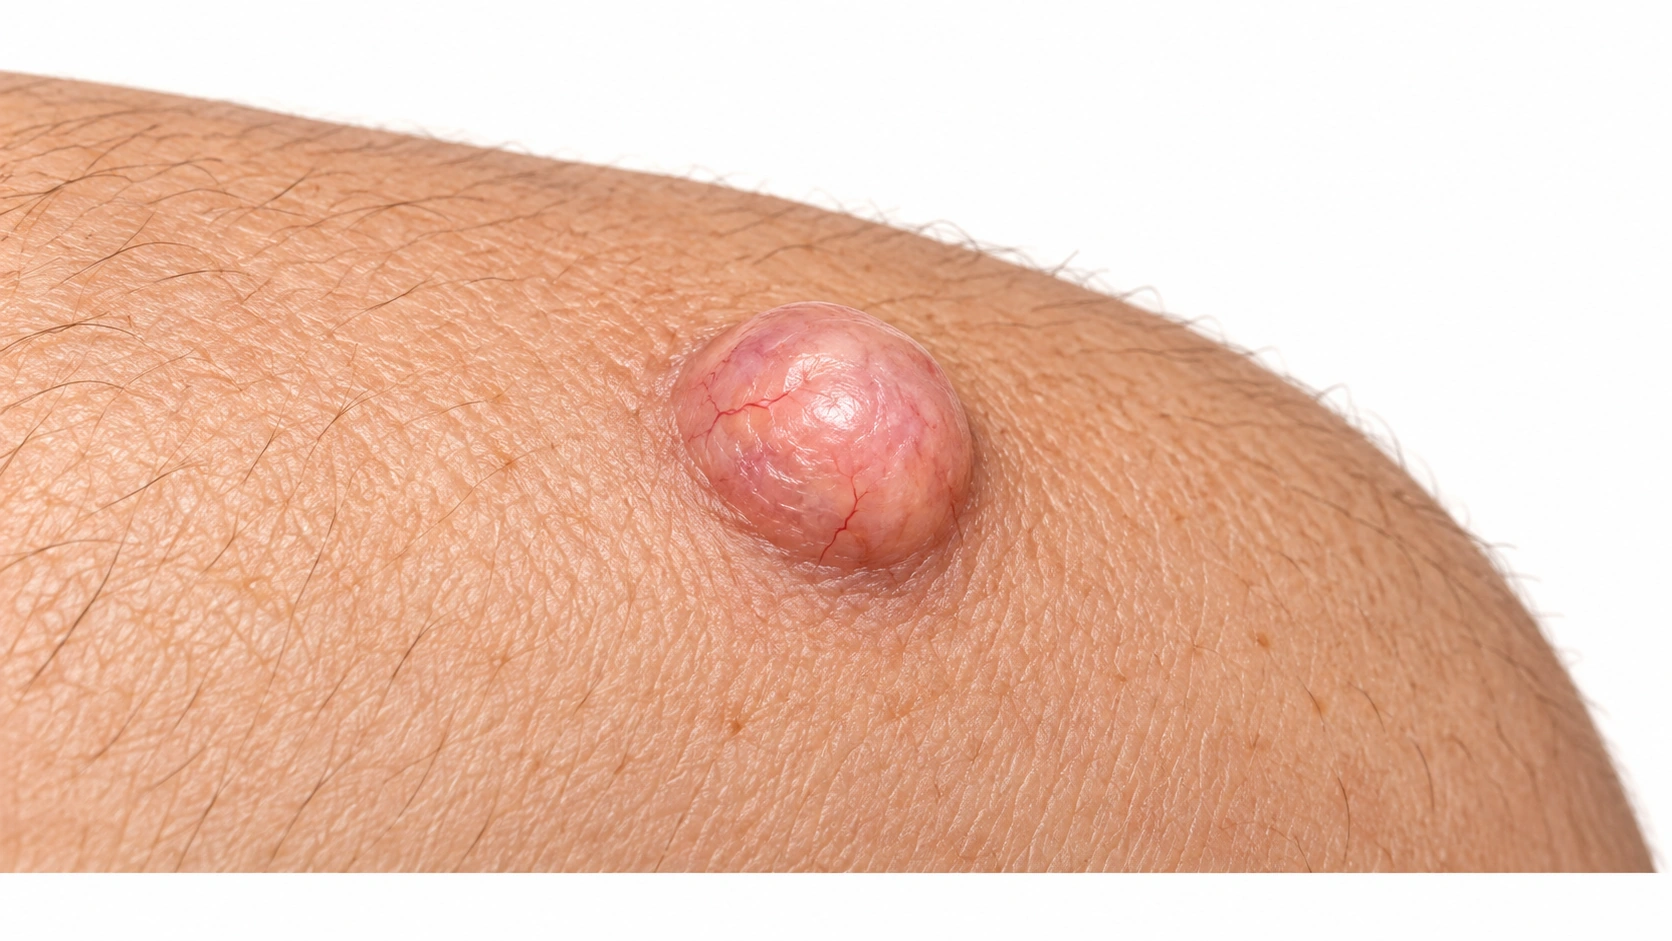
Nodular basal cell carcinoma Pearly bump; most common.
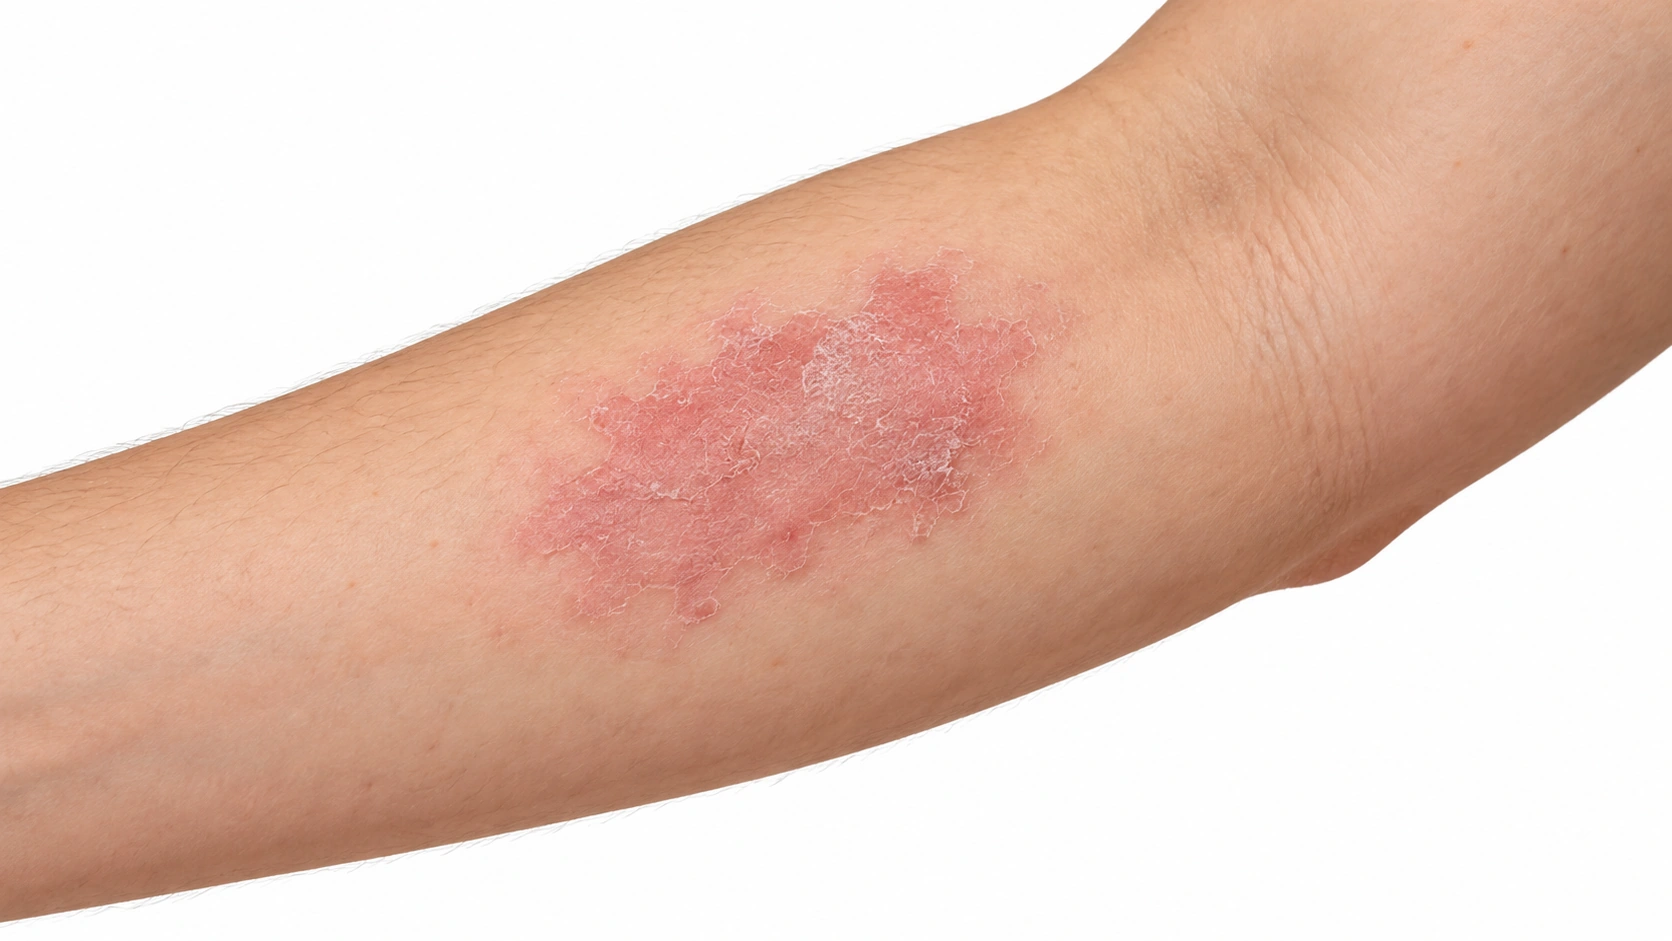
Superficial basal cell carcinoma Flat, scaly pink patch, often on the trunk.
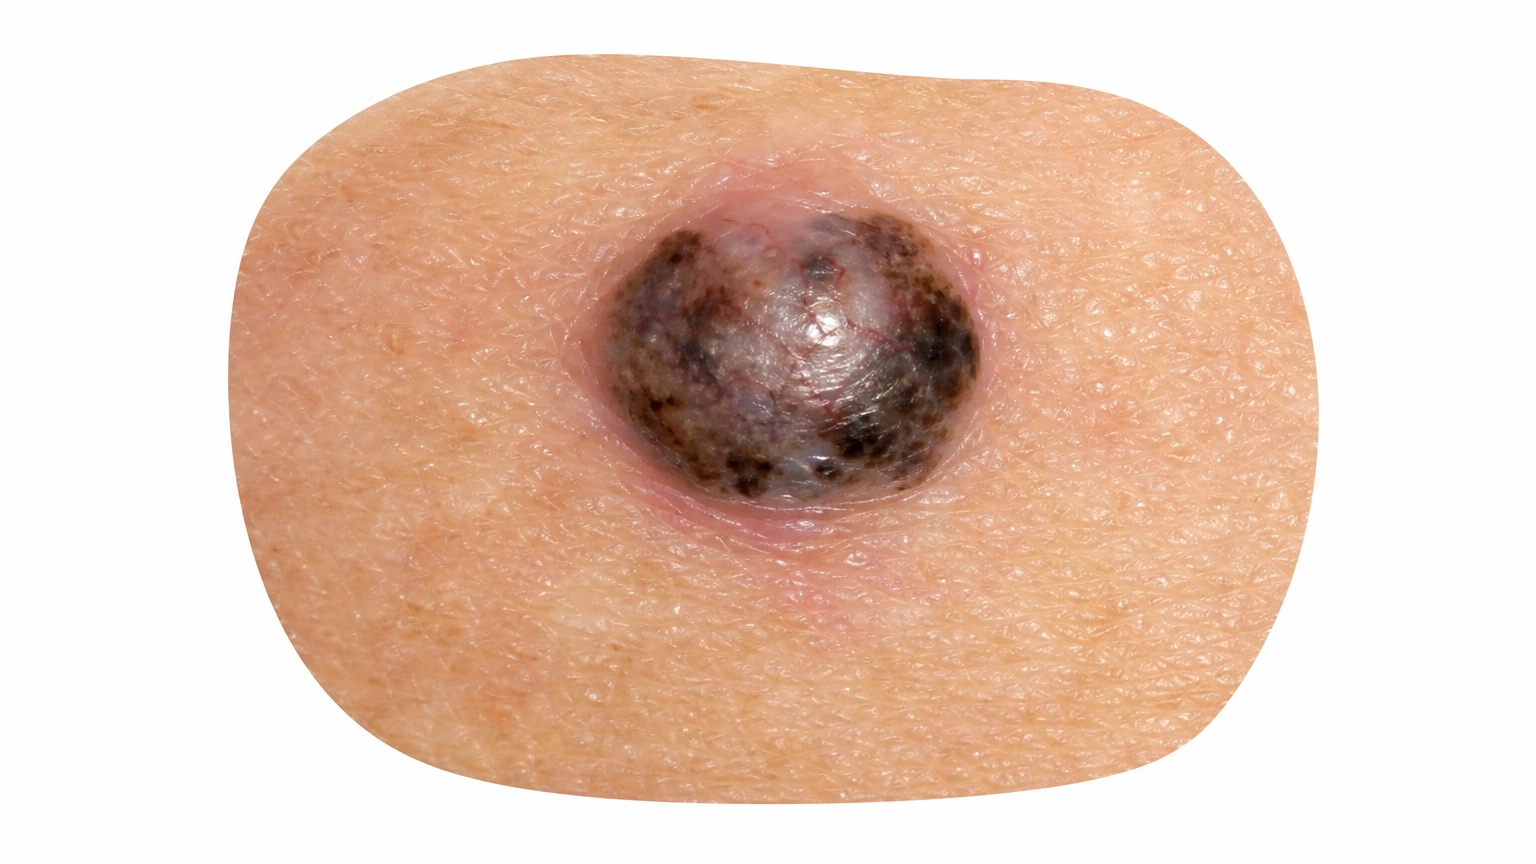
Pigmented basal cell carcinoma Brown to black pearly bump.
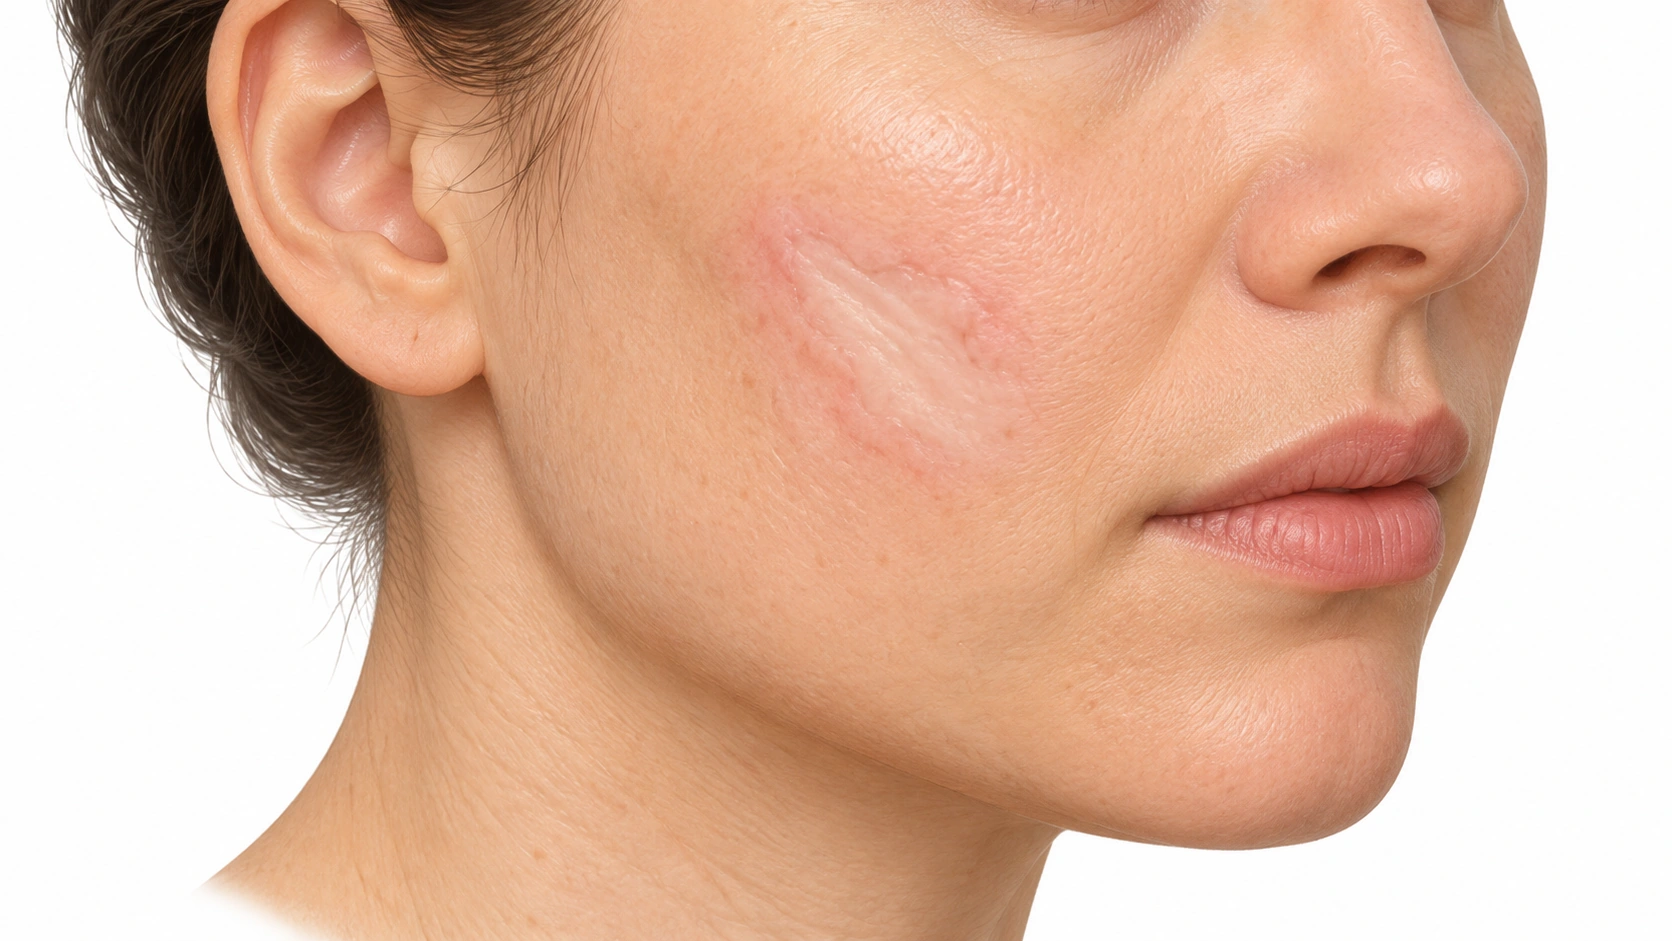
Morpheaform basal cell carcinoma Scar-like and harder to see.
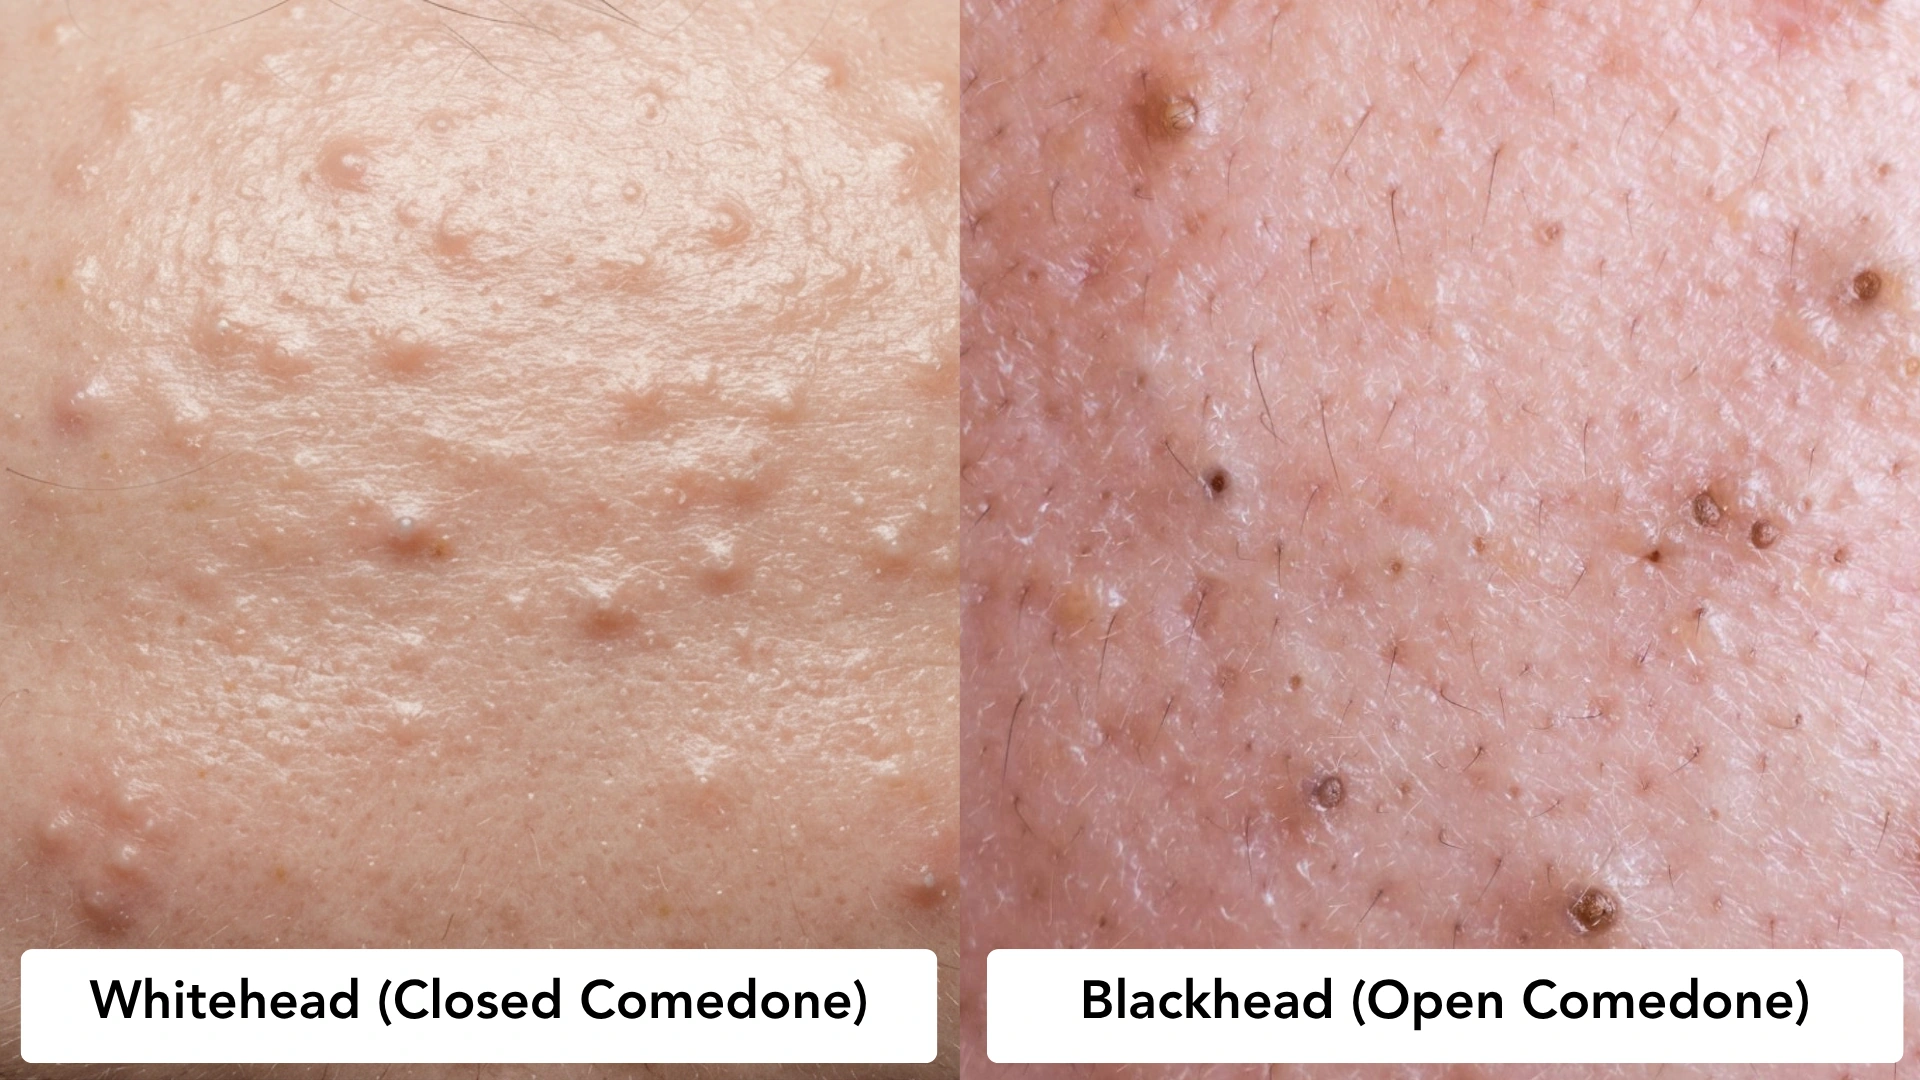
Comedonal acne Mostly blackheads and whiteheads.
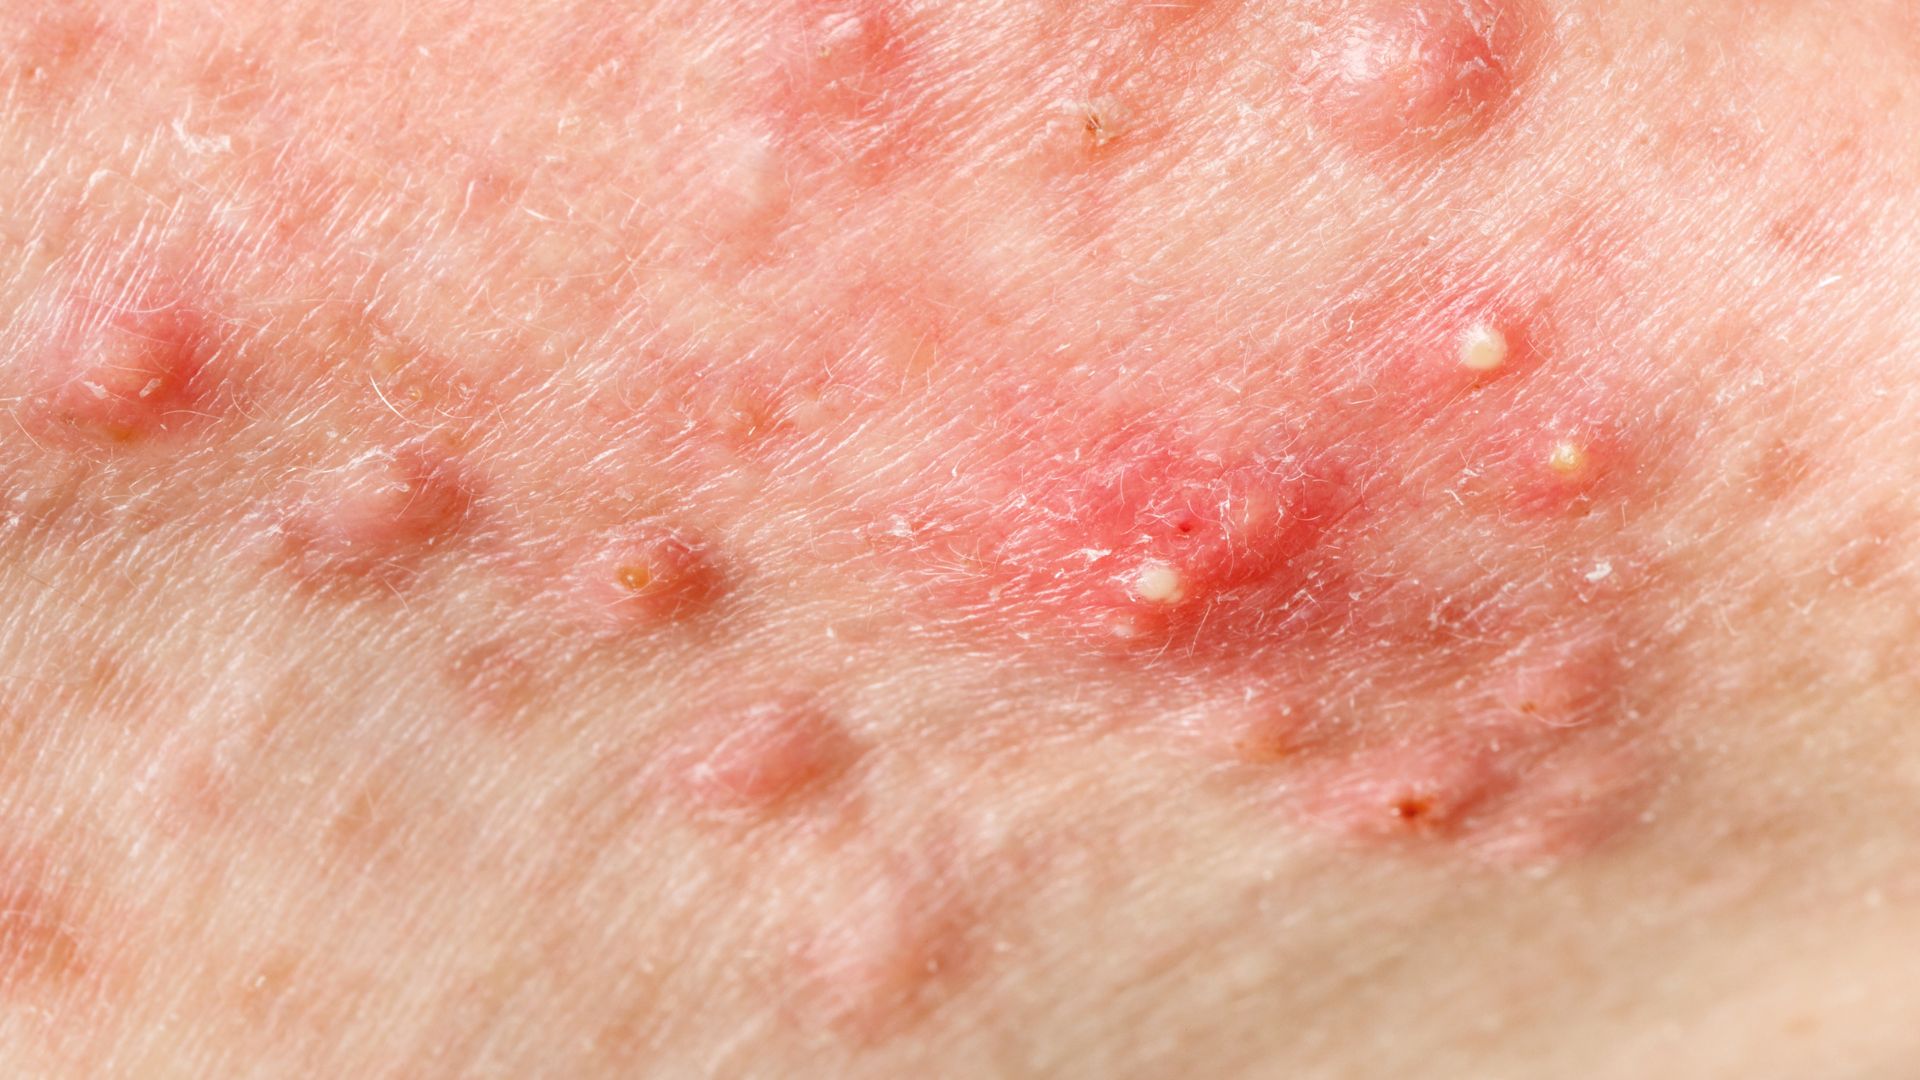
Inflammatory acne Red papules and pustules.
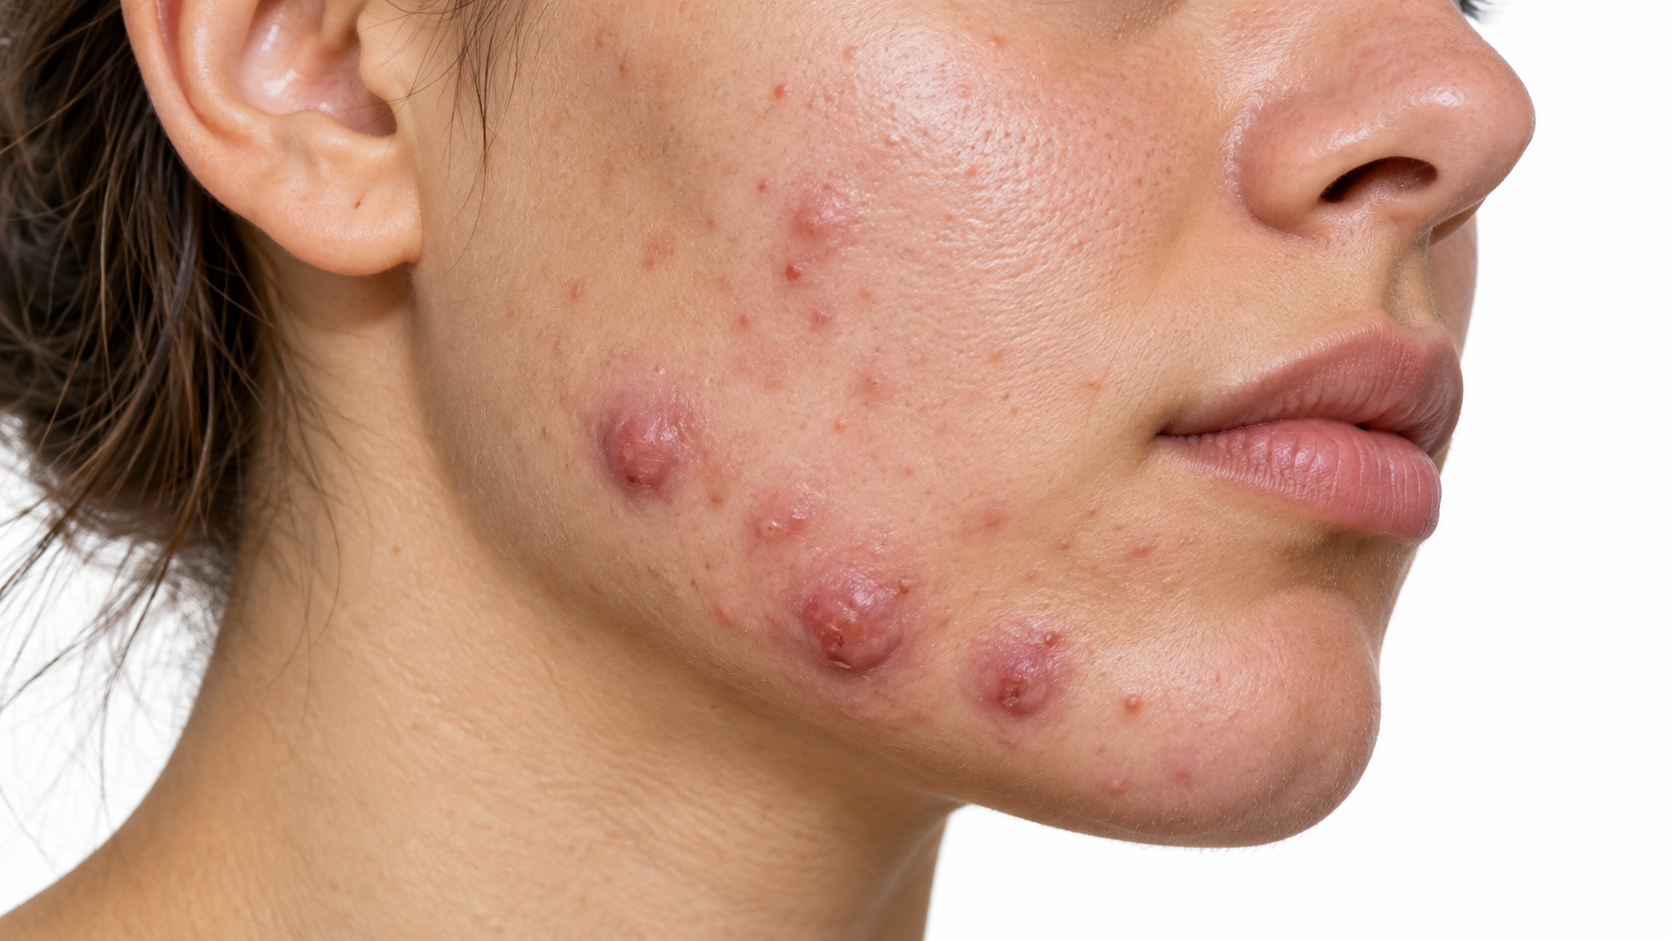
Nodulocystic acne Deep painful lumps that can scar.

Hormonal acne Breakouts along the jaw and chin.
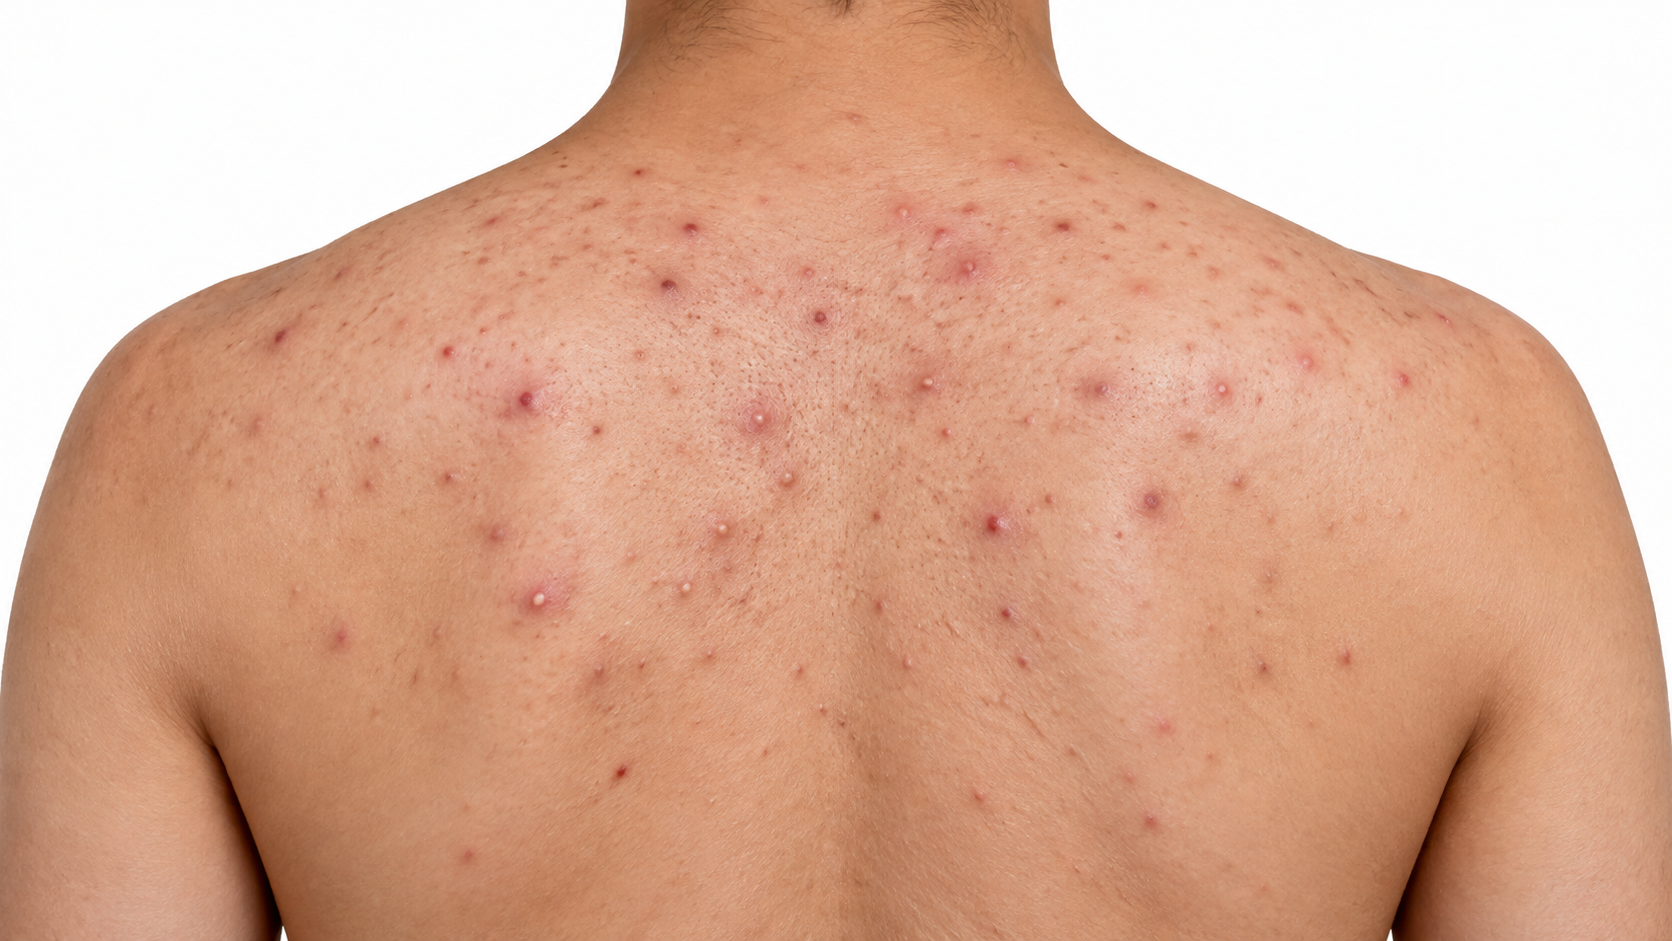
Body acne On the chest, back and shoulders.
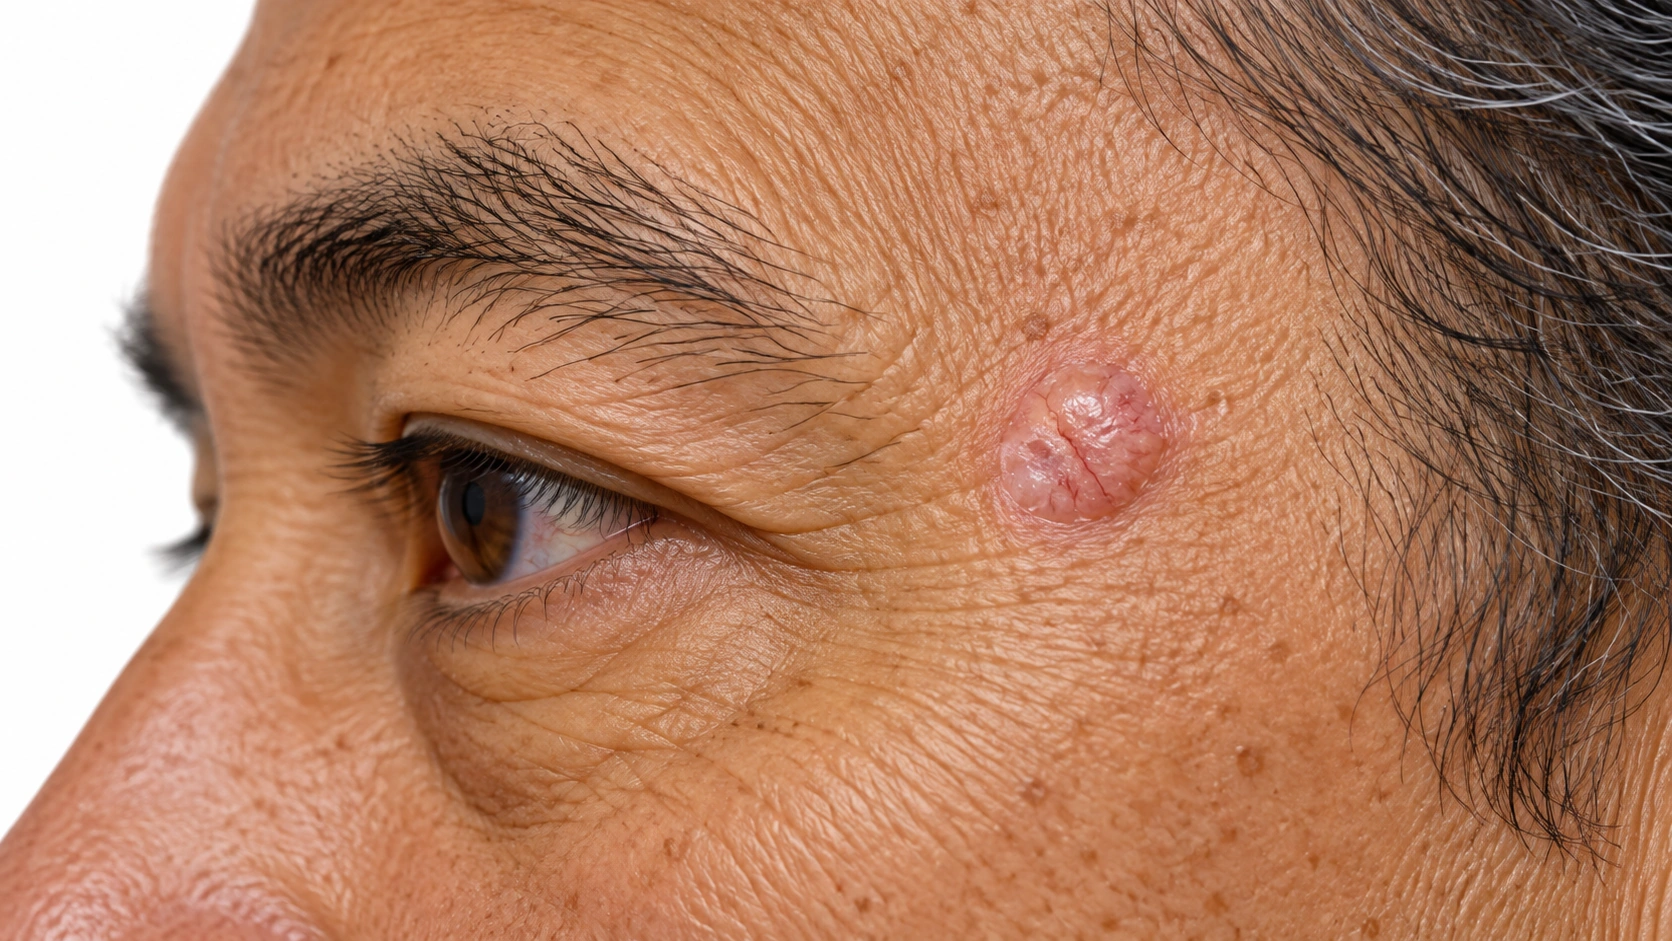
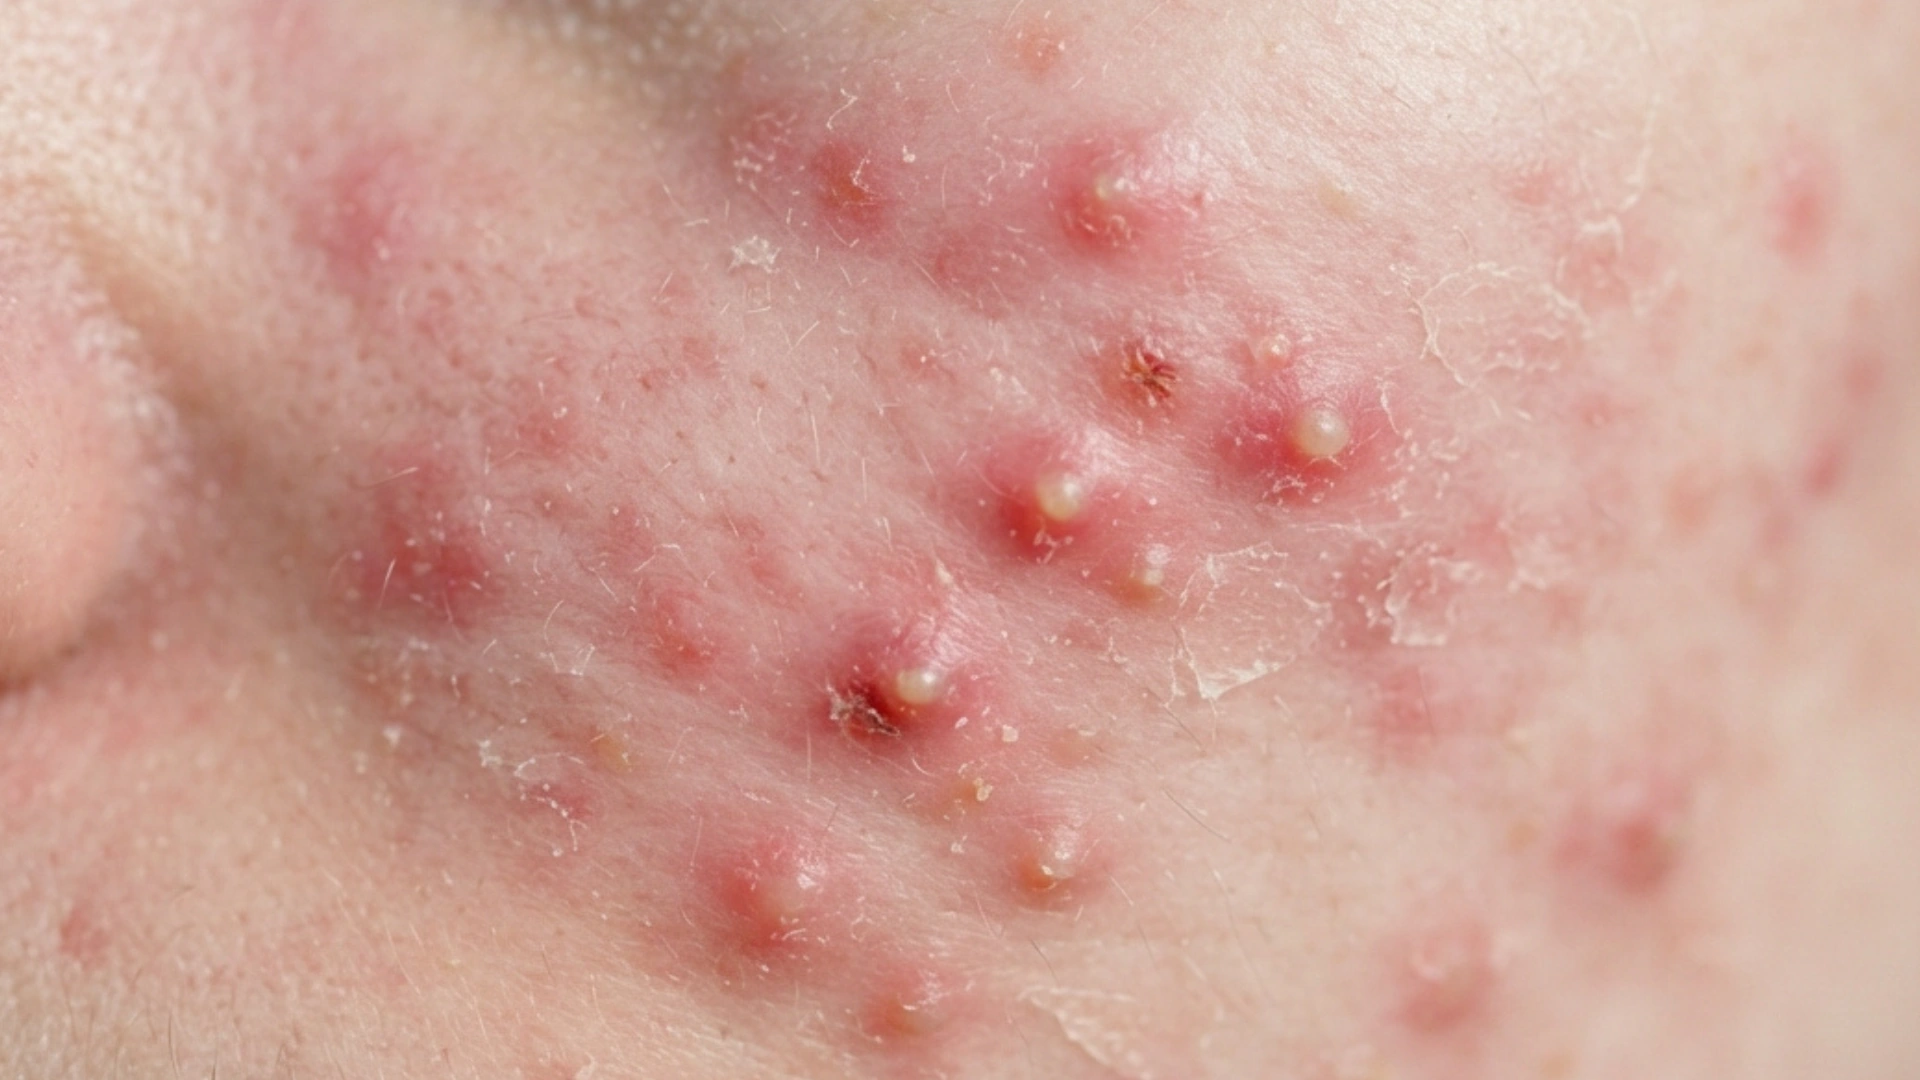
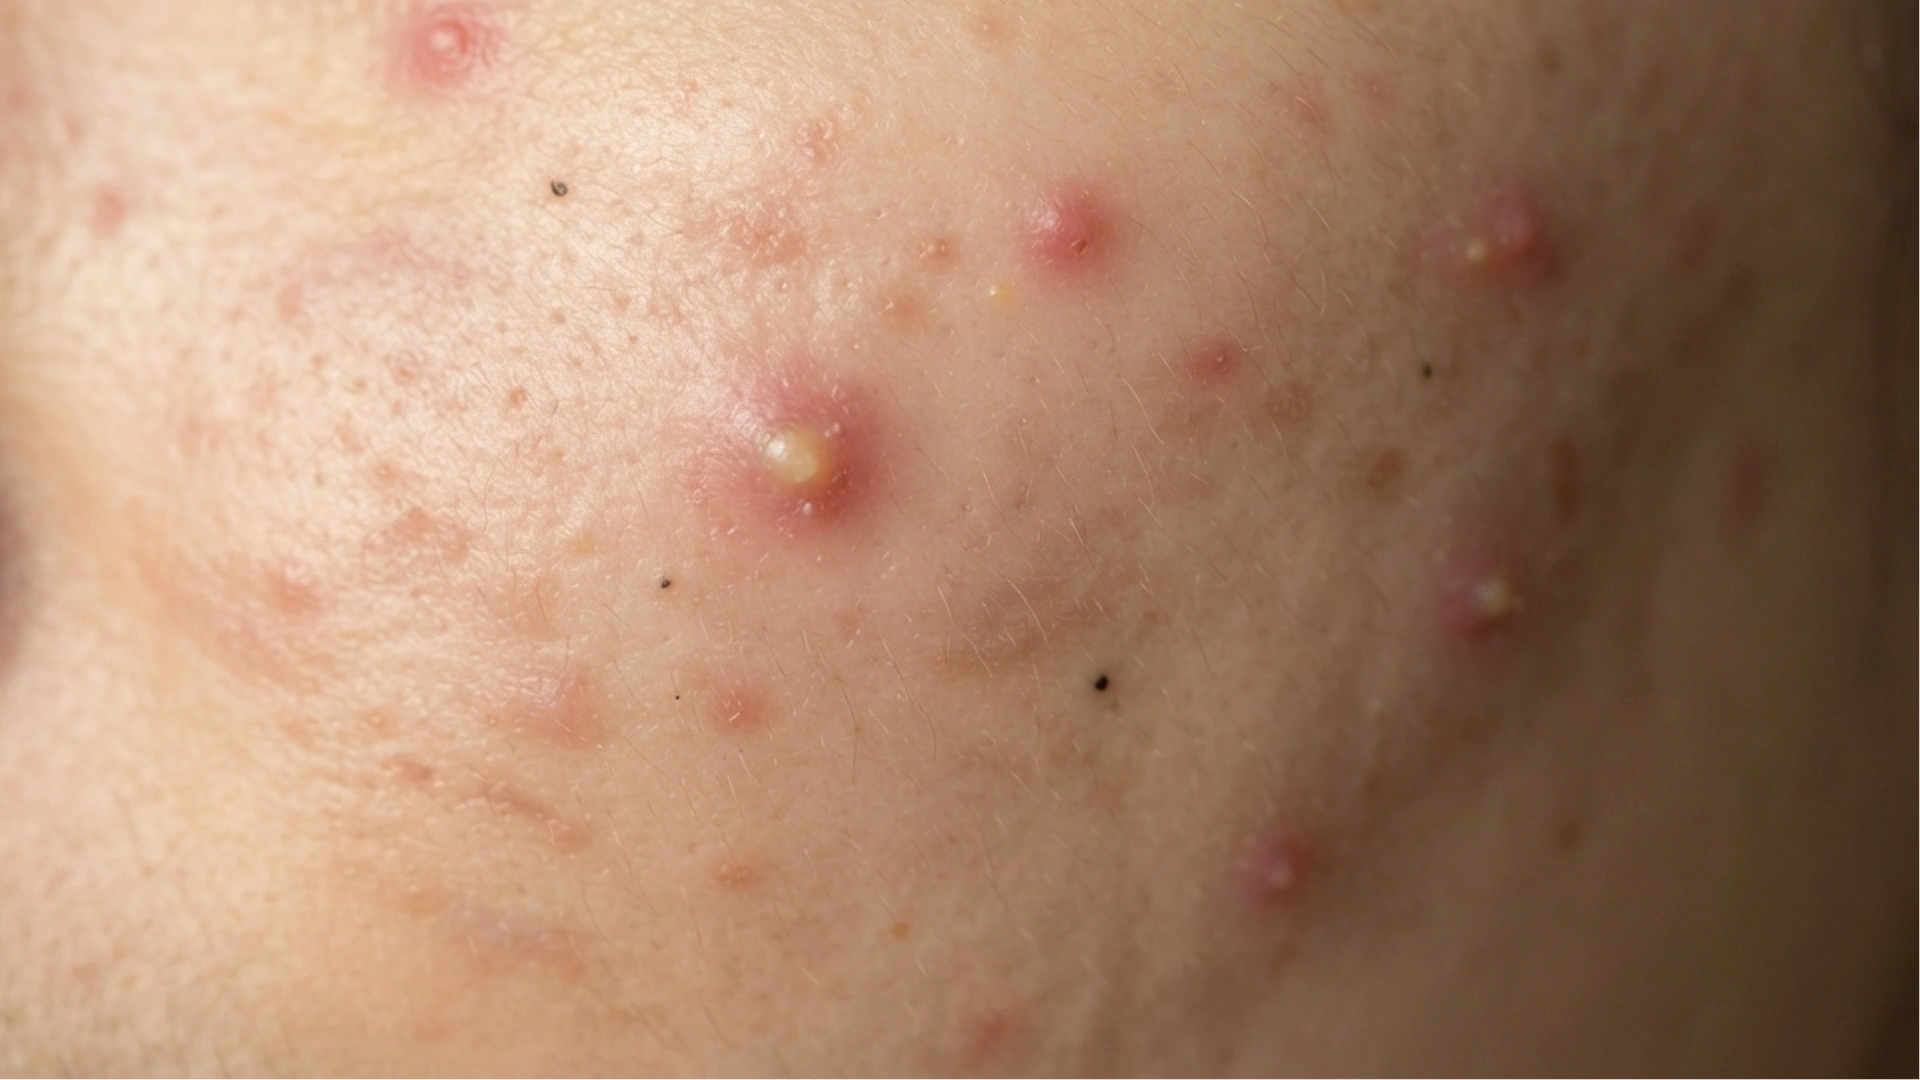
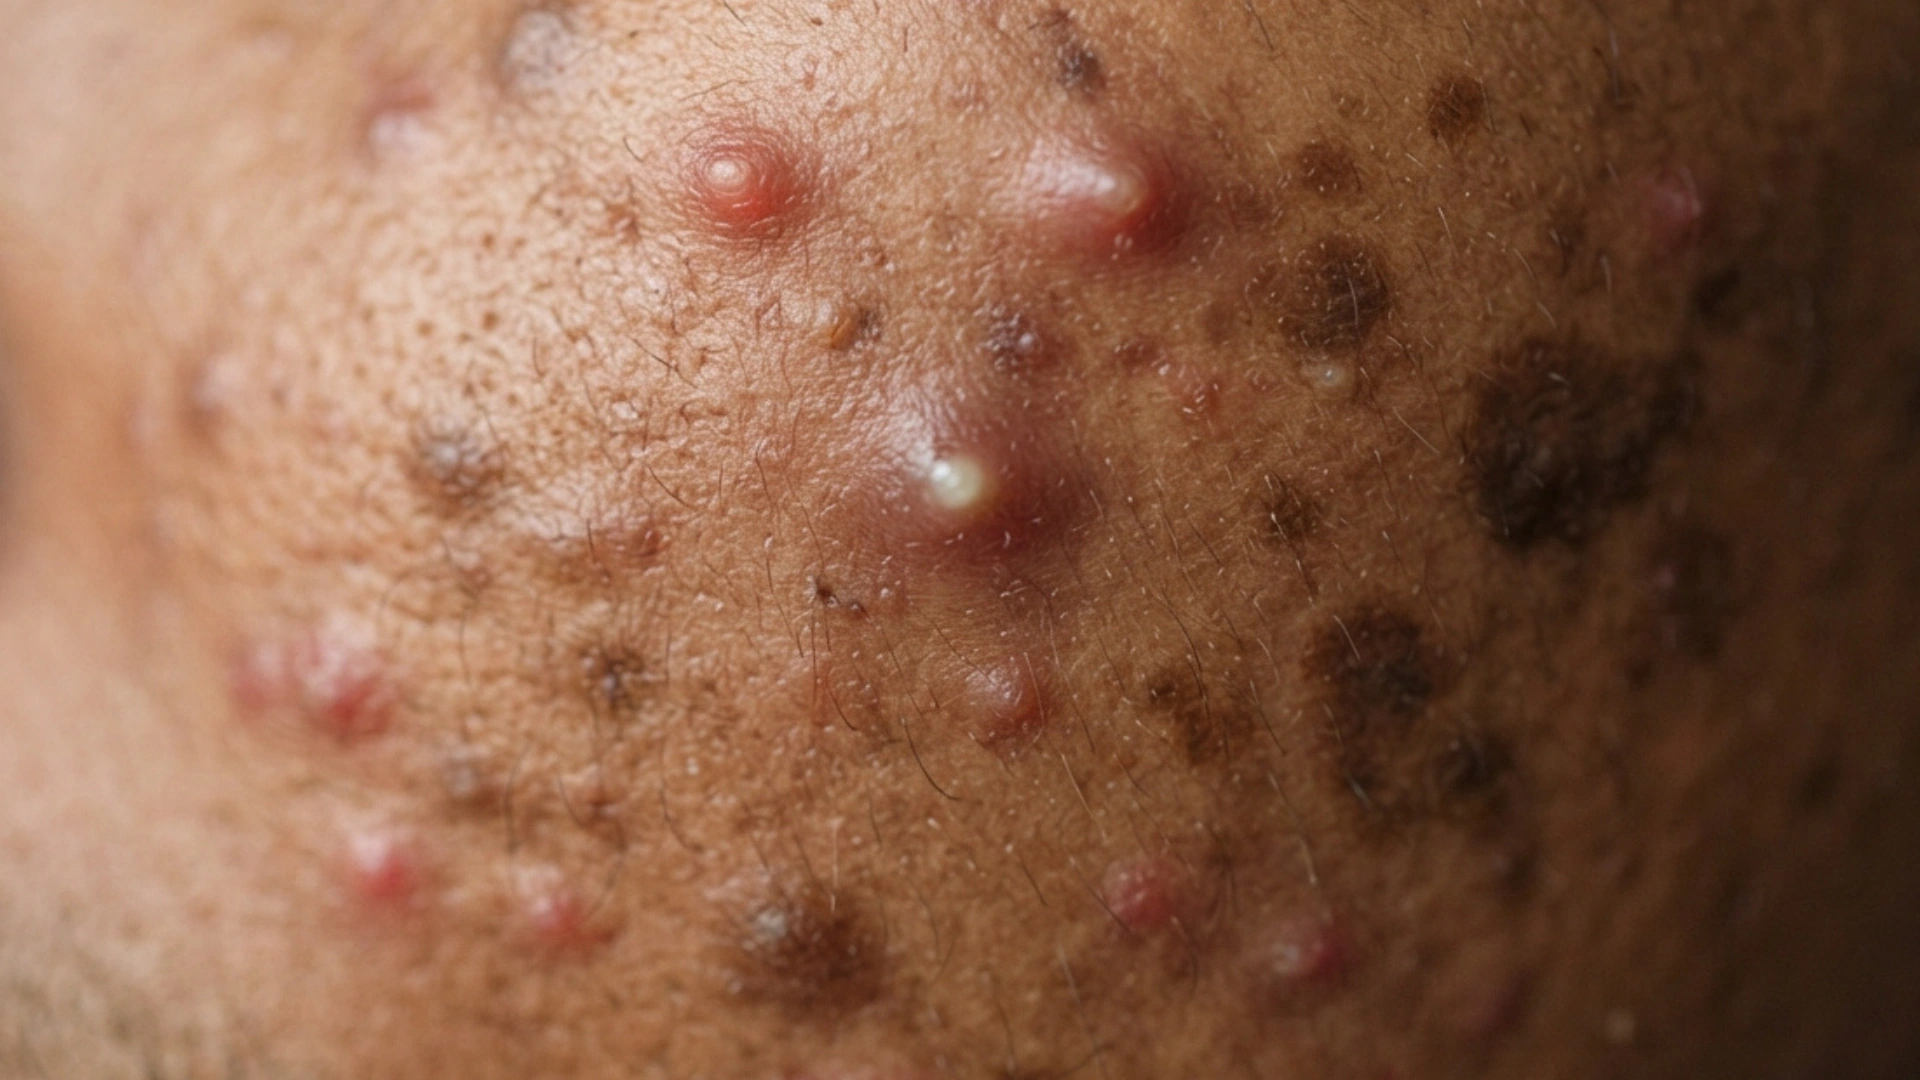
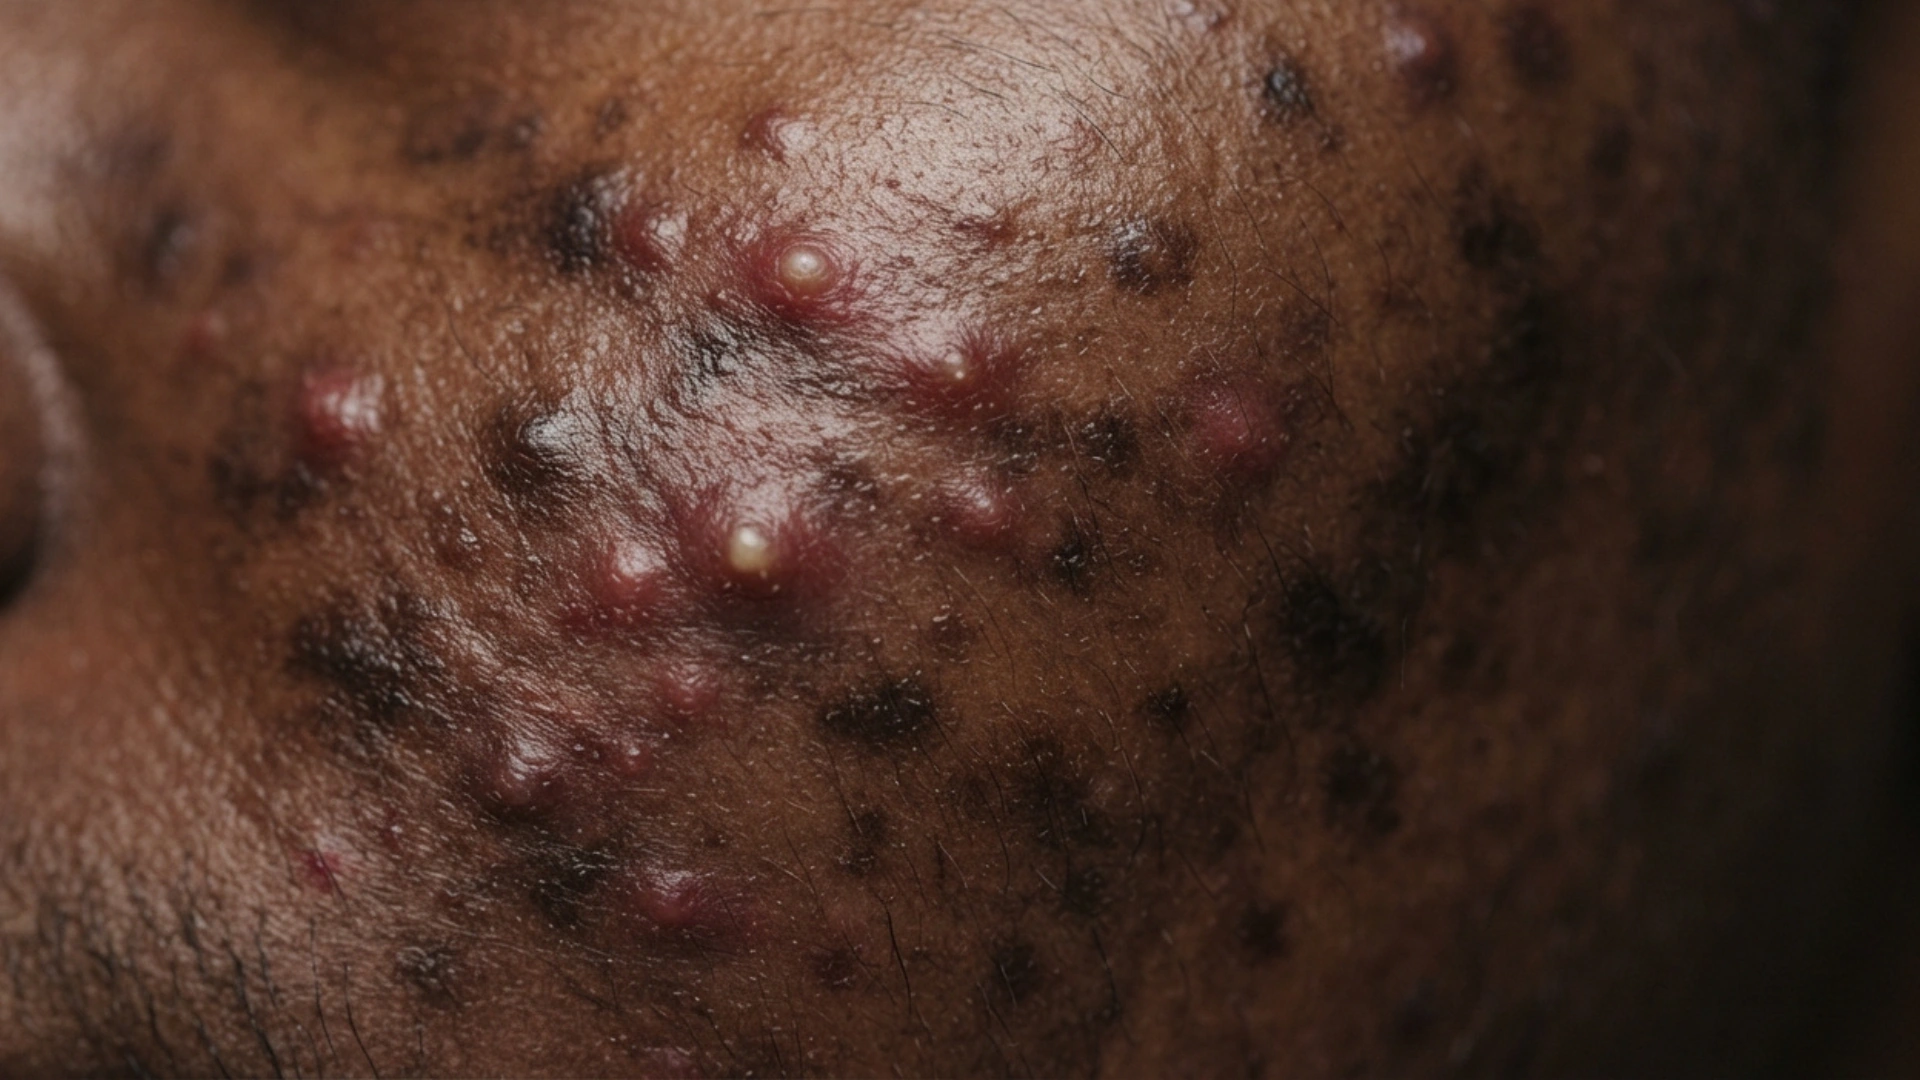


DNA changes disrupt normal growth signals in basal-type skin cells. Abnormal cell clusters can grow into nearby skin and produce a spot that bleeds, breaks down or fails to heal.
Oil and shed skin cells can block a hair follicle, changing the environment inside the pore. Bacterial activity and the immune response contribute to inflammation, swelling and tender spots.
Basal Cell Carcinoma. Most common in adults with cumulative ultraviolet damage, though younger adults can develop it.
Acne. Acne Often in teens Often begins in the teen years; acne can continue or first appear in adulthood.
Basal cell carcinoma starts when ultraviolet light damages basal cells in the lowest layer of the epidermis.
Acne forms when oil and dead skin cells clog pores, acne bacteria grow inside them, and inflammation follows. Hormones that increase oil play a central role.
Oil and dead skin cells block hair follicles. Bacteria within the follicles and inflammation contribute to pimples and deeper spots. Hormonal changes can increase oil production.
Fair skin, and rare conditions like Gorlin syndrome, raise the risk.
Acne often runs in families. A parent with severe acne raises the chance of severe acne.
Acne can run in families. A close relative with deep, painful acne increases the chance of developing that pattern.
Evidence labels come from each condition’s own treatment list.
The strongest thing you can buy without a prescription, and the best first move for most acne. It unclogs pores before they inflame, which is why it prevents spots rather than treating them.

Kills the bacteria involved in inflamed spots, and is the one thing that stops acne bacteria becoming resistant to antibiotics. Lower strengths work about as well as higher ones and sting less. It bleaches towels and pillowcases.

Works on the spot and the mark it leaves at the same time, which makes it useful on deeper skin tones. It is also one of the few acne treatments considered safe in pregnancy.

Gets inside the pore and loosens the plug, so it suits blackheads and whiteheads more than deep spots. Gentler than a retinoid, and weaker than one.

Sold heavily for acne, and the evidence for clearing spots is thin. It is genuinely useful for the marks left behind and for tolerating stronger actives - just not as the treatment itself.
An old treatment, usually a mask or a spot dab, that dries the surface of a spot and mildly loosens plugs. It is gentle enough for skin that cannot tolerate benzoyl peroxide or a retinoid. It smells, and it is weaker than everything above it on this list.

A 5 percent gel reduces inflamed spots in small studies, more slowly than benzoyl peroxide does. Neat oil straight from the bottle is a common cause of an itchy rash, so buy it already diluted. It is a reasonable extra rather than something to build a routine on.

The most studied topical in acne. Stronger than adapalene and more irritating with it, so it is usually the step up rather than the starting point. Not used in pregnancy.

A newer retinoid, and the one specifically tested on chest and back acne rather than just the face. Useful when the trunk is the main problem. Expensive without coverage.
Calms inflamed spots, but should never be used on its own. Guidelines are explicit about this - alone it stops working within months as bacteria adapt, so it is always paired with benzoyl peroxide or a retinoid.

The strongest of the prescription retinoids, and the step to take when tretinoin has stopped making a difference. It is particularly good on stubborn blackheads and whiteheads. It is also the most irritating of them, so it is usually started two or three nights a week. Not used in pregnancy.

Blocks the hormone signal that drives oil production, but only where you put it. It is the first hormonal option that works topically, and the only one that can be used by men as well as women.

Mild on the skin and tends to suit adult women with inflamed spots who cannot tolerate a retinoid. Applied at the same time as benzoyl peroxide it can temporarily stain skin orange, so space them apart.

Brings widespread inflamed acne down quickly, and is meant to be used for three to four months, not indefinitely. Always alongside a topical, which is what carries on once the tablets stop.
The only acne treatment that often produces lasting clearance after the course ends. What it costs you is months of dry lips and skin, blood tests, and strict pregnancy prevention. For acne that scars, that trade is usually worth making early rather than late.

For the pattern rather than the individual spot - deep jawline acne in adult women that flares with the cycle. It works slowly, over three to six months, and can be continued long term. Not used in pregnancy.

Lowers the hormone signal driving oil production across the whole body, so it suits acne on the chest and back as well as the face. Takes about three months to show, and carries a small clot risk that needs weighing up.

Another tetracycline antibiotic for widespread inflamed acne, used the same way as doxycycline: three to four months, always alongside a topical. It is usually kept as the second choice, because it carries rarer but more serious side effects, including a blue-gray skin discoloration with long use.
A narrow-spectrum antibiotic designed specifically for acne, so it disturbs gut bacteria less than doxycycline. One tablet a day, still meant for three to four months and still alongside a topical. It works about as well rather than better, and it is considerably more expensive.
Deals with one stubborn painful lump, not the condition. It settles in a day or two and is the safe alternative to squeezing it. It does nothing to prevent the next one.
The tumor is removed in stages and the edges are examined under a microscope during the same appointment, so complete removal is confirmed before the wound is closed. It has the highest cure rate and spares the most normal tissue, which is why it is used on the face and for aggressive subtypes. It takes several hours, and it is not needed for every tumor.
The tumor is cut out with a margin of normal skin around it and the wound is stitched, with the margins checked by a pathologist afterwards. It is the standard treatment for most tumors away from the face, and it cures the large majority in one visit. If the report comes back with the tumor at the edge, more treatment is needed.

The tumor is scraped away and the base burned, repeated a few times in one visit. It suits small, thin, superficial tumors on the trunk and limbs and is quick and cheap. Nothing is checked under a microscope afterwards, so it is not used on the face or for aggressive subtypes, and it leaves a permanent pale round mark.

A light-sensitizing cream is left on the tumor and then activated with a lamp, usually in two sessions. It is for thin superficial tumors only, confirmed by biopsy, and it has the advantage of treating the sun-damaged skin around them at the same time. It stings during the light, and the cure rate is lower than surgery.
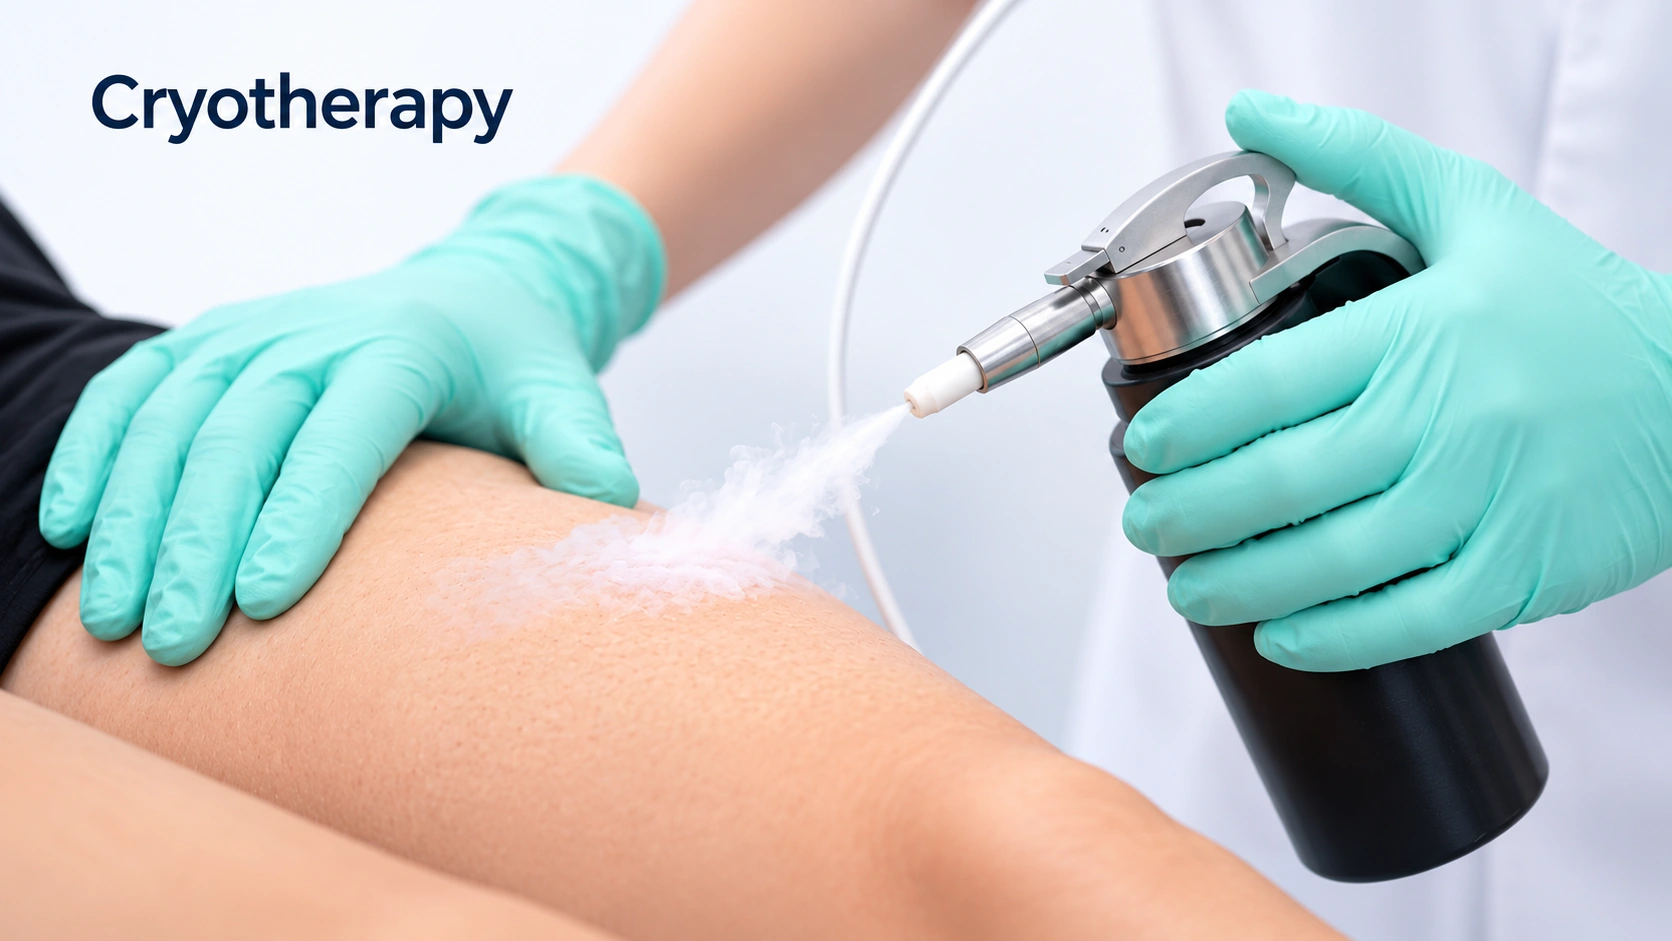
Freezing is quick and occasionally used for small superficial tumors when other options do not suit. Nothing is checked under a microscope, so an incompletely treated tumor can carry on growing under a healed surface. It also leaves a permanent pale patch, which is much more noticeable on deeper skin tones.
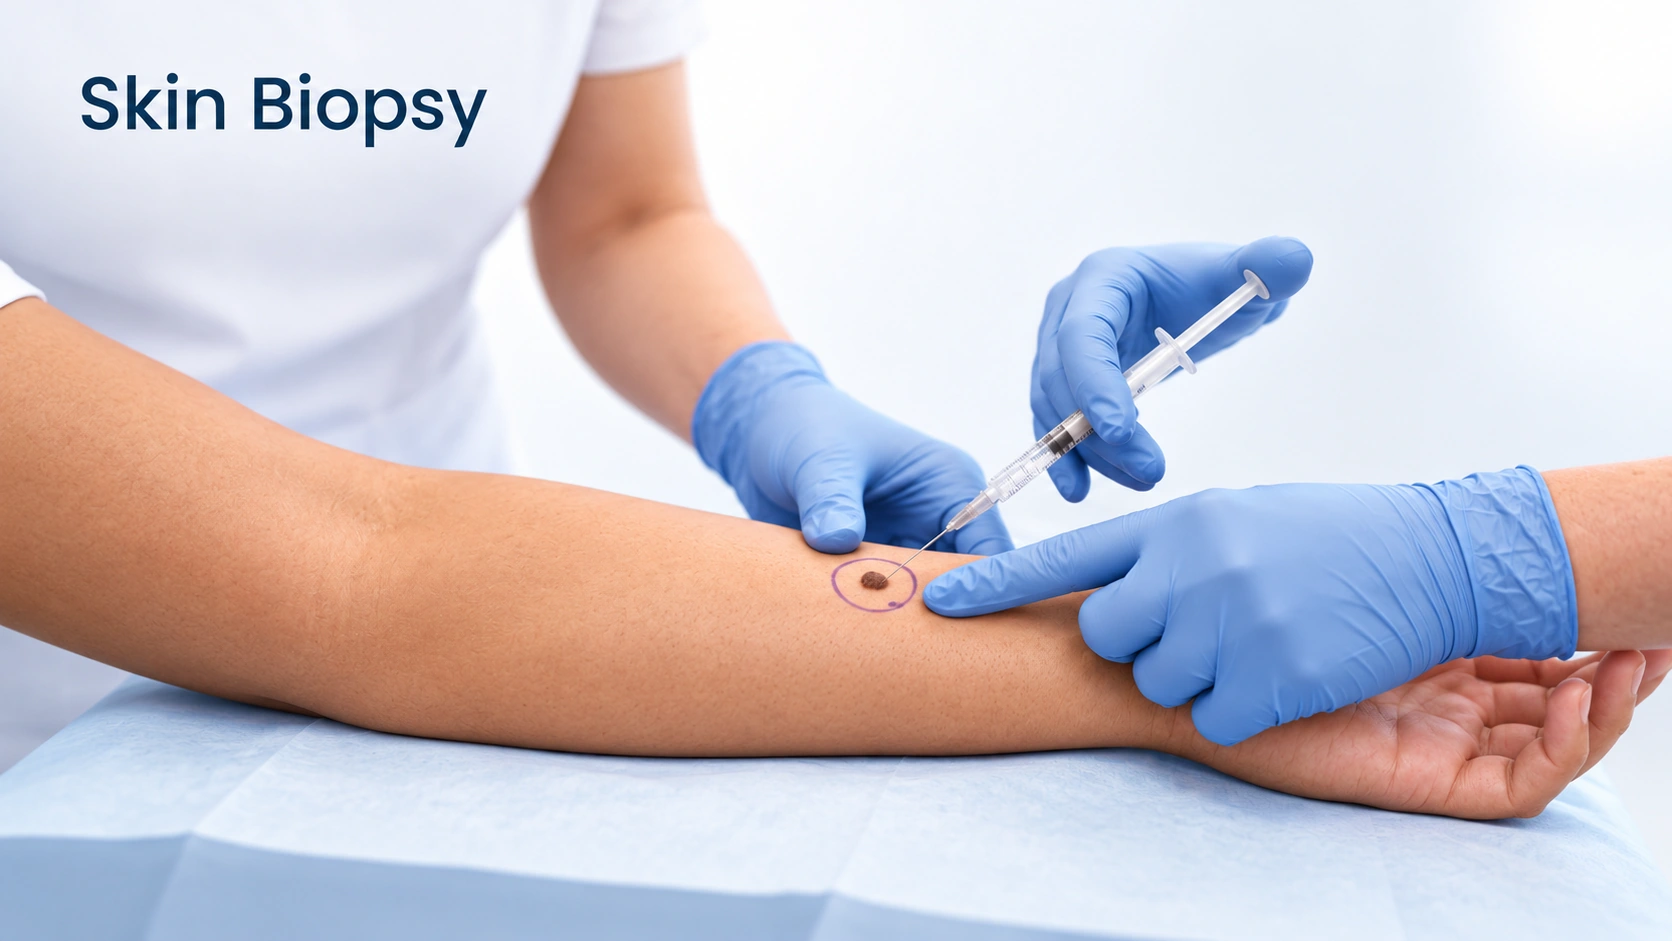
A small sample taken under local anesthetic, usually a shave or a punch, and read by a pathologist. It does two things: it confirms this is a basal cell carcinoma, and it names the subtype. The subtype is what decides which treatment is right, so this comes before the treatment conversation rather than after it.
Can help stubborn inflamed acne, but the protocols vary widely between clinics, the downtime is real, and the evidence is not strong enough to put it ahead of the options above.
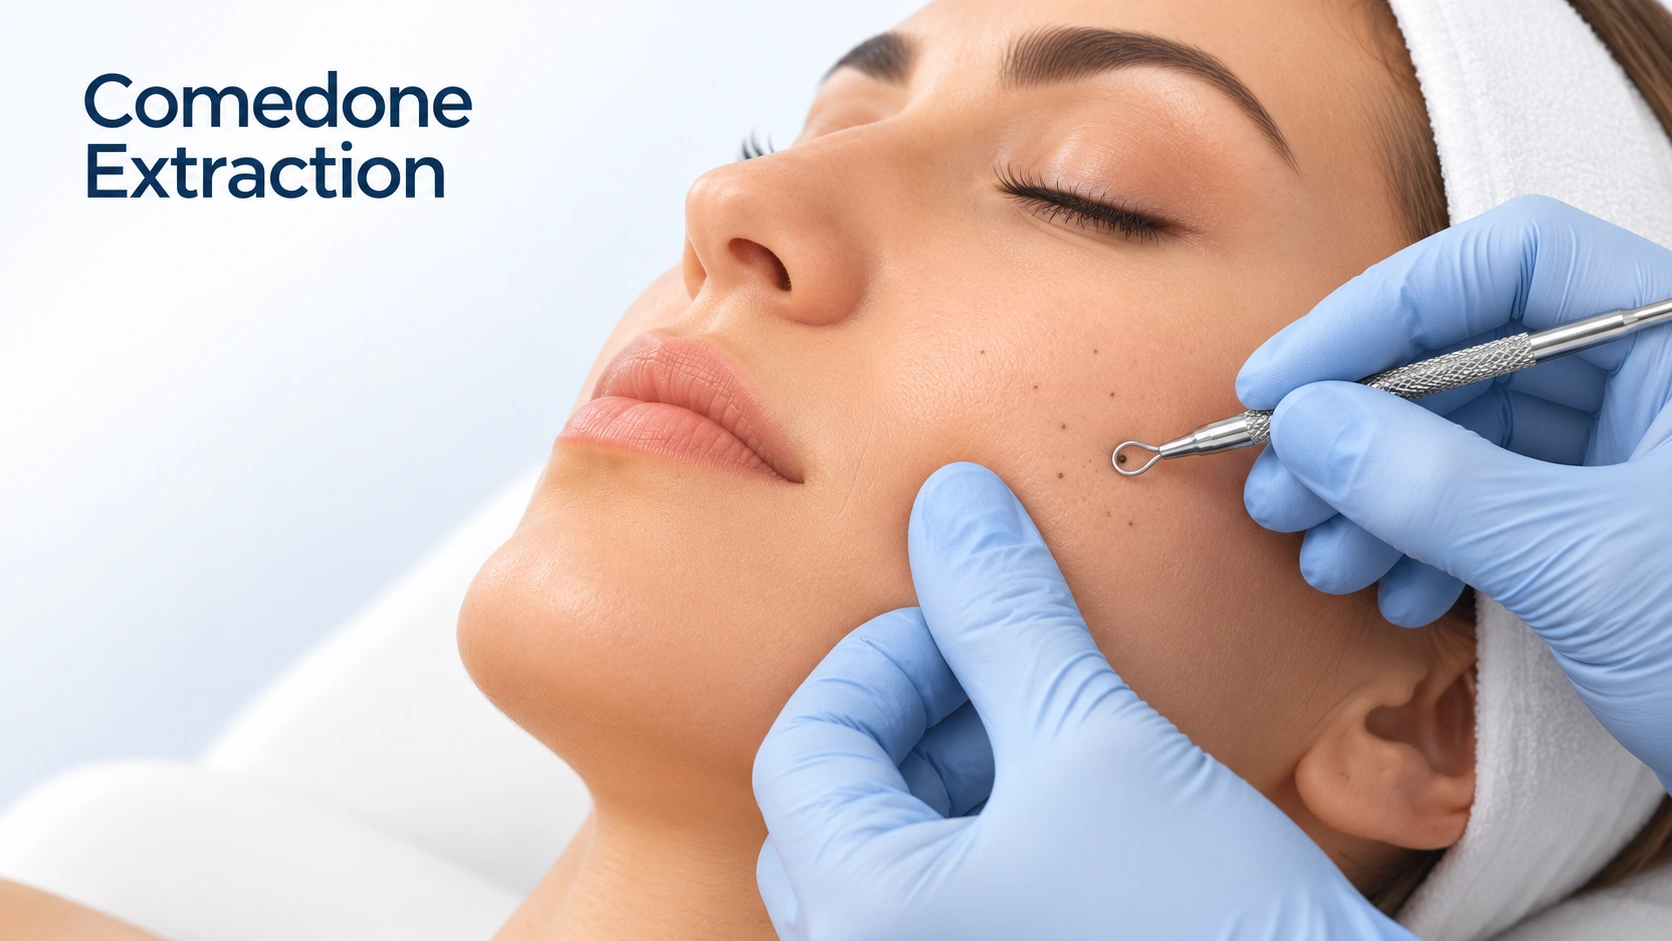
Clears blackheads that are already there, quickly and visibly. It does not stop new ones forming, so it is an add-on to a retinoid rather than a substitute for one.
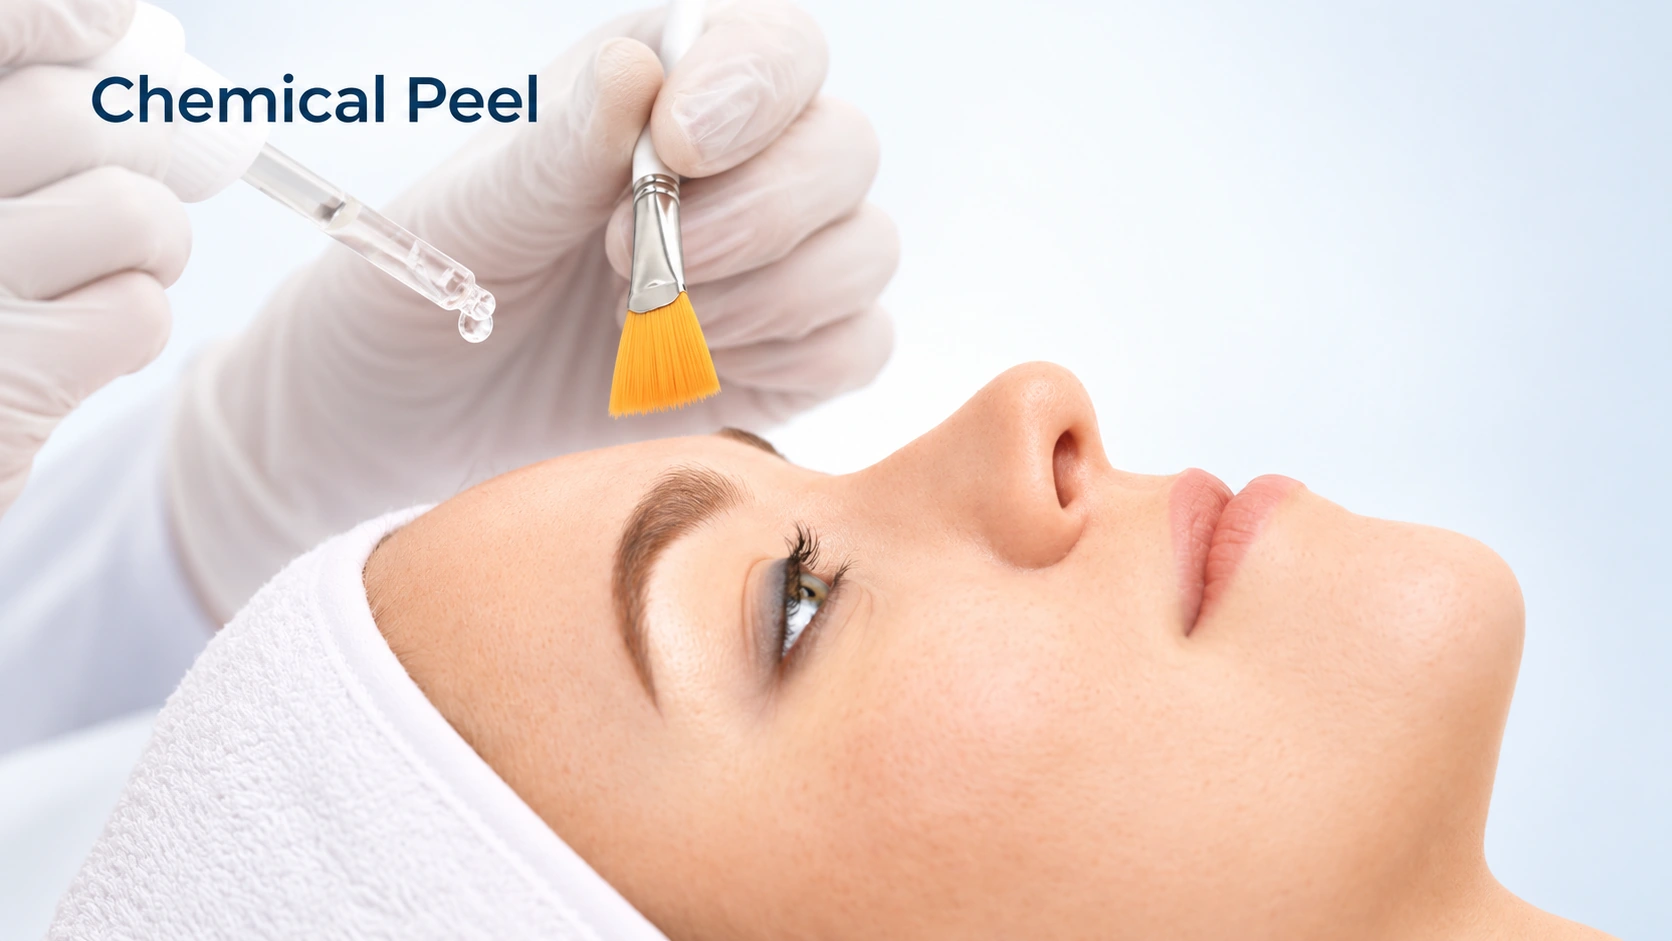
Modest benefit for clogged pores and a better one for the dark marks left behind. Needs repeat sessions, and the benefit fades if the daily treatment stops.
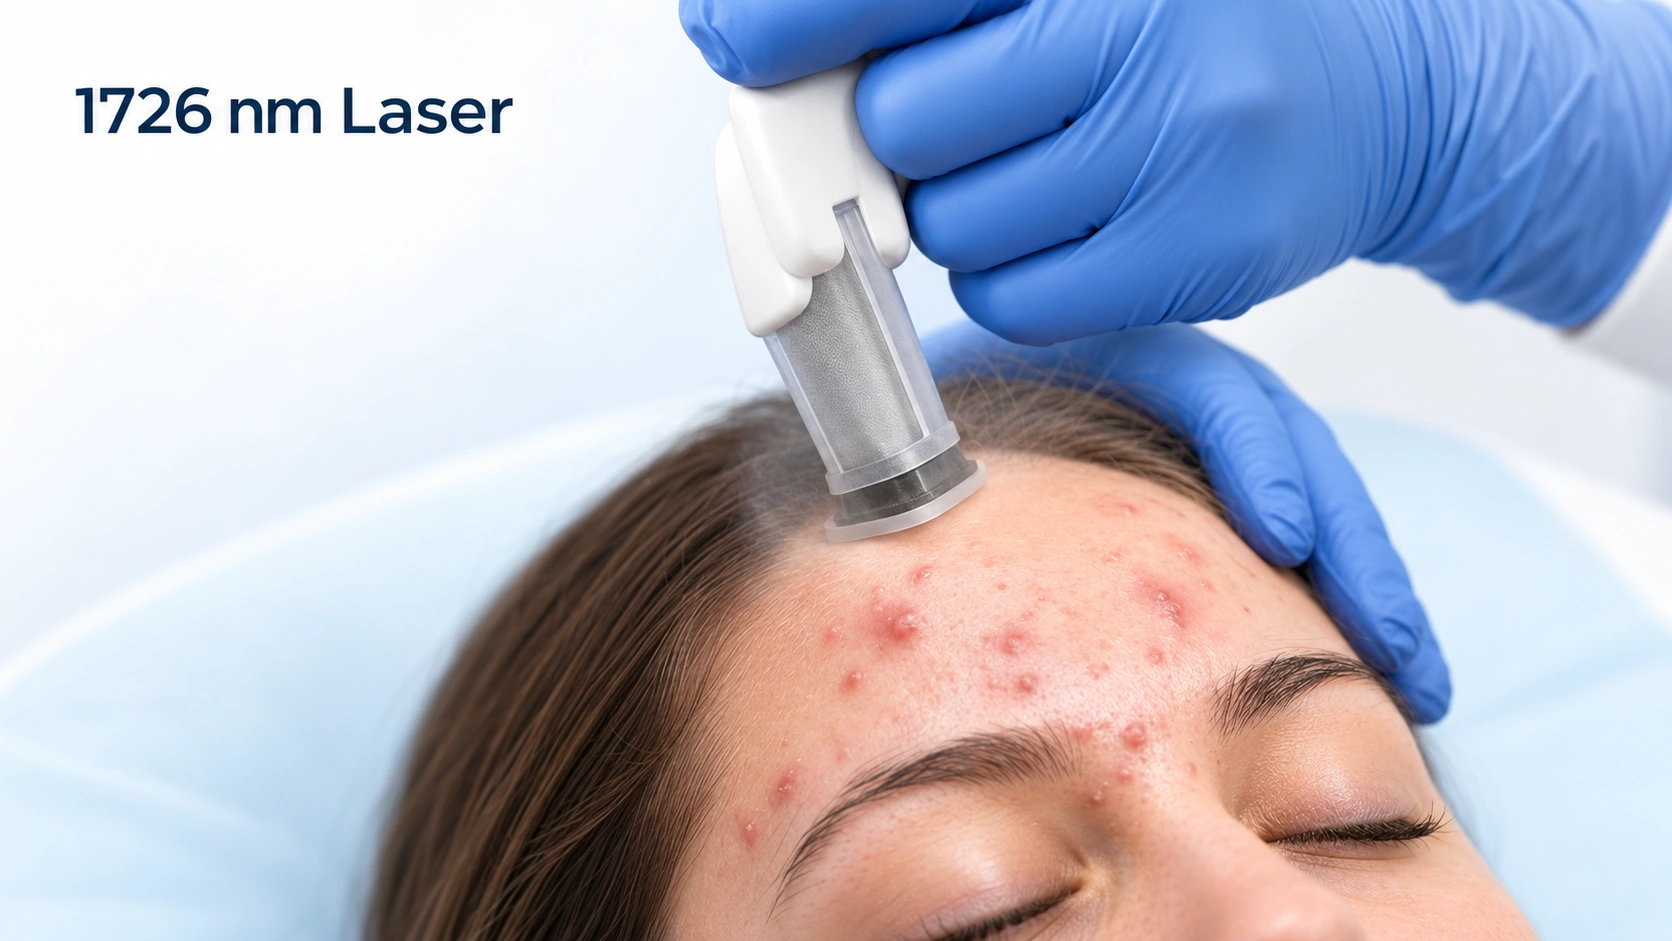
Heats the oil glands themselves, which is a genuinely different approach from everything else on this page. Trial results out to about six months are good, it works across skin tones, and it is expensive and rarely covered. Long-term data is still limited.
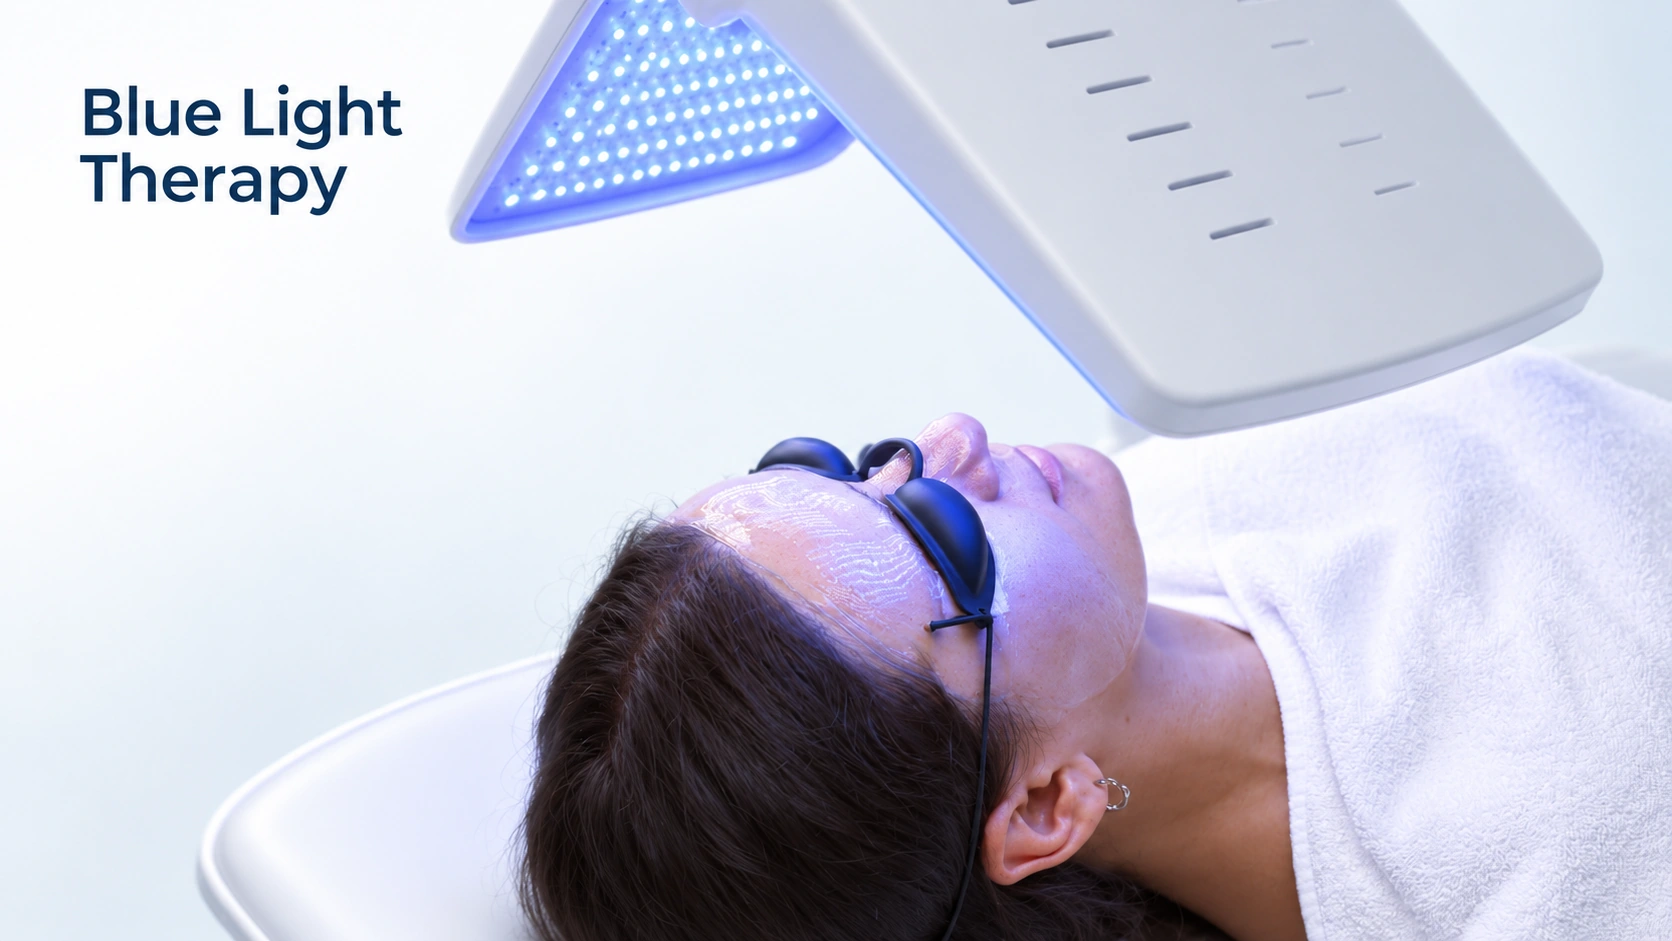
Blue light kills acne bacteria at the surface, so a course can quiet mild inflamed spots for a while. The effect fades within weeks of stopping, and it does nothing for blackheads or deep lumps. In-clinic courses cost far more than a topical that would do more.
Basal cell carcinoma is slow, which is why it gets lived with for too long. It grows in one place over months and years, and the heal-and-return cycle is what finally gets it noticed.
Acne is usually controlled rather than permanently cured. Treatment reduces new breakouts, but improvement takes time and maintenance may be needed. Deep or scarring acne deserves early assessment because existing scars may remain after the active spots settle.
The most useful clue there is
It scabs, bleeds when knocked, shaved over or towel-dried, appears to heal, then breaks down in the same place. People read that cycle as improvement.
It keeps invading nearby tissue
On the nose, eyelid, ear and lip it can reach cartilage and deeper structures, and the repair needed becomes far larger. Ulceration, bleeding and a persistent open area are late features. Some subtypes track along nerves, causing numbness or tingling. Spread to lymph nodes or other organs happens, but is genuinely rare.
Dark marks
Flat brown or violet patches left where a spot was. They are not scars and they do fade, but it commonly takes 6 - 12 months, and sun exposure makes them last longer. These WILL FADE with time.
Redness
Flat pink or red marks left where a spot was, most often on lighter skin. Also not scars. They usually settle on their own, though it can take several months. These WILL FADE with time.
Scars
Permanent dents, pits or raised bumps left where inflammation broke down the skin's structure. Once formed, they can only be improved by procedures. These WILL NOT FADE with time.
Depression and anxiety
Acne can affect self-esteem, confidence and mental health. The link is consistent, and it does not track with how severe the acne looks to anyone else - which is itself a reason to treat it.
Family conflict
This is very common. Acne visits involving a teenager and a parent can sometimes be challenging, particularly when there is ongoing conflict about acne care.
Social impact
People may avoid photos, dating, social situations or activities because of their skin.
Arrange assessment of a persistent pearly bump, ulcer or repeatedly bleeding sore. It usually grows locally and needs treatment rather than observation alone.
Seek help for painful deep spots, scarring, persistent breakouts, or an uncertain diagnosis. Earlier treatment can reduce the chance of more scars.
Do not assume eye symptoms are part of acne. They need their own assessment.
Rarely dangerous to your life, because it almost never spreads to other organs. It is a real risk to the tissue around it, it keeps growing, and it does not resolve, so the question is not whether to treat but how soon. Earlier means a smaller procedure.
Slowly, over months to years, which is why it gets left. The slowness is why early treatment works so well: a tumor caught at a few millimeters on the nose is a short procedure, and the same tumor two years later can need reconstruction.
The tumor is removed in stages and the edges examined under a microscope at the same appointment, so complete removal is confirmed before closing. It spares the most normal tissue and is used mainly on the face and for higher-risk tumors. Ask why a method is recommended for yours.
Sometimes, for thin superficial tumors on the trunk or limbs, and only after a biopsy has shown that subtype. Cure rates are lower, treatment runs for weeks, and the skin gets red, sore and crusted while it works. A trade-off, not an easier option.
A large proportion do, usually within about five years and elsewhere on sun-damaged skin. Not a sign the first treatment failed - it is why skin checks and daily sun protection are part of the plan.
Yes. Every treatment leaves a mark, and how it looks depends on the site and the method. If you have ever had a thickened or keloid scar, say so beforehand; it can change the technique and closure. Silicone and sun protection help once it has healed.
For most people it settles by the mid-twenties. About one in six women still has it into her 30s and 40s, and it can return after pregnancy, after stopping the pill, or with any hormone shift. Controlled rather than cured.
Less than the internet suggests. The evidence points at high-glycemic diets - sugar and refined carbohydrate - and, less consistently, at skim milk. Chocolate and greasy food never held up, and no diet replaces treating the skin.
That is purging. Retinoids speed up clogs already forming under the surface, so weeks of spots arrive at once. It peaks around weeks two to six and settles by week eight. Still worsening past 10 to 12 weeks is irritation, not purging.
No. Squeezing pushes the contents sideways into surrounding skin, turning a spot that would have gone in days into a mark that lasts months, or a scar that lasts forever. A large, painful lump can be injected in clinic instead, and settles in a day or two.
Sometimes, but never alone and never for long. They go alongside benzoyl peroxide or a retinoid, usually for three to four months, then stop while the topical carries on. Alone or indefinitely, they stop working and drive resistance.
Almost all acne is hormonal - hormones drive oil production. The label only matters if it changes treatment: deep spots along the jawline and lower face in an adult woman, flaring before periods, usually respond better to hormonal treatment than to antibiotics.
Sources