Surgical Excision
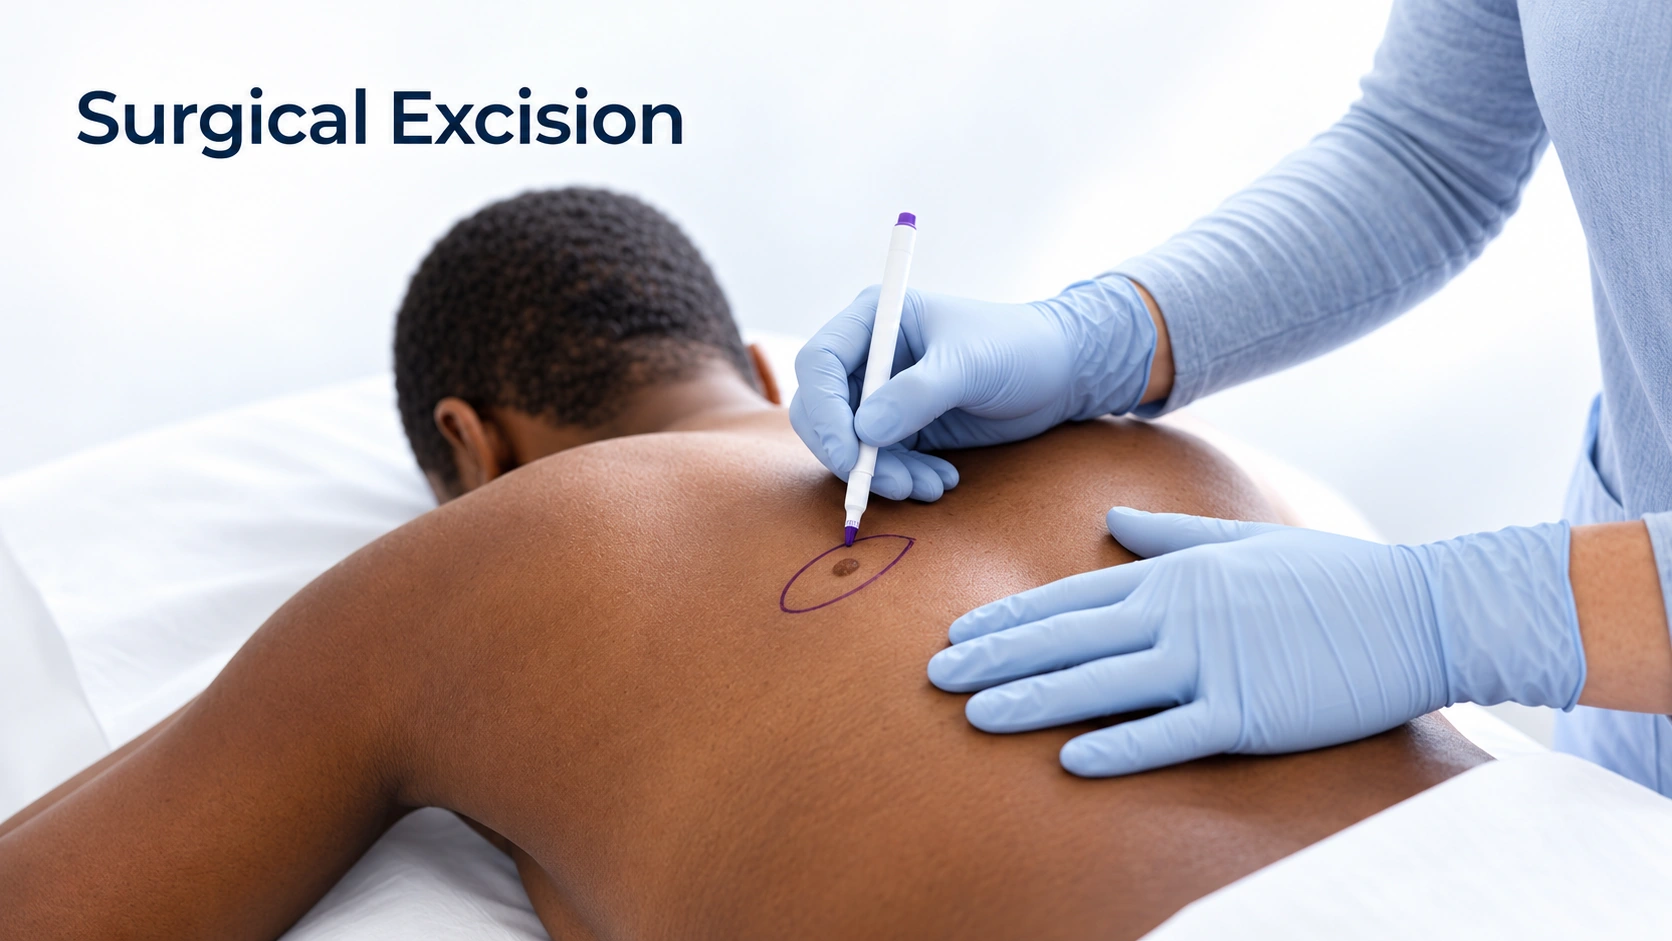
The growth is cut out along with a measured border of normal-looking skin, and the wound is stitched closed. The whole piece goes to a laboratory and the result comes back in about a week. The scar is a line, and it is longer than the spot was.
Key facts
Treats
Selected cancers or skin growths
Recovery
Stitches for about 1–2 weeks
Treatment plan
One procedure, plus follow-up
Typical cost
Medical coverage varies
What is it?
It removes a lesion surgically.
A planned incision removes the lesion and a rim of tissue.
It diagnoses or treats.
It provides tissue or removes a known lesion.
Margins depend on the diagnosis.
They should not be chosen from a generic chart.
Mohs is different.
Standard excision and Mohs assess tissue differently.
What it treats
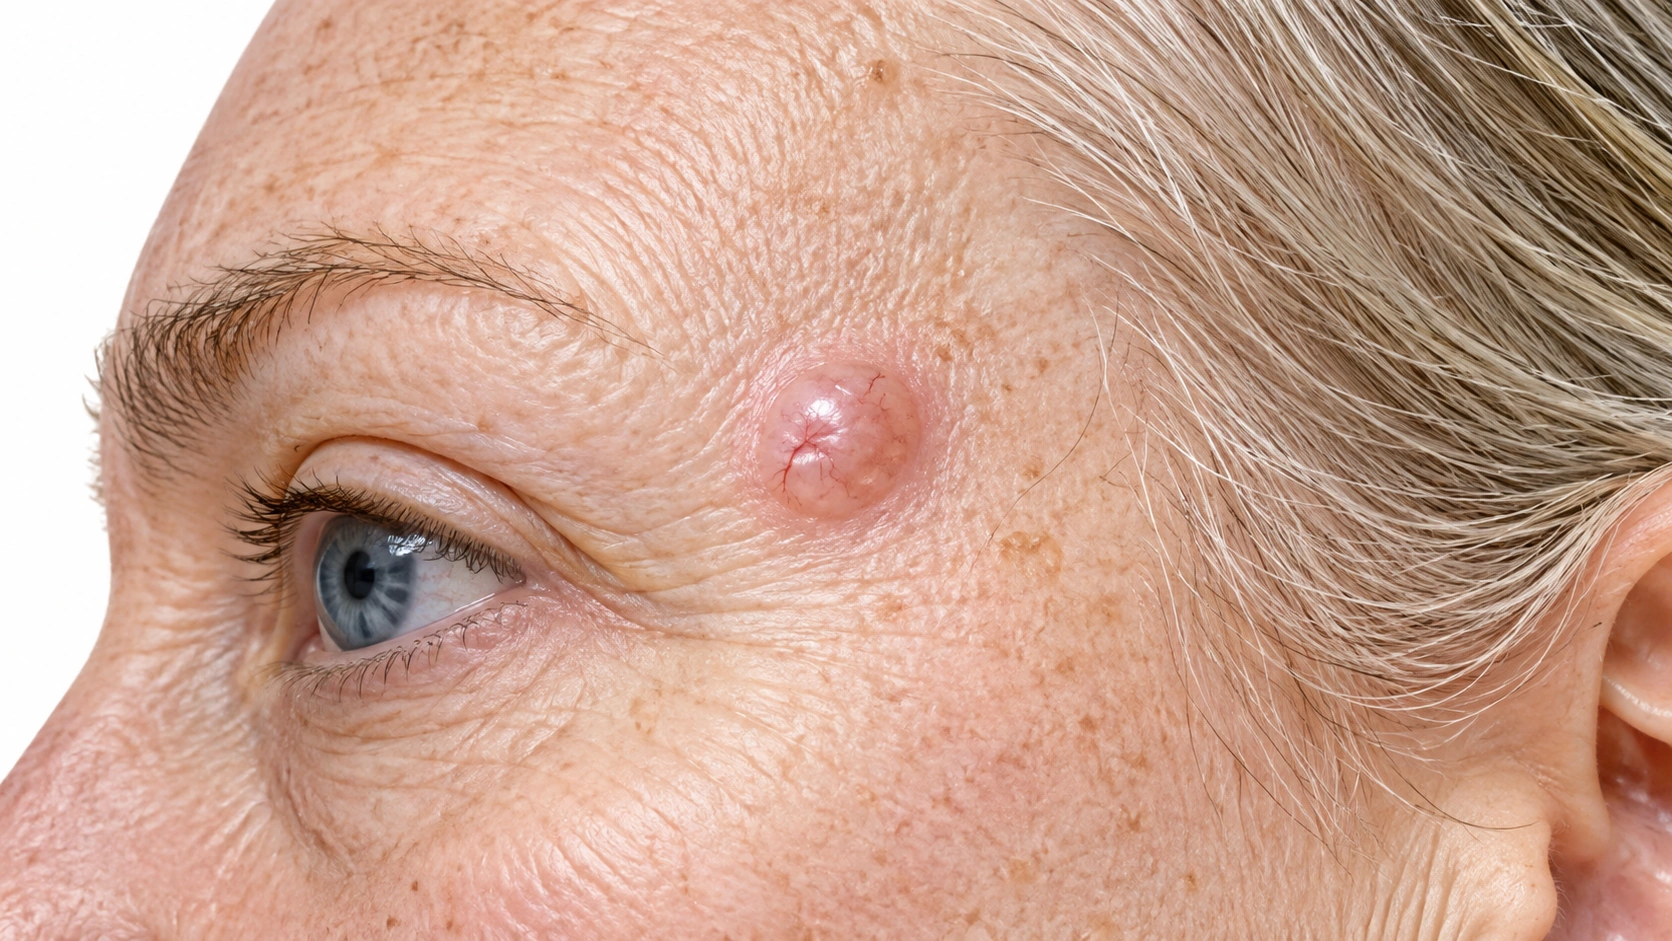
Basal Cell Carcinoma
High cure rates.
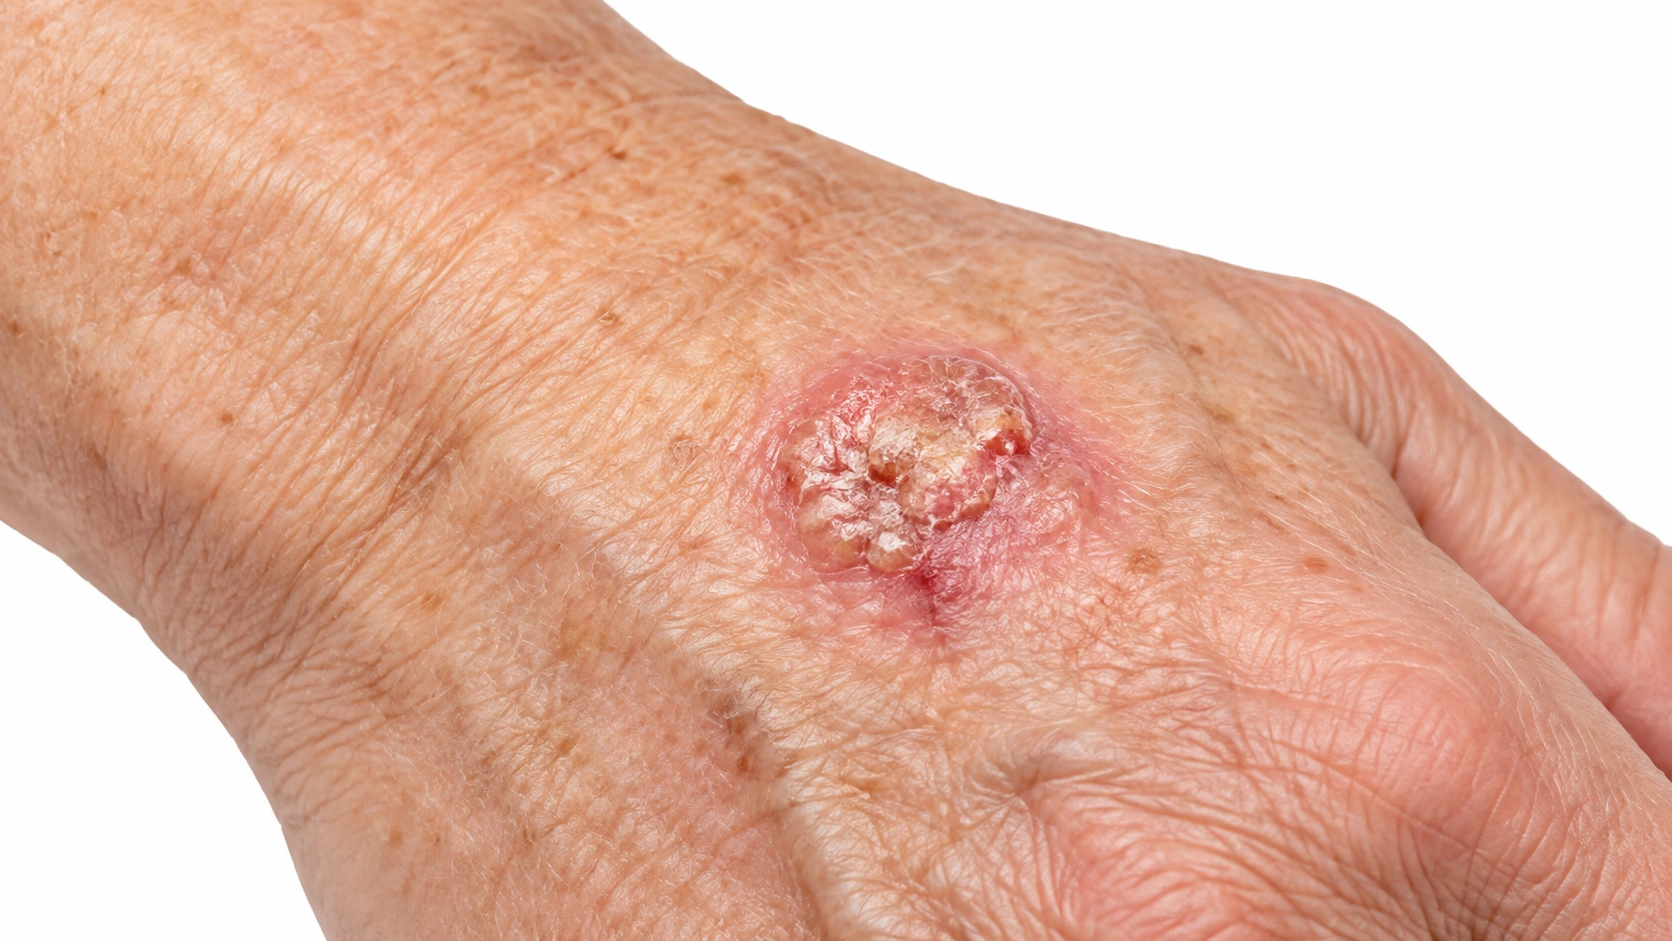
Squamous Cell Carcinoma
Removes the cancer with margins.
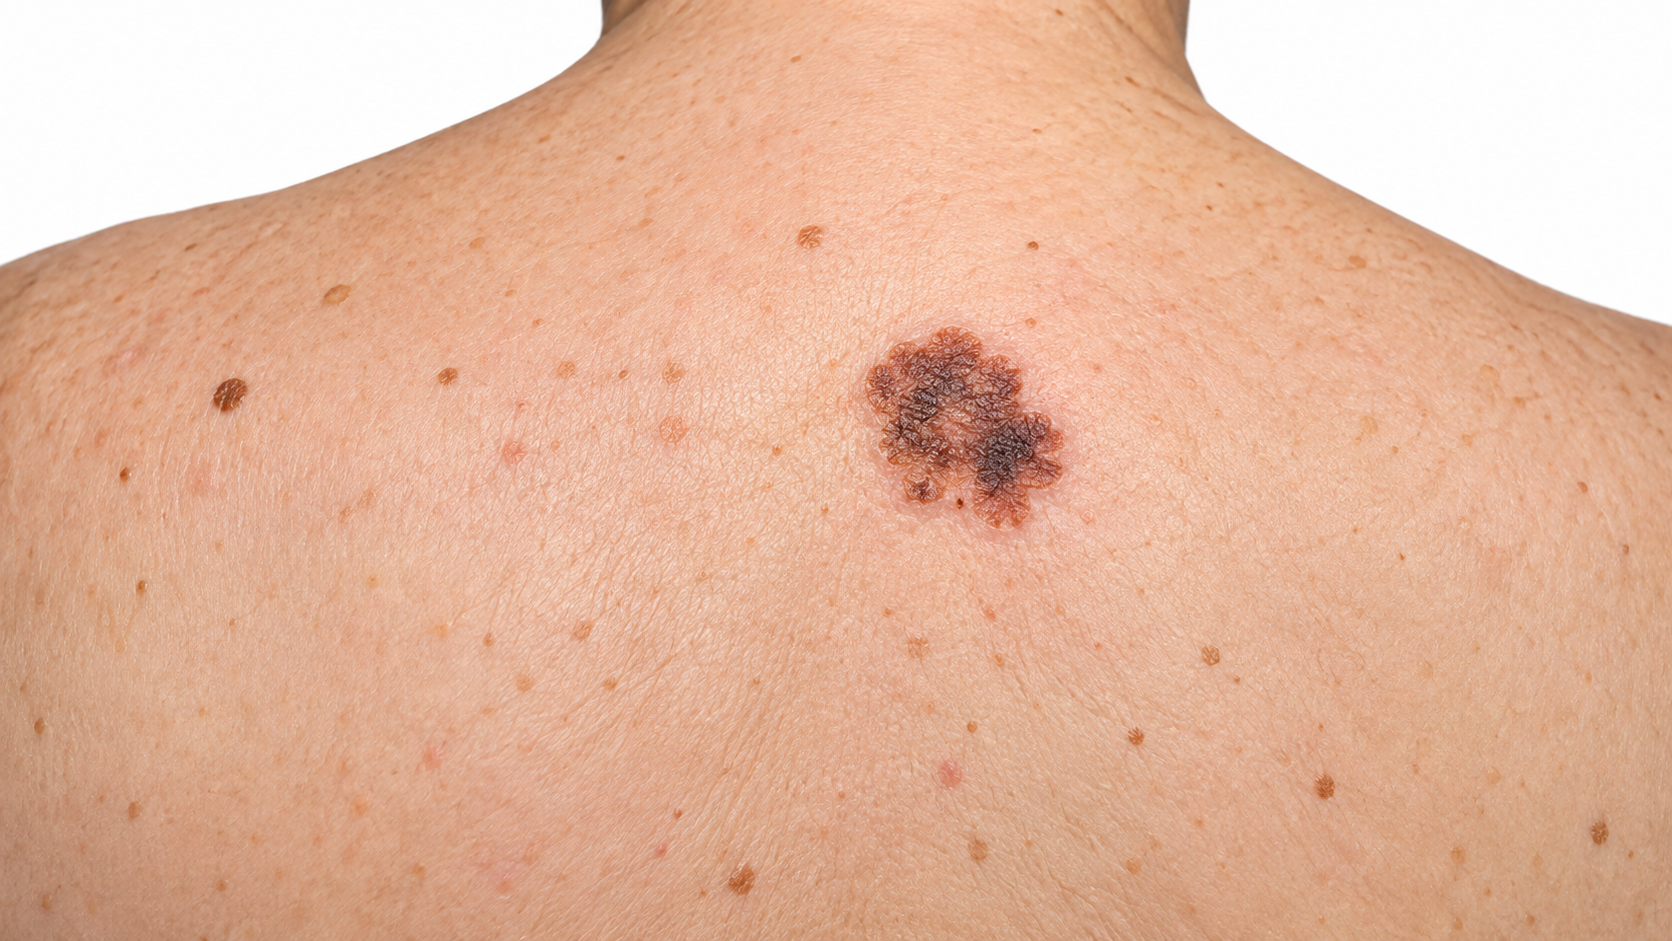
Melanoma
The main treatment.
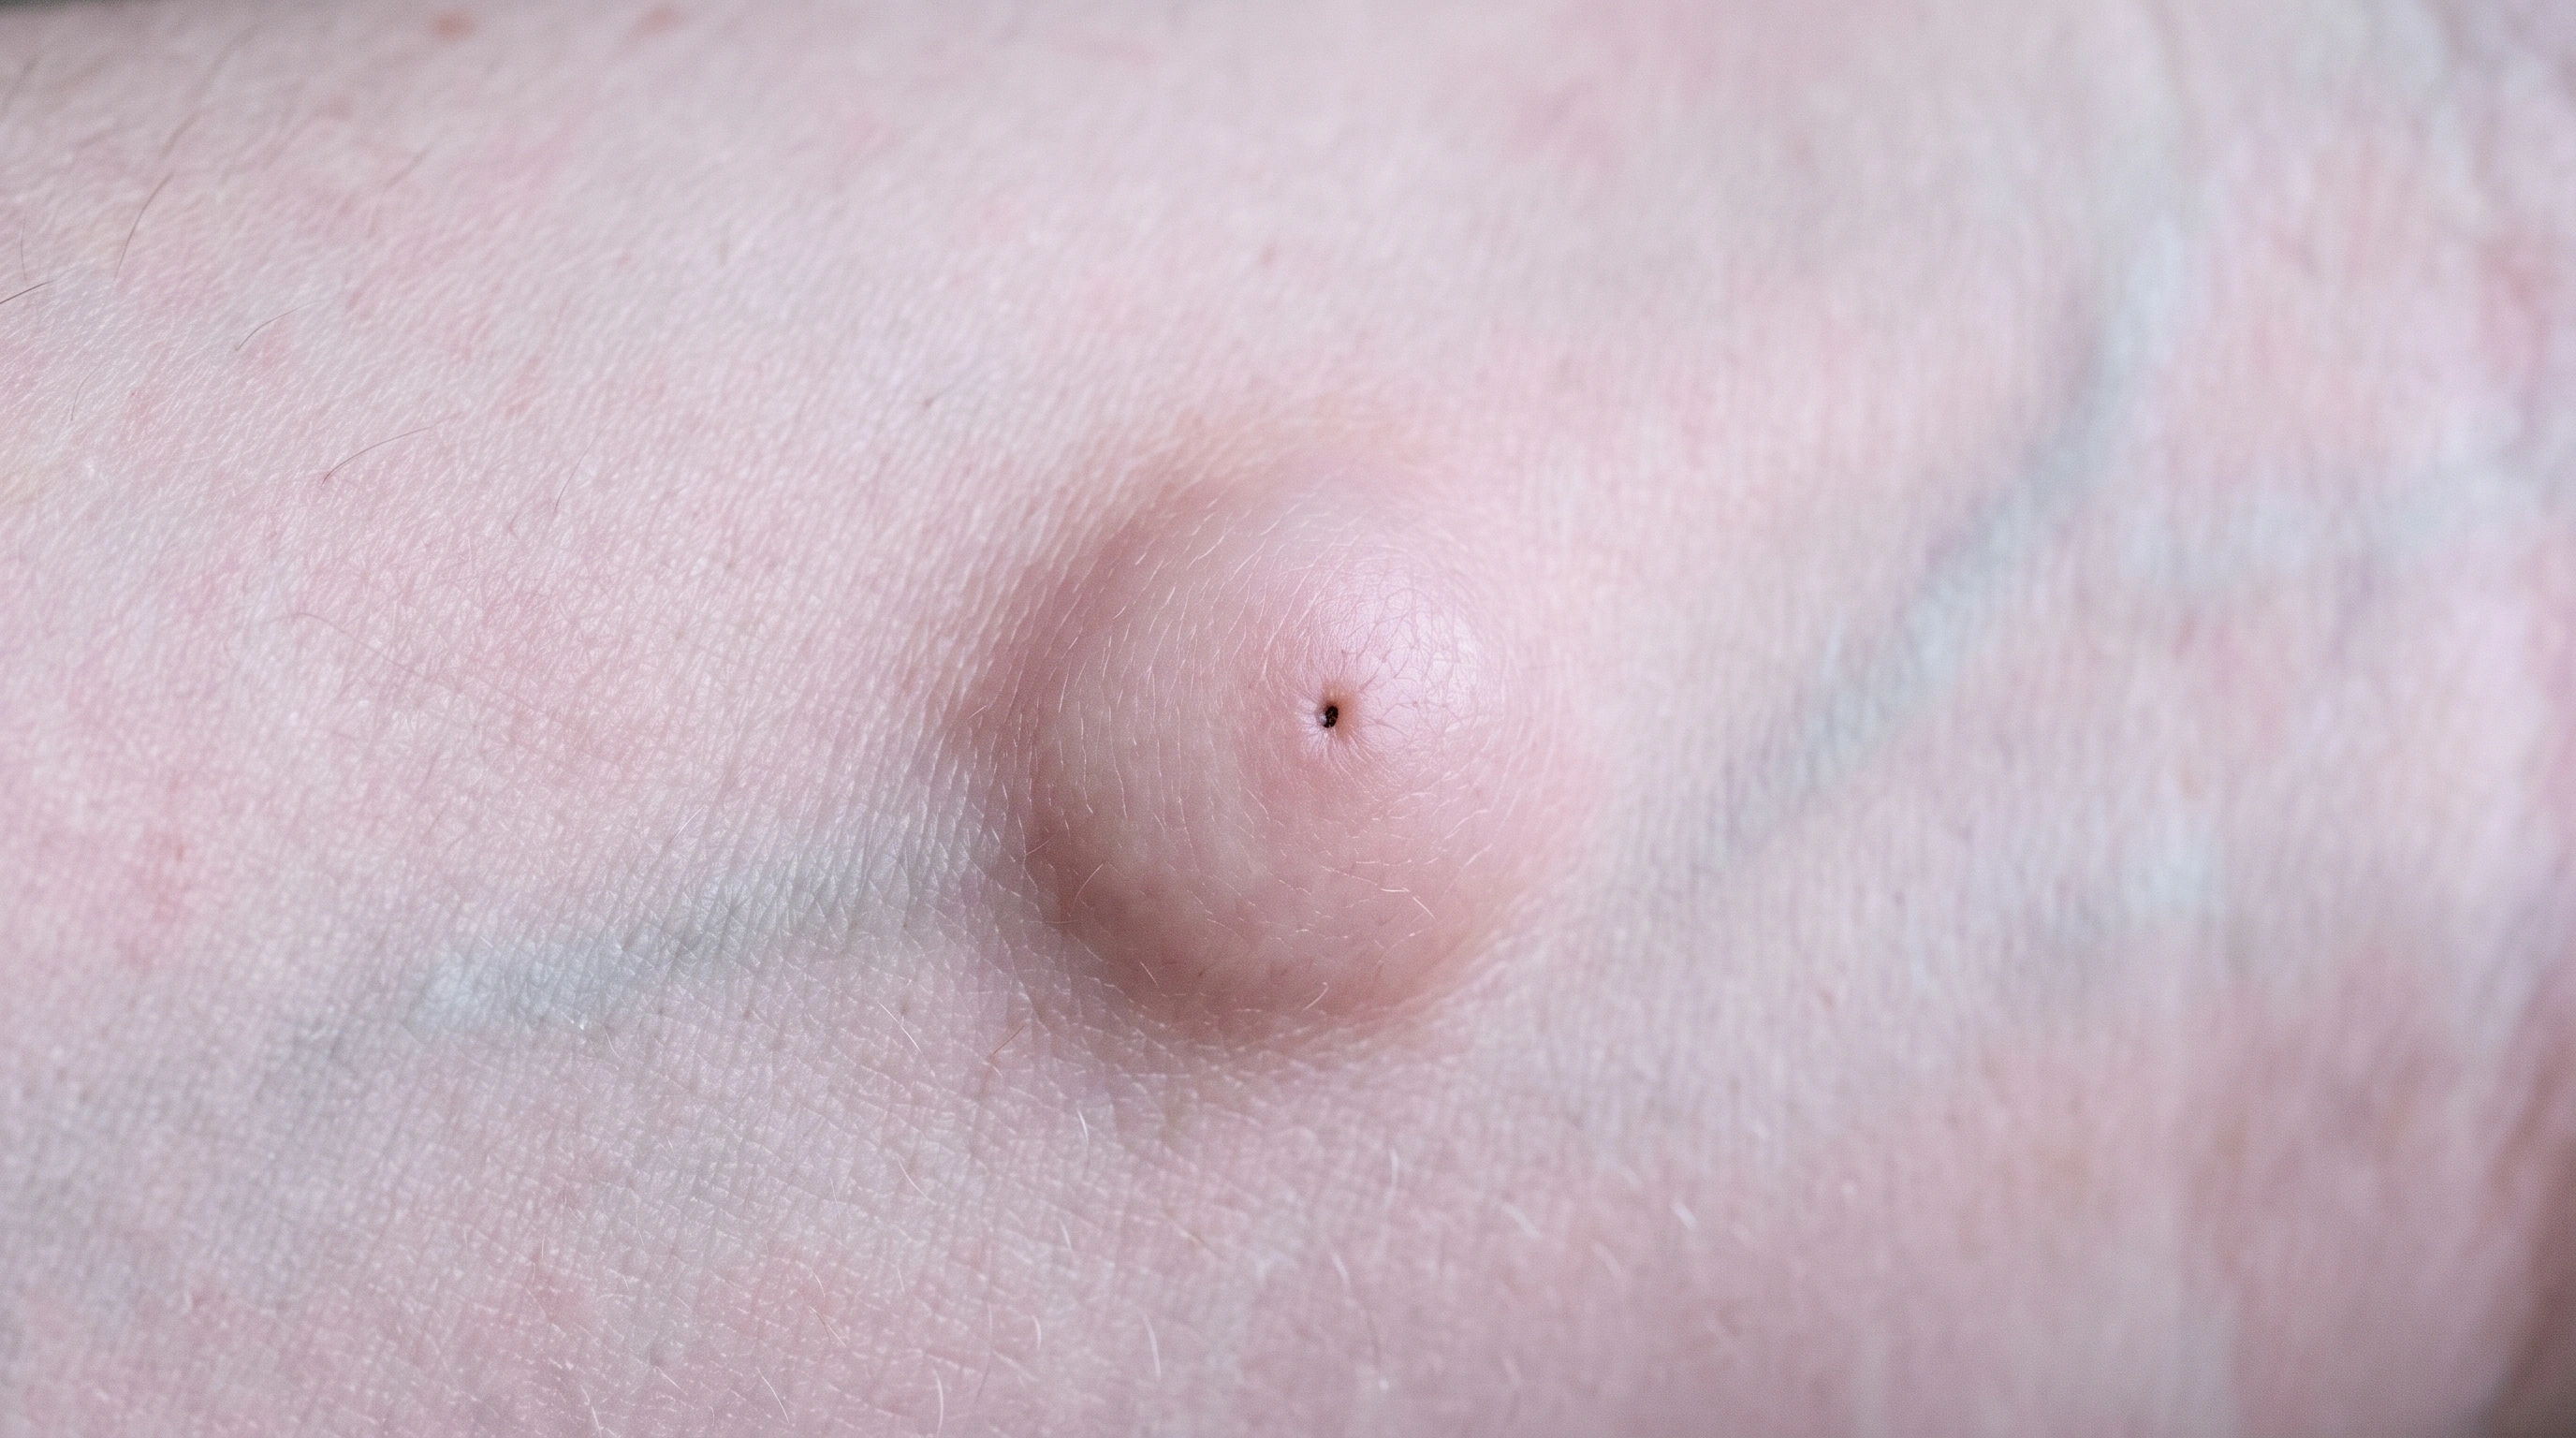
Epidermal Inclusion Cyst
Removes the sac.
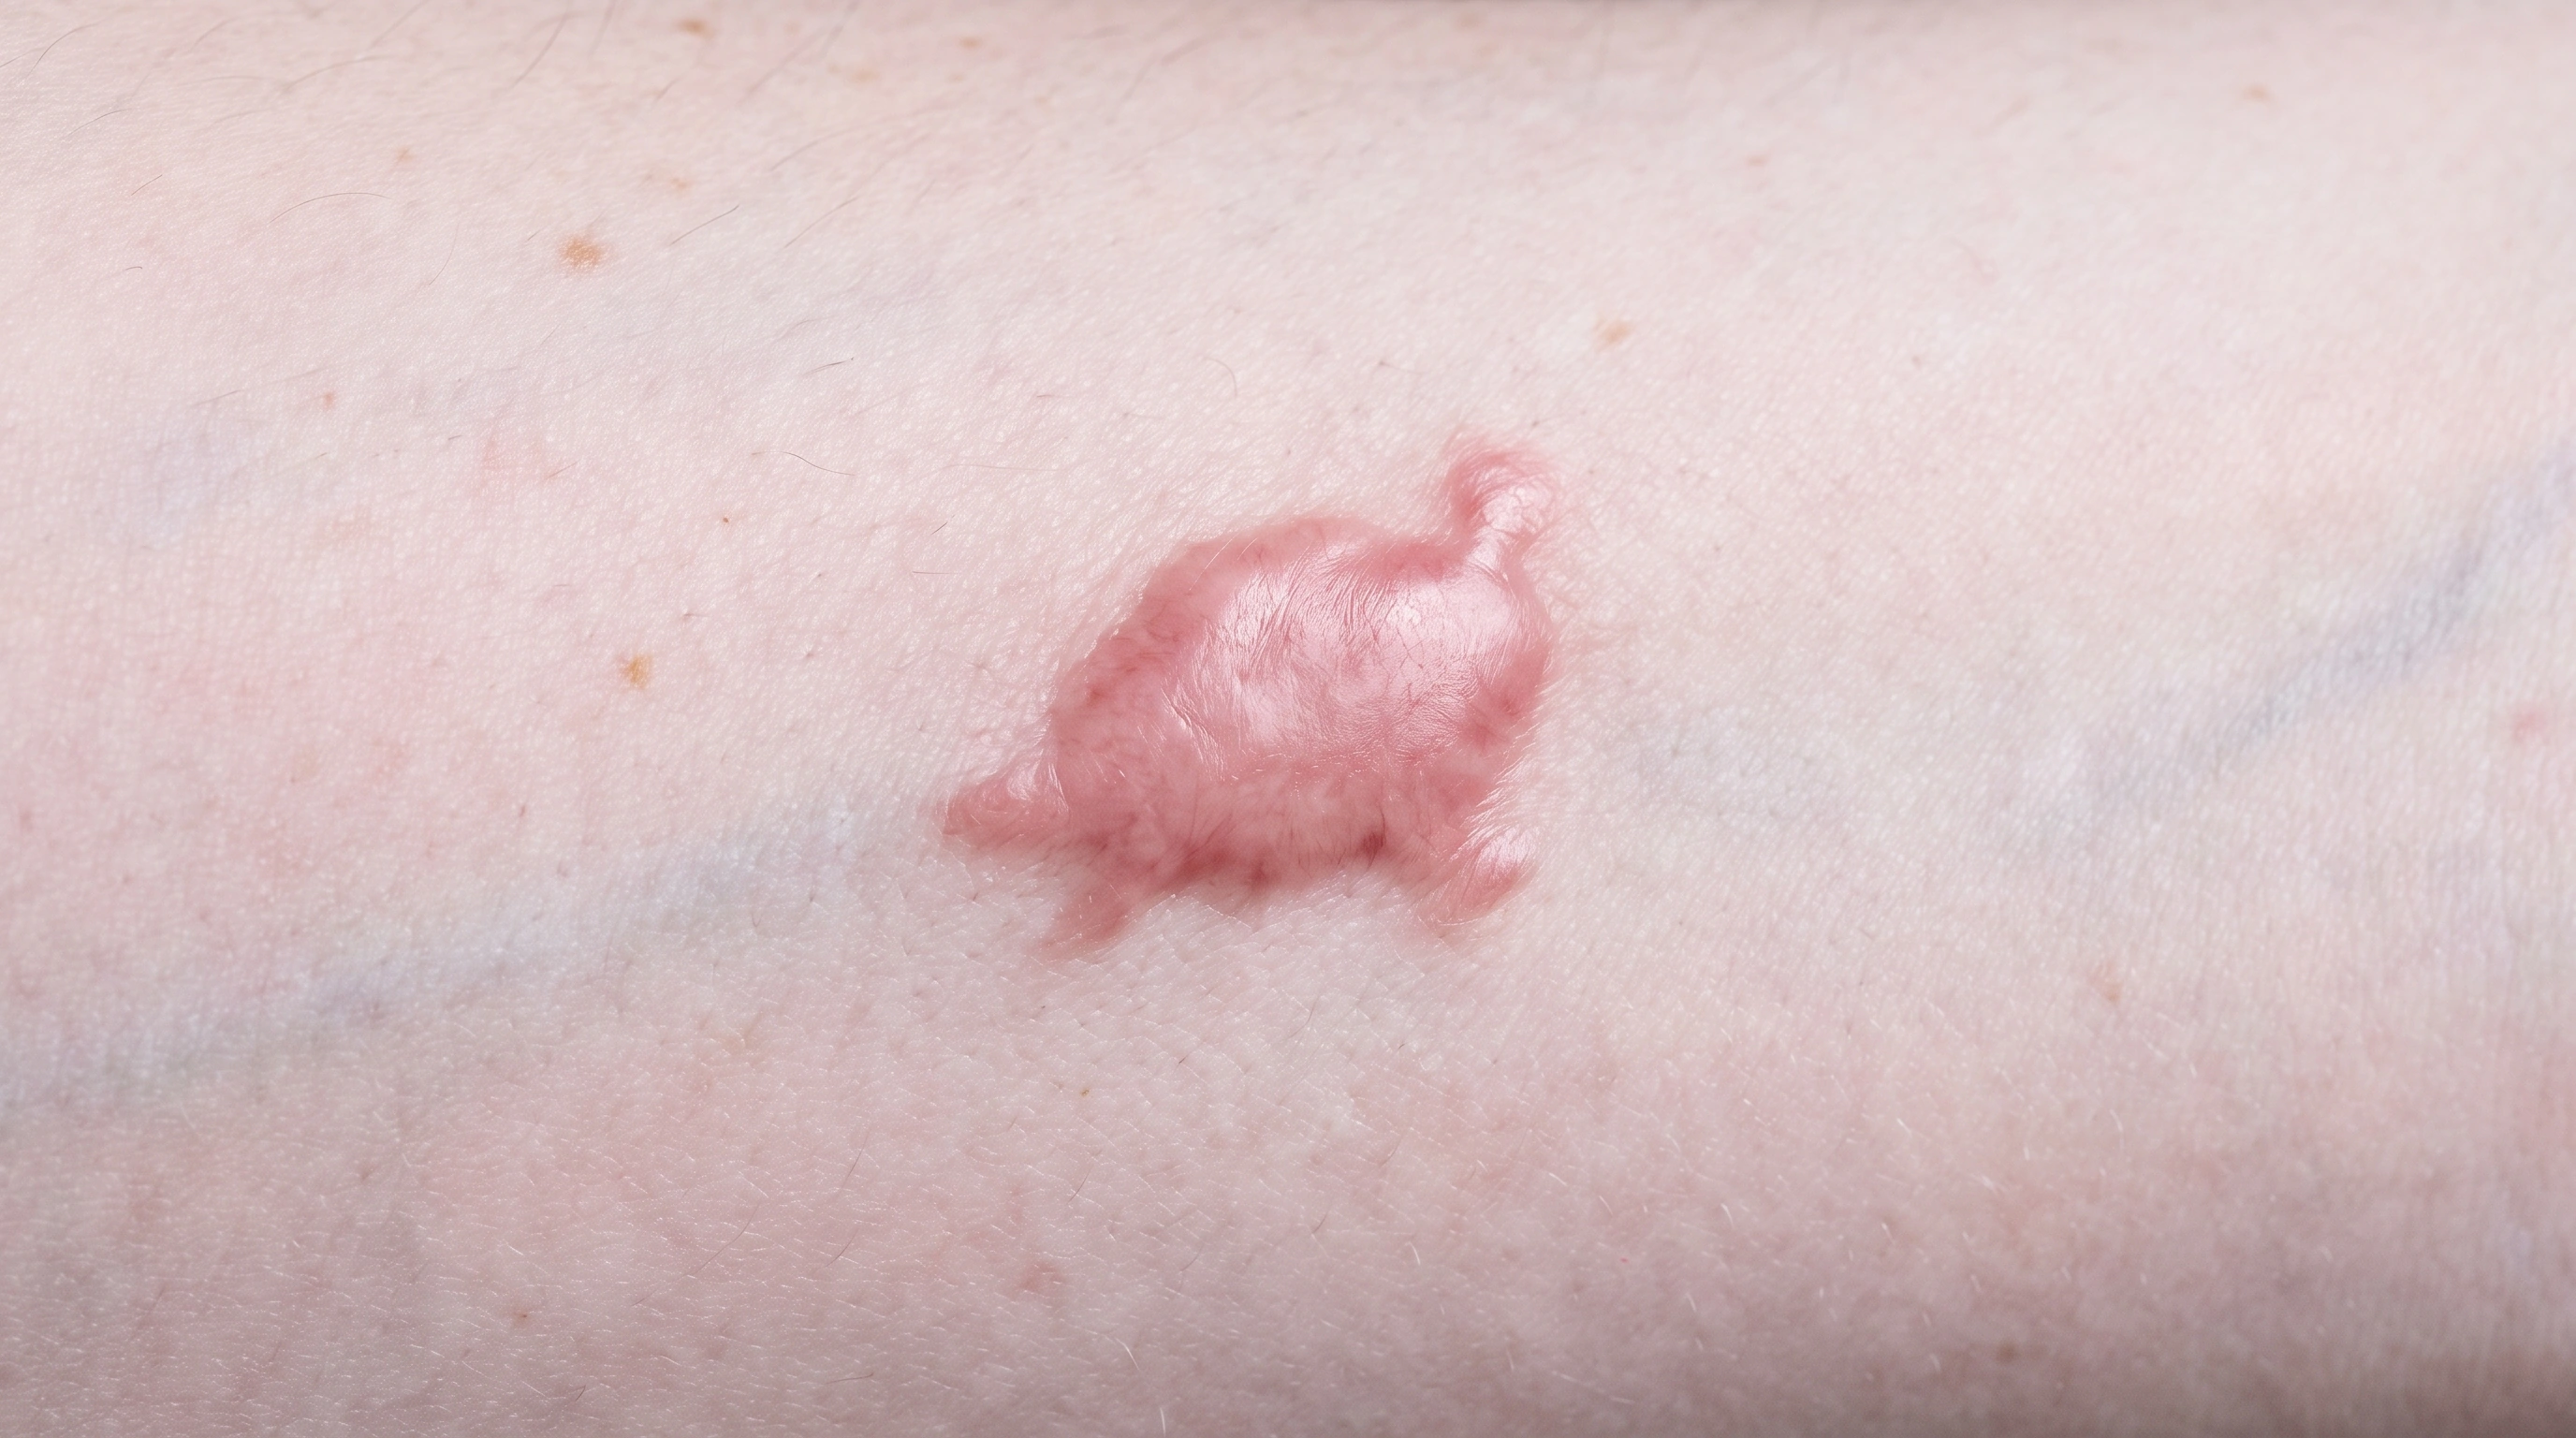
Keloids
Keloids often return larger alone.
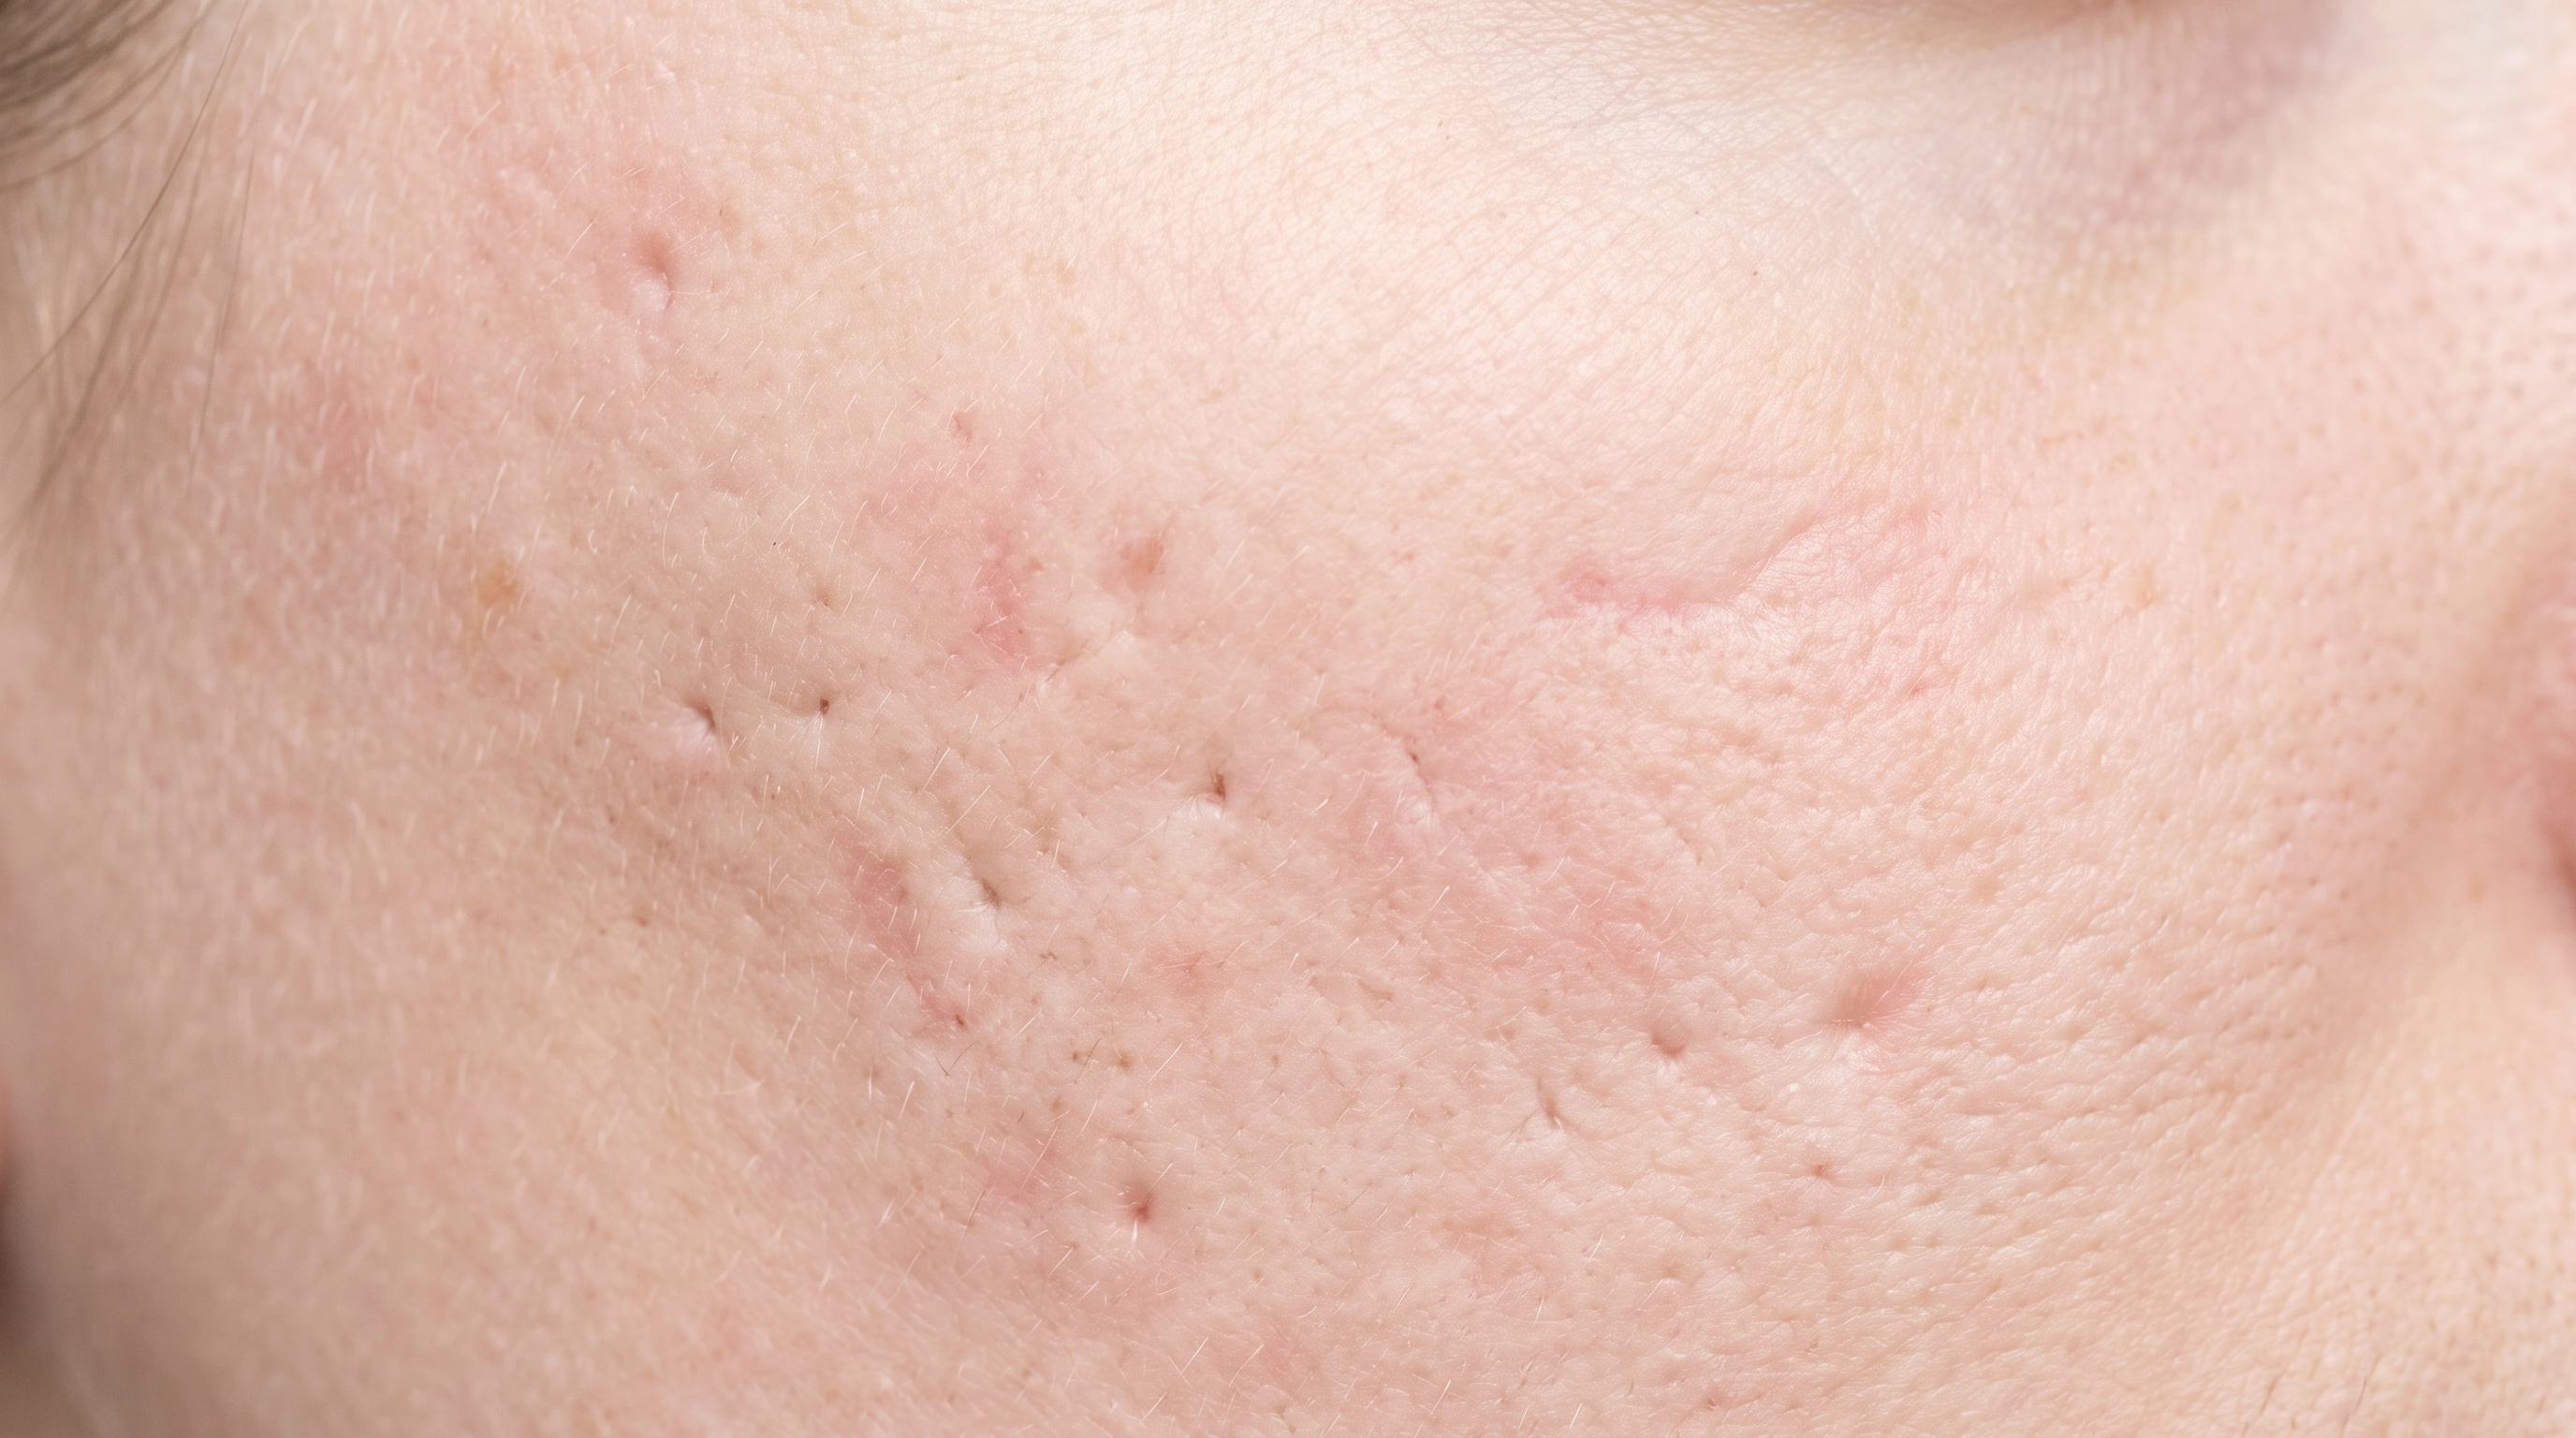
Acne Scarring
Punch excision is used for small scars instead.
Treatment areas
Surgical Excision
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Surgical Excision
The specific lesion, scar or affected patch determines the treatment site; there is no fixed body distribution.
Skin tones
Lighter skin
Low risk
A fine line scar.
Medium skin
Low risk
Scar fades over a year.
Deeper skin
Some risk
Raised or keloid scars possible, especially on chest, back and shoulders.
How it works
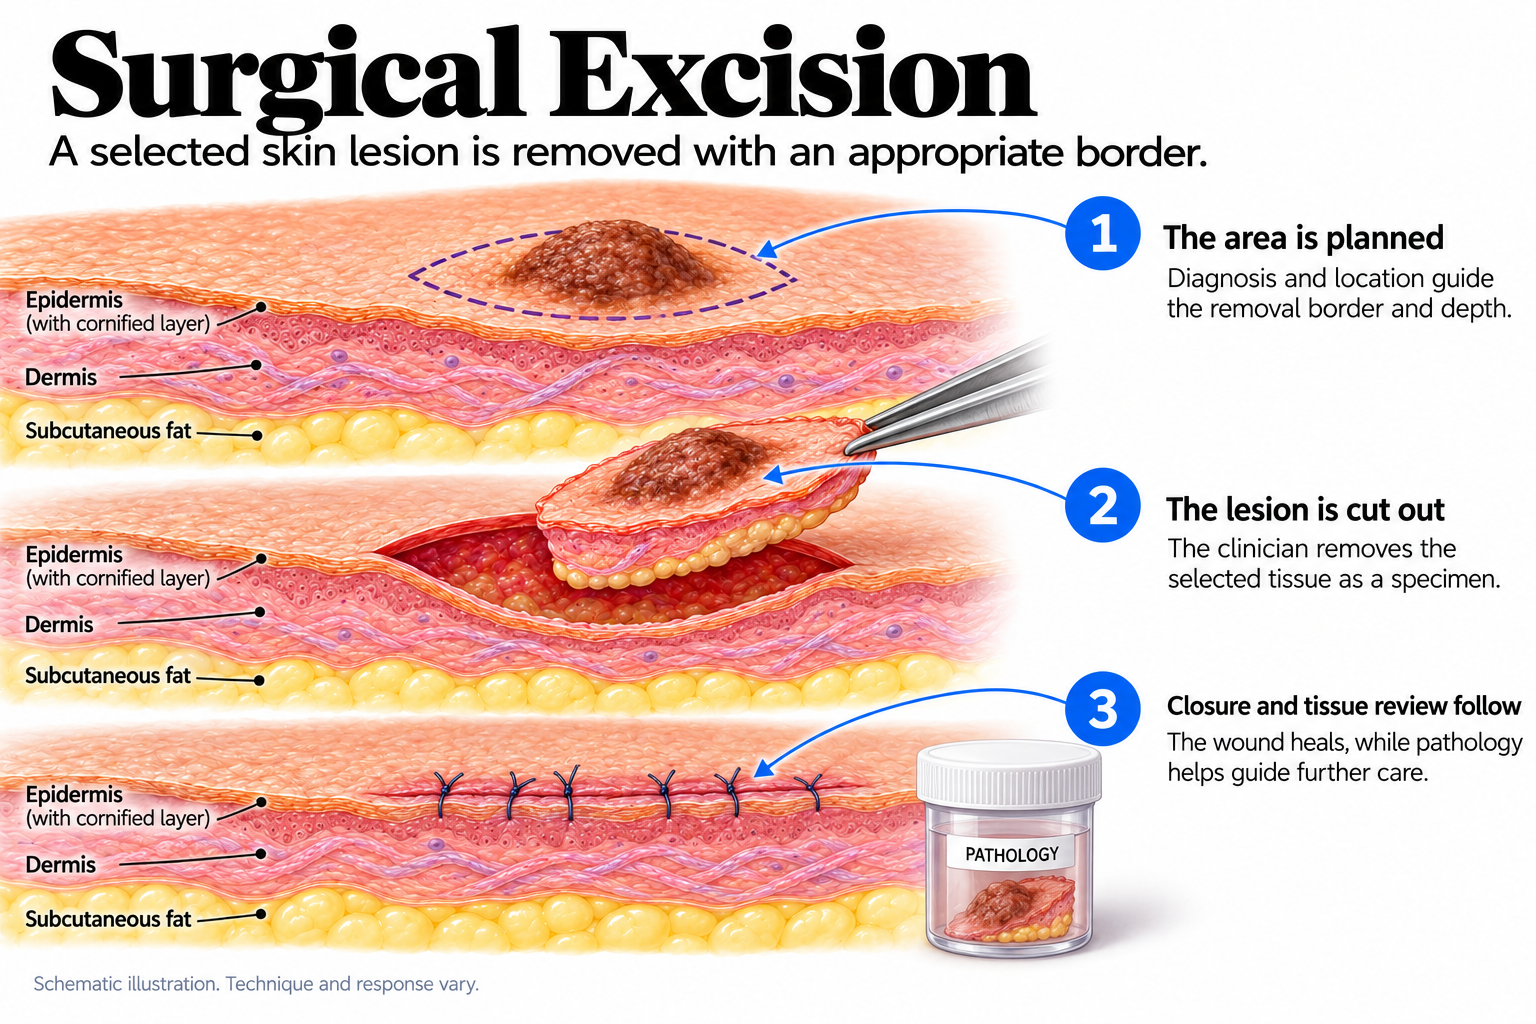
Diagram explanation
The area is planned: Diagnosis and location guide the removal border and depth. The lesion is cut out: The clinician removes the selected tissue as a specimen. Closure and tissue review follow: The wound heals, while pathology helps guide further care.
Schematic illustration. Technique and response vary. This explains a mechanism and does not specify treatment settings.
Before your treatment
The week before
Supplements and alcohol: Non-essential blood thinners such as fish oil, vitamin E and ginkgo are commonly stopped about a week before, and alcohol the night before.
Smoking and vaping: Stop for a week before and two weeks after if you can.
Day of treatment
Before you arrive
Eating and clothes: Eat normally and take your usual morning medicines.
Arrival & prep
The site is confirmed against the biopsy report and you point to it yourself.
Treatment
The surgery: The skin is cleaned and draped.
The surgery: The ellipse is cut out in one piece, bleeding points sealed, and the edges freed so they meet without tension. Closing is in layers — dissolving stitches deep, stitches on the surface. You feel pressure and tugging and hear instruments, but nothing sharp. Most take 20 to 45 minutes, and the site feels tight afterward rather than sore.
Before you leave
A dressing, written wound care, a stitch removal appointment, and a plan for how the pathology result reaches you.
After your treatment
Days 2–7
First week: Keep the dressing dry and in place for 24 to 48 hours, then start daily care — gentle wash, petrolatum, non-stick dressing.
Days 5 to 14: Stitches come out — face at 5 to 7 days, trunk and arms at 10 to 14, legs and back sometimes longer.
Weeks 2–4
From week 2: The scar is hardest, pinkest and most raised at around three to six weeks.
Time to results
Lab result in about a week
How long results last
Permanent
Risks
When to contact your provider
Bleeding: Press firmly and continuously for 15 minutes by the clock without lifting to check.
Bleeding: That stops nearly all of it.
Most excisions heal without incident. A visible scar is a certainty, not a risk. The rest below are uncommon.
A thick, raised or widening scar
A scar climbing rather than flattening after two months, or spreading sideways. Silicone, massage and steroid injections all work better before a scar is fully mature.
Numbness or a firm cord under the skin
Small sensory nerves are cut and usually recover over months, and a firm band along the line is usually healing collagen. Mention both at follow-up.
A stitch that surfaces months later
Buried dissolving stitches sometimes work their way out and cause a small red bump. Easily dealt with, and not infection.
A margin that was not clear
This comes from the report, not from how you feel, and it means a further procedure. Ask exactly what the report said rather than accepting that it was fine.
A pucker at one end of the line
A small fold of skin at the tip, sometimes called a dog ear. Many settle on their own over several months; the rest are simple to correct.
Cost
Typical cost
Usually covered when medically needed
Pricing
An excision costs more than a scrape-and-burn and less than Mohs surgery.
Insurance
In the US the surgical charge is priced by the size of the excision and the body site, with a separate charge for a more complex layered closure.
Alternatives
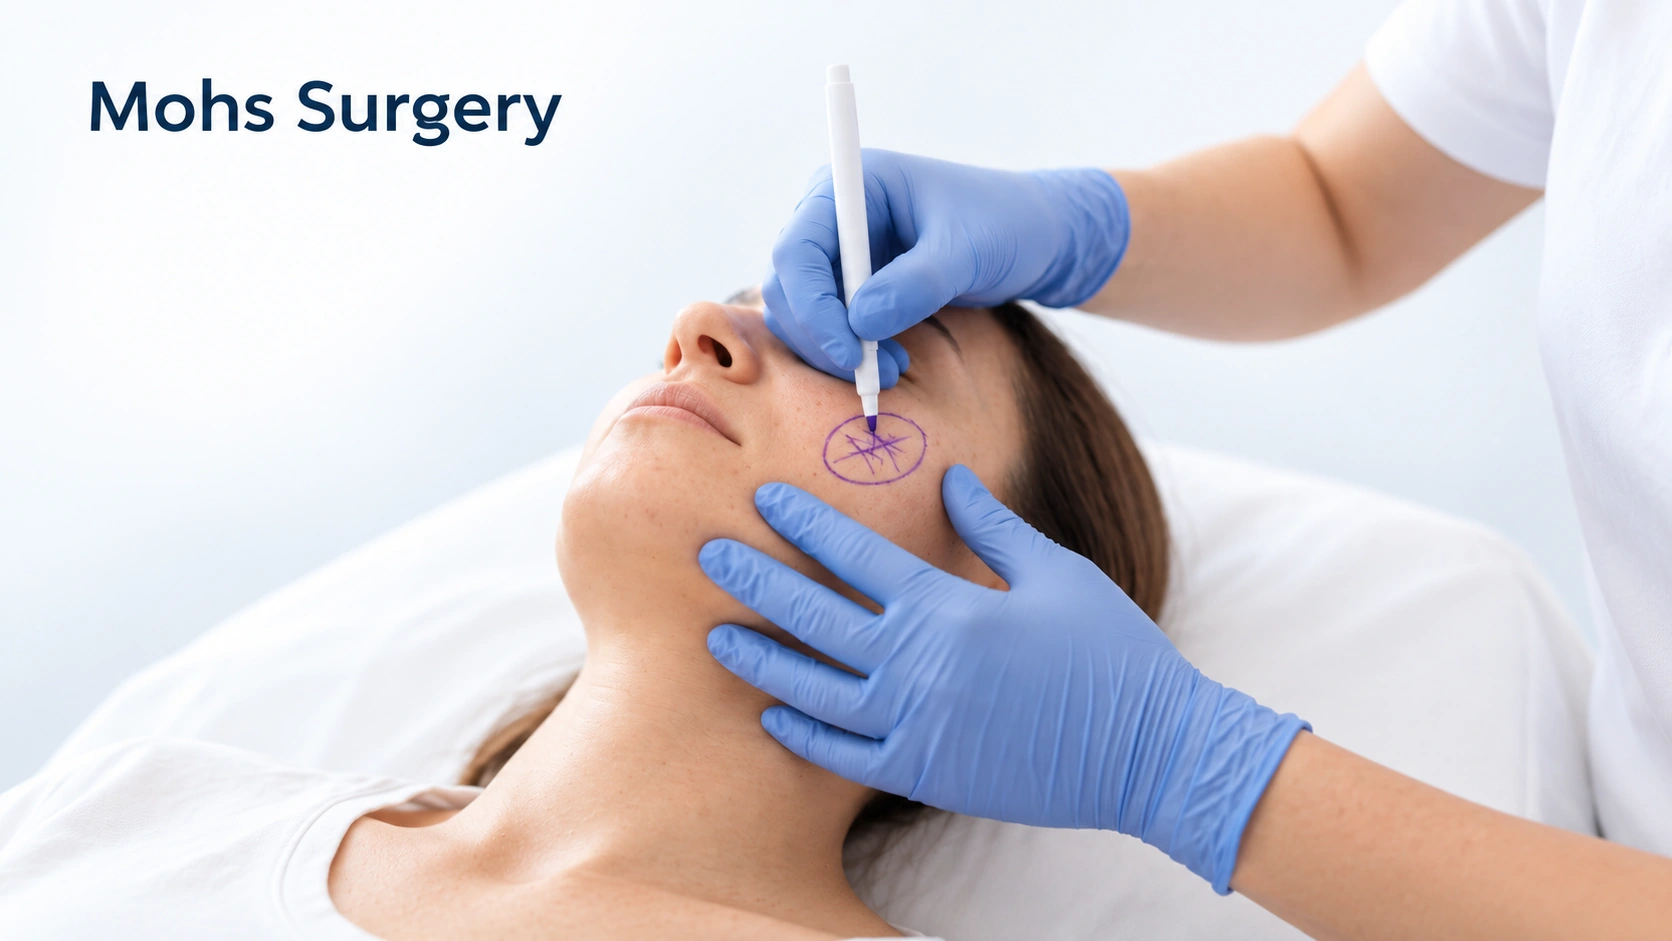
Mohs surgery
The highest cure rate available. Commonly quoted around 99 percent at 5 years for a previously untreated basal cell carcinoma, against around 95 percent for an excision. It examines the entire margin during the appointment and removes the least normal skin. The trades are a four-to-eight-hour day, a much higher cost, and more process than a small low-risk trunk tumor needs.

Electrodesiccation and curettage
For low-risk tumors only. Quicker, cheaper, no stitches, and no activity restriction. The trades are no margin check at all, an open wound for three to six weeks, and a round pale scar rather than a line.
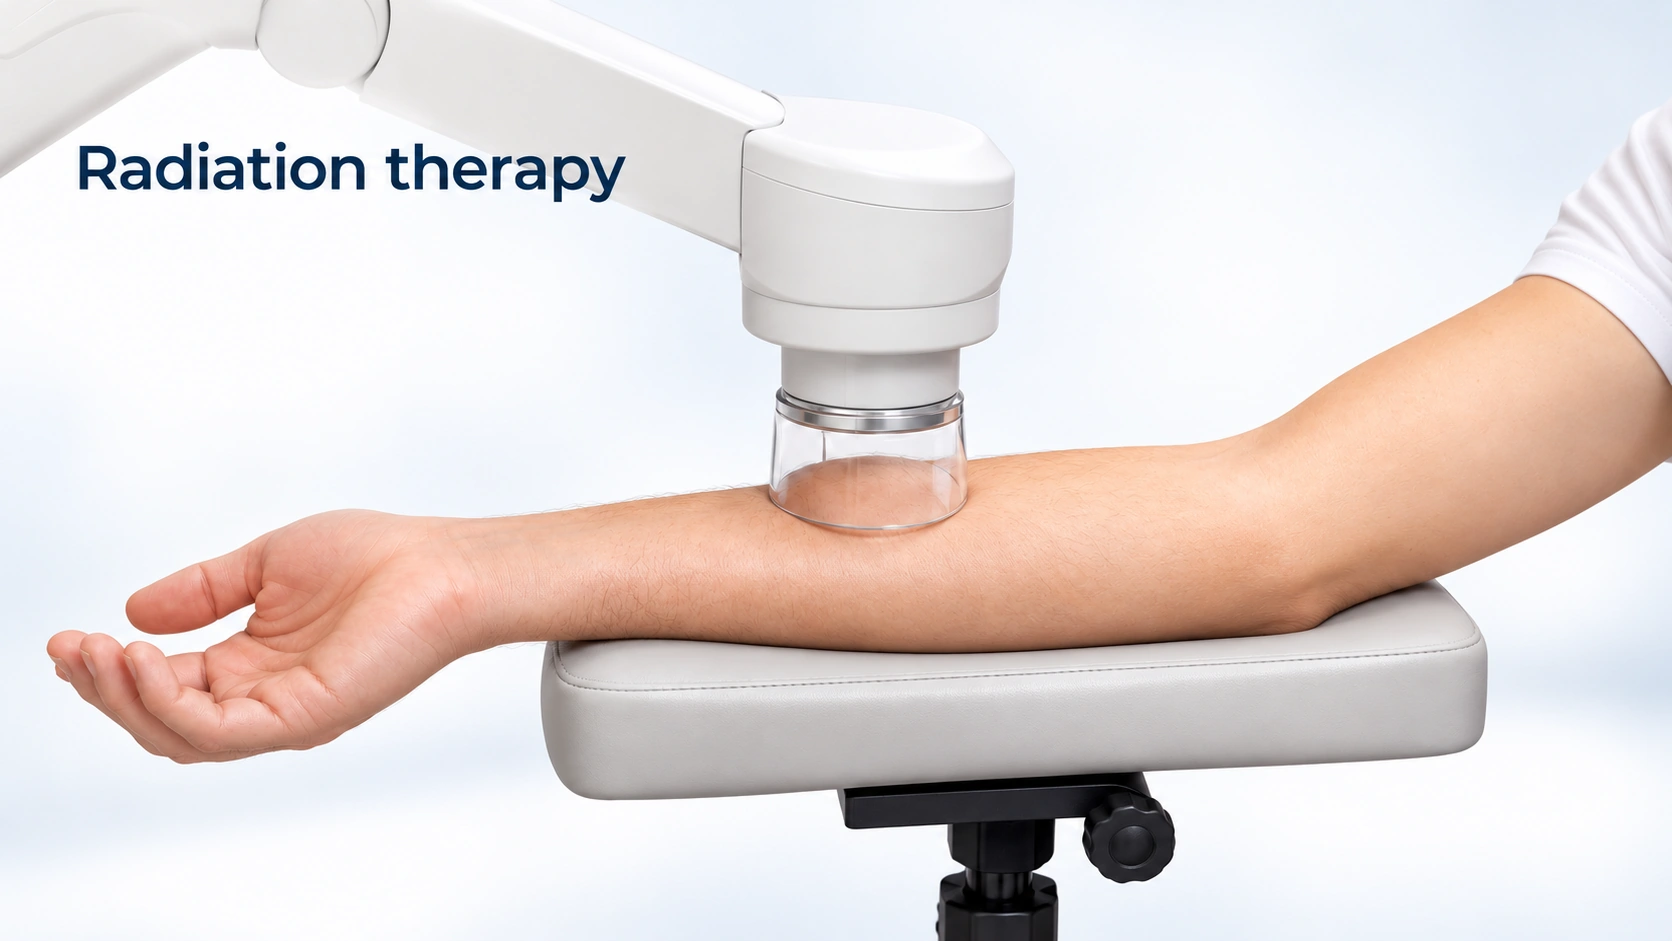
Radiation therapy
Moderate to strong evidence. No cutting, which is useful for people who cannot have surgery or where surgery would be disfiguring. The trades are many visits over weeks, a lower cure rate than surgery, and a permanently altered patch of skin. It is generally avoided in younger people.

Topical imiquimod or 5-fluorouracil
Only for superficial basal cell carcinoma and squamous cell carcinoma in situ. No cutting and no scar, done at home. The trades are weeks of a red, inflamed and uncomfortable course, meaningfully lower cure rates, and no confirmation that the tumor is gone.

Photodynamic therapy
Usually leaves the least visible mark of any of these, and useful when a whole area is sun-damaged. Painful during treatment, several visits, and cure rates below surgery.
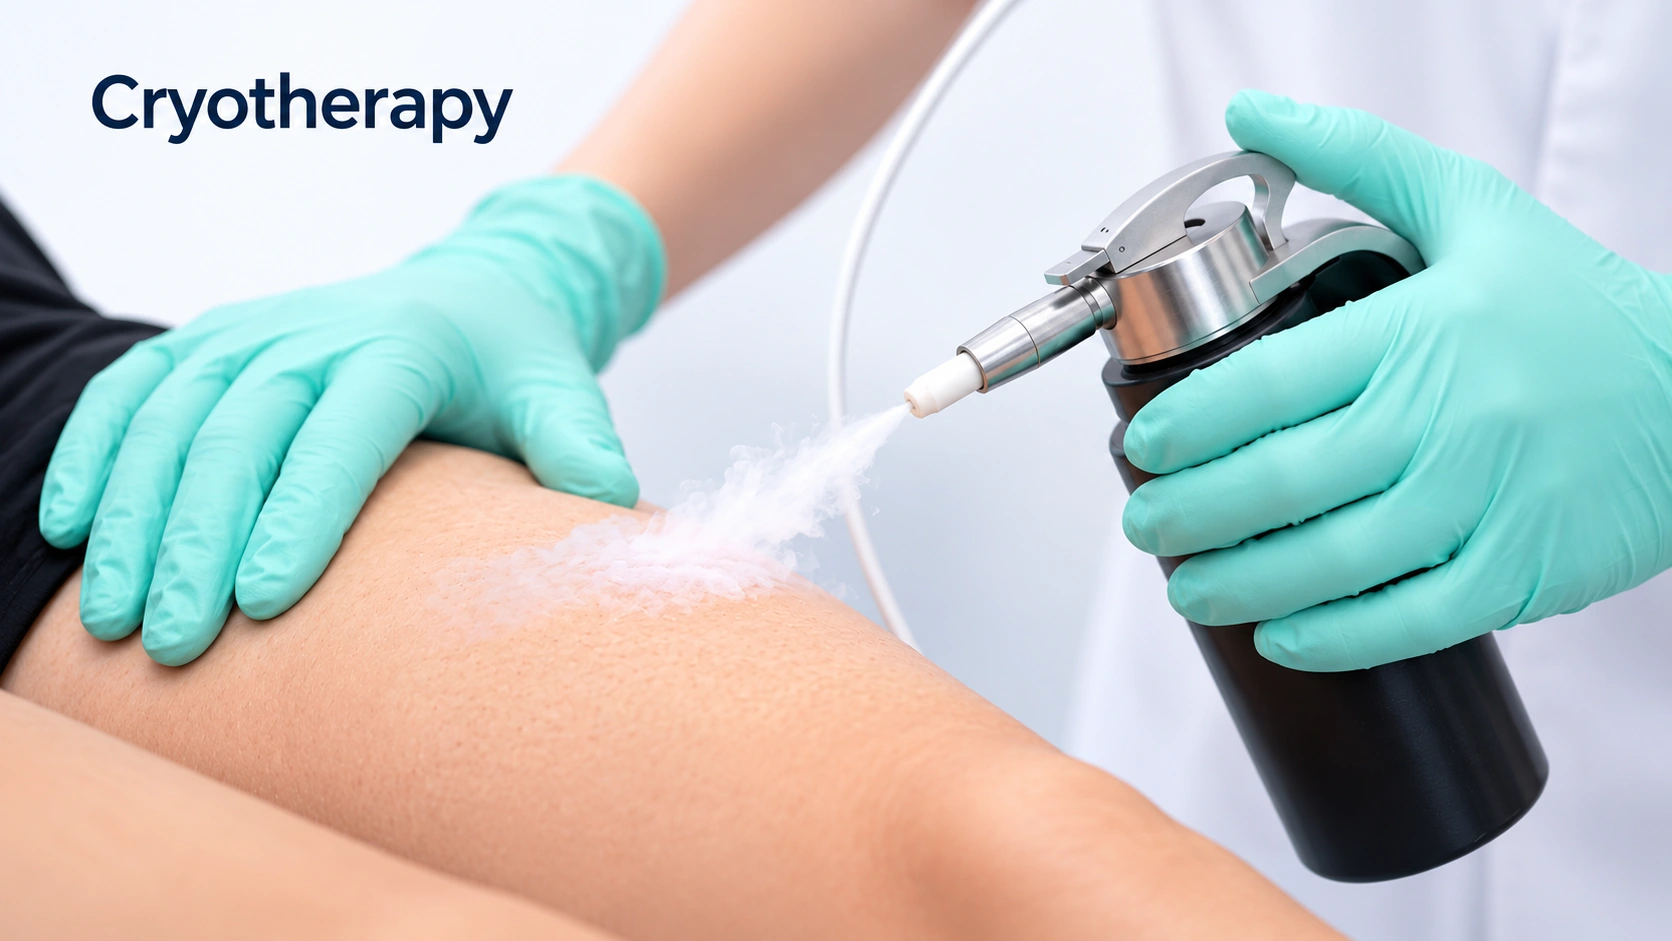
Cryotherapy
For very superficial lesions and strong evidence for precancerous spots. Fast and needs no injection. Depth is hard to judge, there is no margin check, and it leaves a pale mark. It is used for actinic keratoses far more than for a diagnosed cancer.

Watchful waiting
Weak as a plan for a diagnosed cancer, and occasionally reasonable for a very small, slow-growing, low-risk basal cell carcinoma in someone frail or very elderly, where the surgery would cost more than the tumor will. That is a decision made with a doctor, never a default.

What is worth doing at home
Daily broad-spectrum SPF 30 or higher, sun-protective clothing and shade lower the rate of new skin cancers. Checking your own skin monthly, and knowing what to look for, is how the next one gets found early. After the surgery, wound care and silicone on the closed scar are the two home tasks that change the result.
Questions
Why is the scar so much longer than the spot?
Because a round hole cannot be closed flat. The piece taken out is an ellipse roughly three times as long as it is wide, so the edges meet evenly instead of puckering at each end. A spot the size of a pencil eraser becomes a line an inch or more long. It is geometry, not technique, and no surgeon avoids it.
How long until I get the result?
Usually 3 to 10 days, depending on the laboratory. Ask before you leave how and when you will be told, and call if you have heard nothing after about two weeks.
What happens if the margins are not clear?
A further procedure — a re-excision with a wider border, or a referral for Mohs surgery — usually within a few weeks. It is not a mistake. It is the reason the specimen went to a laboratory in the first place.
When can I exercise again?
About 2 weeks for most sites, longer for the back, shoulder and shin. The visible stitches come out sooner, and the deep stitches are still carrying the tension. Lifting or straining is what stretches or splits a wound.
Should I have Mohs surgery instead?
On the face, particularly the nose, eyelids, ears and lips, or for a tumor that is large, has vague borders, has an aggressive subtype on the biopsy, or has come back before, Mohs is often better. For a small low-risk cancer on the trunk or limbs, an excision achieves the same result in a fraction of the time and cost. Ask which category yours is in.
Will the scar fade?
It flattens and pales substantially over about a year, with most of the change in the first six months. Keeping it out of the sun and using silicone gel or sheeting once it is closed are the two things with reasonable evidence behind them. Scars on the chest, shoulders and upper back stay red and raised longest and are the likeliest to widen.
Related

Electrodesiccation and Curettage
Mohs Surgery
Basal Cell Carcinoma
Squamous Cell Carcinoma
Keloids
Melanoma
Photodynamic Therapy
Cryotherapy
Acne Scarring
Epidermal Inclusion Cyst
Cryotherapy vs Surgical Excision