Adapalene
Strong evidenceThe strongest thing you can buy without a prescription, and the best first move for most acne. It unclogs pores before they inflame, which is why it prevents spots rather than treating them.
Acne often includes blackheads, whiteheads, and spots of different sizes. Fungal acne is yeast-related folliculitis, often with similar-looking itchy bumps. Their treatments differ.

The same eight facts on every condition comparison.
It starts in the follicle.
Acne affects the hair follicle and its oil gland.
Spots take several forms.
Plugs form blackheads or whiteheads; inflammation forms pimples and deeper lumps.
It is not about dirt.
Bacteria are only one part of the process.
Tests are rarely needed.
An unusual pattern or hormonal symptoms may call for assessment.
Overview
Oil and dead skin cells block hair follicles. This can cause blackheads, whiteheads, pimples, or deeper painful lumps.
It is a yeast-driven follicle eruption.
Malassezia, which normally lives on skin, can multiply inside follicles.
It has a typical pattern.
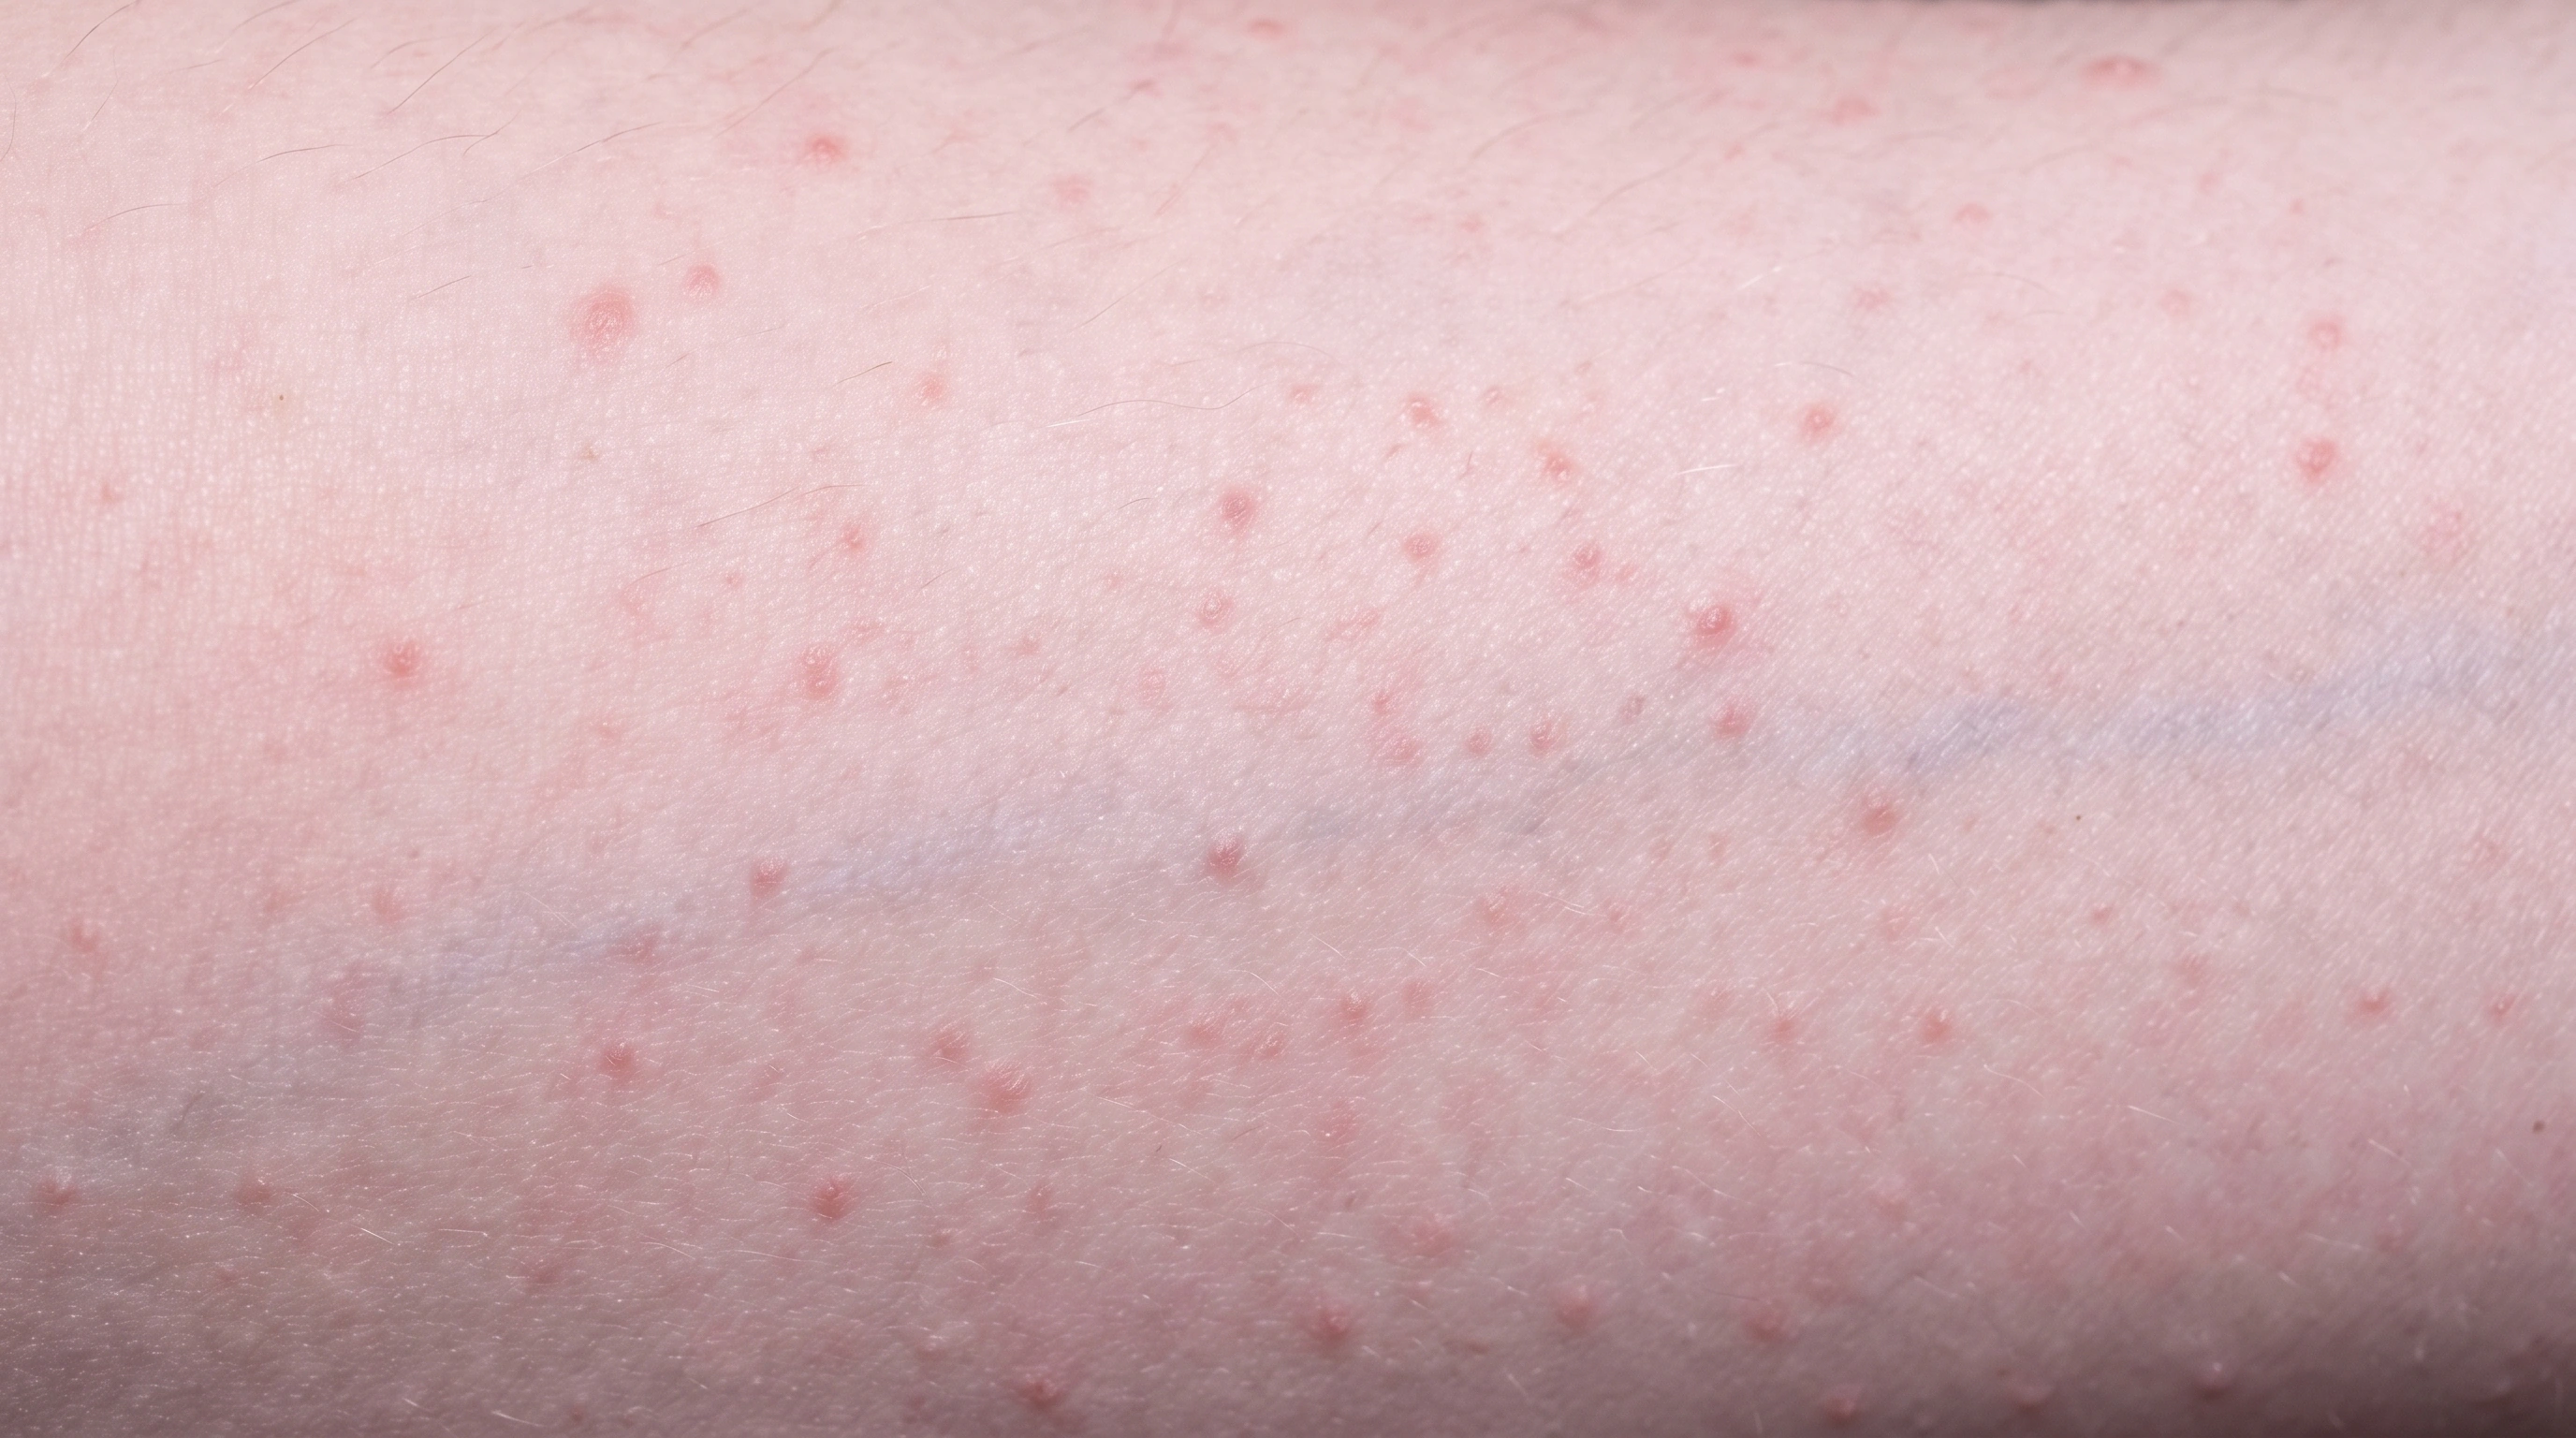
Small itchy bumps cluster on the upper trunk, shoulders, neck or hairline.
The nickname misleads.
Conventional acne treatments may not address the yeast.
It can coexist with acne.
Blackheads, whiteheads and mixed lesion sizes point to acne vulgaris as well.
Overview
Also called Malassezia folliculitis: inflammation around hair follicles linked to yeast. It often produces small, similar-looking, itchy bumps rather than blocked pores.
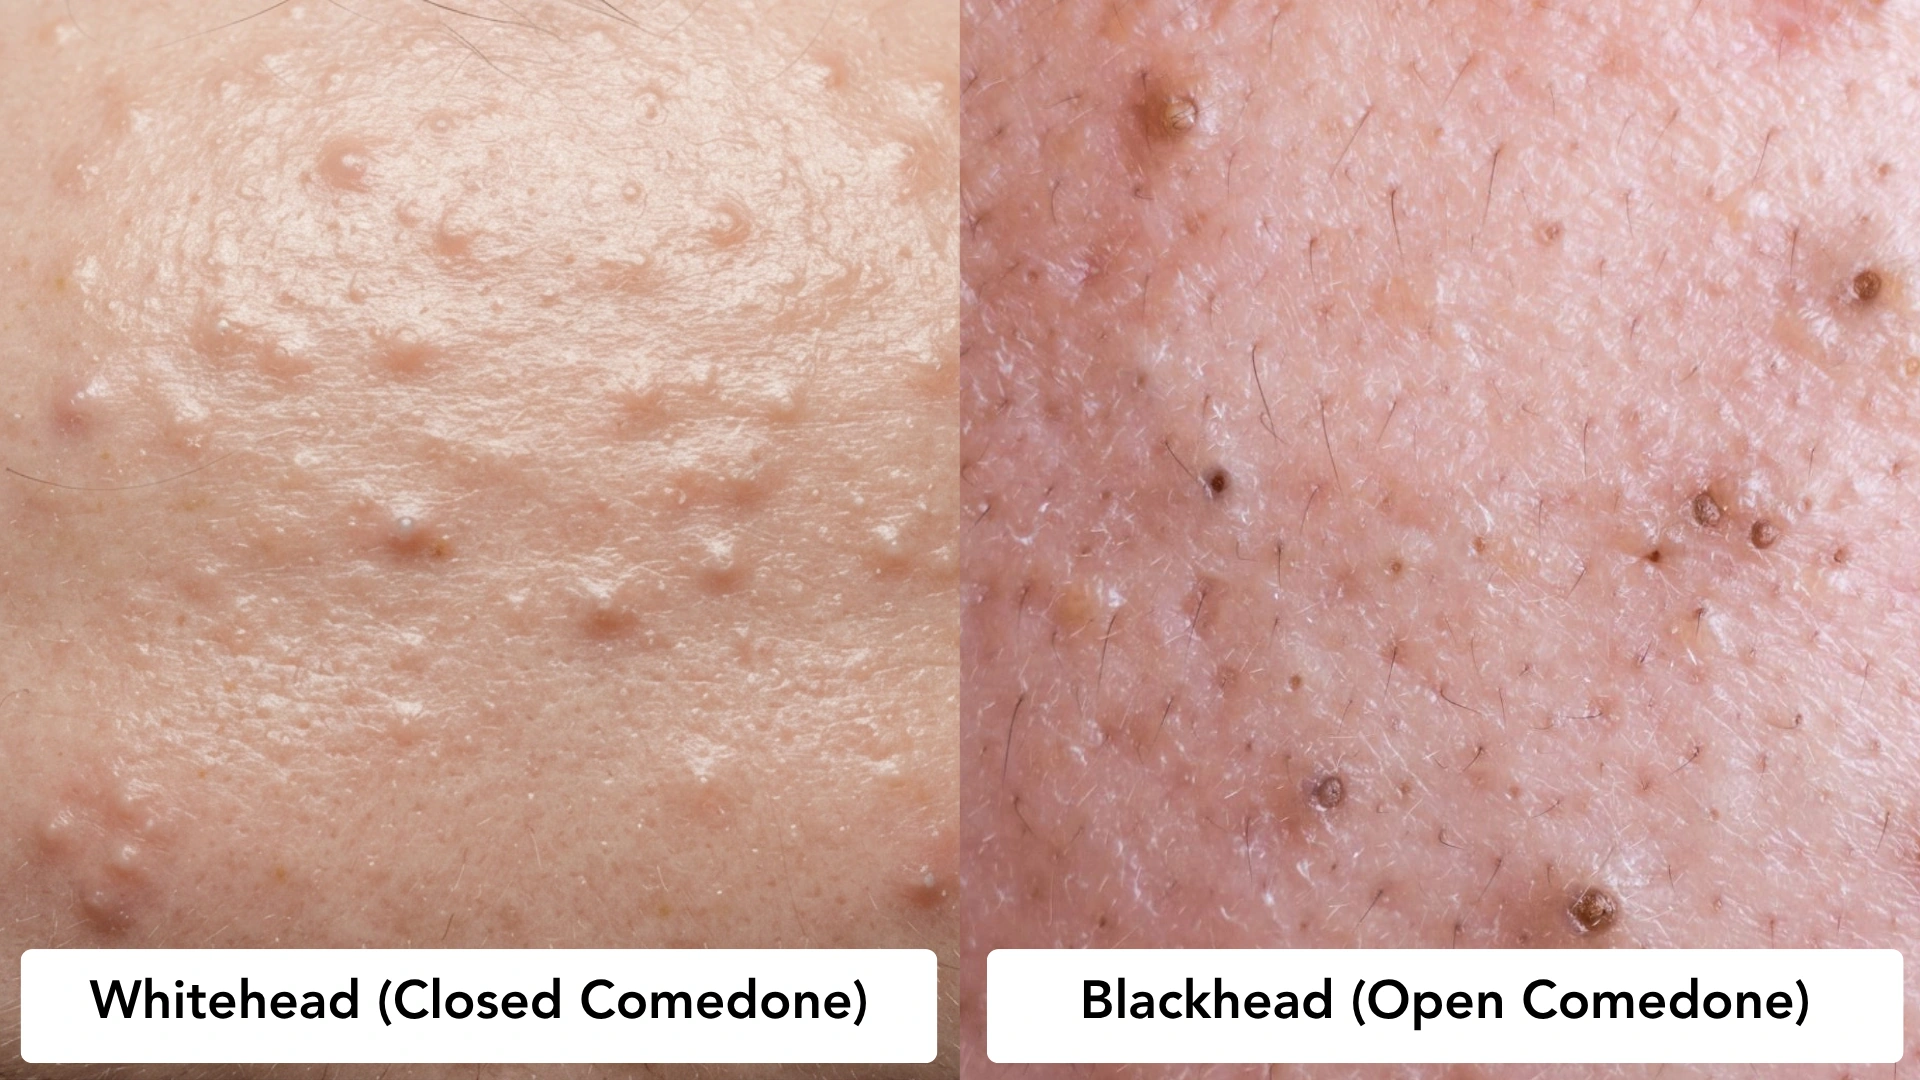
Comedonal acne Mostly blackheads and whiteheads.
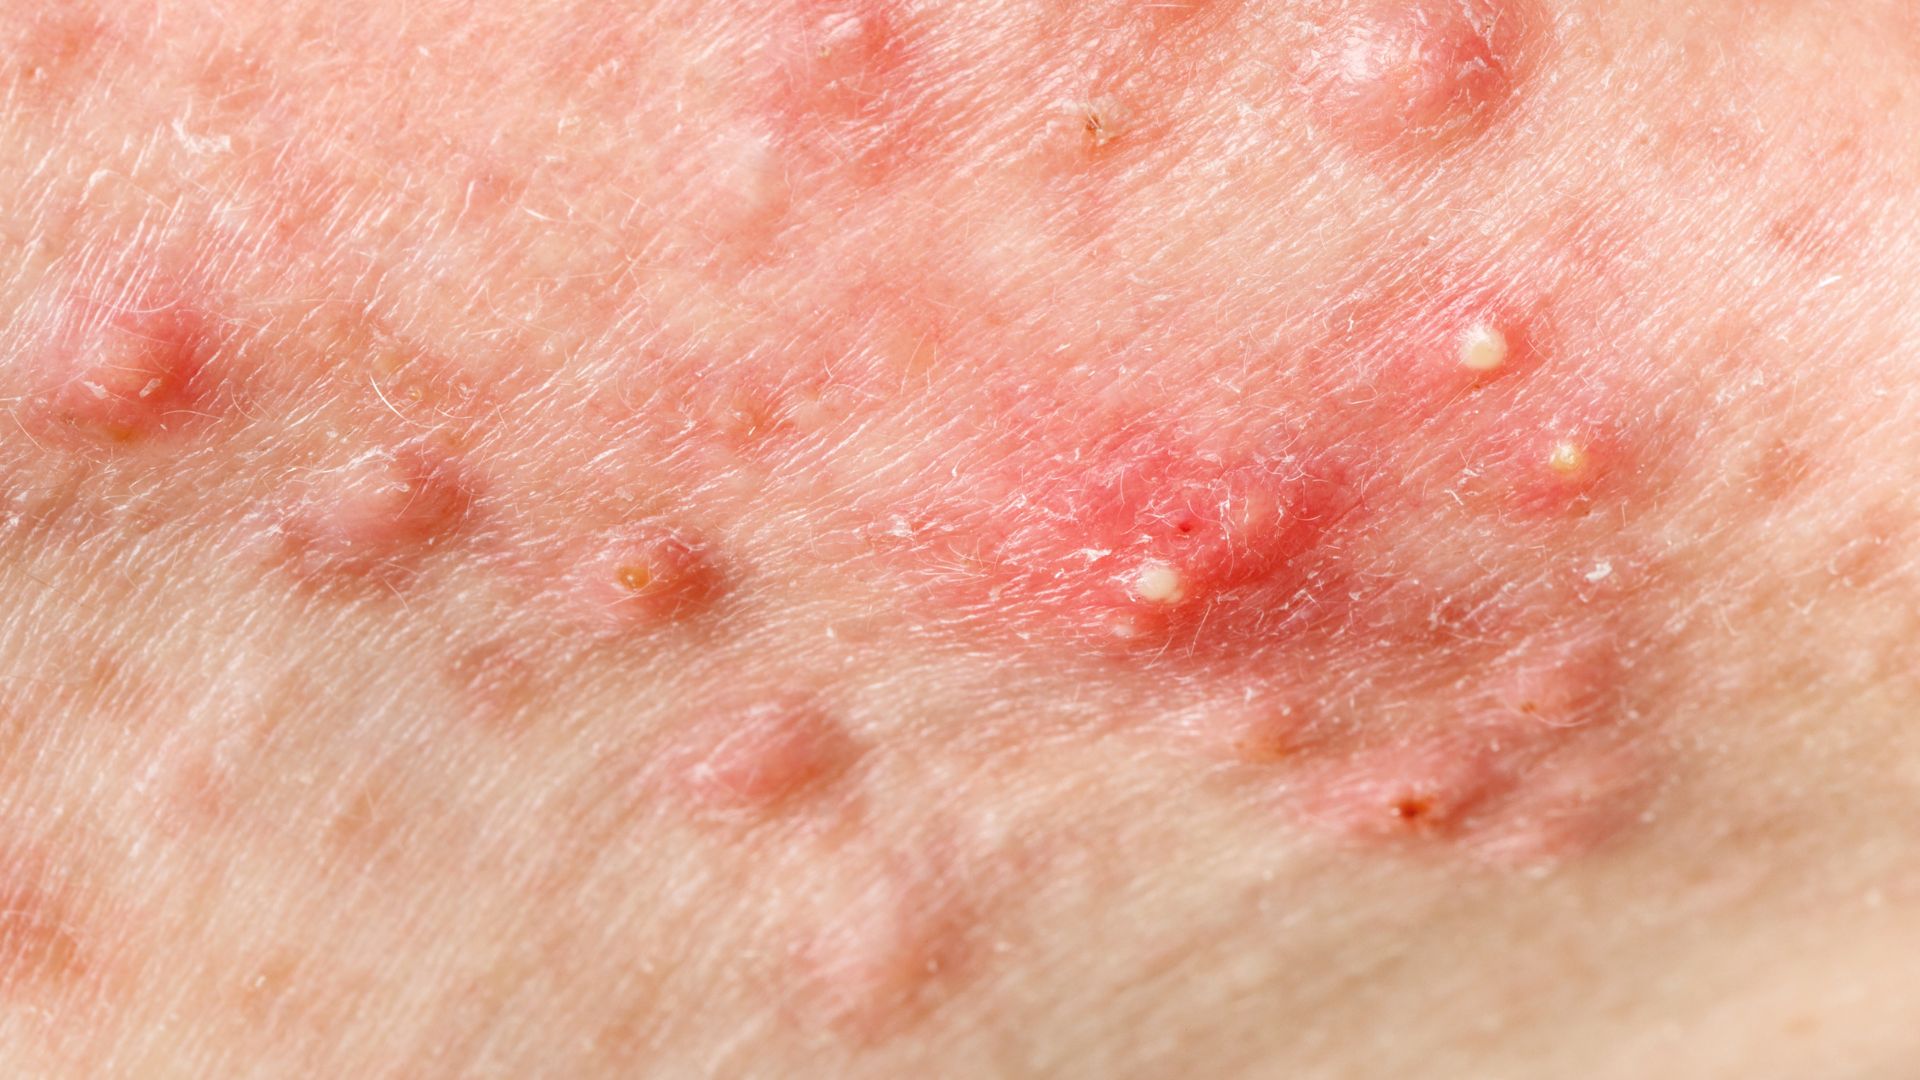
Inflammatory acne Red papules and pustules.
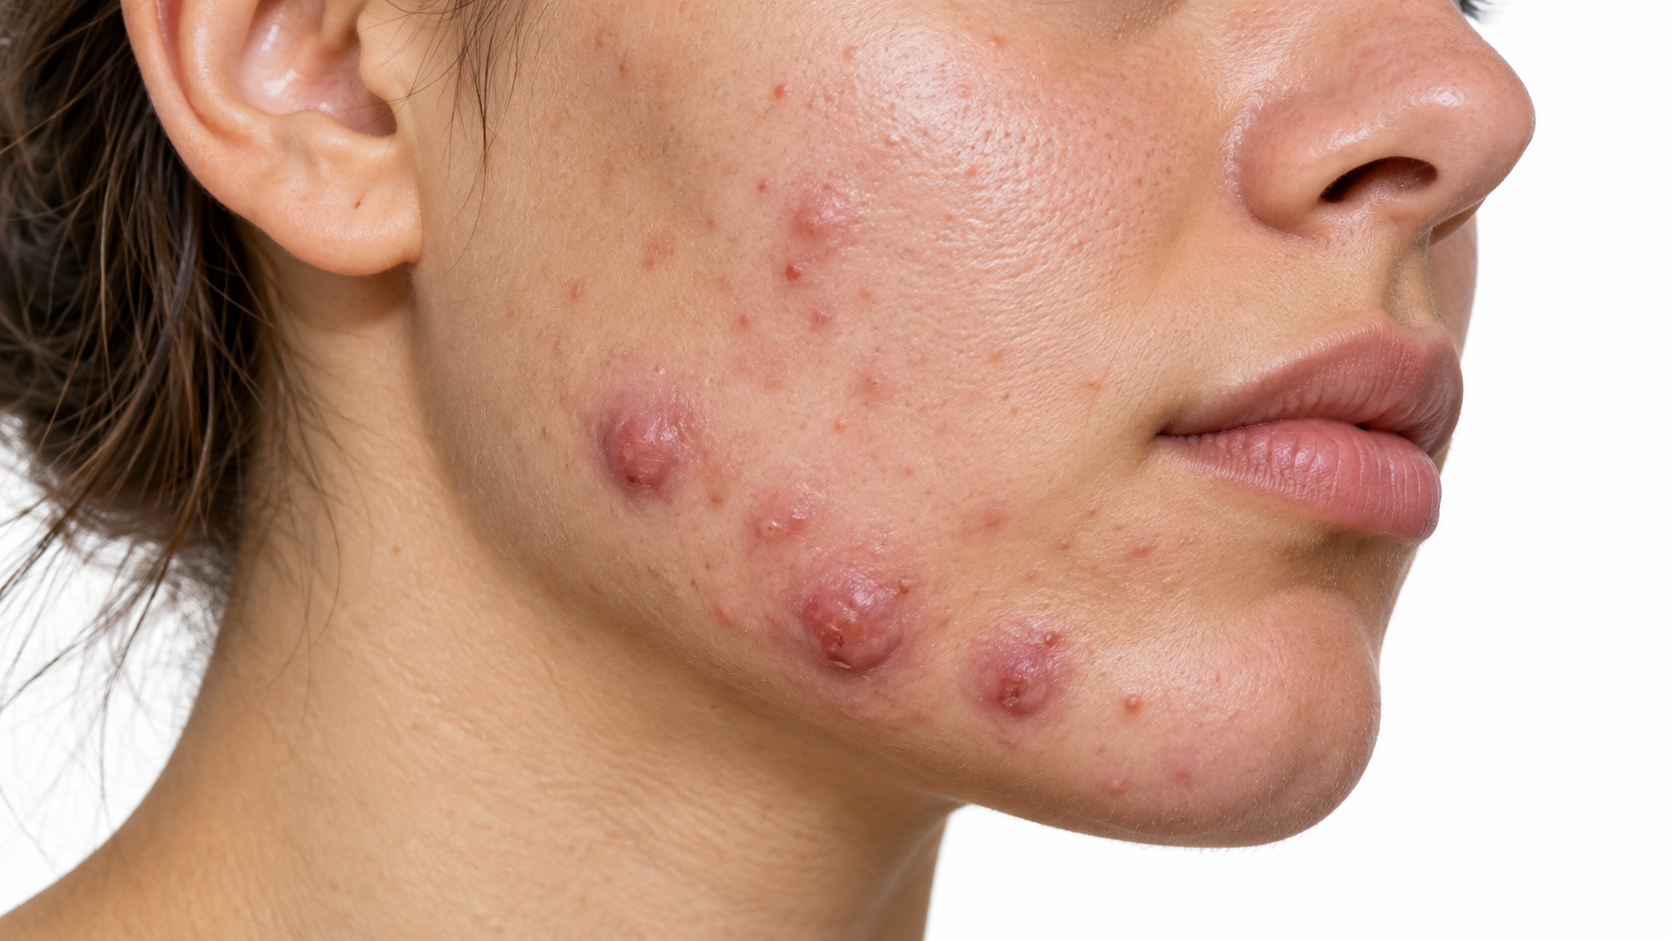
Nodulocystic acne Deep painful lumps that can scar.

Hormonal acne Breakouts along the jaw and chin.
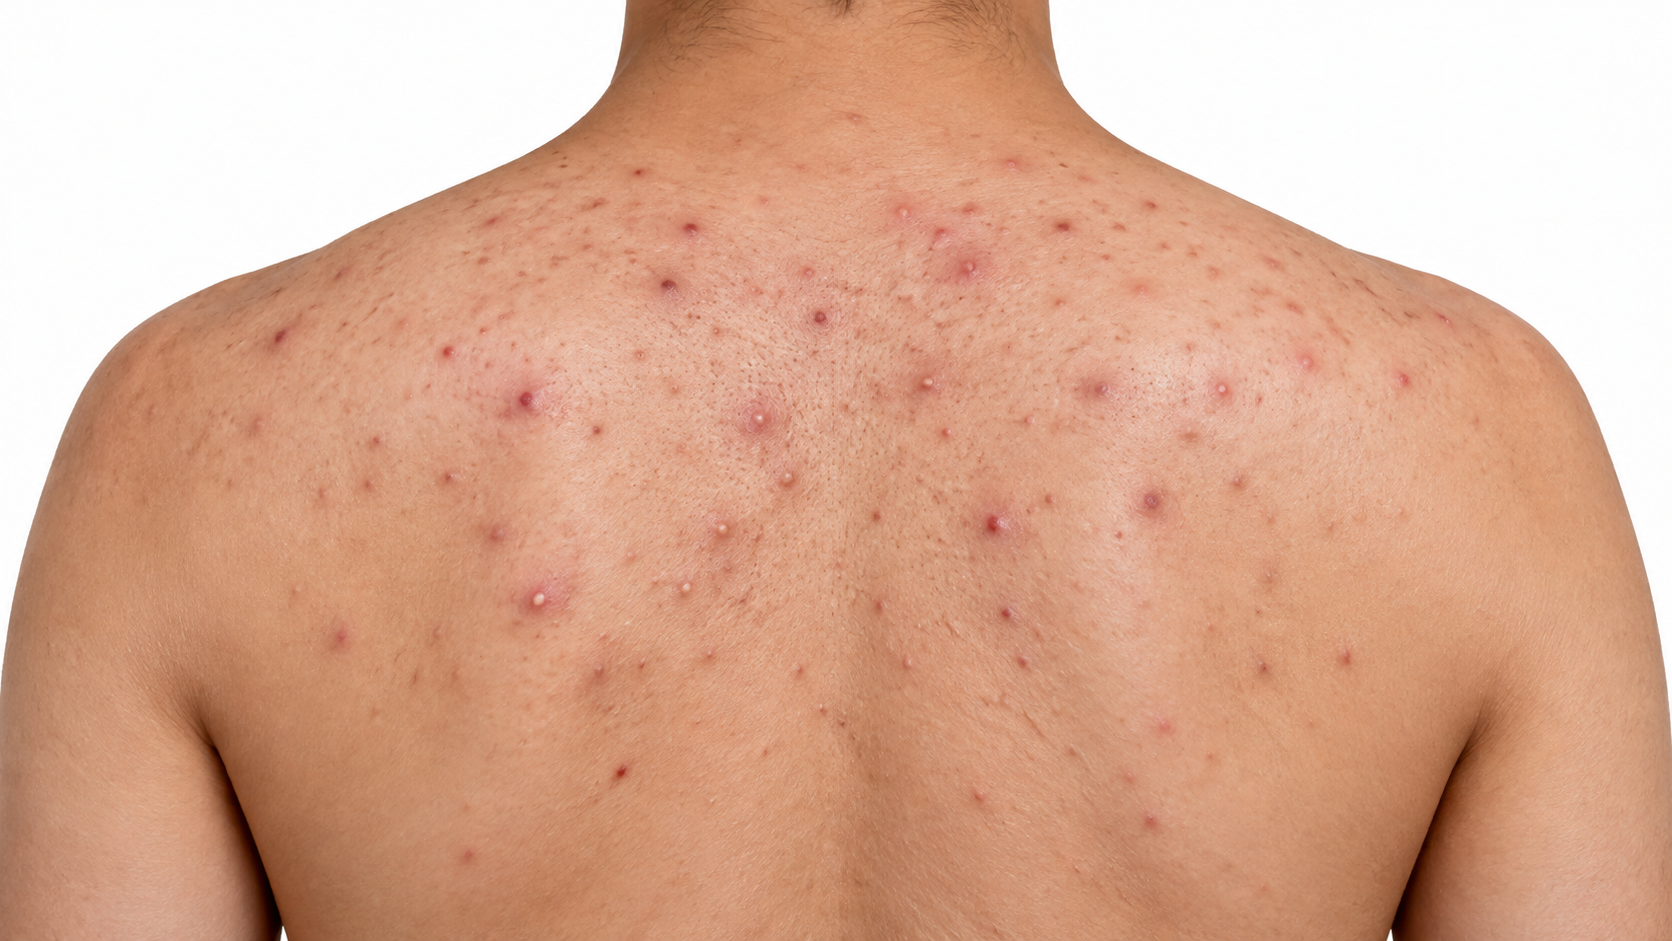
Body acne On the chest, back and shoulders.
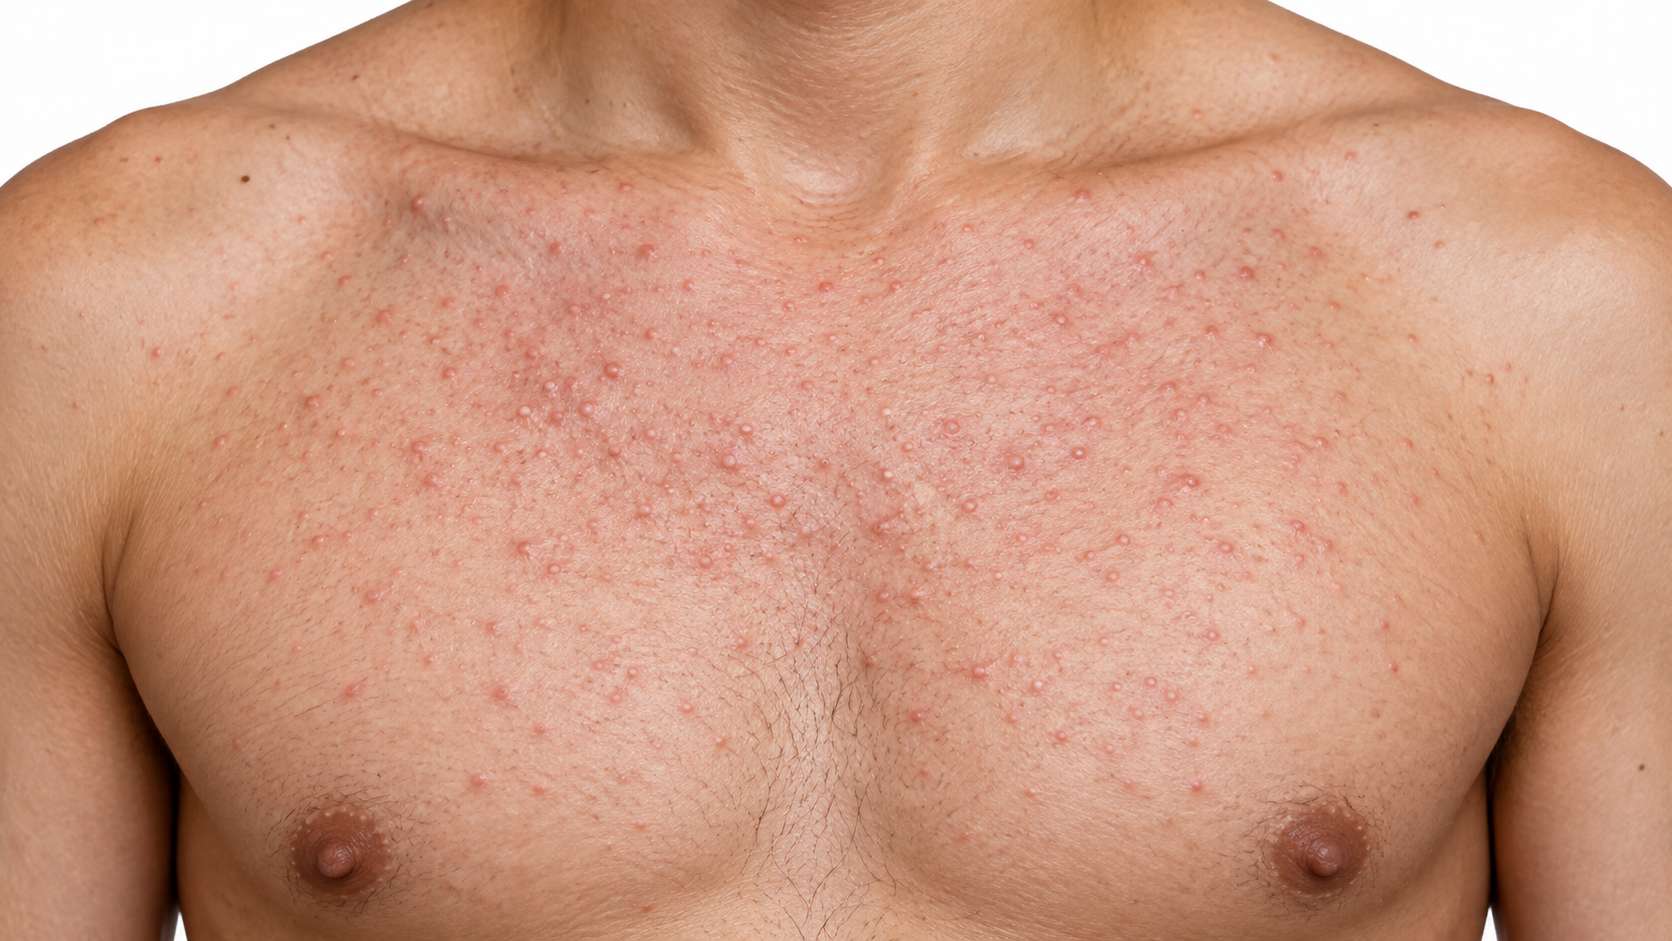
Uniform bumps Small bumps all the same size.
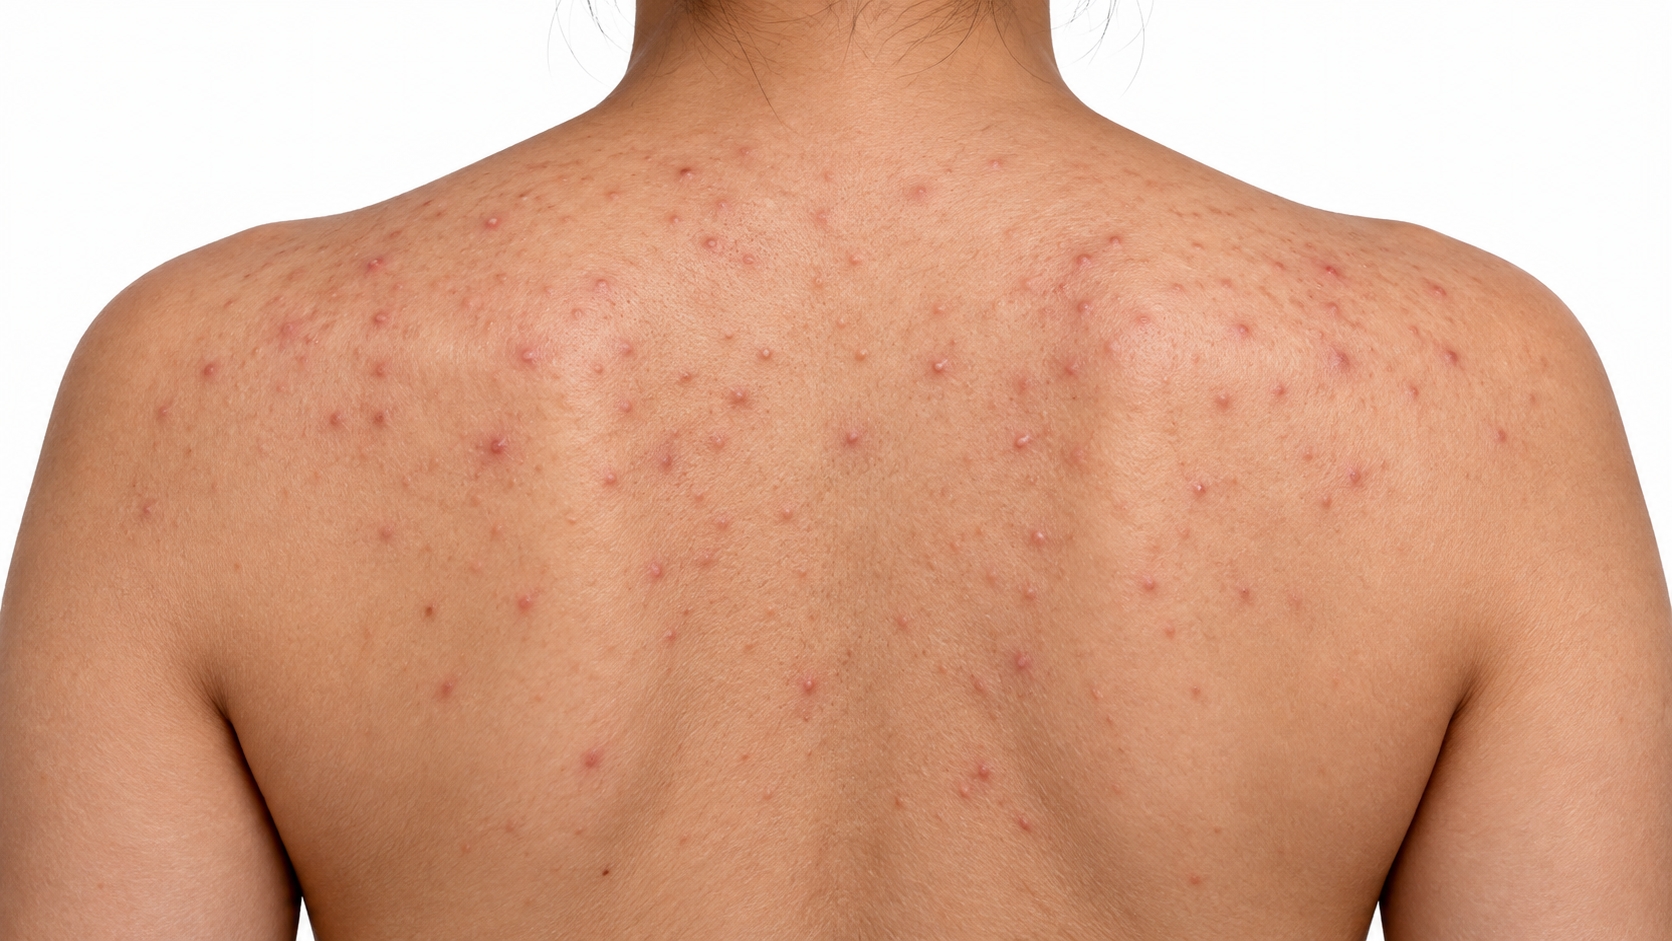
Upper back A common site.

Forehead Clusters along the hairline.
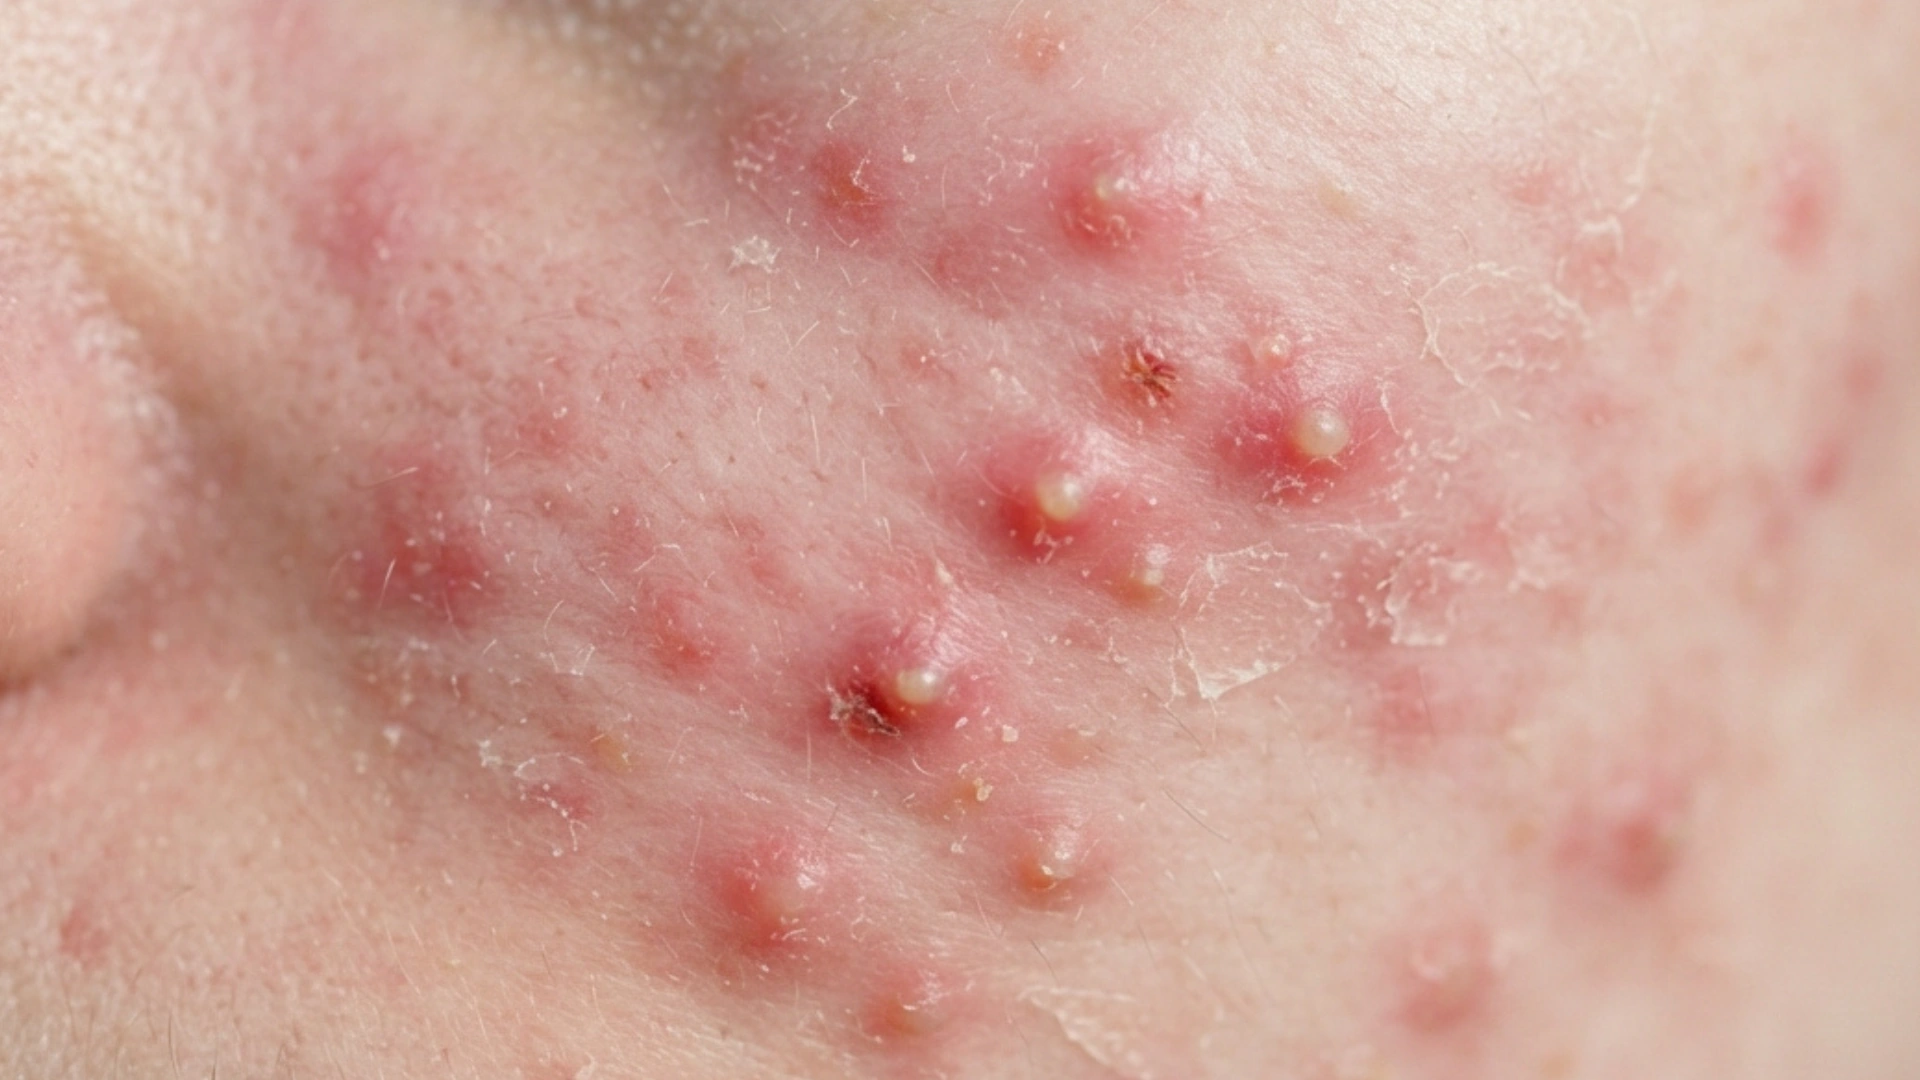
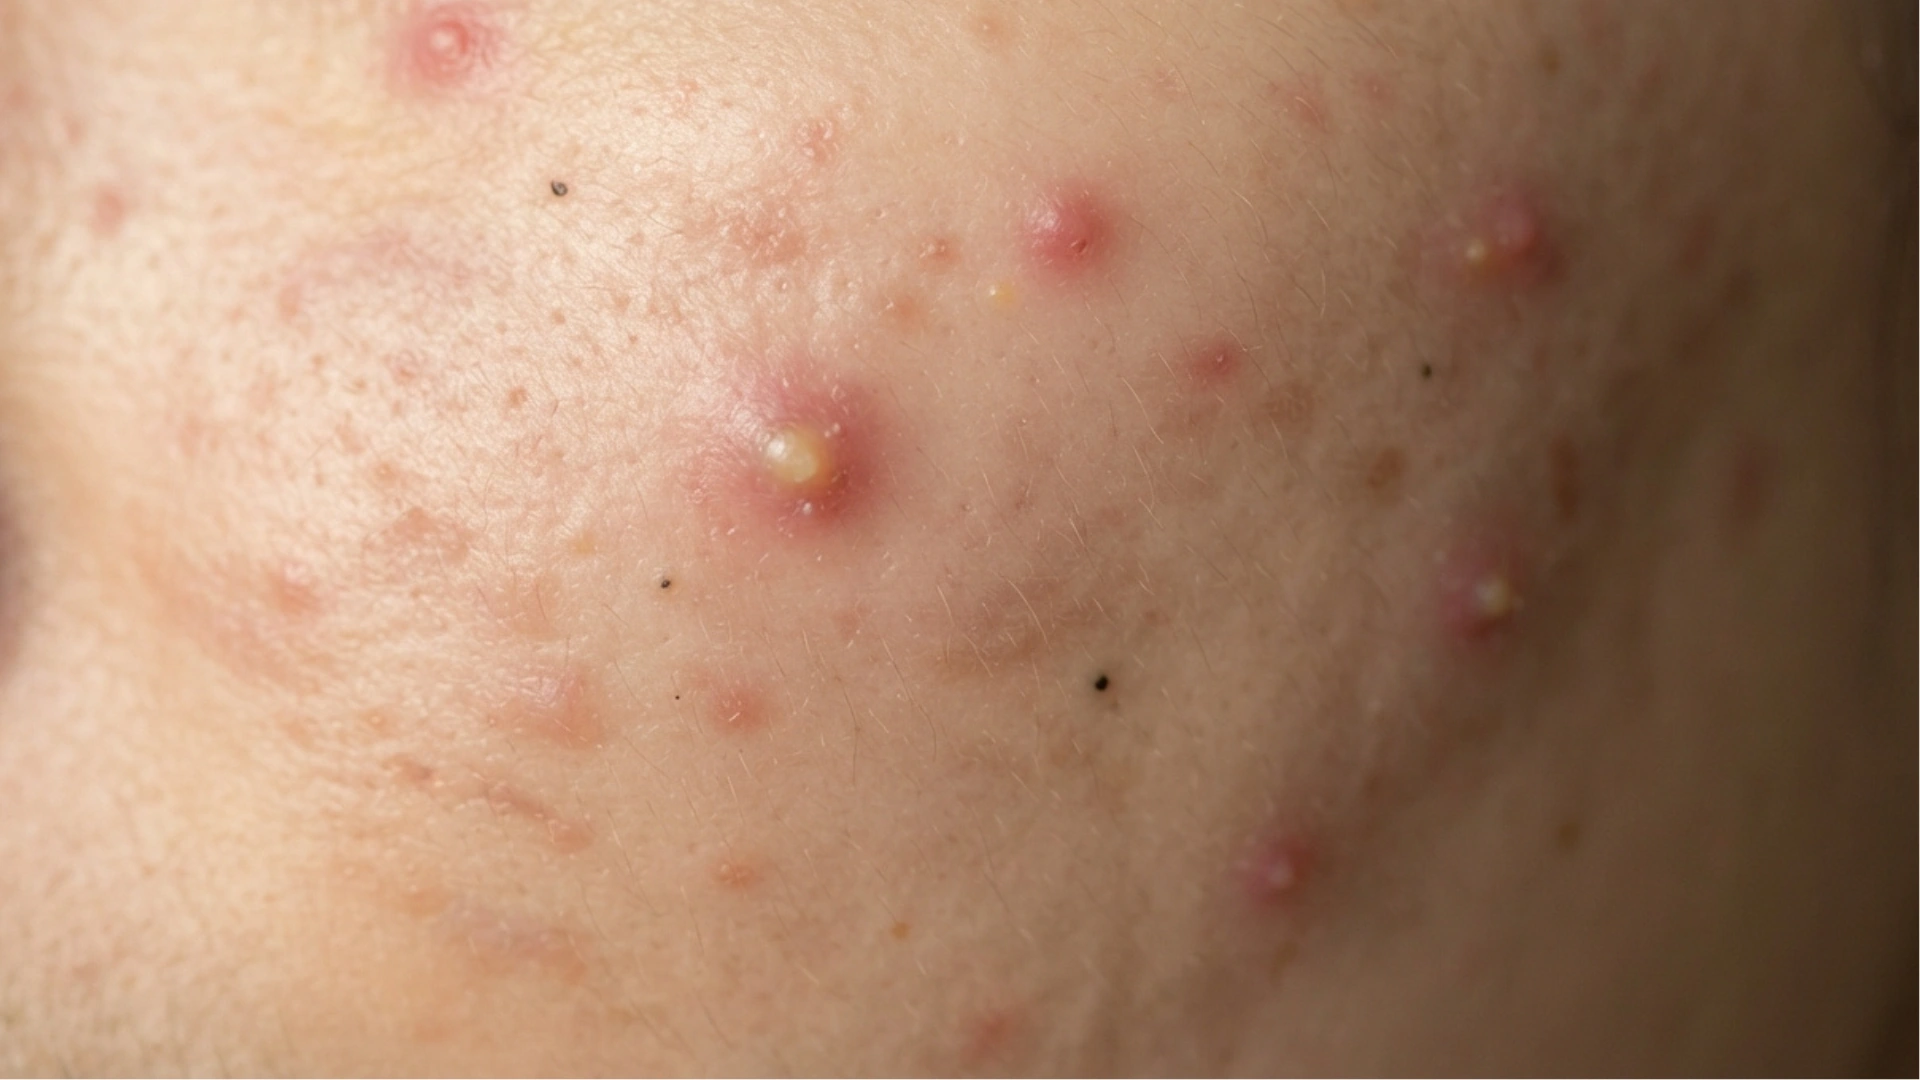
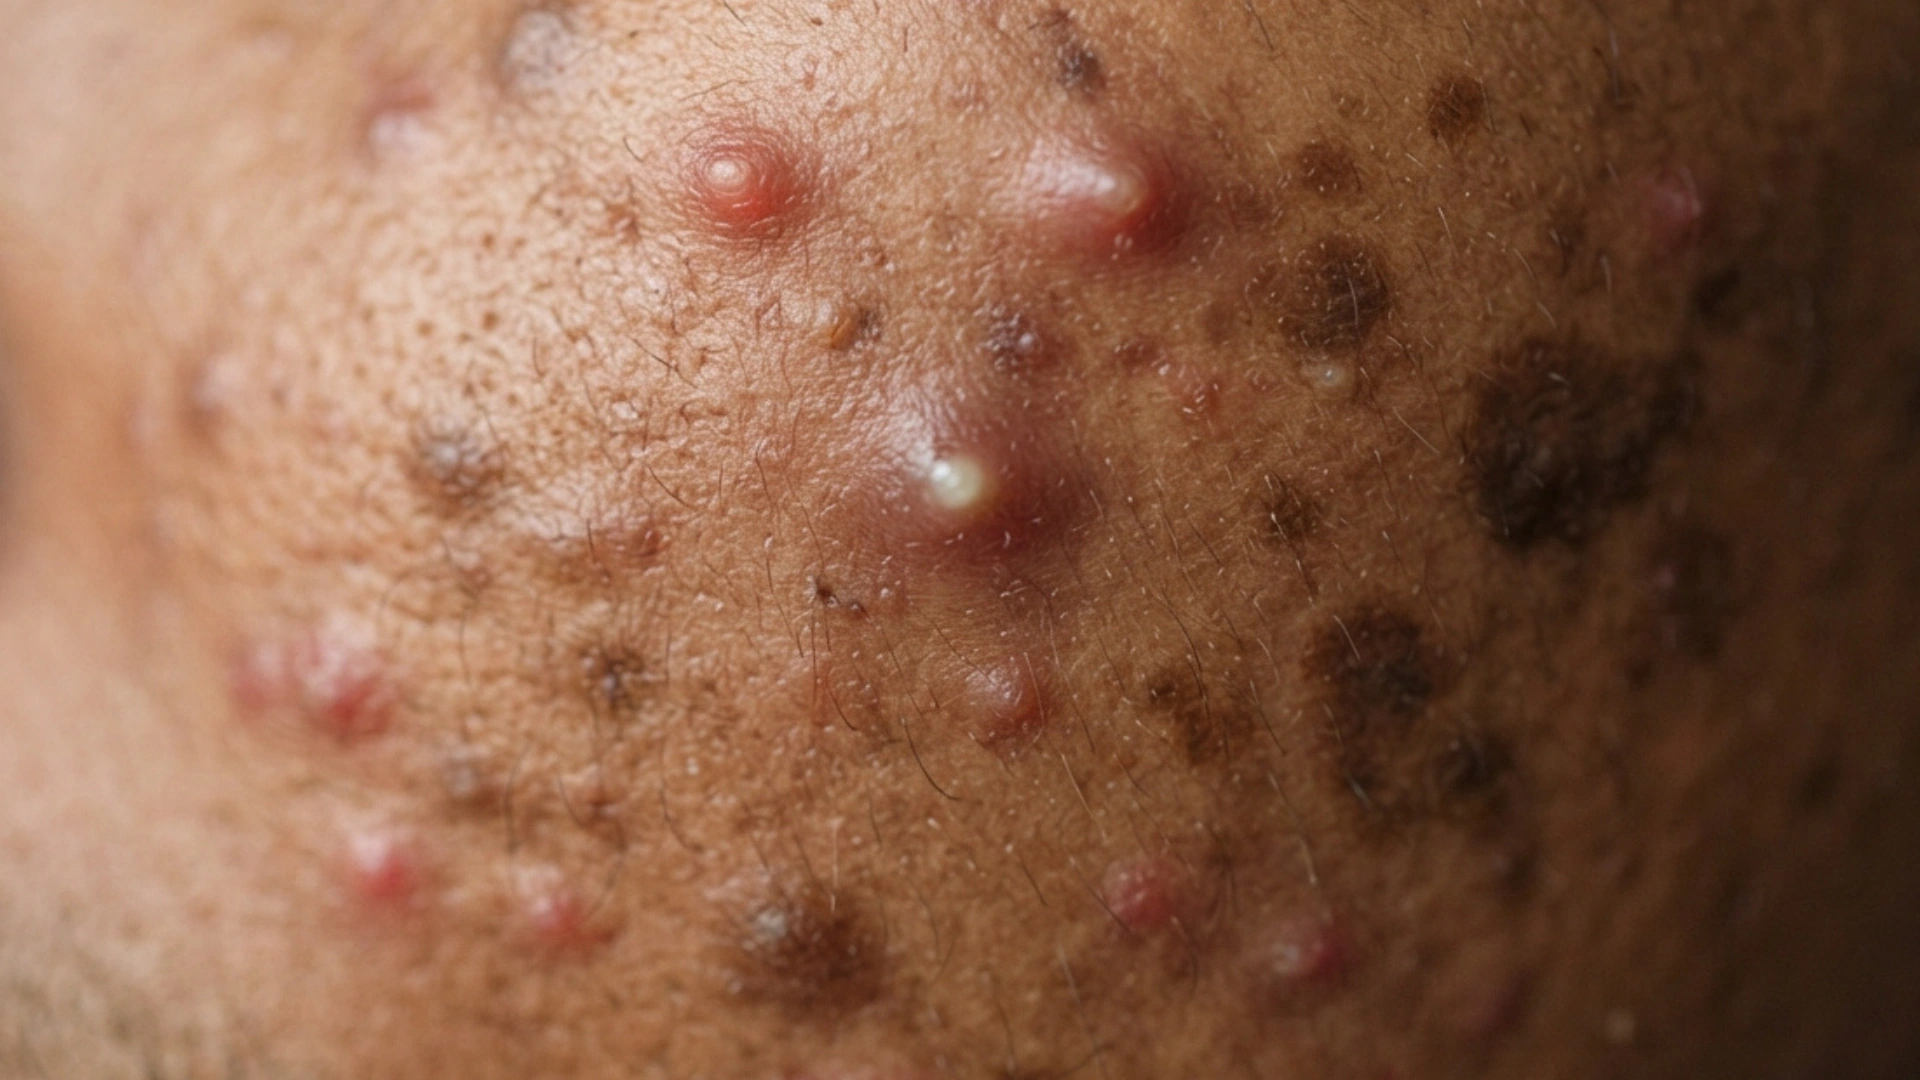
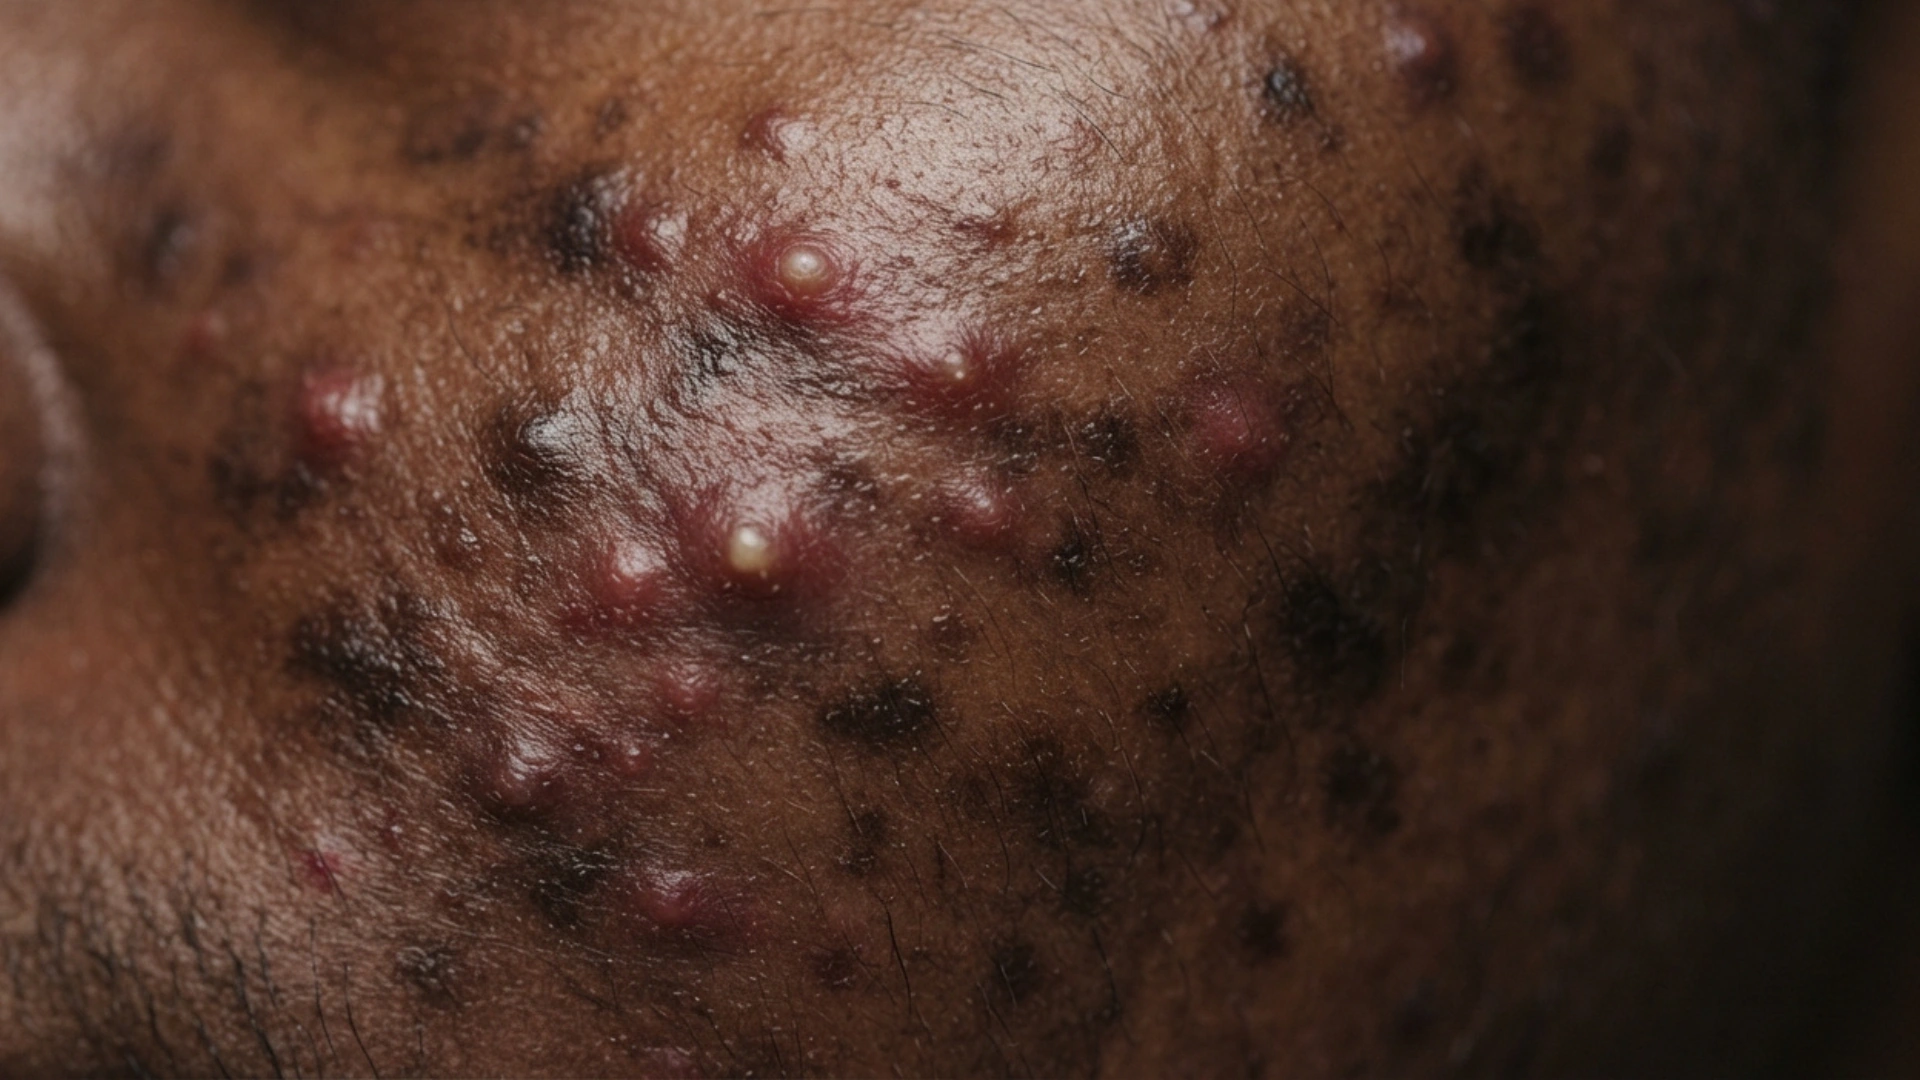
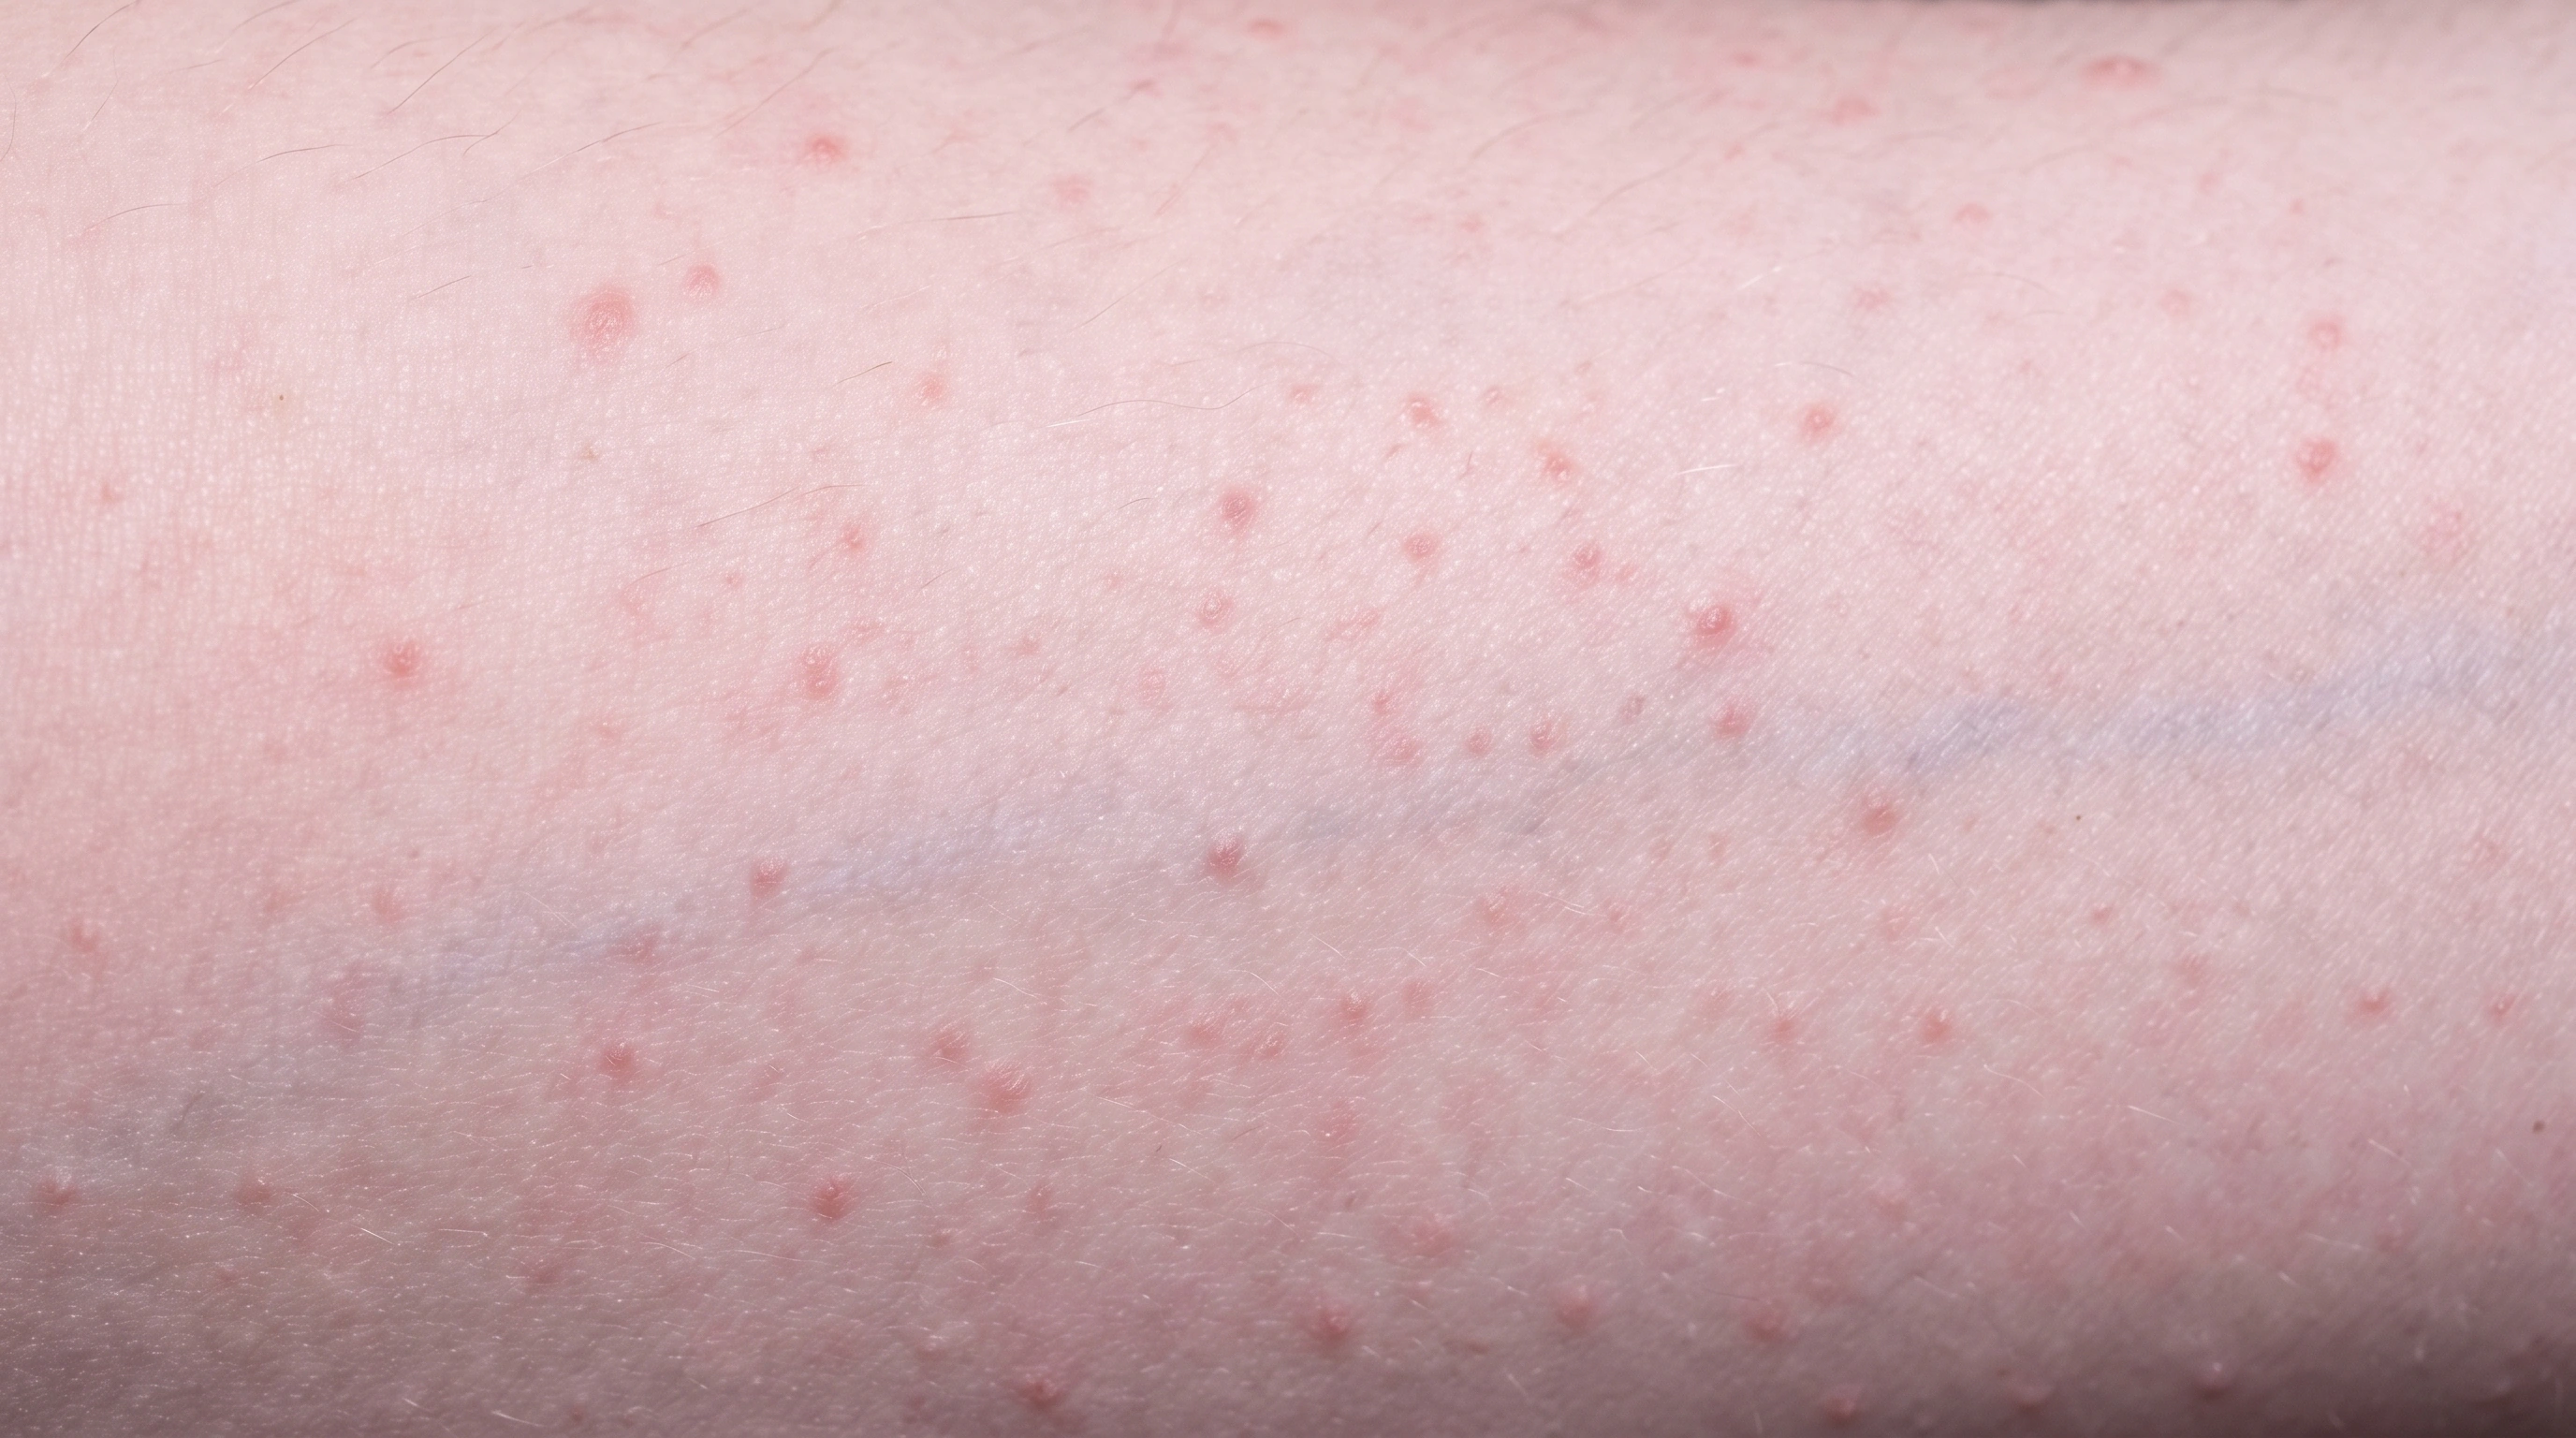
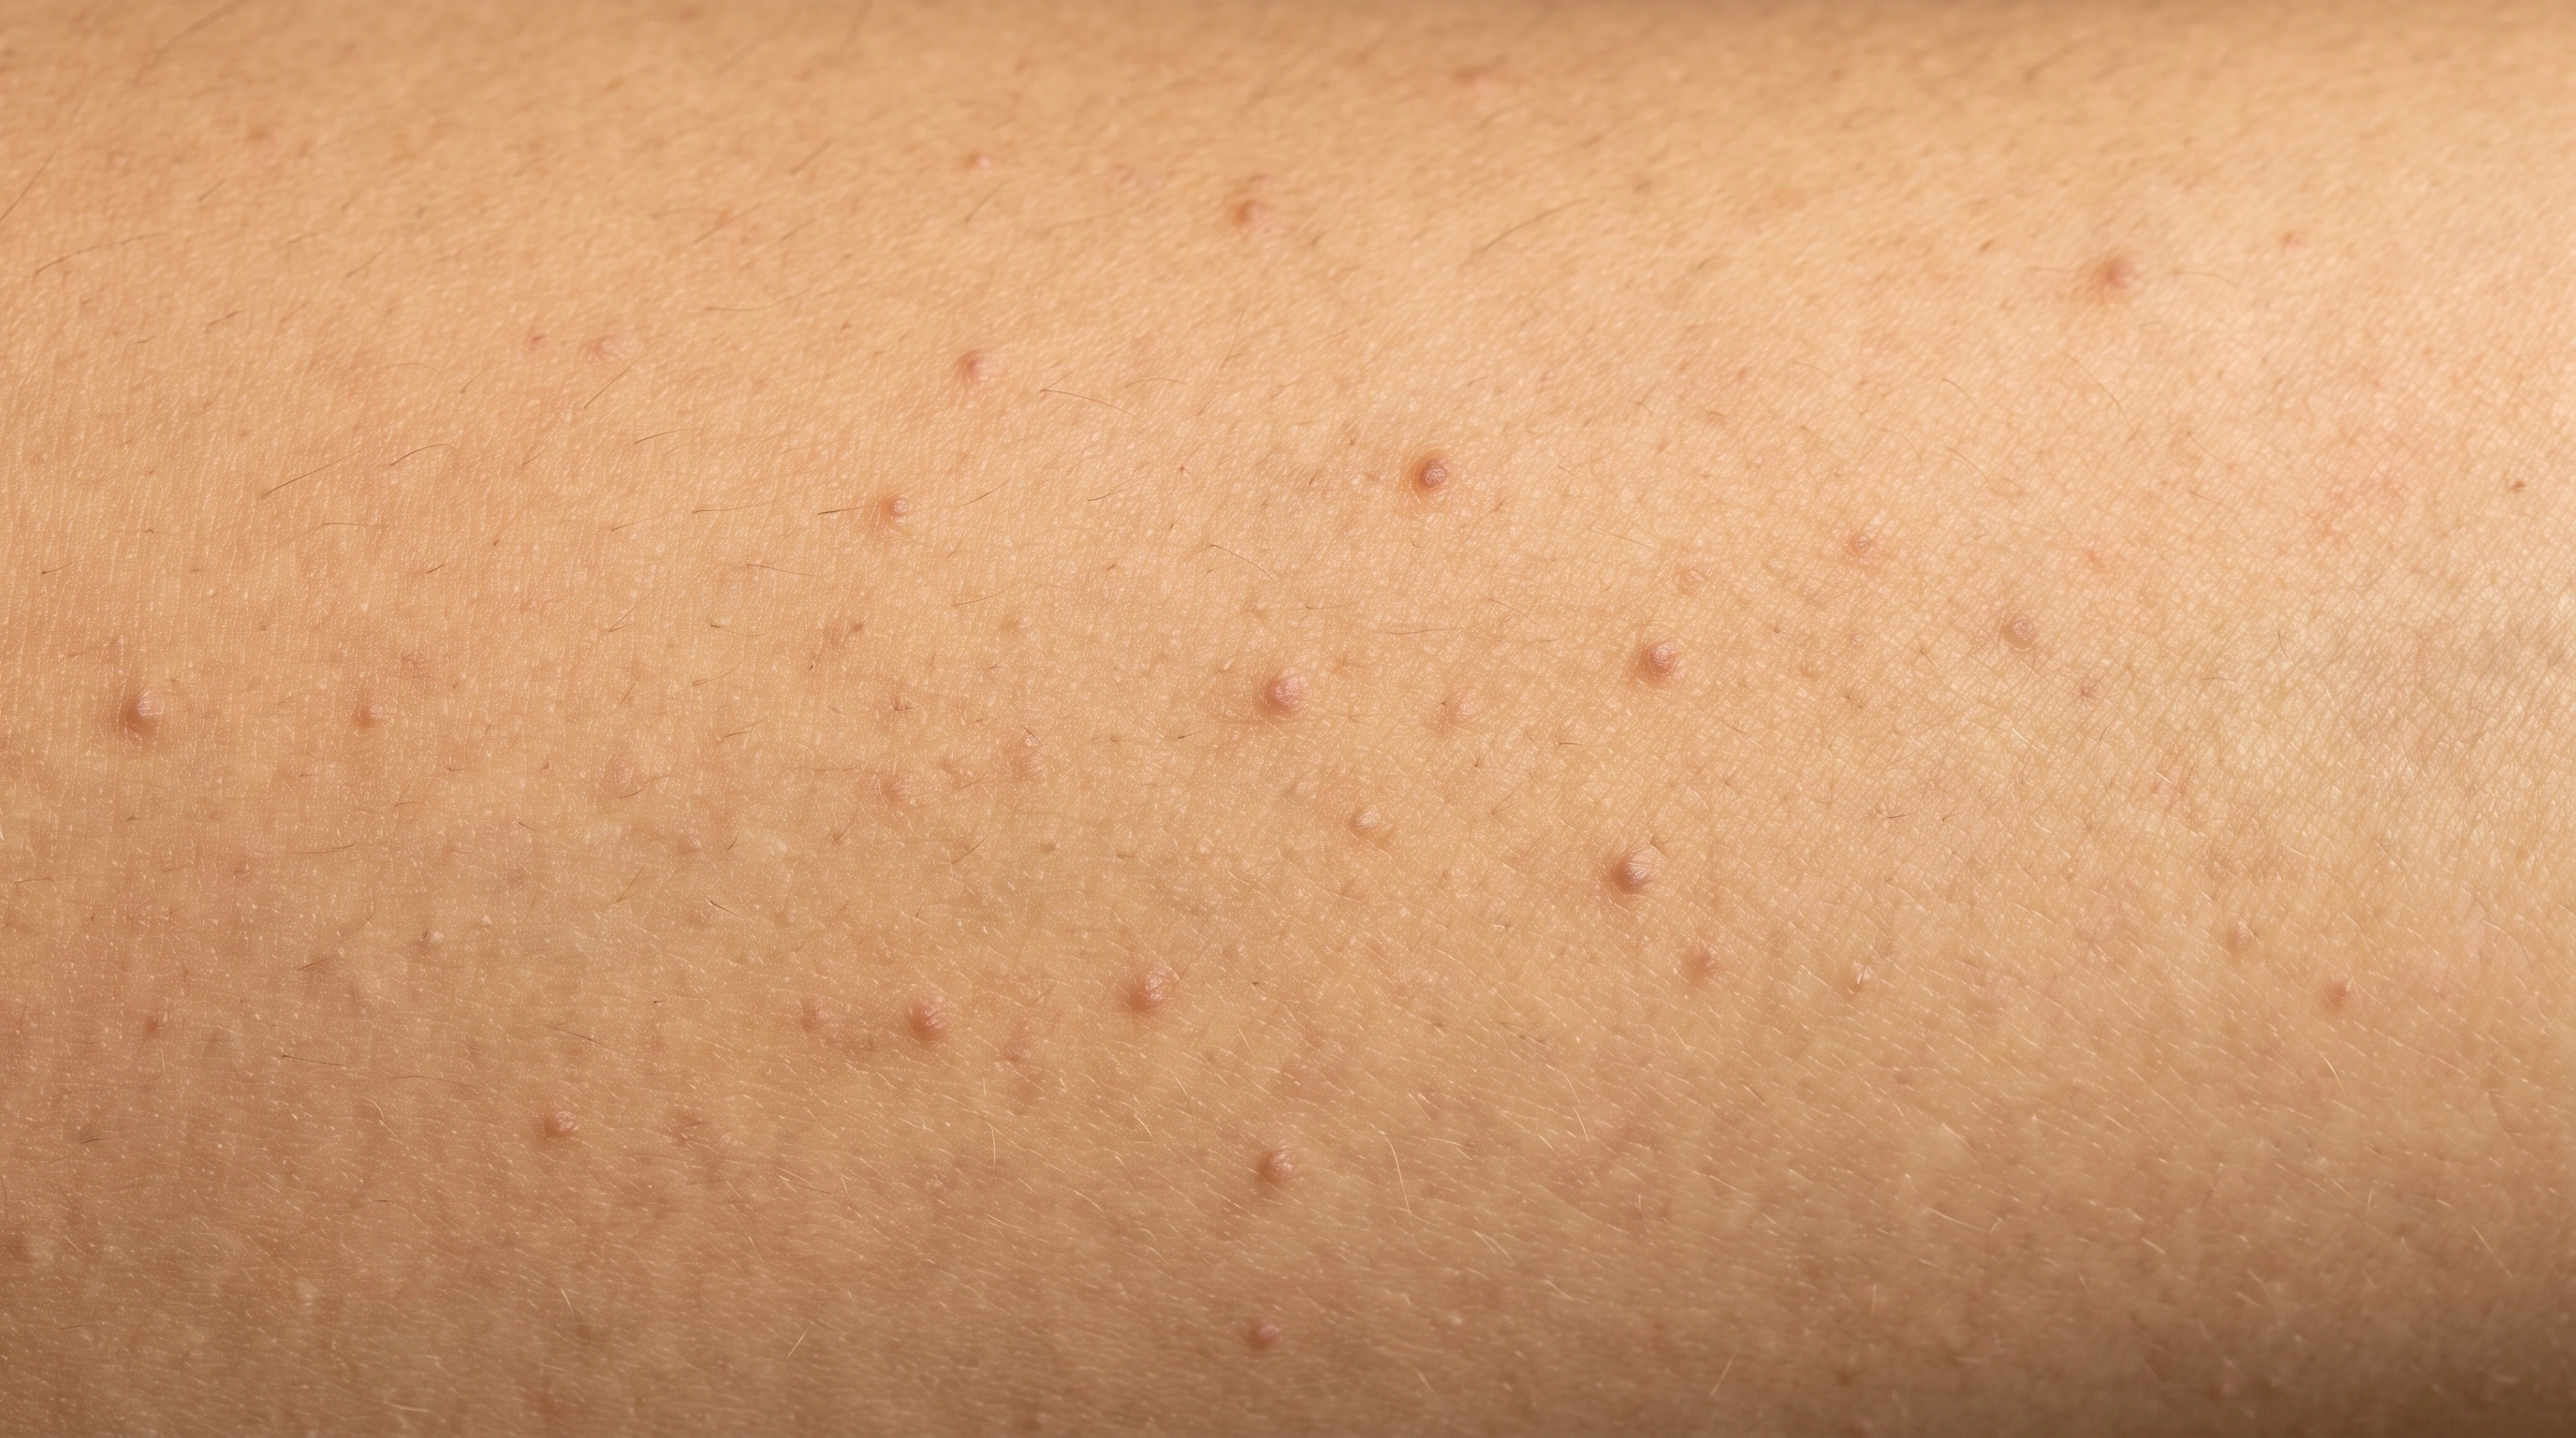
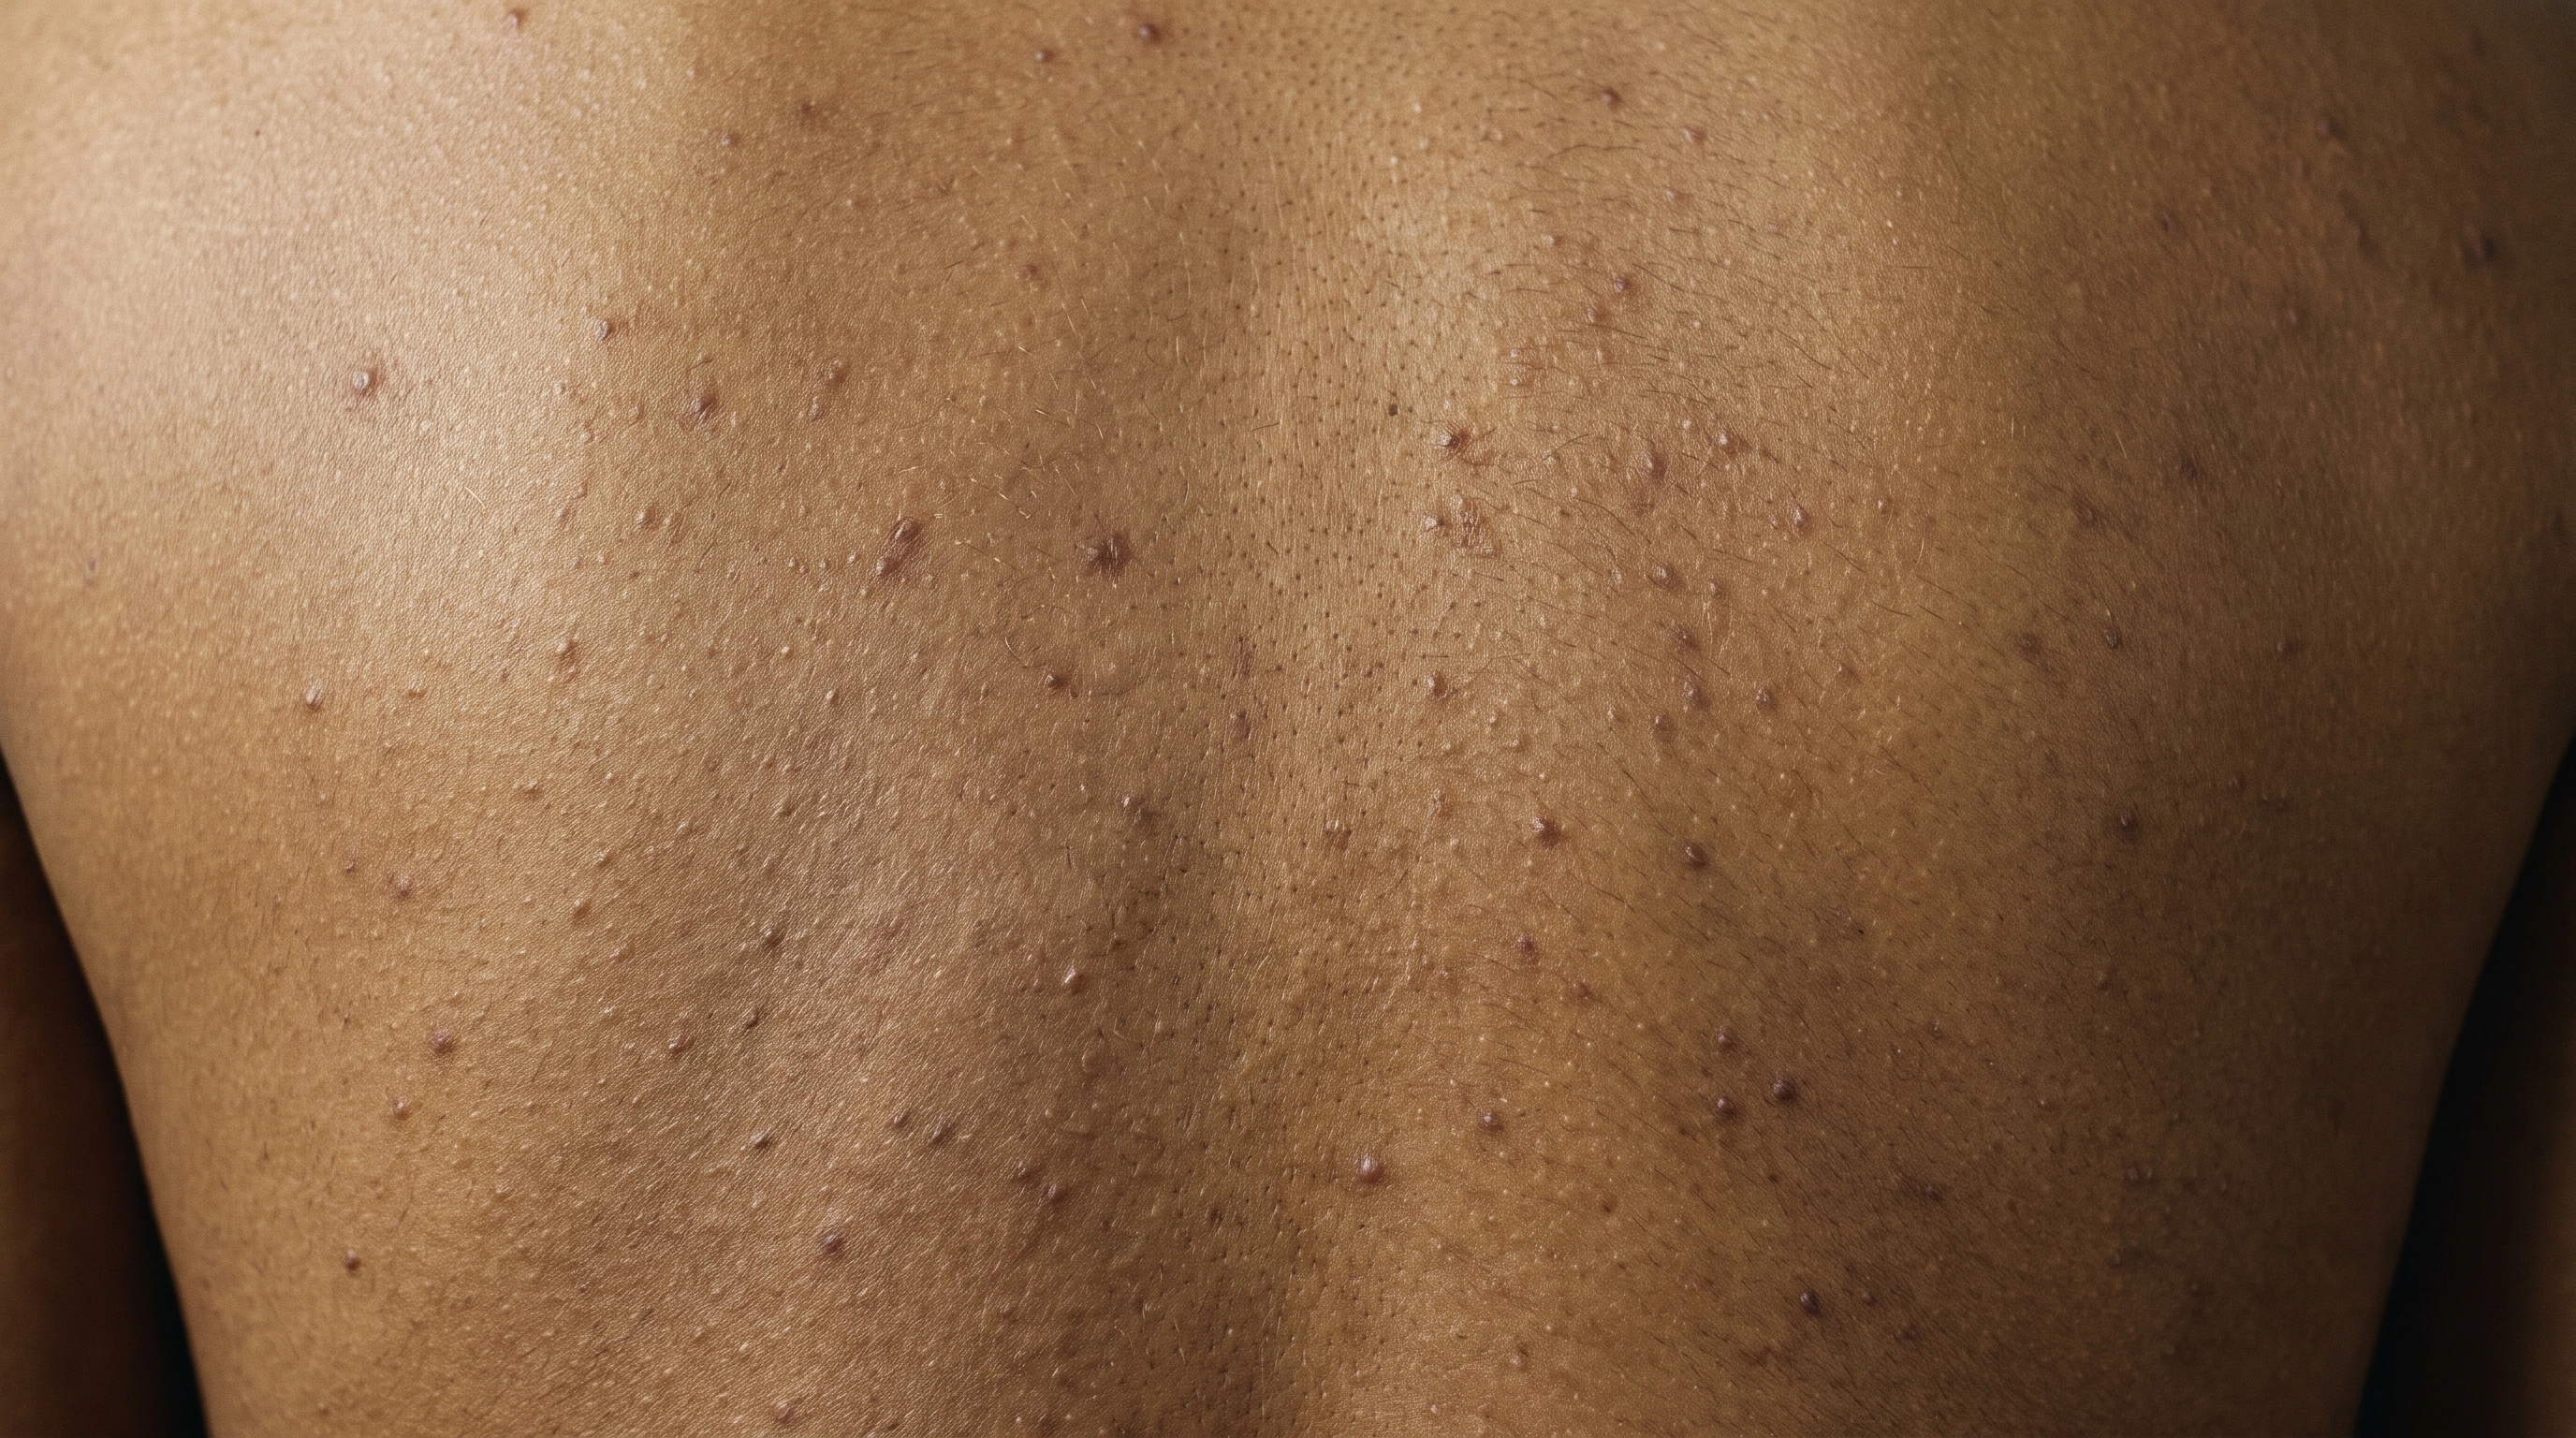
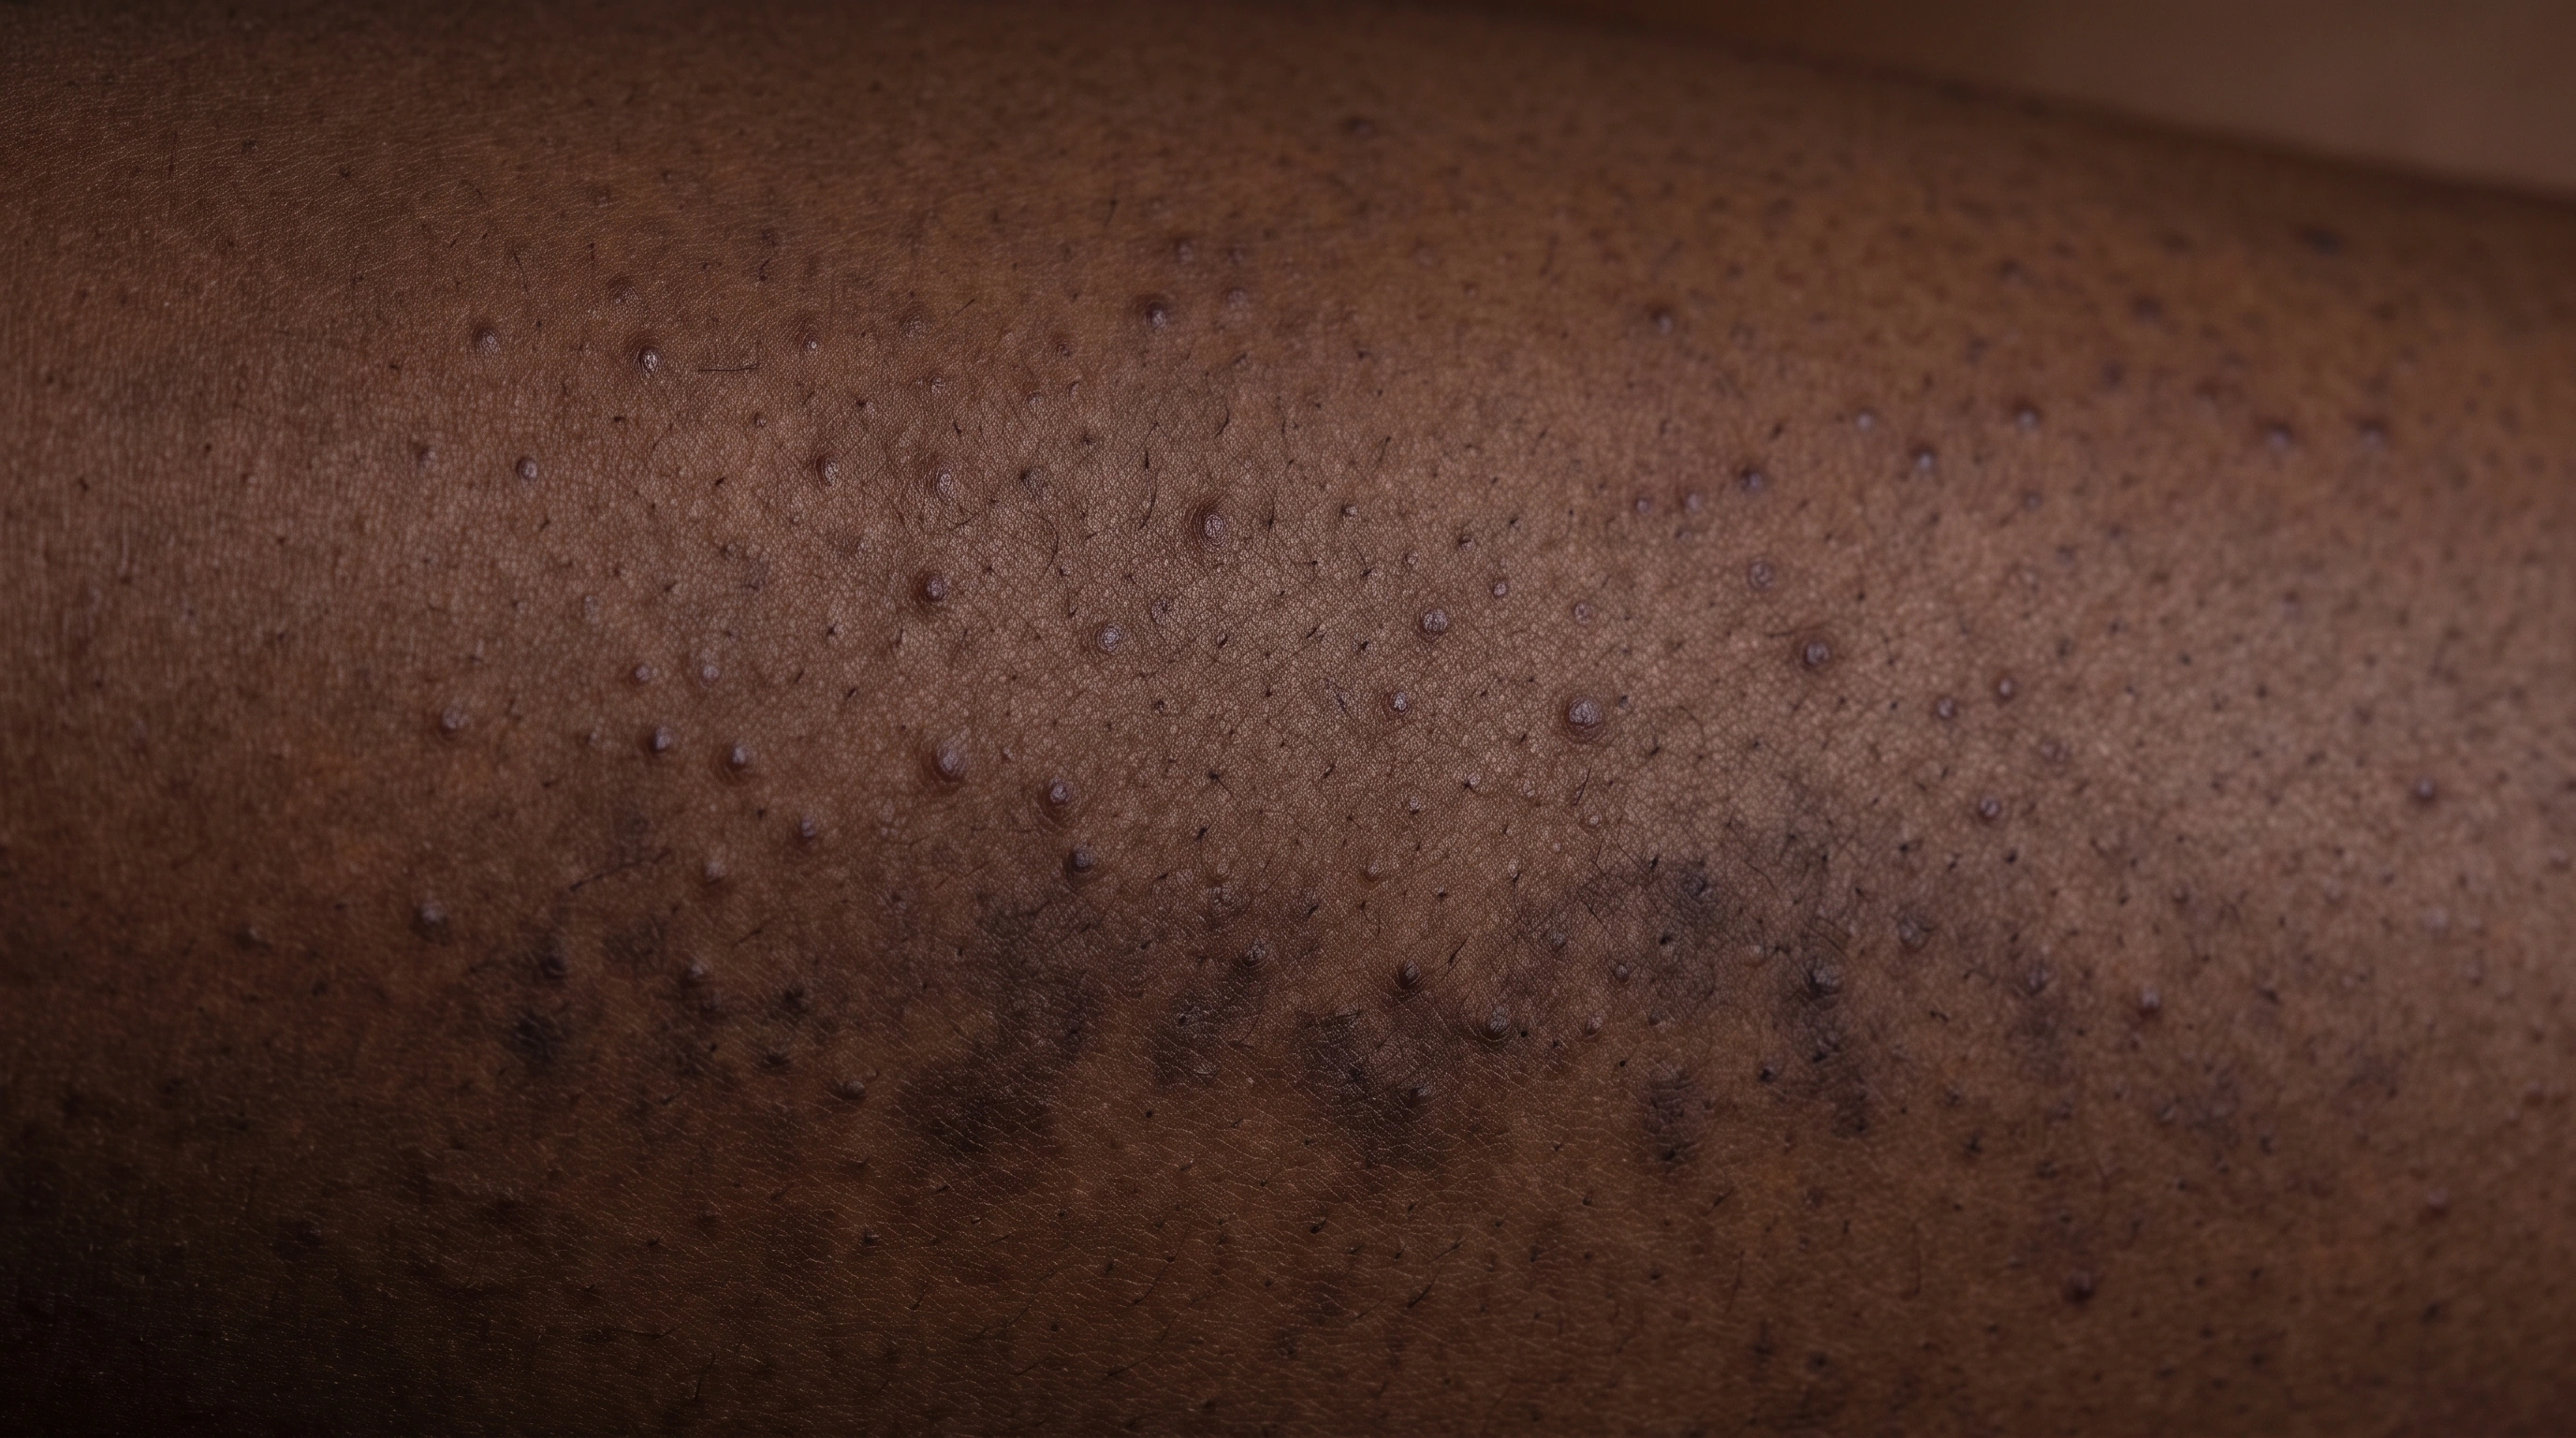


Oil and shed skin cells can block a hair follicle, changing the environment inside the pore. Bacterial activity and the immune response contribute to inflammation, swelling and tender spots.
Malassezia yeast can overgrow inside hair follicles and trigger inflammation. This produces similar-looking itchy bumps and differs from the plugged pores that form blackheads and whiteheads.
Acne. Acne Often in teens Often begins in the teen years; acne can continue or first appear in adulthood.
Fungal Acne. Fungal Acne Often teens and young adults Malassezia folliculitis is more common in adolescents and young adults, but it can occur at other ages. A new rash after heat, sweating, antibiotics or immune suppression can be a useful clue; timing cannot confirm the diagnosis.
Acne forms when oil and dead skin cells clog pores, acne bacteria grow inside them, and inflammation follows. Hormones that increase oil play a central role.
Oil and dead skin cells block hair follicles. Bacteria within the follicles and inflammation contribute to pimples and deeper spots. Hormonal changes can increase oil production.
Fungal acne is caused by an overgrowth of Malassezia yeast inside hair follicles. The yeast normally lives on skin but grows too much in warm, oily, sweaty conditions.
An overgrowth of normally present Malassezia yeast within follicles, followed by inflammation. Malassezia normally lives on skin. Finding surface yeast or noticing itch alone does not confirm that it is causing the rash.
Acne often runs in families. A parent with severe acne raises the chance of severe acne.
Acne can run in families. A close relative with deep, painful acne increases the chance of developing that pattern.
This is not usually considered an inherited disorder. Oily skin and other individual factors can influence susceptibility.
Evidence labels come from each condition’s own treatment list.
The strongest thing you can buy without a prescription, and the best first move for most acne. It unclogs pores before they inflame, which is why it prevents spots rather than treating them.

Kills the bacteria involved in inflamed spots, and is the one thing that stops acne bacteria becoming resistant to antibiotics. Lower strengths work about as well as higher ones and sting less. It bleaches towels and pillowcases.

Works on the spot and the mark it leaves at the same time, which makes it useful on deeper skin tones. It is also one of the few acne treatments considered safe in pregnancy.

Gets inside the pore and loosens the plug, so it suits blackheads and whiteheads more than deep spots. Gentler than a retinoid, and weaker than one.

Sold heavily for acne, and the evidence for clearing spots is thin. It is genuinely useful for the marks left behind and for tolerating stronger actives - just not as the treatment itself.
An old treatment, usually a mask or a spot dab, that dries the surface of a spot and mildly loosens plugs. It is gentle enough for skin that cannot tolerate benzoyl peroxide or a retinoid. It smells, and it is weaker than everything above it on this list.

A 5 percent gel reduces inflamed spots in small studies, more slowly than benzoyl peroxide does. Neat oil straight from the bottle is a common cause of an itchy rash, so buy it already diluted. It is a reasonable extra rather than something to build a routine on.
It has some effect on Malassezia, which is why a few people improve partially on it and then stall. It is not the right tool here, and used as a wash it can leave the chest and back dry and irritated. If it half-works, that is a hint to switch to an antifungal wash rather than to use more of it.
It works by clearing blocked pores, and this is not a blocked-pore condition, so it does not act on the yeast. Some people find a wash mildly helpful for the texture. It will not clear the bumps, and scrubs and brushes usually make an irritated chest and back angrier.
A sulfur wash or soap has some activity against this yeast and is an option if the antifungal shampoos are not tolerated. The evidence in fungal acne specifically is thin. It smells and can be drying on the chest and back.
Widely suggested online for fungal acne and not well studied in it. It irritates inflamed skin easily, and it is a common cause of allergic reactions on the chest and back. A proven antifungal wash costs about the same and is available without a prescription.

The main over-the-counter treatment, used as a body wash rather than for hair. Lather it over the chest, back, shoulders and hairline in the shower and leave it on several minutes before rinsing, daily for two to four weeks. Rinsing it straight off is the most common reason it seems not to work.

An anti-dandruff shampoo used the same way, lathered on the affected areas and left several minutes. A reasonable alternative if ketoconazole irritates or is hard to find. It can be drying and can discolor light-colored hair, so keep it on the body.

The gentlest of the three anti-dandruff washes, and the easiest to keep using long term. It is a good choice for maintenance once the bumps have cleared, once or twice a week through the hot months. It is usually a little weaker than ketoconazole for clearing an active crop.

The most studied topical in acne. Stronger than adapalene and more irritating with it, so it is usually the step up rather than the starting point. Not used in pregnancy.

A newer retinoid, and the one specifically tested on chest and back acne rather than just the face. Useful when the trunk is the main problem. Expensive without coverage.
Calms inflamed spots, but should never be used on its own. Guidelines are explicit about this - alone it stops working within months as bacteria adapt, so it is always paired with benzoyl peroxide or a retinoid.

The strongest of the prescription retinoids, and the step to take when tretinoin has stopped making a difference. It is particularly good on stubborn blackheads and whiteheads. It is also the most irritating of them, so it is usually started two or three nights a week. Not used in pregnancy.

Blocks the hormone signal that drives oil production, but only where you put it. It is the first hormonal option that works topically, and the only one that can be used by men as well as women.

Mild on the skin and tends to suit adult women with inflamed spots who cannot tolerate a retinoid. Applied at the same time as benzoyl peroxide it can temporarily stain skin orange, so space them apart.
A retinoid works on blocked pores, and there is no plug to clear here, so it does not treat the yeast. It is often already in use because the bumps were assumed to be acne. It can stay if you also have genuine acne, but it is not what clears this.
A topical antibiotic reduces the bacteria that compete with the yeast, so at best it does nothing here and at worst the bumps get denser. Skin that gets worse rather than better on an acne antibiotic is one of the strongest clues that this is fungal acne.

Ketoconazole 2% cream. The prescription strength, used as a cream on limited areas such as the jawline, forehead or hairline, or as a shampoo on the body. It is the usual next step when the over-the-counter 1% wash has not been enough. A cream is impractical for a whole back, which is where the wash or tablets take over.
Clotrimazole cream. An older antifungal cream, applied twice a day to small patches. It works against this yeast and is inexpensive and widely available. Like any cream, it only suits areas you can realistically cover, so it is a jawline and hairline option rather than a chest and back one.
Ciclopirox cream or shampoo. Another antifungal option, used when ketoconazole has irritated the skin or has not worked. There is less published evidence in Malassezia folliculitis specifically than for ketoconazole. It is used the same way, with the shampoo left on for several minutes.

Brings widespread inflamed acne down quickly, and is meant to be used for three to four months, not indefinitely. Always alongside a topical, which is what carries on once the tablets stop.
The only acne treatment that often produces lasting clearance after the course ends. What it costs you is months of dry lips and skin, blood tests, and strict pregnancy prevention. For acne that scars, that trade is usually worth making early rather than late.

For the pattern rather than the individual spot - deep jawline acne in adult women that flares with the cycle. It works slowly, over three to six months, and can be continued long term. Not used in pregnancy.

Lowers the hormone signal driving oil production across the whole body, so it suits acne on the chest and back as well as the face. Takes about three months to show, and carries a small clot risk that needs weighing up.

Another tetracycline antibiotic for widespread inflamed acne, used the same way as doxycycline: three to four months, always alongside a topical. It is usually kept as the second choice, because it carries rarer but more serious side effects, including a blue-gray skin discoloration with long use.
A narrow-spectrum antibiotic designed specifically for acne, so it disturbs gut bacteria less than doxycycline. One tablet a day, still meant for three to four months and still alongside a topical. It works about as well rather than better, and it is considerably more expensive.
An antibiotic prescribed for acne is one of the most reliable ways to make this worse, because it clears the bacteria that hold the yeast in check. A crop of itchy bumps appearing a few weeks into or after a course is a classic history. It is not a treatment for fungal acne.

The tablet most often used for stubborn or widespread cases, usually for one to three weeks. It clears extensive chest and back involvement far more reliably than a wash can. It interacts with a long list of other medicines, so the prescriber checks what else you take first.

The other antifungal tablet used here, often as a weekly dose for a few weeks. It suits people who cannot take itraconazole. Tablets clear the yeast but do not change the heat, sweat and occlusion that brought it on, so a maintenance wash is usually continued afterwards.

The antifungal tablet used for nail and foot infections, and it is a poor choice here. Malassezia is not reliably killed by it at the doses used by mouth. If an antifungal tablet is being considered, itraconazole or fluconazole are the ones with evidence in this condition.
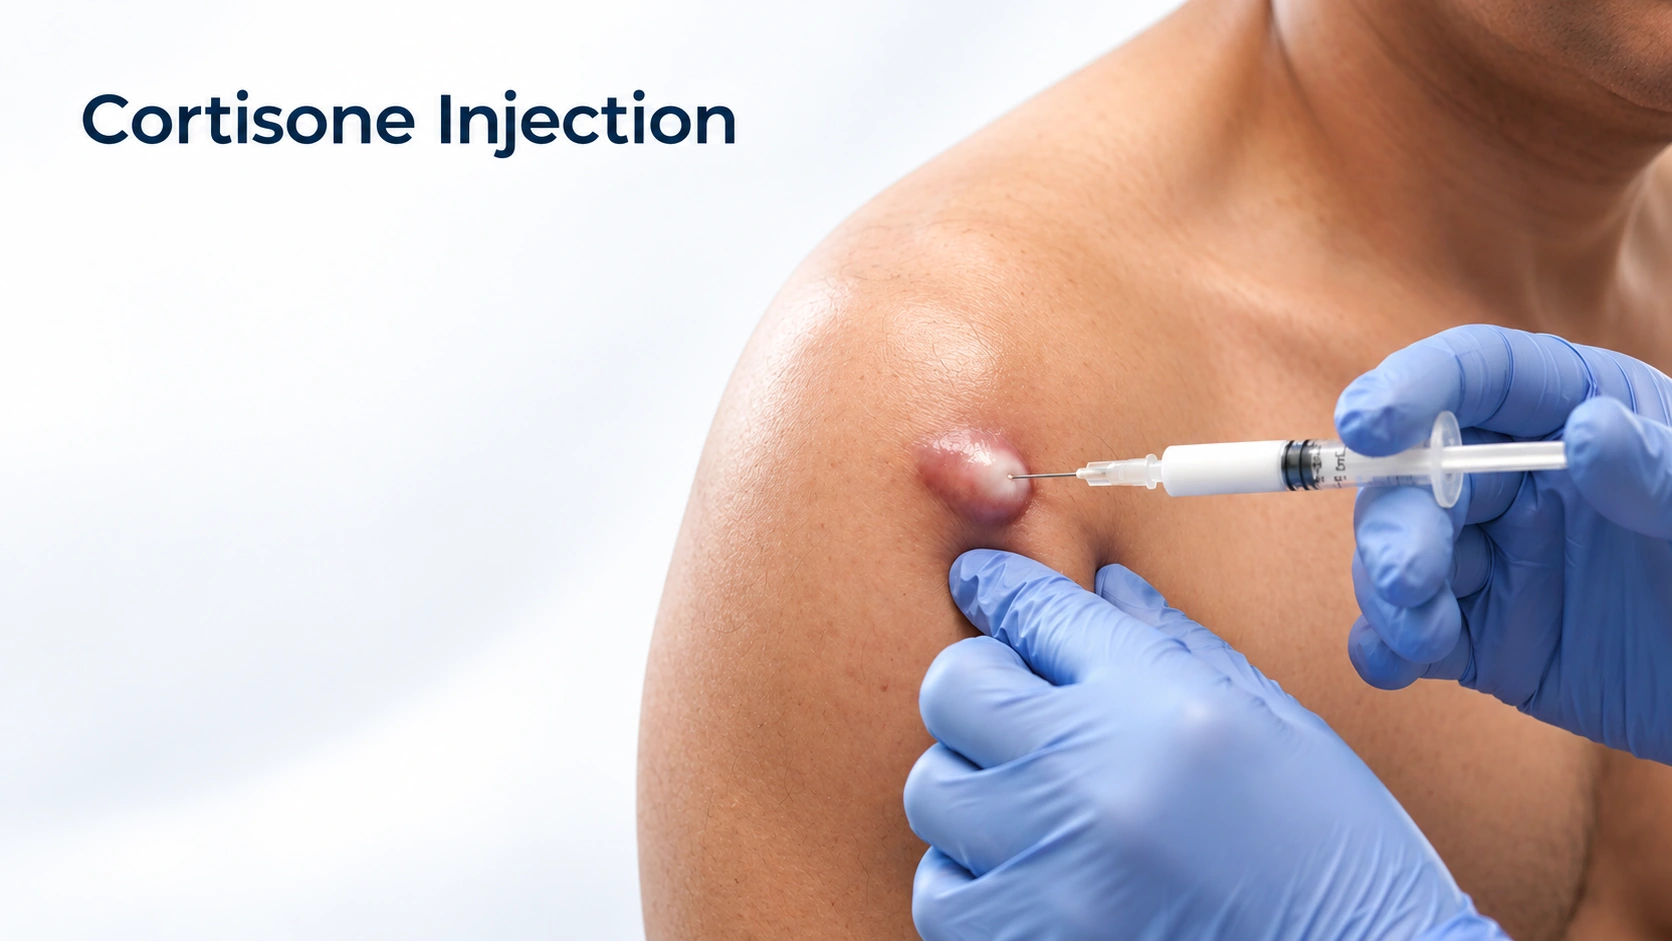
Deals with one stubborn painful lump, not the condition. It settles in a day or two and is the safe alternative to squeezing it. It does nothing to prevent the next one.
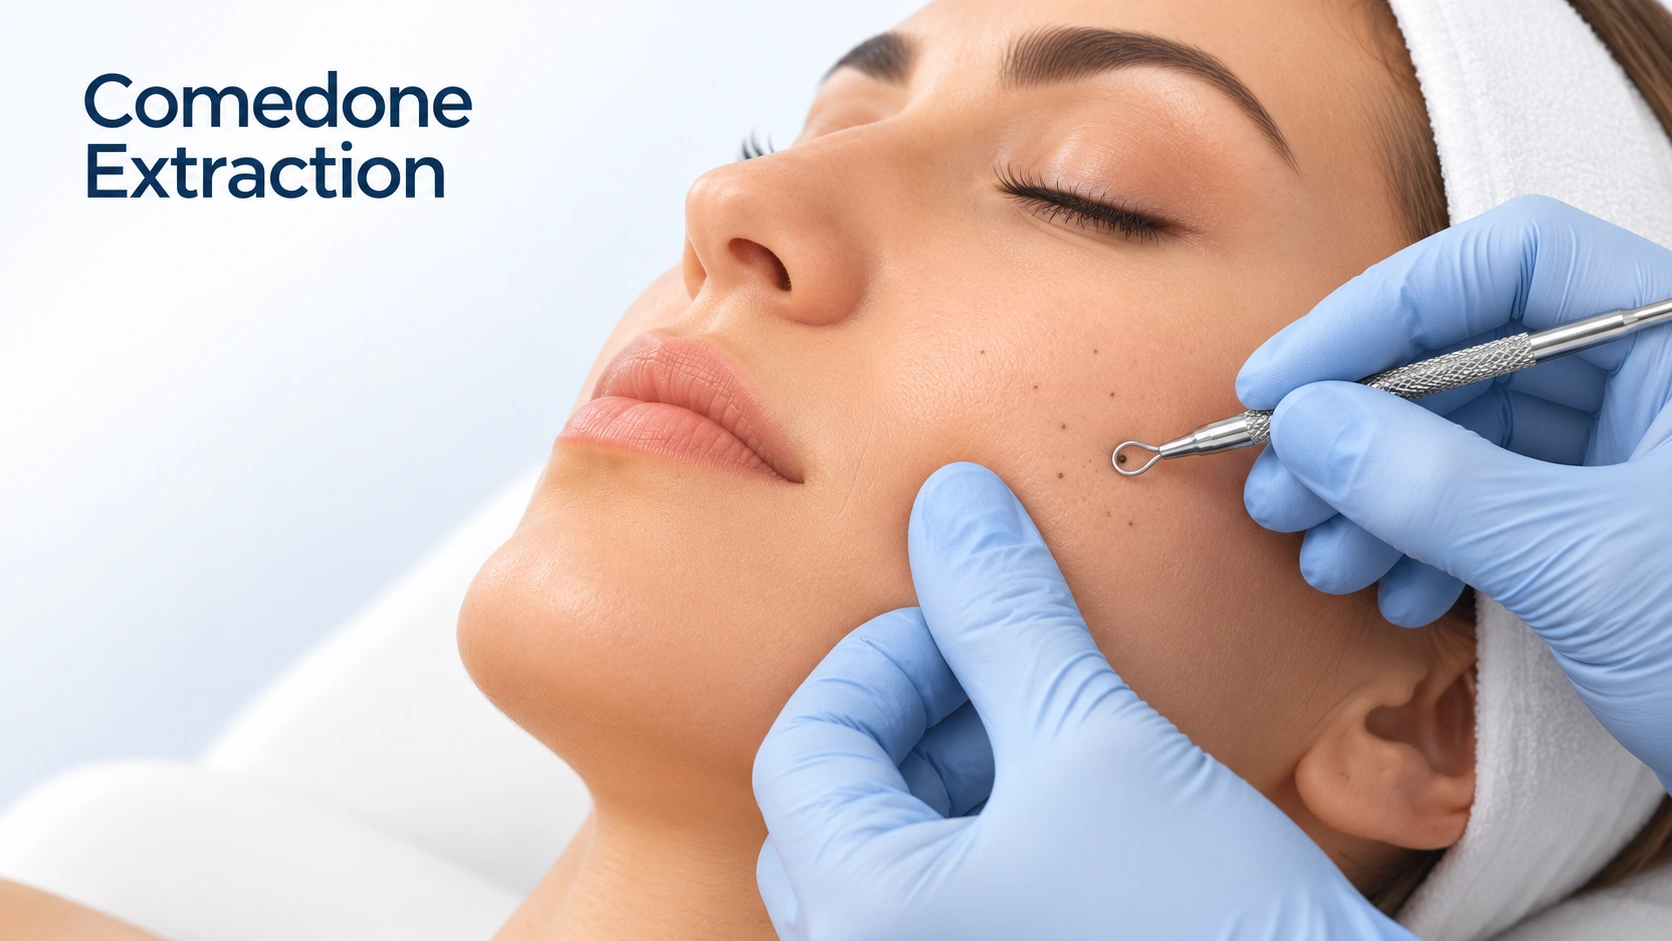
Clears blackheads that are already there, quickly and visibly. It does not stop new ones forming, so it is an add-on to a retinoid rather than a substitute for one.
Modest benefit for clogged pores and a better one for the dark marks left behind. Needs repeat sessions, and the benefit fades if the daily treatment stops.
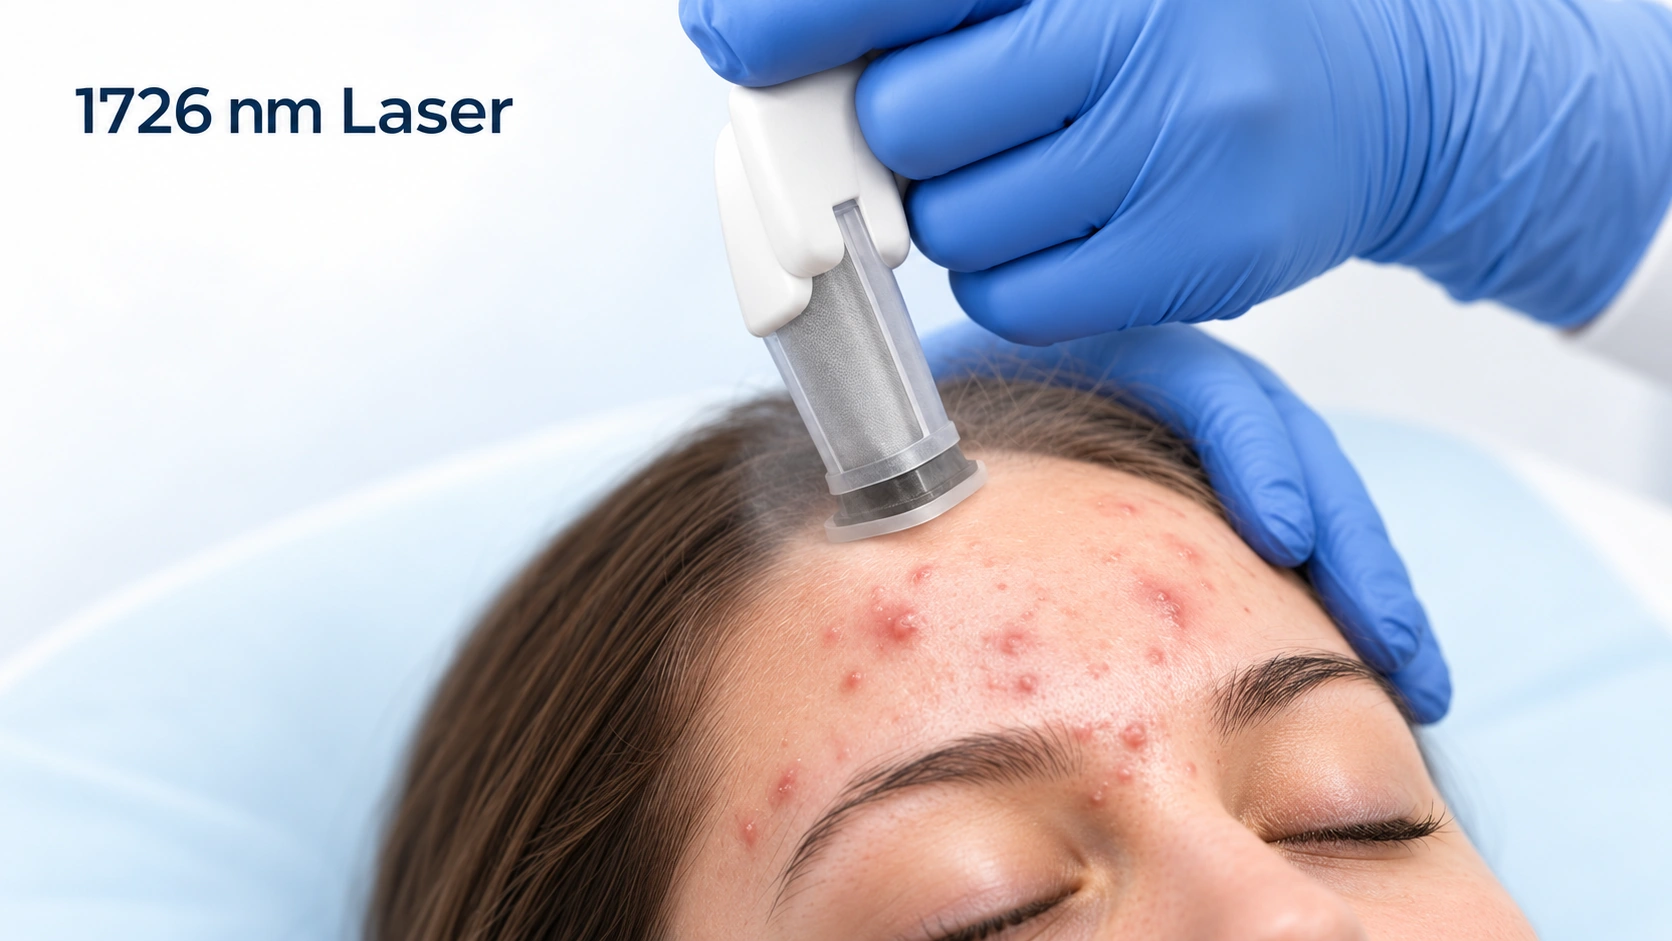
Heats the oil glands themselves, which is a genuinely different approach from everything else on this page. Trial results out to about six months are good, it works across skin tones, and it is expensive and rarely covered. Long-term data is still limited.

Can help stubborn inflamed acne, but the protocols vary widely between clinics, the downtime is real, and the evidence is not strong enough to put it ahead of the options above.
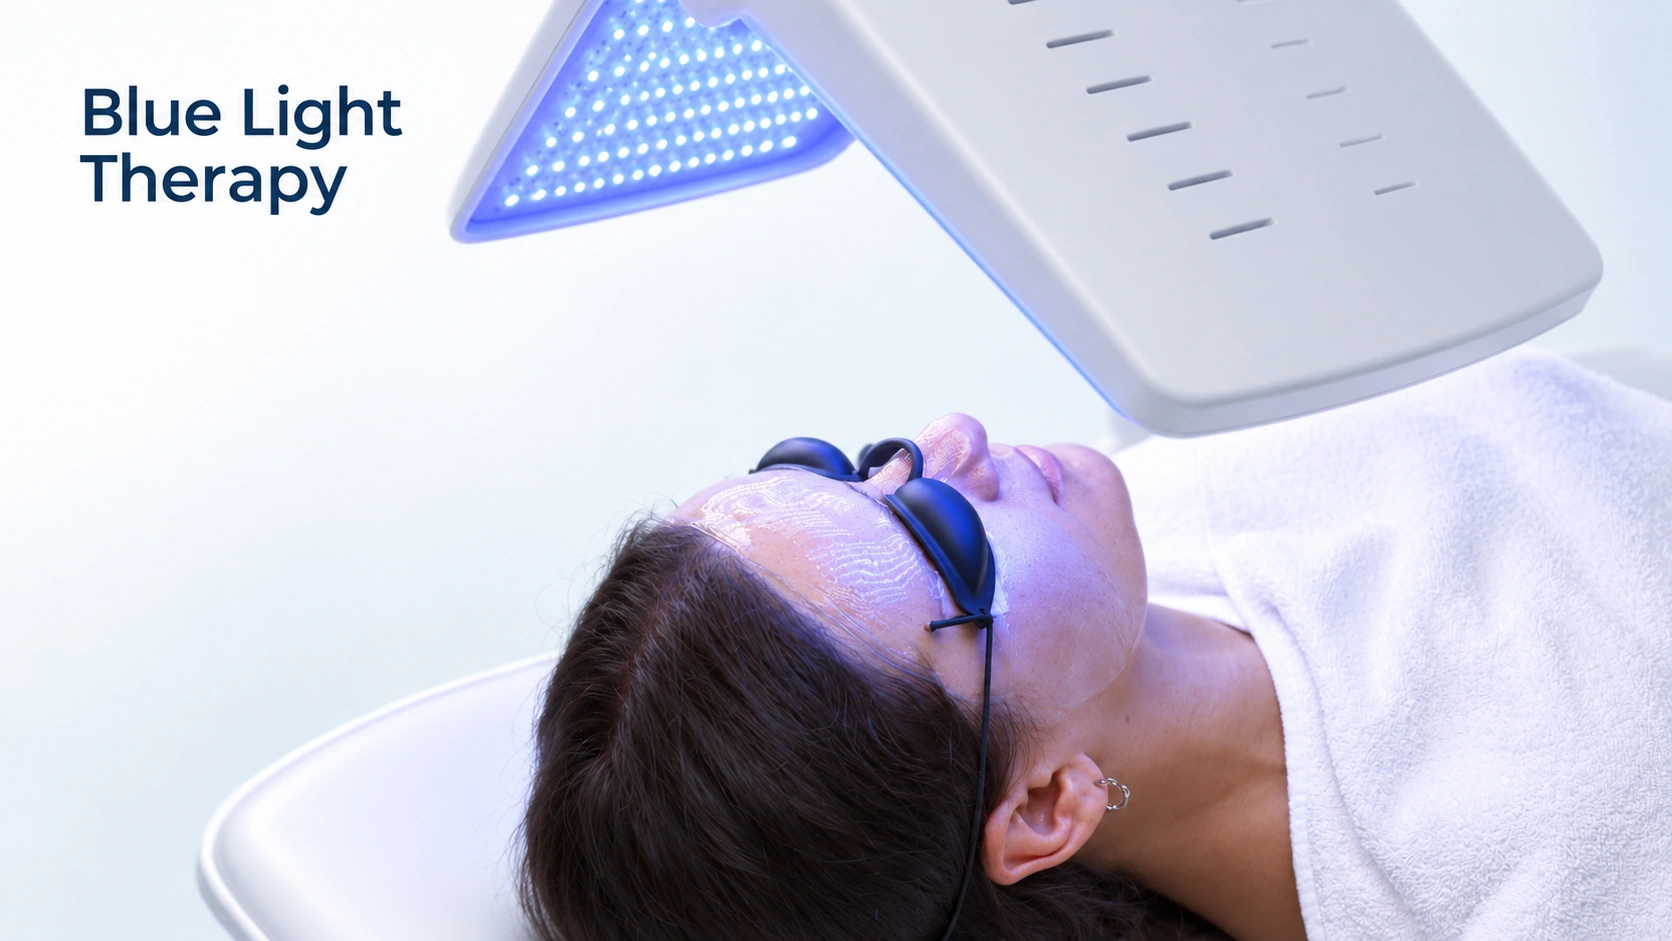
Blue light kills acne bacteria at the surface, so a course can quiet mild inflamed spots for a while. The effect fades within weeks of stopping, and it does nothing for blackheads or deep lumps. In-clinic courses cost far more than a topical that would do more.
Acne is usually controlled rather than permanently cured. Treatment reduces new breakouts, but improvement takes time and maintenance may be needed. Deep or scarring acne deserves early assessment because existing scars may remain after the active spots settle.
Fungal acne appears over a short period rather than gradually, and the right treatment works quickly. It comes back if the conditions return.
Dark marks
Flat brown or violet patches left where a spot was. They are not scars and they do fade, but it commonly takes 6 - 12 months, and sun exposure makes them last longer. These WILL FADE with time.
Redness
Flat pink or red marks left where a spot was, most often on lighter skin. Also not scars. They usually settle on their own, though it can take several months. These WILL FADE with time.
Scars
Permanent dents, pits or raised bumps left where inflammation broke down the skin's structure. Once formed, they can only be improved by procedures. These WILL NOT FADE with time.
Depression and anxiety
Acne can affect self-esteem, confidence and mental health. The link is consistent, and it does not track with how severe the acne looks to anyone else - which is itself a reason to treat it.
Family conflict
This is very common. Acne visits involving a teenager and a parent can sometimes be challenging, particularly when there is ongoing conflict about acne care.
Social impact
People may avoid photos, dating, social situations or activities because of their skin.
The bumps multiply but stay small
They stay small rather than growing. The itch bothers most people more than the bumps.
Seek help for painful deep spots, scarring, persistent breakouts, or an uncertain diagnosis. Earlier treatment can reduce the chance of more scars.
Do not assume eye symptoms are part of acne. They need their own assessment.
<span class="trigger-dash">—</span>
Seek help for a persistent itchy, uniform rash, repeated relapses, or bumps that have not improved with acne treatment. A skin sample may help distinguish causes.
Fever, spreading painful redness, or rapidly worsening bumps need prompt assessment, especially if your immune system is suppressed.
For most people it settles by the mid-twenties. About one in six women still has it into her 30s and 40s, and it can return after pregnancy, after stopping the pill, or with any hormone shift. Controlled rather than cured.
Less than the internet suggests. The evidence points at high-glycemic diets - sugar and refined carbohydrate - and, less consistently, at skim milk. Chocolate and greasy food never held up, and no diet replaces treating the skin.
That is purging. Retinoids speed up clogs already forming under the surface, so weeks of spots arrive at once. It peaks around weeks two to six and settles by week eight. Still worsening past 10 to 12 weeks is irritation, not purging.
No. Squeezing pushes the contents sideways into surrounding skin, turning a spot that would have gone in days into a mark that lasts months, or a scar that lasts forever. A large, painful lump can be injected in clinic instead, and settles in a day or two.
Sometimes, but never alone and never for long. They go alongside benzoyl peroxide or a retinoid, usually for three to four months, then stop while the topical carries on. Alone or indefinitely, they stop working and drive resistance.
Almost all acne is hormonal - hormones drive oil production. The label only matters if it changes treatment: deep spots along the jawline and lower face in an adult woman, flaring before periods, usually respond better to hormonal treatment than to antibiotics.
Three things separate them. Fungal acne itches; acne usually does not. Fungal acne has no blackheads or whiteheads. And the bumps are all the same small size, in a sheet across the chest, shoulders, upper back and hairline, not a mix of sizes on the face. A start after antibiotics, steroids or a hot sweaty stretch adds to the case.
Yes, often. Many people have ordinary acne on the face and Malassezia folliculitis on the chest and back, treated in parallel. A routine aimed only at acne leaves half the problem untouched.
No. The yeast already lives on almost everyone's skin. Nobody gave it to you and you cannot pass it on.
The idea rests on something real — this yeast cannot make its own fats and takes them from its surroundings. But the ingredient lists online are more confident than the evidence. Avoid heavy oils, butters and occlusive products on the affected areas while it is active, and treat the yeast directly rather than rebuilding a routine.
Because the conditions return — heat, sweat and occlusion, usually every summer. That is not treatment failure. Most people who stay clear use the antifungal wash once or twice a week through the warm months.
Scars are uncommon. Flat dark marks are very common, and because the bumps arrive in large numbers they cover a wide area and take months to fade, particularly on deeper skin tones. Not scratching and treating early reduce them most, and daily sunscreen helps them fade faster.
Sources