
Psoriasis
Clears moderate to severe plaques.
Sotyktu: A once-daily tablet for moderate to severe plaque psoriasis. It blocks TYK2, an enzyme inside immune cells, and is taken by mouth rather than injected. Vtama: A once-daily steroid-free cream for plaque psoriasis. It can be used anywhere on the body, including the face and skin folds, and some people stay clear for months after stopping.


Choose for moderate to severe psoriasis when you want a once-daily pill rather than injections.
Choose for psoriasis or eczema anywhere on the body when you want a once-daily non-steroid with no time limit.
Can you take them together?
Vtama can be used on remaining plaques while taking Sotyktu. They do not interact.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.




Inhibits TYK2: Keeps this signaling enzyme in an inactive state. Reduces immune messages: Limits signals from IL-23, IL-12, and type I interferons. Helps psoriasis settle: Inflammation and plaque buildup gradually decrease.
Deucravacitinib allosterically binds the regulatory domain of TYK2. The exact link between biomarker changes and clinical effects is not fully known.

Activates AhR: Binds a receptor that helps regulate skin-cell behavior. May rebalance inflammation: Changes in immune signaling may help calm skin. May support the skin barrier: Changes in barrier proteins may help skin function.
Tapinarof is an AhR agonist; the specific therapeutic mechanisms are unknown. Anti-inflammatory and barrier effects are proposed from experimental evidence and are explicitly qualified.
Dosing is as simple as it gets for a systemic drug. No loading dose, no build-up, no weight adjustment.
Starting dose: 6 mg once a day from day one. Full dose from the start.
Going up: No higher approved dose for psoriasis. If it is not working, the conversation is about switching.
Usual dose: 6 mg once a day, long term.
Kidney function: No dose change for most levels of reduced kidney function.
Severe liver disease: Not recommended, so tell your doctor about any liver condition before you start.
When to Apply: Once a day, at whatever time you will remember. A thin layer over the plaques, rubbed in. It can go on the face, eyelids, armpits, groin and under the breasts, which sets it apart from a steroid. Wash your hands afterwards unless your hands are being treated.
How to Start: Once daily from day one, on every plaque you want treated. No ramp-up, and no cap on how much of the body can be covered, so it does not have to be rationed the way a strong steroid does.
If It Irritates: Small red bumps around hair follicles are the most common problem and usually appear in the first few weeks. Most are not infection and often settle without stopping. Stinging or a rash where you applied it is the other pattern, and that one is worth showing your doctor, because a true contact allergy means stopping.
If It’s Not Working: There is one strength, so there is nothing to increase. Give it a full twelve weeks. If plaques are still thick then, the conversation is about adding something else, phototherapy, or moving to a tablet or injection.
Once a day, at whatever time suits you, with or without food. Pick one time and keep to it, because a daily tablet is easy to lose track of in a way a fortnightly injection is not. Attaching it to something you already do, like brushing your teeth at night, works better than intending to remember.
Swallow the tablet whole with water. Do not crush, split or chew it. If it upsets your stomach, take it with a meal.
Take it as soon as you remember on the same day. If you do not remember until the next day, skip it and take that day's tablet as usual. Never take two in one day. Missing the occasional dose will not undo months of progress, but repeatedly missing them is one of the commonest reasons a treatment looks like it has stopped working.
Everyone is screened for tuberculosis before starting, with a skin test or a TB blood test, and a chest X-ray if positive. Dormant TB is treated first. This applies even though it is a tablet rather than an injected biologic.
Hepatitis B and C are usually checked at the same time.
Liver blood tests are often checked before starting and again if there is a reason to. Some people show a rise in creatine kinase, a muscle enzyme, or in triglycerides, so those may be looked at too. There is no rigid schedule like methotrexate's; how often anything is repeated is your doctor's judgment.
The rest is clinical. Report repeated infections, cold sores that keep coming back, mouth ulcers that will not heal, and unexplained muscle pain. Skin should be checked periodically, as on any drug that damps down the immune response.
No blood tests are required. There is nothing to check on a lab report, which is one of the practical arguments for a topical over a tablet.
Monitoring is a look at the skin and a conversation, usually at about twelve weeks. Two things get asked about: folliculitis, and whether it is a few bumps or enough to be a problem; and whether the treated skin has become itchy and inflamed in a new way, which points to contact dermatitis rather than psoriasis.
Long term there is no organ risk to track and no skin thinning to watch for, so there is no maximum duration. What is genuinely not known yet is what many years of continuous use looks like, because the drug is recent. A common pattern is to treat until clear, stop, and restart when plaques come back.
Approximate windows, not promises.
First doseTaking it: One tablet a day, with or without food.
Weeks 1 to 4Starting: Itch usually eases before the plaques look different. Early side effects show now, most often a cold, a cold sore or a mouth ulcer.
Weeks 1 to 4Starting: Scale and roughness ease before the redness does, often by week four. Folliculitis shows up now if it is going to, usually small tender bumps in hair-bearing areas.
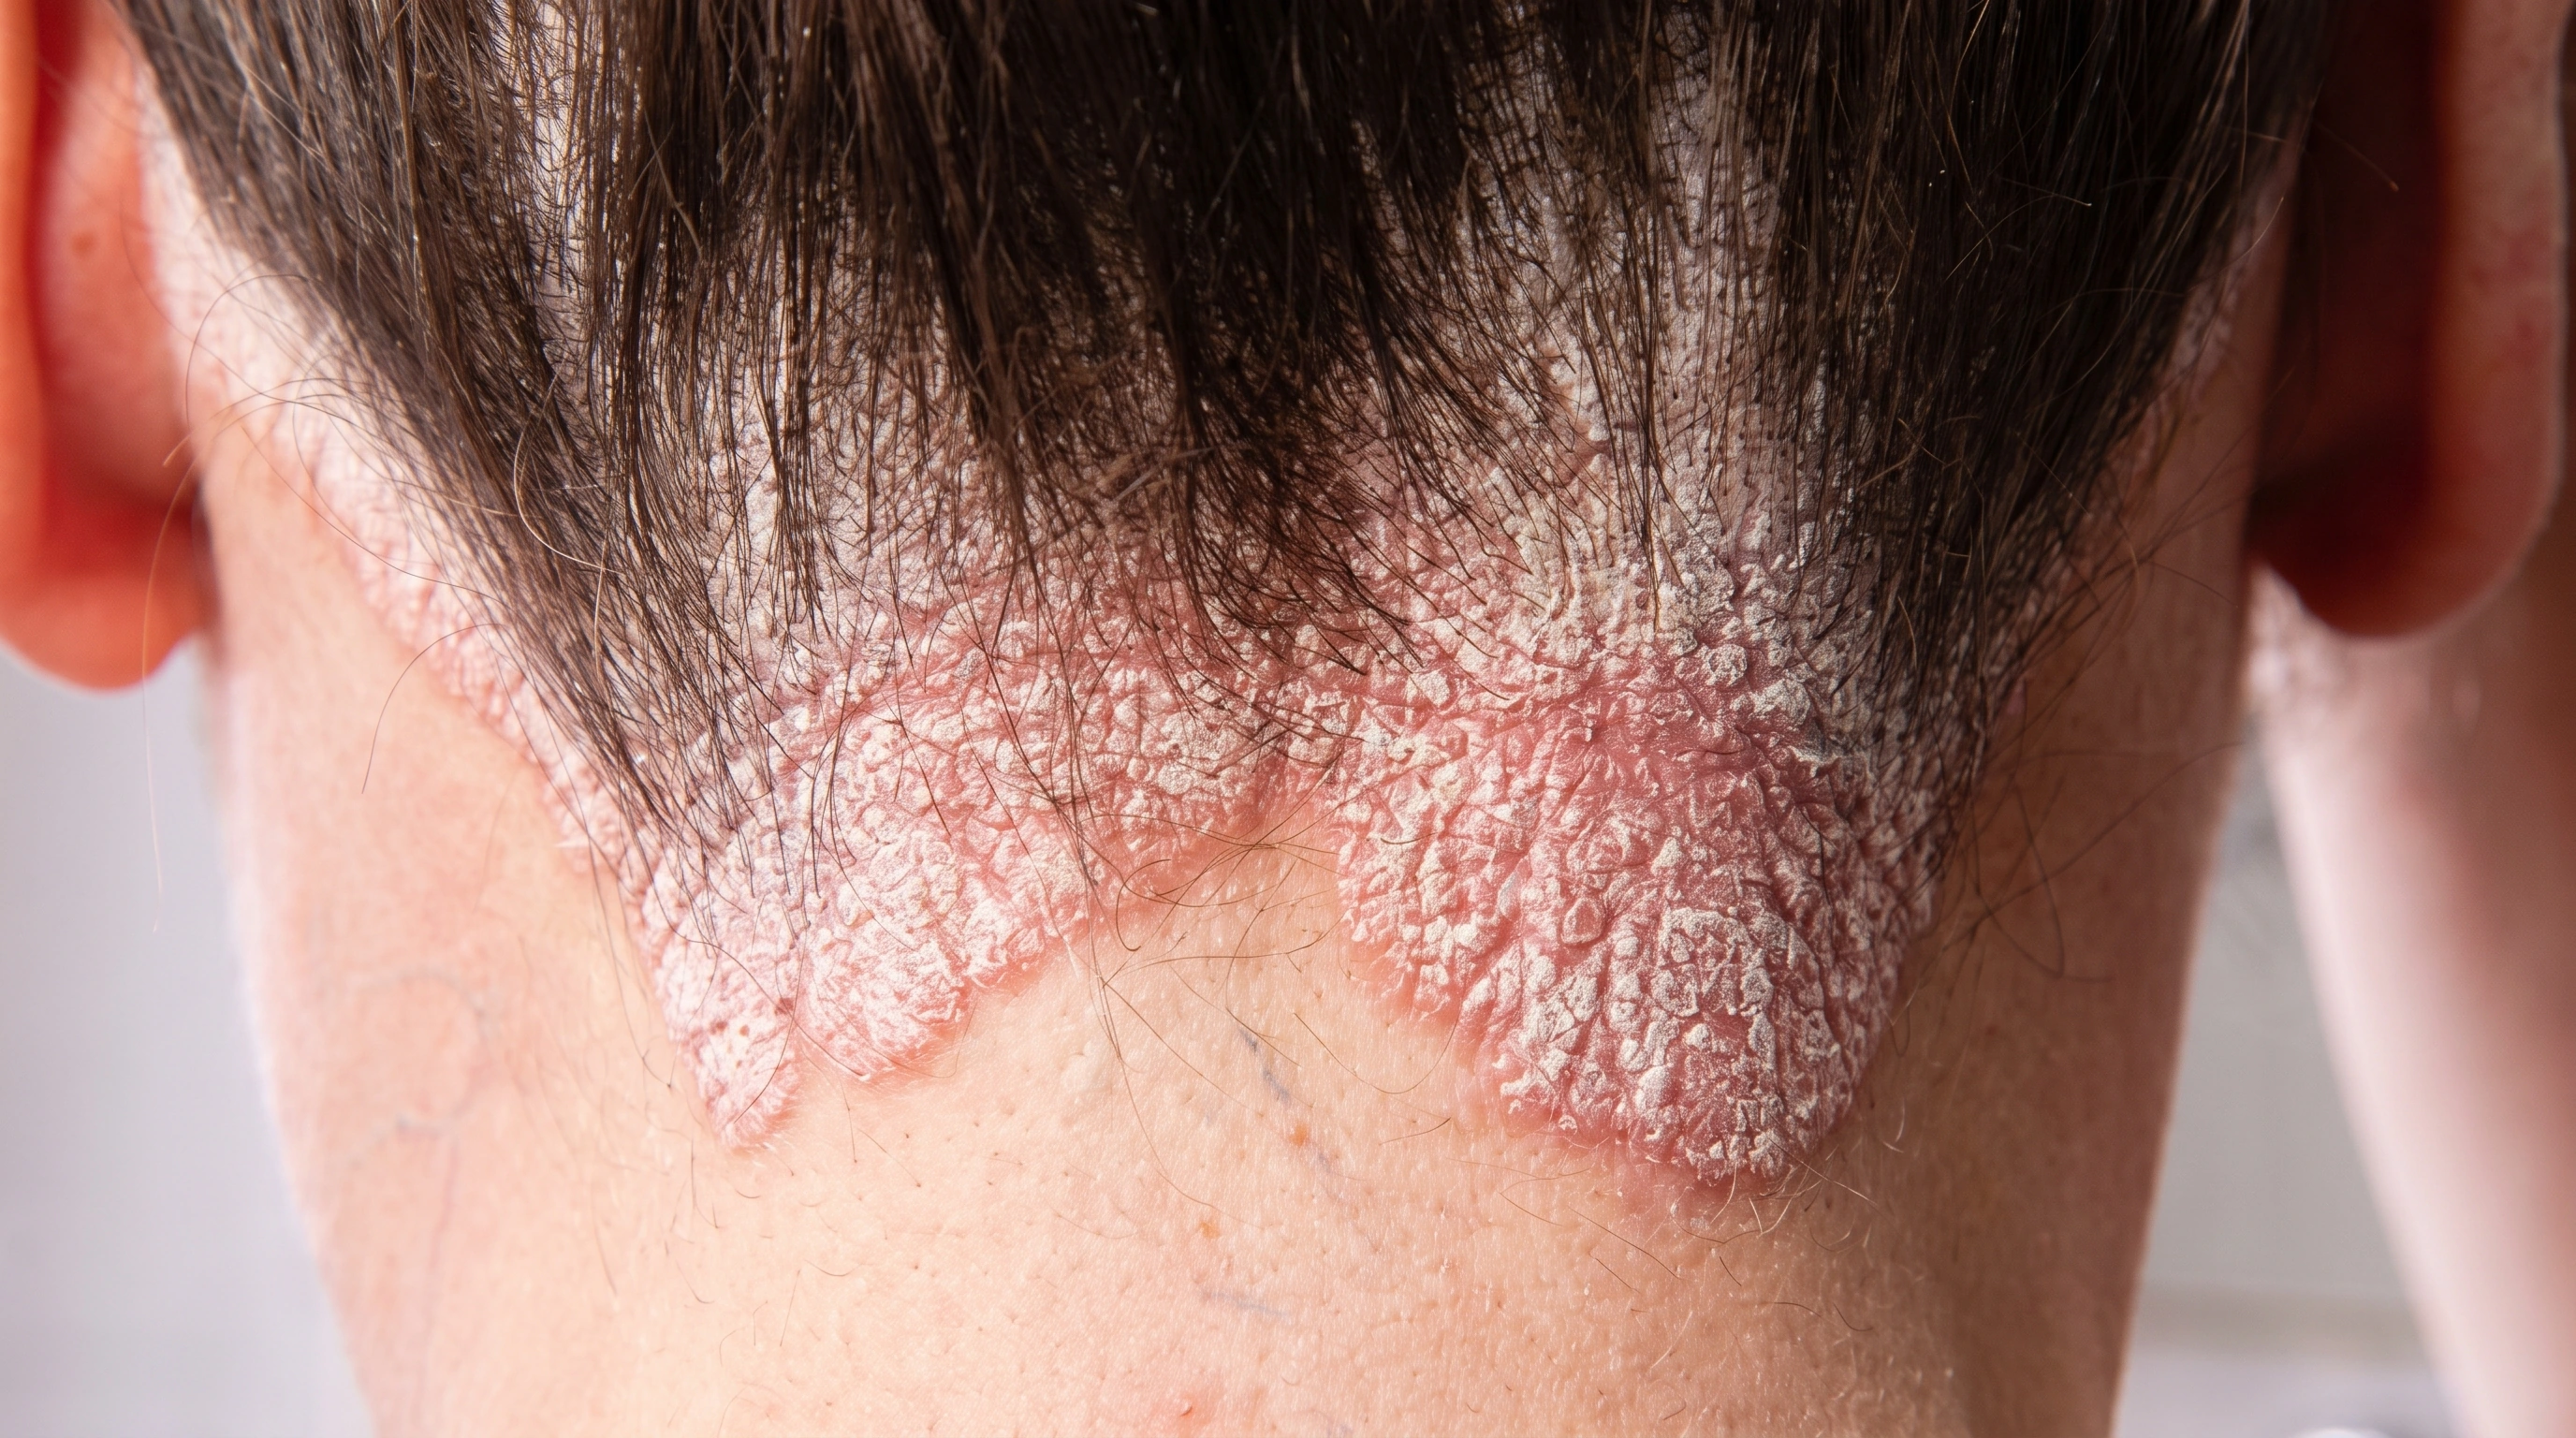
Weeks 4 to 16Working: Scale lifts and plaques flatten steadily. Scalp psoriasis often improves noticeably here, before the trunk.
Week 16Judge it here: Where the trials measured, and the fair point to decide. More than half reached at least a 75 percent improvement in how much skin was involved and how severe it was; a smaller share were clear or nearly clear.
Months 3 to 6Palms and soles: Stubborn on every treatment, slower than plaques elsewhere.
Months 6 to 12Nails: Nails change last, because a nail takes months to grow out. Judge the new growth at the base, not the damaged tip.
Beyond 16 weeksLong term: Responders often keep improving slowly through the first year. Because it is a small molecule, the body does not make antibodies against it, so the gradual loss of effect seen with some injected drugs is not an issue here.
First few minutesApplying it: A thin layer once a day on the plaques.
Weeks 4 to 8Working: Plaques flatten and shrink, and color fades from red toward pink or brown.
Weeks 8 to 12Judge it here: Trials measured their main result at twelve weeks, and many people were still improving then. A meaningful minority reached clear or almost clear skin — a realistic target, not a promise.
After stoppingRemission: Unlike a steroid, it does not usually rebound. People who cleared completely often stayed clear for months before restarting.
Sorted by what to do about them.
Brand only. There is no generic and will not be for years, so there is no cheaper equivalent. The list price is high, in the same range as the injected biologics over a year, which surprises people who assume a tablet must be cheaper.
Almost nobody pays it. What matters is what your plan does, and approval takes paperwork. Prior authorization is close to universal, and most plans want documented failure of something cheaper first: phototherapy, methotrexate or apremilast.
Manufacturer copay cards can bring the monthly cost down to very little on commercial insurance. By law they cannot be used with Medicare or Medicaid. For those plans, or no insurance, the manufacturer's patient assistance program and independent foundations are the usual routes, and the rules change regularly.
One thing in its favor on cost: no infusion visits, no injection training, no cold chain, so the costs around the drug are lower even when the drug is not.
Brand only, with no generic. It is one of the more expensive topicals for psoriasis and costs far more than a generic steroid or generic calcipotriene.
Coverage varies and prior authorization is common; plans frequently want to see a topical steroid, and often a vitamin D analog, tried first. Manufacturer copay cards exist and the terms change, so check the current one.
Because a tube covers only so much, cost climbs quickly with widespread psoriasis, which is one of the main reasons people end up on a tablet or injection instead.
It works on TYK2, an enzyme in the same family, but binds a different part of it and is far more selective. Its label does not carry the boxed warning the JAK inhibitors carry. The distinction is real, not marketing.
On average the injected biologics clear skin more completely. This clears skin well for a lot of people, and it is a daily tablet with no fridge and no needles. Which trade is right depends on how severe your psoriasis is and how you feel about needles.
Tuberculosis and hepatitis before you start, and usually liver tests. After that, testing follows your situation, not a fixed schedule — much lighter than methotrexate monitoring.
Herpes simplex outbreaks and mouth ulcers are commonly reported. Tell your doctor if they are frequent; they can usually be managed without stopping.
No direct interaction, unlike methotrexate. Ordinary drinking is generally not a problem, but confirm with your doctor if you have a liver condition.
Losing response over time is less of an issue than with injected antibodies, since the body makes no antibodies against a small molecule. If it does stop working, the option is switching class, since there is no higher dose.
No. It works on a different switch inside the skin cell, the aryl hydrocarbon receptor. That is why there is no time limit and no skin thinning.
Yes — approved for the face and skin folds, one of its main advantages over a steroid.
Most likely folliculitis — small red bumps around hair follicles where you applied it. The most common side effect in the trials, at roughly one in five people, usually mild, and most carried on.
Give it twelve weeks. Some change usually shows by four.
That is a normal way to use it. In the long-term study, many who cleared completely stayed clear for months, then restarted when plaques returned.
Yes, it is also approved for atopic dermatitis, in adults and in children from age two.






