
Psoriasis
Improves moderate plaque psoriasis.
Otezla: An oral pill for plaque psoriasis, psoriatic arthritis and the mouth ulcers of Behcet's disease. It needs no routine blood tests, and it is gentler and less powerful than the injected treatments. Vtama: A once-daily steroid-free cream for plaque psoriasis. It can be used anywhere on the body, including the face and skin folds, and some people stay clear for months after stopping.


Choose for moderate psoriasis or psoriatic arthritis when you want a pill with no routine blood tests, accepting it's gentler than injections.
Choose for psoriasis or eczema anywhere on the body when you want a once-daily non-steroid with no time limit.
Can you take them together?
Vtama can be used on remaining plaques while taking Otezla. They do not interact.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.


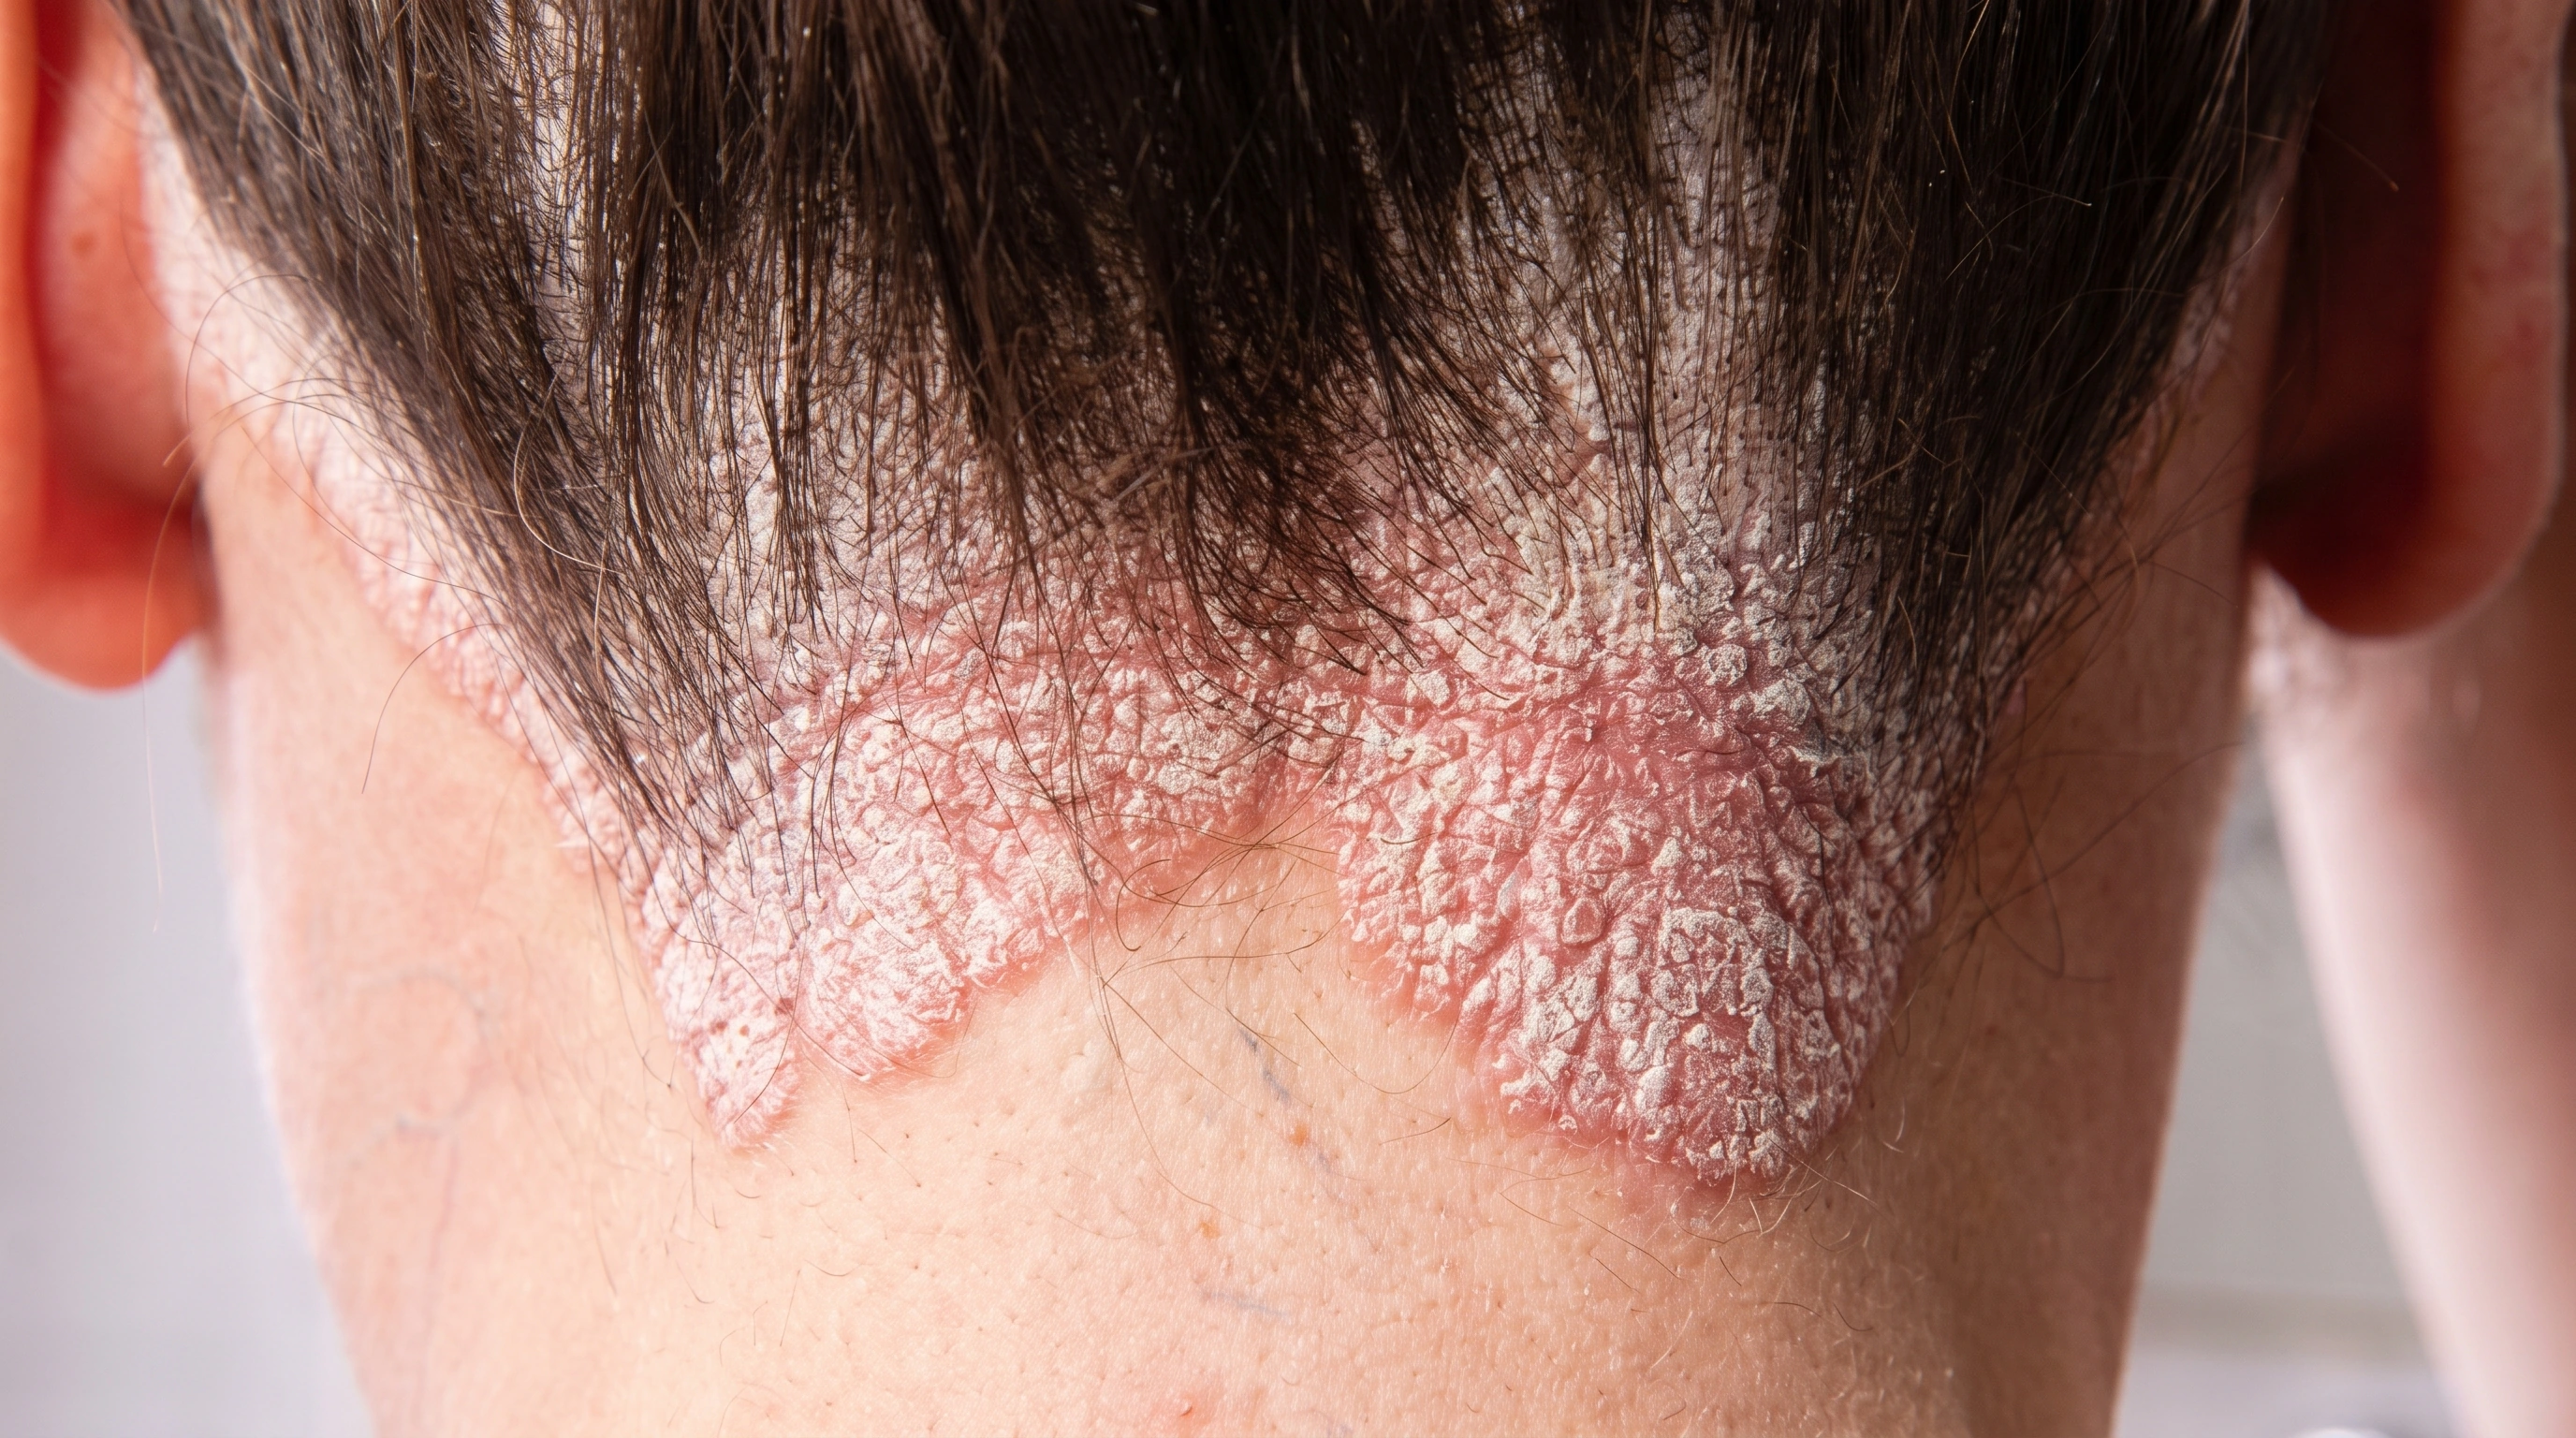



Blocks PDE4: Inhibits an enzyme that breaks down cAMP. Raises cAMP inside cells: Preserves a signal involved in regulating inflammation. Helps inflamed skin settle: Psoriasis plaques become less inflamed.
PDE4 inhibition and increased intracellular cAMP are established. The exact link to clinical improvement is not fully defined; this is a simplified overview, not every downstream pathway.

Activates AhR: Binds a receptor that helps regulate skin-cell behavior. May rebalance inflammation: Changes in immune signaling may help calm skin. May support the skin barrier: Changes in barrier proteins may help skin function.
Tapinarof is an AhR agonist; the specific therapeutic mechanisms are unknown. Anti-inflammatory and barrier effects are proposed from experimental evidence and are explicitly qualified.
Nothing about the dose depends on weight or on how severe your disease is. It is built up gradually only to give your stomach time to settle.
Starting dose: A five-day starter pack, beginning at 10 mg on day one and climbing in 10 mg steps, morning and evening doses in turn, until you reach 30 mg twice a day on day six.
Usual dose: 30 mg twice a day, about 12 hours apart.
If your kidneys are significantly impaired: The dose is halved to 30 mg once a day, and the starter pack is used differently.
Total course: No fixed course. It is taken as long as it helps, judged at about 16 weeks, and the benefit stops when the drug stops.
When to Apply: Once a day, at whatever time you will remember. A thin layer over the plaques, rubbed in. It can go on the face, eyelids, armpits, groin and under the breasts, which sets it apart from a steroid. Wash your hands afterwards unless your hands are being treated.
How to Start: Once daily from day one, on every plaque you want treated. No ramp-up, and no cap on how much of the body can be covered, so it does not have to be rationed the way a strong steroid does.
If It Irritates: Small red bumps around hair follicles are the most common problem and usually appear in the first few weeks. Most are not infection and often settle without stopping. Stinging or a rash where you applied it is the other pattern, and that one is worth showing your doctor, because a true contact allergy means stopping.
If It’s Not Working: There is one strength, so there is nothing to increase. Give it a full twelve weeks. If plaques are still thick then, the conversation is about adding something else, phototherapy, or moving to a tablet or injection.
Twice a day, roughly 12 hours apart, with or without food — food helps some people with nausea. Swallow the tablets whole; do not crush, split or chew them.
Take it as soon as you remember, unless the next dose is close, in which case skip it. Never take two at once. If you have stopped for more than a few days, ask before restarting; the full dose brings the stomach side effects straight back, so the starter pack is usually repeated.
The absence of blood tests is why many people choose this drug. No baseline blood count, no liver panel, no tuberculosis test, no hepatitis screen, nothing repeated. Kidney function is checked once before starting, because severe impairment halves the dose.
What replaces it is clinical monitoring, which is not lighter, only different. Weight comes first. Weight loss is common and can be substantial, with some people losing five to ten percent of their body weight. If you wanted that, it is welcome. If you are older, frail or already underweight, it is a reason to reconsider, and unexplained loss should prompt a review.
Mood is second. Depression, low mood and, rarely, suicidal thoughts have been reported and appear on the label. The risk is low, but new or worsening depression should be reported promptly, and a history of depression belongs on the record before you start.
Diarrhea and nausea are third. They usually settle within the first few weeks, but severe or persistent diarrhea is not something to push through. In older adults, and in anyone on a water tablet or a blood pressure medicine, it has caused dehydration and kidney injury.
The one scheduled checkpoint is the 16-week review of skin or joints. If nothing meaningful has changed, continuing is not useful.
No blood tests are required. There is nothing to check on a lab report, which is one of the practical arguments for a topical over a tablet.
Monitoring is a look at the skin and a conversation, usually at about twelve weeks. Two things get asked about: folliculitis, and whether it is a few bumps or enough to be a problem; and whether the treated skin has become itchy and inflamed in a new way, which points to contact dermatitis rather than psoriasis.
Long term there is no organ risk to track and no skin thinning to watch for, so there is no maximum duration. What is genuinely not known yet is what many years of continuous use looks like, because the drug is recent. A common pattern is to treat until clear, stop, and restart when plaques come back.
Approximate windows, not promises.
First doseStarting: The starter pack steps the dose up over the first week, which softens the early side effects.
Days 1 to 14Adjusting: Loose stools, nausea and headache usually start in the first week or two and settle within a month.
Weeks 2 to 4Itch: Usually the first thing to change, ahead of the plaques. Behcet's mouth ulcers settle here too, one of the faster and more reliable responses.
Weeks 4 to 8Working: The first visible change in the skin. Scale lifts before the redness fades.
Weeks 4 to 8Working: Plaques flatten and shrink, and color fades from red toward pink or brown.
Weeks 12 to 16Judge it here: In the trials roughly one in three people reached a 75 percent improvement. Scalp psoriasis responds better than thick body plaques, a common reason to choose it.
Weeks 16 to 24Psoriatic arthritis: Joint pain, swelling and tenderness improve.
Months 3 and onwardWeight and mood: Weight loss comes on gradually, so weigh yourself regularly rather than going by how clothes feel. Mood changes are uncommon but worth watching.
Months 6 and beyondNails: The slowest of all, because a nail has to grow out before improvement shows.
First few minutesApplying it: A thin layer once a day on the plaques.
Weeks 1 to 4Starting: Scale and roughness ease before the redness does, often by week four. Folliculitis shows up now if it is going to, usually small tender bumps in hair-bearing areas.
Weeks 8 to 12Judge it here: Trials measured their main result at twelve weeks, and many people were still improving then. A meaningful minority reached clear or almost clear skin — a realistic target, not a promise.
After stoppingRemission: Unlike a steroid, it does not usually rebound. People who cleared completely often stayed clear for months before restarting.
Sorted by what to do about them.
Apremilast is expensive, priced far closer to the biologics than to older oral drugs such as methotrexate or acitretin.
So insurers commonly ask that cheaper options be tried first, and prior authorization is usual. The manufacturer runs a copay assistance program, which typically helps people with commercial insurance and is not available on government plans.
What it saves is indirect: no injection supplies, no screening tests, no repeated laboratory work. That does not close the gap with a generic tablet, but it is part of the comparison.
Brand only, with no generic. It is one of the more expensive topicals for psoriasis and costs far more than a generic steroid or generic calcipotriene.
Coverage varies and prior authorization is common; plans frequently want to see a topical steroid, and often a vitamin D analog, tried first. Manufacturer copay cards exist and the terms change, so check the current one.
Because a tube covers only so much, cost climbs quickly with widespread psoriasis, which is one of the main reasons people end up on a tablet or injection instead.
Correct. No monitoring schedule, no tuberculosis screen, no repeated bloodwork. Kidney function is checked once before starting, because severe impairment halves the dose.
For most people it is worst in the first two weeks and settles within a month, which is what the five-day starter pack softens. Diarrhea that is severe or lasts past a month is a reason to be reviewed.
Some people do, and some of them lose five to ten percent of their body weight. It happens gradually, so weigh yourself every few weeks rather than judging by how clothes fit.
Less effective for thick plaques — about one in three reached a seventy-five percent improvement at 16 weeks, where biologics reach much higher figures. What it offers is a tablet, no needles, no screening, no monitoring.
Low mood and depression are uncommon but on the label, and rare reports of suicidal thoughts exist. Report any new or worsening low mood promptly.
About 16 weeks for the skin, up to 24 weeks for joints. If nothing meaningful has changed, continuing is not worthwhile.
No. It works on a different switch inside the skin cell, the aryl hydrocarbon receptor. That is why there is no time limit and no skin thinning.
Yes — approved for the face and skin folds, one of its main advantages over a steroid.
Most likely folliculitis — small red bumps around hair follicles where you applied it. The most common side effect in the trials, at roughly one in five people, usually mild, and most carried on.
Give it twelve weeks. Some change usually shows by four.
That is a normal way to use it. In the long-term study, many who cleared completely stayed clear for months, then restarted when plaques returned.
Yes, it is also approved for atopic dermatitis, in adults and in children from age two.





