Psoriasis
Clears moderate to severe plaques.
Methotrexate: An old, inexpensive tablet or injection for severe psoriasis and psoriatic arthritis. It is taken once a week, not daily, and it needs regular blood tests. Sotyktu: A once-daily tablet for moderate to severe plaque psoriasis. It blocks TYK2, an enzyme inside immune cells, and is taken by mouth rather than injected.


Choose for severe psoriasis, especially with joint pain, as an inexpensive weekly treatment with regular blood tests.
Choose for moderate to severe psoriasis when you want a once-daily pill rather than injections.
Can you take them together?
These are usually used one at a time for psoriasis. Discuss switching rather than combining.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.



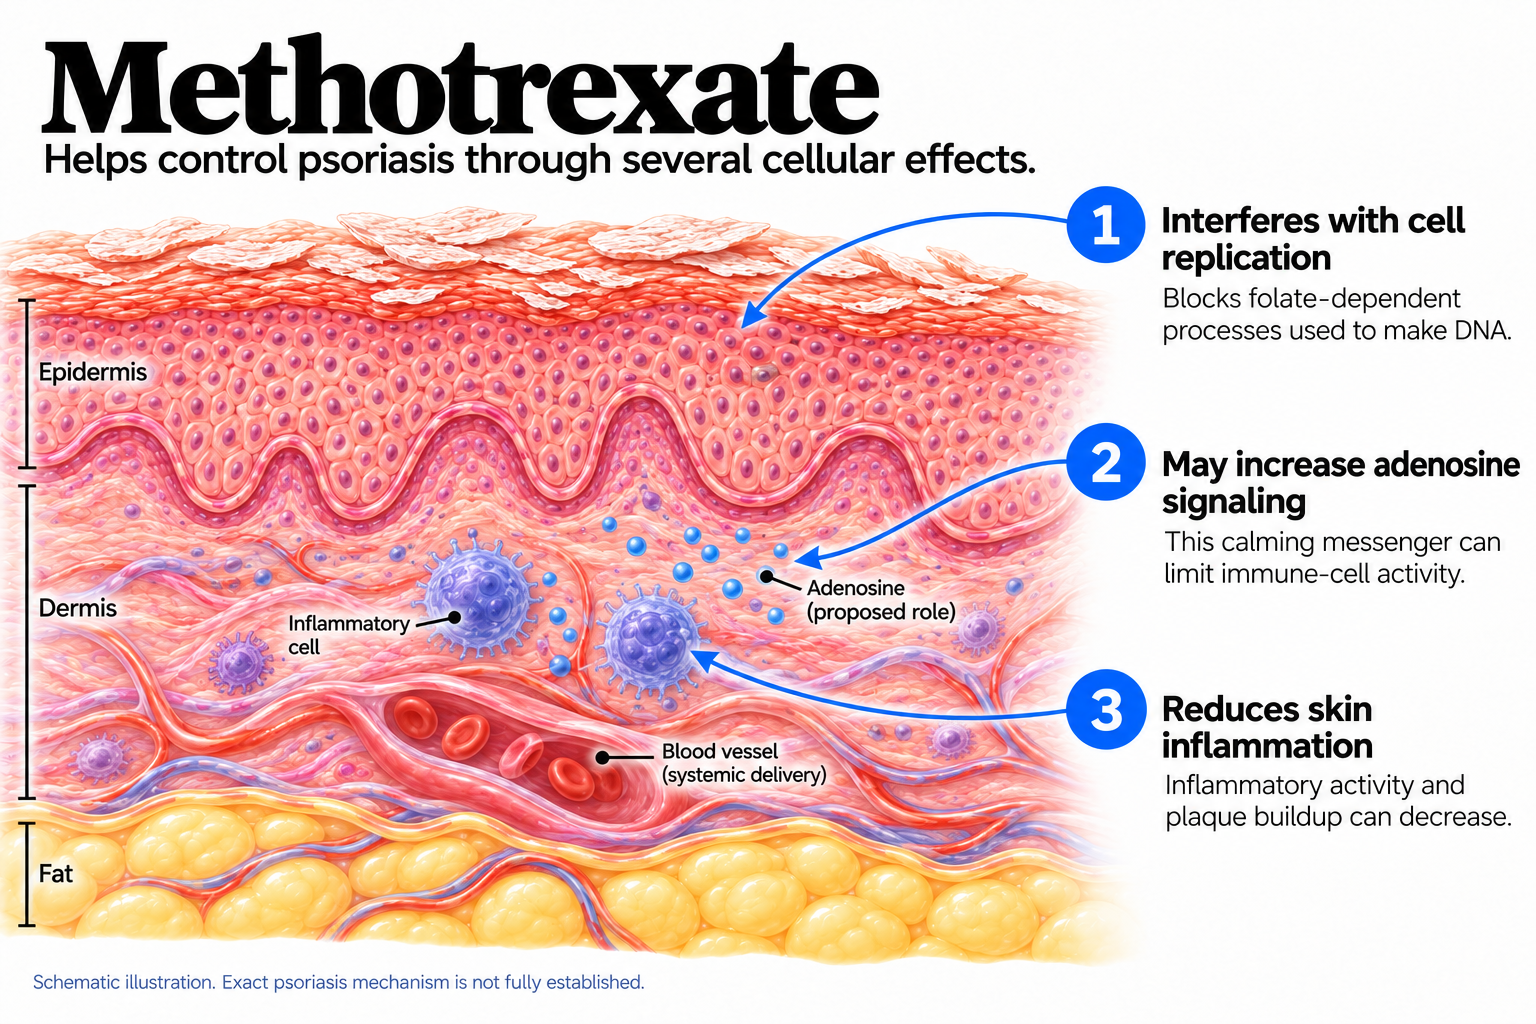
Interferes with cell replication: Blocks folate-dependent processes used to make DNA. May increase adenosine signaling: This calming messenger can limit immune-cell activity. Reduces skin inflammation: Inflammatory activity and plaque buildup can decrease.
The psoriasis mechanism is not fully established. Folate antagonism affects replication, while low-dose anti-inflammatory actions include proposed adenosine pathways supported by experimental work; their precise clinical contributions are unresolved.

Inhibits TYK2: Keeps this signaling enzyme in an inactive state. Reduces immune messages: Limits signals from IL-23, IL-12, and type I interferons. Helps psoriasis settle: Inflammation and plaque buildup gradually decrease.
Deucravacitinib allosterically binds the regulatory domain of TYK2. The exact link between biomarker changes and clinical effects is not fully known.
This drug is taken once a week. Taking it every day can cause fatal bone marrow failure. Pick one day of the week, write it down, and keep to it.
Test dose: A single small dose, often 2.5 mg to 5 mg, with blood counts checked about a week later before going further. A safety check, not the treatment dose.
Starting dose: Commonly 7.5 mg to 15 mg once weekly, adjusted for age, weight, kidney function and other illnesses. Lower in older people and in reduced kidney function.
Going up: Small steps, usually 2.5 mg to 5 mg every few weeks with blood tests in between, until the psoriasis responds or side effects set the ceiling.
Usual dose: Most people settle between 15 mg and 25 mg once weekly. Above about 15 mg tablet absorption gets unreliable, a common point to switch to the injection.
Folic acid alongside it: It reduces nausea, mouth ulcers and blood count problems. Usually a daily dose on the days you are not taking methotrexate, or one larger weekly dose on a different day. It does not stop the drug working.
Total course: No fixed course. It continues as long as it works and blood tests stay normal, which for some people is years.
Dosing is as simple as it gets for a systemic drug. No loading dose, no build-up, no weight adjustment.
Starting dose: 6 mg once a day from day one. Full dose from the start.
Going up: No higher approved dose for psoriasis. If it is not working, the conversation is about switching.
Usual dose: 6 mg once a day, long term.
Kidney function: No dose change for most levels of reduced kidney function.
Severe liver disease: Not recommended, so tell your doctor about any liver condition before you start.
Once a week, on the same day every week. Choose a day you will remember and write it somewhere visible. Some people take the whole dose at once; some split it into two portions about twelve hours apart on the same day to reduce nausea. Do not spread it across different days unless you were told to.
Take tablets with water, and with food if they upset your stomach. An evening dose means the tiredness and mild nausea happen while you are asleep.
Folic acid goes on the other days, as prescribed. It is not a substitute for a missed methotrexate dose.
With the weekly injection, keep to the same day and rotate the site.
Once a day, at whatever time suits you, with or without food. Pick one time and keep to it, because a daily tablet is easy to lose track of in a way a fortnightly injection is not. Attaching it to something you already do, like brushing your teeth at night, works better than intending to remember.
Swallow the tablet whole with water. Do not crush, split or chew it. If it upsets your stomach, take it with a meal.
Take it as soon as you remember if it is within about two days of your usual day. If longer, skip it and take the next on your usual day. Never take two weekly doses close together to catch up, and never take a daily dose to make up for a missed week.
If you have taken more than one weekly dose, or taken it several days in a row, contact a doctor or a poison center straight away. Do not wait to see how you feel. This overdose is treatable caught early and dangerous when it is not.
Take it as soon as you remember on the same day. If you do not remember until the next day, skip it and take that day's tablet as usual. Never take two in one day. Missing the occasional dose will not undo months of progress, but repeatedly missing them is one of the commonest reasons a treatment looks like it has stopped working.
Methotrexate is watched by blood test, and the schedule is not optional. The problems it causes are silent until they are advanced.
Before starting: Full blood count, liver tests, kidney function, and a pregnancy test where relevant. Hepatitis B, hepatitis C, HIV and tuberculosis screening is standard, because the drug damps the immune system. A chest x-ray if there is any history of lung disease.
Early on: Blood counts and liver tests within a week or two of starting, and again after each dose increase. This is when a sudden drop in blood counts would show.
Once stable: Full blood count, liver tests and kidney function every one to three months, depending on the dose and what else you take, for as long as you are on the drug.
The liver over the long term: Years of methotrexate can scar the liver, and the risk rises with total lifetime dose, heavy alcohol use, obesity, diabetes and fatty liver disease. Biopsy used to be the check; most clinics now use a blood marker of scarring and a scan of liver stiffness.
The lungs: A rare but serious lung inflammation can occur. A new dry cough, breathlessness or fever means being seen, not waiting for the next appointment.
What to report between tests: Mouth ulcers, unexplained bruising or bleeding, sore throat or fever, dark urine, yellowing of the eyes or skin, severe nausea, any new cough or breathlessness.
Everyone is screened for tuberculosis before starting, with a skin test or a TB blood test, and a chest X-ray if positive. Dormant TB is treated first. This applies even though it is a tablet rather than an injected biologic.
Hepatitis B and C are usually checked at the same time.
Liver blood tests are often checked before starting and again if there is a reason to. Some people show a rise in creatine kinase, a muscle enzyme, or in triglycerides, so those may be looked at too. There is no rigid schedule like methotrexate's; how often anything is repeated is your doctor's judgment.
The rest is clinical. Report repeated infections, cold sores that keep coming back, mouth ulcers that will not heal, and unexplained muscle pain. Skin should be checked periodically, as on any drug that damps down the immune response.
Approximate windows, not promises.
First doseTaking it: Once a week, not daily, with folic acid on the other days. Nausea, tiredness or mouth soreness in the day or two after each dose is common early on; folic acid usually blunts it.
First doseTaking it: One tablet a day, with or without food.
Weeks 1 to 2Settling in: Nothing visible in the skin yet.
Weeks 4 to 8Working: Plaques thin and spread less, thickness and scale first. Joint pain from psoriatic arthritis often improves in the same window, one reason it is chosen over a skin-only treatment.
About 3 monthsJudge it here: Substantial improvement is the realistic target.
Beyond 3 monthsLong term: Where it suits, the result holds while the dose continues, with regular blood tests. Some stay on it for years.
Many monthsNails: Nail psoriasis can improve, but slowly. Nails always lag behind the skin.
Weeks 1 to 4Starting: Itch usually eases before the plaques look different. Early side effects show now, most often a cold, a cold sore or a mouth ulcer.
Weeks 4 to 16Working: Scale lifts and plaques flatten steadily. Scalp psoriasis often improves noticeably here, before the trunk.
Week 16Judge it here: Where the trials measured, and the fair point to decide. More than half reached at least a 75 percent improvement in how much skin was involved and how severe it was; a smaller share were clear or nearly clear.
Months 3 to 6Palms and soles: Stubborn on every treatment, slower than plaques elsewhere.
Months 6 to 12Nails: Nails change last, because a nail takes months to grow out. Judge the new growth at the base, not the damaged tip.
Beyond 16 weeksLong term: Responders often keep improving slowly through the first year. Because it is a small molecule, the body does not make antibodies against it, so the gradual loss of effect seen with some injected drugs is not an issue here.
Sorted by what to do about them.
Generic methotrexate tablets are among the least expensive systemic treatments in dermatology. Folic acid is cheap too.
The weekly auto-injector pens cost considerably more, and coverage usually requires showing that tablets caused nausea or did not work well enough. Plain injectable vials are cheaper than the pens.
The real cost is the monitoring, repeated blood tests and periodically a liver scan or blood marker. Usually covered, but they are appointments and not optional.
Insurers frequently require a trial of methotrexate before approving a biologic, one reason it is still so often the first systemic drug tried.
Brand only. There is no generic and will not be for years, so there is no cheaper equivalent. The list price is high, in the same range as the injected biologics over a year, which surprises people who assume a tablet must be cheaper.
Almost nobody pays it. What matters is what your plan does, and approval takes paperwork. Prior authorization is close to universal, and most plans want documented failure of something cheaper first: phototherapy, methotrexate or apremilast.
Manufacturer copay cards can bring the monthly cost down to very little on commercial insurance. By law they cannot be used with Medicare or Medicaid. For those plans, or no insurance, the manufacturer's patient assistance program and independent foundations are the usual routes, and the rules change regularly.
One thing in its favor on cost: no infusion visits, no injection training, no cold chain, so the costs around the drug are lower even when the drug is not.
Once a week, on the same day. Never daily. Daily dosing by mistake is the most dangerous error with this drug and it has been fatal. Get medical help the same day if it happens.
Methotrexate blocks folate, and the mouth ulcers, nausea and low blood counts come from that. Folic acid on the other days restores enough folate to reduce them without stopping the treatment working.
Yes. Liver damage and falling blood counts cause no symptoms until they are advanced. The tests are the only early warning.
The concern is regular drinking, not a single glass, because alcohol and methotrexate both stress the liver. Agree an actual limit with your doctor.
No. It must be stopped well before trying to conceive, and the advice covers both partners. It causes miscarriage and serious birth defects. Ask your own doctor how far in advance.
Give it about three months. First changes often show at four to eight weeks, but three months on a tolerated dose is the fair point to judge.
It is chemotherapy at much higher doses. At psoriasis doses it acts as an immune-calming drug, and the experience is not comparable.
It works on TYK2, an enzyme in the same family, but binds a different part of it and is far more selective. Its label does not carry the boxed warning the JAK inhibitors carry. The distinction is real, not marketing.
On average the injected biologics clear skin more completely. This clears skin well for a lot of people, and it is a daily tablet with no fridge and no needles. Which trade is right depends on how severe your psoriasis is and how you feel about needles.
Tuberculosis and hepatitis before you start, and usually liver tests. After that, testing follows your situation, not a fixed schedule — much lighter than methotrexate monitoring.
Herpes simplex outbreaks and mouth ulcers are commonly reported. Tell your doctor if they are frequent; they can usually be managed without stopping.
No direct interaction, unlike methotrexate. Ordinary drinking is generally not a problem, but confirm with your doctor if you have a liver condition.
Losing response over time is less of an issue than with injected antibodies, since the body makes no antibodies against a small molecule. If it does stop working, the option is switching class, since there is no higher dose.