Ingrown Hairs vs Hidradenitis Suppurativa

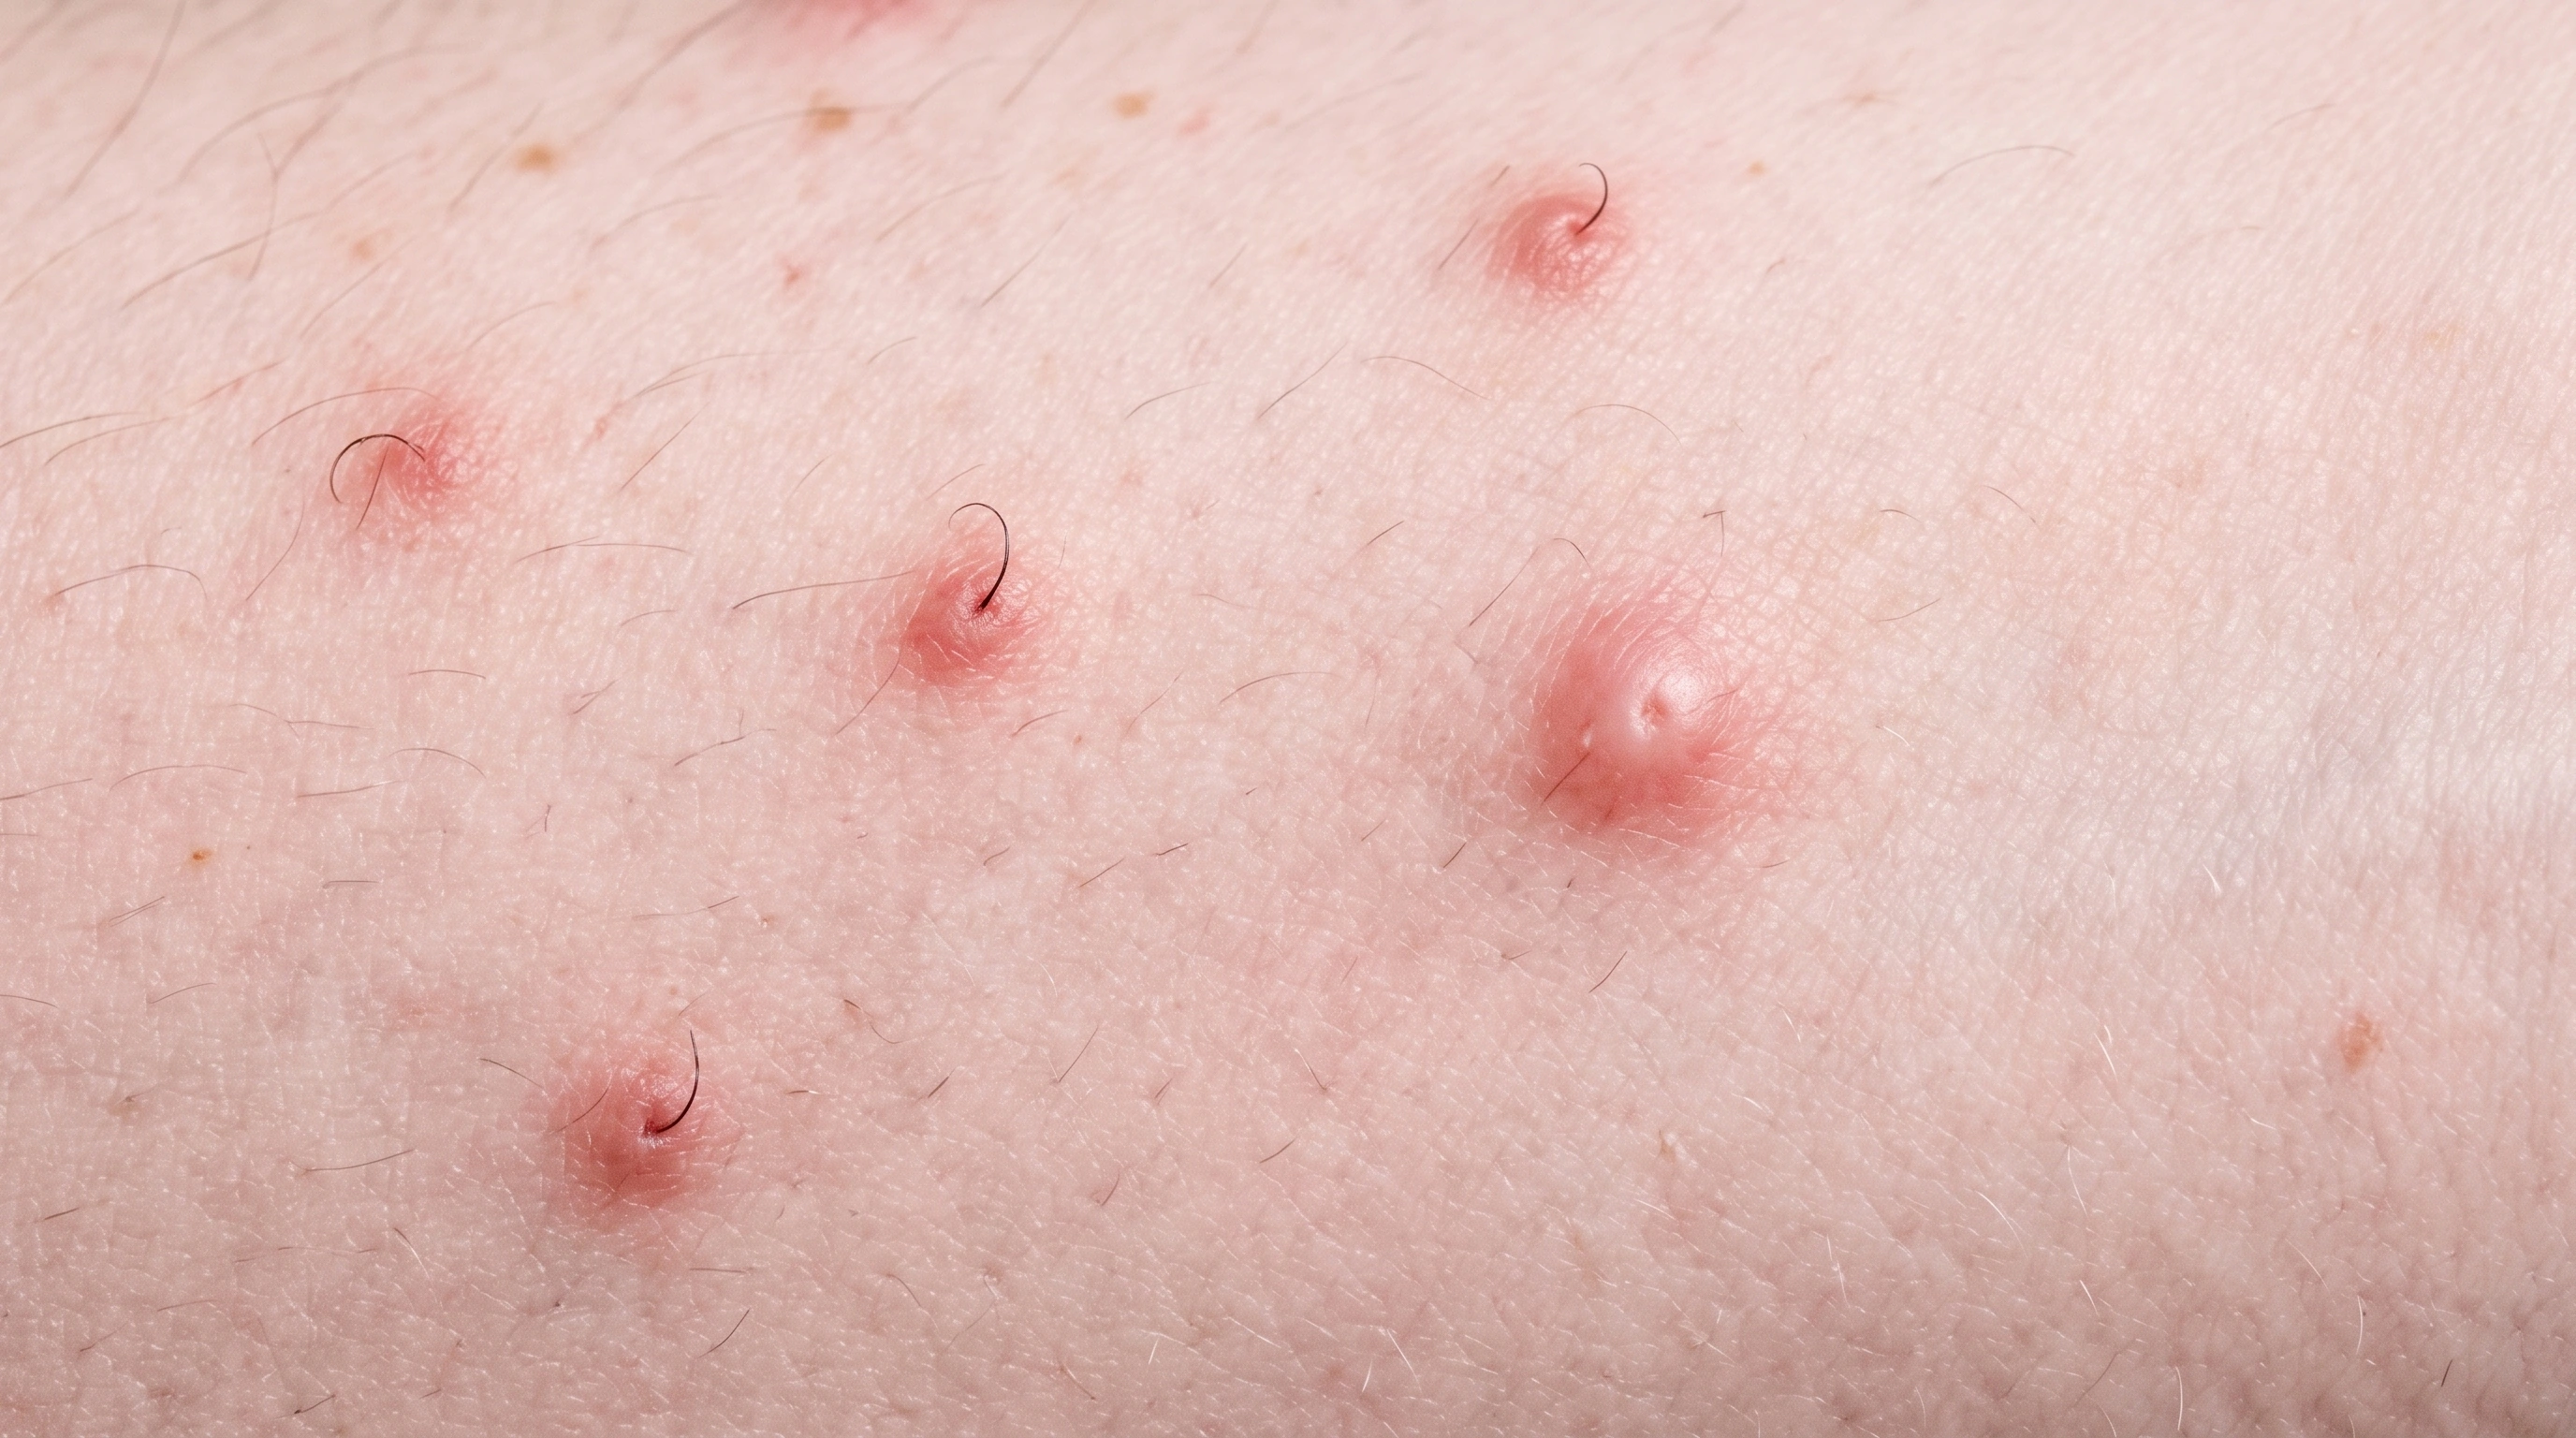
An ingrown hair is a hair that curls back into the skin instead of growing out of it, leaving a tender bump. It is most common and most stubborn in coarse, tightly curled hair, where it has a name of its own: pseudofolliculitis barbae, better known as razor bumps. Hidradenitis suppurativa is a long-term inflammatory condition that causes painful lumps, abscesses and tunnels in the armpits, groin and under the breasts. It is not an infection and it is not caused by poor hygiene, and treating it early is what prevents the scarring.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
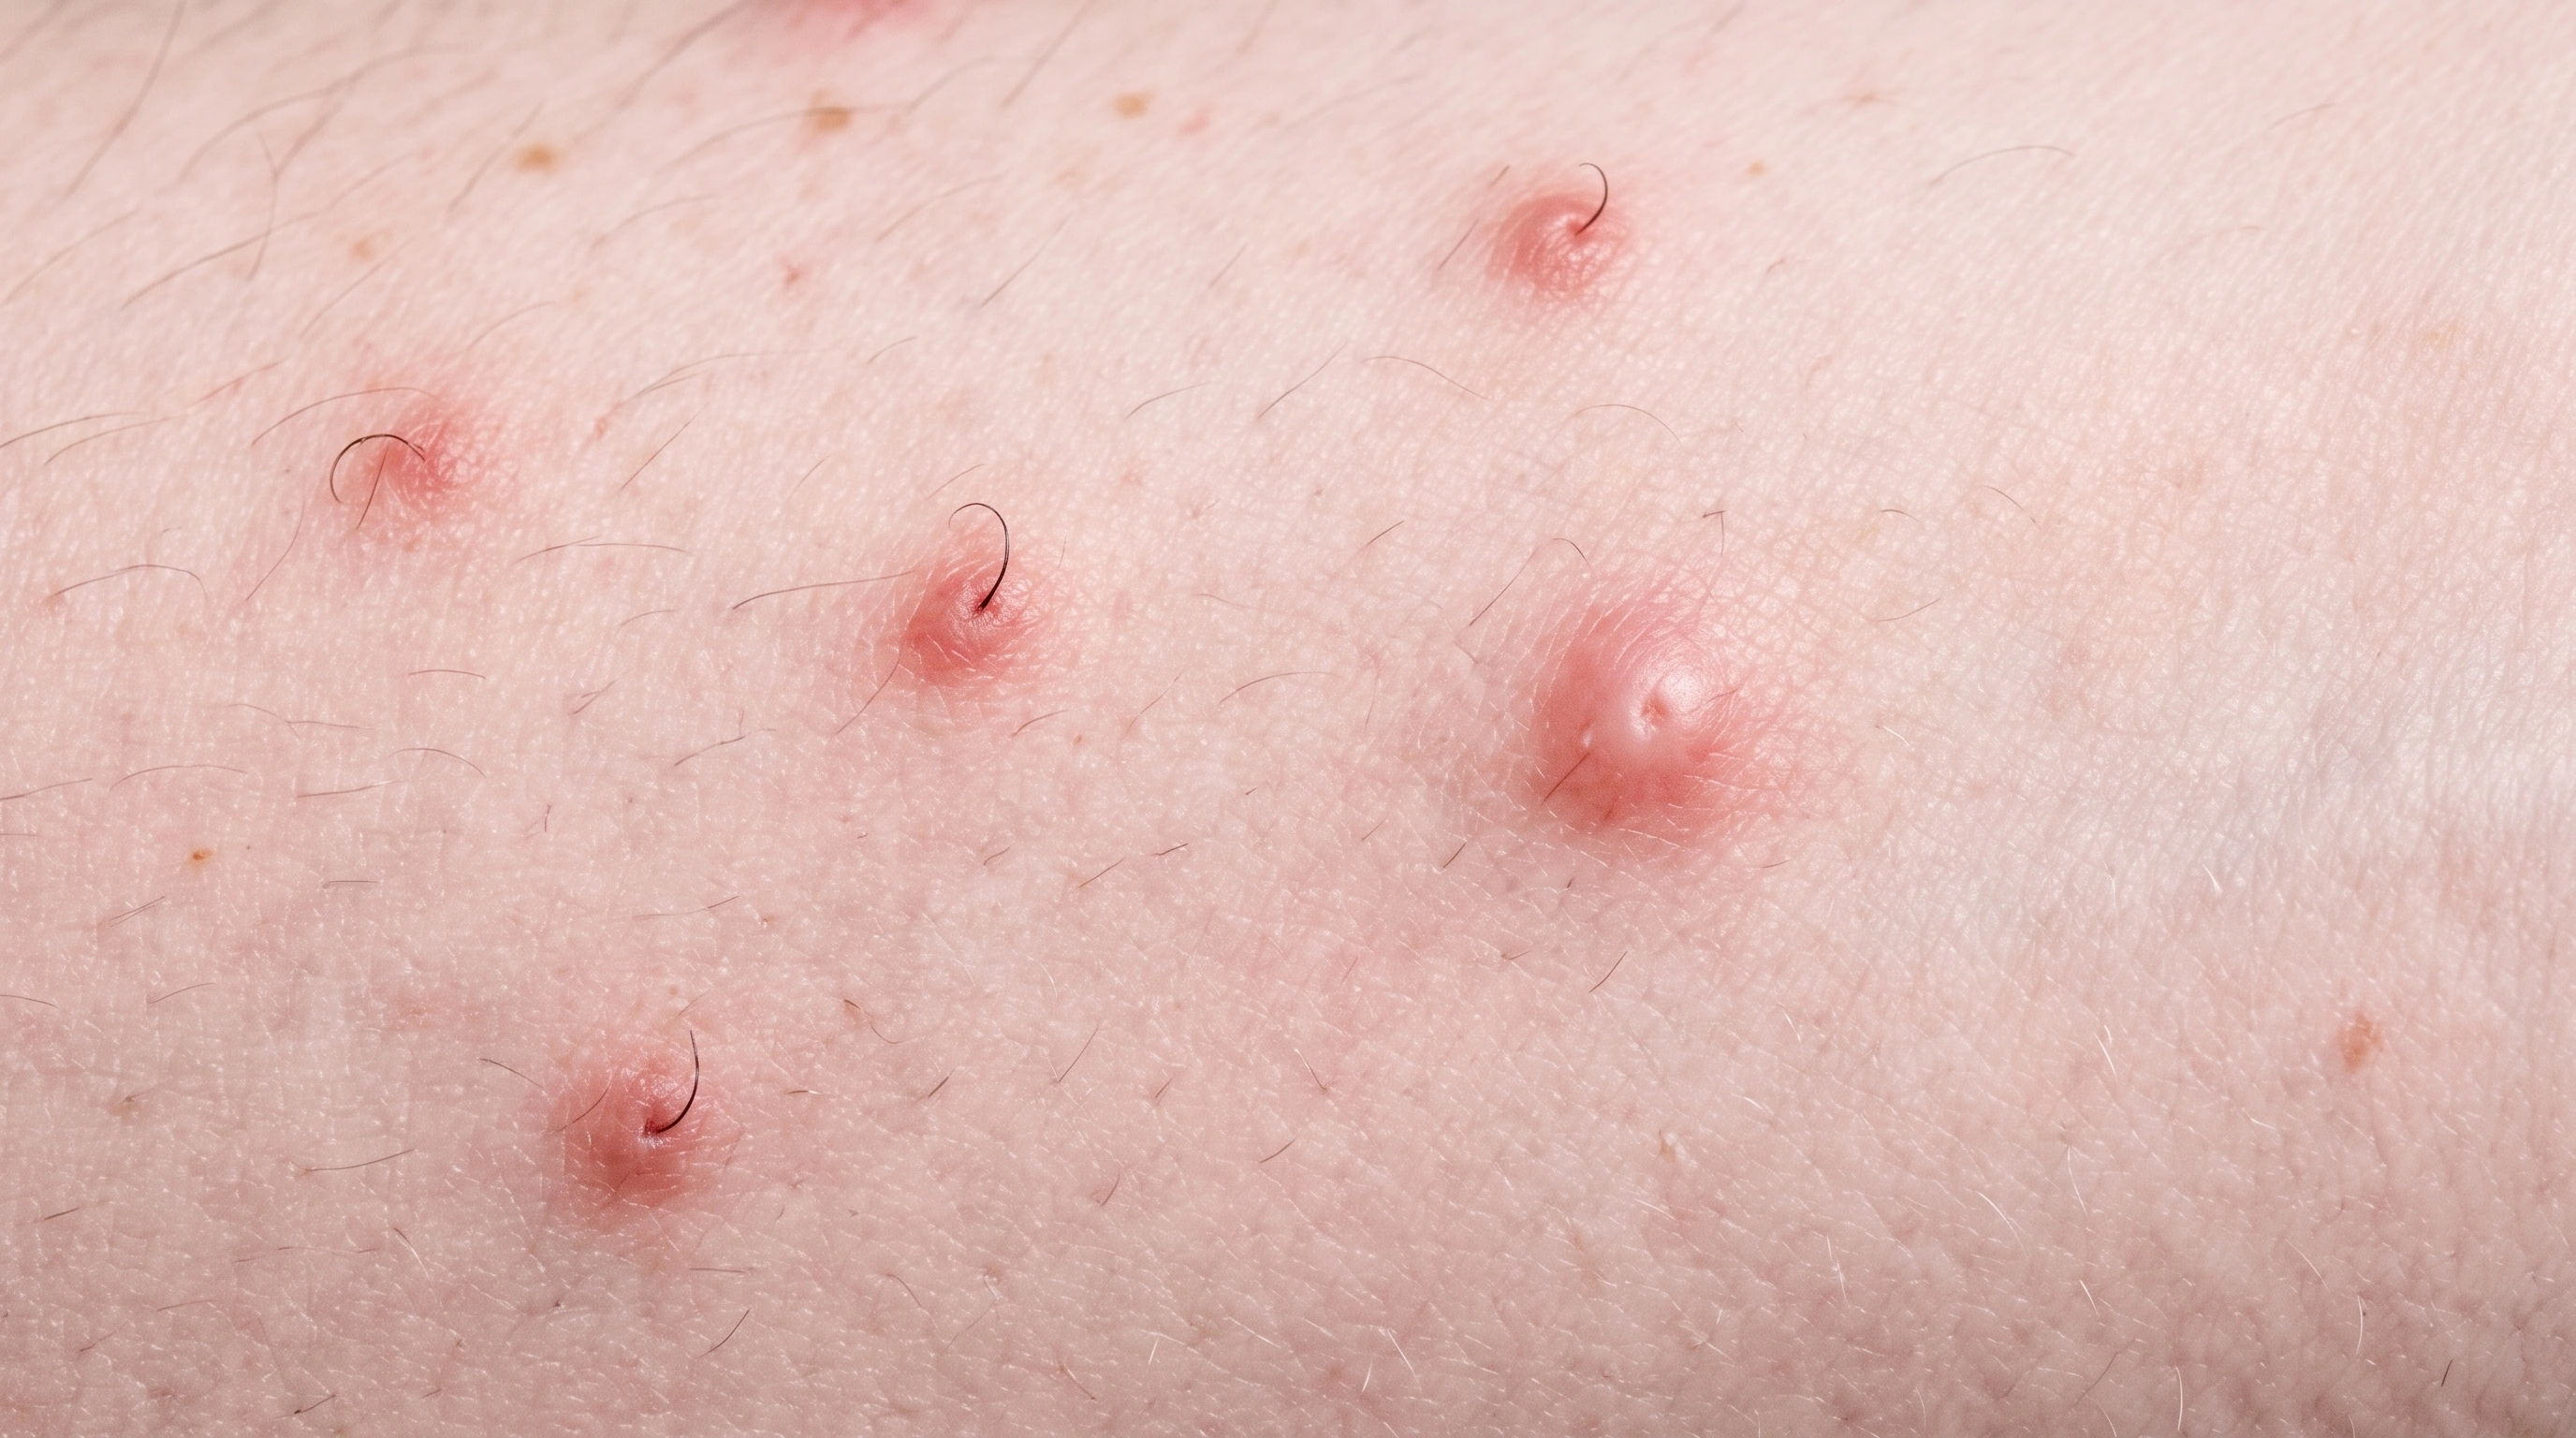
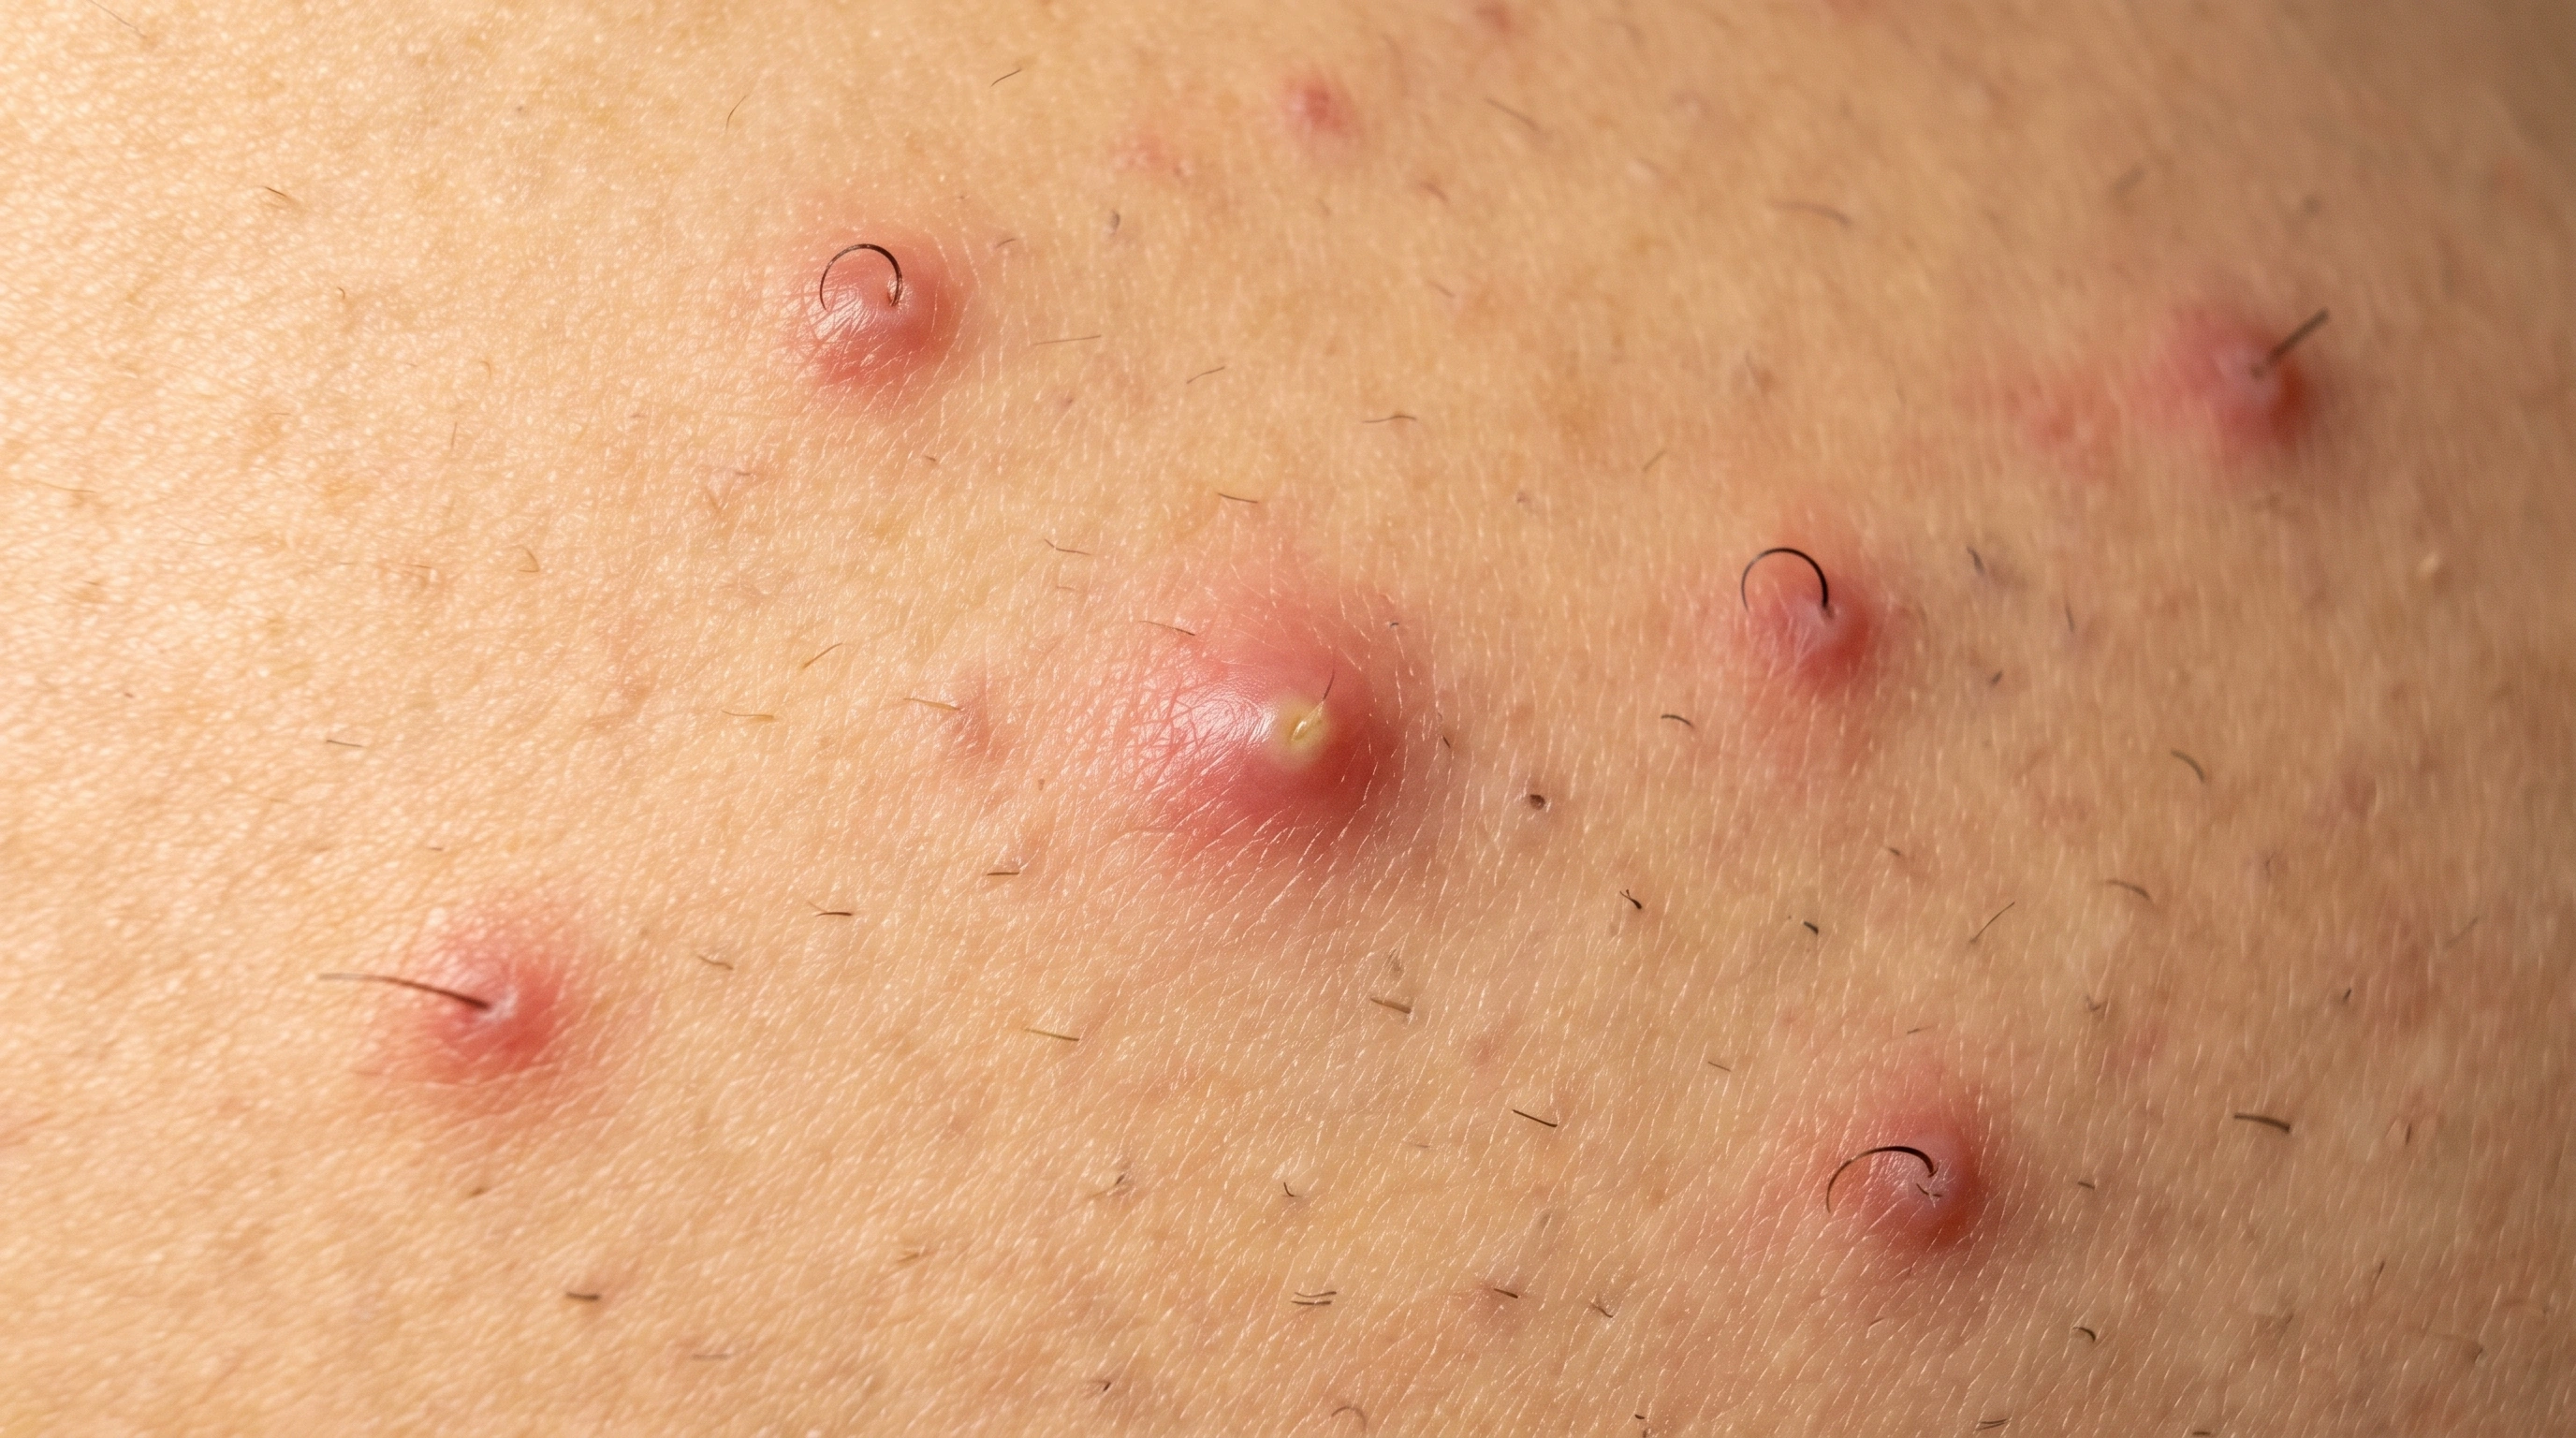
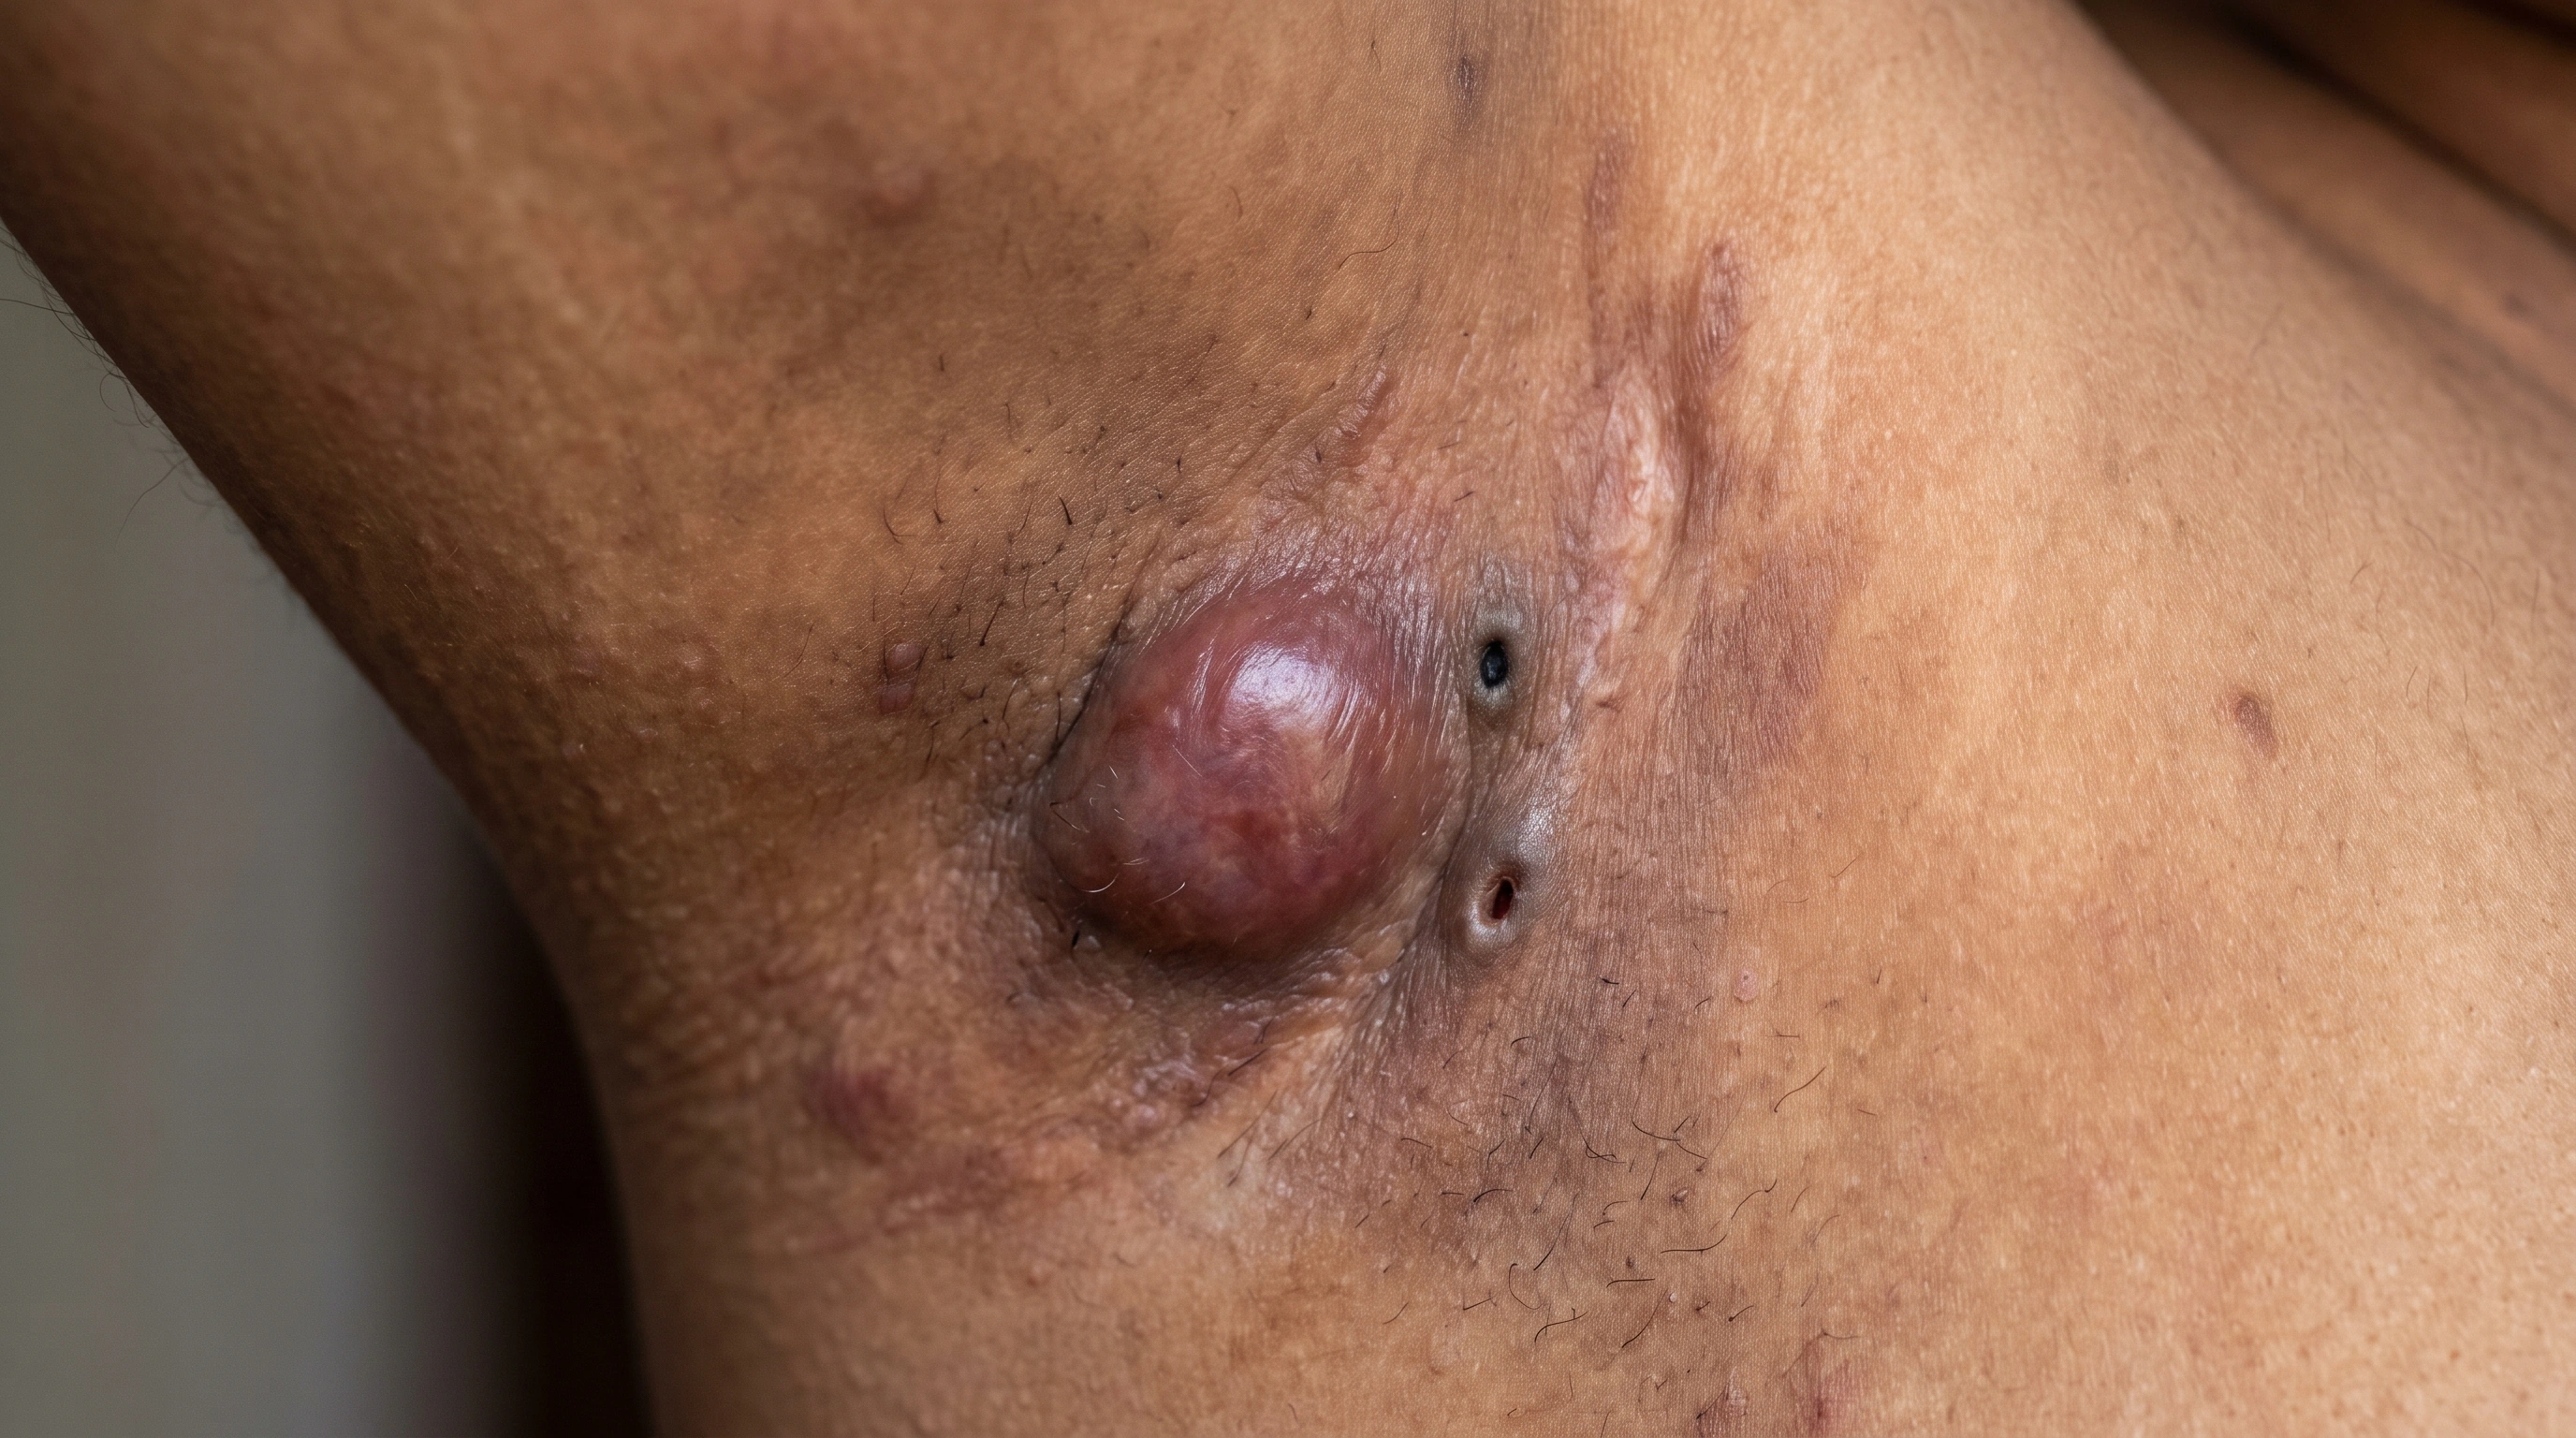
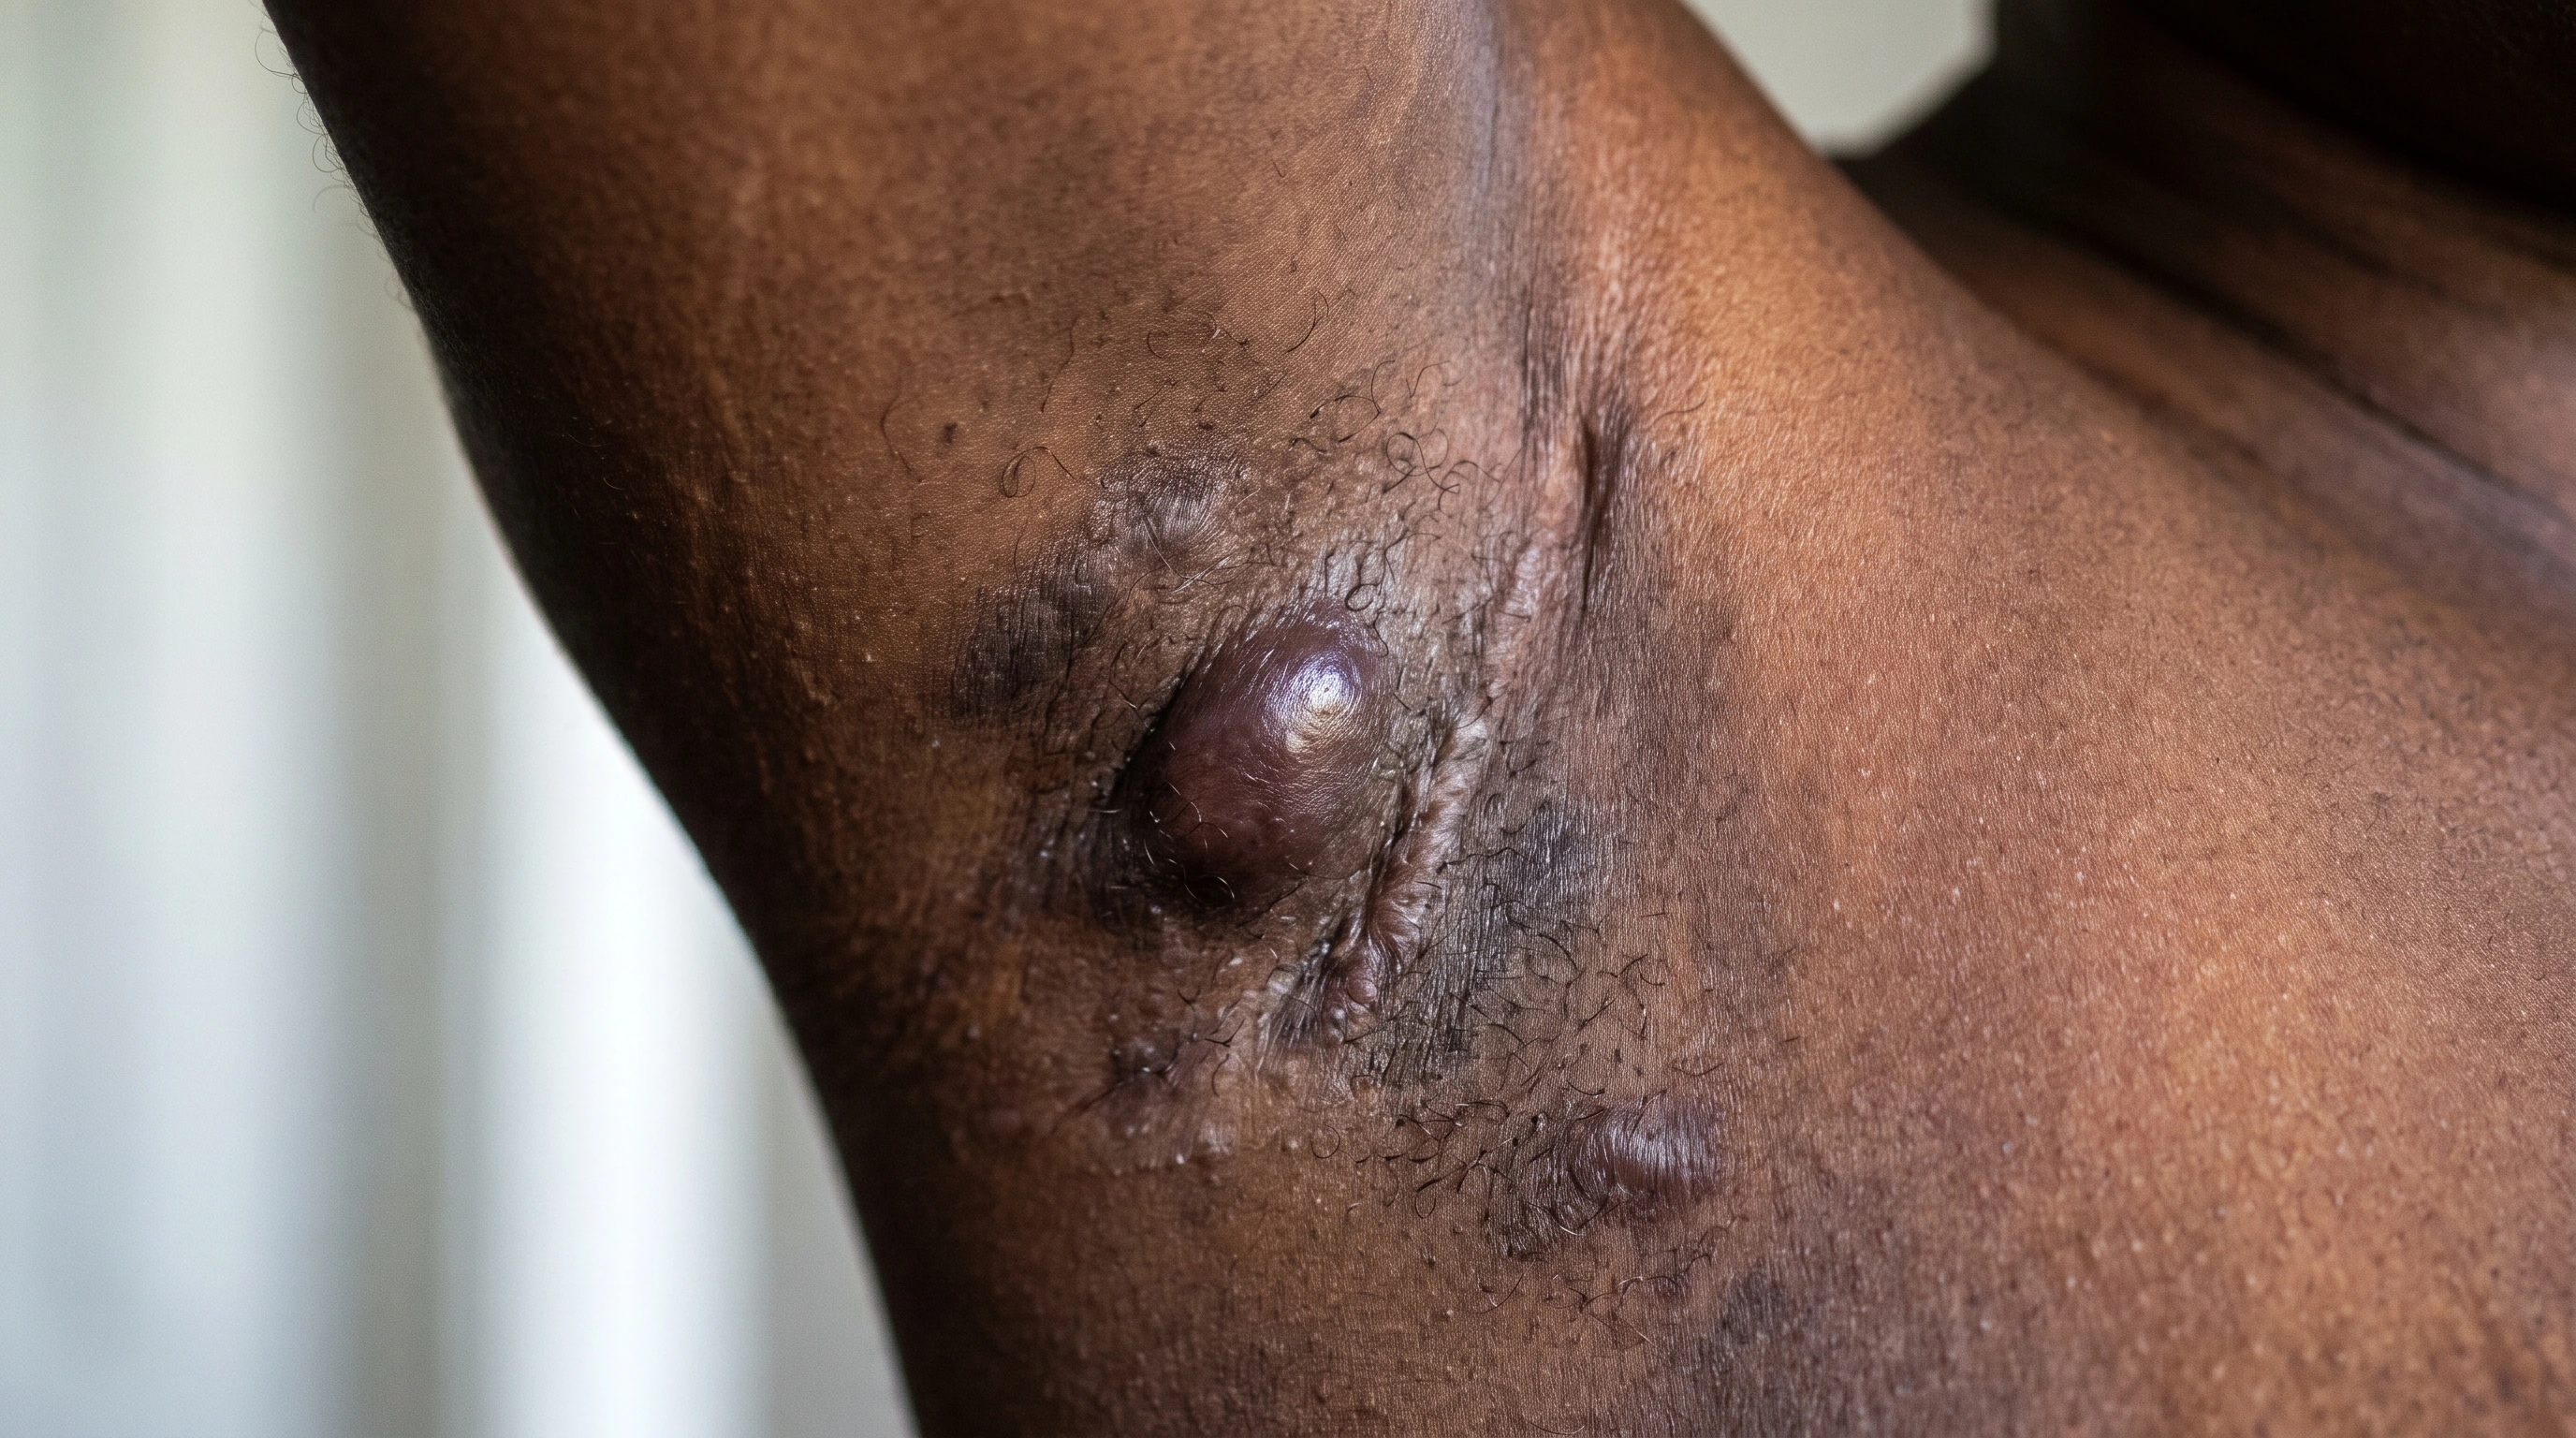
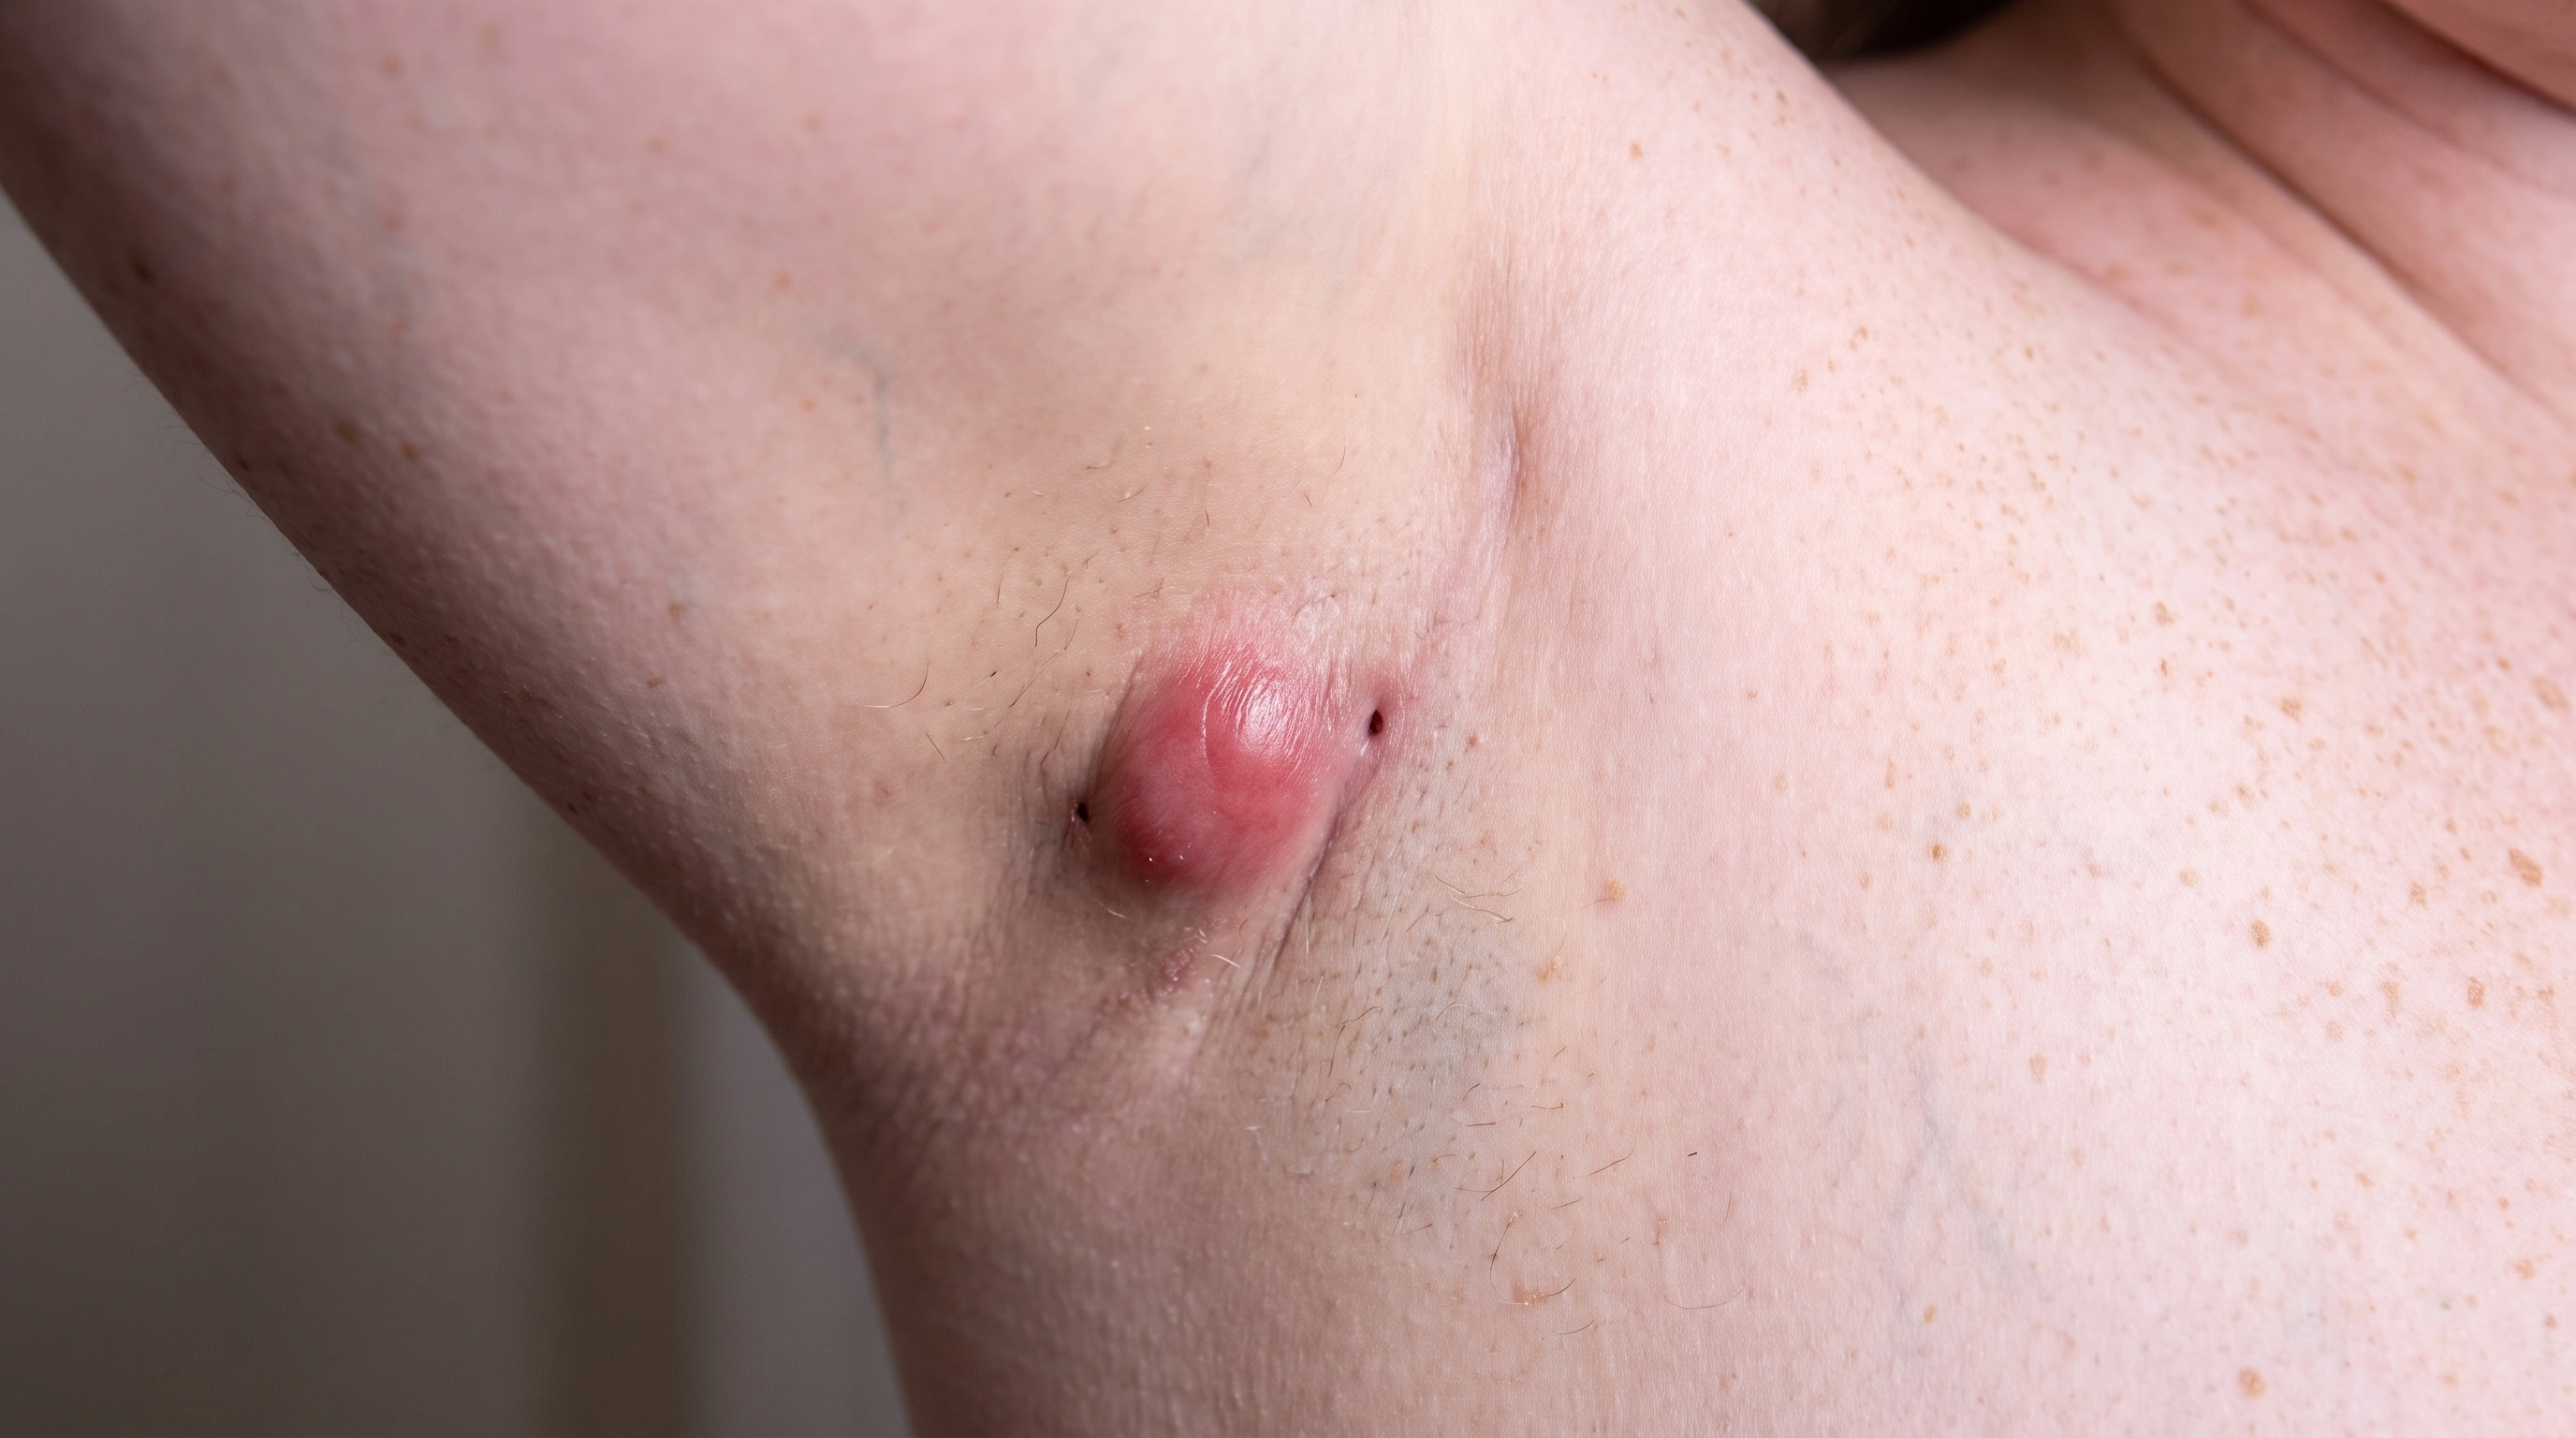
A few firm pink bumps scattered under the jaw and along the upper neck on light skin, with a dark loop of hair visible over one of them.An inflamed lump in the armpit on fair skin. The skin over it is swollen, shiny and red, with a pair of small blackhead-like openings in the skin beside it.

Key differences

The same eight facts on every condition comparison.

Usual age
After puberty
Teens to 40
Where
Beard, legs, armpits, bikini line
Armpits, groin, under breasts, buttocks
Main sign
Tender bumps at shaved hairs
Painful lumps that drain and tunnel
Itch or pain
Tender, itchy
Painful
Contagious
No
No
Long term
Recur with shaving
Long-term; flares
Scars
Dark marks and keloids possible
Often scars
Who gets it
Coarse, curly hair; shavers
Women, smokers, family history

What is it?

Ingrown Hairs
Hidradenitis Suppurativa
What is it?

A hair grows back into skin.
A curved or sharply cut hair pierces the skin or follicle wall.

The skin reacts to it.
The body treats the embedded hair as foreign material.

Curly hair is more prone.
Coarse, curved hair increases risk, but any hair type can be affected.

Deep lumps need assessment.
Painful lumps, drainage or scarring may signal infection or another disorder.

It is a chronic inflammatory disease.
It causes recurrent painful nodules, draining tunnels and scars, usually in skin folds.

It is not contagious.
It is not caused by poor hygiene.

Early recognition matters.
Prompt diagnosis can reduce treatment delays and limit tissue damage.

The whole picture guides care.
Pain, drainage, activity limits and mood all shape the treatment plan.

What it looks like

Ingrown Hairs

Ingrown Hairs: Bumps after shaving; Razor bumps.

Razor bumps Pseudofolliculitis barbae in the beard area.

Representative image of an ingrown hair bump in a skin fold.

Bikini-line ingrown hairs Bumps after shaving or waxing.

A firm raised skin lump with a curled hair, representing an ingrown-hair cyst.

Ingrown-hair cyst A deeper, larger lump.

Ingrown Hairs: Trapped hair.

Individual ingrown hair A hair visible under the skin.

Hidradenitis Suppurativa

Single inflamed hidradenitis suppurativa lump in the armpit.

Hurley stage I Single lumps, no tunnels or scars.

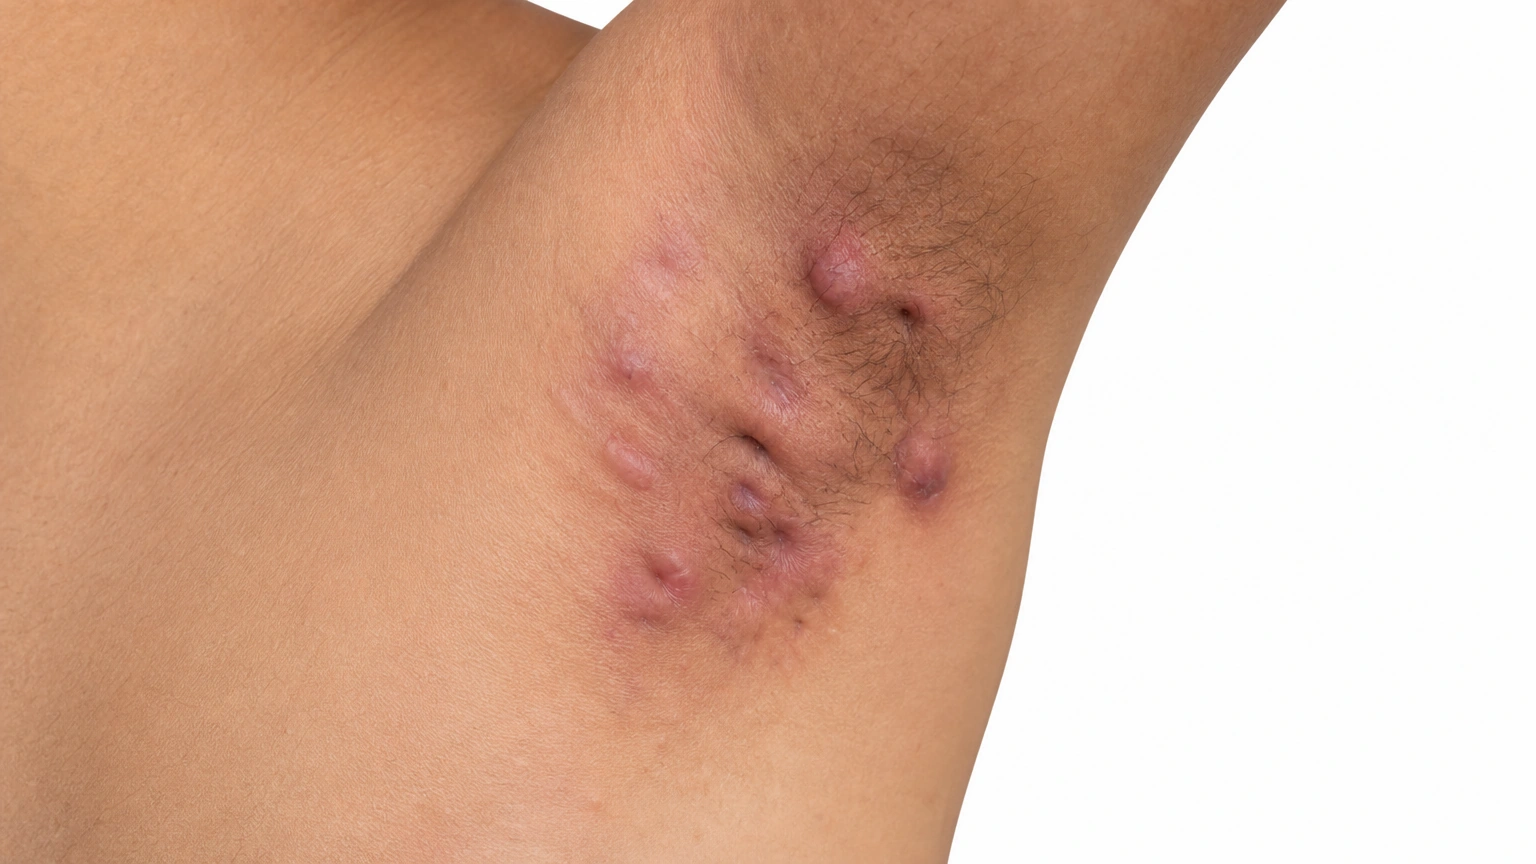
Armpit nodules, small tunnel openings and limited scar bands, representing stage II hidradenitis suppurativa.

Hurley stage II Recurring lumps with tunnels and scars.

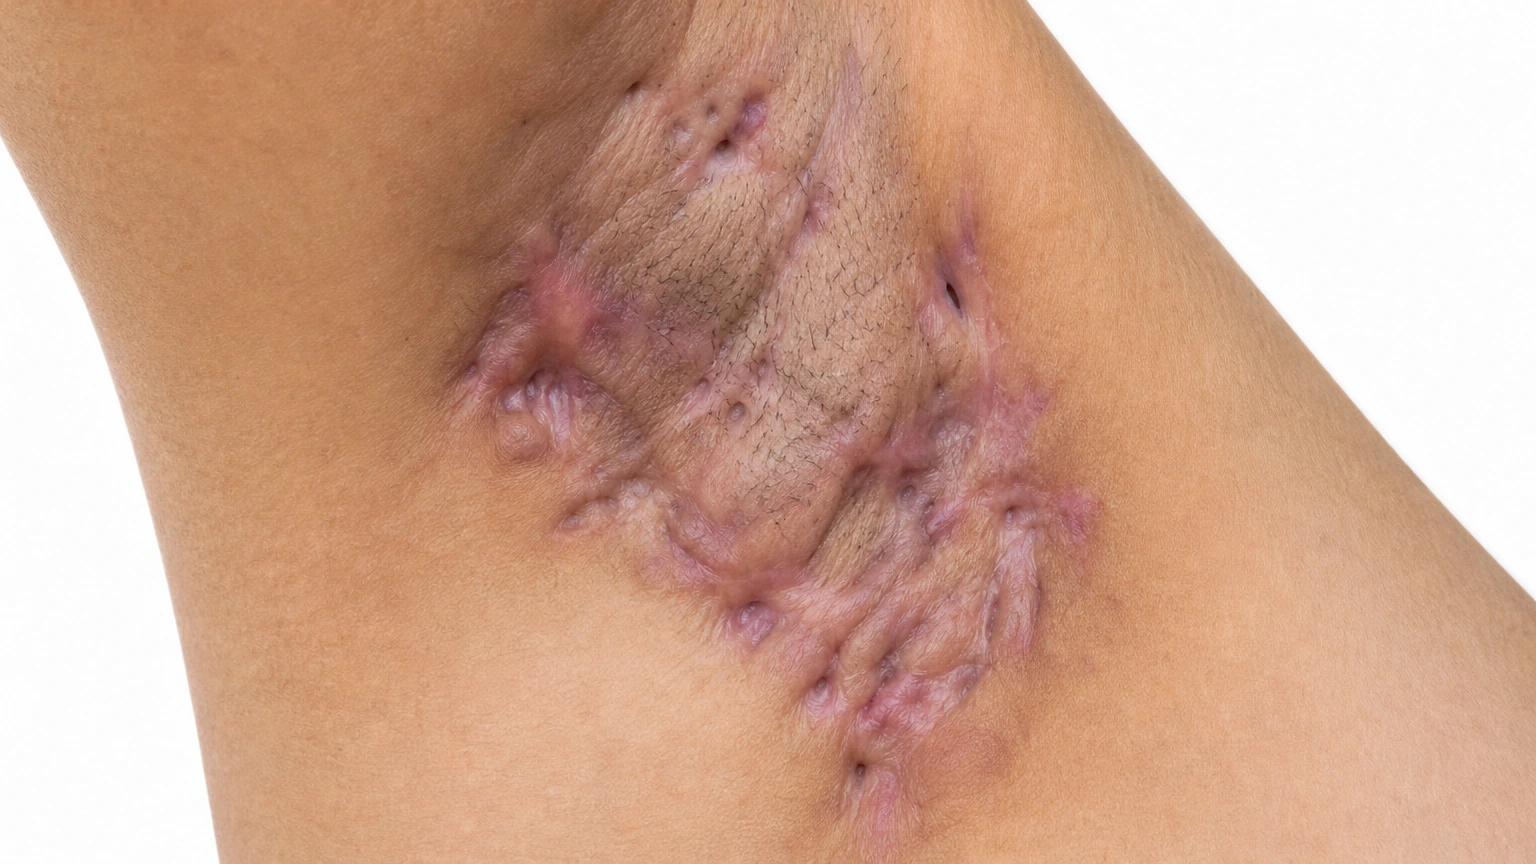
Connected raised scar bands, nodules and tunnel openings across the armpit, representing stage III hidradenitis suppurativa.

Hurley stage III Widespread tunnels and scarring.

Skin tones
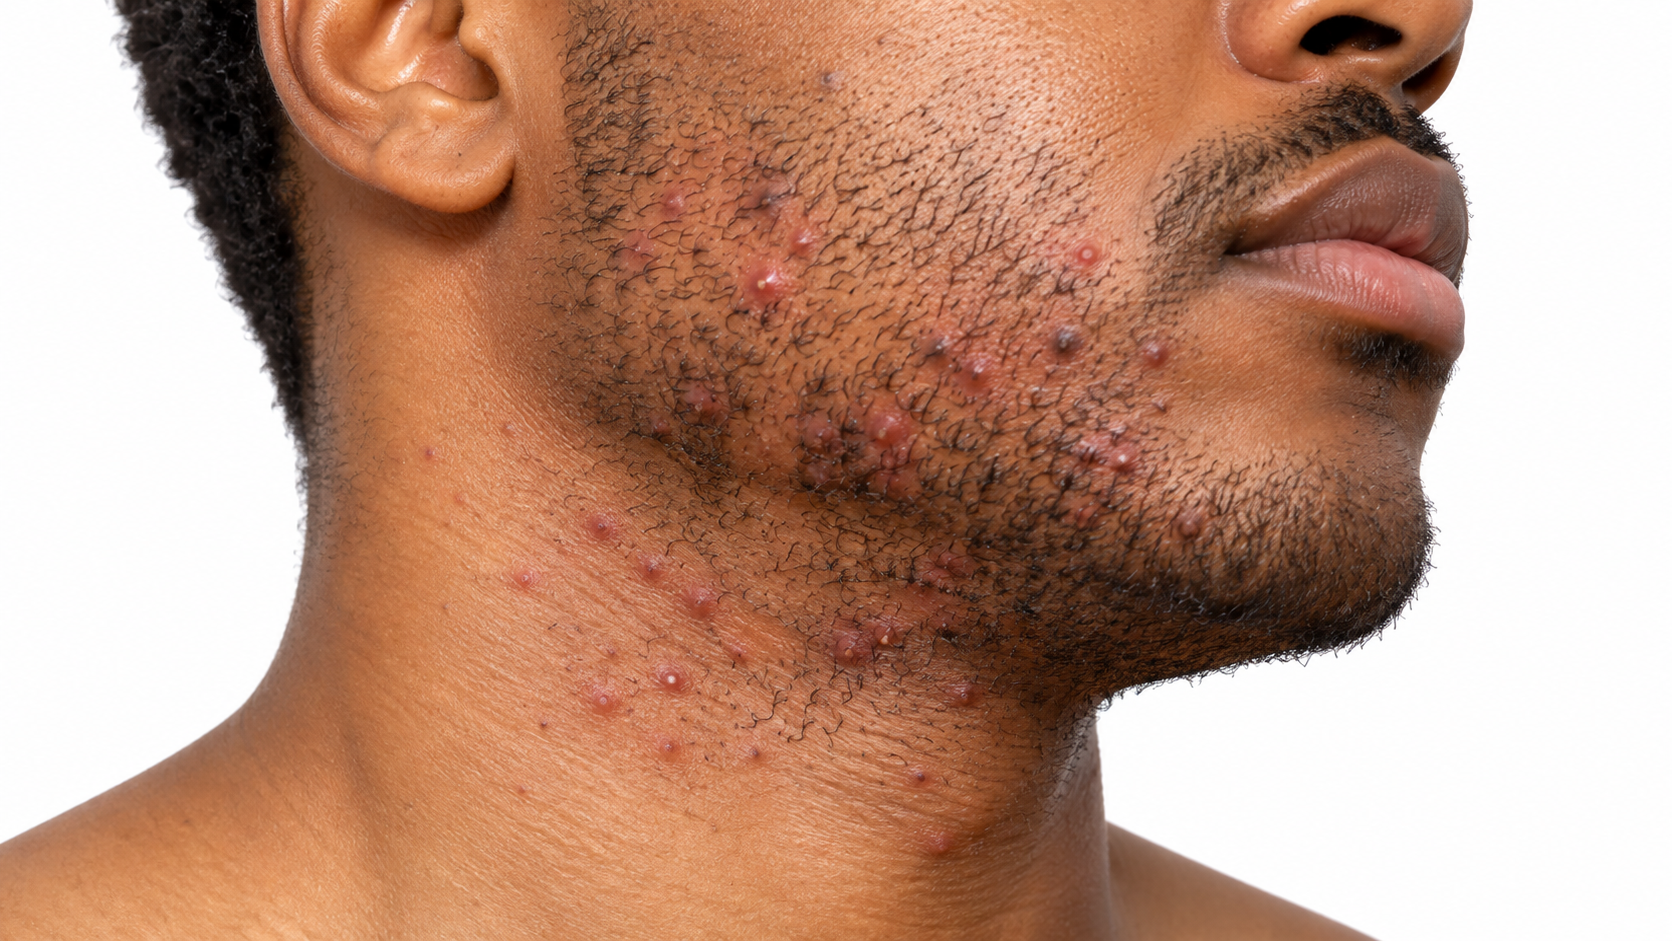
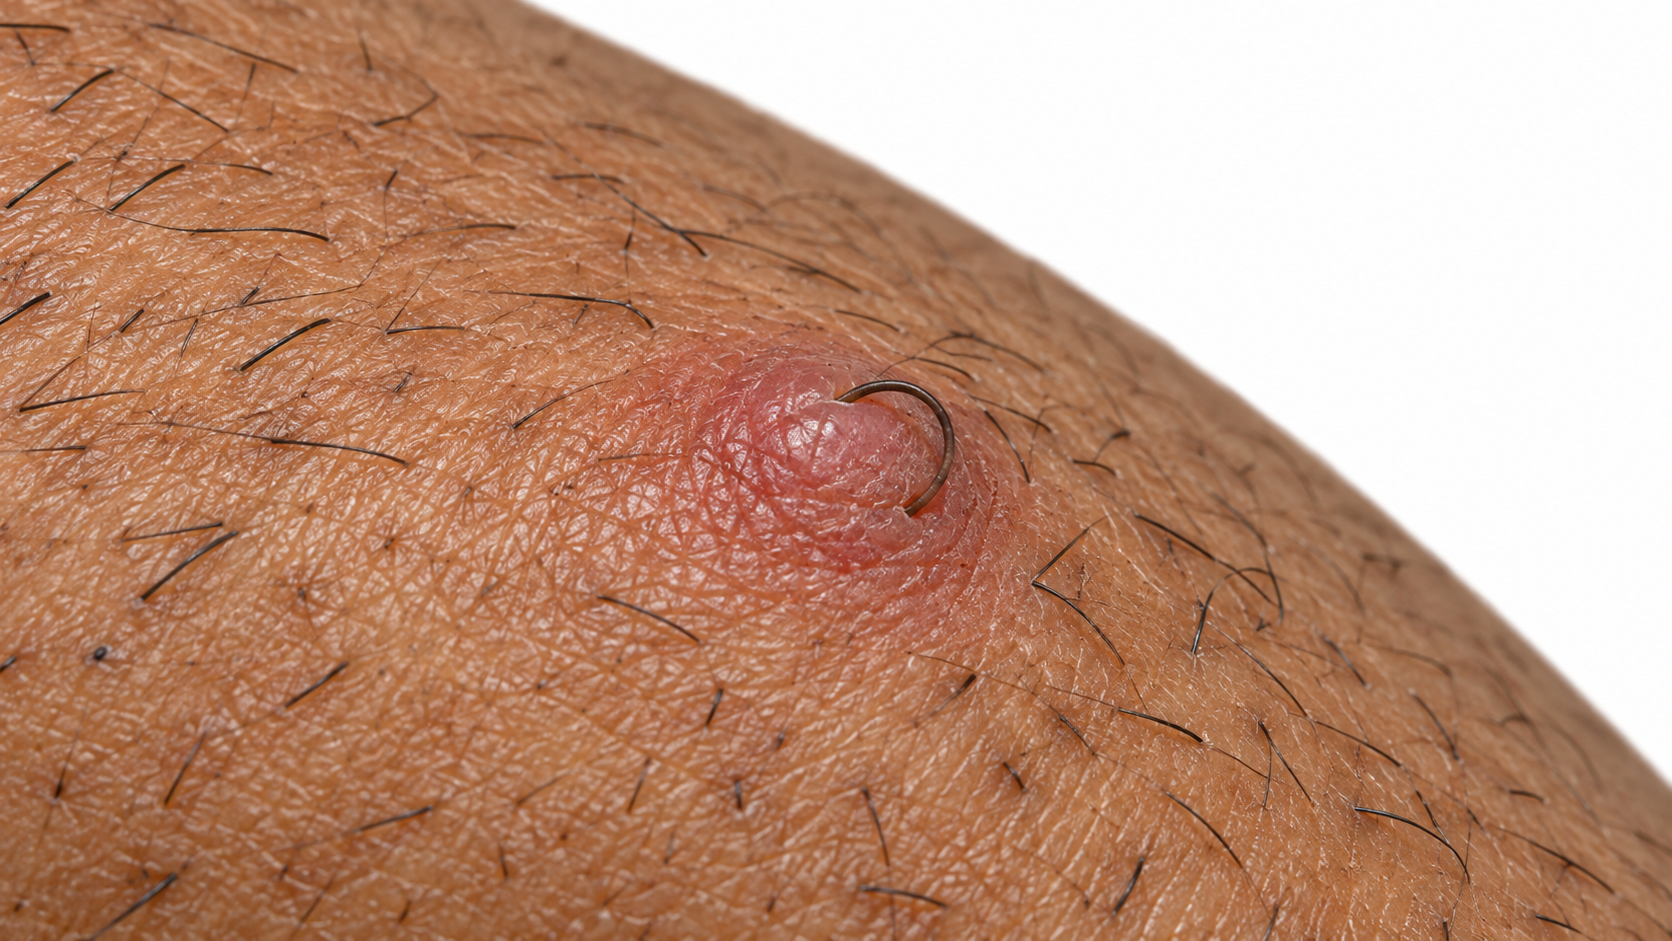
A few firm pink bumps scattered under the jaw and along the upper neck on light skin, with a dark loop of hair visible over one of them.
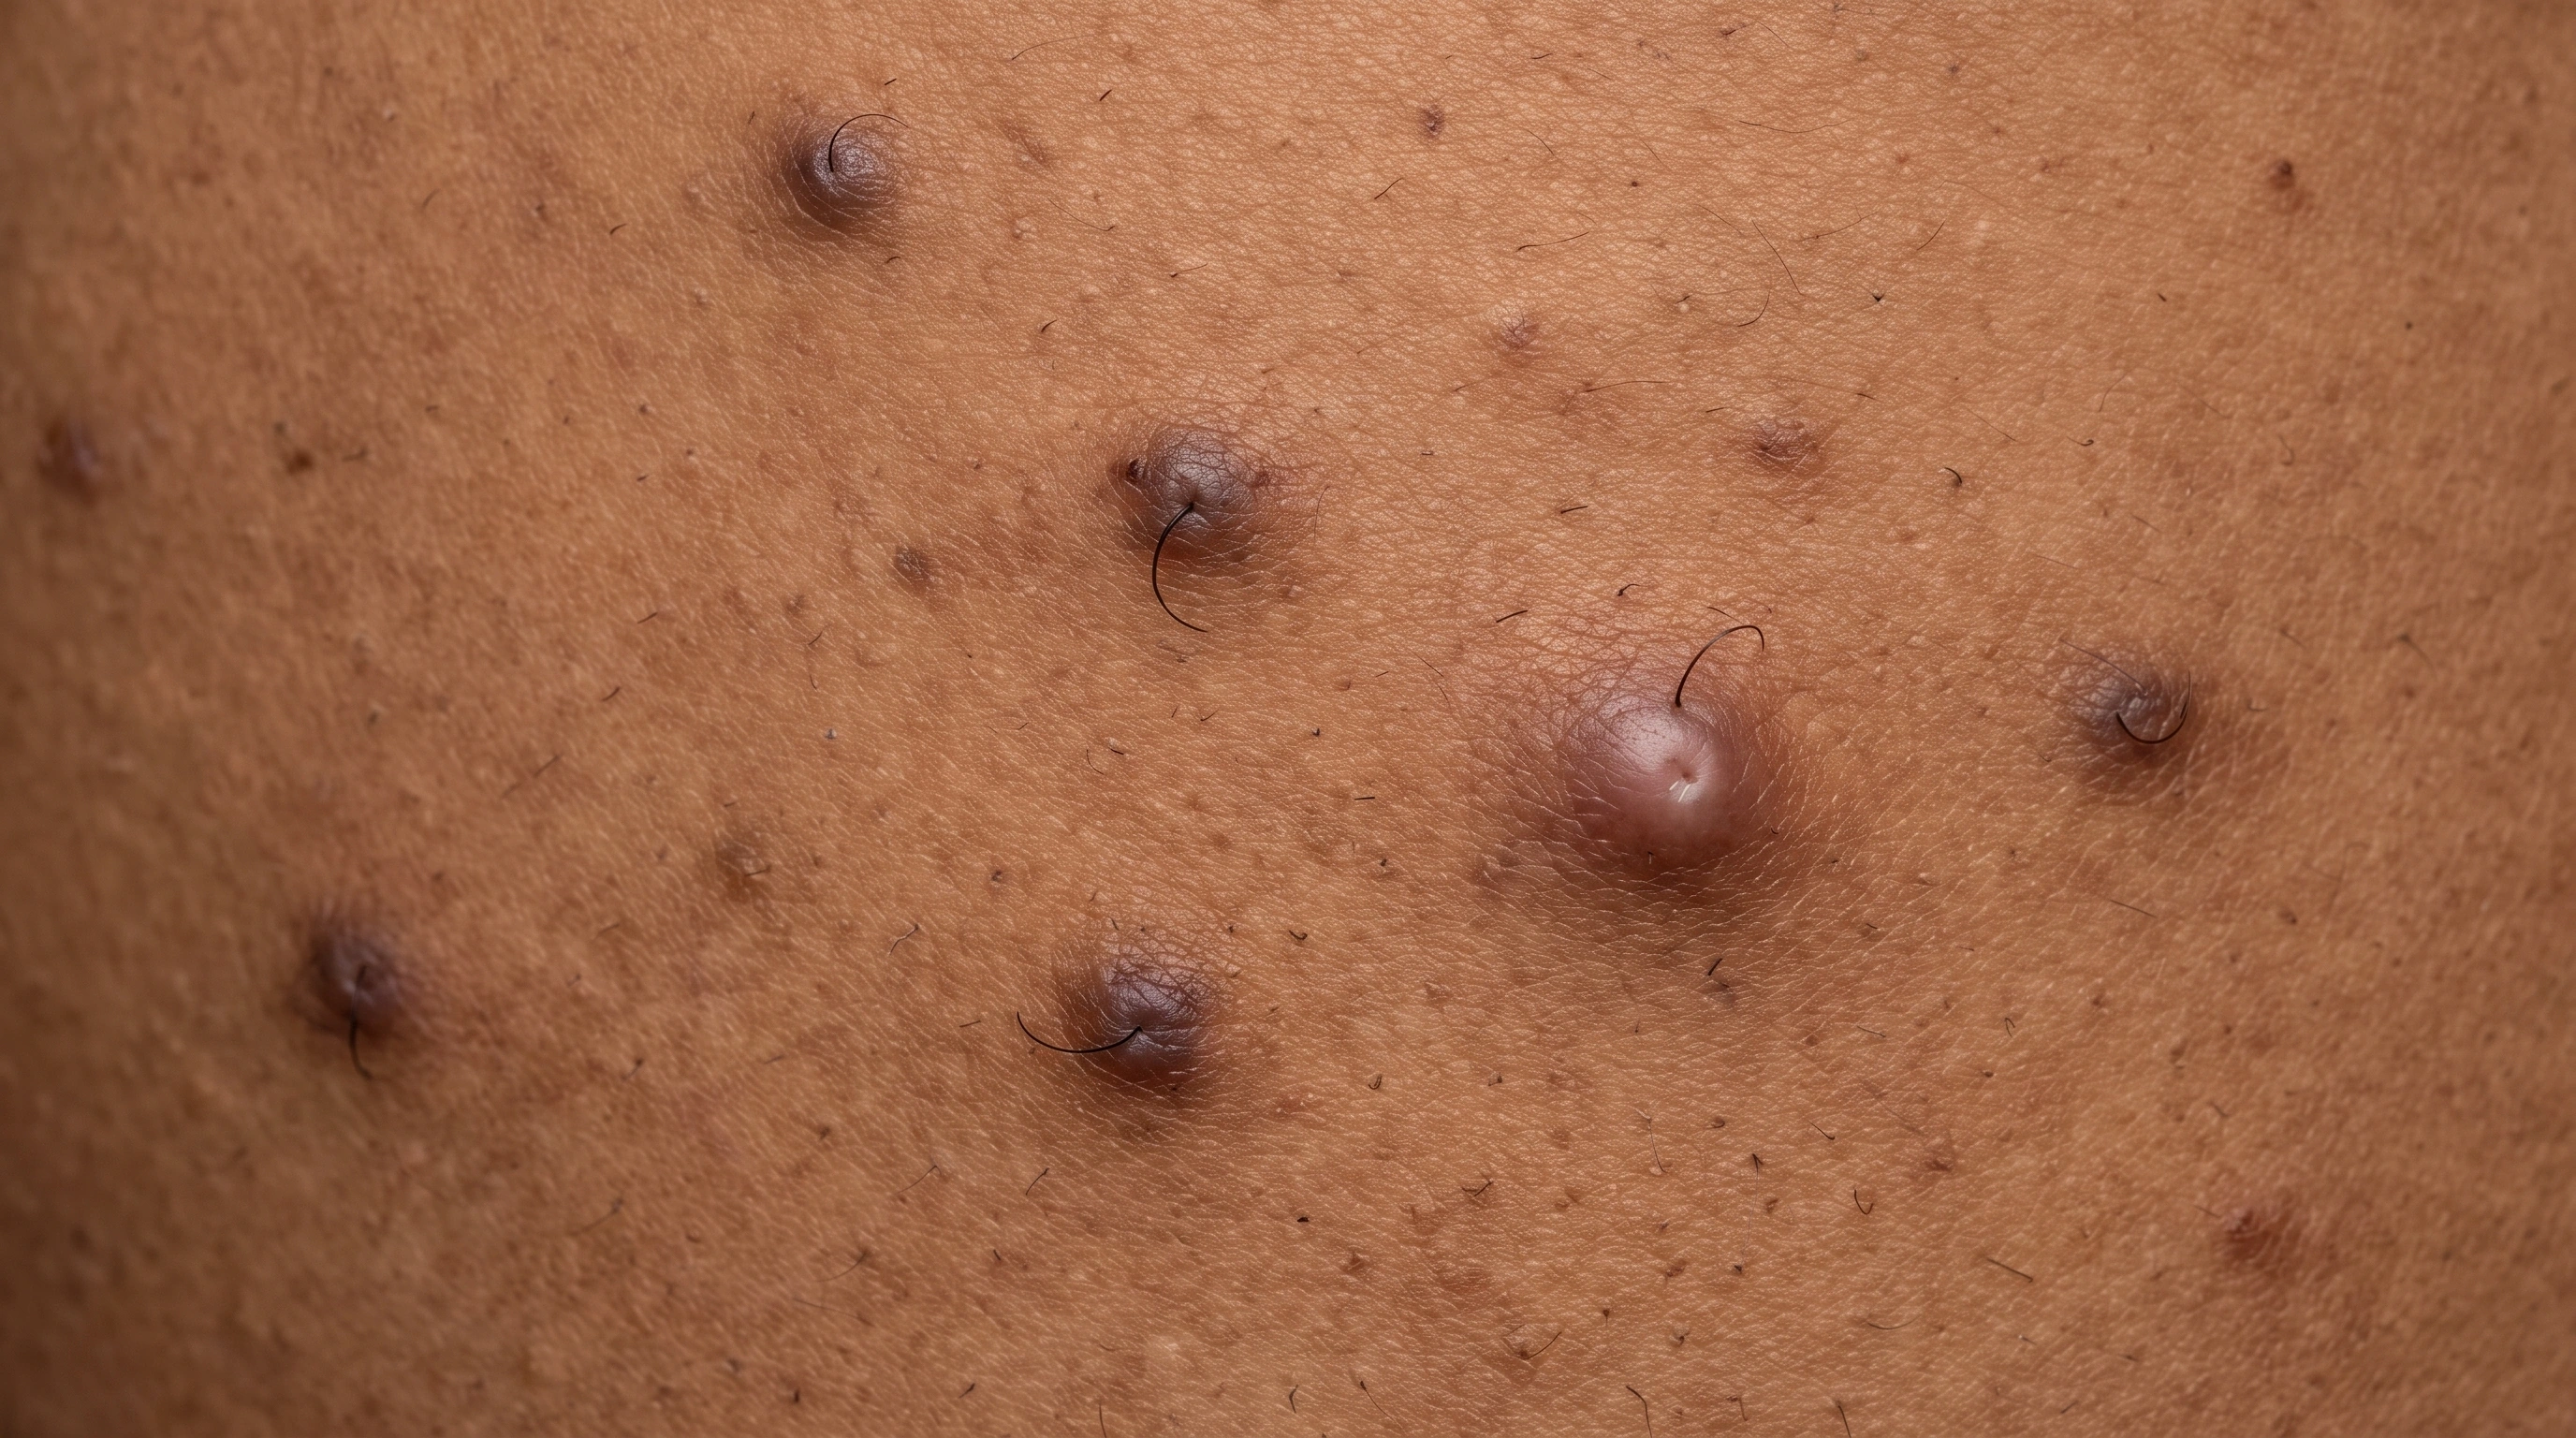
Firm bumps grouped under the jaw and along the upper neck on medium olive-toned skin. The bumps read dusky pink to tan rather than red, and a dark loop of hair is visible over one of them.
Firm bumps crowded under the jaw and along the upper neck on brown skin. The bumps look brown to violet rather than red, and a dark loop of hair is visible over one of them.
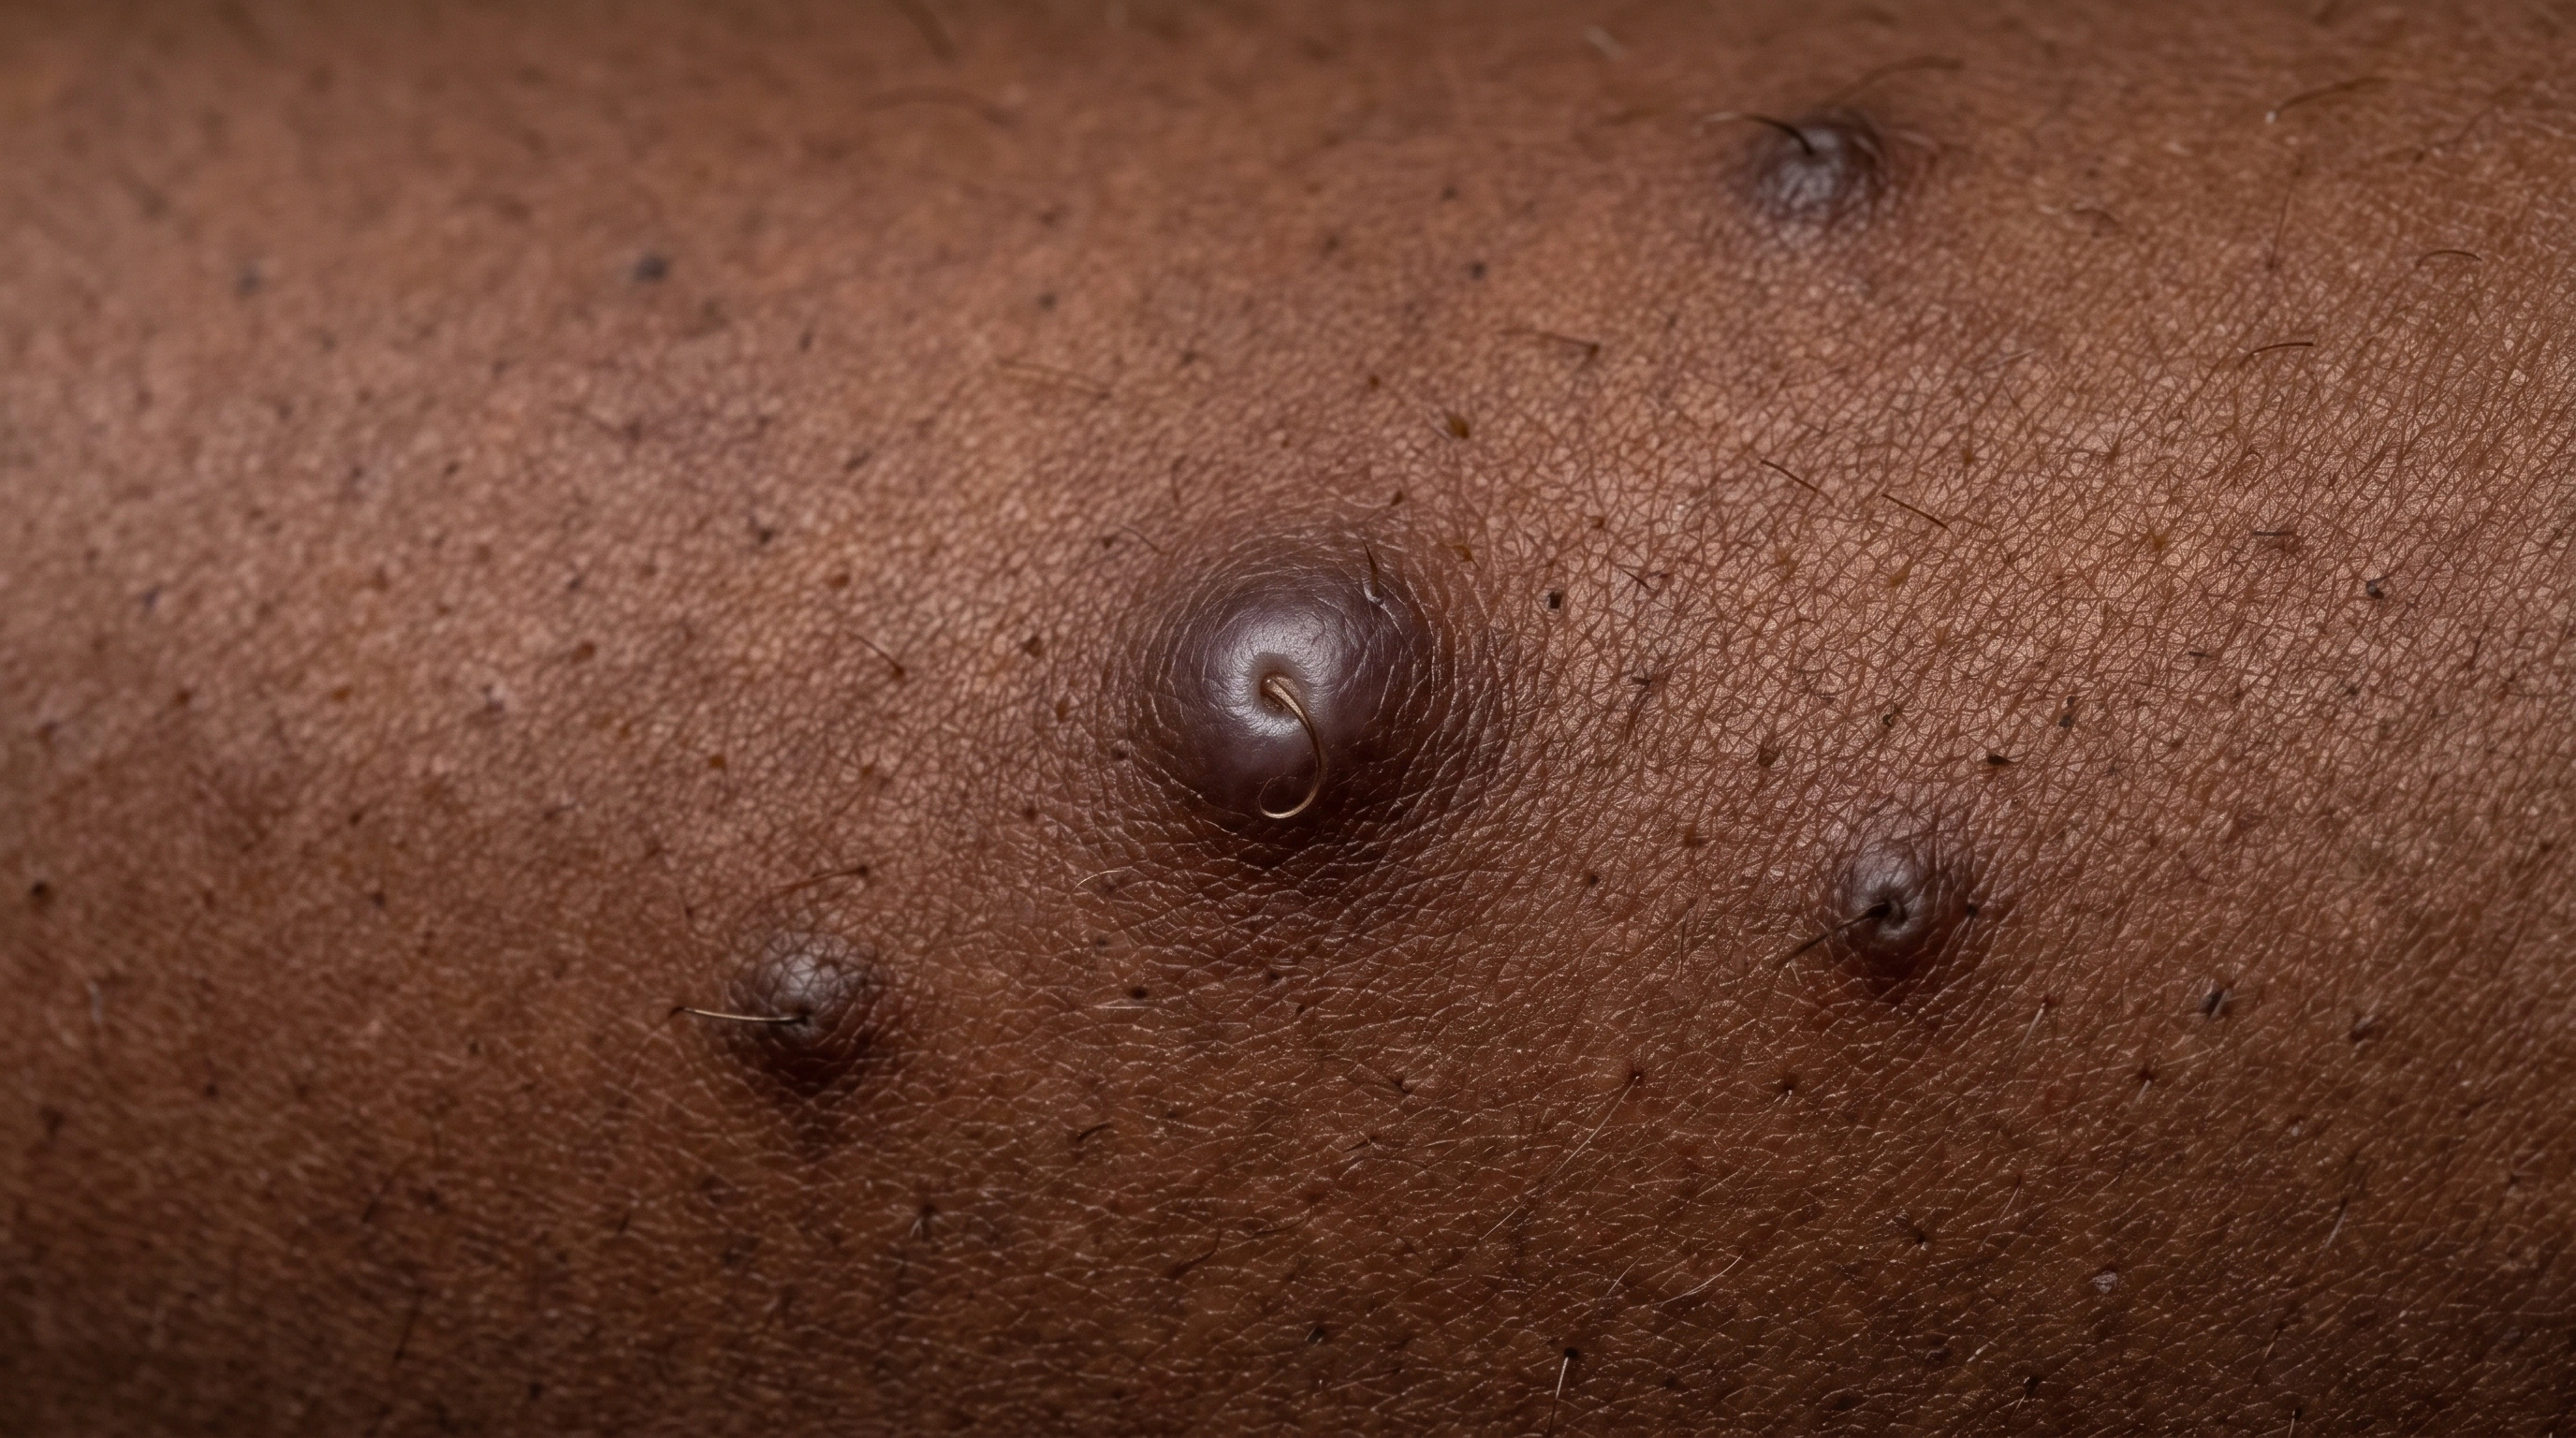
Firm bumps crowded under the jaw and along the upper neck on deep brown skin. The bumps read brown to violet rather than red, with mottled darker marks between them and one firm raised scar along the jaw.
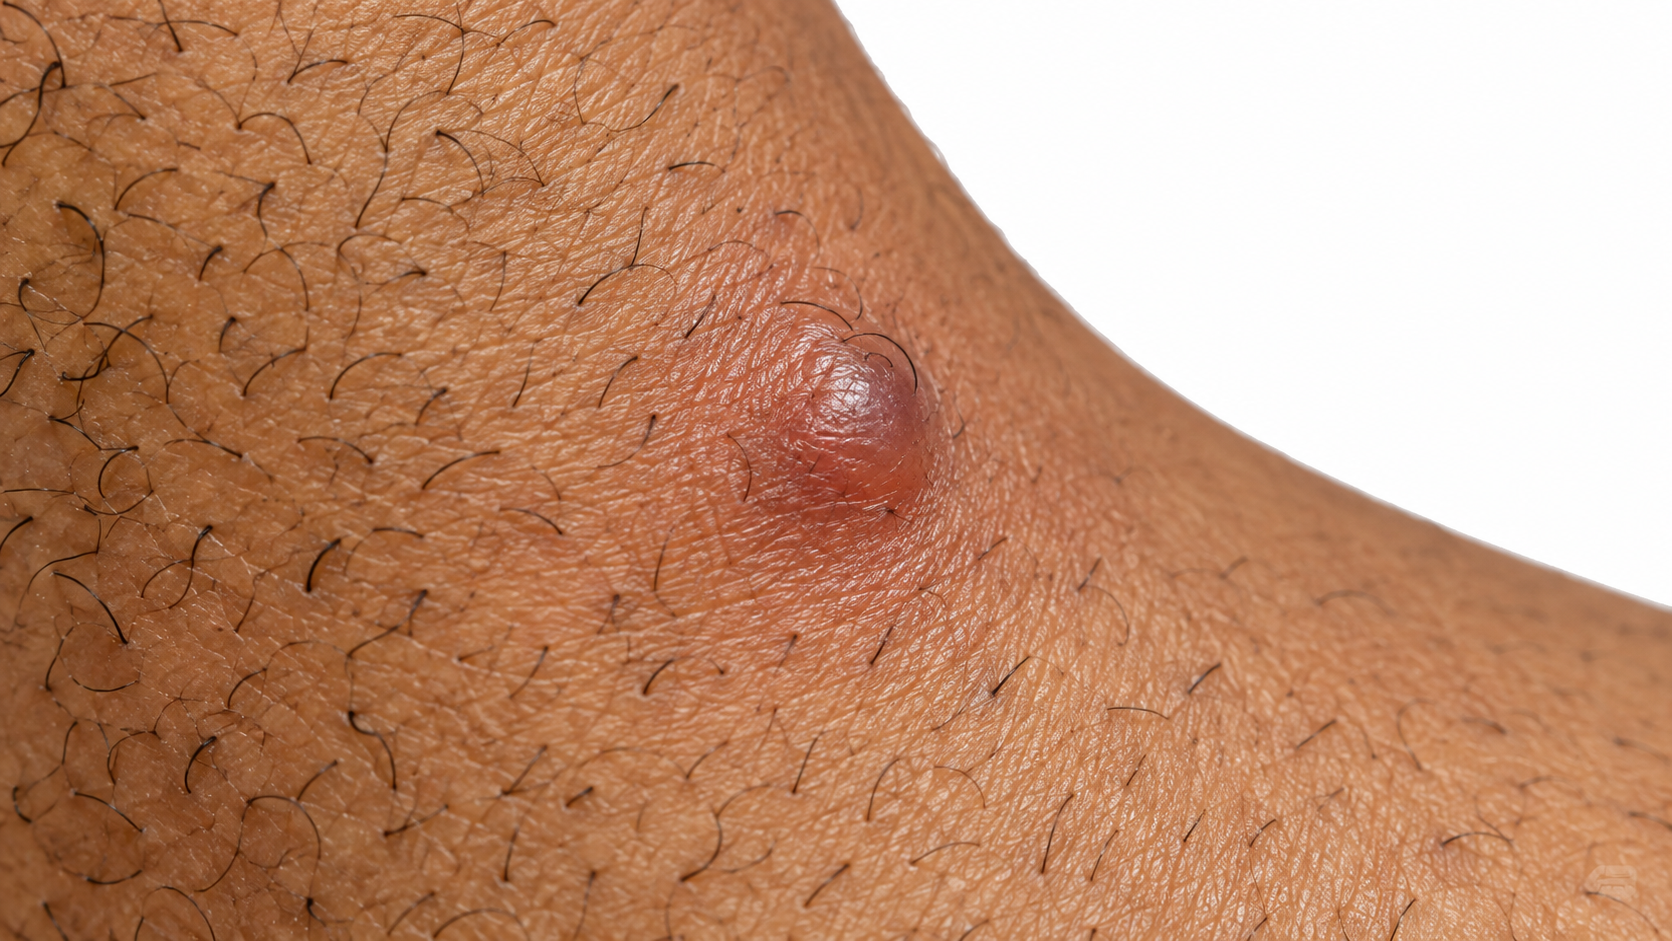
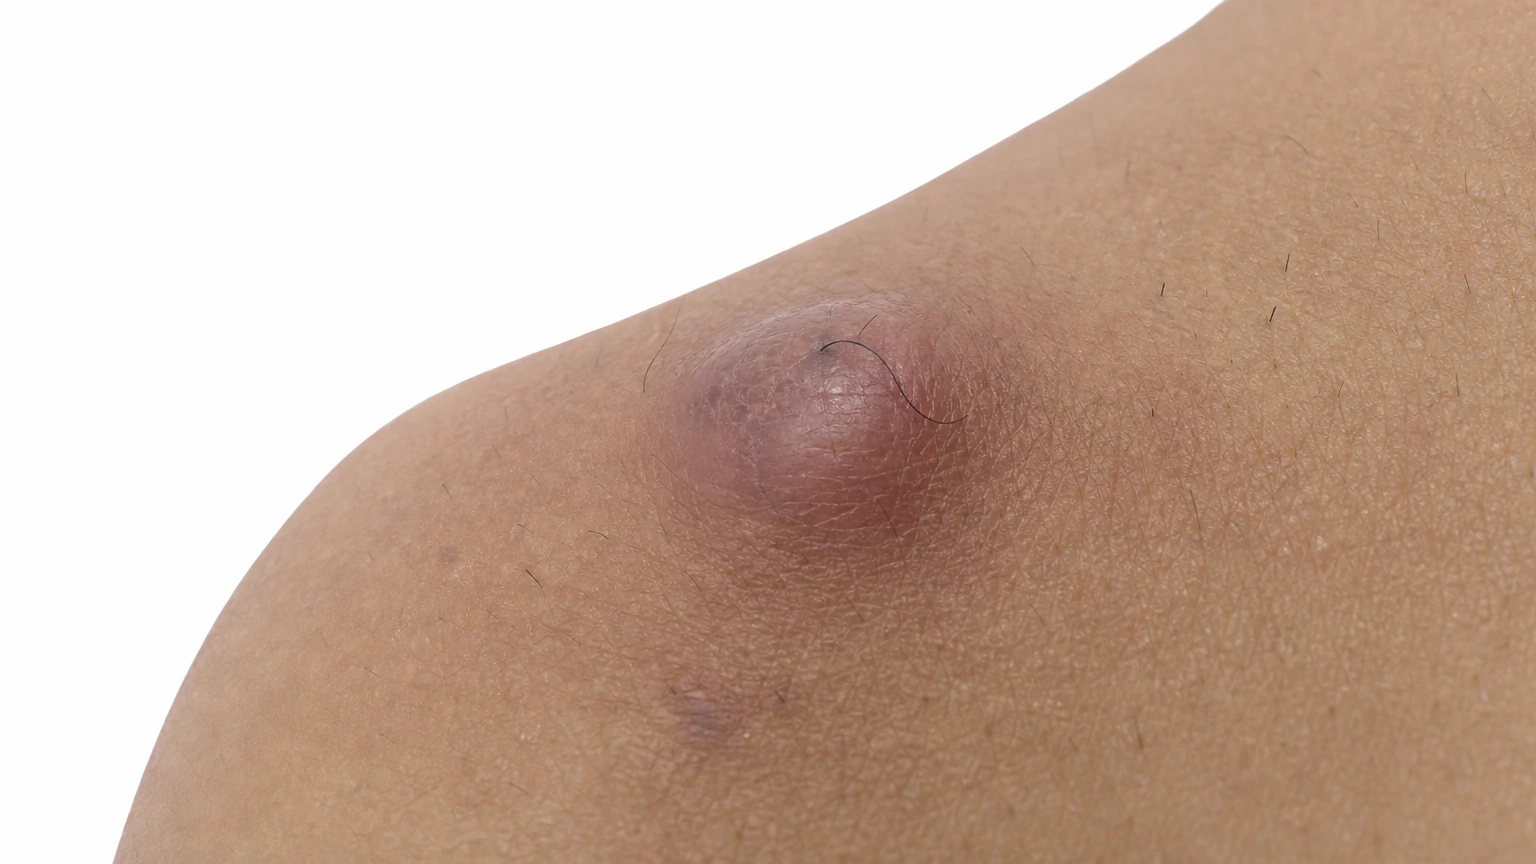
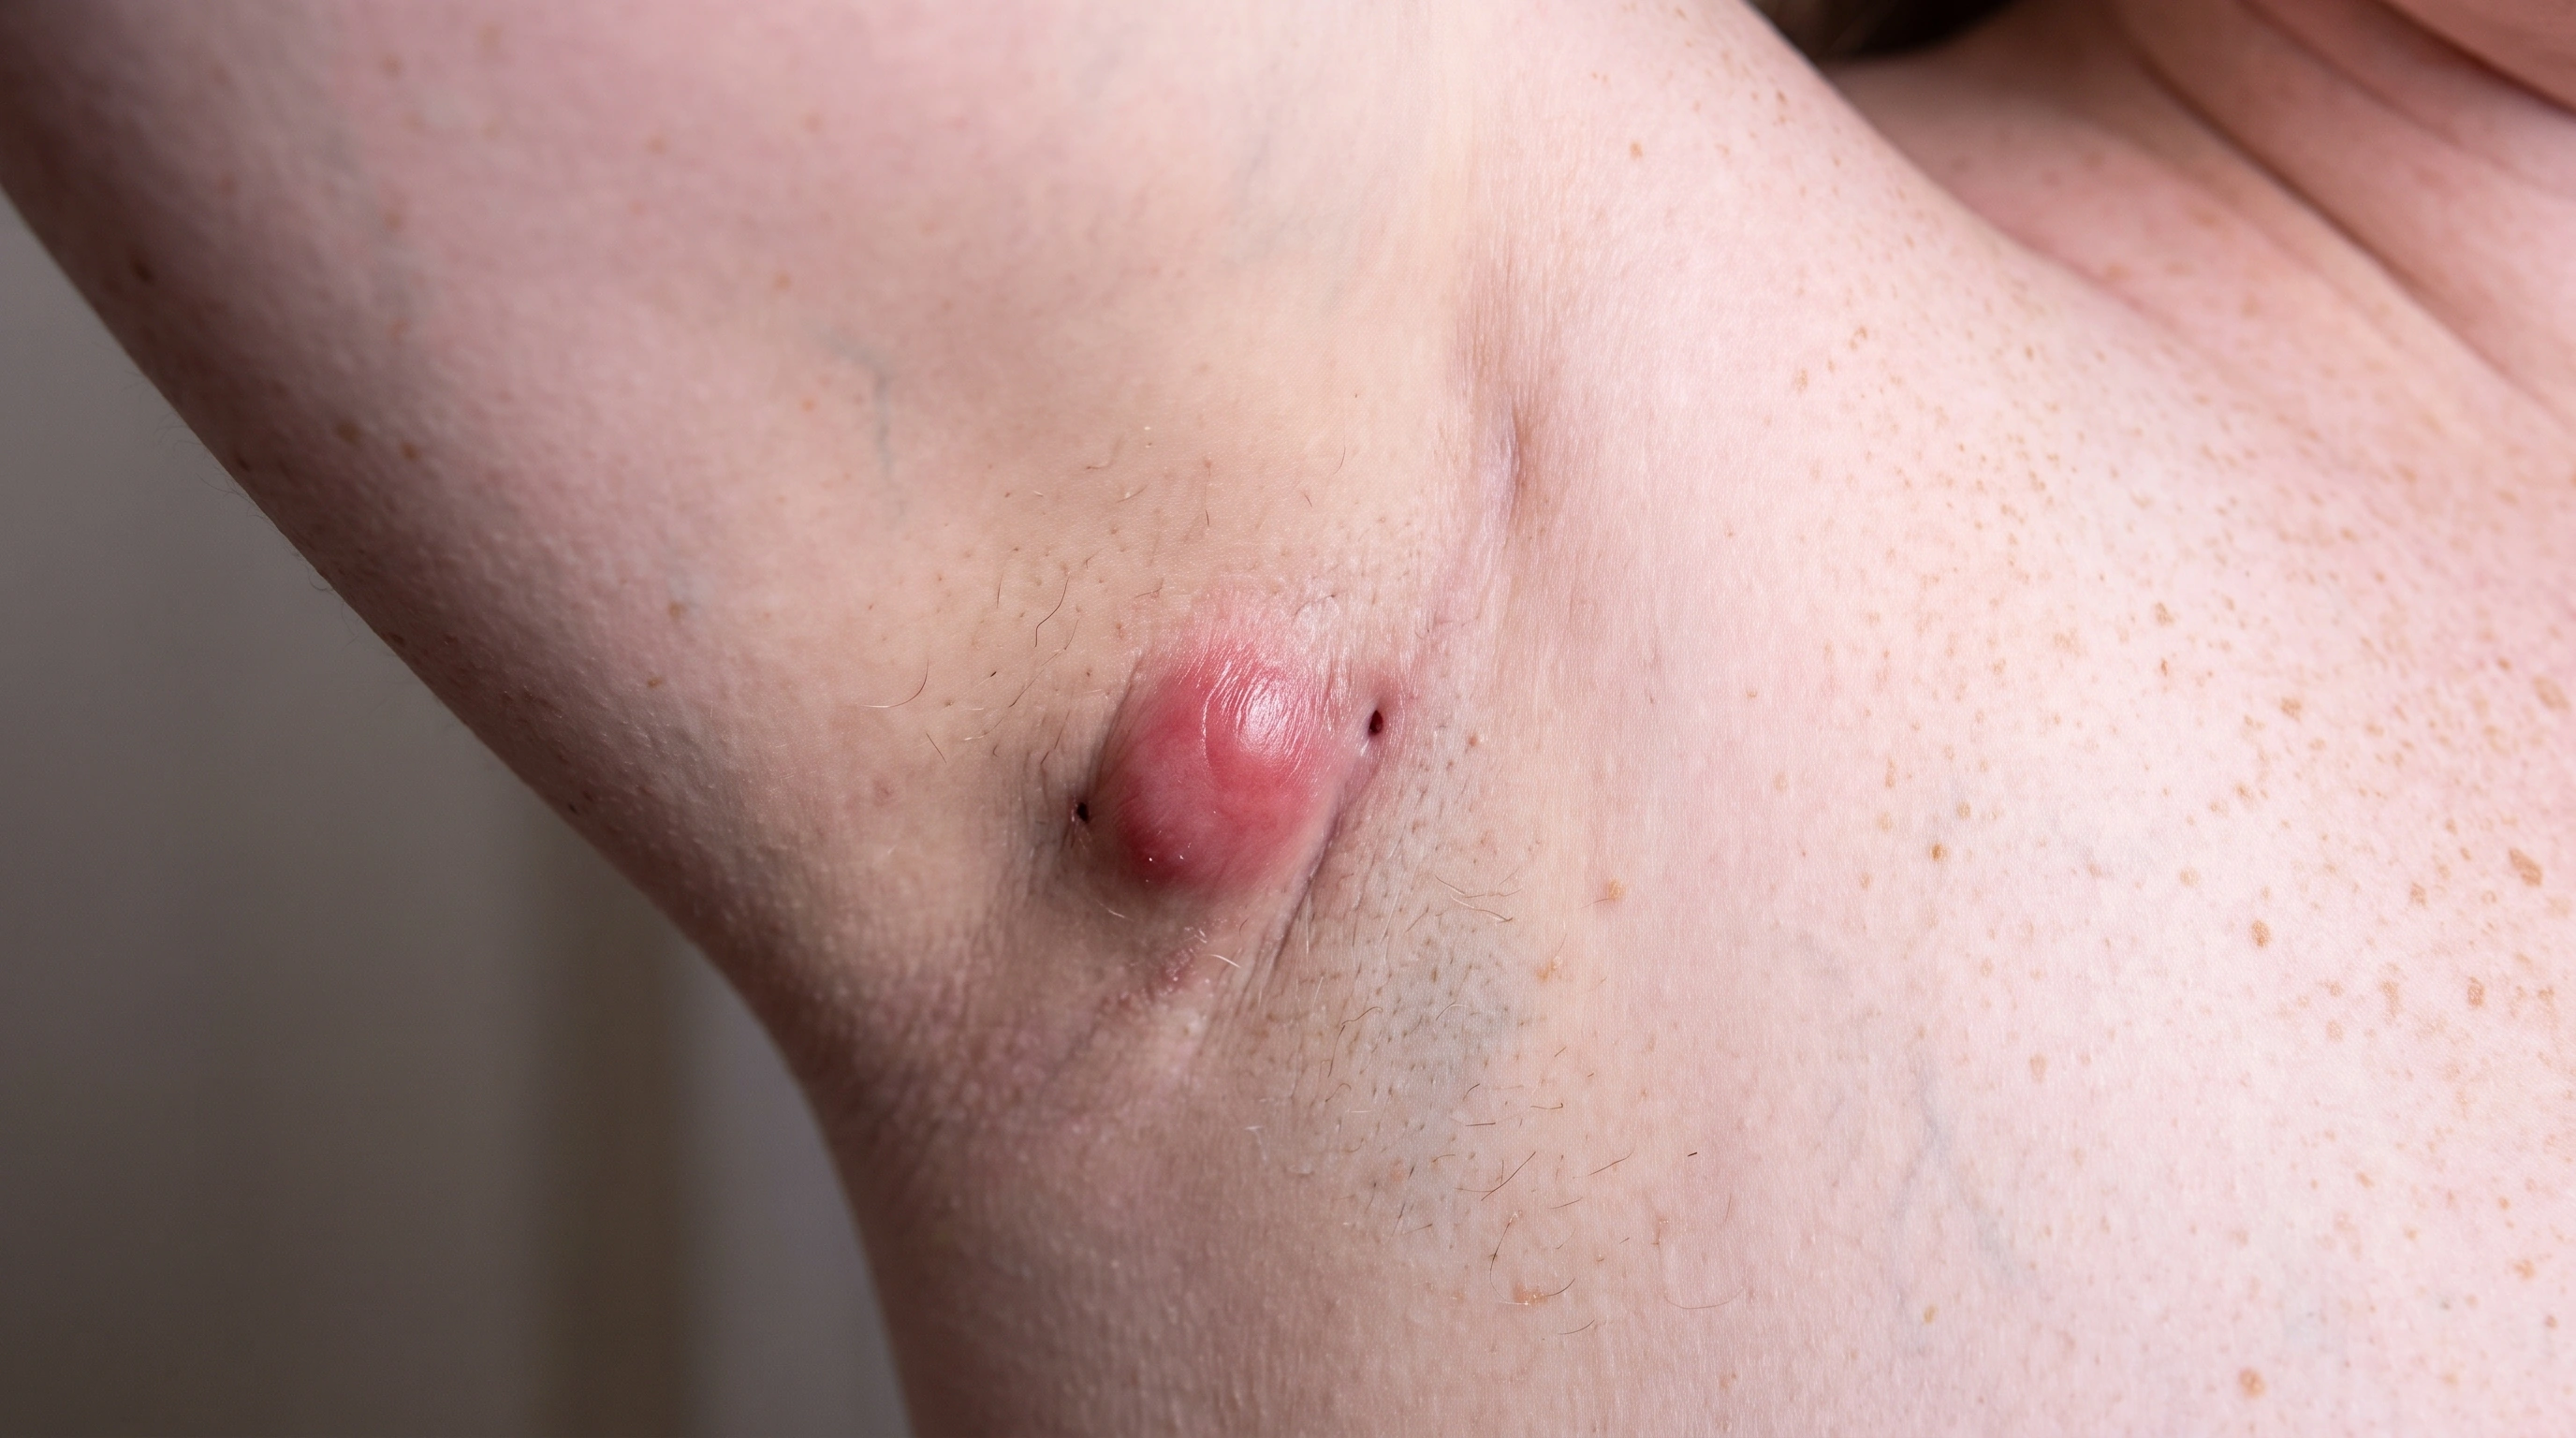
An inflamed lump in the armpit on fair skin. The skin over it is swollen, shiny and red, with a pair of small blackhead-like openings in the skin beside it.
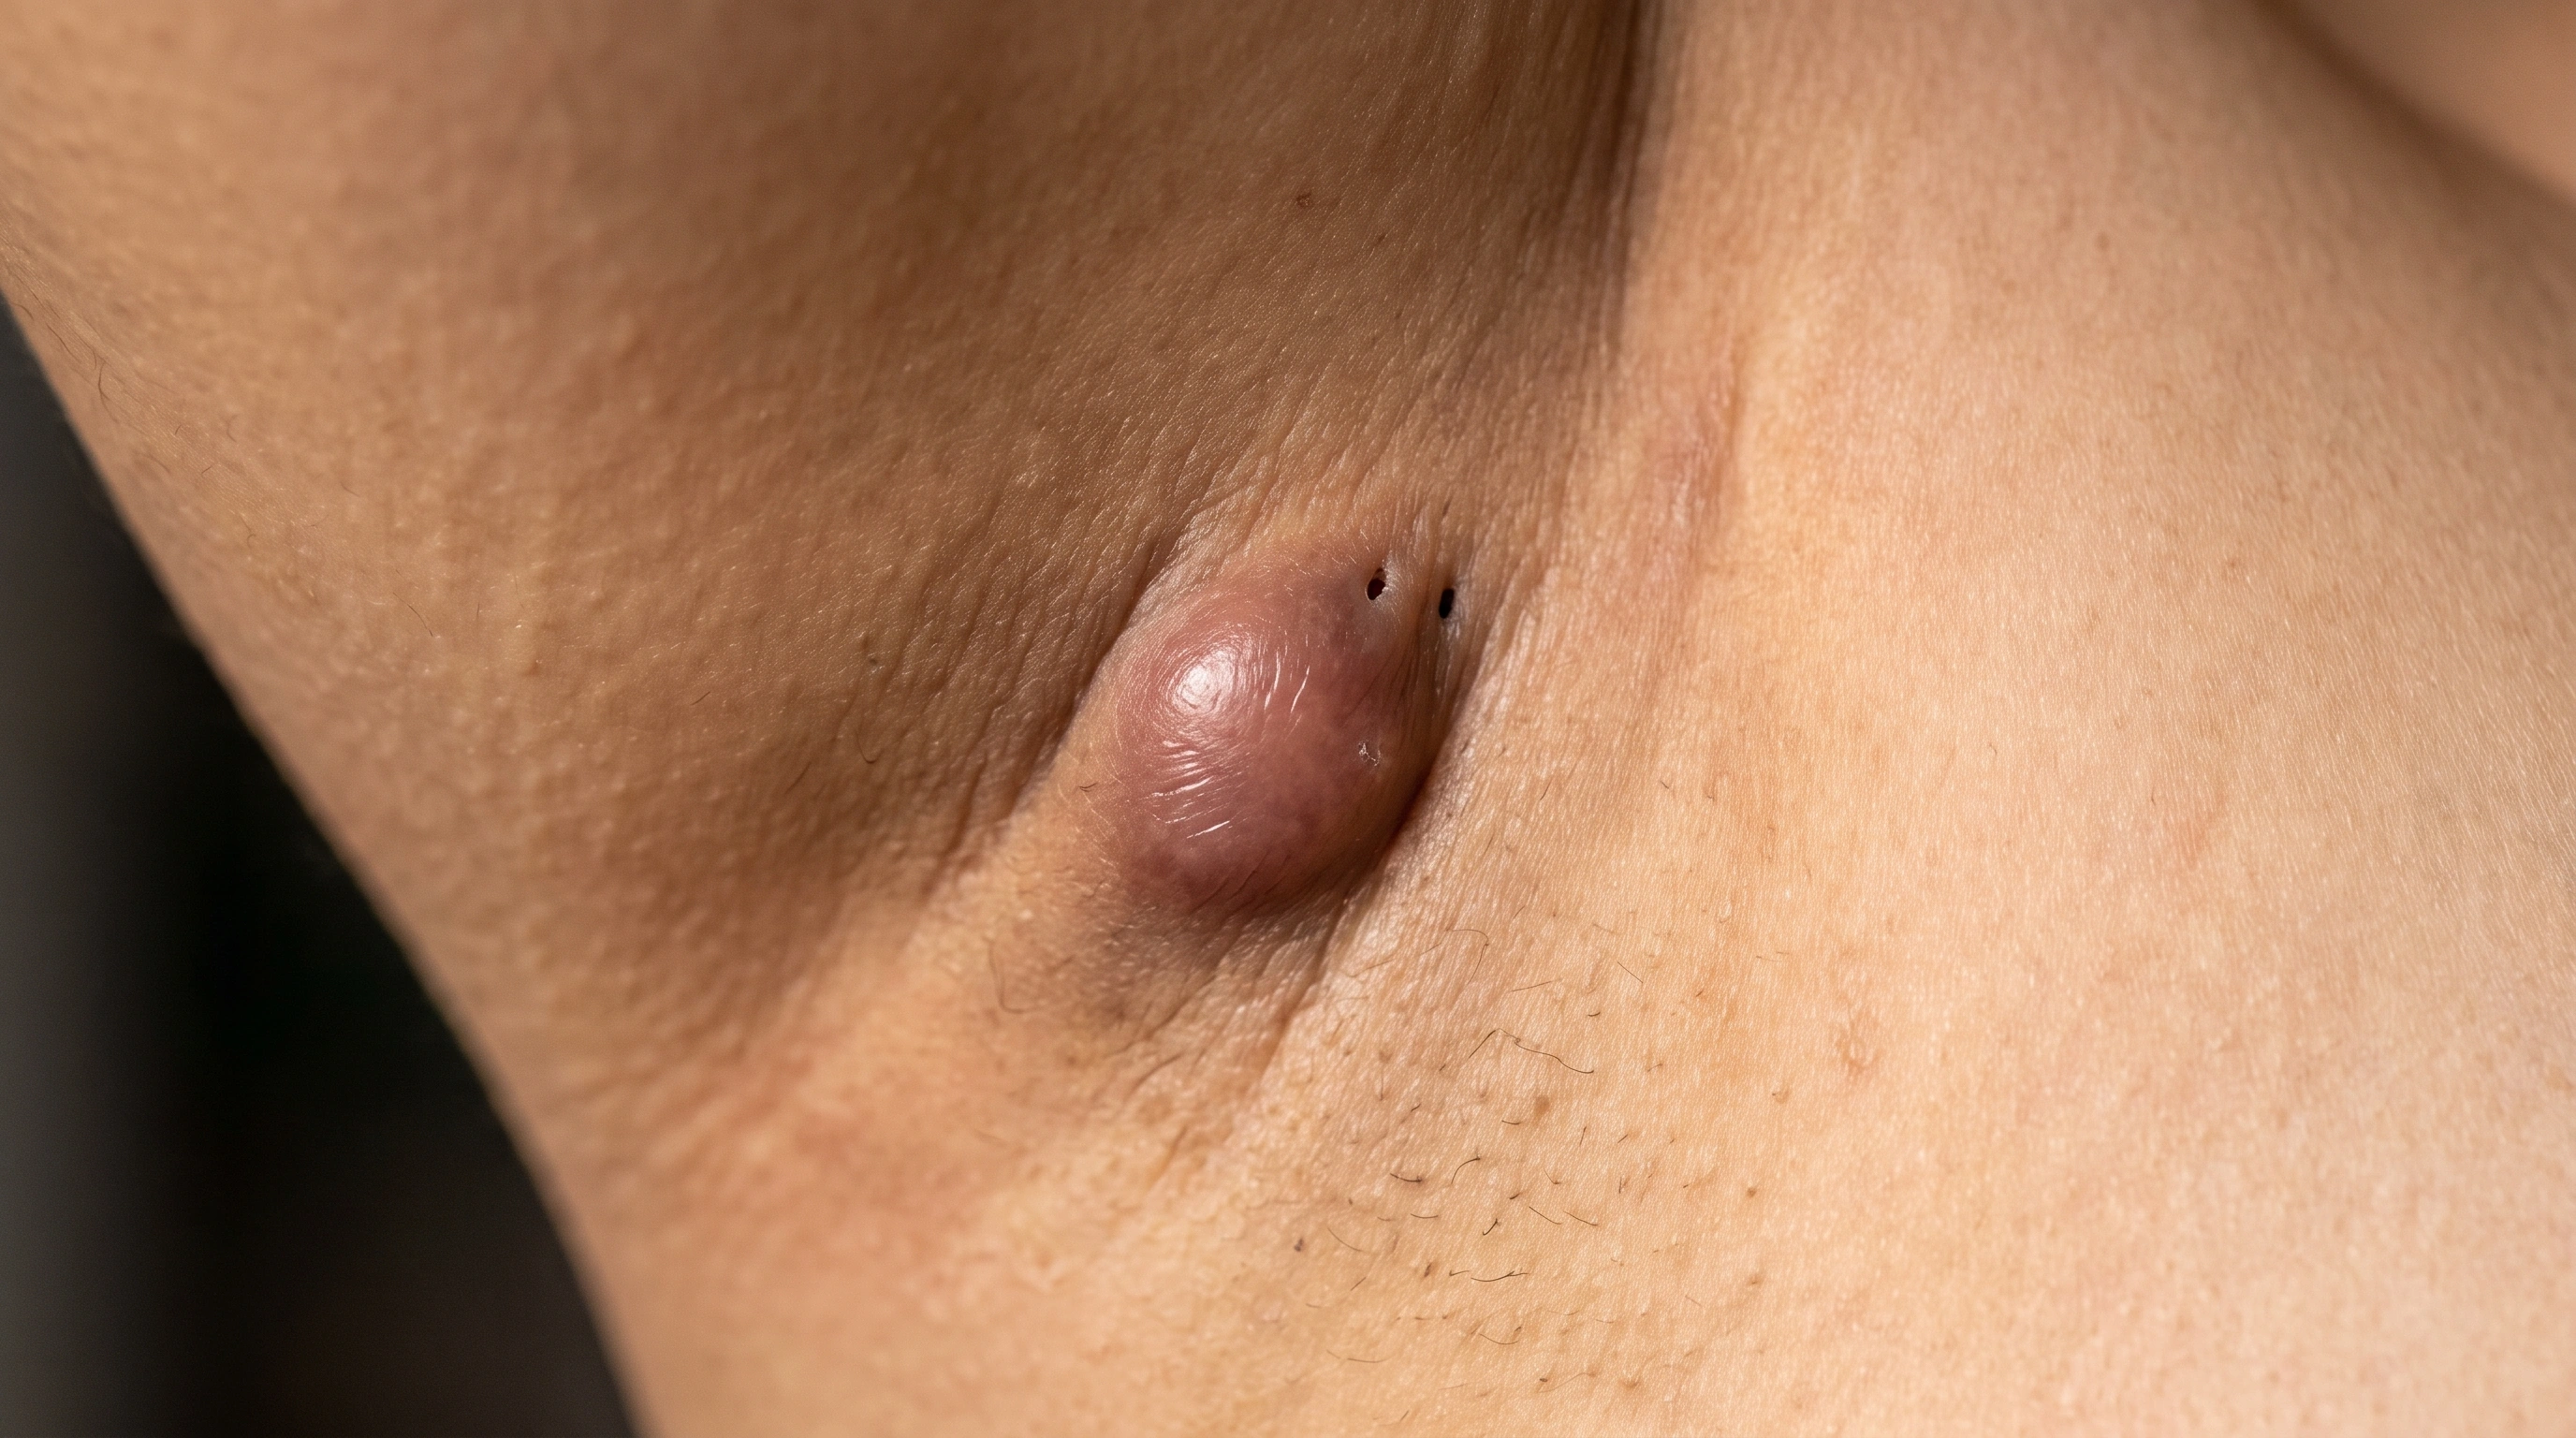
An inflamed lump in the armpit on medium olive skin. The skin over it is swollen and shiny and reads dull pink-brown, with a pair of small blackhead-like openings beside it.
An inflamed lump in the armpit on brown skin. The skin over it is swollen and shiny and reads brown and violet rather than red, with a pair of small blackhead-like openings beside it.
An inflamed lump in the armpit on deep brown skin. The skin over it is swollen and shiny and reads dark brown and violet, with flat dark marks and one thick raised scar from older lumps beside it.
Diagram
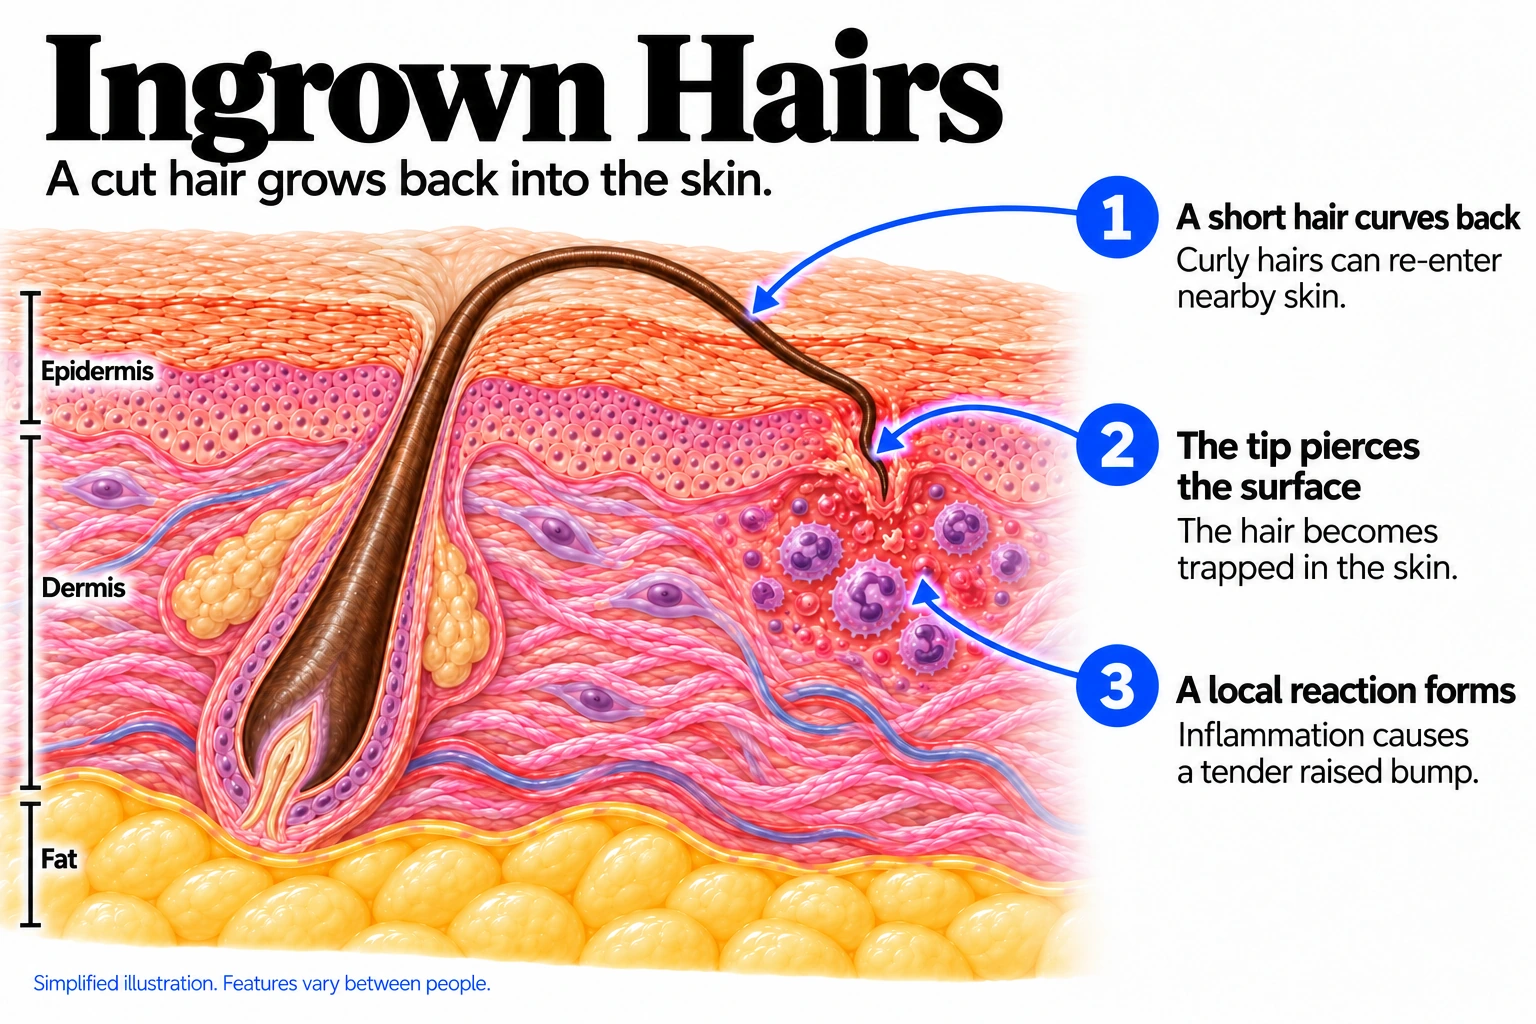
Ingrown Hairs mechanism diagram. A short hair curves back: Curly hairs can re-enter nearby skin. The tip pierces the surface: The hair becomes trapped in the skin. A local reaction forms: Inflammation causes a tender raised bump.
Hidradenitis Suppurativa mechanism diagram. A follicle becomes blocked: The opening widens as material builds up. Rupture drives inflammation: Released contents trigger painful inflammation. Tunnels can develop: Repeated inflammation may leave channels and scars.
In the skin

A hair curves back into nearby skin instead of continuing outward. The trapped hair triggers a local inflammatory reaction that can form a tender raised bump.

Blocked hair follicles can widen and rupture, releasing contents into nearby tissue and triggering painful inflammation. Repeated episodes may lead to tunnels beneath the skin and scarring.

Where it shows up

Shaved or plucked areas
Armpits and other skin folds

When it usually starts

010203040506070+

Ingrown Hairs. Usually begins after shaving or other hair removal, particularly after puberty.

Hidradenitis Suppurativa. Usually begins after puberty, often in the teens or younger adult years.

Causes and triggers

Causes

Ingrown hairs happen when a cut or broken hair curls back into the skin. The body treats the hair as a foreign object and becomes inflamed.

Hidradenitis suppurativa starts with blocked hair follicles in skin folds. The immune system then overreacts, causing deep, painful lumps.

Family tendency

Tightly curled hair is inherited and is the biggest single risk.

About 1 in 3 people with it have a relative with it.

Risk factors
Curly or coarse hair, Frequent shaving, Waxing and plucking
Obesity, Smoking, Female sex, Family history
Trigger
● Ingrown Hairs
● Hidradenitis Suppurativa
Close shaving
Well established
Not listed
Shaving against the grain
Strong link
Not listed
Dull razors
Strong link
Not listed
Tight clothing
Possible
Not listed
Friction and tight clothing
Not listed
Strong link
Heat and sweat
Not listed
Strong link
Hormone changes
Not listed
Strong link
Smoking
Not listed
Well established

Daily Care

Ingrown Hairs
Hidradenitis Suppurativa
Daily care

Habits that help

  • Stop shaving for three to four weeks
    The most effective single treatment.
  • Clippers or a guarded trimmer
    A millimeter of stubble keeps the tip out.
  • A single-blade or safety razor
    Cuts at the surface.
  • Shave with the grain
    Do not stretch, press or repeat.
  • Shave less often
    Every second or third day, never over bumps.
  • Soften first, then lubricate
    Warm water, then gel.
  • An electric foil or rotary shaver
    Cuts above the skin.
  • Sun protection
    Protect healing skin from sunlight to limit darkening of marks.
  • A chemical depilatory cream
    Leaves a soft, feathered end.
  • Eflornithine cream
    Prescription, slows facial hair regrowth.

Avoid

  • Avoid: Shaving as close as possible
    The tip ends below the skin surface.
  • Avoid: Multi-blade cartridge razors
    Later blades cut below the surface.
  • Avoid: Stretching the skin taut while shaving
    The cut hair vanishes as skin relaxes.
  • Avoid: Shaving against the grain
    A closer cut, a sharper tip.
  • Avoid: Going over the same patch repeatedly
    Bumps come from the later passes.
  • Avoid: Shaving every day, or over bumps
    Inflamed skin needs time to settle.
  • Avoid: Dry shaving, or shaving with bar soap
    The blade drags and irritates.
  • Avoid: A dull or dirty blade
    Tugs the hair and leaves a worse tip.
  • Avoid: Waxing, tweezing and epilating
    The regrowing hair has to reopen its way out.
  • Avoid: Digging a hair out with a needle
    Turns a bump into a wound.
  • Avoid: Picking and squeezing
    The same damage, more often.
  • Avoid: Gritty scrubs and stiff brushes
    Inflammation, and the hair stays put.
  • Avoid: Alcohol-heavy aftershaves
    Sting broken skin, add irritation.
  • Avoid: Tight collars, straps and underwear
    Friction pushes hairs back in.
  • Avoid: Sun on healing marks
    Makes marks deeper and slower to fade.

Habits that help

  • Stopping smoking
    The highest-value change available.
  • Warm compresses
    Ease pain and help a lump come to a head.
  • Loose breathable clothing
    Cotton, no waistband over a fold, damp clothes changed promptly.
  • Weight loss where it applies
    Less friction, less background inflammation.
  • Absorbent dressings
    Not treatment, but the right dressing changes daily life.
  • Topical clindamycin
    An antibiotic lotion for mild disease, with benzoyl peroxide.
  • Clindamycin with rifampicin
    Two antibiotics together for moderate disease.
  • Hormonal treatment
    Spironolactone or a combined pill, where flares track the cycle.
  • Metformin
    Added where there is insulin resistance or polycystic ovary syndrome.
  • Track flares around your menstrual cycle
    Many people flare reliably the week before a period.
  • Discuss sustainable weight goals where relevant; avoid blame or crash dieting
    More friction, more affected folds, more background inflammation.

Avoid

  • Avoid: Smoking
    The clearest avoidable factor, and it acts on the disease itself.
  • Avoid: Squeezing or lancing at home
    Pushes the contents sideways and helps a tunnel form.
  • Avoid: Friction and tight clothing
    Waistbands, seams, tight jeans and underwire set flares off.
  • Avoid: Shaving and waxing the area
    Both irritate the follicle and cause ingrowns.
  • Avoid: Heat and trapped sweat
    Hot weather, and damp gym gear left on.
  • Avoid: Deodorants and antiperspirants
    Fragrance or alcohol on inflamed skin irritates.
  • Avoid: Stress and poor sleep
    Both raise background inflammation.
  • Avoid: Waiting it out
    Every untreated year is more chance of tunnels.
  • Avoid: Stopping treatment when it works
    Control is maintenance. Flares return within weeks to months.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Ingrown Hairs
● Hidradenitis Suppurativa
Filter by type
Ingrown hair pattern

Select one or more.

Hidradenitis stage

Select one or more.

Over-the-counter
Illustration: Generic topical cream tube and white cream.

Depilatory cream

Limited evidence

A chemical hair remover dissolves the hair rather than cutting it, leaving a soft feathered end that does not spear the skin. Used every few days instead of shaving it genuinely reduces bumps. The trade-off is real: it smells strong and it irritates or burns some people, so test a small patch and never use it on skin that already has active bumps.

Existing reference image of Microneedling vs Microdermabrasion — At Home.

Exfoliating scrubs and brushes

Limited evidence

Gritty scrubs and stiff brushes are sold for this and they are the wrong tool. Scrubbing does not free a hair that is already through the follicle wall, and it adds inflammation to skin that has too much. If you want exfoliation here, use a gentle glycolic or salicylic acid instead.

Five adapalene gel 0.1% tubes and boxes lined up on white, including Differin, Effaclar, PanOxyl and Neutrogena

Adapalene

Limited evidence

A retinoid gel used at night on the shaved area. It thins the plug over the follicle opening so a growing hair is more likely to find its way out, and it slowly evens the dark marks left by old bumps. It takes six to twelve weeks and it does not stop a hair curving back in, so it works alongside a change of razor rather than instead of one.

Four glycolic acid toner and liquid bottles lined up on white, one with its box

Glycolic Acid

Limited evidence

A leave-on lotion or toner used two or three times a week keeps the follicle openings clear, which is the point where a curved hair gets stuck. It also helps the flat dark marks fade. Use it on days you do not shave, because acid on freshly shaved skin stings and adds irritation.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

Does much the same job as glycolic acid and suits oilier skin and the bikini line better, because it gets into the follicle itself. Two or three times a week is enough. It is not an exfoliating scrub, and it will not free a hair that is already trapped.

Three acne wash tubes on white: Differin Deep Cleanser, CeraVe Acne Foaming Cream Cleanser and PanOxyl

Benzoyl Peroxide

Limited evidence

Worth adding when the bumps carry pinpoints of pus, because bacteria have joined in on top of the trapped hair. A wash or a low-strength gel on the shaved area is enough. It does nothing about the hair itself, and it bleaches towels and collars, so keep the strength low and the expectations modest.

Five azelaic acid tubes and bottles on white, most marked 10 percent, from Peach Slices, Paula's Choice, Facetheory, The Ordinary and Naturium

Azelaic Acid

Limited evidence

Aimed at the marks rather than the bumps. It calms inflammation and slowly lifts the flat dark patches left along the jaw and neck, and it is gentle enough for skin that is shaved regularly. It works over months, not weeks, and only once new bumps have stopped forming.

Three acne wash tubes on white: Differin Deep Cleanser, CeraVe Acne Foaming Cream Cleanser and PanOxyl.

Benzoyl Peroxide wash

Limited evidence

An antiseptic wash used two or three times a week on the affected folds, lathered and rinsed rather than left on. It lowers the bacteria on the skin and is often paired with clindamycin lotion to stop resistance building. It will not stop lumps forming on its own, and it bleaches towels and dark clothing.

Existing Dermapedia illustration of zinc supplements.

Ibuprofen and acetaminophen

Limited evidence

For flare pain, which is at its worst in the day or two before a lump bursts or is drained. Taken regularly through a flare they work better than taken only at the peak. If they are not touching the pain, that is a reason to be seen rather than to take more, because a steroid injection settles a single lump far faster.

Existing Dermapedia illustration of chlorhexidine wash.

Chlorhexidine wash

Limited evidence

An alternative antiseptic wash for the folds if benzoyl peroxide is too drying or bleaches too much. Same use: lather, rinse, a few times a week. It reduces the odor some people find hardest to live with. It does nothing about the inflammation underneath, so it is a support rather than a treatment.

Existing Dermapedia illustration of zinc supplements.

Zinc supplements

Limited evidence

Oral zinc is often suggested online for this condition. The studies behind it are small and uncontrolled, and it has not been shown to change flares in any reliable way. High doses upset the stomach and interfere with copper absorption over time. Worth mentioning to your doctor rather than starting alone.

Existing illustration of Absorbent dressings.

Absorbent dressings

Listed

Not a treatment, but the thing that changes daily life most for anyone with a draining lesion. A soft absorbent pad held with tubular netting or a stretchy vest handles the fluid without an adhesive that tears sore skin. A dermatology nurse can advise which dressing suits which site, and many are available on prescription.

Prescription topicals

Eflornithine

Moderate evidence

Eflornithine cream. A prescription cream that slows facial hair regrowth, so there is less hair to cut and shaving can be done less often. It is used twice a day on the face and neck alongside your usual hair removal, not instead of it. It does not remove hair, and the effect fades within weeks of stopping.

Tretinoin — Header Image

Tretinoin

Limited evidence

The prescription-strength version of the retinoid approach, used at night on the beard and neck. It keeps follicle openings clear and does more for the dark marks than anything else on a shelf. It makes skin drier and more easily irritated by a razor for the first month or two, so build up slowly and shave more gently while you do.

A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Limited evidence

An antibiotic lotion, usually prescribed with benzoyl peroxide, for when a lot of the bumps have gone pustular. It settles the infected ones faster than benzoyl peroxide alone. It is a short course rather than a permanent fix, because the trapped hair, not the bacteria, is what starts each bump.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh

Hydrocortisone

Limited evidence

A low-strength steroid cream calms a badly inflamed patch quickly and takes the soreness out of it. It is a short course of days, prescribed for a specific flare, not something to keep using. Facial and neck skin thins with repeated steroid use, and it does nothing about the hair that caused the bump.

A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Moderate evidence

A twice-daily antibiotic lotion for mild disease, the one topical here with real trial evidence behind it. It reduces the number of lumps and abscesses, and in early disease works about as well as tetracycline tablets. It is nearly always paired with a benzoyl peroxide wash, because clindamycin used alone breeds resistant bacteria.

Resorcinol

Limited evidence

Resorcinol 15% cream. A peeling cream dabbed on a building lump to help it open and settle faster, made up by a compounding pharmacy. Some people find it shortens a flare noticeably. It stings, it can leave a temporary dark stain on deeper skin tones, and it only goes on the lump itself, not across the whole fold.

Prescription pills
None listed
An amber prescription bottle lying on its side on a white background with a plain white label reading Doxycycline, and six small round white tablets spilled out in front of it.

Doxycycline

Moderate evidence

A tetracycline antibiotic taken for two to three months, used here for its anti-inflammatory effect rather than to kill an infection. That is why the course is months rather than a week. It reduces flares for many people with mild to moderate disease, and it generally stops working once it is stopped. Take it with water and stay upright afterwards, and expect to burn more easily in the sun.

Two separate illustrative capsule bottles labeled Clindamycin and Rifampicin.

Clindamycin with rifampicin

Moderate evidence

Two antibiotics taken together for a set ten to twelve week course in moderate disease, usually when tetracyclines have not held. The combination works better than either alone. Rifampicin turns urine and tears orange, stains soft contact lenses, and interferes with several medicines including the contraceptive pill, so the doctor needs your full medicine list.

Spironolactone — Header Image

Spironolactone

Limited evidence

A hormonal tablet that suits people whose flares track the menstrual cycle. The evidence is from clinics rather than large trials, but the response in the right person can be very good. It takes three to six months to judge, it raises potassium so blood tests are needed, and it must not be used in pregnancy.

An illustrative blister pack and white sleeve labeled Birth Control Pills.

Birth Control Pills

Limited evidence

A combined pill can reduce flares that cluster before periods, and it is often used alongside spironolactone rather than instead of it. Progesterone-only methods sometimes make the condition worse. Smoking matters here in two ways: it worsens the disease and it also rules out the combined pill for many people over 35.

An illustrative bottle labeled Metformin beside plain tablets.

Metformin

Limited evidence

A diabetes tablet sometimes added where there is insulin resistance, polycystic ovary syndrome or metabolic syndrome alongside the skin disease. Small studies show fewer flares in that group. It is an add-on, not a main treatment, and it commonly upsets the stomach for the first few weeks.

Prednisone — Header Image

Prednisone

Limited evidence

A short course of steroid tablets to break a severe flare while a longer-term treatment is being arranged. It works quickly. It is not a way to manage this condition, because flares return as the dose comes down and repeated courses cause weight gain, bone loss and blood sugar problems.

A white blister pack photographed flat on a white background, holding eight white oblong capsules in two rows of four under clear domes. ACCUTANE is printed in blue capitals on the empty left half of the foil.

Accutane

Limited evidence

Isotretinoin transforms severe acne, so it is a fair question here. It works much less well for this condition, which starts in the follicle but is not driven by oil, and many people are no better on it. Acitretin, a related tablet, has slightly better results. Neither can be used in pregnancy.

Injections
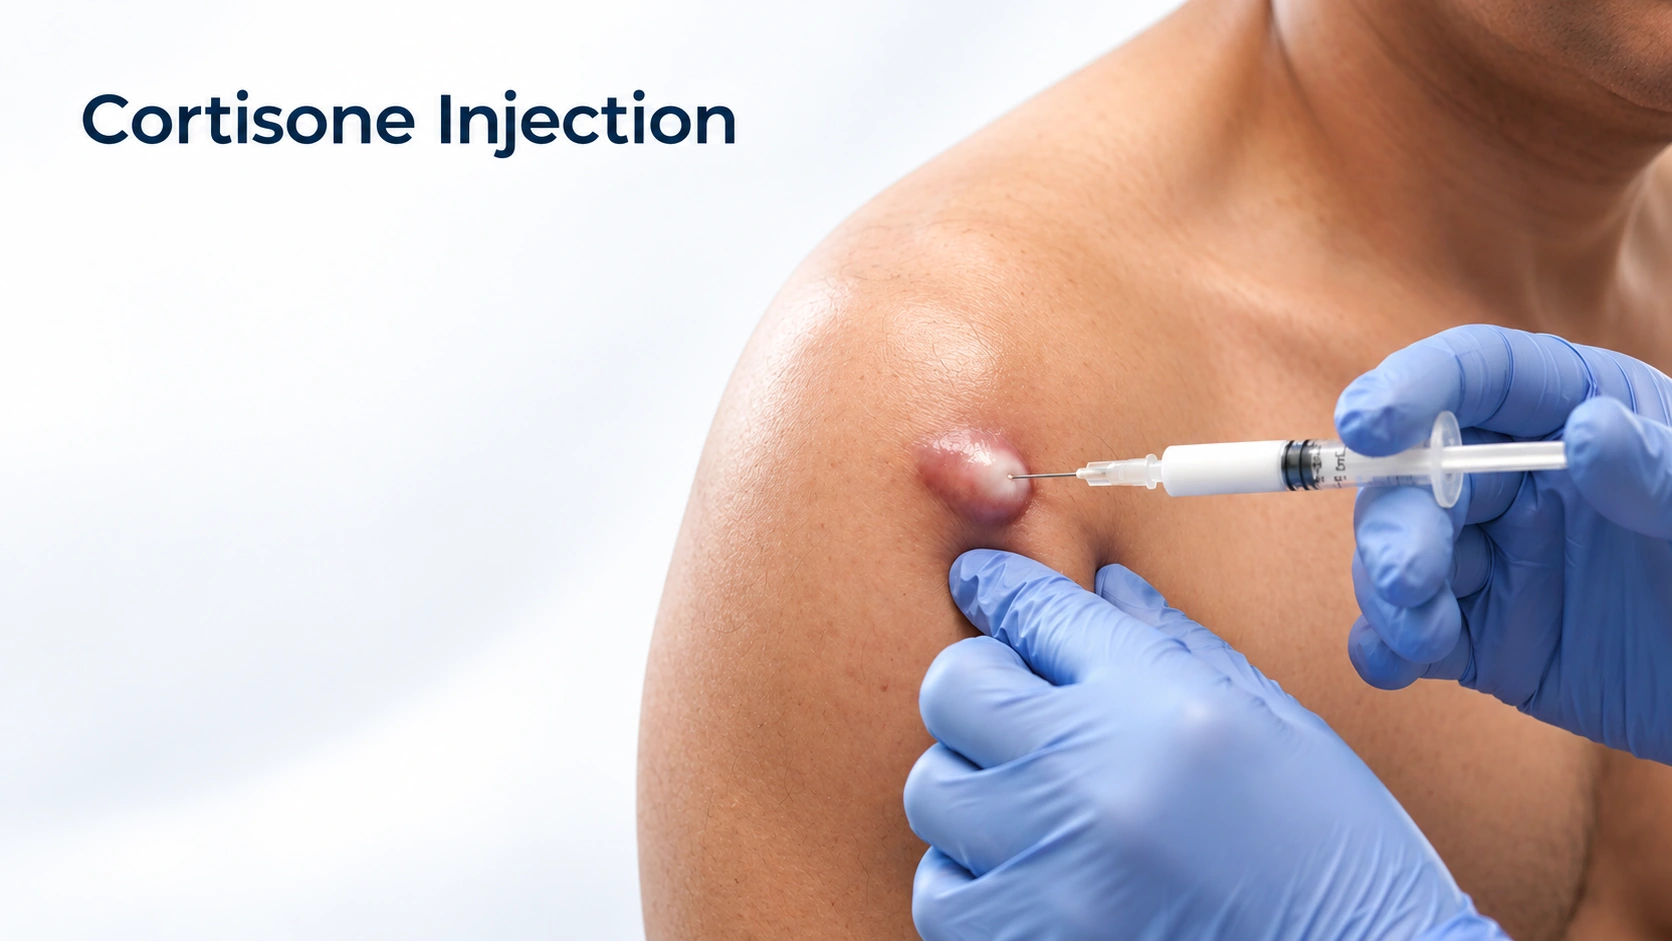
Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Limited evidence

A steroid injected directly into a firm raised or keloid scar left by old bumps. It flattens and softens the scar over a series of visits a few weeks apart. It treats what is already there and does nothing to prevent the next one, and repeated injections can leave a pale or dented patch.

Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Limited evidence

A small amount of steroid injected straight into a single painful lump, which usually settles it within a day or two. It is the fastest thing available for one bad flare and it avoids cutting. It treats that one lump only, and repeated injections in the same spot can thin the skin, so it is not a plan on its own.

A silver and dark pink autoinjector pen labeled Humira lying on a white background

Humira

Strong evidence

The first biologic licensed for this condition, given as a self-injection under the skin every week or two. It blocks one of the immune signals driving the disease and reduces lumps and abscesses in moderate to severe cases. It does not close existing tunnels. You are screened for tuberculosis and hepatitis first, and infections need reporting while you are on it.

An illustrative capped injection pen labeled Cosentyx; packaging is conceptual.

Cosentyx

Strong evidence

A newer biologic injection that blocks a different immune signal, licensed for this condition after trials in moderate to severe disease. It is the usual next step when adalimumab has not worked or has stopped working. Like adalimumab, it treats the inflammation rather than the tunnels, so it is often combined with surgery.

Procedures
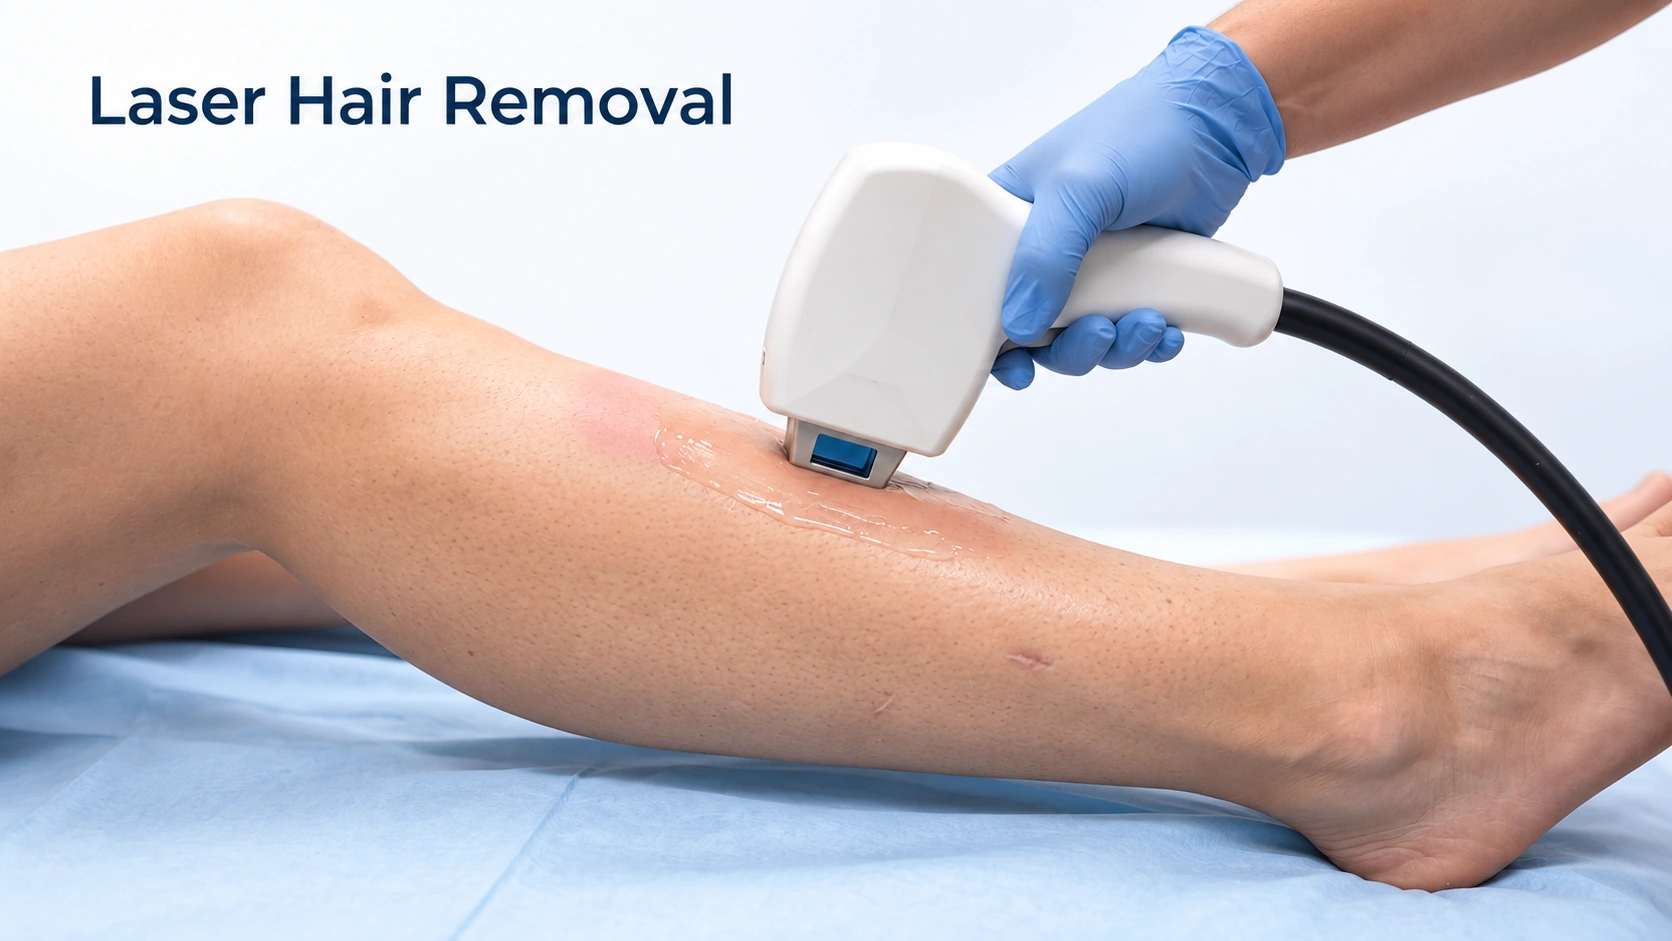
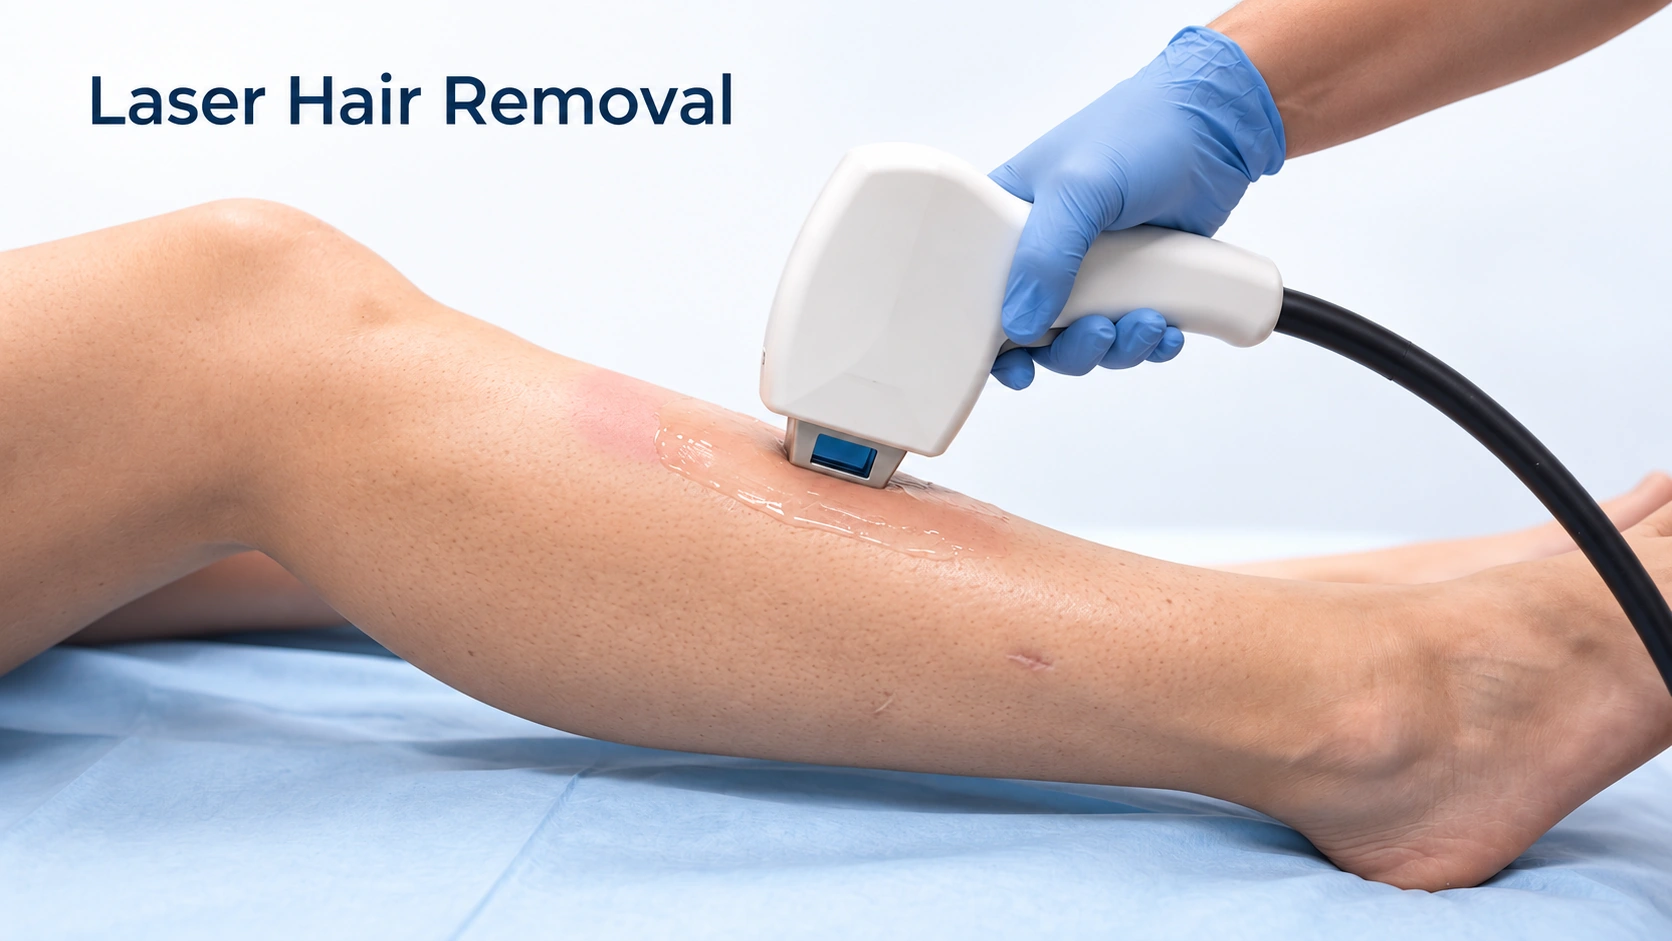
Editorial illustration for Laser Hair Removal, based on the entry’s treatment or equipment reference.

Laser Hair Removal

Strong evidence

The most durable treatment there is for this, because it reduces the number of hairs that can become ingrown at all. It usually takes a series of sessions and it thins rather than eliminates hair for most people, with occasional touch-ups. It is the option to ask about when scarring is starting or when a job requires close shaving.

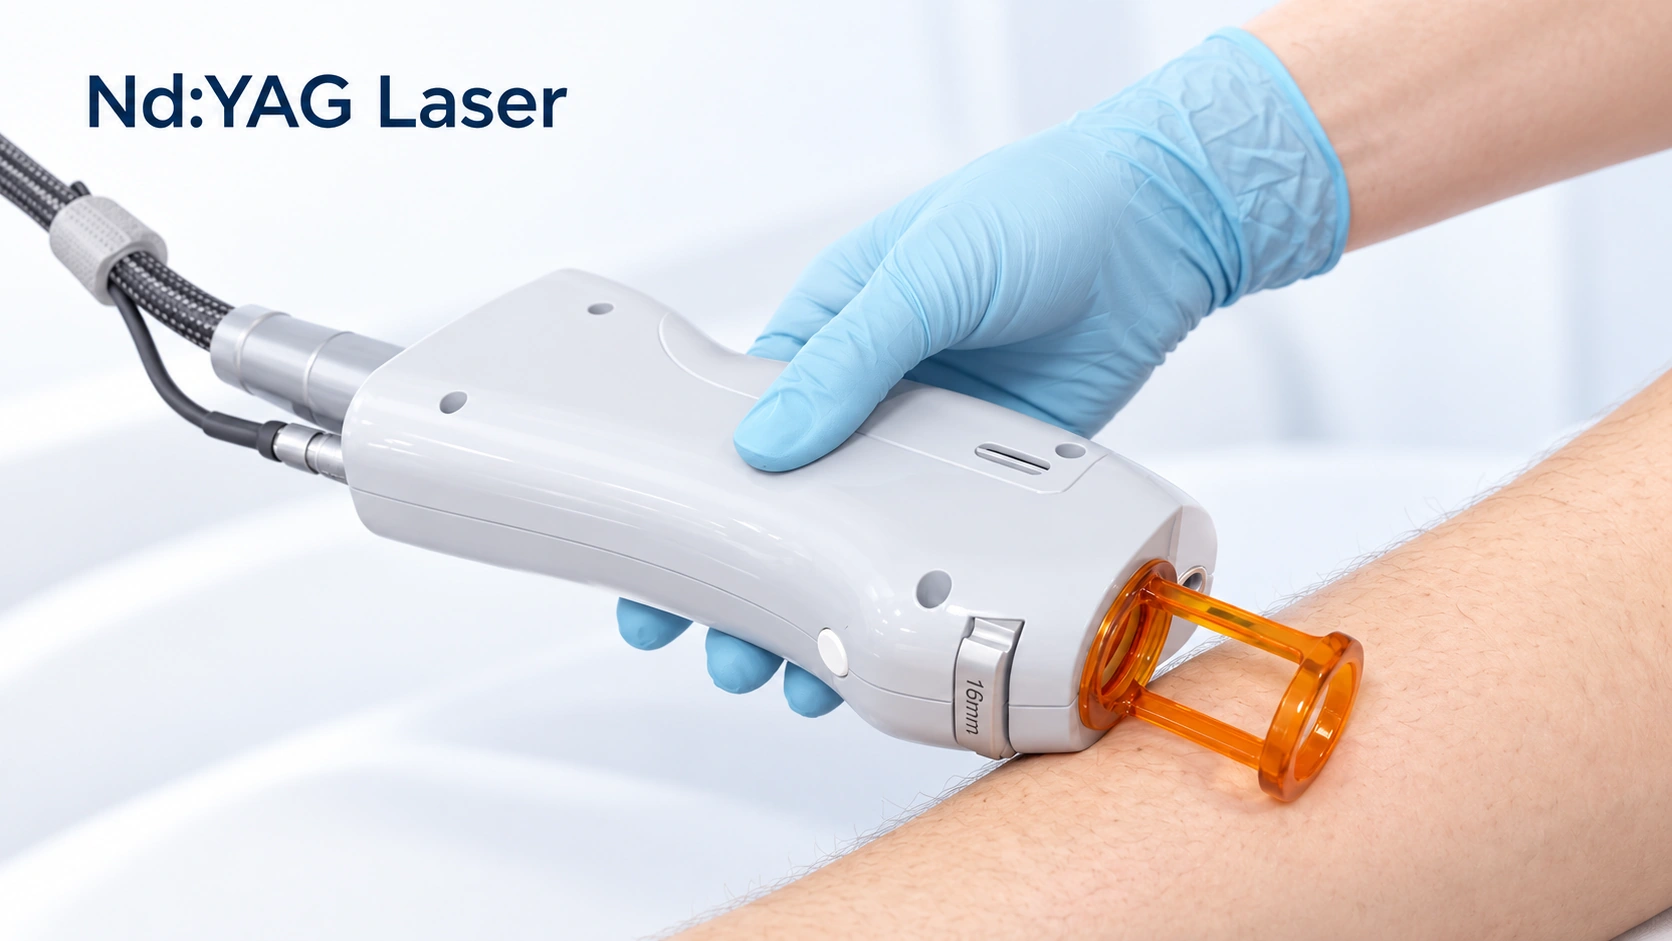
Editorial illustration for Nd:YAG Laser, based on the entry’s treatment or equipment reference.

Nd:YAG Laser

Strong evidence

The specific device used for hair removal on deeper skin tones, at a wavelength of 1064 nm. It passes more safely through pigment in the skin to reach the hair, and it is used routinely for razor bumps. Ask what wavelength a clinic uses, ask how often they treat skin like yours, and have a test patch first, because settings and cooling matter more than the marketing.

Editorial illustration for Chemical Peel, based on the entry’s treatment or equipment reference.

Chemical Peel

Limited evidence

A course of light salicylic or glycolic peels aimed at the mottled dark marks across the beard and neck once the bumps have stopped. On deeper skin tones it has to be done cautiously and by someone who treats them regularly, because too strong a peel causes exactly the darkening you are trying to clear. It does nothing for the bumps themselves.

Editorial illustration for Electrolysis, based on the entry’s treatment or equipment reference.

Electrolysis

Limited evidence

Destroys hairs one follicle at a time with a fine probe, so it can permanently clear a small stubborn patch. It is slow and uncomfortable over a beard-sized area, which is why laser is the usual choice here. It is worth considering for a few repeatedly troublesome spots rather than a whole neck.

Editorial illustration for Laser Hair Removal, based on the entry’s treatment or equipment reference.

Laser Hair Removal

Moderate evidence

Removing the hair removes the follicle that plugs, and several courses of treatment reduce flares in early disease. It works best on Hurley stage one and two, before tunnels form. On deeper skin tones the device matters: the long-pulsed Nd:YAG is the usual choice, and the wrong laser causes burns and pigment change. Ask which one the clinic will use.

Editorial illustration for Deroofing, based on the entry’s treatment or equipment reference.

Deroofing

Moderate evidence

The roof of a tunnel is removed under local anesthetic and the floor is left to heal open. The tunnel does not come back in that spot. It is small, done in clinic, and leaves a flatter result than cutting a wide block of skin out, which matters more on deeper skin tones. It treats the tunnels you have, not the disease, so medication usually continues.

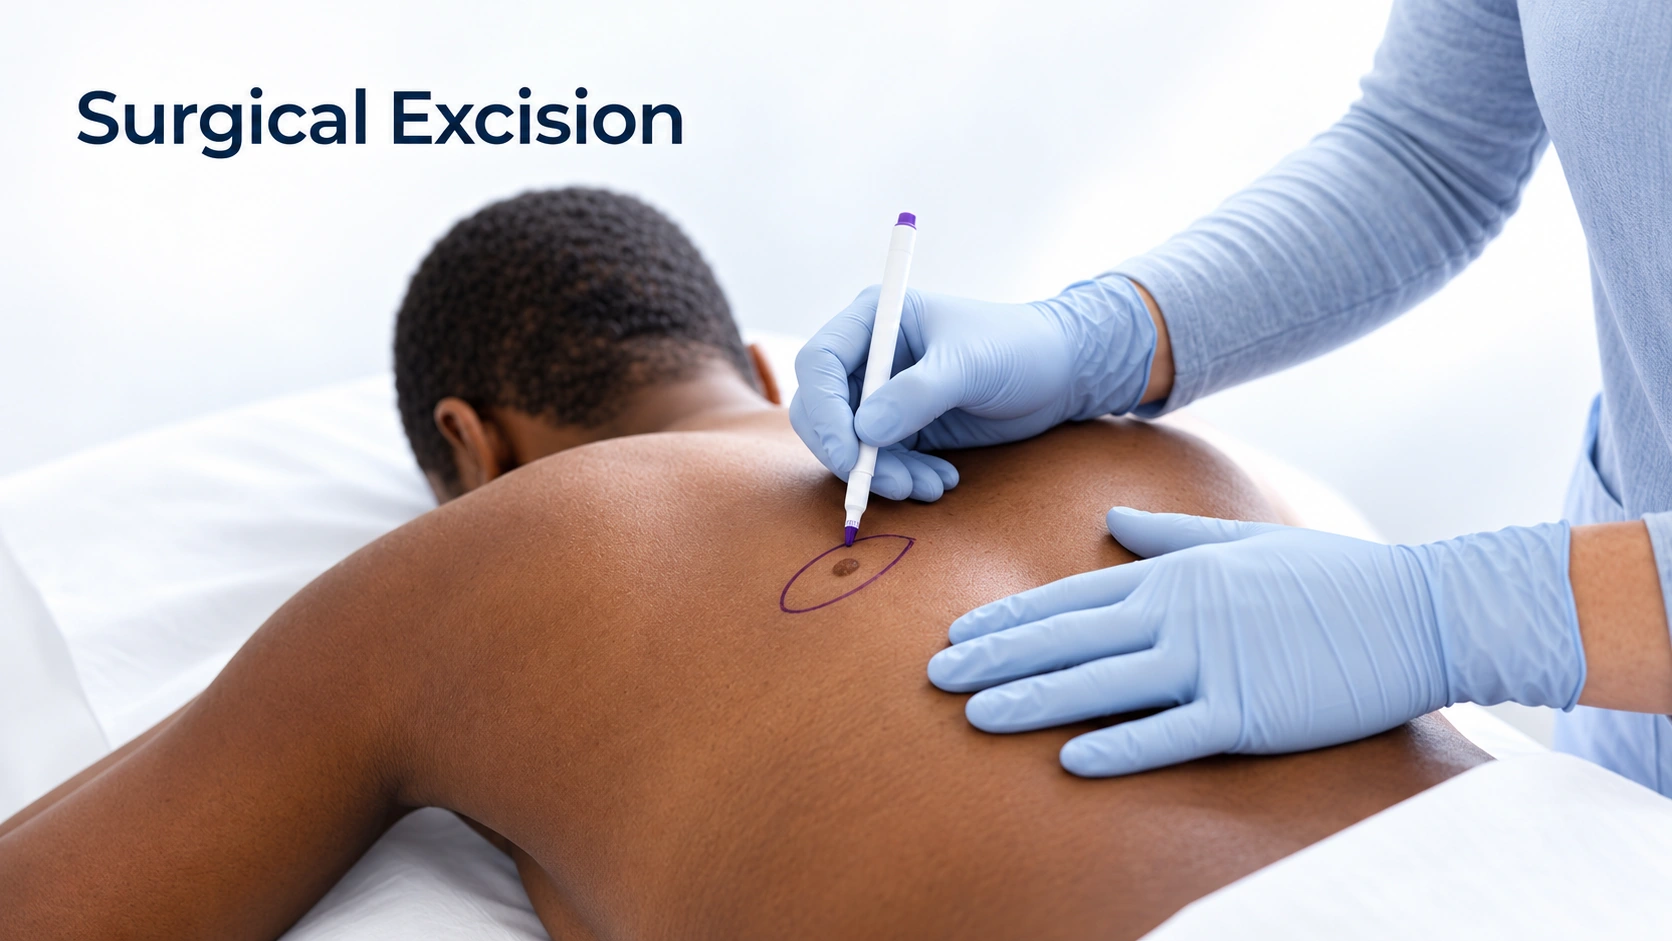
Editorial illustration for Surgical Excision, based on the entry’s treatment or equipment reference.

Surgical Excision

Moderate evidence

Wide excision. A whole affected area is removed surgically, for advanced disease where tunnels run right across an armpit or groin. Disease does not return in the removed area, though it can appear at the edges or in another fold. It is done in an operating theatre, healing takes weeks, and the area may need a skin graft or flap.

Editorial illustration for Incision and Drainage, based on the entry’s treatment or equipment reference.

Incision and Drainage

Limited evidence

Incision and drainage. Cutting a swollen abscess open relieves severe pressure and pain quickly, which is why it is done in emergency departments. It does not change the course of the condition and the lump usually refills in the same place within weeks. Repeated draining of the same spot encourages a tunnel to form, so it is a rescue measure rather than treatment.

Outlook

Long term

A single ingrown hair follows a short, predictable course; the long-term picture depends on what happens to it. Stop removing the hair and this condition stops - beards grown out for three to four weeks usually clear almost completely. Established scarring does not reverse, which is the argument for changing course early.

It runs in flares and quiet periods, and follows a longer arc over years. Not everyone progresses. The toll is real — pain, drainage, dressings, clothes chosen around it, embarrassment about the smell — and rates of depression and anxiety are high, worth raising at an appointment.

Complications

Possible complications
  • Dark marks that outlast the bumps
  • Raised and keloid scars
  • Bumps at the nape of the neck
More details

Dark marks that outlast the bumps
Every inflamed bump can leave a flat darker patch behind, and those patches routinely take several months to fade. They are the most common thing people are left with, and on deeper skin tones they are the most noticeable. They will not clear while new bumps keep forming, so stopping the bumps does more for them than anything applied on top. Daily sunscreen helps, because sun makes them deeper and slower to go.

Raised and keloid scars
Where bumps keep forming in the same place and are shaved over or picked, the skin can build firm raised scars, and in some people keloids that grow beyond the original bump. They form most readily along the jawline, the front of the neck and the nape, and more readily on deeper skin tones. Once a keloid is there it is difficult to treat, so changing the shaving early is worth much more than anything applied later.

Bumps at the nape of the neck
Firm bumps along the hairline at the back of the head are a separate problem called acne keloidalis nuchae. They can thicken into keloid-like scars and leave permanent bald patches, and it is far more common in people with tightly curled hair. It needs treating earlier and harder than bumps anywhere else, because that scarring does not reverse. Bumps in this spot are a reason to book rather than wait.

  • Scarring and restricted movement
  • Depression and anxiety
  • Squamous Cell Carcinoma
More details

Scarring and restricted movement
Years of flares in the same fold leave thick, rope-like scars that pull the skin tight. In an armpit that can limit how far the arm lifts; in the groin it can make sitting or walking uncomfortable. Scars cannot be reversed with medication, so the way to avoid them is to get on proper treatment early. Surgery can release or remove a badly scarred area.

Depression and anxiety
Constant pain, drainage, dressings and the smell wear people down, and rates of depression and anxiety in this condition are high. It is a normal response to a hard illness, not a separate weakness. It is also rarely asked about, so it is worth raising yourself at an appointment. Getting the skin under control usually helps a great deal, and support for the mood side can be arranged at the same time.

Squamous Cell Carcinoma
A rare complication of very long-standing disease, usually after decades of tunnels and scarring on the buttocks or groin. A skin cancer can grow in the damaged skin. The warning sign is a lump, ulcer or growth that behaves differently from your usual flares and does not settle. Anything like that should be looked at and biopsied rather than treated as another flare.

When to get help

When to get help

Seek care for recurring painful bumps, scarring or pus. A large painful swelling or spreading redness may need treatment for infection.

Seek early assessment for recurring painful lumps, drainage or tunnels. Fever, spreading redness or severe pain needs prompt care.

Common questions

Ingrown Hairs:Can I just pull the hair out?

Not out - free it. If a loop of hair crosses the bump, a sterilized needle can lift it from underneath and leave the hair rooted in the follicle. Pulling the whole hair out means the next one grows back through inflamed skin, which often makes another bump in the same place. Never dig for a hair you cannot see. That is how bumps become scars.

Ingrown Hairs:Will laser hair removal work if I have deep skin tone?

Yes. The concern comes from older devices. The standard choice now for deeper skin tones is a long-pulsed 1064 nm Nd:YAG laser, which reaches the hair with less risk to surrounding pigment. It takes a series of sessions, reduces rather than eliminates hair, and touch-ups are common. Ask what wavelength they use, how often they treat skin like yours, and have a test patch.

Ingrown Hairs:Do I have to stop shaving forever?

No. Most people go back to shaving once the bumps clear, as long as it is different from what caused the problem - usually a single blade or trimmer, with the grain, less often, without stretching the skin. If close shaving is unavoidable and bumps keep returning, laser lets you have both.

Ingrown Hairs:Why do I get them on my neck but not my cheeks?

The hair on the neck grows in swirls and changes direction over short distances, so a stroke with the grain in one spot is against it an inch away. The skin there is softer and easier to pull taut. The neck and under the jaw are the classic sites.

Ingrown Hairs:How long do the dark marks take to fade?

Longer than anyone wants. A mark from one bump commonly takes several months. Years of repeated bumps take longer, and nothing fades while new bumps keep forming. Two things speed it up: stopping the new bumps, and daily sunscreen.

Ingrown Hairs:Is this acne?

No, though they look similar and sometimes occur together. Acne begins with a clogged oil gland and features blackheads and whiteheads. This begins with a hair growing back into the skin, appears in shaved areas, and follows the shaving schedule. Some acne treatments help, but not the cause.

Hidradenitis Suppurativa:Is this contagious?

No. It cannot be passed through skin contact, towels, swimming pools or sex. It starts in your own hair follicles and is driven by your own immune system.

Hidradenitis Suppurativa:Why do antibiotics stop working?

They were never killing an infection. Tetracyclines are given for months here because they calm inflammation, and the effect fades when they stop. If antibiotics are not holding, move up to hormonal treatment or a biologic.

Hidradenitis Suppurativa:Will I need surgery?

Only if tunnels have formed, and not everyone reaches that stage. Medication treats inflammation but cannot close a tunnel, so once one exists a small procedure called deroofing is often the cleanest answer. It is done under local anesthetic and the tunnel does not return.

Hidradenitis Suppurativa:Does losing weight fix it?

It helps, and it does not fix it. Losing weight reduces friction, reduces affected folds and lowers background inflammation, and many notice fewer flares. But people of every size get this, and treating it as a weight problem is one reason people are sent away without proper treatment.

Hidradenitis Suppurativa:Can I still shave or have laser hair removal?

Shaving and waxing tend to provoke flares, so clipping is better day to day. Laser hair removal often reduces flares by removing the follicle and is worth considering, particularly in early disease. On deeper skin tones the device matters — ask which laser will be used.

Hidradenitis Suppurativa:Will it affect having children?

The condition does not affect fertility, but several treatments are not suitable in pregnancy, including some antibiotics and hormonal treatments. Many find it flares in pregnancy and improves afterwards, or the reverse. Plan ahead with the doctor managing your pregnancy, and never start or stop a medicine on your own.
Sources

Sources and further reading

  1. DermNet
  2. DermNet
Dermapedia on YouTube