



Hyperhidrosis vs Night Sweats

Hyperhidrosis is sweating far more than the body needs to stay cool. It usually affects the underarms, palms, soles or face, and there is a clear treatment ladder that starts with an antiperspirant used correctly and goes up from there. Sweating during sleep that is excessive for the room temperature and bedding.

Research updated 2026-10-23
Moist palms with visible perspiration.AI-generated educational illustration: An adult in bed with perspiration and damp pajama fabric, representing night sweats.

Key differences

The same eight facts on every condition comparison.

Usual age
Childhood or teens
Any age
Where
Underarms, palms, soles, face
Whole body, during sleep
Main sign
Sweating far beyond what's needed
Soaking sweat at night
Itch or pain
No
Neither
Contagious
No
No
Long term
Long-term; controlled with treatment
Depends on the cause
Scars
No
No
Who gets it
Often runs in families
Anyone; persistent cases need a check-up

What is it?

Hyperhidrosis
Night Sweats
What is it?
  • It is excess sweating.
    Sweating exceeds what is needed to regulate temperature.
  • It can be focal or general.
    Palms, soles, armpits or face may be affected, or the whole body.
  • The cause matters.
    Primary sweating and sweating from medicines or illness need different assessment.
  • Primary sweating has a pattern.
    It begins early, affects both sides and usually stops during sleep.
  • What it is
    Sweating during sleep that is excessive for the room temperature and bedding.

What it looks like

Hyperhidrosis

Hyperhidrosis: Primary focal.

Primary focal hyperhidrosis Starts young, affects hands, feet, underarms or face.

Damp patches extend beyond the underarms of the shirt.

Underarm sweating Damp patches extend beyond the underarms of the shirt.

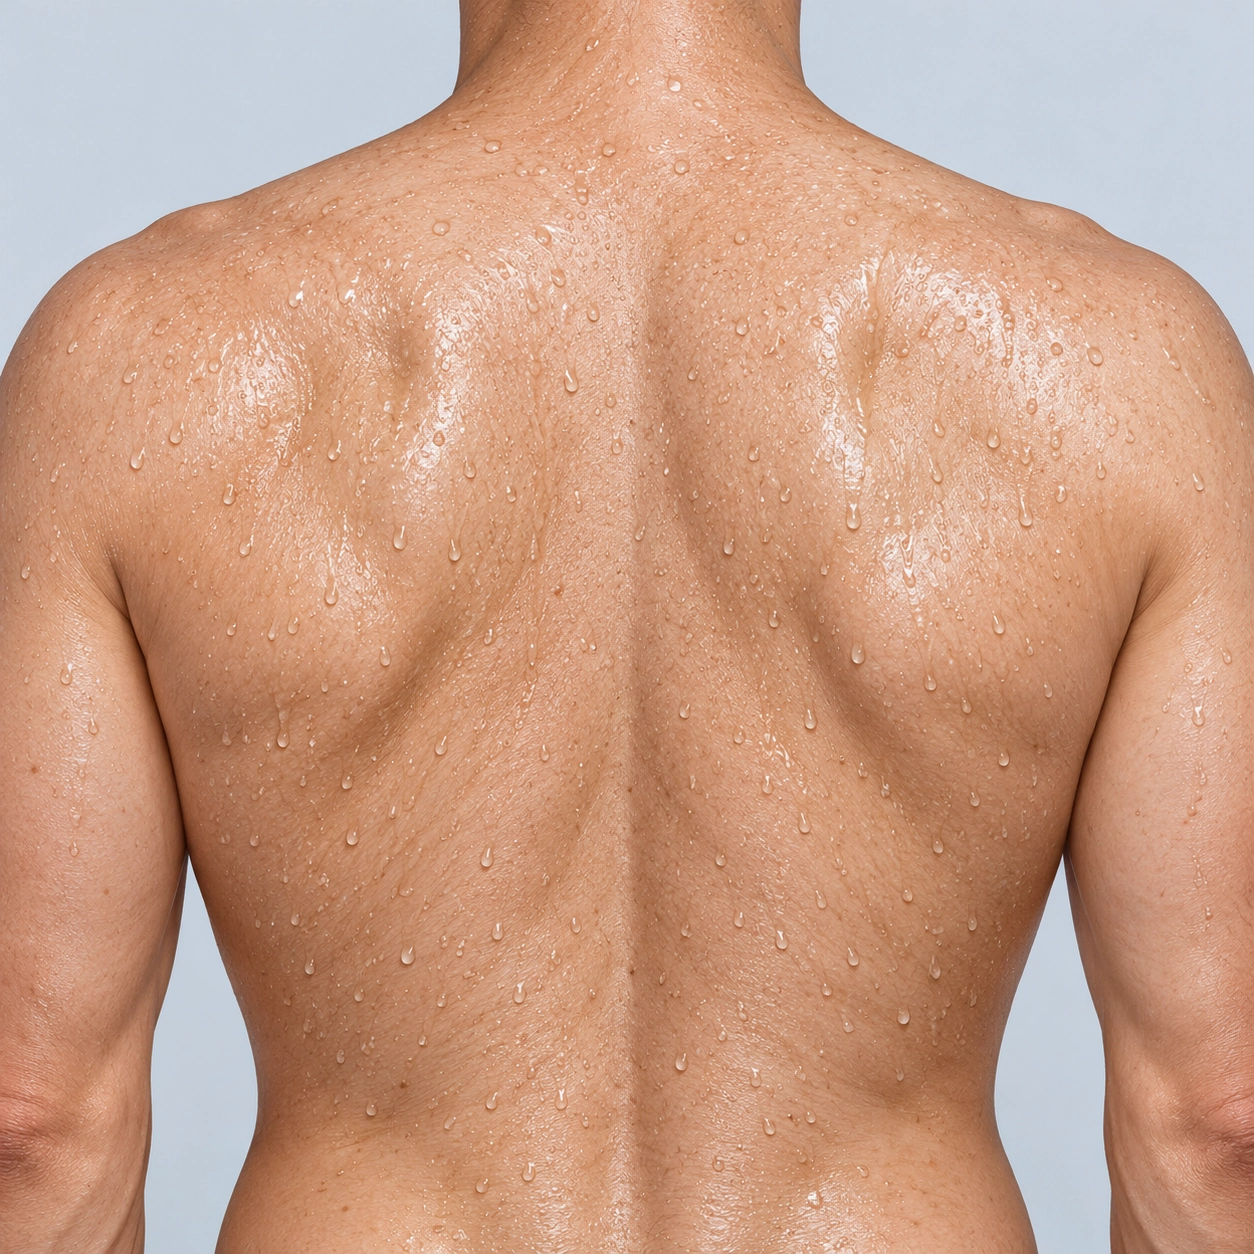
Generated image: Sweat covering the back and torso. Not a patient photograph.

Secondary generalized hyperhidrosis Generated illustration. Whole-body sweating from a medical cause or drug.

Night Sweats

A person lying in bed with a damp shirt and moisture visible on the face.

Night Sweats The scene shows damp clothing and bedding during a night in bed.

Skin tones
Moist palms with visible perspiration.
Sweat droplets across a medium-toned palm.
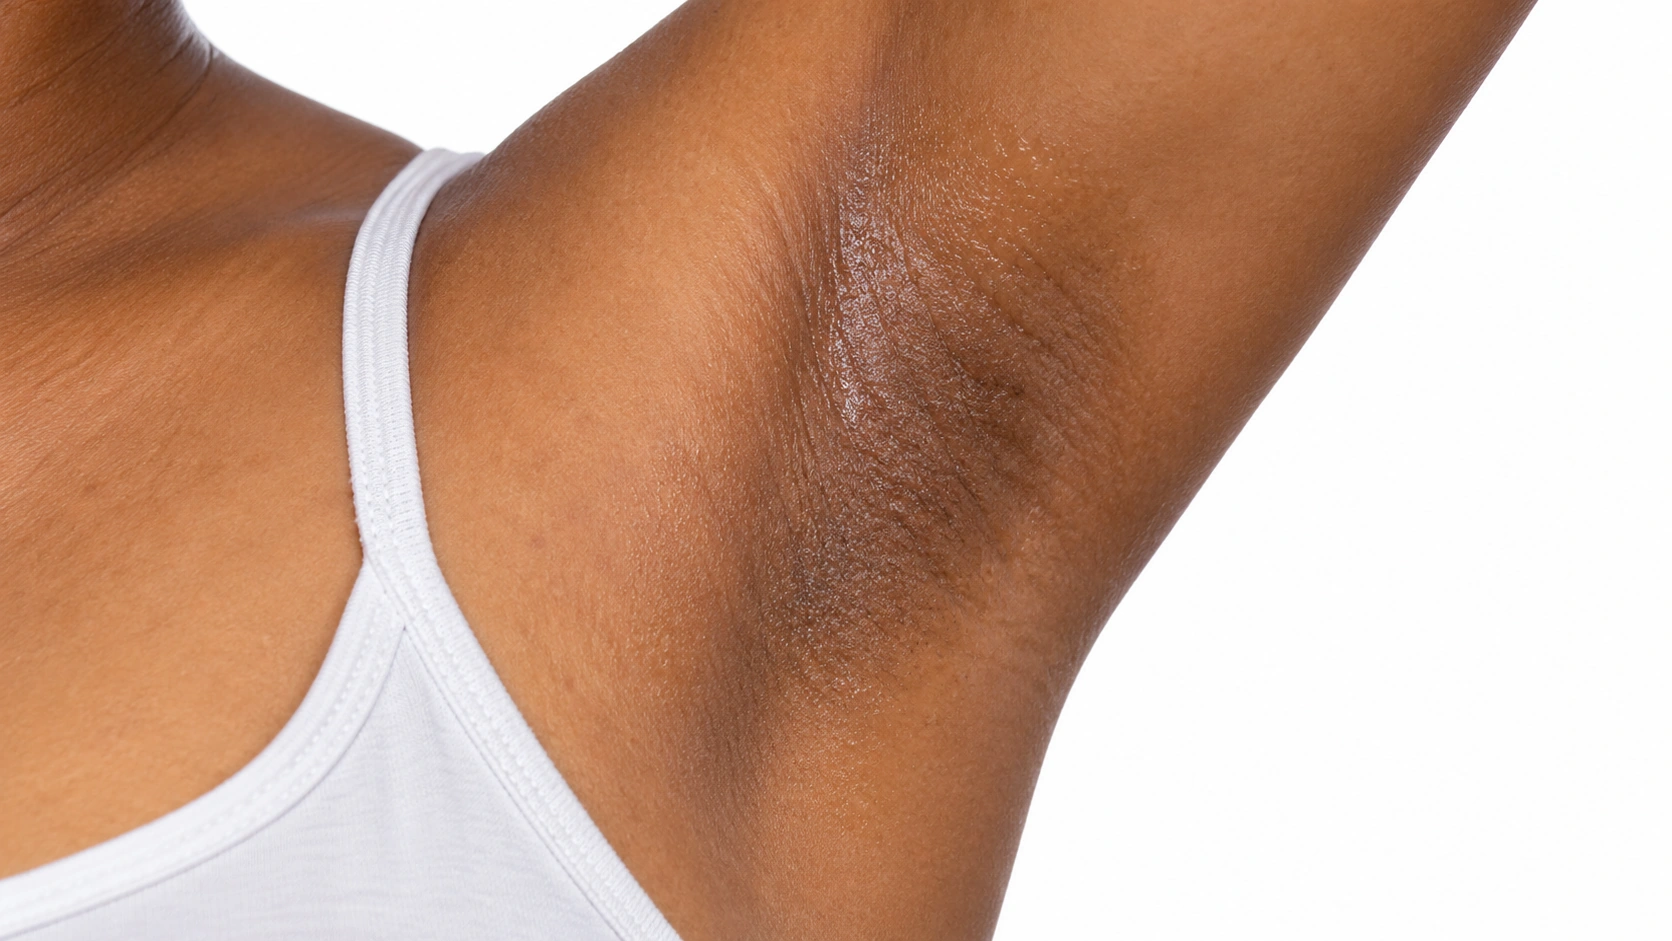
a damp-looking underarm fold with mild darkening on brown skin.
a moist underarm fold with mild darkening on deep brown skin.
A person resting in bed with damp clothing and bedding.
Diagram
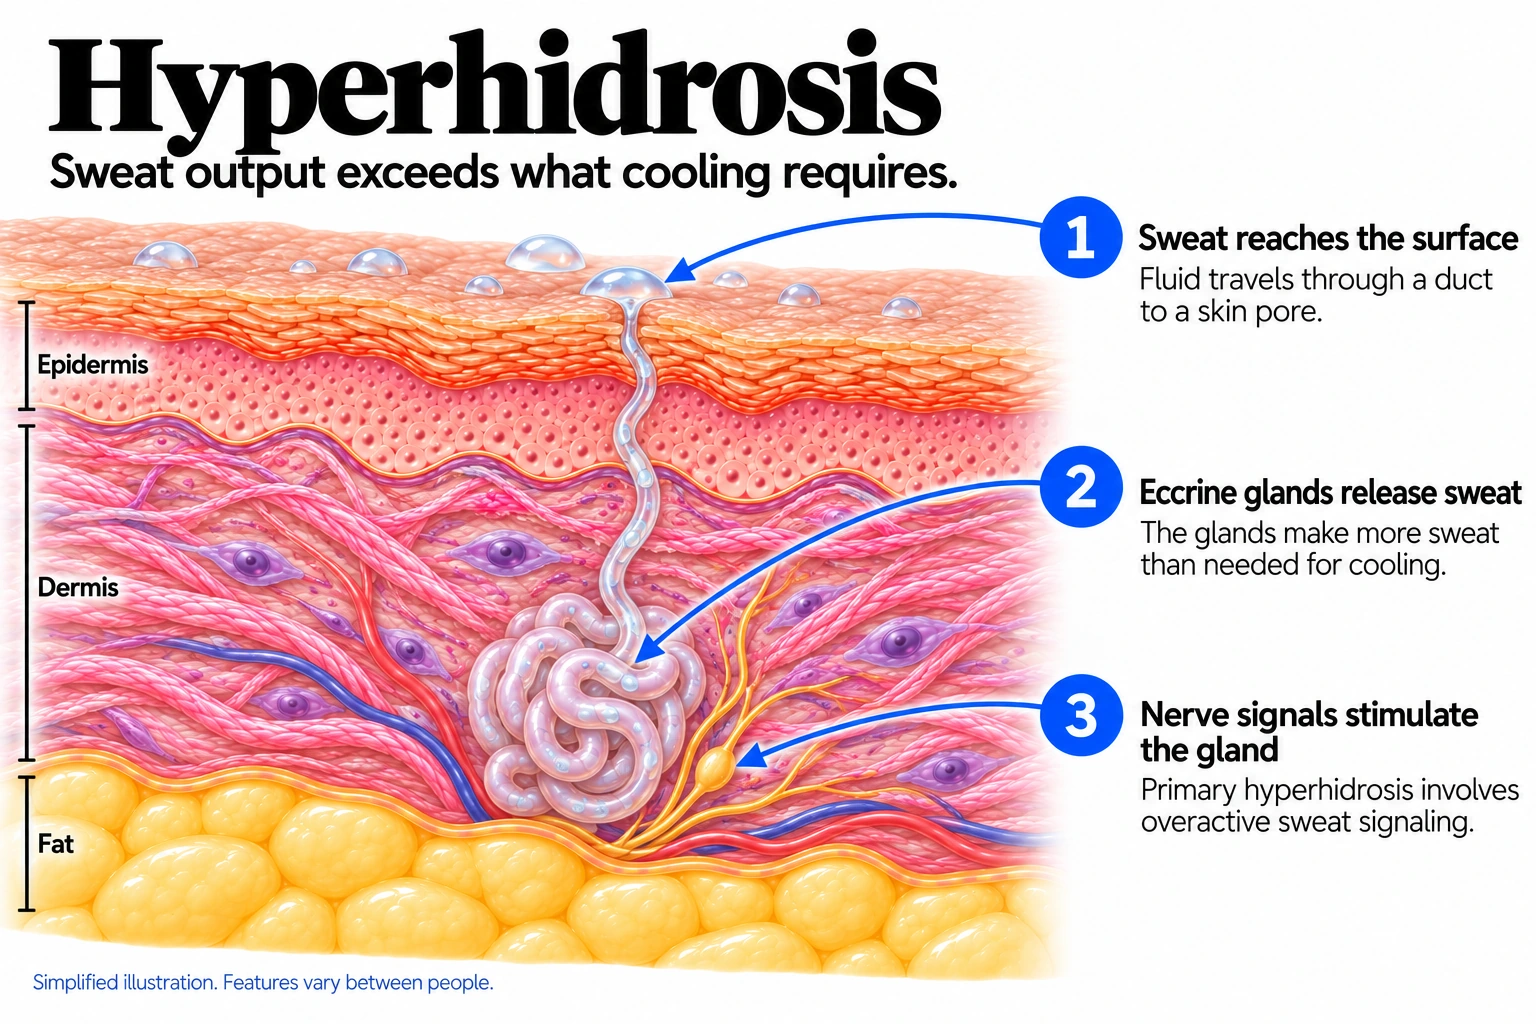
Hyperhidrosis mechanism diagram. Sweat reaches the surface: Fluid travels through a duct to a skin pore. Eccrine glands release sweat: The glands make more sweat than needed for cooling. Nerve signals stimulate the gland: Primary hyperhidrosis involves overactive sweat signaling.
In the skin

Sweat glands release more sweat than the body needs for cooling. In primary hyperhidrosis, overactive nerve signaling stimulates otherwise normal sweat glands.

Temperature regulation, hormones, medicines or illness can increase sweat-gland activity during sleep. The sweating reflects a response with several possible causes rather than one specific skin disease.

When it usually starts

010203040506070+

Hyperhidrosis. Primary focal sweating often begins in childhood or adolescence; new generalized sweating in adulthood needs assessment.

Night Sweats. Can occur at any age; persistent unexplained episodes warrant assessment.

Causes and triggers

Causes

Hyperhidrosis is sweating more than the body needs to cool down. In the most common type, the nerves that signal sweat glands are overactive.

Temperature, hormonal changes, medicines, infections or other conditions can alter nighttime sweating.

Family tendency

About 1 in 3 to 1 in 2 people with primary hyperhidrosis have a family member with it.

Risk factors
Family history, Starting in childhood or teens, Obesity, Menopause
Hot sleep environment, Medicines, Hormonal or systemic causes
Trigger
● Hyperhidrosis
● Night Sweats
Stress and anxiety
Well established
Not listed
Heat and humidity
Well established
Not listed
Spicy food
Strong link
Not listed
Caffeine
Possible
Not listed
Alcohol
Possible
Not listed
Overheating
Not listed
Can contribute
Underlying illness
Not listed
Can contribute
Medicine exposure
Not listed
Can contribute

Daily Care

Hyperhidrosis
Night Sweats
Daily care

Habits that help

  • Absorbent underarm liners
    They change how much shows and what gets ruined.
  • Wicking socks and rotated shoes
    Wear moisture-wicking socks and let each pair of shoes dry between uses.
  • An aluminum antiperspirant at night
    Bone-dry skin, overnight, washed off in the morning.
  • Prescription aluminum chloride
    The usual next step, every second or third night.
  • Glycopyrronium cloth for underarms
    A prescription wipe once a day, away from the eyes.
  • Iontophoresis for hands and feet
    Hands or feet sit in trays with a weak current.
  • Anticholinergic tablets
    Glycopyrrolate or oxybutynin, reducing sweating everywhere.
  • Microwave treatment of the underarm
    An in-office procedure that destroys underarm glands.
  • Surgery to cut the sympathetic nerve
    The last resort; most then sweat more elsewhere.
  • Treating anxiety
    Where dread of sweating is its own problem, treat both.
  • Review possible medicine triggers with the prescriber; do not stop medicines yourself
    Certain antidepressants and pain medicines increase sweating.
  • Arrange assessment for symptoms of thyroid disease
    Whole-body sweating no skin product will fix.
  • Review irritating antiperspirant use rather than applying through raw skin
    Follow label advice, reduce frequency or stop if needed, and seek advice for persistent burning or a rash.
  • Follow the specific antiperspirant application schedule
    Some stronger aluminum-containing products are applied to completely dry skin at night. Product instructions take priority.

Avoid

  • Avoid: Heat and humidity
    The ordinary trigger, and why people book in summer.
  • Avoid: Stress and social pressure
    Exams, presentations, interviews, first meetings.
  • Avoid: Dreading the sweating itself
    Worry about sweat raises the signal.
  • Avoid: Spicy food, caffeine, alcohol, nicotine
    All raise sweating; spicy food hits the face in minutes.
  • Avoid: Closed shoes and synthetic socks
    Trapped moisture means macerated skin and athlete's foot.
  • Avoid: Wearing the same shoes every day
    Shoes need about a day to dry.
  • Avoid: Sitting in damp clothes
    Prolonged wetness causes rashes in the folds.
  • Avoid: Shaving, then treating that night
    The recipe for a burning underarm.
  • Avoid: Applying it to damp skin
    Aluminum chloride reacts with water and irritates more.
  • Avoid: Using a deodorant to reduce sweat
    Deodorant handles odor, not sweat.

Habits that help

  • Choose breathable clothing and change damp garments
    Spare layers can improve comfort and reduce prolonged skin wetness.
  • Change damp socks and let shoes dry between wears
    Moisture held against the feet encourages maceration and fungal infection.
  • Keep the sleeping or working space comfortably cool
    Use lighter bedding or a fan if heat worsens symptoms.
  • Track when sweating happens and any new medicines
    A short record helps distinguish triggers from symptoms needing investigation.
  • Discuss underlying-cause assessment
    Review medicines and associated symptoms; treatment targets the cause rather than assuming primary hyperhidrosis.

Avoid

  • Avoid: Abruptly stopping prescribed medicines
    Discuss suspected medicine-related sweating with the prescriber.
  • Avoid: Ignoring new unexplained or drenching sweats
    Sweating with fever, weight loss or other illness needs medical assessment.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Hyperhidrosis
● Night Sweats
Filter by type
Sweating location

Select one or more.

All types
Treatment approach
—

Treatment depends on the underlying cause. Review associated symptoms and medicines with a clinician; do not assume night sweats should be treated as primary hyperhidrosis.

Over-the-counter
Aluminum antiperspirant at night.

Aluminum antiperspirant at night

Moderate evidence

The first and most important treatment, and the one most people are using wrongly. It has to go on completely dry skin at night, when sweating is lowest, so the aluminum can settle into the duct and form a plug; washed off in the morning, the plug stays. Used in the morning on damp skin it is rinsed out before it works. Give it two weeks. It works on soles and palms as well as underarms.


Clinical strength antiperspirant.

Clinical strength antiperspirant

Moderate evidence

Sold over the counter and considerably stronger than an ordinary antiperspirant, so it is the sensible next step before anything is prescribed. Same rules apply: dry skin, at night, washed off in the morning. If it stings, drop to every second or third night rather than stopping — irritation usually means the schedule needs easing, not that the product is wrong.

Deodorant.

Deodorant

Listed

A common and costly mix-up. Deodorant works on the bacteria that turn sweat into odor; it does not block sweat at all. If the label says deodorant only, it will do nothing for how wet you get. Many products combine both, so check that the word antiperspirant is on it.

None listed
Prescription topicals
16:9 hero for Qbrexza. Never cropped: the tone strip and the corner logo depend on the full frame.

Qbrexza

Strong evidence

A prescription glycopyrronium wipe used once a day on the underarms. It blocks the chemical message from the nerve to the gland, which is a different step from an antiperspirant, so it is an option when aluminum has failed or is too irritating. Wash your hands afterwards and keep it well away from the eyes — touching the eyes after using it causes blurred vision and an enlarged pupil.

Aluminum Chloride

Moderate evidence

Aluminum chloride 20%. The prescription-strength version of the same idea, and the usual next step when clinical strength has not been enough. It is started every second or third night rather than nightly, because stinging and redness are common. Apply to bone-dry skin, and never on the night you shave — that combination is the classic cause of a burning underarm.

None listed
Prescription pills
An illustrative bottle labeled Glycopyrrolate beside plain tablets.

Glycopyrrolate

Moderate evidence

A tablet that blocks the same chemical message everywhere in the body at once, which makes it the option when sweating affects several areas or the whole body rather than one patch. The trade-off is that it dries everything: dry mouth, dry eyes, blurred vision and constipation are common, and it reduces your ability to cool down, so it needs care in hot weather and heavy exercise.

An illustrative bottle labeled Oxybutynin beside plain tablets.

Oxybutynin

Moderate evidence

The main alternative tablet, usually started low and built up slowly to find the point where sweating drops before dry mouth becomes intolerable. It works the same way as glycopyrrolate and has the same trade-offs. It is used more cautiously in older adults, where it can cause confusion.

Propranolol

Limited evidence

Propranolol before an event. A beta blocker taken as a one-off before a presentation, an interview or a performance. It blunts the physical side of nerves — the racing heart, the shaking and some of the sweating — so it suits people whose worst sweating is tied to specific occasions. It does nothing for everyday sweating and is not a treatment for the condition itself.

None listed
Procedures

Botox

Strong evidence

Botox. A grid of small injections that block the nerve signal reaching the sweat glands in that patch of skin. It starts working within a few days to a week and lasts several months before it needs repeating. Underarm injections are well tolerated; palms and soles hurt more and are usually done with numbing, and palm injections can cause temporary weakness of grip. It is an approved medical treatment for severe underarm sweating, not a cosmetic one, and insurance often covers it once antiperspirants have been tried and documented.

Editorial illustration for Iontophoresis, based on the entry’s treatment or equipment reference.

Iontophoresis

Moderate evidence

Hands or feet sit in shallow trays of water while a weak electrical current passes through them, about 20 to 30 minutes a session. It is the best option for palms and soles, where antiperspirants are hardest to keep on. It takes several sessions a week at first, then a maintenance session every week or two, and it stops working if you stop. Machines can be bought for home use, which is how most people end up doing it.

miraDry

Moderate evidence

An in-office treatment that uses microwave energy to destroy the sweat glands in the underarm, so the reduction is permanent rather than repeating like injections. It is for underarms only. Most people need one or two sessions, the underarms are swollen and tender for a week or two afterwards, and temporary numbness in the upper arm can happen. It is not usually covered by insurance.

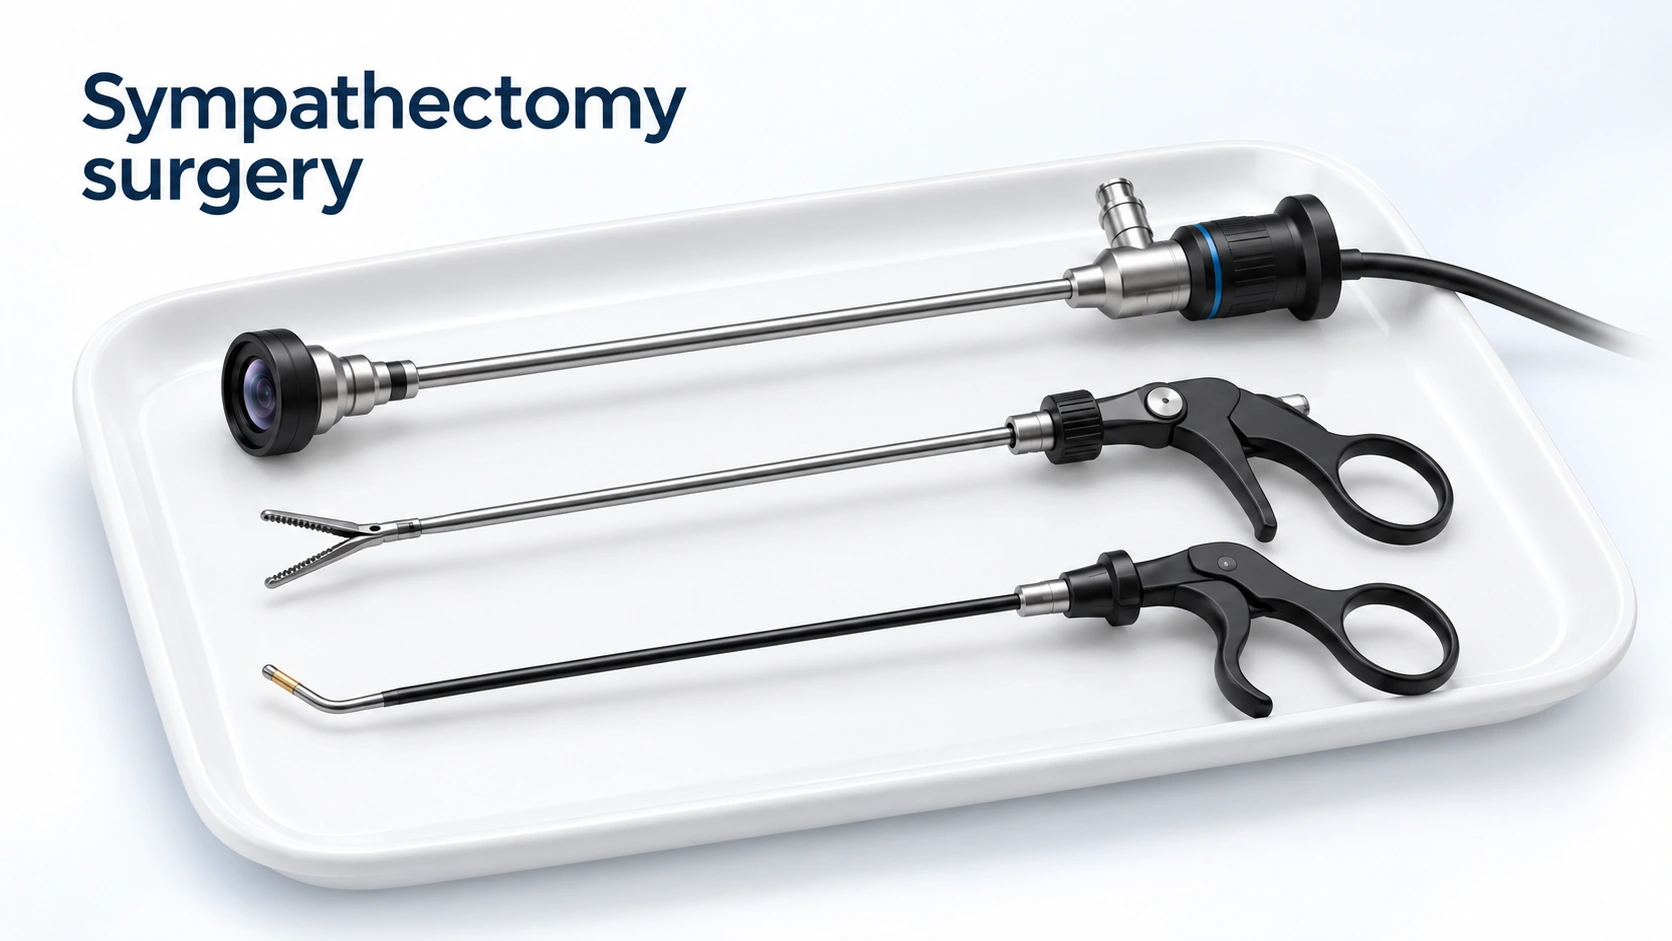
Editorial illustration for Sympathectomy surgery, based on the entry’s treatment or equipment reference.

Sympathectomy surgery

Moderate evidence

Keyhole surgery that cuts the sympathetic nerve in the chest. It reliably and permanently stops palm sweating, which is why it is still done. The problem is that a large share of people go on to sweat far more heavily on the trunk, back or legs, and that cannot be undone. It is reasonable to consider only for severe palm sweating after antiperspirants, iontophoresis, injections and tablets have all genuinely been tried.

None listed

Outlook

Long term

Primary hyperhidrosis can continue for years, although treatment can control sweating while it is used. Symptoms may return after treatment stops. Secondary hyperhidrosis has a different outlook that depends on its underlying cause.

The outlook depends on the cause rather than the amount of sweating alone. New drenching sweats, especially with fever, weight loss or enlarged glands, need medical assessment.

Complications

Possible complications
  • Athlete's foot and foot odor
  • Macerated skin and skin-fold rash
  • Compensatory sweating after surgery
More details

Athlete's foot and foot odor
Feet that stay wet inside shoes are ideal ground for fungus, so athlete's foot comes back again and again in people with sweaty soles, and the odor comes from bacteria working on the trapped sweat. Both are treatable in their own right, but they keep returning while the wetness is untreated. Antiperspirant works on the soles as well as the underarms, and rotating shoes so each pair dries for a day makes a real difference.

Macerated skin and skin-fold rash
Skin that is wet for hours at a time swells, turns soft and white, and starts to break down. In the underarms, the groin and under the breasts this becomes a sore, weeping rash in the crease, which then gets colonised by yeast or bacteria. It is common and it settles once the area is kept dry, but on deeper skin tones the soreness looks brown or violet rather than red and is often judged milder than it is.

Compensatory sweating after surgery
Cutting the sympathetic nerve reliably stops palm sweating, but a large share of people then sweat much more heavily somewhere else, usually the trunk, back or thighs. It can be worse than the problem they started with, and it cannot be reversed. This is the reason surgery sits at the very end of the ladder, after antiperspirants, iontophoresis, injections and tablets have all been genuinely tried.

Drenching sweats with unexplained fever, weight loss or enlarged nodes need investigation.

When to get help

When to get help

Seek care if sweating disrupts daily life or begins suddenly. New night sweats, generalized sweating or other symptoms warrant assessment for an underlying cause.

Arrange care for persistent or recurrent drenching sweating or associated systemic symptoms.

Common questions

Hyperhidrosis:Is hyperhidrosis dangerous?

The primary form is not dangerous in itself. Its costs are practical and social, plus skin problems from constant wetness - athlete's foot, rashes in folds, macerated skin. Sweating that is new, generalized, happens during sleep, or comes with weight loss or fever should be checked.

Hyperhidrosis:Why does my antiperspirant not work?

Usually because of when you use it. In the morning on damp skin, the active ingredient washes out of the duct before it settles. The same product at night on completely dry skin often works. If two weeks of that with a clinical-strength product has not helped, that is genuine failure, and time for prescription options.

Hyperhidrosis:How long do botulinum toxin injections last, and do they hurt?

They start working within a few days to a week and last several months. Underarm injections are well tolerated. Palms and soles are more uncomfortable and usually done with numbing, and palm injections can cause temporary hand weakness.

Hyperhidrosis:Will treatment make me stop sweating everywhere?

No. Antiperspirants, wipes and injections act only where applied, on a small share of your sweat glands. Tablets work body-wide, which is why they reduce heat tolerance and need care in hot weather or heavy exercise. You keep plenty of capacity to cool yourself.

Hyperhidrosis:Will it go away on its own?

Primary hyperhidrosis usually persists, though it often eases with age, particularly on the palms - controlled rather than cured. Secondary hyperhidrosis resolves once whatever drives it is treated.

Hyperhidrosis:Should I have the surgery?

For most people, no. It reliably stops palm sweating, but a large share then sweat more heavily elsewhere, usually the trunk, and that is permanent. Consider it only for severe palm sweating after antiperspirants, iontophoresis, injections and tablets have all been genuinely tried.

Night Sweats:What is Night Sweats?

Sweating during sleep that is excessive for the room temperature and bedding.

Night Sweats:What can I do day to day?

Wear breathable clothing, change damp garments and keep a record of symptoms and medicines.

Night Sweats:When should I get medical advice?

Arrange care for persistent or recurrent drenching sweating or associated systemic symptoms.

Sources

Sources and further reading

  1. DermNet
  2. Hyperhidrosis
Dermapedia on YouTube