
Eyelid Dermatitis vs Seborrheic Dermatitis

Eczema of the thin eyelid skin, often related to irritation or contact allergy. Seborrheic dermatitis is a common, long-term rash that causes greasy flaking and inflammation where the skin is oiliest - the scalp, the eyebrows, the sides of the nose, the ears and the chest. Dandruff is its mildest form. It responds well to treatment and returns when treatment stops.

Research updated 2026-10-23
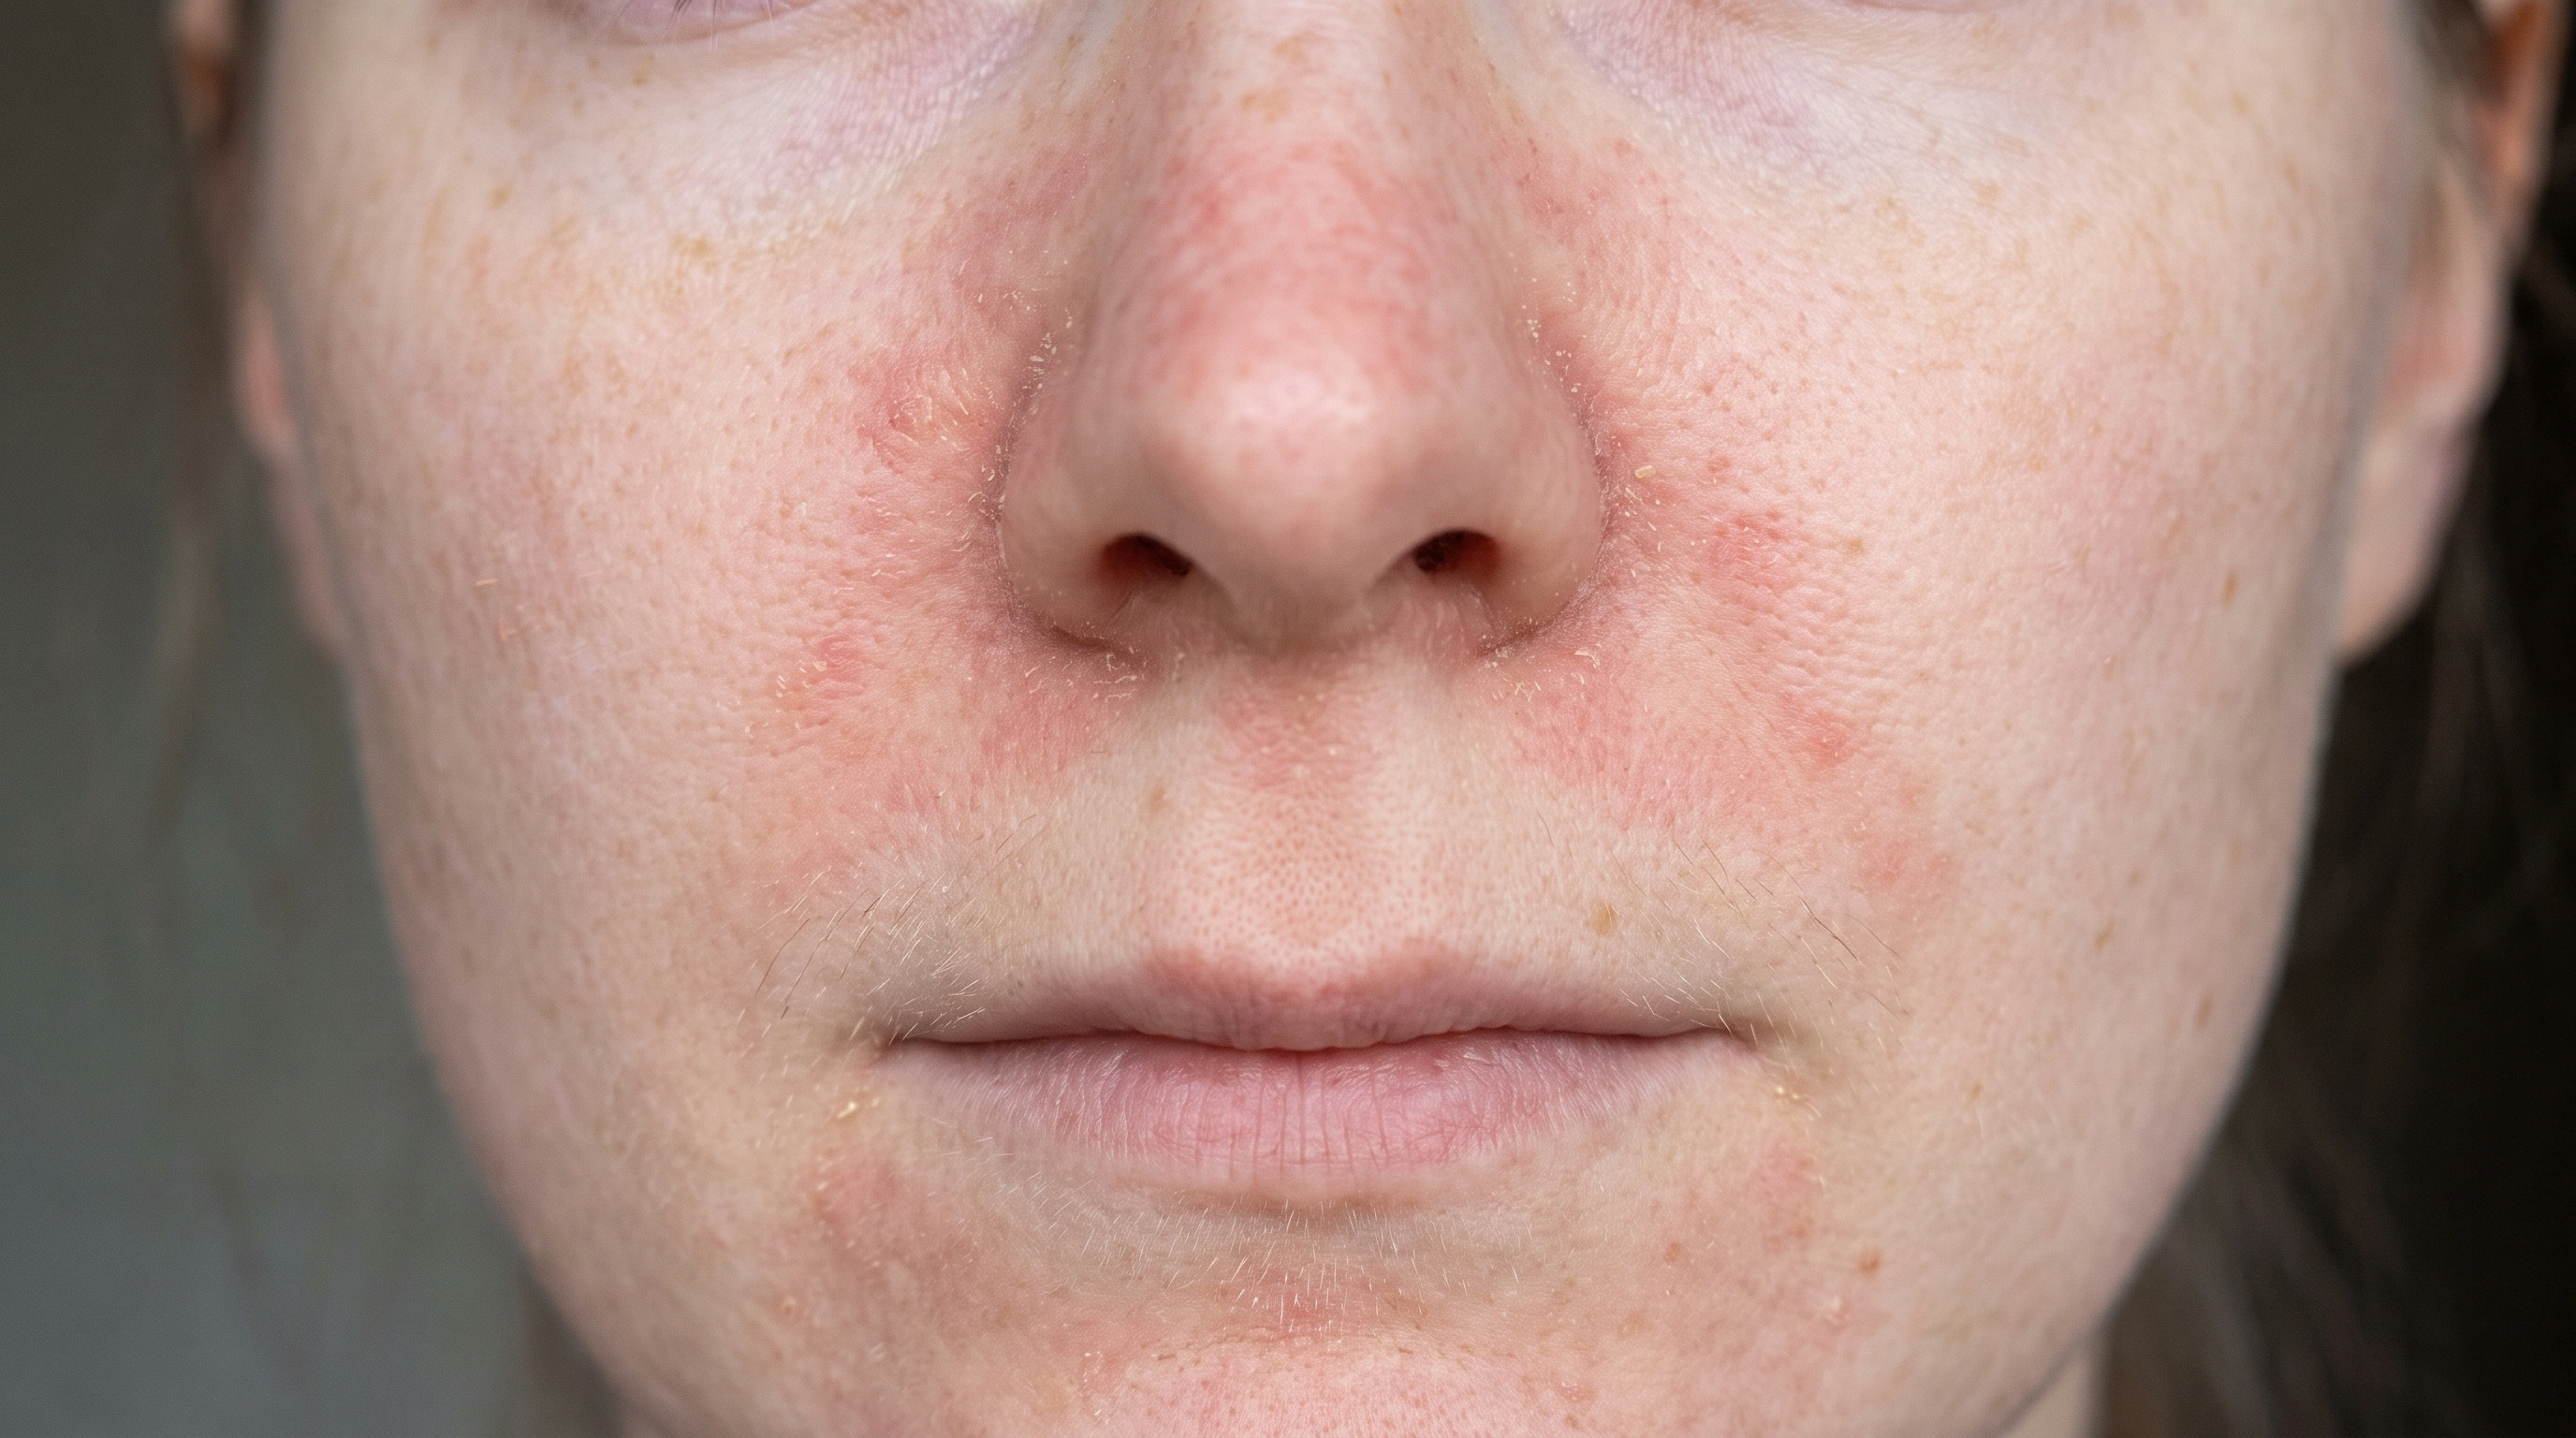
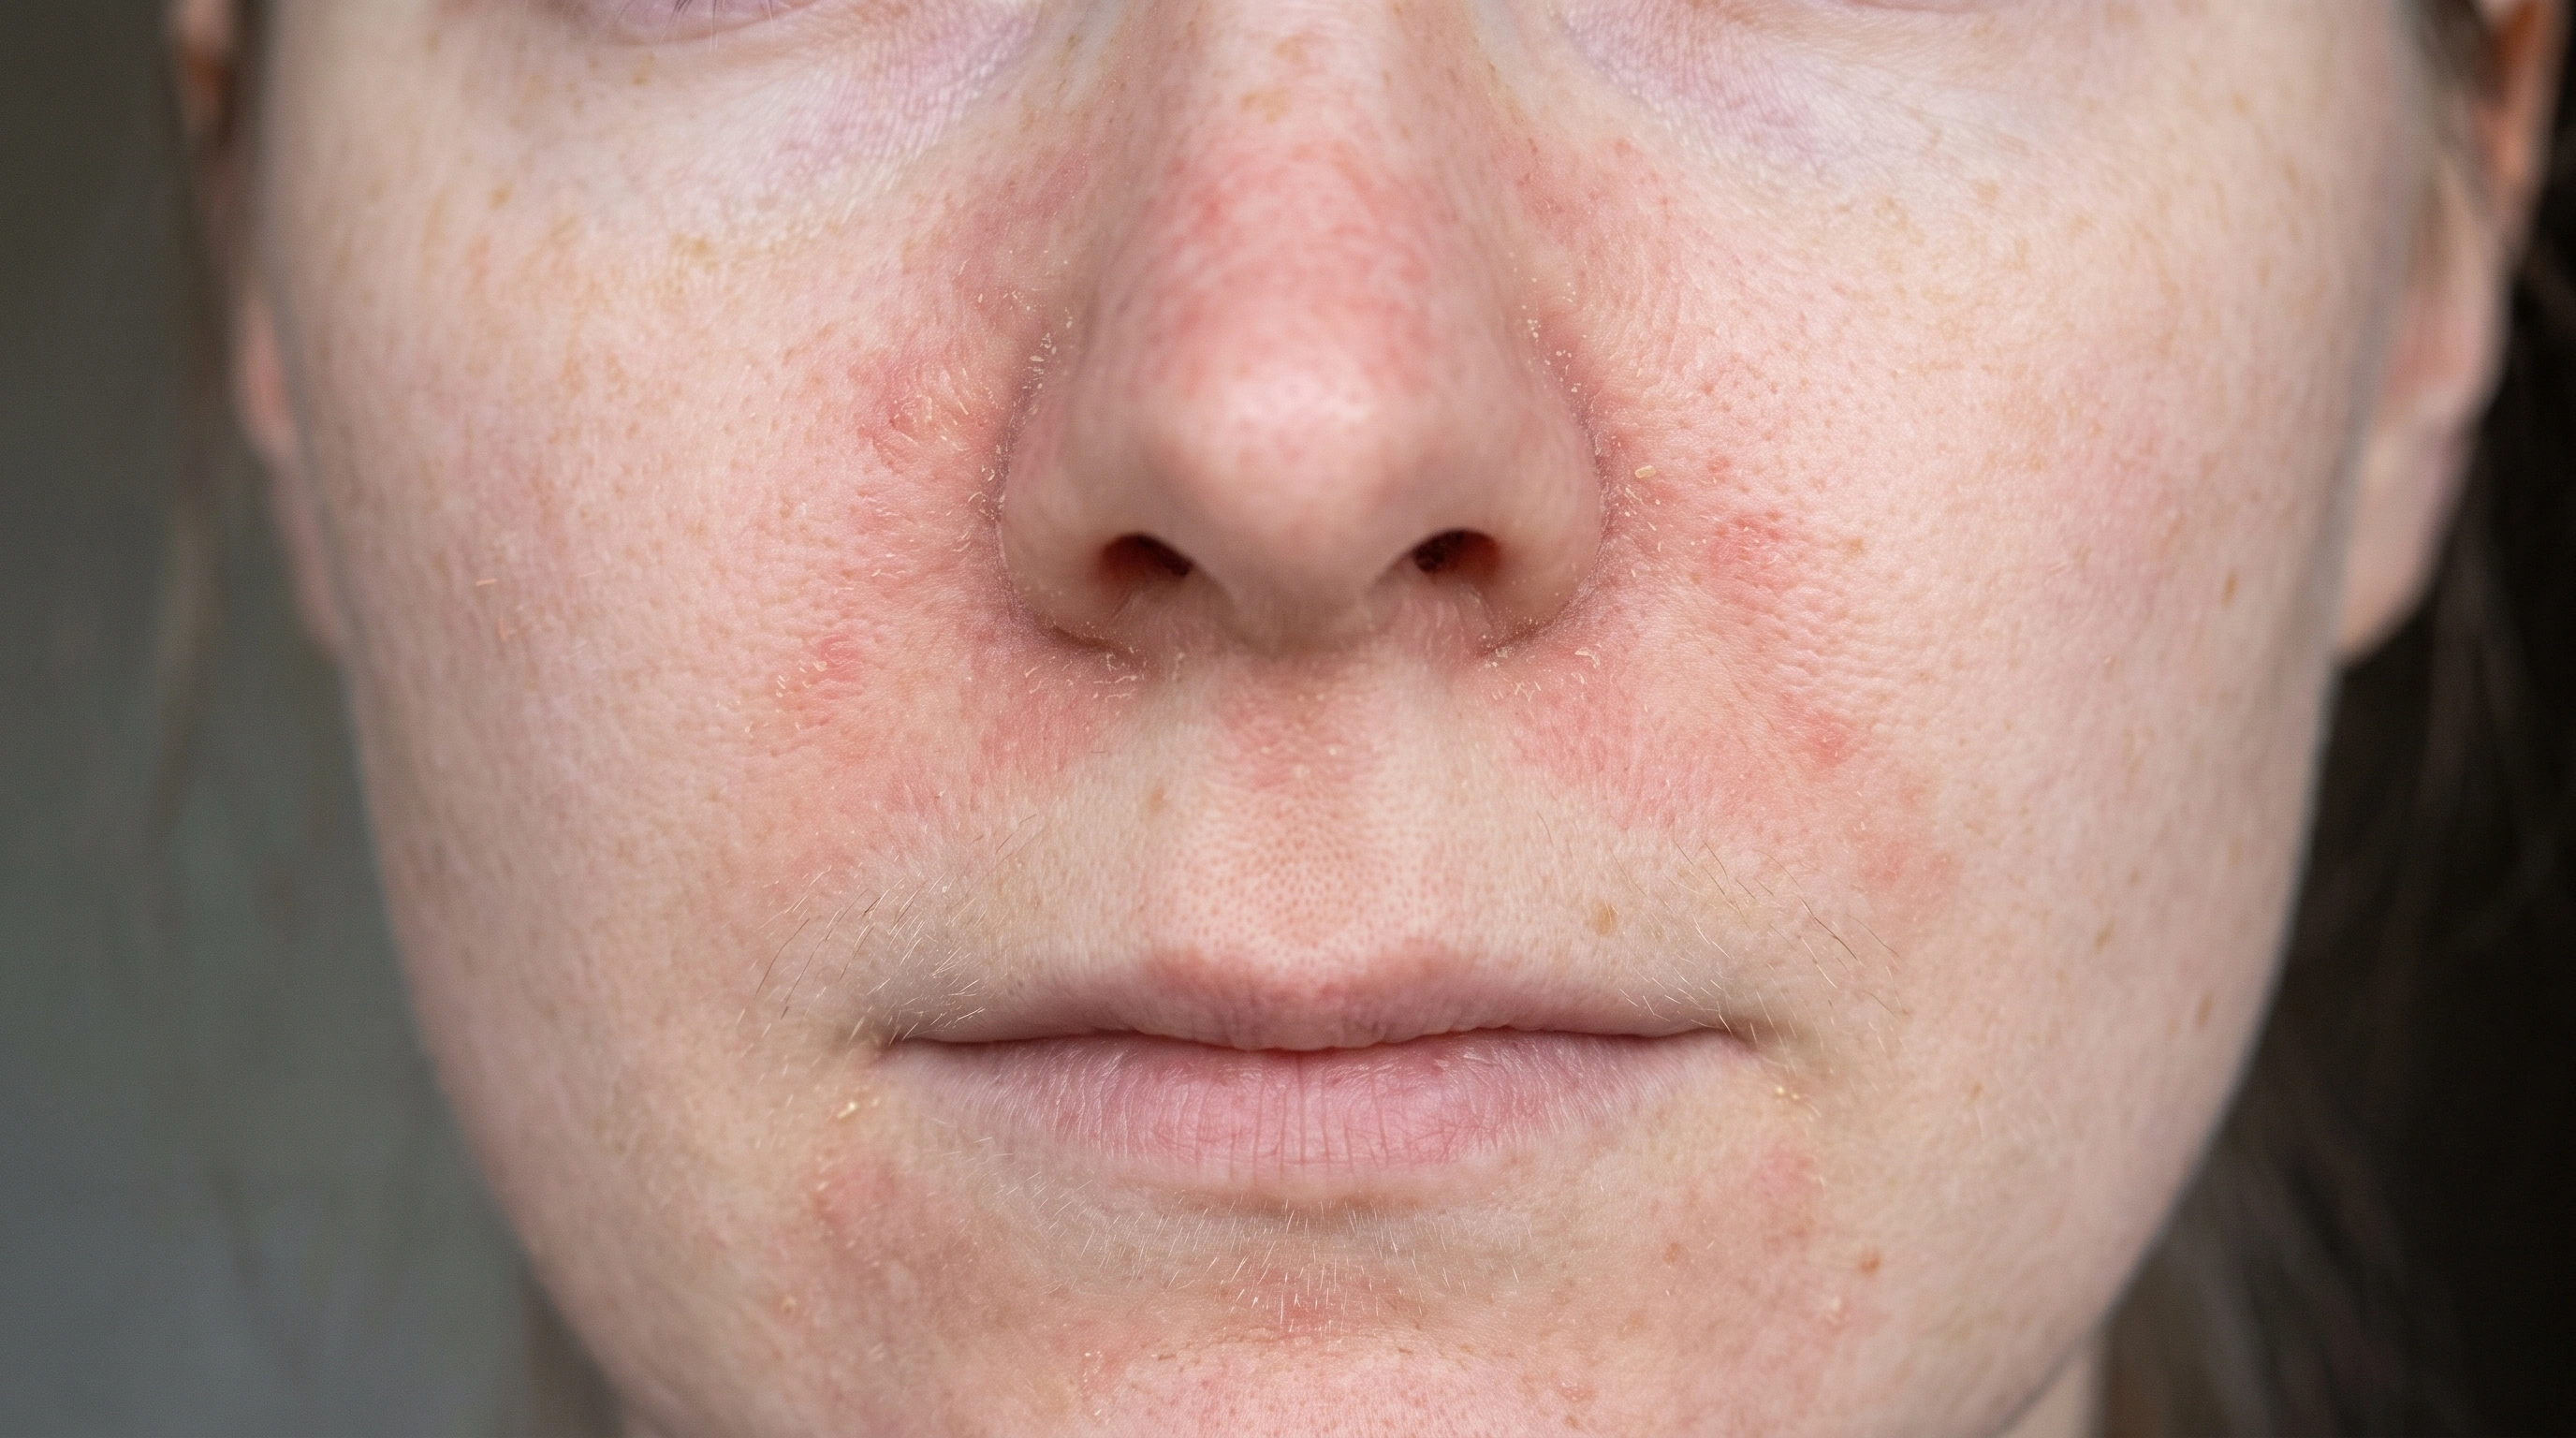
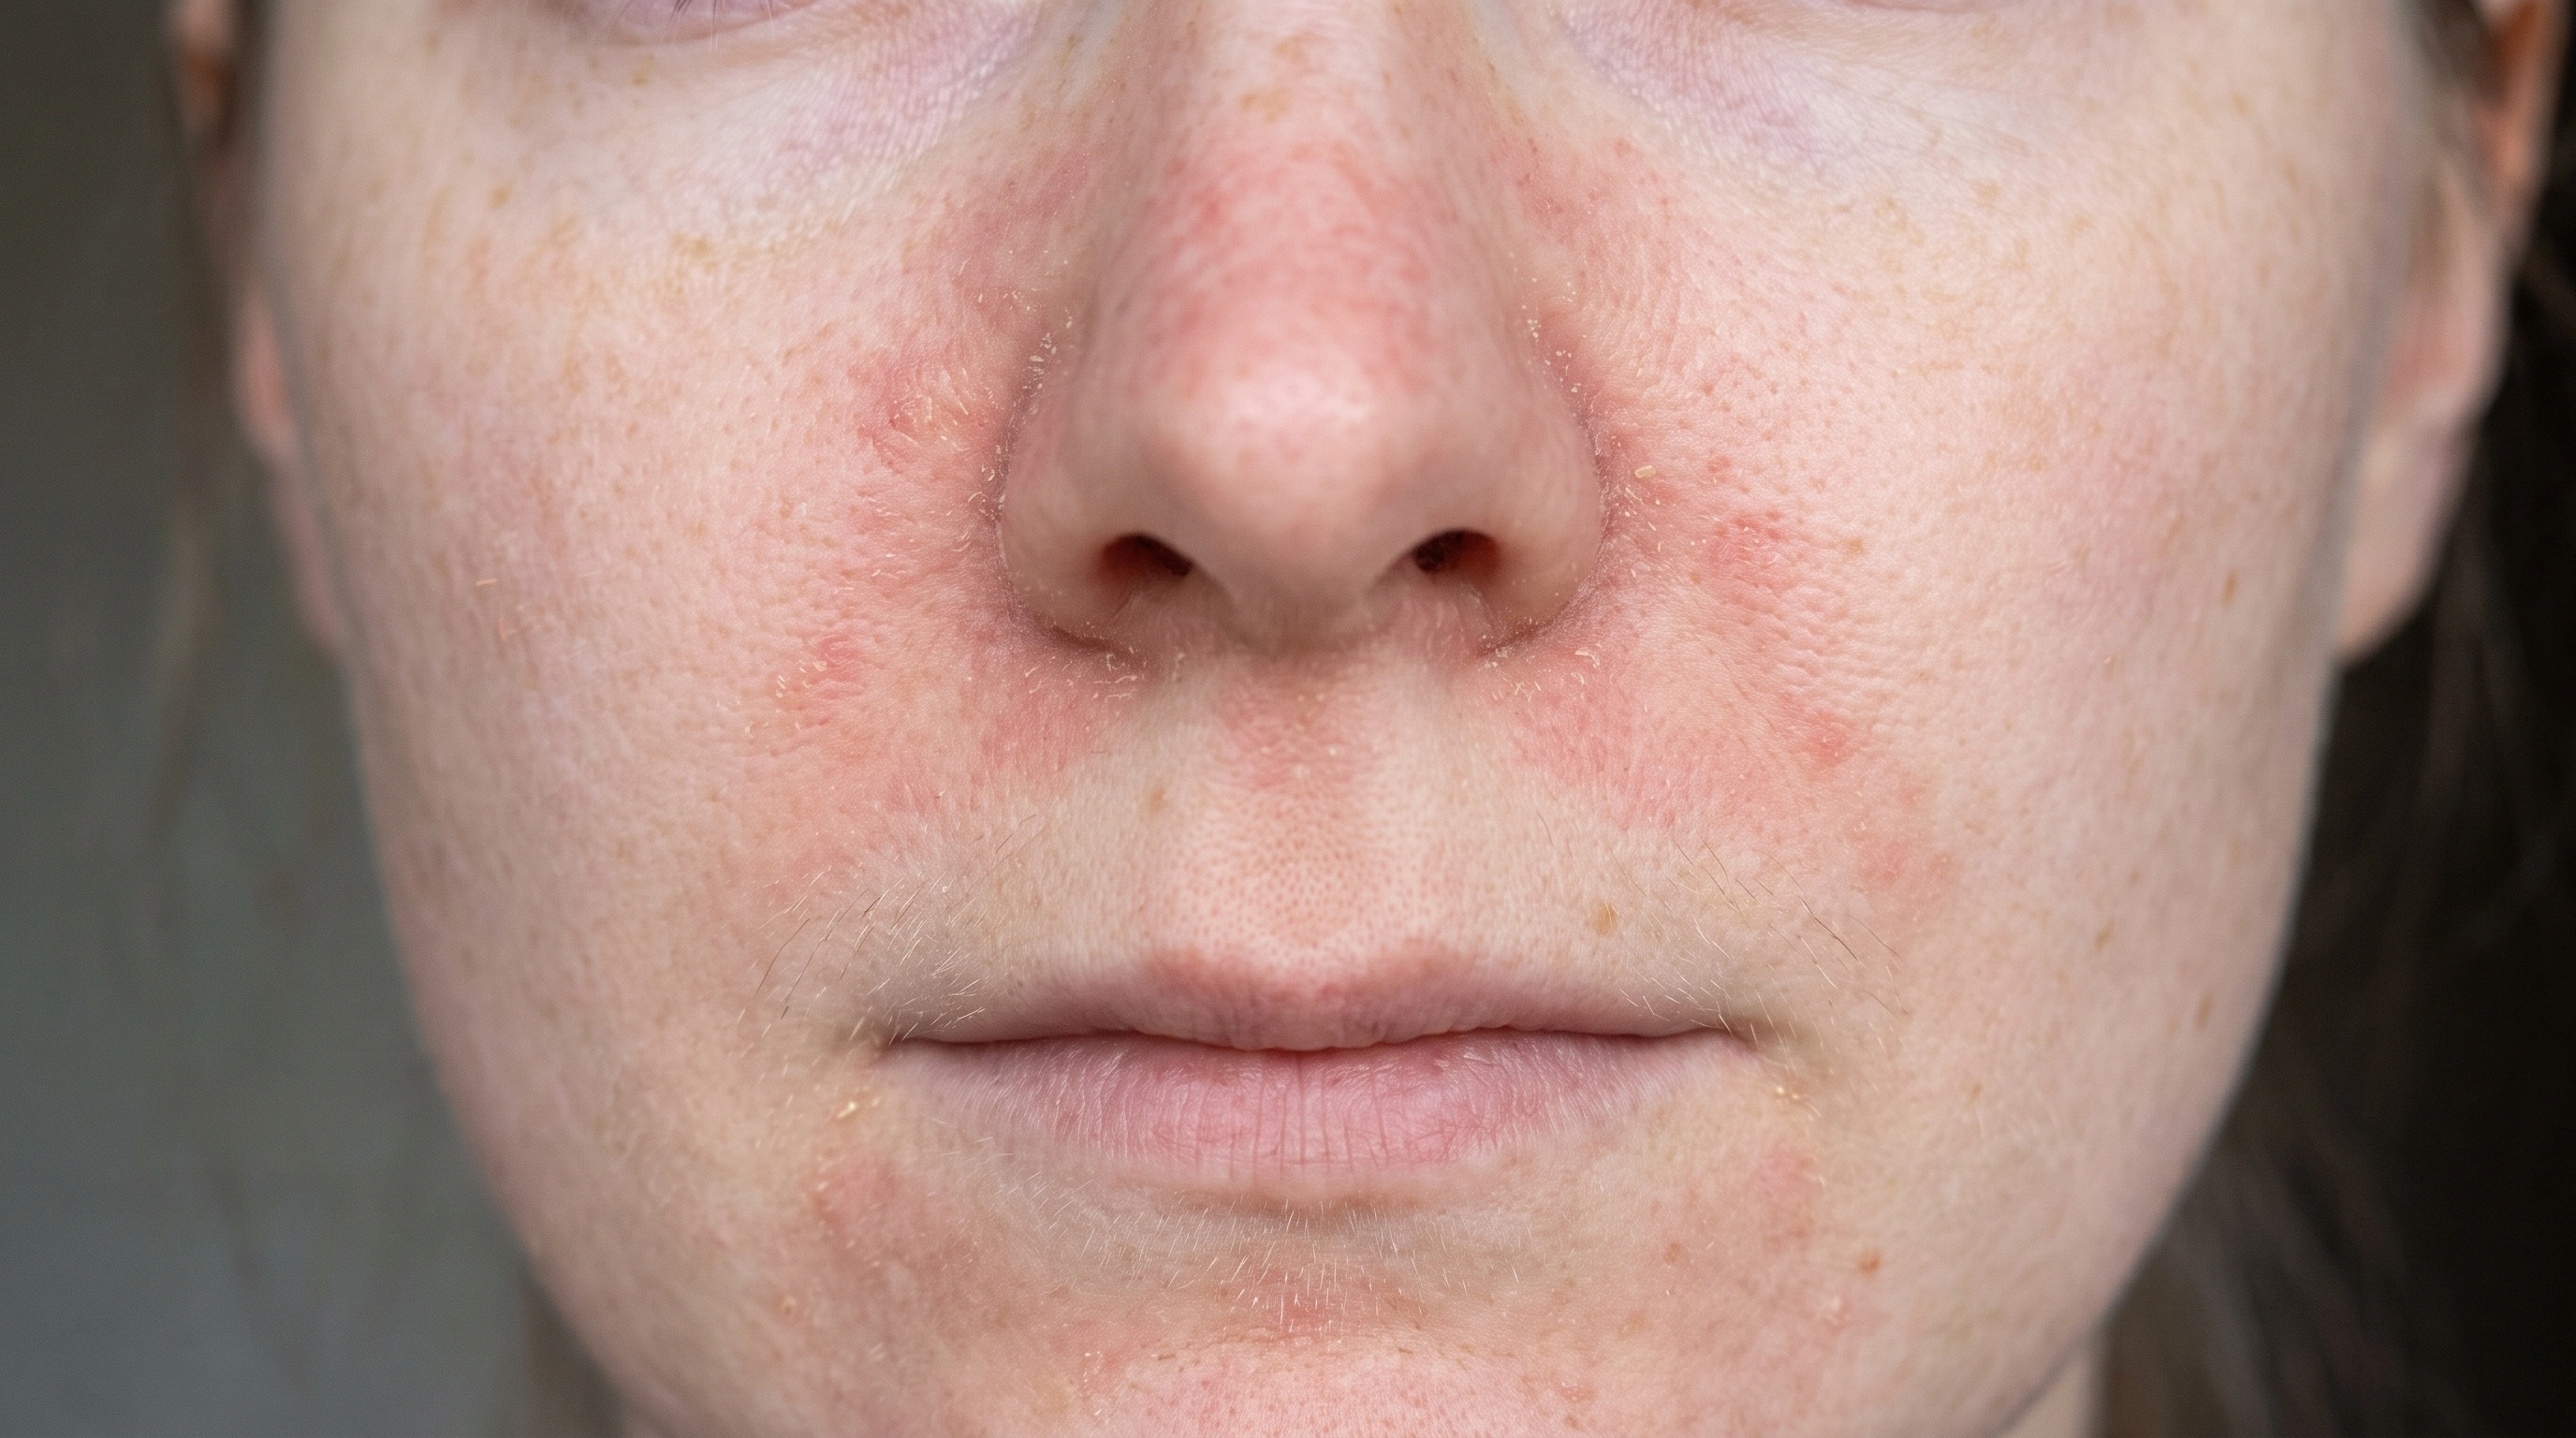
AI-generated educational illustration: Close adult eye with dry mildly red scaly eyelid skin, eye itself normal, no pus or lash crusts.Salmon-pink patches with fine greasy yellowish scale in the crease beside the nose and through the eyebrow on fair skin, with soft edges that fade into normal skin.

Key differences

The same eight facts on every condition comparison.

Usual age
Any age
Babies, then adults
Where
Eyelids
Scalp, brows, sides of nose, ears
Main sign
Dry, itchy, scaly eyelids
Greasy yellow flakes on redness
Itch or pain
Itchy, stinging
Itchy
Contagious
No
No
Long term
Clears when the trigger is found
Long-term, flares
Scars
No
No
Who gets it
Eczema, cosmetics, nail polish allergy
Babies; adults 30 to 60

What is it?

Eyelid Dermatitis
Seborrheic Dermatitis
What is it?
  • What it is
    Eczema of the thin eyelid skin, often related to irritation or contact allergy.
  • It affects oil-rich areas.
    It produces scale and inflammation in sebaceous areas of the skin.
  • Yeast plays a part.
    Malassezia normally lives on skin; an altered response to it contributes to disease.
  • Dandruff is the mild end.
    Dandruff is a milder, scalp-only form of the same spectrum.
  • Care depends on the site.
    A strong scalp treatment may not suit the eyes or facial folds.

What it looks like

Eyelid Dermatitis

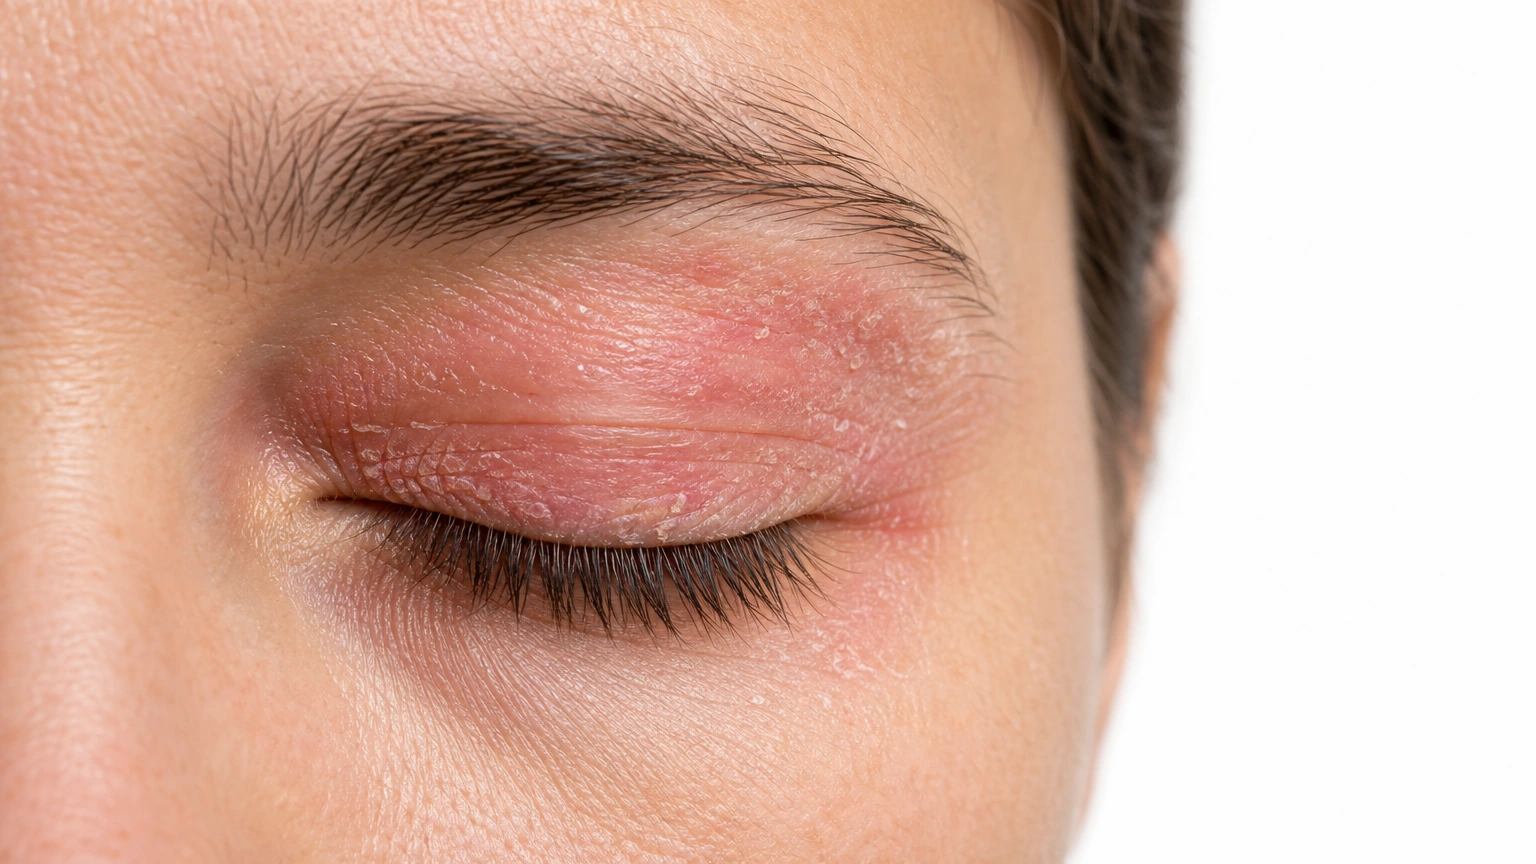
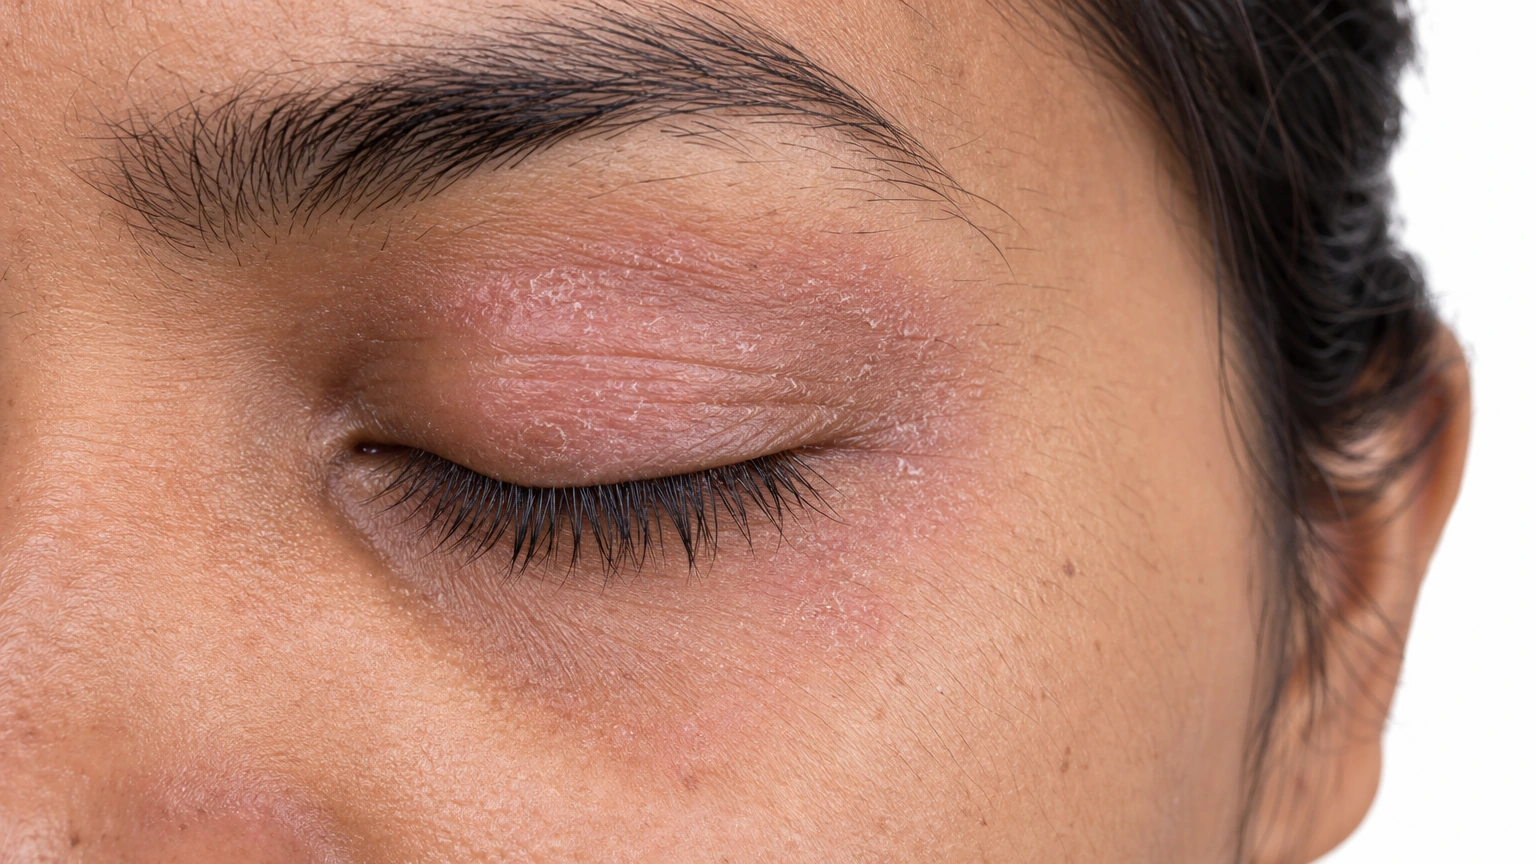
A closed eye with a red swollen-looking upper eyelid and fine surface scale.

Eyelid Dermatitis The upper eyelid has a rough pink patch extending toward the outer corner.

Seborrheic Dermatitis

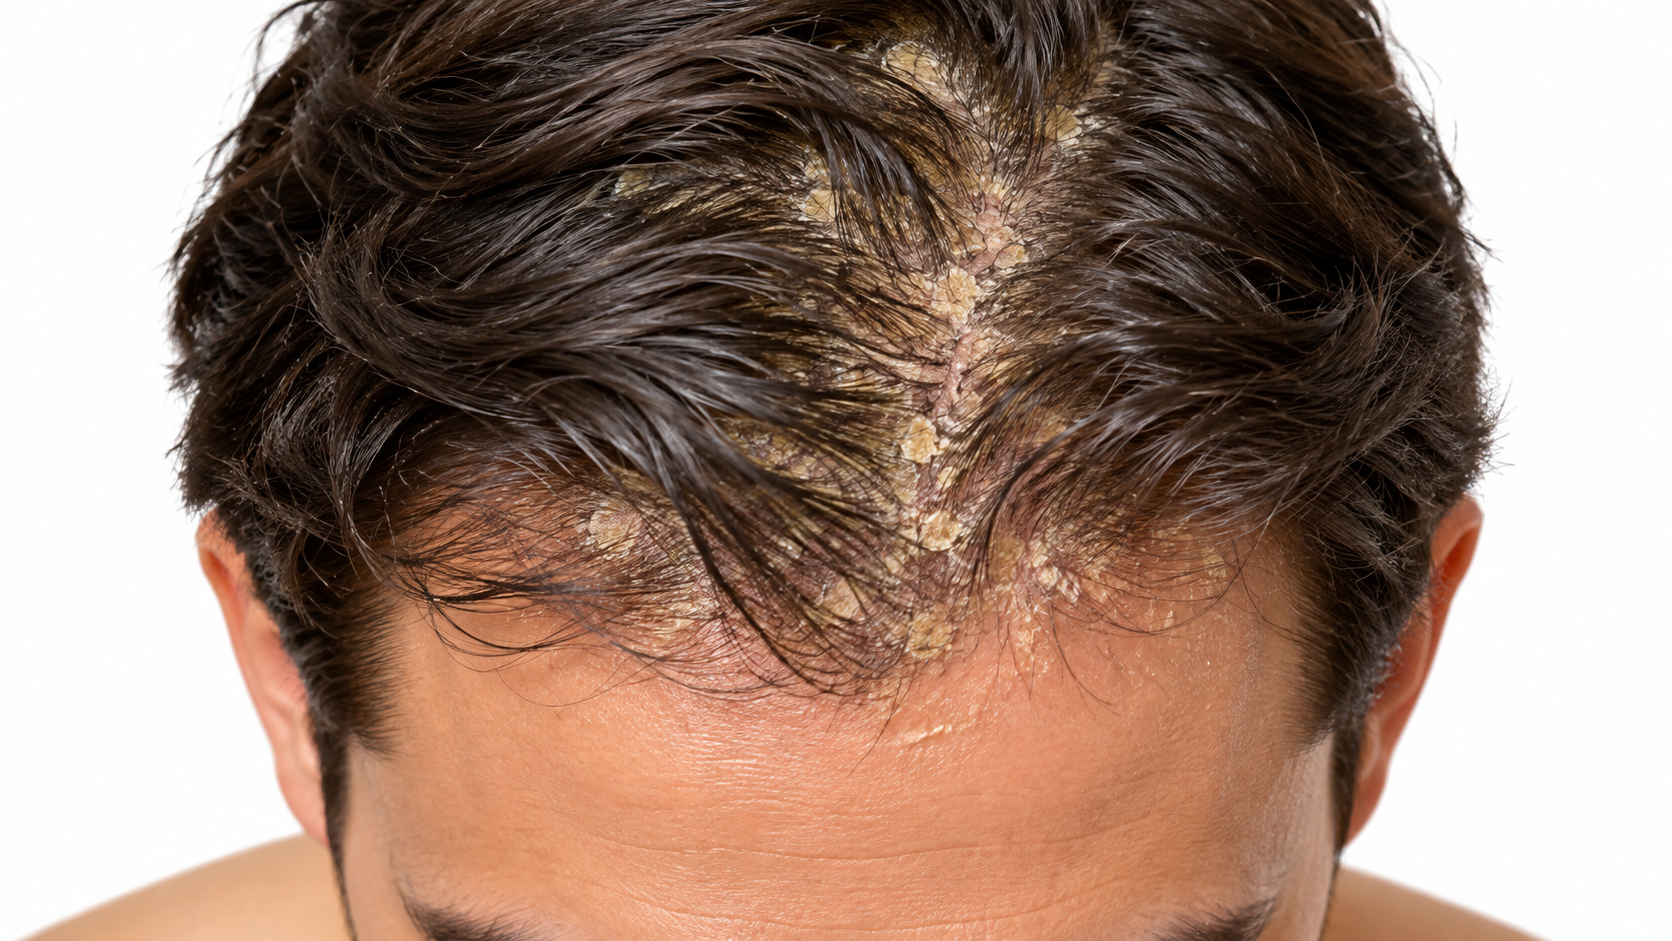
Seborrheic Dermatitis: Greasy scale; Scalp.

Scalp seborrheic dermatitis From mild dandruff to thick scale.

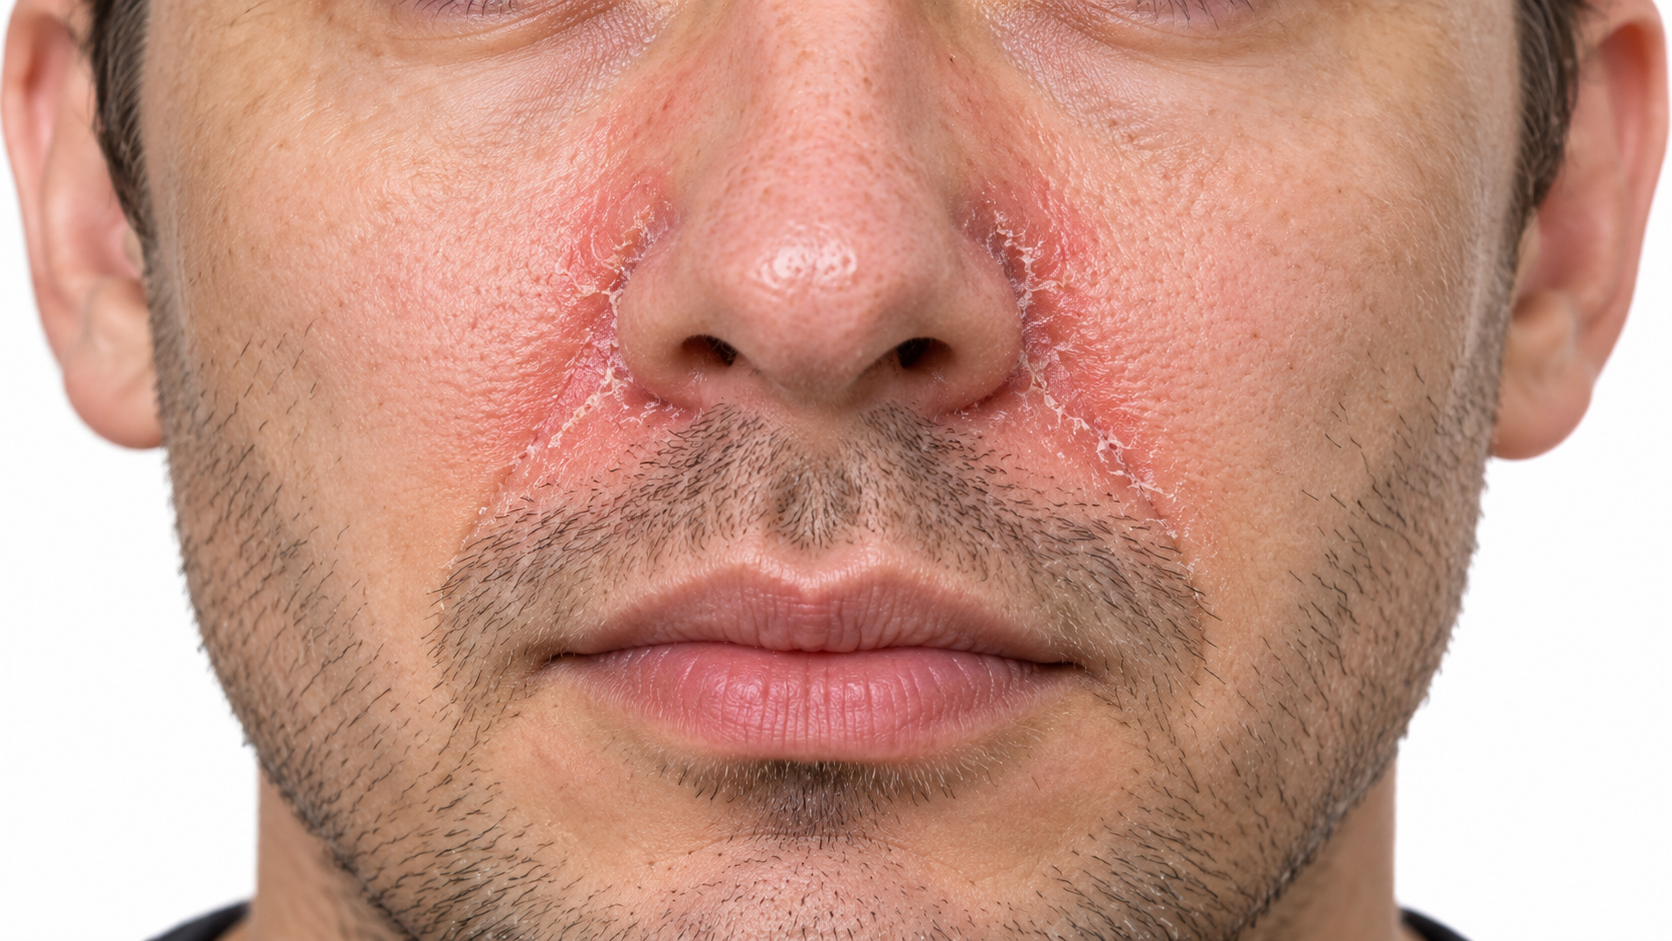
Seborrheic Dermatitis: Sides of the nose; Facial.

Facial seborrheic dermatitis Nose folds, eyebrows and beard.

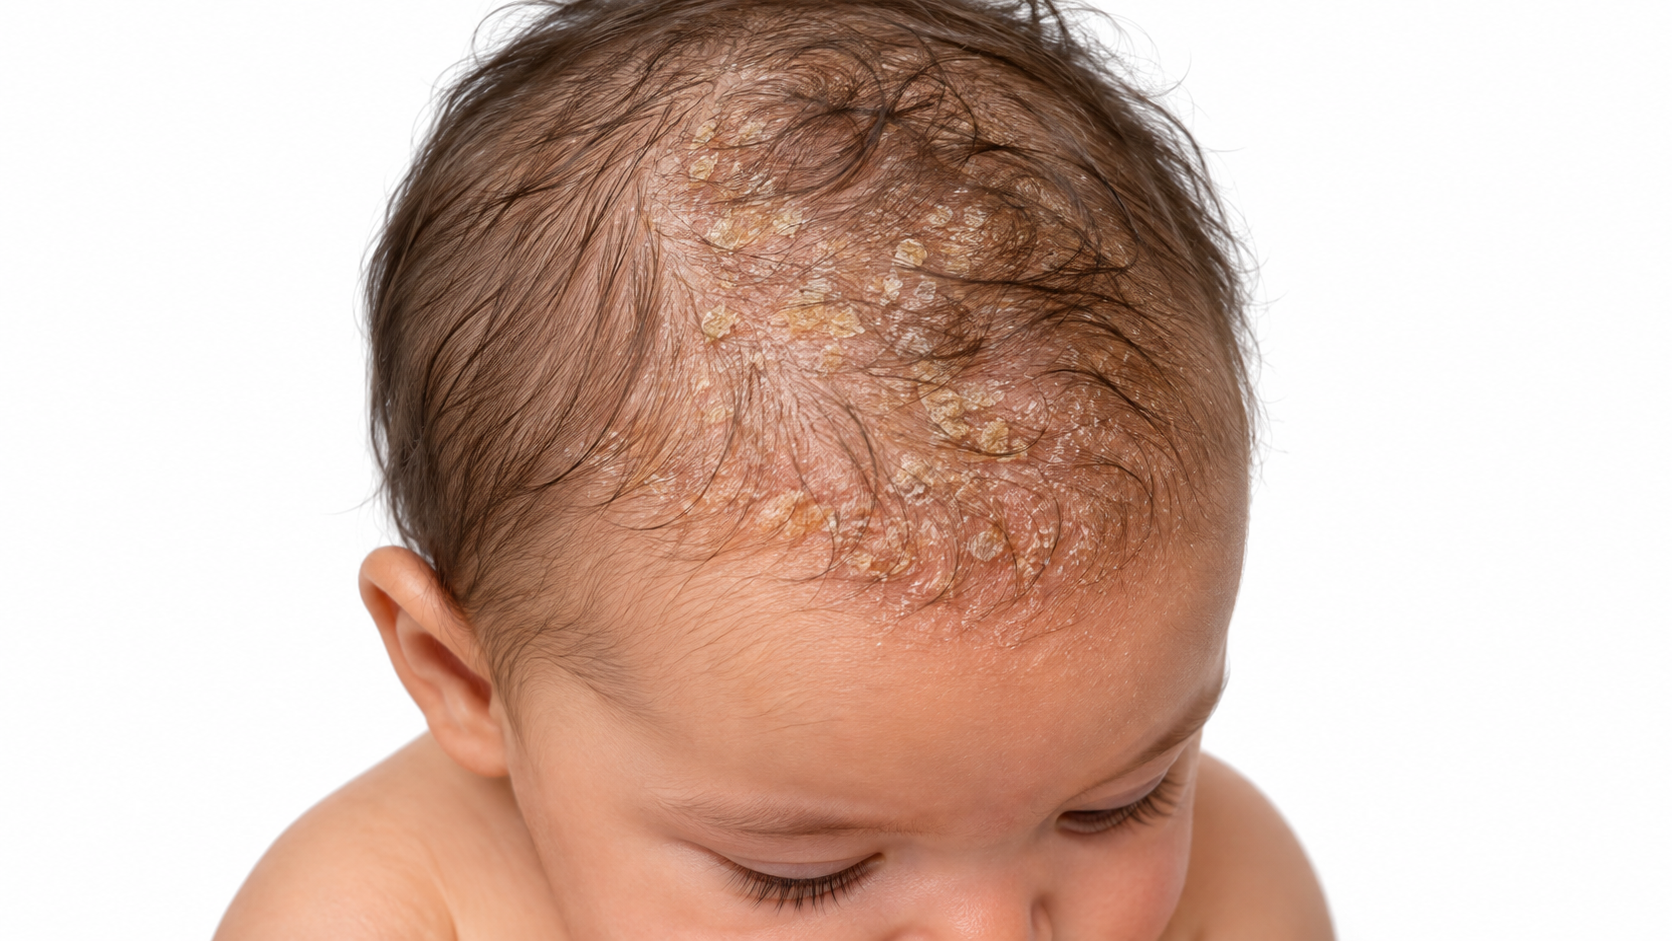
Seborrheic Dermatitis: Cradle cap.

Cradle cap Thick yellow scale on a baby's scalp.

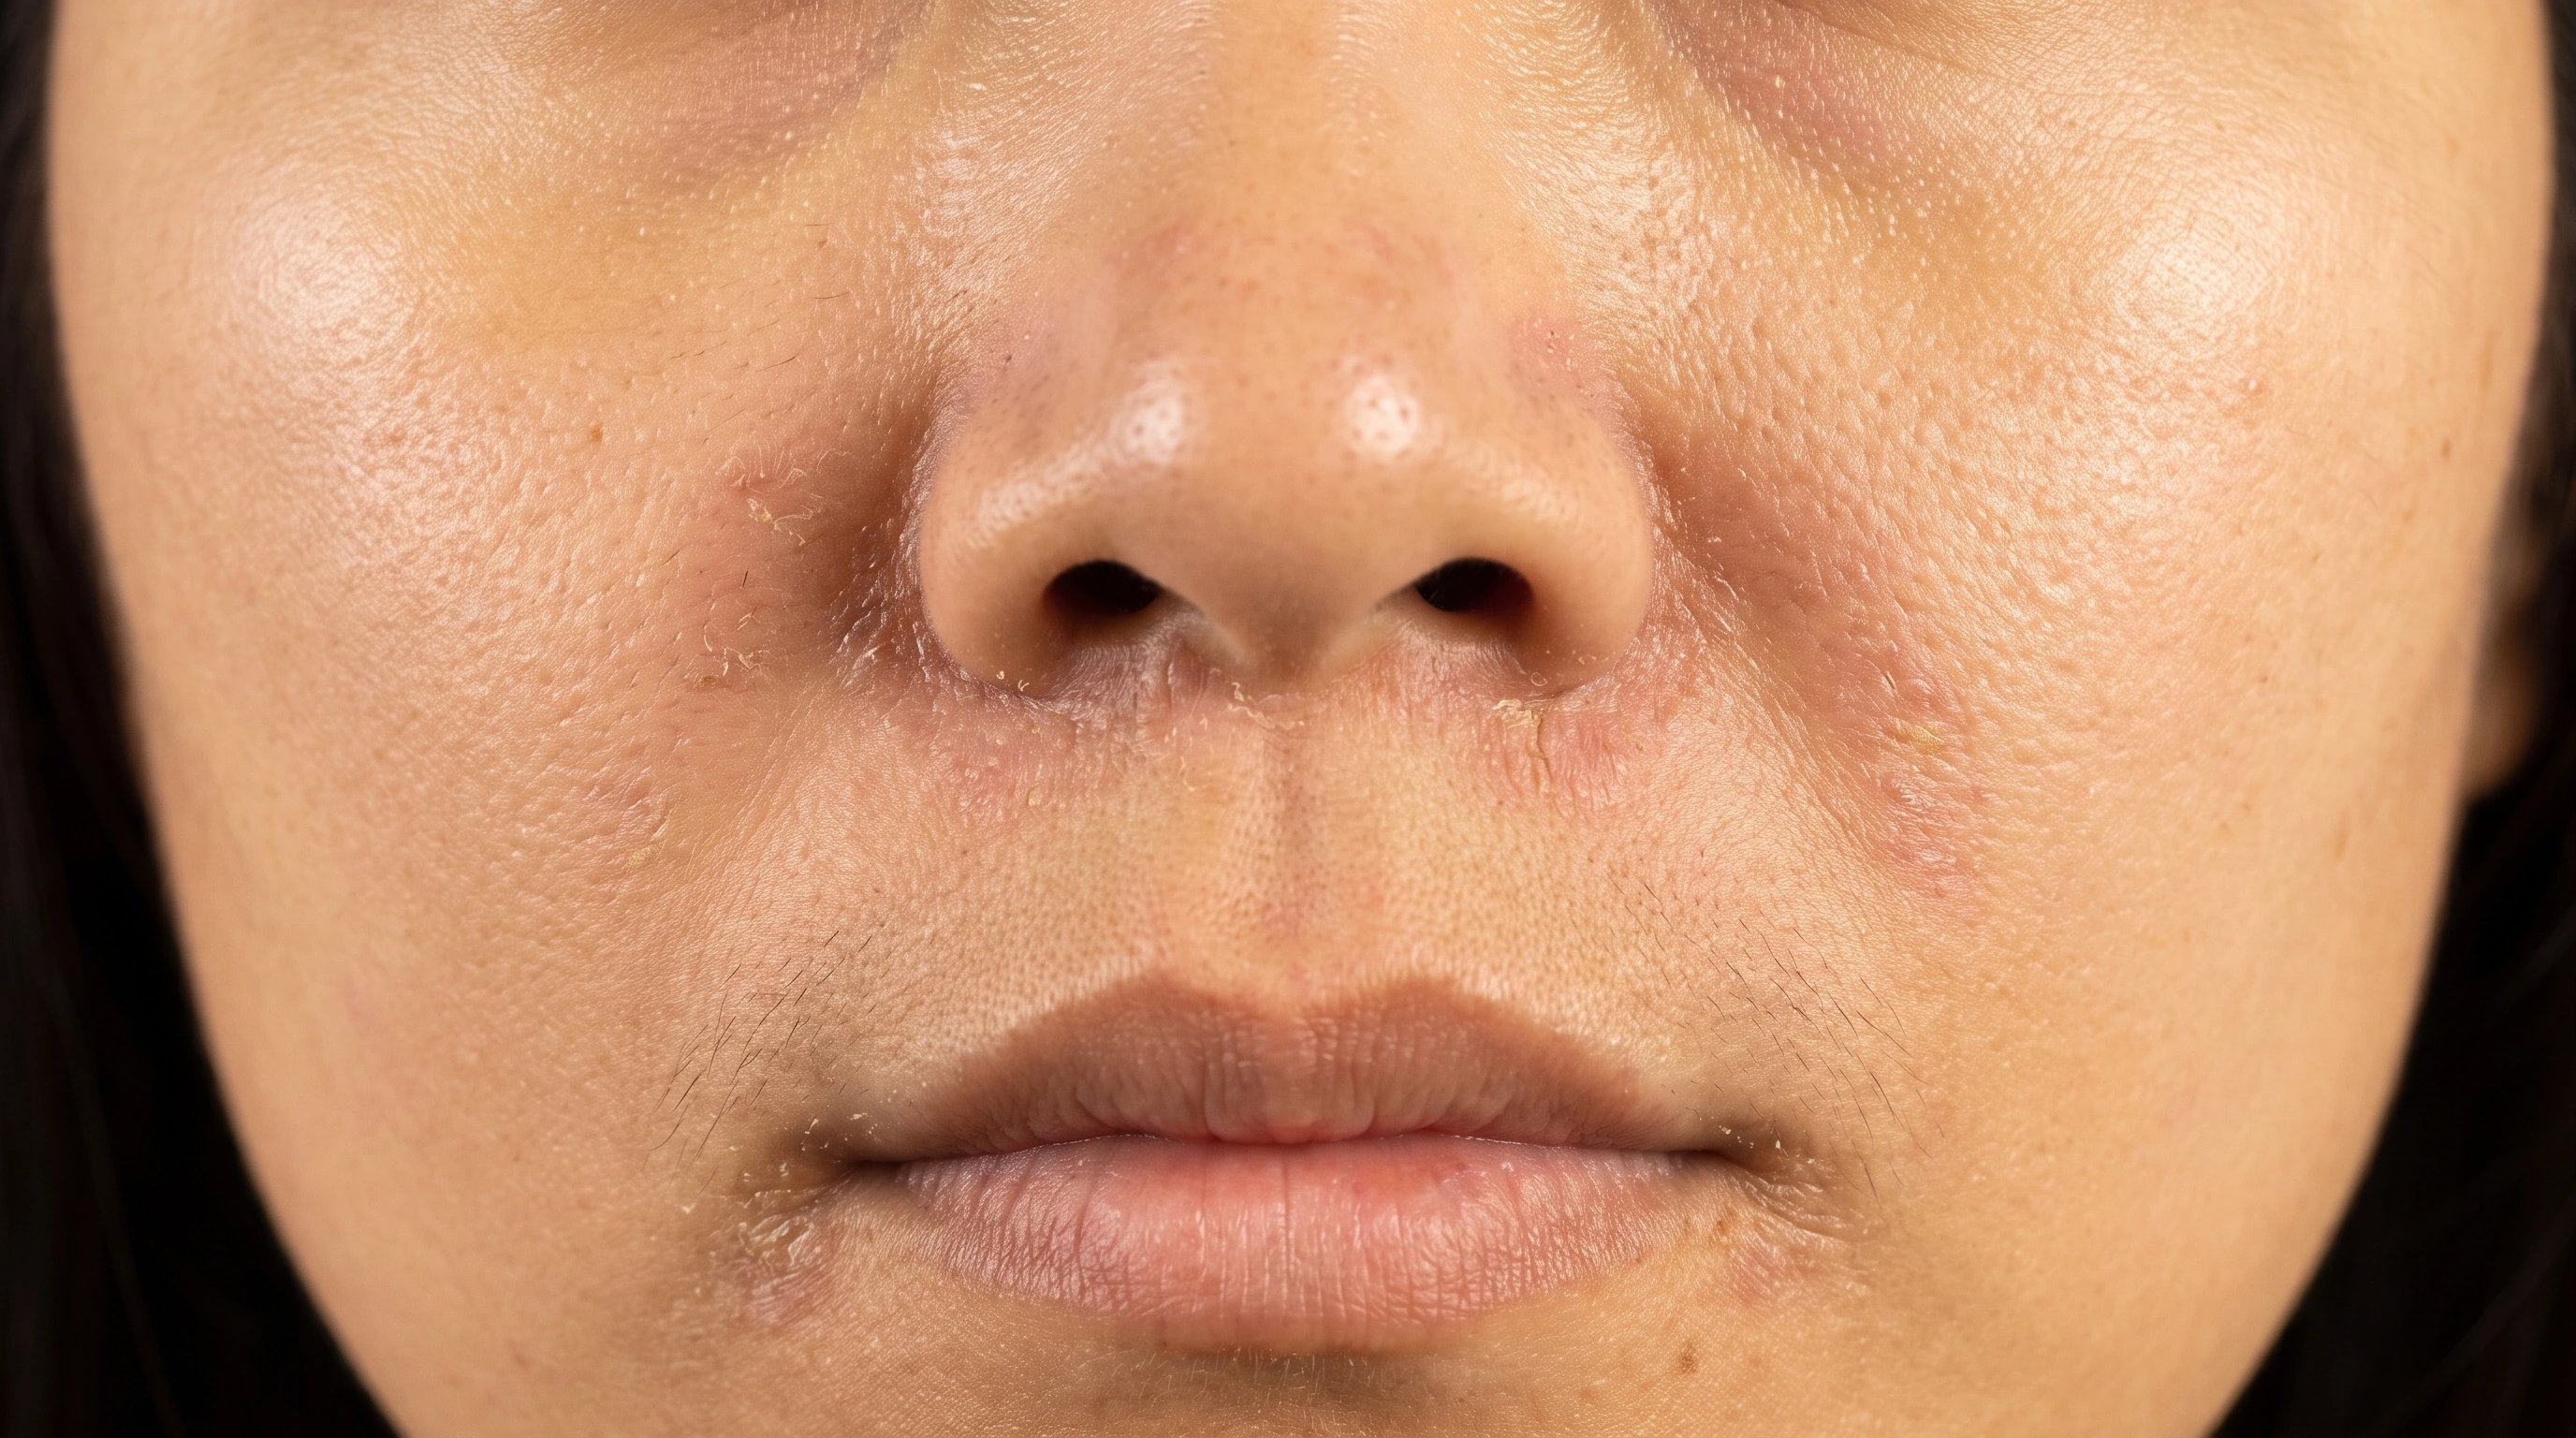
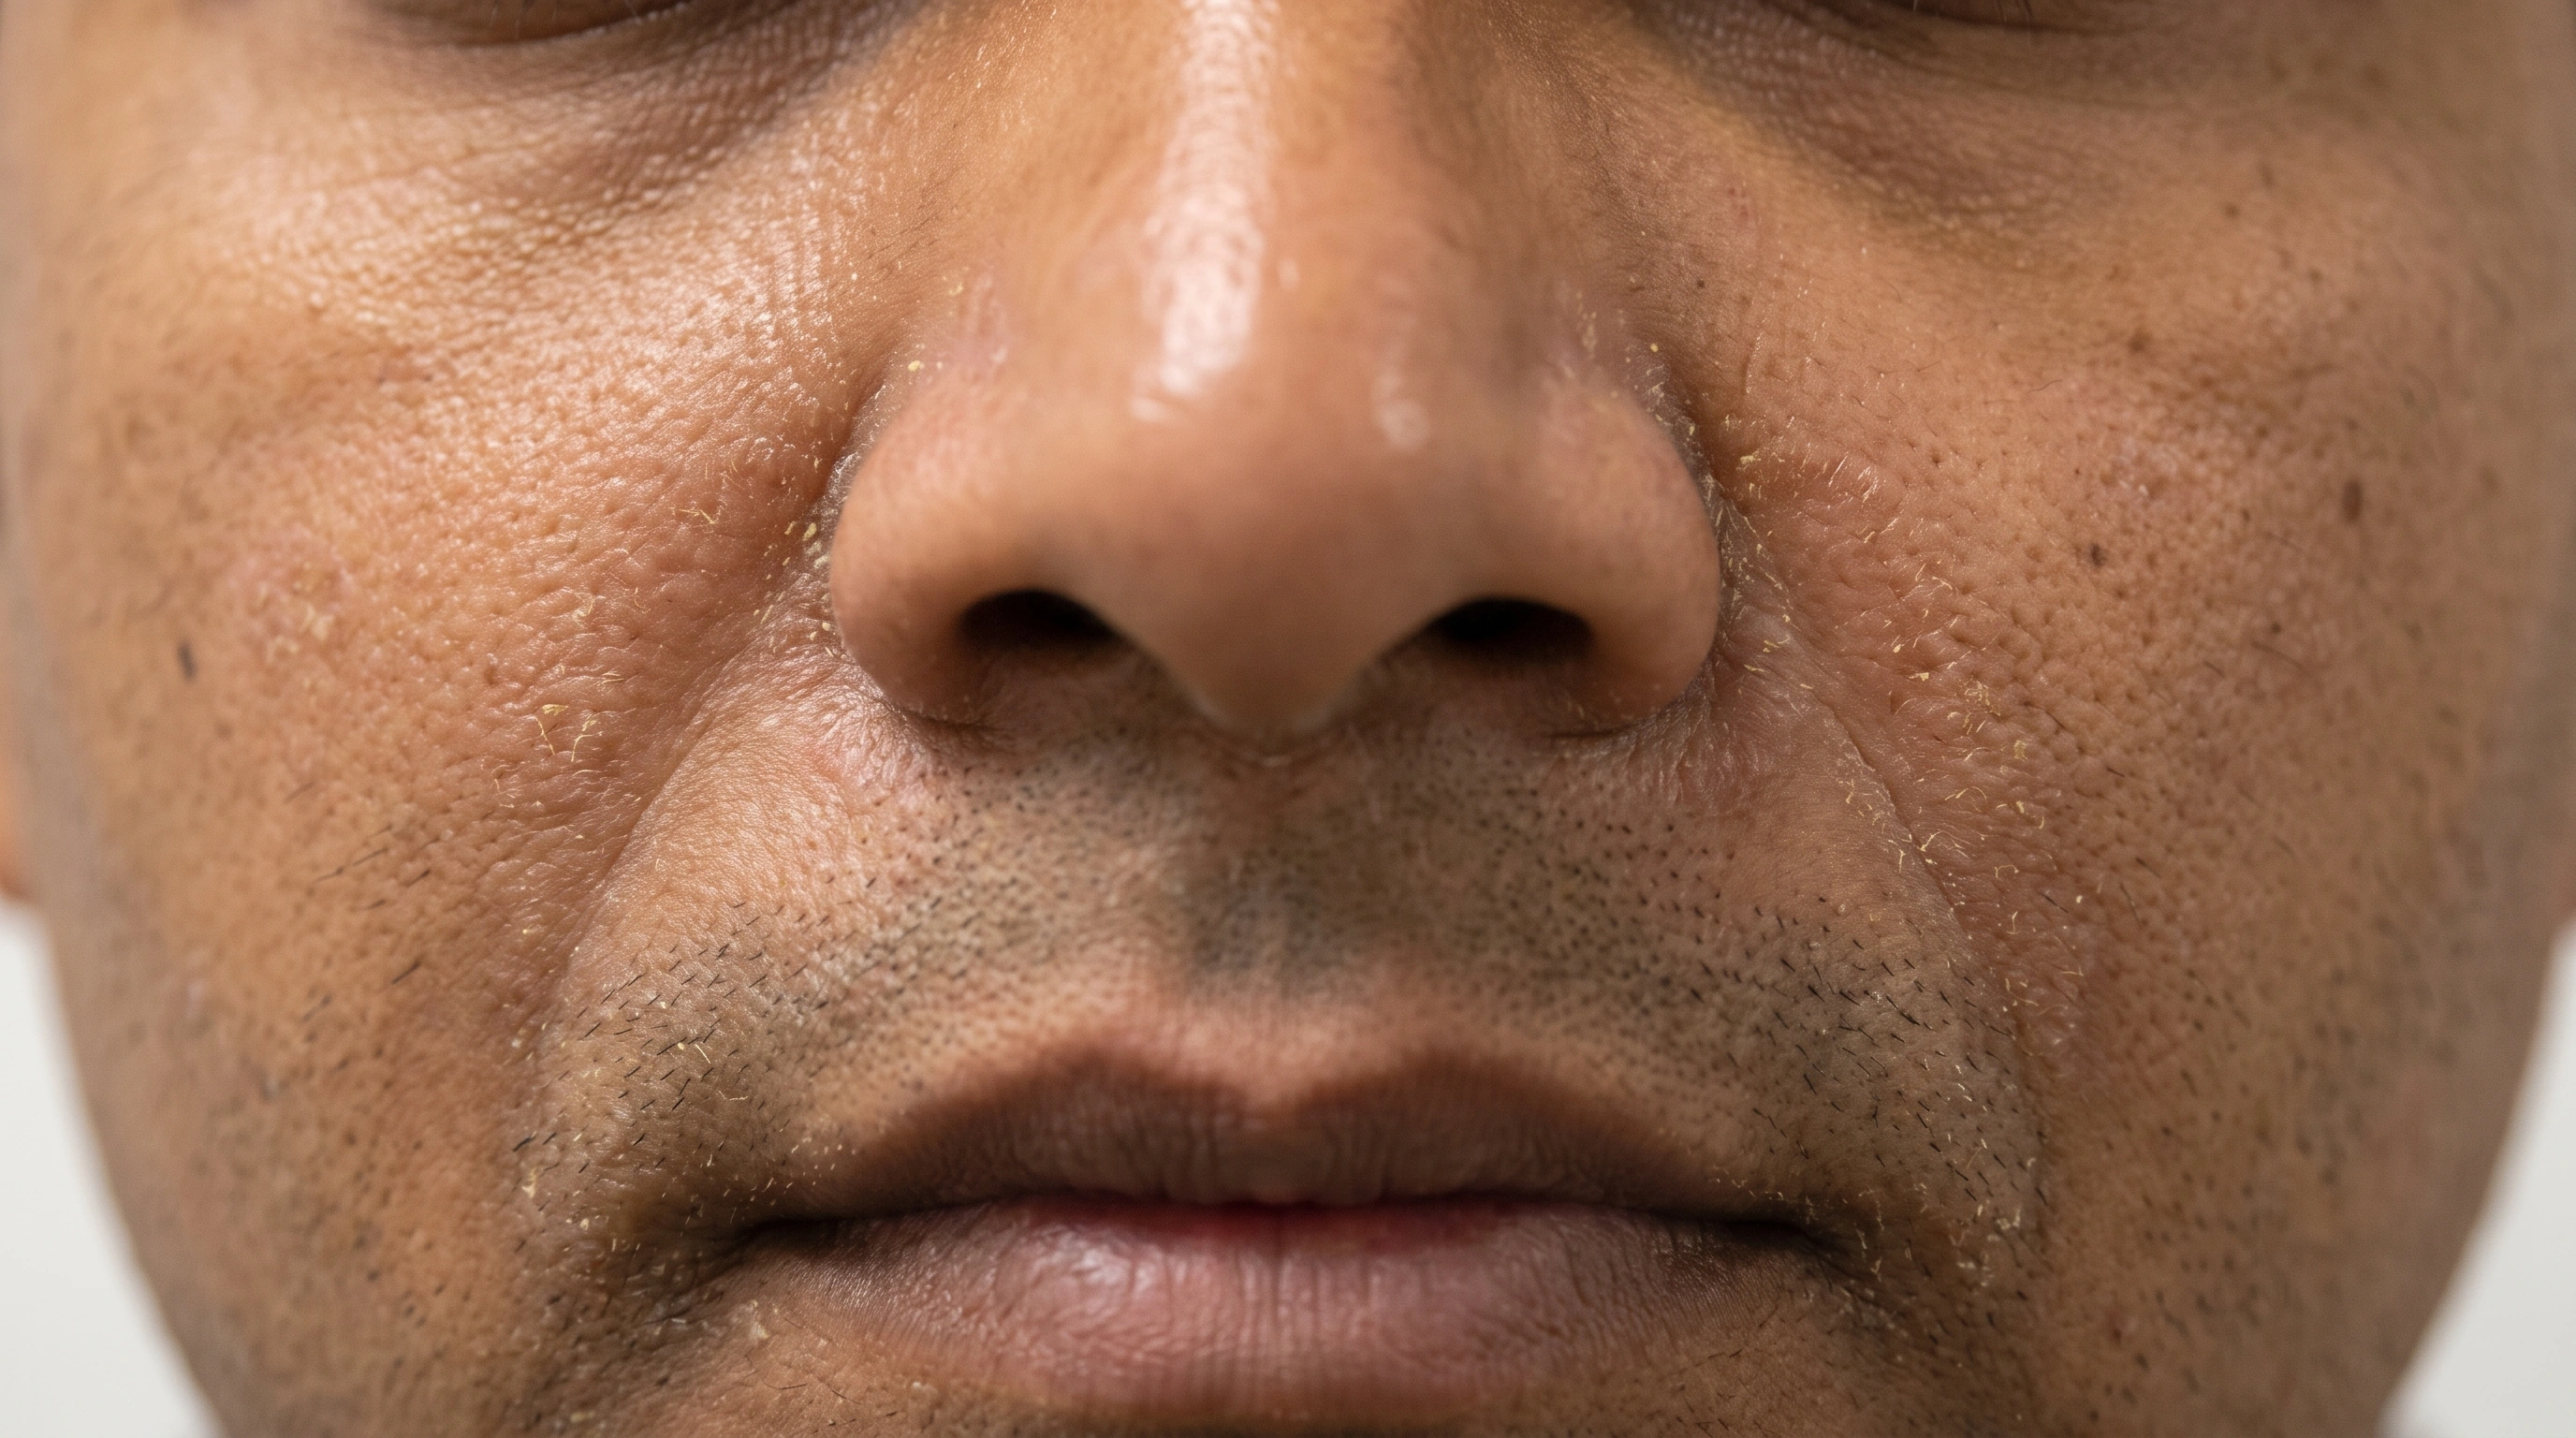
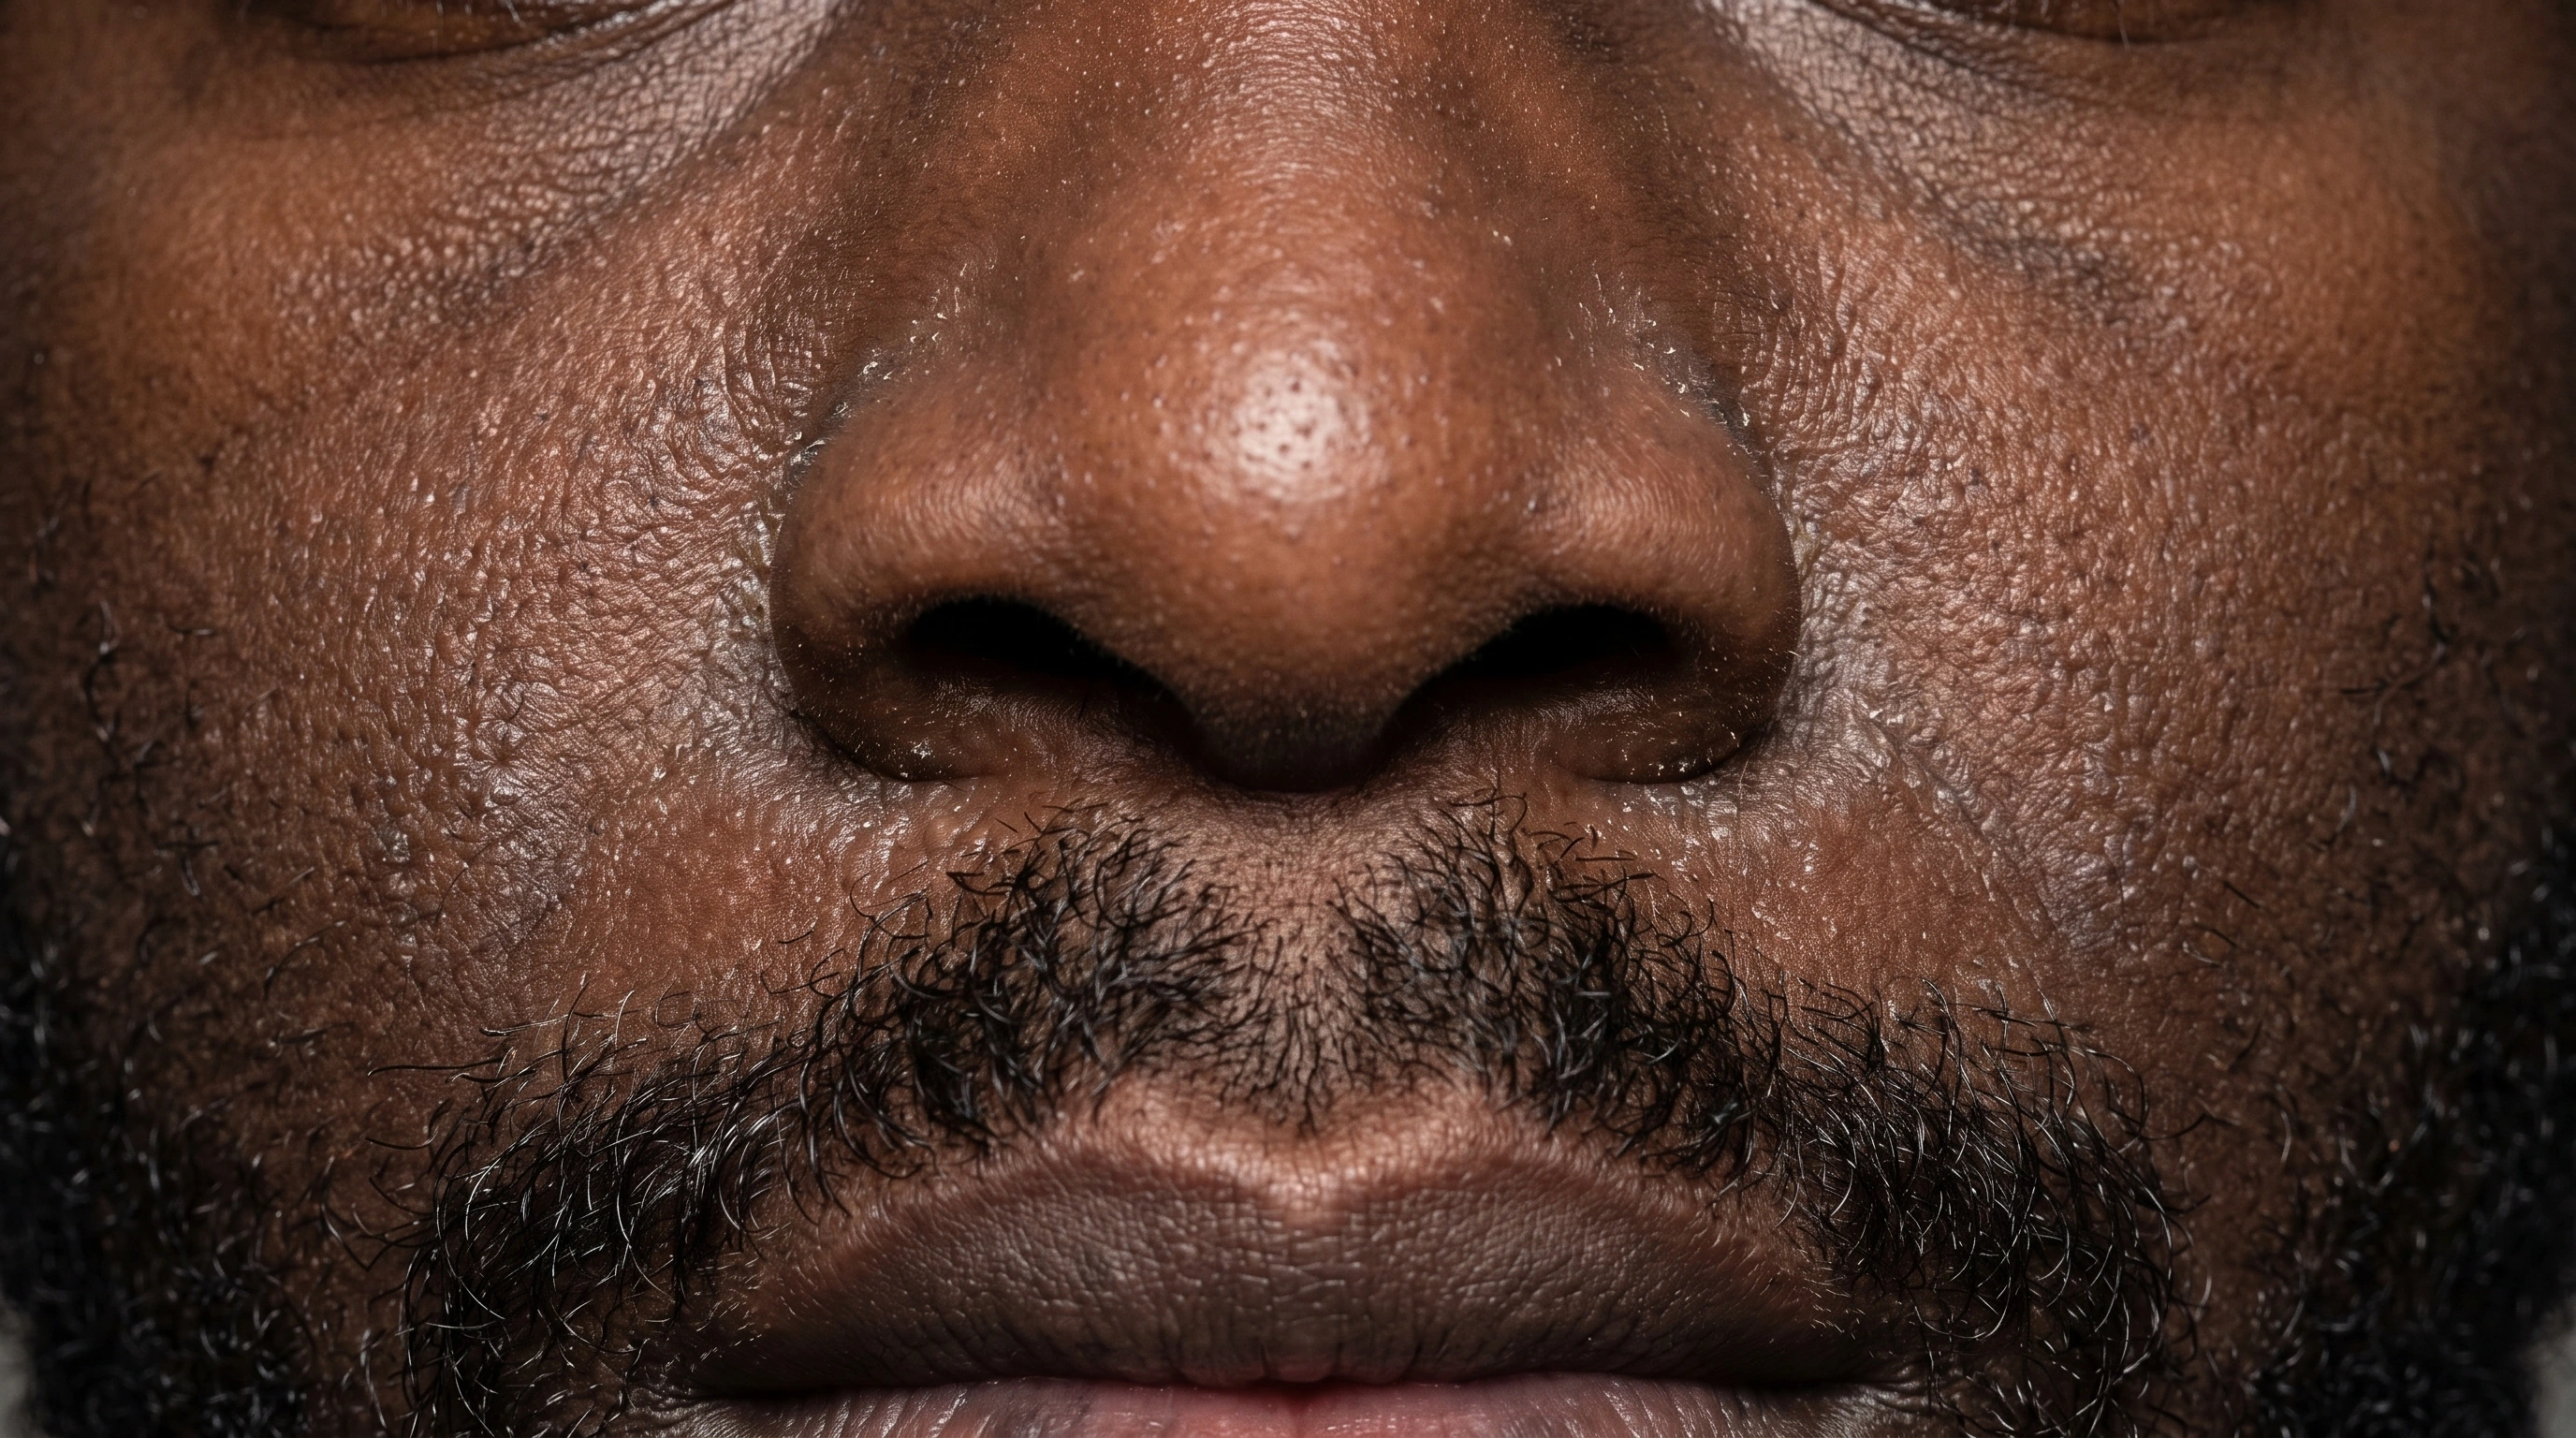
Skin tones
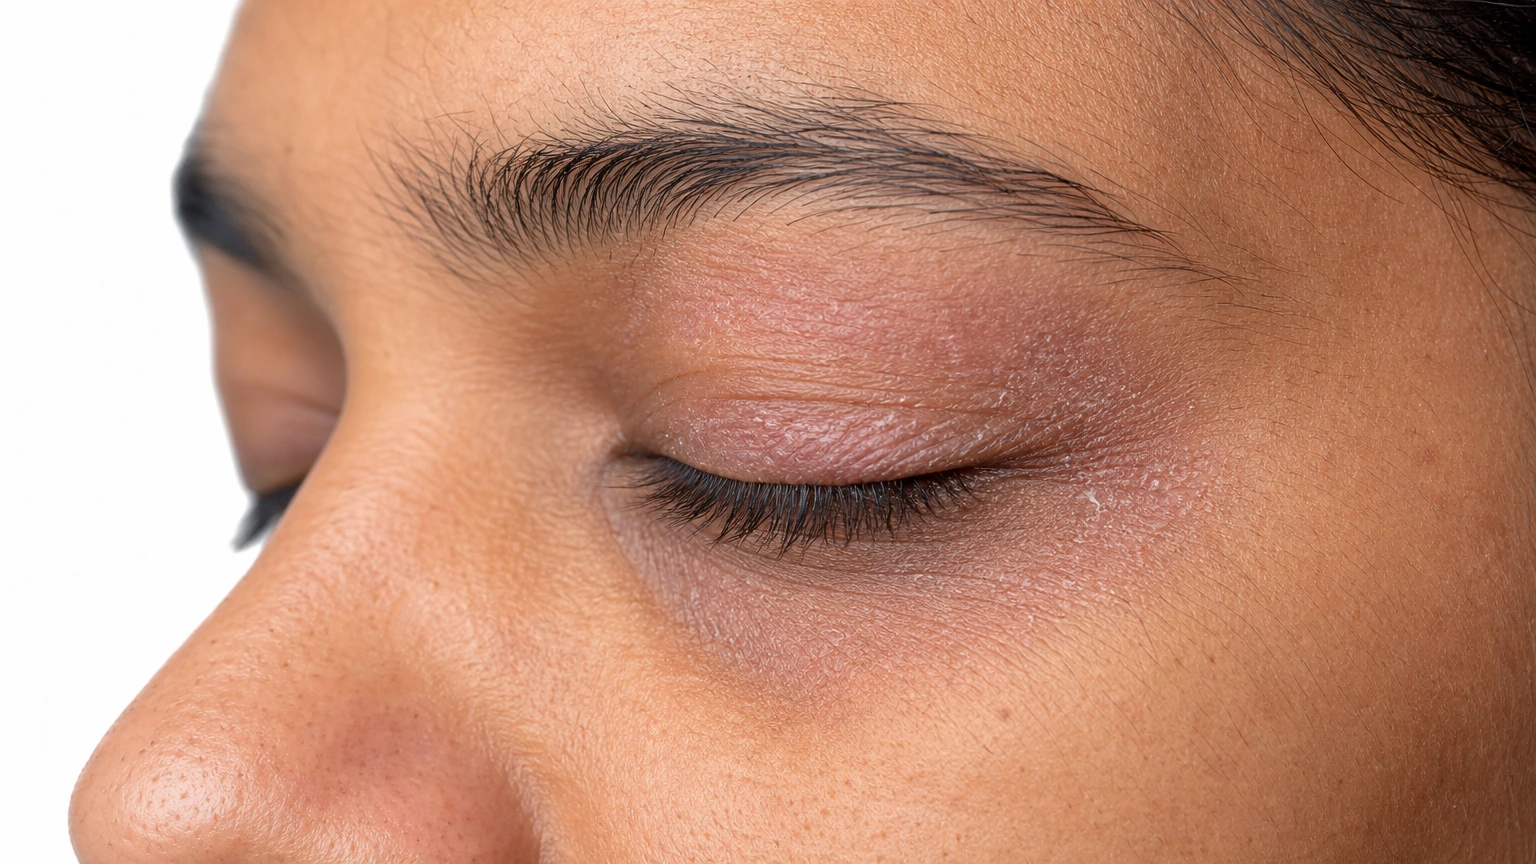
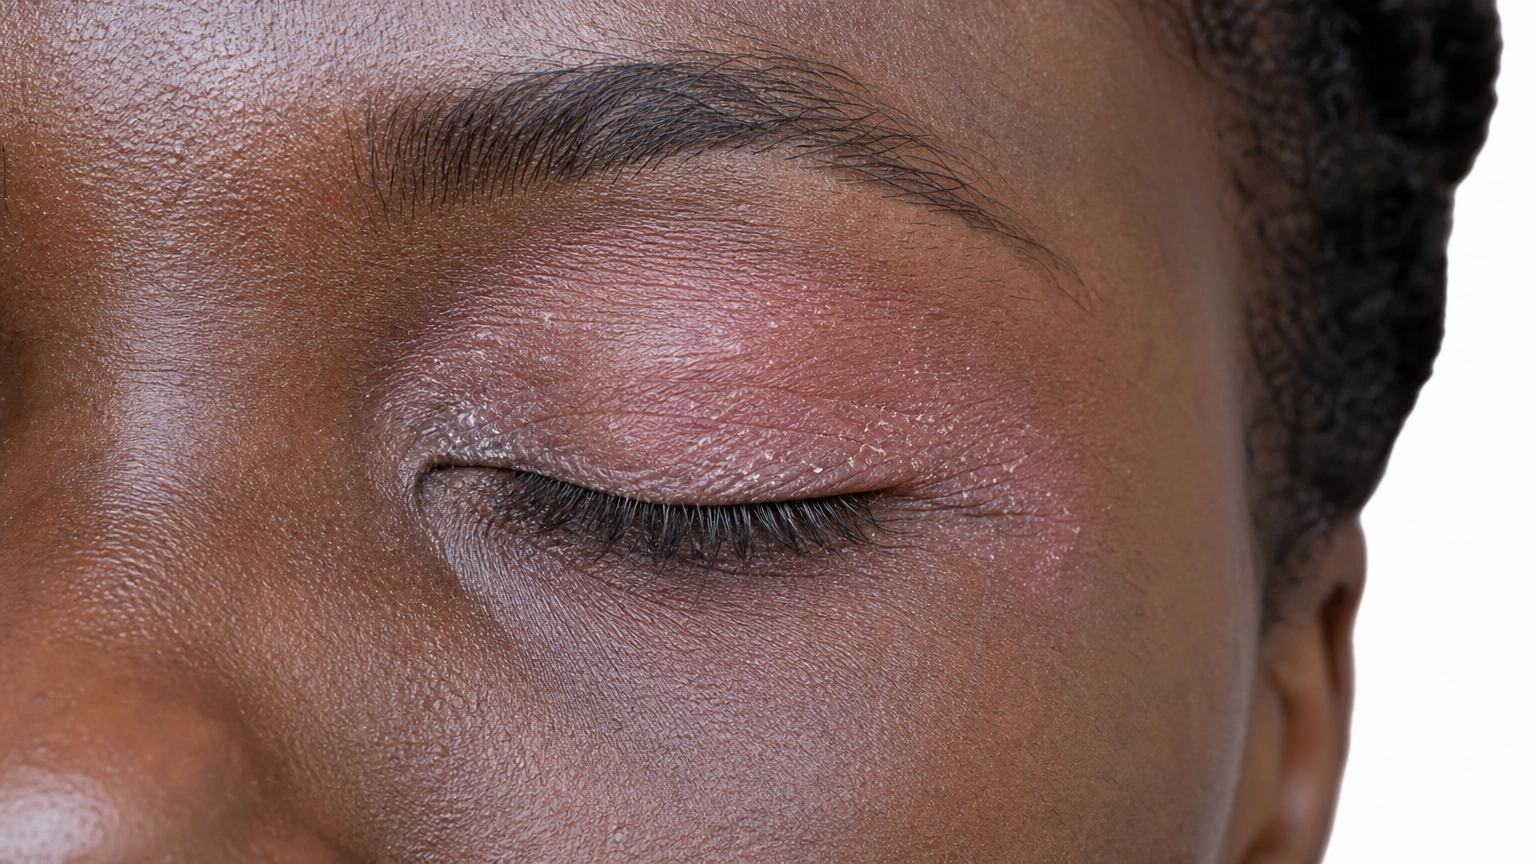
Close adult eye with dry mildly red scaly eyelid skin, eye itself normal, no pus or lash crusts.
Eyelid Dermatitis on medium skin.
Eyelid Dermatitis on brown skin.
Eyelid Dermatitis on deep skin.
Salmon-pink patches with fine greasy yellowish scale in the crease beside the nose and through the eyebrow on fair skin, with soft edges that fade into normal skin.
Dull pink-brown patches with greasy scale through an eyebrow and beside the nose on medium olive skin, one of them slightly lighter than the surrounding skin at its center.
Ring-shaped and petal-shaped patches on brown facial skin along the hairline, each one lighter than the surrounding skin with fine scale across it and soft edges.
Pale patches along a hairline and through the beard area on deep brown skin, some with a trace of fine scale, blending into the surrounding skin without a clear border.
Diagram
Seborrheic Dermatitis mechanism diagram. Yeast uses surface oils: Malassezia lives in oil-rich areas. Sensitive skin becomes inflamed: The skin response contributes to irritation. Greasy scale builds up: Flakes collect on the affected surface.
In the skin

The thin eyelid barrier is especially vulnerable to irritating exposures. Delayed contact allergy can also trigger inflammation, even when the substance reaches the eyelids indirectly.

Malassezia yeast and the skin's response to it contribute to inflammation in oil-rich areas. Irritation and altered surface shedding produce patches with greasy scale.

When it usually starts

010203040506070+

Eyelid Dermatitis. Can start at any age after relevant exposures or barrier damage.

Seborrheic Dermatitis. Occurs in infancy as cradle cap and commonly recurs or begins in adult life.

Causes and triggers

Causes

The thin eyelid barrier is vulnerable to irritants and delayed allergy.

Seborrheic dermatitis is an inflammatory reaction to Malassezia yeast in oily areas of skin. The yeast is normal; the reaction to it is what differs.

Family tendency

It tends to run in families.

Risk factors
Repeated wet work, Irritating products, Eczema tendency
Parkinson's disease, HIV, Babies and adults aged 30 to 60, Oily skin
Trigger
● Eyelid Dermatitis
● Seborrheic Dermatitis
Detergents
Can contribute
Not listed
Friction
Can contribute
Not listed
Repeated wetting
Can contribute
Not listed
Stress
Not listed
Strong link
Cold, dry weather
Not listed
Strong link
Illness
Not listed
Possible
Harsh soaps
Not listed
Possible

Daily Care

Eyelid Dermatitis
Seborrheic Dermatitis
Daily care

Habits that help

  • Touch the eyelids only with clean, rinsed hands
    Product residue on the fingers can transfer irritants or allergens.
  • Wash gently with plain water or a tolerated sensitive-skin cleanser
    Avoid scrubbing the lid margins or getting cleanser in the eye.
  • Pause eye cosmetics and suspect products during a flare
    Nail products, hair dye and face products may also transfer to the eyelids.
  • Use only a bland moisturizer and the agreed eyelid treatment
    Delicate eyelid skin needs a specific plan.

Avoid

  • Avoid: Rubbing, scratching and fragranced products
    These can prolong inflammation and skin thickening.
  • Avoid: Unsupervised steroid creams near the eyes
    Persistent rash, eye pain or vision change needs professional assessment.

Habits that help

  • A plain moisturizer on the face
    Use a plain moisturizer to reduce dryness, stinging and flaking.
  • Gentle washing, not aggressive washing
    Mild cleanser, lukewarm water, no scrubs.
  • Use antifungal shampoo according to the label or prescription
    Apply to the affected scalp and leave on for the contact time specified for that product before rinsing.
  • Use the prescribed facial or chest antifungal schedule
    Frequency and maintenance use depend on the diagnosis and product; follow the agreed plan.
  • Seek assessment for widespread disease or immune suppression
    Widespread disease needs a doctor.
  • Adjust skin care during winter and dry indoor conditions
    The rash returns every year at the same time.

Avoid

  • Avoid: Heavy oils, pomades and greasy products
    The yeast feeds on their fats.
  • Avoid: Growing a beard
    A new warm, oily area, often read as dry skin.
  • Avoid: Sweating under hats and helmets
    Warmth and moisture suit it.
  • Avoid: Washing less often than the scalp needs
    Oil and scale build up.
  • Avoid: Using only a moisturizer on the face
    Nothing touches the yeast.
  • Avoid: Stress, poor sleep and being run down
    A reliable trigger.
  • Avoid: Picking or scraping the scale off
    More damage, more flaking.
  • Avoid: Scrubs, toners and acids on the face
    They strip skin that is already inflamed.
  • Avoid: Stopping the medicated shampoo
    The most common reason it comes back.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Eyelid Dermatitis
● Seborrheic Dermatitis
Filter by type
All types
Seborrheic dermatitis location

Select one or more.

Over-the-counter
None listed
A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh

Hydrocortisone

Moderate evidence

A mild steroid cream that settles the stinging and redness on the face within a few days, which no antifungal does that quickly. Use it for a week or two to break a flare, not as the ongoing plan — the skin beside the nose and on the eyelids thins with repeated use. Something anti-yeast has to run underneath it.


Four dandruff shampoo bottles: DHS Zinc, Head and Shoulders Classic Clean, CeraVe Anti-Dandruff and Head and Shoulders Bare

Pyrithione Zinc

Moderate evidence

The active ingredient in most ordinary anti-dandruff shampoos, and a reasonable choice for scalp flaking without much inflammation. It is gentler and easier to use often than ketoconazole. If it has stopped helping, rotating to a different active ingredient usually works better than looking for something stronger.

Two Selsun Blue bottles, two Head and Shoulders Clinical Strength bottles and a Vichy Dercos bottle and box

Selenium Sulfide

Moderate evidence

Another shampoo that reduces the same yeast by a different route, useful when ketoconazole has lost its edge. It works well on a thickly scaling scalp. It has a strong smell and can discolor light, gray or chemically treated hair, so rinse thoroughly and keep it off the length where you can.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

A descaler for a scalp that has built up a thick crust. It loosens the scale so the antifungal underneath can actually reach the skin. It does nothing to the yeast or the inflammation, and on an already stinging face it is more likely to irritate than to help.

Five medicated scalp products on white, including Amazon Basics tar gel, T+Plus, MG217, RoyceDerm and Nizoral

Coal Tar

Limited evidence

An older shampoo that slows scaling and helps some people with a stubborn, thickly flaking scalp. It is more useful when psoriasis is in the picture too. It smells strong and can stain light hair, and there are gentler options with better evidence for this condition, so it is rarely where to start.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Limited evidence

A 5% shampoo has been tested in dandruff with a modest result, and some people do find it helps. It is a common cause of allergic reactions on the face, so it is best kept to the scalp. Undiluted oil straight onto inflamed skin is a reliable way to make things worse.

Five coconut oil bottles and a jar on white, most labeled fractionated or organic virgin coconut oil

Coconut Oil

Avoid

The most popular home remedy for this, and one of the few that can genuinely backfire. Malassezia feeds on the fats in most plant oils, so oiling the scalp can hand it more of what it uses, and heavy oils also trap scale against the skin. Softening a crust before washing is the one job an oil does well here.

Prescription topicals

Clinician-selected eyelid treatment

Listed

A brief low-potency steroid or a steroid-sparing medicine may be appropriate; avoid unsupervised potent steroids near eyes.

Ketoconazole — Header Image

Ketoconazole

Strong evidence

Ketoconazole 2% cream. The prescription strength, as a cream for the face, ears, beard area and chest, where a shampoo is impractical. Used daily it settles a facial flare in one to two weeks, then drops to twice a week to hold it. It treats the yeast and not the inflammation, so a sore, stinging face often needs something alongside it for the first week.

Representative medication packaging labelled Zoryve, lying sideways on a white background.

Zoryve

Strong evidence

A once-daily non-steroid foam approved specifically for seborrheic dermatitis, and it works on the scalp and the face with the same product. It suits people who have been leaning on steroid creams on the face for a long time. Cost and insurance coverage are usually the deciding factor rather than the medicine.

Protopic — Header Image

Protopic

Moderate evidence

Calms the inflammation on the face without thinning the skin, which is what makes it useful around the nose creases and the eyebrows where steroids cannot be used for long. It stings or feels warm for the first few applications and then settles. It is often used twice a week to hold a face that keeps flaring.

16:9 hero for Elidel. Never cropped: the tone strip and the corner logo depend on the full frame.

Elidel

Moderate evidence

The gentler of the two non-steroid creams, and usually the better fit for thin, easily irritated facial skin. It works a little more slowly than tacrolimus and stings less. Like tacrolimus, its main job here is keeping a face clear without steroids.

16:9 hero for Desonide. Never cropped: the tone strip and the corner logo depend on the full frame.

Desonide

Moderate evidence

A mild prescription steroid for a face that is inflamed and sore, used for one to two weeks to break the flare. It is stronger than over-the-counter hydrocortisone and still gentle enough for facial skin. It is a short course, not a maintenance plan — long steroid use on the face causes its own rash.

Clobetasol — Header Image

Clobetasol

Moderate evidence

Clobetasol scalp solution. A strong steroid shampoo or solution, used on the scalp only, for a thickly scaling flare that an antifungal has not shifted. Two to four weeks at most. It is never for the face, and the antifungal has to keep running underneath it or the flare simply comes back when the steroid stops.

Prescription pills
None listed
Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Limited evidence

Antifungal tablets, usually a short course, for seborrheic dermatitis that is severe, widespread, or has not responded to creams and shampoos used properly. They clear it faster than anything applied on the skin. It interacts with a long list of other medicines and needs a full list of what you take before it is started.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Limited evidence

A weekly antifungal tablet sometimes used for widespread or stubborn disease when itraconazole does not suit. The evidence for it in this condition is thinner. Either way, tablets clear a flare rather than change the condition, so the shampoo or cream still has to continue afterwards.

A white blister pack photographed flat on a white background, holding eight white oblong capsules in two rows of four under clear domes. ACCUTANE is printed in blue capitals on the empty left half of the foil.

Accutane

Limited evidence

A low dose shrinks the oil glands, and with less oil there is less for the yeast to feed on. It is reserved for severe disease that nothing else has controlled, because it dries the skin, lips and eyes and requires strict pregnancy prevention and monitoring. It is an unusual choice here, not a routine one.

Terbinafine — Header Image

Terbinafine

Limited evidence

A common antifungal tablet that people are often given for this, and it is a poor match — it works well on the fungi behind athlete's foot and nail infections but has little effect on Malassezia. If a course of it has done nothing, that is expected rather than a sign the diagnosis was wrong.

Procedures
None listed
Editorial illustration for Phototherapy, based on the entry’s treatment or equipment reference.

Phototherapy

Limited evidence

Narrowband UVB in a clinic, considered only for widespread disease on the body that has not responded to creams. It fits with the fact that most people improve in summer. It means several visits a week for weeks, which is a lot of effort for a condition that usually answers to a shampoo, so it is rarely used.

Outlook

Long term

Eyelid eczema can improve once irritating or allergic exposures are identified and avoided. Recurrence is common with further exposure; persistent symptoms may need testing or a revised treatment plan.

Seborrheic dermatitis commonly returns after treatment is stopped, so maintenance may be needed. Symptoms can be controlled even when the tendency remains. Infantile seborrheic dermatitis usually follows a shorter course and often settles as the baby grows.

Complications

Possible complications

Cracked skin may become infected; repeated exposure can make the rash persistent.

  • Pale marks left behind
  • Sore, crusted eyelid edges
  • Infection in scratched skin
More details

Pale marks left behind
On deeper skin tones the rash commonly leaves flat pale patches, often ring-shaped or petal-shaped, along the hairline and on the face. For many people these are the real complaint, not the flaking. The color comes back — the inflammation interrupted pigment production rather than destroying it — but it can take several months, and treating the inflammation early is what shortens it.

Sore, crusted eyelid edges
Seborrheic dermatitis can settle on the rims of the eyelids, where it causes greasy crusting at the base of the lashes, redness along the edge, grittiness and morning stickiness. It is common and it is treatable, but face creams and shampoos are not safe this close to the eye. It needs its own plan, so mention it rather than treating it yourself.

Infection in scratched skin
Scratching or scraping the scale off breaks the skin, and bacteria can settle in the damage. The signs are golden-yellow crust, weeping, a hot sore area, or swollen glands in the neck. It is uncommon, and it clears with antibiotics, but it needs to be seen rather than treated with more shampoo.

When to get help

When to get help

Seek care for persistent symptoms; eye pain, vision change or fever with marked swelling needs urgent assessment.

Seek care when the diagnosis is uncertain, the rash is extensive or painful, or routine care does not control it.

Common questions

Eyelid Dermatitis:What is Eyelid Dermatitis?

Eczema of the thin eyelid skin, often related to irritation or contact allergy.

Eyelid Dermatitis:What can I do day to day?

Pause suspect cosmetics and keep products simple. Do not put steroid creams near the eyes without advice.

Eyelid Dermatitis:When should I get medical advice?

Seek care for persistent symptoms; eye pain, vision change or fever with marked swelling needs urgent assessment.

Seborrheic Dermatitis:Is dandruff the same thing as seborrheic dermatitis?

The same process at different intensities. Dandruff is the mild end - flaking and itch with little visible inflammation. Seborrheic dermatitis is the fuller version, with inflamed, discolored skin and greasy scale, and it can involve the face, ears and chest too. The same treatments work for both, and many people move between them over the years.

Seborrheic Dermatitis:Will it ever go away for good?

The infant version clears on its own, almost always within the first year. The adult version is long term. It is very treatable, and most people keep it more or less invisible with a once or twice weekly routine, but controlled is not cured. It fluctuates with season, stress and general health, so quiet spells are normal and not proof it has gone.

Seborrheic Dermatitis:Does washing my hair more often help or make it worse?

For most people it helps, because washing removes the oil and scale the yeast uses. That does not suit every hair type, and frequent washing of textured or treated hair can do real damage. If two or three times a week is not realistic, ask for a leave-on antifungal foam, lotion or cream, or apply the shampoo to the scalp in sections without lathering the length. The plan should fit your hair.

Seborrheic Dermatitis:Is the yeast an infection? Should I be worried about spreading it?

No, on both counts. Malassezia lives on the skin of essentially every adult as a normal resident. Seborrheic dermatitis is your immune system reacting to that normal resident, not an infection you caught, and nobody can catch it from you.

Seborrheic Dermatitis:Can it cause hair loss?

It does not destroy hair follicles or cause permanent hair loss. Severe inflammation and persistent scratching can cause temporary shedding, which recovers once the scalp settles. Hair lost in a defined pattern, or a scarring scalp with smooth bald patches, is a different problem and worth having looked at.

Seborrheic Dermatitis:Why does my face flake right where I use my skincare?

Because the creases beside the nose and the eyebrows are where seborrheic dermatitis lives, and it is easy to read that as your products drying you out. More moisturizer will not shift it, and acids and scrubs make it worse. The test is simple - an antifungal cream a few times a week there usually improves it within two weeks.

Sources

Sources and further reading

  1. Eyelid contact dermatitis
  2. DermNet
Dermapedia on YouTube