Rosacea
Low doses reduce bumps.
Doxycycline: An oral antibiotic for moderate to severe inflamed acne. It is meant as a short bridge alongside topical treatment, not a long-term drug. Mirvaso: A gel that narrows facial blood vessels to fade redness for about half a day. It treats color only, it does nothing for bumps, and in some people the redness returns worse as it wears off.

Choose for a short 3–4 month bridge to calm moderate inflamed acne or rosacea while a retinoid and benzoyl peroxide start working.
Choose to fade rosacea redness for a day or an event — it treats color only, not bumps.
Can you take them together?
They treat different parts of rosacea: doxycycline for bumps, Mirvaso for redness. They do not interact.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

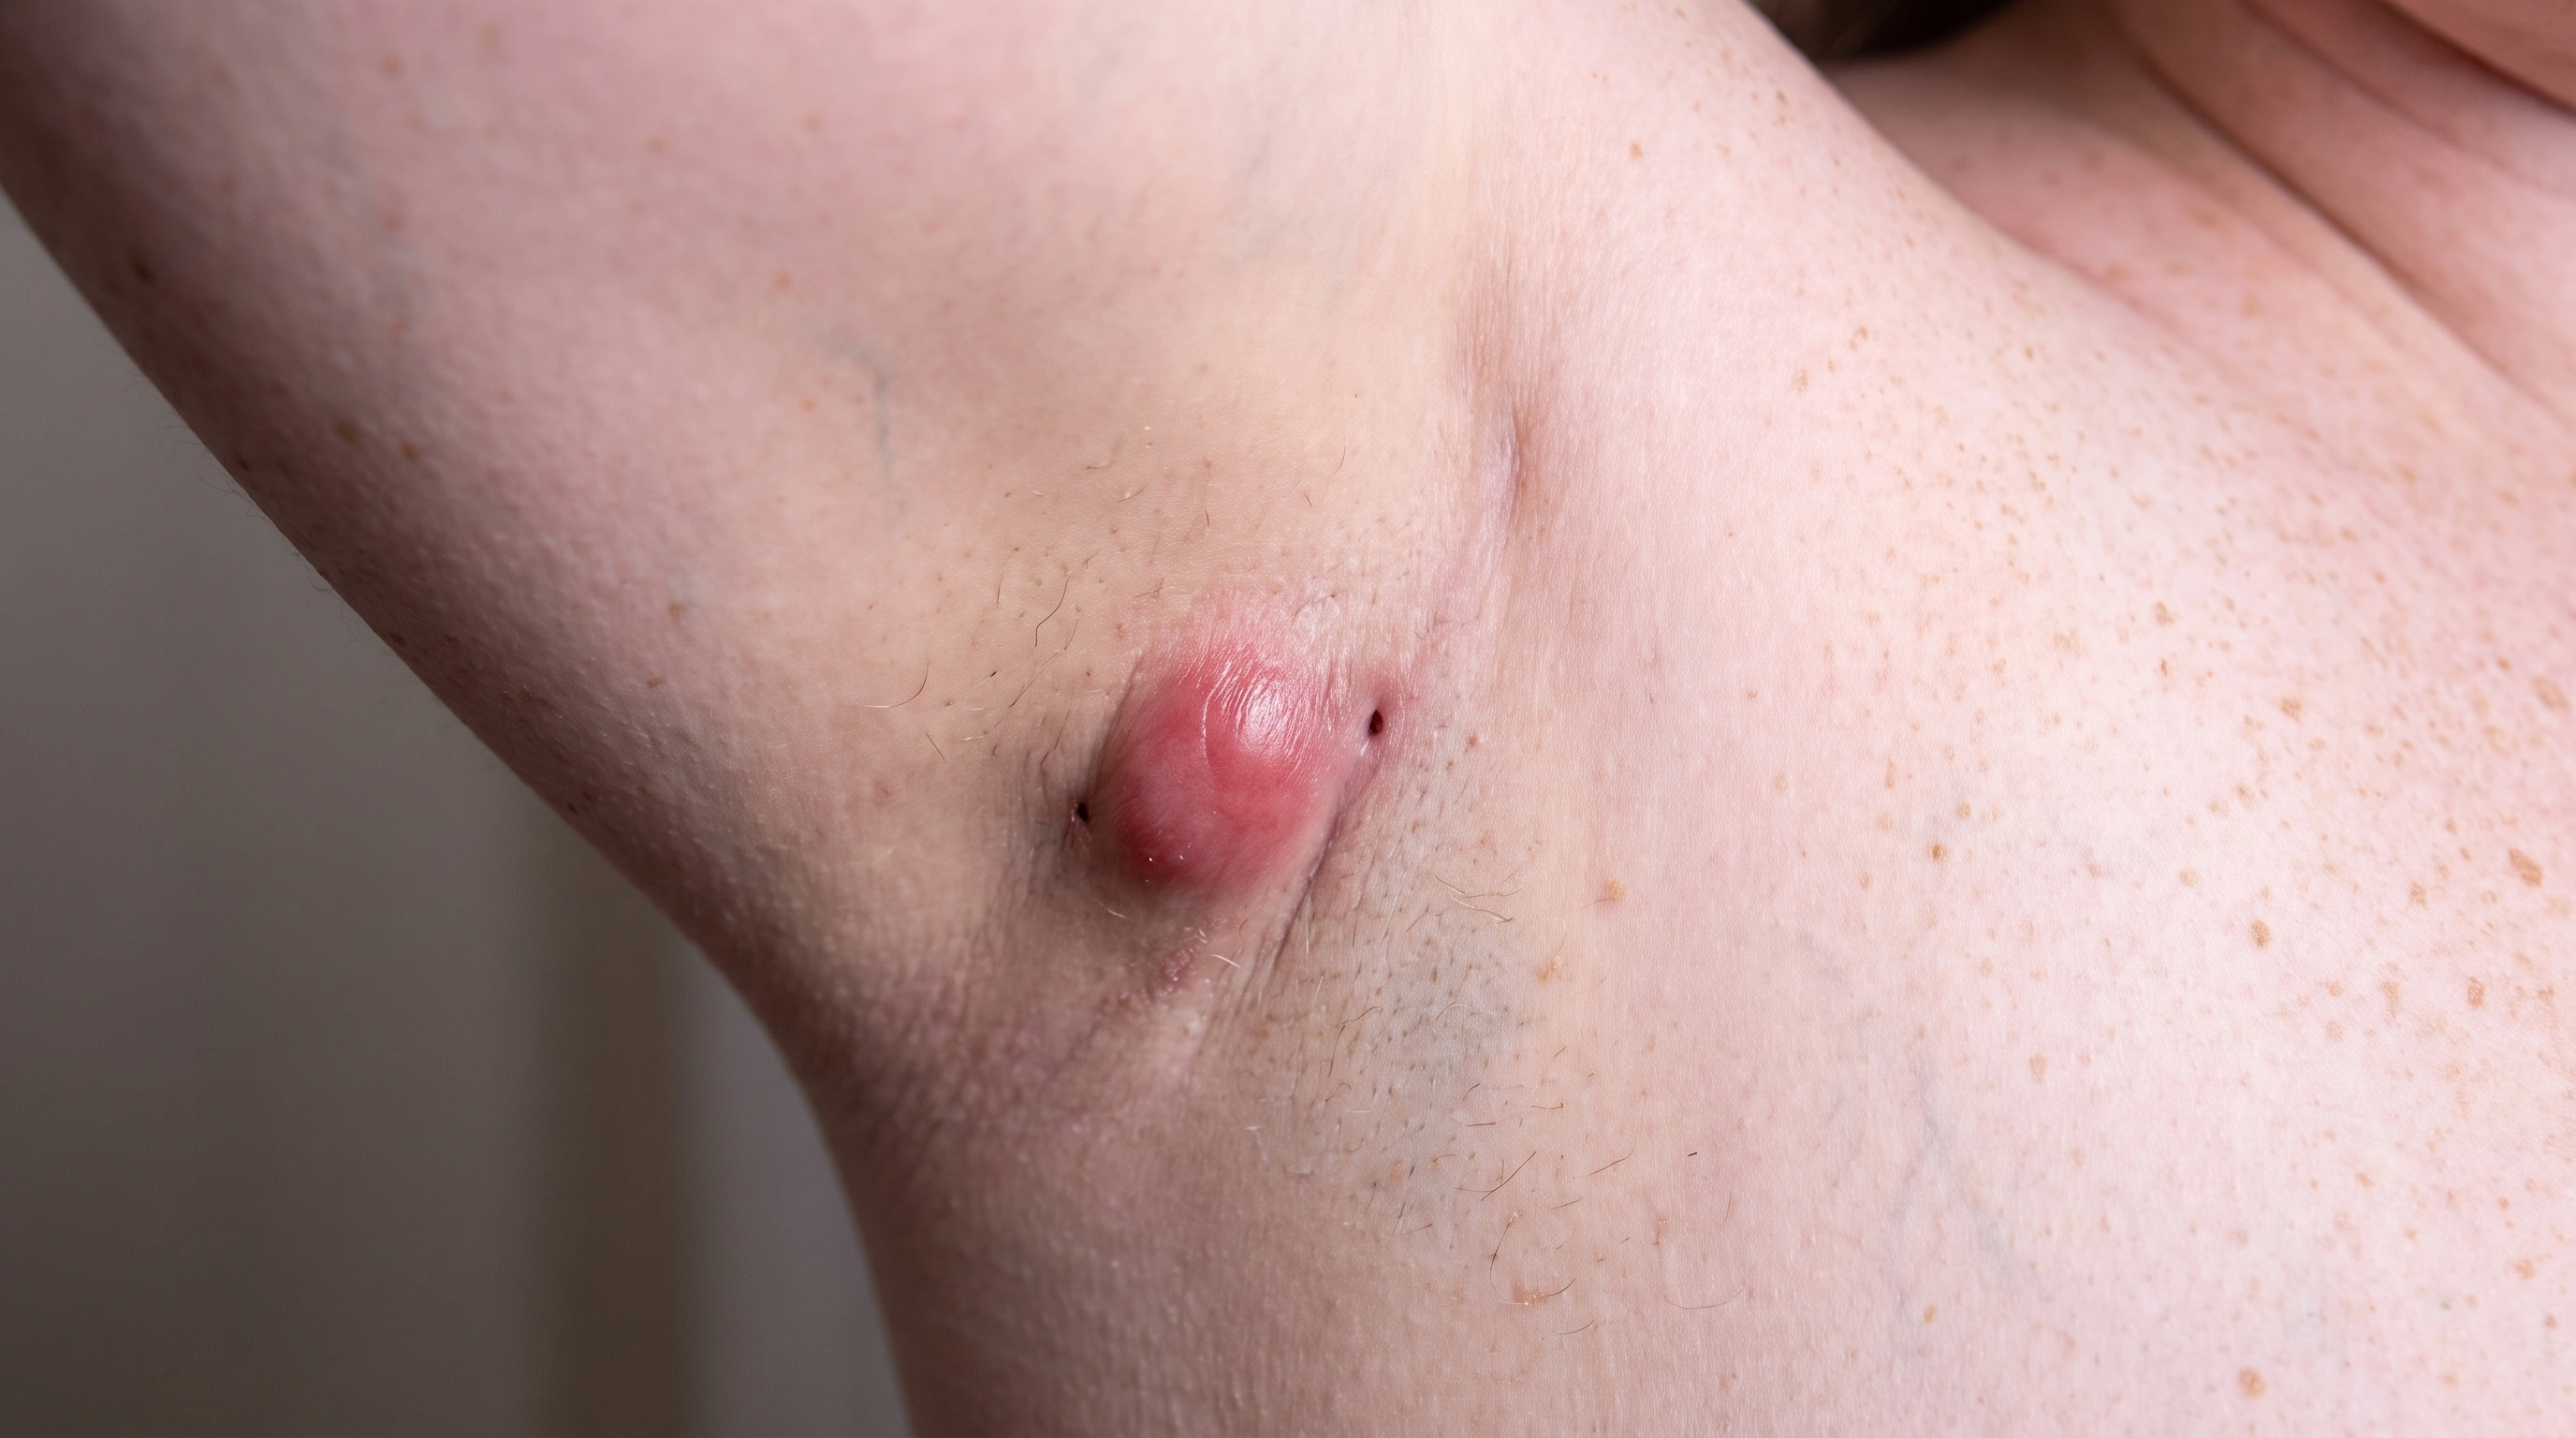

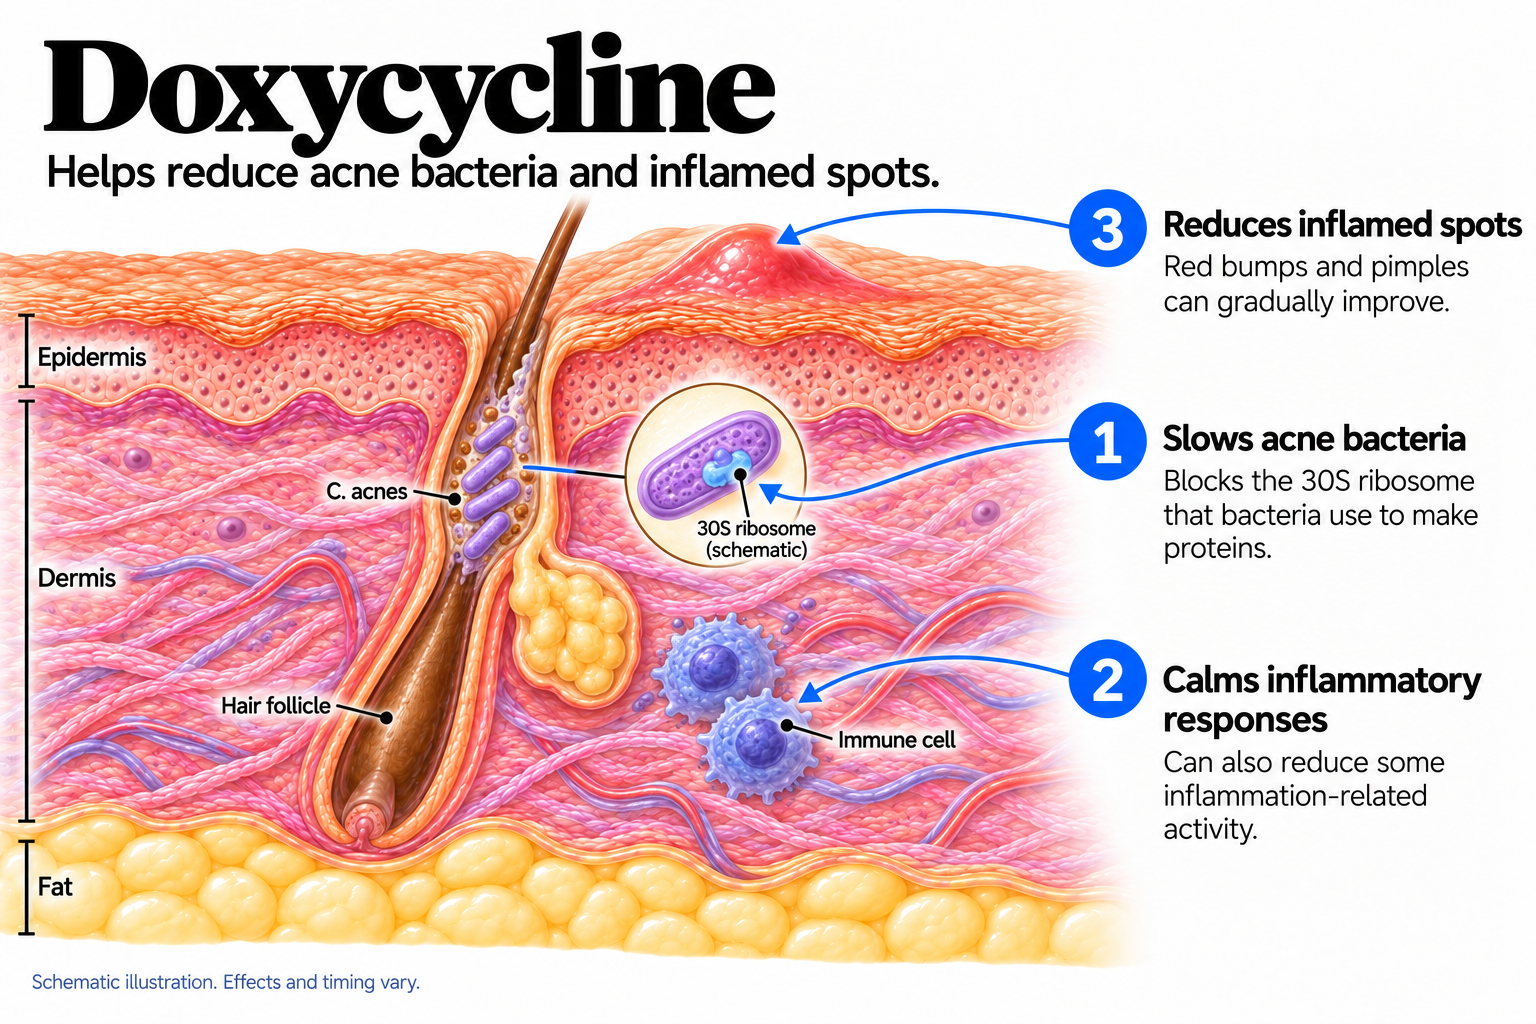
Slows acne bacteria: Blocks the 30S ribosome that bacteria use to make proteins. Calms inflammatory responses: Can also reduce some inflammation-related activity. Reduces inflamed spots: Red bumps and pimples can gradually improve.
Bacterial protein-synthesis inhibition is established. The complete acne mechanism and the contribution of individual antibacterial and anti-inflammatory effects are not fully defined. This does not imply direct exfoliation, oil-gland shrinkage, or treatment of resistant bacteria.
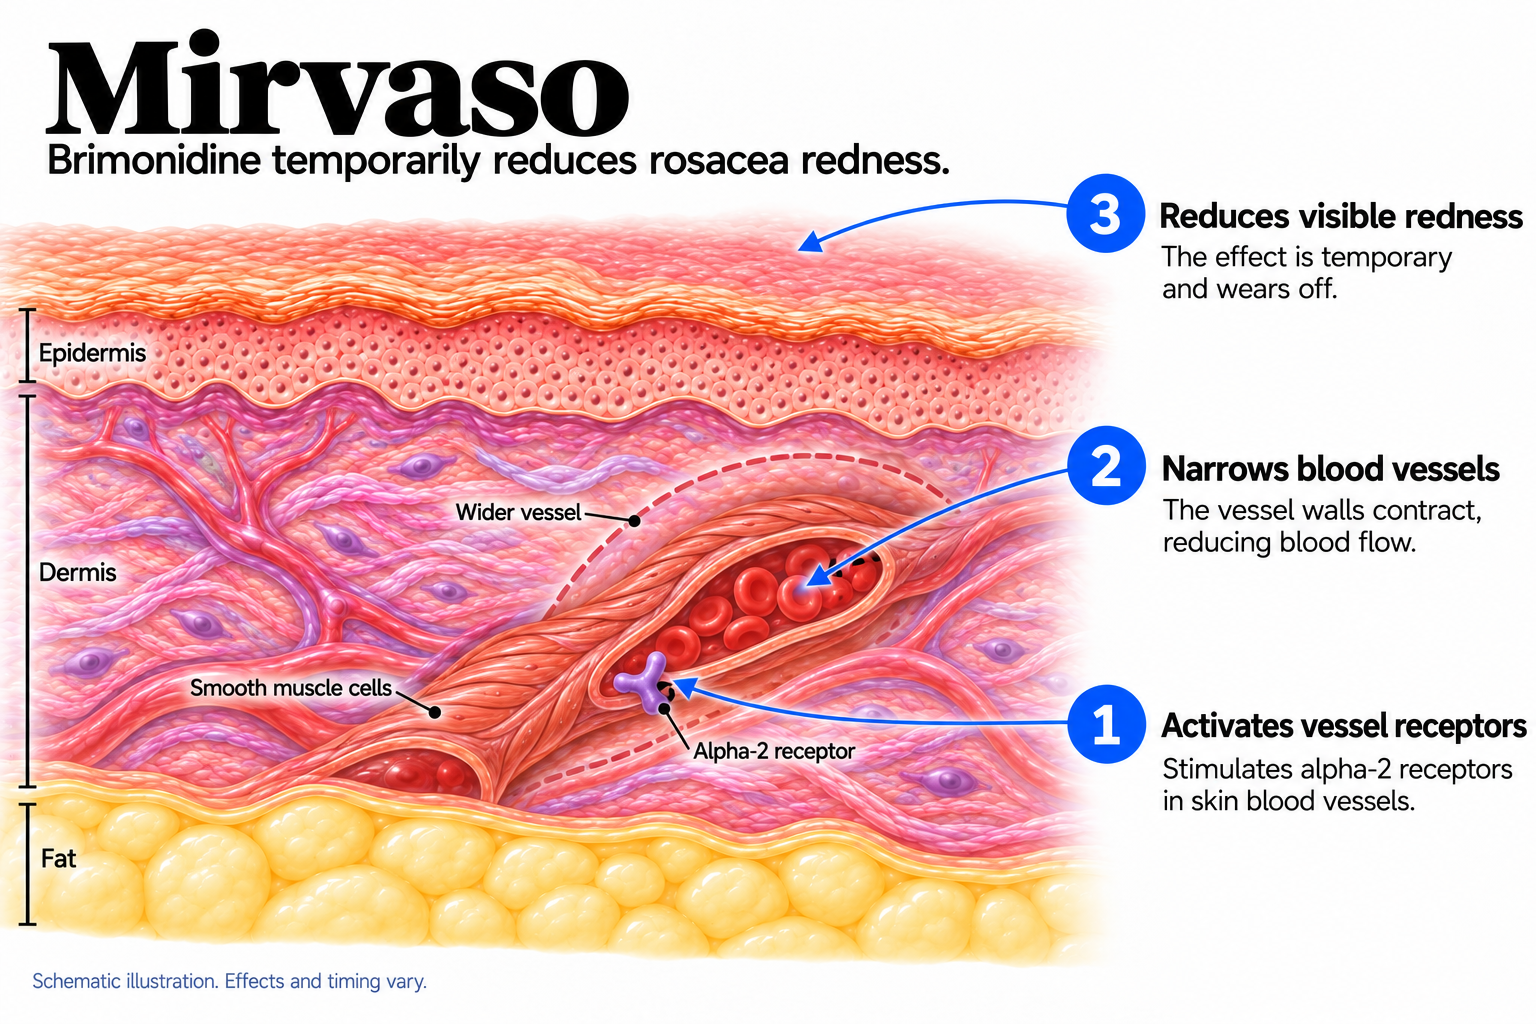
Activates vessel receptors: Stimulates alpha-2 receptors in skin blood vessels. Narrows blood vessels: The vessel walls contract, reducing blood flow. Reduces visible redness: The effect is temporary and wears off.
Brimonidine is a relatively selective alpha-2 agonist. This explains temporary vasoconstriction, not permanent removal of blood vessels or cure of rosacea.
Dose depends on what your stomach tolerates, not body weight. Kidney or liver problems can lower it.
Starting dose: 50 mg to 100 mg once or twice a day. Some doctors start low to see how your stomach does.
Going up: Raised after a week or two if you tolerate it and the acne has not budged.
Usual dose: Around 100 mg once or twice daily. Low-dose anti-inflammatory regimens use much less.
Total course: Three to four months. Reassess at three months and stop once topical treatment can hold the result.
When to Apply: Once a day on clean dry skin, timed for when you most want the redness down. A pea-sized amount for the whole face, divided between forehead, nose, chin and cheeks and spread thinly. Makeup and sunscreen go on once it has dried.
How to Start: Test one small area, such as one cheek, for several days first. That is the cheapest way to find out whether you get rebound. Use less than a pea-sized amount, and never more than once a day.
If It Irritates: Burning, stinging or itching where you applied it is common early and often settles. If redness worsens, or comes back stronger as the gel wears off, stop and speak to your doctor. Rebound does not settle by pushing through it.
If It's Not Working: There is one strength, and more gel is not the answer. The next steps are oxymetazoline cream, which works on a different receptor, or laser and light treatment, which treats the vessels themselves.
With a full glass of water and with food. Stay upright for 30 minutes afterward, and never right before bed — a tablet stuck in the food pipe can burn the lining. Food cuts the nausea and does not block absorption.
Take it when you remember, unless the next dose is close. Never double up — you will just be nauseated.
No blood tests are needed for a standard acne course in a healthy person. Monitoring is clinical, with a review at about three months.
This is not a drug to stay on for years. What builds is antibiotic resistance — in your skin bacteria and in the rest of your body — along with effects on the gut. Keep oral courses for acne as short as possible, with a topical retinoid running alongside to take over.
No blood tests for ordinary use. What is monitored is what you can see: does the redness fade, does it come back worse, does burning settle.
A small amount is absorbed, so the gel carries the theoretical body-wide effects of its class — low blood pressure, a slow heart rate, drowsiness, dizziness. These are rare on intact skin, but they are why heart disease, low blood pressure, circulatory problems or an existing brimonidine eye drop should be raised before you start.
Review a few weeks in — is this worth continuing.
Approximate windows, not promises.
Weeks 1 to 2Little change. Any stomach upset shows up now.
Weeks 2 to 6Fewer, less painful inflamed spots. Blackheads do not change.
After 12 weeksIf inflamed acne is no better, continuing will not help. Reassess rather than extend.
First 30 minutesStarting: Redness begins to fade. Some tingling or warmth is normal.
3 to 6 hoursPeak: The face is at its least red. The fixed pink of cheeks, nose and forehead visibly lightens.
9 to 12 hoursWearing off: Color returns, in most people to where it started.
Days 1 to 14Watching for rebound: In a minority, redness comes back worse than it started, sometimes with burning. It can appear on day one or after a week or two.
OngoingNo build-up: It does not accumulate. Day ninety works like day one.
Sorted by what to do about them.
Generic doxycycline is cheap, though prices have swung at times. Branded high-dose and modified-release versions cost far more and rarely work better. Monohydrate and hyclate are both generic — if one upsets your stomach, try the other.
Brand priced for most of its life, and often not covered, because insurers treat facial redness as cosmetic. Generic brimonidine gel has appeared in some markets, bringing the price down unevenly.
A tube lasts a long time if you stick to the pea-sized rule.
If cost is the barrier, the honest question is whether a treatment lasting twelve hours that does not change the disease is where the budget should go, or whether laser or light treatment is the better buy.
Three to four months. A year on it means the plan needs revisiting, not refilling.
Occasional drinking is fine. Heavy drinking can lower drug levels.
No. There is no meaningful interaction with combined oral contraceptives. Rifampin is the one that interferes.
It makes skin much more reactive to ultraviolet light, and reverses after you stop.
No. That combination raises the risk of pressure around the brain.
Redness that comes back worse than it started, as the gel wears off or after several days of use, sometimes with burning. A minority of users, but the main reason people stop. It settles within a couple of weeks of stopping.
Use less than you think — a pea-sized amount for the whole face, once a day at most — and test one small area for several days first. Over-application is the pattern most linked to trouble.
No. It is a blood vessel treatment. Bumps and pustules need a separate medicine, and the two are often prescribed together.
It begins around thirty minutes, peaks at three to six hours, and is gone by twelve. It does not accumulate, so daily use is not needed if you want it for occasions.
Yes, once it has dried.
Not really. Those are visible individual vessels; they need laser or light. Brimonidine pales the background around them, which can make them look less obvious.