Acne
Clears severe and stubborn acne.
Accutane: A high-dose oral vitamin A drug for severe or scarring acne. It is the only acne treatment that can produce lasting remission after a fixed course. MetroGel: A long-standing prescription gel or cream for the bumps and pustules of rosacea. It calms inflammation rather than treating an infection.
Choose for severe, scarring or stubborn acne that keeps coming back after other treatments. It is the only acne medicine that can give lasting remission after one course.
Choose for rosacea bumps and pustules as a gentle, inexpensive long-standing cream.
Can you take them together?
MetroGel is gentle and can be used for rosacea during an Accutane course if your dermatologist recommends it. Keep the rest of the routine bland and moisturizing.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.


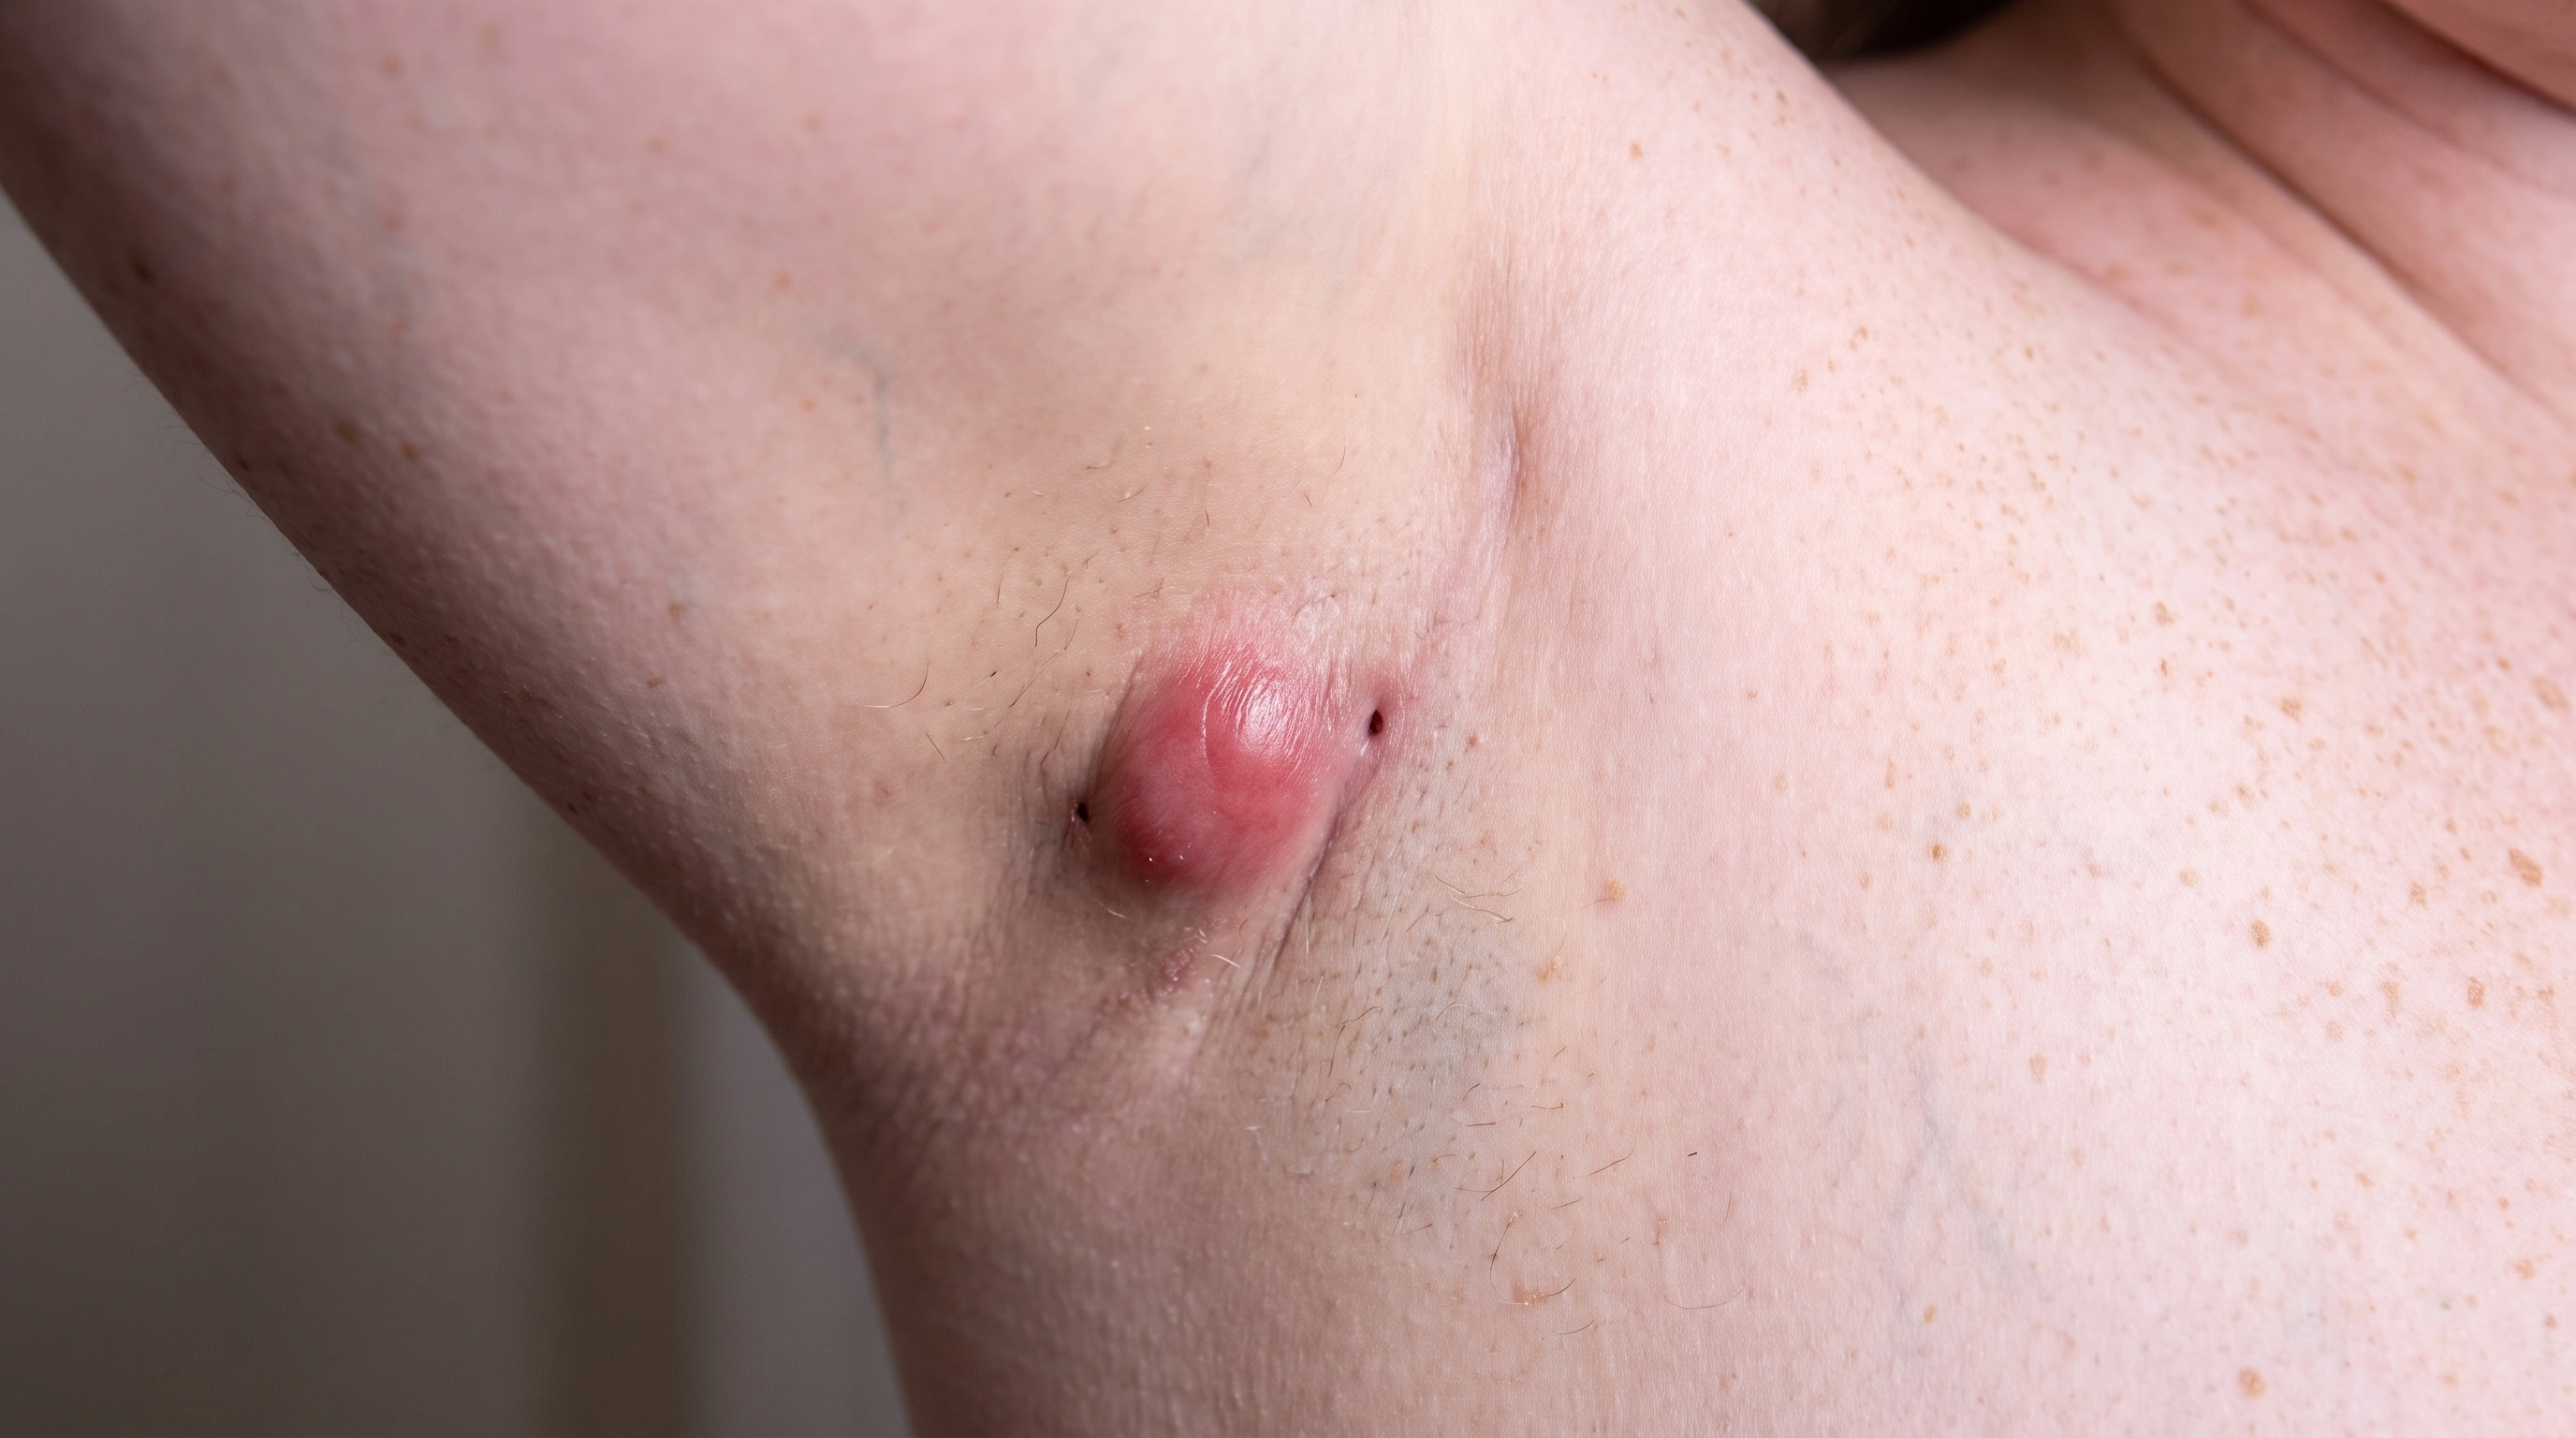
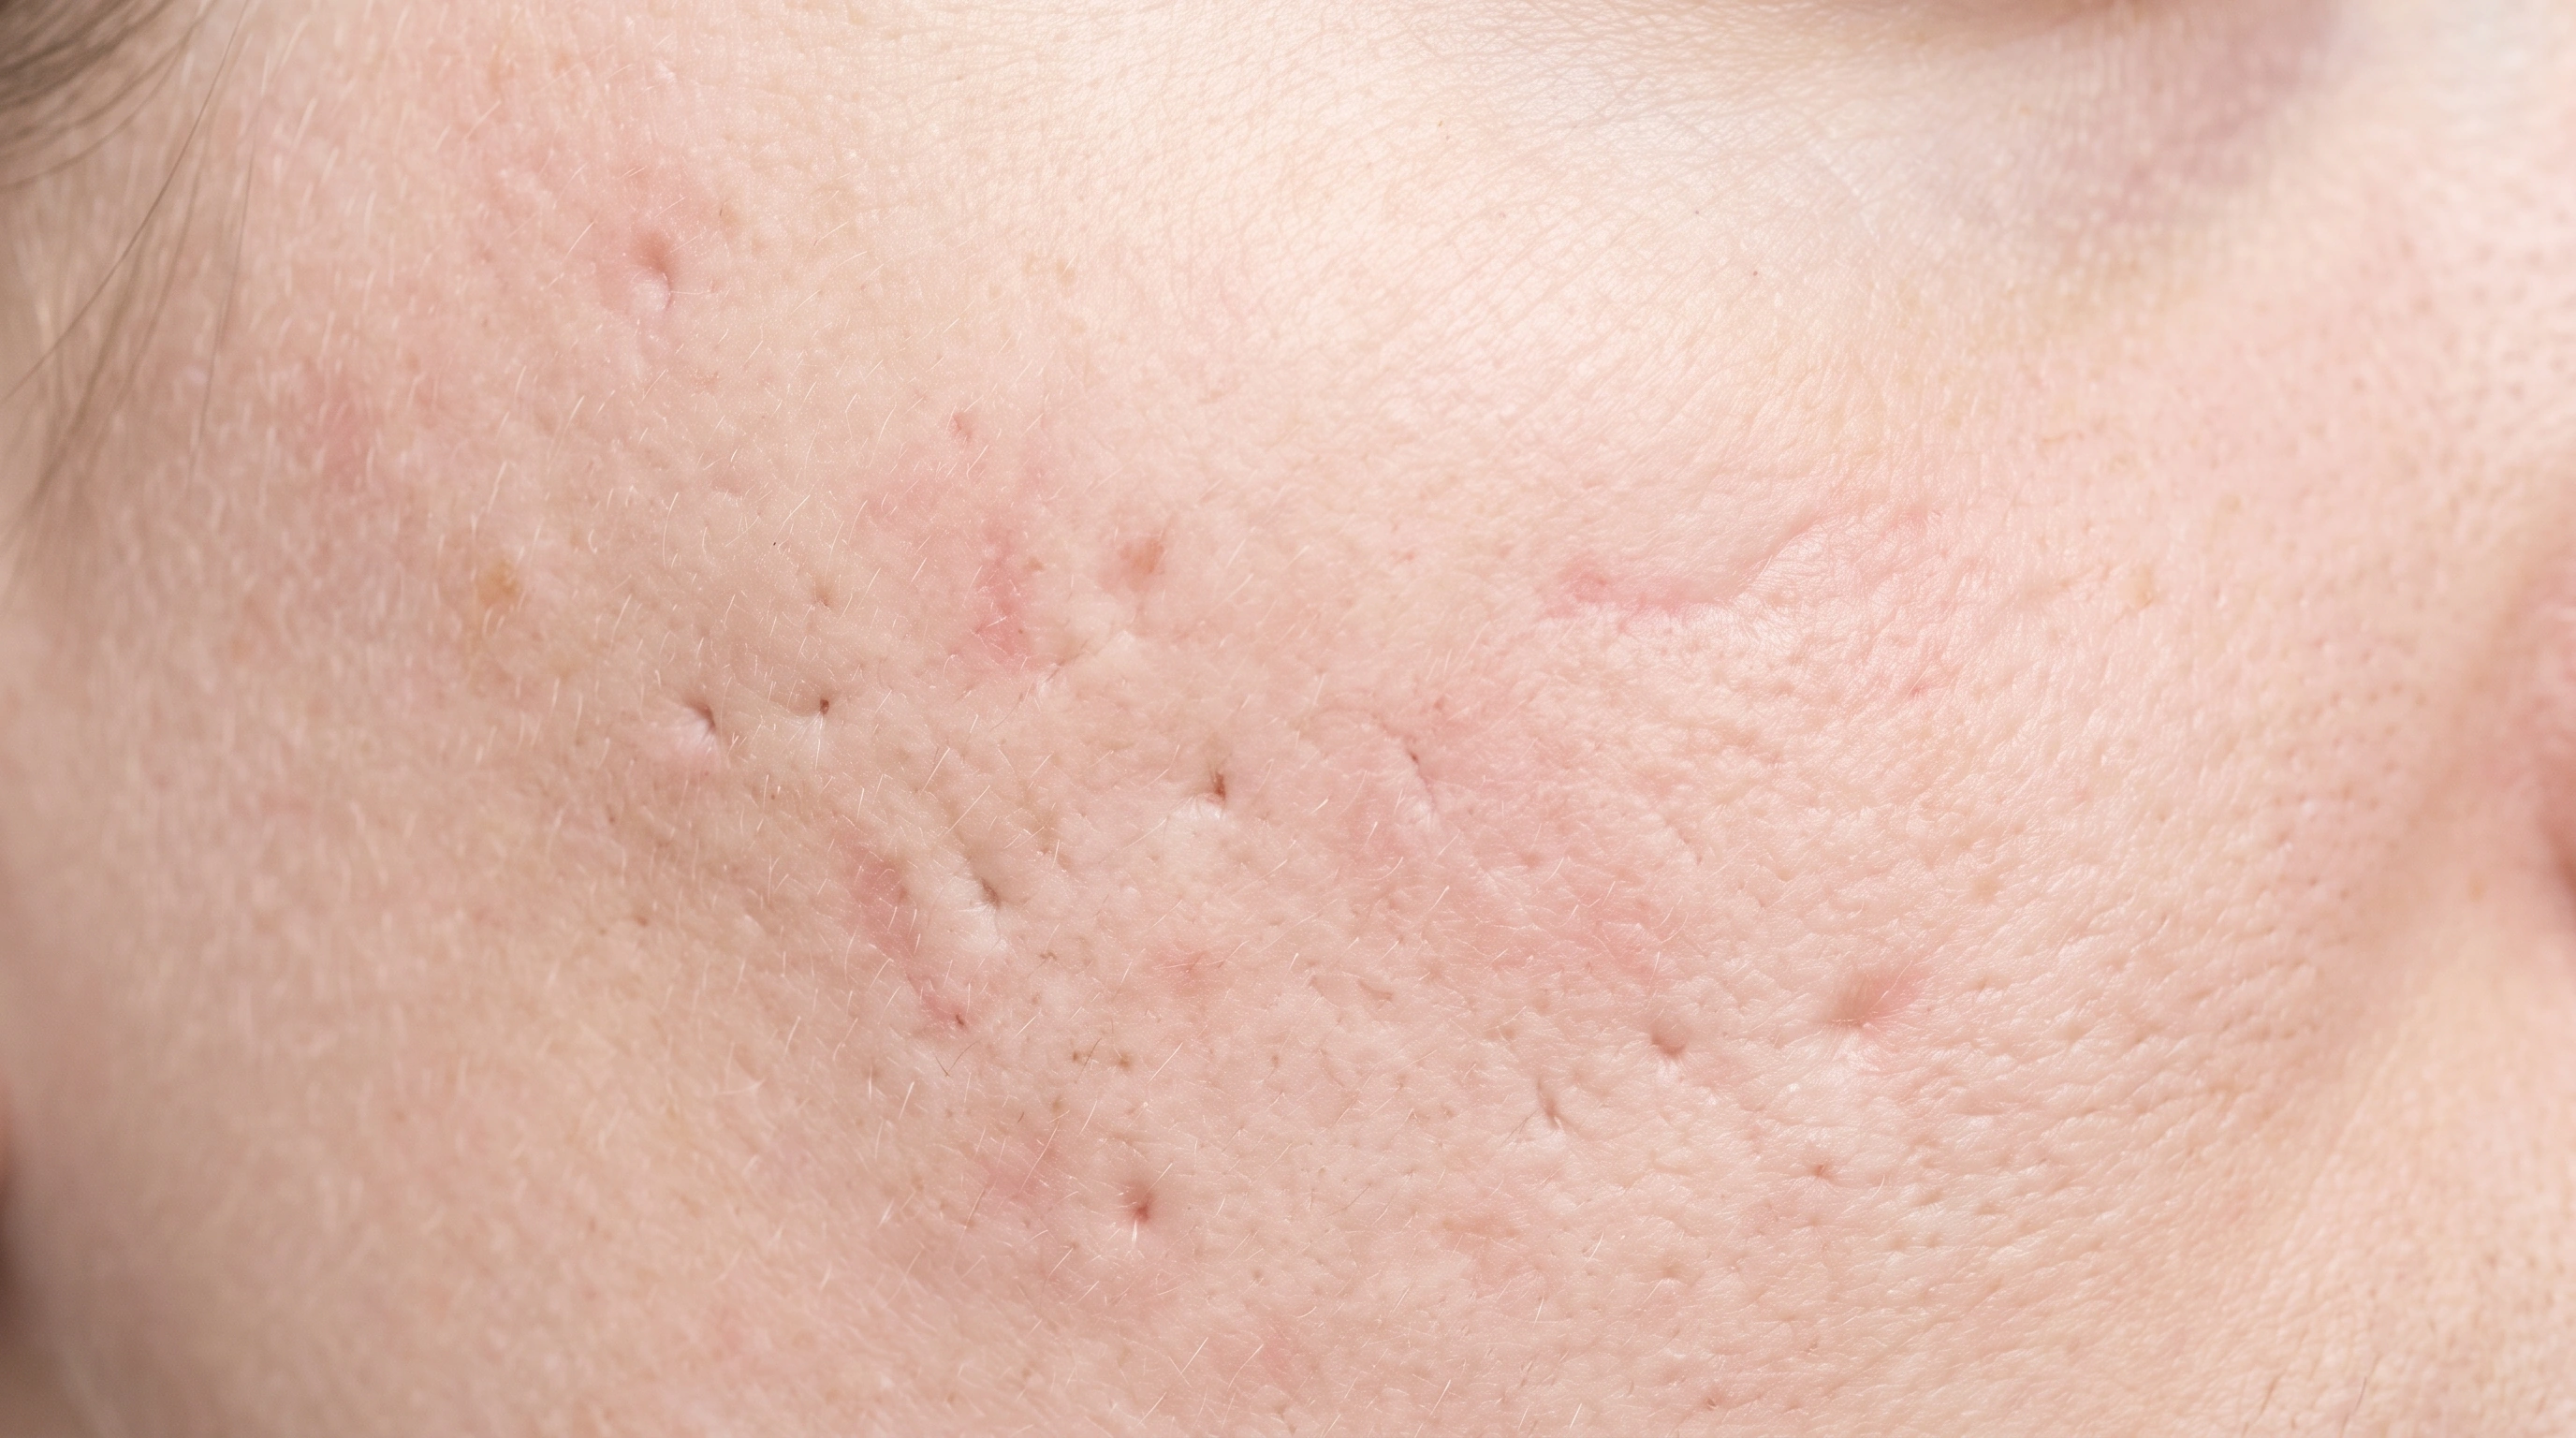


Reduces pore clogging: Helps normalize cell buildup inside follicles. Reduces acne bacteria: Less oil makes follicles less favorable for C. acnes. Makes less oil: Shrinks oil glands and reduces their oil output. Calms inflammation: Dampens immune responses involved in acne.
Oral isotretinoin mechanism overview. Reduced C. acnes is an indirect effect of a changed follicular environment, not antibiotic action. The complete mechanism is not known. Gland outline is conceptual, not a measured size reduction or permanent cure.

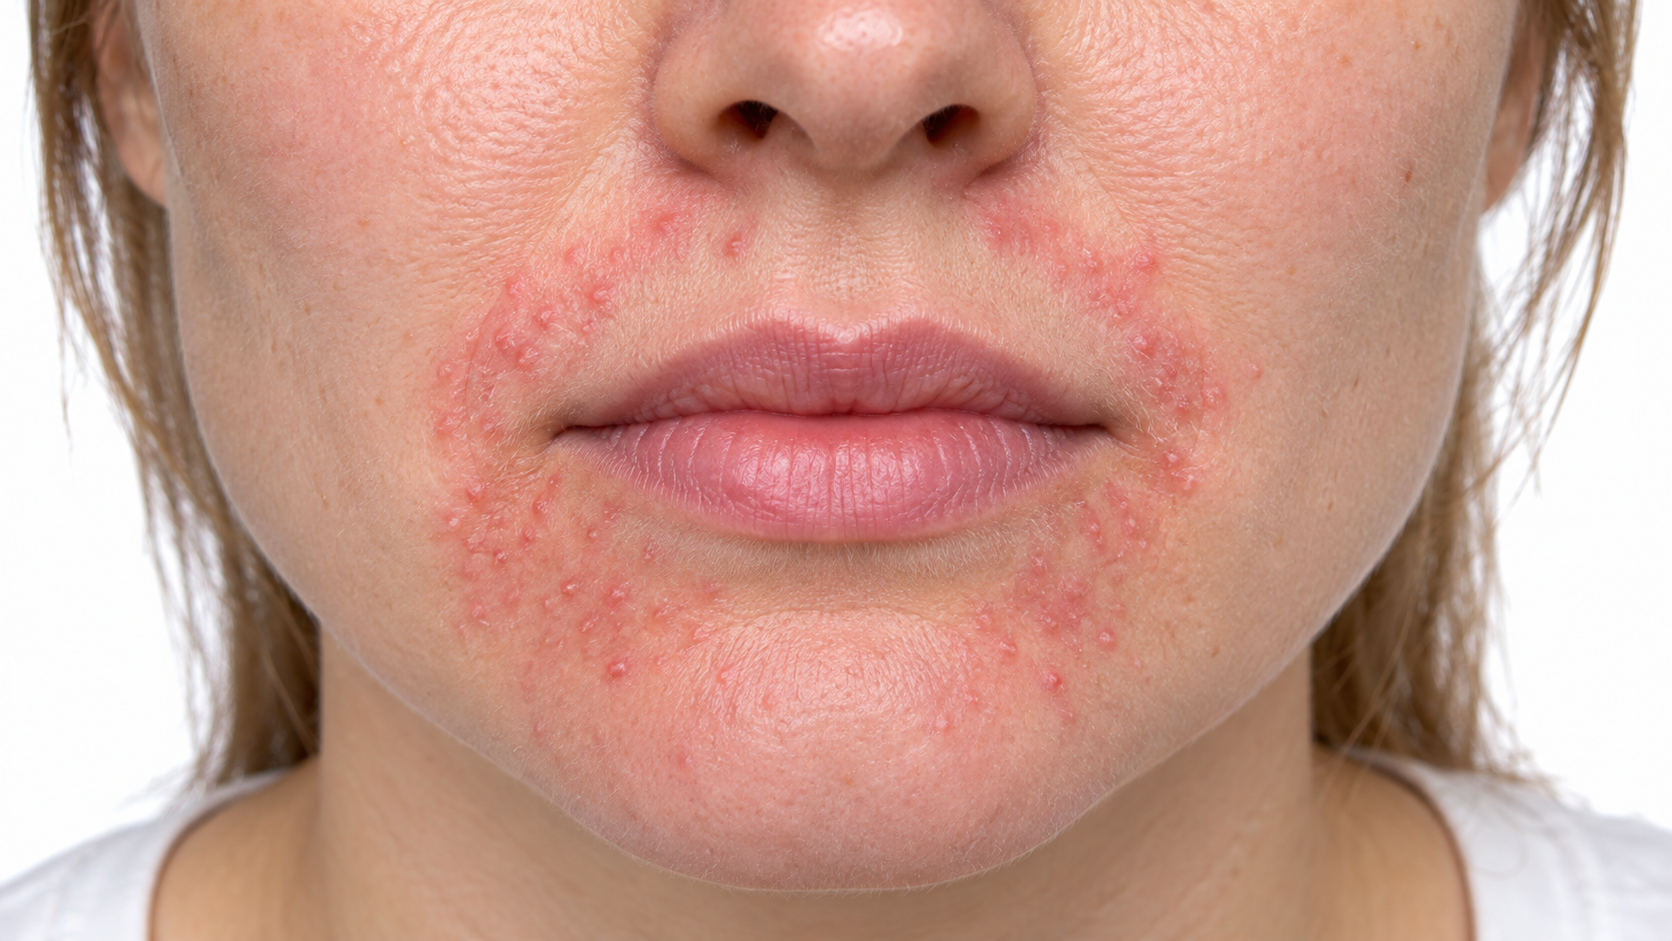
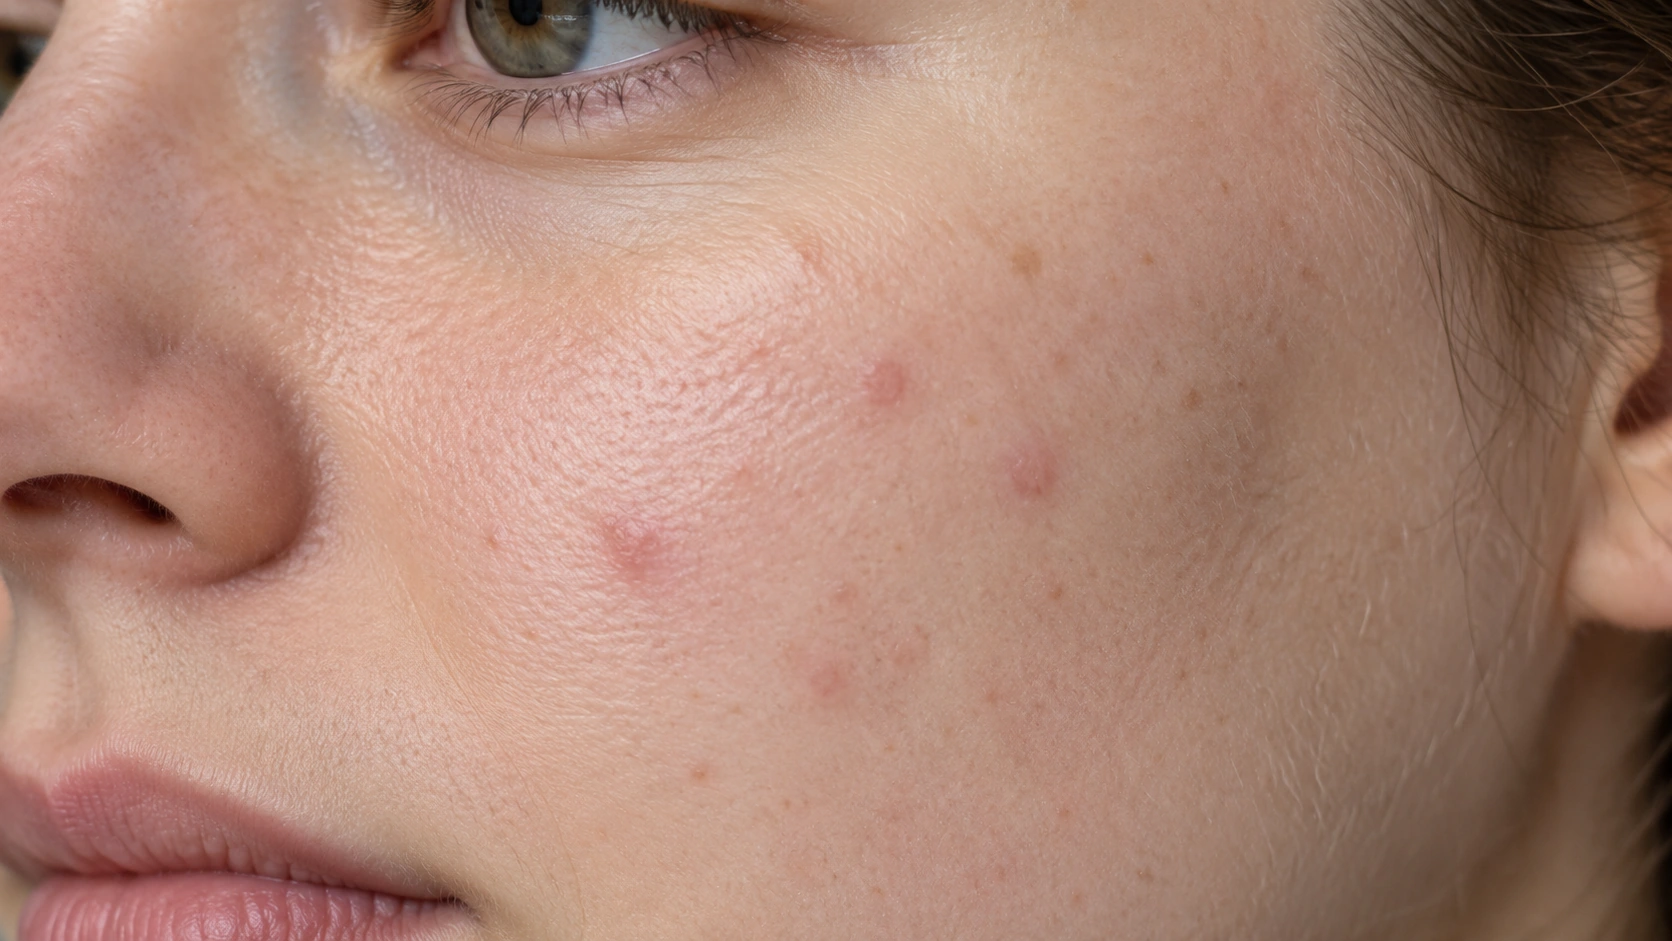
May reduce inflammatory oxidants: Can limit reactive oxygen released by immune cells. Helps calm inflammation: Reduces the inflammatory activity around skin lesions. Reduces bumps and pimples: Rosacea spots gradually become less active.
The rosacea mechanism is not fully established. Reactive-oxygen effects derive from experimental systems and are presented as a proposed explanation; this does not imply killing Demodex or treating all redness.
Dose is set by body weight, and the total across the whole course matters more than any single day.
Starting dose: Often about 0.5 mg/kg a day, sometimes lower to ease into the side effects. Not the target.
Going up: Usually raised after the first month or two if blood tests and side effects allow, commonly to about 1 mg/kg a day.
Usual dose: About 0.5 to 1 mg/kg daily for most of the course.
Total course: Judged by cumulative dose, usually about 120 to 150 mg/kg of body weight. Reaching that total is what cuts relapse. Most people need five to eight months.
When to Apply: A thin layer over the whole affected area, not dabbed on individual spots. Twice a day for 0.75%, once a day for 1%. Apply to clean dry skin and let it settle before moisturizer or sunscreen.
How to Start: Straight in at full frequency — this is one of the gentler prescription topicals. If your skin is very reactive, use it once daily for a week first.
If It Irritates: Mild stinging or dryness in the first week is usually the base, not the drug. Moisturizer underneath settles it, and switching from gel to cream helps most people.
If It’s Not Working: Give it eight to twelve weeks. If bumps keep coming, the next step is usually azelaic acid or ivermectin, or a low-dose oral treatment. If redness or visible vessels are the problem, this drug was never going to fix them.
With a fatty meal, unless you have the formulation made to work without food. Absorption of standard capsules roughly doubles with fat, so an empty stomach lowers your dose. Splitting the daily amount into two doses with meals is common.
Take it with your next meal if it is the same day, otherwise skip it. Do not double up. The total over months is what counts, and the missed dose moves to the end of the course.
Liver enzymes and triglycerides are checked before you start and again during the course, usually in the early months and after a dose increase. Cholesterol and triglycerides commonly rise, then settle afterwards.
Anyone who can become pregnant is enrolled in iPLEDGE, a federal safety program requiring two forms of contraception or documented abstinence, a pregnancy test before starting, monthly tests during, and pickup inside set time windows. Miss a window and that month starts again.
Nobody stays on this drug. The course ends, and the effect on the oil gland lasts, so most people need nothing more than a topical retinoid. A smaller group needs a second course.
No blood tests and no routine monitoring. Almost none of the drug reaches the bloodstream from the skin, so the cautions on metronidazole tablets do not transfer.
Monitoring means a review at eight to twelve weeks to decide whether it is doing enough, then occasional check-ins if you stay on it for years. Long-term use is normal here.
Watch for rosacea in the eyes. A facial gel does not treat it, so mention gritty, burning or persistently dry eyes rather than reaching for drops off the shelf.
Approximate windows, not promises.
Weeks 1 to 4Dry lips first, almost always. Skin dries. Acne may flare.
Weeks 4 to 12Steady clearing. Dryness peaks and stays.
Months 4 to 6Most people are clear or nearly clear.
After the courseSkin keeps improving for a few months, and dryness clears within weeks to a couple of months.
First few minutesApplying it: A thin layer over the whole affected area, not spot-treating.
Weeks 1 to 3Adjusting: Little visible change. Stinging or dryness, if it happens, shows up and settles here, faster with a moisturizer alongside.
Weeks 3 to 6Working: Fewer new bumps and pustules, and the existing ones look less angry.
Weeks 8 to 12Judge it here: Where the trials measured their main result. Most people see a clear drop in inflamed bumps, and some background redness lifts with them.
Beyond 12 weeksHolding: Continued use holds the result. Stopping is the usual reason rosacea comes back.
Sorted by what to do about them.
Generic isotretinoin is moderately priced; the formulations that absorb without food cost much more. The real obstacle is not cost but iPLEDGE, with monthly appointments and pickup windows to plan travel and work around.
Generic metronidazole gel, cream and lotion are widely available and among the cheaper rosacea prescriptions. Coverage is generally good, and this is often what plans want tried first.
Branded versions and the once-daily 1% products cost more. Since the higher strength has not been shown to clear rosacea better, you are paying for convenience.
If the quoted price seems high, ask about the other forms and strengths — the gap can be large for the same drug.
The label warns about mood changes and some people report them. Large studies have not shown that isotretinoin causes depression, and severe acne itself is strongly linked to low mood. Mood is asked about at every visit, and any change should be reported.
The concern came from case reports, and larger studies have not shown a clear causal link. Severe abdominal pain or bloody diarrhea still needs assessment.
iPLEDGE applies the same rules to everyone who can become pregnant. A program rule, not a judgement about you.
For most people, yes. About one in five needs a second, and stopping short of the cumulative target is the most avoidable reason.
Occasional drinking is usually fine. Heavy drinking adds to the liver and triglyceride effects already being monitored.
An early flare is common in the first few weeks, especially with more severe acne. It is managed, not a reason to stop.
Early change around three to four weeks. Judge it fairly at eight to twelve weeks.
It helps the redness that comes with inflamed bumps. Persistent background redness and visible vessels need different treatments, so be clear about which one bothers you.
The alcohol warning belongs to the tablets, not the gel, since so little is absorbed. Alcohol is a common rosacea trigger in its own right, which is a separate question.
Gel for oilier skin, cream for dry or easily irritated skin, lotion in between. Same drug, so pick on comfort.
Usually yes. It is often paired with azelaic acid, a redness-reducing gel, or low-dose oral treatment. Check the combination with your doctor.
Not forever, but longer than most people expect. Rosacea usually returns within weeks to months of stopping, so treatment often continues at a reduced frequency once the skin settles.