Acne
Clears severe and stubborn acne.
Accutane: A high-dose oral vitamin A drug for severe or scarring acne. It is the only acne treatment that can produce lasting remission after a fixed course. Birth Control Pills: Birth control pills containing estrogen and a progestin. Four are FDA-approved for acne, and they work by lowering the amount of active testosterone in the blood.

Choose for severe, scarring or stubborn acne that keeps coming back after other treatments. It is the only acne medicine that can give lasting remission after one course.
Choose for hormonal acne along the jaw and chin when you also want contraception and have no clot risk factors.
Can you take them together?
Effective contraception is required for anyone who could become pregnant while taking Accutane, because isotretinoin causes severe birth defects. The pill is one of the most common choices, usually with a second method.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.


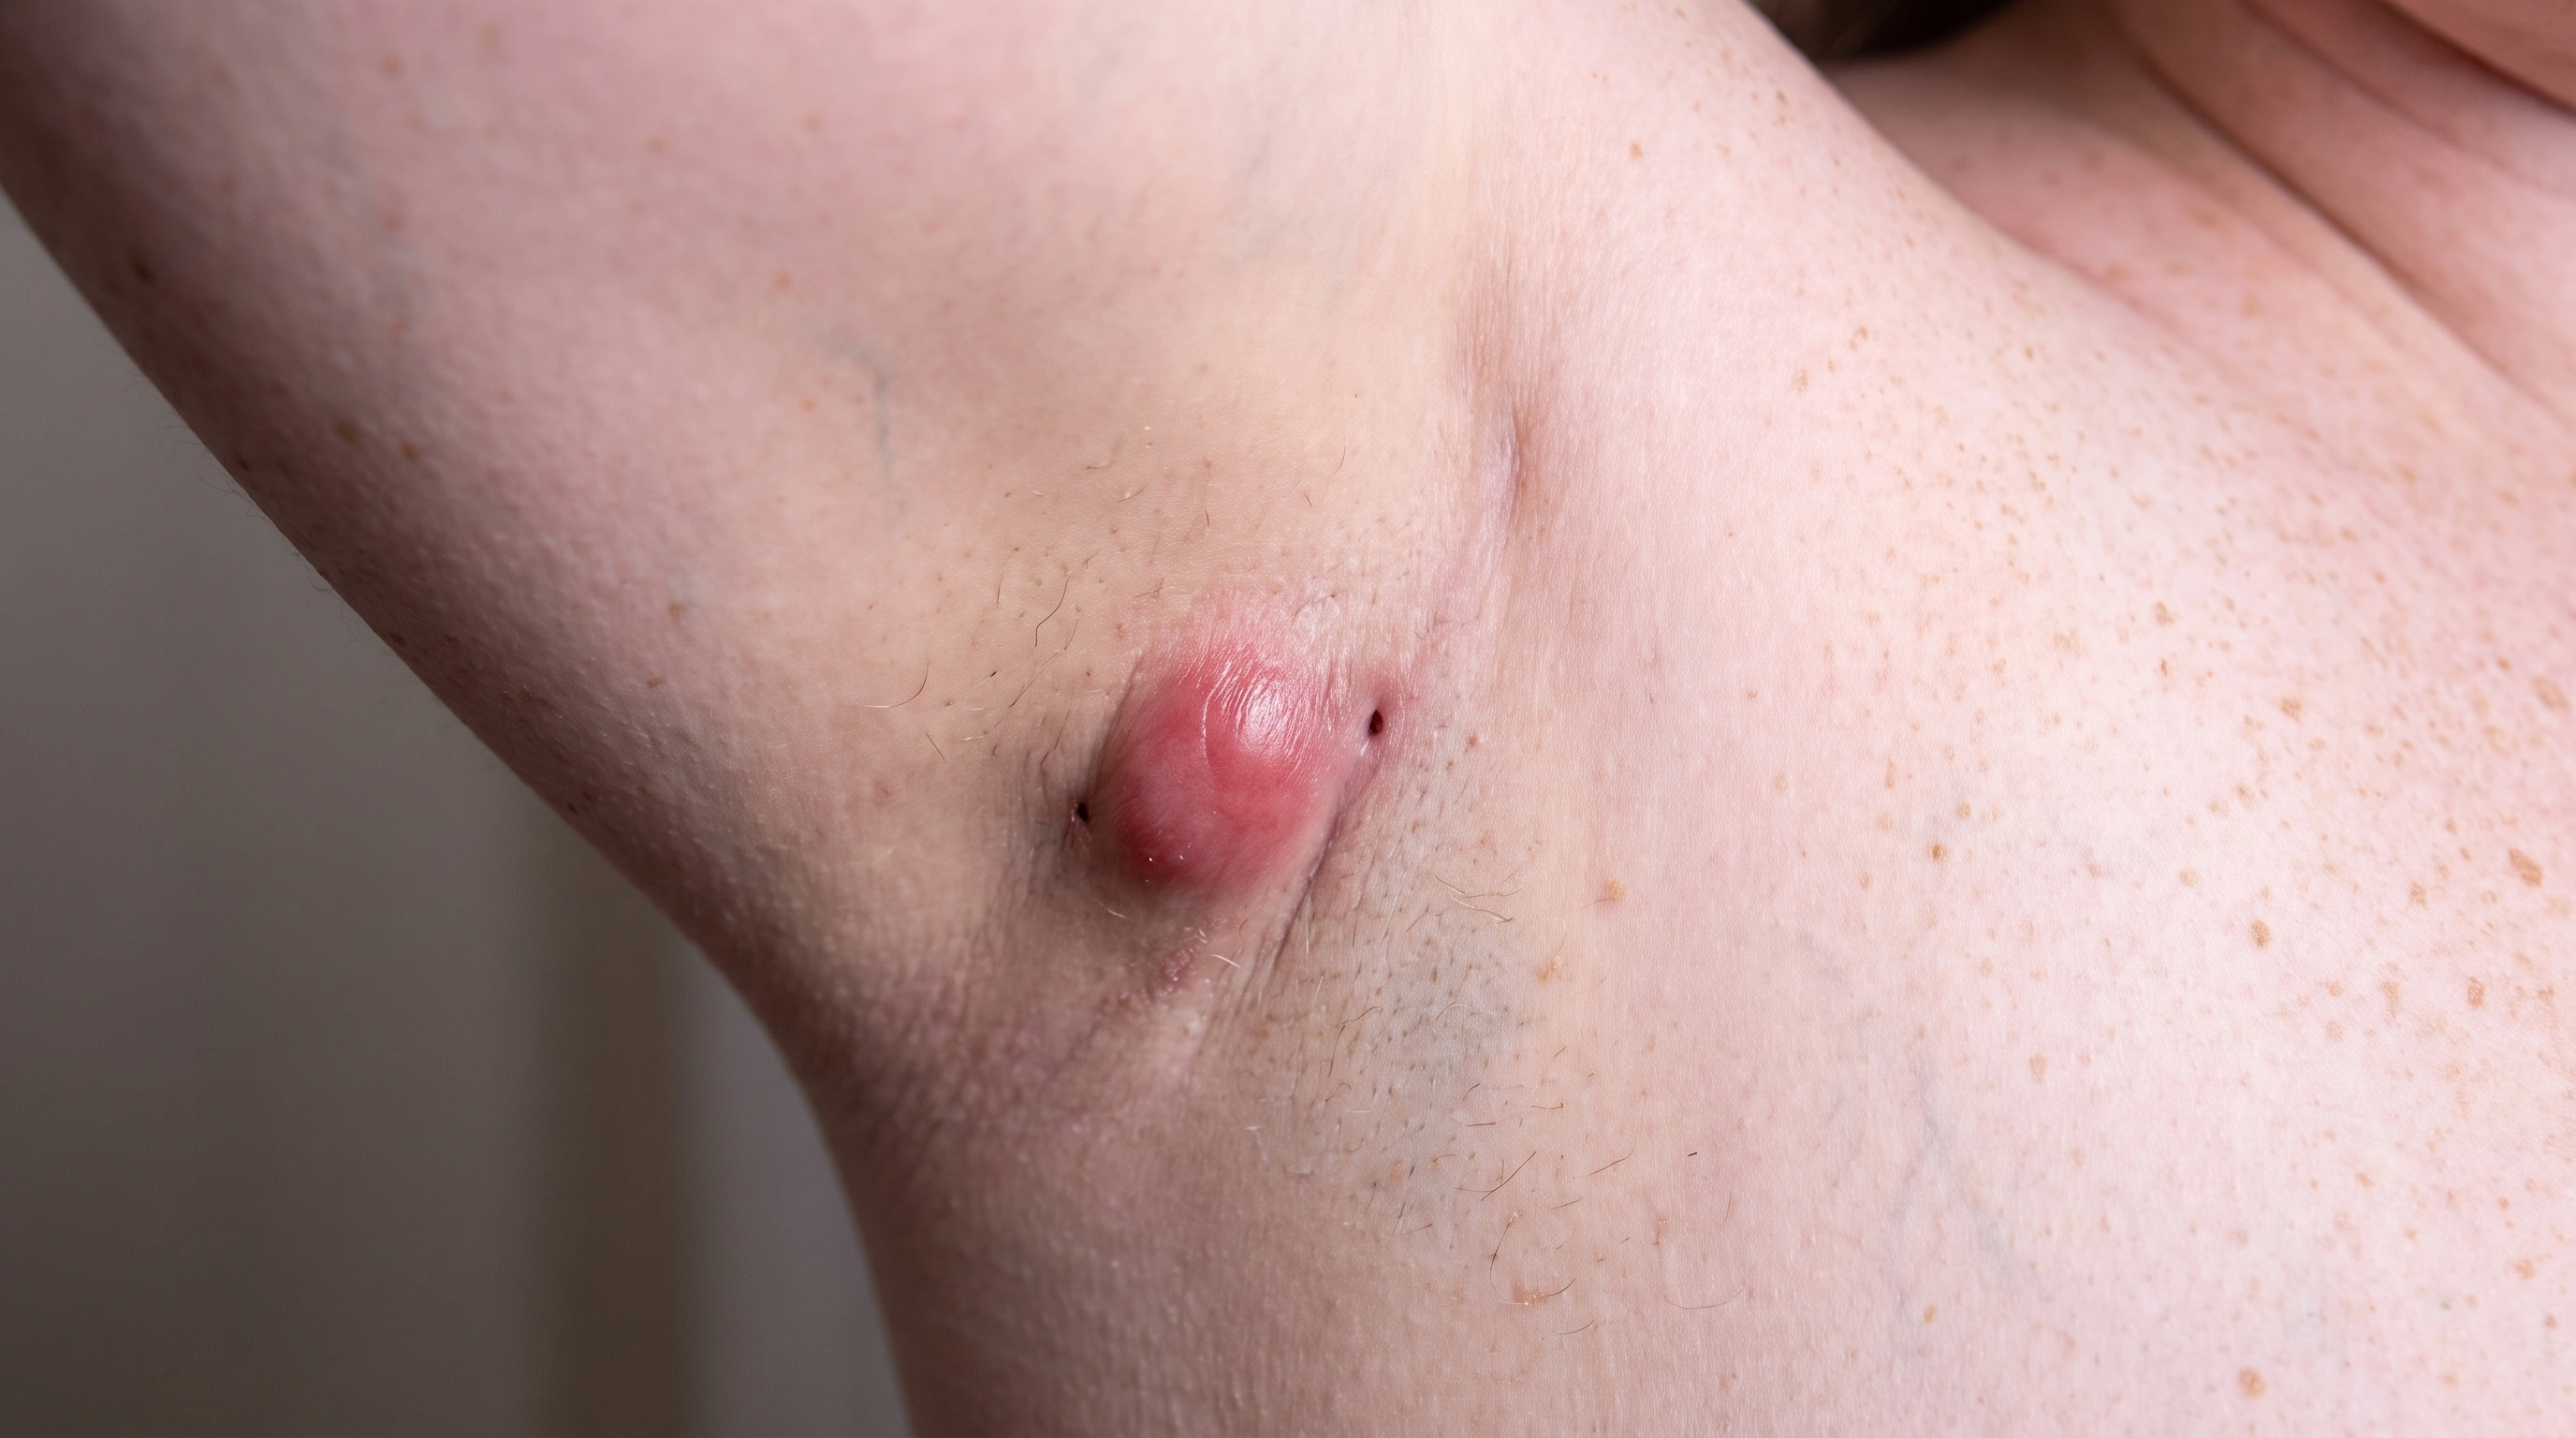
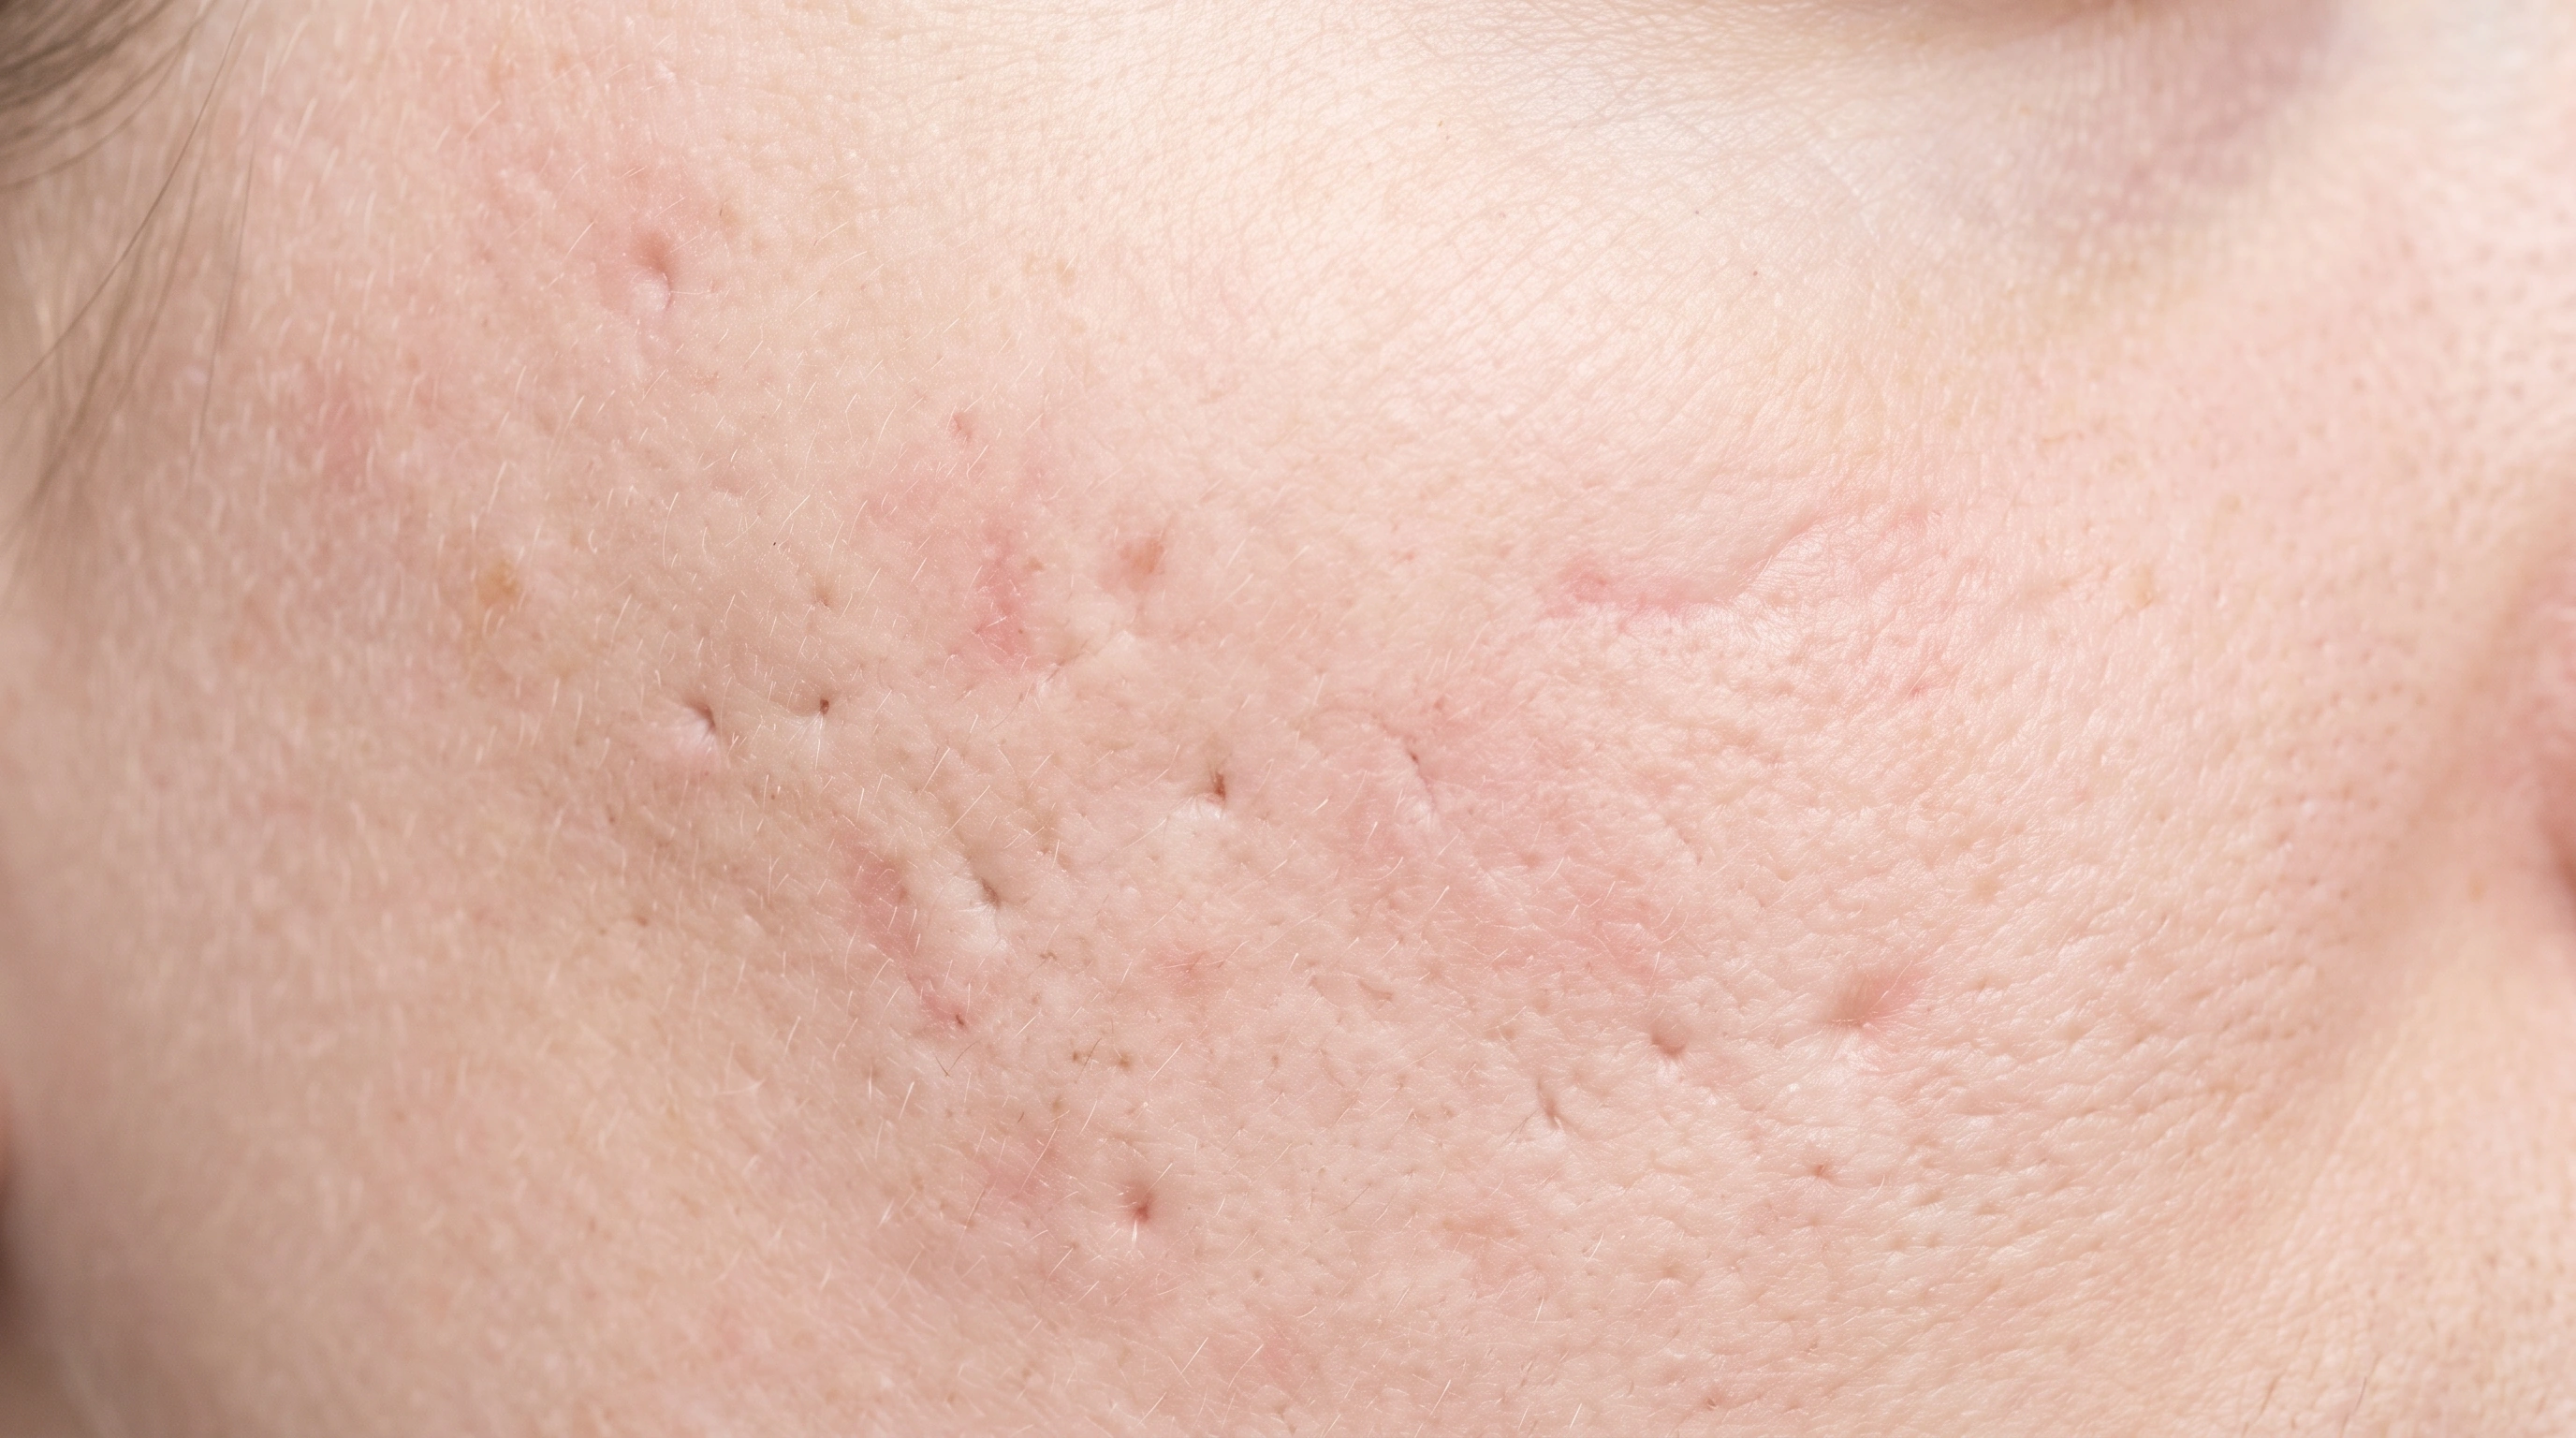


Reduces pore clogging: Helps normalize cell buildup inside follicles. Reduces acne bacteria: Less oil makes follicles less favorable for C. acnes. Makes less oil: Shrinks oil glands and reduces their oil output. Calms inflammation: Dampens immune responses involved in acne.
Oral isotretinoin mechanism overview. Reduced C. acnes is an indirect effect of a changed follicular environment, not antibiotic action. The complete mechanism is not known. Gland outline is conceptual, not a measured size reduction or permanent cure.

Reduces ovarian androgens: Combined hormones lower androgen production by the ovaries. Binds more testosterone: Estrogen raises SHBG, leaving less testosterone free to act. Turns down oil stimulation: Less available androgen means less oil-gland stimulation. Reduces acne over time: Hormone-driven breakouts can gradually improve.
This refers to combined estrogen-progestin pills, not progestin-only contraception. Estrogen effects include suppression of ovarian androgen production and increased SHBG, reducing free testosterone. Specific formulations and clinical responses differ.
Dose is set by body weight, and the total across the whole course matters more than any single day.
Starting dose: Often about 0.5 mg/kg a day, sometimes lower to ease into the side effects. Not the target.
Going up: Usually raised after the first month or two if blood tests and side effects allow, commonly to about 1 mg/kg a day.
Usual dose: About 0.5 to 1 mg/kg daily for most of the course.
Total course: Judged by cumulative dose, usually about 120 to 150 mg/kg of body weight. Reaching that total is what cuts relapse. Most people need five to eight months.
The pack is the dose.
Starting dose: One active tablet daily, begun where in the cycle your prescriber says.
Going up: No increase. If acne has not responded by six months, change the formulation or add another drug.
Usual dose: One tablet daily at about the same time.
Total course: As long as contraception and acne control are both wanted.
With a fatty meal, unless you have the formulation made to work without food. Absorption of standard capsules roughly doubles with fat, so an empty stomach lowers your dose. Splitting the daily amount into two doses with meals is common.
One tablet daily at the same time, with food if it causes nausea. Backup contraception covers the first week unless you start at a set point.
Take it with your next meal if it is the same day, otherwise skip it. Do not double up. The total over months is what counts, and the missed dose moves to the end of the course.
Take it as soon as you remember, even if that means two in a day. For more than one, follow the pack instructions and use backup contraception. Missed pills affect pregnancy protection far more than acne.
Liver enzymes and triglycerides are checked before you start and again during the course, usually in the early months and after a dose increase. Cholesterol and triglycerides commonly rise, then settle afterwards.
Anyone who can become pregnant is enrolled in iPLEDGE, a federal safety program requiring two forms of contraception or documented abstinence, a pregnancy test before starting, monthly tests during, and pickup inside set time windows. Miss a window and that month starts again.
Nobody stays on this drug. The course ends, and the effect on the oil gland lasts, so most people need nothing more than a topical retinoid. A smaller group needs a second course.
Blood pressure and a careful history come before the first prescription: migraines, past clots, smoking, family history. Blood tests are not routinely needed.
People stay on this for years, and what drifts is risk, not the drug. Clot risk is highest in the first year and after restarting, and rises with age, weight, smoking and immobility. Blood pressure is rechecked periodically, and the decision is revisited around age 35.
Approximate windows, not promises.
Weeks 1 to 4Dry lips first, almost always. Skin dries. Acne may flare.
Weeks 1 to 4Nausea, breast tenderness and spotting between periods. Acne may briefly worsen.
Weeks 4 to 12Steady clearing. Dryness peaks and stays.
Weeks 4 to 12Oiliness drops and inflamed spots become less frequent.
Months 4 to 6Most people are clear or nearly clear.
After the courseSkin keeps improving for a few months, and dryness clears within weeks to a couple of months.
After 12 weeksThe fair judgment point, though improvement often runs to six months. Nothing changed by then means a different formulation or drug.
Sorted by what to do about them.
Generic isotretinoin is moderately priced; the formulations that absorb without food cost much more. The real obstacle is not cost but iPLEDGE, with monthly appointments and pickup windows to plan travel and work around.
Most combined pills are generic and cheap, and many plans cover contraception with no copay. The branded acne-approved versions cost more with no advantage. Availability without a prescription varies by state.
The label warns about mood changes and some people report them. Large studies have not shown that isotretinoin causes depression, and severe acne itself is strongly linked to low mood. Mood is asked about at every visit, and any change should be reported.
The concern came from case reports, and larger studies have not shown a clear causal link. Severe abdominal pain or bloody diarrhea still needs assessment.
iPLEDGE applies the same rules to everyone who can become pregnant. A program rule, not a judgement about you.
For most people, yes. About one in five needs a second, and stopping short of the cumulative target is the most avoidable reason.
Occasional drinking is usually fine. Heavy drinking adds to the liver and triglyceride effects already being monitored.
An early flare is common in the first few weeks, especially with more severe acne. It is managed, not a reason to stop.
Combined pills, which contain estrogen. Four are FDA-approved for acne; many others work similarly. The mini-pill, implant and hormonal coil can make acne worse.
Sometimes, in the first month or two. It settles.
Rifampin does. Doxycycline and the other acne antibiotics do not.
The increase is real, but absolute risk stays low in healthy non-smokers, and pregnancy itself carries a higher clot risk. It rises sharply with smoking after 35, a family history of clots, and migraine with aura.
Acne commonly flares for a few months. Plan the next step before you stop.