
Ringworm vs Pityriasis Rosea

Ringworm is a common fungal skin infection that spreads outward in a scaly ring with a raised edge. There is no worm involved. It clears with antifungal treatment, as long as the treatment is used for long enough and steroid creams are kept away from it. A usually temporary eruption of oval scaly patches, sometimes beginning with one larger herald patch.

Research updated 2026-10-23
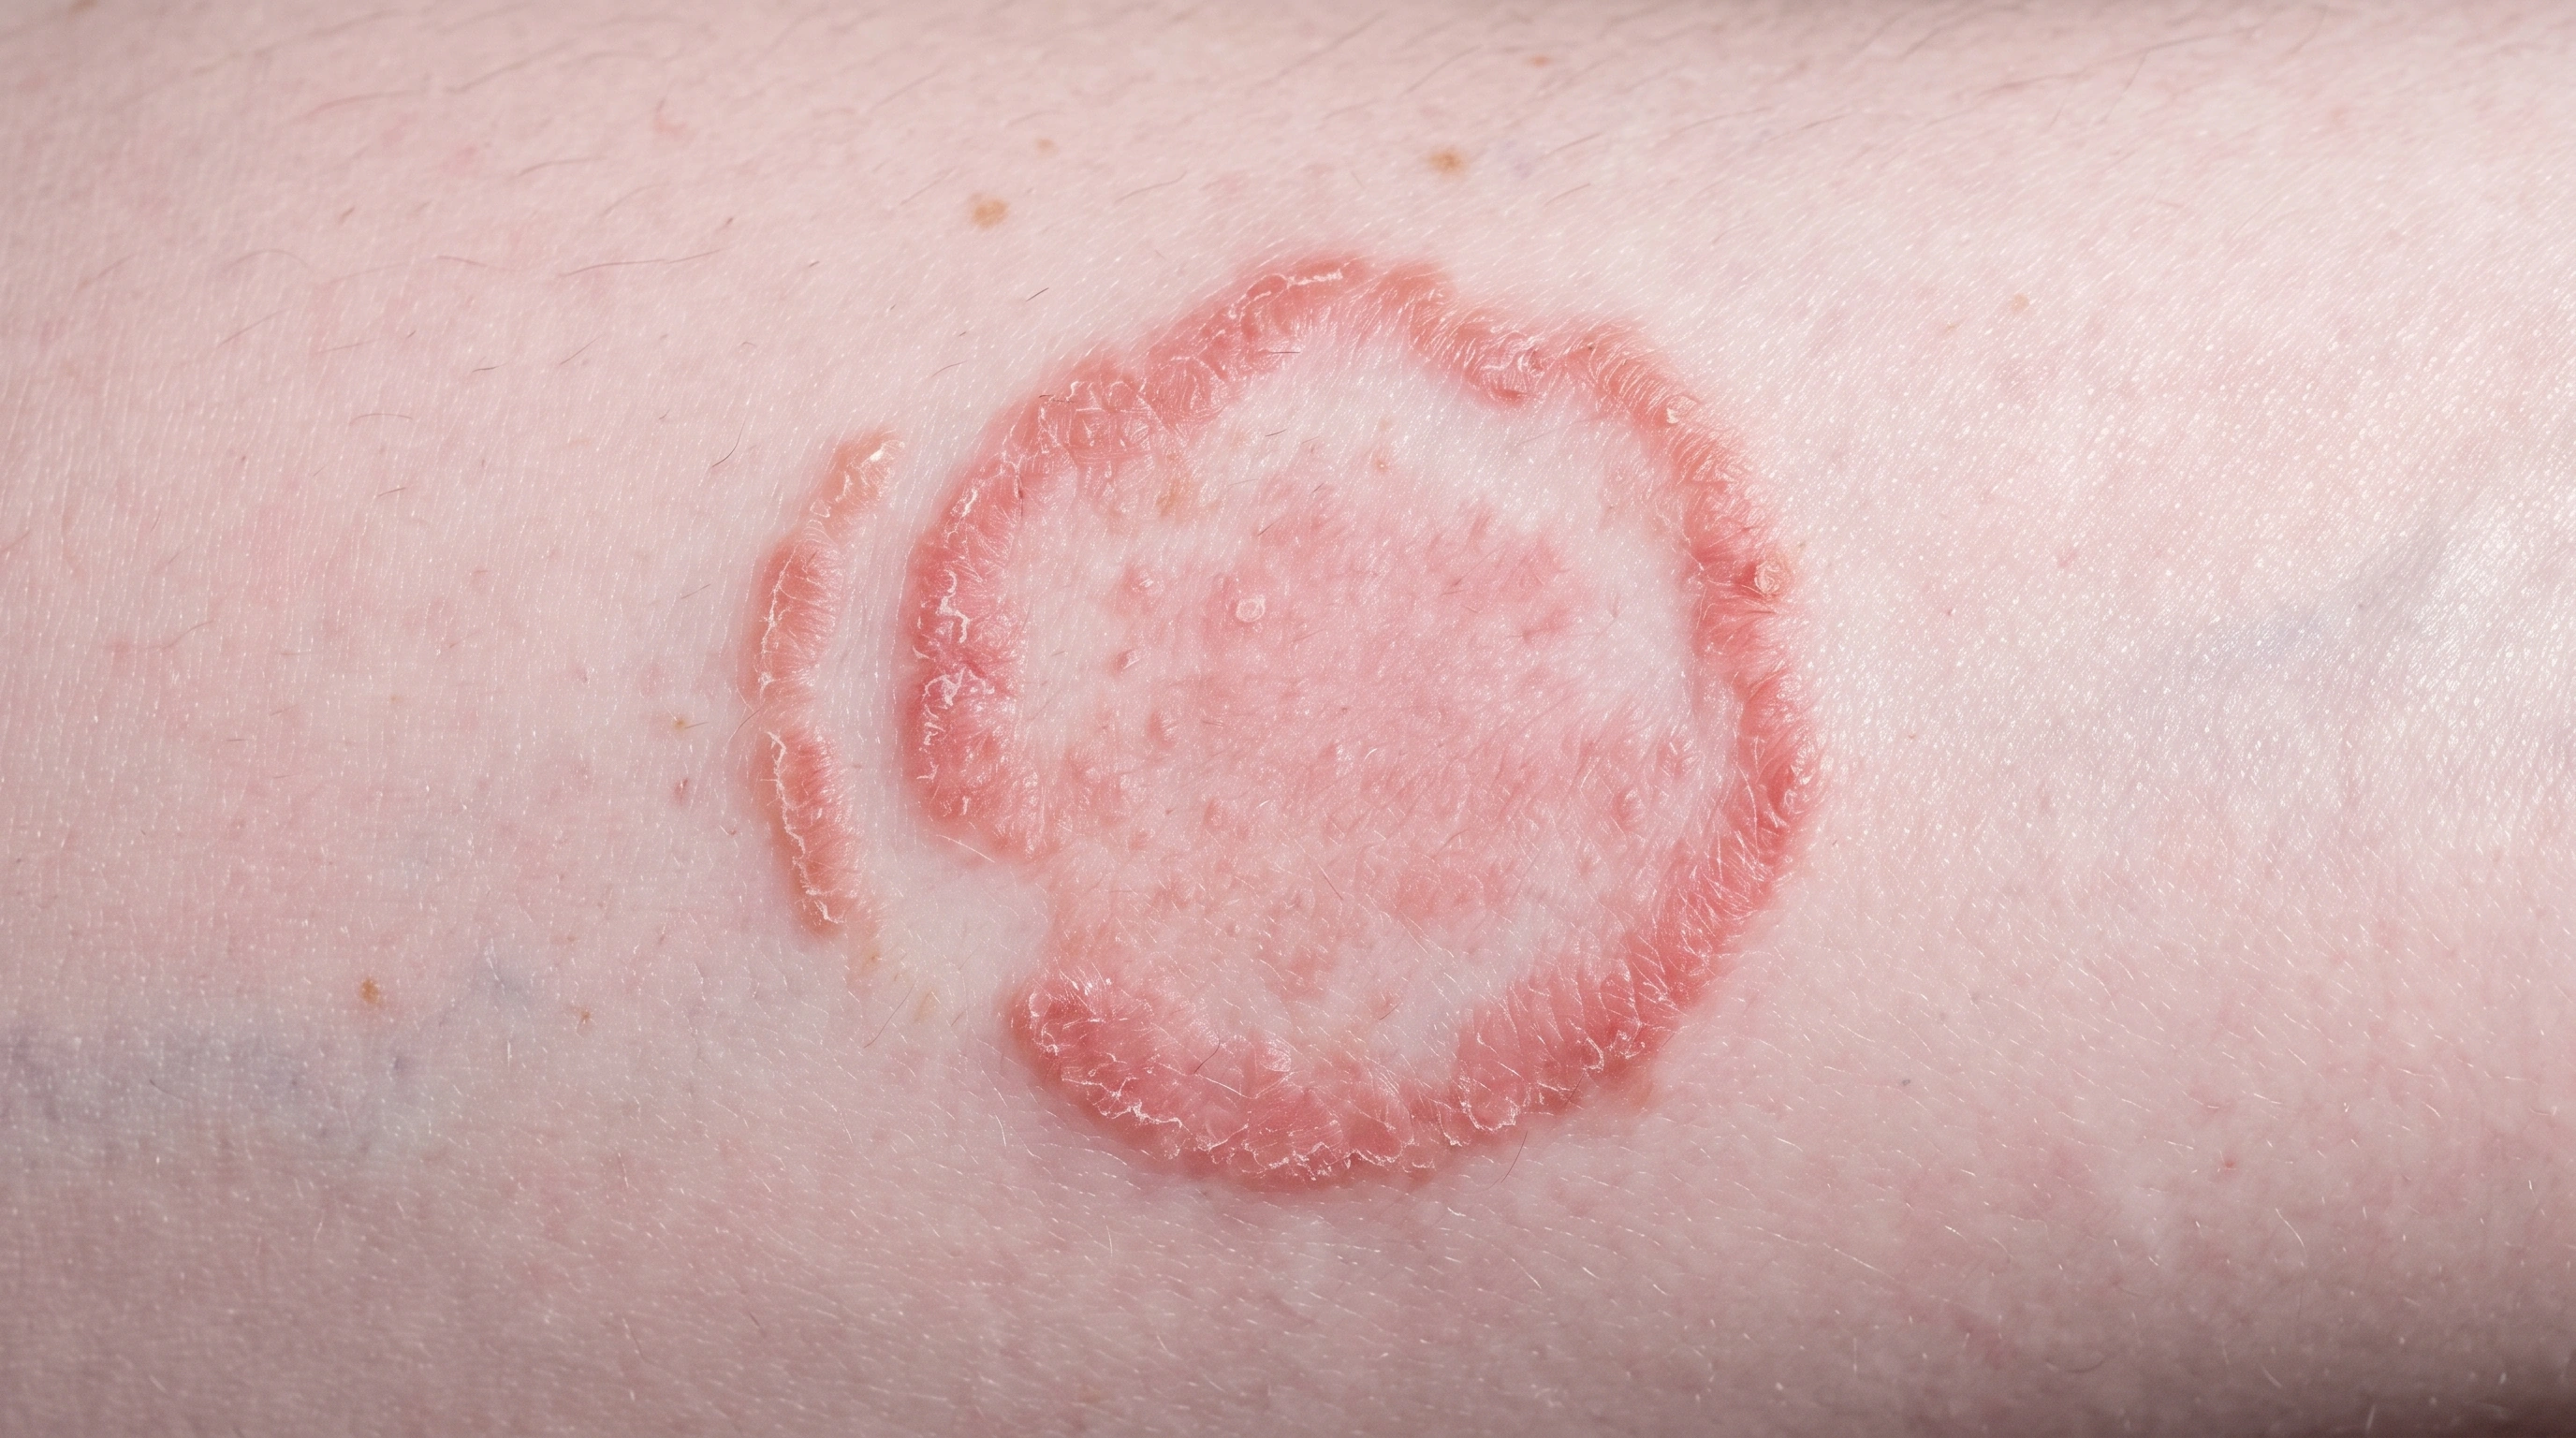
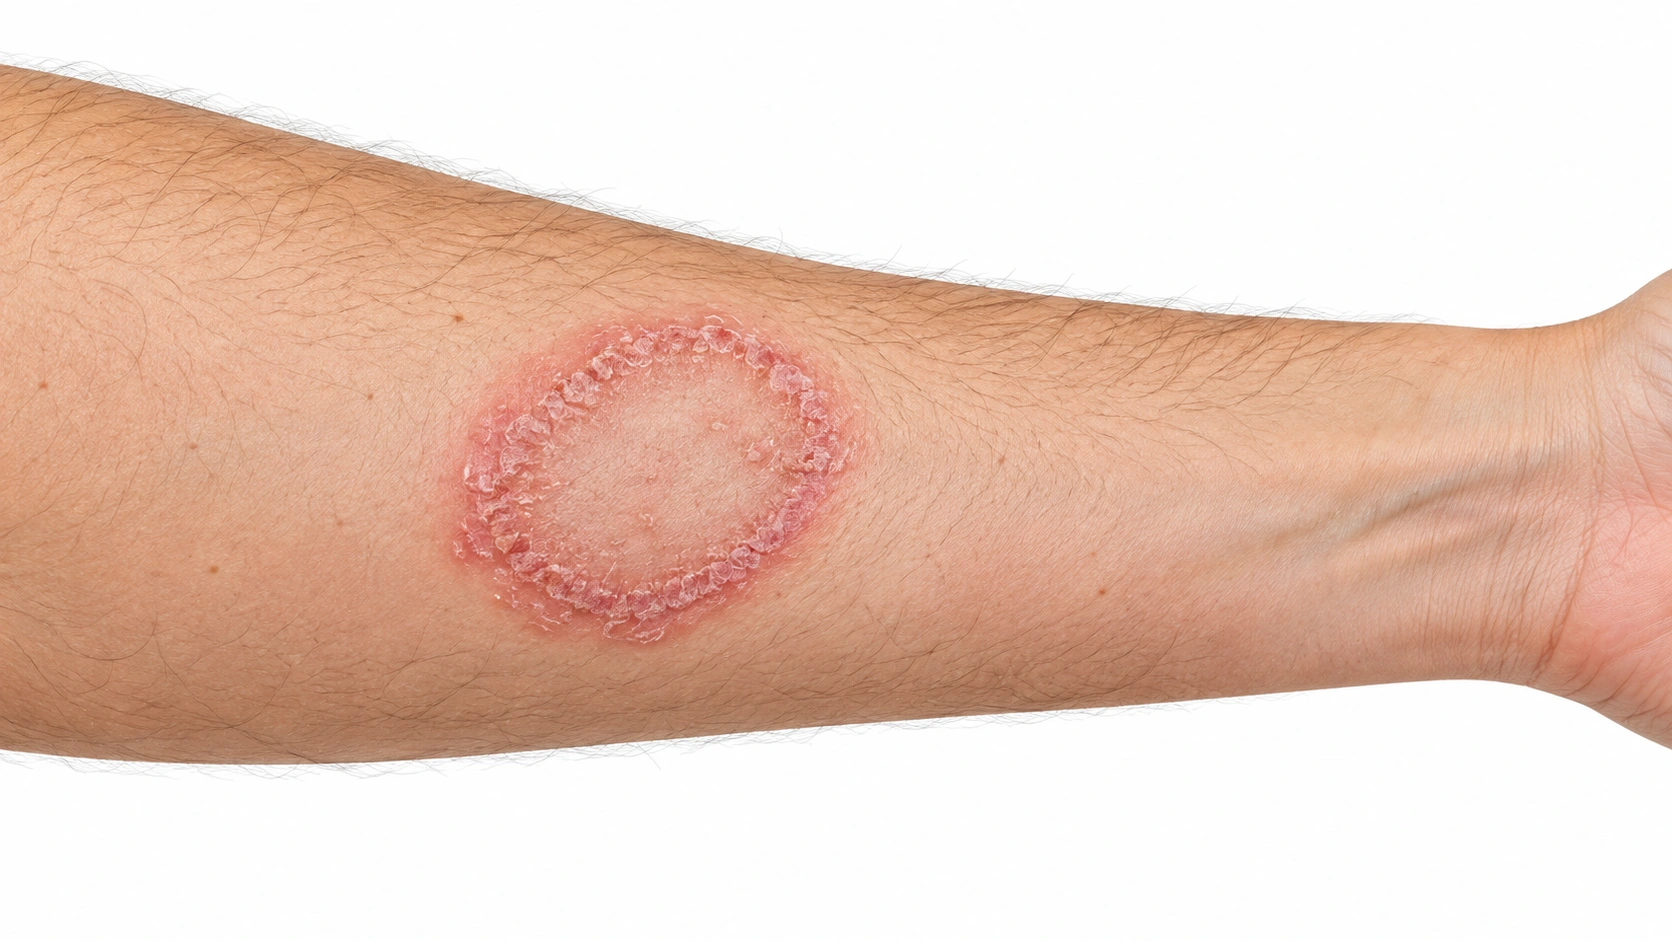
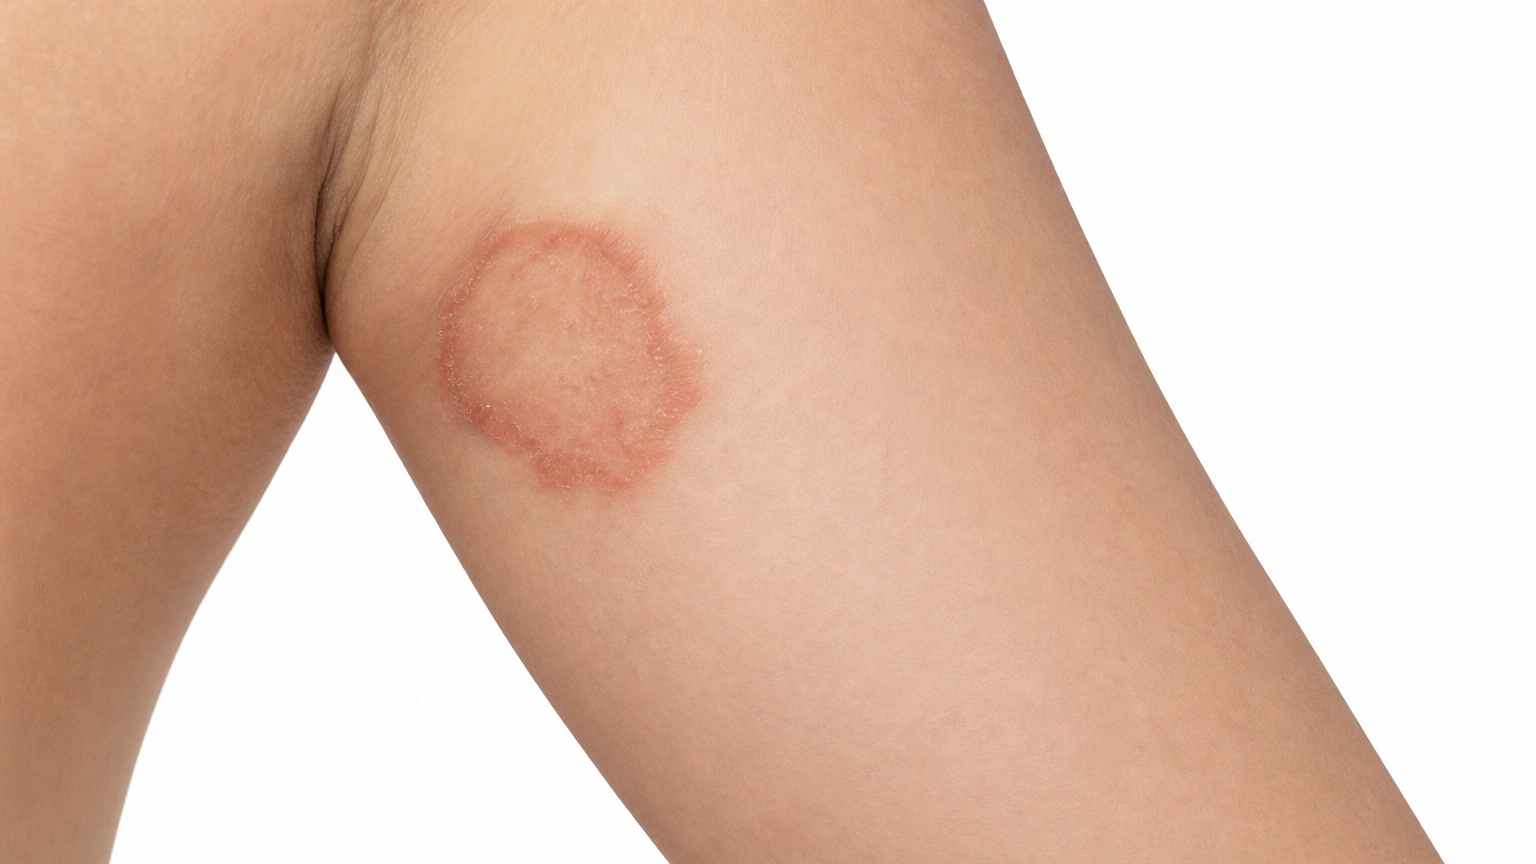
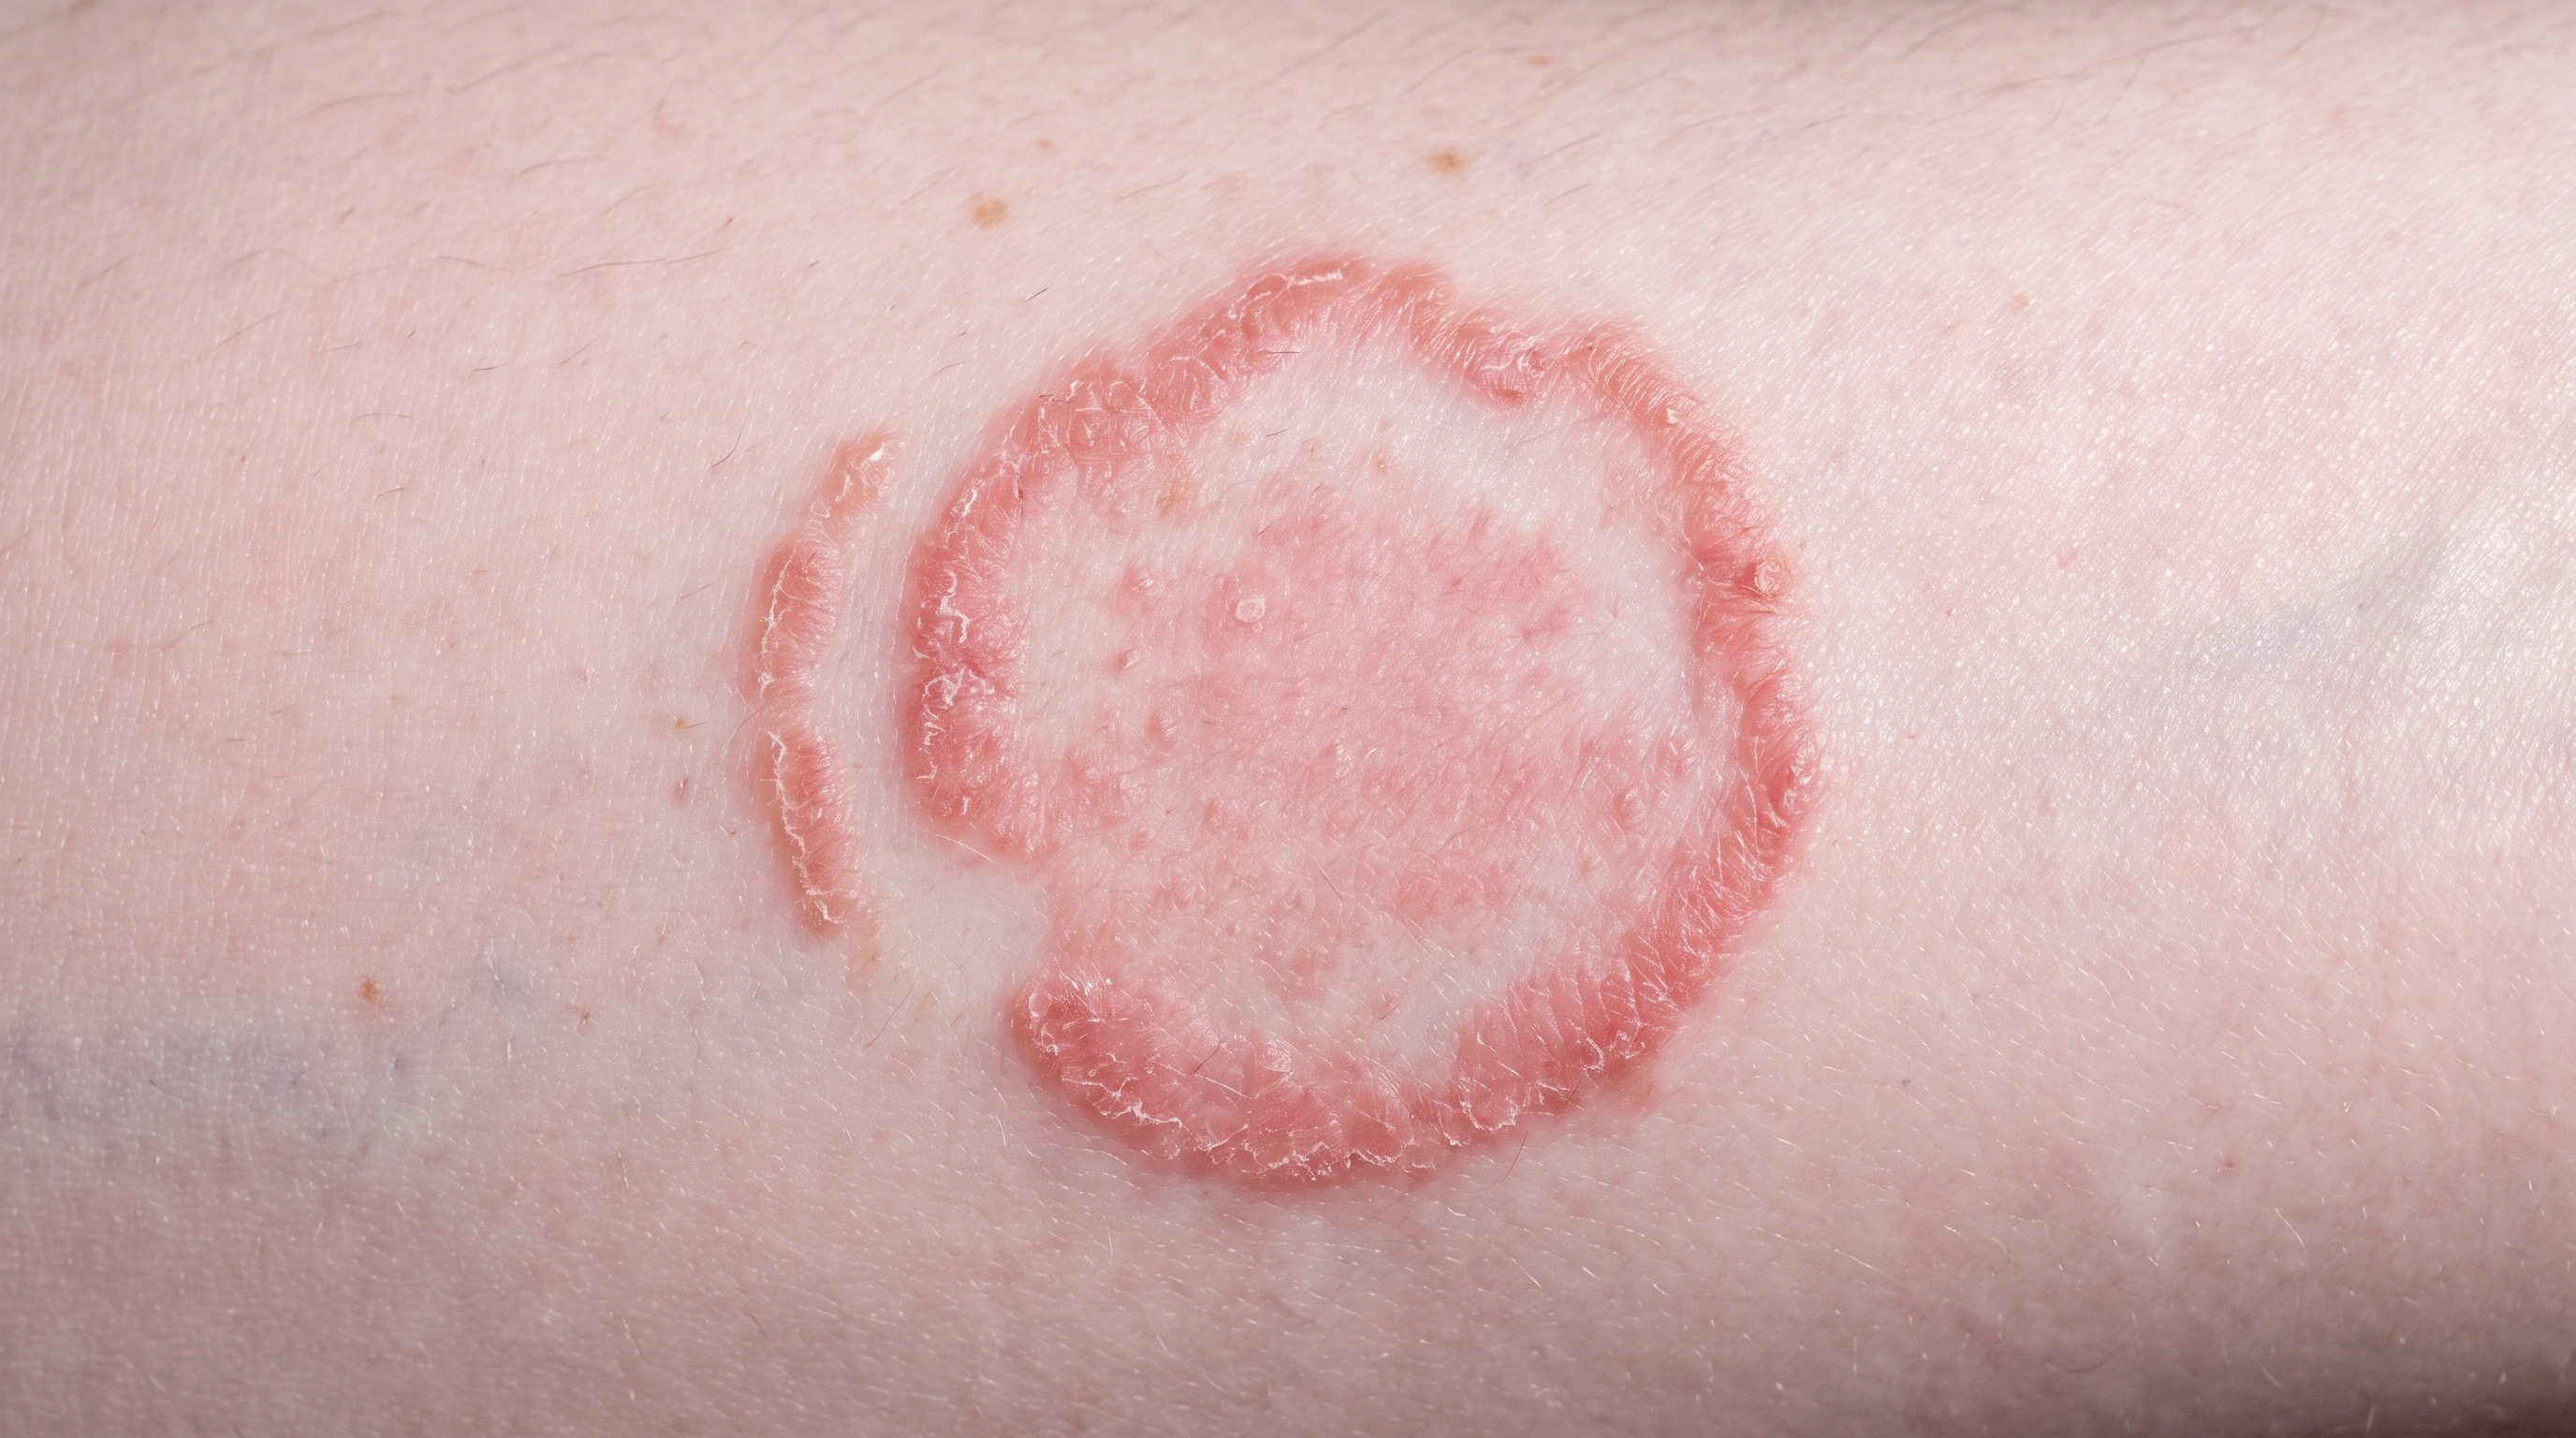
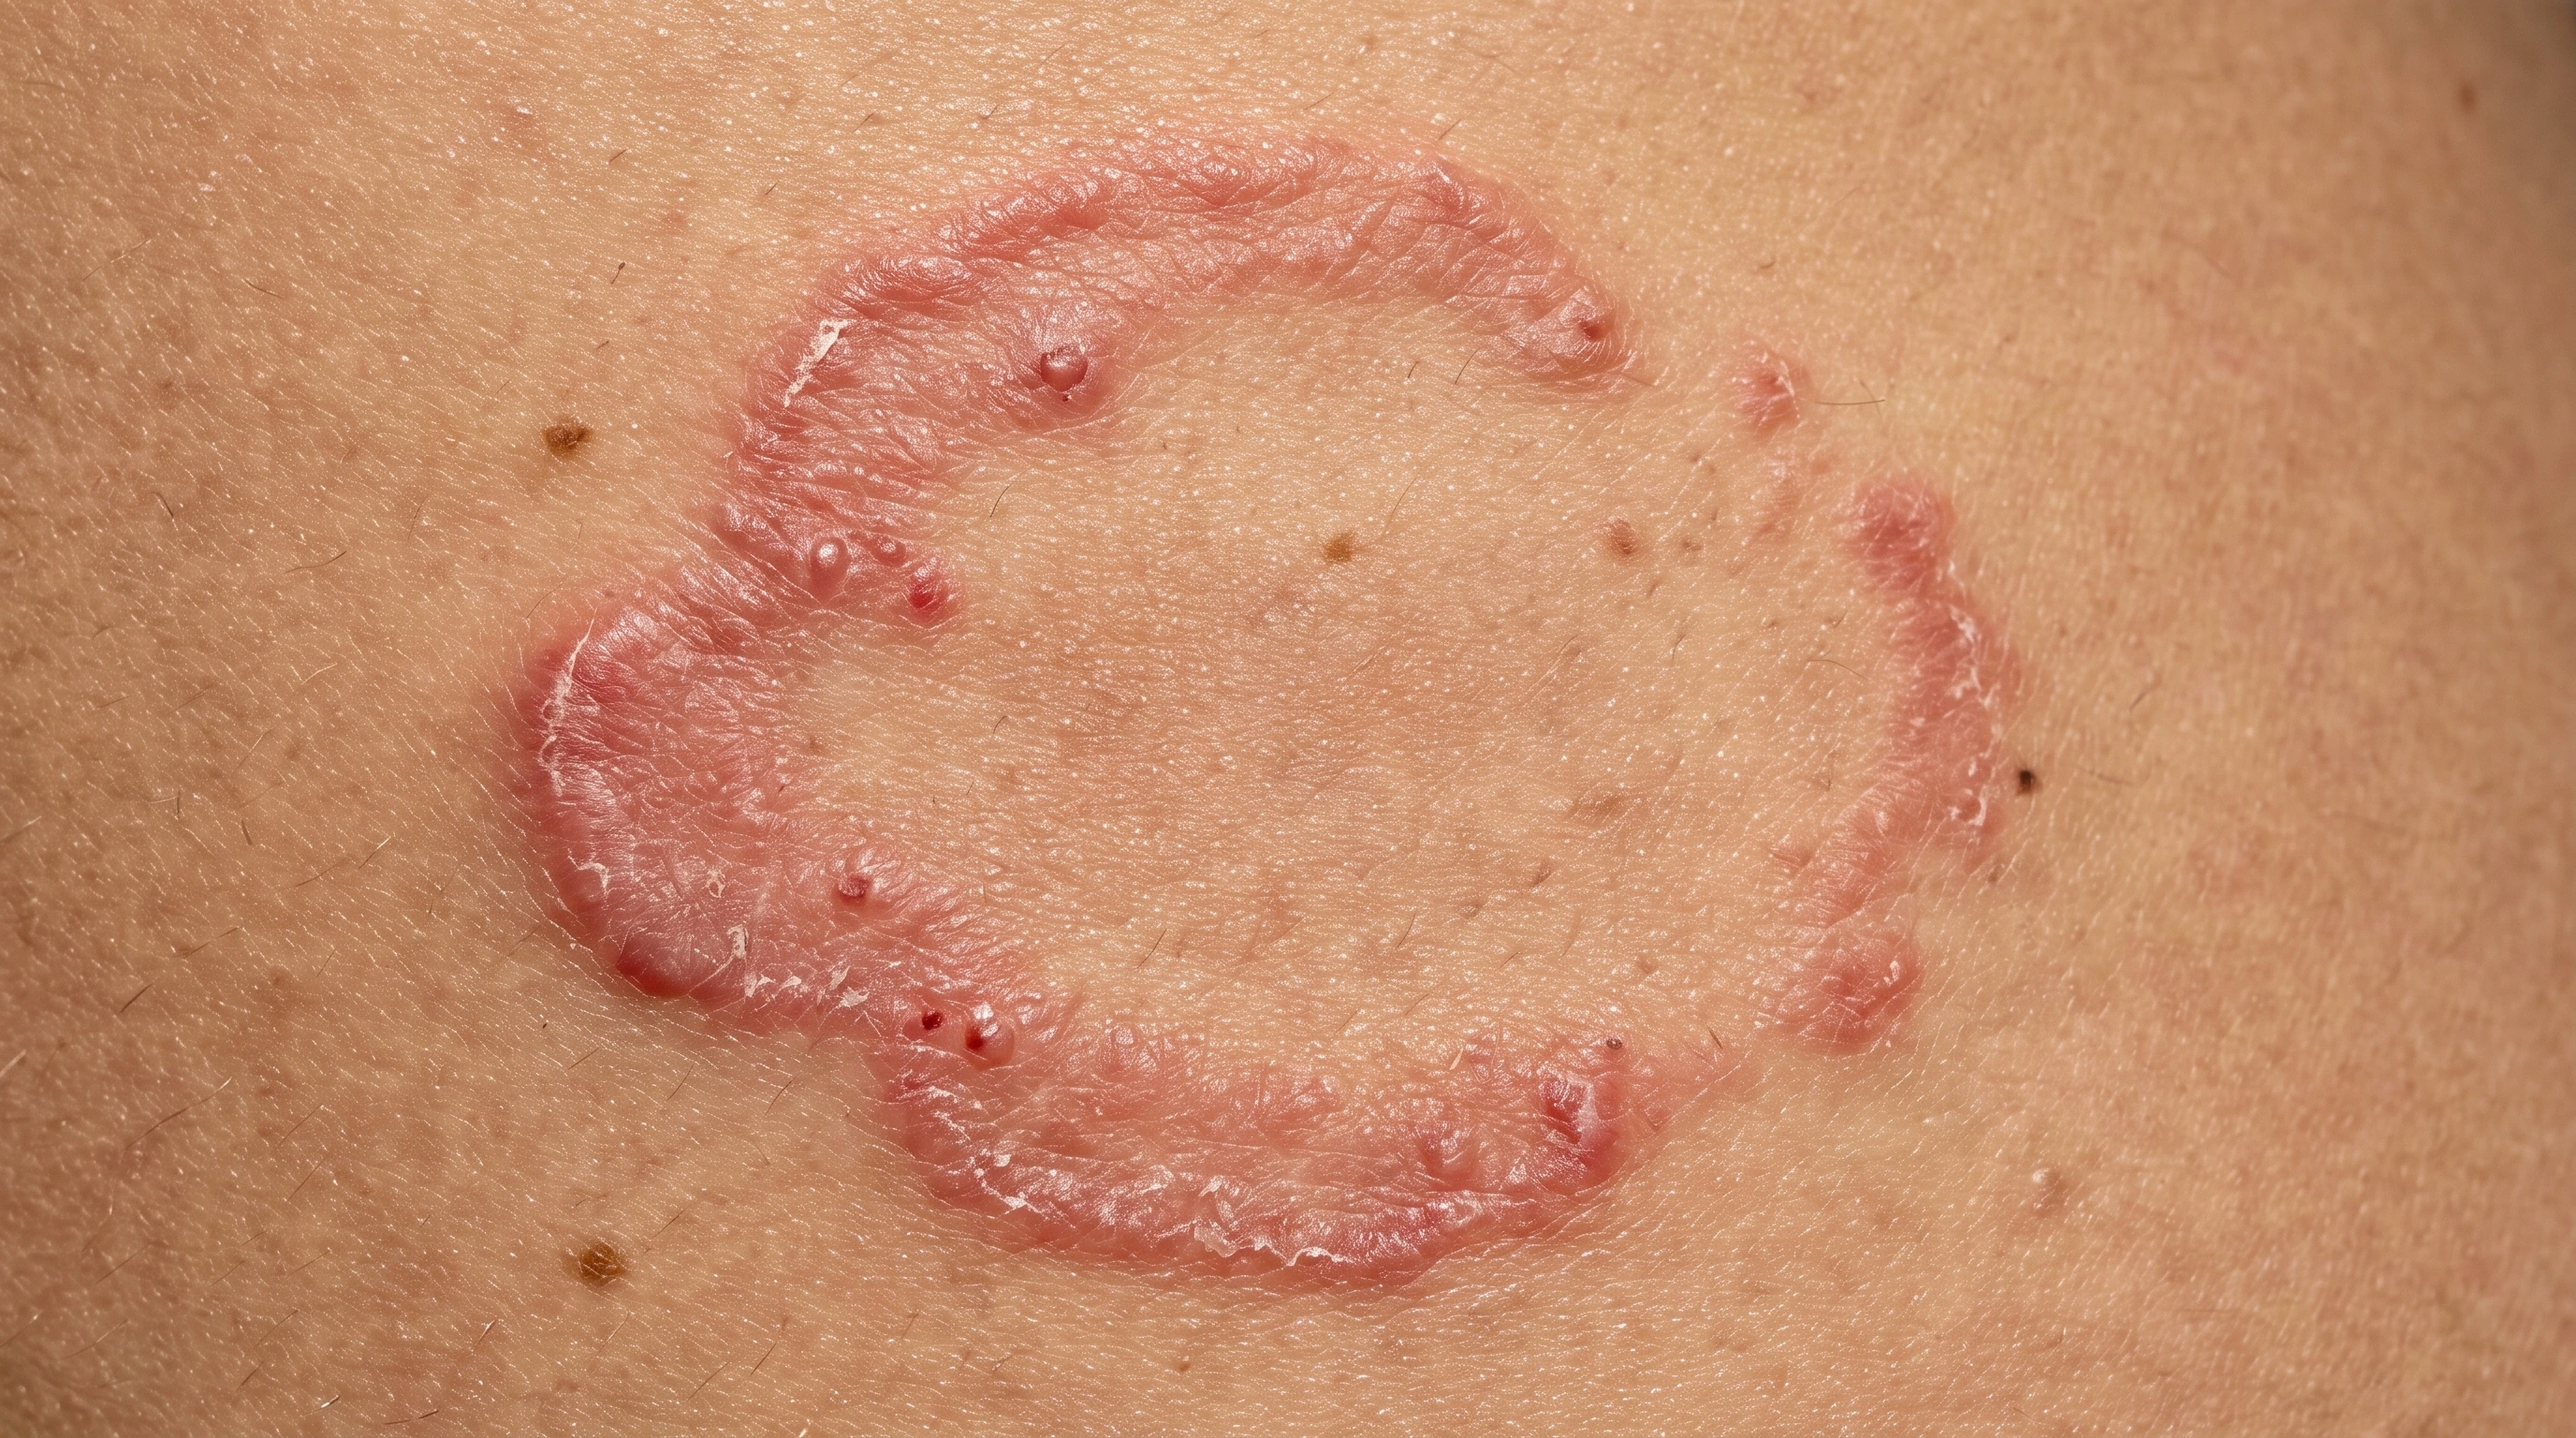
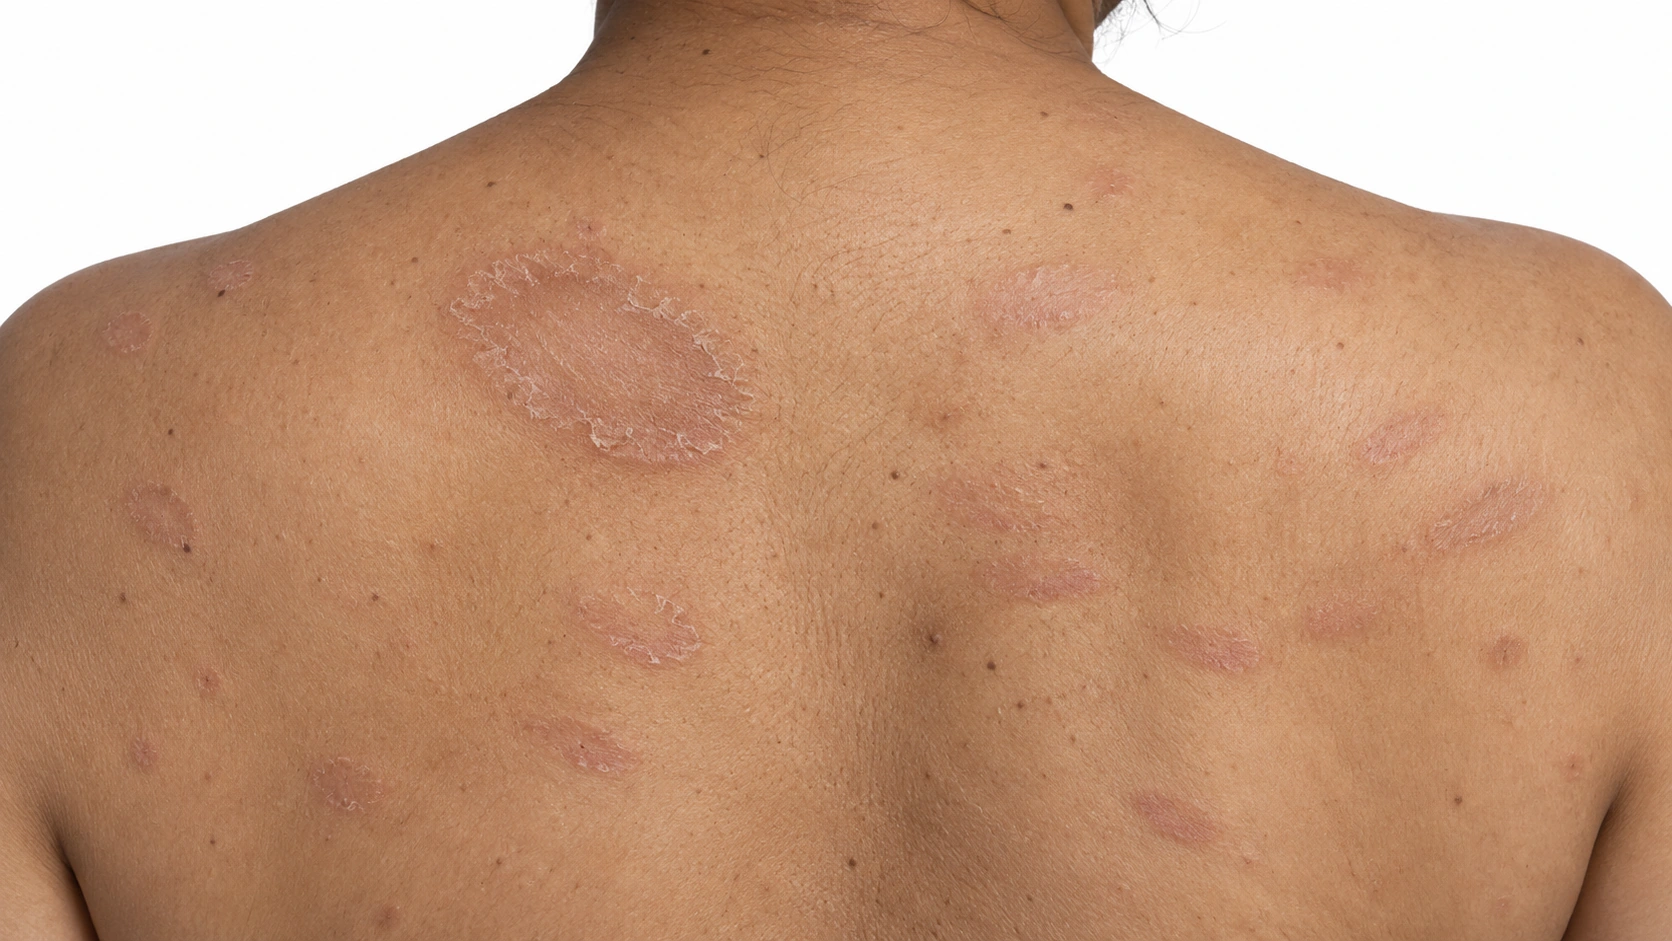
A round patch on a forearm on fair light skin, with a raised pink scaly border and a flatter, clearer middle.Oval patches with fine collarette scale on the upper back.

Key differences

The same eight facts on every condition comparison.

Usual age
Any age
10 to 35
Where
Body, groin, feet, scalp
Trunk and upper arms
Main sign
Ring with a scaly raised edge
Herald patch, then oval scaly patches
Itch or pain
Itchy
Mild itch
Contagious
Yes
Not really
Long term
Clears with antifungals
Clears in 6 to 12 weeks
Scars
No
No
Who gets it
Children, athletes, pet owners
Teens and young adults

What is it?

Ringworm
Pityriasis Rosea
What is it?
  • It is a fungal skin infection.
    Tinea corporis is dermatophyte infection of body skin.
  • The ring is a clue only.
    It may be absent, especially after steroid creams.
  • It is an umbrella term.
    Related infections affect the scalp, nails and other sites.
  • Testing guides treatment.
    Scrapings or culture confirm infection; scalp and nail infections need different care.
  • What it is
    A usually temporary eruption of oval scaly patches, sometimes beginning with one larger herald patch.

What it looks like

Ringworm

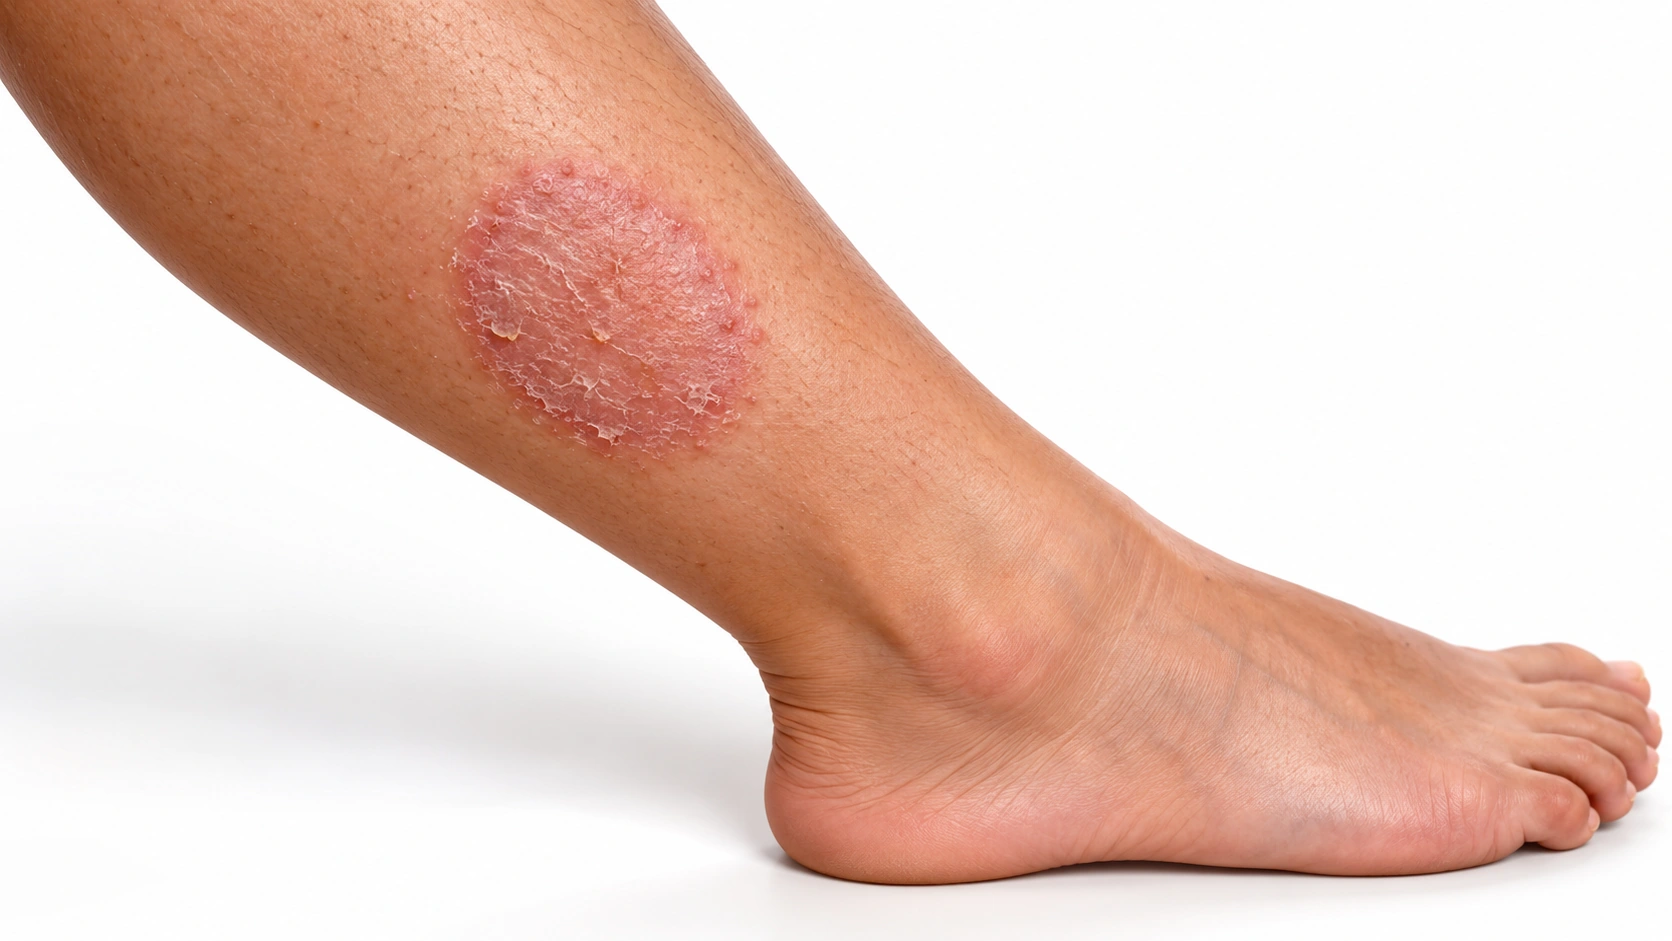
Representative image of ringworm body. Reused for related Supporting concepts; it is not an exact depiction of every subtype, location or stage, or a diagnostic reference.

Tinea corporis (body ringworm) Rings on the body and limbs.

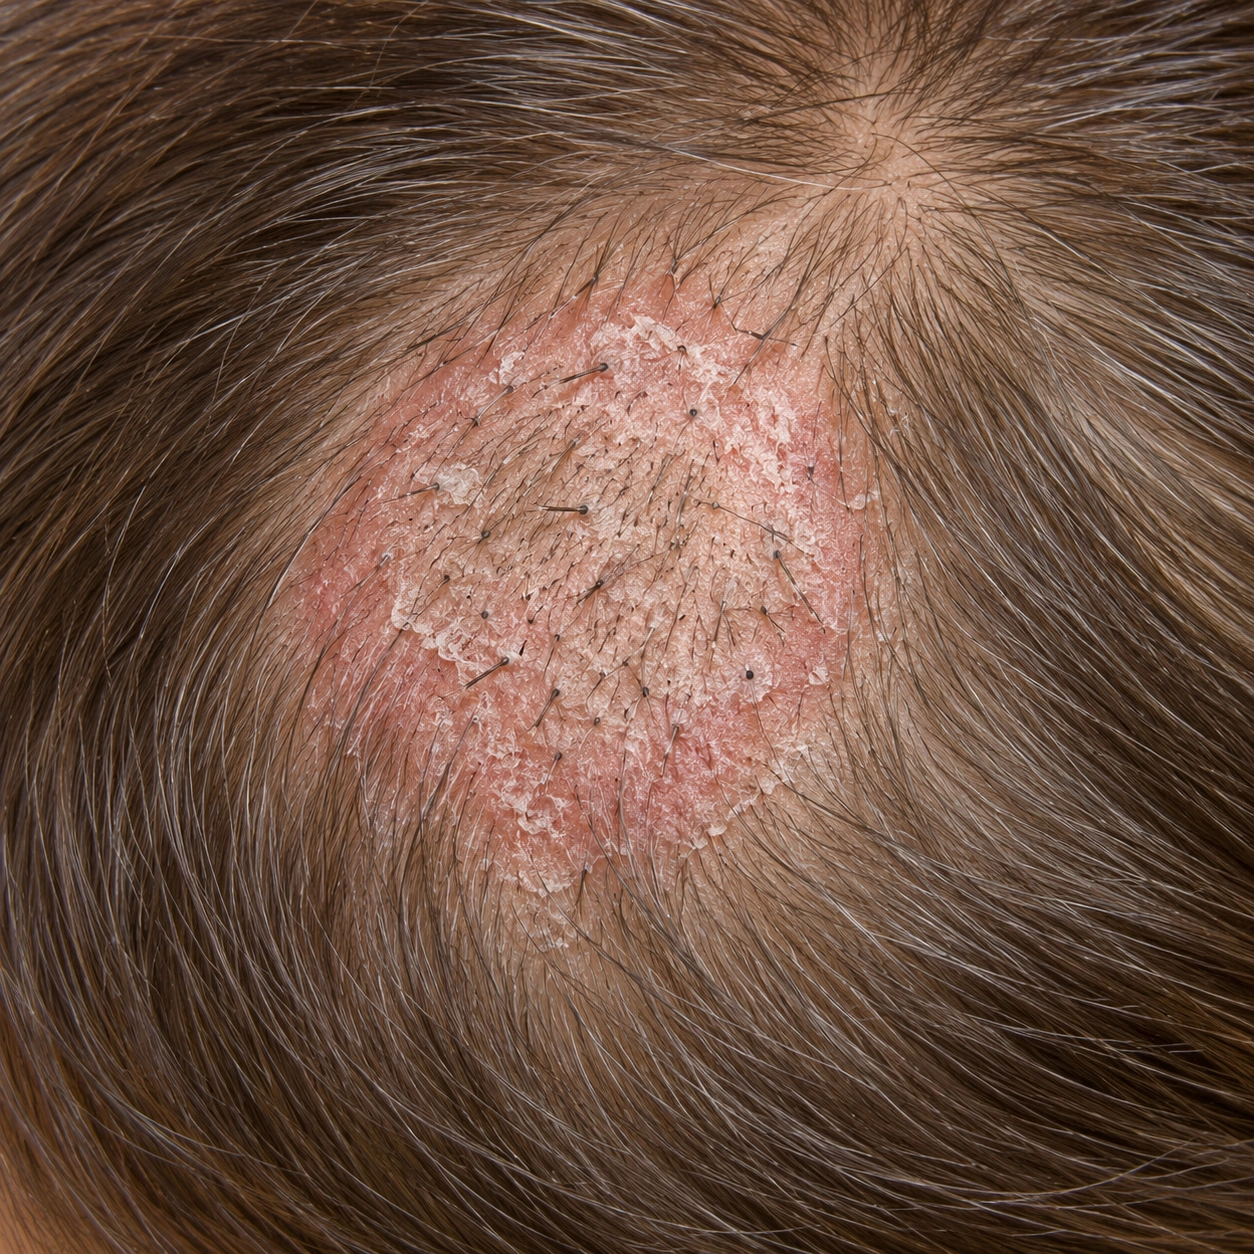
Generated image: Scaly patch with broken hairs on a child's scalp. Not a patient photograph.

Tinea capitis (scalp ringworm) Generated illustration. Scaly patches with hair loss.

A red annular scaly patch on the inner thigh with relative central clearing, representing ringworm.

Tinea cruris (jock itch) Jock itch in the inner thighs.

16:9 hero for Athlete's Foot. Never cropped: the tone strip and the corner logo depend on the full frame.

Tinea pedis (athlete’s foot) Athlete's foot.

Pityriasis Rosea

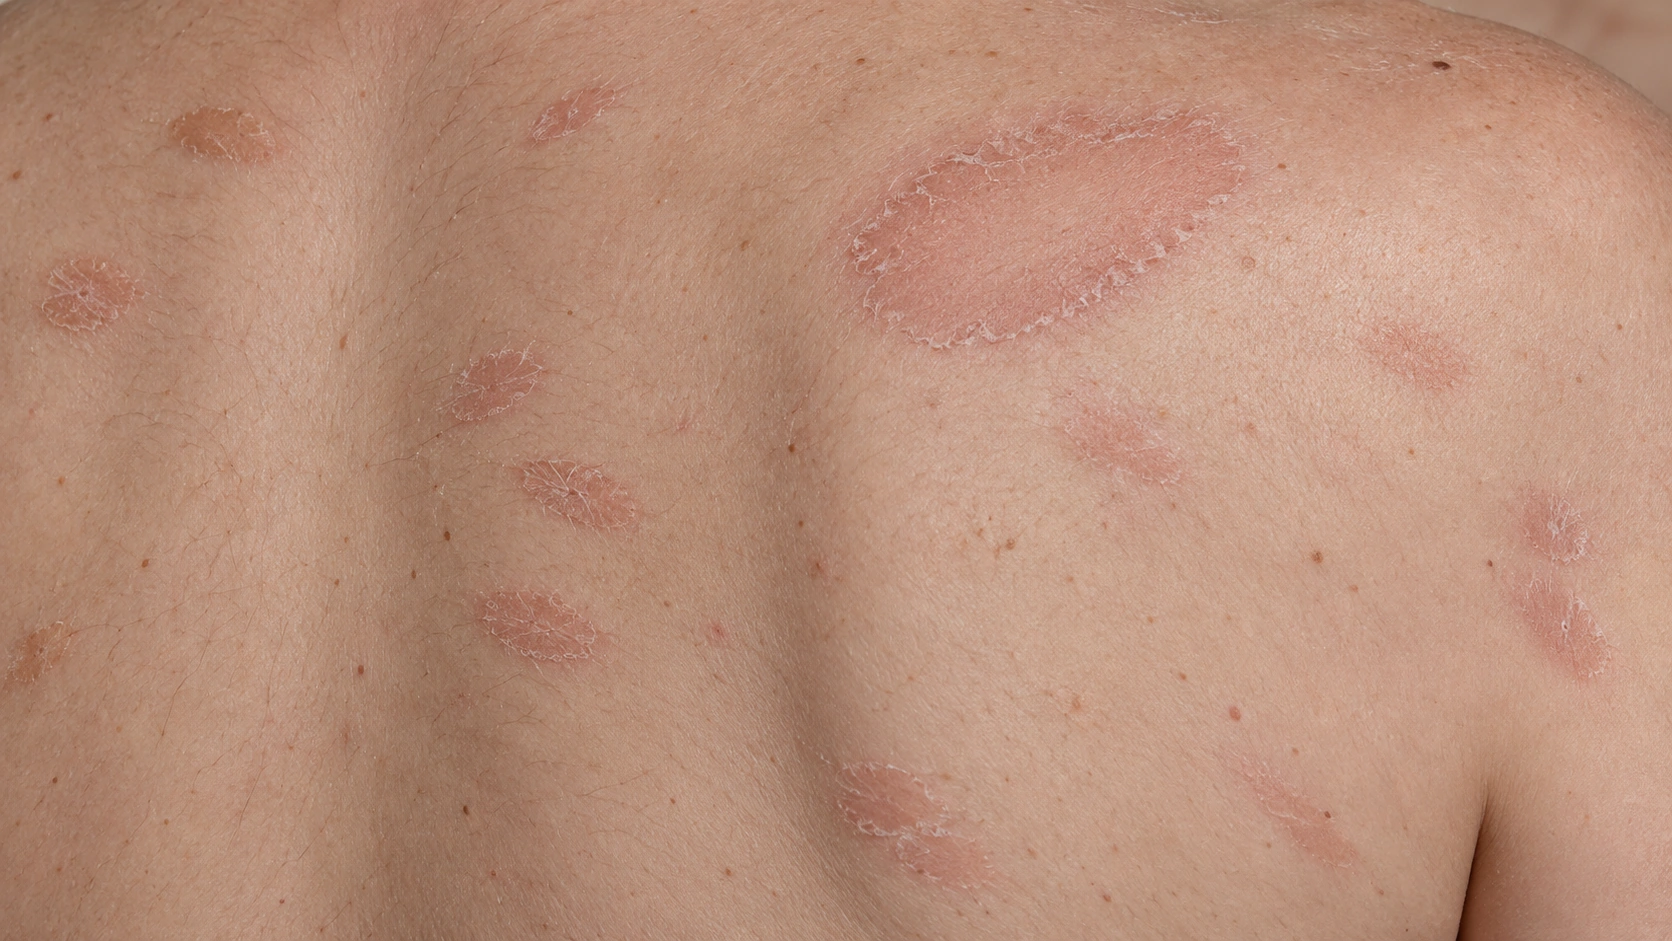
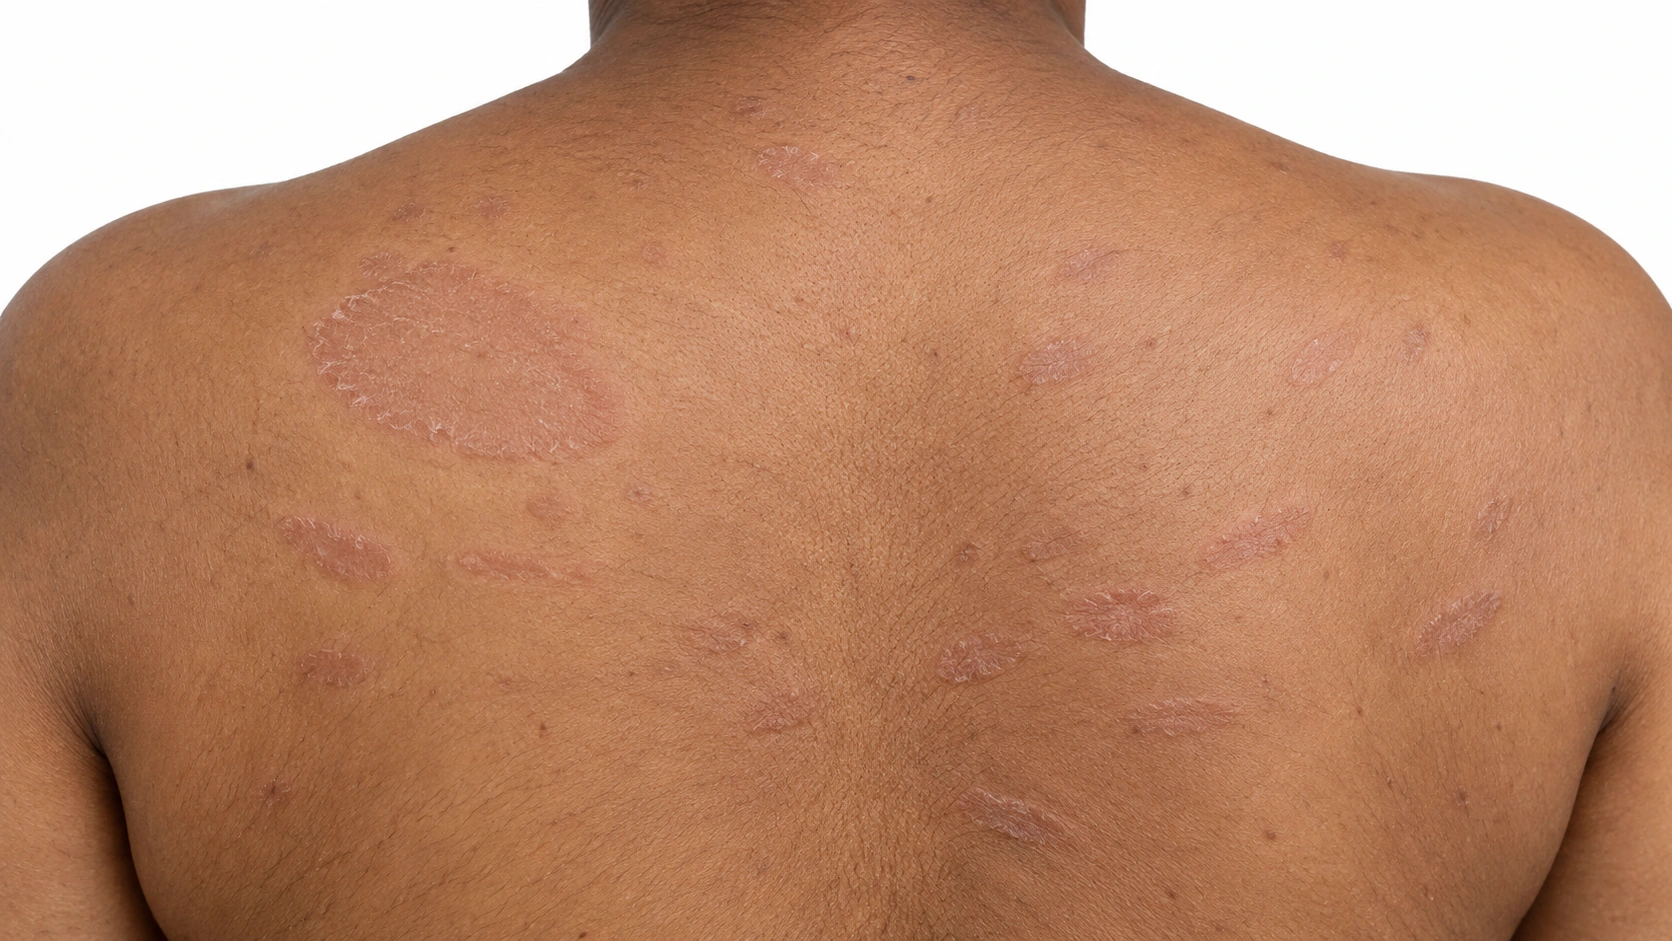
An upper back with one larger dusky oval patch and multiple smaller pink patches.

Larger patch and smaller spots A larger patch sits among several smaller pink marks.

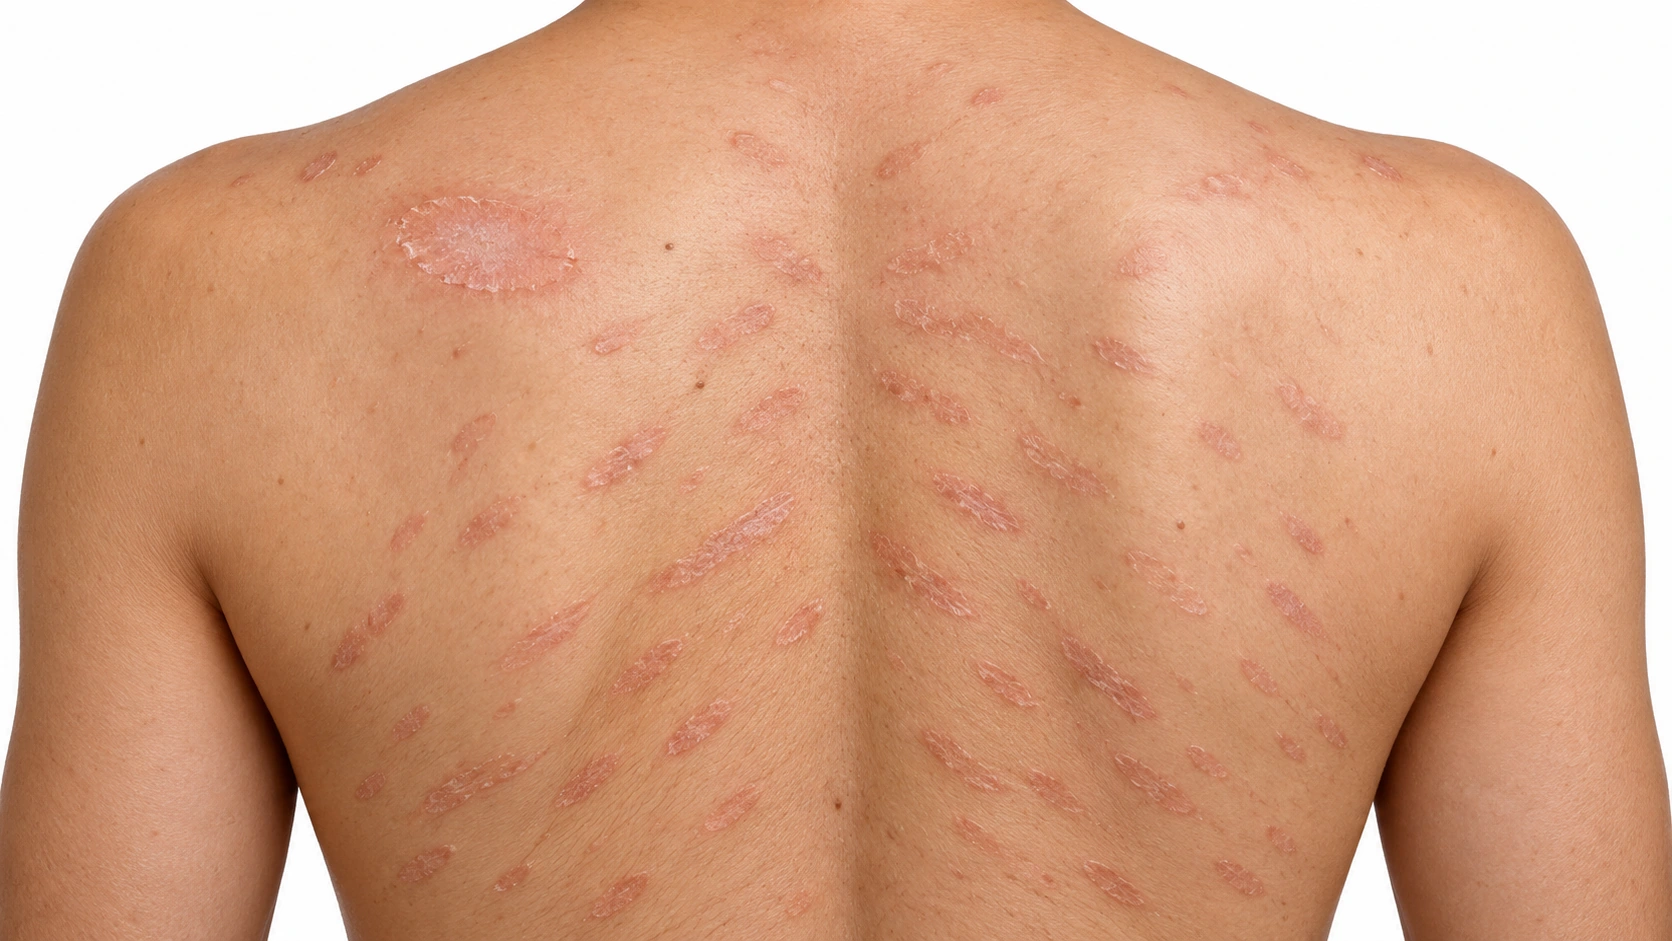
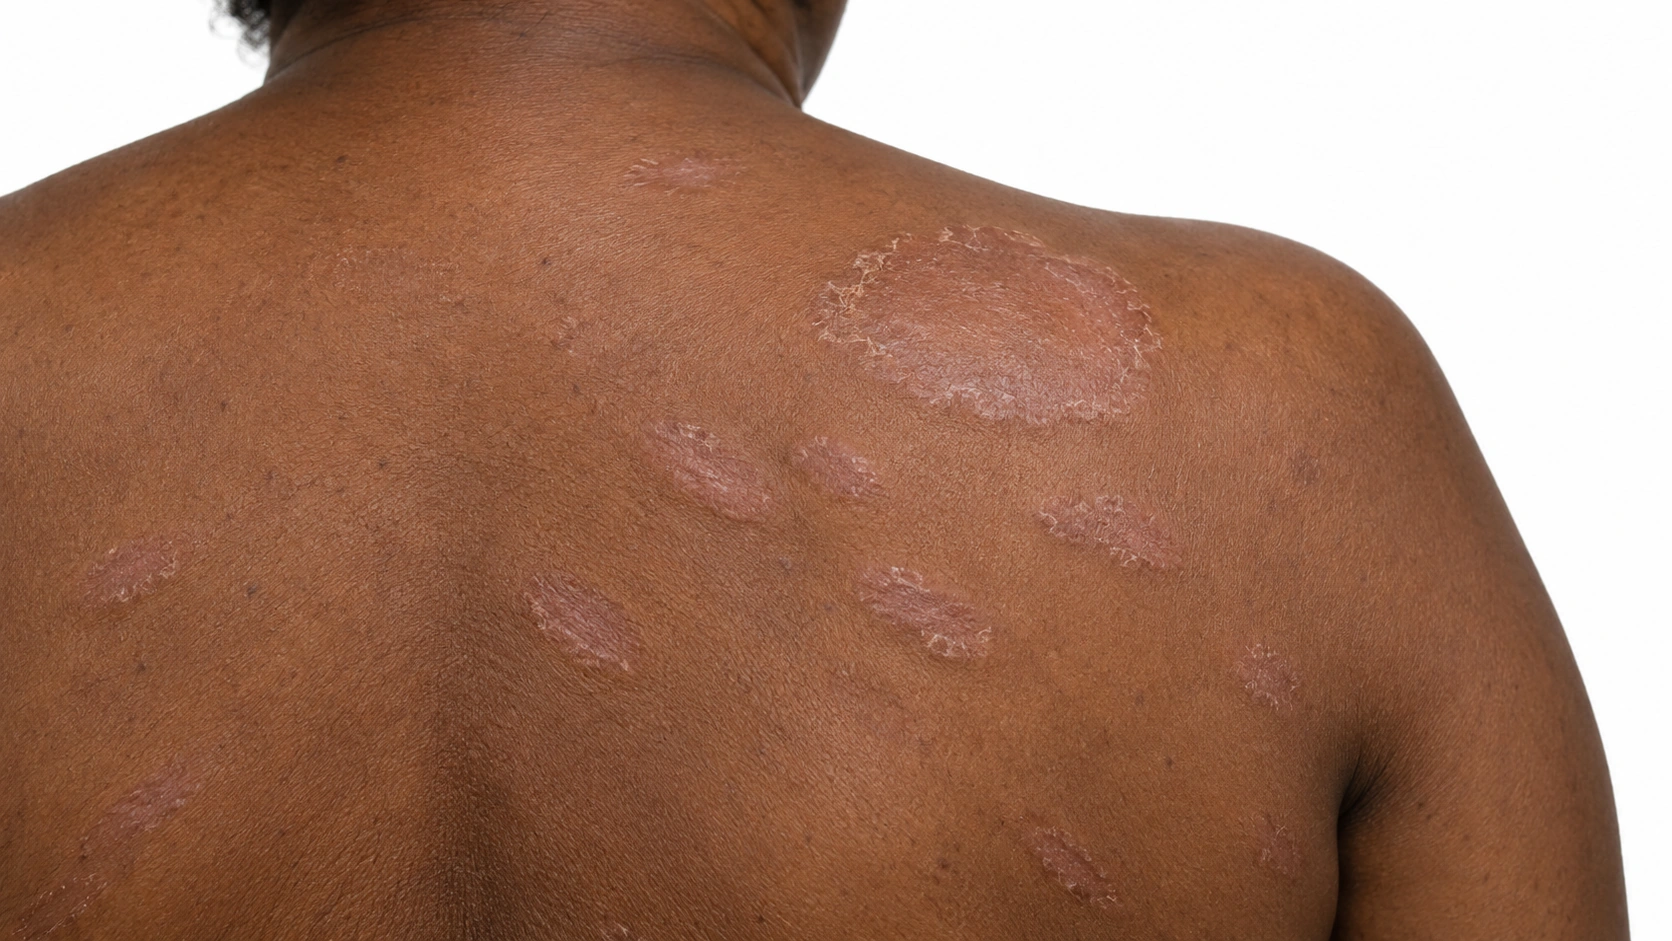
Oval rash patches slope outward from the spine in a branching pattern.

Branching back pattern Oval patches follow sloping lines across the back in a branching pattern.

Skin tones
A round patch on a forearm on fair light skin, with a raised pink scaly border and a flatter, clearer middle.
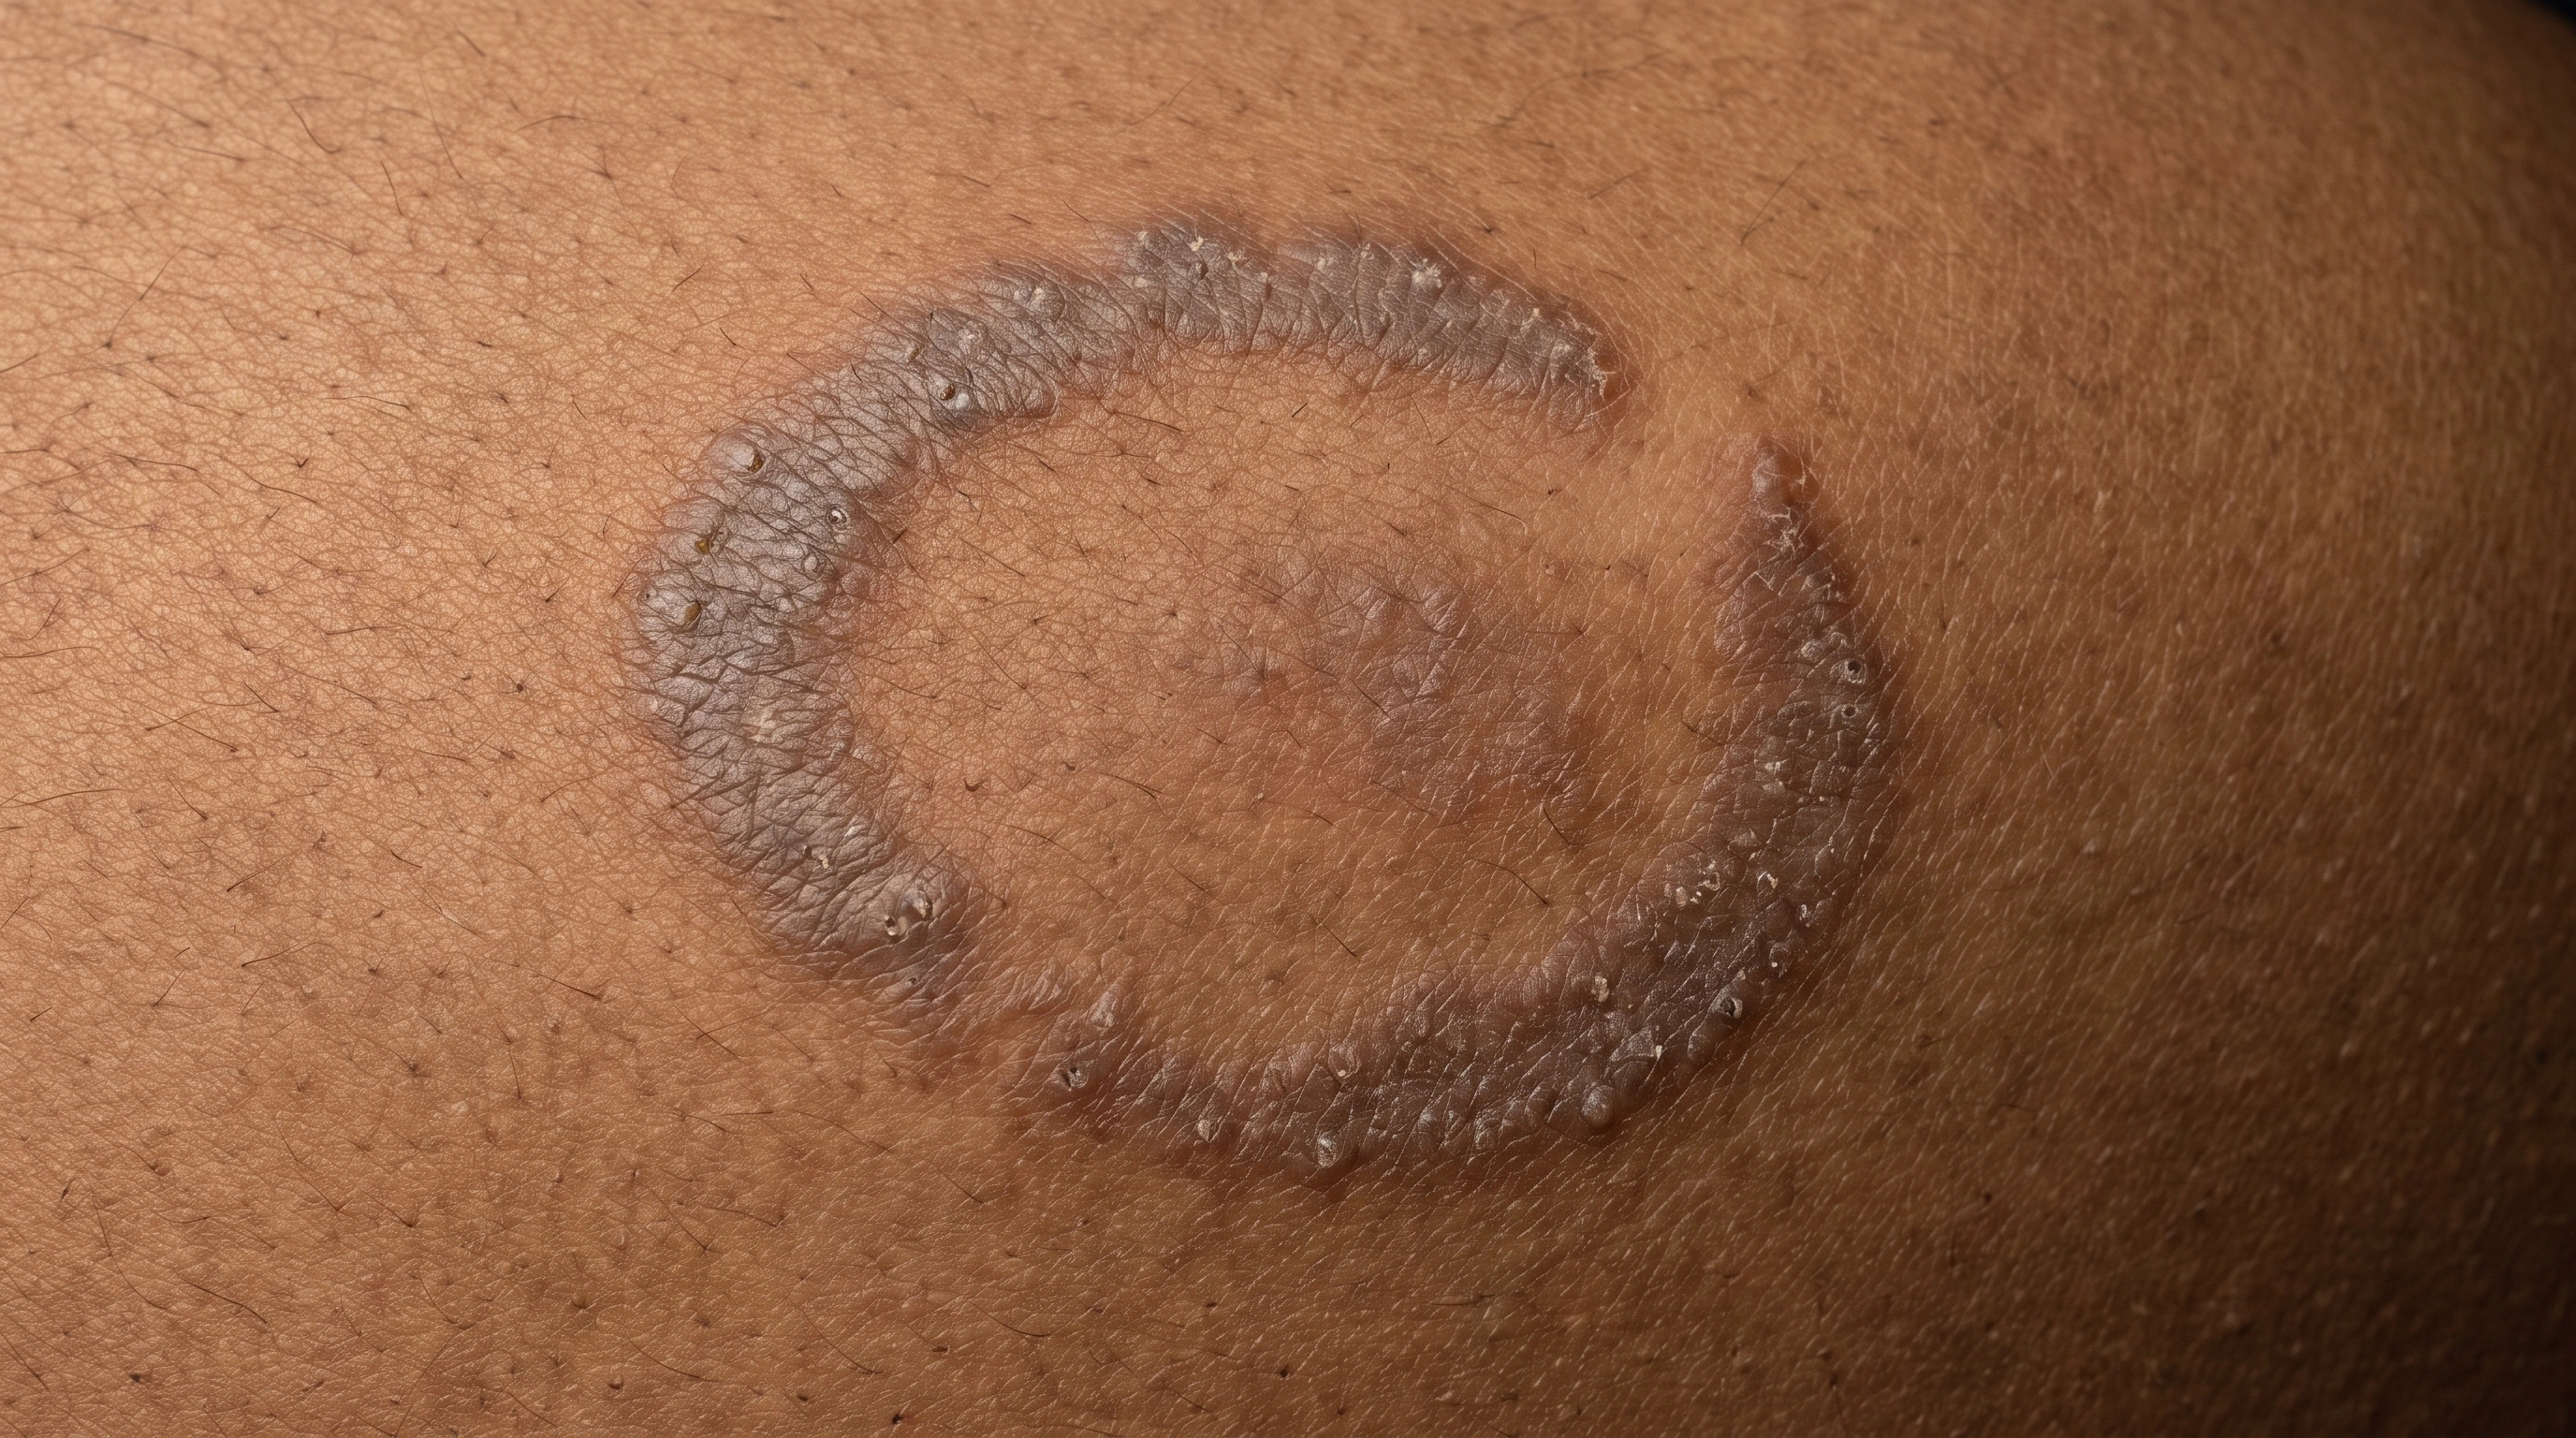
A round patch on a forearm on medium olive-tan skin, with a raised tan-brown scaly border and a flatter middle. The color difference from the surrounding skin is slight.
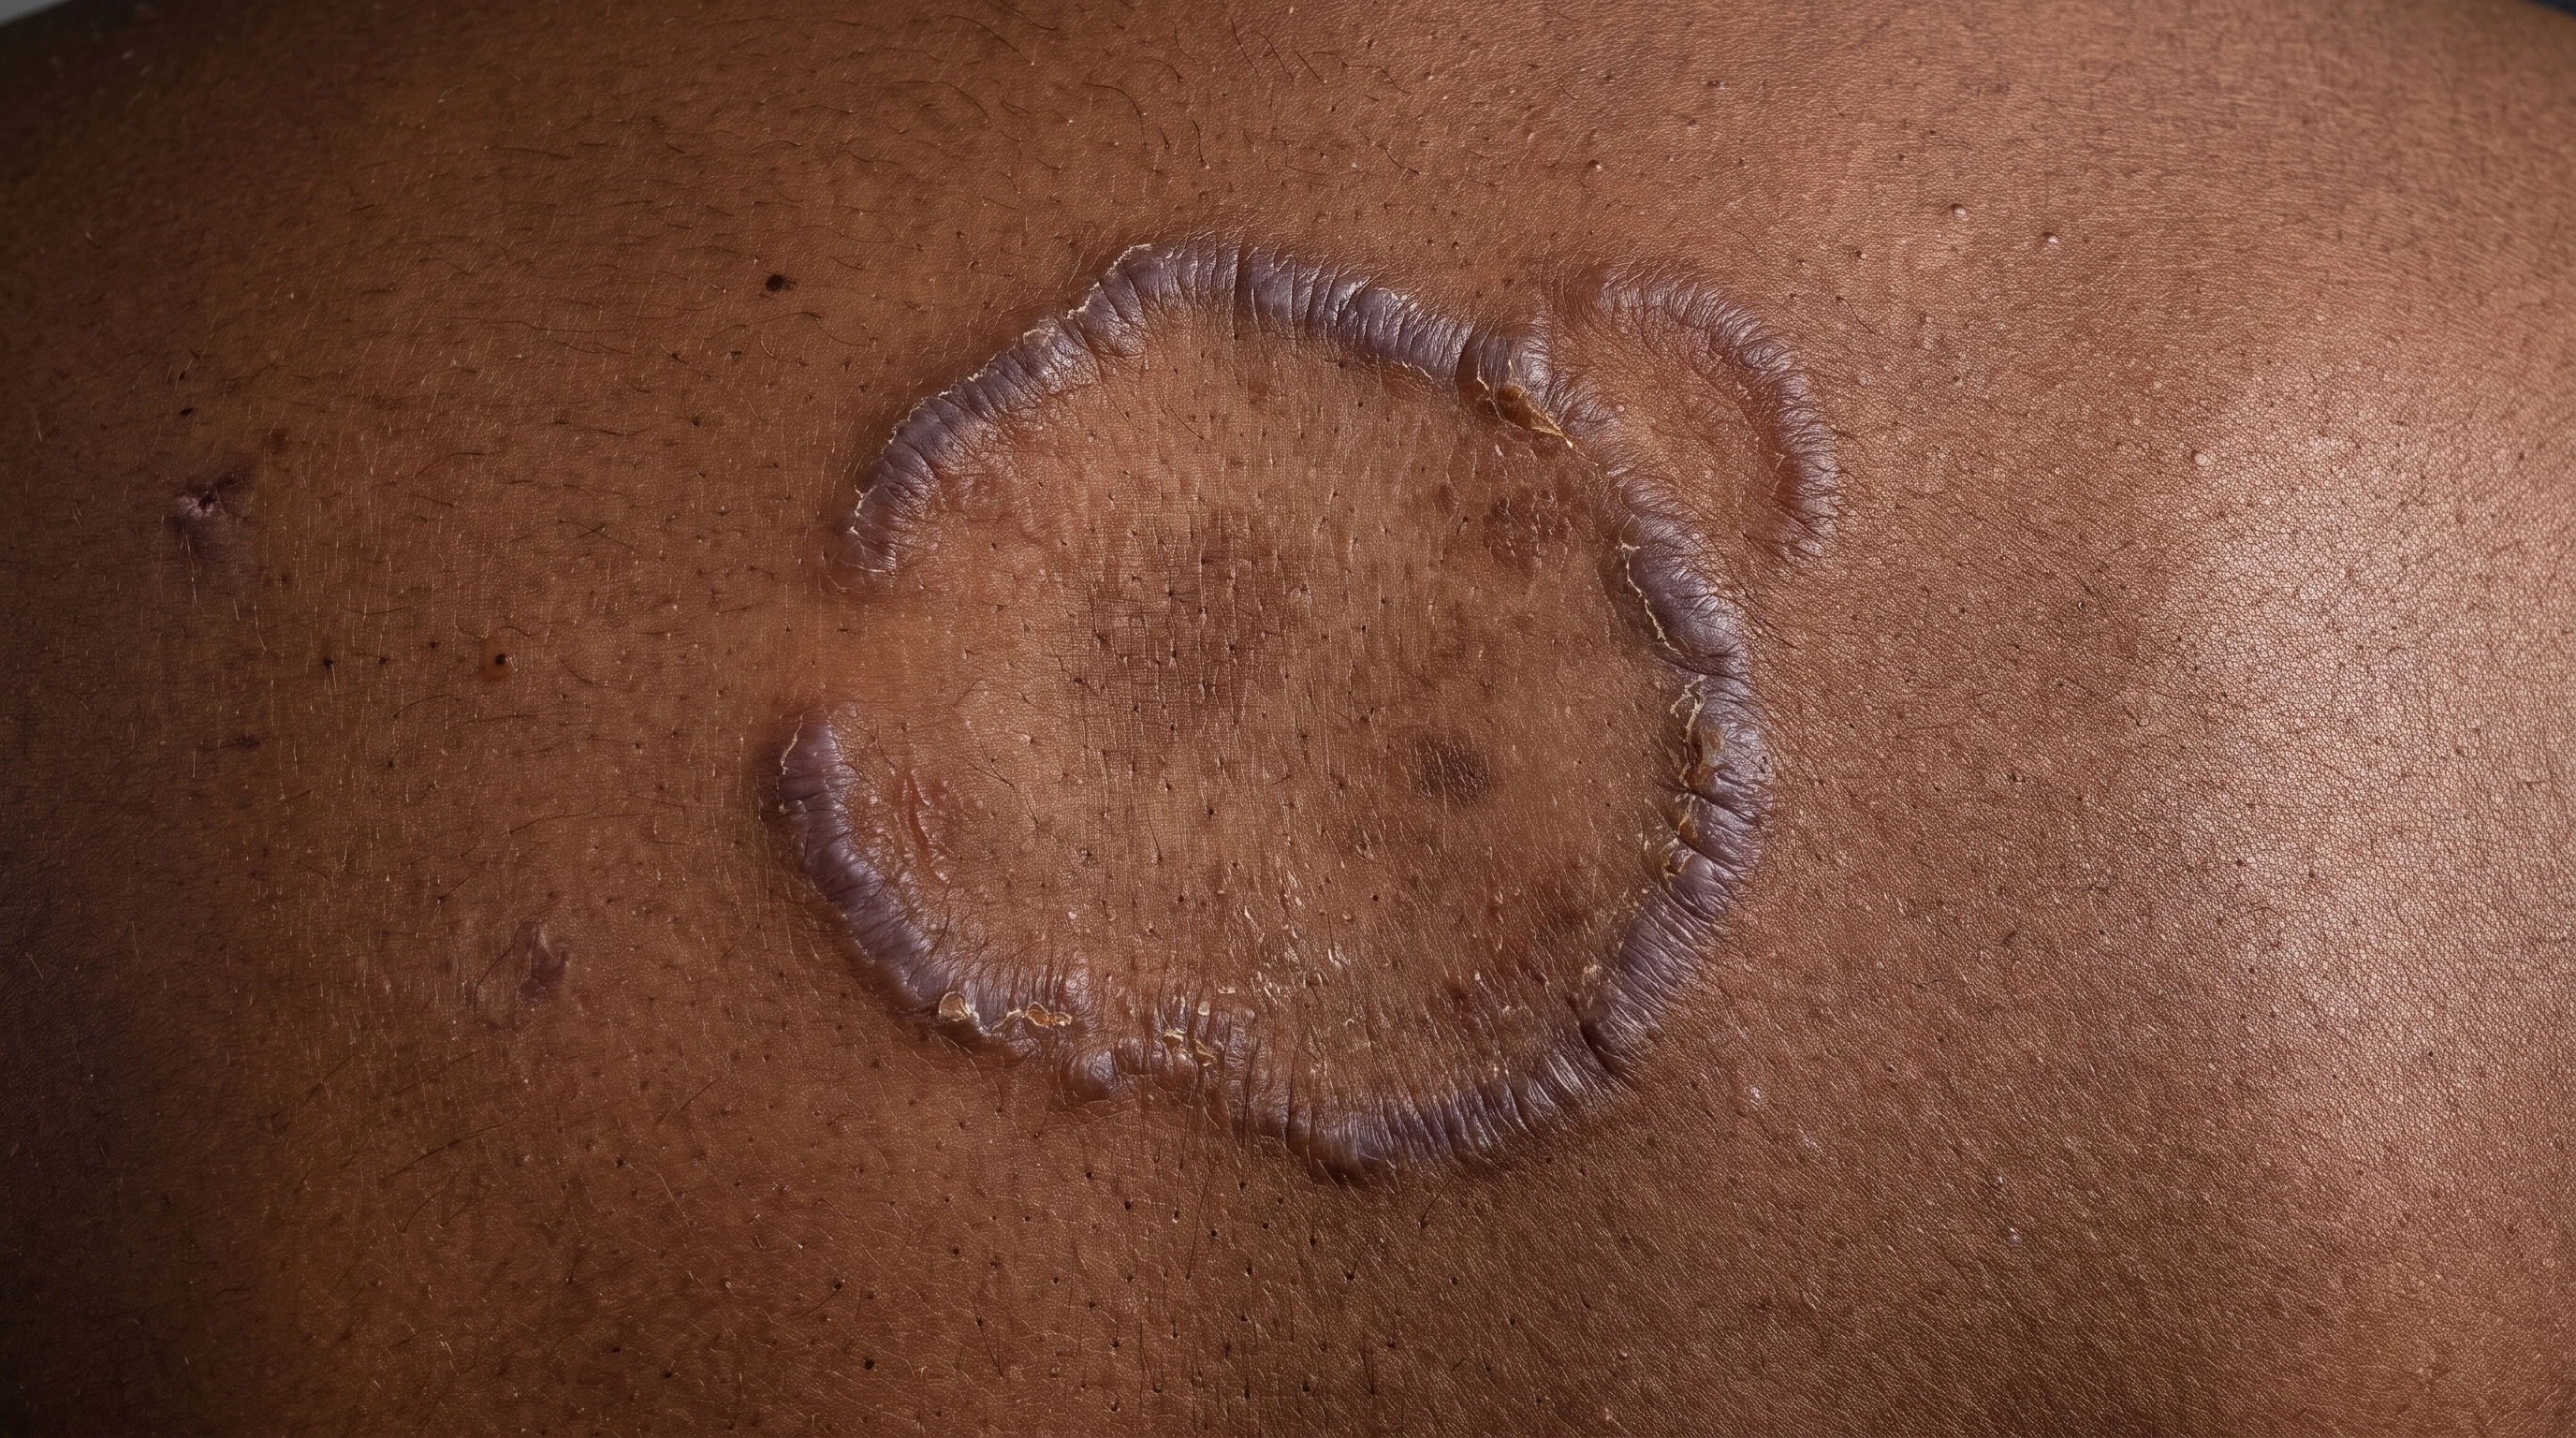
A round patch on a forearm on brown skin, with a raised scaly border a shade darker and grayer than the surrounding skin and a flatter middle. There is no redness anywhere in the patch.
A round patch on a forearm on deep dark brown skin. The raised scaly border is barely darker than the skin around it, and the flatter middle is visible mainly by its smoother texture.
Oval patches with fine collarette scale on the upper back.
Diagram
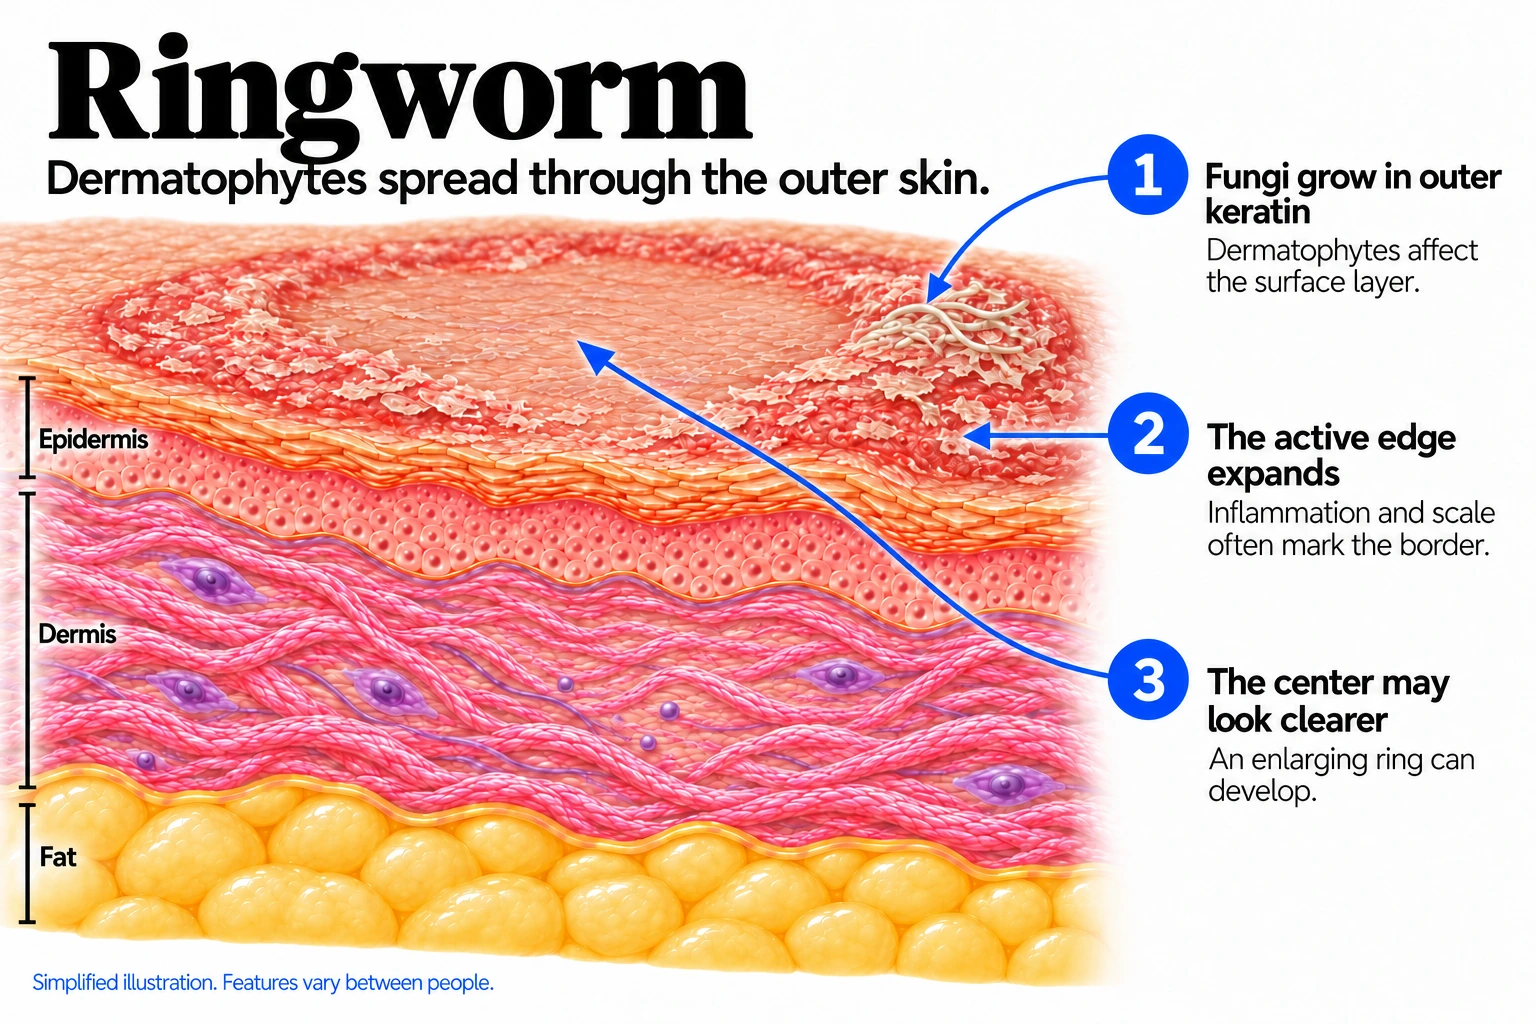
Ringworm mechanism diagram. Fungi grow in outer keratin: Dermatophytes affect the surface layer. The active edge expands: Inflammation and scale often mark the border. The center may look clearer: An enlarging ring can develop.
In the skin

Dermatophyte fungi grow in the keratin of the outer skin and spread outward. Inflammation and scale often concentrate at an expanding border, while the center may look clearer.

An inflammatory skin eruption develops for reasons that are not fully understood. A viral association is suspected, but the exact cause remains uncertain.

When it usually starts

010203040506070+

Ringworm. Can occur at any age after exposure to an infected person, animal or contaminated material.

Pityriasis Rosea. Most often affects adolescents and young adults.

Causes and triggers

Causes

Ringworm is a fungal infection of the skin's outer layer. It isn't caused by a worm; the name comes from the ring-shaped rash.

The exact cause is uncertain; a viral association is suspected.

Risk factors
Children, Contact sports, Weakened immunity, Diabetes
Adolescence or young adulthood
How it spreads
  • Skin-to-skin contact — Well established
  • Infected pets, especially cats — Well established
  • Shared towels, combs and mats — Strong link
  • Damp, warm skin — Strong link
Trigger
● Ringworm
● Pityriasis Rosea
No established short-term flare trigger
Not listed
Not a typical trigger

Daily Care

Ringworm
Pityriasis Rosea
Daily care

Habits that help

  • Wash and separate towels and bedding
    Hot wash, no sharing until it clears.
  • Have the pet checked
    Animal ringworm often shows as thin or crusty fur.
  • Shower and change soon after sport
    The single best habit if you train.
  • Keep the area dry
    Dry thoroughly, change sweaty clothes, wear loose cotton.
  • Treat the feet and nails too
    Otherwise they reseed it.
  • An over-the-counter antifungal cream
    Terbinafine, clotrimazole, miconazole, ketoconazole.
  • Apply the antifungal over the recommended margin and complete the labeled course
    Cover the affected area and the margin directed on the label. Duration differs between products and sites.

Avoid

  • Avoid: Sharing household items
    Towels, bedding, clothes or hairbrushes pass it on.
  • Avoid: Walking barefoot
    Communal showers and pool areas are a classic route.
  • Avoid: Contact sport before it is treated
    Very transmissible skin to skin.
  • Avoid: Staying in damp clothes
    Fungi need moisture. The easiest thing here to fix.
  • Avoid: Tight, occlusive clothing over the patch
    Traps heat and sweat over the fungus.
  • Avoid: Scratching
    Breaks the skin and carries fungus to new sites.
  • Avoid: Not treating the pet
    If an animal is the source, treating only people means it returns.
  • Avoid: Untreated athlete's foot or nail fungus
    A permanent source for the body.
  • Avoid: Stopping treatment when it looks clear
    Skin clears before the fungus does.
  • Avoid: Hydrocortisone 1%
    It takes the itch away for a few days, and that is exactly the problem. Steroid cream damps down the immune reaction that was holding the fungus at the edge, so the infection spreads while the rash looks better. What returns is bigger, shapeless and harder to recognize. Do not put it on an undiagnosed rash.
  • Avoid: Steroid–antifungal combinations
    Creams that mix an antifungal with a strong steroid are widely prescribed and are a poor choice for ringworm. The steroid part lets the fungus spread and thins the skin, particularly in the groin, and cure rates are lower than with an antifungal alone. If you have one at home, check the label before using it here.

Habits that help

  • Moisturize dry or itchy areas with a plain cream
    Fragrance-free products are less likely to sting inflamed skin.
  • Keep baths and showers brief and lukewarm
    Gentle washing is usually more comfortable than hot water and scrubbing.
  • Wear loose, breathable clothing
    Reduce overheating and friction if they worsen itch.
  • Use a cool damp cloth for itch relief
    Keep nails short and avoid scratching the rash.
  • Arrange review if the diagnosis is uncertain or you are pregnant
    A similar-looking rash may need testing, and pregnancy changes the assessment.

Avoid

  • Avoid: Deliberate tanning or burning to clear the rash
    Sunburn adds skin injury; discuss any light treatment with a clinician.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Ringworm
● Pityriasis Rosea
Filter by type
Ringworm location

Select one or more.

All types
Over-the-counter
Existing educational treatment illustration: Spinosad

Terbinafine cream

Strong evidence

The most effective cream you can buy for ringworm on the body, and it kills the fungus rather than just stopping it growing, so the course is shorter — often one to two weeks. Take it a couple of centimetres past the visible edge. It does not work on the scalp or the nails, where the fungus sits out of reach.


Clotrimazole or miconazole.

Clotrimazole or miconazole

Strong evidence

The familiar azole creams, sold everywhere and cheap. They work well on body ringworm, but they stop the fungus growing rather than killing it, so they are used twice a day for two to four weeks and for one to two weeks after the skin looks clear. Stopping at the point it looks better is the usual reason it returns.

Tolnaftate.

Tolnaftate

Moderate evidence

An older antifungal, most often sold as a powder or spray. It works on body and foot ringworm but more slowly than terbinafine, and it is weaker on stubborn patches. Its real use is keeping the feet and shoes dry after treatment, since untreated feet are what reseed the rest of the skin.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Avoid

It does have some antifungal activity, and it is the home remedy people ask about most. The trouble is that it clears ringworm far less reliably than a pharmacy cream, it commonly irritates the skin, and weeks spent on it are weeks the patch keeps spreading. There is no reason to choose it over a proven cream that costs about the same.

None listed
Prescription topicals
Ketoconazole — Header Image

Ketoconazole

Strong evidence

Ketoconazole 2% cream. The prescription strength of a familiar antifungal, used for body ringworm that has not cleared on an over-the-counter cream, and for larger patches. It is applied once or twice a day for two to four weeks. Like every cream, it is the wrong tool for the scalp and nails.

Ciclopirox

Strong evidence

Ciclopirox cream. A broad antifungal that also settles inflammation a little, which suits an angry, very itchy patch. It is a reasonable choice when azole creams have not worked or have irritated the skin. It still needs the full course and the same treating past the edge.

Econazole

Strong evidence

Econazole cream. A prescription azole cream used much like clotrimazole, applied once daily for two to four weeks. It has some activity against bacteria as well, which is occasionally useful in a moist fold or between the toes where both are present.

Symptom-directed treatment

Listed

A clinician may recommend an appropriate topical anti-inflammatory if itch is troublesome.

Prescription pills
Terbinafine — Header Image

Terbinafine

Moderate evidence

Terbinafine tablets. The usual tablet for ringworm that cream cannot reach — scalp infections, nails, widespread patches and stubborn cases. Typically two to four weeks for the scalp and several months for nails, because the nail has to grow out. Liver blood tests are checked for longer courses, and it interacts with a number of other medicines.

Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Moderate evidence

An equally effective alternative, often used for nails, for widespread infection and for cases that have not responded to terbinafine. It is sometimes given in pulses of one week a month. It interacts with a long list of common medicines, including statins and some heart drugs, so bring your full list to the appointment.

Illustration: Generic oral tablet bottle and tablets.

Griseofulvin

Moderate evidence

The oldest scalp treatment and still a first choice in children for some species of fungus. It needs six to twelve weeks, and it is absorbed much better when taken with a fatty meal. Newer tablets work faster, so which one is used depends on the species the lab identifies.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Moderate evidence

A once-weekly tablet, used mainly when terbinafine and itraconazole do not suit. It clears dermatophyte infections less reliably than either, so it is a second-line option here rather than a first choice, even though it is the antifungal most people have heard of.

None listed

Outlook

Long term

Untreated, ringworm expands slowly rather than resolving. Treated, it is predictable. Scalp and nail infections run much longer and need tablets — weeks for the scalp, months for nails, which have to grow out.

The rash usually clears on its own in about 6–10 weeks. Color changes can last longer, particularly after inflammation; another episode is uncommon.

Complications

Possible complications
  • Kerion and permanent hair loss
  • Ringworm hidden by steroid cream
  • Nail Fungus
More details

Kerion and permanent hair loss
Scalp ringworm can turn into a kerion — a boggy, tender, pus-oozing swelling where the immune reaction has gone deep around the hair follicles. It happens mostly in children, and it can destroy follicles and leave a permanently bald scar. Oral antifungal tablets started early are what prevent it, which is why scalp involvement is never treated with cream.

Ringworm hidden by steroid cream
Steroid cream calms the itch and flattens the edge while the fungus keeps spreading underneath. What comes back is larger, shapeless and much harder to recognize, and it is often treated as eczema for months. If a rash improved on a steroid and then grew, say so at the appointment — it changes both the diagnosis and the test.

Nail Fungus
Ringworm that reaches the nails thickens and discolors them and lifts the nail from its bed. It matters twice over: creams cannot reach fungus under a nail, so it needs months of tablets, and until it is treated it acts as a reservoir that reseeds the feet, groin and body again and again. This is one of the most common reasons ringworm keeps coming back.

Pigment changes may persist after the rash. Pregnancy warrants discussion with a clinician.

When to get help

When to get help

Seek care for widespread, recurrent or uncertain rash, or scalp involvement. Steroid cream alone can disguise and worsen a fungal infection.

Seek assessment for a first unexplained rash, pregnancy, mouth or genital lesions, or an unwell feeling.

Common questions

Ringworm:Is there actually a worm?

No. Ringworm is a fungal infection of the outer layer of skin, related to athlete's foot. The name describes the rash, named long before the cause was understood.

Ringworm:How long am I contagious?

For most body infections, much less so after a day or two of treatment. Contact sports set their own rules — wrestling commonly requires around 72 hours of treatment and the area covered. Check with your club or school rather than guessing.

Ringworm:Did my cat give it to me?

Possibly. Kittens and puppies are common sources, often with only a small patch of thin or crusty fur, or nothing. If a new pet arrived shortly before the rash, ask a vet to check it. Treating people and not the animal is a common reason it keeps returning.

Ringworm:Can I use athlete's foot cream on my body?

Yes. Same medicines — terbinafine, clotrimazole, miconazole — and the same infection elsewhere. The exception is the scalp and nails, where creams do not work whatever the tube says.

Ringworm:Why does it keep coming back?

Usually one of three reasons: treatment stopped as soon as the skin looked clear, an untreated reservoir such as athlete's foot or fungal toenails, or a steroid cream somewhere in the routine. Occasionally an infection really is resistant, which needs testing and a prescription.

Ringworm:Do I need tablets?

Not for a small patch on the body, which almost always responds to cream. Tablets are needed for scalp and nail infections, and widespread, deep or stubborn cases. That needs a doctor, partly because some oral antifungals interact with other medicines.

Pityriasis Rosea:What is Pityriasis Rosea?

A usually temporary eruption of oval scaly patches, sometimes beginning with one larger herald patch.

Pityriasis Rosea:What can I do day to day?

Use gentle washing and moisturizer; avoid overheating if it worsens itch.

Pityriasis Rosea:When should I get medical advice?

Seek assessment for a first unexplained rash, pregnancy, mouth or genital lesions, or an unwell feeling.

Sources

Sources and further reading

  1. DermNet
  2. Pityriasis rosea
Dermapedia on YouTube