Mandelic Acid vs Retinol

Mandelic Acid: Exfoliates skin; clinical evidence is mainly from professional acne peels. Retinol: Targets fine lines and photoaged texture over months.

Research updated 2026-10-25
Five mandelic acid serums and their boxes lined up on white with clear gel swatchesSix retinol products lined up, including SkinCeuticals Retinol 0.5, Murad, CeraVe, First Aid Beauty, RoC and Replenix

Which one is right for you?

Choose Mandelic Acid if…

Consider for exfoliation; evidence for acne comes mainly from supervised peels.

  • Acne-prone or darker skin wanting a gentler AHA
  • Mild texture concerns
  • Sensitive skin that stings with glycolic

Choose Retinol if…

Choose for fine lines and uneven texture; introduce slowly and judge results over months.

  • Fine lines and uneven texture
  • You want an over-the-counter retinoid
  • You can wait months for results
Use care together

Can you use both?

Alternate nights to avoid irritation.

At a glance

● Mandelic Acid
● Retinol
Type
Alpha hydroxy acid (AHA)
Vitamin A (retinoid)
What it does
Exfoliates skin; clinical evidence is mainly from professional acne peels.
Improves fine lines, tone and texture
Best for
Acne
Fine lines; uneven tone
Studied concentrations
45% professional peels in the cited acne trial.
0.1% and 0.4% retinol
When to use
Start on a few evenings weekly; increase only if comfortable.
Night
Time to results
Often 8–12 weeks in small cosmetic studies; results may be subtle
About 8–12 weeks for early changes; months for fuller benefit
Irritation
Can cause stinging, peeling or irritation; avoid active eczema and rosacea flares.
Dryness, redness or peeling can occur
Sensitive skin
Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.
Start slowly; avoid use on actively irritated skin
Available
Cosmetic or OTC products; some high-strength procedures are separate treatments.
Over the counter

What it helps

Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

Evidence level
Mandelic Acid
Retinol
Moderate evidenceSome supportive research
—
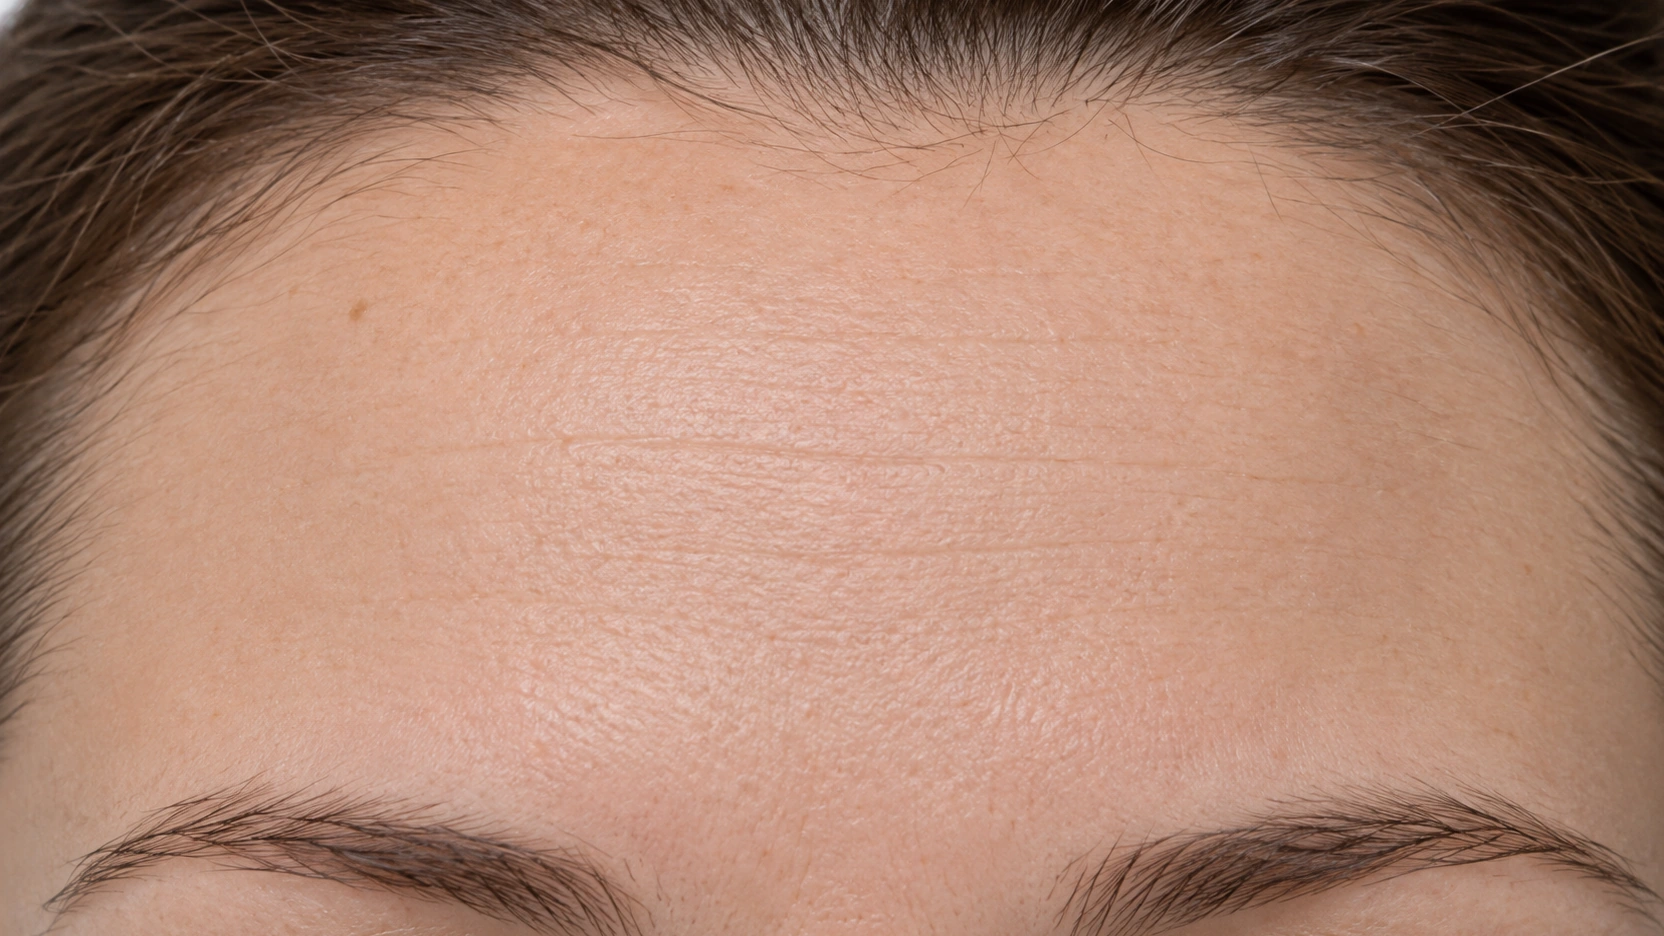
A relaxed forehead with faint shallow horizontal fine lines.

Wrinkles and Fine Lines

Controlled trials support fine-line improvement with regular use over months.
Uneven Skin Tone.

Uneven Skin Tone

Controlled studies of stabilized retinol show improvement in mottled pigmentation.
Limited evidenceEarly or small studies
Inflamed acne on light skin. The spots sit in a patch of pink, and the ring of redness around each one is easy to see. A few have a yellow-white head, and the skin between them is dry and flaking.

Acne

Professional mandelic peels improved acne in a small comparative trial.
Inflamed acne on light skin. The spots sit in a patch of pink, and the ring of redness around each one is easy to see. A few have a yellow-white head, and the skin between them is dry and flaking.

Acne

An exploratory study reported fewer lesions; evidence is less established than for acne medicines.
Oiliness.

Oiliness

An exploratory four-week study reported lower sebum levels without a retinol-free control.
Enlarged Pores on light skin.

Enlarged Pores

A small exploratory study reported improved pore measurements; permanent shrinkage is unproven.
Insufficient evidence
Flat light-brown residual marks on a fair cheek.

Post-Inflammatory Hyperpigmentation

The cited acne-peel trial does not establish reliable fading of post-acne marks.
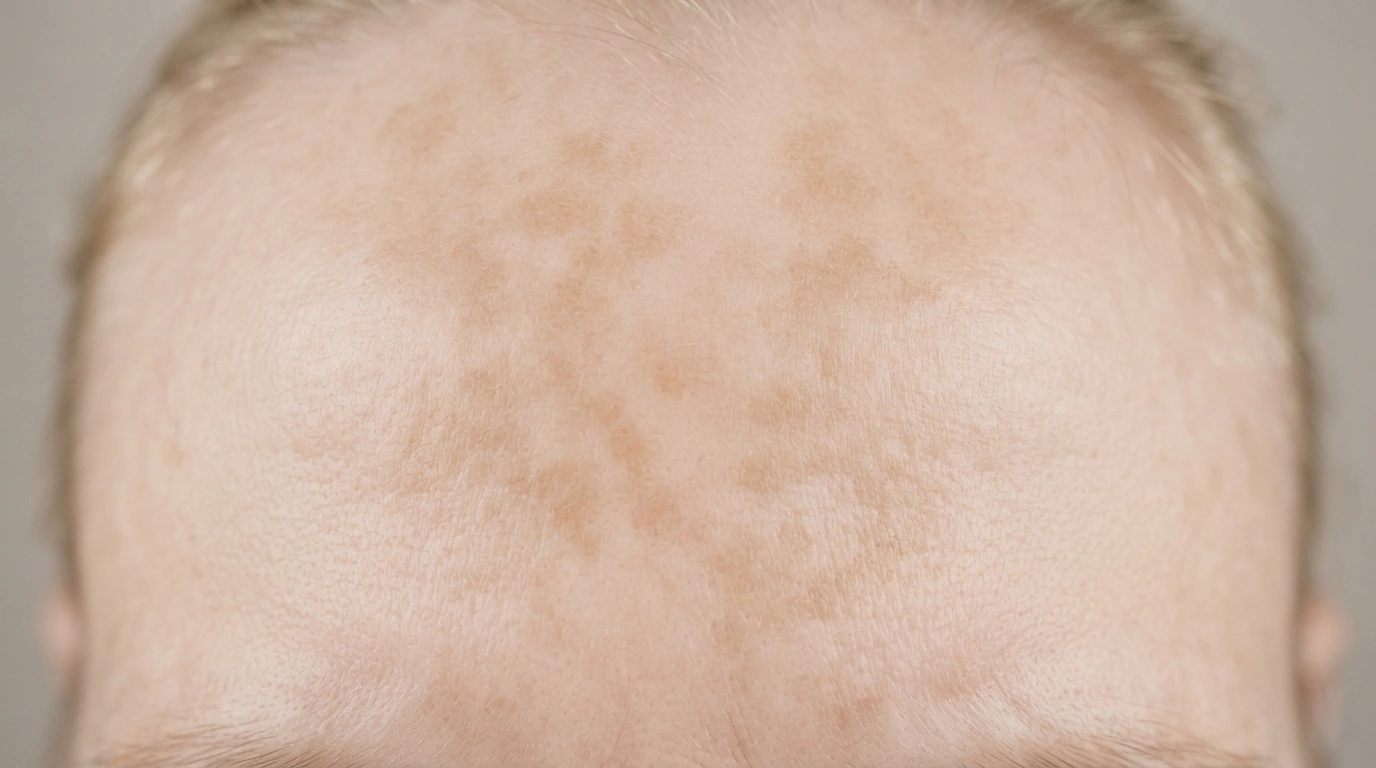
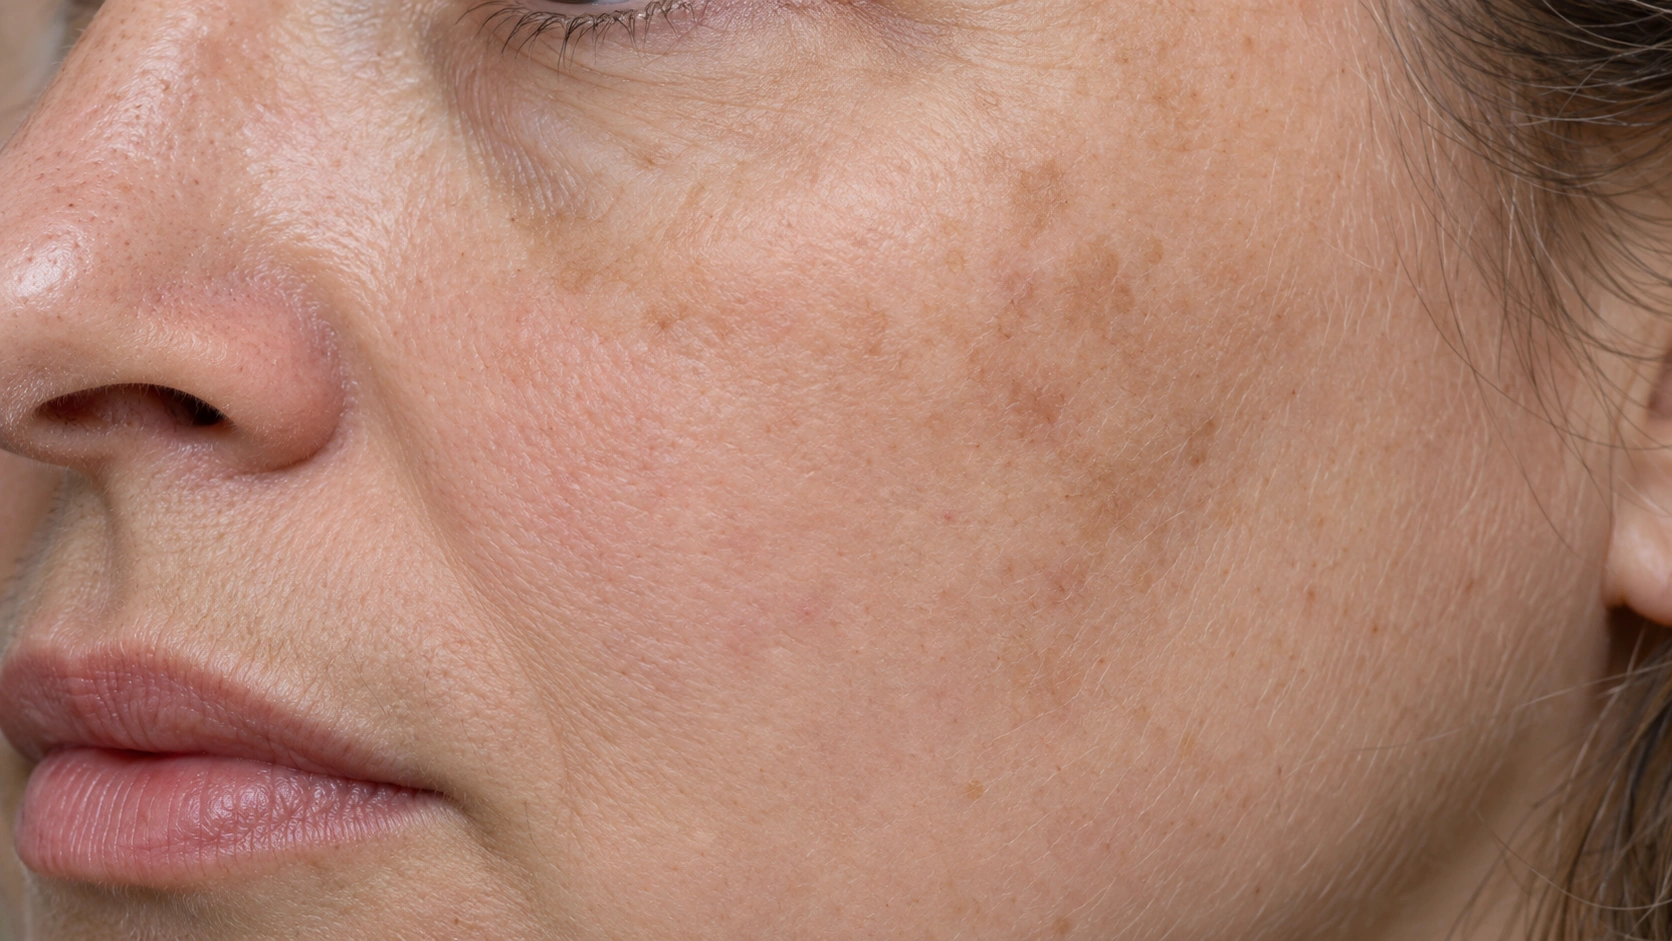
Flat tan patches with soft irregular edges across the forehead and upper cheek of an adult with light skin, the surface completely smooth.

Melasma

The reviewed sources do not establish this ingredient as a treatment for this concern.
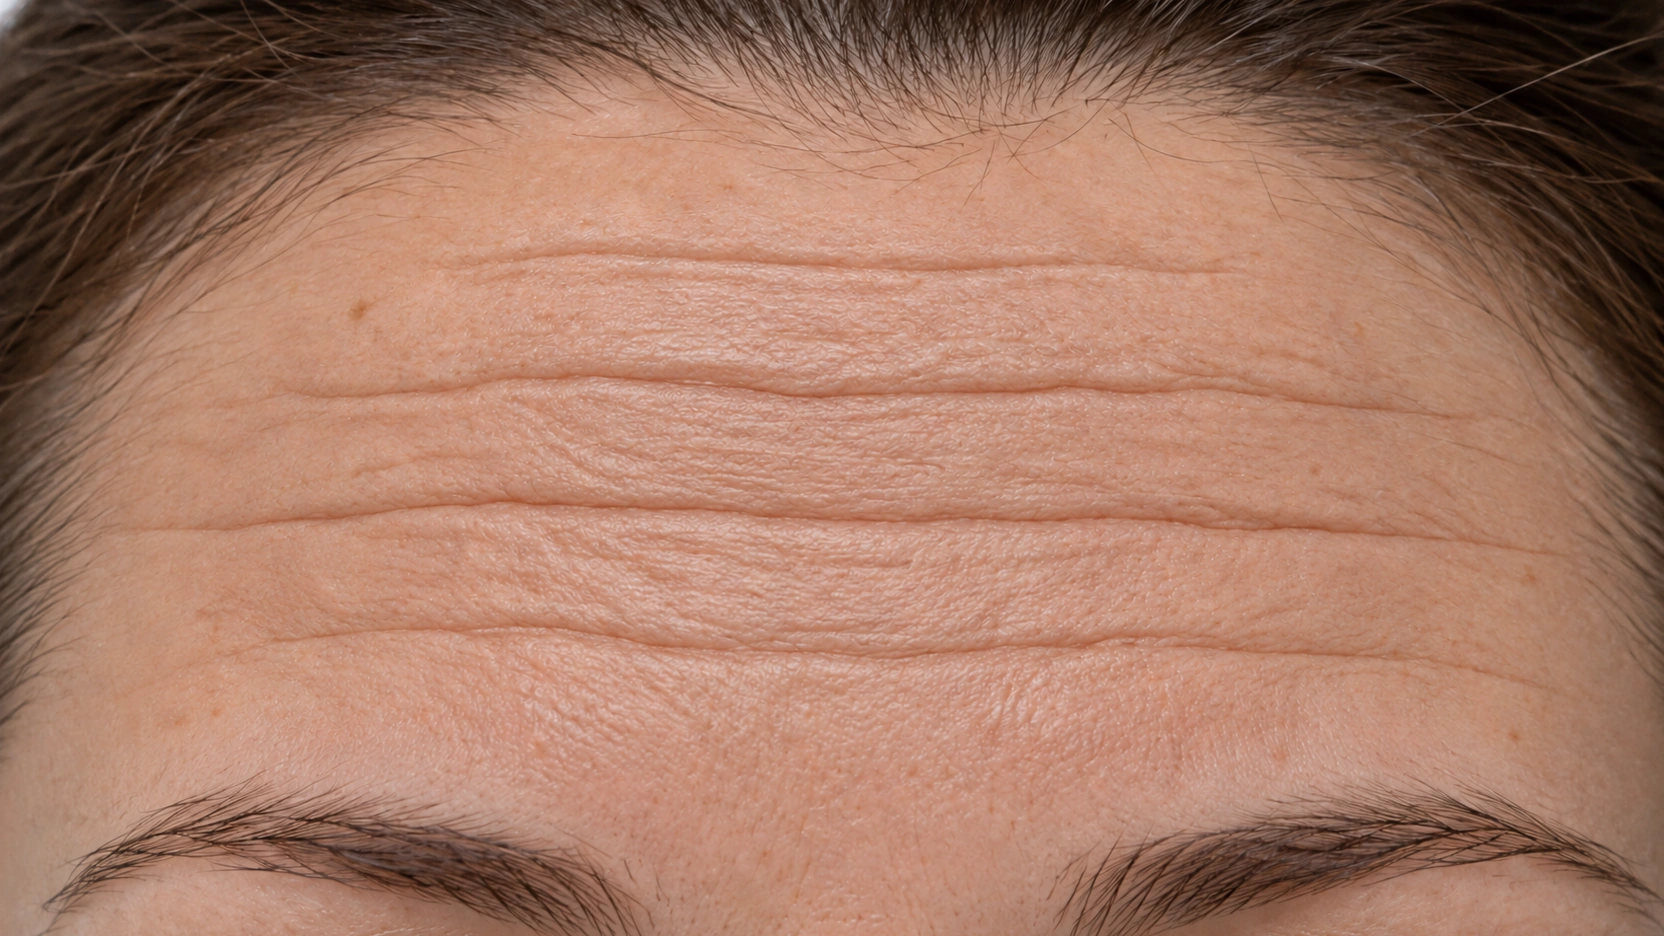
A relaxed forehead with pronounced deep horizontal furrows.

Deep Wrinkles

The reviewed sources do not establish this ingredient as a treatment for this concern.
Redness and fine superficial vessels across a light-skinned cheek and nose.

Rosacea

The reviewed sources do not establish this ingredient as a treatment for this concern.
Flat tan patches with soft irregular edges across the forehead and upper cheek of an adult with light skin, the surface completely smooth.

Melasma

Photoaging trials do not establish retinol alone as a melasma treatment.
A relaxed forehead with pronounced deep horizontal furrows.

Deep Wrinkles

Fine-line studies do not establish correction of deep folds.
Redness and fine superficial vessels across a light-skinned cheek and nose.

Rosacea

Not an established rosacea treatment; it may irritate easily flushed skin.
a very close view of irritated dry skin with fine flaking and no identifiable body part on light skin.

Barrier Support

A retinol moisturizer may hydrate, but retinol itself is not established as a barrier treatment.
Extreme close-up of light skin in an active eczema flare, too close to tell which part of the body it is. Blotchy pink-red inflammation covers the whole frame with no clear edge, with small raised bumps, fine dry scale and a few fresh scratch marks.

Eczema

Not an eczema treatment; dryness and irritation may aggravate inflamed skin.
How it works

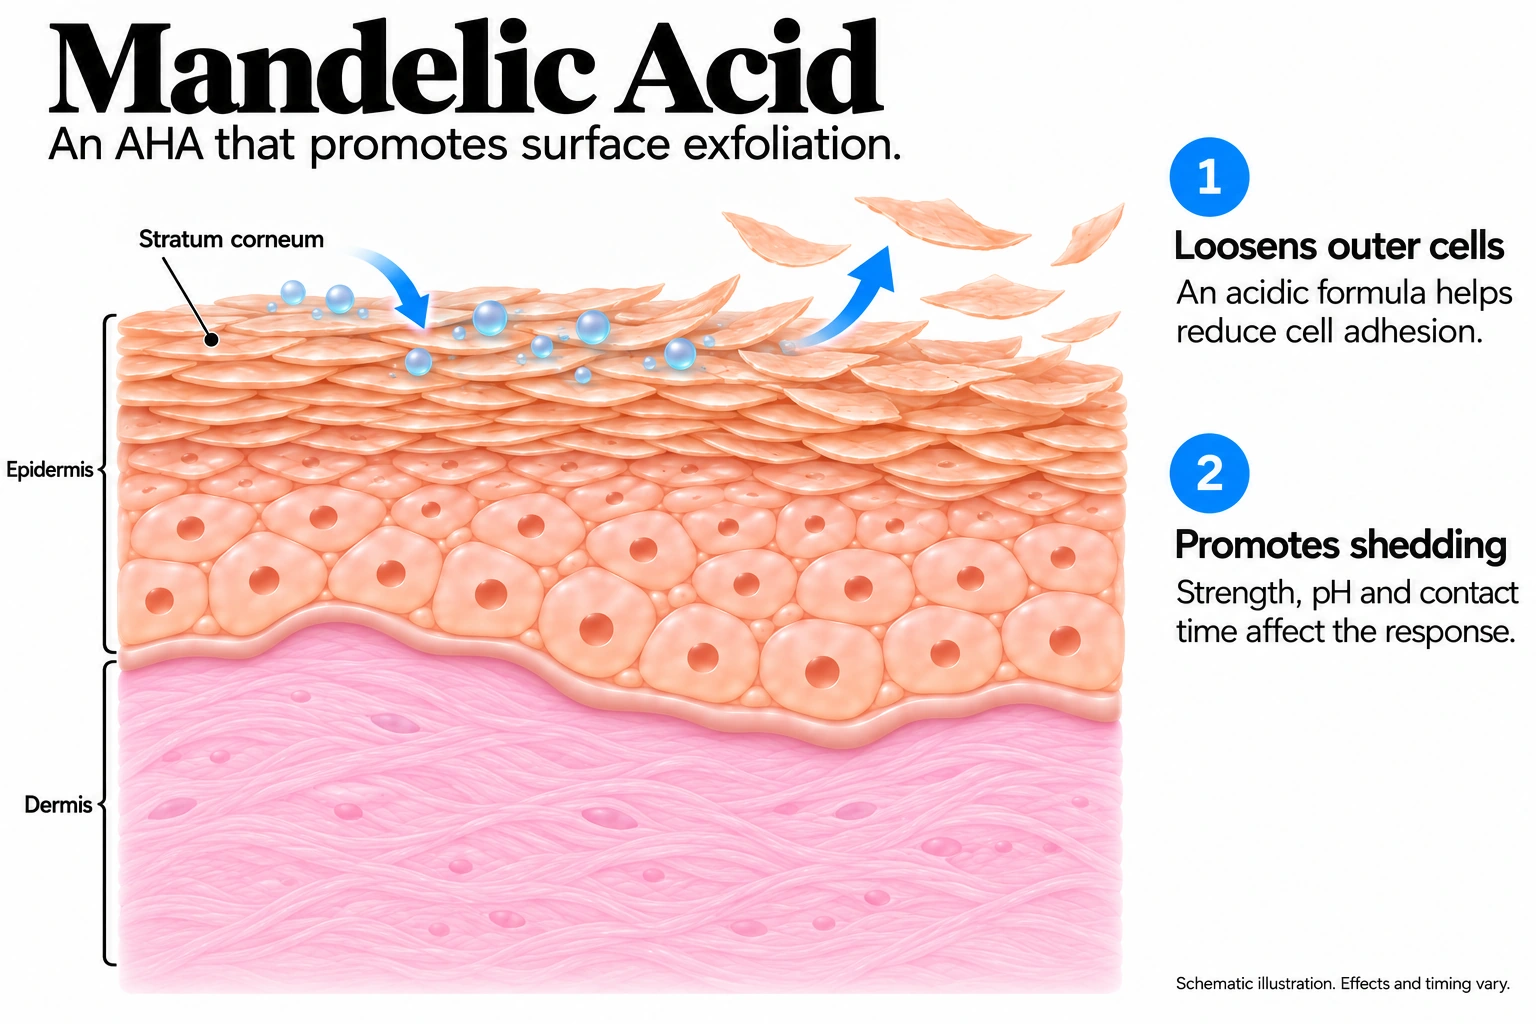
Mandelic Acid

Mandelic Acid mechanism diagram. Loosens outer cells: An acidic formula helps reduce cell adhesion. Promotes shedding: Strength, pH and contact time affect the response.
Open full-size diagram
Diagram explanation and sources

Loosens outer cells: An acidic formula helps reduce cell adhesion. Promotes shedding: Strength, pH and contact time affect the response.

Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.

Source 1 · Source 2

Retinol

Retinol mechanism diagram. Converts in the skin: Retinol becomes retinal, then retinoic acid. Changes cell activity: Retinoic acid acts through nuclear receptors. Supports collagen renewal: Studies show improved fine wrinkles with continued use.
Open full-size diagram
Diagram explanation and sources

Converts in the skin: Retinol becomes retinal, then retinoic acid. Changes cell activity: Retinoic acid acts through nuclear receptors. Supports collagen renewal: Studies show improved fine wrinkles with continued use.

Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.

Source 1 · Source 2 · Source 3 · Source 4

Using both in one routine

Built from where each one usually sits in a routine. Introduce one at a time.

Morning
Step 1
Cleanser
Step 2
Moisturizer
Step 3
Sunscreen
Night
Step 1
Cleanser
Step 2
Mandelic AcidNight
Step 3
RetinolNight
Step 4
Moisturizer

Strengths and forms

Concentrations

Mandelic acid skincare and office peels are different products. Controlled acne studies have used professional peels around 40–45%; those strengths are not a target for facial home use.

40–45%

Studied professional peels

Clinician-applied peels studied for mild-to-moderate acne. This describes specific procedures, not a recommended home concentration.

Choosing a strength: For home skincare, use the finished product’s label and your tolerance. Do not assume that a marketed serum reproduces an office peel study.

Higher strengths: Mandelic acid can still burn or irritate skin. Being described as a gentler acid does not make concentrated peels suitable for unsupervised use.

Formula matters: Acidity, vehicle and exposure time influence the effect; percentage alone cannot rank safety or compare mandelic acid with other acids.

Studied retinol strengths include 0.1%, 0.3%, 0.4% and 1%. The finished formula and your skin’s tolerance matter more than choosing the highest number.

0.1%

0.3–0.4%

1%

Lower-strength studied formula

Stabilized formulas have improved signs of sun damage in controlled trials. A low percentage can still be active.

Intermediate studied formulas

Studied for skin aging. These are examples from particular formulas, not interchangeable doses or a required next step.

Higher studied formula

Studied in a skin-remodeling model; it was not clearly better than 0.3% in that study. More is not automatically better.

Choosing a strength: Choose a well-formulated product you can use comfortably; introduce it gradually. Retinol, retinaldehyde and prescription retinoids do not have equivalent percentages.

Higher strengths: Do not increase strength while skin is persistently dry, red or stinging. A high-strength label does not guarantee better results.

Formula matters: Stability, packaging and delivery affect performance. Local cosmetic concentration limits differ; study strengths are not a statement that every product is permitted everywhere.

Forms
Serum · Toner · Peel
Serum · Cream · Eye cream

When you’ll see results

Approximate windows, not promises.

● Mandelic Acid
● Retinol
First few weeks

First few weeksAssess tolerance and texture; immediate softness can come from the base formula.

First few weeksAssess comfort. Dryness or peeling can occur; irritation is not required for benefit.

4–8 weeks

4–8 weeksSubtle changes may appear in some tested products; evidence varies.

4–8 weeksSome tested formulas showed early changes in texture or pigmentation.

8–12 weeks

8–12 weeksCompare photographs in the same lighting and reassess benefit.

8–12 weeksReassess tone and texture; fine-line changes may still be subtle.

3–6 months

3–6 monthsPhotoaging trials often need several months; expect modest rather than dramatic change.

3–6 monthsA useful period to assess fine lines; a 24-week controlled trial supports benefit.

6–12 months

6–12 monthsLong-term evidence is limited for many cosmetic actives; continue only if useful.

6–12 monthsA 52-week study of stabilized 0.1% retinol found continued improvement.

Safety and sensitive skin

Common reactions

Can cause stinging, peeling or irritation; avoid active eczema and rosacea flares.

Dryness, redness, peeling or stinging may occur, especially when introduced too quickly. Irritation can leave dark marks in some skin tones.

When to stop

Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.

Pause for persistent burning or a painful rash. Stop and seek advice for swelling, blistering or signs of an allergic reaction.

Sensitive or inflamed skin

Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.

Introduce slowly on comfortable skin. Active rosacea, eczema or a damaged barrier may need treatment before adding a retinol product.

Important limits

Do not use a cosmetic product as a substitute for diagnosis of an unexplained, changing or persistent skin problem.

Cosmetic retinol is not interchangeable with prescription retinoids, and higher strength does not guarantee a better result.

Pregnancy

Low-strength leave-on acids are generally considered acceptable; avoid peels and ask the clinician managing your pregnancy.

Not covered in this guide yet
Pregnancy & breastfeeding
Not covered in this guide yet

Avoid retinol during pregnancy; discuss alternatives when planning pregnancy. Ask your clinician about breastfeeding use and avoid application where an infant could contact it.

How it works

In the skin

On the skin. The finished product delivers mandelic acid in a particular vehicle.

Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.

Conversion. No activation step is established as necessary for its intended topical role.

Skin response. Promotes shedding of surface cells; formula acidity and contact time influence irritation and effect.

Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.

On the skin. An oil-soluble vitamin used in creams and serums.

Entering skin. It must leave the formula and cross the outer skin barrier.

Conversion. Skin converts retinol to retinal, then to retinoic acid, which acts at nuclear receptors.

Skin response. Retinoic-acid signaling changes skin-cell activity, supporting improvements in texture.

Additional effects. Trials show improvements in fine wrinkles and markers of collagen production.

Getting in
Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Below the 500 Da guideline. Delivery depends on the formula, stability and skin condition.
Molecule size
Mandelic Acid · 152 Da
Retinol · 286 Da
Smaller than 500 Da passes the outer skin more easily. Size isn’t an effectiveness score.
500 Da guideline

Product examples

Mandelic Acid
  • The Ordinary Mandelic Acid 10% + HA
  • Naturium The Energizer Mandelic Acid Body Wash
  • Paula's Choice Skin Perfecting 6% Mandelic Acid + 2% Lactic Acid
Retinol
  • RoC Retinol Max Hydration Cream — The same undisclosed retinol as the rest of the Correxion line, in a richer base and the same jar.
  • Neutrogena Rapid Wrinkle Repair Retinol Regenerating Cream — A cheap retinol cream that will not tell you its strength — in a jar, and fragranced.

Common questions

Mandelic Acid:What should I choose mandelic acid for?

Consider for exfoliation; evidence for acne comes mainly from supervised peels.

Mandelic Acid:How strong is the evidence?

A 50-person, 12-week trial compared 45% mandelic with 30% salicylic peels. It had no vehicle arm and does not establish the benefit of 5–10% home serums.

Retinol:Is retinol the same as tretinoin?

No. Retinol is converted through retinal to retinoic acid in skin. Tretinoin is retinoic acid; their percentages and clinical evidence are not interchangeable.

Retinol:Does retinol have to cause peeling?

No. Peeling is a possible adverse effect, not a requirement for benefit. Reduce frequency or pause if skin remains irritated.

Retinol:Is 1% better than 0.1%?

A higher percentage is not a reliable promise of a better result. Stability, formulation, tolerance and how consistently you can use the product all matter.

Retinol:Can retinol replace an acne medicine?

Not automatically. Retinol-specific acne evidence is limited compared with established acne retinoids. Painful, persistent or scarring acne needs appropriate medical care.

Retinol:Can I use retinol during pregnancy?

Avoid retinol during pregnancy. Review alternatives with your clinician, including when planning pregnancy or considering use while breastfeeding.

Sources

Sources and further reading

  1. Comparative study of efficacy and safety of 45% mandelic acid versus 30% salicylic acid peels in mild-to-moderate acne vulgaris. (2020)
  2. FDA alpha-hydroxy acid sun-sensitivity guidance
  3. 4% retinol and fine wrinkles
  4. 1% stabilized retinol and photodamage
  5. 1% stabilized retinol and photodamage
  6. Retinol, acne and pores
  7. American Academy of Dermatology
  8. American Academy of Dermatology
  9. The 500 Dalton rule
  10. NIST Chemistry WebBook
  11. Randomized study of 40% mandelic acid versus 30% salicylic acid peels
  12. FDA: professional supervision for chemical peels
  13. Comparison of 0.3% and 1% retinol in photodamaged skin
  14. EU Regulation 2024/996: cosmetic concentration restrictions
Dermapedia on YouTube