Ingrown Hairs vs Molluscum Contagiosum

An ingrown hair is a hair that curls back into the skin instead of growing out of it, leaving a tender bump. It is most common and most stubborn in coarse, tightly curled hair, where it has a name of its own: pseudofolliculitis barbae, better known as razor bumps. Molluscum contagiosum is a common viral skin infection that causes small, firm, dome-shaped bumps with a dimple in the middle. It is harmless, it spreads easily among children, and it clears on its own - though that can take a year or more.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
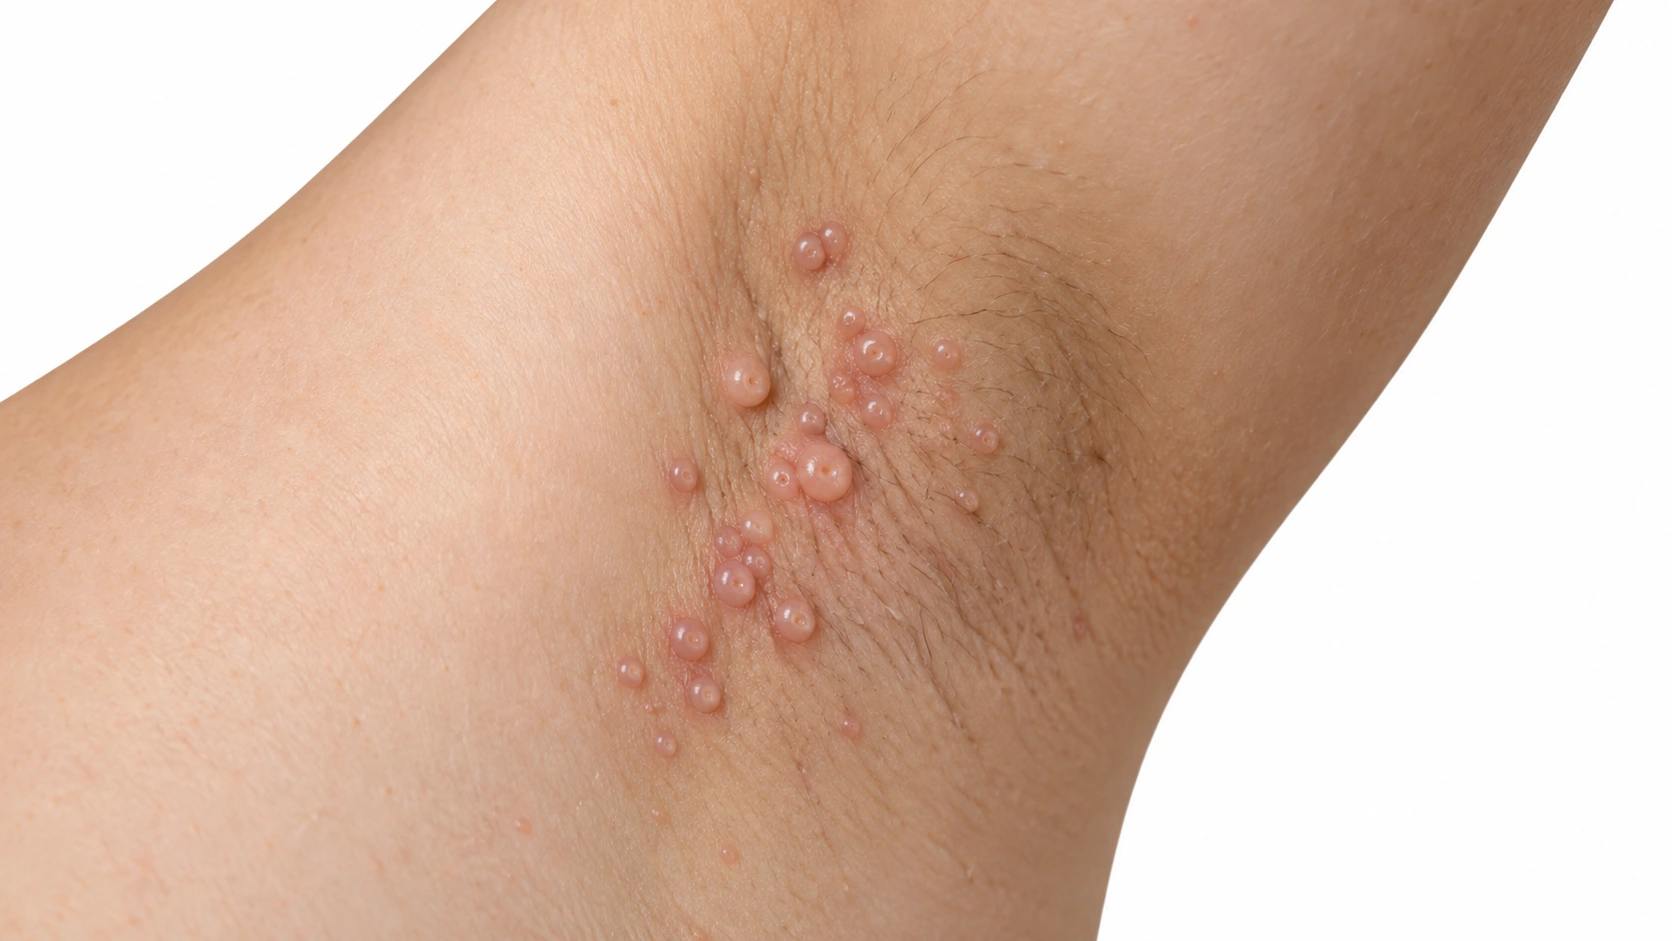
A few firm pink bumps scattered under the jaw and along the upper neck on light skin, with a dark loop of hair visible over one of them.A cluster of firm, dome-shaped pink and pearly white bumps on the side of a child's trunk on light skin, each two to five millimetres across with a small dip in the center.

Key differences

The same eight facts on every condition comparison.

Usual age
After puberty
Young children
Where
Beard, legs, armpits, bikini line
Trunk, arms, legs, folds
Main sign
Tender bumps at shaved hairs
Firm pearly bumps with a central dimple
Itch or pain
Tender, itchy
Sometimes itchy
Contagious
No
Yes
Long term
Recur with shaving
Clears on its own in months to a year or two
Scars
Dark marks and keloids possible
Rarely
Who gets it
Coarse, curly hair; shavers
Children; eczema skin

What is it?

Ingrown Hairs
Molluscum Contagiosum
What is it?

A hair grows back into skin.
A curved or sharply cut hair pierces the skin or follicle wall.

The skin reacts to it.
The body treats the embedded hair as foreign material.

Curly hair is more prone.
Coarse, curved hair increases risk, but any hair type can be affected.

Deep lumps need assessment.
Painful lumps, drainage or scarring may signal infection or another disorder.

It is a poxvirus infection.
It produces small firm bumps, often with a central dip.

It is common in children.
In healthy people it usually clears without treatment.

It spreads by contact.
Skin contact, shared objects and scratching can spread it.

Some cases need review.
Genital lesions, or many large lesions in an adult, warrant assessment.

What it looks like

Ingrown Hairs

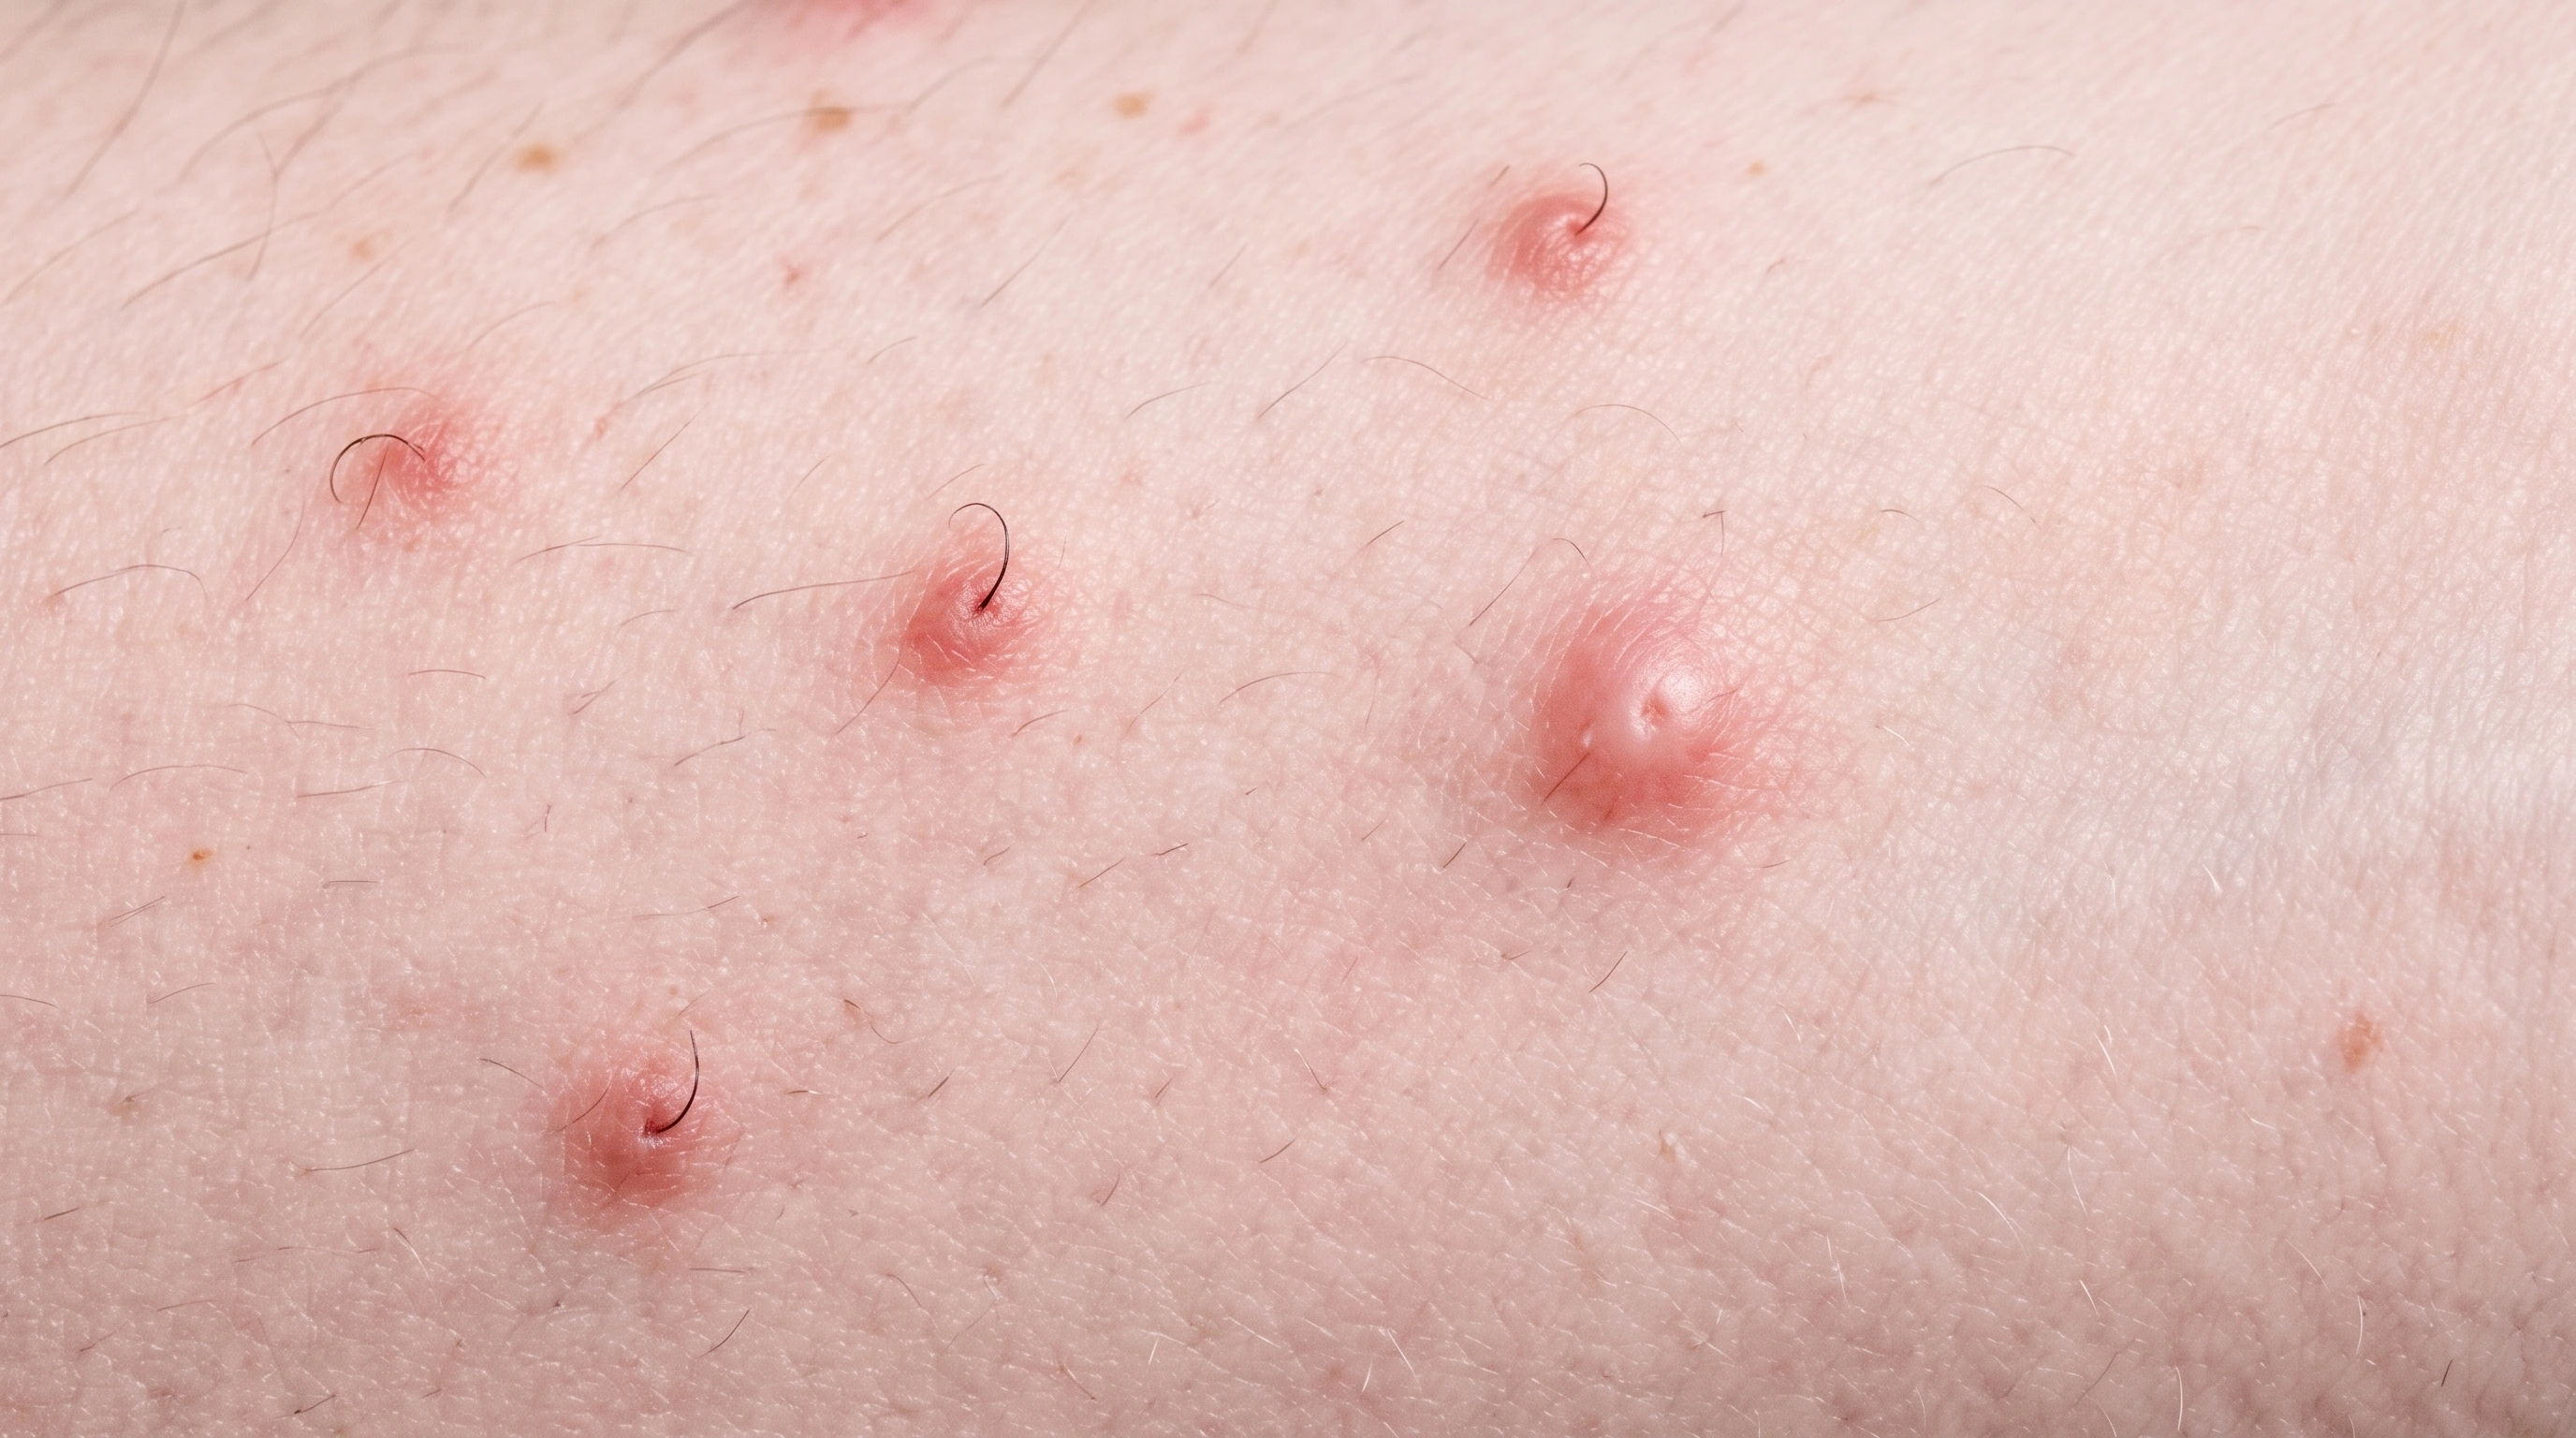
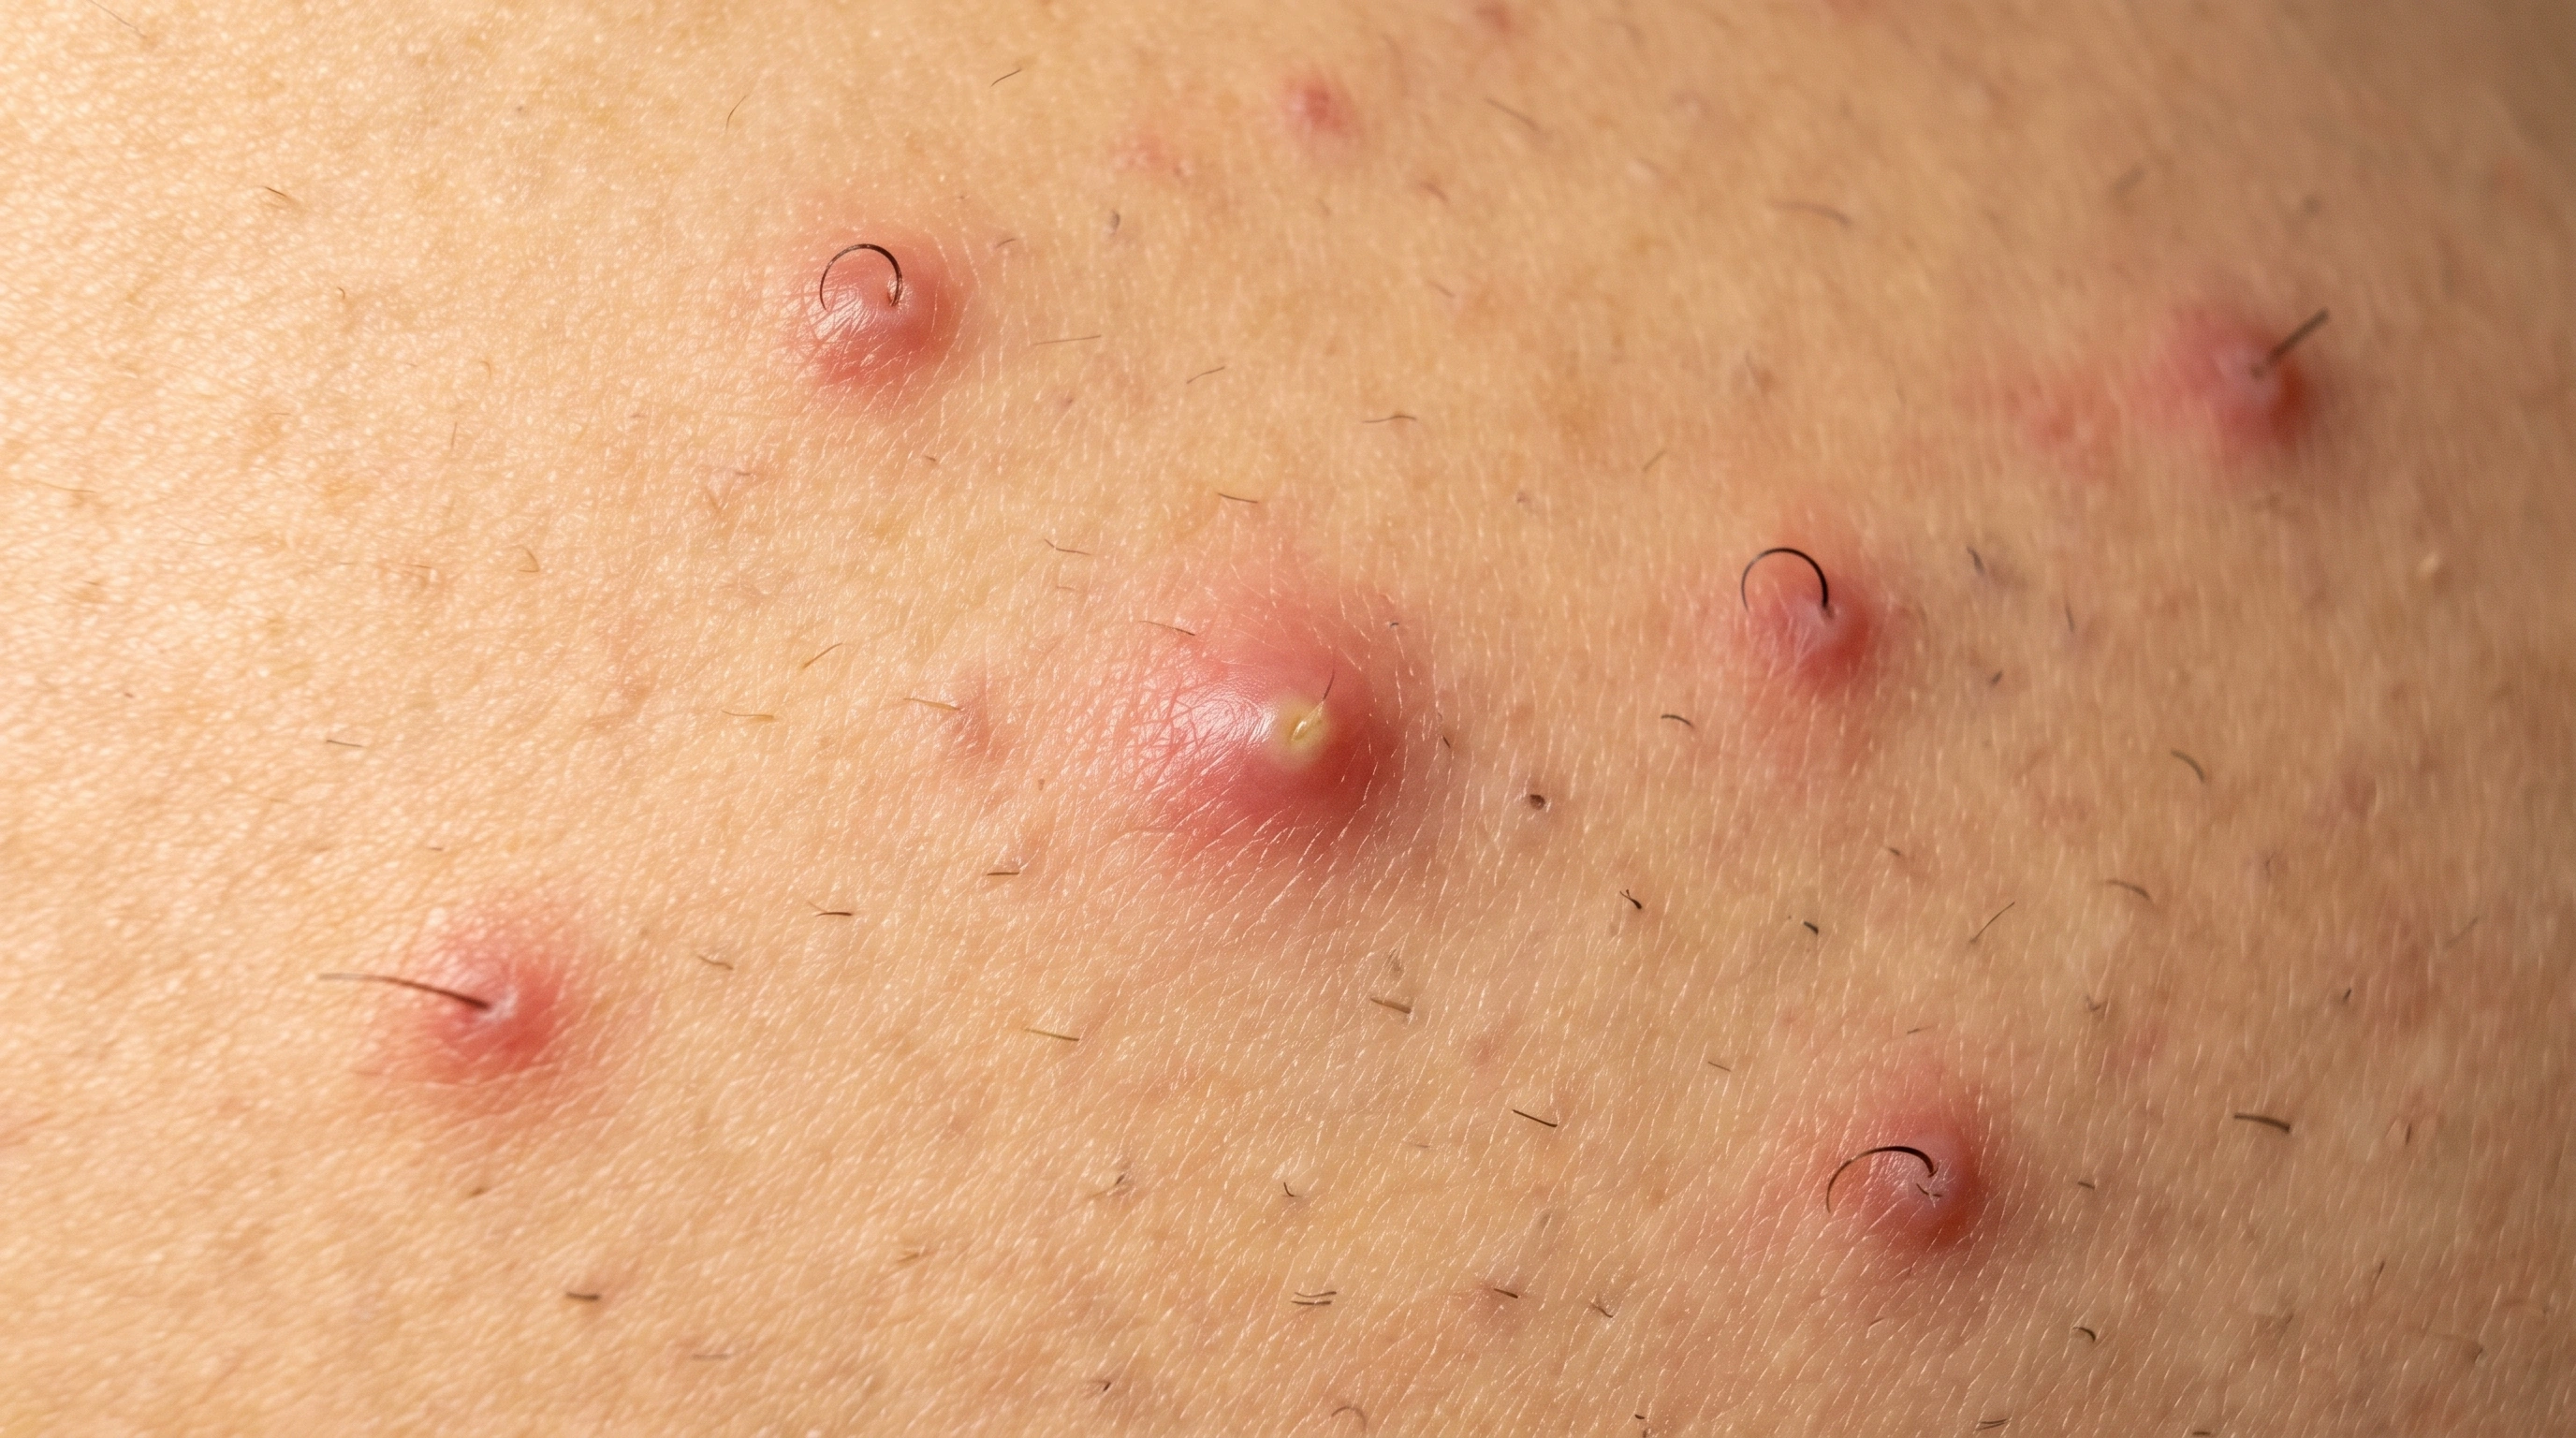
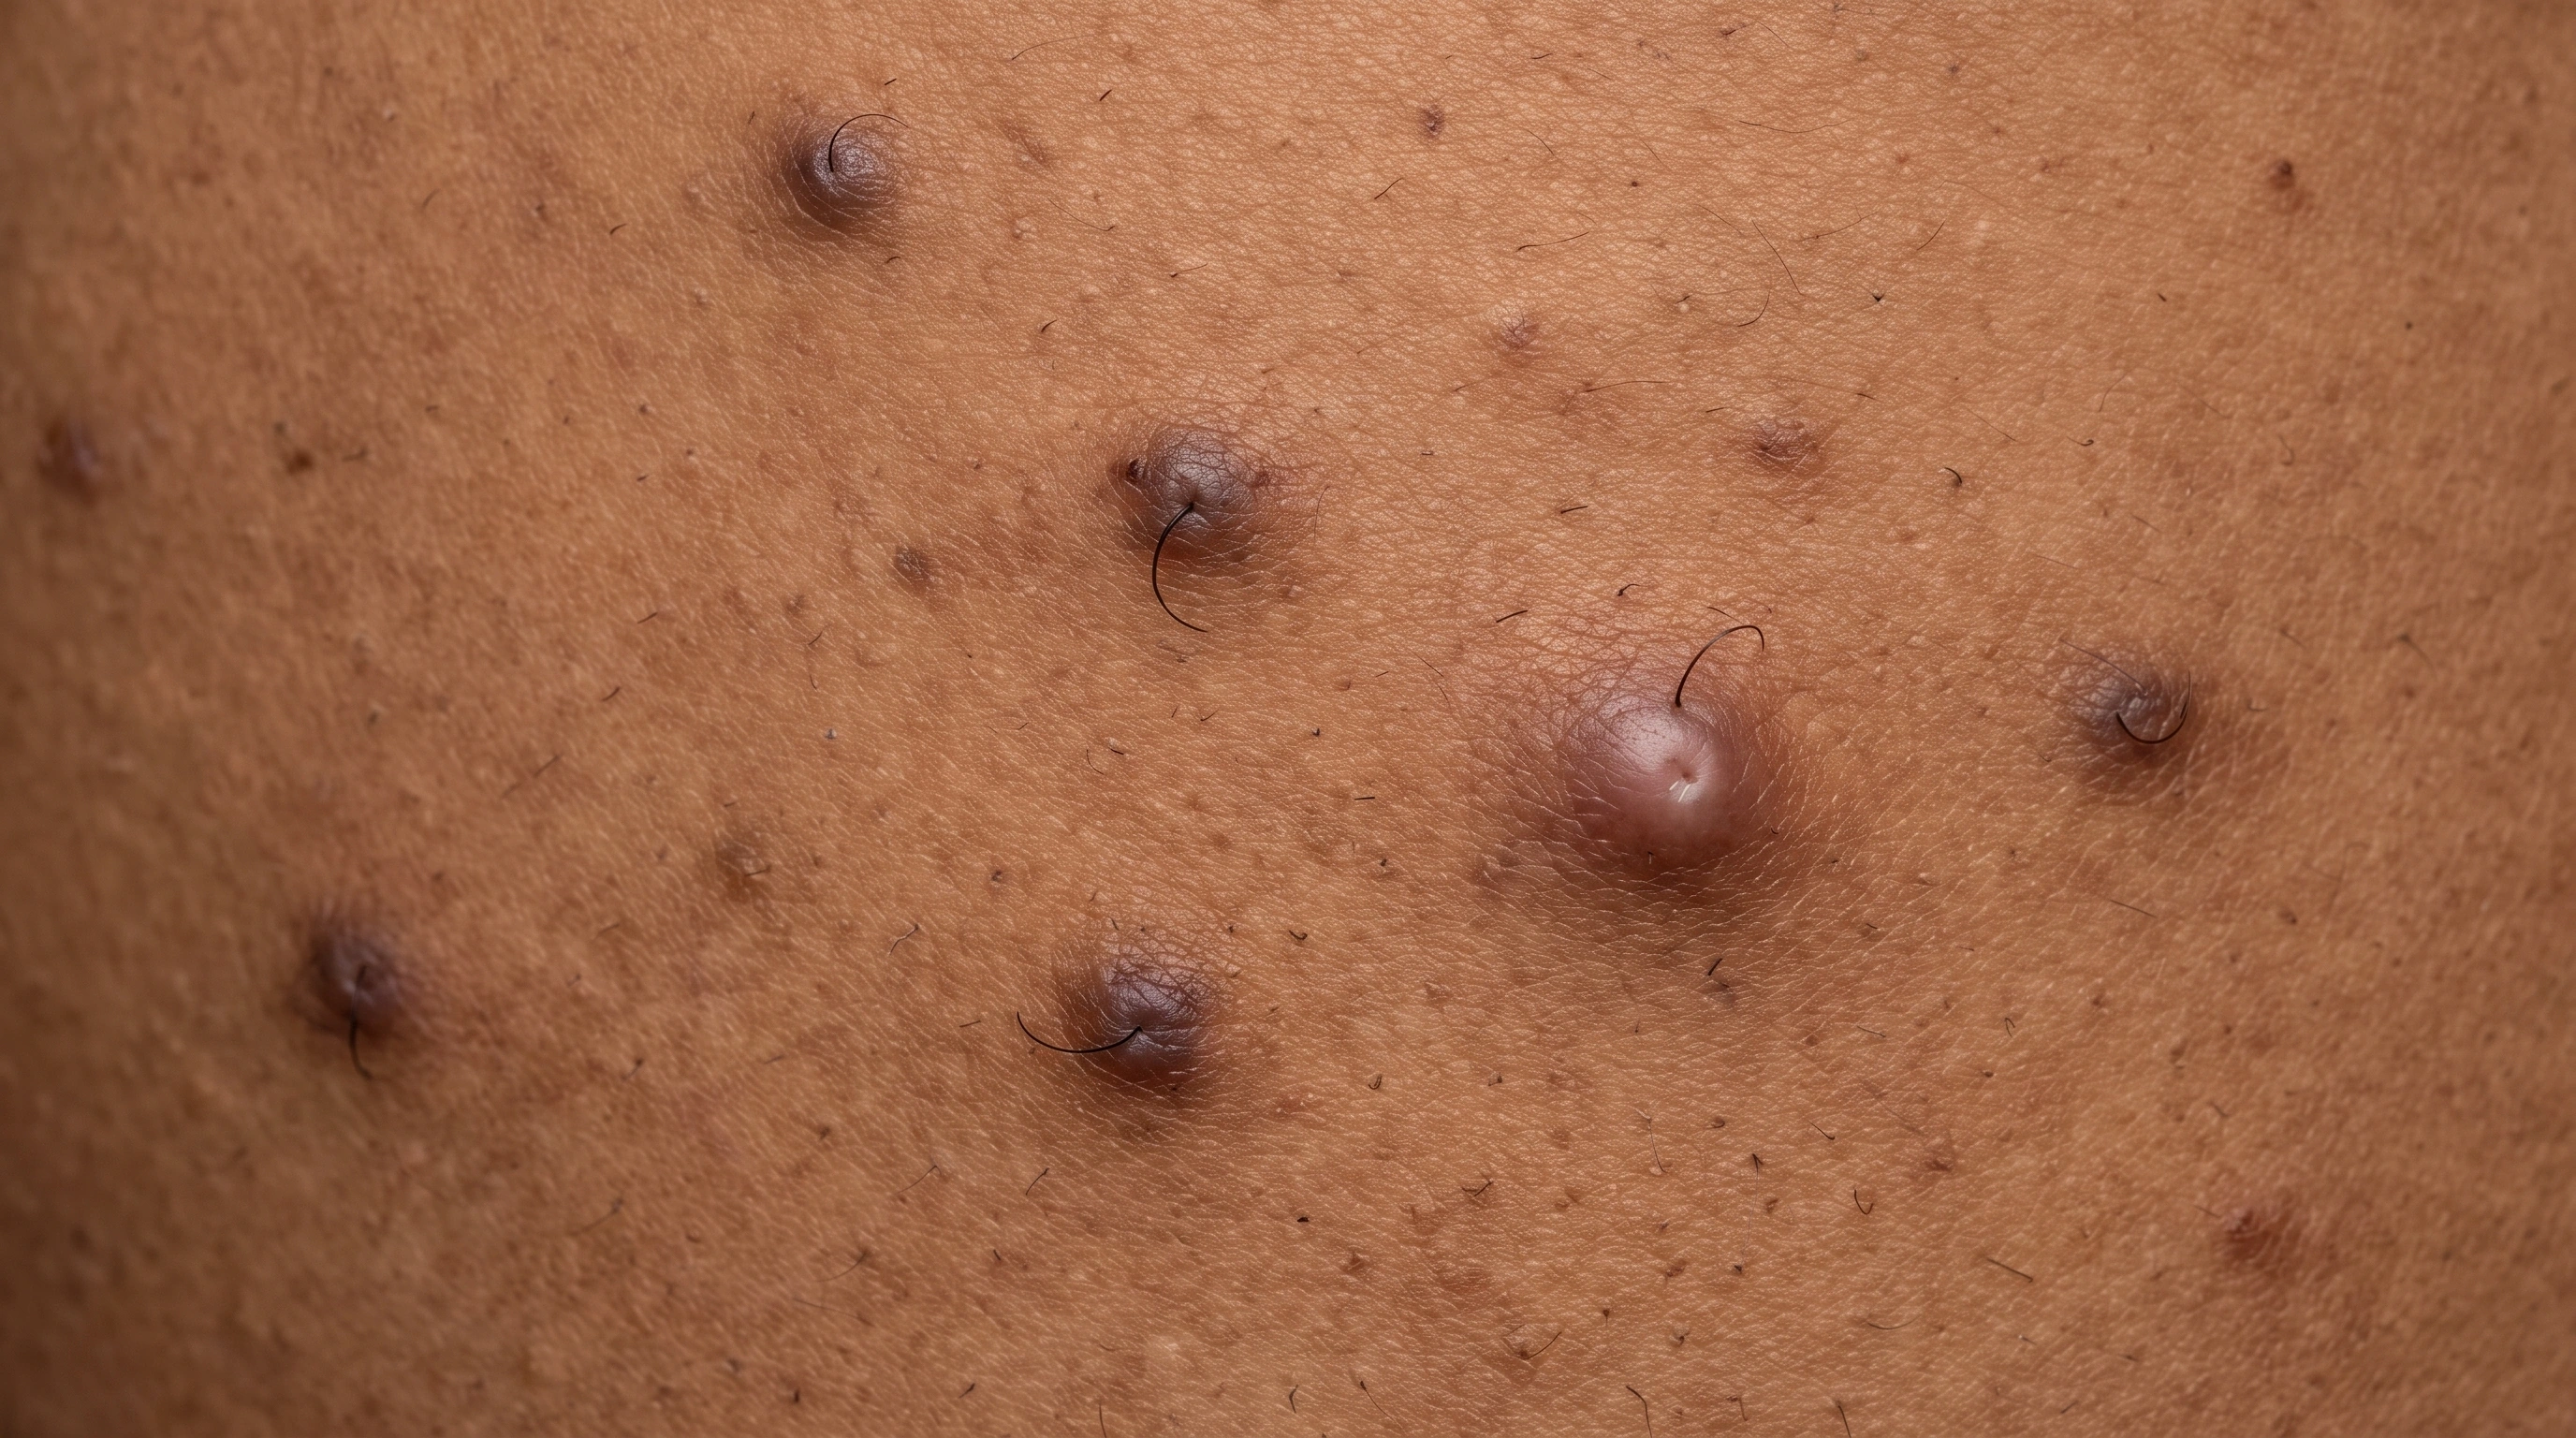
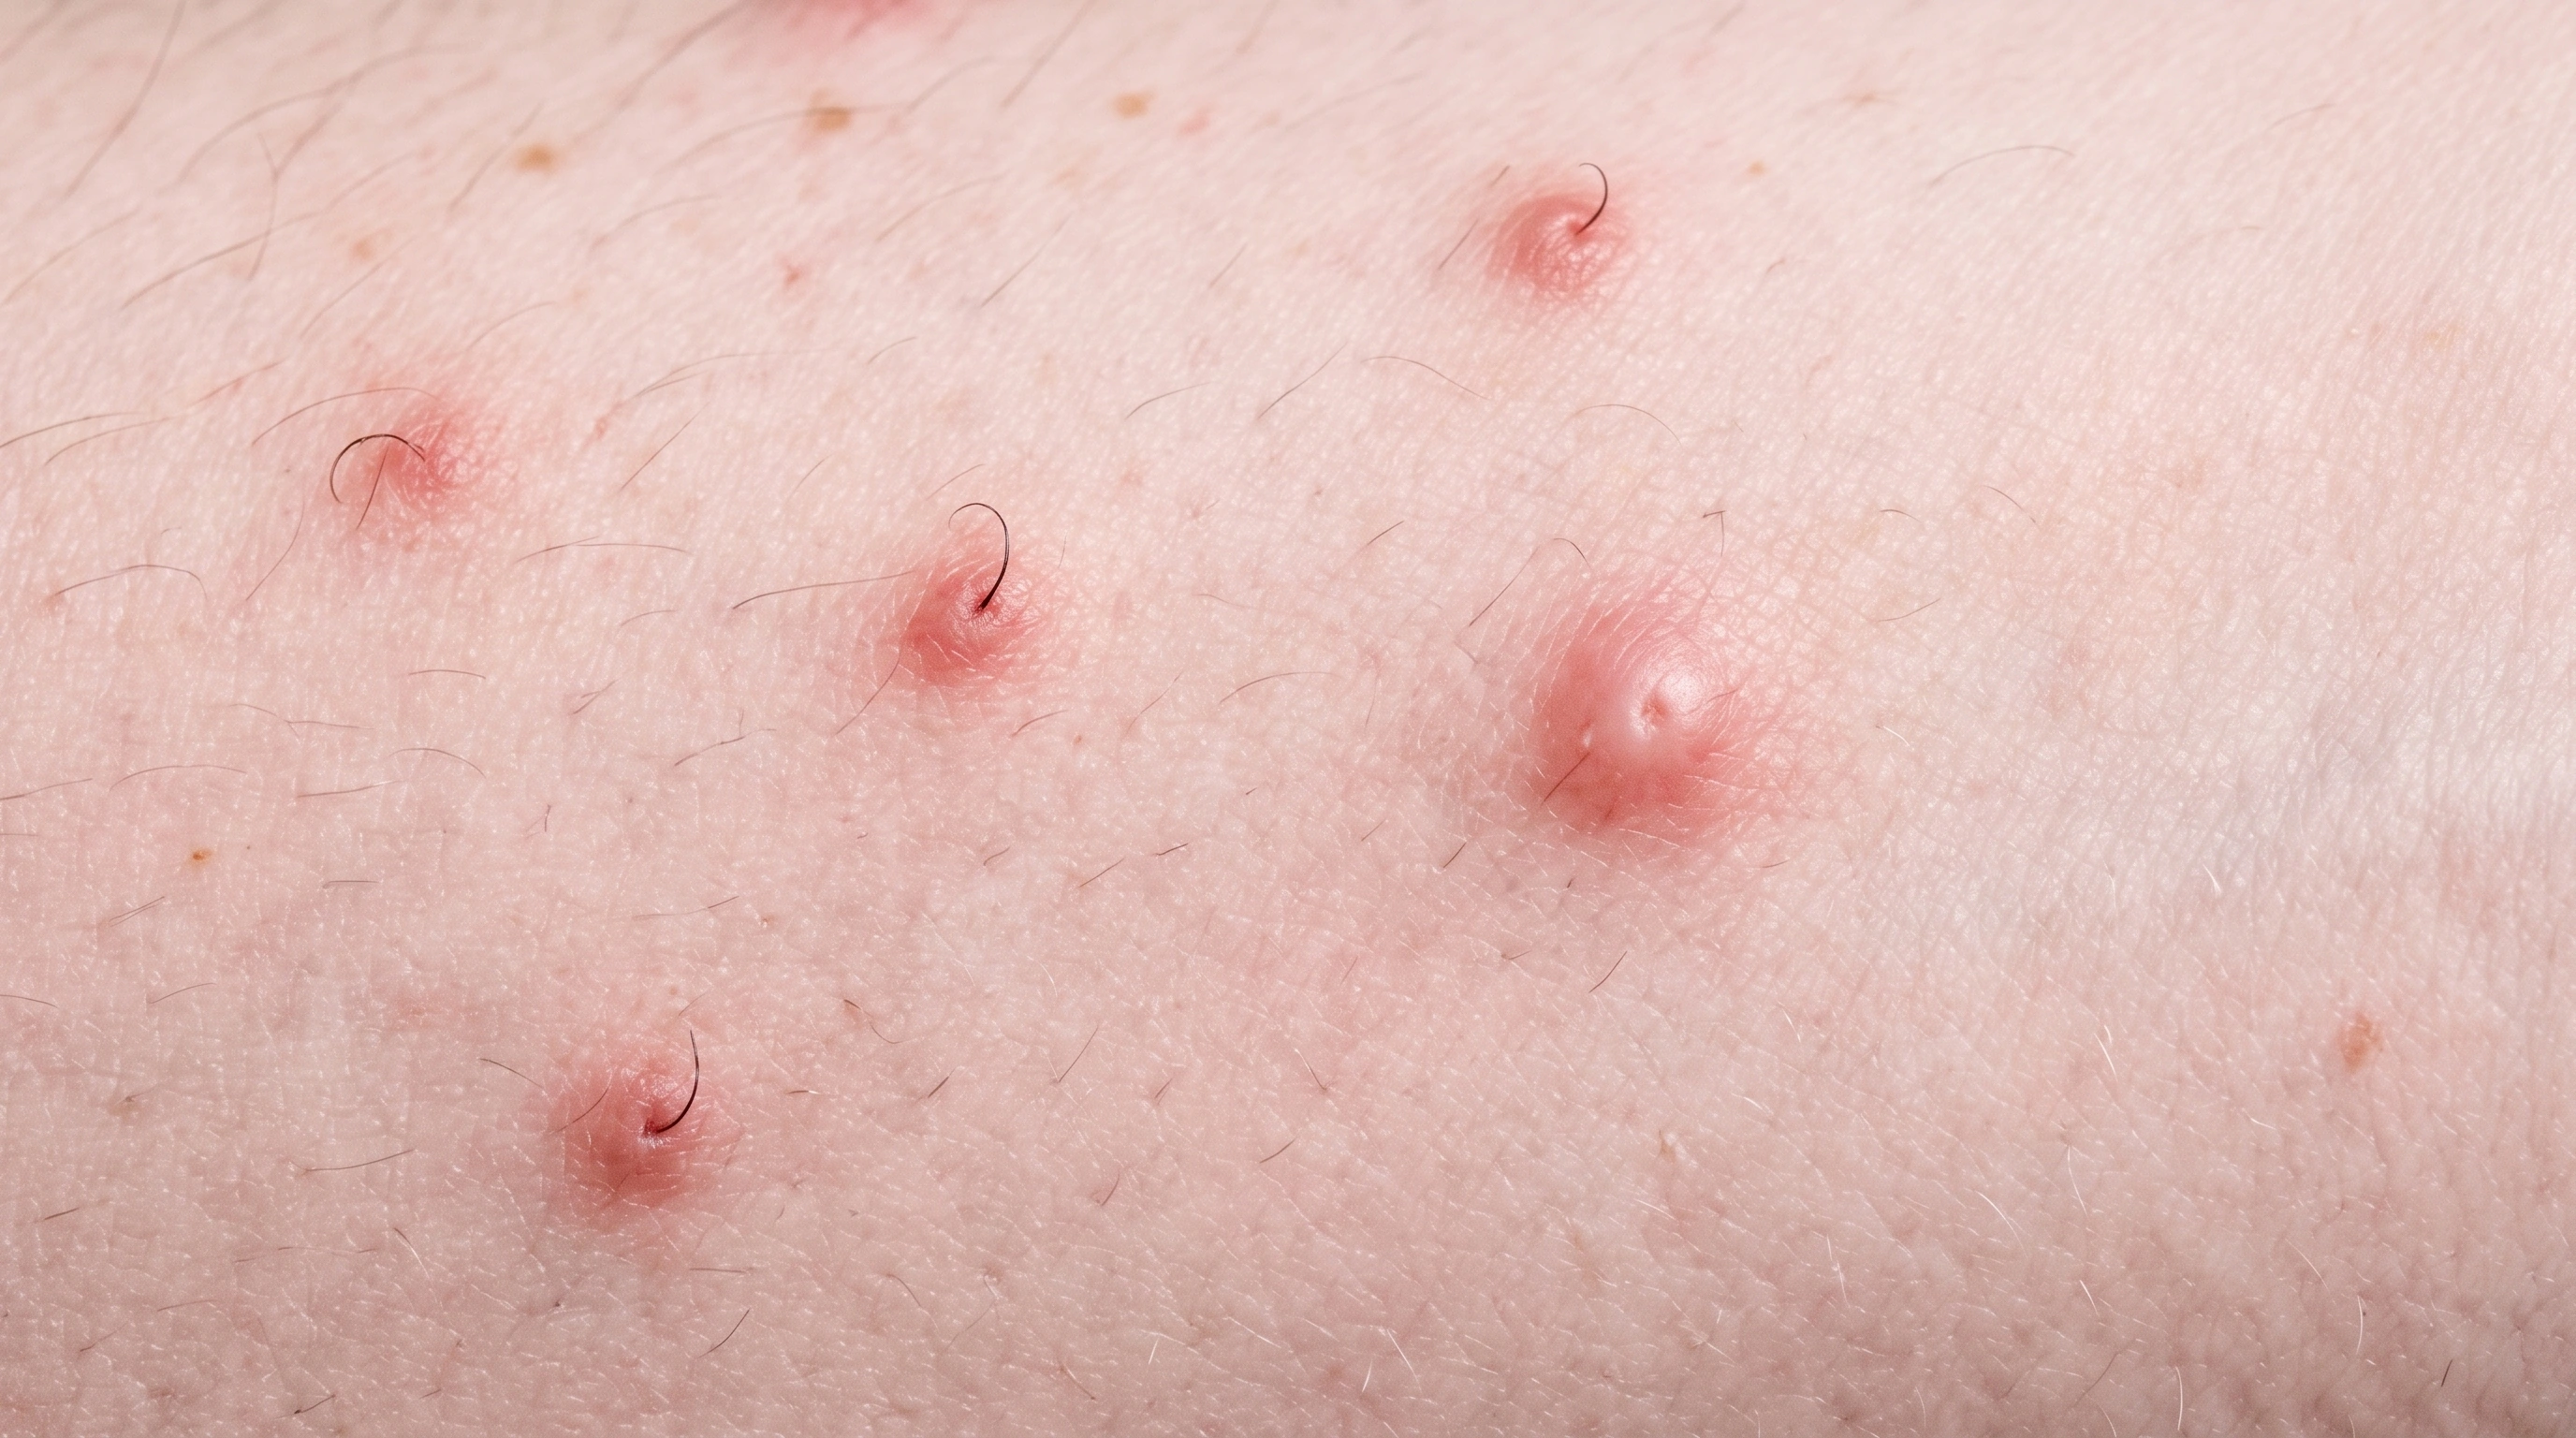
Ingrown Hairs: Bumps after shaving; Razor bumps.

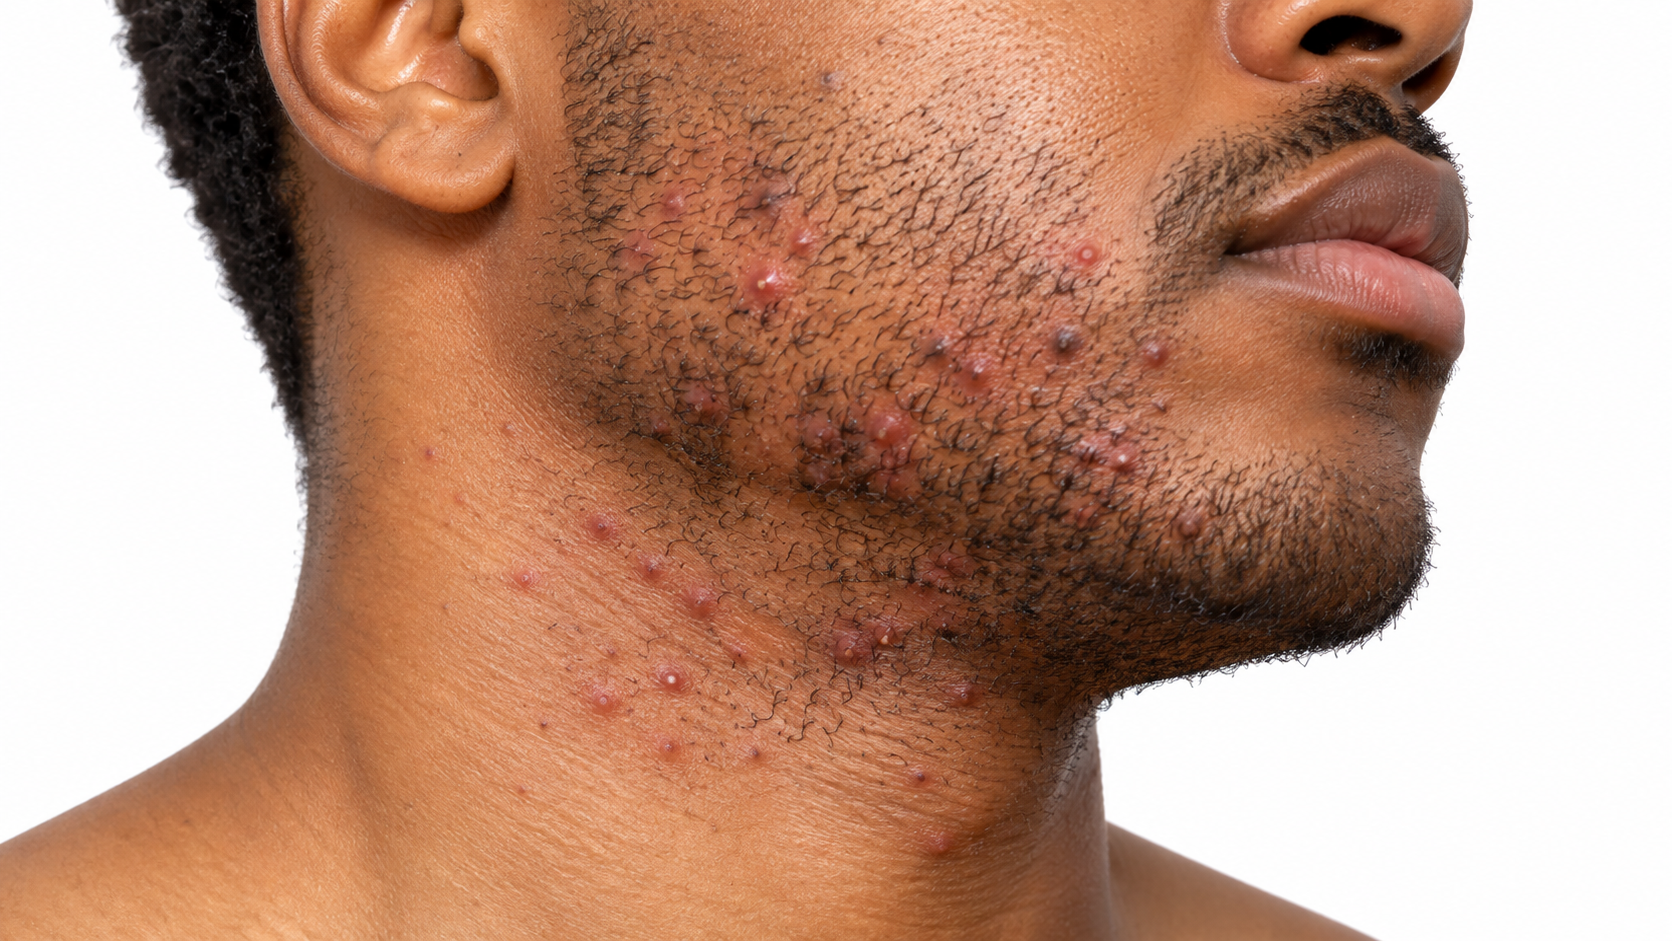
Razor bumps Pseudofolliculitis barbae in the beard area.

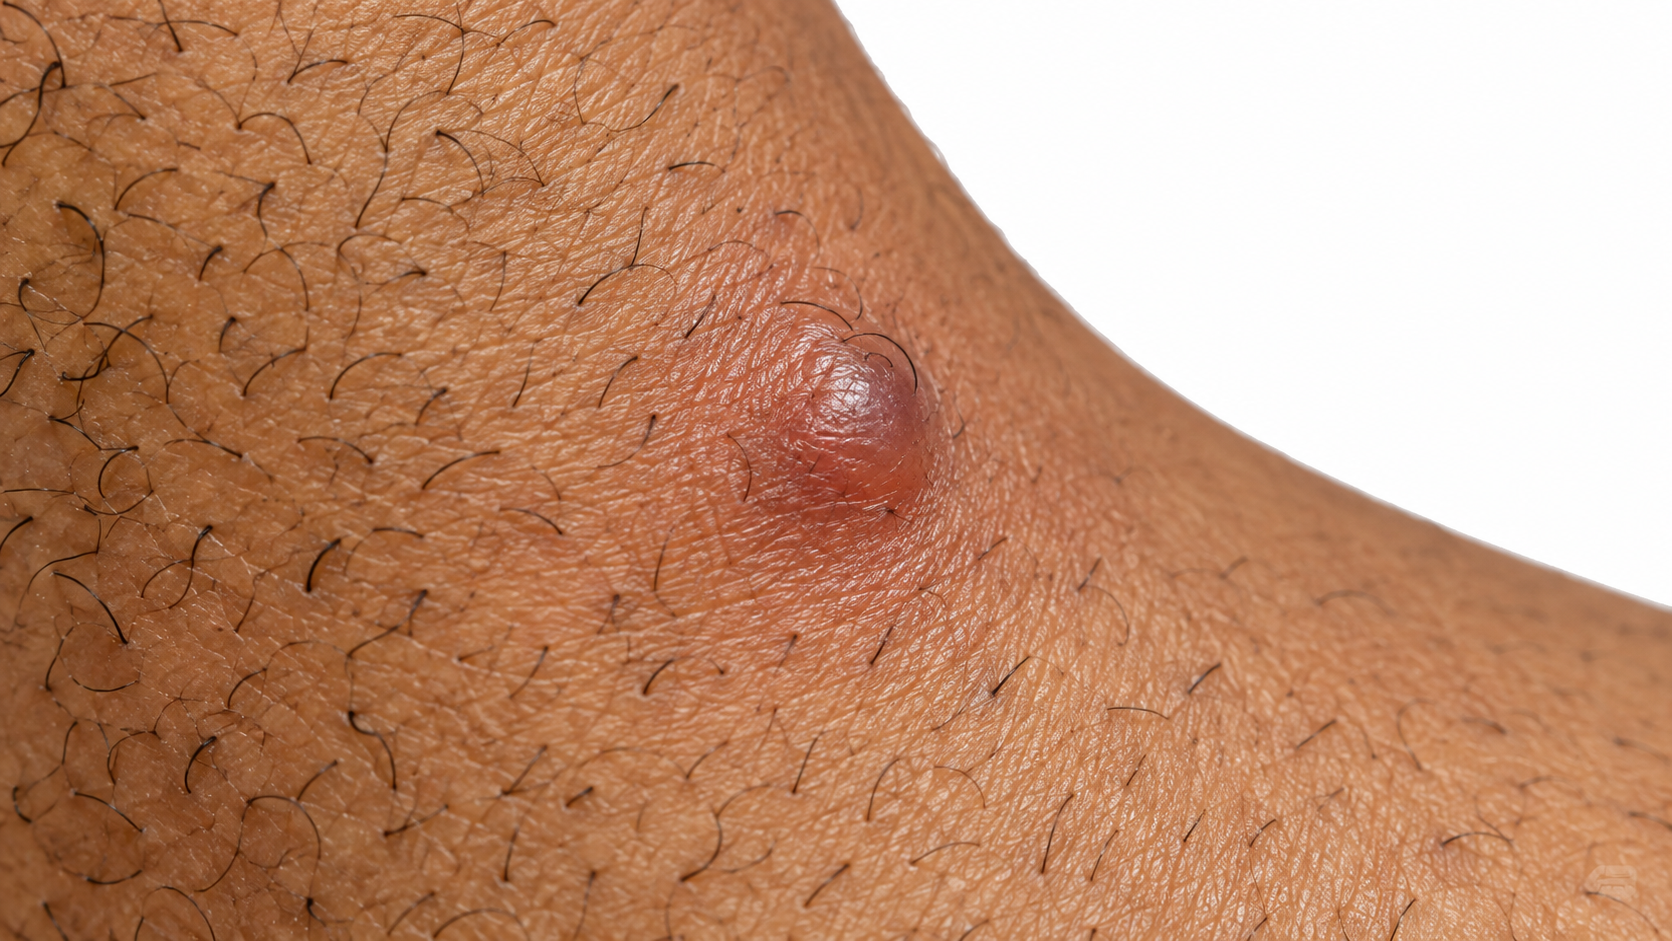
Representative image of an ingrown hair bump in a skin fold.

Bikini-line ingrown hairs Bumps after shaving or waxing.

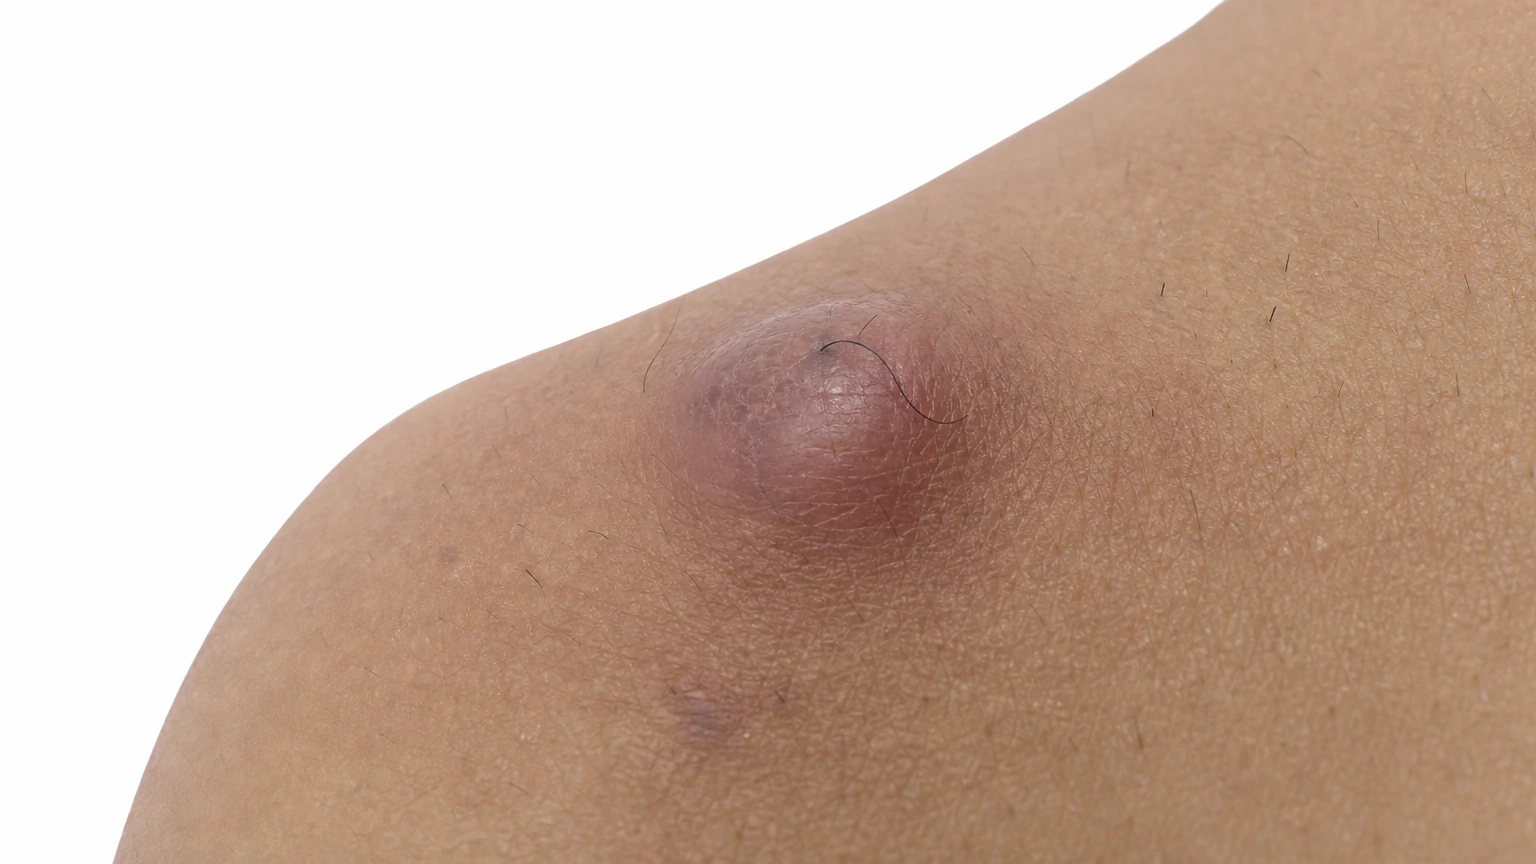
A firm raised skin lump with a curled hair, representing an ingrown-hair cyst.

Ingrown-hair cyst A deeper, larger lump.

Ingrown Hairs: Trapped hair.

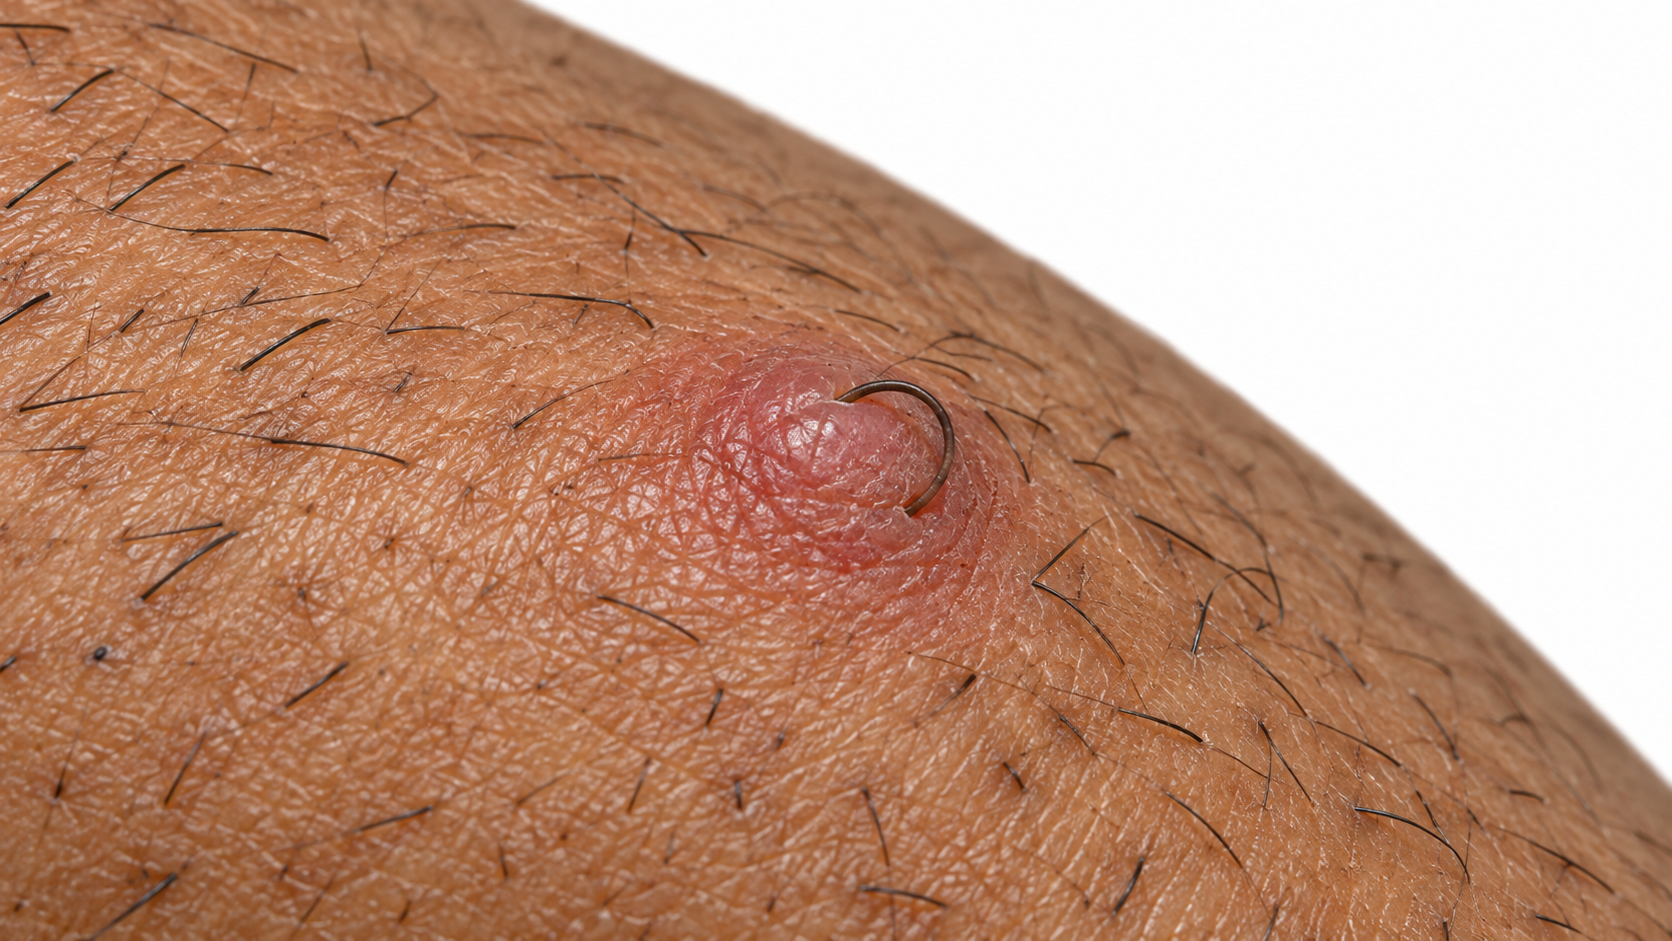
Individual ingrown hair A hair visible under the skin.

Molluscum Contagiosum

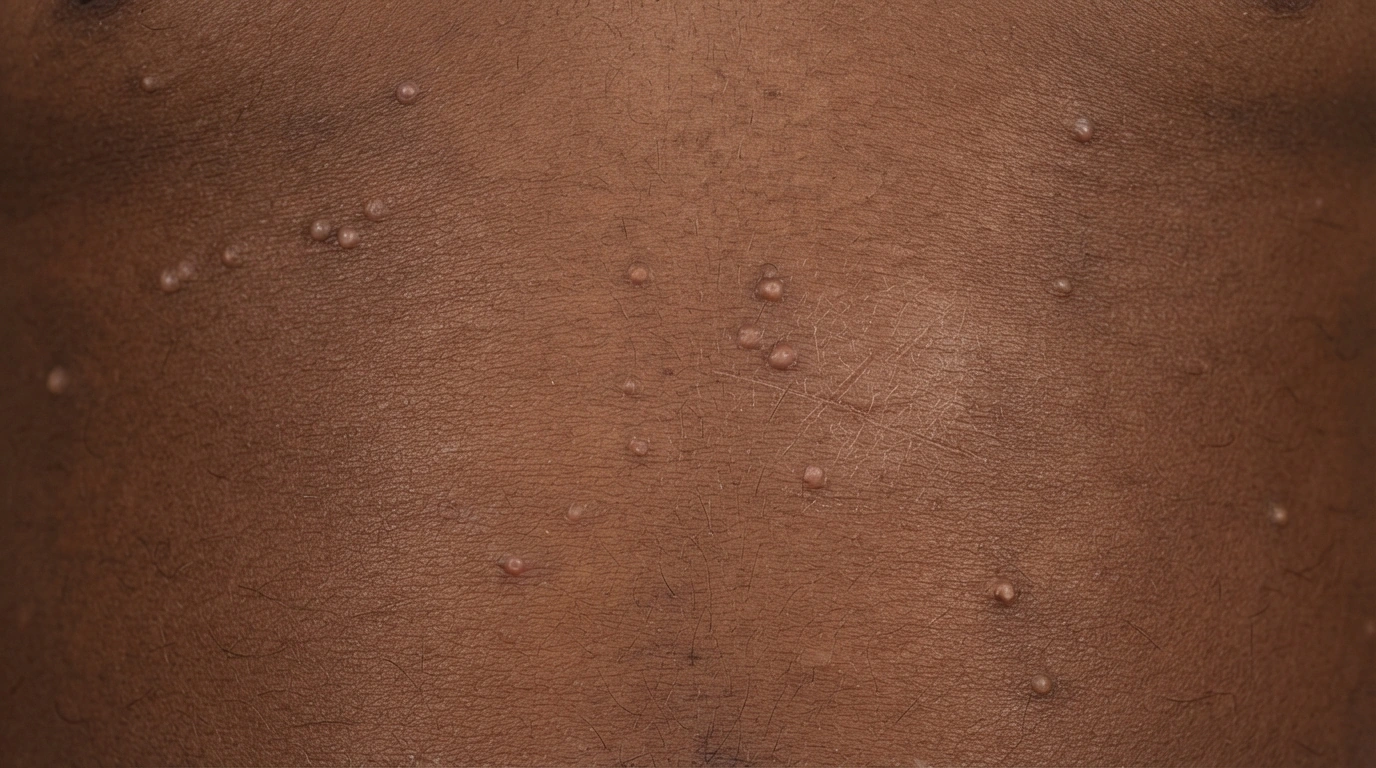
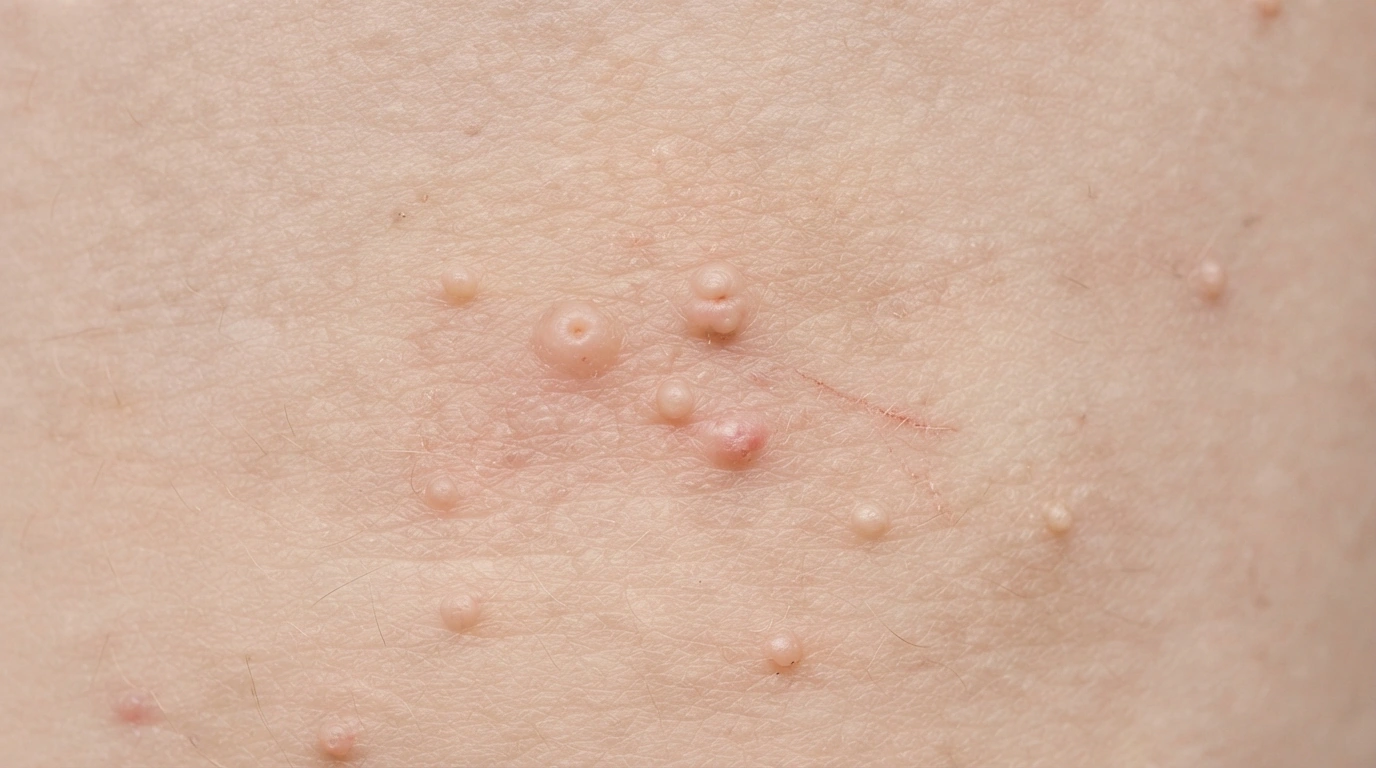
Smooth, shiny and dome-shaped, with a tiny dip in the center.

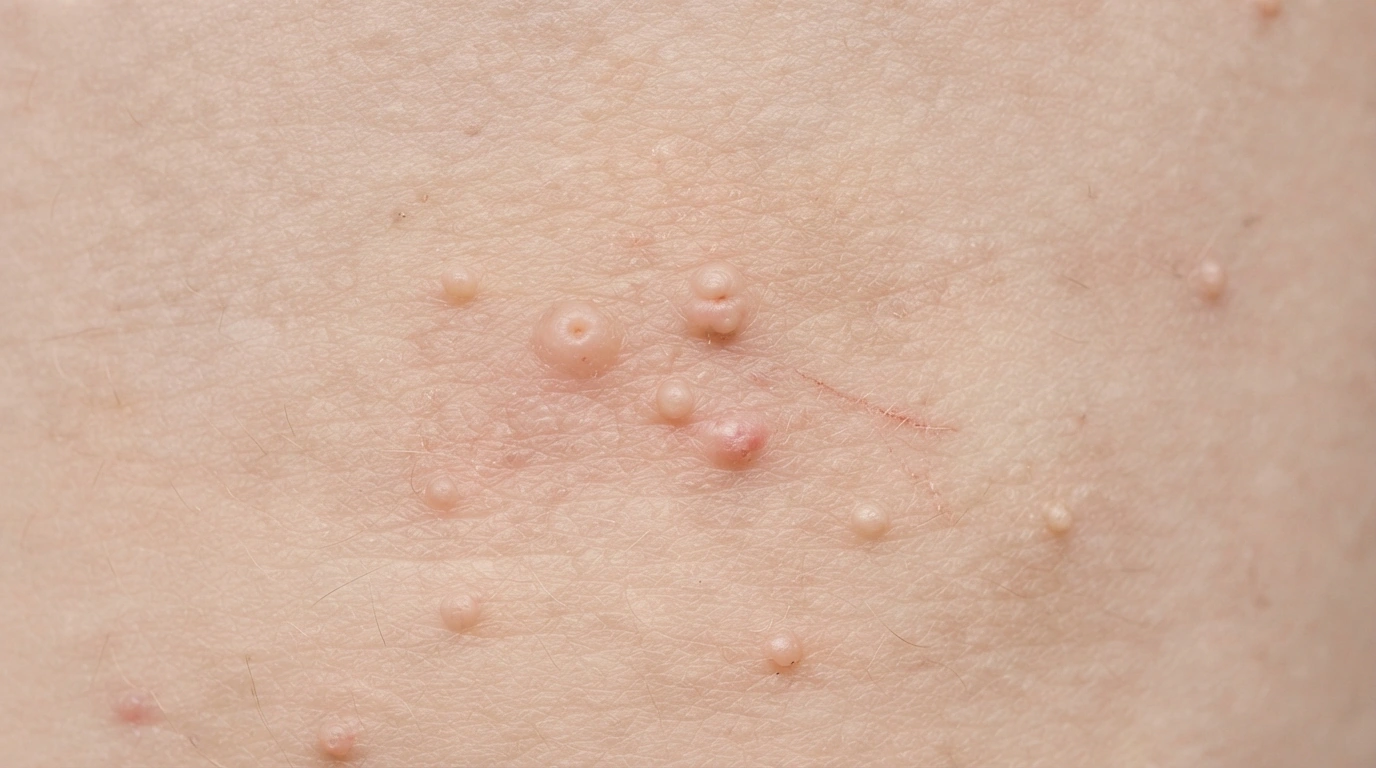
Pearly bumps with a central dimple Smooth, shiny and dome-shaped, with a tiny dip in the center.

Groups in skin folds.

Clusters Groups in skin folds.

Skin tones
A few firm pink bumps scattered under the jaw and along the upper neck on light skin, with a dark loop of hair visible over one of them.
Firm bumps grouped under the jaw and along the upper neck on medium olive-toned skin. The bumps read dusky pink to tan rather than red, and a dark loop of hair is visible over one of them.
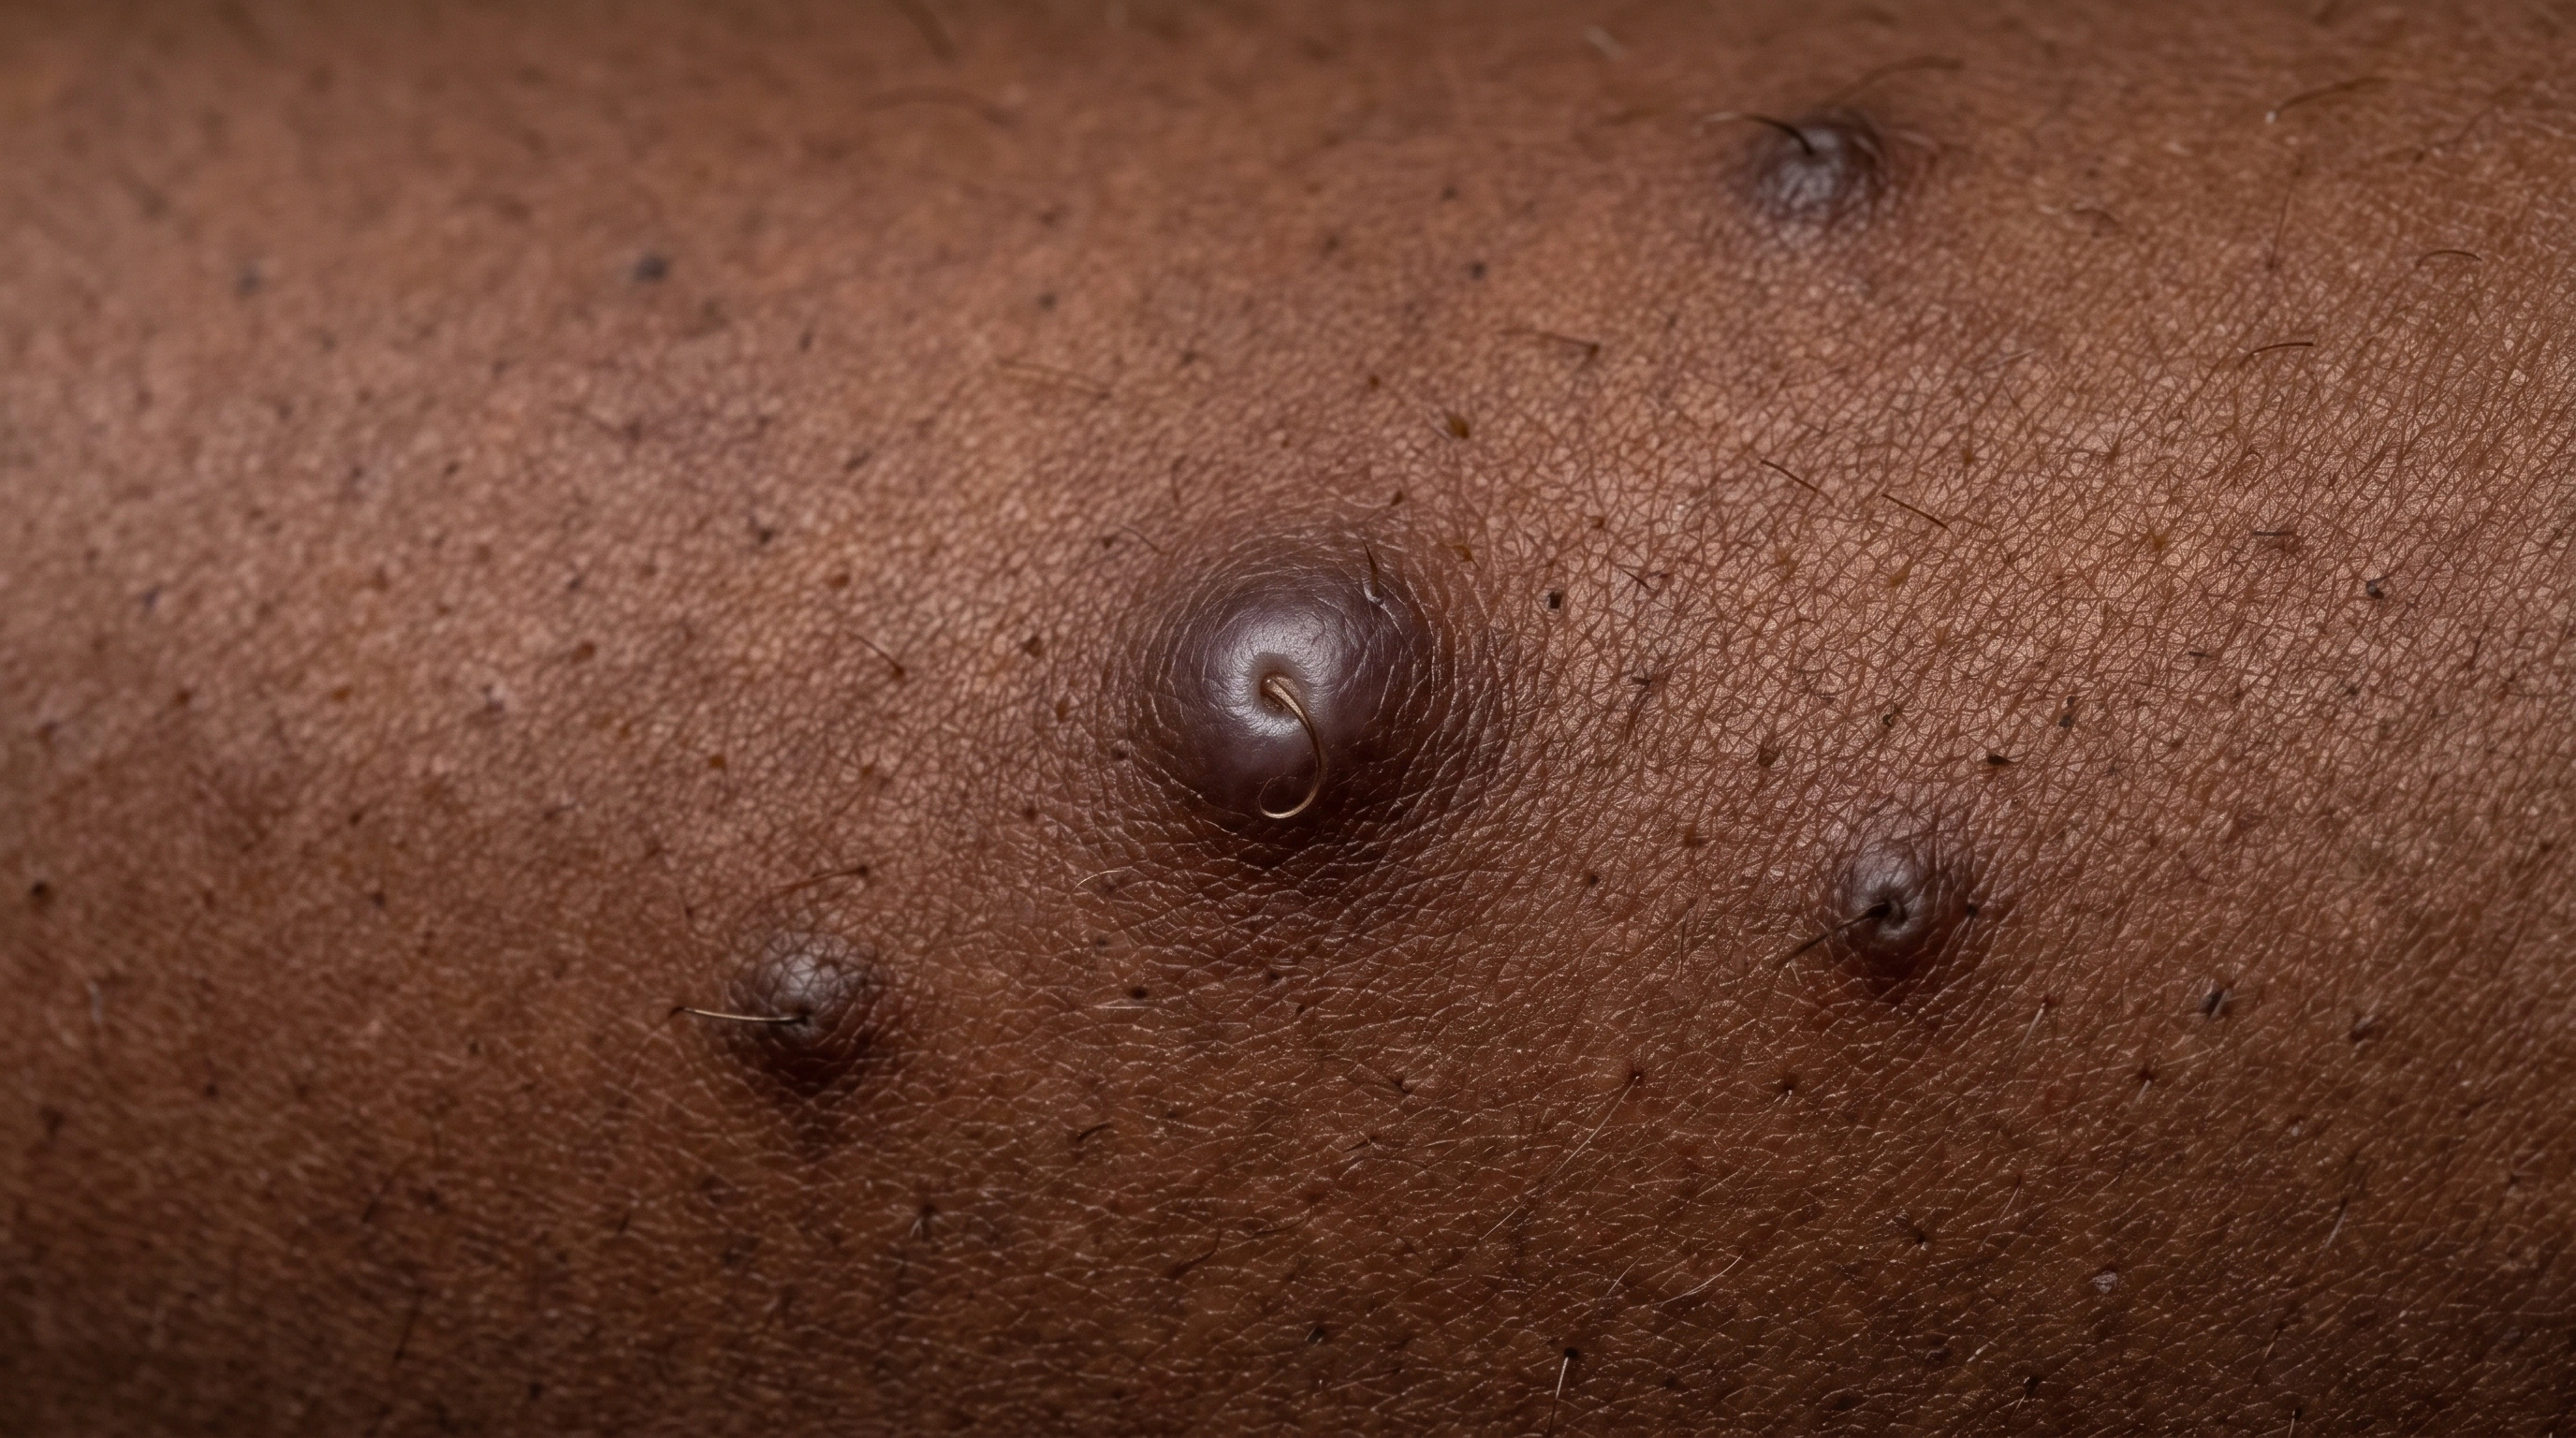
Firm bumps crowded under the jaw and along the upper neck on brown skin. The bumps look brown to violet rather than red, and a dark loop of hair is visible over one of them.
Firm bumps crowded under the jaw and along the upper neck on deep brown skin. The bumps read brown to violet rather than red, with mottled darker marks between them and one firm raised scar along the jaw.
A cluster of firm, dome-shaped pink and pearly white bumps on the side of a child's trunk on light skin, each two to five millimetres across with a small dip in the center.
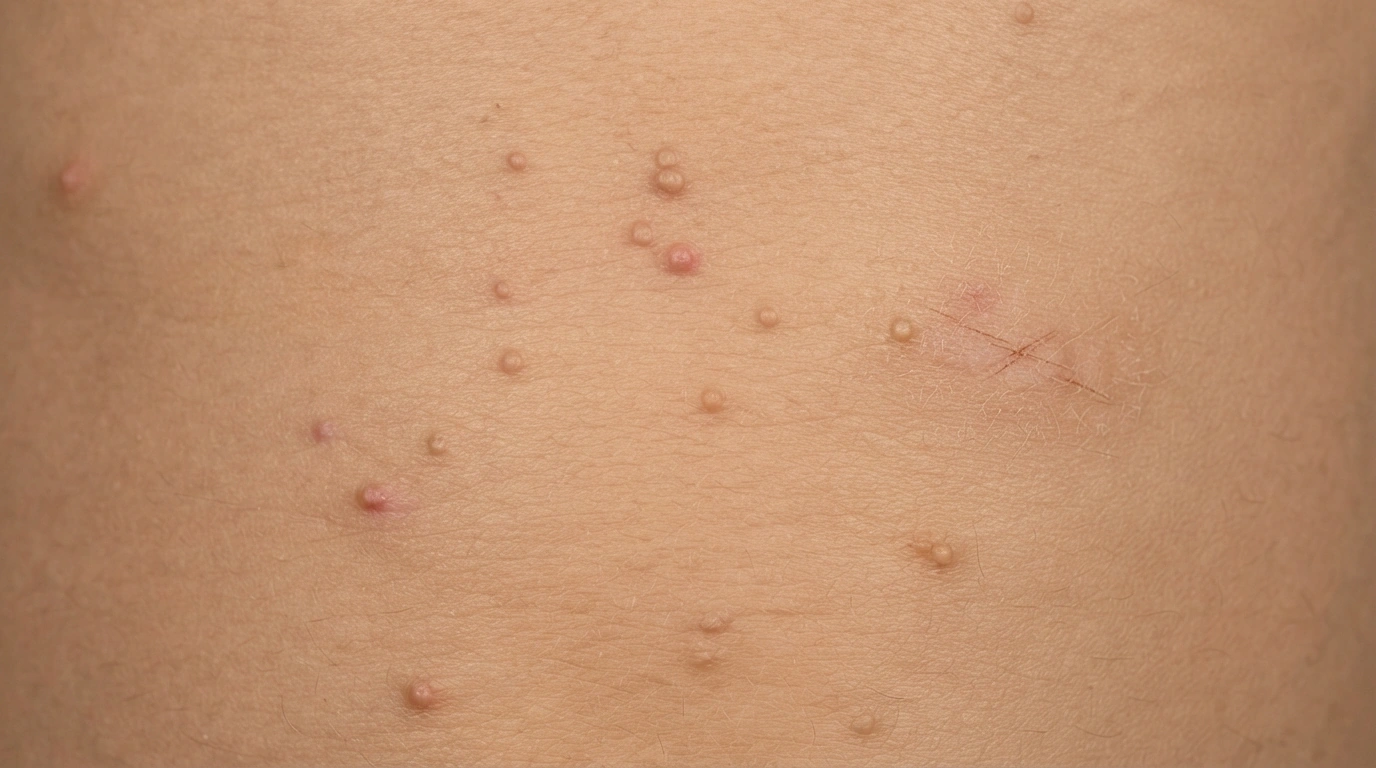
A cluster of firm, dome-shaped pale pink to skin-colored bumps on the side of a child's trunk on medium olive-toned skin, one of them redder and swollen.
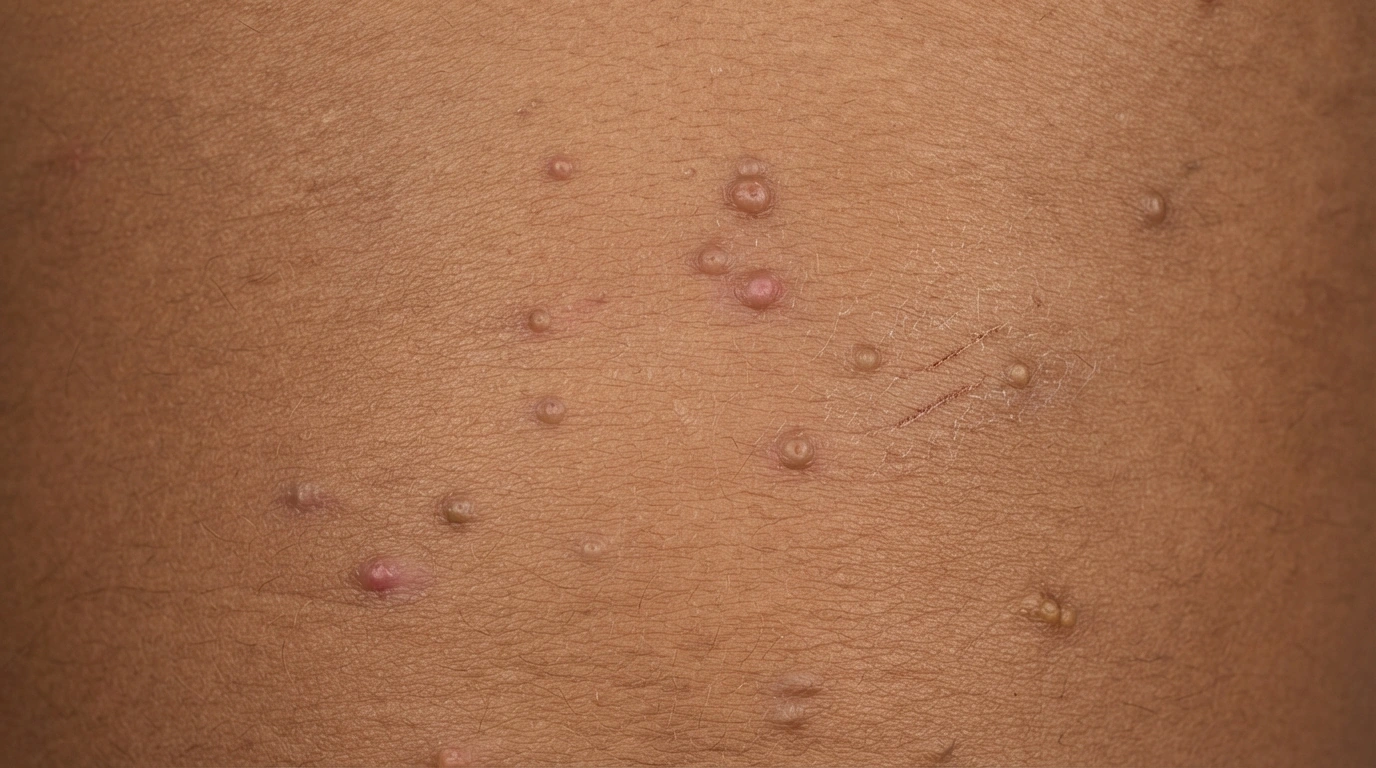
A cluster of firm, dome-shaped bumps on the side of a child's trunk on brown skin. The bumps are skin-colored to slightly gray rather than pink, each with a small dip in the center.
A cluster of firm, dome-shaped skin-colored to gray bumps on the side of a child's trunk on deep brown skin, with two flat darker marks nearby where earlier bumps have healed.
Diagram
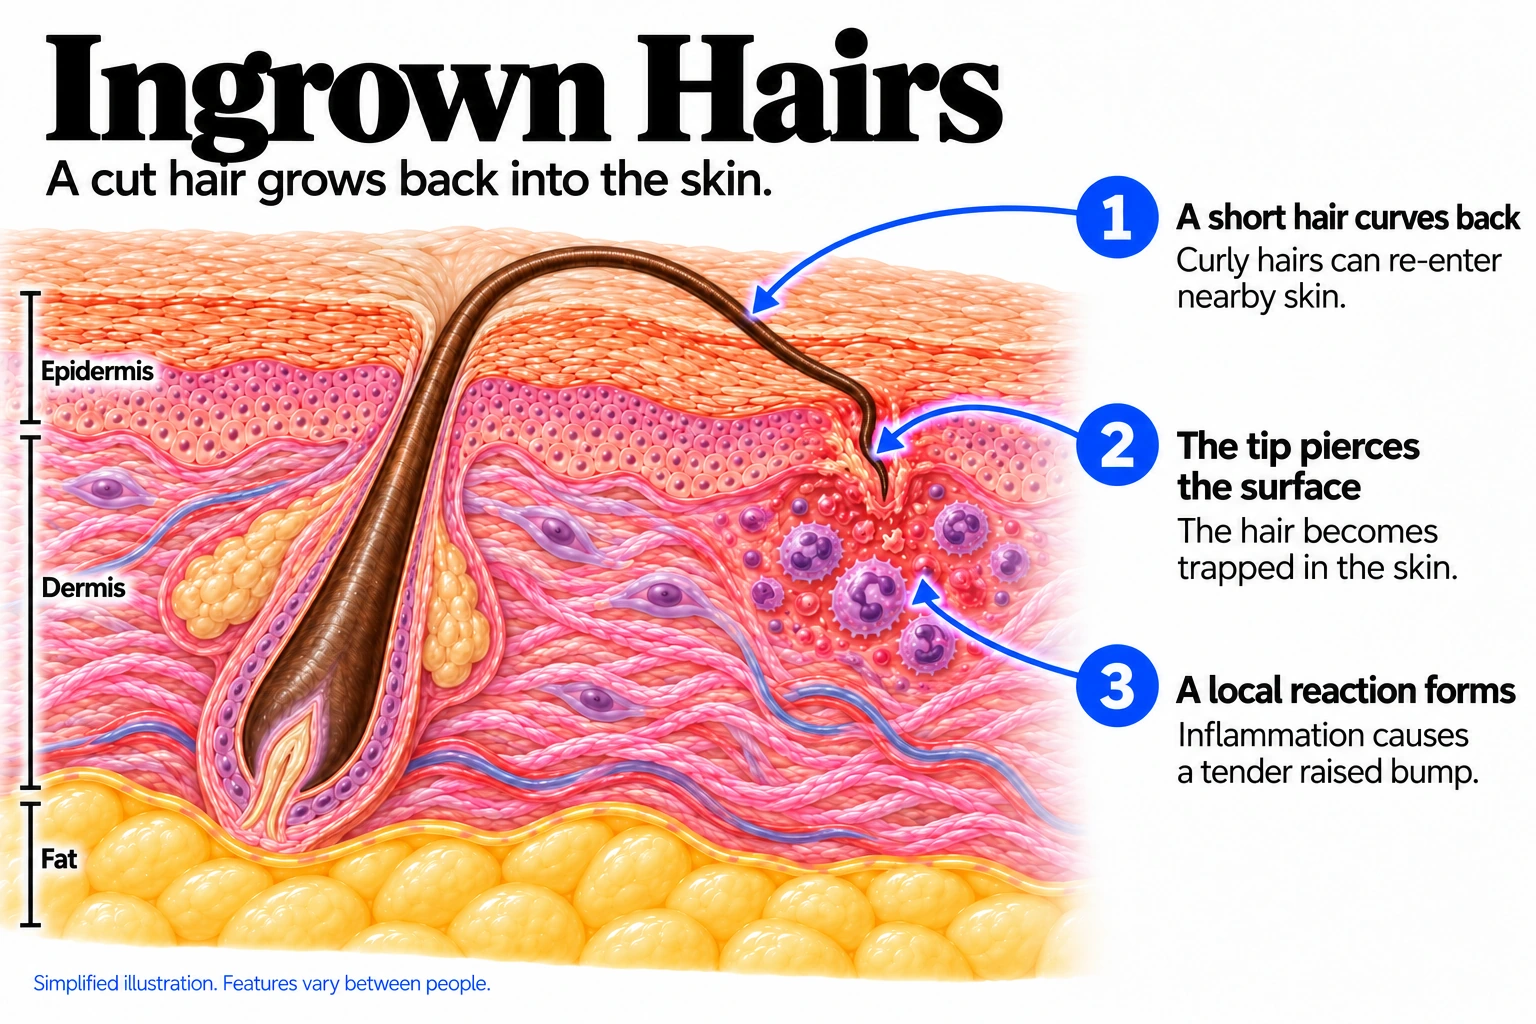
Ingrown Hairs mechanism diagram. A short hair curves back: Curly hairs can re-enter nearby skin. The tip pierces the surface: The hair becomes trapped in the skin. A local reaction forms: Inflammation causes a tender raised bump.
Molluscum Contagiosum mechanism diagram. The virus reaches skin cells: Contact spreads the molluscum virus. Infected cells enlarge: Viral material collects inside affected cells. A dimpled bump appears: The center often has a small depression.
In the skin

A hair curves back into nearby skin instead of continuing outward. The trapped hair triggers a local inflammatory reaction that can form a tender raised bump.

The molluscum virus infects surface skin cells and causes them to enlarge. A small smooth bump develops, often with a characteristic central dimple.

Where it shows up

Shaved or plucked areas
Trunk, limbs and skin folds

When it usually starts

010203040506070+

Ingrown Hairs. Usually begins after shaving or other hair removal, particularly after puberty.

Molluscum Contagiosum. Most common in young children; adults can also acquire it, including through sexual contact.

Causes and triggers

Causes

Ingrown hairs happen when a cut or broken hair curls back into the skin. The body treats the hair as a foreign object and becomes inflamed.

Molluscum contagiosum is caused by a poxvirus that infects the top layer of skin.

Family tendency

Tightly curled hair is inherited and is the biggest single risk.

Risk factors
Curly or coarse hair, Frequent shaving, Waxing and plucking
Children aged 1 to 10, Eczema, Weakened immunity
How it spreads
  • Skin-to-skin contact — Well established
  • Scratching and spreading to other areas — Well established
  • Shared towels and bath toys — Strong link
  • Swimming pools — Possible
  • Sexual contact in adults — Strong link
Trigger
● Ingrown Hairs
● Molluscum Contagiosum
Close shaving
Well established
Not listed
Shaving against the grain
Strong link
Not listed
Dull razors
Strong link
Not listed
Tight clothing
Possible
Not listed

Daily Care

Ingrown Hairs
Molluscum Contagiosum
Daily care

Habits that help

  • Stop shaving for three to four weeks
    The most effective single treatment.
  • Clippers or a guarded trimmer
    A millimeter of stubble keeps the tip out.
  • A single-blade or safety razor
    Cuts at the surface.
  • Shave with the grain
    Do not stretch, press or repeat.
  • Shave less often
    Every second or third day, never over bumps.
  • Soften first, then lubricate
    Warm water, then gel.
  • An electric foil or rotary shaver
    Cuts above the skin.
  • Sun protection
    Protect healing skin from sunlight to limit darkening of marks.
  • A chemical depilatory cream
    Leaves a soft, feathered end.
  • Eflornithine cream
    Prescription, slows facial hair regrowth.

Avoid

  • Avoid: Shaving as close as possible
    The tip ends below the skin surface.
  • Avoid: Multi-blade cartridge razors
    Later blades cut below the surface.
  • Avoid: Stretching the skin taut while shaving
    The cut hair vanishes as skin relaxes.
  • Avoid: Shaving against the grain
    A closer cut, a sharper tip.
  • Avoid: Going over the same patch repeatedly
    Bumps come from the later passes.
  • Avoid: Shaving every day, or over bumps
    Inflamed skin needs time to settle.
  • Avoid: Dry shaving, or shaving with bar soap
    The blade drags and irritates.
  • Avoid: A dull or dirty blade
    Tugs the hair and leaves a worse tip.
  • Avoid: Waxing, tweezing and epilating
    The regrowing hair has to reopen its way out.
  • Avoid: Digging a hair out with a needle
    Turns a bump into a wound.
  • Avoid: Picking and squeezing
    The same damage, more often.
  • Avoid: Gritty scrubs and stiff brushes
    Inflammation, and the hair stays put.
  • Avoid: Alcohol-heavy aftershaves
    Sting broken skin, add irritation.
  • Avoid: Tight collars, straps and underwear
    Friction pushes hairs back in.
  • Avoid: Sun on healing marks
    Makes marks deeper and slower to fade.

Habits that help

  • Keeping nails short and hands busy
    Short nails help limit skin damage from scratching.
  • Covering bumps with clothing or a plaster
    Cover bumps to reduce touching and skin-to-skin spread.
  • Own towel, own flannel, no shared baths
    Keep towels and washcloths separate and avoid sharing bathwater.
  • Stopping shaving over the affected area
    Avoid shaving over bumps, which can spread them to nearby skin.
  • Treating eczema properly
    Less itching, less scratching, less spread.
  • Cantharidin, applied in clinic
    A blistering agent painted on, washed off hours later.
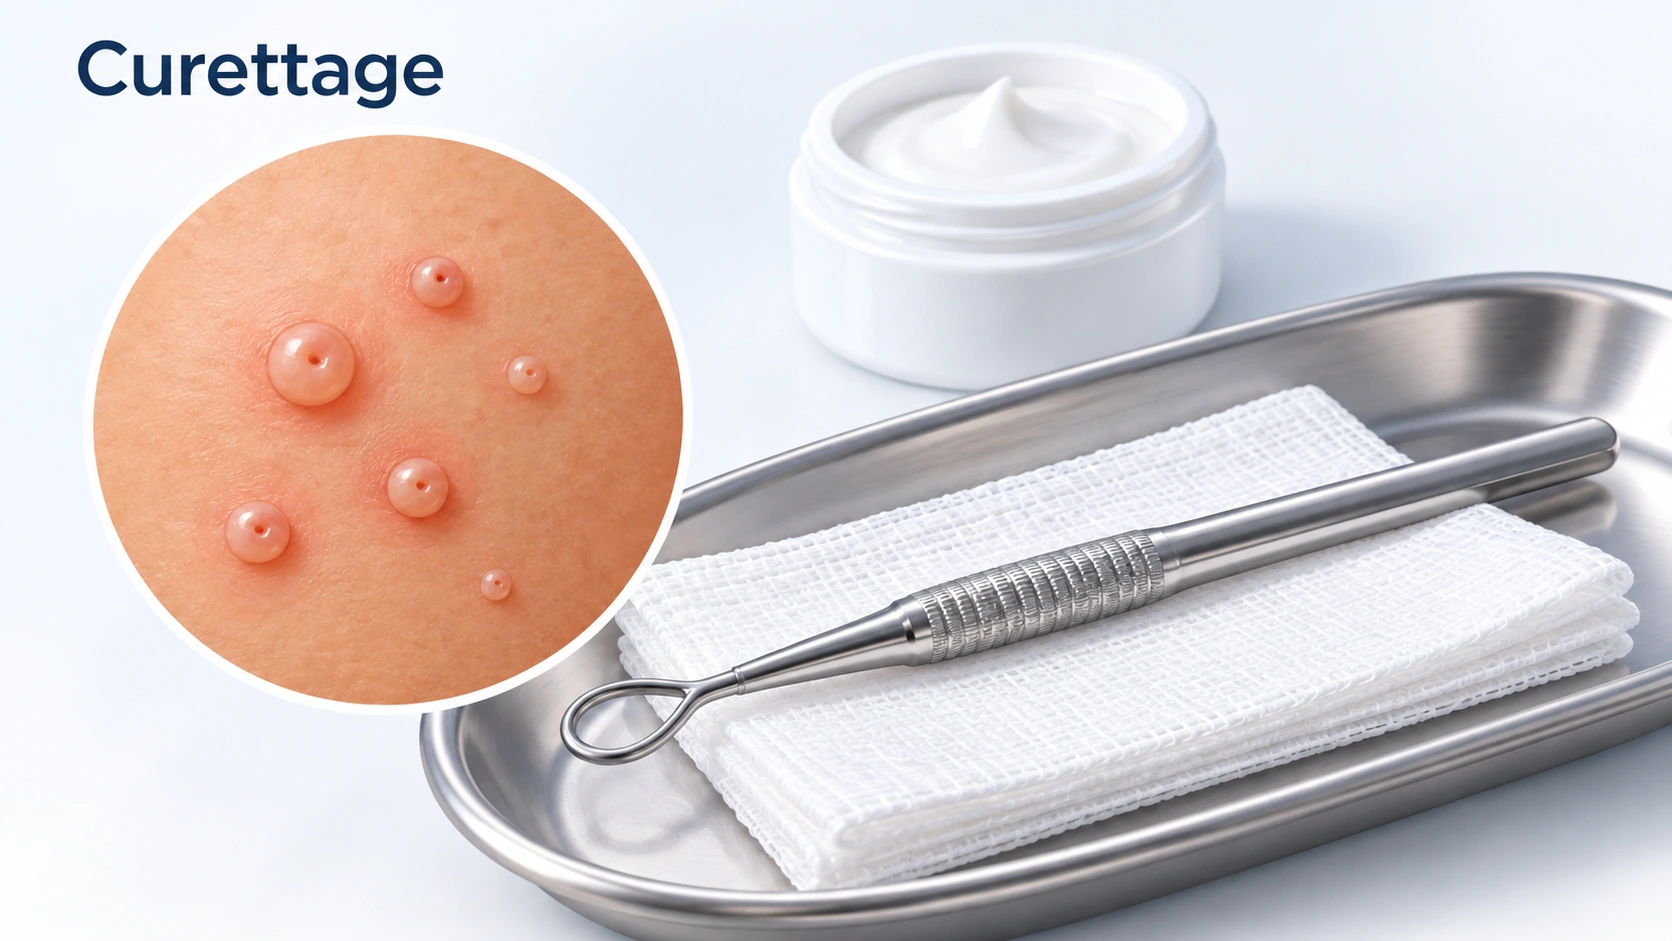
  • Curettage
    Bumps scraped off in one visit, after numbing cream.
  • Prescription topical treatments
    Berdazimer gel, retinoids and potassium hydroxide.
  • Treating a few bumps first
    Shows how the skin reacts before thirty.
  • Review immune-suppressing medicines with the prescriber; do not stop them yourself
    Immune suppression can affect infection persistence. Tell the treating clinician and do not stop a prescribed medicine on your own.
  • Watchful waiting
    Many cases clear without treatment; discuss whether observation is appropriate with a clinician.

Avoid

  • Avoid: Scratching
    Breaks a bump open and plants virus nearby.
  • Avoid: Picking or squeezing bumps
    Releases the virus-packed core onto nearby skin.
  • Avoid: Shaving over or near bumps
    Seeds molluscum along the path.
  • Avoid: Sharing bath things
    Towels, flannels, sponges and bath water.
  • Avoid: Shared mats and equipment
    Avoid sharing unclean mats or equipment that touches affected skin.
  • Avoid: Rubbing, friction and occlusive clothing
    Friction breaks the surface and moves virus.
  • Avoid: Untreated eczema
    An open door and a reason to scratch.
  • Avoid: Aggressive home treatment
    Digging or burning leaves scars and dark marks.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Ingrown Hairs
● Molluscum Contagiosum
Filter by type
Ingrown hair pattern

Select one or more.

All types
Over-the-counter
Illustration: Generic topical cream tube and white cream.

Depilatory cream

Limited evidence

A chemical hair remover dissolves the hair rather than cutting it, leaving a soft feathered end that does not spear the skin. Used every few days instead of shaving it genuinely reduces bumps. The trade-off is real: it smells strong and it irritates or burns some people, so test a small patch and never use it on skin that already has active bumps.

Existing reference image of Microneedling vs Microdermabrasion — At Home.

Exfoliating scrubs and brushes

Limited evidence

Gritty scrubs and stiff brushes are sold for this and they are the wrong tool. Scrubbing does not free a hair that is already through the follicle wall, and it adds inflammation to skin that has too much. If you want exfoliation here, use a gentle glycolic or salicylic acid instead.

Five adapalene gel 0.1% tubes and boxes lined up on white, including Differin, Effaclar, PanOxyl and Neutrogena

Adapalene

Limited evidence

A retinoid gel used at night on the shaved area. It thins the plug over the follicle opening so a growing hair is more likely to find its way out, and it slowly evens the dark marks left by old bumps. It takes six to twelve weeks and it does not stop a hair curving back in, so it works alongside a change of razor rather than instead of one.

Four glycolic acid toner and liquid bottles lined up on white, one with its box

Glycolic Acid

Limited evidence

A leave-on lotion or toner used two or three times a week keeps the follicle openings clear, which is the point where a curved hair gets stuck. It also helps the flat dark marks fade. Use it on days you do not shave, because acid on freshly shaved skin stings and adds irritation.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

Does much the same job as glycolic acid and suits oilier skin and the bikini line better, because it gets into the follicle itself. Two or three times a week is enough. It is not an exfoliating scrub, and it will not free a hair that is already trapped.

Three acne wash tubes on white: Differin Deep Cleanser, CeraVe Acne Foaming Cream Cleanser and PanOxyl

Benzoyl Peroxide

Limited evidence

Worth adding when the bumps carry pinpoints of pus, because bacteria have joined in on top of the trapped hair. A wash or a low-strength gel on the shaved area is enough. It does nothing about the hair itself, and it bleaches towels and collars, so keep the strength low and the expectations modest.

Five azelaic acid tubes and bottles on white, most marked 10 percent, from Peach Slices, Paula's Choice, Facetheory, The Ordinary and Naturium

Azelaic Acid

Limited evidence

Aimed at the marks rather than the bumps. It calms inflammation and slowly lifts the flat dark patches left along the jaw and neck, and it is gentle enough for skin that is shaved regularly. It works over months, not weeks, and only once new bumps have stopped forming.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

The wart products in the pharmacy are the wrong tool here. Molluscum is a poxvirus, not the wart virus, and the bumps are soft domes rather than thickened skin for an acid to dissolve. On thin skin, on a child, and on thirty bumps at once, it mostly buys irritation and dark marks. If a bump is going to be treated, the clinic options are more reliable and better controlled.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh.

Hydrocortisone 1%

Limited evidence

For the dry itchy eczema-like patch that develops around the bumps in about a third of children — not for the bumps themselves. Treating it properly matters, because the itch drives the scratching and the scratching is what spreads the infection. Use it on the skin between and around the bumps, thinly and for a short course. Strong steroid creams applied over the bumps calm the redness and can help the virus stay longer.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Limited evidence

A common suggestion, usually combined with iodine, and the evidence behind it is a small number of low-quality studies. Against an infection that clears by itself, that is very hard to read. The real drawback is that it stings and it commonly causes an allergic rash on children's skin, which then itches, which then gets scratched.

Prescription topicals

Eflornithine

Moderate evidence

Eflornithine cream. A prescription cream that slows facial hair regrowth, so there is less hair to cut and shaving can be done less often. It is used twice a day on the face and neck alongside your usual hair removal, not instead of it. It does not remove hair, and the effect fades within weeks of stopping.

Tretinoin — Header Image

Tretinoin

Limited evidence

The prescription-strength version of the retinoid approach, used at night on the beard and neck. It keeps follicle openings clear and does more for the dark marks than anything else on a shelf. It makes skin drier and more easily irritated by a razor for the first month or two, so build up slowly and shave more gently while you do.

A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Limited evidence

An antibiotic lotion, usually prescribed with benzoyl peroxide, for when a lot of the bumps have gone pustular. It settles the infected ones faster than benzoyl peroxide alone. It is a short course rather than a permanent fix, because the trapped hair, not the bacteria, is what starts each bump.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh

Hydrocortisone

Limited evidence

A low-strength steroid cream calms a badly inflamed patch quickly and takes the soreness out of it. It is a short course of days, prescribed for a specific flare, not something to keep using. Facial and neck skin thins with repeated steroid use, and it does nothing about the hair that caused the bump.

Tretinoin — Header Image

Tretinoin

Limited evidence

A retinoid dabbed onto individual bumps to irritate them into clearing. It is sometimes chosen for bumps on the face, where blistering or scraping is less appealing. The evidence for it in molluscum is thin, it is slow, and it makes the skin around the bumps red and flaky, which is its own reason to scratch.

Berdazimer

Strong evidence

Berdazimer gel. A newer prescription gel mixed and applied at home once a day, designed specifically for molluscum. In its trials about a third of children had all their bumps clear at twelve weeks, against roughly one in five given the placebo gel — a real effect, but a modest one. Redness and irritation where it is applied are common, and cost and availability are the practical limits.

Educational still life: topical solution.

Potassium hydroxide solution

Limited evidence

A dilute alkaline solution dabbed on individual bumps at home, usually once or twice a day until each bump becomes inflamed and then clears. It is cheap and it can be done without appointments. It stings, it works by irritating the skin, and it can leave dark or pale marks if it is overdone — so it goes on the bumps only, and starting with a few is sensible.

Illustration: Generic topical cream tube and white cream.

Imiquimod

Limited evidence

This one was studied properly in children, in two large trials, and it did not work any better than the placebo cream — while causing more skin reactions, and in some children pain and swelling. It is still prescribed for molluscum out of habit. On the evidence there is, it should not be.

Prescription pills
None listed
An illustrative bottle labeled Cimetidine beside plain tablets.

Cimetidine

Limited evidence

An old stomach-acid tablet, taken by mouth for several weeks in the hope of nudging the immune system into recognizing the virus. It appeals because it is painless and needs no procedure, which matters for a frightened child with many bumps. The trials do not support it, and it interacts with a number of other medicines, so it is a long shot rather than a plan.

Injections
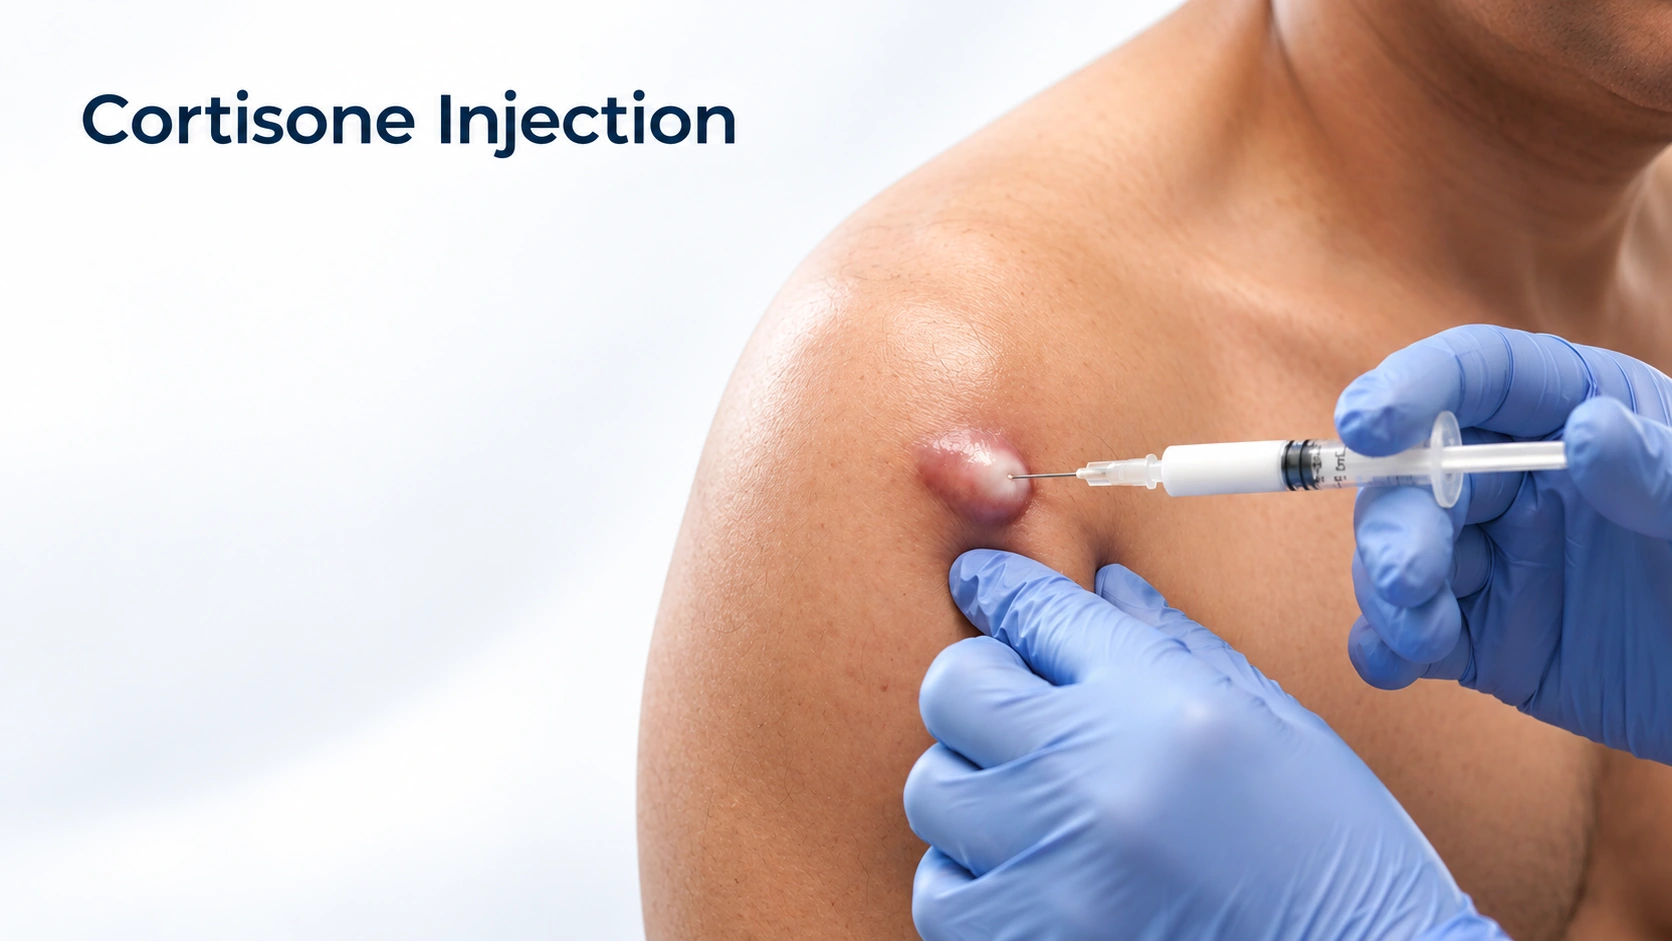
Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Limited evidence

A steroid injected directly into a firm raised or keloid scar left by old bumps. It flattens and softens the scar over a series of visits a few weeks apart. It treats what is already there and does nothing to prevent the next one, and repeated injections can leave a pale or dented patch.

None listed
Procedures
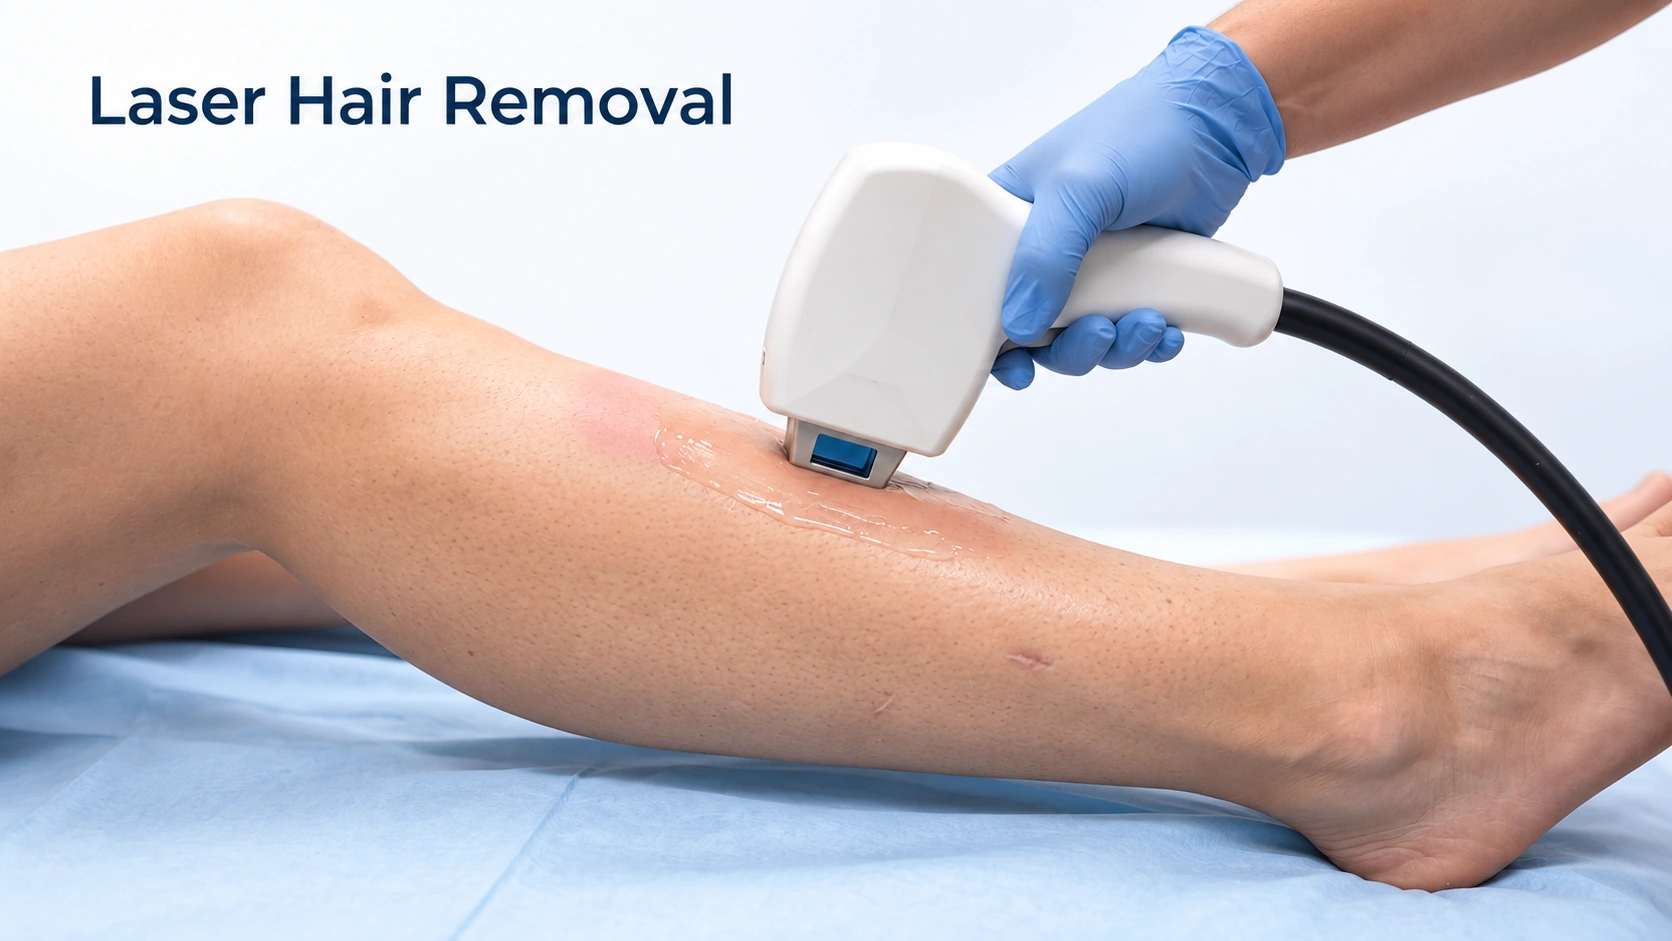
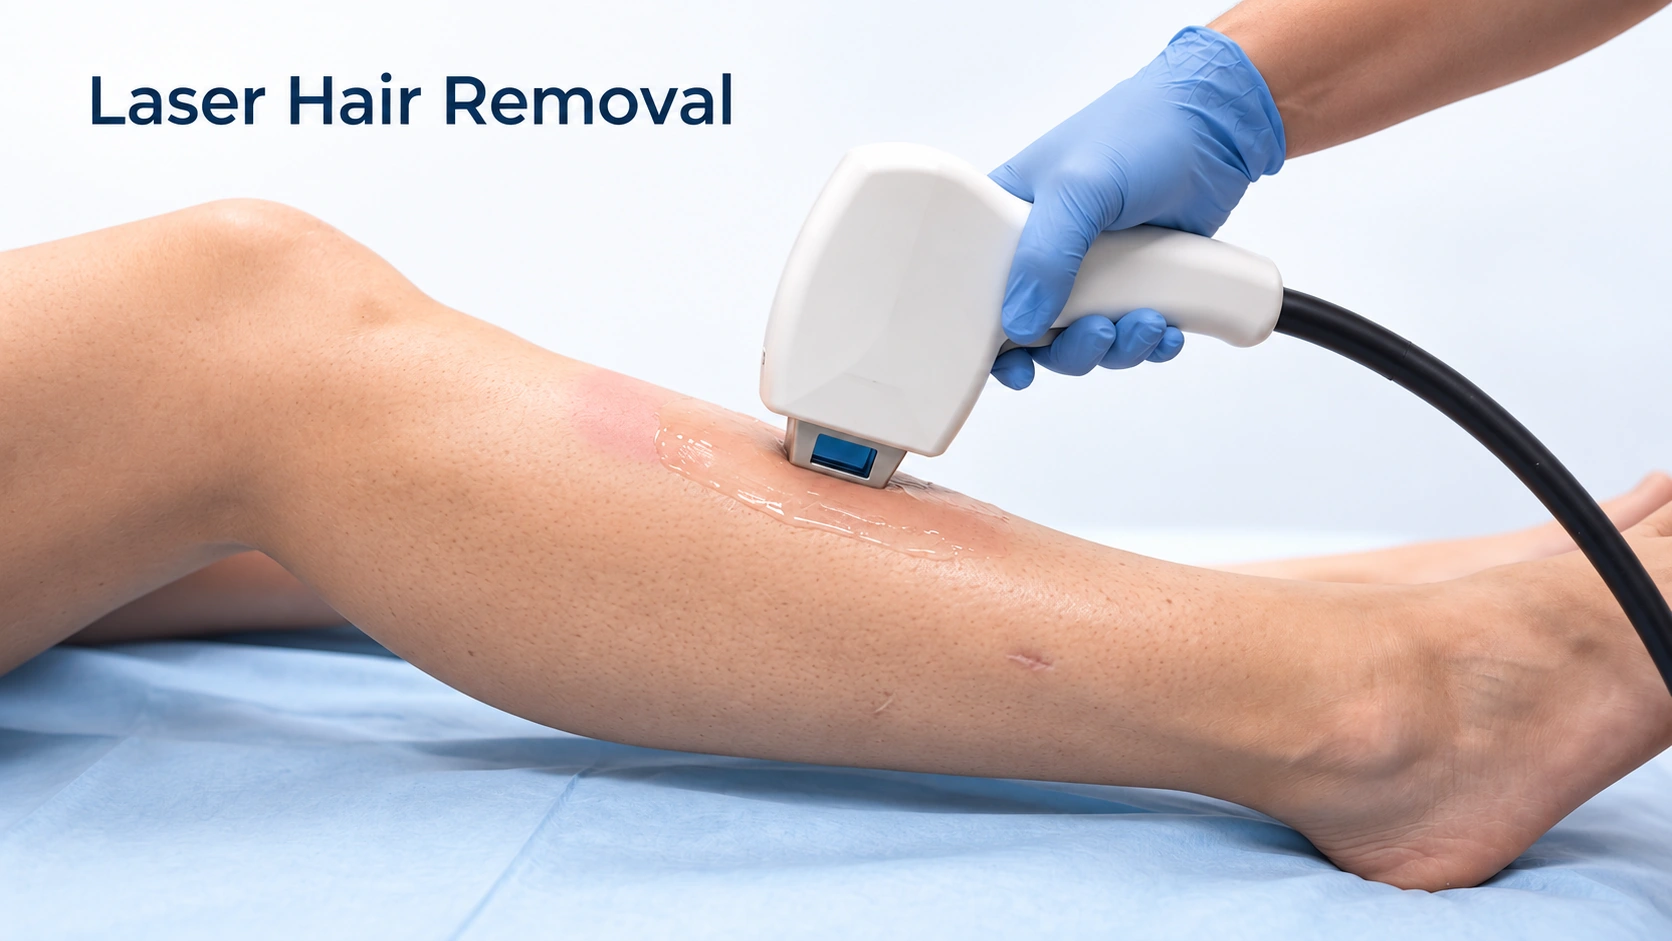
Editorial illustration for Laser Hair Removal, based on the entry’s treatment or equipment reference.

Laser Hair Removal

Strong evidence

The most durable treatment there is for this, because it reduces the number of hairs that can become ingrown at all. It usually takes a series of sessions and it thins rather than eliminates hair for most people, with occasional touch-ups. It is the option to ask about when scarring is starting or when a job requires close shaving.

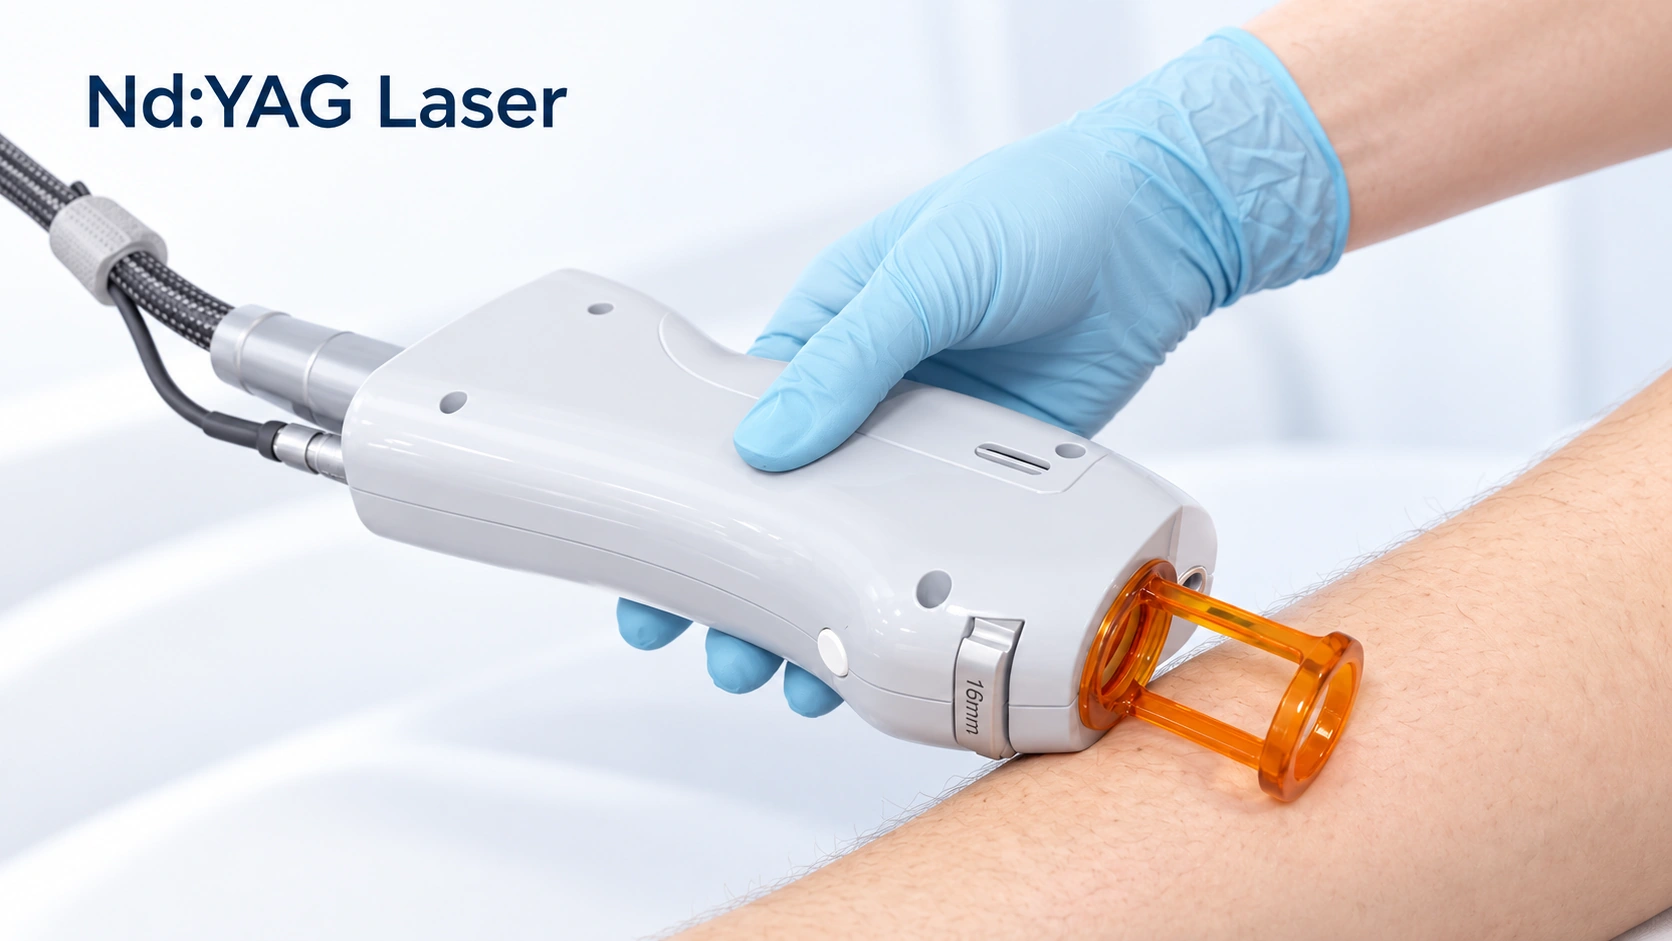
Editorial illustration for Nd:YAG Laser, based on the entry’s treatment or equipment reference.

Nd:YAG Laser

Strong evidence

The specific device used for hair removal on deeper skin tones, at a wavelength of 1064 nm. It passes more safely through pigment in the skin to reach the hair, and it is used routinely for razor bumps. Ask what wavelength a clinic uses, ask how often they treat skin like yours, and have a test patch first, because settings and cooling matter more than the marketing.

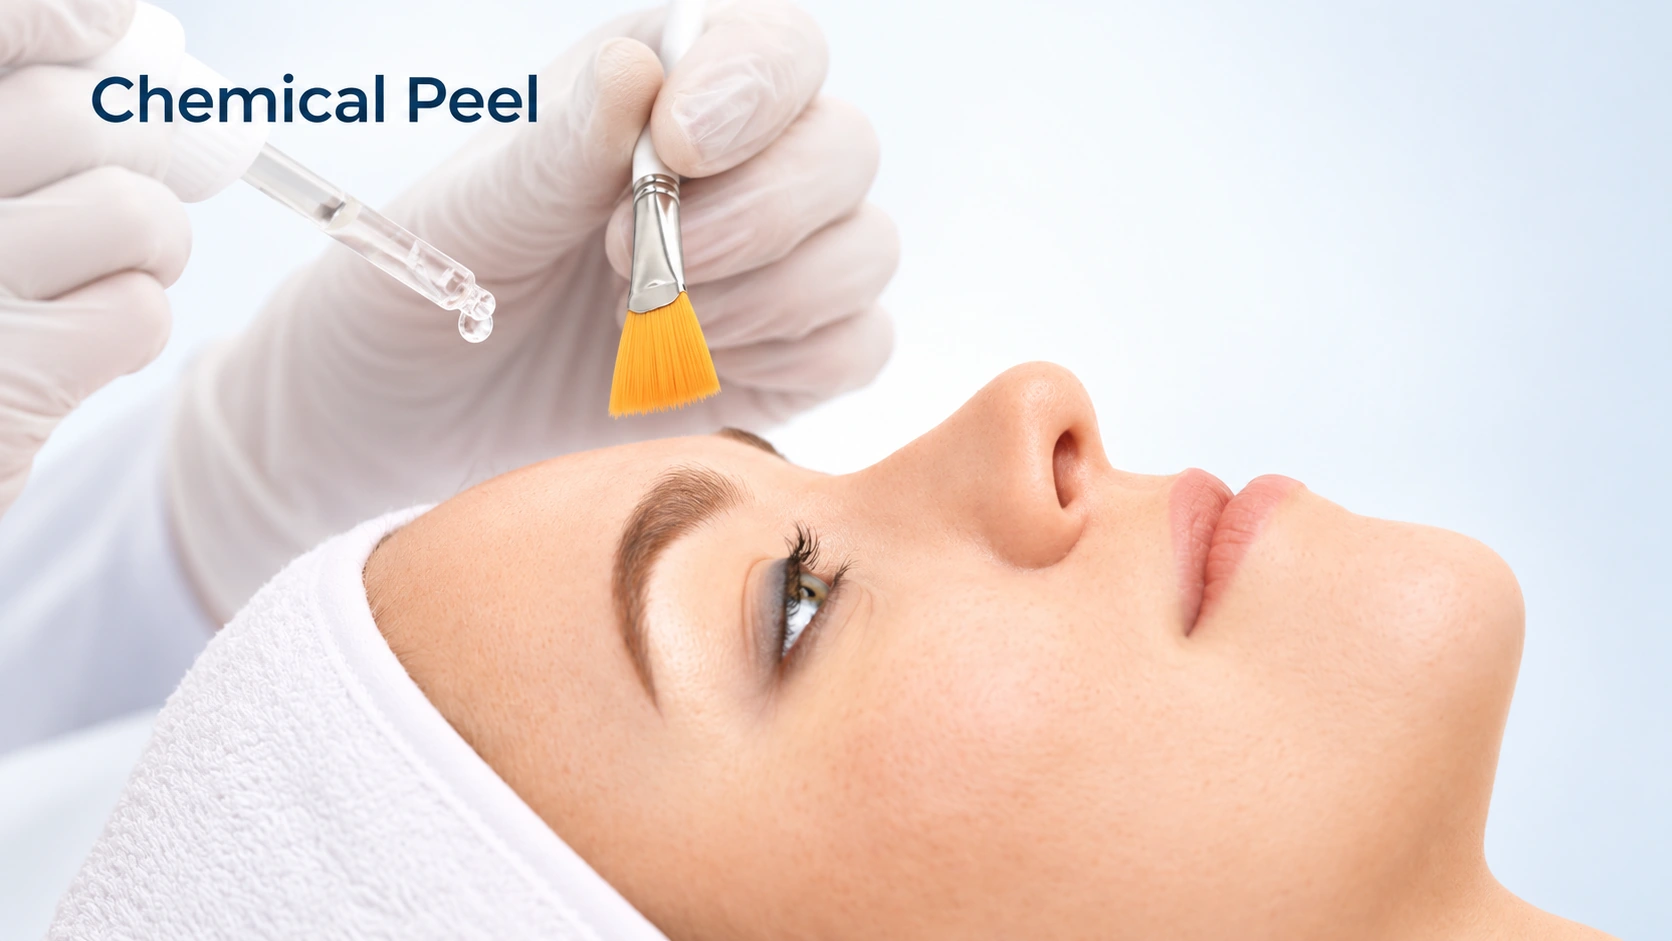
Editorial illustration for Chemical Peel, based on the entry’s treatment or equipment reference.

Chemical Peel

Limited evidence

A course of light salicylic or glycolic peels aimed at the mottled dark marks across the beard and neck once the bumps have stopped. On deeper skin tones it has to be done cautiously and by someone who treats them regularly, because too strong a peel causes exactly the darkening you are trying to clear. It does nothing for the bumps themselves.

Editorial illustration for Electrolysis, based on the entry’s treatment or equipment reference.

Electrolysis

Limited evidence

Destroys hairs one follicle at a time with a fine probe, so it can permanently clear a small stubborn patch. It is slow and uncomfortable over a beard-sized area, which is why laser is the usual choice here. It is worth considering for a few repeatedly troublesome spots rather than a whole neck.

Editorial illustration for Cantharidin, based on the entry’s treatment or equipment reference.

Cantharidin

Strong evidence

A blistering liquid painted onto each bump in the clinic and washed off a few hours later at home. A small blister forms over the next day and the bump lifts off with it. It is painless to apply, which is why it suits children, and it usually takes two or three visits. It is not used on the face or the genitals, and it can leave a dark or pale mark, so a few bumps are treated first to see how the skin reacts.

Editorial illustration for Curettage, based on the entry’s treatment or equipment reference.

Curettage

Moderate evidence

The bumps are scraped off with a small looped instrument, usually after numbing cream has been left on for an hour. It is the fastest option — most of a crop can be dealt with in one visit — and it is the one that gives an immediate result. It is uncomfortable even with numbing, small children often find it distressing, and it can leave small marks or pitted scars where bumps were deep.

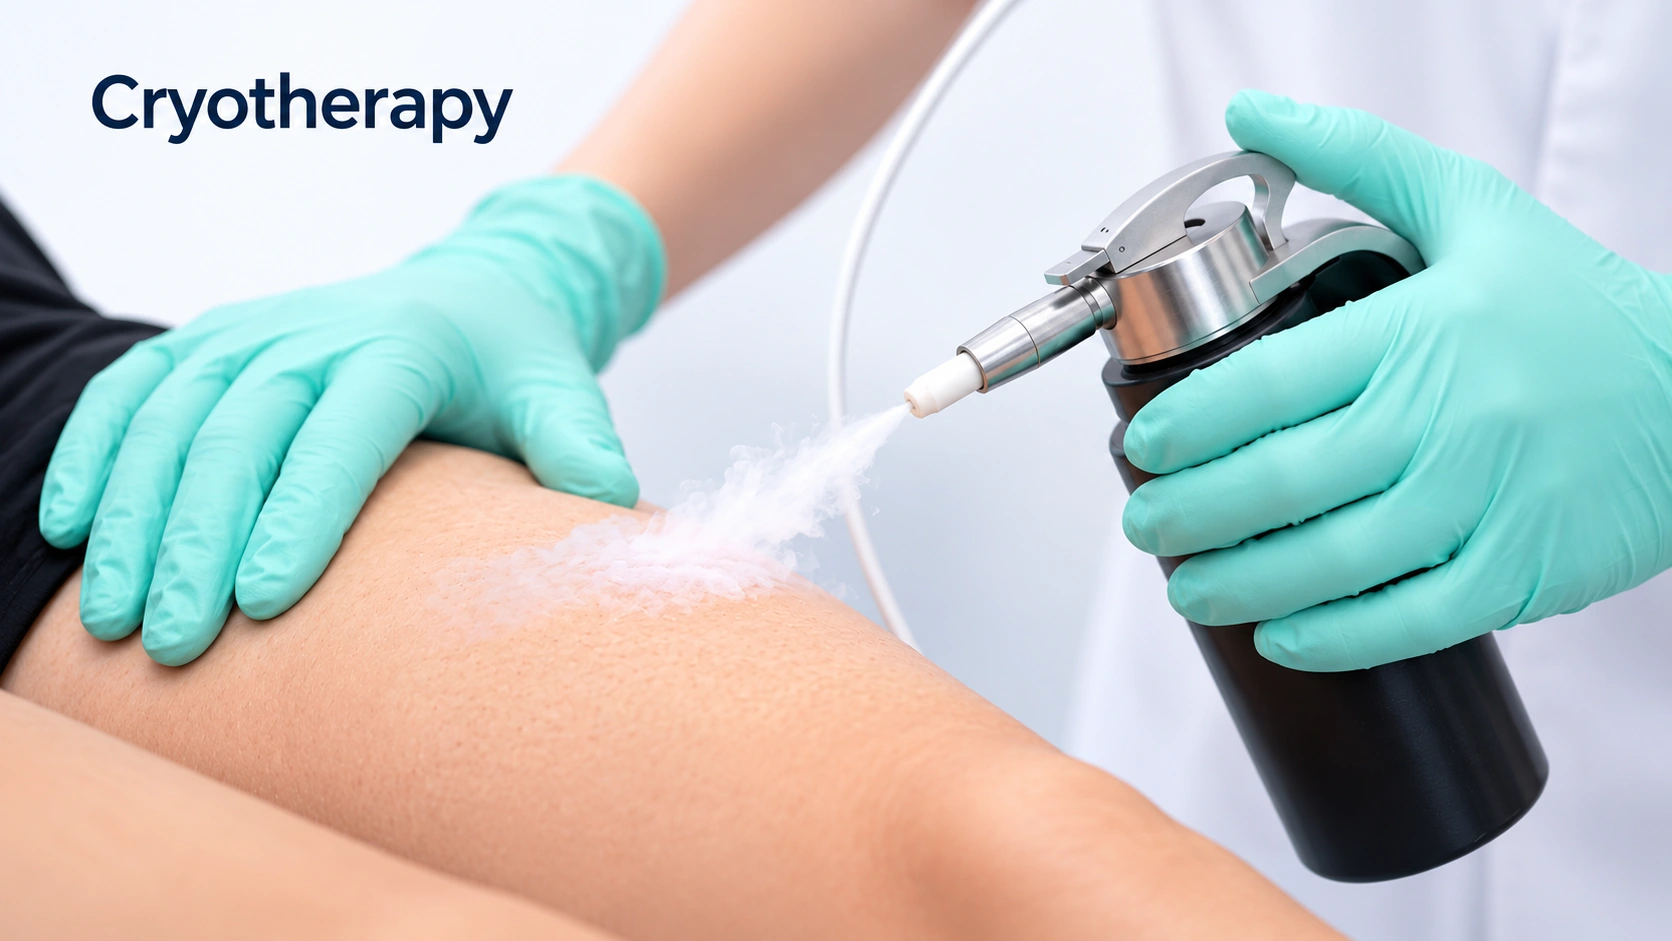
Editorial illustration for Cryotherapy, based on the entry’s treatment or equipment reference.

Cryotherapy

Moderate evidence

Each bump is frozen for a few seconds, and it usually takes several visits a few weeks apart. It works, and it is quick. It also stings sharply at the time, which most young children will not sit through twice, and it leaves dark or pale marks more readily than the other options — a real consideration on deeper skin tones, where those marks can last longer than the infection would have.

Outlook

Long term

A single ingrown hair follows a short, predictable course; the long-term picture depends on what happens to it. Stop removing the hair and this condition stops - beards grown out for three to four weeks usually clear almost completely. Established scarring does not reverse, which is the argument for changing course early.

Molluscum is self-limiting and usually clears within six to eighteen months, occasionally two years or more in children with eczema. The shape of the course catches people out, because the bumps do not all appear at the start and fade together.

Complications

Possible complications
  • Dark marks that outlast the bumps
  • Raised and keloid scars
  • Bumps at the nape of the neck
More details

Dark marks that outlast the bumps
Every inflamed bump can leave a flat darker patch behind, and those patches routinely take several months to fade. They are the most common thing people are left with, and on deeper skin tones they are the most noticeable. They will not clear while new bumps keep forming, so stopping the bumps does more for them than anything applied on top. Daily sunscreen helps, because sun makes them deeper and slower to go.

Raised and keloid scars
Where bumps keep forming in the same place and are shaved over or picked, the skin can build firm raised scars, and in some people keloids that grow beyond the original bump. They form most readily along the jawline, the front of the neck and the nape, and more readily on deeper skin tones. Once a keloid is there it is difficult to treat, so changing the shaving early is worth much more than anything applied later.

Bumps at the nape of the neck
Firm bumps along the hairline at the back of the head are a separate problem called acne keloidalis nuchae. They can thicken into keloid-like scars and leave permanent bald patches, and it is far more common in people with tightly curled hair. It needs treating earlier and harder than bumps anywhere else, because that scarring does not reverse. Bumps in this spot are a reason to book rather than wait.

  • Bacterial infection
  • Marks and scars from picking
  • Bumps on the eyelid
More details

Bacterial infection
A bump that has been scratched or torn open can let ordinary skin bacteria in, and it can turn into impetigo. This is the one thing that looks like the harmless red flare of a bump clearing, so the difference is worth knowing: redness that spreads outward into the skin around the bump, warmth, pus, or fever means it needs checking that week. A single angry bump with normal skin around it is usually good news. Keeping nails short and covering broken bumps is most of the prevention.

Marks and scars from picking
Molluscum itself does not scar. Small round pitted scars come from picking, deep scratching and treatments that burn or blister the skin harder than they needed to. Flat dark or pale marks are far more common and are not scars — they fade over months, more slowly on deeper skin tones. Leaving the bumps alone, treating the itchy skin around them, and starting with a few bumps rather than thirty is how most of this is avoided.

Bumps on the eyelid
A bump on the eyelid margin or very close to the eye can rub the surface of the eye and cause a red, watery, irritated eye that does not settle. It is uncommon, and it is one of the few molluscum situations that should not simply be waited out. The bumps here are treated carefully rather than frozen or scraped, and an eye assessment is sometimes needed as well.

When to get help

When to get help

Seek care for recurring painful bumps, scarring or pus. A large painful swelling or spreading redness may need treatment for infection.

Seek advice for uncertain lesions, extensive disease, eyelid involvement or weakened immunity. Adults with genital bumps should be assessed for other possible causes.

Common questions

Ingrown Hairs:Can I just pull the hair out?

Not out - free it. If a loop of hair crosses the bump, a sterilized needle can lift it from underneath and leave the hair rooted in the follicle. Pulling the whole hair out means the next one grows back through inflamed skin, which often makes another bump in the same place. Never dig for a hair you cannot see. That is how bumps become scars.

Ingrown Hairs:Will laser hair removal work if I have deep skin tone?

Yes. The concern comes from older devices. The standard choice now for deeper skin tones is a long-pulsed 1064 nm Nd:YAG laser, which reaches the hair with less risk to surrounding pigment. It takes a series of sessions, reduces rather than eliminates hair, and touch-ups are common. Ask what wavelength they use, how often they treat skin like yours, and have a test patch.

Ingrown Hairs:Do I have to stop shaving forever?

No. Most people go back to shaving once the bumps clear, as long as it is different from what caused the problem - usually a single blade or trimmer, with the grain, less often, without stretching the skin. If close shaving is unavoidable and bumps keep returning, laser lets you have both.

Ingrown Hairs:Why do I get them on my neck but not my cheeks?

The hair on the neck grows in swirls and changes direction over short distances, so a stroke with the grain in one spot is against it an inch away. The skin there is softer and easier to pull taut. The neck and under the jaw are the classic sites.

Ingrown Hairs:How long do the dark marks take to fade?

Longer than anyone wants. A mark from one bump commonly takes several months. Years of repeated bumps take longer, and nothing fades while new bumps keep forming. Two things speed it up: stopping the new bumps, and daily sunscreen.

Ingrown Hairs:Is this acne?

No, though they look similar and sometimes occur together. Acne begins with a clogged oil gland and features blackheads and whiteheads. This begins with a hair growing back into the skin, appears in shaved areas, and follows the shaving schedule. Some acne treatments help, but not the cause.

Molluscum Contagiosum:How long will this last?

Usually six to eighteen months, sometimes longer, with new bumps appearing while older ones clear. That is the normal course, not a sign something is wrong. Children with eczema are at the longer end.

Molluscum Contagiosum:One of the bumps has gone red and angry. Is it infected?

Most often it is clearing. As the immune system recognizes the virus, bumps become red, swollen and tender, sometimes crusted, then disappear — the beginning-of-the-end sign. Genuine bacterial infection is possible, so redness spreading outward with warmth, pus or fever should be checked the same week.

Molluscum Contagiosum:Should my child stay home from school or stop swimming?

No. Molluscum is not a reason to miss school, nursery or swimming. Cover the bumps where practical, use your own towel, and do not share kickboards and floats.

Molluscum Contagiosum:Does it need to be treated?

Not for medical reasons - it clears on its own and leaves nothing behind if left alone. Treating is reasonable when the bumps are in an awkward place, being scratched raw, very numerous, keeping eczema stirred up, or when the family has had enough.

Molluscum Contagiosum:Will it leave scars?

The infection itself does not scar. Scars come from picking, deep scratching or aggressive treatment. Flat dark or pale marks where bumps sat are not scars - they fade over several months, more slowly on deeper skin tones.

Molluscum Contagiosum:I am an adult with these in my groin. What does that mean?

In adults, molluscum in the groin, genitals and inner thighs is usually passed through sexual contact, so it is worth being seen and worth testing for other sexually transmitted infections. It can also arrive by ordinary skin contact or shared towels, including from a child in the house, so it is not proof of anything.
Sources

Sources and further reading

  1. DermNet
  2. DermNet
Dermapedia on YouTube