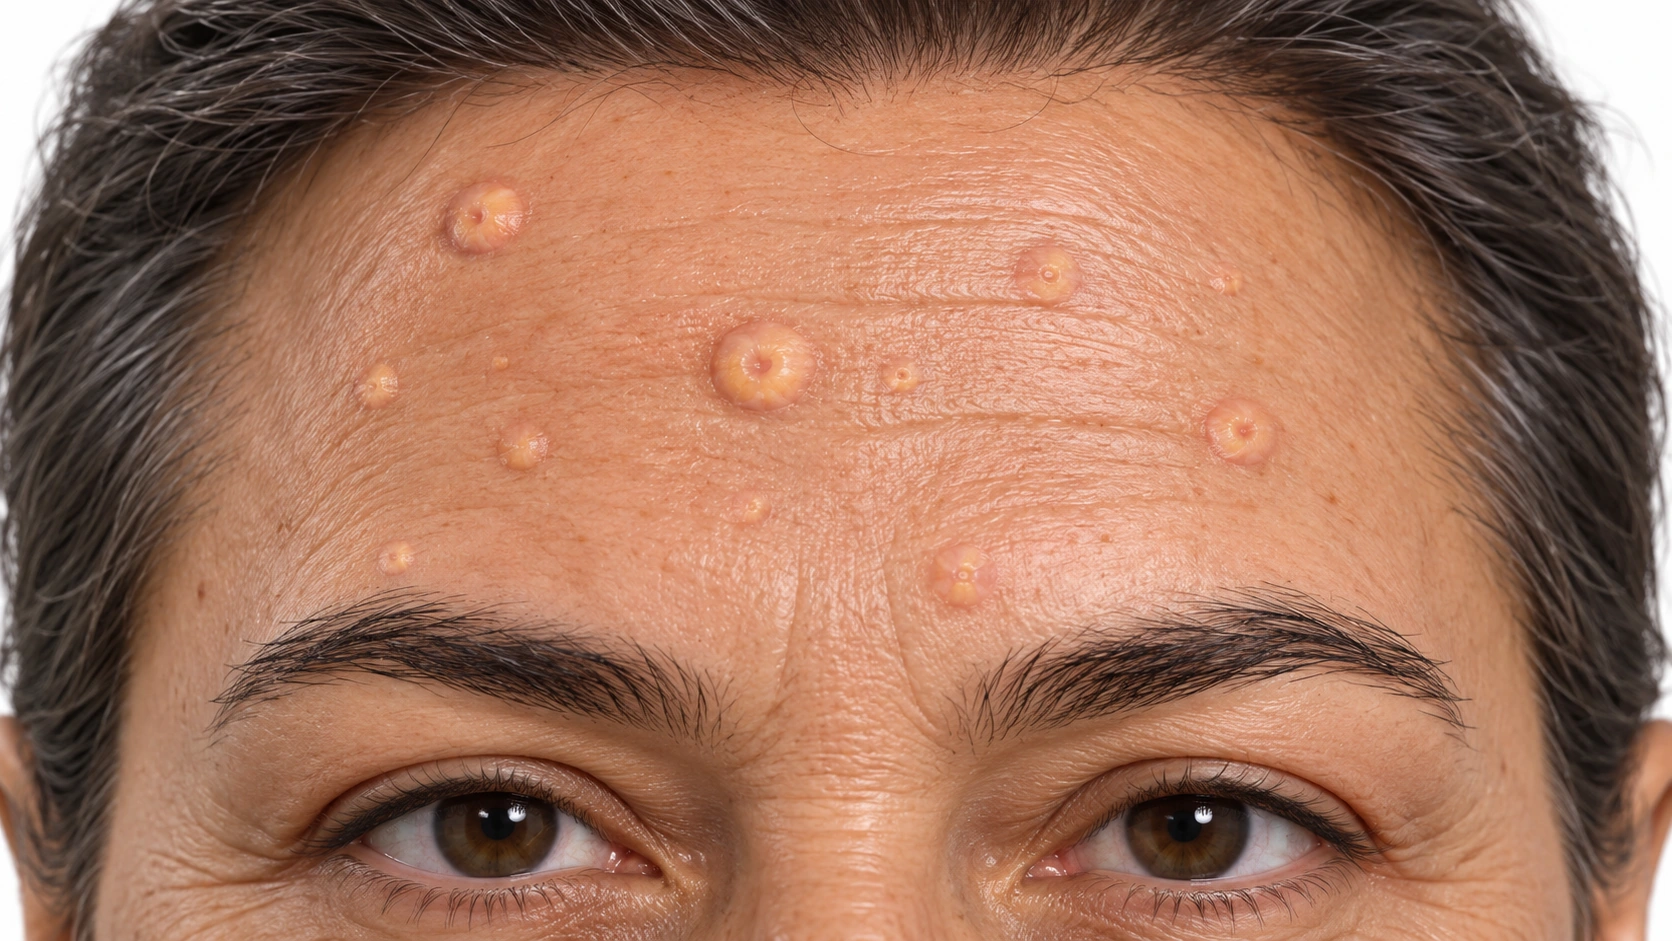
Molluscum Contagiosum
Molluscum contagiosum is a common viral skin infection that causes small, firm, dome-shaped bumps with a dimple in the middle. It is harmless, it spreads easily among children, and it clears on its own - though that can take a year or more.
Key facts
Molluscum Contagiosum at a glance.
Typical signs
Pearly bumps with central dimples
Common locations
Trunk, limbs, skin folds
Expected course
Usually clears over months to years
Treatment options
Observation or targeted treatment
What is it?
Top things to know about Molluscum Contagiosum
- It is a poxvirus infection. It produces small firm bumps, often with a central dip.
- It is common in children. In healthy people it usually clears without treatment.
- It spreads by contact. Skin contact, shared objects and scratching can spread it.
- Some cases need review. Genital lesions, or many large lesions in an adult, warrant assessment.
What it looks like
What Molluscum Contagiosum looks like
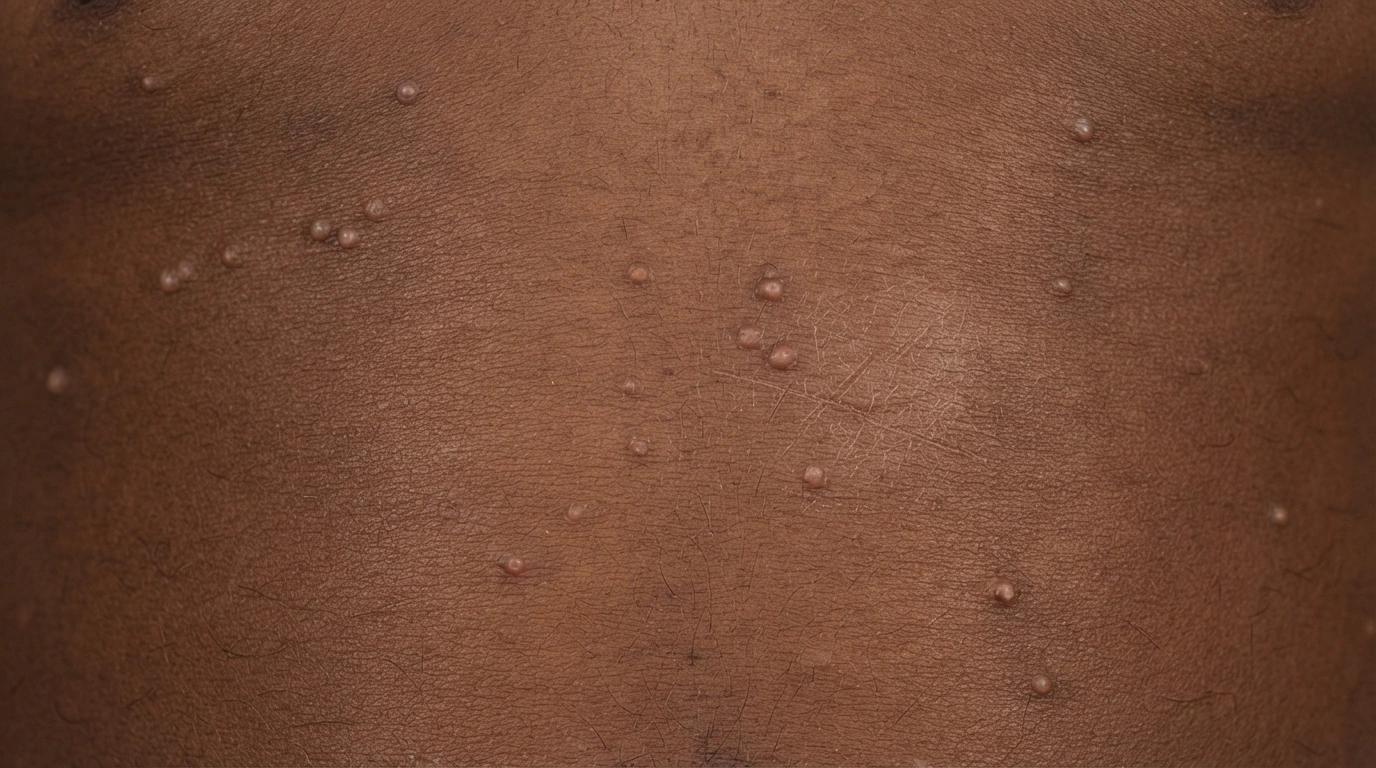
Molluscum contagiosum is a common viral skin infection, especially in children. It causes small, firm, smooth, dome-shaped bumps, usually 2 to 5 millimeters across, that are pearly or skin-colored. Many have a tiny dimple in the center. The bumps often appear in groups on the trunk, arms, legs and in skin folds. They can spread by scratching and usually clear on their own within months to a couple of years.
Pearly bumps with a central dimple
Smooth, shiny and dome-shaped, with a tiny dip in the center.
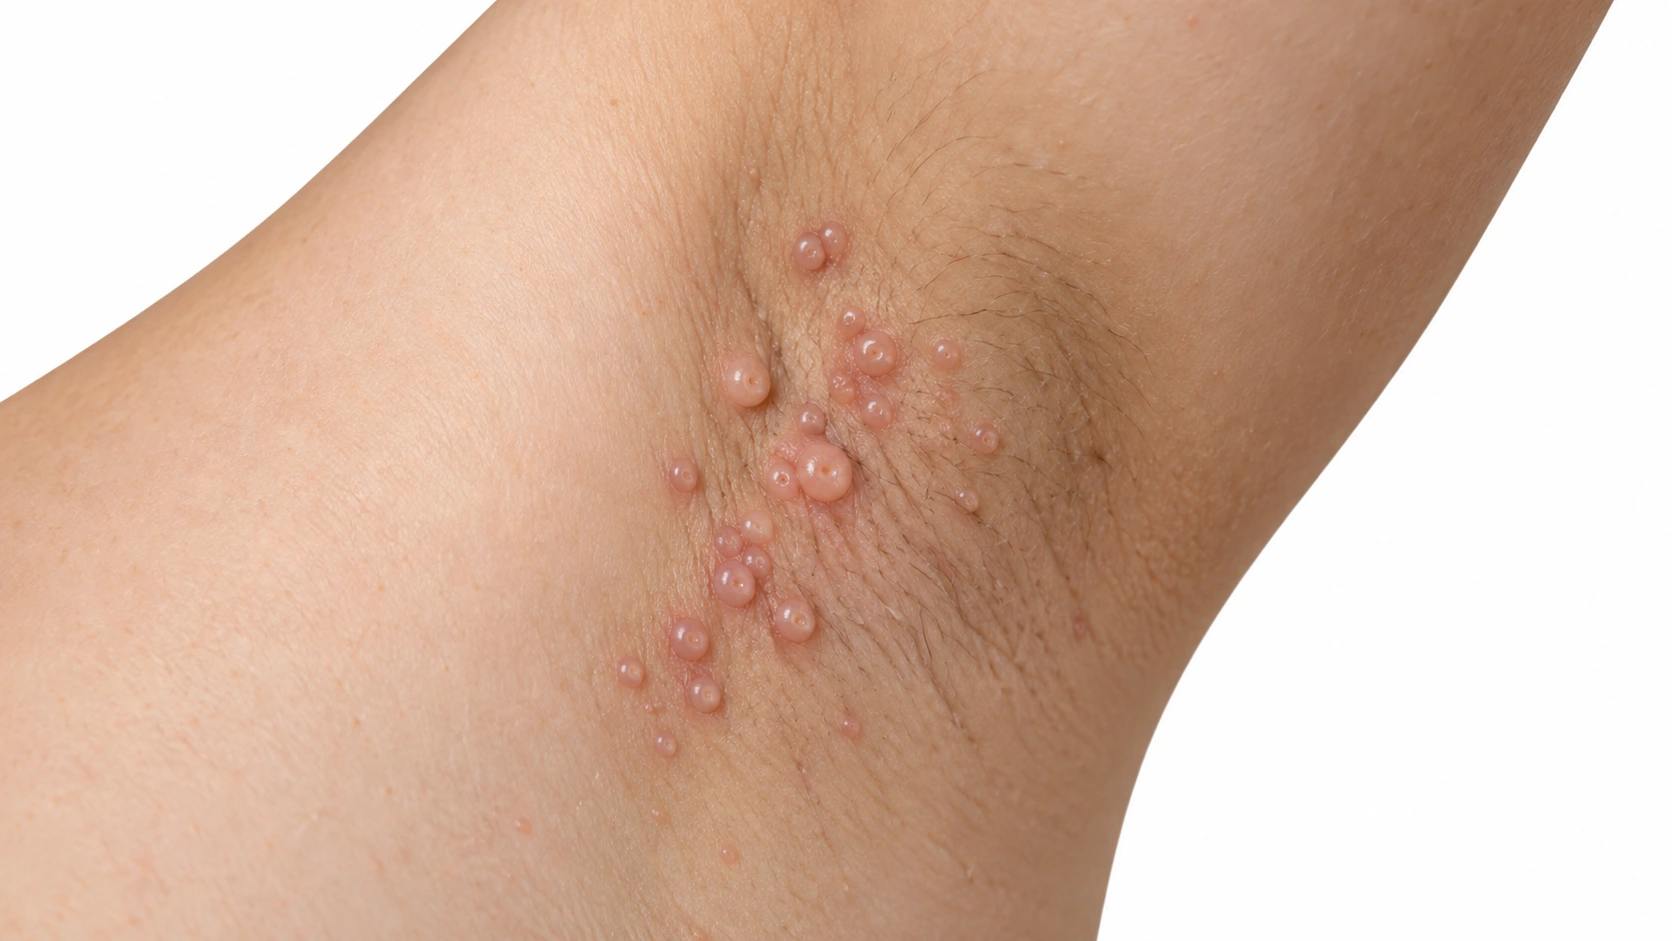
Clusters
Groups in skin folds.
Where it shows up
Molluscum can cluster on the trunk, arms, legs and folds. Genital involvement can occur, particularly in adults.
Upper arms
Locations on the outer upper arms.
Trunk
Locations on the front of the trunk.
Armpits
Locations in the underarm folds.
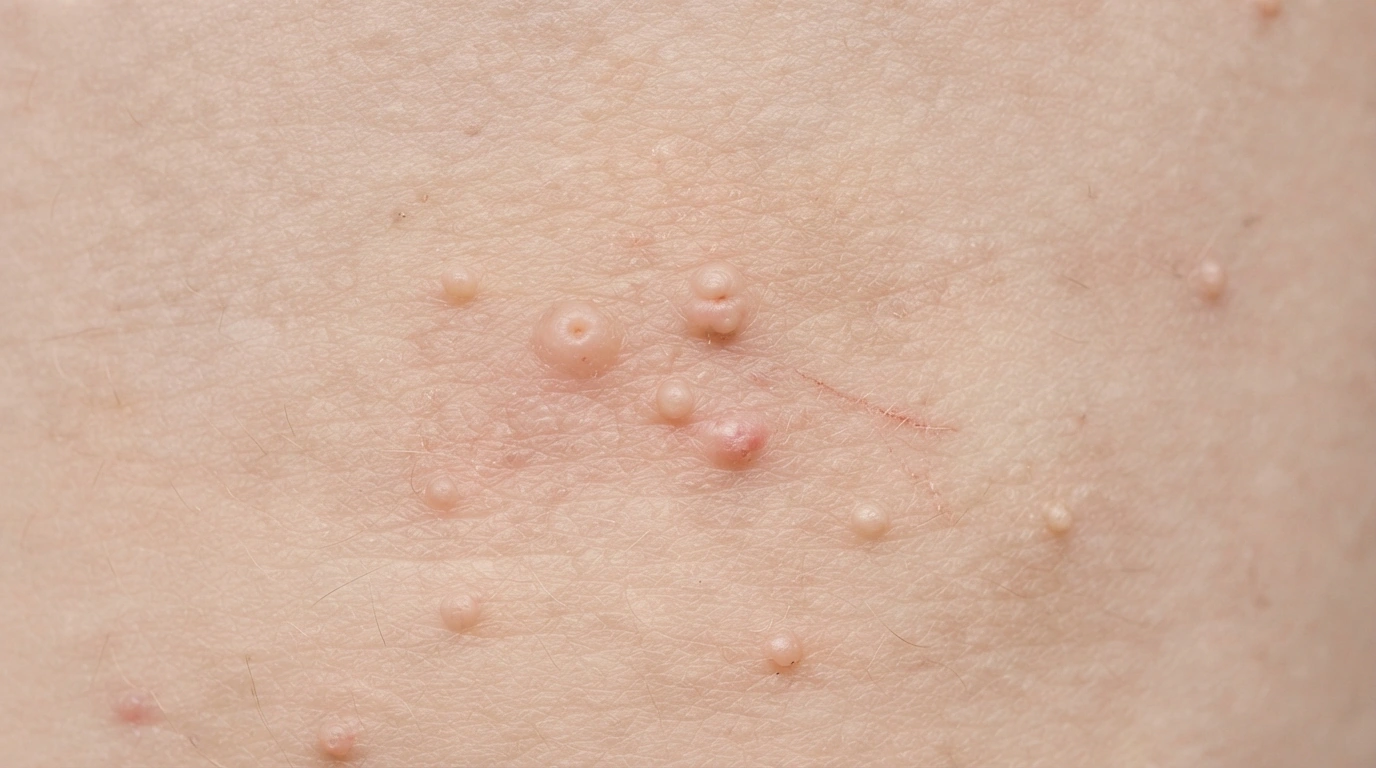
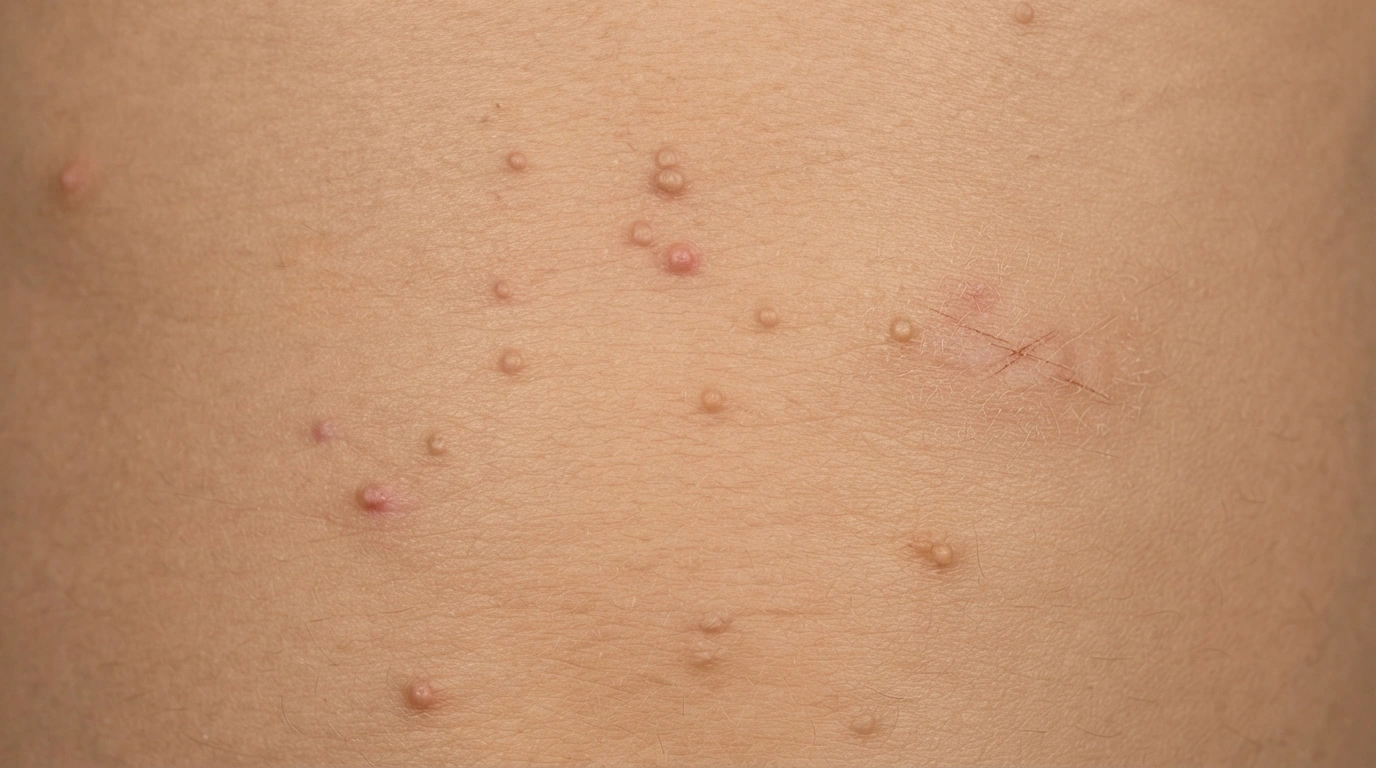
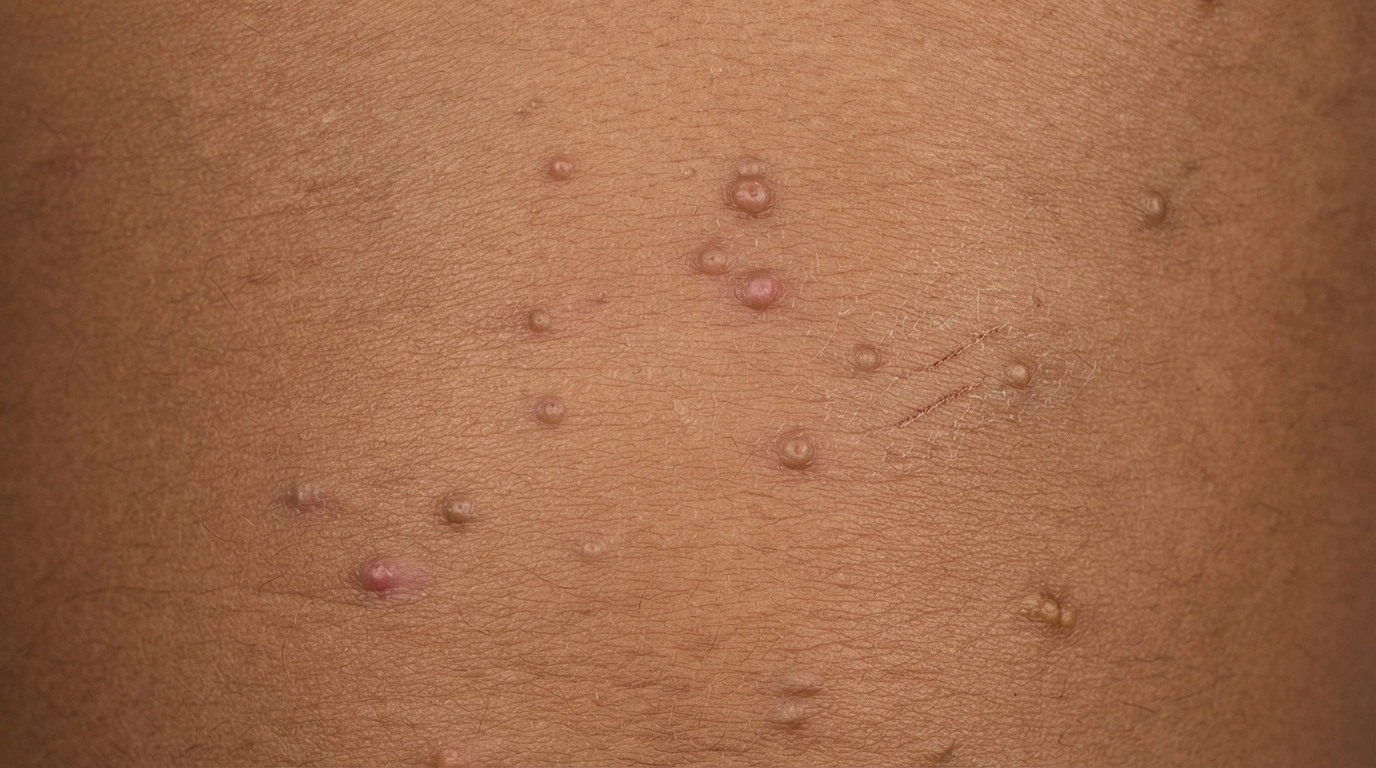
On different skin tones
Molluscum Contagiosum on different skin tones
Molluscum looks similar on all skin tones as pearly, skin-colored bumps. On brown and Black skin, the bumps may look slightly lighter or darker than the surrounding skin, and healing bumps can leave temporary light or dark spots.
What happens in Molluscum Contagiosum?

The molluscum virus infects surface skin cells and causes them to enlarge. A small smooth bump develops, often with a characteristic central dimple.
- A dimpled bump appears: The center often has a small depression.
- The virus reaches skin cells: Contact spreads the molluscum virus.
- Infected cells enlarge: Viral material collects inside affected cells.
Causes and triggers
What causes Molluscum Contagiosum
Causes
Why it happens
Molluscum contagiosum is caused by a poxvirus that infects the top layer of skin.
Risk factors
Raise the odds
- Children aged 1 to 10
- Eczema
- Weakened immunity
Triggers
Passes it on
- Skin-to-skin contact (Well established)
- Scratching and spreading to other areas (Well established)
- Shared towels and bath toys (Strong link)
- Sexual contact in adults (Strong link)
- Swimming pools (Possible)
When it usually starts
When it usually starts
Molluscum Contagiosum
Most common in young children; adults can also acquire it, including through sexual contact.
Daily care
Daily care for Molluscum Contagiosum
Keeping nails short and hands busy
Short nails help limit skin damage from scratching.
Covering bumps with clothing or a plaster
Cover bumps to reduce touching and skin-to-skin spread.
Own towel, own flannel, no shared baths
Keep towels and washcloths separate and avoid sharing bathwater.
Stopping shaving over the affected area
Avoid shaving over bumps, which can spread them to nearby skin.
Treating eczema properly
Less itching, less scratching, less spread.
Cantharidin, applied in clinic
A blistering agent painted on, washed off hours later.
Curettage
Bumps scraped off in one visit, after numbing cream.
Prescription topical treatments
Berdazimer gel, retinoids and potassium hydroxide.
Treating a few bumps first
Shows how the skin reacts before thirty.
Review immune-suppressing medicines with the prescriber; do not stop them yourself
Immune suppression can affect infection persistence. Tell the treating clinician and do not stop a prescribed medicine on your own.
Watchful waiting
Many cases clear without treatment; discuss whether observation is appropriate with a clinician.
Avoid: Scratching
Breaks a bump open and plants virus nearby.
Avoid: Picking or squeezing bumps
Releases the virus-packed core onto nearby skin.
Avoid: Shaving over or near bumps
Seeds molluscum along the path.
Avoid: Sharing bath things
Towels, flannels, sponges and bath water.
Avoid: Shared mats and equipment
Avoid sharing unclean mats or equipment that touches affected skin.
Avoid: Rubbing, friction and occlusive clothing
Friction breaks the surface and moves virus.
Avoid: Untreated eczema
An open door and a reason to scratch.
Avoid: Aggressive home treatment
Digging or burning leaves scars and dark marks.
Treatments
Treatments for Molluscum Contagiosum

Hydrocortisone 1%
For the dry itchy eczema-like patch that develops around the bumps in about a third of children — not for the bumps themselves. Treating it properly matters, because the itch drives the scratching and the scratching is what spreads the infection. Use it on the skin between and around the bumps, thinly and for a short course. Strong steroid creams applied over the bumps calm the redness and can help the virus stay longer.

Salicylic Acid
The wart products in the pharmacy are the wrong tool here. Molluscum is a poxvirus, not the wart virus, and the bumps are soft domes rather than thickened skin for an acid to dissolve. On thin skin, on a child, and on thirty bumps at once, it mostly buys irritation and dark marks. If a bump is going to be treated, the clinic options are more reliable and better controlled.

Tea Tree Oil
A common suggestion, usually combined with iodine, and the evidence behind it is a small number of low-quality studies. Against an infection that clears by itself, that is very hard to read. The real drawback is that it stings and it commonly causes an allergic rash on children's skin, which then itches, which then gets scratched.
Berdazimer
Berdazimer gel. A newer prescription gel mixed and applied at home once a day, designed specifically for molluscum. In its trials about a third of children had all their bumps clear at twelve weeks, against roughly one in five given the placebo gel — a real effect, but a modest one. Redness and irritation where it is applied are common, and cost and availability are the practical limits.
Potassium hydroxide solution
A dilute alkaline solution dabbed on individual bumps at home, usually once or twice a day until each bump becomes inflamed and then clears. It is cheap and it can be done without appointments. It stings, it works by irritating the skin, and it can leave dark or pale marks if it is overdone — so it goes on the bumps only, and starting with a few is sensible.

Tretinoin
A retinoid dabbed onto individual bumps to irritate them into clearing. It is sometimes chosen for bumps on the face, where blistering or scraping is less appealing. The evidence for it in molluscum is thin, it is slow, and it makes the skin around the bumps red and flaky, which is its own reason to scratch.
Imiquimod
This one was studied properly in children, in two large trials, and it did not work any better than the placebo cream — while causing more skin reactions, and in some children pain and swelling. It is still prescribed for molluscum out of habit. On the evidence there is, it should not be.
Cimetidine
An old stomach-acid tablet, taken by mouth for several weeks in the hope of nudging the immune system into recognizing the virus. It appeals because it is painless and needs no procedure, which matters for a frightened child with many bumps. The trials do not support it, and it interacts with a number of other medicines, so it is a long shot rather than a plan.

Cantharidin
A blistering liquid painted onto each bump in the clinic and washed off a few hours later at home. A small blister forms over the next day and the bump lifts off with it. It is painless to apply, which is why it suits children, and it usually takes two or three visits. It is not used on the face or the genitals, and it can leave a dark or pale mark, so a few bumps are treated first to see how the skin reacts.
Curettage
The bumps are scraped off with a small looped instrument, usually after numbing cream has been left on for an hour. It is the fastest option — most of a crop can be dealt with in one visit — and it is the one that gives an immediate result. It is uncomfortable even with numbing, small children often find it distressing, and it can leave small marks or pitted scars where bumps were deep.
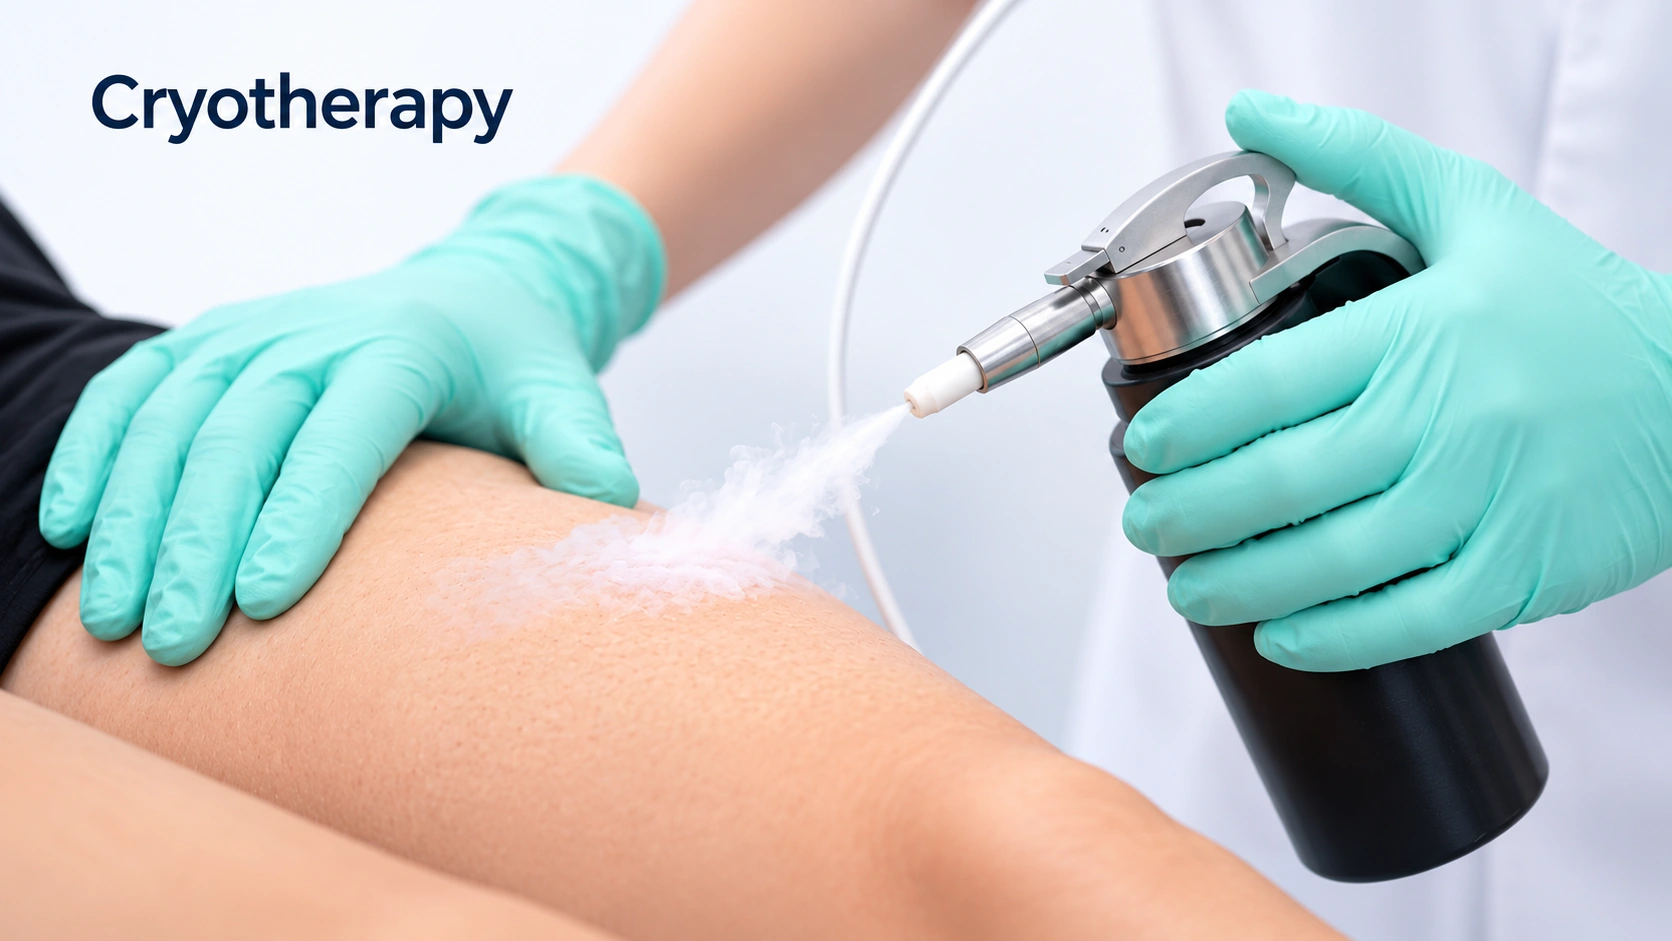
Cryotherapy
Each bump is frozen for a few seconds, and it usually takes several visits a few weeks apart. It works, and it is quick. It also stings sharply at the time, which most young children will not sit through twice, and it leaves dark or pale marks more readily than the other options — a real consideration on deeper skin tones, where those marks can last longer than the infection would have.
Outlook
What to expect with Molluscum Contagiosum
Molluscum is self-limiting and usually clears within six to eighteen months, occasionally two years or more in children with eczema. The shape of the course catches people out, because the bumps do not all appear at the start and fade together.
- 1
Early weeks · The first bumps
Individual bumps last a few weeks to a few months. Only a few are there at the start, so the size of the problem now says little about where it goes.
- 2
The middle months · Numbers rising
New bumps keep arriving while older ones resolve, so the total rises for months before it falls, often peaking around the middle.
- 3
Along the way · Any point in the episode
Roughly a third of children develop a dry, itchy eczema-like patch around the bumps. It is a reaction to the virus, not a new problem, and it settles as the bumps do. Treat it anyway, because the itching drives scratching and scratching spreads the infection.
- 4
The end · Over a month or two
As the immune system recognizes the virus, a bump becomes red, swollen, tender, sometimes crusted. This gets mistaken for bacterial infection and treated with antibiotics that were not needed. When one bump does it, others follow within weeks and the crop can clear.
- 5
After clearing · The months that follow
Immunity is usually good afterwards. Flat dark or pale marks can remain and fade over months. True scars come from picking, deep scratching or aggressive treatment, not the infection.
Complications
Complications to know about
Bacterial infection
A bump that has been scratched or torn open can let ordinary skin bacteria in, and it can turn into impetigo. This is the one thing that looks like the harmless red flare of a bump clearing, so the difference is worth knowing: redness that spreads outward into the skin around the bump, warmth, pus, or fever means it needs checking that week. A single angry bump with normal skin around it is usually good news. Keeping nails short and covering broken bumps is most of the prevention.
Marks and scars from picking
Molluscum itself does not scar. Small round pitted scars come from picking, deep scratching and treatments that burn or blister the skin harder than they needed to. Flat dark or pale marks are far more common and are not scars — they fade over months, more slowly on deeper skin tones. Leaving the bumps alone, treating the itchy skin around them, and starting with a few bumps rather than thirty is how most of this is avoided.
Bumps on the eyelid
A bump on the eyelid margin or very close to the eye can rub the surface of the eye and cause a red, watery, irritated eye that does not settle. It is uncommon, and it is one of the few molluscum situations that should not simply be waited out. The bumps here are treated carefully rather than frozen or scraped, and an eye assessment is sometimes needed as well.
When to get help
When to get help
When to seek care
Seek advice for uncertain lesions, extensive disease, eyelid involvement or weakened immunity. Adults with genital bumps should be assessed for other possible causes.
Lookalikes
What else could it be?
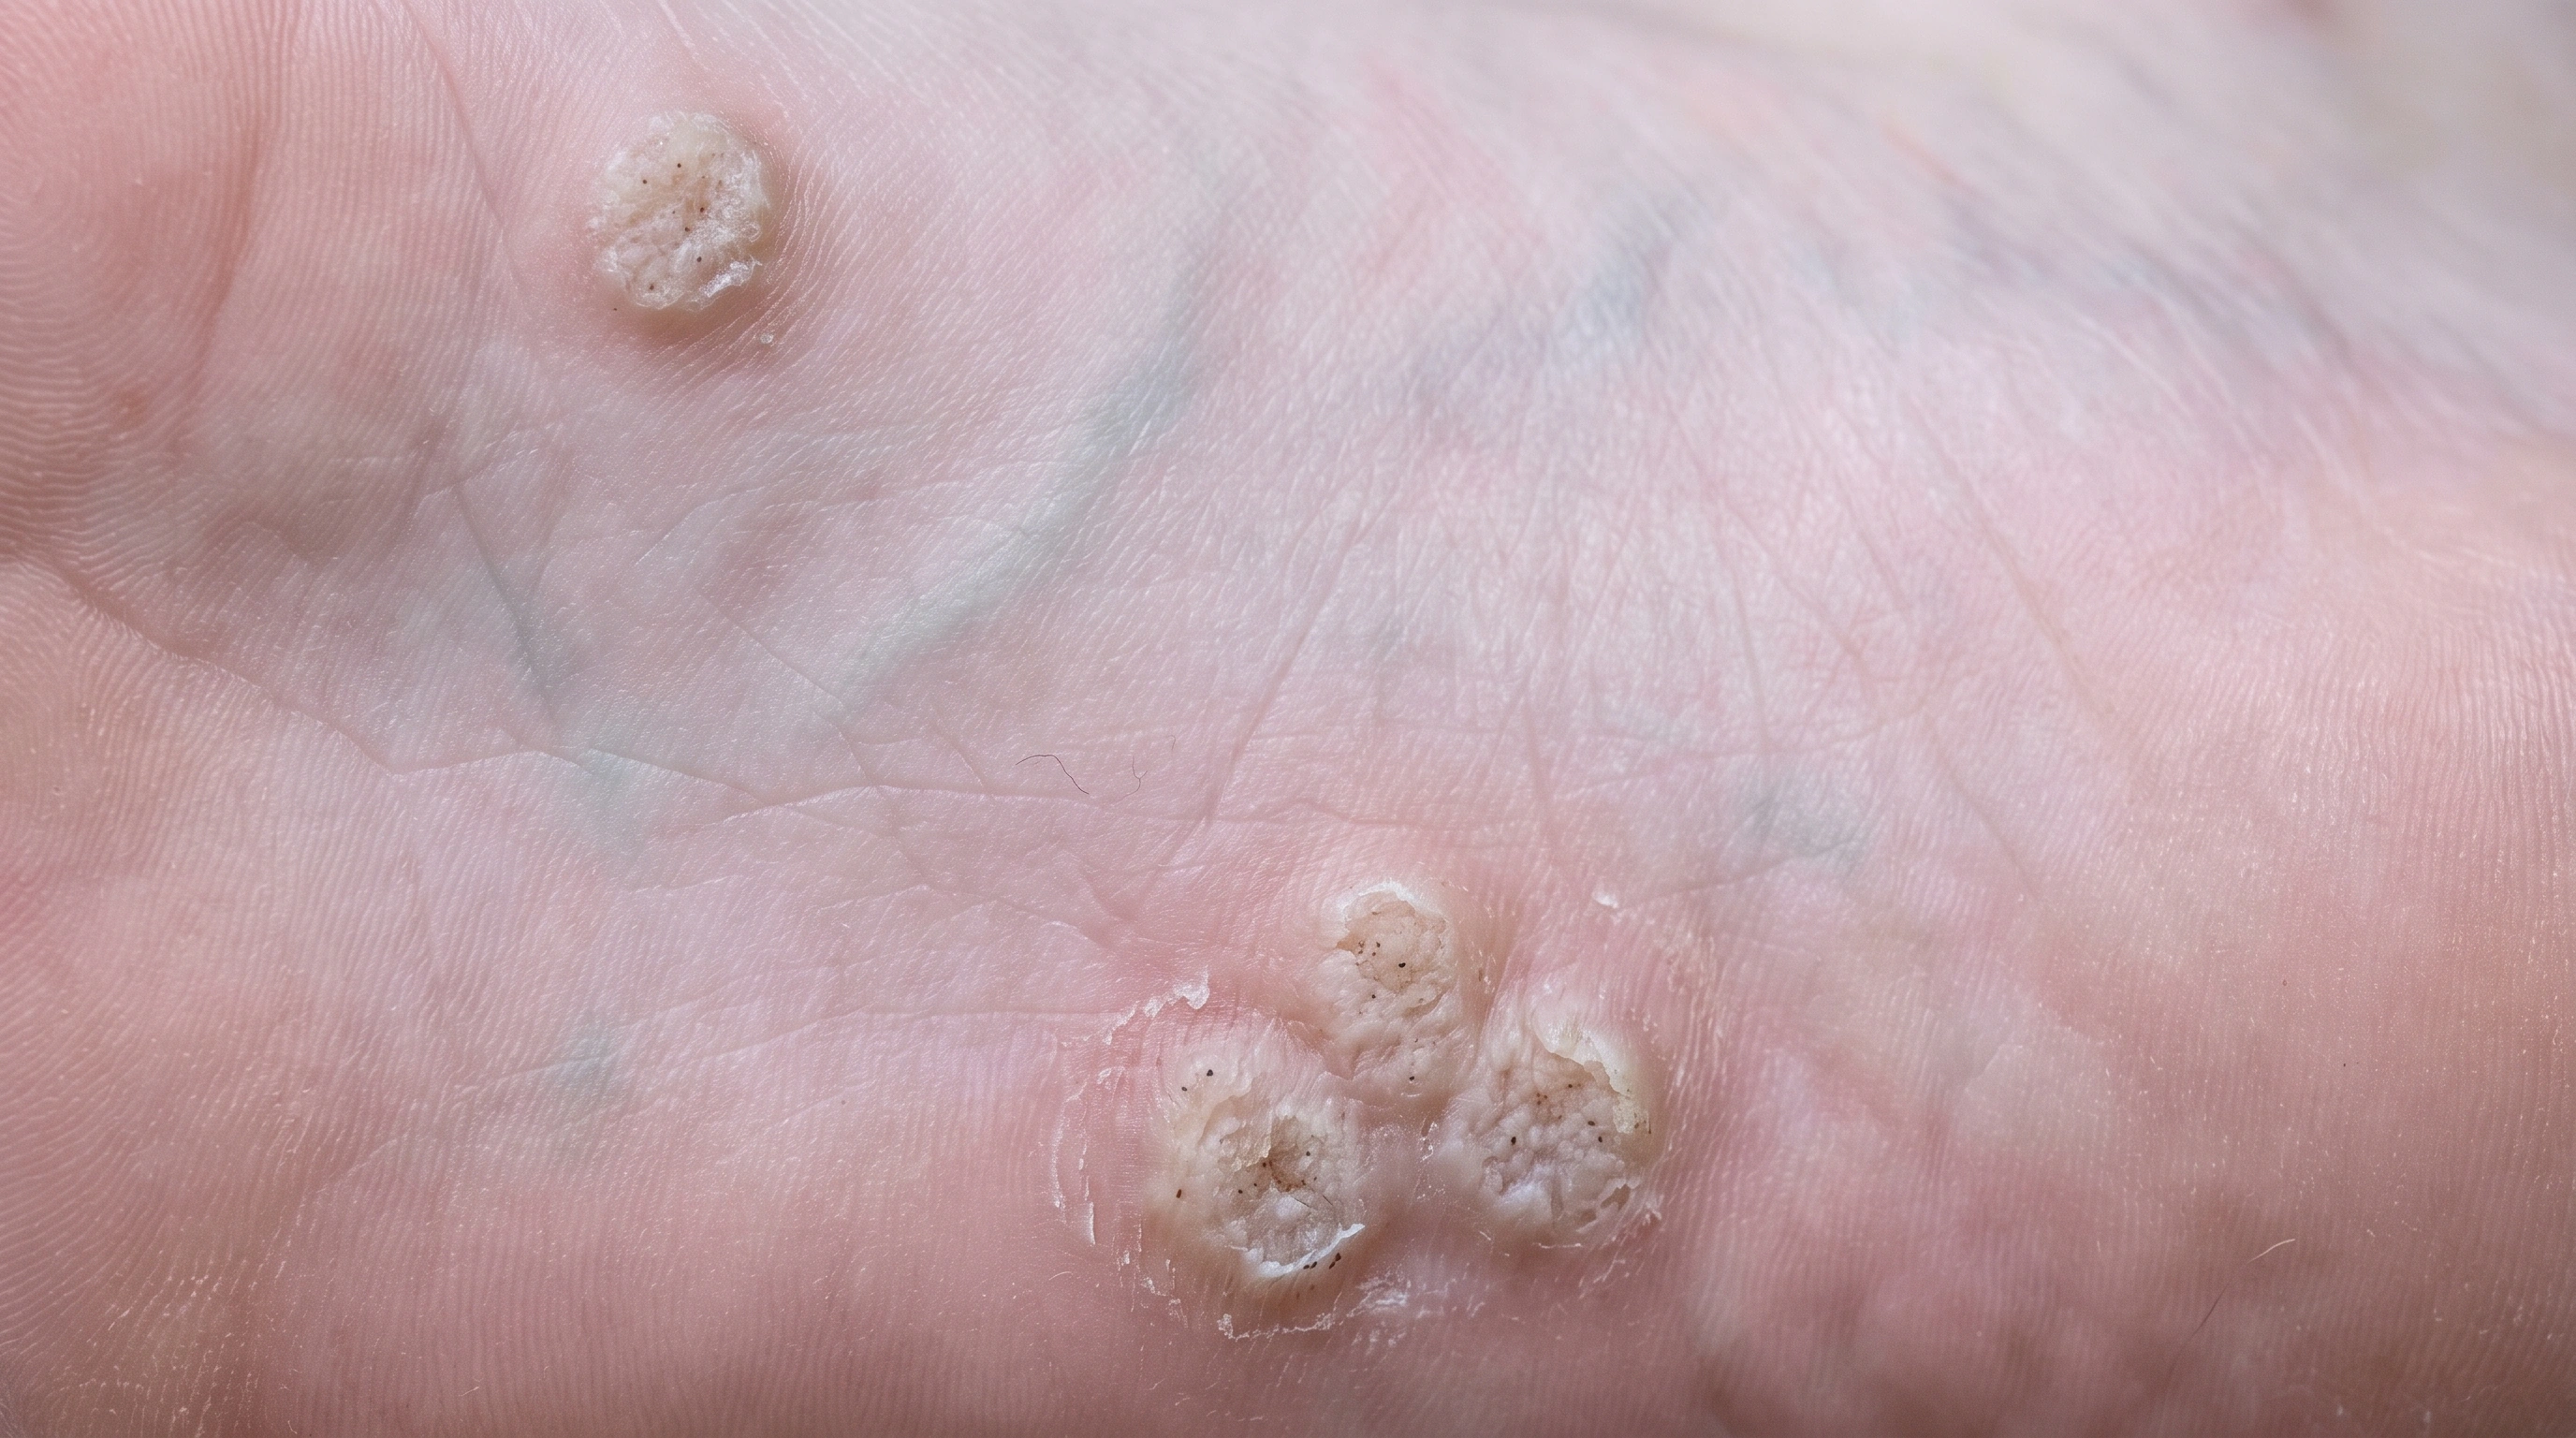
Warts
Warts usually have a rough surface, sometimes with tiny dark dots. Molluscum bumps are smoother and often have a small dip in the center.

Milia
Milia are usually tiny, firm white bumps without a central dip. Molluscum bumps are often larger, dimpled, and appear in multiplying clusters.
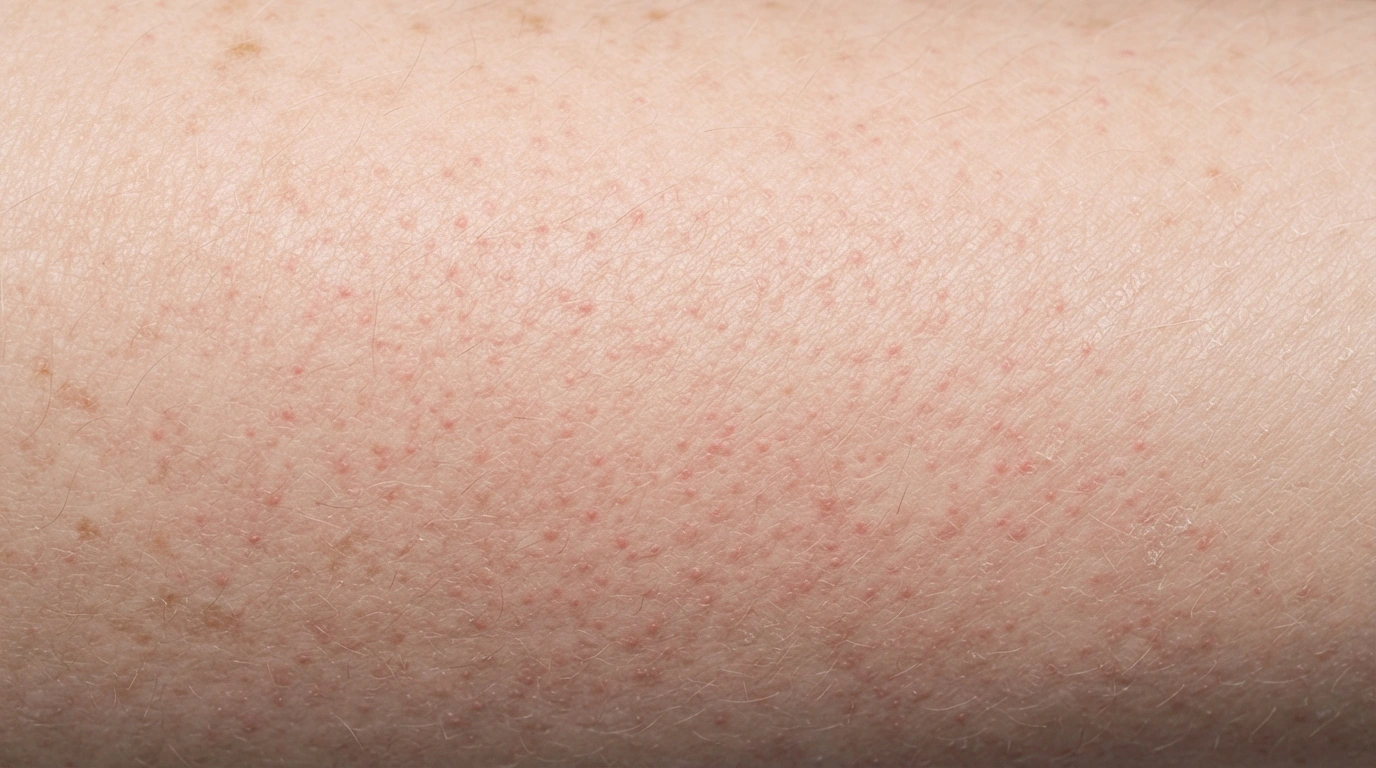
Keratosis Pilaris
Keratosis pilaris feels rough and is evenly spread around hairs. Molluscum forms larger, smoother bumps with central dips, often in scattered clusters.
Questions
Questions you might be asking.
How long will this last?
Usually six to eighteen months, sometimes longer, with new bumps appearing while older ones clear. That is the normal course, not a sign something is wrong. Children with eczema are at the longer end.
One of the bumps has gone red and angry. Is it infected?
Most often it is clearing. As the immune system recognizes the virus, bumps become red, swollen and tender, sometimes crusted, then disappear — the beginning-of-the-end sign. Genuine bacterial infection is possible, so redness spreading outward with warmth, pus or fever should be checked the same week.
Should my child stay home from school or stop swimming?
No. Molluscum is not a reason to miss school, nursery or swimming. Cover the bumps where practical, use your own towel, and do not share kickboards and floats.
Does it need to be treated?
Not for medical reasons - it clears on its own and leaves nothing behind if left alone. Treating is reasonable when the bumps are in an awkward place, being scratched raw, very numerous, keeping eczema stirred up, or when the family has had enough.
Will it leave scars?
The infection itself does not scar. Scars come from picking, deep scratching or aggressive treatment. Flat dark or pale marks where bumps sat are not scars - they fade over several months, more slowly on deeper skin tones.
I am an adult with these in my groin. What does that mean?
In adults, molluscum in the groin, genitals and inner thighs is usually passed through sexual contact, so it is worth being seen and worth testing for other sexually transmitted infections. It can also arrive by ordinary skin contact or shared towels, including from a child in the house, so it is not proof of anything.
Sources
Sources and further reading
Related
Keep exploring.
Milia

Cantharidin
Warts
Keratosis Pilaris
Salicylic Acid
Tea Tree Oil
Cryotherapy
Tretinoin
Milia vs Molluscum Contagiosum
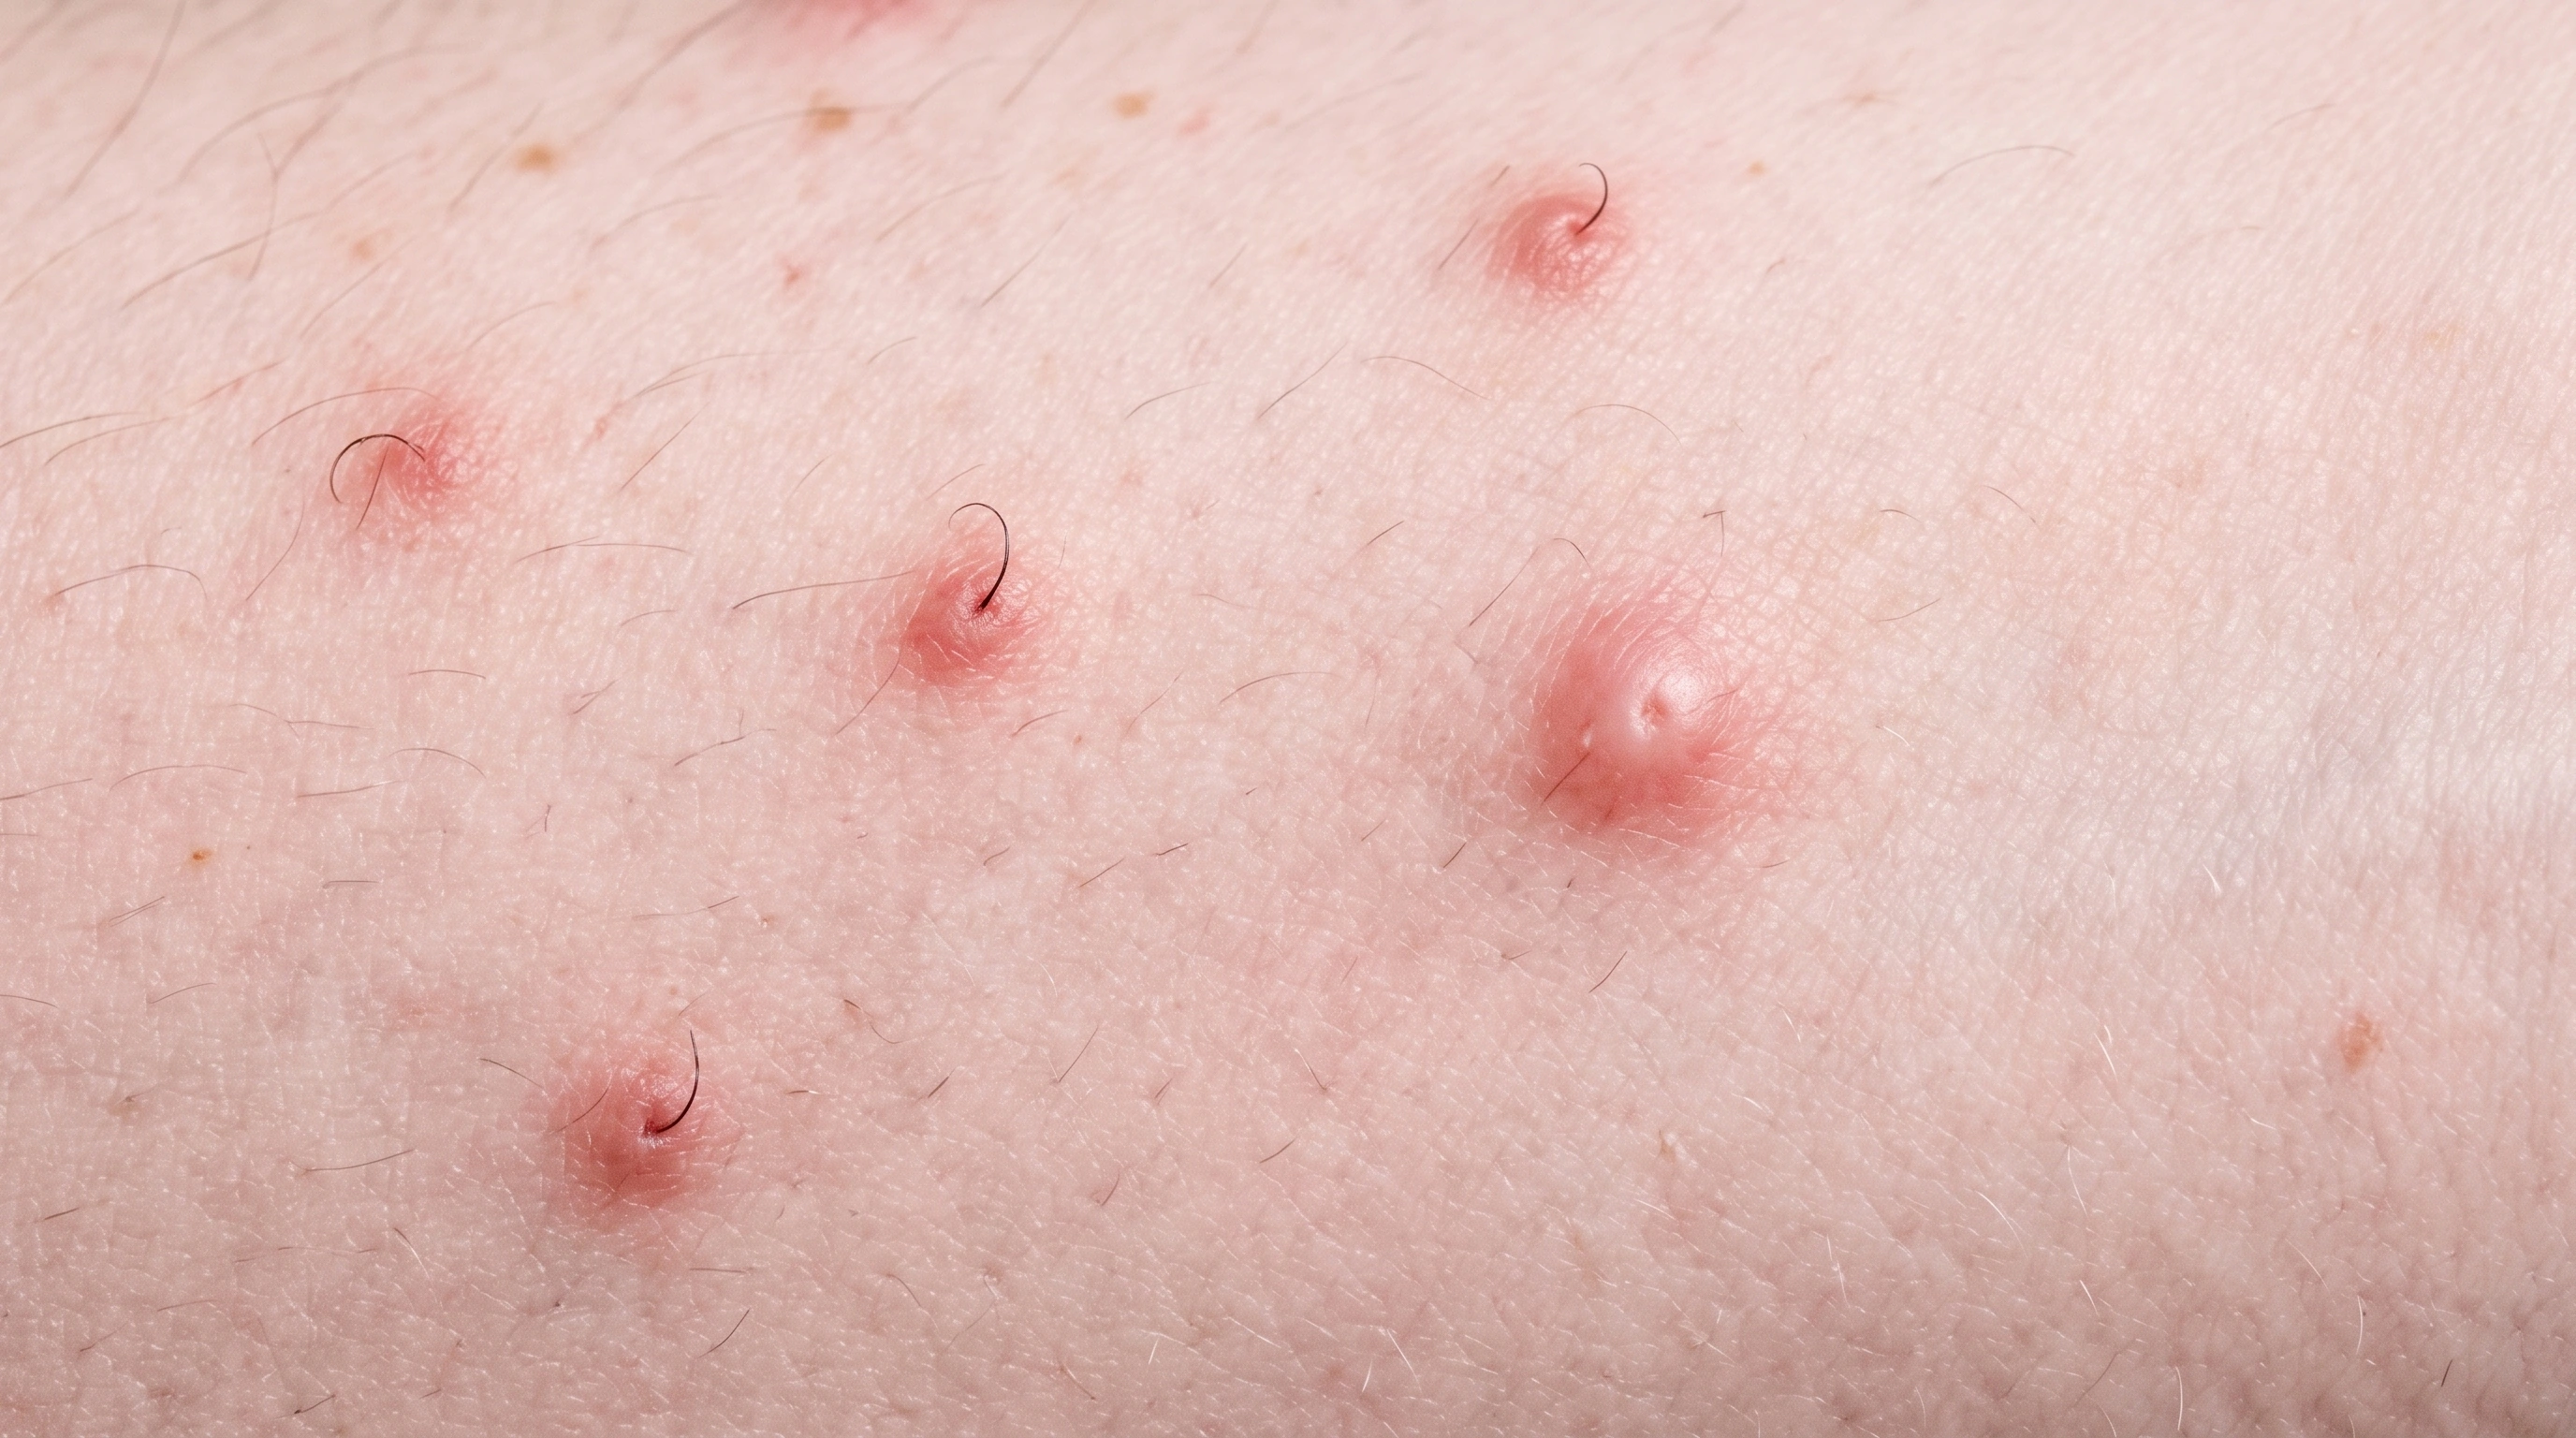
Ingrown Hairs vs Molluscum Contagiosum

Genital Warts vs Molluscum Contagiosum