
Hot Tub Folliculitis vs Fungal Acne

A follicular eruption after exposure to water contaminated with Pseudomonas bacteria.

Research updated 2026-10-23
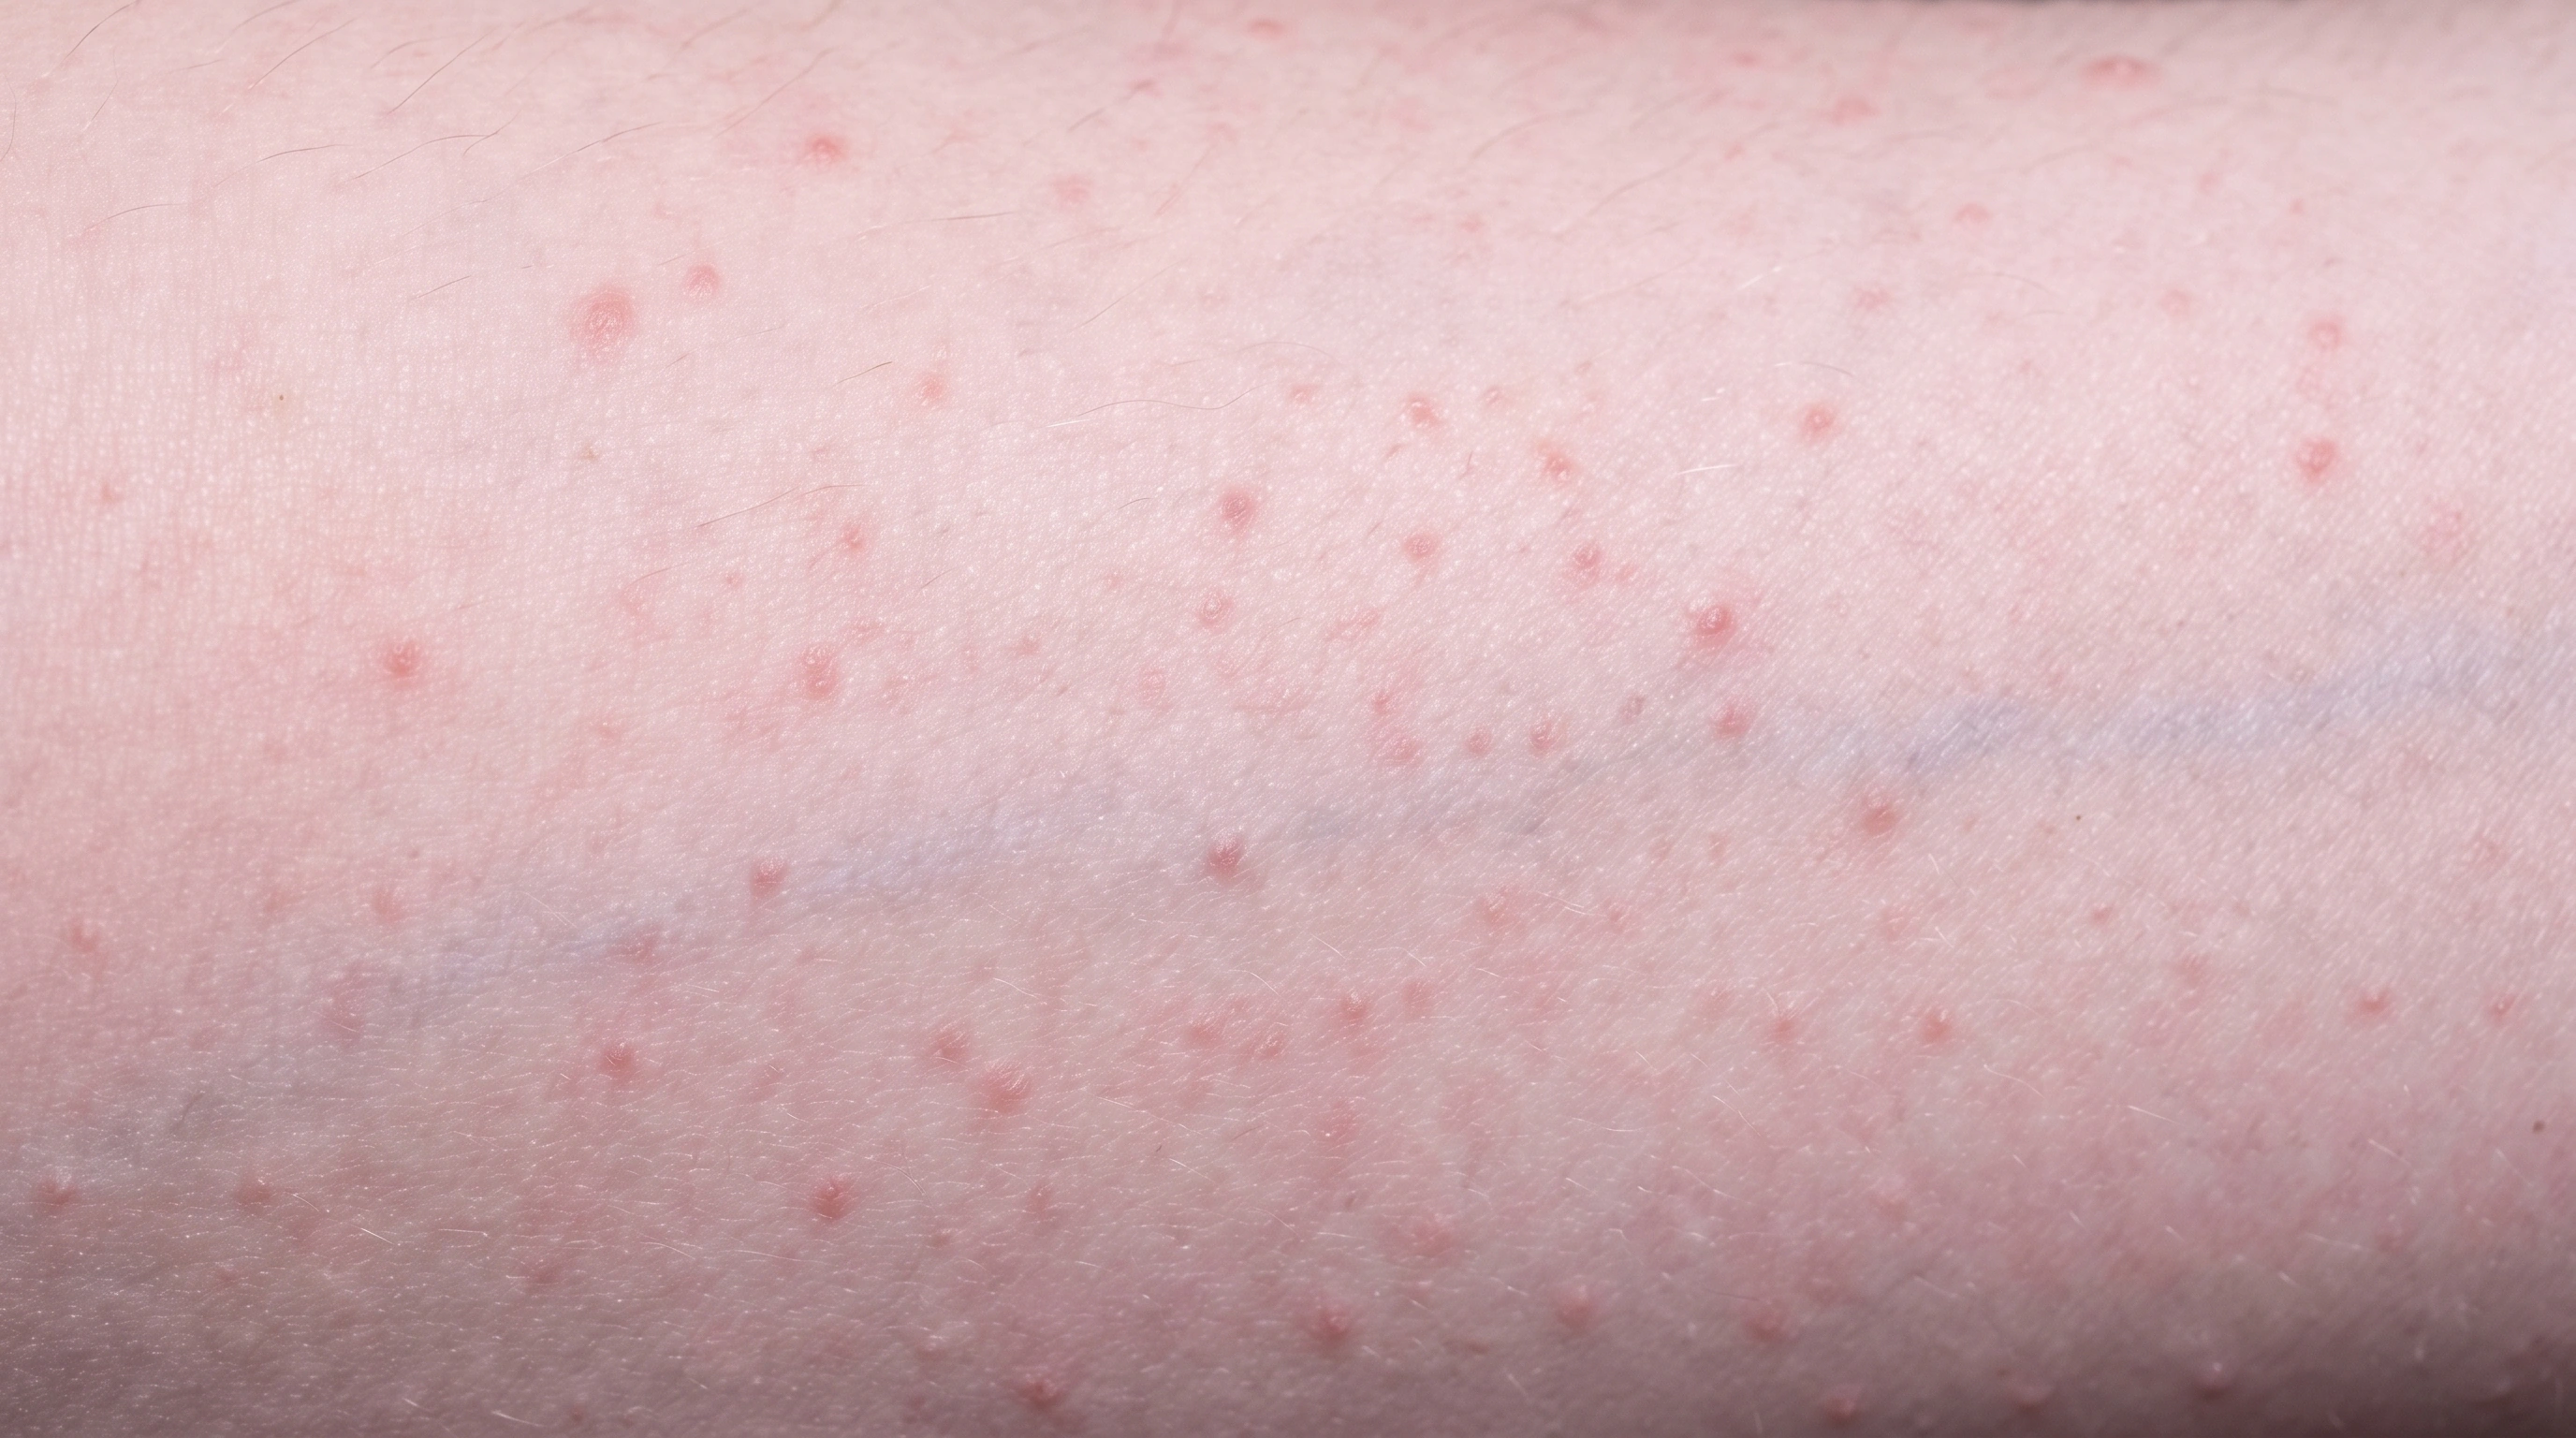
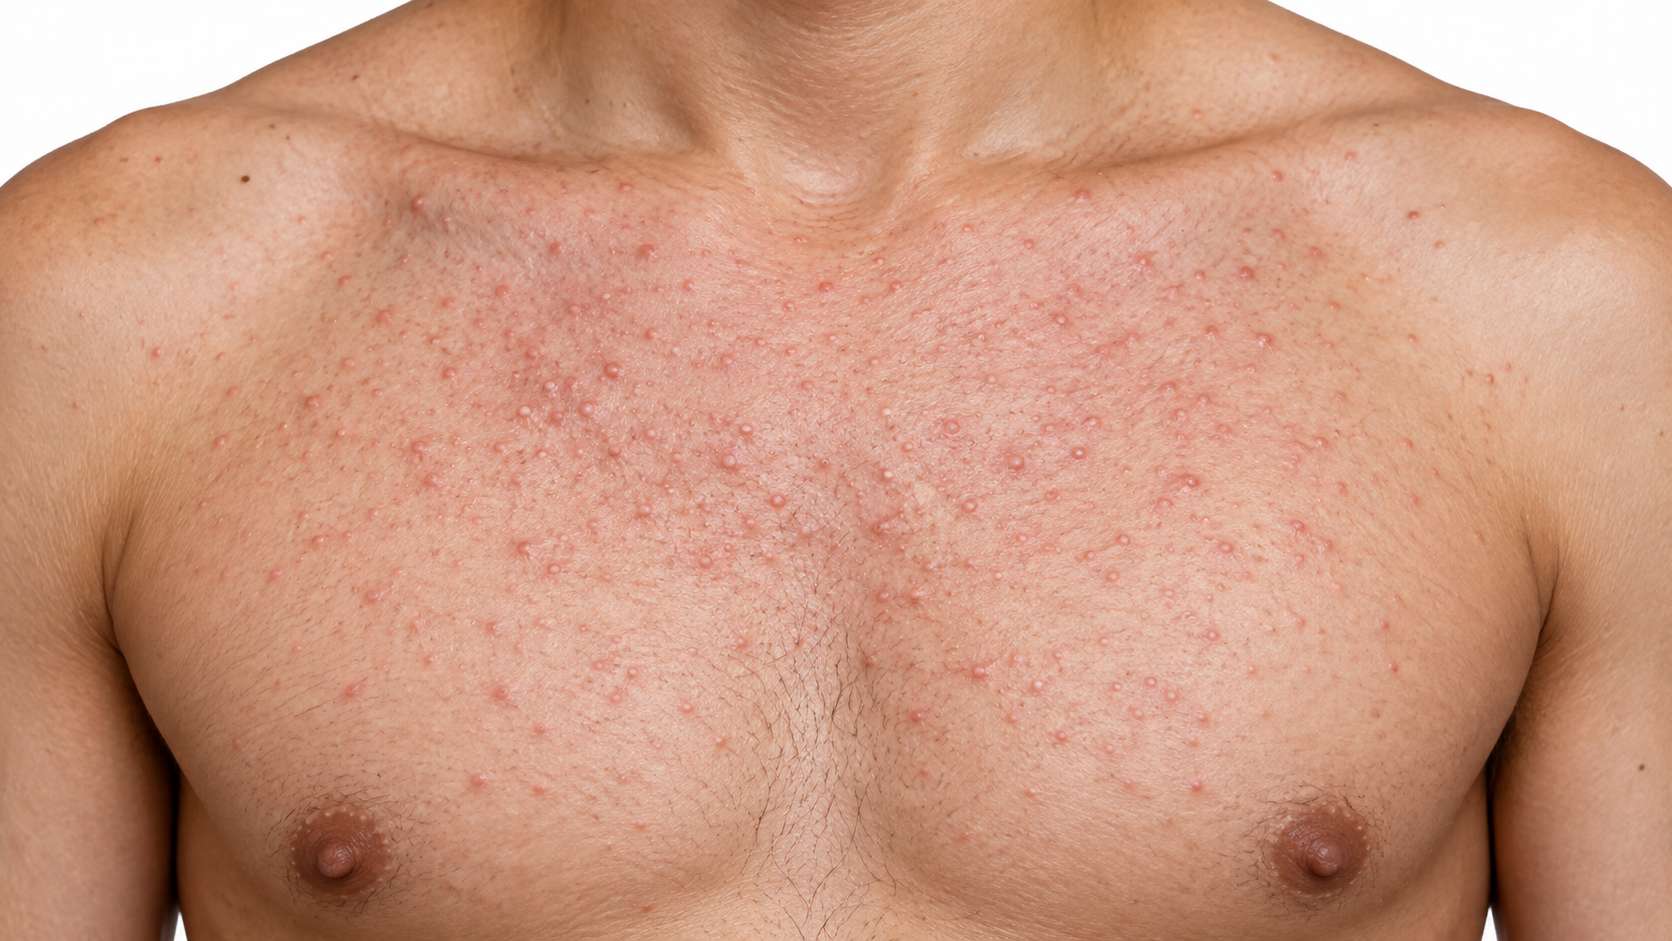
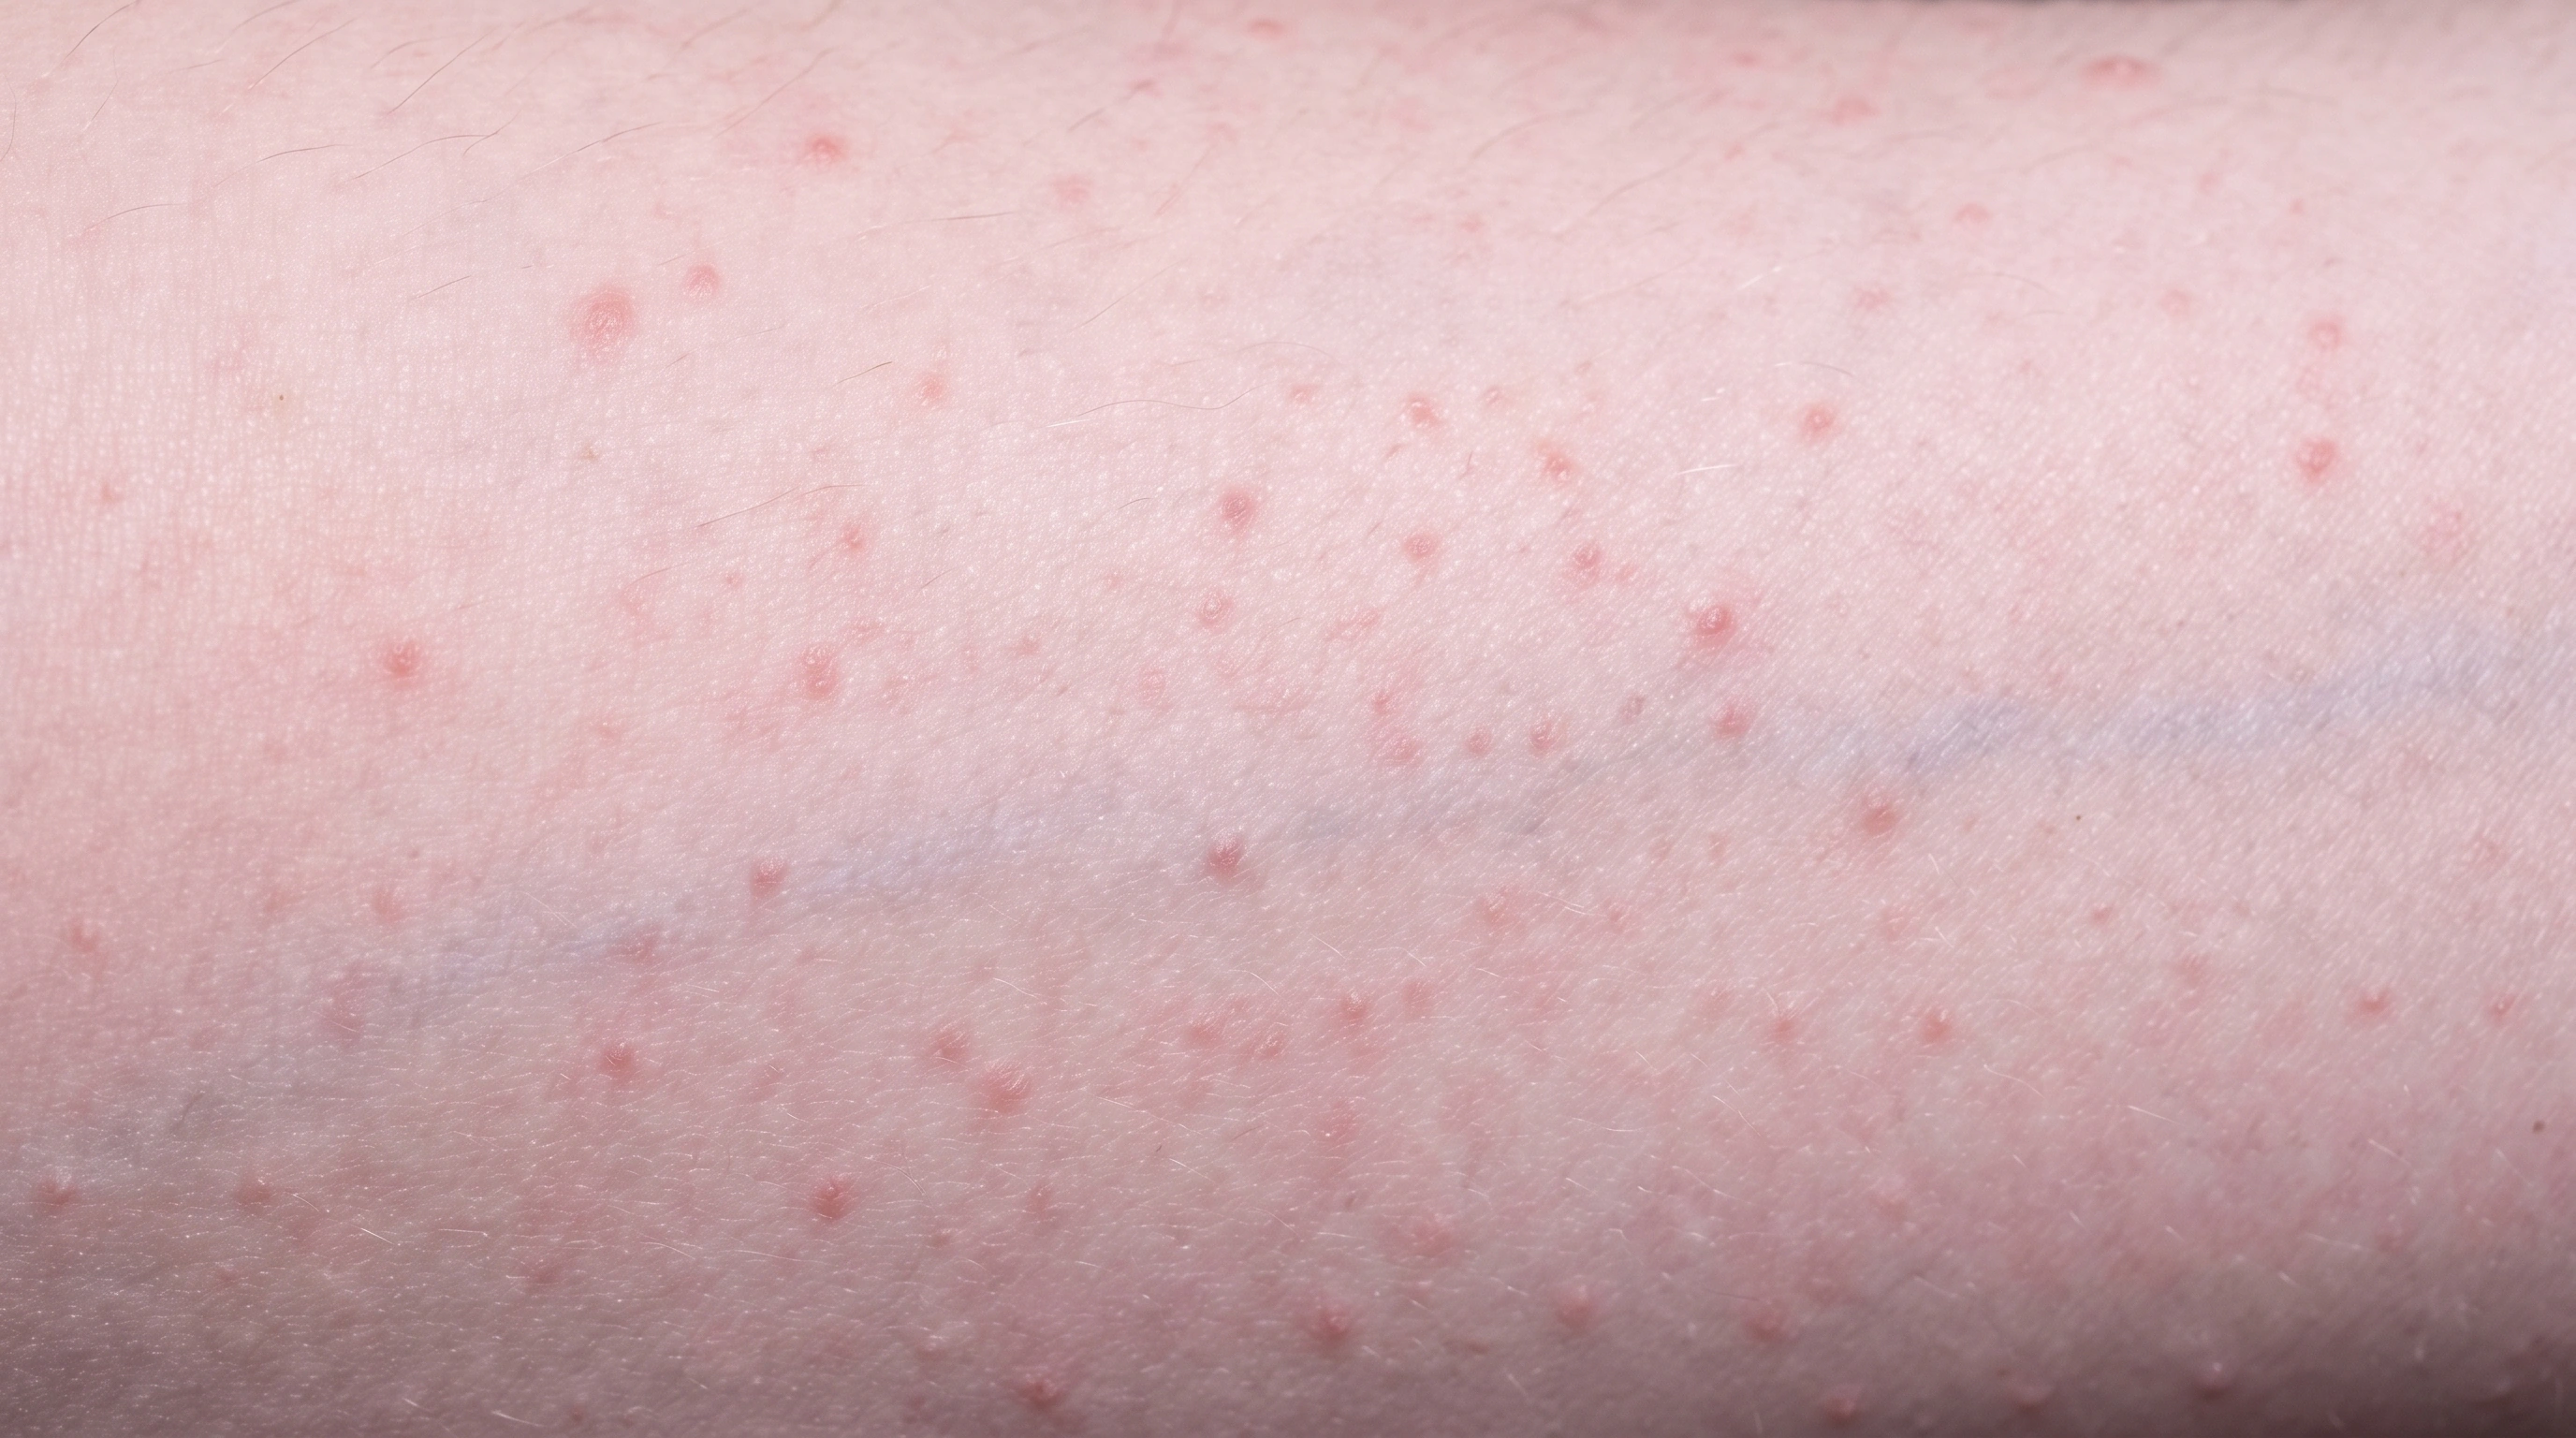
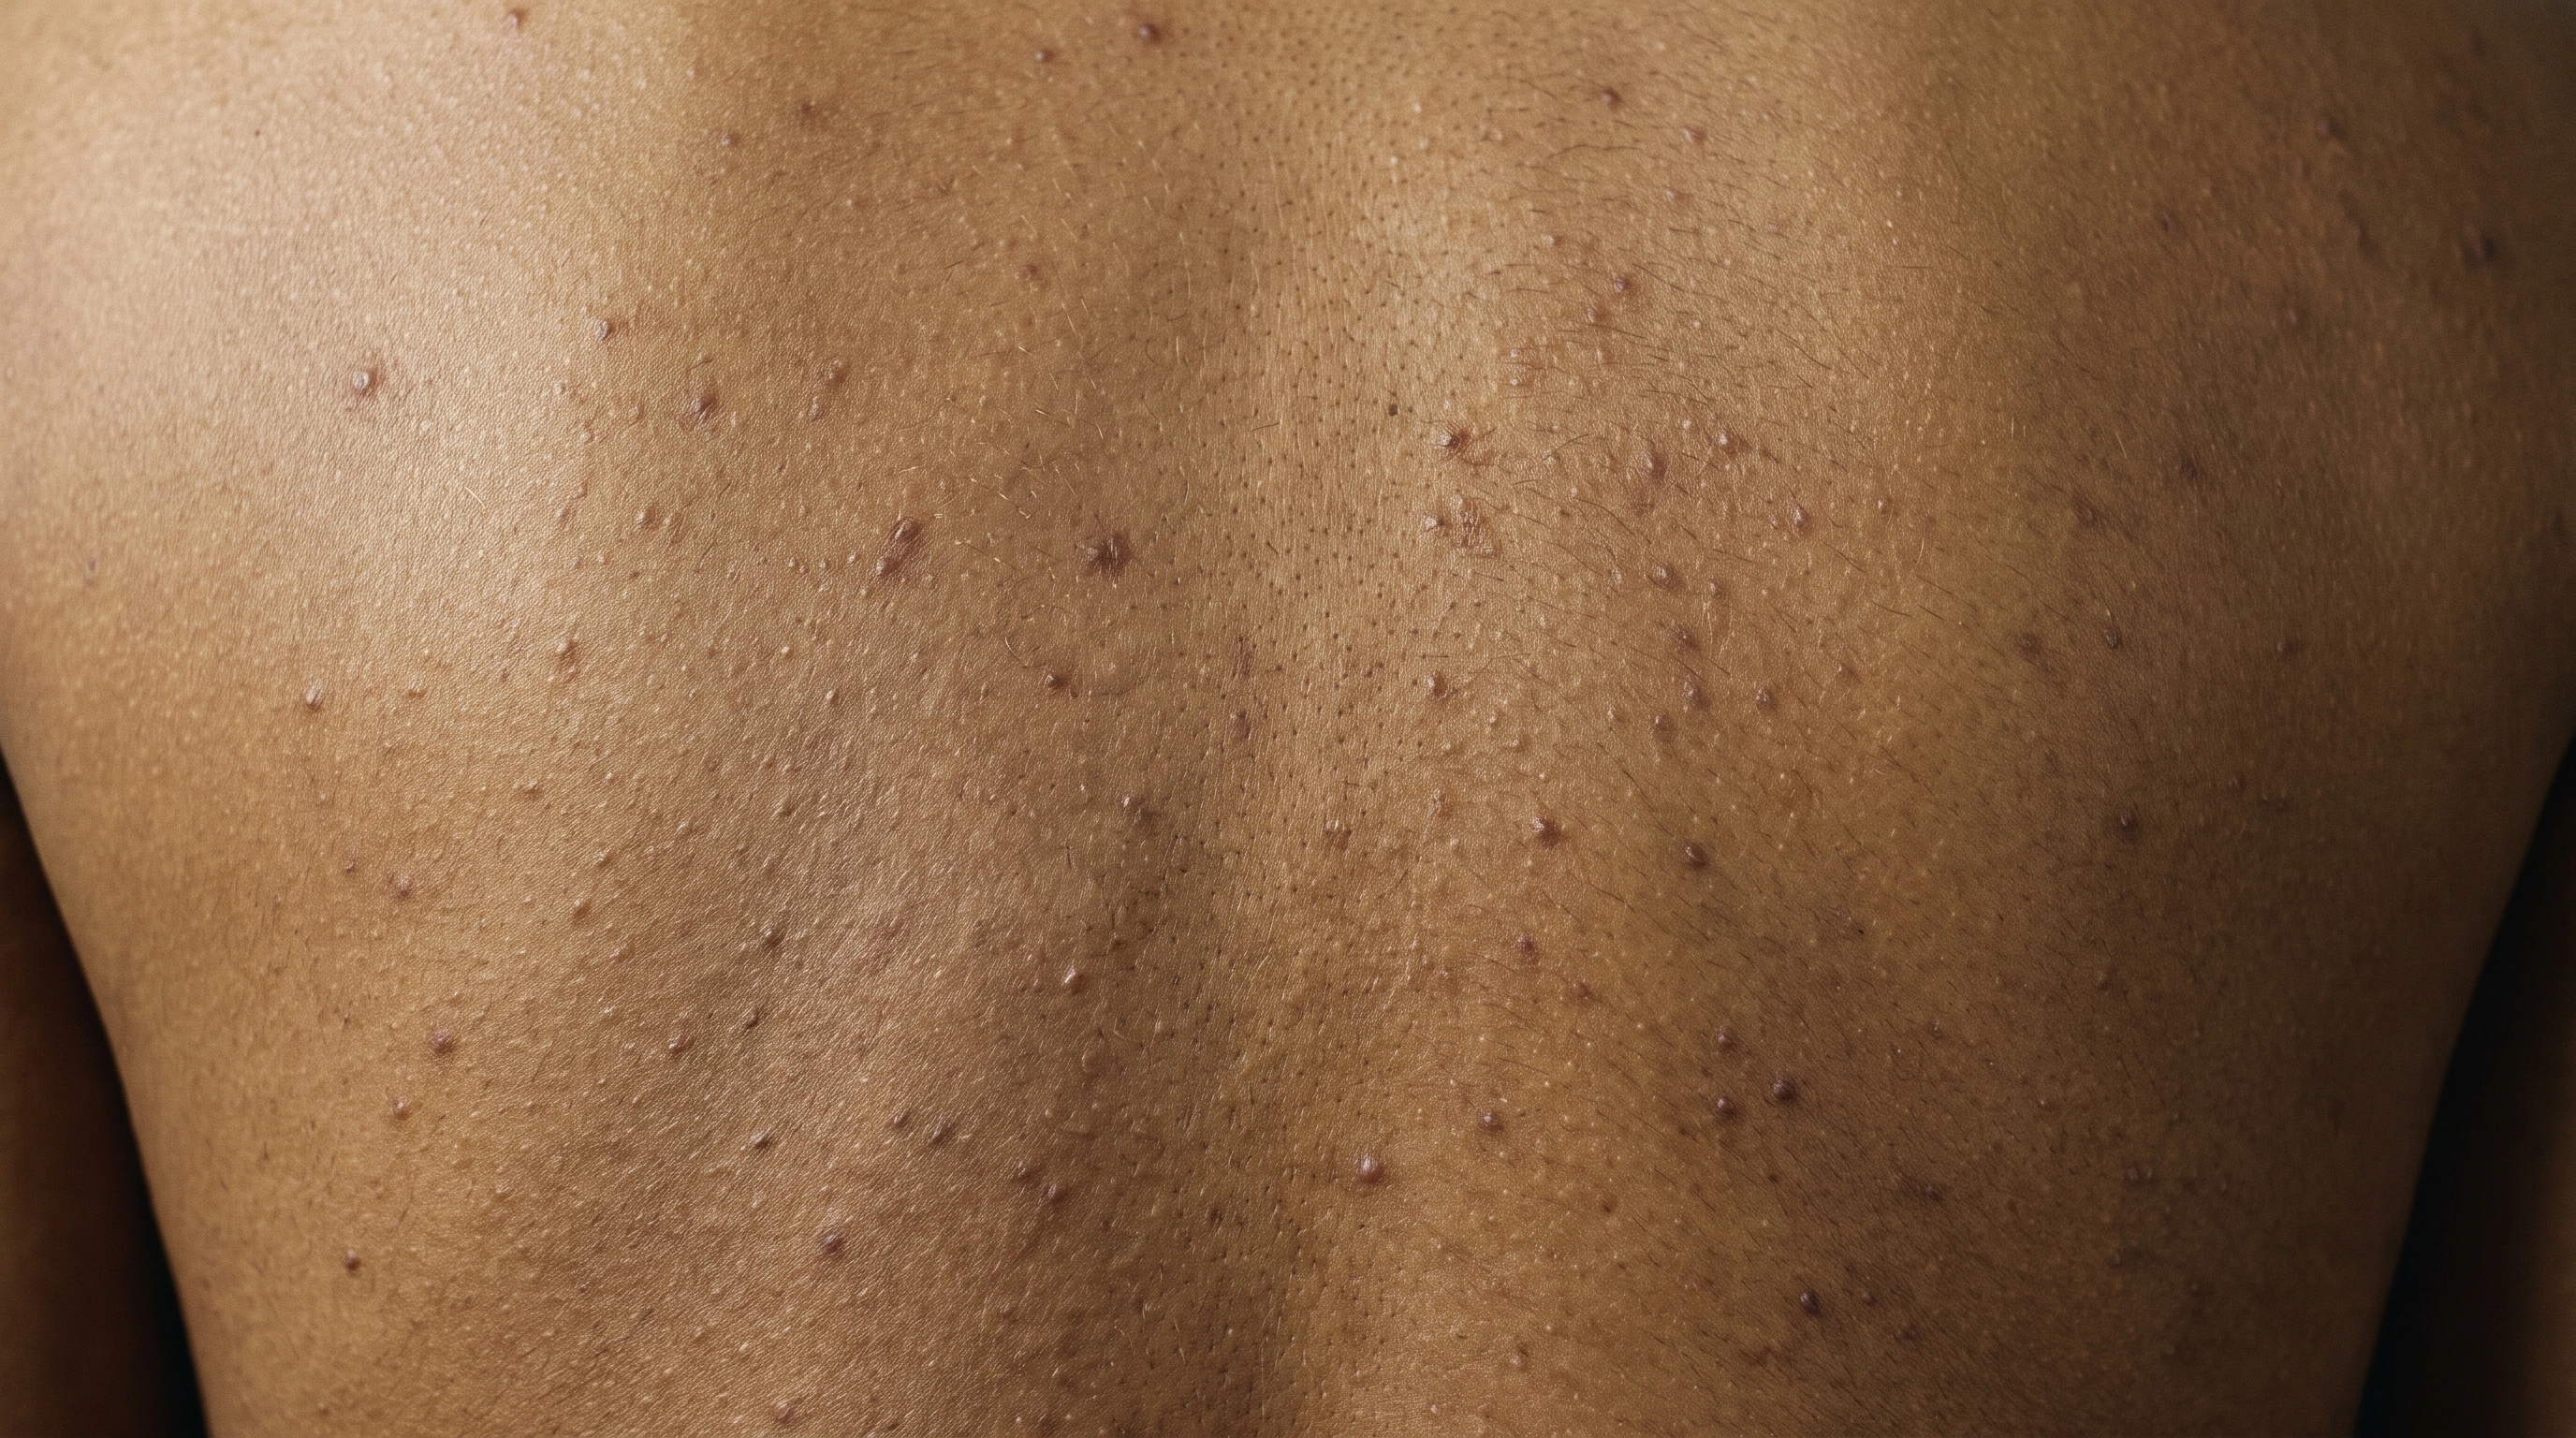
AI-generated educational illustration: Adult upper shoulder and chest crop with scattered discrete red follicle-centered papules and tiny pustules; no nude full body.Shoulders and upper back on fair skin, covered in a sheet of many small pink-red bumps, all of them the same size and packed close together.

Key differences

The same eight facts on every condition comparison.

Usual age
Any age
Teens and young adults
Where
Trunk, under swimwear
Chest, back, shoulders, hairline
Main sign
Itchy red bumps after a hot tub
Small, itchy, same-sized bumps
Itch or pain
Itchy
Itchy
Contagious
No (from the water)
No
Long term
Clears in 1–2 weeks
Clears with antifungals; often returns
Scars
No
No
Who gets it
Hot tub or pool users
Hot, humid climates; sweating; antibiotics

What is it?

Hot Tub Folliculitis
Fungal Acne
What is it?
  • What it is
    A follicular eruption after exposure to water contaminated with Pseudomonas bacteria.
  • It is a yeast-driven follicle eruption.
    Malassezia, which normally lives on skin, can multiply inside follicles.
  • It has a typical pattern.
    Small itchy bumps cluster on the upper trunk, shoulders, neck or hairline.
  • The nickname misleads.
    Conventional acne treatments may not address the yeast.
  • It can coexist with acne.
    Blackheads, whiteheads and mixed lesion sizes point to acne vulgaris as well.
  • Overview
    Also called Malassezia folliculitis: inflammation around hair follicles linked to yeast. It often produces small, similar-looking, itchy bumps rather than blocked pores.

What it looks like

Hot Tub Folliculitis

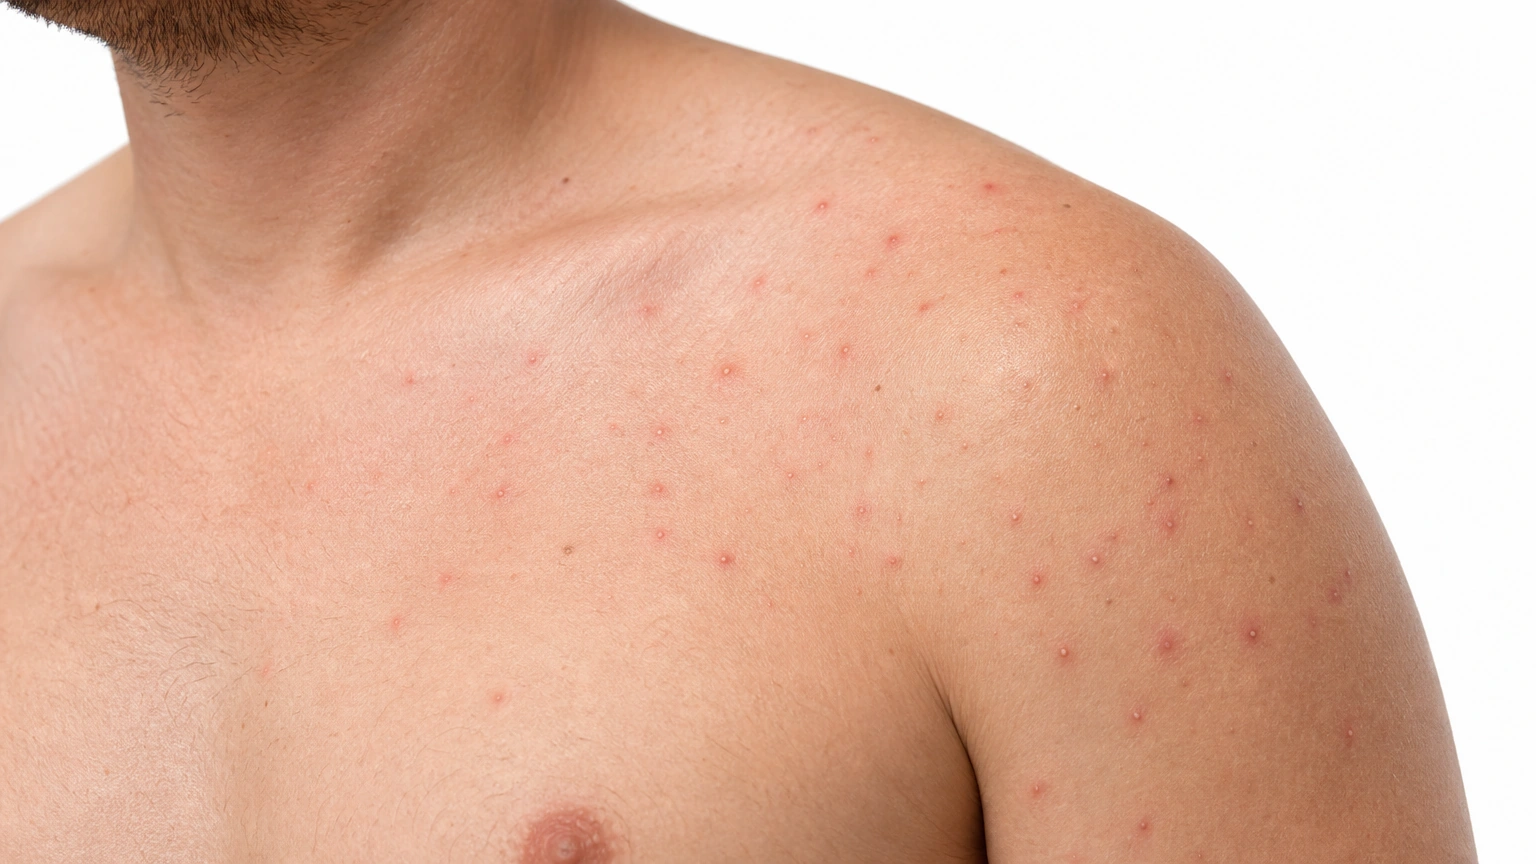
An upper chest and shoulder with many small red bumps.

Hot Tub Folliculitis Numerous pink spots are scattered over the upper chest and shoulder.

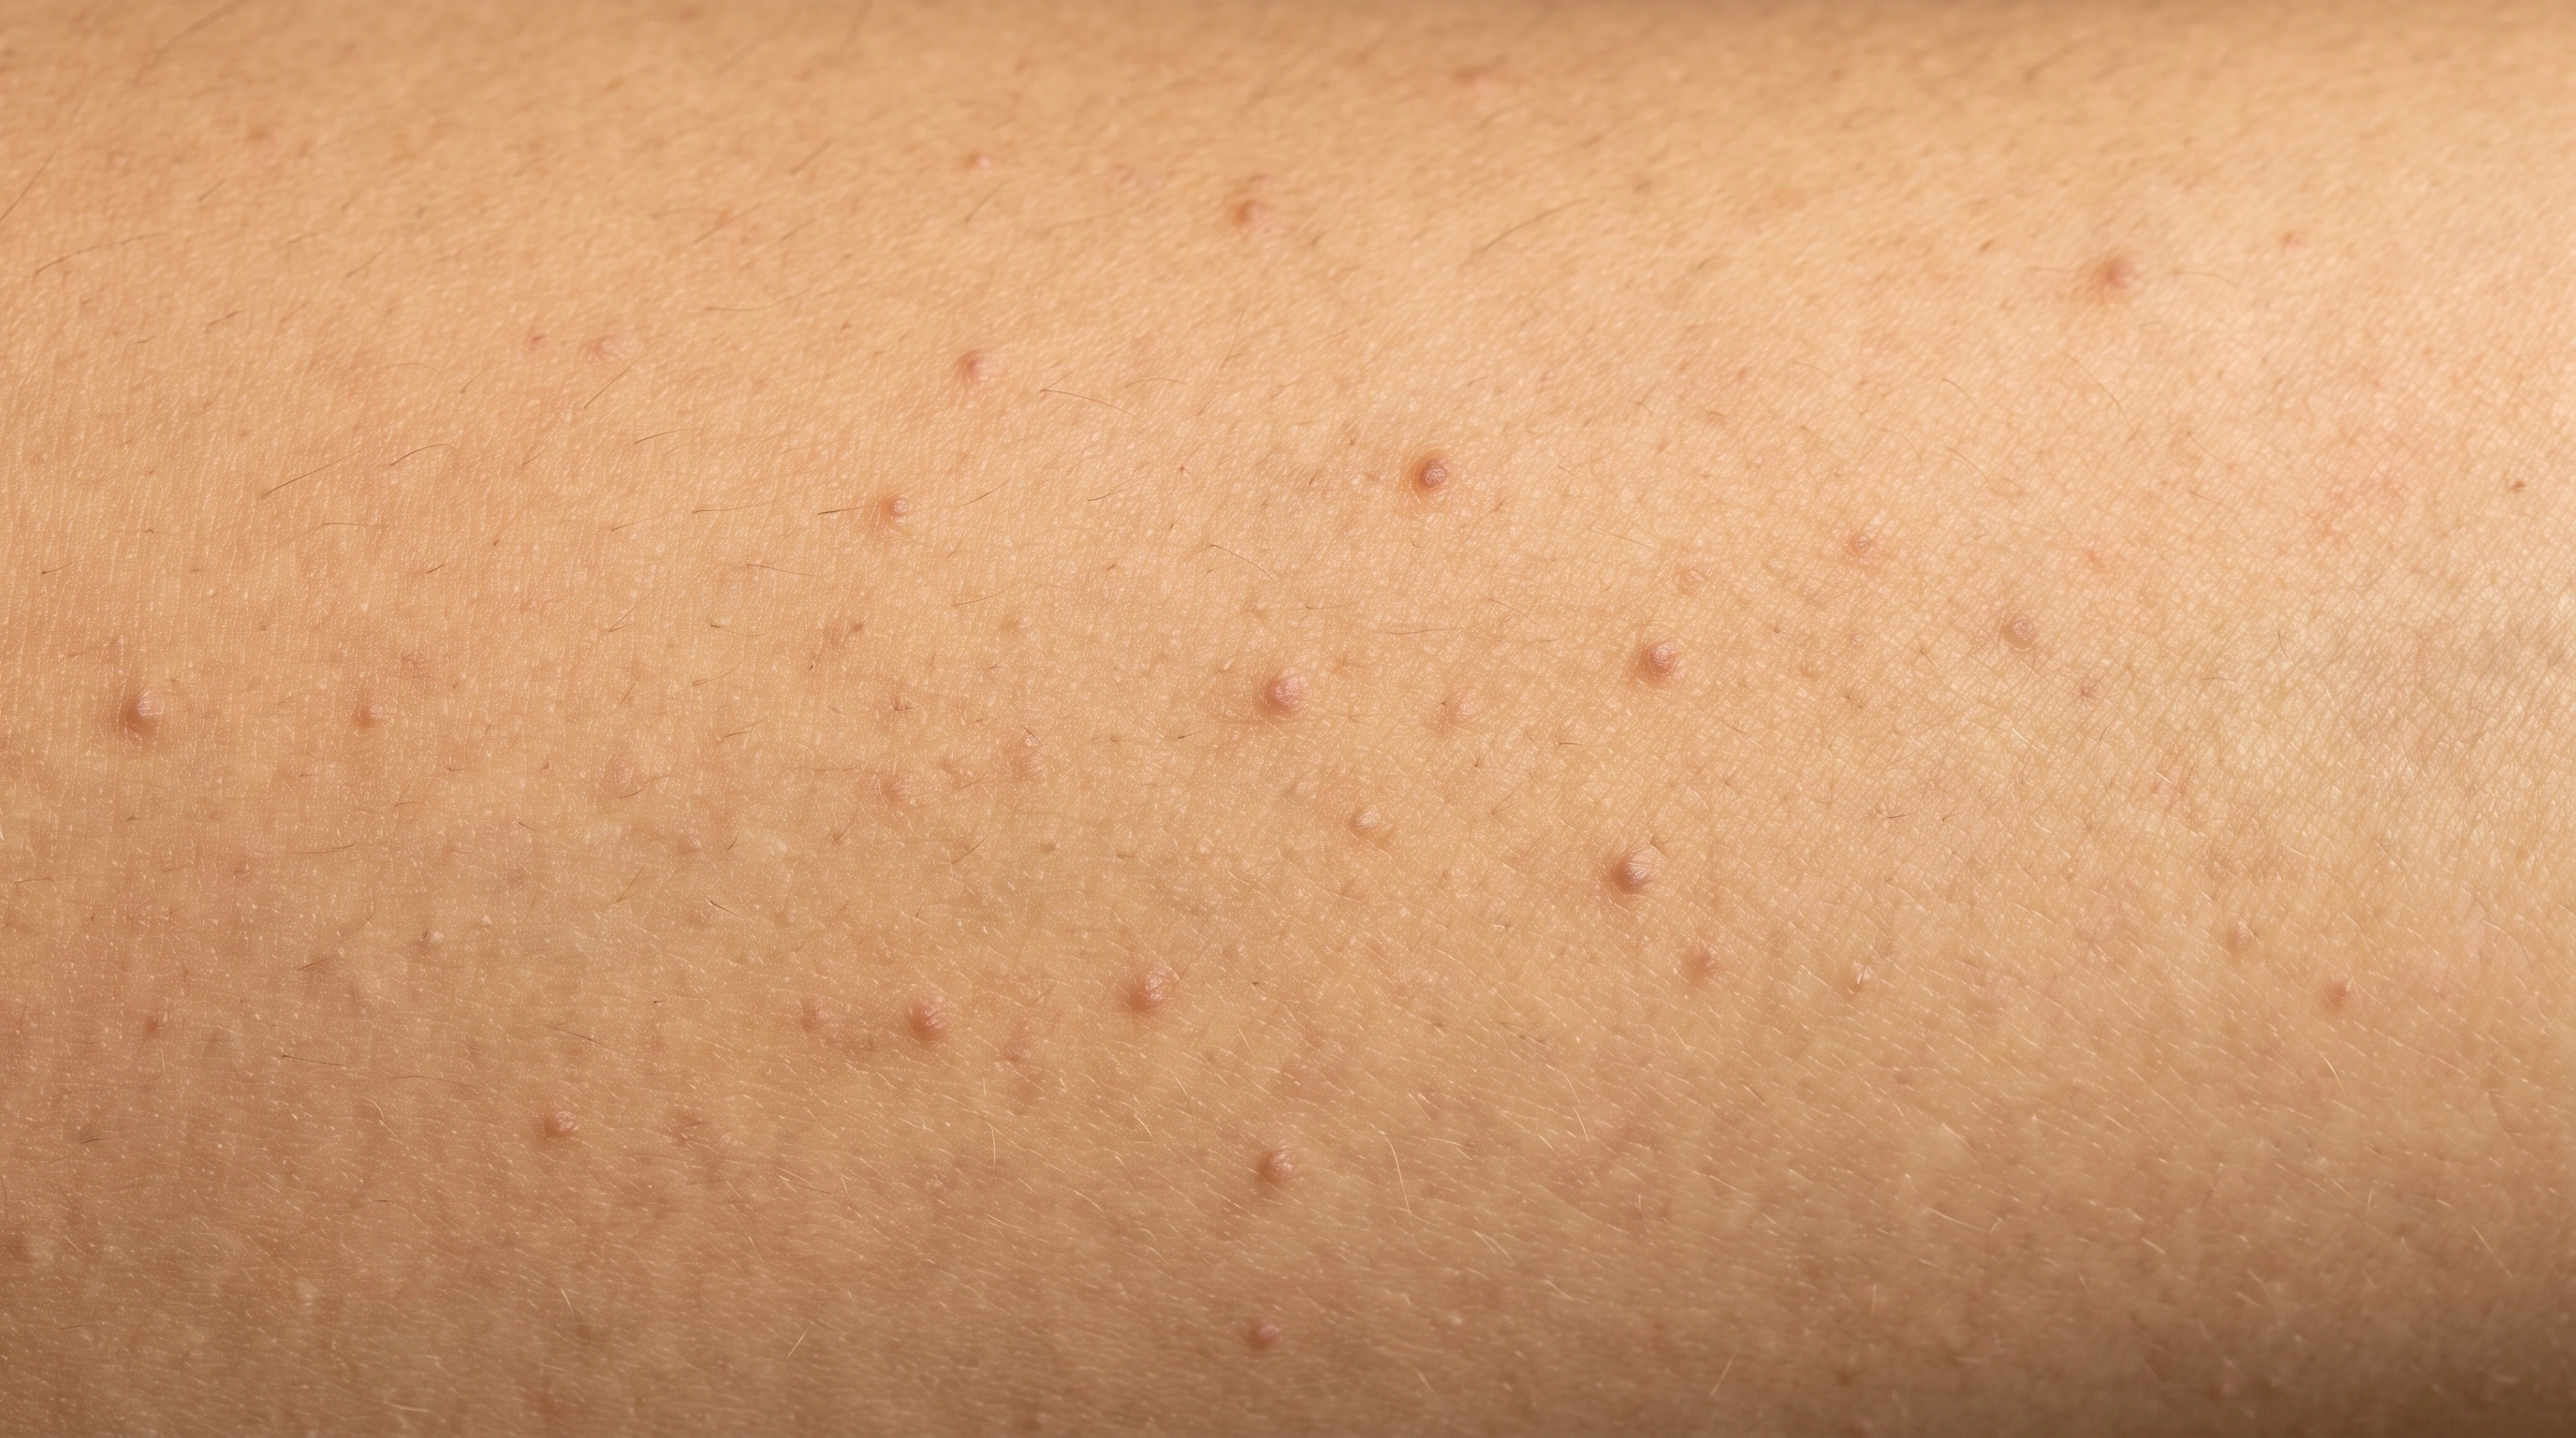
Fungal Acne

Fungal Acne: Uniform bumps.

Uniform bumps Small bumps all the same size.

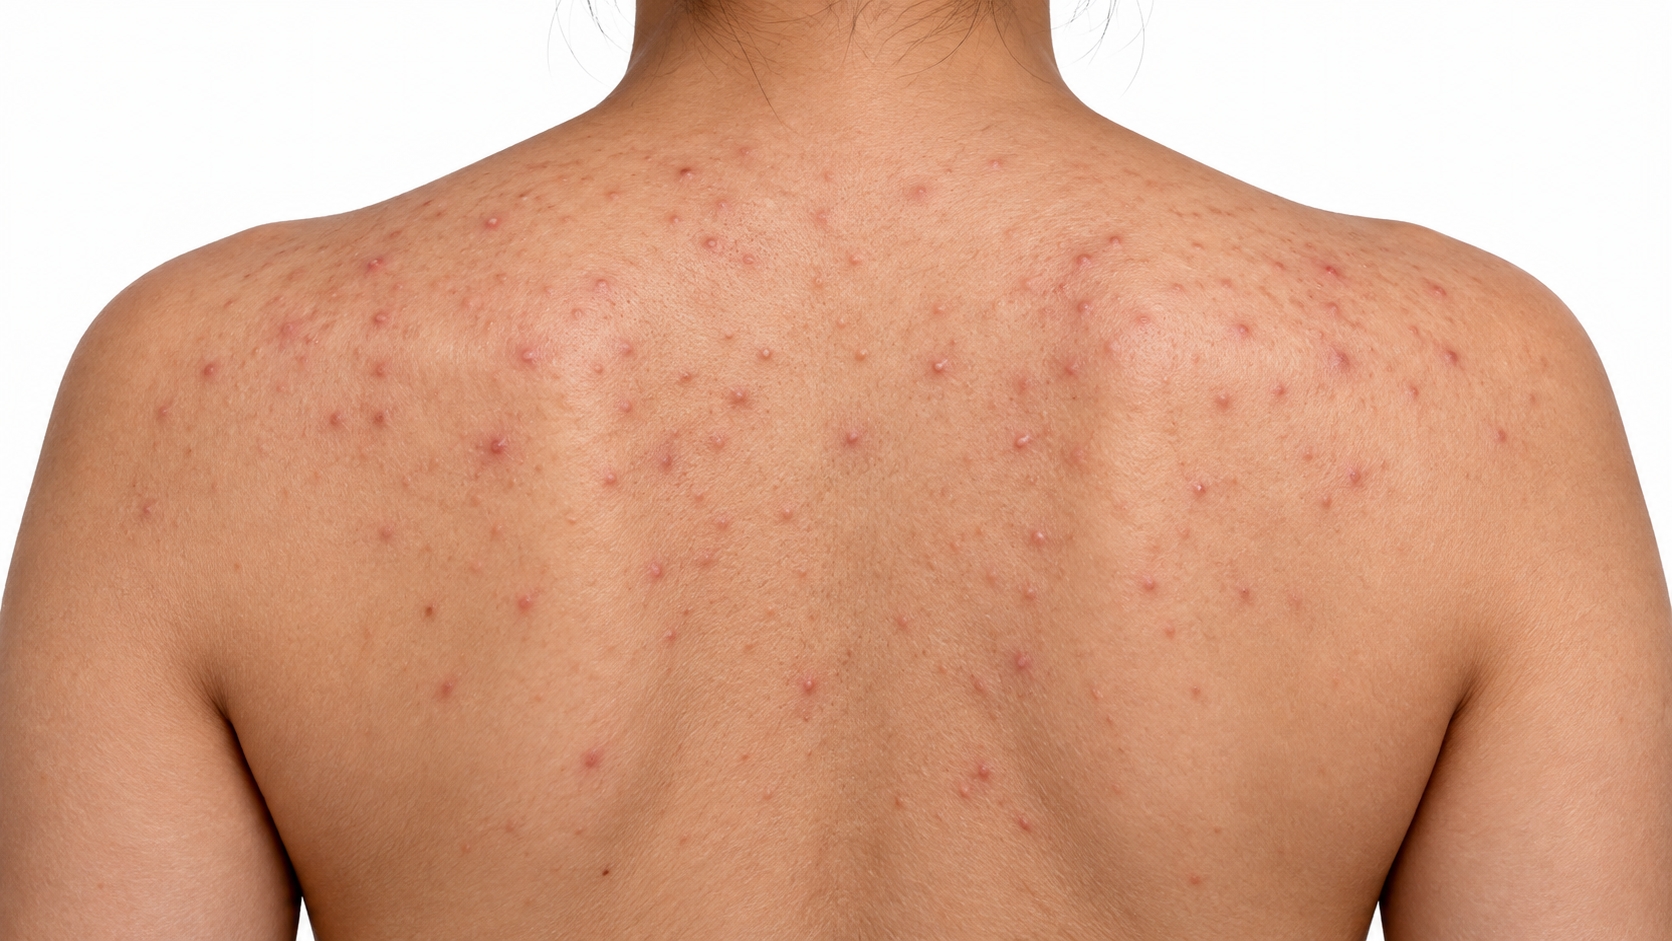
Fungal Acne: Upper back.

Upper back A common site.

Fungal Acne: Forehead.

Forehead Clusters along the hairline.

Skin tones
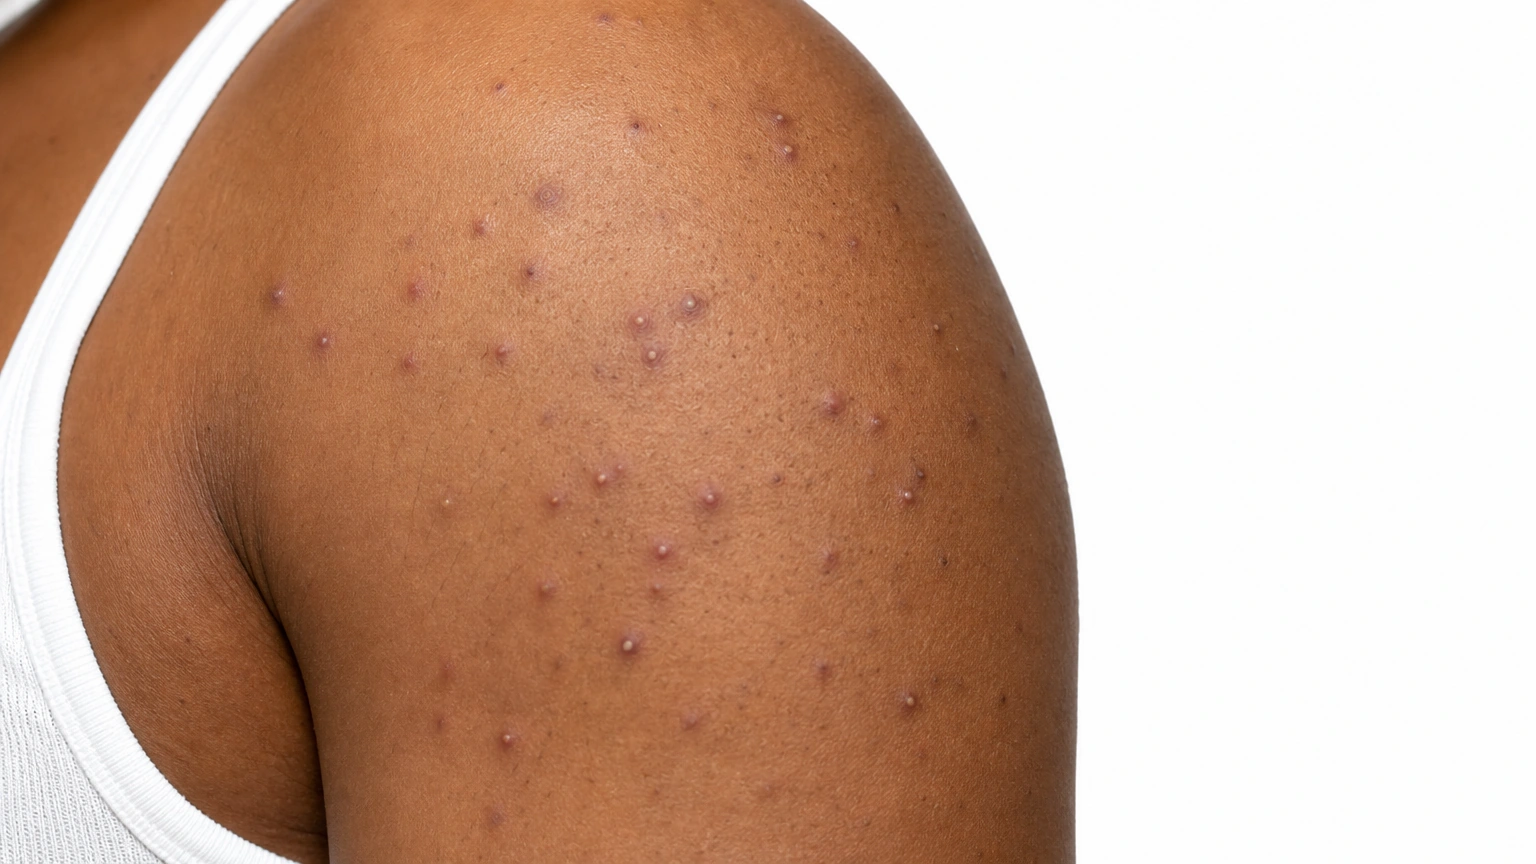
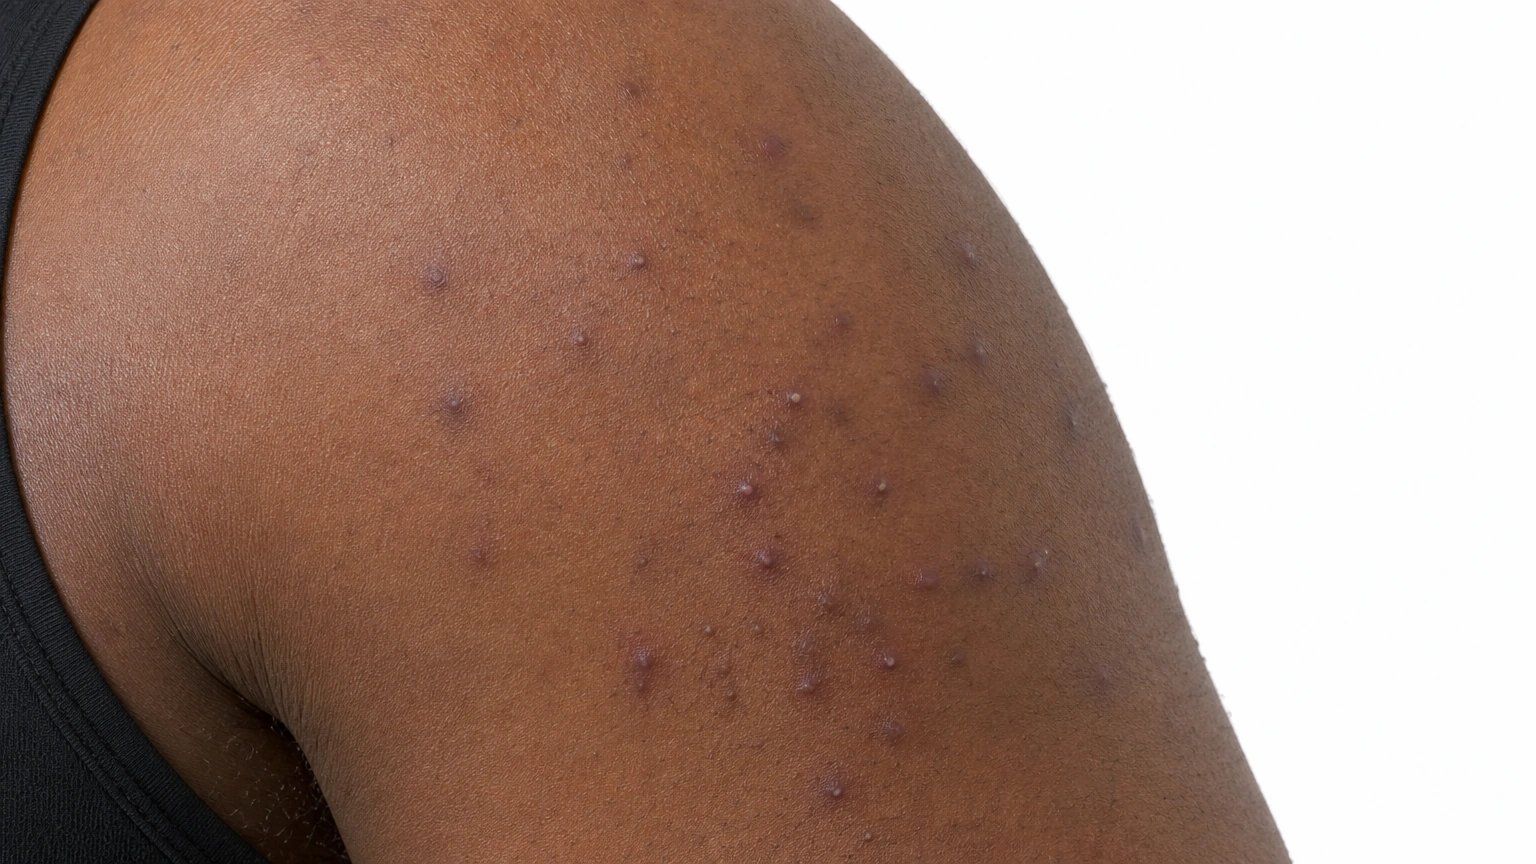
Adult upper shoulder and chest crop with scattered discrete red follicle-centered papules and tiny pustules; no nude full body.
Hot Tub Folliculitis on medium skin.
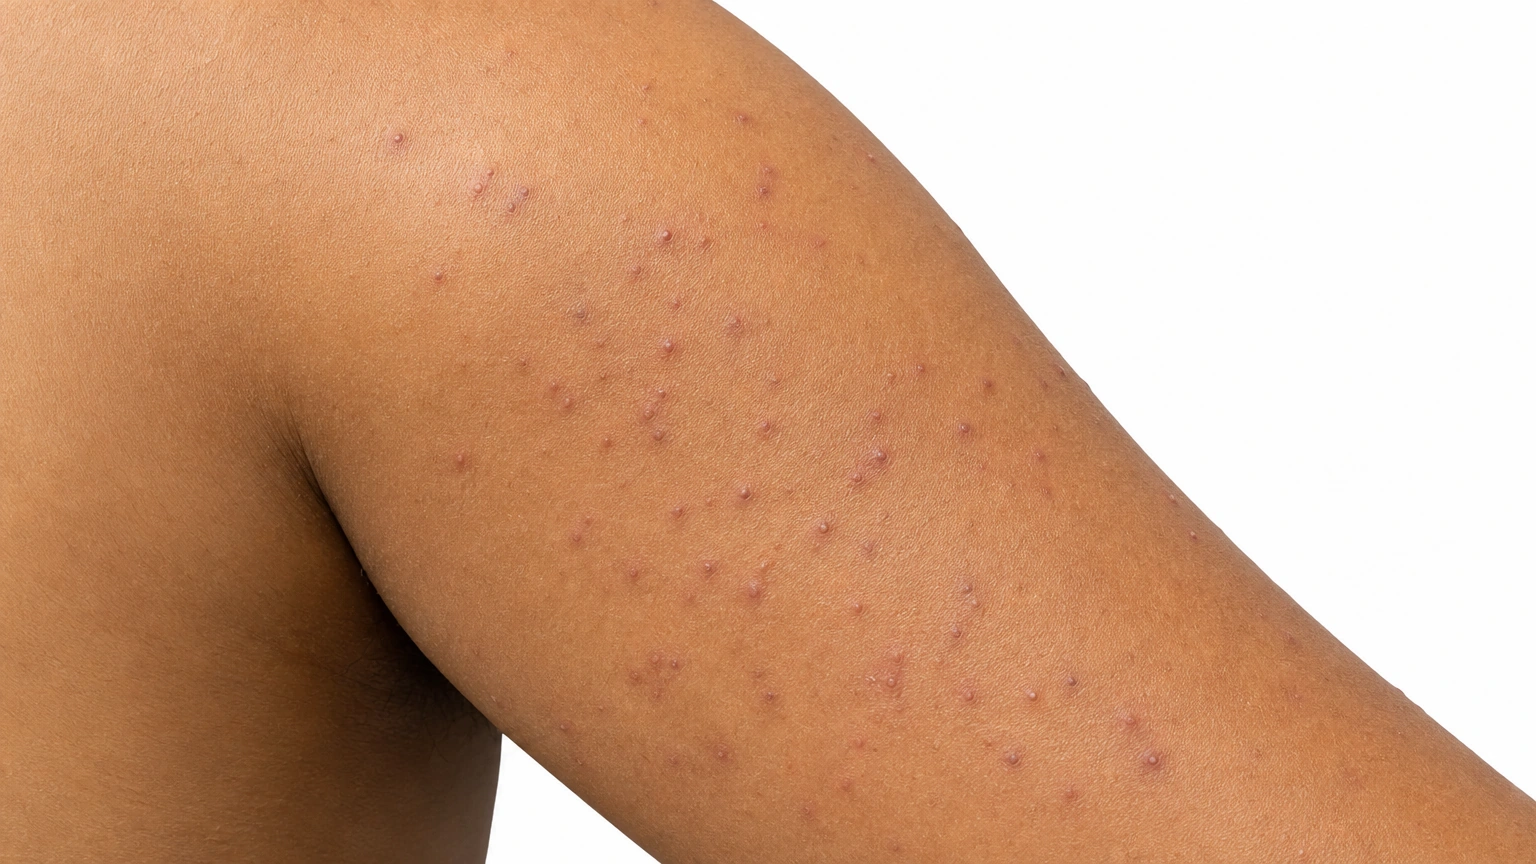
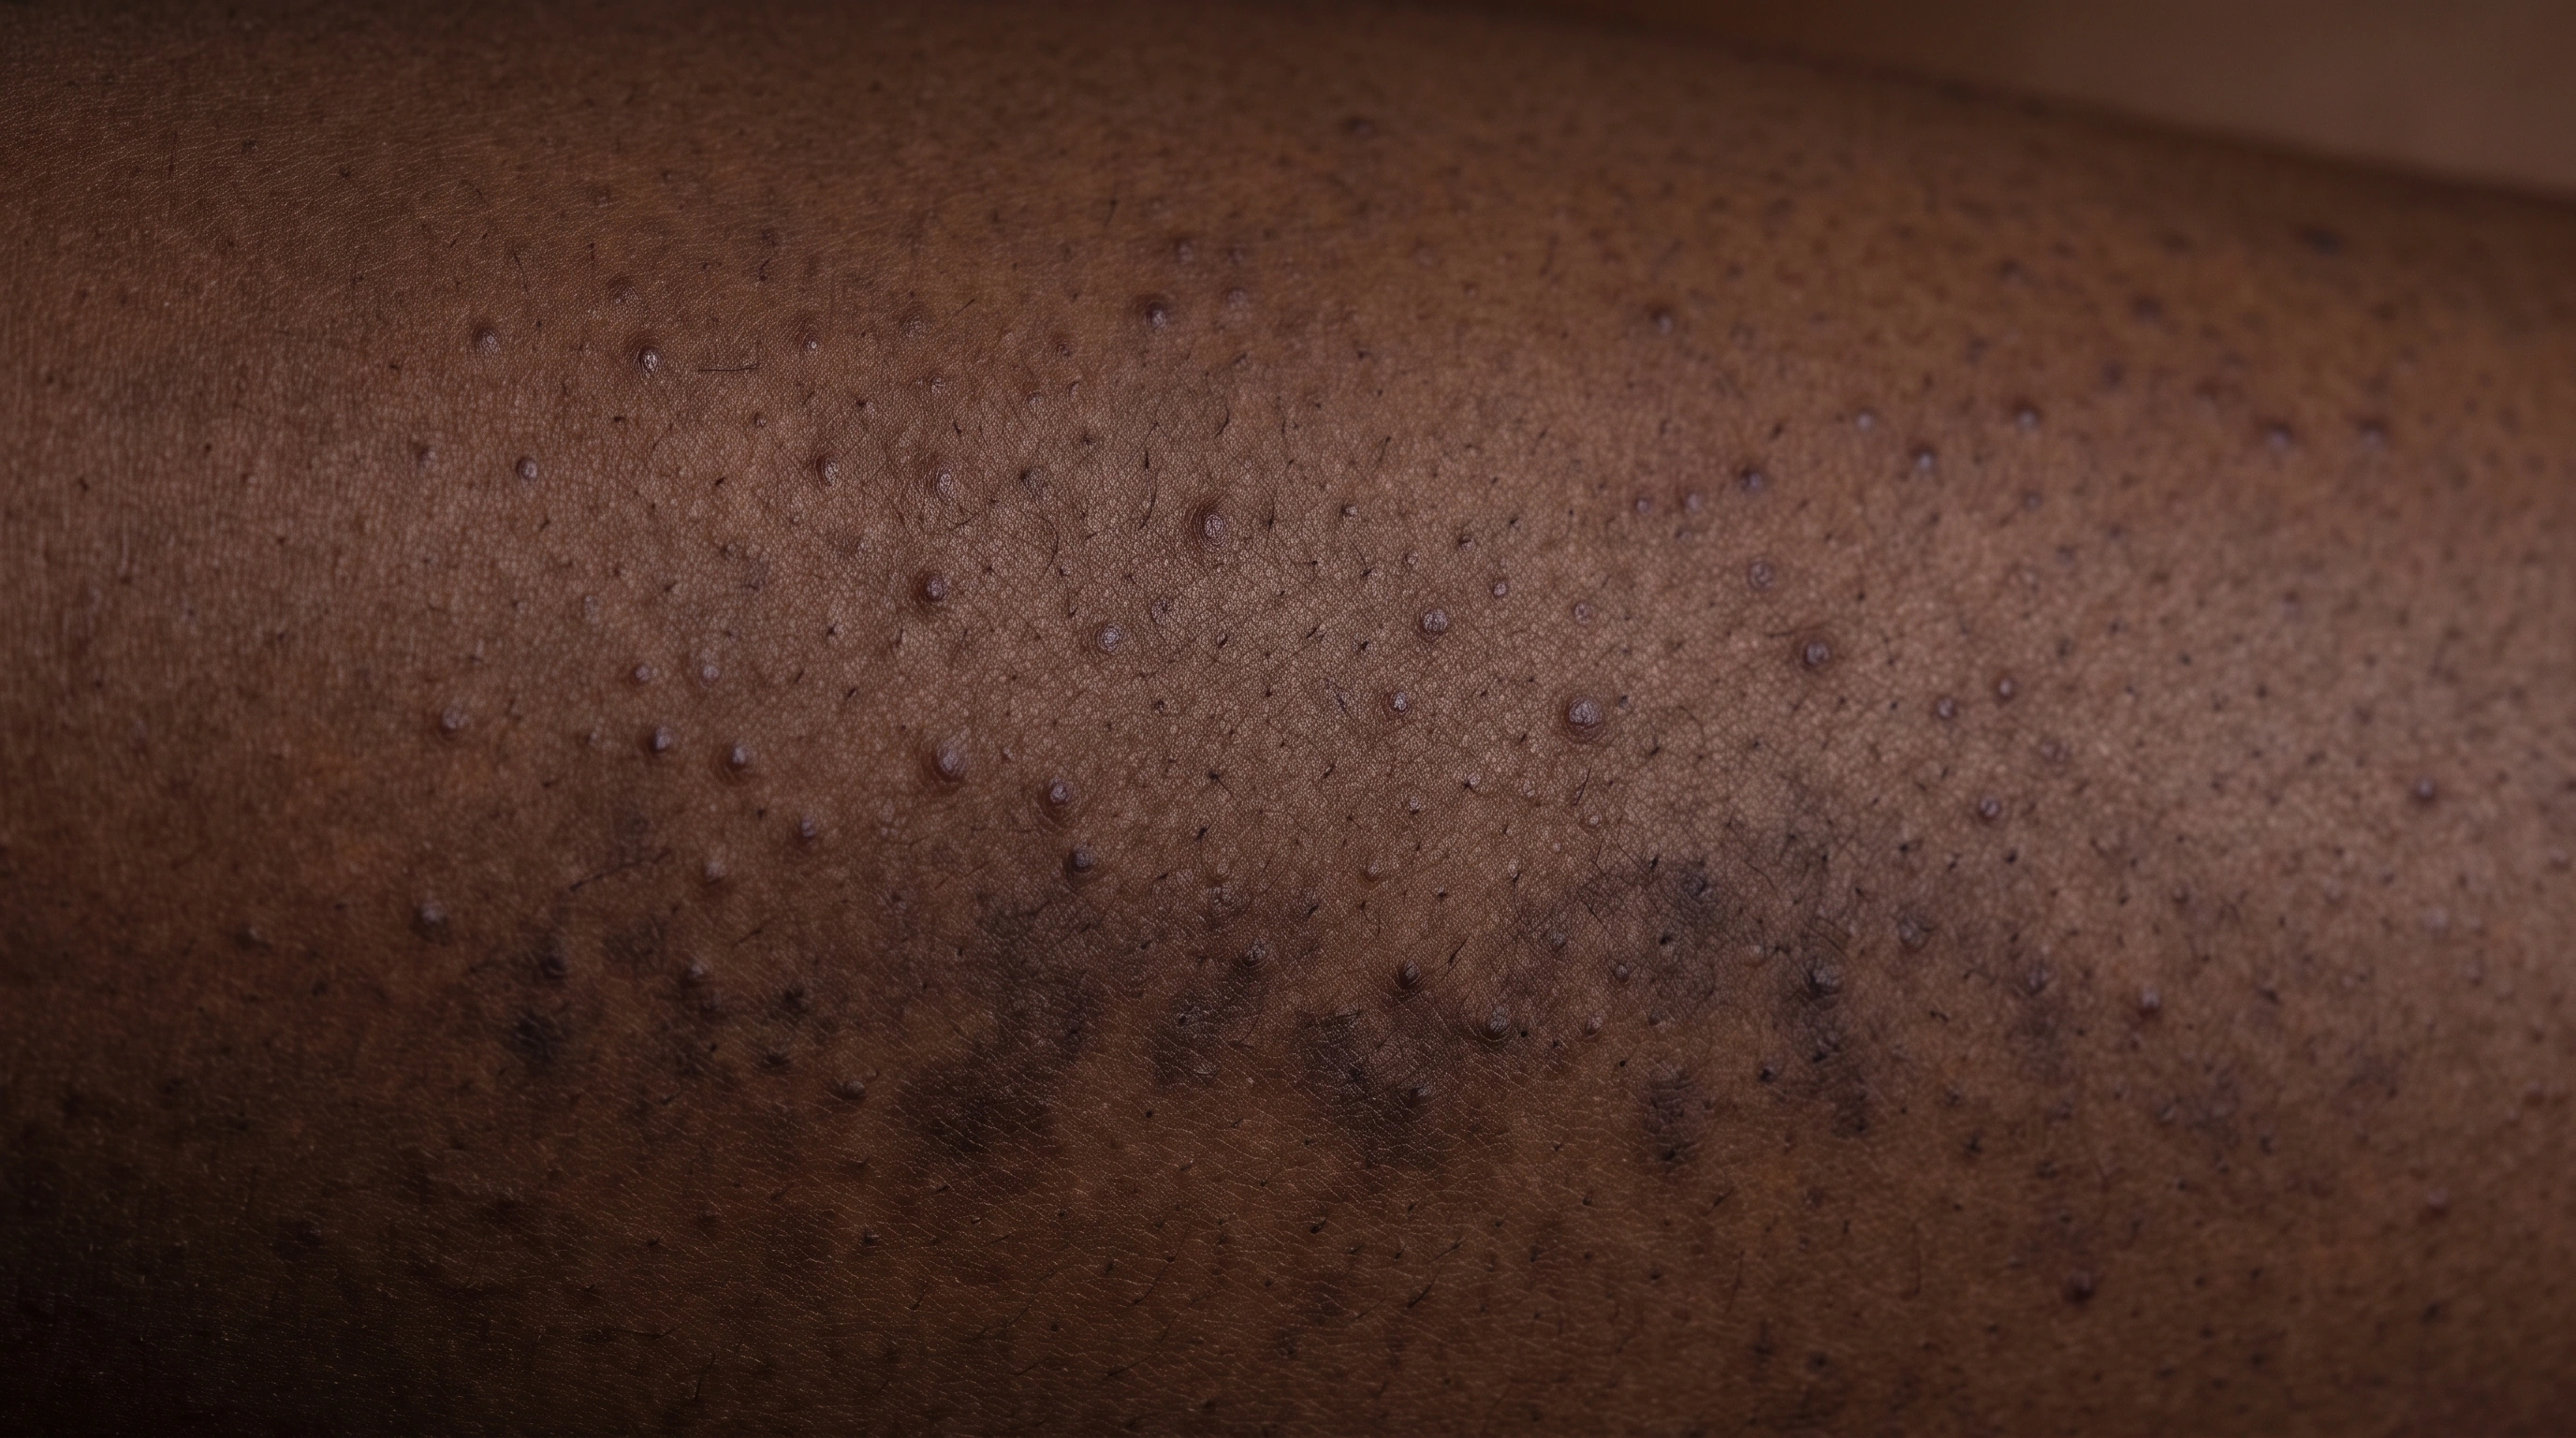
Hot Tub Folliculitis on brown skin.
Hot Tub Folliculitis on deep skin.
Shoulders and upper back on fair skin, covered in a sheet of many small pink-red bumps, all of them the same size and packed close together.
Shoulders and upper back on medium olive skin, covered in a sheet of many small dull pink-brown bumps, all of them the same size and packed close together.
Shoulders and upper back on brown skin, covered in a sheet of many small bumps of identical size that read brown and violet rather than red.
Shoulders and upper back on deep brown skin, with a sheet of small bumps of identical size and, beside them, a wide field of flat, evenly darker marks where earlier bumps have healed.
Diagram
Fungal Acne mechanism diagram. Yeast grows inside a follicle: Malassezia can overgrow in suitable conditions. The follicle becomes inflamed: The immune response surrounds the affected follicle. Similar itchy bumps appear: Small follicular bumps may look alike.
In the skin

Bacteria in contaminated water enter hair follicles. Local inflammation develops around the follicles and can produce small bumps or pustules.

Malassezia yeast can overgrow inside hair follicles and trigger inflammation. This produces similar-looking itchy bumps and differs from the plugged pores that form blackheads and whiteheads.

When it usually starts

010203040506070+

Hot Tub Folliculitis. Can occur at different ages after a relevant exposure or follicular inflammation.

Fungal Acne. Fungal Acne Often teens and young adults Malassezia folliculitis is more common in adolescents and young adults, but it can occur at other ages. A new rash after heat, sweating, antibiotics or immune suppression can be a useful clue; timing cannot confirm the diagnosis.

Causes and triggers

Causes

Contaminated water introduces bacteria into follicles.

Fungal acne is caused by an overgrowth of Malassezia yeast inside hair follicles. The yeast normally lives on skin but grows too much in warm, oily, sweaty conditions.

An overgrowth of normally present Malassezia yeast within follicles, followed by inflammation. Malassezia normally lives on skin. Finding surface yeast or noticing itch alone does not confirm that it is causing the rash.

Family tendency

This is not usually considered an inherited disorder. Oily skin and other individual factors can influence susceptibility.

Risk factors
Poorly maintained hot tubs or pools, Wet swimwear
Oily skin, Weakened immunity, Diabetes, Heat and humidity, Sweating, Immune suppression
Trigger
● Hot Tub Folliculitis
● Fungal Acne
Contaminated hot-tub exposure
Can contribute
Not listed
Heat and humidity
Not listed
Well established
Sweating in tight clothes
Not listed
Strong link
Antibiotics
Not listed
Strong link
Steroid medicines
Not listed
Strong link
Heavy oils on the skin
Not listed
Possible
Stress
Not listed
Not a typical trigger
Hormonal changes
Not listed
Not a typical trigger
Pore-clogging products
Not listed
Can contribute
Sun exposure
Not listed
Not a typical trigger
Heat and sweating
Not listed
Common trigger
Alcohol
Not listed
Not a typical trigger
Spicy foods
Not listed
Not a typical trigger
Harsh skin care
Not listed
Not a typical trigger
Friction and tight clothing
Not listed
Can contribute
Shaving or waxing
Not listed
Not a typical trigger
Poorly maintained hot tubs
Not listed
Not a typical trigger
Prolonged antibiotic use
Not listed
Can contribute

Daily Care

Hot Tub Folliculitis
Fungal Acne
Daily care

Habits that help

  • Stop using the suspected pool or hot tub
    Return only when it has been appropriately cleaned and maintained.
  • Remove wet swimwear and shower after swimming
    Wash the swimwear and let it dry fully before reusing it.
  • Keep affected skin cool and clothing loose
    Reduce rubbing and prolonged moisture over the bumps.
  • Wash gently and leave the spots alone
    A mild cleanser is less irritating than scrubbing.
  • Seek review for worsening illness or a rash that does not settle
    Fever, significant pain or immune suppression changes the need for assessment.

Avoid

  • Avoid: Squeezing bumps or shaving across the rash
    This can worsen irritation and introduce another infection.

Habits that help

  • Shower and change after sweating
    The habit that prevents recurrence.
  • Breathable clothing, changed promptly
    Loose cotton or moisture-wicking, not a fitted top.
  • Keeping the routine simple
    A gentle cleanser, light moisturizer and sunscreen.
  • Sunscreen on exposed areas
    It stops the dark marks from deepening.
  • An antifungal shampoo as a body wash
    Ketoconazole, selenium sulfide or zinc pyrithione, over the counter.
  • A topical antifungal cream
    Ketoconazole or clotrimazole for limited patches.
  • Reduce prolonged heat and dampness when possible
    Cases rise every summer. People who clear in winter flare again.

Avoid

  • Avoid: Staying in damp workout clothes
    Sweat held against skin is what the yeast needs.
  • Avoid: Occlusive clothing, straps and gear
    The bumps follow what was worn.
  • Avoid: Heavy oils and butters
    They add the fats the yeast lives on and hold heat in.
  • Avoid: Scratching
    Turns bumps into marks that last months.
  • Avoid: Long gaps before showering
    The delay matters more than the sweating.
  • Avoid: Stacking more acne actives
    A fourth product adds irritation, not clearance.
  • Avoid: Treating it as acne
    Retinoids and salicylic acid target blocked pores. This is not one.
  • Avoid: Stopping treatment early
    Stop the moment it looks clear and it returns within weeks.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Hot Tub Folliculitis
● Fungal Acne
Over-the-counter
None listed
Ketoconazole 1% shampoo.

Ketoconazole 1% shampoo

Moderate evidence

The main over-the-counter treatment, used as a body wash rather than for hair. Lather it over the chest, back, shoulders and hairline in the shower and leave it on several minutes before rinsing, daily for two to four weeks. Rinsing it straight off is the most common reason it seems not to work.


Two Selsun Blue bottles, two Head and Shoulders Clinical Strength bottles and a Vichy Dercos bottle and box

Selenium Sulfide

Moderate evidence

An anti-dandruff shampoo used the same way, lathered on the affected areas and left several minutes. A reasonable alternative if ketoconazole irritates or is hard to find. It can be drying and can discolor light-colored hair, so keep it on the body.

Four dandruff shampoo bottles: DHS Zinc, Head and Shoulders Classic Clean, CeraVe Anti-Dandruff and Head and Shoulders Bare

Pyrithione Zinc

Limited evidence

The gentlest of the three anti-dandruff washes, and the easiest to keep using long term. It is a good choice for maintenance once the bumps have cleared, once or twice a week through the hot months. It is usually a little weaker than ketoconazole for clearing an active crop.

Four sulfur acne products: Kate Somerville EradiKate, De La Cruz 10% sulfur ointment, The Ordinary and Thayers

Sulfur

Limited evidence

A sulfur wash or soap has some activity against this yeast and is an option if the antifungal shampoos are not tolerated. The evidence in fungal acne specifically is thin. It smells and can be drying on the chest and back.

Three acne wash tubes on white: Differin Deep Cleanser, CeraVe Acne Foaming Cream Cleanser and PanOxyl

Benzoyl Peroxide

Limited evidence

It has some effect on Malassezia, which is why a few people improve partially on it and then stall. It is not the right tool here, and used as a wash it can leave the chest and back dry and irritated. If it half-works, that is a hint to switch to an antifungal wash rather than to use more of it.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

It works by clearing blocked pores, and this is not a blocked-pore condition, so it does not act on the yeast. Some people find a wash mildly helpful for the texture. It will not clear the bumps, and scrubs and brushes usually make an irritated chest and back angrier.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Limited evidence

Widely suggested online for fungal acne and not well studied in it. It irritates inflamed skin easily, and it is a common cause of allergic reactions on the chest and back. A proven antifungal wash costs about the same and is available without a prescription.

Prescription topicals
None listed
Ketoconazole — Header Image

Ketoconazole

Moderate evidence

Ketoconazole 2% cream. The prescription strength, used as a cream on limited areas such as the jawline, forehead or hairline, or as a shampoo on the body. It is the usual next step when the over-the-counter 1% wash has not been enough. A cream is impractical for a whole back, which is where the wash or tablets take over.

Clotrimazole

Limited evidence

Clotrimazole cream. An older antifungal cream, applied twice a day to small patches. It works against this yeast and is inexpensive and widely available. Like any cream, it only suits areas you can realistically cover, so it is a jawline and hairline option rather than a chest and back one.

Ciclopirox

Limited evidence

Ciclopirox cream or shampoo. Another antifungal option, used when ketoconazole has irritated the skin or has not worked. There is less published evidence in Malassezia folliculitis specifically than for ketoconazole. It is used the same way, with the shampoo left on for several minutes.

Five adapalene gel 0.1% tubes and boxes lined up on white, including Differin, Effaclar, PanOxyl and Neutrogena

Adapalene

Limited evidence

A retinoid works on blocked pores, and there is no plug to clear here, so it does not treat the yeast. It is often already in use because the bumps were assumed to be acne. It can stay if you also have genuine acne, but it is not what clears this.

A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Limited evidence

A topical antibiotic reduces the bacteria that compete with the yeast, so at best it does nothing here and at worst the bumps get denser. Skin that gets worse rather than better on an acne antibiotic is one of the strongest clues that this is fungal acne.

Prescription pills

Antibiotic assessment

Listed

Persistent, severe or systemic illness needs a clinician; antibiotics are not routinely required for every mild case.

Representative medication packaging labelled Itraconazole, lying sideways on a white background.

Itraconazole

Moderate evidence

The tablet most often used for stubborn or widespread cases, usually for one to three weeks. It clears extensive chest and back involvement far more reliably than a wash can. It interacts with a long list of other medicines, so the prescriber checks what else you take first.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Moderate evidence

The other antifungal tablet used here, often as a weekly dose for a few weeks. It suits people who cannot take itraconazole. Tablets clear the yeast but do not change the heat, sweat and occlusion that brought it on, so a maintenance wash is usually continued afterwards.

Terbinafine — Header Image

Terbinafine

Limited evidence

The antifungal tablet used for nail and foot infections, and it is a poor choice here. Malassezia is not reliably killed by it at the doses used by mouth. If an antifungal tablet is being considered, itraconazole or fluconazole are the ones with evidence in this condition.

An amber prescription bottle lying on its side on a white background with a plain white label reading Doxycycline, and six small round white tablets spilled out in front of it.

Doxycycline

Limited evidence

An antibiotic prescribed for acne is one of the most reliable ways to make this worse, because it clears the bacteria that hold the yeast in check. A crop of itchy bumps appearing a few weeks into or after a course is a classic history. It is not a treatment for fungal acne.

Outlook

Long term

Most uncomplicated cases clear within about two weeks. Another exposure to contaminated water can cause recurrence; fever, worsening illness or immune suppression warrants medical advice.

Fungal acne appears over a short period rather than gradually, and the right treatment works quickly. It comes back if the conditions return.

Complications

Possible complications

Scratching can cause crusting and secondary infection.

  • The bumps multiply but stay small
More details

The bumps multiply but stay small
They stay small rather than growing. The itch bothers most people more than the bumps.

When to get help

When to get help

Seek care for fever, worsening pain, immune suppression or a rash that does not settle.

<span class="trigger-dash">—</span>

Seek help for a persistent itchy, uniform rash, repeated relapses, or bumps that have not improved with acne treatment. A skin sample may help distinguish causes.

Fever, spreading painful redness, or rapidly worsening bumps need prompt assessment, especially if your immune system is suppressed.

Common questions

Hot Tub Folliculitis:What is Hot Tub Folliculitis?

A follicular eruption after exposure to water contaminated with Pseudomonas bacteria.

Hot Tub Folliculitis:What can I do day to day?

Leave the contaminated water, remove wet swimwear, shower and wash the swimwear.

Hot Tub Folliculitis:When should I get medical advice?

Seek care for fever, worsening pain, immune suppression or a rash that does not settle.

Fungal Acne:How do I know if it is fungal acne rather than acne?

Three things separate them. Fungal acne itches; acne usually does not. Fungal acne has no blackheads or whiteheads. And the bumps are all the same small size, in a sheet across the chest, shoulders, upper back and hairline, not a mix of sizes on the face. A start after antibiotics, steroids or a hot sweaty stretch adds to the case.

Fungal Acne:Can I have both at the same time?

Yes, often. Many people have ordinary acne on the face and Malassezia folliculitis on the chest and back, treated in parallel. A routine aimed only at acne leaves half the problem untouched.

Fungal Acne:Is it contagious?

No. The yeast already lives on almost everyone's skin. Nobody gave it to you and you cannot pass it on.

Fungal Acne:Do I really need fungal-acne-safe products?

The idea rests on something real — this yeast cannot make its own fats and takes them from its surroundings. But the ingredient lists online are more confident than the evidence. Avoid heavy oils, butters and occlusive products on the affected areas while it is active, and treat the yeast directly rather than rebuilding a routine.

Fungal Acne:Why does it keep coming back?

Because the conditions return — heat, sweat and occlusion, usually every summer. That is not treatment failure. Most people who stay clear use the antifungal wash once or twice a week through the warm months.

Fungal Acne:Will it leave marks or scars?

Scars are uncommon. Flat dark marks are very common, and because the bumps arrive in large numbers they cover a wide area and take months to fade, particularly on deeper skin tones. Not scratching and treating early reduce them most, and daily sunscreen helps them fade faster.

Sources

Sources and further reading

  1. Spa pool folliculitis
  2. DermNet: Malassezia folliculitis
Dermapedia on YouTube