Rosacea
Low doses reduce bumps.
Doxycycline: An oral antibiotic for moderate to severe inflamed acne. It is meant as a short bridge alongside topical treatment, not a long-term drug. Tazarotene: A strong prescription retinoid for acne, psoriasis and sun damage. It does more than the gentler retinoids and irritates more, and it must not be used in pregnancy.


Choose for a short 3–4 month bridge to calm moderate inflamed acne or rosacea while a retinoid and benzoyl peroxide start working.
Choose for acne or psoriasis that needs a stronger retinoid than tretinoin or adapalene, and you can tolerate more irritation.
Can you take them together?
A standard plan for moderate acne: doxycycline for about 3 months plus tazarotene, which continues once the antibiotic stops.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.




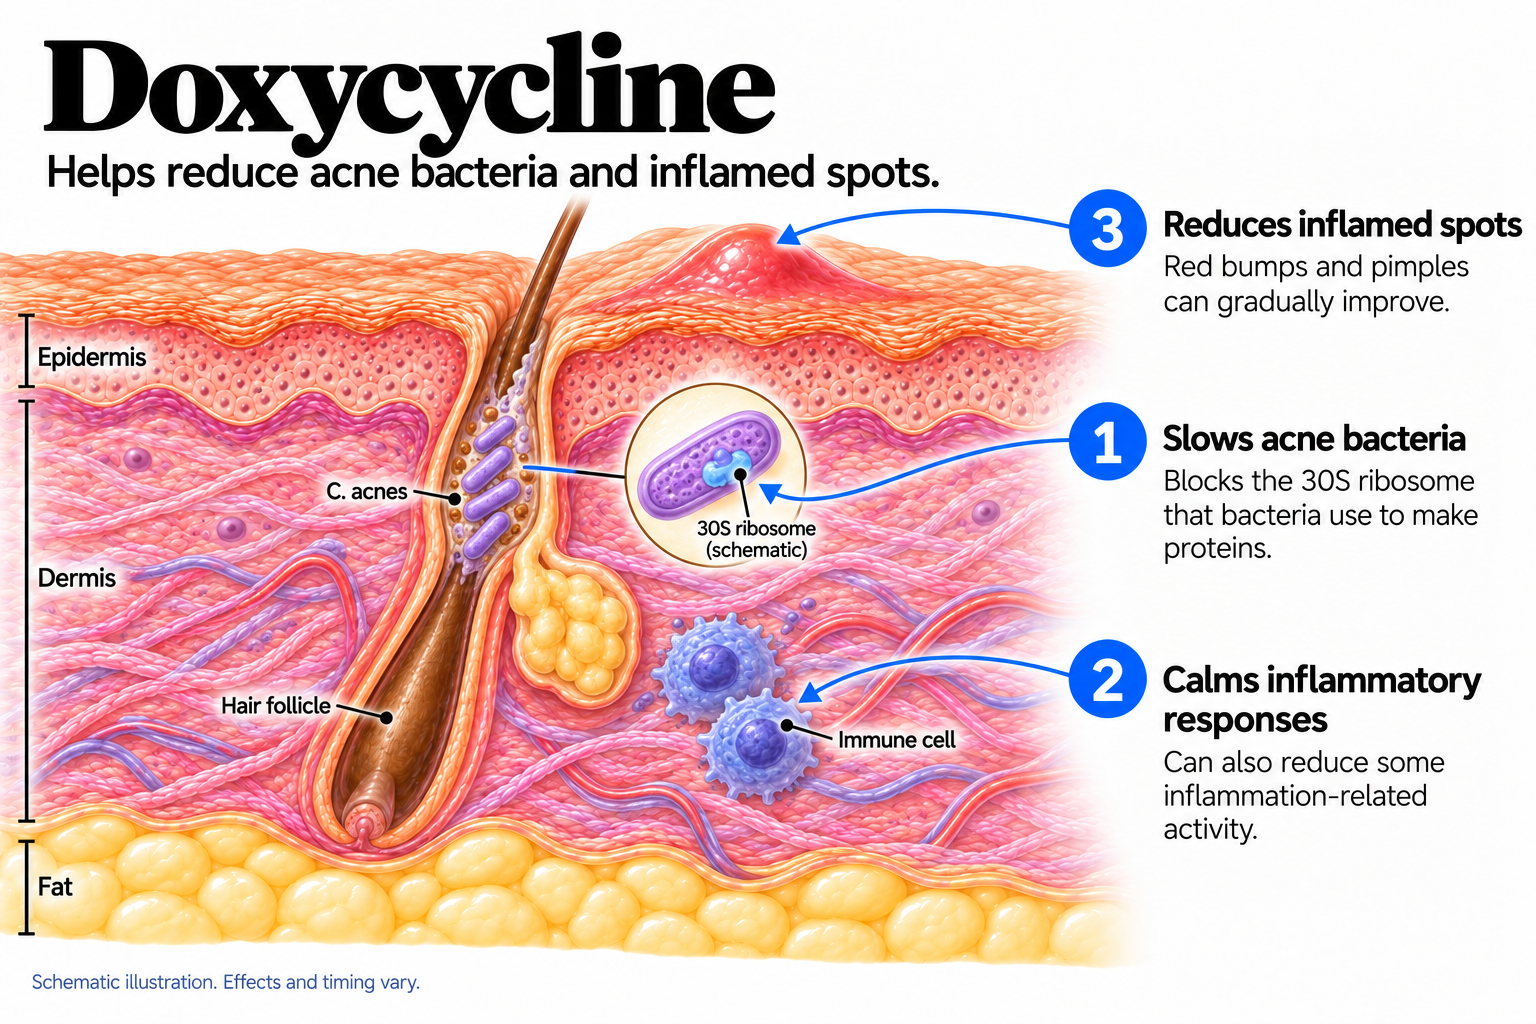
Slows acne bacteria: Blocks the 30S ribosome that bacteria use to make proteins. Calms inflammatory responses: Can also reduce some inflammation-related activity. Reduces inflamed spots: Red bumps and pimples can gradually improve.
Bacterial protein-synthesis inhibition is established. The complete acne mechanism and the contribution of individual antibacterial and anti-inflammatory effects are not fully defined. This does not imply direct exfoliation, oil-gland shrinkage, or treatment of resistant bacteria.

Activates retinoid receptors: Skin converts it to an active form that changes gene signals. Helps unclog pores: Normalizes cell buildup inside follicles. Reduces excess skin growth: Helps psoriasis cells grow and mature more normally. Improves sun-damaged skin: Can improve fine wrinkles and uneven pigmentation.
Tazarotene is converted to tazarotenic acid, which preferentially activates RAR-beta/gamma. Full clinical mechanisms are not defined. Acne, psoriasis and photodamage evidence comes from different formulations/strengths; clinical benefits are not guaranteed.
Dose depends on what your stomach tolerates, not body weight. Kidney or liver problems can lower it.
Starting dose: 50 mg to 100 mg once or twice a day. Some doctors start low to see how your stomach does.
Going up: Raised after a week or two if you tolerate it and the acne has not budged.
Usual dose: Around 100 mg once or twice daily. Low-dose anti-inflammatory regimens use much less.
Total course: Three to four months. Reassess at three months and stop once topical treatment can hold the result.
When to Apply: At night only, on completely dry skin — about twenty minutes after washing, because damp skin absorbs more and stings more. A pea-sized amount covers the whole face. Moisturizer underneath, on top, or both. Sunscreen every morning is part of the treatment.
How to Start: Two or three nights a week for the first two to four weeks, then build toward nightly as the skin allows. Most people who quit started nightly. For thick psoriasis plaques some doctors use short contact — applied, then washed off after twenty to thirty minutes — but only if you were told to.
If It Irritates: Moisturizer before and after, drop back a night or two a week, and take two or three nights off if the skin is raw. Do not scale up other actives at the same time. Cold, wind and hot showers make it worse.
If It’s Not Working: Give it a full twelve weeks. If acne is still active, step up the strength, change to the gel, or add benzoyl peroxide or an oral option. Check first that you are treating the whole area, not dabbing spots.
With a full glass of water and with food. Stay upright for 30 minutes afterward, and never right before bed — a tablet stuck in the food pipe can burn the lining. Food cuts the nausea and does not block absorption.
Take it when you remember, unless the next dose is close. Never double up — you will just be nauseated.
No blood tests are needed for a standard acne course in a healthy person. Monitoring is clinical, with a review at about three months.
This is not a drug to stay on for years. What builds is antibiotic resistance — in your skin bacteria and in the rest of your body — along with effects on the gut. Keep oral courses for acne as short as possible, with a topical retinoid running alongside to take over.
No blood tests are needed. Two things get monitored: how the skin is tolerating it, and pregnancy status.
Because tazarotene is contraindicated in pregnancy, anyone who could become pregnant should expect a conversation about reliable contraception before starting, and in some settings a pregnancy test. Very little reaches the bloodstream, but the restriction is absolute.
The other checkpoint is a review at around twelve weeks: hold the strength, step up, or add something. People stay on this for years, and nothing accumulates that needs testing.
Approximate windows, not promises.
Weeks 1 to 2Little change. Any stomach upset shows up now.
Weeks 2 to 6Fewer, less painful inflamed spots. Blackheads do not change.
After 12 weeksIf inflamed acne is no better, continuing will not help. Reassess rather than extend.
First few minutesApplying it: A pea-sized amount on dry skin at night. Mild stinging is normal.
Weeks 1 to 4The adjustment: Dryness, flaking around the nose and mouth, mild redness, peaking in weeks two to three. Acne can look worse first as forming clogs surface.
Weeks 4 to 8Adapting: Peeling settles and new spots get less frequent. Most quit before reaching this.
Weeks 8 to 12Judge it here for acne: Fewer new spots, fewer blackheads and whiteheads. Trials measured here, and it keeps building. Psoriasis plaques thin on the same timeline and often stay thinner after stopping.
4 to 6 monthsTexture and fine lines: Gradual smoothing. A months-to-years treatment, not a course.
6 months or moreMottled pigment and dark marks: The slowest of all. Sunscreen does as much work as the retinoid.
ThroughoutSun and flushing: Skin burns more easily, so daily sunscreen is not optional. Stinging, and a flush after alcohol or hot drinks, settle.
Sorted by what to do about them.
Generic doxycycline is cheap, though prices have swung at times. Branded high-dose and modified-release versions cost far more and rarely work better. Monohydrate and hyclate are both generic — if one upsets your stomach, try the other.
This is the honest weak point. The lotion and the foam are brand-only and expensive, coverage is inconsistent, and prior authorization is common — plans usually want a cheaper retinoid tried first.
Generic cream and gel cost considerably less, though still more than tretinoin. Adapalene is sold without a prescription in many places and is the least expensive retinoid. If cost is the barrier, ask about generic cream or gel at 0.05%.
Three to four months. A year on it means the plan needs revisiting, not refilling.
Occasional drinking is fine. Heavy drinking can lower drug levels.
No. There is no meaningful interaction with combined oral contraceptives. Rifampin is the one that interferes.
It makes skin much more reactive to ultraviolet light, and reverses after you stop.
No. That combination raises the risk of pressure around the brain.
Little for the first month, real change between weeks eight and twelve. Texture and pigment take longer.
Clogs already forming are being pushed to the surface sooner. It settles by weeks six to eight.
No. Tazarotene is contraindicated in pregnancy and should be stopped before trying to conceive. Ask your doctor what to use instead.
Generally yes, and more irritating for the same reason. Whether it works better depends on whether you can use it consistently.
Yes — about a week beforehand, and tell whoever is treating you that you use a prescription retinoid.
Yes. Unlike tretinoin, it is not broken down by benzoyl peroxide. The pair can be drying, so use one in the morning and one at night.