Clotrimazole or another topical antifungal
ListedTreats Candida in a suitable formulation; follow clinician or local product advice.
Yeast infection affecting an inflamed skin fold. Contact dermatitis is a rash caused by something that touched the skin. It comes in two forms - irritation from a substance that would bother anyone given enough exposure, and an allergic reaction to something only some people react to. Both clear once the cause is found and removed.
The same eight facts on every condition comparison.
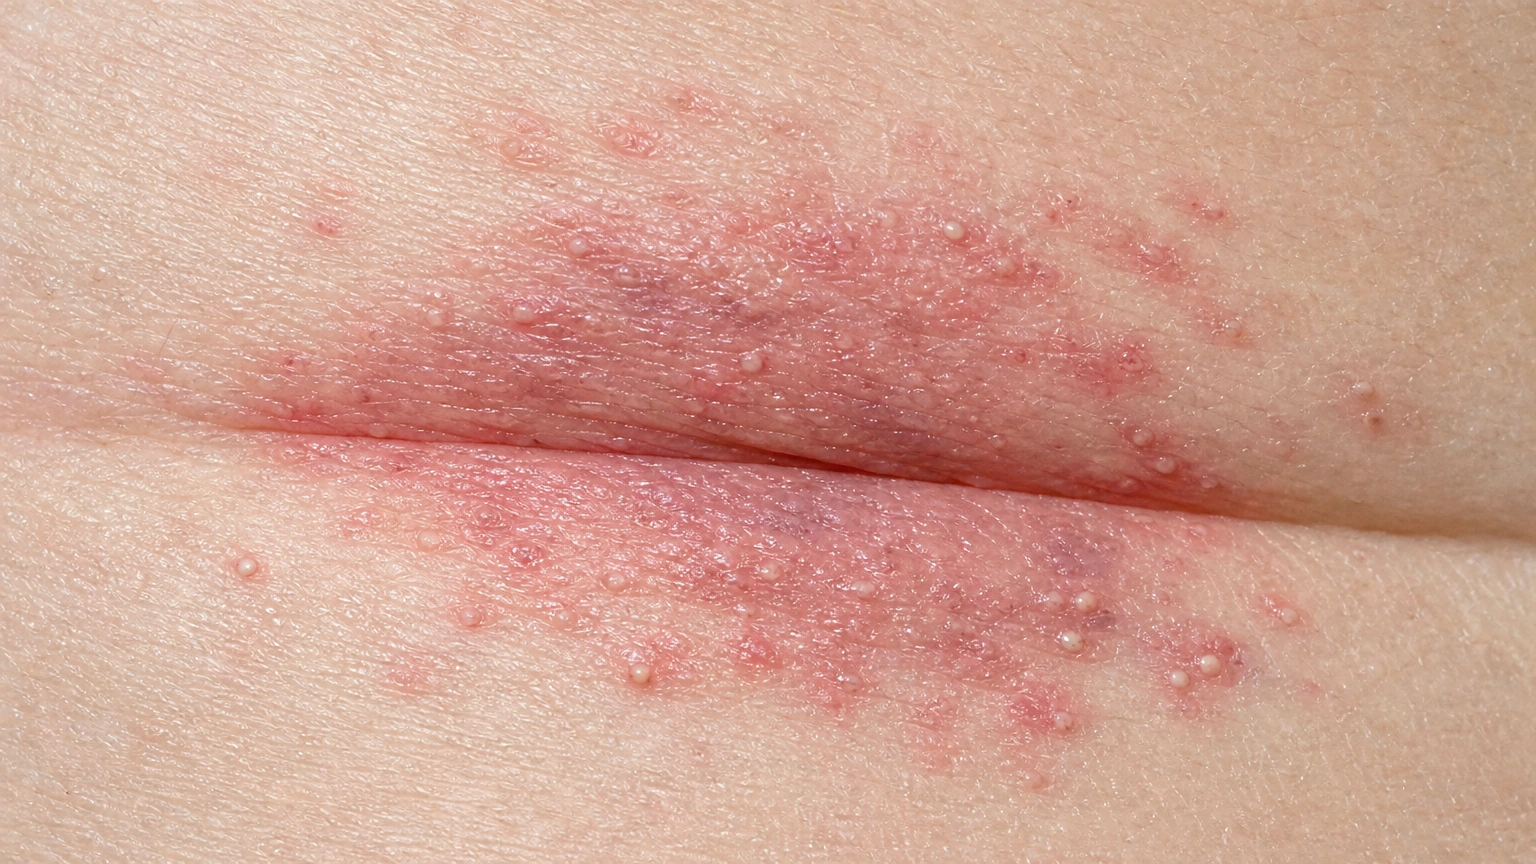
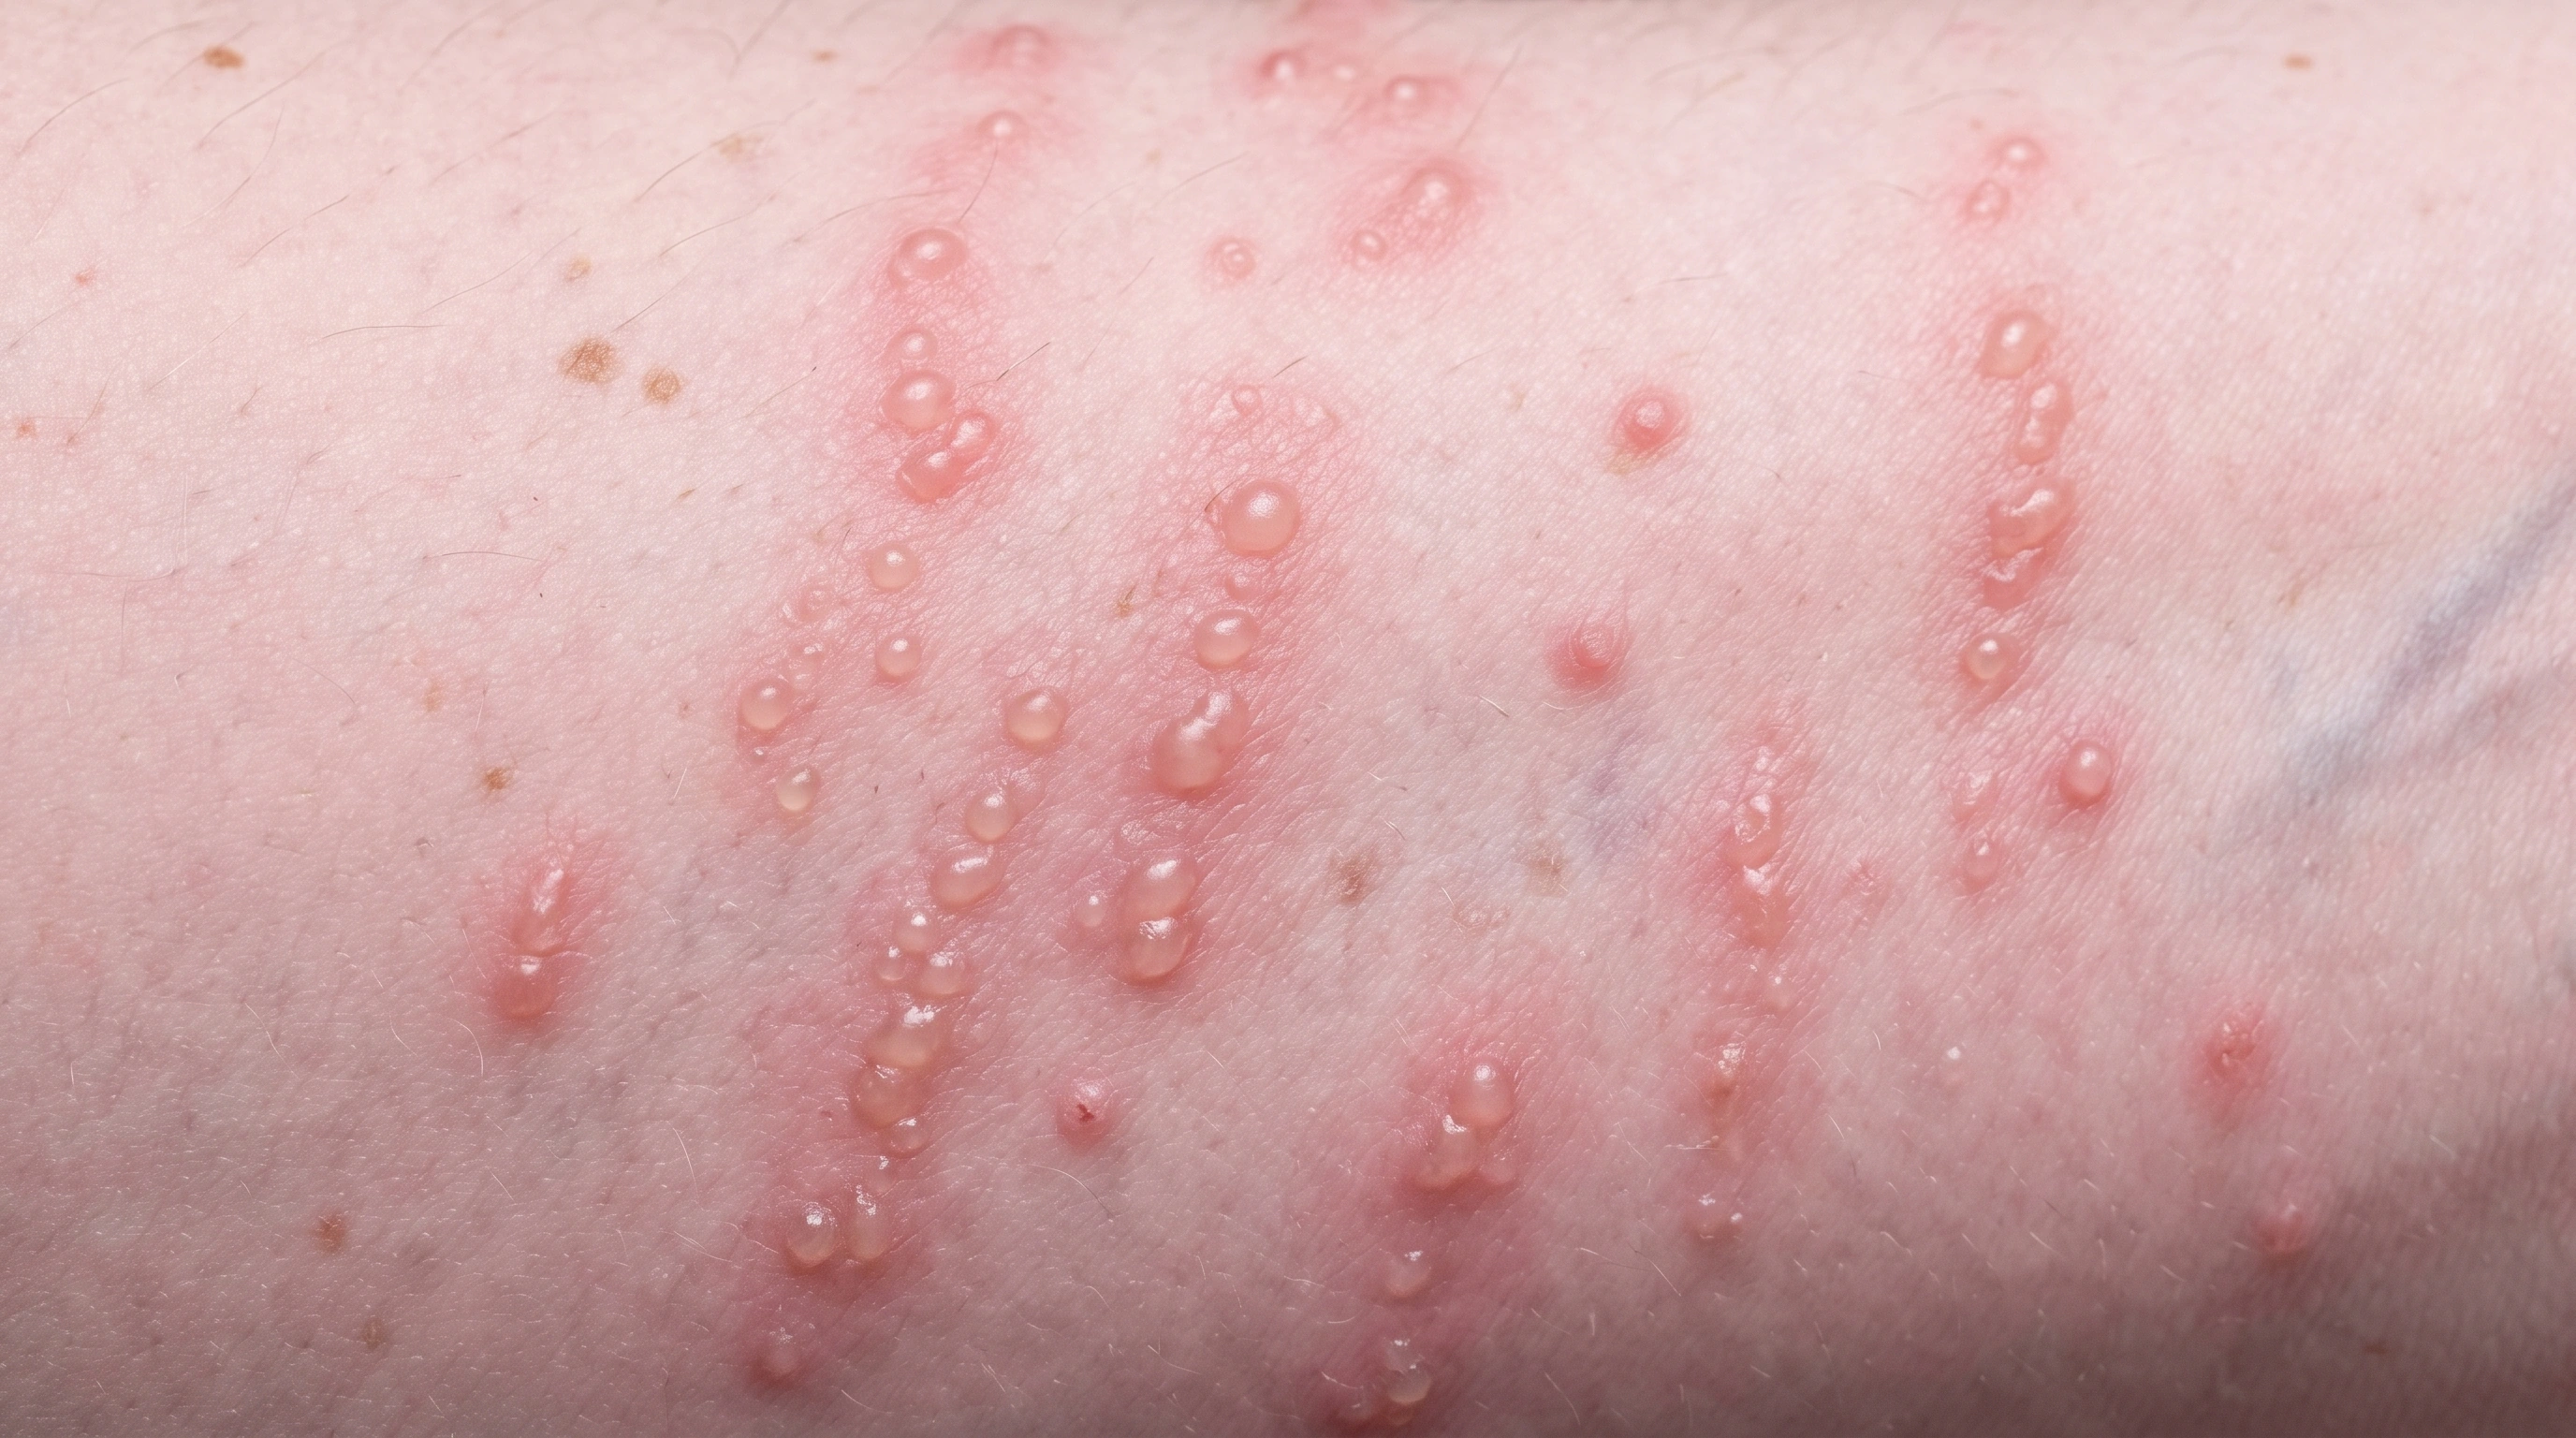
Candidal Intertrigo A bright red crease is surrounded by smaller scattered spots.
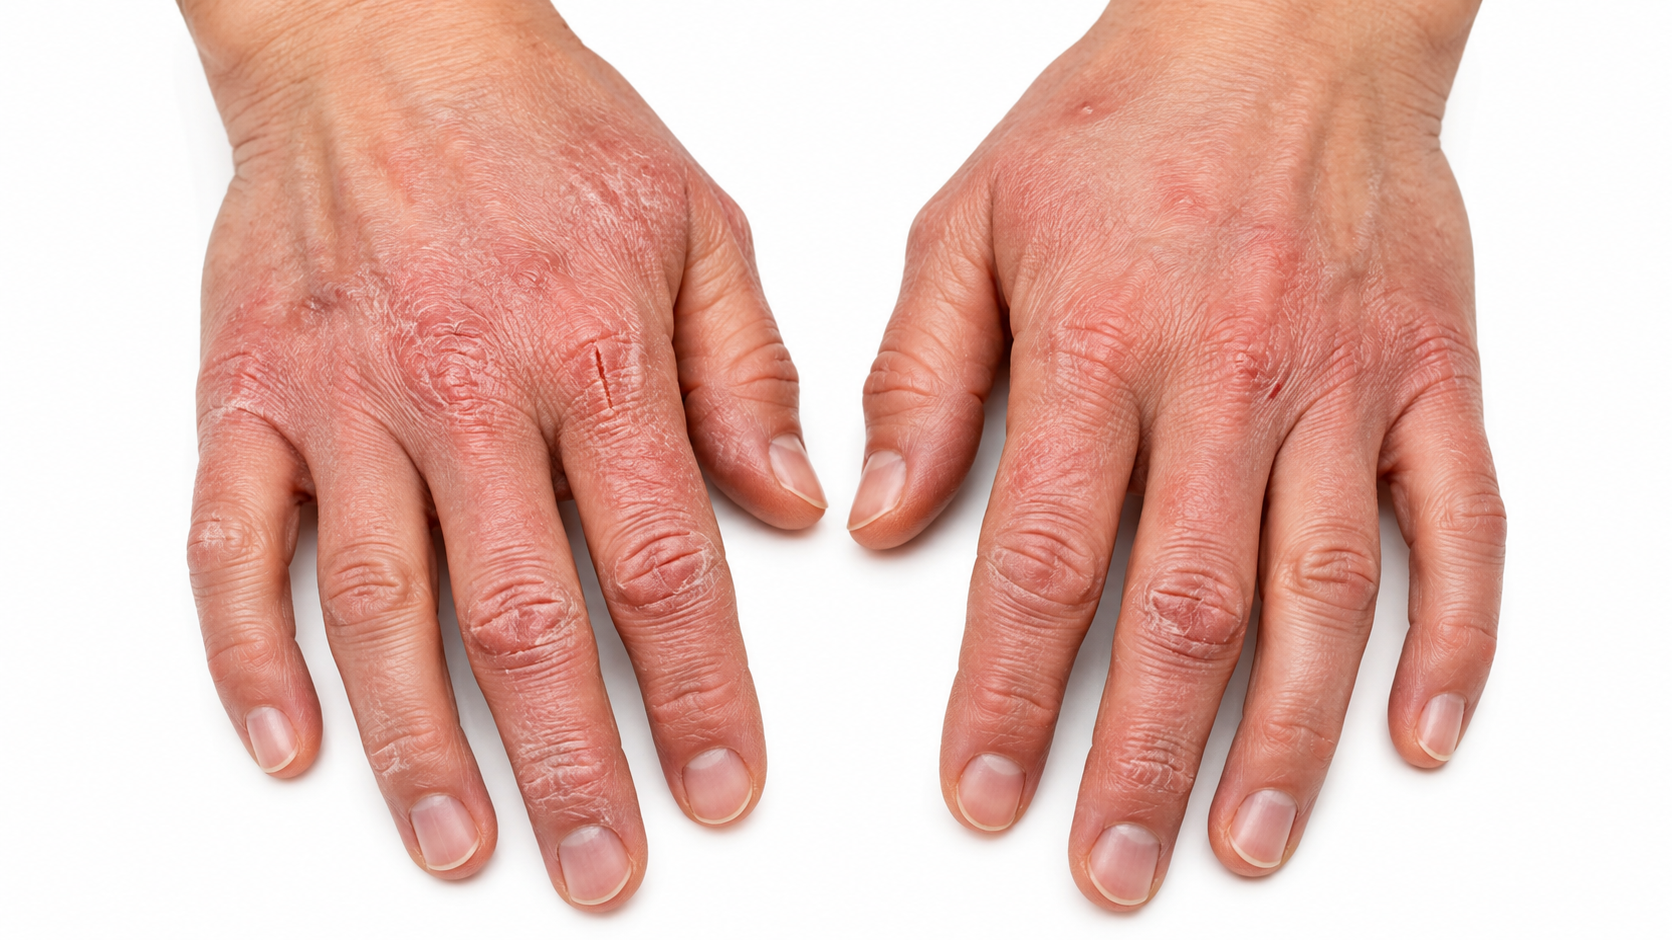
Irritant contact dermatitis Damage from soaps, solvents or water; most common.

Allergic contact dermatitis Immune reaction to nickel, fragrance, plants and more.
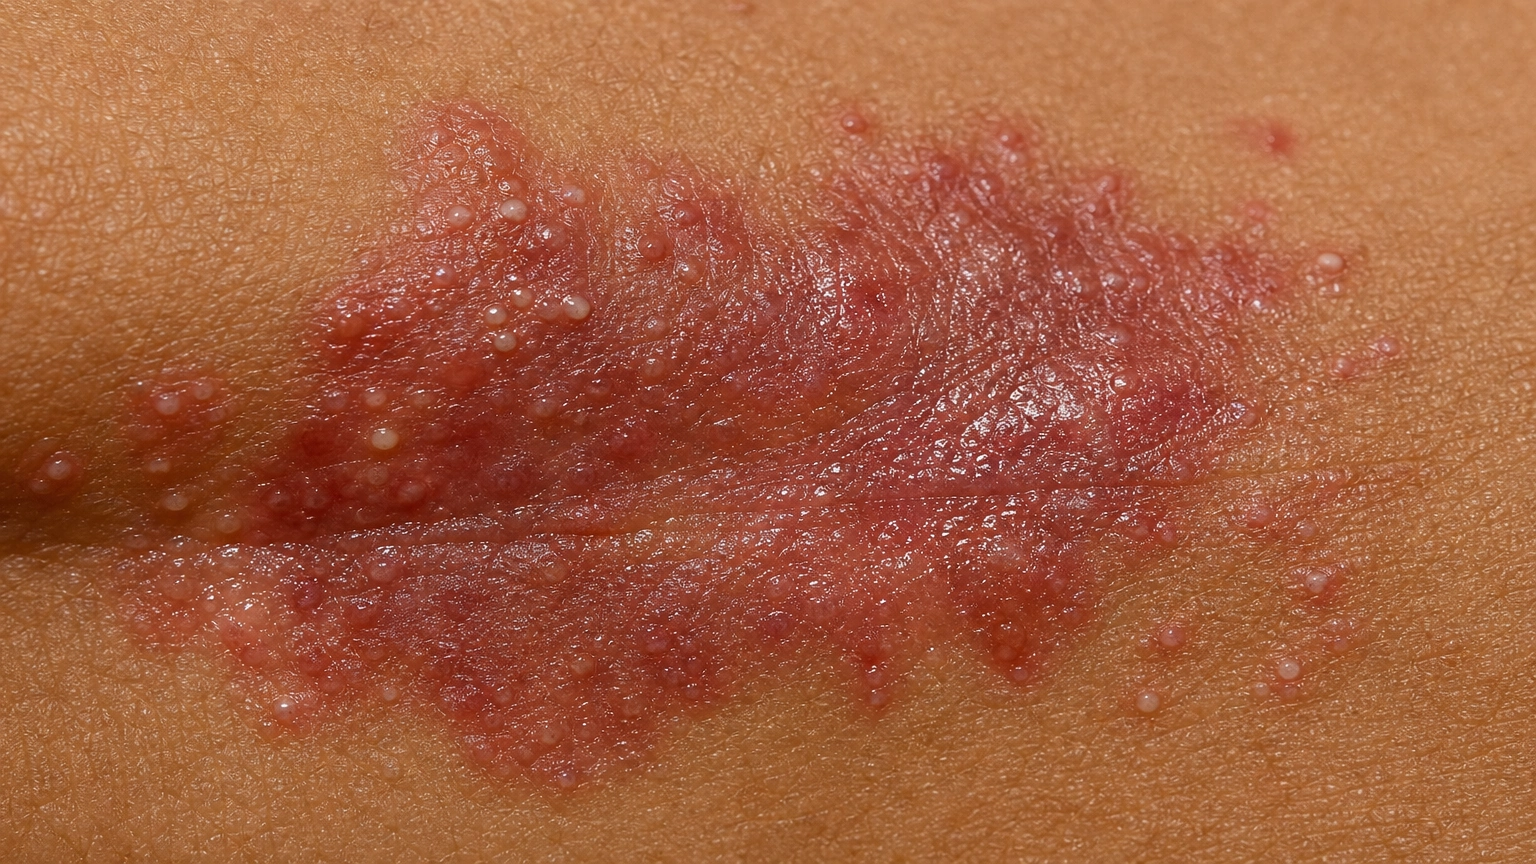
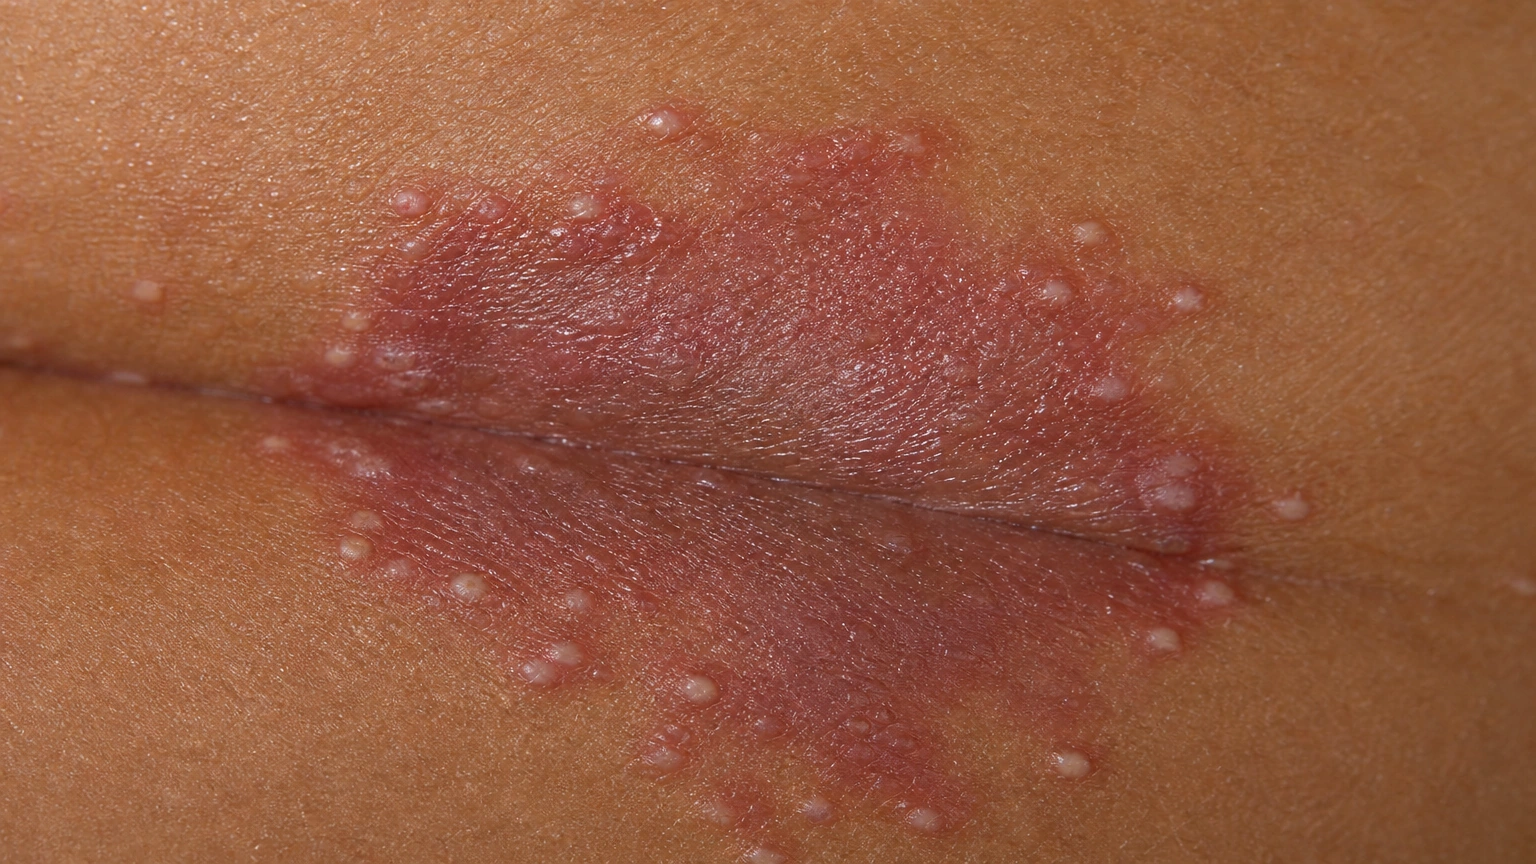
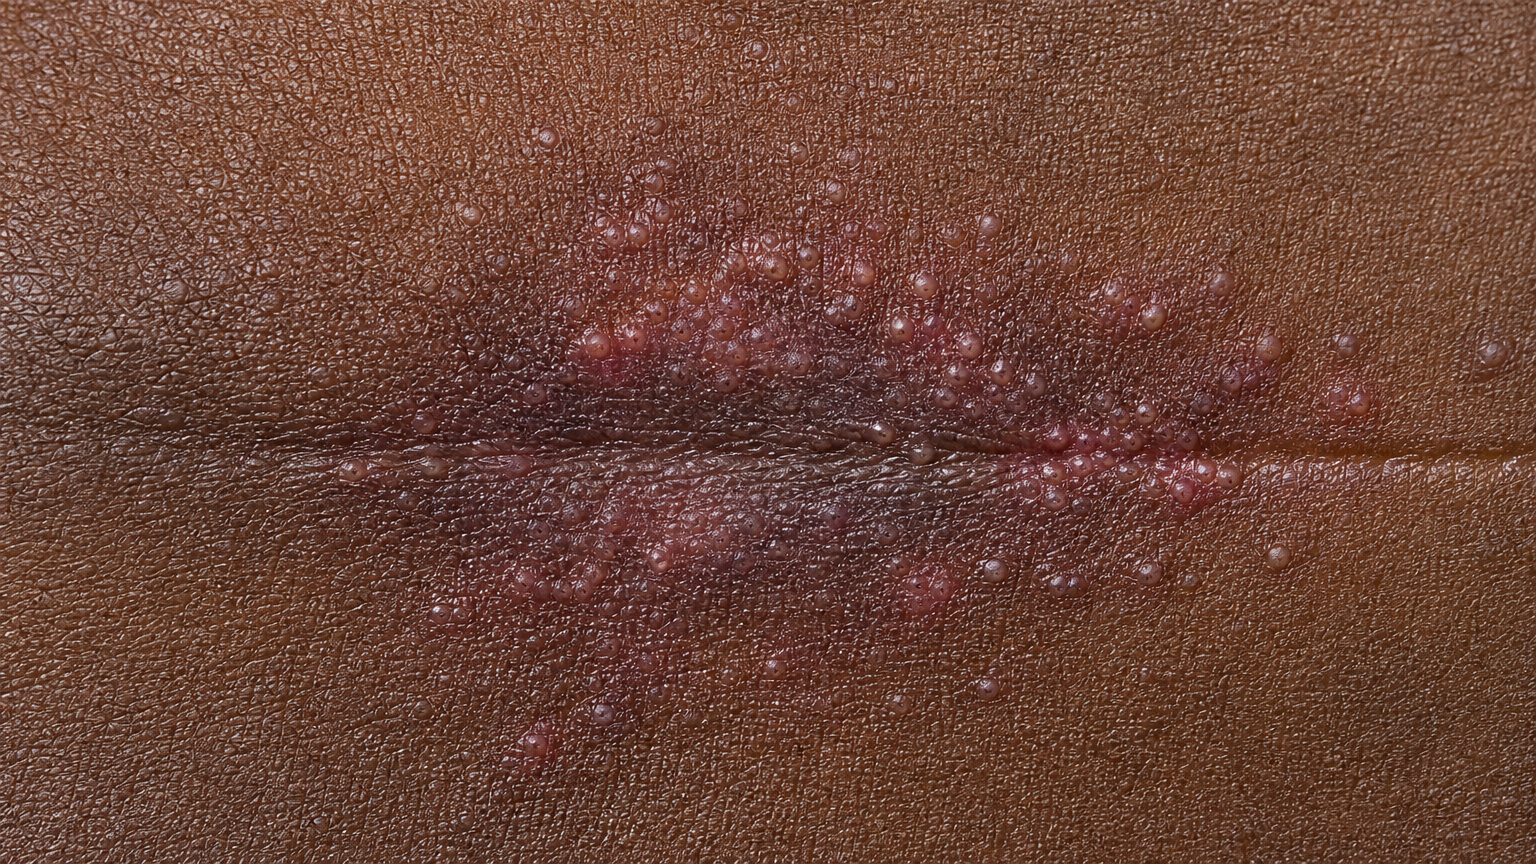
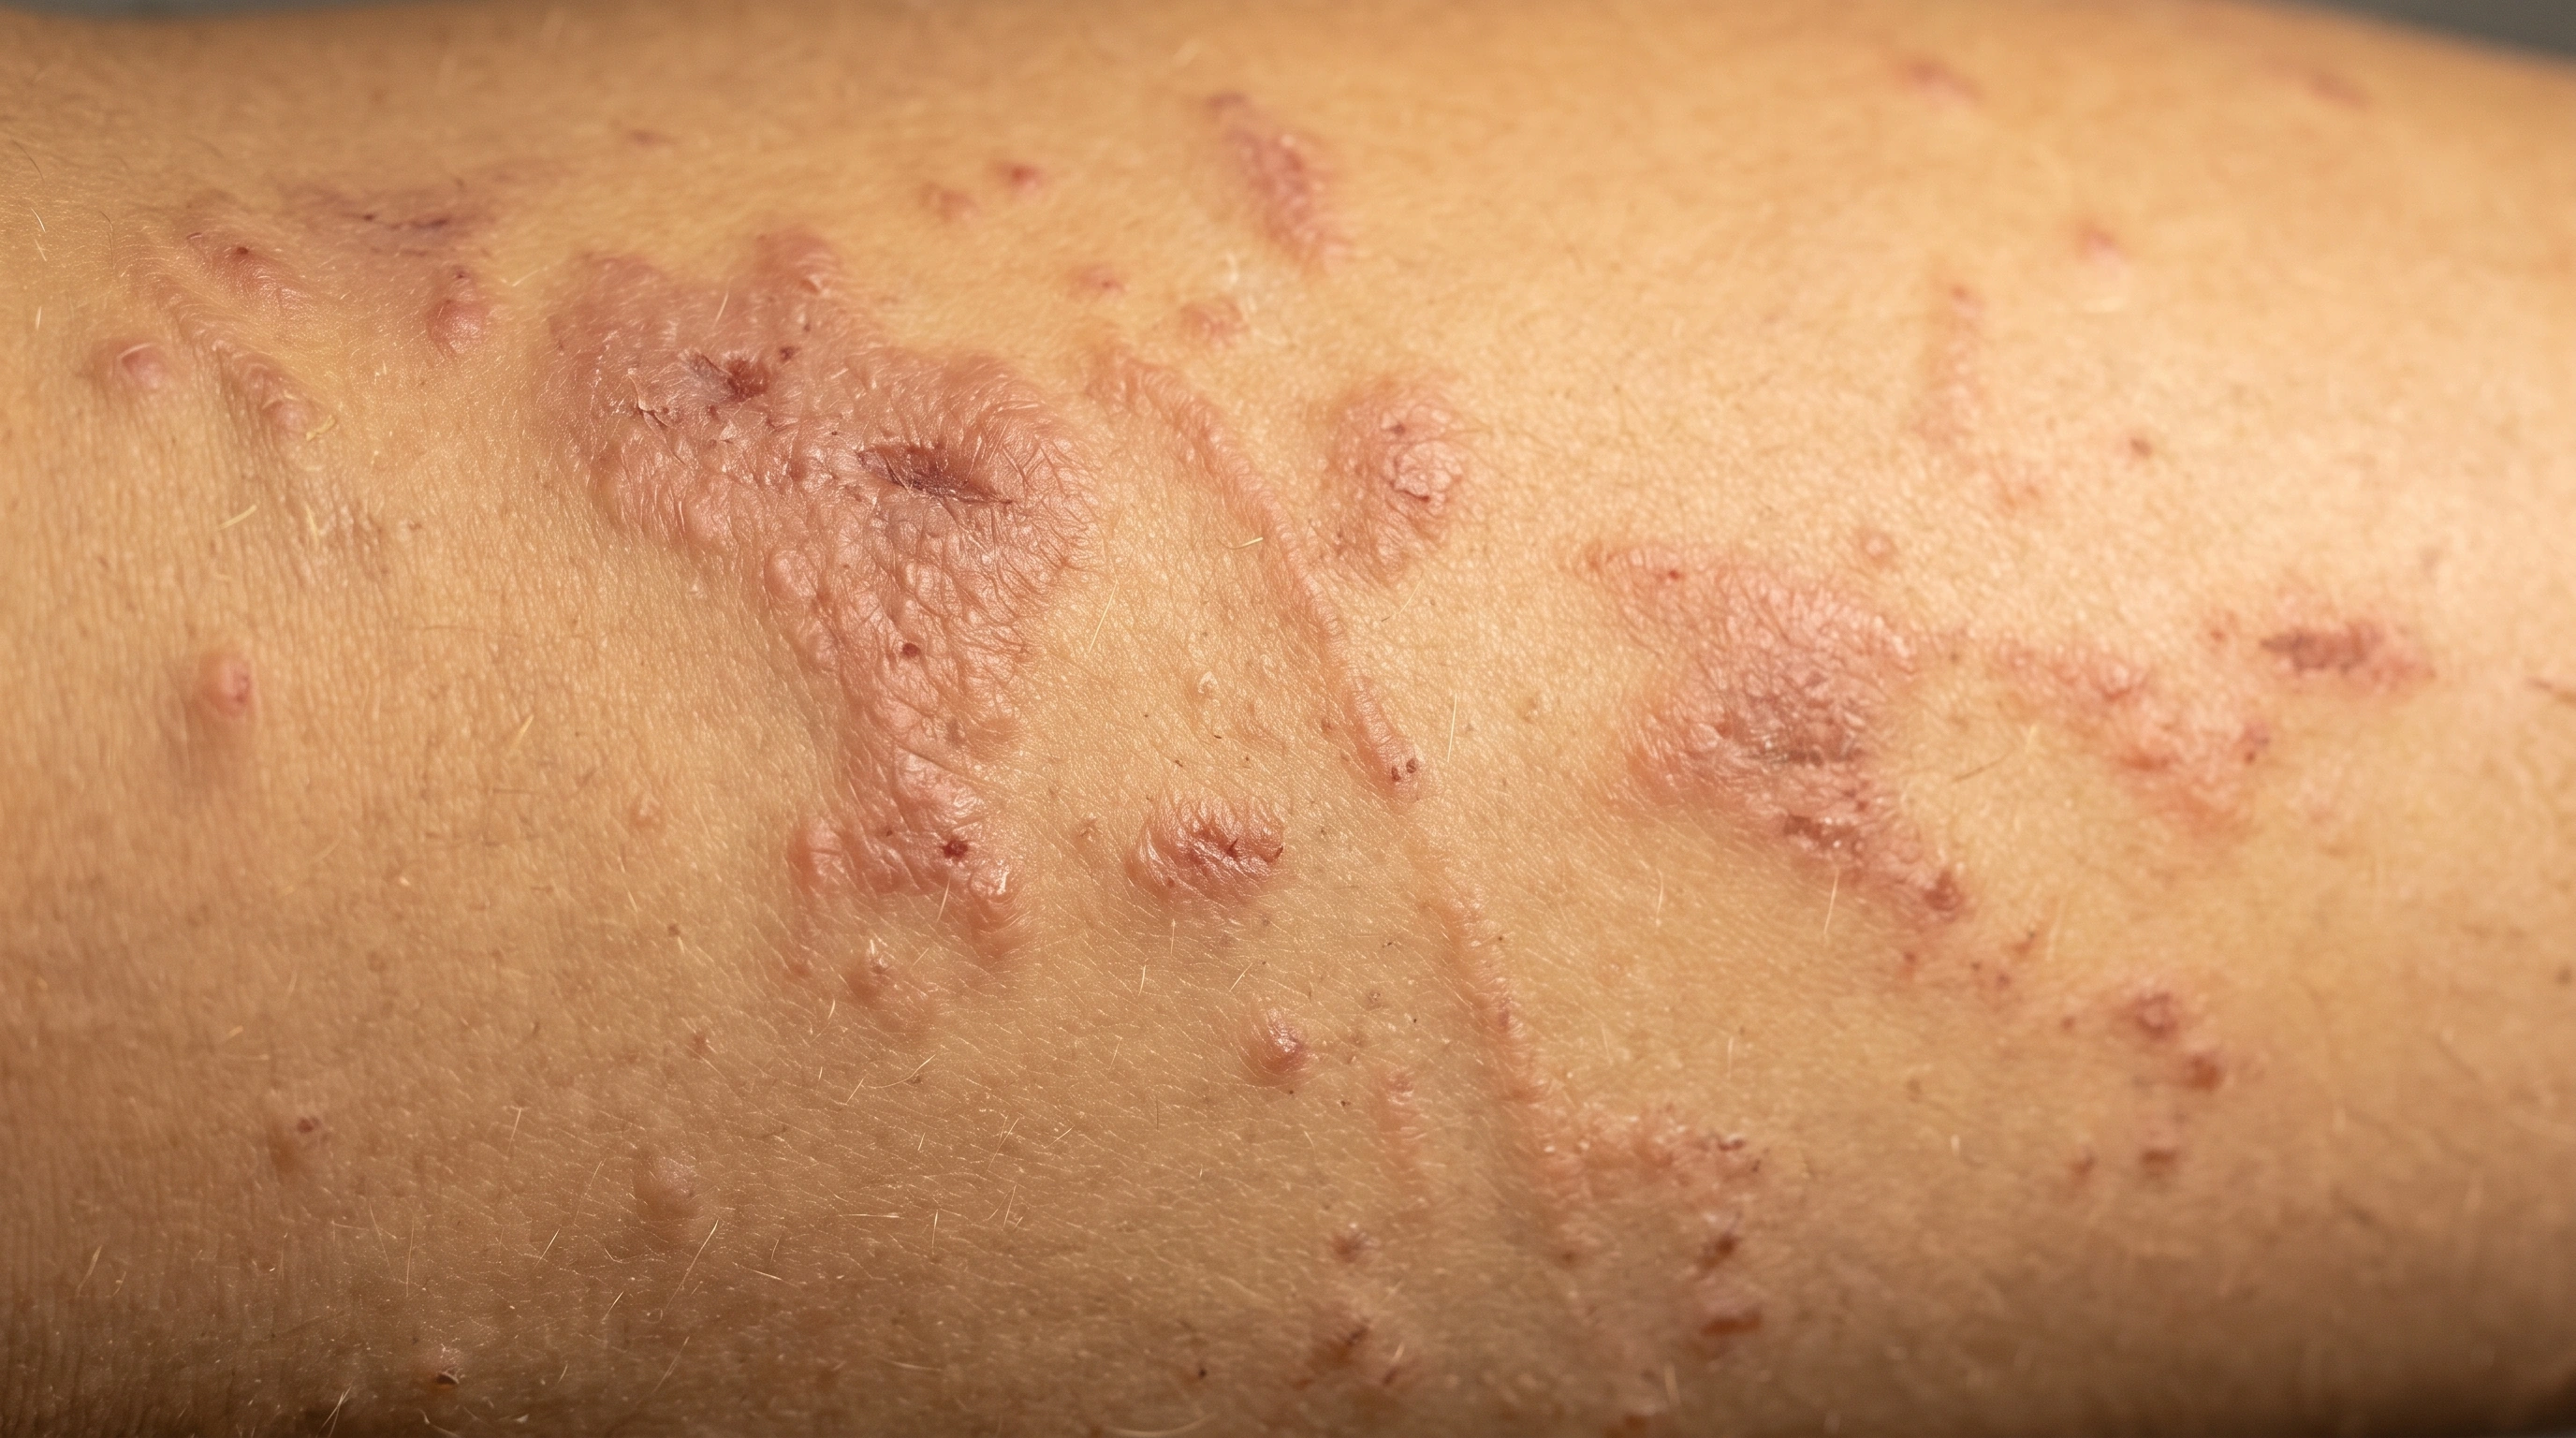
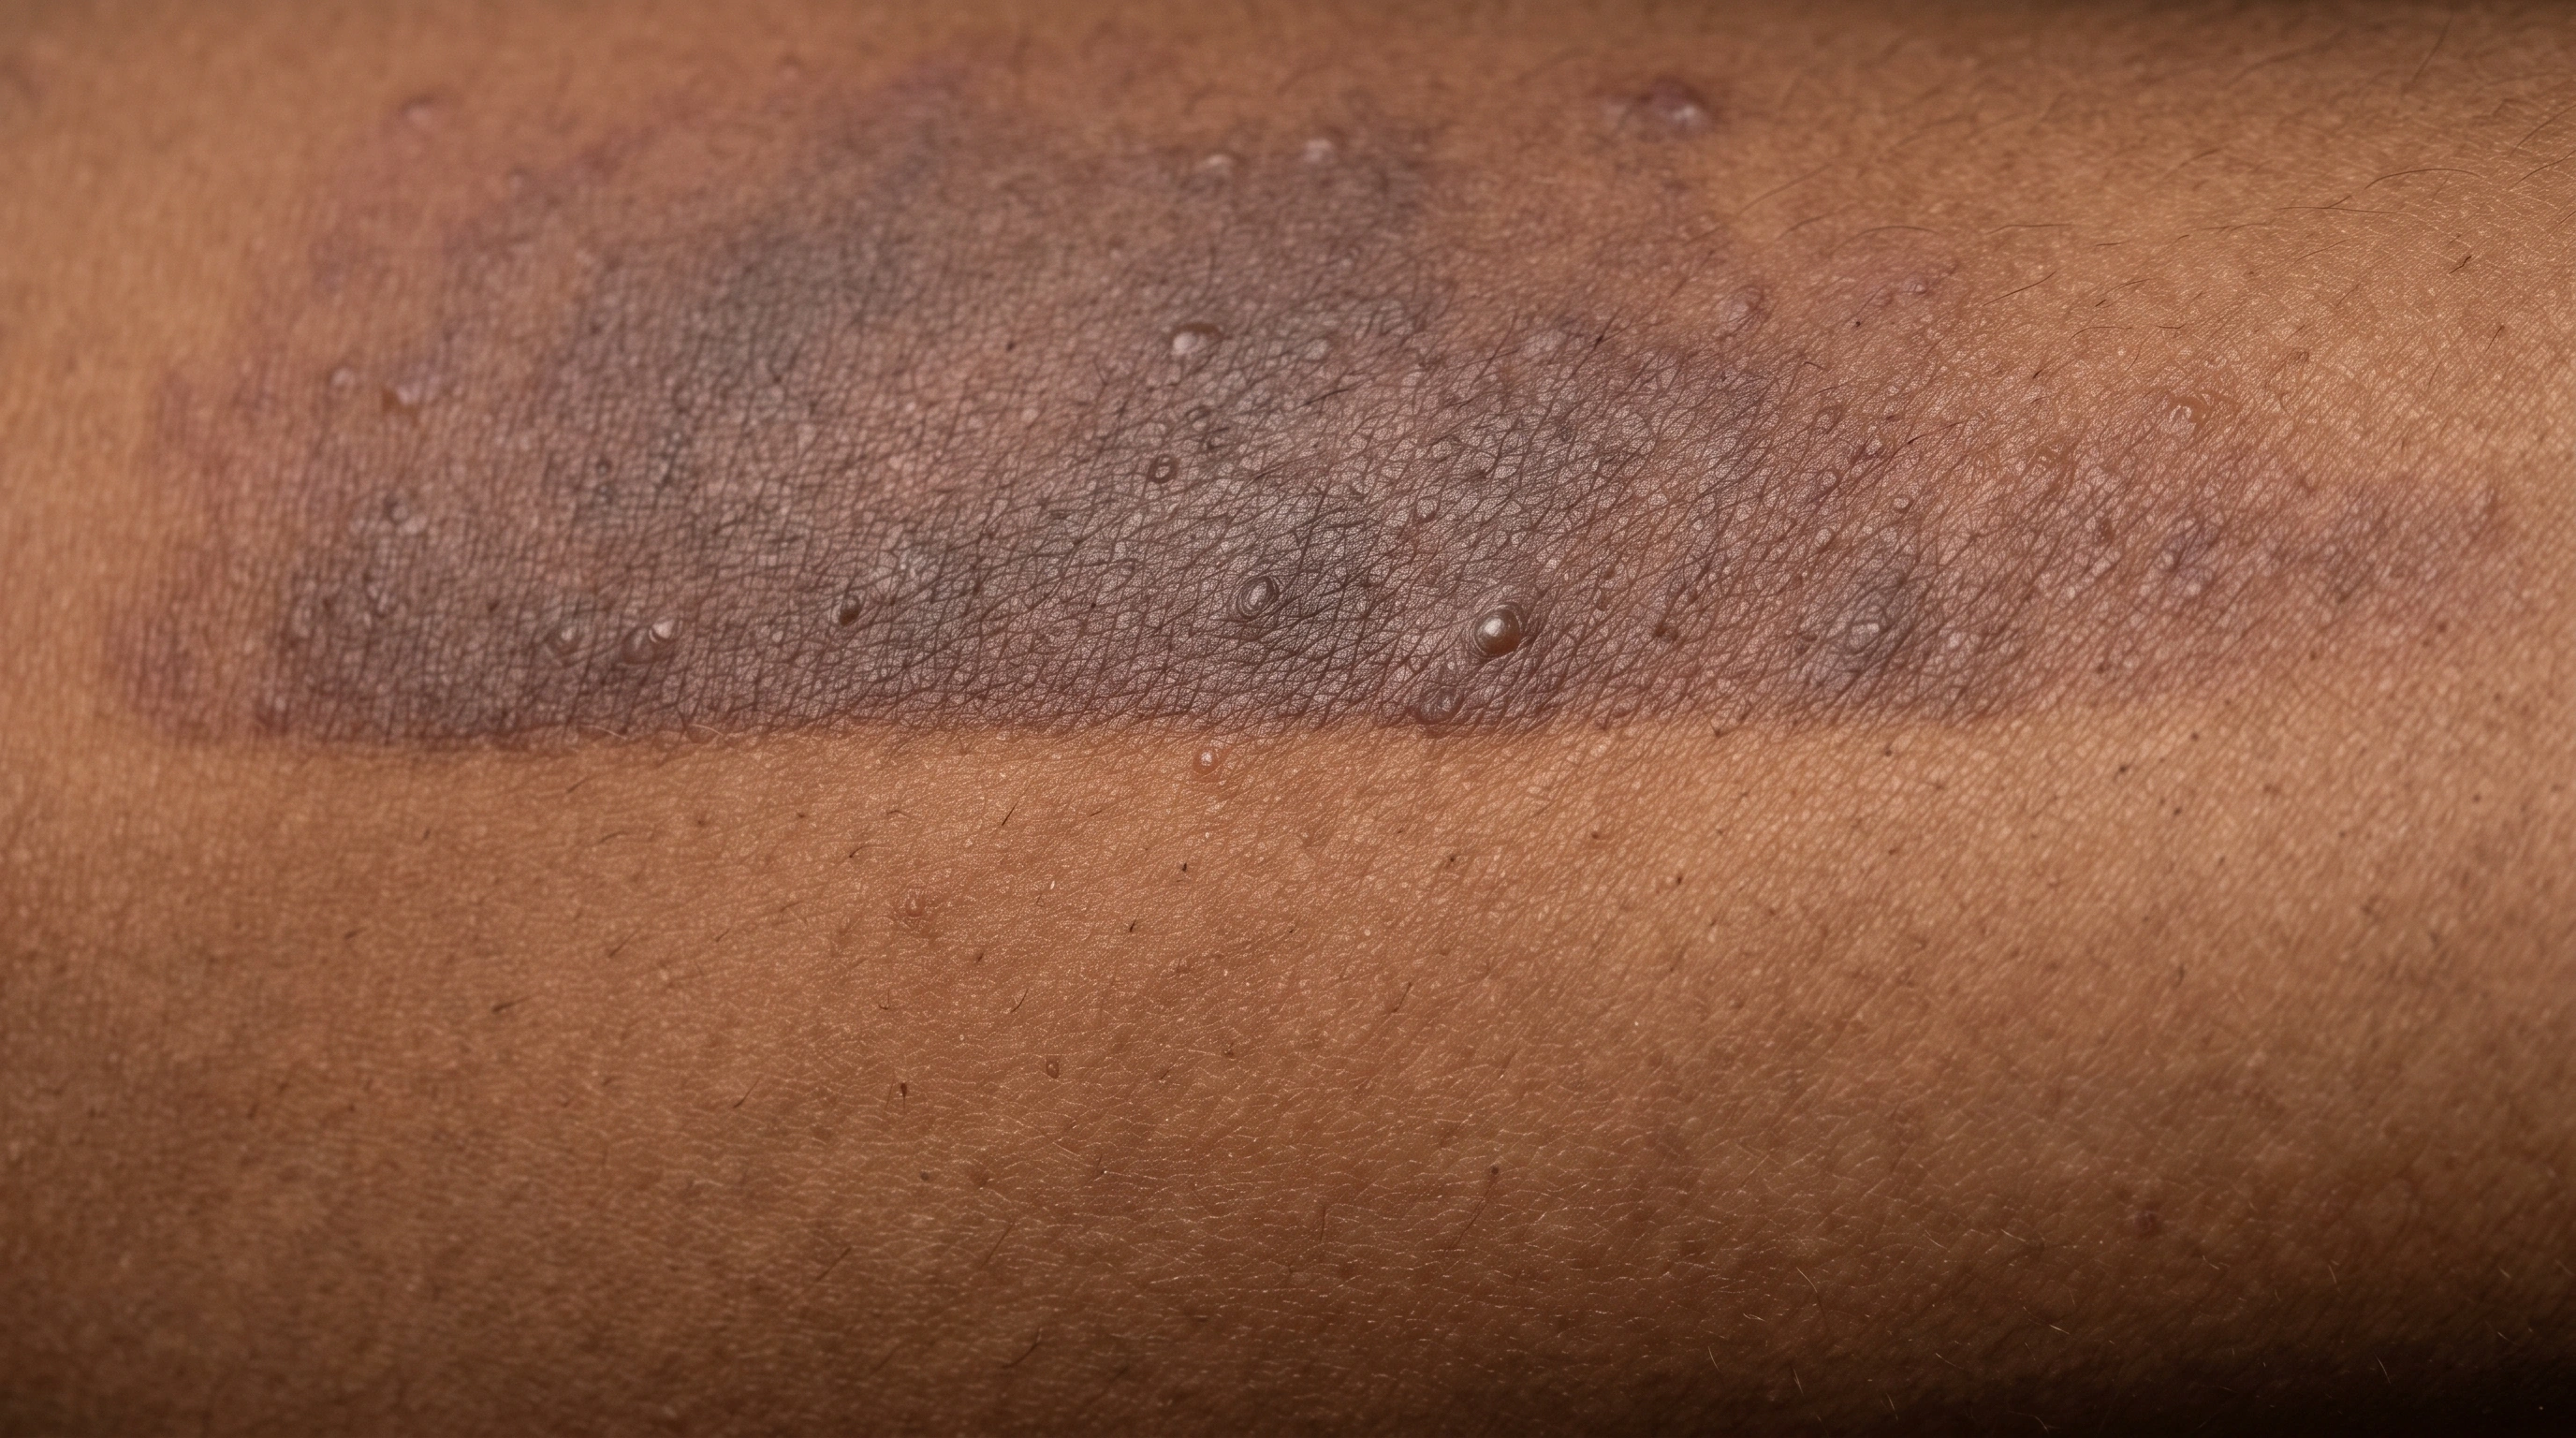
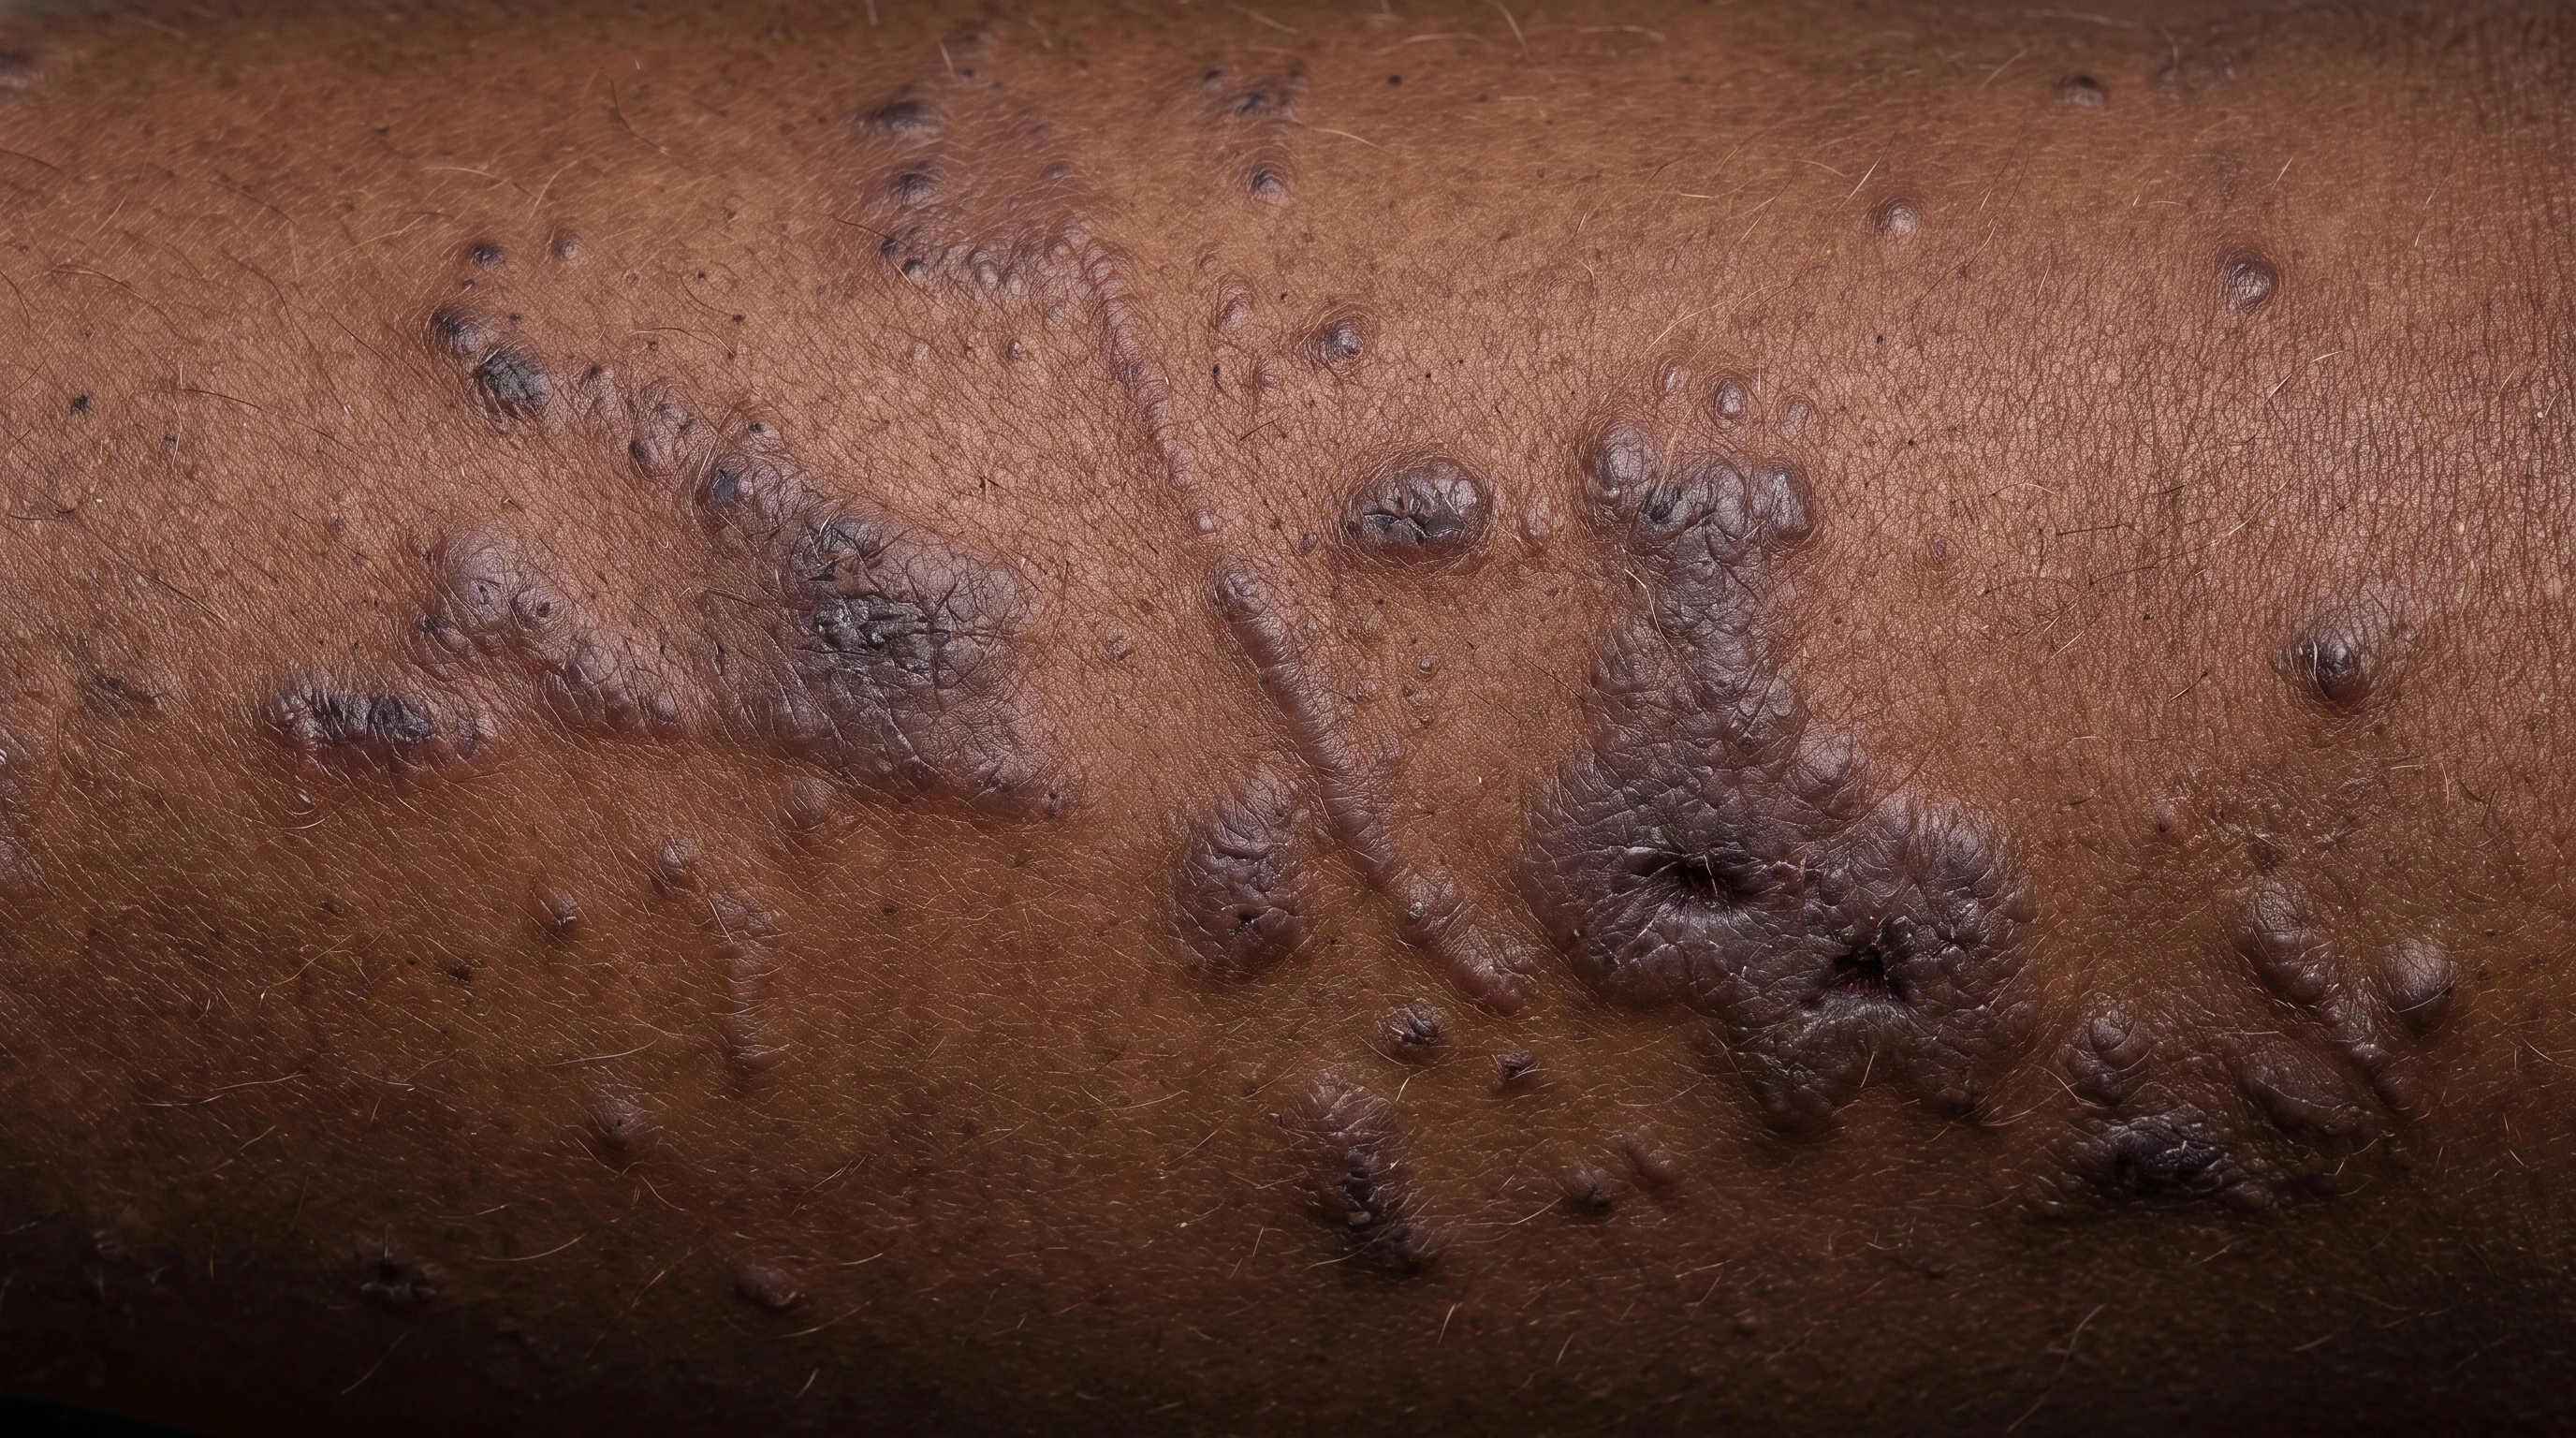
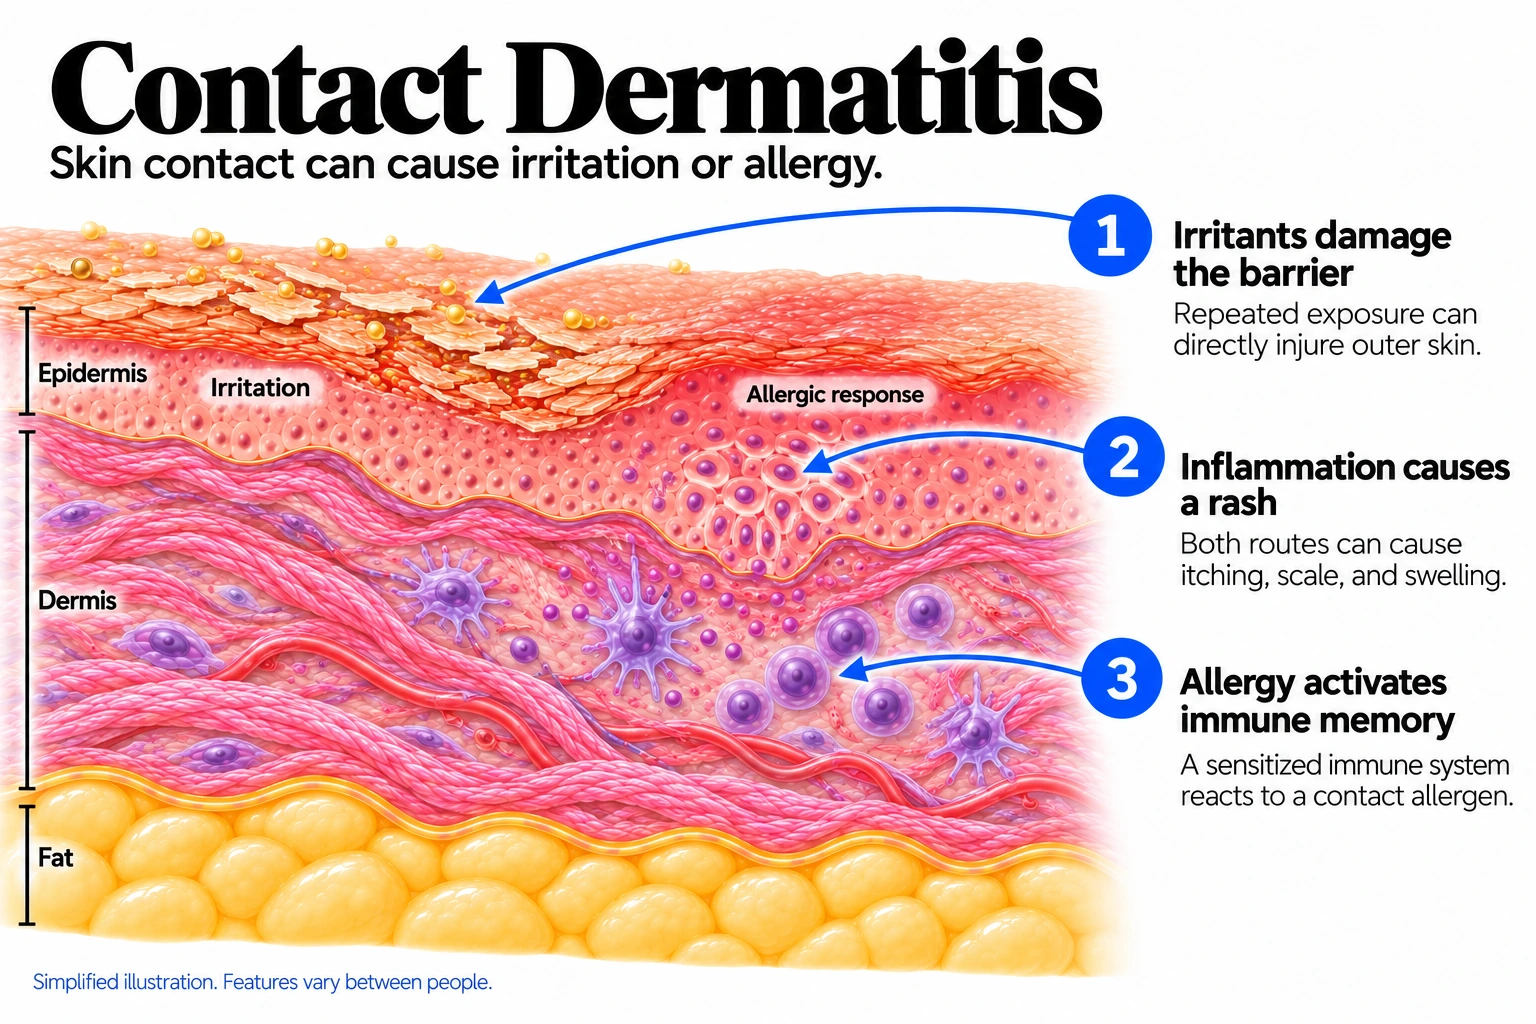
Candida yeast overgrows in a warm, moist skin fold with a weakened barrier. The yeast and the immune response add inflammation to the damaged skin.
Skin contact can cause inflammation through direct irritation or a delayed allergic reaction. These are different routes to a rash that may itch, swell, blister or scale.
Candidal Intertrigo. Can occur whenever skin remains damp and occluded.
Contact Dermatitis. Can begin at any age after irritation or sensitization to a contacting substance.
Candida overgrows in a damaged moist fold.
Contact dermatitis happens when something touching the skin either damages it directly or sets off an allergic reaction. The rash shows up where the contact happened.
People with eczema or a family history of allergies react more easily.
Evidence labels come from each condition’s own treatment list.
Treats Candida in a suitable formulation; follow clinician or local product advice.

The mildest topical steroid, and enough for a small patch on the body once the contact has stopped. Use it twice a day for one to two weeks rather than dabbing it on now and then. It is often too weak for the hands or feet, and on the face or eyelids it should be short-term and worth asking about first.

Contact dermatitis is not driven by histamine, so antihistamines do very little for the rash itself. A sedating one at night can help you sleep through the itching instead of scratching, which is worth something. The non-drowsy daytime ones sold for hay fever will not make much difference here.
Worth naming because they are so often reached for. Neomycin and bacitracin are among the most common contact allergens there are, so an ointment used on an itchy rash can become the reason the rash will not go. Unless the skin is genuinely infected, plain petroleum jelly does the same job with none of the risk.

Plain petroleum jelly, or any thick fragrance-free ointment, rebuilds the barrier that irritation broke. Barrier repair is genuinely half the treatment in irritant hand dermatitis, and it works because it has no fragrance, preservative or botanical in it to start a second reaction. Apply after every hand wash, not once a day.
An oatmeal bath can take the edge off the itch of a widespread reaction, in cool rather than hot water. It is comfort only. Pick a plain one, because an itch product with fragrance or botanicals in it is a common way people acquire a second allergy on top of the first.

A mid-strength steroid cream or ointment, the usual prescription for contact dermatitis on the body, arms or legs. Two weeks of it will clear most reactions once the contact has stopped. It is too strong for the eyelids and the folds, and it is a treatment for the inflammation, not for the cause.

Clobetasol Propionate. A potent steroid ointment for hands and feet, where the skin is thick enough that milder creams barely register. It is used in short bursts of two to three weeks with breaks in between, not continuously. Nothing above the neck, and remember that hand dermatitis takes six weeks or more to settle even when the steroid is doing its job.
A non-steroid ointment for the eyelids, face and skin folds, where repeated steroid use thins the skin. It calms the same immune reaction without that risk, which makes it useful for eyelid dermatitis that keeps returning while the trigger is being tracked down. It stings for the first few days, and that usually passes.

A mild steroid stronger than over-the-counter hydrocortisone but gentle enough for the face and eyelids in short courses. It is the usual first prescription when a reaction has landed above the neck. Use it for the days it is prescribed for, not as something kept in the drawer.

A gentler alternative to tacrolimus for the face and eyelids, and easier to tolerate for people who cannot get past the initial burning. It is not strong enough for hand dermatitis. Like tacrolimus, it buys comfort while the actual trigger is being identified.

Steroid tablets for a widespread, blistering reaction, most often poison ivy covering large areas or a rash on the face that is closing an eye. The course has to run two to three weeks with a taper; the short packs are the usual reason the rash rebounds a few days after finishing. It is for the big reactions only, not for a patch on one arm.

A short specialist course for severe hand dermatitis that has not responded to strong steroids and proper avoidance. It works quickly and reliably, which is exactly why it is used for a few months rather than long term — blood pressure and kidney function have to be watched throughout. It is a bridge, not an answer.

A weekly tablet sometimes used for chronic hand dermatitis when avoidance and creams have genuinely failed. The evidence in contact dermatitis specifically is thin, mostly borrowed from eczema. It needs regular blood tests, and it is a specialist decision rather than a next step.
Used only when bacteria have moved into the broken skin — spreading warmth and pain, pus, or fever. They treat the infection sitting on top and do nothing to the dermatitis underneath, so the steroid and the avoidance carry on alongside them.
An injected biologic increasingly asked about for chronic hand dermatitis. Reports are encouraging for the eczema-like cases, but it is not approved for allergic contact dermatitis and some allergens appear not to respond to it. It does not replace finding and removing the trigger, and it is a specialist conversation.
Yeast-related fold rash can improve with appropriate antifungal treatment and moisture control. Recurrence is possible when the folds remain damp or another contributing factor persists.
Timing is the best clue to which form you have. The rash is temporary; the allergy is not - sensitization is generally lifelong, so avoidance is permanent. Once the substance is named and avoided, most people stay clear.
Damaged skin can develop secondary yeast or bacterial infection.
Infection in the broken skin
Weeping, cracked or scratched skin gives bacteria an opening, most often on the hands. The signs are honey-colored crusts, pus, increasing pain, or redness and warmth spreading outward. It is common and it is treatable, but it needs antibiotics rather than more steroid cream, so it is worth being seen rather than waiting it out.
Chronic hand dermatitis
When the exposure carries on, hand dermatitis stops settling between flares. The skin thickens, the normal lines deepen, and painful cracks open across the fingertips and knuckles that catch on everything and are slow to close. It is the reason contact dermatitis is a leading work-related skin problem, and it is largely preventable by naming the cause early instead of treating the rash for months.
Time off work
Hand dermatitis is one of the leading work-related health problems, and for people in wet or chemical work it can mean weeks of light duties, a change of role, or leaving a trade. It is also the part most often left out of the conversation. Naming the cause early, and getting the right gloves and routine in place, is what keeps the job.
Seek care for spreading pain, broken or weeping skin, fever or failure to improve.
Seek help for persistent or recurrent rash; patch testing may identify contact allergy. Pain, spreading warmth, pus or fever require prompt assessment.
Yeast infection affecting an inflamed skin fold.
Clean gently, pat dry and reduce moisture and rubbing.
Seek care for spreading pain, broken or weeping skin, fever or failure to improve.
Start with location and shape, not a list of products. Photograph the rash, note where its edges are, and look for an object or habit that matches that outline. An allergic reaction shows up one to three days after contact, so look at what happened two days before, not that morning. Include things you have used for years - those are the likeliest candidates, not the least. If a few weeks of attention does not settle it, patch testing ends the guessing.
An irritant reaction improves within days of contact stopping. An allergic reaction takes two to four weeks to settle even with treatment, because the immune cells doing the damage take that long to stand down. Hands are slowest, often six weeks or more, because the skin there is used and washed constantly. Judging it at day three tells you very little.
No. This is your own skin reacting to a substance, not an infection. You cannot pass it on by touch. If two people in a household get the same rash, they were both exposed to the same thing.
Generally no. Once your immune system has learned a substance, that memory is permanent, and tiny amounts can trigger a reaction years later. In practice it is less grim than it sounds - people who know their allergen and avoid it stay clear indefinitely, and the avoidance is usually narrower than they feared.
Eyelid skin is the thinnest on your body, so it reacts to amounts the rest of your skin ignores. Nail polish, hair products, face creams and airborne particles reach the eyelids from your hands or from your scalp. When a rash is on the eyelids alone, the cause is usually somewhere else.
For a small, mild patch on the body, often yes, alongside stopping the contact. Over-the-counter hydrocortisone is a mild strength and rarely clears thicker skin on hands or feet. On the face and eyelids keep it short-term, and ask first. It treats the inflammation, not the cause - if the rash returns each time you stop, find the trigger.
Sources